Skip to Content
  • 3.3
    Impact Factor
  • 5.2
    CiteScore
  • 17 days
    Submission to First Decision
  • 3 days
    Acceptance to Publication

Journal of Clinical Medicine

Journal of Clinical Medicine is an international, peer-reviewed, open access journal of clinical medicine, published semimonthly online by MDPI. The International Bone Research Association (IBRA), Spanish Society of Hematology and Hemotherapy (SEHH), Japan Association for Clinical Engineers (JACE), European Independent Foundation in Angiology/ Vascular Medicine (VAS) and others are all affiliated with JCM, and their members receive a discount on article processing charges.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (54,597)

  • Article
  • Open Access

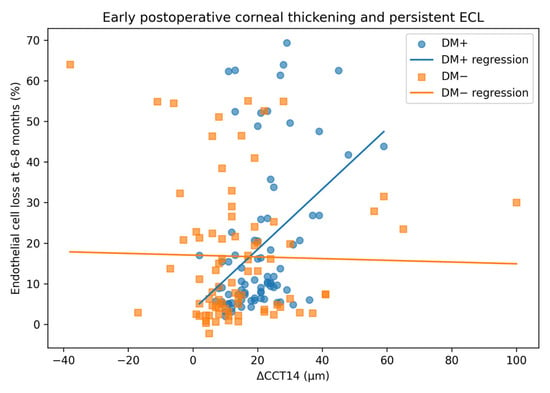
Background: Patients with diabetes mellitus may have reduced corneal endothelial reserve and increased susceptibility to surgical stress. We investigated whether diabetes modifies the association between early postoperative corneal thickening and endothelial cell loss (ECL) after uncomplicated phacoemulsification. Methods: This secondary exploratory analysis included 160 eyes of 160 patients: 80 with well-controlled type 2 diabetes mellitus (DM+) and 80 without diabetes (DM−). Central corneal thickness (CCT) and endothelial cell density (ECD) were assessed preoperatively and at 14 days, 3 months, and 6–8 months postoperatively. Early corneal thickness change was defined as ΔCCT14 = CCT14d − CCTbaseline. The primary outcome was percentage ECL at 6–8 months. Results: Mean ΔCCT14 was greater in DM+ than in DM− participants (20.80 ± 9.87 vs. 14.51 ± 18.08 µm; p = 0.007). ΔCCT14 correlated with ECL in DM+ (Spearman ρ = 0.428; p < 0.001) but not in DM− (ρ = 0.114; p = 0.313). In the adjusted multivariable model, the DM × ΔCCT14 interaction was significant (β = 7.01 percentage points per 10 µm increase; 95% CI, 2.88–11.14; p = 0.001), while cumulative dissipated energy was associated with ECL in the primary model (β = 3.06; 95% CI, 1.67–4.45; p < 0.001). ΔCCT14 was not associated with additional ECL occurring between 14 days and 6–8 months. Conclusions: These findings suggest that early postoperative corneal thickening may represent a marker of established endothelial injury in patients with well-controlled type 2 diabetes rather than a predictor of progressive endothelial deterioration. Endothelial cell loss in this cohort was higher and more widely dispersed than in several contemporary series, and although an internal analysis indicates that random measurement error accounts for only a small fraction of this dispersion, a cohort-specific contribution of surgical or measurement conditions cannot be excluded. The findings are therefore hypothesis-generating and require prospective external validation before clinical application.

J. Clin. Med.

18 November 2026

Association between early postoperative change in central corneal thickness and endothelial cell loss at 6–8 months according to diabetes status.
  • Review
  • Open Access

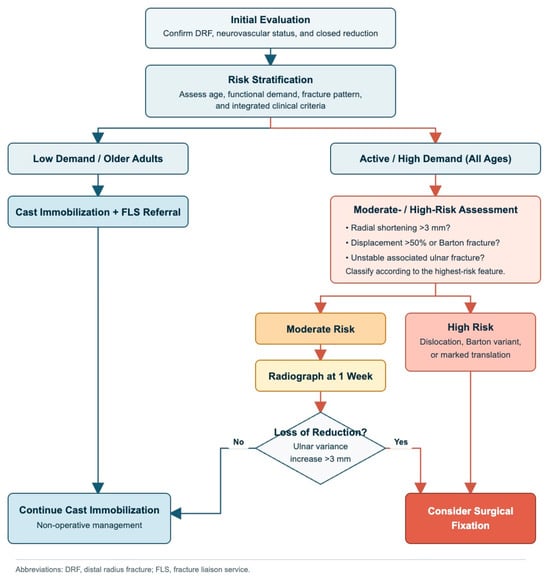
Background/Objectives: Distal radius fractures (DRFs) are highly prevalent injuries, particularly in the aging demographic. Their management is currently undergoing a fundamental paradigm shift away from a strict focus on generic radiographic alignment toward personalized, functional recovery. Furthermore, in the geriatric population, a DRF is no longer viewed merely as an isolated orthopaedic injury, but as a critical sentinel event indicating systemic skeletal fragility. Previous consensus statements and reviews have left critical controversies unresolved, presenting conflicting guidelines regarding surgical indications, instability prediction, and rehabilitation. The purpose of this review is to explicitly identify these historical controversies, provide evidence-graded recommendations, and highlight translational innovations specifically for the older adult demographic. Methods: This current concepts review synthesizes the recent literature to provide an evidence-based update on the continuum of care for DRFs. Clinical recommendations were established through collaborative review and synthesis by a panel of orthopaedic surgeons that focus on orthopaedic trauma and/or hand surgery. Results: The classic Lafontaine criteria for predicting instability have shown unacceptable discriminative performance, prompting innovative adoption of integrated and machine learning (ML) predictive models utilizing pre- and post-reduction parameters. Whilst previous consensus had controversy on surgical thresholds in the elderly, the recent literature presents a nuanced debate; although some network meta-analyses suggest superior functional scores with surgical fixation, robust evidence confirms that for low-demand, physiologically older patients, these differences are rarely clinically significant, making conservative management a highly viable option. Older patients also face a high imminent risk of secondary fractures following a DRF, and orthogeriatric co-management via a Fracture Liaison Service (FLS) is becoming a vital translational solution. Economically, DRF operative care has also shifted toward ambulatory pathways, primarily utilizing regional blocks with sedation in North America, alongside the emerging alternative of Wide-Awake Local Anaesthesia No Tourniquet (WALANT) for highly selected fracture patterns. To mitigate operative complications, the use of intraoperative safety checklist can be a useful adjunct. Emerging technologies including AI-guided robotic-assisted reduction systems offer experimental promise in enhancing surgical precision. Postoperatively, wearable biofeedback sensors optimize functional rehabilitation, and novel biological adjuncts such as low-magnitude high-frequency vibration (LMHFV) and Platelet-Rich Plasma (PRP), and dual-drug (testosterone/alendronate) coated membranes are being explored to enhance osteoporotic fracture healing. Conclusions: The innovation of this review lies in redefining DRF management through a patient-specific and risk-stratified approach. By resolving past controversies, we recommend a translated continuum of care that emphasizes secondary fracture prevention through FLS pathways, AI-integrated instability prediction, activity-demand treatment thresholds, ambulatory care alternatives, intraoperative safety checklists, experimental robotic-assisted precision, technology-assisted rehabilitation, biological enhancement of fracture healing.

J. Clin. Med.

18 November 2026

Proposed Clinical Flowchart for DRF Management (created with FigureLabs by YH Choi https://www.figurelabs.ai/ (accessed on 4 November 2026)).
  • Feature Paper
  • Article
  • Open Access

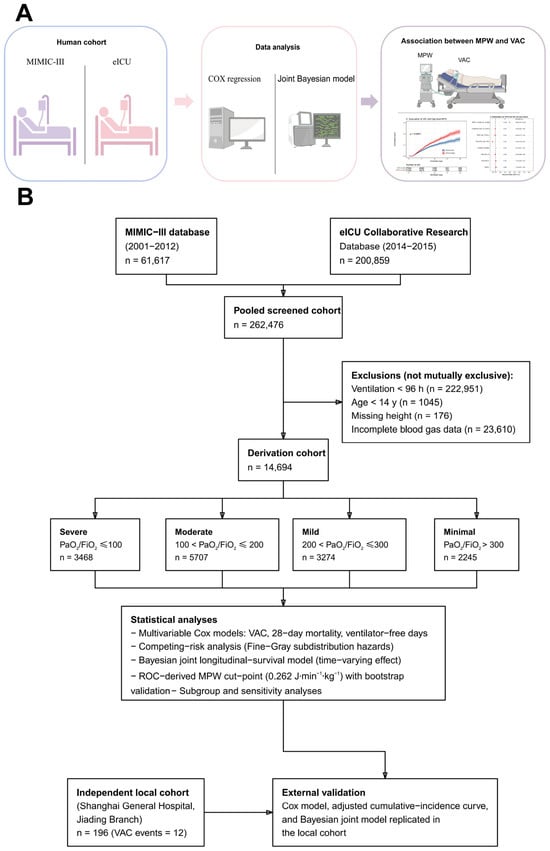
Background: While mechanical power (MP) quantifies energy transfer during ventilation, its relationship with ventilator-associated conditions (VAC) remains underexplored. We hypothesized that predicted body weight (PBW)-adjusted mechanical power (MPW) is independently associated with VAC and mortality in patients requiring prolonged ventilation. Methods: This multi-database retrospective cohort study included 14,694 patients requiring prolonged mechanical ventilation (≥14 years; ≥96 h of ventilation) from MIMIC-III and eICU, with verification in an independent local cohort. The primary outcome was 28-day VAC; secondary outcomes were mortality and ventilator-free days. We employed Cox models, Bayesian joint longitudinal-survival analysis, and a competing-risk analysis treating 28-day death as a competing event. Results: VAC occurred in 8.2% (n = 1209) of 14,694 patients. Each 0.1 J·min−1·kg−1 MPW increase independently predicted a higher VAC hazard ratio (HR 1.04, 95% credible interval [CI] 1.02–1.06, p < 0.001) and 28-day mortality (HR 1.03, 95% CI 1.01–1.04, p = 0.01). Bayesian modeling revealed a time-dependent MPW effect, peaking at day 22 (HR 1.12, 95% credible interval (CI) 1.08–1.17). Patients exceeding the receiver operating characteristic (ROC) curve-derived MPW threshold (0.262 J·min−1·kg−1) had a higher VAC hazard (HR 1.36, 95% CI 1.21–1.52, p < 0.001). With death as a competing event for VAC, the association persisted (subdistribution HR 1.25, 1.11–1.41; Gray’s test p < 0.001), whereas cumulative death incidence did not differ by MPW group (p = 0.968). In an independent local cohort (n = 196; 12 VAC events), the core analyses were replicated with directionally consistent results (MPW-threshold adjusted hazard ratio 3.96, 95% CI 1.01–15.54; Bayesian time-varying effect rising from <1 to approximately 6.6 per 0.1 J·min−1·kg−1 by day 30). Conclusions: MPW was independently associated with VAC and mortality. These findings support further study of mechanical-power-guided ventilation strategies and require validation before clinical use.

J. Clin. Med.

18 November 2026

Study design and analytical workflow. (A). This study utilized cohorts derived from the MIMIC-III and eICU databases. Two analytical approaches, Cox regression and a Bayesian joint model, were used to investigate the relationship between MPW and VAC. (B). A total of 262,476 patients were screened from MIMIC-III (n = 61,617) and eICU (n = 200,859). Patients were excluded based on the following criteria: ventilation duration &lt; 96 h, age &lt; 14 years, missing height, and incomplete blood gas data. This resulted in a final enrollment of 14,694 patients. Patients were stratified based on PaO2/FiO2 ratios into groups representing severe, moderate, mild, and minimal hypoxemia. MPW and volume-control/pressure-control ventilation parameters were calculated. Statistical analyses included Cox regression for associations between MPW and VAC/mortality, linear regression for ventilator-free days, a Bayesian joint model to assess the time-varying effect of MPW on VAC, and further analyses including ROC analysis, mediation analysis, and sensitivity analyses (subgroup analysis and multiple imputation). Exclusion criteria were not mutually exclusive, so the total number of excluded cases is greater than the initial number screened.
  • Article
  • Open Access

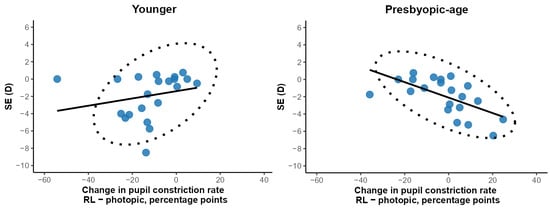
Background/Objectives: Near-vision difficulties associated with presbyopia may become apparent under reduced luminance despite preserved distance visual acuity. We compared near visual function and pupillary responses between younger and presbyopic-age adults under photopic and reduced-luminance (RL) conditions. Methods: This prospective cross-sectional study included 21 younger adults aged 20–35 years and 21 presbyopic-age adults aged 40–55 years. Corrected distance visual acuity (CDVA), distance-corrected near visual acuity (DCNVA), corrected near visual acuity (CNVA), accommodative amplitude, pupil area, and pupil constriction rate were assessed under photopic and RL conditions. RL conditions were produced using a neutral-density 0.9 filter (chart luminance, 9.63 cd/m2). Results: CDVA did not differ significantly between groups under either condition. DCNVA and CNVA were worse in the presbyopic-age group under both conditions (all p < 0.05), and the declines in both measures from photopic to RL conditions were greater in this group (both p < 0.01). Increasing the near add power improved CNVA under RL conditions in the presbyopic-age group, although CNVA remained worse than under photopic conditions (p = 0.003). In the younger group, CNVA under RL conditions with the RL near add power did not differ significantly from photopic CNVA. Pupil constriction rates were higher in the presbyopic-age group under both photopic (p < 0.05) and RL (p < 0.001) conditions. Under RL conditions, mean pupil area was larger during near viewing than during distance viewing in the younger group, whereas the opposite pattern was observed in the presbyopic-age group. Conclusions: Under RL conditions, the decline in near visual acuity was greater in presbyopic-age participants than in younger participants, despite preserved distance visual acuity. Pupillary responses differed between the groups, but their relationship with near visual deterioration remains to be established. Further studies are needed to determine whether near visual assessment under RL conditions provides additional clinical value.

J. Clin. Med.

18 November 2026

Association between spherical equivalent (SE) and the change in pupil constriction rate from photopic to reduced-luminance (RL) conditions in the younger group (left) and the presbyopic-age group (right). Pupil constriction rate was calculated as described in Table 2. The change in pupil constriction rate was calculated as the RL value minus the photopic value and is expressed in percentage points. Positive values indicate a higher pupil constriction rate under RL conditions than under photopic conditions; negative values indicate a lower rate under RL conditions. Lines represent fitted least-squares regression lines. Ellipses represent 95% probability regions based on a bivariate normal distribution and do not represent confidence intervals for the regression lines. Both are included for descriptive purposes. Correlations were assessed using Spearman’s rank correlation coefficient (ρ).

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
J. Clin. Med. - ISSN 2077-0383