
Skip to Content

Transplantology

Transplantology is an international, peer-reviewed, open access journal on all areas of experimental and clinical transplantation, published quarterly online by MDPI.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (199)

Background: Patients with end-stage kidney disease commonly develop hyperparathyroidism, which may impair muscle strength and physical function. Elevated parathyroid hormone (PTH) levels have been associated with weakness and poor Timed Up and Go (TUG) test performance. We hypothesized that elevated PTH at kidney transplantation would correlate with worse TUG performance and poorer post-transplant outcomes. Methods: We performed a retrospective cohort study of 226 kidney transplant recipients (2015–2023) at a single transplant center with documented TUG testing and PTH levels. Patients were divided into normal PTH (≤600 pg/mL, nPTH) and high PTH (>600 pg/mL, hPTH) groups. Demographics, clinical characteristics, and transplant outcomes, including graft and patient survival, were analyzed. Results: The hPTH group (n = 16) was younger than the nPTH group (41.8 vs. 55.4 years, p < 0.001) and more likely to have English as a second language (62.5% vs. 35.6%, p = 0.032). They also had lower estimated post-transplant survival scores (29.3 vs. 52.0, p = 0.003) and higher rates of hyperphosphatemia (18.8% vs. 4.3%, p = 0.044). TUG pass rates, acute rejection, delayed graft function, and patient survival were similar between groups. However, the hPTH group demonstrated shorter mean graft survival (6.6 vs. 7.7 years, p = 0.022). On multivariable Cox regression, elevated PTH at transplantation remained independently associated with graft failure (adjusted hazard ratio 20.6, 95% CI 1.91–222). Conclusions: Elevated PTH at transplant was associated with poorer graft survival despite similar rejection rates and patient survival. Although not directly measured in this study, high PTH may reflect increased medical complexity or adherence-related challenges.

Transplantology

18 August 2026
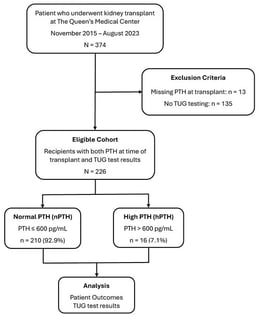
STROBE diagram showing the patient selection process.

Background/Objectives: Hepatocellular carcinoma (HCC) frequently develops in the set-ting of chronic liver disease, and liver transplantation (LT) represents the most effective curative option for selected patients. Despite advances in patient selection and surveillance, HCC recurrence after LT remains a major cause of post-transplant mortality and is associated with limited therapeutic options. Immune checkpoint inhibitors (ICIs) have transformed the management of advanced HCC in non-transplant populations; however, their role after liver transplantation remains controversial due to safety concerns and the risk of allograft rejection. This narrative review aims to critically evaluate the current evidence on immunotherapy for recurrent HCC after liver transplantation. Methods: A structured narrative review of PubMed/MEDLINE was conducted through 31 May 2026. Primary clinical reports describing ICI treatment for recurrent HCC after LT were selected using predefined eligibility criteria. Results: Twenty-one primary publications were included, consisting predominantly of case reports and small case series, supplemented by three retrospective cohorts. The reports described heterogeneous oncological outcomes, including occasional durable responses, but progressive disease remained common. Allograft rejection was an important safety concern and was sometimes associated with graft failure and death. More favourable outcomes were observed among some recipients treated at longer intervals after LT; however, this pattern remains hypothesis-generating and may reflect selection and survivor bias, tumour biology, graft stability, and differences in maintenance immunosuppression. Conclusions: ICI treatment for recurrent HCC after LT is associated with uncertain oncological benefit and a clinically important risk of allograft rejection. Its use should be restricted to highly selected recipients following multidisciplinary assessment and, whenever possible, within prospective studies or structured registries.

Transplantology

18 September 2026

Early vs. Late Extubation After Bilateral Lung Transplantation: Predictors and Outcomes

  • Nicolò Sella,
  • Sabrina Congedi and
  • Annalisa Boscolo
  • + 21 authors

Background: Early extubation after bilateral lung transplantation (LT) may reduce intensive care unit (ICU) complications, but evidence from heterogeneous real-world cohorts and of its impact on mid-term functional recovery remains limited. Methods: We conducted a single-centre observational study of 149 consecutive adult bilateral LT recipients (February 2016–February 2023). Patients extubated within 24 h were assigned to the early extubation (EE) group (n = 63, 42%) (extubated within 24 h of the end of surgery), while those extubated later comprised the late extubation (LE) group (n = 86, 58%) (extubated beyond 24 h). Multivariable logistic regression identified predictors of late extubation. Outcomes included postoperative extracorporeal membrane oxygenation (ECMO), pneumonia, ICU length of stay, and spirometric parameters at 9–12 months after LT. Results: Higher Lung Allocation Score (LAS; adjusted OR 1.19, 95% CI 1.02–1.38) and intraoperative red blood cell (RBC) transfusions (adjusted OR 1.47, 95% CI 1.04–2.06) independently predicted late extubation. Compared with the LE group, EE recipients required less postoperative ECMO (2% vs. 23%; p = 0.008), had shorter inhaled nitric oxide treatment (7 vs. 17 h; p = 0.006), lower pneumonia rates (8% vs. 23%; p = 0.043), and shorter ICU stays (6 vs. 9 days; p = 0.005). In-hospital and 1-year mortality were similar between groups. At 9 ± 1 months, EE recipients showed better volumetric lung recovery, with higher FVC as a percentage of pre-transplant baseline (78.0% vs. 69.5%; p = 0.048) and higher TLC percentage predicted (77% vs. 68%; p = 0.015). Airflow indices and respiratory muscle strength did not differ. Conclusions: In a broadly inclusive LT cohort, higher LAS and intraoperative RBC transfusion independently predicted late extubation. Early extubation was associated with lower postoperative support requirements and was associated with higher FVC relative to pretransplant baseline, an association that should be interpreted in light of the unadjusted comparison and baseline heterogeneity rather than as evidence of a causal benefit.

Transplantology

11 August 2026

Accurate donor–recipient allograft size matching remains a critical determinant of outcomes in lung transplantation, yet current approaches rely predominantly on predicted total lung capacity (pTLC) and height-based metrics derived from population-based equations. These simplified surrogates fail to capture individual anatomical variability, disease-specific alterations in thoracic geometry, and the spatial relationship between donor lungs and recipient chest cavities. In this review, we examine the limitations of conventional size matching and synthesize emerging evidence supporting imaging-based approaches, including computed tomography (CT) volumetry, radiomics, and machine learning. CT-derived volumetric analysis enables individualized anatomical assessment and has been associated with clinically relevant prediction of primary graft dysfunction and mortality. Advanced computational methods may further support the extraction of imaging-derived features and integration with clinical data, although these approaches remain investigational. Collectively, these developments signal a paradigm shift from crude population-based metrics toward imaging-driven and computational approaches in the modern era. With rigorous validation and careful clinical integration, imaging-based approaches may complement conventional size metrics and support more individualized donor–recipient assessment.

Transplantology

3 July 2026

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
Transplantology - ISSN 2673-3943
