Skip to Content
You are currently on the new version of our website. Access the old version .
  • 25 days
    Submission to First Decision
  • 7 days
    Acceptance to Publication

Journal of CardioRenal Medicine

Journal of CardioRenal Medicine is an international, peer-reviewed, open access journal on the interdisciplinary field of medical science that focuses on study of how the heart and kidneys are interconnected published quarterly online by MDPI.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (18)

  • Review
  • Open Access

Perspectives of Artificial Intelligence Enabled Diagnosis and Treatment Management of Cardiorenal Syndrome

  • Harsha Pudhota,
  • Gianeshwaree Alias Rachna Panjwani and
  • Shivaram P. Arunachalam
  • + 23 authors

Cardiorenal syndrome (CRS) encompasses a spectrum of disorders arising from bidirectional interactions between the heart and kidneys and is associated with substantial morbidity, mortality, and healthcare burden. Early recognition remains challenging because conventional biomarkers and imaging modalities may inadequately detect subclinical disease or distinguish functional changes from true organ injury. This narrative review examines the epidemiology, classification, pathophysiology, diagnostic approaches, and contemporary management of CRS, with particular emphasis on the emerging role of artificial intelligence (AI). Relevant evidence regarding established and emerging diagnostic and therapeutic approaches was reviewed, including biomarkers, imaging, guideline-directed medical therapy, ultrafiltration, cardiac devices, transplantation, and AI-based applications. Current evidence demonstrates the multifactorial nature of CRS and highlights the importance of early diagnosis and individualized management. Machine learning and deep learning approaches have shown potential to integrate electronic health records, biomarkers, imaging, physiological signals, and multi-omics data to support early detection, risk stratification, outcome prediction, and therapeutic decision-making. AI-assisted approaches may complement conventional diagnostic and management strategies and facilitate more precise and proactive CRS care. However, limitations related to data quality, model interpretability, external validation, and clinical implementation must be addressed before widespread clinical adoption.

J. CardioRenal Med.

31 October 2026

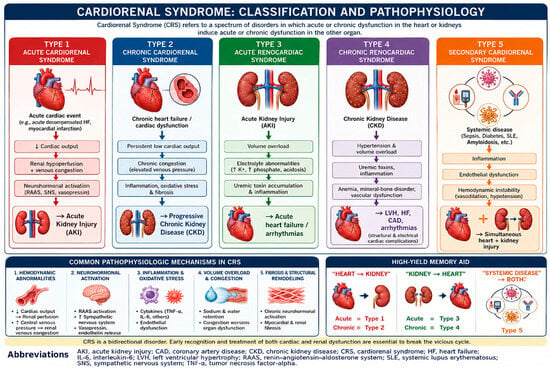
Classification and Pathophysiology of Cardiorenal Syndrome.
  • Case Report
  • Open Access

Background: Dialysis adequacy is commonly assessed using Kt, a measure of urea clearance. Vascular access dysfunction, particularly thrombosis and access recirculation, may compromise dialysis efficiency despite apparently adequate treatment parameters. Ultrasound assessment of vascular anatomy can help identify individualized cannulation strategies to optimize dialysis delivery. Case Presentation: We report the case of a 78-year-old man undergoing maintenance hemodialysis who exhibited persistently low Kt values despite adequate dialysis time and blood flow. Doppler ultrasound revealed complete occlusive thrombosis involving the cephalic vein, resulting in altered venous drainage. Based on these findings, the conventional cannulation configuration was reversed by exchanging the arterial and venous needle positions. Dialysis adequacy during 11 consecutive sessions using reverse cannulation was compared with that of the previous 12 conventional sessions matched for treatment duration and dialysis volume. Results: Reverse needle cannulation was associated with improved dialysis adequacy. Mean Kt increased from 46.9 ± 6.7 L with conventional cannulation to 57.3 ± 5.8 L after reverse cannulation (p = 0.002), while dialysis duration and processed blood volume remained comparable between both periods. Conclusions: In selected patients with complex vascular anatomy secondary to arteriovenous fistula thrombosis, ultrasound-guided reverse needle cannulation may improve dialysis adequacy without changing treatment duration or the prescribed extracorporeal blood flow rate. This case highlights the value of individualized vascular access assessment and tailored cannulation strategies in patients with vascular access dysfunction.

J. CardioRenal Med.

3 September 2026

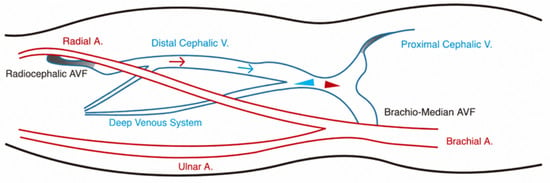
Schematic representation of the patient’s vascular access anatomy and cannulation configurations. The diagram shows the arteriovenous anastomosis, complete occlusive thrombosis of the proximal cephalic vein, a vessel coursing toward deeper tissue planes and draining toward the deep venous system, and the positions and directions of the arterial and venous needles during conventional and reverse cannulation. Shaded areas indicate thrombosed segments; arrows indicate the direction of blood flow; red and blue markers indicate the arterial withdrawal and venous return needles, respectively.
  • Review
  • Open Access

From Petro-Polymers to Biopolymers: Chitosan Strategies for Sustainable Hemodialysis

  • Maria Martingo,
  • Patrícia Henriques and
  • Sandra Borges
  • + 1 author

Hemodialysis (HD) remains the most widely adopted renal replacement therapy for patients with end-stage kidney disease; however, its delivery entails a substantial environmental burden due to high water and energy consumption and extensive reliance on single-use synthetic polymeric membranes. As the global prevalence of chronic kidney disease increases, the ecological footprint of dialysis systems has become a critical challenge for sustainable healthcare. Conventional HD membranes, based on petroleum-derived polymers, provide controlled permeability but are inherently non-renewable, non-biodegradable, and susceptible to fouling and bio-incompatibility, underscoring the need for alternative, more sustainable materials. Chitosan has emerged as a promising biopolymer owing to its biodegradability, intrinsic antimicrobial activity, chemical versatility, and favorable hemocompatibility. This review presents a comprehensive analysis of chitosan-based hybrid membranes for HD, with emphasis on sustainability-driven material innovation. The structural chemistry and functional properties of chitosan are discussed in relation to molecular weight, degree of deacetylation, and supramolecular organization, followed by a comparative assessment of chitosan derived from crustacean, insect, fungal, and cephalopod sources. Attention is given to fungal chitosan as a naturally deacetylated, high-purity, and reproducible biomaterial aligned with circular bioeconomy principles. Eco-innovative extraction and purification strategies, including enzymatic and low-energy processes, are critically examined alongside membrane fabrication approaches such as polymer blending, electrospinning of hollow fibers, and functionalization strategies aimed at improving hemocompatibility, antimicrobial performance, and fouling resistance. Key challenges related to membrane reuse, scale-up, regulatory compliance, and clinical translation are also addressed. Overall, this review highlights fungal-derived chitosan as a sustainable platform for next-generation HD membranes.

J. CardioRenal Med.

9 August 2026

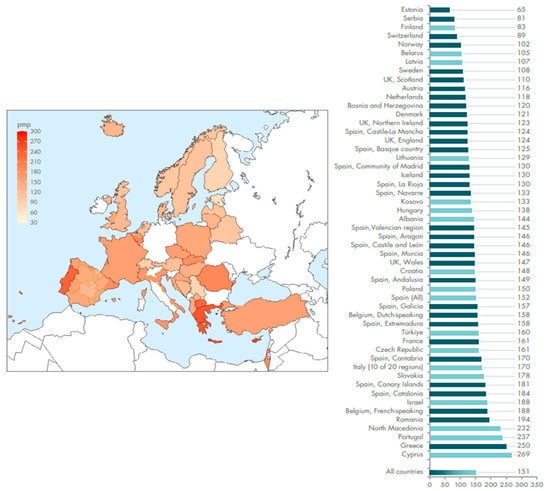
Incidence per million population by country/region by the beginning of 2023 [5].
  • Article
  • Open Access

Introduction: Coronary artery bypass grafting (CABG) in patients with chronic kidney disease/chronic renal failure (CKD/CRF) poses additional surgical risk, both perioperatively and beyond, compared to their non-renal failure counterparts. Patients with end-stage renal disease (ESRD) are at particularly high risk for complications with prognoses limited by cardiovascular (e.g., myocardial infarction, heart failure, stroke) and non-cardiovascular (e.g., infection) conditions associated with the disease itself and the treatment of it (i.e., dialysis). For decades, cardiac surgeons have continued to offer CABG to patients with ESRD on dialysis with variable success. The purpose of this report is to describe a relatively contemporary analysis of CABG surgery in ESRD patients utilizing a pump-assisted beating-heart technique with the analysis of and comparison to outcomes reported by other investigators as well as predictions generated by the Society of Thoracic Surgery outcome tool. We report both short- and intermediate-term outcomes. Methods: From 1 January 2019 through 31 May 2025, the data from all consecutive patients undergoing BH-CABG at a single institution by a single surgeon were collected. Demographic information as well as a preoperative risk assessment was performed using the Society of Thoracic Surgeon (STS) Risk Assessment tool. The BH-CABG was performed via median sternotomy with maintenance of normothermia and ventilation throughout the case. Postoperative outcomes were recorded including mortality, major morbidity, and length of stay (LOS). Hospital/operative results were compared to the STS risk calculations. On-going intermediate-term follow-up beyond the index hospitalization was completed using direct or indirect methods (i.e., clinic, telephone, email). Results: There were 439 BH-CABG patients during the study period. Fifty-nine patients (13.4%) had ESRD on HD. There were 39 men and 20 women with a mean age of 61 years (41–76 years). Fifty-one (86%) underwent pump-assisted BH-CABG (PADCAB) and eight patients underwent complete off-pump BH-CABG (OPCAB). The mean ejection fraction (EF) was 48% (15–70%). The mean number of grafts was 2.3 (1 to 4) and the mean cardiopulmonary bypass (CPB) time for the PADCAB cases was 80 min (34 to 118 min). Patient presentation consisted of the following: one with cardiogenic shock, one with cardiac arrest, two with STEMI, 18 with NSTEMIs, 10 with CHF, five with NSTEMI/CHF, six with unstable angina (USA), and 16 with a positive stress test in preparation for renal transplant consideration. There was one operative mortality (1.7%), one stroke (1.7%), no reoperation for bleeding, no deep sternal wound infection, one prolonged ventilation (1.7%), and one prolonged length of stay (1.7%); overall mortality/morbidity was 5.1%. Comparatively, the STS-predicted mortality was 5.7%, stroke 2.2%, reoperation for bleeding 3.5%, deep sternal wound infection 0.6%, prolonged ventilation 17.8%, prolonged LOS 14.8%, and combined mortality/morbidity 26.8%. Thirty-six of the 59 patients remained alive (61%) in the follow-up period. Twenty-three patients expired (39%) in the follow-up: 11 of cardiac issues, eight of sepsis, two of stroke, one of gastrointestinal issues, and one of cancer. The average duration of survival for expired patients was 2.28 years (13 days to 5 years and 4 months). Nine patients (15%) underwent renal transplantation and six of them remained alive (67%). Conclusions: CABG surgery in patients with ESRD is complicated with historically high mortality and morbidity. The results of this study demonstrate significant improvement in the reduction in hospital mortality and morbidity. However, intermediate-term outcomes remain poor with a preponderance of cardiovascular and infectious deaths. A trend toward improved intermediate-term outcomes appears in patients in whom CABG surgery was performed for purposes of renal transplantation.

Dr. Willem Kolff and Dr. Louis Samuels (author) with the AbioCor™ Total Artificial Heart (Abiomed, Inc., Danvers, MA, USA) (personal photograph—author’s (L.S.) collection). Dr. Kolff, a cardiac surgeon, is considered the ‘father of dialysis’, having invented the semipermeable membrane for treating patients with ESRD.

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
J. CardioRenal Med. - ISSN 3042-6987