Skip to Content
You are currently on the new version of our website. Access the old version .
  • 3.3
    Impact Factor
  • 5.2
    CiteScore
  • 17 days
    Submission to First Decision
  • 3 days
    Acceptance to Publication

Journal of Clinical Medicine

Journal of Clinical Medicine is an international, peer-reviewed, open access journal of clinical medicine, published semimonthly online by MDPI. The International Bone Research Association (IBRA), Spanish Society of Hematology and Hemotherapy (SEHH), Japan Association for Clinical Engineers (JACE), European Independent Foundation in Angiology/ Vascular Medicine (VAS) and others are all affiliated with JCM, and their members receive a discount on article processing charges.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (54,302)

  • Systematic Review
  • Open Access

Treatment-Induced Neuropathy of Diabetes: Clinical Insights from a Case Series and Systematic Review

  • Nicu Catalin Draghici,
  • Ruxandra Mosorescu and
  • Dafin Fior Mureșanu
  • + 5 authors

Background/Objectives: Treatment-induced neuropathy of diabetes (TIND) is an under-recognized iatrogenic neuropathy that follows a rapid fall in glycated hemoglobin (HbA1c). We aimed to systematically summarize the published cases of TIND and to compare them with two patients evaluated at our center. Methods: We evaluated two patients at our center and systematically reviewed PubMed, Scopus, Web of Science and Google Scholar, following PRISMA 2020, for primary clinical studies of TIND. Data were synthesized descriptively. Results: Both patients developed painful neuropathy with autonomic symptoms after HbA1c falls of 15.3 and 6.4 percentage points and improved substantially, but incompletely, over two years. Moreover, the review included 47 publications (219 patients) and painful neuropathy with autonomic dysfunction predominated. In case reports, the median HbA1c fall was 7.3 percentage points, and onset occurred within 8 weeks in 26 of 47 publications. Recovery was complete in 8 and partial in 21 of 32 case reports with documented outcomes. Follow-up data were missing for 136 of 219 patients. Conclusions: Published cases show a recurrent temporal association between TIND and rapid HbA1c reduction, but cannot establish causality or prognosis. TIND should be recognized early, and gradual, monitored glycemic correction may be reasonable in high-risk patients.

J. Clin. Med.

9 November 2026

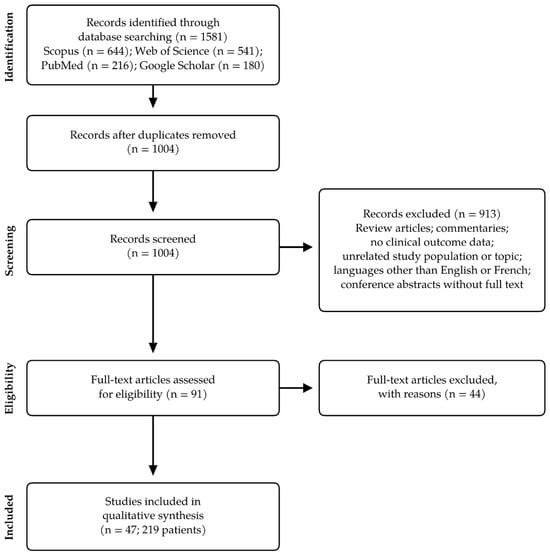
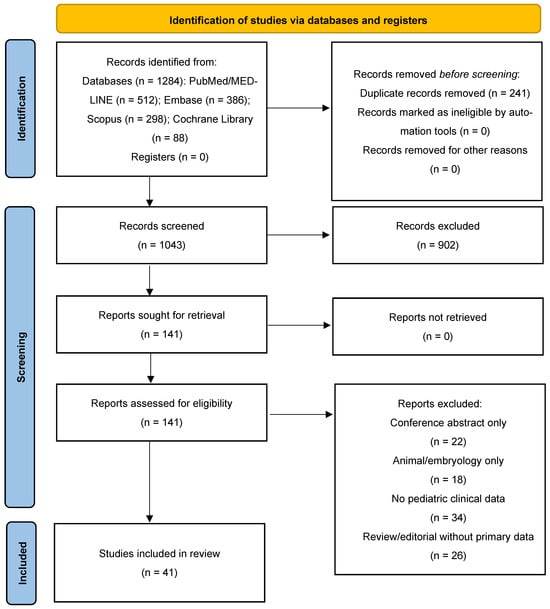
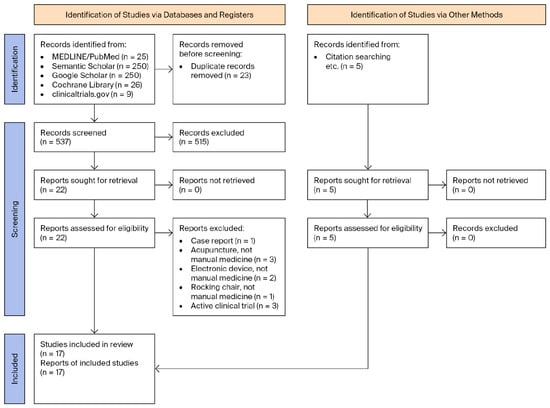
PRISMA flow diagram of the study selection process.
  • Case Report
  • Open Access

Background: Ecthyma gangrenosum (EG) associated with Pseudomonas aeruginosa can be life-threatening in immunocompromised patients with haematological malignancies. Severe neutropenia and antimicrobial resistance complicate treatment, while the roles of surgery and supportive therapies remain uncertain. Methods: We retrospectively reviewed five paediatric patients with leukaemia who developed life-threatening P. aeruginosa infections during chemotherapy. Cases were identified through a tertiary paediatric oncology centre’s clinical registry and verified using archived medical records. Clinical, microbiological, therapeutic, and outcome data, including surgical interventions, supportive therapies, and chemotherapy interruptions, were analysed. Results: All five patients developed severe infections during chemotherapy. EG affected the perineal or genital region in several cases, including two cases of Fournier’s gangrene. Four patients underwent surgical excision or debridement; surgery was not feasible in one because of critical deterioration. All received antimicrobials, with regimens adjusted according to microbiological findings and susceptibility profiles. Supportive treatments included granulocyte colony-stimulating factor, immunoglobulins, and granulocyte transfusions. Two patients survived into adulthood, including one who remained in remission after haematopoietic stem cell transplantation; three died, one from infection-associated multiorgan failure before surgery, one following leukaemia relapse, and one from post-transplant complications. Infection and its treatment substantially delayed or modified chemotherapy. Conclusions: EG associated with P. aeruginosa during paediatric leukaemia treatment can cause death and disrupt anticancer therapy. Early multidisciplinary assessment, appropriate antimicrobial treatment, and timely surgical management of necrotic tissue should be considered when feasible. Immunomodulatory interventions and discharge between chemotherapy cycles may benefit selected patients, but their efficacy cannot be established from this small retrospective series. Further multicentre studies are needed to clarify optimal management.

J. Clin. Med.

9 November 2026

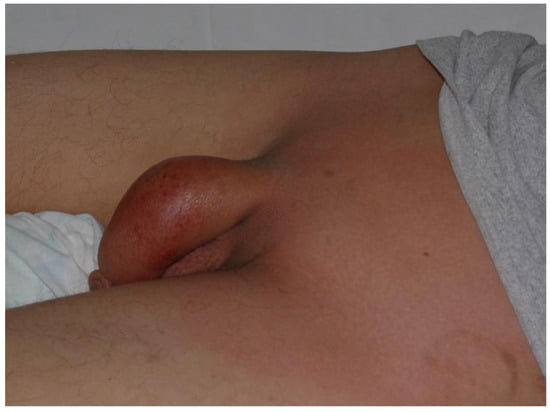
Initial presentation of Fournier’s gangrene in a 17-year-old boy.
  • Article
  • Open Access

Background/Objectives: To compare the postoperative analgesic efficacy of the serratus posterior superior intercostal plane (SPSIP) block and pectoral nerve block II (PECS II) in patients undergoing unilateral modified radical mastectomy (MRM). Methods: This single-center retrospective cohort study included 100 patients who underwent unilateral MRM and received either an SPSIP block (n = 34) or a PECS II block (n = 66). The primary outcome was the time from extubation to the first administration of rescue analgesia. Secondary outcomes included Numeric Rating Scale (NRS) pain scores at 1, 4, 8, and 12 h postoperatively, the maximum NRS pain score, and cumulative opioid consumption within the first 24 postoperative hours. The primary outcome was analyzed using a generalized linear model with a gamma distribution and log-link function adjusted for operative duration. A sensitivity analysis additionally adjusted for age, body mass index, American Society of Anesthesiologists (ASA) physical status, and smoking status. Results: Among 100 patients (SPSIP, n = 34; PECS II, n = 66), operative duration was longer in the PECS II group (p < 0.001). Time to first rescue analgesia was longer with SPSIP (7.5 [5.0–8.8] vs. 5.0 [3.0–8.0] h; p = 0.004), but the difference was not significant after adjustment for operative duration (exp(B) = 1.21, 95% CI 0.98–1.49; p = 0.077) or additional covariates (exp(B) = 1.17, 95% CI 0.94–1.46; p = 0.153). NRS scores were lower with SPSIP at 1 h (p < 0.001) and with PECS II at 8 and 12 h (Holm-adjusted p = 0.013 and p < 0.001). Twenty-four-hour tramadol consumption was similar (p = 0.922). No block-related complications were documented. Conclusions: After adjustment for operative duration, the longer time to first rescue analgesia observed in the SPSIP group did not retain statistical significance, and a similar result was obtained in the sensitivity analysis. The findings should be interpreted cautiously in view of the retrospective design and limited sample size.

J. Clin. Med.

9 November 2026

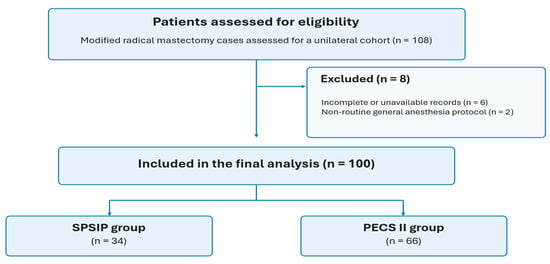
Patient selection flow diagram.
  • Review
  • Open Access

Background: Kidney stone disease is increasingly prevalent worldwide, resulting in a growing use of ureteroscopy (URS) for stone management. Although URS is generally safe and effective, elevated intrarenal pressure (IRP) during the procedure may contribute to perioperative morbidity, particularly infectious complications. Excessive IRP can promote intrarenal backflow into tubular, venous, lymphatic, and interstitial compartments, potentially resulting in tissue injury, impaired renal perfusion, and systemic exposure to bacteria and endotoxins. Advances in pressure-monitoring technology have enabled continuous intraoperative assessment of IRP and highlighted substantial pressure variability and transient spikes during routine URS. Methods: This narrative review examines the historical understanding and contemporary evidence surrounding IRP during URS, based on a structured search of PubMed/MEDLINE, the Cochrane Library and Europe PMC (January 1980 to October 2026), supplemented by manufacturer and regulatory sources. The review evaluates current approaches to IRP measurement, the pathophysiological and clinical consequences of elevated pressure, patient-specific susceptibility, and strategies aimed at pressure mitigation. Results: Available experimental and clinical evidence indicates that elevated IRP may contribute to acute renal tissue injury, impaired renal perfusion and intrarenal backflow, although most reported pressure thresholds derive from experimental models rather than validated human safety limits. IRP is influenced by irrigation inflow, outflow resistance, and renal compliance, and may vary considerably during URS, with transient pressure spikes occurring even during routine procedures. Multiple strategies can reduce IRP. Novel pressure-guided platforms integrating real-time pressure monitoring with automated irrigation and suction control can regulate IRP in early studies, but evidence that they improve clinical outcomes remains limited. Suction-assisted access sheaths are associated with fewer postoperative infectious complications in comparative studies, although this benefit has not been shown to result specifically from IRP reduction. Conclusions: IRP is an increasingly recognised and potentially modifiable determinant of safety during ureteroscopy. Further clinical research, including standardised reporting of IRP metrics, is required to establish clinically relevant pressure thresholds and determine whether pressure-guided URS improves patient outcomes. The integration of real-time monitoring with automated irrigation and suction control represents a promising direction toward safer, pressure-conscious endourological practice.

J. Clin. Med.

9 November 2026

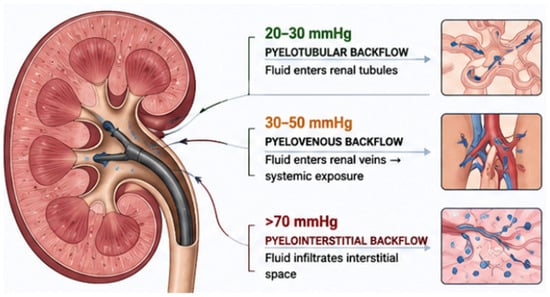
Schematic representation of IRP and IRB pathways. The pressure ranges and backflow pathways shown are derived predominantly from experimental and animal studies and do not represent validated human clinical thresholds [15,18]. Figure generated with AI assistance (Chat GPT 5.5) [17].

Featured Articles of Last Quarter

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
J. Clin. Med. - ISSN 2077-0383