Skip to Content

Journal of Clinical Medicine

Journal of Clinical Medicine is an international, peer-reviewed, open access journal of clinical medicine, published semimonthly online by MDPI. The International Bone Research Association (IBRA), Spanish Society of Hematology and Hemotherapy (SEHH), Japan Association for Clinical Engineers (JACE), European Independent Foundation in Angiology/ Vascular Medicine (VAS) and others are all affiliated with JCM, and their members receive a discount on article processing charges.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (53,140)

  • Review
  • Open Access

The Biomarker Revolution in Kidney Transplantation

  • Elizabeth Cho,
  • Yvette Y. Lopez and
  • Sami Alasfar

Since the first successful kidney transplant in 1954, transplant medicine has advanced significantly, achieving favorable one-year outcomes. However, despite excellent short-term outcomes, long-term renal allograft survival remains sub-optimal, with acute rejection continuing to be a major contributor to death-censored allograft loss. Current approaches for post-transplant surveillance and rejection monitoring rely on either nonspecific markers that often detect injury late in their course or invasive procedures associated with procedural risks and complications. To address these limitations, numerous non-invasive biomarkers have been introduced into solid organ transplantation research with the goal of improving allograft surveillance, facilitating earlier detection of rejection and complementing existing diagnostic approaches. Although several biomarkers have demonstrated clinical promise, none currently possess sufficient accuracy to replace kidney allograft biopsy. Biomarkers under investigation include blood-, tissue- and urine-based specimens. Their development and validation as independent markers have been limited by smaller sample size, heterogenous targets, variable performance characteristics and suboptimal sensitivity and specificity. In response, the field has increasingly shifted toward multimodal approaches that combine biomarkers and incorporate artificial intelligence to improve diagnostic accuracy and outcomes prediction. This review summarizes current biomarkers, discusses their limitations and explores future directions for biomarker development and clinical implementation.

J. Clin. Med.

30 September 2026
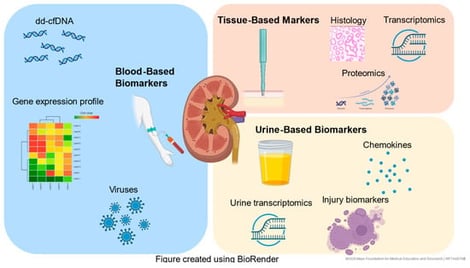
Current landscape of biomarkers: blood-based, urine-based and tissue-based tests. Blood-based biomarkers are minimally invasive and include dd-cfDNA, gene expression profiling and viruses. Tissue-based biomarkers measure sets of transcriptional signatures to define a disease phenotype. Urine-based biomarkers such as chemokines, cytokines, mRNA and urinary exosomal mRNA, can offer direct insight into the allograft microenvironment.
  • Article
  • Open Access

Background/Objectives: Faricimab is a bispecific antibody targeting vascular endothelial growth factor A and angiopoietin-2, developed to extend treatment intervals in neovascular age-related macular degeneration (nAMD). Real-world evidence on faricimab within the Polish national drug program remains scarce. This study aimed to assess one-year clinical and treatment outcomes of faricimab for nAMD using real-world data from the Polish Therapeutic Program Monitoring System (SMPT). Methods: In this retrospective, non-randomized registry study, 322 patient-eye records treated with faricimab within the national drug program between January 2024 and April 2025 were analysed. Eligibility required at least 360 days between the first and last injections. Eyes were stratified into treatment-naïve (n = 70) and continuation (switched from another anti-vascular endothelial growth factor (anti-VEGF) agent; n = 252). Results: Median baseline best-corrected visual acuity (BCVA) was 70 [60, 77] letters overall, with no significant difference between subgroups (p = 0.59). At one year, treatment-naïve eyes improved to 75 [66, 79] letters (Δ +5 [0, 10]), whereas continuation eyes were maintained (Δ 0 [−5, 5]; between-group p < 0.001). A clinically meaningful (≥10-letter) gain occurred in 16% of eyes overall, more often in treatment-naïve than continuation eyes (27% vs. 12%; p = 0.004). Central retinal thickness (CRT) decreased significantly in all subgroups, with a greater reduction in treatment-naïve eyes. Intraocular pressure (IOP) remained stable (median Δ 0 mmHg). Patients received a median of 8 [7, 8] injections; injection numbers fell from 5 [4, 5] in the first half-year to 3 [2, 3] in the second, and intervals extended from approximately four to eight weeks. Conclusions: Within the Polish program, one year of faricimab was associated with stable-to-improved vision, anatomical improvement, and progressive extension of injection intervals after the mandated loading phase. Given the observational, single-arm design and the persister-only cohort, findings represent associations rather than comparative effectiveness.

J. Clin. Med.

30 September 2026
Clinical outcomes over the first year of faricimab treatment in treatment-naïve (n = 70) and continuation (n = 252) eyes. Box plots show (A) best-corrected visual acuity (BCVA, ETDRS letters), (B) central retinal thickness (CRT, µm), and (C) intraocular pressure (IOP, mmHg) at baseline, the first half-year, and one year. Boxes show the median and interquartile range; whiskers extend to 1.5 × IQR; points are outliers. In panel (B), the y-axis is truncated at 550 µm (25 values above this range not shown).
  • Systematic Review
  • Open Access

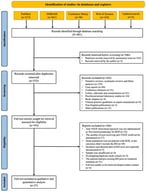
Objectives: To estimate the incidence of reported retinal detachment (RD) after primary anti-vascular endothelial growth factor (anti-VEGF) treatment for retinopathy of prematurity (ROP) and to explore study-level factors associated with RD incidence. Methods: PubMed, EMBASE, Cochrane Library, and Web of Science were searched up to 24 May 2026, for English-language studies reporting RD outcomes after anti-VEGF monotherapy for ROP. Pooled incidence was estimated with a random-effects model using Freeman–Tukey double arcsine transformation. Heterogeneity, subgroup differences, publication bias, and leave-one-out sensitivity were assessed. Results: Twenty-seven studies (5598 eyes; 135 RD events) were included, comprising twelve case series, thirteen cohort studies, and two randomized controlled trials; thus, the evidence was predominantly retrospective. The pooled RD incidence was 1.4% (95% CI, 0.5–2.7%; I2 = 80.8%). The estimate remained stable on leave-one-out sensitivity analysis; the exclusion of Tong et al. markedly reduced heterogeneity. Higher RD incidence was observed in Asian studies, single-center studies, and studies with predominantly Zone I ROP or aggressive ROP (AROP). Incidence varied by postmenstrual age at treatment, gestational age, birth weight, and anti-VEGF agent. No significant publication bias was detected. Conclusions: RD after primary anti-VEGF therapy for ROP is uncommon but sight-threatening, with higher incidence associated with greater disease severity and postmenstrual age. Prolonged, risk-stratified follow-up is warranted for infants with Zone I or AROP. Standardized RD definitions, subtype classification, and severity-adjusted prospective comparisons are needed.

J. Clin. Med.

30 September 2026
The PRISMA flow diagram detailing the literature search and selection.
  • Technical Note
  • Open Access

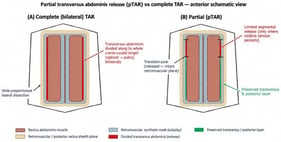
Background: Posterior component separation with transversus abdominis release (TAR) enables tension-free reconstruction of large midline incisional hernias but, when performed as a complete bilateral release, may expose selected patients to extensive lateral dissection and related morbidity. In daily practice, many surgeons already limit the release to the segment that is strictly required (“tailored”, “limited” or “modified” TAR), but this conservative use of TAR has never been explicitly defined, illustrated or reported in a reproducible way. We define this approach as partial transversus abdominis release (pTAR) and describe it in a standardized, stepwise fashion, reporting the preliminary outcomes of an initial single-surgeon series. Methods: We retrospectively reviewed all patients who underwent open midline incisional hernia repair with retromuscular synthetic mesh and pTAR performed by a single surgeon at a single center between January 2024 and January 2025. Complex hernias were defined a priori. Continuous variables are reported as mean ± standard deviation. The report is a technical note and preliminary case series. Results: Ten patients with complex W2–W3 midline incisional hernias were included. pTAR was performed in the subxiphoid segment in eight cases and in the periumbilical/middle segment in two cases. No major intraoperative complications occurred. Two patients developed a postoperative seroma, both classified as surgical site occurrences (SSO) not requiring intervention. One recurrence and one readmission were recorded; no reoperation or death occurred. Conclusions: pTAR is presented as a reproducible, standardized variant of posterior component separation rather than as a novel operation or as proof of superiority over complete TAR. Since this is a small, retrospective, single-surgeon, single-center series with a follow-up shorter than 12 months, the data demonstrate feasibility only; the hypothesized tissue-sparing advantage must be tested in prospective, registered, comparative studies.

J. Clin. Med.

30 September 2026
Schematic anterior view of the abdominal wall comparing complete (bilateral) transversus abdominis release (A) with partial TAR (pTAR) (B). In complete TAR, the transversus is divided along its whole cranio–caudal length bilaterally, with wide preperitoneal dissection. In pTAR the transversus and posterior layer are preserved except over the limited segment where midline tension persists; the transition zones between the released and the intact retromuscular plane are indicated. The retromuscular synthetic mesh is placed in the same plane in both techniques.

Featured Articles of Last Quarter

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

Chronic Complications of Type 2 Diabetes
Reprint

Chronic Complications of Type 2 Diabetes

Prevalence, Prevention, and Management
Editors: Ilias Migdalis
Sleep and Circadian Rhythms in Patients with Physical and Mental Disorders
Reprint

Sleep and Circadian Rhythms in Patients with Physical and Mental Disorders

Editors: Argyro Pachi, Ioannis Ilias, Athanassios Tselebis
XFacebookLinkedIn
J. Clin. Med. - ISSN 2077-0383