- Article

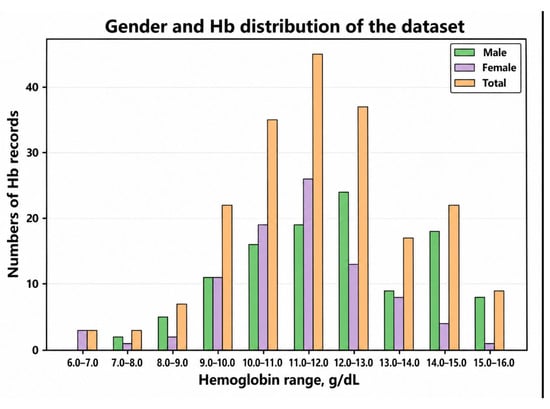
Background: Hemoglobin (Hb) is a key perioperative indicator of oxygen transport and tissue oxygenation. Intraoperative Hb measurement currently relies mainly on arterial blood gas analysis or laboratory testing, both of which are accurate but invasive and intermittent. This study evaluated the preliminary performance of a self-developed multi-wavelength photoplethysmography (PPG)-based non-invasive Hb detection system and assessed the effect of individualized calibration. Methods: This prospective observational study included 61 adults undergoing elective non-cardiac surgery with invasive arterial monitoring. Intraoperative multi-wavelength PPG signals and arterial blood gas Hb values were collected simultaneously. PPG-derived features were used to develop machine-learning models for Hb estimation. Model performance was evaluated using Pearson correlation, Bland–Altman analysis, and the proportions of predictions with absolute errors ≤ 1.0 g/dL and ≤1.5 g/dL. Performance before and after individualized calibration was compared. Results: A total of 200 paired Hb–PPG observations were obtained. Before calibration, the bias between predicted and reference Hb was 0.006 g/dL, with 95% limits of agreement (LoA) from −2.869 to +2.880 g/dL, and the correlation was moderate (r = 0.661). Absolute errors ≤ 1.0 g/dL and ≤1.5 g/dL were observed in 49.22% and 66.84% of predictions, respectively. After calibration using each patient’s first quality-controlled Hb measurement as individualized prior information, the bias was −0.006 g/dL, the 95% LoA narrowed to −1.834 to +1.822 g/dL, and the correlation increased to 0.870. The proportions of predictions with absolute errors ≤ 1.0 g/dL and ≤1.5 g/dL increased to 70.68% and 90.23%, respectively. Conclusions: The proposed multi-wavelength PPG-based system showed preliminary feasibility for non-invasive intraoperative Hb estimation. Individualized calibration further improved prediction accuracy and agreement, indicating the importance of patient-specific baseline information. At this stage, the system should be regarded as an adjunctive monitoring tool rather than a replacement for arterial blood gas analysis or laboratory Hb testing.
22 November 2026