
Skip to Content

Diabetology

Diabetology is an international, peer-reviewed, open access journal on diabetes research published monthly online by MDPI.  
  • Open Access— free for readers, with article processing charges (APC) paid by authors or their institutions.
  • High Visibility: indexed within  ESCI (Web of Science)ScopusEBSCO, and other databases.
  • Rapid Publication: manuscripts are peer-reviewed and a first decision is provided to authors approximately 22.6 days after submission; acceptance to publication is undertaken in 6.9 days (median values for papers published in this journal in the first half of 2026).
  • Journal Rank: CiteScore - Q2 (Medicine (miscellaneous))
  • Recognition of Reviewers: Reviewers whose reports are timely and of high quality receive an APC discount voucher for a future publication in an MDPI journal. Become a reviewer.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (524)

Contemporary diabetes care is largely organised around one-to-one clinical consultations and the regulation of biomedical outcomes. While such approaches remain essential, they may be insufficient for addressing the social and behavioural aspects of chronic disease management. Based on this conceptual perspective, we propose the Friendly Neighbourhood Hospital as an approach to supporting peer contact and self-management, complementing clinical care. Drawing on affordance theory, social architecture, and urban social geography, we argue that hospital environments can shape participation, learning, and behavioural change through mechanisms including peer interaction, tacit knowledge, situated learning, and institutional trust. We illustrate this approach using five settings: communal cooking, movement and social interaction, public and cultural events, flexible access, and digital participation. These examples are illustrative and not evaluated interventions, and their anticipated effects, ranging from immediate participation and belonging to longer-term behavioural change, remain hypotheses for future testing. From this perspective, we do not advocate for replacing individual consultations but rather for repositioning them within a broader social and spatial context.

Diabetology

11 September 2026
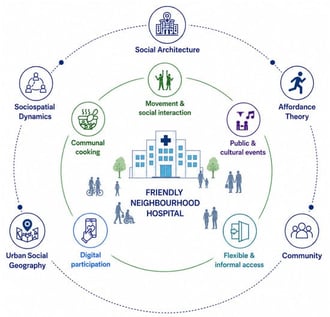
Conceptual illustration of the Friendly Neighbourhood Hospital. The central concept is surrounded by five illustrative settings for participation and engagement, while the outer circle represents the theoretical perspectives informing how these opportunities may be shaped by social and spatial environments.

Background/Objectives: Type 2 diabetes (T2D) is one of the fastest growing chronic pediatric conditions worldwide. Indigenous children tend to be diagnosed younger, have severe progression of disease, and poorer health outcomes. While biomedical advancements have yielded more effective treatment outcomes, few resources have been implemented to prevent T2D in Indigenous youth. Therefore, an exploratory pilot study was conducted in one Canadian province with an overall purpose of co-creating, pilot-testing, and evaluating an Indigenous community-led T2D education resource called the wîcihitowin: Helping Each Other with Type 2 Diabetes Education Program. Methods: Data for this analysis were derived from a pre- and post-test evaluation of the digital education resource with a purposeful sample of Indigenous youth (n = 87) from two Cree communities living in a western Canadian province. Descriptive statistics, paired t-tests, and correlations were used to measure the differences from pre- to post-participation in the education program. Results: The youth had moderate knowledge baseline scores of diabetes, nutrition, and physical activity. Participants reported improved knowledge on all the education topics after participating in the wîcihitowin: Helping Each Other with Type 2 Diabetes Program. Significant positive correlations were found between all knowledge areas. Conclusions: The digital education resource effectively enhanced youths’ knowledge of diabetes, nutrition, and physical activity. Additionally, these findings highlighted the importance of culturally safe teachings for Indigenous peoples, emphasizing the need for T2D education to be community and culturally driven. These results are particularly important given the lack of existing evidence evaluating the effectiveness of T2D education among Indigenous youth.

Diabetology

10 September 2026

Diabetes disproportionately affects African American and Native American populations in the United States; however, diabetes disparities are frequently examined either collectively across minority populations or within individual groups, limiting understanding of the distinct mechanisms that drive inequities. This narrative review compares differences in diabetes diagnosis, culturally grounded management, diabetes self-management education and support (DSMES), and diabetes-related complications among African American and Native American adults in the United States to identify both shared and population-specific pathways contributing to disparities. A narrative review of peer-reviewed literature published between 2010 and 2025 was conducted using PubMed, Scopus, and Google Scholar. Studies addressing diabetes diagnosis, management, diabetes education, or complications among African American and Native American adults were included and synthesized using a comparative thematic approach. Disparities were evident across the continuum of diabetes care, but their underlying drivers differed substantially between populations. Among African Americans, diagnostic challenges reflected both structural inequities and limitations of commonly used glycemic markers such as hemoglobin A1c. Among Native Americans, delayed diagnosis was more closely associated with geographic isolation and under-resourced healthcare systems. Culturally grounded management also differed, with Native American communities demonstrating greater integration of Indigenous frameworks and traditional practices, whereas African American communities relied more heavily on family- and faith-based support systems. DSMES remained underutilized in both populations because of referral gaps, structural barriers, and limited cultural tailoring, with access barriers particularly pronounced in rural and tribal settings. Both populations experienced disproportionately high rates of diabetes-related complications, although Native Americans frequently exhibited earlier onset while African Americans often experienced greater severity of outcomes. Findings suggest that similar diabetes disparities emerge through different structural, cultural, and healthcare system pathways. Recognizing these differences can inform the development of more targeted clinical interventions, community-based programs, and health policies aimed at reducing diabetes inequities in underserved populations.

Diabetology

10 September 2026

Background: Calcaneal osteomyelitis is a severe form of diabetic foot osteomyelitis associated with poor healing, major amputation, and increased mortality. Evidence on the use of bone graft substitutes in this setting remains limited. Methods: We conducted a retrospective single-center cohort study including 103 consecutive patients with diabetic calcaneal osteomyelitis treated at a tertiary diabetic foot center. In total, 29 patients received bone graft substitutes following surgical debridement, while 74 underwent conventional surgical treatment. Outcomes included healing, time to healing, major amputation, and mortality for all-cause. Results: Overall healing rates were similar between the bone graft and control groups (58.6% vs. 54.1%; p = 0.83). However, healing within one year was more frequent in patients treated with bone graft substitutes (65.4% vs. 45.8%). In multivariable analysis, bone graft substitute treatment was independently associated with healing within one year (OR 4.96, 95% CI 1.18–20.79; p = 0.029). Median healing time was significantly shorter in the bone graft group (90 [IQR 60–120] vs. 210 [IQR 150–370] days; p < 0.001), corresponding to a 67% reduction after adjustment. Major amputation rates were low and comparable between groups (10.3% vs. 13.5%; p = 0.75). Observed three-year mortality was lower in the bone graft group (33.3% vs. 54.8%), and bone graft substitute treatment remained independently associated with reduced 3-year mortality (OR 0.29, 95% CI 0.09–0.88; p = 0.028). Conclusions: In diabetic calcaneal osteomyelitis, bone graft substitutes were associated with faster healing, improved 1-year healing outcomes, and lower long-term mortality, while maintaining high limb-salvage rates. These findings suggest that bone graft substitutes may represent a promising adjunct to surgical treatment and warrant confirmation in prospective studies.

Diabetology

9 September 2026

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

Risk of Type 2 Diabetes Mellitus
Reprint

Risk of Type 2 Diabetes Mellitus

Cardiorenometabolic Syndrome and Its Components
Editors: Andrej Belančić, Bojan Jelaković, Martina Matovinović
Feature Papers in Diabetology 2023
Reprint

Feature Papers in Diabetology 2023

Editors: Peter Clifton
XFacebookLinkedIn
Diabetology - ISSN 2673-4540

