- Systematic Review

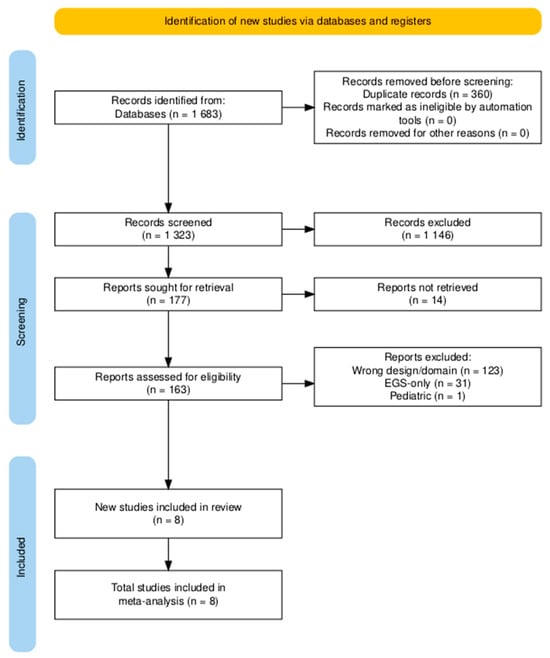
Background/Objectives: GLP-1 and dual GLP-1/GIP receptor agonists (GLP-1 RAs) delay gastric emptying, increasing residual gastric content (RGC) during upper endoscopy (EGS) under standard fasting. Concurrent colonoscopy requires 24–48 h of a clear-liquid diet and osmotic bowel preparation, which may mitigate this risk without drug interruption. We conducted a systematic review and meta-analysis to quantify RGC rates in GLP-1 RA users undergoing combined same-session EGS and colonoscopy compared with EGS alone. Methods: MEDLINE and Cochrane CENTRAL were searched without date restriction. We included studies enrolling adults on GLP-1 RAs undergoing elective EGS with or without concurrent colonoscopy. The primary outcome was clinically significant RGC at the time of endoscopy. Random-effects inverse-variance meta-analysis was performed. Risk of bias was assessed with ROBINS-I and RoB 2. Certainty of evidence was assessed using the GRADE framework. Results: Of 1683 records identified, eight studies met eligibility criteria and were included. RGC rates in combined-procedure groups ranged from 0% to 4.9%. Pooled analysis demonstrated significantly higher odds of RGC among EGS-alone patients (OR 3.76, 95% CI 2.81–5.03; I2 = 0%). The effect was consistent across observational studies (OR 3.71, 95% CI 2.77–4.96; I2 = 0%) and directionally equal in the single RCT. No procedure was aborted due to RGC in the combined-procedure groups. Conclusions: In adults on GLP-1 RAs, concurrent colonoscopy with standard bowel preparation appears to effectively mitigate RGC risk during same-session EGS across eight studies with consistent, large-magnitude effect estimates. These findings support the hypothesis that bowel preparation achieves adequate gastric emptying, potentially obviating routine GLP-1 RA interruption in this procedural context.
12 November 2026