Skip to Content
  • 5.5
    Impact Factor
  • 10.2
    CiteScore
  • 17 days
    Submission to First Decision
  • 3 days
    Acceptance to Publication

Antibiotics

Antibiotics is an international, peer-reviewed, open access journal on all aspects of antibiotics, published monthly online by MDPI. The Croatian Pharmacological Society (CPS) and Northern Greece Society of Medical Biopathology (EIBBE) are affiliated with Antibiotics, and their members receive discounts on the article processing charges.
  • Open Access— free for readers, with article processing charges (APC) paid by authors or their institutions.
  • High Visibility: indexed within Scopus, SCIE (Web of Science), PubMed, PMC, Embase, CAPlus / SciFinder, and other databases.
  • Journal Rank: JCR - Q1 (Infectious Diseases) / CiteScore - Q1 (General Pharmacology, Toxicology and Pharmaceutics )
  • Rapid Publication: manuscripts are peer-reviewed and a first decision is provided to authors approximately 16.4 days after submission; acceptance to publication is undertaken in 2.9 days (median values for papers published in this journal in the first half of 2026).
  • Recognition of Reviewers: Reviewers whose reports are timely and of high quality receive an APC discount voucher for a future publication in an MDPI journal. Become a reviewer.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (10,226)

  • Article
  • Open Access

Background: Antimicrobial administration is a major contributor to healthcare-associated waste. We evaluated the environmental impact of changing the default metronidazole dosing frequency from three-times-daily (TID) to twice-daily (BID) administration in a three-hospital system. Methods: We conducted a quasi-experimental uncontrolled interrupted time-series study across an integrated health system. Inpatient oral and intravenous metronidazole utilization was assessed from January 2023 through December 2024, before and after a change in the default metronidazole dosing on 1 February 2024. Overall utilization was measured as days of therapy (DOT)/1000 days present (DP), and frequency-specific utilization was standardized as dispensed doses/1000 DP. Plastic waste was estimated using EcoRxChoice, and modeled disposal-related carbon dioxide-equivalent (CO2e) emissions reflected facility-specific incineration and transportation processes. Results: Overall metronidazole utilization remained similar (36.4 pre-intervention vs. 37.2 DOT/1000 DP post-intervention). After implementation TID utilization decreased relative to baseline (−4.41 dispensed doses/1000 DP per month; 95% CI, −6.02 to −2.80 p < 0.001), whereas twice-daily utilization increased (+1.32 dispensed doses/1000 DP per month; 95% CI, 0.37 to 2.27 p = 0.007). Mean modeled plastic waste decreased from approximately 200 to 164 kg/month. Over the 11-month post-intervention period, the monthly trend decreased by 14.63 kg/month relative to the pre-intervention trend (95% CI, −21.42 to −7.83; p < 0.001) and modeled disposal-related 351.3 kg of CO2e. Conclusions: Optimizing antibiotic dosing frequency is a simple, scalable antimicrobial stewardship strategy that was associated with reductions in modeled metronidazole plastic waste and modeled disposal-related emissions while leveraging the established clinical non-inferiority of twice-daily metronidazole dosing.

Antibiotics

18 October 2026
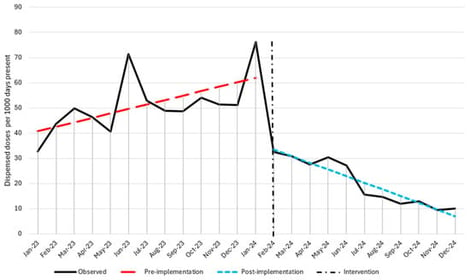
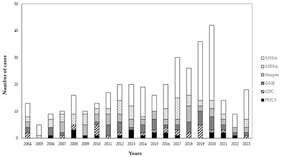
Monthly defined daily dose of three-times-a-day metronidazole before and after implementation.
  • Article
  • Open Access

Background: Temocillin is a narrow-spectrum β-lactam with activity against extended-spectrum β-lactamase (ESBL)- and AmpC-producing Enterobacterales and represents a potential carbapenem-sparing option, especially for urinary tract infections (UTIs). This multicentre study evaluated the real-world use, clinical outcomes, and tolerability of temocillin in Italian clinical practice. Methods: We retrospectively included adults treated with temocillin for UTIs, with or without concomitant bloodstream infection, for at least 5 days at three Italian hospitals between November 2024 and May 2026. Data were collected from electronic medical records. Results: The study included 30 patients. Median age was 51 years (IQR 39–74); 50% presented with sepsis and 40% had UTI-associated bacteraemia. Pyelonephritis was the most common presentation (53.3%). At least one positive culture was obtained in 76.7% of patients, yielding 28 isolates. Of these, 27 were Enterobacterales, and 21/27 (77.8%) were ESBL producers. E. coli accounted for 64.3% of all isolates. Temocillin was administered at 6 g/day in 80% of patients and by continuous infusion in 76.7%. Outpatient parenteral antimicrobial therapy (OPAT) using elastomeric pumps was used in 16.7% of patients. Clinical success at the end of the overall antimicrobial treatment course was achieved in 28/30 patients (93.3%; 95% CI 77.9–99.2%). No recurrence occurred within 30 days, and no treatment-related adverse events directly attributable to temocillin were recorded. Two patients developed Clostridioides difficile infection within 60 days after treatment completion, with no established causal relationship with temocillin. Conclusions: This first Italian multicentre real-world experience reports favourable clinical outcomes with temocillin in UTIs, including in selected patients with sepsis or UTI-associated bloodstream infection, and describes the use of continuous infusion and OPAT in appropriately selected patients.

Antibiotics

17 October 2026

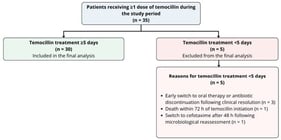
Patient selection flowchart. Flowchart of patient selection during the study period. Thirty-five patients received at least one dose of temocillin; 30 received temocillin for ≥5 days and were included in the final analysis, while 5 received temocillin for &lt;5 days and were excluded. Reasons for treatment duration &lt; 5 days are detailed in the figure.
  • Article
  • Open Access

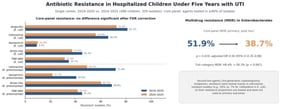
Background/Objectives: We evaluated changes in antibiotic resistance among urine culture isolates from children under five years hospitalized with urinary tract infection (UTI) at a single center in 2019–2020 and 2024–2025. Methods: This retrospective, repeated cross-sectional study included 498 children and analyzed 359 isolates of Escherichia coli, Klebsiella pneumoniae, Pseudomonas aeruginosa, and Proteus spp. As second-line agents were tested selectively, primary outcomes (defined post hoc) were resistance to a core panel of agents tested in at least 90% of isolates and core-panel multidrug resistance (MDR) in Enterobacterales; other comparisons were exploratory. Fisher’s exact test, Benjamini–Hochberg correction, and adjusted Firth regression were used. Results: Second-line agents were tested mainly in cefuroxime-resistant isolates (95% vs. 7% for ceftazidime in E. coli), biasing resistance estimates. In the core panel, no difference was significant in E. coli, and the decrease in cefuroxime resistance in K. pneumoniae did not survive correction. Core-panel MDR was lower in 2024–2025 (51.9% vs. 38.7%; p = 0.019; adjusted OR 0.56, 95% CI 0.35–0.88); full-category MDR was not (68.4% vs. 58.3%; p = 0.067). Conclusions: Differences may reflect testing practices and case mix rather than true changes in resistance. Findings apply only to hospitalized children under five years at this center and require confirmation.

Antibiotics

16 October 2026

Flow diagram of the study population. UTI, urinary tract infection. Target species: E. coli, K. pneumoniae, P. aeruginosa, and Proteus spp.
  • Review
  • Open Access

Background: It is estimated that approximately 20–30% of women suffer from recurrent urinary tract infections (rUTIs). The disease is primarily bacterial, especially Escherichia coli, making antibiotics the standard treatment. Increasing antibiotic resistance of uropathogens reduces treatment effectiveness. Therefore, non-antibiotic approaches are increasingly being investigated for the management of rUTIs. This narrative review provides a comprehensive overview of currently available and emerging methods of treatment and prevention of rUTIs in women. Methods: This paper employs a narrative review with a structured literature search and synthesizes data from three major databases, including PubMed, Web of Science, and Scopus. The review was conducted in accordance with the Scale for the Assessment of Narrative Review Articles (SANRA) checklist. Scientific articles were searched using the following keywords: ‘recurrent urinary tract infections in women’, ‘antibiotic prophylaxis’, ‘immunoprophylaxis’, ‘urinary microbiome’. Results: Observational evidence has reported an association between continuous antibiotic prophylaxis and severe outcomes, including pyelonephritis and septicemia; however, these findings are susceptible to confounding by indication and should not be interpreted as evidence of a causal relationship. Clinical studies suggest that immunomodulatory approaches, such as OM-89 bacterial lysate, next-generation polybacterial mucosal vaccines (e.g., MV140), and oral immunostimulants, have potential to reduce the frequency of rUTI recurrences in women, although the strength and certainty of evidence vary between interventions. Bacteriophage therapy is an emerging and exploratory targeted approach supported by early clinical and experimental evidence, but its efficacy for preventing recurrent uncomplicated UTIs remains uncertain, though rapid development of phage resistance remains a potential limitation. Prophylactic strategies, including Lactobacillus-based probiotics, low-dose estriol, and microbiota transplantation, have shown preliminary or variable results, with limited evidence for rUTI prevention. In particular, findings on vaginal dysbiosis and microbiota modulation should not be interpreted as a direct evidence of rUTI prevention. Conclusions: While antibiotic therapy remains essential, continuous prophylaxis may contribute to antimicrobial resistance and disrupt microbial balance. Therefore, novel therapeutic strategies are still being studied. Several non-antibiotic strategies, including immunoprophylaxis and microbiome modulation, represent potential preventive approaches, whereas bacteriophage therapy and vaginal microbiota transplantation remain exploratory and require further clinical validation. Their preventive efficacy against rUTIs remains unestablished. Moreover, antimicrobial peptides (AMPs), nanotechnology, molecularly targeted therapies, and precision medicine strategies are being investigated. Plant-based therapies may provide benefit, but their clinical efficacy remains to be established. Overall, further clinical studies are needed to confirm the preventive efficacy of these emerging approaches.

Antibiotics

16 October 2026

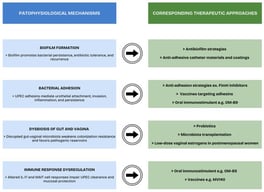
Pathophysiological background of recurrent UTIs with corresponding therapeutic approaches. Abbreviations: UPEC—Uropathogenic Escherichia coli; IL—interleukin; MAIT—Mucosal-associated invariant T.

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

Antibiotic Resistance in a One Health Context
Reprint

Antibiotic Resistance in a One Health Context

Bridging Environmental, Agricultural, Nutritional, Veterinary, and Clinical Perspectives
Editors: Pedro A. Jiménez Gómez, Marina Robas Mora
Microbial Natural Products as a Source of Novel Antimicrobials
Reprint

Microbial Natural Products as a Source of Novel Antimicrobials

Editors: Patricia Branco, Marc Maresca, Elisabete Muchagato Mauricio, Luisa Brito
XFacebookLinkedIn
Antibiotics - ISSN 2079-6382