

-
Safety and Early Clinical Outcomes of Sacroiliac Fusion for Sacral Fractures via a Modified S1 Corridor: An Exploratory Comparison of Triangular and Threaded 3D-Printed Titanium Implants -
Robotic-Assisted Total Hip Arthroplasty: Implications for Surgical Practice and Operating Theatre Design -
Bleeding Events During Anticoagulation After Acute Pulmonary Embolism: Real-Life Experience -
An Inflammation-Adjusted Framework for Nutritional Assessment in Multimorbid Patients with Advanced Neurological Diseases -
Volume and Structure of Maxillofacial Trauma Before, During, and After COVID-19 Restrictions: A Multicentre Interrupted Time-Series and Period-Comparative Analysis of 3954 Patients
Journal Description
Medicina
Medicina
is an international, peer-reviewed, open access journal covering all problems related to medicine, published monthly online. It is the official journal of the Lithuanian University of Health Sciences (LUHS). The Lithuanian Medical Association (LMA), Vilnius University, Rīga Stradiņš University, University of Latvia, and University of Tartu are affiliated with Medicina, serving as their official journal. Members of these organizations receive discounts on the article processing charges.
- Open Access— free for readers, with article processing charges (APC) paid by authors or their institutions.
- High Visibility: indexed within Scopus, SCIE (Web of Science), PubMed, MEDLINE, PMC, and other databases.
- Journal Rank: JCR - Q1 (Medicine, General and Internal) / CiteScore - Q1 (General Medicine)
- Rapid Publication: manuscripts are peer-reviewed and a first decision is provided to authors approximately 17.4 days after submission; acceptance to publication is undertaken in 2.8 days (median values for papers published in this journal in the first half of 2026).
- Recognition of Reviewers: Reviewers whose reports are timely and of high quality receive an APC discount voucher for a future publication in an MDPI journal. Become a reviewer.
Impact Factor:
2.9 (2025);
5-Year Impact Factor:
3.0 (2025)
Latest Articles
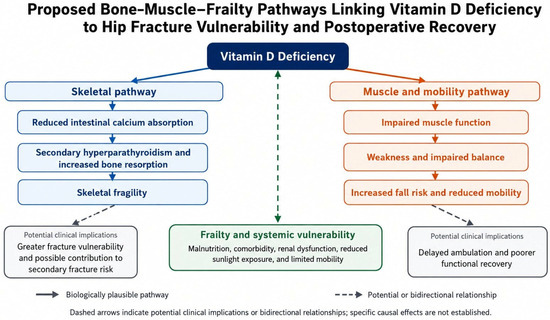
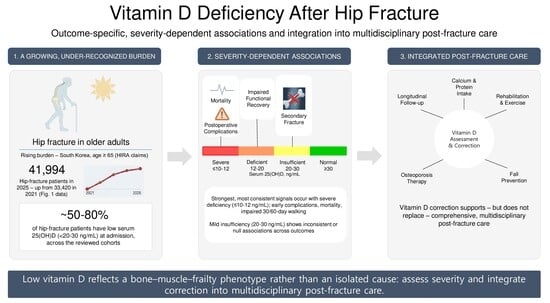
Vitamin D Deficiency in Hip Fracture Patients: Outcome-Specific Associations and Post-Fracture Management—A Narrative Review
Medicina 2026, 62(9), 1794; https://doi.org/10.3390/medicina62091794 (registering DOI) - 17 Sep 2026
Abstract
Background and Objectives: Vitamin D deficiency is common in older adults with hip fracture and has been associated with adverse postoperative outcomes. However, heterogeneity in deficiency thresholds, outcome definitions, and patient populations has complicated the interpretation and clinical application of existing evidence. This
[...] Read more.
Background and Objectives: Vitamin D deficiency is common in older adults with hip fracture and has been associated with adverse postoperative outcomes. However, heterogeneity in deficiency thresholds, outcome definitions, and patient populations has complicated the interpretation and clinical application of existing evidence. This narrative review aimed to summarize current evidence regarding perioperative vitamin D status, its associations with postoperative complications, mortality, functional recovery, and secondary fracture, and the role of vitamin D supplementation after hip fracture. Materials and Methods: Relevant studies were identified through PubMed searches and manual screening of reference lists. Cohort studies, randomized controlled trials, systematic reviews, meta-analyses, and clinical guidelines addressing vitamin D status, supplementation, hip fracture outcomes, fracture prevention, or postoperative recovery in older adults were narratively synthesized. Results: Low serum 25-hydroxyvitamin D was associated with selected early medical complications, mortality, impaired functional recovery, and secondary hip fracture, although these associations varied across outcomes. The strongest prognostic associations with mobility were observed in patients with severe deficiency (approximately ≤10–12 ng/mL), whereas mild insufficiency showed less consistent associations. Heterogeneity among studies reflected differences in deficiency thresholds, sampling timing, outcome definitions, follow-up duration, study populations, and adjustment for frailty and comorbidity. Vitamin D supplementation consistently increased serum 25-hydroxyvitamin D concentrations but did not consistently improve gait, postoperative complications, mortality, or recurrent fracture. Favorable outcomes reported with exercise- and nutrition-based multimodal interventions could not be attributed to vitamin D supplementation alone. Conclusions: Vitamin D deficiency should be interpreted within the broader context of frailty, nutritional status, muscle function, and skeletal health after hip fracture. Vitamin D assessment and correction should be integrated into comprehensive post-fracture care alongside osteoporosis treatment, adequate calcium and protein intake, rehabilitation, and fall prevention. However, clinical benefits of supplementation beyond correction of deficiency remain uncertain, and future studies should focus on patients with severe deficiency and clinically meaningful, patient-centered outcomes.
Full article
(This article belongs to the Special Issue Clinical Diagnosis and Treatment of Osteoporosis and Fractures)
►
Show Figures
Open AccessArticle
Patterns of Care in the Final Week of Life: A Comparative Analysis of Aggressive Treatment Versus Comfort-Centered Care Across Healthcare Settings
by
Camelia Ancuta, Nicoleta Mitrea, Mariana Sporis, Flavia Hurducas and Daniela Mosoiu
Medicina 2026, 62(9), 1793; https://doi.org/10.3390/medicina62091793 (registering DOI) - 17 Sep 2026
Abstract
Background and Objectives: End-of-life care in oncology demands a holistic, multidisciplinary framework that pivots clinical priorities from disease-directed therapies toward symptom optimization, comfort, and patient dignity. Within this context, the present study investigated care delivery patterns among advanced cancer patients during their
[...] Read more.
Background and Objectives: End-of-life care in oncology demands a holistic, multidisciplinary framework that pivots clinical priorities from disease-directed therapies toward symptom optimization, comfort, and patient dignity. Within this context, the present study investigated care delivery patterns among advanced cancer patients during their final week of life. Materials and Methods: A retrospective medical record review was conducted, comparing an oncology ward, an intensive care unit, an inpatient palliative unit, and a home-based palliative care setting. We analyzed aggressive interventions, end-of-life care pathways, symptom management, medication use and rationalization, and transitions between care settings. Results: Among the 306 patients studied, diagnostic testing and artificial hydration were universally administered in the oncology and intensive care unit (p < 0.001), where prescriptions focused primarily on pain management. Conversely, palliative care settings addressed a wider range of terminal symptoms. The rationalization of non-essential medications took place between 1.8 and 2.9 days before death, varying significantly across medication classes and clinical settings (p < 0.001). Additionally, intensive care unit admissions were more prevalent among patients with advanced cancer, while home-based patients underwent the greatest number of care transitions. Conclusions: These findings highlight substantial differences in care across settings, emphasizing the need for coordinated planning, continuity, and patient-centered approaches to ensure comfort and dignity in the final week of life.
Full article
(This article belongs to the Special Issue Cancer Care at the End of Life: Balancing Disease-Directed Treatment, Palliative Care, and Symptom-Oriented Approaches)
Open AccessArticle
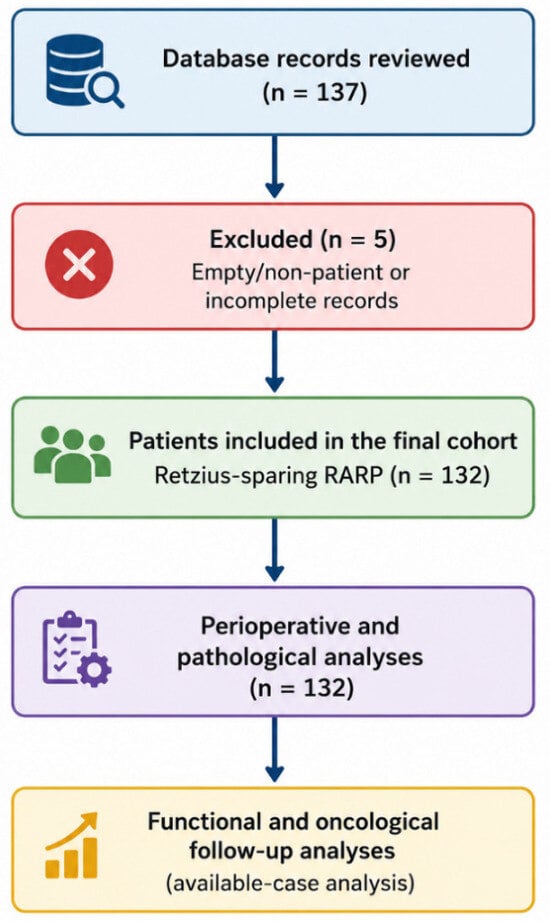
Retzius-Sparing Robot-Assisted Radical Prostatectomy: Analysis of Functional and Oncological Outcomes
by
Fırat Akdeniz, Sıtkı Ün, Uğur Boylu and Aylin Köseler
Medicina 2026, 62(9), 1792; https://doi.org/10.3390/medicina62091792 - 17 Sep 2026
Abstract
Background and Objectives: Retzius-sparing robot-assisted radical prostatectomy (RS-RARP) has emerged as an alternative surgical approach designed to preserve pelvic anatomical structures involved in urinary continence. This study aimed to evaluate the perioperative, pathological, functional, and early postoperative oncological findings of RS-RARP in
[...] Read more.
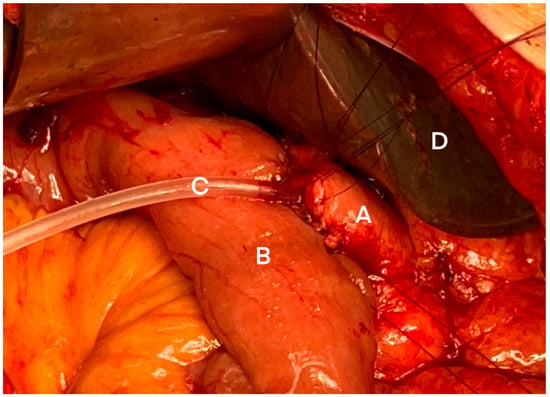
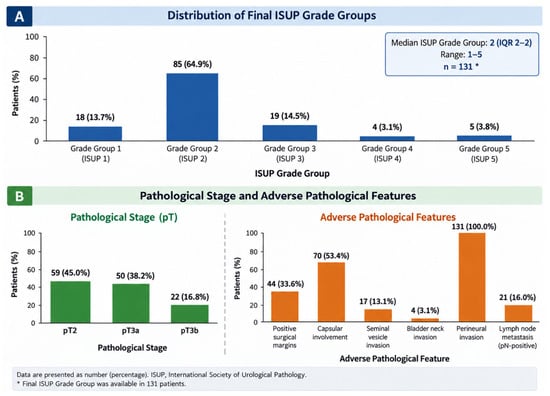
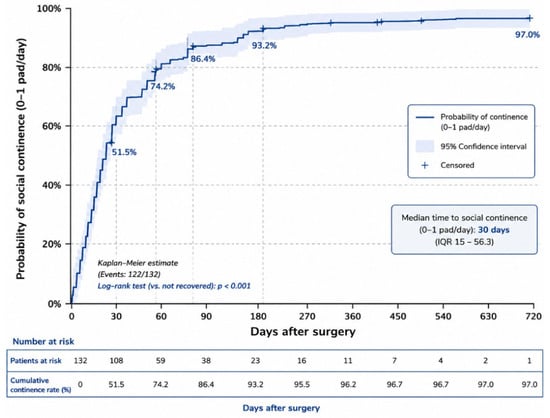
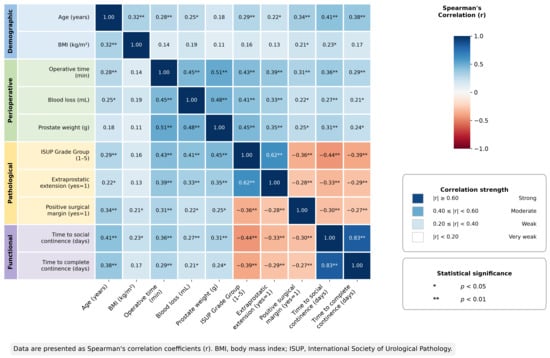
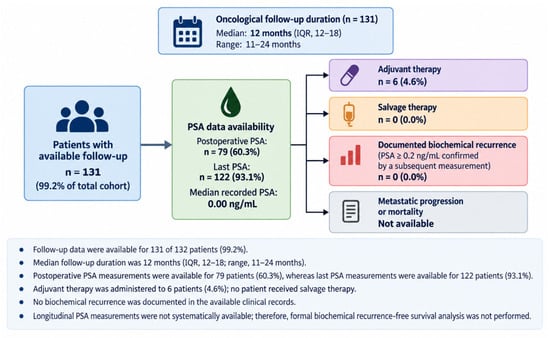
Background and Objectives: Retzius-sparing robot-assisted radical prostatectomy (RS-RARP) has emerged as an alternative surgical approach designed to preserve pelvic anatomical structures involved in urinary continence. This study aimed to evaluate the perioperative, pathological, functional, and early postoperative oncological findings of RS-RARP in patients with clinically localized prostate cancer. Materials and Methods: This retrospective single-cohort study included 132 consecutive patients who underwent RS-RARP at a single institution between January 2017 and February 2020. Demographic, perioperative, pathological, functional, and postoperative oncological data were retrospectively collected. The primary functional outcome was postoperative urinary continence recovery. Pathological outcomes included final ISUP Grade Group and positive surgical margin status, while postoperative prostate-specific antigen (PSA) measurements and treatment-related oncological follow-up data were evaluated where available. Results: The median operative time was 170 min (IQR, 160–200), and the median estimated blood loss was 100 mL (IQR, 70–150). Blood transfusion was required in one patient (0.8%), and no Clavien–Dindo grade ≥ III complications were observed. Final pathological examination demonstrated ISUP Grade Group 2 disease in 64.9% of patients, and the overall positive surgical margin rate was 33.6%. The median time to both social continence (0–1 pad/day) and complete continence (0 pad/day) was 30 days. Among 130 patients with available current pad-use data, 108 (83.1%) were completely pad-free, 13 (10.0%) required one safety pad per day, and 9 (6.9%) required two or more pads per day. The median oncological follow-up was 12 months. Follow-up data were available for 131 patients; postoperative PSA measurements were available for 79 patients and last PSA measurements for 122 patients. No salvage therapy or biochemical recurrence was documented in the available clinical records. However, incomplete longitudinal PSA data precluded reliable assessment of biochemical recurrence-free survival. Conclusions: In this retrospective single-cohort study, RS-RARP was associated with low perioperative morbidity, acceptable pathological outcomes, and favorable early urinary continence recovery. However, the absence of a conventional RARP comparator group, the relatively short follow-up period, and incomplete longitudinal PSA and recurrence-related data preclude conclusions regarding comparative effectiveness and long-term oncological efficacy. Prospective multicenter comparative studies with standardized functional assessment, systematic PSA monitoring, and longer oncological follow-up are warranted.
Full article
(This article belongs to the Special Issue Advances and Perspectives in Urologic Surgery)
►▼
Show Figures

Figure 1
Open AccessArticle
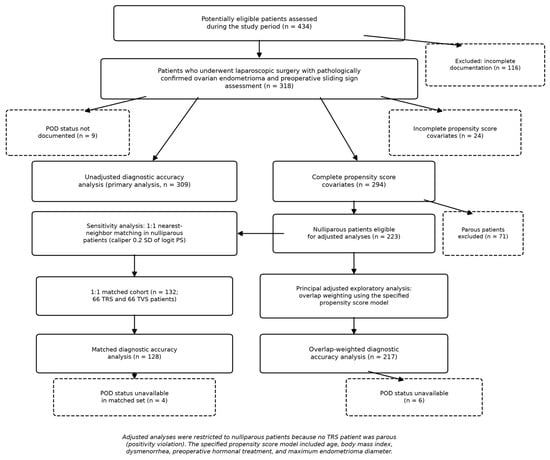
Ultrasound Sliding Sign Assessed by Transvaginal or Transrectal Route for Predicting Complete Pouch of Douglas Obliteration in Patients with Ovarian Endometriomas: An Exploratory Retrospective Study
by
Dong Liu, Huanli He, Yuebo Yang and Qingjian Ye
Medicina 2026, 62(9), 1791; https://doi.org/10.3390/medicina62091791 - 17 Sep 2026
Abstract
Background and Objective: The ultrasound sliding sign dynamically assesses pouch of Douglas (POD) obliteration in suspected endometriosis. Transvaginal (TVS) and transrectal (TRS) ultrasound are used in patients with and without a self-reported history of vaginal intercourse, respectively, and thus in clinically distinct
[...] Read more.
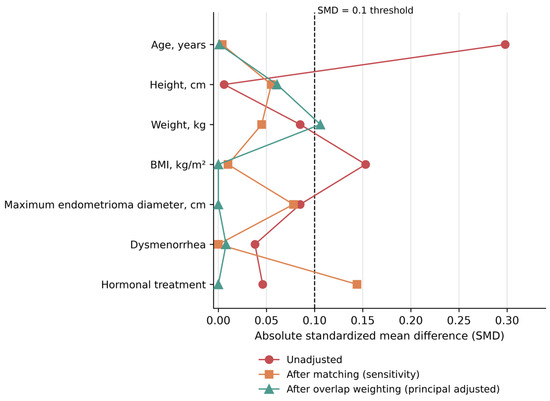
Background and Objective: The ultrasound sliding sign dynamically assesses pouch of Douglas (POD) obliteration in suspected endometriosis. Transvaginal (TVS) and transrectal (TRS) ultrasound are used in patients with and without a self-reported history of vaginal intercourse, respectively, and thus in clinically distinct populations. We evaluated sliding sign performance for predicting surgically confirmed complete POD obliteration in patients with ovarian endometriomas and described findings in route-defined TVS and TRS groups. Materials and Methods: This retrospective cohort study enrolled 318 patients with surgically and pathologically confirmed ovarian endometriomas; intraoperative POD status was evaluable in 309. Patients with and without a self-reported history of vaginal intercourse underwent TVS (n = 247) and TRS (n = 71), respectively. A negative sliding sign (absent movement between the uterus and rectum) was the positive index test result for complete POD obliteration. The unadjusted full-cohort diagnostic accuracy analysis was the primary analysis. Because no parous patient underwent TRS (a lack of overlap in examination-route assignment among parous patients), exploratory adjusted analyses were restricted to nulliparous patients, using overlap weighting (principal adjusted analysis) and 1:1 propensity score matching (sensitivity analysis). Results: In the primary unadjusted analysis of the full cohort (n = 309), the negative sliding sign showed limited to moderate discriminative ability (sensitivity 0.71, 95% CI 0.63–0.78; specificity 0.60, 95% CI 0.52–0.67; PLR 1.78, 95% CI 1.44–2.20; NLR 0.48, 95% CI 0.36–0.64) and was associated with complete POD obliteration (p < 0.001). The between-route sensitivity difference was inconclusive (0.19, 95% CI −0.01 to 0.38). In the exploratory overlap-weighted analysis of nulliparous patients (n = 217), the association remained significant (weighted OR = 2.80, 95% CI 1.17–6.69; p = 0.021), without significant sliding sign-by-route interaction (p = 0.302); findings were consistent in the matching sensitivity analysis (66 pairs). Conclusions: The sliding sign was associated with surgically confirmed complete POD obliteration in patients with ovarian endometriomas, but evidence that this association differed between route-defined groups was inconclusive. Route-specific findings are exploratory because the examination route was determined by sexual history rather than randomization. Whether TRS offers performance comparable to TVS remains undetermined, because the two techniques were not evaluated in the same population and TRS feasibility was not formally assessed.
Full article
(This article belongs to the Special Issue Advanced Ultrasound Technology and Its Application to Gynecologic Practice)
►▼
Show Figures

Figure 1
Open AccessReview
Augmented Reality, Mixed Reality, Computer Vision, and Three-Dimensional Modeling in Fertility-Preserving Minimally Invasive Gynecologic Surgery: A Scoping Review with Narrative Synthesis
by
Eleni Karatrasoglou, Alexandros Rodolakis, Themistoklis Grigoriadis and Athanasios Protopapas
Medicina 2026, 62(9), 1790; https://doi.org/10.3390/medicina62091790 - 17 Sep 2026
Abstract
Background and Objectives: Augmented reality (AR), mixed reality (MR), computer vision, artificial intelligence (AI), and three-dimensional (3D) modeling may be particularly relevant in fertility-preserving gynecologic surgery, where disease must be treated while uterine architecture, reproductive anatomy, and future fertility potential are preserved.
[...] Read more.
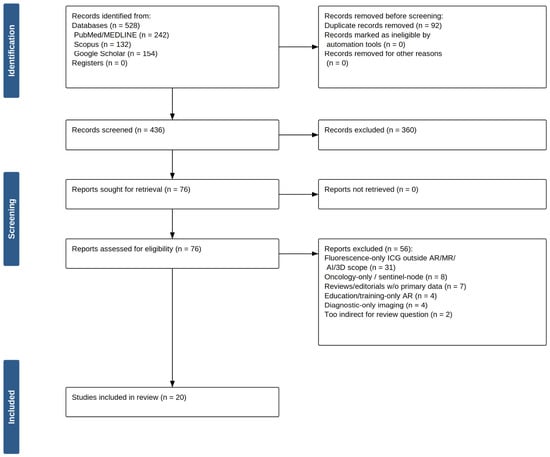
Background and Objectives: Augmented reality (AR), mixed reality (MR), computer vision, artificial intelligence (AI), and three-dimensional (3D) modeling may be particularly relevant in fertility-preserving gynecologic surgery, where disease must be treated while uterine architecture, reproductive anatomy, and future fertility potential are preserved. This scoping review mapped and appraised the current evidence, with emphasis on myomectomy, adenomyomectomy, and endometriosis surgery. Materials and Methods: A scoping review with narrative synthesis was conducted and reported according to the PRISMA Extension for Scoping Reviews (PRISMA-ScR). PubMed/MEDLINE, Scopus, and Google Scholar were searched from database inception to 16 May 2026. Records were appraised with design-appropriate instruments: Joanna Briggs Institute (JBI) principles, Risk Of Bias In Non-randomized Studies of Interventions (ROBINS-I), randomized-trial risk-of-bias domains, and structured feasibility criteria. Results: Of 528 records identified, 20 were included. Eleven involved application of the technology in the care of patients; of these, only two were comparative—one retrospective matched case–control study of AR-assisted myomectomy and adenomyomectomy, and one single-center randomized controlled trial of 3D-printed model-assisted myomectomy. The remaining nine were enabling technologies validated on image datasets, operative video, ex vivo models, or animal models. Only one study reported a reproductive outcome—pregnancy rates in a retrospective matched series of 34 patients, which did not differ between groups—and no study reported live birth, obstetric, or long-term reproductive-safety outcomes. Conclusions: Current evidence supports technical feasibility and preoperative planning value but does not demonstrate improvement in reproductive outcomes; here “fertility-preserving” denotes the clinical context of the surgery rather than a demonstrated reproductive benefit. Adequately powered controlled studies reporting fertility-relevant endpoints are required.
Full article
(This article belongs to the Special Issue Advances in Reproductive Surgeries)
►▼
Show Figures

Figure 1
Open AccessReview
Individualizing Perioperative Analgesia: Patient-Specific Determinants of Postoperative Pain and Opioid-Related Outcomes
by
Sarah Kazemeini, Ryan Shih, Sunny Zhang, Raphael Cohen, Nathaniel LaBarre, Moonis Ghani and George Tsao
Medicina 2026, 62(9), 1789; https://doi.org/10.3390/medicina62091789 - 17 Sep 2026
Abstract
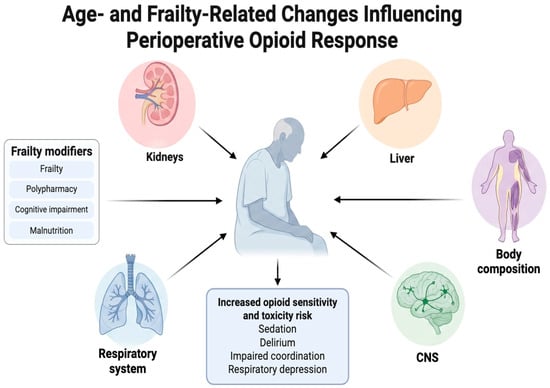
Background and Objectives: Postoperative pain and opioid requirements can vary widely, even among patients undergoing similar procedures. This narrative review examines how biological sex, age, frailty, chronic pain, preoperative opioid exposure, and psychological factors may affect postoperative pain, opioid response, and recovery.
[...] Read more.
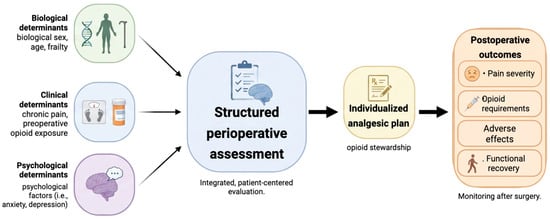
Background and Objectives: Postoperative pain and opioid requirements can vary widely, even among patients undergoing similar procedures. This narrative review examines how biological sex, age, frailty, chronic pain, preoperative opioid exposure, and psychological factors may affect postoperative pain, opioid response, and recovery. Materials and Methods: PubMed and Google Scholar were searched from database inception through 18 June 2026. Relevant systematic reviews, meta-analyses, clinical guidelines, randomized trials, and observational studies involving adult surgical patients were included, with a focus on postoperative pain, opioid use, adverse effects, persistent pain, and functional recovery. Human perioperative evidence was prioritized, while experimental and preclinical evidence was used selectively to explain relevant biological mechanisms. Results: The available evidence was heterogeneous across patient populations, surgical procedures, analgesic techniques, and outcome definitions. No single patient characteristic consistently predicts postoperative pain or opioid requirements. Female sex is associated with a greater risk of postoperative nausea and vomiting, but reported differences in pain and opioid efficacy are inconsistent. Older and frail patients may be more susceptible to sedation, respiratory depression, delirium, and other opioid-related adverse effects. Patients with chronic pain or prior opioid exposure often have more difficult postoperative pain control because of tolerance, dependence, or possible opioid-induced hyperalgesia. Anxiety, depression, and pain catastrophizing may also contribute to greater pain and poorer recovery, although their relationship with opioid consumption is less consistent. Conclusions: Perioperative analgesia should be based on the patient’s overall clinical picture rather than any single risk factor. The proposed framework is conceptual and has not been clinically validated. Considering these characteristics together may help clinicians select appropriate multimodal treatments, anticipate analgesic needs, monitor for adverse effects, and support recovery.
Full article
(This article belongs to the Special Issue Anesthesia and Analgesia in Surgery)
►▼
Show Figures

Figure 1
Open AccessArticle
Post-Pancreatectomy Acute Pancreatitis in Pancreatic Cancer: A Single-Center Experience
by
Ewa Grudzińska, Magdalena Gajda, Karolina Majewska, Wojciech Dubaj and Sławomir Mrowiec
Medicina 2026, 62(9), 1788; https://doi.org/10.3390/medicina62091788 - 16 Sep 2026
Abstract
Background and Objectives: In 2022, the International Study Group of Pancreatic Surgery (ISGPS) introduced a definition of postoperative acute pancreatitis (PPAP). This study aimed to assess the perioperative factors associated with clinically relevant PPAP (CR-PPAP) after pancreatoduodenectomy (PD) due to pancreatic ductal
[...] Read more.
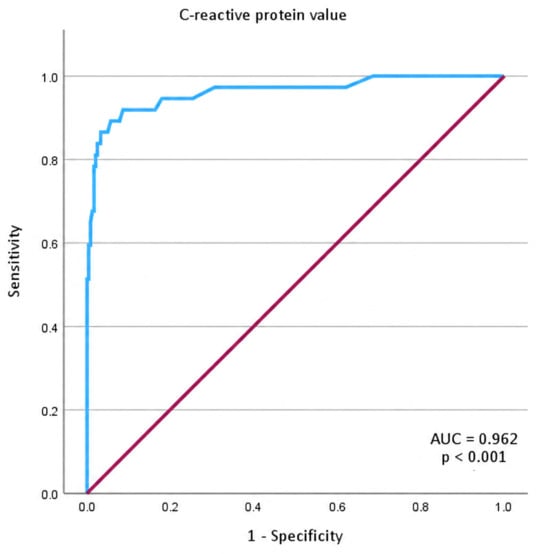
Background and Objectives: In 2022, the International Study Group of Pancreatic Surgery (ISGPS) introduced a definition of postoperative acute pancreatitis (PPAP). This study aimed to assess the perioperative factors associated with clinically relevant PPAP (CR-PPAP) after pancreatoduodenectomy (PD) due to pancreatic ductal adenocarcinoma (PDAC) and to present the real-world treatment strategies for this complication. Materials and Methods: We performed a retrospective single-center analysis of 282 patients who underwent pancreatoduodenectomy for PDAC between 2010 and 2023. Results: CR-PPAP was diagnosed in 13.1% of patients. This group had significantly higher CRP (219 vs. 42 mg/L) and more frequently elevated drain amylase activity (97.3% vs. 18%). CR-PPAP was associated with significantly higher rates of reoperation (37.8% vs. 3.3%), delayed gastric emptying (73% vs. 16.3%), hemorrhage (21.6% vs. 0.8%) and pancreatic fistula (97.3% vs. 0.8%), as well as longer hospitalization (15 vs. 13 days). Antibiotics were administered significantly more often in the CR-PPAP group (86.5% vs. 6.5%), while somatostatin was used in all CR-PPAP patients and octreotide in 62.2%. Thirty-day mortality did not differ significantly between groups. In multivariate analysis, a small main pancreatic duct was the only independent factor associated with CR-PPAP. Conclusions: PPAP, as defined by the ISGPS 2022 criteria, is a relatively common complication following PD for malignancy, with a small pancreatic duct being a major risk factor. PPAP is strongly associated with other major postoperative complications and prolonged hospitalization, but not with increased mortality. Despite the frequent use of antibiotics, octreotide, and somatostatin in clinical practice, evidence-based treatment recommendations for CR-PPAP remain lacking, highlighting the need for management guidelines.
Full article
(This article belongs to the Special Issue Acute Pancreatitis: From Pathogenesis to Treatment)
►▼
Show Figures

Figure 1
Open AccessArticle
Left Atrial Strain as an Integrative Marker of Diastolic Dysfunction and Atrial Fibrillation in Hypertrophic Cardiomyopathy: A Retrospective Cross-Sectional Study
by
Eglė Tamulėnaitė-Stuokė, Joana Ažukaitė, Marius Šukys and Eglė Ereminienė
Medicina 2026, 62(9), 1787; https://doi.org/10.3390/medicina62091787 - 16 Sep 2026
Abstract
Background and Objectives: Echocardiographic assessment of left ventricular diastolic dysfunction (LVDD) in hypertrophic cardiomyopathy (HCM) is challenging, as conventional parameters correlate poorly with left ventricular filling pressure. Emerging evidence suggests that left atrial (LA) strain is associated with atrial fibrillation (AF). This
[...] Read more.
Background and Objectives: Echocardiographic assessment of left ventricular diastolic dysfunction (LVDD) in hypertrophic cardiomyopathy (HCM) is challenging, as conventional parameters correlate poorly with left ventricular filling pressure. Emerging evidence suggests that left atrial (LA) strain is associated with atrial fibrillation (AF). This study aimed to compare LA reservoir strain (LASr)-based and conventional LVDD grading, evaluate associations between LA strain and clinical and echocardiographic parameters, and explore its relationship with AF. Materials and Methods: This retrospective cross-sectional single-center study included 109 adult HCM patients with comprehensive echocardiographic data. LVDD was graded using conventional echocardiographic parameters and LASr-based thresholds (≥35% (grade 0), ≥24% to <35% (grade 1), ≥19% to <24% (grade 2), and < 19% (grade 3)). Results: LASr-based grading revealed a significantly greater prevalence of advanced LVDD compared with conventional assessment (grade 3: 39% vs. 3%, p < 0.001), with poor intermethod agreement (κ = 0.07). Overall, approximately 45% of patients were reclassified into higher LVDD grades using LASr, particularly among nonobstructive HCM patients. Higher LASr-based LVDD grades were associated with worse conventional diastolic indices, reduced biventricular strain parameters, and higher natriuretic peptide levels. Reduced LA reservoir and conduit strain were independently associated with documented AF after adjustment for age, LA volume index, and left ventricular mass index. Conclusions: LASr provides additional information on diastolic dysfunction in HCM patients and is associated with documented AF. LASr-based grading assigned more patients to advanced LVDD grades than conventional assessment. The observed association with AF requires prospective validation before LA strain can be used for risk stratification.
Full article
(This article belongs to the Section Cardiology)
Open AccessArticle
Initial Experience with Standalone Thoracoscopic Left Atrial Appendage Occlusion Using AtriClip Pro2: A Single-Center Retrospective Cohort Study in Latvia
by
Diāna Kalniņa, Kaspars Kupics, Renāta Rimdjonoka, Inga Urtāne, Daniels Siļčonoks, Andrejs Ērglis and Pēteris Stradiņš
Medicina 2026, 62(9), 1786; https://doi.org/10.3390/medicina62091786 - 16 Sep 2026
Abstract
Background and Objectives: Left atrial appendage (LAA) closure is an established strategy for stroke prevention in selected patients with atrial fibrillation (AF), particularly when long-term oral anticoagulation (OAC) is contraindicated. Thoracoscopic epicardial LAA occlusion using the AtriClip Pro2 device provides a minimally invasive
[...] Read more.
Background and Objectives: Left atrial appendage (LAA) closure is an established strategy for stroke prevention in selected patients with atrial fibrillation (AF), particularly when long-term oral anticoagulation (OAC) is contraindicated. Thoracoscopic epicardial LAA occlusion using the AtriClip Pro2 device provides a minimally invasive surgical approach; however, evidence for standalone use remains limited. This study aimed to describe the initial feasibility and early clinical outcomes of standalone thoracoscopic LAA occlusion using AtriClip Pro2 in Latvia. Materials and Methods: We performed a single-center retrospective observational study including all consecutive patients who underwent standalone thoracoscopic LAA occlusion at the Department of Cardiac Surgery, Pauls Stradins Clinical University Hospital, between December 2024 and March 2026. Baseline characteristics, procedural outcomes, perioperative complications, rehospitalizations, and antithrombotic therapy status were assessed. LAA closure was assessed by transesophageal echocardiography (TEE). Results: Fourteen patients were included. Mean age was 63.6 ± 16.7 years (median 67.0; IQR 54.8–76.8), and 64.3% were female. Thoracoscopic completion was achieved in 13/14 patients (92.9%; 95% CI 68.5–98.7%); one patient (7.1%) required conversion to median sternotomy because of intraoperative bleeding. Complete LAA exclusion without residual flow or stump was documented in all 14 patients (100%; 95% CI 78.5–100%). No perioperative stroke or mortality occurred. At three months, follow-up data were available for all patients, and antithrombotic therapy had been discontinued in 12/14 patients (85.7%). Conclusions: This small, heterogeneous, single-center series supports the technical feasibility of standalone thoracoscopic AtriClip Pro2 implantation in selected patients. These encouraging early findings warrant further evaluation in larger cohorts with longer clinical follow-up and standardized postoperative imaging.
Full article
(This article belongs to the Special Issue Clinical Research in Minimally Invasive Cardiac Surgery)
Open AccessArticle
Perioperative Hydrogen Inhalation and Postoperative Pain After Endoscopic Discectomy: A Pilot Non-Randomized Clinical Study with Exploratory Murine Data
by
Chao-Hsien Sung, Wen-Chin Ko, Chia-Chi Kung and Chi-Feng Hung
Medicina 2026, 62(9), 1785; https://doi.org/10.3390/medicina62091785 - 16 Sep 2026
Abstract
Background/Objectives: Postoperative pain after endoscopic discectomy may reflect acute surgical nociception superimposed on pre-existing radicular symptoms. Molecular hydrogen (H2) has antioxidant and anti-inflammatory properties, but clinical evidence for perioperative analgesia is limited. We evaluated the association between perioperative H2
[...] Read more.
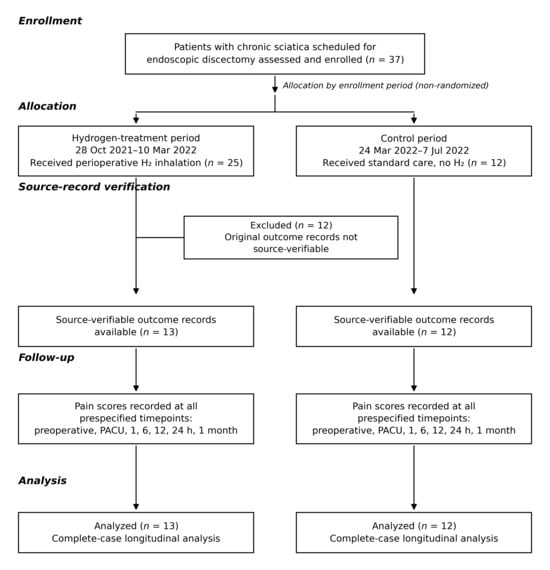
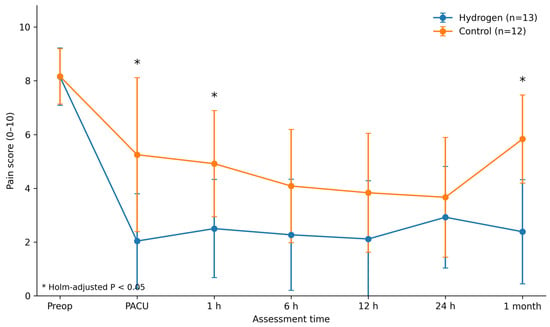
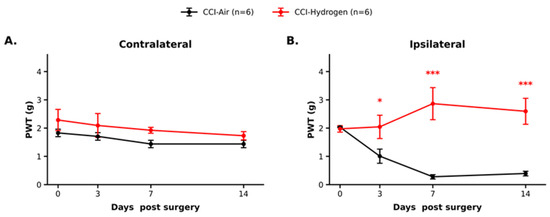
Background/Objectives: Postoperative pain after endoscopic discectomy may reflect acute surgical nociception superimposed on pre-existing radicular symptoms. Molecular hydrogen (H2) has antioxidant and anti-inflammatory properties, but clinical evidence for perioperative analgesia is limited. We evaluated the association between perioperative H2 inhalation and postoperative pain and analgesic requirements. Methods: This open-label, non-randomized pilot study enrolled 37 patients in two consecutive periods (H2, n = 25; control, n = 12). Because original outcome records for 12 H2-period participants could no longer be retrieved at the time of manuscript preparation, the complete-case clinical analysis included 25 source-verifiable participants (H2, n = 13; control, n = 12). H2 was delivered via nasal cannula as a 66.7% H2/33.3% O2 source gas at 2 L/min (estimated inspired H2 approximately 4%). Pain was evaluated with a numerical rating scale (NRS) preoperatively, at post-anesthesia care unit (PACU) arrival, at 1, 6, 12, and 24 h, and at 1 month. Longitudinal scores were analyzed using generalized estimating equations with Holm-adjusted comparisons. A parallel exploratory murine chronic constriction injury (CCI) experiment (n = 6/group) assessed mechanical allodynia over 14 days of daily H2 inhalation. Results: The group-by-time interaction was significant (Wald χ2(6) = 56.68, p < 0.001). After Holm adjustment, pain scores were lower with H2 at PACU arrival (difference, −3.21; adjusted p = 0.002), 1 h (−2.42; adjusted p = 0.004), and 1 month (−3.45; adjusted p < 0.001). Intraoperative fentanyl use and rescue analgesic use were also lower in the H2 group; no adverse events were documented in the analyzed cohort. In the murine CCI experiment, H2-treated mice showed higher ipsilateral paw withdrawal thresholds than air-exposed controls. Conclusions: Perioperative H2 inhalation was associated with lower pain scores at selected time points and reduced analgesic requirements. These preliminary findings require confirmation in randomized trials. Trial registration: ClinicalTrials.gov NCT05476575.
Full article
(This article belongs to the Section Intensive Care/ Anesthesiology)
►▼
Show Figures

Figure 1
Open AccessArticle
Clinical Outcomes of Ultrasound-Guided Stellate Ganglion Block in Highly Treatment-Resistant Chronic Migraine: A 6-Month Prospective Single-Group Interventional Study
by
Sukriye Dadali, Emel Basar, Ulku Sabuncu, Gulcin Babaoglu, Ali Costu and Erkan Yavuz Akcaboy
Medicina 2026, 62(9), 1784; https://doi.org/10.3390/medicina62091784 - 16 Sep 2026
Abstract
Background and Objectives: Chronic migraine (CM) remains a major cause of neurological disability, and a subset of patients remains highly treatment-resistant despite previous preventive and interventional treatments. Stellate ganglion block (SGB) has been proposed as a sympathetic neuromodulatory intervention, but evidence in
[...] Read more.
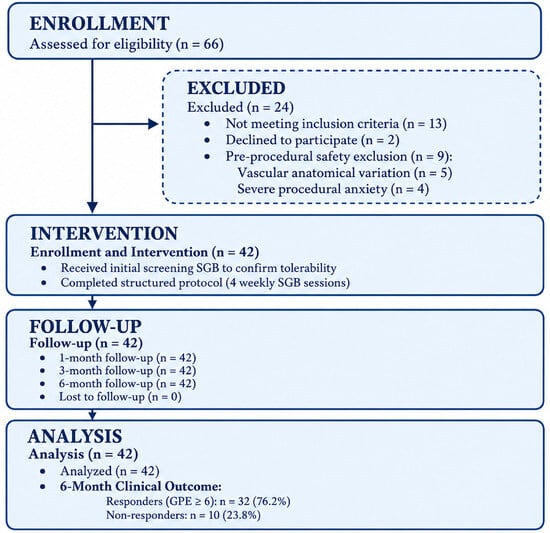
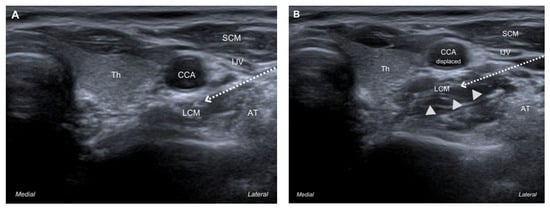
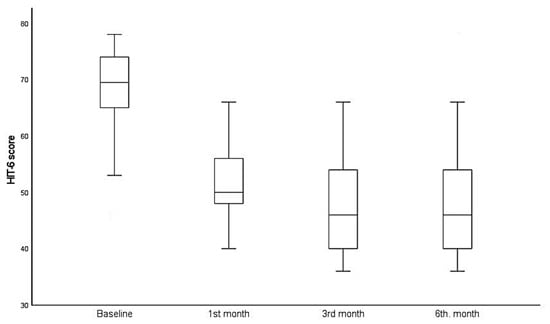
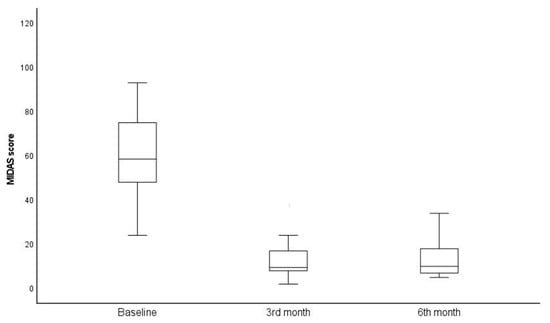
Background and Objectives: Chronic migraine (CM) remains a major cause of neurological disability, and a subset of patients remains highly treatment-resistant despite previous preventive and interventional treatments. Stellate ganglion block (SGB) has been proposed as a sympathetic neuromodulatory intervention, but evidence in this population remains limited. This study evaluated 6-month clinical outcomes and tolerability after a structured ultrasound-guided SGB protocol. Materials and Methods: This prospective, single-center, uncontrolled, single-group interventional study enrolled 42 adults with CM who had experienced insufficient benefit from prior preventive migraine treatment and previous interventional headache procedures. After an initial ultrasound-guided SGB to assess anatomical suitability and procedural tolerability, all participants proceeded to four additional weekly ultrasound-guided SGB sessions using 5 mL of 1% lidocaine, for five protocol-defined sessions in total. The primary outcome was the change in monthly headache days (MHD) from baseline to 6 months. Results: All 42 participants (mean age: 44.4 ± 7.4 years) completed the 6-month follow-up. Median MHD decreased from 29.0 days at baseline to 6.0 days at 6 months (Kendall’s W = 0.643, p < 0.001), corresponding to a median within-participant reduction of 17.0 days (BCa 95% CI: 13.0–19.0). A ≥50% reduction in MHD was achieved by 73.8% of participants (95% CI: 58.9–84.7) at 6 months, whereas 14.3% (95% CI: 6.7–27.8) achieved a ≥50% reduction in mean pain intensity. HIT-6 and MIDAS scores also improved significantly (p < 0.001). Six participants (14.3%) reported mild, self-limited adverse effects; no serious adverse events were documented. Conclusions: Ultrasound-guided SGB was associated with sustained reductions in headache frequency, analgesic use, and migraine-related disability over 6 months. Because this was an uncontrolled single-group study, the findings should be considered preliminary and hypothesis-generating. The frequency-dominant pattern of improvement and favorable tolerability support further controlled evaluation of SGB as a potential adjunctive neuromodulatory strategy in highly treatment-resistant CM.
Full article
(This article belongs to the Section Intensive Care/ Anesthesiology)
►▼
Show Figures

Figure 1
Open AccessReview
Artificial Intelligence for Precision Antiarrhythmic Drug Therapy in Atrial Fibrillation: From Recurrence Prediction to Comparative Treatment Selection
by
Alina Scridon, Vasile-Bogdan Halațiu and Dan-Alexandru Cozac
Medicina 2026, 62(9), 1783; https://doi.org/10.3390/medicina62091783 - 16 Sep 2026
Abstract
Rhythm control therapy has an important role in atrial fibrillation (AF) management, and antiarrhythmic drugs (AADs) remain essential for pharmacological cardioversion, maintenance of sinus rhythm, reduction in AF burden, and treatment before or after catheter ablation. However, their efficacy varies substantially among patients,
[...] Read more.
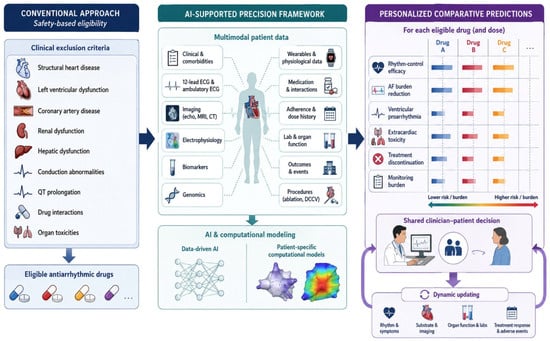
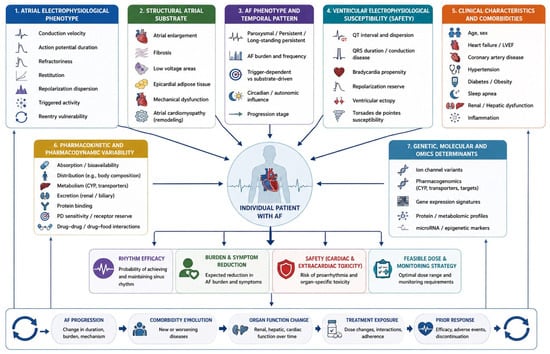
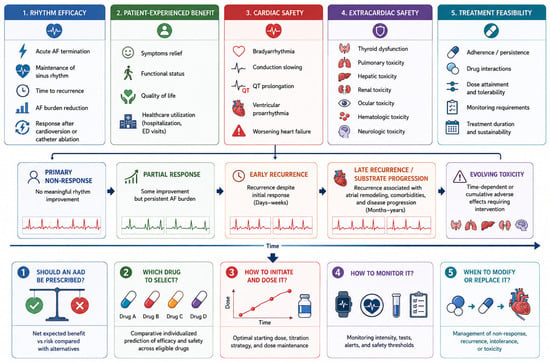
Rhythm control therapy has an important role in atrial fibrillation (AF) management, and antiarrhythmic drugs (AADs) remain essential for pharmacological cardioversion, maintenance of sinus rhythm, reduction in AF burden, and treatment before or after catheter ablation. However, their efficacy varies substantially among patients, while proarrhythmia, organ toxicity, drug interactions, and treatment discontinuation frequently limit their use. Current drug selection therefore relies mainly on safety-based exclusion based on structural heart disease, ventricular function, coronary disease, renal or hepatic function, and baseline conduction and repolarization characteristics, rather than on individualized prediction of comparative therapeutic benefit. This narrative review examines the potential role of artificial intelligence (AI), machine learning (ML), computational electrophysiology, and cardiac digital twins across the AAD treatment pathway. Particular attention is given to patient selection, comparative drug choice, prediction of cardioversion success and sinus-rhythm maintenance, dose optimization, proarrhythmia assessment, extracardiac toxicity, and longitudinal safety surveillance. AI can potentially integrate clinical, electrocardiographic (ECG), imaging, wearable, genomic, and pharmacological data to estimate patient-specific efficacy and toxicity. ML models have already demonstrated the feasibility of predicting drug-induced QT prolongation from electronic health records and detecting ECG signatures associated with drug-induced arrhythmic risk. Moreover, patient-specific AF digital twins have been used to simulate electrophysiological responses to amiodarone and identify patients with different subsequent rhythm outcomes. Nevertheless, most available applications remain retrospective, single-center, non-comparative, or proof-of-concept, and few directly support selection among alternative AADs. Most are prognostic, estimate outcomes under observed care, or predict drug-specific toxicity; models that estimate outcomes under alternative AADs remain the essential missing element. AI-supported antiarrhythmic therapy represents a promising transition from population-based prescribing toward individualized estimation of efficacy, toxicity, and monitoring requirements. Its clinical adoption will require multicenter external validation, causal treatment-effect modeling, prospective workflow evaluation, randomized impact trials, transparent uncertainty reporting, and continued clinician oversight.
Full article
(This article belongs to the Special Issue Atrial Fibrillation: Mechanisms and Management)
►▼
Show Figures

Figure 1
Open AccessArticle
Management and Clinical Outcomes of Liver Hemangiomas: A Retrospective Comparative Study of Transcatheter Arterial Embolization and Surgery
by
Sefa Ergün, Fadime Kutluk, Rauf Hamid, Yasemin Pekmezci, Seyfullah Halit Karagöz, Mehmet Velidedeoğlu, Server Sezgin Uludağ, Ahmet Baş, Fatih Gülşen and Salih Pekmezci
Medicina 2026, 62(9), 1782; https://doi.org/10.3390/medicina62091782 - 16 Sep 2026
Abstract
Background and Objectives: Hemangiomas are the most common benign tumors of the liver. Surgical options such as enucleation, segmentectomy, and hepatectomy are the primary treatment choices, though the morbidity and complication rates remain high. Transcatheter arterial embolization (TAE) has emerged as a
[...] Read more.
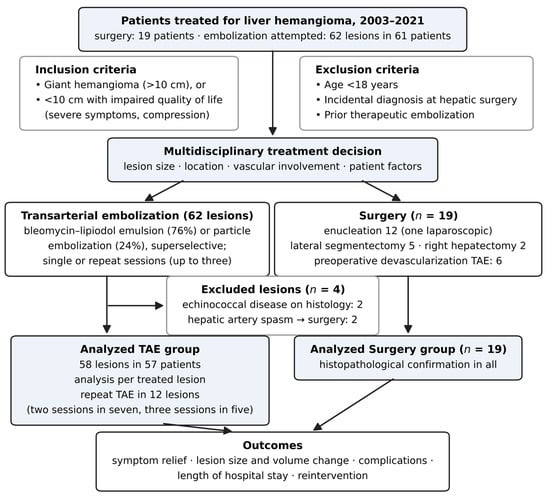
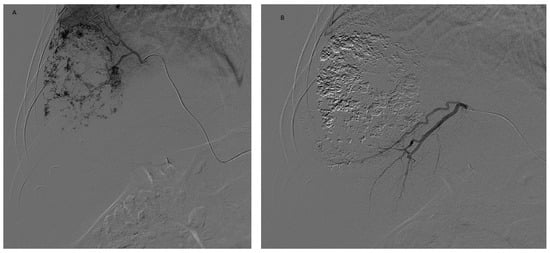
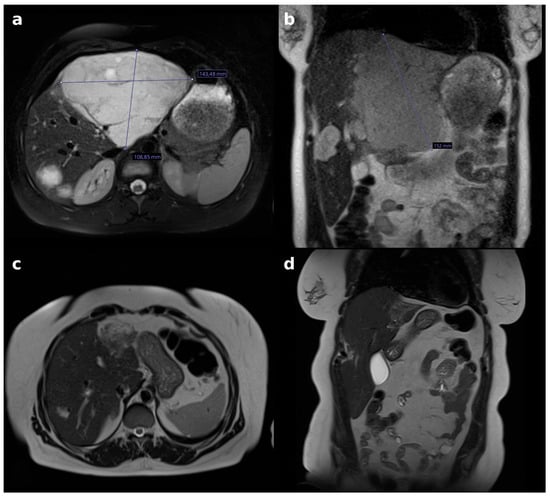
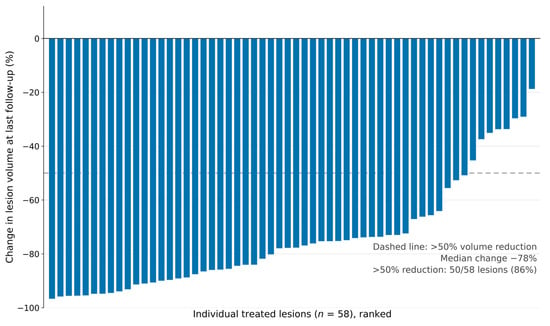
Background and Objectives: Hemangiomas are the most common benign tumors of the liver. Surgical options such as enucleation, segmentectomy, and hepatectomy are the primary treatment choices, though the morbidity and complication rates remain high. Transcatheter arterial embolization (TAE) has emerged as a safe and effective alternative treatment option that has gained popularity in recent years. Materials and Methods: We retrospectively evaluated data from patients who underwent either surgical intervention (n = 19) or transarterial embolization (62 lesions in 61 patients; analyses performed per treated lesion) for liver hemangioma between 2003 and 2021. Outcomes were assessed separately for each modality without a composite efficacy endpoint: clinical success (relief of the presenting symptoms, assessed in patients symptomatic at baseline), technical success and radiological response for embolization, treatment-related complications, length of hospital stay, and the need for reintervention. Results: There was no significant difference in the pretreatment size of the lesions between the TAE and surgery groups (median of 10.0 [IQR 7.8–13.9] versus 10.0 [IQR 9.0–17.0] cm; p = 0.100). The length of hospital stay was shorter in the TAE group (median of 1 versus 6 days; p < 0.001), although era-related differences in perioperative care may contribute to this difference, and follow-up was longer in surgically treated patients, reflecting the later adoption of embolization at our institution. Postoperative mortality did not occur in either group. In the embolization group, there were significant reductions in lesion size and volume and the complication rate was low, with no serious complications, supporting the safety profile of TAE. Conclusions: In this retrospective, non-randomized, single-center series, transarterial embolization was found to be a safe and effective minimally invasive treatment for liver hemangiomas and was associated with a shorter hospital stay. Because treatment allocation was not randomized, we cannot establish therapeutic equivalence between the two modalities, and the comparison should be regarded as descriptive; TAE represents an effective minimally invasive treatment option in appropriately selected patients and may be considered within a multidisciplinary treatment strategy, while surgery remains necessary in selected cases such as embolization failure, complicated lesion vascularization, or localization.
Full article
(This article belongs to the Special Issue Abdominal Surgery: Clinical Updates and Future Perspectives)
►▼
Show Figures

Figure 1
Open AccessArticle
Improvements in Gait Function Following Integrative Korean–Western Medicine Treatment in Older Adults with Chronic Stroke: A Retrospective Exploratory Study
by
Hyangyu Park, Yeonghun Wi and Cheol-Hyun Kim
Medicina 2026, 62(9), 1781; https://doi.org/10.3390/medicina62091781 - 16 Sep 2026
Abstract
Background and Objectives: Patients with chronic stroke aged 65 years or older and who are more than 6 months post-onset are generally considered to have reached a rehabilitation plateau, beyond which further functional improvement is difficult to achieve. This study aimed to evaluate
[...] Read more.
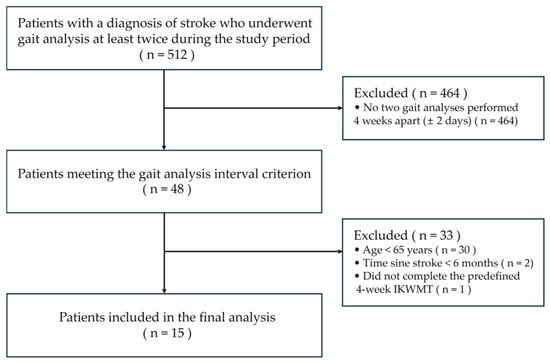
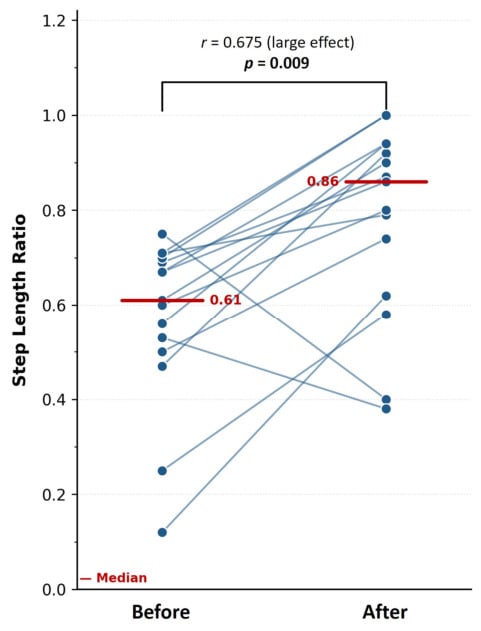
Background and Objectives: Patients with chronic stroke aged 65 years or older and who are more than 6 months post-onset are generally considered to have reached a rehabilitation plateau, beyond which further functional improvement is difficult to achieve. This study aimed to evaluate changes in gait function before and after integrative Korean–Western medicine treatment in older adults with chronic stroke. Materials and Methods: In this single-center, retrospective, single-group pre–post observational study, we analyzed the medical records of 15 patients with chronic stroke aged ≥65 years who received integrative Korean–Western medicine treatment five times per week for 4 weeks. The primary outcome was the step length ratio, reflecting gait symmetry. Secondary outcomes included walking velocity, lateral symmetry, center of pressure (COP)-related parameters, manual muscle test (MMT) scores, and Fugl-Meyer Assessment (FMA) scores. Results: The step length ratio increased significantly from 0.61 [0.50–0.70] before treatment to 0.86 [0.62–0.94] after treatment (p = 0.009, r = 0.675). Walking velocity (p = 0.006, r = 0.715) and mean COP velocity (p = 0.007, d = −0.822) also improved significantly. In contrast, no significant changes were observed in MMT or FMA scores, and no treatment-related adverse events were recorded. Conclusions: In this retrospective, uncontrolled, single-group study, significant improvements in gait symmetry, walking velocity, and postural control were observed following integrative Korean–Western medicine treatment in older adults with chronic stroke. The improvement in gait function without a corresponding change in FMA-based motor function—although both MMT and FMA scores were relatively high at baseline, potentially limiting sensitivity to detect further motor improvement—raises the hypothesis that other mechanisms, potentially including enhanced sensorimotor integration, may have contributed to these changes; however, this mechanistic interpretation remains speculative and was not directly tested. Randomized controlled trials with appropriate control groups are warranted to further verify these findings.
Full article
(This article belongs to the Special Issue Recent Advances in Neurorehabilitation: From Brain Injury to Autonomic and Pelvic Dysfunction)
►▼
Show Figures

Figure 1
Open AccessArticle
Beyond Pain Intensity: Central Sensitization and Psychosocial Symptom Burden in Women with Rheumatoid Arthritis
by
Maja Vučković, Dragana Kožul, Tamara Popović, Ivan Soldatović, Sandra Trivunović, Tatjana Nožica Radulović, Daria Ćupurdija and Snežana Tomašević Todorović
Medicina 2026, 62(9), 1780; https://doi.org/10.3390/medicina62091780 - 16 Sep 2026
Abstract
Background and Objectives: Persistent pain in rheumatoid arthritis (RA) may reflect mechanisms not fully captured by systemic inflammatory markers. This study estimated the frequency of elevated Central Sensitization Inventory (CSI) scores in women with RA and examined associations with pain, fatigue, depressive
[...] Read more.
Background and Objectives: Persistent pain in rheumatoid arthritis (RA) may reflect mechanisms not fully captured by systemic inflammatory markers. This study estimated the frequency of elevated Central Sensitization Inventory (CSI) scores in women with RA and examined associations with pain, fatigue, depressive symptoms, function, inflammatory markers, and disease activity. Materials and Methods: This prospective single-center observational cohort included 97 female inpatients who completed a standardized three-week rehabilitation program. The CSI was used as a symptom-based screening instrument. Pain, function, fatigue, and depressive symptoms were assessed with the Visual Analog Scale (VAS), Health Assessment Questionnaire (HAQ), FACIT-Fatigue scale, and Beck Depression Inventory-II (BDI-II), respectively. Results: Fifty-seven participants (58.8%) had CSI scores ≥ 40. Higher CSI scores were associated with greater pain, more depressive symptoms, more fatigue, and higher DAS28-CRP scores, but not with ESR, CRP, IL-6, or disease duration. In adjusted baseline models, the association with VAS pain was statistically significant but modest (unstandardized beta = 0.024 per CSI point; standardized beta = 0.273). Across the three-week follow-up, VAS pain decreased by 2.53 points; mean FACIT-Fatigue and HAQ changes were smaller than commonly cited clinically important thresholds, and CSI changed only modestly. In adjusted multivariable models, higher CSI scores remained independently associated with VAS pain, FACIT-Fatigue, and BDI-II scores, whereas no significant association was found with HAQ. CSI was not associated with CRP, IL-6, or disease duration. Conclusions: In this cohort of women with RA, elevated CSI scores identified a greater self-reported symptom burden and were independently associated with pain, fatigue, and depressive symptoms after adjustment, though the pain association remained modest in magnitude. No meaningful association was found with functional disability. The uncontrolled, single-arm design and restricted inflammatory-marker range preclude causal conclusions or proof that symptoms were independent of inflammation.
Full article
(This article belongs to the Section Neurology)
Open AccessArticle
Recurrence of Benign Vocal Fold Lesions: Risk Factors and an Exploratory Comparison of Cold-Instrument and CO2 Laser Surgery in a Retrospective Cohort
by
Alexandru Vlase, Octavian Dragos Palade, Dragoș Munteanu, Ionut Andrei Roman, Stefan Moscalu, Ana Doina Roxana, Andreea Rusescu, Ruxandra Oana Aliuș and Catalina Voiosu
Medicina 2026, 62(9), 1779; https://doi.org/10.3390/medicina62091779 - 16 Sep 2026
Abstract
Background and Objectives: Benign vocal fold lesions (BVFLs) are common causes of persistent dysphonia, but recurrence estimates are influenced by lesion type, outcome definition, and follow-up. We evaluated recurrence after documented lesion resolution and explored clinical factors and surgical technique. Materials and Methods:
[...] Read more.
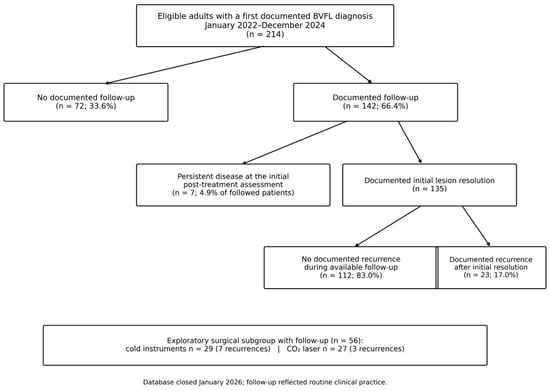
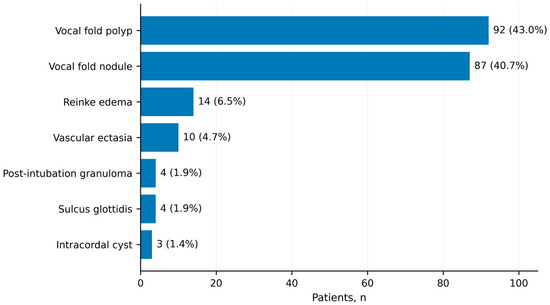
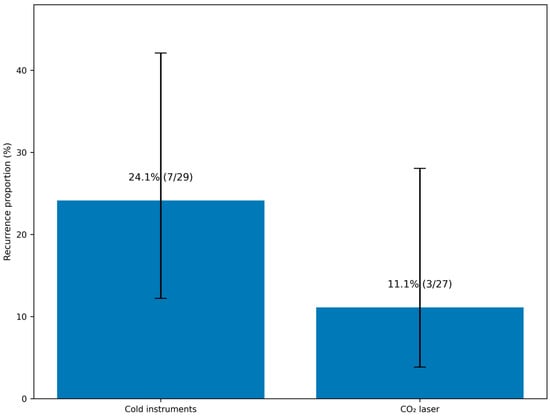
Background and Objectives: Benign vocal fold lesions (BVFLs) are common causes of persistent dysphonia, but recurrence estimates are influenced by lesion type, outcome definition, and follow-up. We evaluated recurrence after documented lesion resolution and explored clinical factors and surgical technique. Materials and Methods: We performed a single-center retrospective cohort study of 214 adults with a first documented BVFL diagnosis between January 2022 and December 2024. Clinical records were reviewed through January 2026. Recurrence was defined as lesion reappearance after documented resolution at the initial post-treatment laryngeal assessment; persistent lesions were classified separately. Results: Follow-up was documented in 142 patients (66.4%). Initial lesion resolution was documented in 135 patients, of whom 23 developed recurrence (17.0%); 7 patients had persistent disease at the initial post-treatment assessment. No evaluated demographic or clinical factor was significantly associated with recurrence in univariate analyses. In the secondary exploratory surgical analysis, recurrence occurred in 7/29 patients treated with cold instruments (24.1%) and 3/27 treated with CO2 laser (11.1%; OR 2.55, 95% CI 0.58–11.08; Fisher exact p = 0.299). Conclusions: Documented recurrence after initial lesion resolution occurred in 17.0% of patients. The surgical technique comparison was underpowered and unadjusted and does not establish superiority of either technique. Variable follow-up and differential attrition should be considered when interpreting the recurrence proportion.
Full article
(This article belongs to the Section Surgery)
►▼
Show Figures

Figure 1
Open AccessArticle
Treatment Gaps in Women Aged 65 Years and Older with Stress or Stress-Predominant Mixed Urinary Incontinence: Age-Stratified Patterns of Active Therapy, Containment Use, Frailty, and Anxiety
by
Doğucan Nuri Uğur and Kadir Böcü
Medicina 2026, 62(9), 1778; https://doi.org/10.3390/medicina62091778 - 16 Sep 2026
Abstract
Background and Objectives: Older women with stress or stress-predominant mixed urinary incontinence may rely on pads or diapers despite bothersome symptoms. We examined age-stratified treatment patterns and whether age remained associated with a treatment gap after accounting for frailty and symptom burden. Materials
[...] Read more.
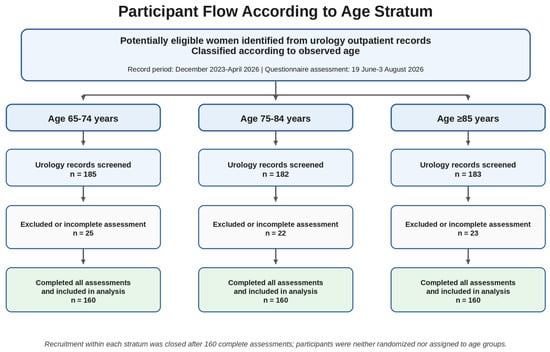
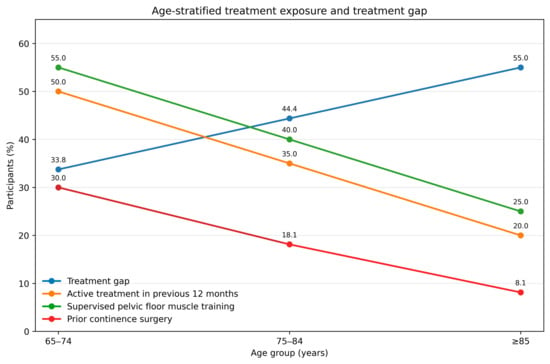
Background and Objectives: Older women with stress or stress-predominant mixed urinary incontinence may rely on pads or diapers despite bothersome symptoms. We examined age-stratified treatment patterns and whether age remained associated with a treatment gap after accounting for frailty and symptom burden. Materials and Methods: This single-center observational study combined record review (December 2023–April 2026) with a questionnaire assessment (19 June–3 August 2026). Within the 65–74, 75–84, and ≥85-year strata, 185, 182, and 183 women were screened; after 25, 22, and 23 exclusions or incomplete assessments, respectively, 160 evaluable women remained in each stratum. The treatment gap required International Consultation on Incontinence Questionnaire-Urinary Incontinence Short Form (ICIQ-UI SF) score ≥ 8, daily pad/diaper use, pad/diaper-only management, and no active treatment in the previous 12 months. Frailty and anxiety were assessed with the fatigue, resistance, ambulation, illnesses, and loss of weight (FRAIL) scale and Geriatric Anxiety Inventory. Results: Treatment-gap prevalence was 33.8%, 44.4%, and 55.0%. Supervised pelvic floor muscle training declined from 55.0% to 40.0% and 25.0%; recent active treatment from 50.0% to 35.0% and 20.0%; and previous continence surgery from 30.0% to 18.1% and 8.1%. After adjustment, age was not independently associated. Higher ICIQ-UI SF scores [adjusted odds ratio (aOR) 1.10 per point, 95% confidence interval (CI) 1.02–1.19] and stress-predominant mixed incontinence (aOR 1.53, 95% CI 1.03–2.25) remained associated. Conclusions: Containment dependence increased and active-treatment exposure decreased with age, but symptom burden and phenotype explained more adjusted risk than age. Regular reassessment may distinguish appropriate containment from remediable under-treatment.
Full article
(This article belongs to the Section Urology & Nephrology)
►▼
Show Figures

Figure 1
Open AccessArticle
Current Diabetes Self-Management and the Number of Documented Complications in Adults with Type 2 Diabetes: A Cross-Sectional Study
by
Paula-Alexandra Popovici, Andreea Diana Igna, Bianca-Lăcrimioara Petca, Timea Claudia Ghitea and Mihaela Simona Popoviciu
Medicina 2026, 62(9), 1777; https://doi.org/10.3390/medicina62091777 - 16 Sep 2026
Abstract
Background and Objectives: Current self-management behavior may not reflect the long-term exposures that led to established complications in people with type 2 diabetes (T2D). To assess whether Diabetes Self-Management Questionnaire (DSMQ) scores were associated with the number of documented diabetes-related and cardiovascular
[...] Read more.
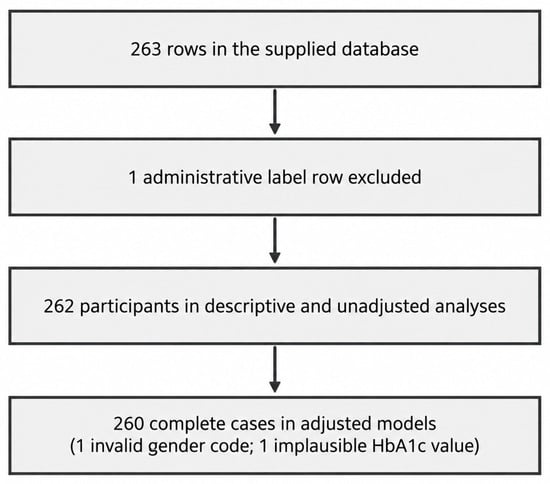
Background and Objectives: Current self-management behavior may not reflect the long-term exposures that led to established complications in people with type 2 diabetes (T2D). To assess whether Diabetes Self-Management Questionnaire (DSMQ) scores were associated with the number of documented diabetes-related and cardiovascular conditions and whether the finding was robust to alternative outcome constructions. Materials and Methods: This single-center cross-sectional reanalysis included 262 adults with T2D. The DSMQ was re-calculated from item-level responses. The primary outcome was an unweighted count of seven database-recorded conditions. Spearman correlation and multivariable Poisson regression with HC3 robust standard errors were used. Sensitivity analyses excluded heart failure, separated microvascular and cardiovascular counts, and substituted estimated glomerular filtration rate <60 mL/min/1.73 m2 for the recorded chronic kidney disease field. Results: Median DSMQ Sum Scale was 5.10 (IQR 3.13–7.08), and median condition count was 3 (IQR 2–3). No evidence of an unadjusted association was identified (ρ = −0.056; p = 0.368). In the adjusted model (n = 260), the DSMQ estimate was IRR 0.988 per point (95% CI 0.962–1.014; p = 0.355). The result remained nonsignificant after excluding heart failure (IRR 0.993; 95% CI 0.960–1.027), for the microvascular count (IRR 0.993; 95% CI 0.964–1.024), and for the cardiovascular count including heart failure (IRR 0.980; 95% CI 0.945–1.015). Pearson dispersion was 0.587, providing no evidence of overdispersion. Conclusions: No evidence of an association between current DSMQ-measured self-management and the number of recorded conditions was identified in this cohort. The result does not demonstrate equivalence and does not imply that sustained self-management is unrelated to long-term complication risk. In practice, contemporary DSMQ scores should guide cur-rent education and support needs, not be used as a proxy for historical com-plication exposure.
Full article
(This article belongs to the Section Endocrinology)
►▼
Show Figures

Figure 1
Open AccessArticle
Sex-Related Differences in Clinical Characteristics and Outcomes Among Patients Clinically Managed for Suspected Bacterial Infection in the Emergency Department
by
Daian-Ionel Popa, Larysa Alexandra Bălulescu, Ovidiu Alexandru Mederle, Codrina Mihaela Levai, Tiberiu Buleu, Anca Tudor, Ion Petre, Raluca Ibănescu, Carmen Gabriela Williams, Dumitru Sutoi, Dragos Fortofoiu, Cătălina Băzăvan, Adelin Ciudoiu, Răzvan Roșca and Florina Buleu
Medicina 2026, 62(9), 1776; https://doi.org/10.3390/medicina62091776 - 16 Sep 2026
Abstract
►▼
Show Figures
Background and Objectives: Suspected bacterial infection is one of the leading presentations to the Emergency Department (ED) and is still associated with considerable morbidity and mortality. There is increasing evidence that biological sex may influence host immune responses, disease manifestations, therapeutic requirements,
[...] Read more.
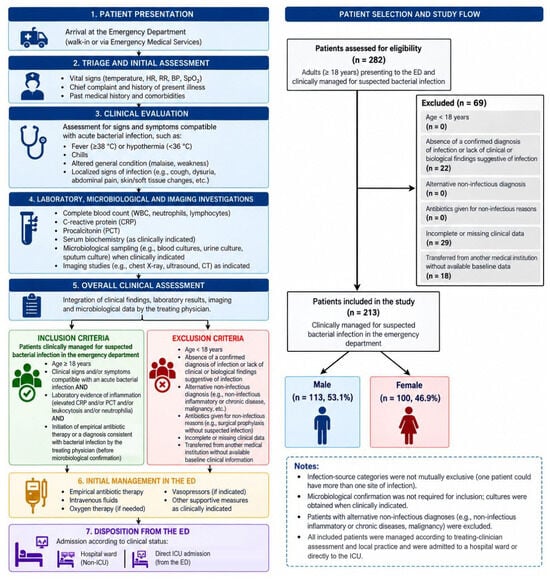
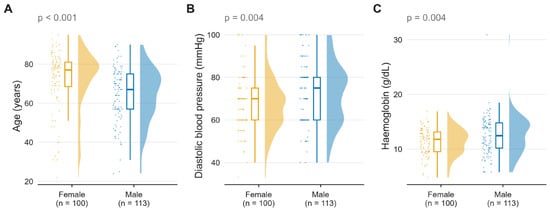
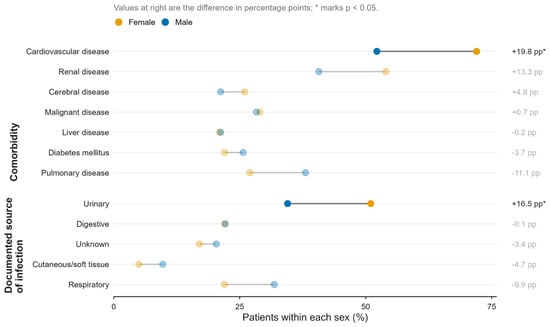
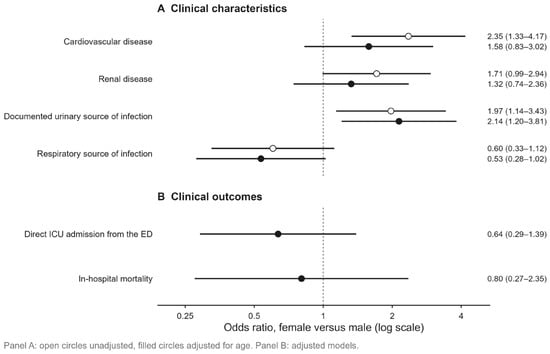
Background and Objectives: Suspected bacterial infection is one of the leading presentations to the Emergency Department (ED) and is still associated with considerable morbidity and mortality. There is increasing evidence that biological sex may influence host immune responses, disease manifestations, therapeutic requirements, and clinical outcomes in infectious diseases. However, sex-specific differences among patients clinically managed for suspected bacterial infection in ED remain incompletely defined. This study, therefore, aimed to assess demographic characteristics, clinical presentation, and clinical management as well as short-term outcomes related to sex among these patients. Materials and Methods: This retrospective single-center observational study included consecutive adults presenting with suspected bacterial infection to the ED between 1 June and 31 August 2025. Demographic, clinical, laboratory, treatment, infection-source, and outcome data were extracted from medical records. Between-group comparisons were followed by planned age-adjusted analyses and multivariable logistic regression. Results: A total of 213 patients were included, comprising 100 women (46.9%) and 113 men (53.1%). Women were older than men (median 77.0 vs. 67.0 years, p < 0.001), had lower diastolic blood pressure (70 vs. 75 mmHg, p = 0.004), and lower hemoglobin concentrations (11.79 vs. 12.45 g/dL, p = 0.004). Cardiovascular disease was more frequent among women than men (72.0% vs. 52.2%, p = 0.003), although this difference was attenuated and no longer significant after adjustment for age. A documented urinary source of infection was more frequent among women (51.0% vs. 34.5%, p = 0.015) and remained significantly associated with female sex after age adjustment (OR 2.14, 95% CI 1.20–3.81, p = 0.010; Benjamini–Hochberg-adjusted p = 0.039). No significant difference was detected in Emergency Department treatment: supplemental oxygen, vasopressors and broad-spectrum antibiotics were given with similar frequency to women and men (all p ≥ 0.139). Direct intensive care unit (ICU) admission from the ED occurred in 14 of 100 women (14.0%) and 21 of 113 men (18.6%; OR 0.71, 95% CI 0.34–1.49), and in-hospital mortality in 7 women (7.0%) and 9 men (8.0%; OR 0.87, 95% CI 0.31–2.43). After adjustment, female sex was not independently associated with direct ICU admission (OR 0.64, 95% CI 0.29–1.39; p = 0.257) or in-hospital mortality (OR 0.80, 95% CI 0.27–2.35; p = 0.690). Conclusions: In this single-center retrospective cohort of adults clinically managed for suspected bacterial infection in the emergency department, women were older and more frequently had a documented urinary source of infection. After adjustment for age, female sex remained associated with a documented urinary source of infection. The study did not provide precise evidence that sex was independently associated with direct ICU admission or in-hospital mortality; however, the confidence intervals were wide and clinically relevant differences cannot be excluded. Larger prospective multicenter studies with standardized diagnostic criteria, microbiological confirmation, and adequate outcome-event numbers are needed.
Full article

Figure 1
Open AccessArticle
Myocardial Injury and Predictors of In-Hospital Mortality in Severe or Critical COVID-19: A Single-Center Observational Cohort Study
by
Valentina Negrea, Septimiu Toader Voidazan, Adina Huțanu, Vlad Adrian Pop and Anca Meda Văsieșiu
Medicina 2026, 62(9), 1775; https://doi.org/10.3390/medicina62091775 - 16 Sep 2026
Abstract
►▼
Show Figures
Background and Objectives: In-hospital mortality remains high among patients with severe or critical COVID-19. This study aimed to identify independent predictors of in-hospital mortality and assess the prognostic value of myocardial injury in this high-risk population. Materials and Methods: This single-center
[...] Read more.
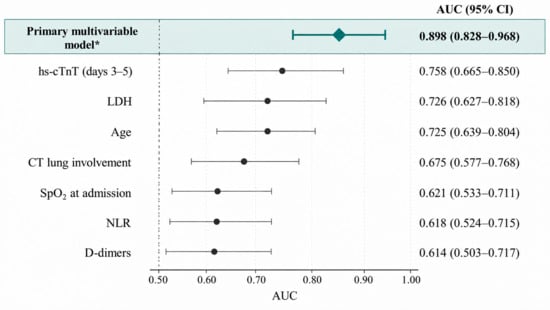
Background and Objectives: In-hospital mortality remains high among patients with severe or critical COVID-19. This study aimed to identify independent predictors of in-hospital mortality and assess the prognostic value of myocardial injury in this high-risk population. Materials and Methods: This single-center observational cohort study included 172 adults hospitalized with severe or critical COVID-19 across multiple pandemic waves. Mortality-associated factors were assessed using logistic regression and receiver operating characteristic curve analysis. Myocardial injury was defined as hs-cTnT > 14 ng/L, measured on days 3–5 after admission. Results: Of 172 patients, 60 died during hospitalization (34.9%). In the primary multivariable model, based on 126 complete cases and 37 deaths, age (aOR = 2.55 per 10-year increase; 95% CI, 1.55–4.22), pre-existing cardiovascular disease (aOR = 3.06; 95% CI, 1.03–9.07), LDH (aOR = 6.31 per doubling; 95% CI, 2.70–14.78), and CT pulmonary involvement (aOR = 1.34 per 10% increase; 95% CI, 1.01–1.80), were independently associated with in-hospital mortality. In a separate analysis of 121 patients with 35 deaths, myocardial injury remained independently associated with mortality after adjustment for age, cardiovascular disease, and pulmonary involvement (aOR = 5.19; 95% CI, 1.82–14.77). Among 131 patients with complete phenotype data, mortality was 6.7% (2/30) in patients with neither component, 19.6% (11/56) with isolated respiratory involvement, 50.0% (3/6) with isolated myocardial injury, and 56.4% (22/39) with both components. The primary multivariable model had an apparent AUC of 0.898 (95% CI, 0.828–0.968). Conclusions: Age, LDH, and myocardial injury were independently associated with in-hospital mortality, while the associations of cardiovascular disease and CT involvement were attenuated in the multiple-imputation sensitivity analysis. Combined assessment of clinical, pulmonary, and cardiac factors may improve risk stratification, but these findings require validation in independent cohorts.
Full article

Figure 1
Journal Menu
► ▼ Journal Menu-
- Medicina Home
- Aims & Scope
- Editorial Board
- Reviewer Board
- Topical Advisory Panel
- Early Career Editorial Board
- Instructions for Authors
- Special Issues
- Topics
- Sections & Collections
- Article Processing Charge
- Indexing & Archiving
- Editor’s Choice Articles
- Most Cited & Viewed
- Journal Statistics
- Journal History
- Journal Awards
- Society Collaborations
- Conferences
- Editorial Office
Journal Browser
► ▼ Journal BrowserHighly Accessed Articles
Latest Books
E-Mail Alert
News
11 September 2026
Medicina | Highly Cited Papers Published in 2024–2025 and Hot Topic Special Issues in the “Orthopedics” Section
10 September 2026
Summary of the MDPI Academic Publishing Workshop at the School of Medicine, Walailak University, Held on 19 August 2026
Topics
Topic in
Healthcare, Hospitals, JCM, Safety, Medicina, Medicines
Drug Use and Patient Safety in Primary and Secondary Care Settings
Topic Editors: Kingston Rajiah, Ashuin Kammar-GarcíaDeadline: 31 October 2026
Topic in
JCM, Medicina, Prosthesis, IJMS, Clinics and Practice
Innovations in Plastic Surgery and Regenerative Medicine—2nd Edition
Topic Editors: Francesco D’Andrea, Jean Paul Meningaud, Barbara Hersant, Simone La PadulaDeadline: 30 November 2026
Topic in
JCM, JPM, Medicina, Healthcare
New Advances in Physical Therapy and Occupational Therapy, 2nd Edition
Topic Editors: Hye-Rim Suh, Suk-Chan Hahm, Hwi-Young Cho, Ki-Hun ChoDeadline: 15 December 2026
Topic in
Diagnostics, Healthcare, JCM, Medicina, Dentistry Journal
Digital Patient Care: Bridging Technology and Clinical Practice
Topic Editors: Christos Rahiotis, Panagiotis NtovasDeadline: 31 December 2026
Conferences
Special Issues
Special Issue in
Medicina
Imaging-Guided Techniques in Oncology: An Update on Imaging Tools for Interventional Procedures
Guest Editors: Salvatore Silipigni, Antonio Bottari, Pierpaolo BiondettiDeadline: 18 September 2026
Special Issue in
Medicina
The Role of Physical Exercise in Bone Health and Osteoporosis Prevention
Guest Editor: António MonteiroDeadline: 20 September 2026
Special Issue in
Medicina
Advances in Reproductive Surgeries
Guest Editor: Dimitrios PapageorgiouDeadline: 20 September 2026
Special Issue in
Medicina
Nutritional Management of Adults with Obesity
Guest Editors: Alessandro Laviano, Salvatore VaccaroDeadline: 20 September 2026
Topical Collections
Topical Collection in
Medicina
New Concepts for Dental Treatments and Evaluations
Collection Editors: Cosmin Sinescu, Virgil-Florin Duma
Topical Collection in
Medicina
Interdisciplinary Medicine – The Key For Personalized Medicine
Collection Editor: Camelia Diaconu
Topical Collection in
Medicina
Pain, Bleeding, Trauma and Infections: The 4 Horsemen of the Apocalypse for the Emergency Medicine
Collection Editor: Marcello Candelli
Topical Collection in
Medicina
Advances in Cornea, Cataract, and Refractive Surgery
Collection Editor: Ivo Guber