


Abstract
Iron deficiency (ID) and restlessness are associated with sleep/wake-disorders (e.g., restless legs syndrome (RLS)) and neurodevelopmental disorders (attention deficit/hyperactivity and autism spectrum disorders (ADHD; ASD)). However, a standardized approach to assessing ID and restlessness is missing. We reviewed iron status and family sleep/ID history data collected at a sleep/wake behavior clinic under a quality improvement/quality assurance project. Restlessness was explored through patient and parental narratives and a ‘suggested clinical immobilization test’. Of 199 patients, 94% had ID, with 43% having a family history of ID. ADHD (46%) and ASD (45%) were common conditions, along with chronic insomnia (61%), sleep-disordered breathing (50%), and parasomnias (22%). In unadjusted analysis, a family history of ID increased the odds (95% CI) of familial RLS (OR: 5.98, p = 0.0002, [2.35–15.2]), insomnia/DIMS (OR: 3.44, p = 0.0084, [1.37–8.64]), and RLS (OR: 7.00, p = 0.01, [1.49–32.93]) in patients with ADHD, and of insomnia/DIMS (OR: 4.77, p = 0.0014, [1.82–12.5]), RLS/PLMS (OR: 5.83, p = 0.009, [1.54–22.1]), RLS (OR: 4.05, p = 0.01, [1.33–12.3]), and familial RLS (OR: 2.82, p = 0.02, [1.17–6.81]) in patients with ASD. ID and restlessness were characteristics of ADHD and ASD, and a family history of ID increased the risk of sleep/wake-disorders. These findings highlight the need to integrate comprehensive blood work and family history to capture ID in children and adolescents with restless behaviors.
1. Introduction
Iron, classified as a trace element, is present in all of the body’s cells and serves as a component of hemoglobin and myoglobin. Its primary role involves carrying oxygen in both the bloodstream and muscles [1]. Recently, iron has received increasing attention due to its role in sleep disorders [2,3], as well as wake behaviors associated with mental health (MH) and/or neurodevelopmental disorders (NDDs) such as attention deficit hyperactivity disorder (ADHD) [4,5], autism spectrum disorder (ASD), and prenatal alcohol exposure/fetal alcohol spectrum disorder (PAE/FASD) [6].
During development, iron plays a substantial role in several central nervous system processes, including neurogenesis, the differentiation of brain cells, myelination, and the neurotransmitter metabolism. Perinatal iron deficiency (ID) in animal models may alter the neurochemical profile of the hippocampus [7], lead to dysfunction in the striatum accompanied by behavioral changes [8], and have persistent effects on brain myelination [9]. These proposed mechanisms are derived from iron’s modulating role in the brain and spinal cord [10], leading us to consider central ID rather than focusing exclusively on brain ID [11,12].
Iron is present as a trace element in neurons, oligodendrocytes, astrocytes, and microglia, and plays an essential role in the transfer of electrons and the synthesis of neurotransmitters such as dopamine, epinephrine, norepinephrine, and serotonin. These neurotransmitters are involved in various functions, including emotions, the sleep/wake cycle, movement, attention, memory, and learning through its cofactor function for phenylalanine hydroxylase [13] and tryptophan hydroxylase [14]. Furthermore, iron serves as an important cofactor for tyrosine hydroxylase which regulates the dopamine synthesis pathway by converting tyrosine to dihydroxy-phenylalanine (DOPA) [15,16]. Collectively, these findings suggest that both perinatal and postnatal ID might play a substantial role in behavioral medicine, including both sleep and wake behaviors.
Non-anemic ID is associated with multiple sleep/wake disorders; however, a standardized assessment of iron status in the diagnostic work-up for sleep/wake-disorders has not been established in clinical practice [3]. The most frequent causes of sleep/wake disturbances associated with central ID are sleep/wake disorders presenting with hyper-motor restlessness, hyper-arousability, restless leg syndrome (RLS) [17,18,19,20], periodic limb movements in sleep (PLMS) [21,22], and restless sleep disorder (RSD) [23]. RLS is a neurological sensorimotor disorder which is a frequently unrecognized and/or underestimated cause of intractable chronic insomnia [24,25]. The characteristic “urge-to-move” can manifest in several different body parts and is associated with paresthesias, discomfort, or even pain. As RLS was first described in adults and has been approached from an adult neurology perspective [26], the natural history of pediatric RLS has not been thoroughly investigated and pediatric RLS phenotypes have not yet been described. The role of RLS in neurodevelopmental disorders such as PAE/FASD [27], Down Syndrome [28], or ASD [29] has been questioned, but not investigated systematically. Diagnoses are made based on adult sleep medicine and reporting an “urge-to-move”, which presents as restlessness. This is alleviated by voluntary movements while awake, but results in disturbances in the onset and maintenance of sleep. PLMS are believed to be a continuum of RLS symptoms during sleep that impact sleep quality and are characterized by repetitive small movements of the toes, leading to larger movements involving the ankle and knee [21,22].
RLS, PLMS, and ADHD share hypermotor restlessness and hyper-arousability as common factors that lead to non-restorative sleep. While RLS may present with ADHD-like behaviors during the daytime [18,30], ADHD itself has been associated with a variety of sleep phenotypes [31] and is considered to be a 24 h disorder. RSD is characterized by frequent body movements of large muscle groups that disrupt both sleep and wakefulness, and was first described in 2018. Characterizing hyper-motor restlessness during sleep as a new diagnostic entity supports our understanding that disorders presenting with hypermotor-restlessness and/or hyper-arousability need an in-depth phenotyping approach from a pediatric sleep medicine perspective [23].
Given the experimental and clinical evidence of the effects of iron on the central nervous system and sleep/wake behaviors [2,3,12,32,33,34,35], we implemented an iron status assessment as a standard investigation in our clinical setting. Here, we present findings on iron status in children and adolescents referred to a Sleep/Wake-Behaviour Clinic at a tertiary care center with a focus on the common neurodevelopmental disorders, ADHD and ASD.
2. Materials and Methods
2.1. Patients
Patient data collection was conducted at the Sleep/Wake-Behavior Clinic in the Division of Child & Adolescent Psychiatry of BC Children’s Hospital in Vancouver, Canada. Patients were referred to the clinic by the hospital and/or community-based general practitioners, pediatricians, or psychiatrists. We conducted a retrospective analysis of the prospectively collected data via structured intake forms (Supplementary Table S1) and clinical assessments from our clinic over a time period of 18 months (2021 to 2023).
2.2. Inclusion Criteria
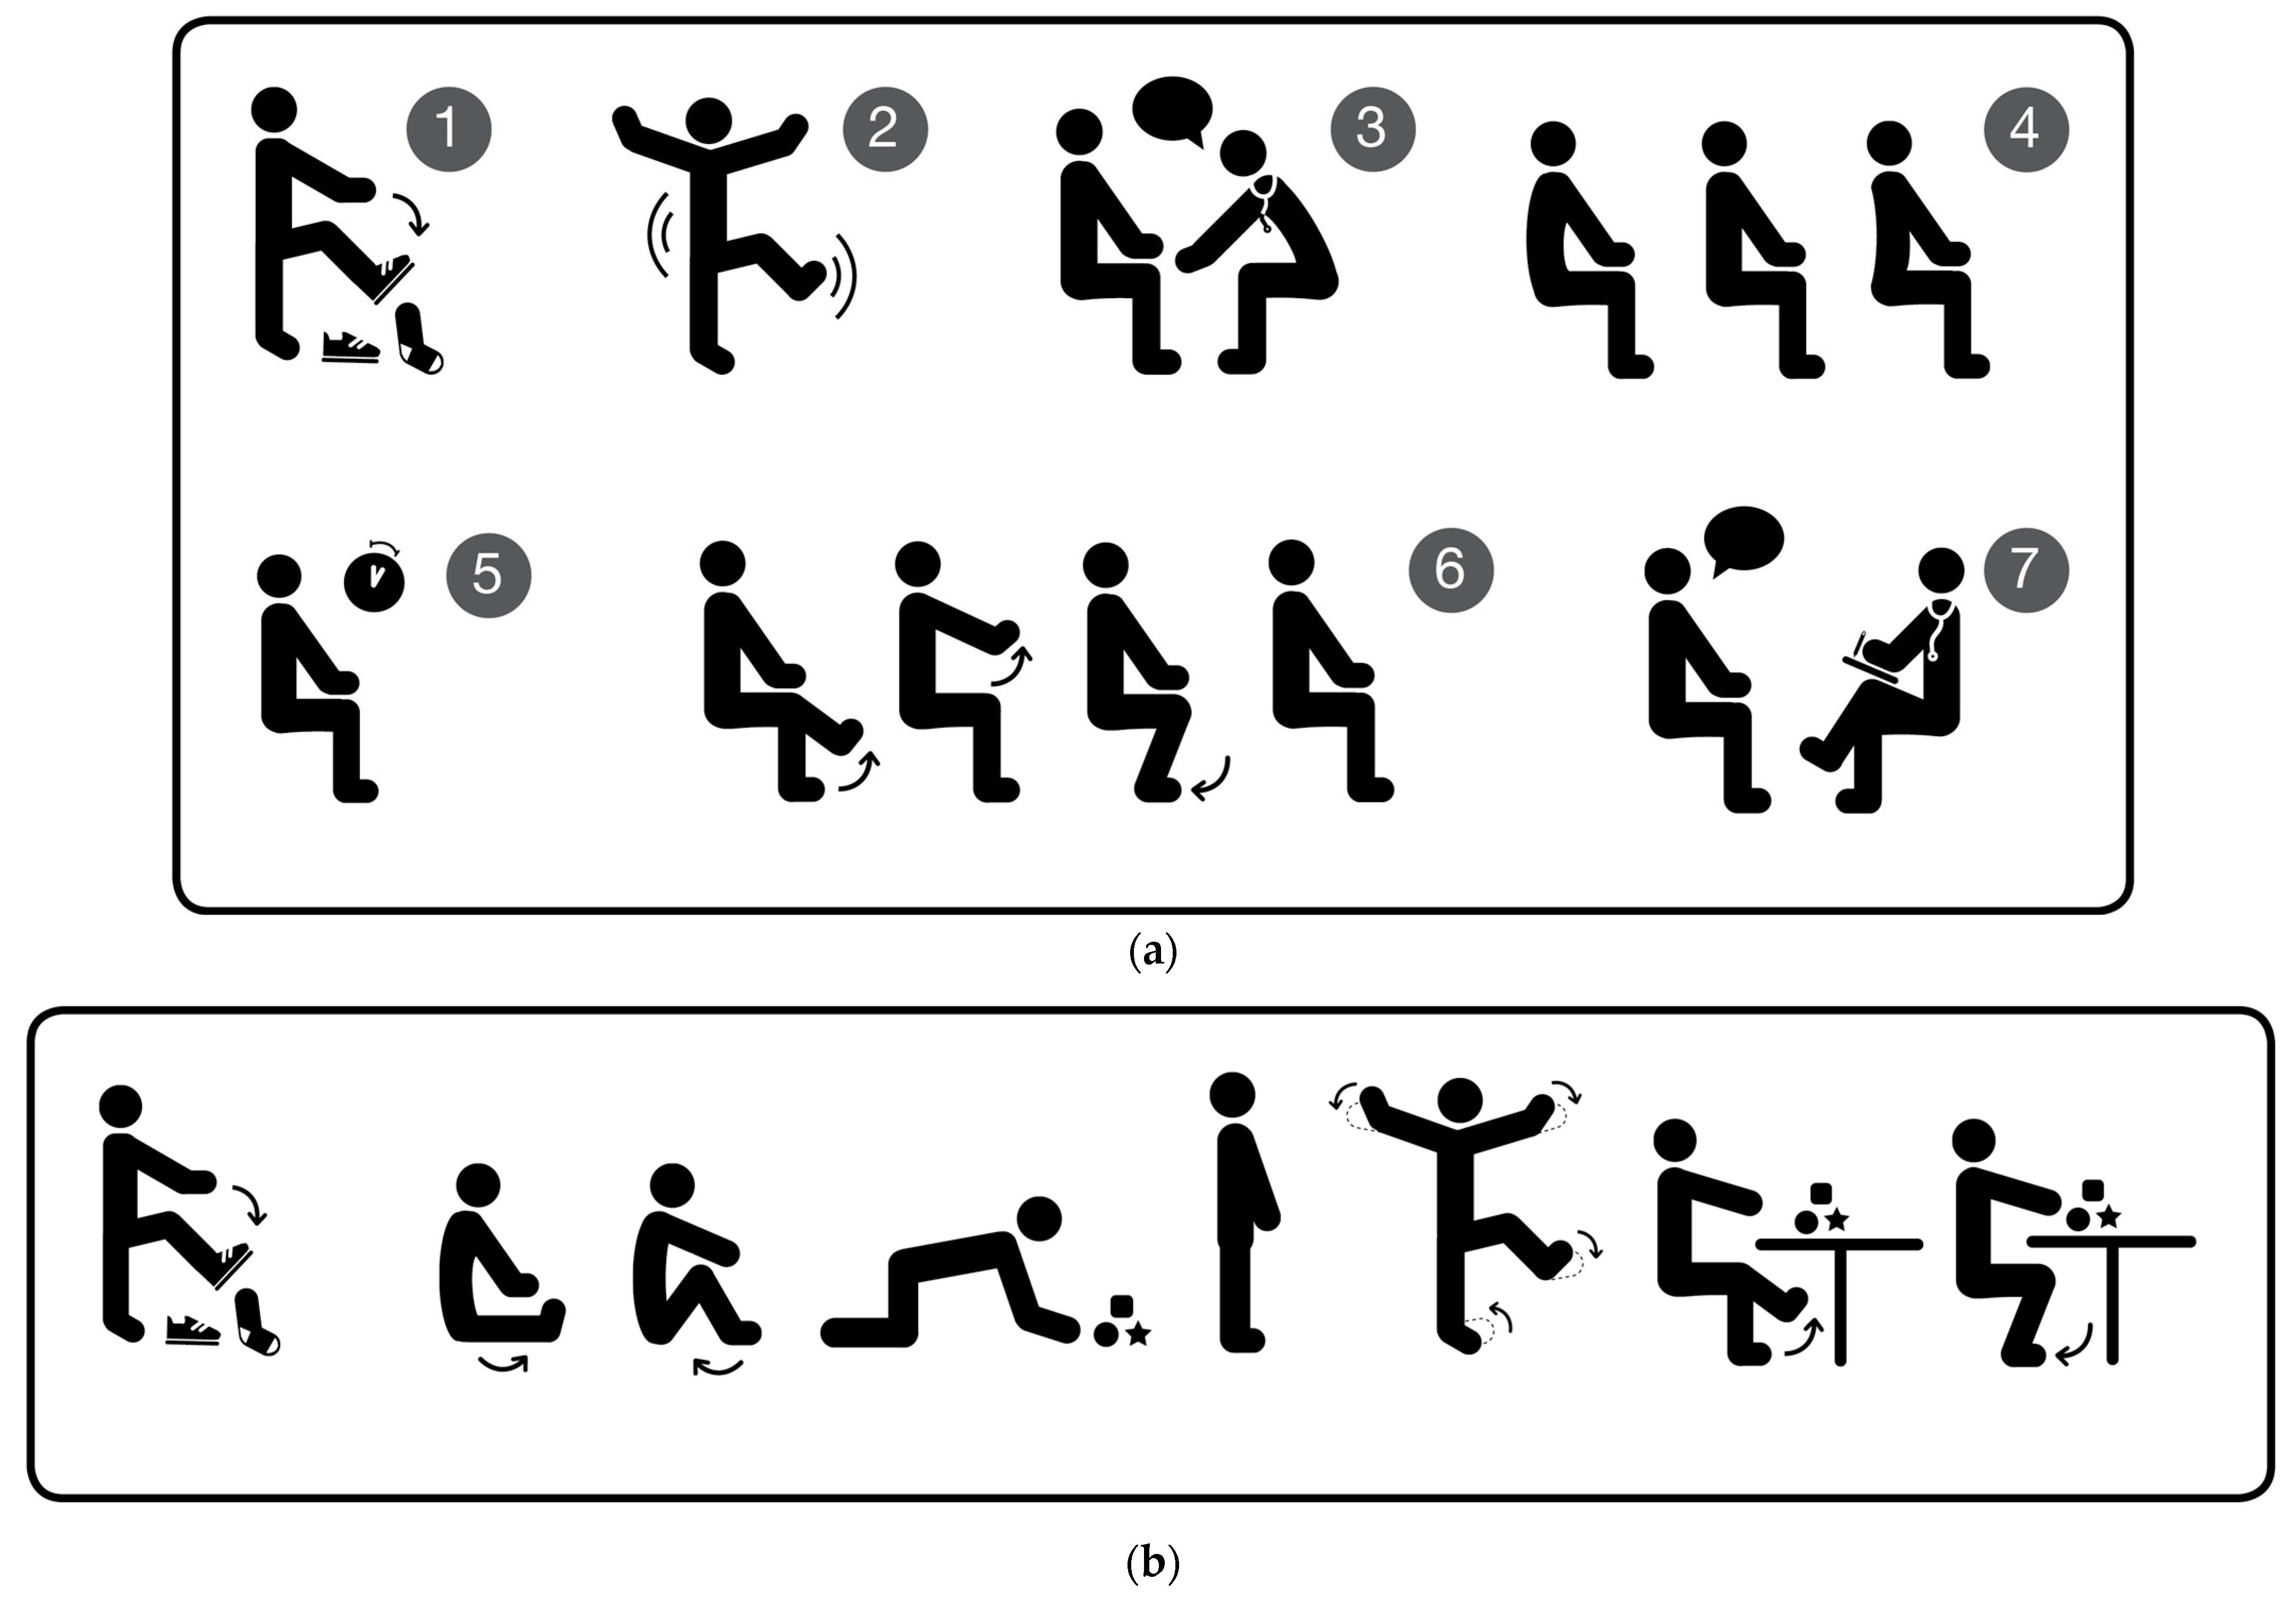
(1) Completion of electronic intake forms independently or with the assistance of the team prior to the clinical assessment. (2) Full clinical assessment (in-person or via telehealth) that included the suggested clinical immobilization test (SCIT) of the patient and/or accompanying biological family member (parent and/or sibling; note that applicability of the formal SCIT depends on the developmental age and capacity of the participating patient and the applicability of the informal SCIT on age and ability to move; see Figure 1). (3) Collection of information on the patient’s most recent iron status and parental ID history. Furthermore, we collected information on demographics, comorbidities and medications. Exclusion criteria were any hematologic comorbidities such as thalassemia or sickle cell anemia. Patients included had a mean age of 10.83 years (median: 12 years; min: 3 months; max: 23 years).
2.3. Iron Deficiency
Iron status was investigated in 199 patients. Non-anemic ID was defined as normal hemoglobin with serum ferritin < 50 µg/L, as per the RLS guidelines from the International Restless Legs Syndrome Study Group, with negative CRP and no signs of inflammation/infection in the lab (e.g., elevated CRP or WBC/differential) and/or clinically (e.g., asthma, eczema, acne, or parasites), and/or a fasting iron status with low fasting serum iron, low iron saturation, and/or high TIBC [19,24,25]. Additional RBC indices were reviewed as indicators of anemia, including mean corpuscular volume (MCV), mean corpuscular hemoglobin (MCH), and mean corpuscular hemoglobin concentration (MCHC). Parents with a clear self-reported history of ID were appropriately identified, and in cases where the evidence was inconclusive but clinical symptoms of restlessness and/or RLS were evident, parental serum ferritin values were reviewed using electronic records with the consent of the individual (no additional data collection). ID in adults was defined as serum ferritin < 75 µg/L with negative CRP and no clinical or laboratory signs of inflammation/infection [19].
2.4. Clinical Assessment
The screening and assessment methods for an in-depth assessment of disruptive sleep/wake-behaviors were developed during an interdisciplinary PhD research endeavor utilizing qualitative methodologies to optimize clinical best practices, as previously described [25,36].
For transparency, an overview of the clinical assessment methodology is described below (Table 1 and Figure 1) [36,37,38]. A table version of the electronic intake forms is shown in Supplementary Table S1. The intake process utilizes REDCap, an electronic data collection tool [39], since 2021. All patients receive an intake form consisting of qualitative open-ended questions regarding observed/experienced sleep situations utilizing the bedtime, excessive daytime sleepiness, awakenings, routines, snoring or sleep-disordered breathing, quality of sleep, and non-specific concerns domains [40]. Furthermore, individual goals [41] and concerns [36] of the family and, if applicable, of the patient were collected. Information regarding daytime functioning and medication information was also collected. For quantitative information, the following questionnaires were used: the Sleep Disturbance Scale for Children (SDSC) [42] and the ADHD Rating Scale-IV [43].
Table 1.
Suggested Clinical Immobilization Test procedure adapted from Ipsiroglu et al. [25,44].
Figure 1.
(a) Formal SCIT, visual depiction of the steps (①–⑦) as described in Table 1, which is used to capture descriptions of sensations from the affected individual in combination with observations from the assessing professional in a structured manner for exploring individual RLS symptoms (courtesy of kleanthes Publishers, Dresden [25,37,44]). (b) Informal SCIT, visual depiction of the play situations as described in Table 1, which is used in children and individuals who cannot participate in a formal SCIT. Here we explore the balance between movements and resting from an RLS perspective together with the caregivers based solely on observations (courtesy of kleanthes Publishers, Dresden [25,37,44]).
2.5. Data Analysis
We performed a comprehensive descriptive analysis to examine neurodevelopmental conditions, mental health diagnoses, sleep disorders, and medication use, stratified by ID status (ID versus no ID, and ID with versus without family history). Frequency and percentage are presented for all categorical variables. We then used unadjusted logistic regression to investigate the association of ID with family history (versus no ID or ID with no family history) and various sleep/wake disorders among the two main patient cohorts of ADHD and ASD. Finally, multivariate logistic regression models were constructed for the main sleep disorder, RLS (RLS only, familial RLS, and probable painful RLS) with ID (ID with a family history versus ID without family history versus no ID), ADHD, ASD, and the clinical RLS-associated symptoms of bedtime resistance, restlessness before falling asleep, and restlessness during sleep, as well as age and sex. Odds ratios (OR) with 95% confidence intervals (CI) and two-sided p-values are reported.
3. Results
3.1. Descriptive Statistics
Out of 250 patients referred to the Sleep/Wake-Behavior clinic between 2021 and 2023, 199/250 (80%) patients met the inclusion criteria. In total, 21 patients were excluded due to incomplete intake forms and another 30 patients were excluded because they had only been screened and not fully assessed at the time of analysis.
Based on the lab findings of the 199 included patients, 188 (94%) patients fulfilled the criteria for anemic or non-anemic ID, whereas 11 (6%) patients did not have biochemical evidence of ID. In total, 41% of all patients had a family history of ID. A family history of ID mainly traced back to birth mothers who experienced chronic or intermittent ID since their teenage years and/or during pregnancy. Fathers less frequently reported experiencing ID, but if so, patients had more first-degree relatives with ID. We further explored the history of ID and sleep in the patient’s siblings. Iron deficiency diagnosis for family members was typically made by their family doctors or pediatricians and was reported by the parent or caregiver during the screening and/or assessment.
Based on previous clinical assessments, 100 (50%) patients presented with an externalizing disorder or disorders of disruptive behaviors, with ADHD being the most common diagnosis (n = 92; 46%). In total, 84 (42%) patients had an internalizing disorder, with anxiety disorders being the most common (n = 81; 41%). The most common neurodevelopmental presentations were ASD (n = 89; 45%), neurologic conditions (n = 38, 19%), global developmental delay/intellectual disability (n = 26; 13%), and genetic conditions (n = 21; 11%).
Based on the clinical assessment at the Sleep/Wake-Behaviour Clinic, 121 (61%) patients met the International Classification of Sleep Disorders (Third Edition) criteria [45] for chronic insomnia and had problems with falling and/or maintaining sleep. In total, 32 (16%) patients fulfilled the criteria for circadian rhythm sleep disorder (CRSD); subtypes were captured, but as our cohort comprised individuals of various ages and changing sleep patterns, we are not presenting these data. In total, 43 (22%) patients experienced parasomnias, and 100 (50%) had signs of sleep-disordered breathing. In total, 148 (74%) patients had RLS, 103 (52%) had a family history of RLS, and 22 (11%) had probable painful RLS. Among the 22 patients with painful RLS, 9 (41%) had self-injurious behaviors; among this group, 6 (67%) had a family history of ID and 3 (33%) had no family history of ID. PLMS/Restless sleep was noted in 60 (30%) patients.
Descriptive statistics are presented in Table 2.
Table 2.
Frequency and percent of patients with various comorbidities across different categories: all patients, patients without ID, patients with ID, patients without a family history of ID, and patients with a family history of ID.
3.2. Subgroup Analysis ADHD
In sub-analyses of only patients with ADHD (n = 92), a family history of ID significantly increased the odds of having familial RLS (OR: 5.98, p = 0.0002, 95% CI [2.35, 15.20]), insomnia/DIMS (OR: 3.44, p = 0.0084, 95% CI [1.37, 8.64]), and RLS (OR: 7.00, p = 0.0014, 95% CI [1.49, 32.93]). There was also evidence of increased odds of probable painful RLS (OR: 3.48, p = 0.053, 95% CI [0.99, 12.30]) and SWTD (OR: 4.41, p = 0.079, 95% CI [0.84, 23.17]). The results of all of the odds ratio analysis are presented in Supplementary Table S5.
3.3. Subgroup Analysis ASD
In sub-analyses of patients with ASD (n = 89), a family history of ID significantly increased the odds of having insomnia/DIMS (OR: 4.77, p = 0.0014, 95% CI [1.82, 12.48]), RLS/PLMS/Restlessness (OR: 5.83, p = 0.0094, 95% CI [1.54, 22.07]), RLS (OR: 4.05, p = 0.013, 95% CI [1.33, 12.33]), and familial RLS (OR: 2.82, p = 0.02, 95% CI [1.17, 6.81]). The results of all odds ratios analysis are presented in Supplementary Table S5.
3.4. Multivariate Logistic Regression Analyses
Analysis of RLS only: A family history of ID was associated with over six times the odds of having RLS, compared to patients with no ID (OR: 6.25, p = 0.013, 95% CI [1.46, 26.74]), while no family history of ID was associated with over twice the odds, though this was not significant at p < 0.05 (OR: 2.67, p = 0.158, 95% CI [0.68, 10.39]). Patients with ADHD had about twice the odds of having RLS (OR: 2.12, p = 0.046, 95% CI [1.01, 4.42]) compared to those with no ADHD; ASD was not associated with RLS. Bedtime resistance and restlessness did not appear to be associated with RLS, either. See Supplementary Table S2.
Familial RLS analysis: A family history of ID was associated with over four times the odds of familial RLS compared to patients with no ID (OR: 4.38, p = 0.048, 95% CI [1.01, 18.94]). ADHD was not associated with RLS, but patients with ASD had about 70% higher odds of familial RLS, although this was not significant at p < 0.05 (OR: 1.71, p = 0.103, 95% CI [0.90, 3.24]). Bedtime resistance and restlessness did not appear to be associated with familial RLS. See Supplementary Table S3.
Probable Painful RLS analysis: Patients without ID were excluded from the analysis, as none of them had probable painful RLS. A family history of ID was associated with over twice the odds of probable painful RLS compared to patients with no family history of ID, although this was not significant at p < 0.05 (OR: 2.20, p = 0.113, 95% CI [0.83, 5.82]). ADHD and ASD were not associated with probable painful RLS, and neither were bedtime resistance or restlessness. See Supplementary Table S4.
3.5. Medications
Results are presented in Supplementary Table S6a,b.
4. Discussion
This QIQA-study identified ID and family history of ID as being significant risk factors for sleep problems in patients referred to a Sleep/Wake-Behavior Clinic located in the Division of Child & Adolescent Psychiatry in a tertiary care hospital. As part of the project that included a structured intake procedure, all patients completed intake forms, had their iron status checked, and received clinical assessments. Notably, 94% of patients were diagnosed with either anemic or non-anemic ID. Among these patients, MH/NDDs, such as ADHD and ASD, along with sleep disorders such as RLS (76%) and insomnia (61%), were the most prevalent comorbidities. Prior scoping reviews conducted by our team have revealed associations between ID in children/adolescents and prevalent NDDs and MH conditions such as ADHD and ASD [3,6]. Upon reviewing the ADHD and ASD subgroups in our patient data, we identified specific sleep/wake-disorders that were more likely to occur in children/adolescents with a family history of ID. In the ADHD sub-group, patients with family history of ID had an increased risk of familial RLS, insomnia/DIMS, RLS, probable painful RLS, and sleep-wake transition disorder, compared to patients without ID or with no family history of ID. For patients with ASD, a family history of ID increased the risk of insomnia/DIMS, RLS/PLMS, RLS, and familial RLS compared to patients without ID or no family history of ID.
Interestingly, restlessness, a common symptom of sleep/wake disturbances that can be associated with ID [38], emerged as a strong risk factor across both the overall patient population in our review as well as the ADHD and ASD subgroups. Despite its high prevalence, restlessness is often missed in pediatric patients, likely due to several reasons. Firstly, pediatric sleep medicine has historically been derived from adult sleep medicine. Typically, pediatric patients are not actively involved in the clinical assessments and the symptom of restlessness is not explored from the child’s or adolescents’ perspective. In adult neurology, RLS is based on history-taking and the explicit mentioning of uncomfortable sensations. However, in pediatric sleep medicine, the proactive and structured involvement of pediatric patients in the assessment of their sleep/wake behaviors is a recent development [18,25,36]. Another reason restlessness is commonly missed is because the primary method of assessment, verbal communication, may pose challenges for pediatric patients who struggle to articulate their discomfort and pain, e.g., for young, non-verbal patients, and/or patients with developmental delays and intellectual disabilities [46]. Most importantly, restlessness is considered to be an intrinsic characteristic of patients with NDDs and MH-conditions such as ADHD, ASD, and PAE/FASD, and remains largely unexplored [2,4,29,47]. This is particularly evident in conditions such as RLS, where symptoms may be underrecognized due to the patients’ inability to express their discomfort accurately, or because they may not recognize the ‘baseline’ state [25,36]. Considering these factors, we aimed to ensure that restlessness was not overlooked. By following the recommendation of the Pediatric International RLS Study Group to conduct structured behavioral observations [18], we adapted the formal SCIT and applied an informal SCIT in cases where a formal SCIT was not applicable. The informal SCIT allows the observer and caregiver to review and explore movement patterns of the affected individual from an RLS perspective (see Table 1, Figure 1a,b). The methodology of explorative history-taking, combined with the review of a family history of RLS and ID among the patient’s parents and siblings helped to collect additional information in a structured manner and may have created a unique perspective for our patient population.
While the high percentage of pediatric patients diagnosed with RLS might be explained by exploratory observations, including the non-formal SCIT and investigation of family history, diagnosing probable painful RLS involves exploring its potential link with self-injurious behaviors (SIBs) in a high-risk population whose behaviors might be triggered by pain. Thus, in British Columbia, all pediatric patients referred to the Provincial SIB-Clinic receive a sleep/wake behavior assessment, and the frequency and intensity of the SIBs are explored using the explorative questioning criteria as described (Table 3). While SIBs in children with NDDs have been associated with frustrations in communication [48], which may lead to learned SIBs, painful RLS in children has not been described yet. Therefore, we have used the diagnosis of probable painful RLS retrospectively only in patients whose behavioral patterns and patterns of falling asleep/sleep maintenance and restlessness started to change after iron treatment. Our attempt to review restlessness by applying the formal and informal SCIT and conducting a structured iron status revealed an interesting new perspective. Out of the 22 patients with painful RLS, only 9 had self-injurious behaviors and 6/9 had a family history of ID, showing that in the subpopulation with self-injurious behaviors, ID, and particularly a family history of ID, may act as aggravating factors of self-injurious behaviors. The clinical conclusion is that the link between ID and SIBs should be further investigated.
Table 3.
The five essential diagnostic criteria for RLS [20], and the adaptations, as well as examples, of pediatric patients. Note that in some patients, parental descriptions are used for describing the behavioral observations.
5. Limitations and Strengths
(1) Reviewing a subgroup of patients all presenting with NDDs and MH conditions and not having a control group may have confounded clinical results. (2) Only a subgroup of patients were medication-naive, and some of the medications (e.g., stimulants or antipsychotics) may affect sensations associated with RLS and/or ADHD. For example, the negative association between sensory processing dysfunction (SPD) and a family history of ID in the ADHD subgroup is not explainable without the data of controls and without reviewing the effects of medications on sensory processing. (3) We have reported a retrospective analysis of data, despite collecting the data prospectively. A limitation in retrospectively analyzing data is the absence of a structured categorization for certain data which may have helped strengthen our analysis. For example, we did not distinguish between anemic and nonanemic ID in our electronic intake forms. Additionally, data regarding family history of ID, either of their mother or father, was not separated. Lastly, the relatively small sample sizes and small number of patients without ID reduced the statistical power in logistic regression analyses and resulted in reduced precision/wide confidence intervals. While all of these limitations raise questions about the generalizability of our results to the broader pediatric population, the high prevalence of ID (94%) and family history of ID (43%), and the potential link between self-injurious behaviors with ID serve as the strengths of our study. The mechanisms of ID in this population are likely multifactorial with inadequate nutrition, inflammation, and malabsorption being potential contributors. However, as our analysis was limited, we did not capture information on the possible causes. These aspects contribute valuable insights to the ongoing discourse about how ID and non-anemic ID should be explored [49].
6. Conclusions
While in-depth phenotyping of restlessness has been applied for some time in the field of sleep medicine [20,50], definitions of pediatric restlessness in sleep have been based on adult criteria and do not fully acknowledge physiological differences present in children. Therefore, further phenotyping of pediatric restlessness is necessary to identify these signs and symptoms in a clinical setting. In the context of ADHD, daytime restlessness has been considered to be a key diagnostic criterion, but nighttime restlessness and restless sleep are not included in the current DSM-V criteria [51], despite ADHD being a 24 h disorder. Interestingly, restless sleep was part of the diagnostic criteria for ADHD in the 1980 DSM-III, but has since been omitted in subsequent revisions [52,53]. The recent polysomnography-based descriptions for ADHD [31] and RSD [23] sleep phenotypes ask for a more in-depth investigation of clinical observations and biochemical imbalances, with ID and other factors affecting iron homeostasis (such as inflammation) becoming a focus of interest. To apply this concept, we developed an exploratory observation-based approach to RLS [25,36,44,54] and investigated ID among patients with NDDs and MH conditions. Our results indicate that ID and a family history of ID are significant risk factors for restless sleep and wake behaviors in patients with ADHD and ASD. This finding is critical, as ID can often be effectively treated with iron supplementation, potentially improving sleep in children and adolescents affected by these conditions.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/nu16183064/s1, Table S1. Questions and response options for intake forms provided to patients/caregivers. All content on the intake forms was approved by the Provincial Health Services Authority. Table S2. Results from a multivariate logistic regression analysis analyzing the relationship between RLS with ID (with/without a family history of ID), ADHD, ASD, bedtime resistance, restlessness before falling asleep, restlessness during sleep, age, and sex. Table S3. Multivariate logistic regression analysis examining the relationship between familial RLS with ID (with/without a family history of ID), ADHD, ASD, bedtime resistance, restlessness before falling asleep, restlessness during sleep, age, and sex. Table S4. Multivariate logistic regression analysis examining the relationship between painful RLS with ID (with/without a family history of ID), ADHD, ASD, bedtime resistance, restlessness before falling asleep, restlessness during sleep, age, and sex. Table S5. Odds ratios of having a family history of ID & (ADHD or ASD) with various sleep/wake-disorders. Table S6a. Number of patients taking various medications across different categories: all patients, patients without ID, patients with ID, patients without a family history of ID, and patients with a family history of ID. Table S6b. Number of patients taking melatonin in combination with various medications across different categories: all patients, patients without ID, patients with ID, patients without a family history of ID, and patients with a family history of ID. Figure S1. Visual representation of the log(odds ratio) in the subgroup analysis of ADHD. Error bars represent the 95% confidence intervals. Heat maps representing p-values were used to optimize readability. CRSD: circadian rhythm sleep disorders; DA: disorders of arousal; EDS/DOES: excessive daytime sleepiness/disorders of excessive somnolence; RLS: restless legs syndrome; SDB: sleep disordered breathing; SIB: self-injurious behaviours; SPD: sensory processing disorder; SWTD: sleep wake transition disorders. Figure S2. Visual representation of the log(odds ratio) in the subgroup analysis of ASD. Error bars represent the 95% confidence intervals. Heat maps representing p-values were used to optimize readability. CRSD: circadian rhythm sleep disorders; DA: disorders of arousal; EDS/DOES: excessive daytime sleepiness/disorders of excessive somnolence; RLS: restless legs syndrome; SDB: sleep disordered breathing; SIB: self-injurious behaviours; SPD: sensory processing disorder; SWTD: sleep wake transition disorders. Figure S3. Visual representation of the log(odds ratio) based on family history of ID and familial RLS. Error bars represent the 95% confidence intervals. Heat maps representing p-values were used to optimize readability. CRSD: circadian rhythm sleep disorders; DA: disorders of arousal; EDS/DOES: excessive daytime sleepiness/disorders of excessive somnolence; RLS: restless legs syndrome; SDB: sleep disordered breathing; SIB: self-injurious behaviours; SPD: sensory processing disorder; SWTD: sleep wake transition disorders.
Author Contributions
Conceptualization: O.S.I.; investigation: K.E., R.F., O.S.I., M.S.L., and A.R.; methodology: O.S.I., C.K., E.K., and A.L.W.; formal analysis: O.H. and P.K.P., and M.B.; data curation: O.H.; writing—original draft preparation: O.S.I.; writing—review and editing: C.K., D.W., E.K., P.K.P., O.H., S.M., O.S.I., and M.B.; visualization: P.K.P. and O.S.I.; supervision: O.S.I.; project administration: O.S.I. and D.W.; funding acquisition: O.S.I. and E.K. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by BC Children’s Hospital Research Foundation. Account: Sleep Research, KRZ75155.
Institutional Review Board Statement
The Quality Improvement Quality Assurance study was conducted in accordance with the Declaration of Helsinki, and as exempted by the Institutional Review Board (or Ethics Committee), it was reviewed by the institutional Data Collection & Solutions Steering Committee/—joint committee of the Provincial Health Services Authority (PHSA) and the Research Ethics Board at the University of British Columbia. Application: 31 January 2021. Project approval: 15 February 2021. Project intake #:216.
Informed Consent Statement
Informed consent was obtained via an electronic REDCap form.
Data Availability Statement
The original contributions presented in the study are included in the article and Supplementary Materials; further inquiries can be directed to the corresponding author.
Acknowledgments
We acknowledge BC Children’s Hospital Research Institute for their ongoing support of our work, and BC Children’s Hospital Foundation. We acknowledge with gratitude that we live and work on the traditional, ancestral, and unceded territories of the Coast Salish peoples—the Musqueam, Squamish, and Tsleil-Waututh Nations.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- National Research Council (US) Committee on Diet and Health. Diet and Health: Implications for Reducing Chronic Disease Risk; National Academies Press: Washington, DC, USA, 1989; ISBN 0-309-03994-0. [Google Scholar]
- Silvestri, R. The Importance of Diagnosing and Treating Iron Deficiency in Sleep Disorders. Sleep Med. Rev. 2020, 51, 101314. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leung, W.; Singh, I.; McWilliams, S.; Stockler, S.; Ipsiroglu, O.S. Iron Deficiency and Sleep—A Scoping Review. Sleep Med. Rev. 2020, 51, 101274. [Google Scholar] [CrossRef] [Scilit]
- Silvestri, R. Sleep and ADHD: A Complex and Bidirectional Relationship. Sleep Med. Rev. 2022, 63, 101643. [Google Scholar] [CrossRef] [Scilit]
- McWilliams, S.; Zhou, T.; Stockler, S.; Elbe, D.; Ipsiroglu, O.S. Sleep as an Outcome Measure in ADHD Randomized Controlled Trials: A Scoping Review. Sleep Med. Rev. 2022, 63, 101613. [Google Scholar] [CrossRef] [Scilit]
- McWilliams, S.; Singh, I.; Leung, W.; Stockler, S.; Ipsiroglu, O.S. Iron Deficiency and Common Neurodevelopmental Disorders—A Scoping Review. PLoS ONE 2022, 17, e0273819. [Google Scholar] [CrossRef] [Scilit]
- Rao, R.; Tkac, I.; Townsend, E.L.; Ennis, K.; Gruetter, R.; Georgieff, M.K. Perinatal Iron Deficiency Predisposes the Developing Rat Hippocampus to Greater Injury from Mild to Moderate Hypoxia—Ischemia. J. Cereb. Blood Flow. Metab. 2007, 27, 729–740. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ward, K.L.; Tkac, I.; Jing, Y.; Felt, B.; Beard, J.; Connor, J.; Schallert, T.; Georgieff, M.K.; Rao, R. Gestational and Lactational Iron Deficiency Alters the Developing Striatal Metabolome and Associated Behaviors in Young Rats. J. Nutr. 2007, 137, 1043–1049. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beard, J.L.; Wiesinger, J.A.; Connor, J.R. Pre- and Postweaning Iron Deficiency Alters Myelination in Sprague-Dawley Rats. Dev. Neurosci. 2003, 25, 308–315. [Google Scholar] [CrossRef] [Scilit]
- Hare, D.; Ayton, S.; Bush, A.; Lei, P. A Delicate Balance: Iron Metabolism and Diseases of the Brain. Front. Aging Neurosci. 2013, 5, 34. [Google Scholar] [CrossRef] [Scilit]
- McWilliams, S.; Hill, O.; Ipsiroglu, O.S.; Clemens, S.; Weber, A.M.; Chen, M.; Connor, J.; Felt, B.T.; Manconi, M.; Mattman, A.; et al. Iron Deficiency and Sleep/Wake Behaviors: A Scoping Review of Clinical Practice Guidelines—How to Overcome the Current Conundrum? Nutrients 2024, 16, 2559. [Google Scholar] [CrossRef] [Scilit]
- Silvani, A.; Ghorayeb, I.; Manconi, M.; Li, Y.; Clemens, S. Putative Animal Models of Restless Legs Syndrome: A Systematic Review and Evaluation of Their Face and Construct Validity. Neurotherapeutics 2023, 20, 154–178. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gottschall, D.W.; Dietrich, R.F.; Benkovic, S.J.; Shiman, R. Phenylalanine Hydroxylase. Correlation of the Iron Content with Activity and the Preparation and Reconstitution of the Apoenzyme. J. Biol. Chem. 1982, 257, 845–849. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kuhn, D.M.; Ruskin, B.; Lovenberg, W. Tryptophan Hydroxylase. The Role of Oxygen, Iron, and Sulfhydryl Groups as Determinants of Stability and Catalytic Activity. J. Biol. Chem. 1980, 255, 4137–4143. [Google Scholar] [CrossRef] [Scilit]
- Ramsey, A.J.; Hillas, P.J.; Fitzpatrick, P.F. Characterization of the Active Site Iron in Tyrosine Hydroxylase. Redox States of the Iron. J. Biol. Chem. 1996, 271, 24395–24400. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, J.; O’Reilly, B.; Venkataraman, R.; Mysliwiec, V.; Mysliwiec, A. Efficacy of Oral Iron in Patients with Restless Legs Syndrome and a Low-Normal Ferritin: A Randomized, Double-Blind, Placebo-Controlled Study. Sleep Med. 2009, 10, 973–975. [Google Scholar] [CrossRef] [Scilit]
- Schulte, E.C.; Kaffe, M.; Schormair, B.; Winklemann, J. Iron in Restless Legs Syndrome. Mov. Disord. Clin. Pract. 2014, 1, 161–172. [Google Scholar] [CrossRef] [Scilit]
- Picchietti, D.L.; Bruni, O.; de Weerd, A.; Durmer, J.S.; Kotagal, S.; Owens, J.A.; Simakajornboon, N. Pediatric Restless Legs Syndrome Diagnostic Criteria: An Update by the International Restless Legs Syndrome Study Group. Sleep Med. 2013, 14, 1253–1259. [Google Scholar] [CrossRef] [Scilit]
- Allen, R.P.; Picchietti, D.L.; Auerbach, M.; Cho, Y.W.; Connor, J.R.; Earley, C.J.; Garcia-Borreguero, D.; Kotagal, S.; Manconi, M.; Ondo, W.; et al. Evidence-Based and Consensus Clinical Practice Guidelines for the Iron Treatment of Restless Legs Syndrome/Willis-Ekbom Disease in Adults and Children: An IRLSSG Task Force Report. Sleep Med. 2018, 41, 27–44. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Allen, R.P.; Picchietti, D.L.; Garcia-Borreguero, D.; Ondo, W.G.; Walters, A.S.; Winkelman, J.W.; Zucconi, M.; Ferri, R.; Trenkwalder, C.; Lee, H.B.; et al. Restless Legs Syndrome/Willis-Ekbom Disease Diagnostic Criteria: Updated International Restless Legs Syndrome Study Group (IRLSSG) Consensus Criteria—History, Rationale, Description, and Significance. Sleep Med. 2014, 15, 860–873. [Google Scholar] [CrossRef] [Scilit]
- Bonnet, M.; Carley, D.; Carskadon, M.; Easton, P.; Guilleminault, C.; Harper, R.; Hayes, B.; Hirshkowitz, M.; Ktonas, P.; Keenan, S.; et al. Recording and Scoring Leg Movements. The Atlas Task Force. Sleep 1993, 16, 748–759. [Google Scholar]
- Sateia, M.J. International Classification of Sleep Disorders-Third Edition: Highlights and Modifications. Chest 2014, 146, 1387–1394. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Del Rosso, L.M.; Bruni, O.; Ferri, R. Restless Sleep Disorder in Children: A Pilot Study on a Tentative New Diagnostic Category. Sleep 2018, 41, zsy102. [Google Scholar] [CrossRef] [Scilit]
- Wagner, A.L. Familial Willis Ekbom Disease/Restless Legs Syndrome: Presentations in Children with Neurodevelopmental Conditions and Their Mothers. Ph.D. Thesis, Paracelsus Medical University, Salzburg, Austria, 2015. [Google Scholar]
- Ipsiroglu, O.S.; Beyzaei, N.; Berger, M.; Wagner, A.L.; Dhalla, S.; Garden, J.; Stockler, S. “Emplotted Narratives” and Structured “Behavioral Observations” Supporting the Diagnosis of Willis-Ekbom Disease/Restless Legs Syndrome in Children with Neurodevelopmental Conditions. CNS Neurosci. Ther. 2016, 22, 894–905. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coccagna, G.; Vetrugno, R.; Lombardi, C.; Provini, F. Restless Legs Syndrome: An Historical Note. Sleep Med. 2004, 5, 279–283. [Google Scholar] [CrossRef]
- Ipsiroglu, O.S.; McKellin, W.H.; Carey, N.; Loock, C. “They Silently Live in Terror…” Why Sleep Problems and Night-Time Related Quality-of-Life Are Missed in Children with a Fetal Alcohol Spectrum Disorder. Soc. Sci. Med. 2013, 79, 76–83. [Google Scholar] [CrossRef] [Scilit]
- Tse, E.; Marwaha, A.; Beyzaei, N.; Berger, M.; Chan, M.; McKenna, D.; Hanbury, P.; Stockler, S.; Ipsiroglu, O. Sleep Problems in Children with down Syndrome. Sleep Med. 2017, 40, e142. [Google Scholar] [CrossRef] [Scilit]
- Kanney, M.L.; Durmer, J.S.; Trotti, L.M.; Leu, R. Rethinking Bedtime Resistance in Children with Autism: Is Restless Legs Syndrome to Blame? J. Clin. Sleep Med. 2020, 16, 2029–2035. [Google Scholar] [CrossRef] [Scilit]
- Cortese, S.; Konofal, E.; Yateman, N.; Mouren, M.-C.; Lecendreux, M. Sleep and Alertness in Children with Attention-Deficit/Hyperactivity Disorder: A Systematic Review of the Literature. Sleep 2006, 29, 504–511. [Google Scholar] [CrossRef] [Scilit]
- Miano, S.; Amato, N.; Foderaro, G.; Pezzoli, V.; Ramelli, G.P.; Toffolet, L.; Manconi, M. Sleep Phenotypes in Attention Deficit Hyperactivity Disorder. Sleep Med. 2019, 60, 123–131. [Google Scholar] [CrossRef] [Scilit]
- Salminen, A.V.; Silvani, A.; Allen, R.P.; Clemens, S.; Garcia-Borreguero, D.; Ghorayeb, I.; Ferré, S.; Li, Y.; Ondo, W.; Picchietti, D.L.; et al. Consensus Guidelines on Rodent Models of Restless Legs Syndrome. Mov. Disord. 2021, 36, 558–569. [Google Scholar] [CrossRef] [Scilit]
- Huebner, S.; Tran, T.D.; Rufer, E.S.; Crump, P.M.; Smith, S.M. Maternal Iron Deficiency Worsens the Associative Learning Deficits and Hippocampal and Cerebellar Losses in a Rat Model of Fetal Alcohol Spectrum Disorders. Alcohol. Clin. Exp. Res. 2015, 39, 2097–2107. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rufer, E.S.; Tran, T.D.; Attridge, M.M.; Andrzejewski; Flentke, G.R.; Smith, S.M. Adequacy of Maternal Iron Status Protects against Behavioral, Neuroanatomical, and Growth Deficits in Fetal Alcohol Spectrum Disorders. PLoS ONE 2012, 7, e47499. [Google Scholar] [CrossRef] [Scilit]
- Silvestri, R.; Ipsiroglu, O.S. Behavioral Sleep Medicine-The Need for Harmonization of Clinical Best Practice Outcome Measures in Children and Adolescents with Intellectual or Developmental Disabilities and Restless Sleep. Front. Psychiatry 2022, 13, 1003019. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ipsiroglu, O.S. Applying Ethnographic Methodologies & Ecology to Unveil Dimensions of Sleep Problems in Children & Youth with Neurodevelopmental Conditions. Ph.D. Thesis, University of British Columbia, Vancouver, BC, Cananda, 2016. [Google Scholar]
- Beyzaei, N.; Wagner, A.; Berger, M.; Milner, R.; Stockler, S.; Ipsiroglu, O. Suggested Clinical Immobilization Test (SCIT) for Diagnosis of Willis–Ekbom Disease in Clinical Practice. Sleep Med. 2015, 16, S205–S206. [Google Scholar] [CrossRef] [Scilit]
- Ipsiroglu, O.S.; Bhathella, J.; Boldut, R.P.; Elbe, D.; Hill, O.; Keys, E.; McWilliams, S.; Silvestri, R.; Wensley, D.F. Understanding Patient Characteristics and Medication Prescriptions in Children with Mental Health and Neurodevelopmental Disorders Referred to a Sleep Clinic—A Quality Improvement/Quality Assurance Analysis. Front. Psychiatry 2022, 13, 878356. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Harris, P.A.; Taylor, R.; Thielke, R.; Payne, J.; Gonzalez, N.; Conde, J.G. Research Electronic Data Capture (REDCap)—A Metadata-Driven Methodology and Workflow Process for Providing Translational Research Informatics Support. J. Biomed. Inf. 2009, 42, 377–381. [Google Scholar] [CrossRef] [Scilit]
- Owens, J.A.; Dalzell, V. Use of the “BEARS” Sleep Screening Tool in a Pediatric Residents’ Continuity Clinic: A Pilot Study. Sleep Med. 2005, 6, 63–69. [Google Scholar] [CrossRef] [Scilit]
- Kiresuk, T.J.; Sherman, R.E. Goal Attainment Scaling: A General Method for Evaluating Comprehensive Community Mental Health Programs. Community Ment. Health J. 1968, 4, 443–453. [Google Scholar] [CrossRef] [Scilit]
- Bruni, O.; Ottaviano, S.; Guidetti, V.; Romoli, M.; Innocenzi, M.; Cortesi, F.; Giannotti, F. The Sleep Disturbance Scale for Children (SDSC). Construction and Validation of an Instrument to Evaluate Sleep Disturbances in Childhood and Adolescence. J. Sleep Res. 1996, 5, 251–261. [Google Scholar] [CrossRef] [Scilit]
- DuPaul, G.J.; Power, T.J.; Anastopoulos, A.D.; Reid, R. ADHD Rating Scale—IV: Checklists, Norms, and Clinical Interpretation; The Guilford Press: New York, NY, USA, 1998. [Google Scholar]
- Ipsiroglu, O.S.; Kloesch, G.; Beyzaei, N.; McCabe, S.; Berger, M.; Kühle, H.J.; Kohn, B.; Puyat, J.; Van der Loos, H.F.M.; Garn, H. Video Recordings of Naturalistic Observations: Pattern Recognition of Disruptive Behaviours in People with Mental Health or Neurodevelopmental Conditions. In Brücken Bauen—Kinderschlafmedizin Verbindet. Aktuelle Kinderschlafmedizin 2017; Kleanthes: Dresden, Germany, 2017; pp. 54–76. [Google Scholar]
- American Academy of Sleep Medicine. International Classification of Sleep Disorders—Third Edition (ICSD-3); American Academy of Sleep Medicine: Darien, IL, USA, 2014. [Google Scholar]
- Picchietti, D.L.; Arbuckle, R.A.; Abetz, L.; Durmer, J.S.; Ivanenko, A.; Owens, J.A.; Croenlein, J.; Allen, R.P.; Walters, A.S. Pediatric restless legs syndrome: Analysis of symptom descriptions and drawings. J. Child Neurol. 2011, 26, 1365–1376. [Google Scholar] [CrossRef] [Scilit]
- Dosman, C.; Witmans, M.; Zwaigenbaum, L. Iron’s Role in Paediatric Restless Legs Syndrome—A Review. J. Pediatr. Child. Health 2012, 17, 193–197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oliver, C.; Richards, C. Practitioner Review: Self-Injurious Behaviour in Children with Developmental Delay. J. Child. Psychol. Psychiatry 2015, 56, 1042–1054. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhu, X.-Y.; Wu, T.-T.; Wang, H.-M.; Li, X.; Ni, L.-Y.; Chen, T.-J.; Qiu, M.-Y.; Shen, J.; Liu, T.; Ondo, W.G.; et al. Correlates of Nonanemic Iron Deficiency in Restless Legs Syndrome. Front. Neurol. 2020, 11, 298. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Trotti, L.M.; Goldstein, C.A.; Harrod, C.G.; Koo, B.B.; Sharon, D.; Zak, R.; Chervin, R.D. Quality Measures for the Care of Adult Patients with Restless Legs Syndrome. J. Clin. Sleep Med. 2015, 11, 293–310. [Google Scholar] [CrossRef] [Scilit]
- American Psychiatric Association. DSM-V Diagnostic Criteria for ADHD. In Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-V); American Psychiatric Association: Washington, DC, USA, 2013. [Google Scholar]
- American Psychiatric Association. DSM-III Diagnostic Criteria for ADHD. In Diagnostic and Statistical Manual of Mental Disorders, Third Edition (DSM-III); American Psychiatric Association: Washington, DC, USA, 1980. [Google Scholar]
- American Psychiatric Association. DSM-III-R Diagnostic Criteria for ADHD. In Diagnostic and Statistical Manual of Mental Disorders, Third Edition-Revised (DSM-III-R); American Psychiatric Association: Washington, DC, USA, 1987. [Google Scholar]
- Ipsiroglu, O.S.; Hung, Y.-H.A.; Chan, F.; Ross, M.L.; Veer, D.; Soo, S.; Ho, G.; Berger, M.; McAllister, G.; Garn, H.; et al. “Diagnosis by Behavioral Observation” Home Videosomnography—A Rigorous Ethnographic Approach to Sleep of Children with Neurodevelopmental Conditions. Front. Psychiatry 2015, 6, 39. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).