


Abstract
Coenzyme Q10 (CoQ10) is an essential lipid-soluble molecule that plays a central role in mitochondrial energy production as a mobile electron carrier. In addition to its bioenergetic function, CoQ10 participates in antioxidant defense, redox homeostasis, lipid and nucleotide metabolism, and mitochondrial quality control. Primary CoQ10 deficiencies are rare inherited mitochondrial disorders caused by pathogenic variants in nuclear genes involved in CoQ10 biosynthesis. These defects lead to reduced CoQ10 levels and impaired mitochondrial functions. Clinically, primary CoQ10 deficiencies display remarkable phenotypic heterogeneity, ranging from isolated organ involvement, notably renal or cerebellar disease, to severe multisystemic disorders affecting the nervous system, skeletal muscle, heart, and other organs. Disease onset spans from the antenatal period to adulthood, and clinical severity varies widely, even among patients carrying variants in the same gene. This diversity cannot be fully explained by defective ATP production alone. Growing evidence indicates that disruption of non-bioenergetic functions of CoQ10, including oxidative stress regulation and CoQ-dependent metabolic pathways, contributes significantly to disease pathophysiology and tissue vulnerability. In this review, we summarize current knowledge on CoQ10 biology, biosynthesis, and the clinical spectrum of primary CoQ10 deficiencies, and we discuss emerging mechanisms linking CoQ10 depletion to mitochondrial dysfunctions and human diseases.
1. Introduction
CoQ10, also known as ubiquinone/ubiquinol, is a ubiquitous and essential lipid-soluble molecule that plays a central role in cellular metabolism. Best known for its function as a mobile electron carrier within the mitochondrial respiratory chain (MRC), CoQ10 is indispensable for oxidative phosphorylation and ATP production. Beyond its bioenergetic role, CoQ10 participates in a wide range of cellular processes, including antioxidant defense, regulation of redox homeostasis, lipid metabolism, and the activity of several mitochondrial and extra-mitochondrial enzymes. Given its multifaceted functions and ubiquitous distribution, it is not surprising that disturbances in CoQ10 homeostasis have profound consequences for cellular functions and physiology.
Primary CoQ10 deficiency is a rare group of inherited mitochondrial disorders caused by pathogenic variants in nuclear genes encoding proteins involved in CoQ10 biosynthesis. To date, mutations in 11 genes of this pathway have been identified in humans, leading to reduced CoQ10 levels in tissues and impaired mitochondrial functions. Clinically, primary CoQ10 deficiency is remarkable for its extreme phenotypic heterogeneity. Patients may present with isolated organ involvement, notably the kidney or the cerebellum, or with severe, multisystemic disease affecting the central and peripheral nervous systems, skeletal muscle, heart, and other organs. Age at onset ranges from the antenatal or neonatal period to adulthood, and disease severity varies from rapidly fatal forms to slowly progressive or relatively stable phenotypes.
This clinical variability contrasts with the shared biochemical defect underlying these disorders and raises fundamental questions regarding disease mechanisms. While impaired mitochondrial ATP production is a key consequence of CoQ10 deficiency, it alone cannot fully explain the tissue specificity and phenotypic diversity observed in affected individuals. Increasing evidence suggests that disruption of non-bioenergetic functions of CoQ10, including its roles in redox signaling, lipid and nucleotide metabolism, mitochondrial quality control, and oxidative stress regulation, also contributes substantially to disease pathophysiology. Moreover, differences in residual CoQ10 levels, tissue-specific metabolic demands, and the stability of the CoQ biosynthetic complex likely modulate disease expression.
In this review, we provide an updated and comprehensive overview of mitochondrial dysfunctions associated with primary CoQ10 deficiencies in humans. We first summarize the biochemical properties, cellular localization, and biosynthesis of CoQ10, with particular emphasis on the organization of the CoQ biosynthetic machinery. We then review the clinical spectrum of primary CoQ10 deficiencies, highlighting genotype–phenotype correlations and organ-specific manifestations. Finally, we discuss current pathophysiological hypotheses linking CoQ10 deficiency to mitochondrial and cellular dysfunctions, with the aim of clarifying the mechanisms underlying tissue vulnerability and phenotypic variability in these disorders.
2. About Coenzyme Q10
2.1. Structure
CoQ10 was discovered in 1955 when Festenstein and colleagues isolated and described a “substance SA” from lipid fractions of various animal tissues (rat, pig, horse) [1]. This compound was characterized as relatively non-polar, possibly a hydrocarbon, steroid, or fat-soluble vitamin. Infrared spectral analysis suggested the presence of a chromophore with conjugated double bonds linked to one or two ketone groups, alongside one or more isopropyl side chains. Two years later, Crane et al. extracted a “quinone compound Q-275” (absorbing at 275 nm in ethanol) from beef heart mitochondria and demonstrated its role as a coenzyme in the mitochondrial respiratory chain through reversible redox cycling (Figure 1) [2]. They further identified this compound and four homologues in yeasts and bacteria, collectively termed coenzyme Q or ubiquinones [3].
Figure 1.
Redox states of CoQ. Ubiquinone (CoQ) represents the fully oxidized form, Ubiquinol (CoQH2) the fully reduced form, and semiquinone (CoQH°−) the intermediate radical form. Depending on the species, the side chains contain between 6 and 10 isoprene units.
The molecular structure of CoQ was definitively characterized in 1958 by Wolf and colleagues [4]. Ubiquinones are amphipathic organic molecules composed of a polar headgroup and a hydrophobic isoprenoid side chain. The general structure features a 2-methyl-5,6-dimethoxy-1,4-benzoquinone ring substituted at position 3 by an isoprenoid chain, the length of which varies between species (Figure 1). This side chain typically contains 6 to 10 isoprene units, a feature that underlies the nomenclature CoQn, where n denotes the number of isoprenoid repeats. In humans, CoQ10 is the predominant active form. By contrast, rodents and Caenorhabditis elegans primarily produce CoQ9 [5], Enterobacteria synthesize CoQ8 [6], and Saccharomyces cerevisiae produces CoQ6 [7]. The benzoquinone ring constitutes the redox-active center of CoQ, capable of existing in three principal oxidation states: fully oxidized ubiquinone (CoQ), partially reduced semiquinone radical (CoQH°−), and fully reduced ubiquinol (CoQH2) bearing two hydroxyl groups (Figure 1). This reversible redox cycling, involving one- or two-electron transfers without structural alteration of the molecule, underpins CoQ’s roles as a coenzyme, mobile electron carrier in the MRC, and antioxidant [8].
2.2. Localization
The total pool of CoQ10 in humans is estimated to range between 0.5 and 1.5 g, distributed predominantly between a large tissue reservoir and a smaller circulating blood pool. CoQ is ubiquitous and is present in virtually all tissues and cells. In humans, the highest concentrations are found in organs with high energy demands, such as the heart, liver, skeletal muscles, neurons and kidneys [5]. The heart, in particular, is exceptionally rich in CoQ10, where it plays a vital role in ATP (adenosine triphosphate) production necessary for myocardial contraction through oxidative phosphorylation. CoQ10 levels also vary considerably among cellular compartments, with the highest concentrations localized in the inner mitochondrial membrane, the site of the electron transport chain (ETC). It is also found in lysosomes, the Golgi apparatus, and the endoplasmic reticulum, where it acts as an antioxidant and an enzymatic cofactor, beyond bioenergetics [9]. In the bloodstream, CoQ10 circulates mainly bound to lipoproteins, with approximately 76% found in the plasma fraction and 24% within blood cells. Within plasma from fasting subjects, about 58% of CoQ10 associates with low-density lipoproteins (LDLs), 26% with high-density lipoproteins (HDLs), and 16% with other lipoprotein particles [10].
Within tissues and cells, CoQ10 is associated with plasma membranes, where it acts as a potent antioxidant, protecting lipids and proteins from oxidative damage, which is especially important in tissues exposed to high metabolic rates and reactive oxygen species (ROS, see Section 5.2.3). However, its precise intramembrane localization is not fully elucidated and seems to vary depending on its redox state. Due to its amphipathic nature, CoQ10 likely adopts a configuration analogous to phospholipids, with the polar benzoquinone headgroup oriented toward the membrane surface and the hydrophobic isoprenoid tail embedded within the membrane core [11,12]. Molecular dynamics simulations have shown that ubiquinol tends to localize near the membrane surface, stabilized by hydrogen bonding with phosphoryl groups of glycerophospholipids, whereas the ubiquinone resides more centrally within the lipid bilayer [13]. CoQ10 exhibits rapid lateral and transbilayer mobility within membranes, allowing it to efficiently shuttle electrons between enzymatic complexes of the respiratory chain, necessary for ATP synthesis [14].
It is also important to note that CoQ10 levels are dynamic and influenced by several factors. Aging is associated with a gradual decline in CoQ10 tissue concentrations, potentially contributing to reduced mitochondrial efficiency and increased oxidative stress [15]. Dietary intake, CoQ10 supplementation, and pathological states such as mitochondrial diseases, cardiovascular disorders, and neurodegenerative conditions can significantly affect CoQ10 levels, highlighting its clinical relevance [16].
2.3. Pharmacokinetics
Although most CoQ10 in the body is synthesized endogenously, a small amount is obtained from the diet. Typical dietary intake is low, around 3–5 mg per day, mainly from meat, poultry, fatty fish, and some vegetables and fruits [17]. Dietary CoQ10 can contribute up to 25% of the plasma CoQ10 pool [18]. CoQ10 has poor intestinal absorption due to its large molecular weight and hydrophobic nature, with bioavailability estimated at only 2–3%. Absorption is enhanced when CoQ10 is ingested with lipids, following a process similar to fat-soluble vitamins. In the small intestine, bile and pancreatic secretions emulsify CoQ10 into micelles, which are passively absorbed by enterocytes. Inside these cells, CoQ10 is reduced to ubiquinol and incorporated into chylomicrons that enter the lymphatic system and subsequently the bloodstream. Chylomicrons are metabolized by lipoprotein lipase, and CoQ10 is transferred to LDL and very-low-density lipoprotein (VLDL) particles for systemic distribution [19]. Peak plasma concentrations are typically reached 6 to 8 h post-ingestion, with a secondary peak around 24 h due to enterohepatic recycling [20]. However, CoQ10 plasma levels increase nonlinearly with dosage, and prolonged supplementation (2–4 weeks) leads to steady-state plasma concentrations without tissue accumulation [21]. CoQ10 exhibits a plasma half-life of approximately 33 h in humans [22], and elimination occurs mainly via the biliary-fecal route (90–95%) either unchanged or as glucuronide conjugates, while a smaller fraction (5–10%) is excreted renally as phosphorylated metabolites [23].
The circulating plasma pool contributes minimally to the tissue CoQ10 pool under normal physiological conditions. Tissue uptake of exogenous CoQ10 is limited, with significant distribution mainly observed in the liver, spleen, and circulating white blood cells, while energy-demanding tissues such as the heart, brain, and skeletal muscles show poor absorption unless high doses are administered [24,25]. This explains the challenges in achieving adequate tissue levels through oral supplementation. Endogenous synthesis remains the primary source of CoQ10 in tissues, and exogenous supplementation does not downregulate this production. However, in specific pathological conditions such as primary CoQ10 deficiency (due to biosynthetic gene mutations) or increased demand (due to imbalanced redox status), oral supplementation (especially with the more bioavailable reduced form, ubiquinol) can partially restore tissue levels and improve clinical outcomes [26].
3. Biosynthesis of Coenzyme Q10
In mammalian cells, tissue CoQ10 is mainly provided by the biosynthetic pathway. CoQ10 biosynthesis is a multi-step and evolutionarily conserved process involving biochemical reactions that take place in the cytosol and the mitochondrial matrix, although evidence suggests that limited synthesis may also take place in other subcellular compartments [27]. In humans, CoQ10 biosynthesis involves at least ten dedicated enzymes, many of which (COQ3, COQ4, COQ5, COQ6, COQ7, COQ8, COQ9) are assembled into a large multiprotein structure known as complex Q, or the Q synthome (see Section 3.5) [28]. This assembly exemplifies a metabolon: a dynamic and transient complex that enables sequential enzymatic reactions through substrate channeling, thereby improving metabolic efficiency and minimizing the release of potentially harmful intermediates [29]. Those enzymes, which are encoded by nuclear genes, contain a mitochondrial targeting sequence that enables their importation into the mitochondria via translocases of the outer and the inner membranes [30].
This biosynthetic pathway can be broadly divided into four stages: (1) synthesis of the aromatic head group, (2) production of the isoprenoid tail, (3) attachment of the head group to the tail, and (4) a series of modifications to the ring structure (Figure 2) [31]. Much of our understanding of this pathway derives from studies in model organisms such as Escherichia coli and Saccharomyces cerevisiae, using CoQ-deficient mutants [32,33]. Although the enzymatic functions and characteristics of human proteins implicated in CoQ10 biosynthesis are poorly understood, their functions have been indirectly verified by the restoration of CoQ production after expressing the human genes in their corresponding yeast coq null mutants and by studying patients’ fibroblasts with pathogenic variants in COQ genes. In yeast, most of the CoQ biosynthetic proteins are referred to as “CoqX”, derived from the corresponding coqX genes, whereas in humans, the nomenclature follows “COQX” for proteins and COQX for genes. Complete disruption of CoQ biosynthesis is embryonically lethal in most animal models, underlining its vital role in cellular metabolism. Despite significant advances, many aspects of CoQ10 biosynthesis, transport, and regulation remain incompletely understood, posing challenges for the effective treatment of primary CoQ10 deficiencies in humans.
Figure 2.
Coenzyme Q10 biosynthetic pathway in humans. The (?) indicates steps that are catalyzed by unknown enzyme(s) or unknown synthetic intermediates, thus resulting in an uncertainty in the order of reactions. Intermediates in the pathway include 4-HPP (4-hydroxyphenylpyruvate), 4-HMA (4-hydroxymandelate), 4-HBF (4-hydroxybenzoylformate), 4-HBz (4-hydroxybenzaldehyde), 4-HB (4-hydroxybenzoate), DMAP (dimethylallylpyrophosphate), IPP (isopentenyl pyrophosphate), GPP (geranylpyrophosphate), FPP (farnesylpyrophosphate), PPHB (3-polyprenyl-4-hydroxy-benzoate), PBQ (3-polyprenyl-1,4-benzohydroquinone), PBHQ (3-polyprenyl-5-hydroxy-1,4-benzohydroquinone), PPDHB (3-polyprenyl-4,5-dyhydroxybenzoate), PPVA (3-polyprenylvanillic acid), PPMP (2-polyprenyl-6-methoxyphenol), DDMQ (Demethoxy-demethylCoQ10, 3-polyprenyl-5-methoxy-1,4-benzohydroquinone), DMQ (DemethoxyCoQ10, 2-methyl-3-polyprenyl-5-methoxy-1,4-benzohydroquinone), DMeQ (DemethylCoQ10, 2-methyl-3-polyprenyl-5-methoxy-6-hydroxy-1,4-benzohydroquinone). Enzymes include TAT (tyrosine aminotransferase), AADAT (alpha-aminoadipate aminotransferase), HPDL (hydroxyphenylpyruvate dioxygenase-like protein), LDHD (lactate dehydrogenase D), D2HGDH (D-2-hydroxyglutarate dehydrogenase), ALDH3A1 (aldehyde dehydrogenase 3 Family Member 1).
3.1. Head Group Production
The biosynthesis of CoQ10 universally relies on the conserved head group precursor 4-hydroxybenzoate (4-HB), which is derived from tyrosine in eukaryotic cells. In humans, the presence of phenylalanine hydroxylase (PAH), which converts phenylalanine into tyrosine, enables the use of both amino acids as potential precursors for 4-HB production [34]. While the overall pathway from tyrosine to 4-HB is conserved, several steps remain incompletely understood.
In human cells, tyrosine aminotransferase (TAT) and alpha-aminoadipate aminotransferase (AADAT) are considered plausible candidates for catalyzing the initial transamination of tyrosine to 4-hydroxyphenylpyruvate (4-HPP). Recent metabolic tracing experiments using isotopically labeled oxygen identified 4-hydroxymandelate (4-HMA) as a novel intermediate, formed from 4-HPP via the hydroxyphenylpyruvate dioxygenase-like protein (HPDL). The conversion of 4-HMA to 4-HBz is proposed to proceed through 4-hydroxybenzoylformate (4-HBF), potentially catalyzed by lactate dehydrogenase D (LDHD) or D-2-hydroxyglutarate dehydrogenase (D2HGDH) [35]. The final oxidation step, from 4-HBz to 4-HB, may be mediated by aldehyde dehydrogenase 3 Family Member A1 (ALDH3A1), which has been shown to catalyze this reaction in vitro. However, its physiological role in CoQ10 biosynthesis in mammalian cells has yet to be firmly established [36].
Beyond 4-HB, several natural aromatic compounds can serve as alternative precursors for CoQ biosynthesis, such as resveratrol, p-coumaric acid and kaempferol. These dietary polyphenols are thought to be metabolized into 4-HB, thereby offering an alternative source of the aromatic ring in conditions of impaired endogenous 4-HB synthesis [37,38].
3.2. Isoprenoid Tail Production
The mevalonate pathway comprises a series of enzymatic reactions that convert acetyl-CoA into farnesyl pyrophosphate (FPP) [39]. The long isoprenoid tail of CoQ10 originates from polyprenyl pyrophosphate (PPP), which results from the condensation of isopentenyl pyrophosphate (IPP) with FPP [40]. This reaction is catalyzed by a heterotetramer composed of the protein subunits PDSS1 and PDSS2 (decaprenyl-diphosphate synthase subunits 1 and 2) [41]. The mechanisms by which both 4-HB and isoprenoid precursors are transported from the cytosol into the mitochondrial matrix remain unknown.
3.3. Attachment of the Isoprenoid Tail to the Head Group Precursor
The subsequent step in CoQ10 biosynthesis is the conjugation of the decaprenylpyrophosphate chain to 4-HB, resulting in the formation of 3-polyprenyl-4-hydroxybenzoate (PPHB), the first prenylated intermediate in the pathway. This reaction is catalyzed by the parahydroxybenzoate-polyprenyltransferase COQ2, an integral protein of the inner mitochondrial membrane (IMM) whose active site is oriented toward the mitochondrial matrix [42,43,44]. The availability of endogenous 4-HB directly influences the rate of this reaction, making it a key rate-limiting step in CoQ production [45]. COQ2 exhibits broad substrate specificity and can prenylate alternative exogenous aromatic substrates such as 2,4-dihydroxybenzoic acid (2,4-diHB), 3,4-dihydroxybenzoic acid (3,4-diHB), and vanillic acid. These hydroxylated or methoxylated 4-HB analogs may bypass specific enzymatic blocks within the CoQ biosynthetic pathway [46].
3.4. Head Group Modifications
The final phase of CoQ10 biosynthesis entails a sequence of modifications of the PPHB head, including decarboxylation, hydroxylation at three positions, and three methylation reactions, that are mediated by COQ proteins. In both bacteria and yeast, the methyl and hydroxyl groups added during these modifications are derived from S-adenosyl methionine (SAM) and molecular oxygen (O2), respectively, a mechanism that is also presumed to operate in mammals [47,48].
The proposed sequence of enzymatic modifications is inferred from the identification of CoQ intermediates in bacterial and yeast mutants and generally aligns with the chemical principles of electrophilic aromatic substitution. However, the precise order in which these modifications occur remains under debate. Classical models based on yeast data suggest that the first modification is a C5 hydroxylation catalyzed by COQ6, followed by a methylation step mediated by COQ3, and subsequently the decarboxylation and hydroxylation at C1 (Figure 2—path 2) [33,49]. Yet, this sequence may be more flexible than previously thought: in both yeast and human cells deficient in COQ6, 3-polyprenyl-1,4-benzohydroquinone (PBQ) accumulates, indicating that C1 decarboxylation and hydroxylation can, in some contexts, occur prior to C5 modifications (Figure 2—path 1). This flexibility was further supported by recent findings implicating COQ4 in the decarboxylation/hydroxylation step [50].
COQ4, originally thought to act only as a structural chaperone within the CoQ biosynthetic complex, has been shown to have a direct enzymatic role in CoQ10 synthesis [51,52]. Studies in HEK293 cells demonstrate that COQ4 catalyzes the oxidative decarboxylation of prenylated CoQ10 precursors: the loss of COQ4 blocks CoQ10 production and causes strong accumulation of PPHB, indicating that COQ4 converts PPHB to PBQ in a single decarboxylation step. The preferential accumulation of PPHB in COQ4-deficient cells, together with the PBQ accumulation observed in COQ6-deficient cells, positions COQ4 early in the sequence of head-group modifications (Figure 2—Path 1), preceding COQ6-mediated hydroxylation, although alternative pathways consistent with yeast models (Figure 2—Path 2) remain possible [50]. Additional evidence shows that COQ4 can process prenylated substrates with a C5 methoxy group and that COQ6 may have both C5 and C1 hydroxylation activity (Figure 2—Path 3) [28,53]. Overall, the data suggest that COQ4 has a core catalytic function and that the eukaryotic CoQ pathway may exhibit flexibility in the ordering of enzymatic steps.
The penultimate step in the CoQ biosynthetic pathway is the hydroxylation at the C6 position, catalyzed by the COQ7 enzyme [54,55]. In human fibroblasts with COQ7-associated CoQ10 deficiencies, accumulation of demethoxyCoQ10 (DMQ) was observed, and treatment with 2,4-dihydroxybenzoate (2,4-diHB, a 4-HB analog already hydroxylated at C6) improved CoQ10 levels. The efficacy of this treatment depends on the specific COQ7 mutations present in patients. The success of such bypass therapy likely requires a stable presence of other COQ proteins and their ability to assemble into the Q complex [56,57].
The hydroxyl groups introduced at positions C5 and C6 are subsequently methylated by the COQ3 enzyme [58,59]. To date, no mutations in the human COQ3 gene have been identified as a cause of primary CoQ10 deficiency. Methylation at the C2 position is catalyzed by the COQ5 enzyme, whose activity depends on the structural integrity and stability of the CoQ synthome [60].
3.5. The Complex Q
Building on findings in yeast, research suggests that human cells also utilize a “complex Q” for CoQ10 biosynthesis. This multi-protein assembly consists of enzymes, chaperone proteins, CoQ10 itself, and its biosynthetic intermediates. While the core complex includes COQ3 through COQ9, proteins such as COQ1, COQ2, and COQ10 operate independently [61]. In a study using human 143B cells, transient knockdown of PDSS1, PDSS2, and several COQ genes led to altered expression levels of other COQ proteins, with both decreases and compensatory increases observed. Notably, PDSS1, PDSS2, and COQ3 appear essential for maintaining the stability of the overall complex. Interestingly, COQ5 protein levels were reduced following PDSS1, PDSS2, and COQ9 knockdown. These results also revealed a potential functional interplay between COQ3 and COQ6, as the loss of one protein destabilized the other. Moreover, the mechanisms underlying COQ5 and COQ6 upregulation after COQ4 knockdown, as well as increased COQ4 levels following COQ7 knockdown, remain unclear. These effects may reflect compensatory regulatory mechanisms aimed at preserving CoQ10 biosynthesis under conditions of partial deficiency. The observation that COQ5 expression is particularly sensitive to moderate and transient COQ9 loss underscores the underappreciated role of COQ9 in stabilizing the complex [62]. This is further supported by other studies reporting reduced COQ5 levels in fibroblasts from patients with COQ9 deficiency [63]. Altogether, the organization, stability, and protein–protein interactions within complex Q appear to be highly dynamic and context-dependent, likely varying across different cellular models and physiological and pathological conditions.
3.6. Other Proteins Implicated in Coenzyme Q10 Biosynthesis
Other proteins were suggested to participate in the CoQ10 biosynthetic pathway, including ADCK (aarF domain-containing kinase) proteins, which share structural features with kinase-like proteins. Although COQ8A and COQ8B (formerly known as ADCK3 and ADCK4) are required for CoQ10 production, their precise roles remain unresolved. In humans, COQ8A has no kinase activity in vitro but instead exhibits ATPase activity when bound to cardiolipins, suggesting that ATP hydrolysis helps to recruit CoQ10 precursors and assemble the CoQ10 biosynthetic machinery, functioning in a chaperone-like manner [64]. Likewise, COQ8B shows ATPase activity and was hypothesized to act as a COQ3 kinase [28]. Both COQ8A and COQ8B genes have been associated with primary CoQ10 deficiency with completely different phenotypes. COQ8A pathogenic variations cause cerebellar ataxia and encephalopathy, whereas COQ8B mutations mainly cause steroid-resistant nephrotic syndrome (see Section 4). ADCK2 haploinsufficiency was shown to cause an adult-onset myopathy with CoQ10 deficiency and defects in mitochondrial fatty acid β-oxidation, revealing another clinical phenotype for ADCK pathogenic variations [65].
In humans, COQ9 has been shown to physically interact with COQ7 and is essential for the hydroxylation step catalyzed by this protein [66]. COQ9 contains a hydrophobic lipid-binding pocket that can accommodate various lipids, including CoQ intermediates, suggesting a role in the transport or presentation of these intermediates to other COQ enzymes. Cryo-EM studies have revealed that COQ9 and COQ7 interact through a well-defined interface stabilized by hydrogen bonds, hydrophobic contacts, and an intermolecular salt bridge [67]. Functional interdependence between the two proteins is further supported by the accumulation of DMQ (the substrate of COQ7) in fibroblasts deficient for either COQ7 or COQ9. Both deficiencies can be partially rescued by treatment with 2,4-diHB, a hydroxylated analog of 4-HB that bypasses the COQ7-catalyzed hydroxylation step [57,68].
While in yeast the ortholog of the two isoforms COQ10A and COQ10B was suggested to act as a chaperone-like protein by allowing binding of CoQ intermediates, no disease-causing mutations have been reported for those genes in humans [69].
3.7. Extra-Mitochondrial Coenzyme Q10 Biosynthesis
Cell fractionation studies have demonstrated that while CoQ10 is primarily concentrated within the mitochondria, it is also distributed, albeit to a lesser extent, to extra-mitochondrial compartments, notably the plasma membrane, where it functions as an antioxidant [70,71]. This extra-mitochondrial presence has been hypothesized to result from an alternative biosynthetic pathway. For instance, Mugoni et al. identified the ubiad1 gene in zebrafish, showing that its deletion causes oxidative stress-induced cardiovascular lesions. In humans, the Golgi-localized prenyltransferase UBIAD1 is thought to facilitate this alternative synthesis [72]. However, since this pathway remains unconfirmed in other experimental models, its contribution may be uniquely restricted to cardiac tissue.
3.8. Intracellular Coenzyme Q10 Transport
Following its synthesis within the mitochondria, CoQ10 is redistributed to various intracellular compartments. A recent study by Deshwal et al. identified STARD7, a protein localized in both the mitochondrial intermembrane space and the cytosol, as a key factor of this transport process [73]. The mitochondrial form of STARD7 is indispensable for CoQ10 biosynthesis and respiratory cell growth. In contrast, its cytosolic counterpart facilitates the trafficking of CoQ10 to the plasma membrane, where it serves as a robust antioxidant, protecting membrane phospholipids from peroxidation and inhibiting ferroptotic cell death (see Section Antioxidant Systems). However, we cannot rule out the possibility that the extra-mitochondrial localization of CoQ10 results from lipid exchange between the mitochondria and other intracellular compartments. Extensive evidence has demonstrated that mitochondria and the endoplasmic reticulum (ER) maintain close contact through structures known as mitochondria-associated membranes (MAMs), which facilitate lipid exchange between these organelles [74]. Lipids within the ER can then be transported to the plasma membrane (PM) either via the secretory pathway or directly through ER-PM contact sites. Current data remain insufficient to determine if CoQ10 levels across these compartments exist in dynamic equilibrium or if independent regulatory mechanisms allow for the selective control of CoQ10 in one compartment without influencing others.
4. Clinical Features and Phenotypes Associated with Primary Coenzyme Q10 Deficiency in Humans
Although dietary intake contributes some CoQ10, tissue concentrations depend predominantly on the endogenous biosynthetic pathway described in Section 3 of this review. This is illustrated by the fact that recessive pathogenic variants in 11 of the 14 genes involved in this pathway can lead to primary CoQ10 deficiency. In this section, we focus exclusively on the symptoms and organs affected by these primary deficiencies in humans to help clinicians and geneticists consider primary CoQ10 deficiency when relevant signs are present. Because mitochondria are found in most human cell types and CoQ10 participates in multiple cellular functions, it is not surprising that primary CoQ10 deficiencies cause damage in numerous organs, particularly those with high energy demands, as depicted in Figure 3. As we will show, symptoms may manifest during the prenatal period, during infancy, during childhood, or in adulthood.
Figure 3.
The organs affected and main genes involved in primary CoQ10 deficiencies according to different stages of life. The different COQ genes involved and the organs affected are shown. Primary CoQ10 deficiency occurs either as a multisystemic disease or by affecting a single organ; in this latter case, genes are indicated in bold. IUGR: intra-uterine growth retardation. Created in BioRender. https://BioRender.com/, accessed on 20 December 2025.
4.1. Antenatal and Neonatal Presentations
Antenatal manifestations generally include intrauterine growth retardation (IUGR), oligohydramnios, cardiac abnormalities (such as cardiomegaly), cerebral anomalies (lissencephaly, thin corpus callosum, cerebellar hypoplasia), renal cysts, intestinal abnormalities (echogenic bowel with dilatations), reduced fetal movements, limb abnormalities, arthrogryposis, and cystic hygroma. Bi-allelic pathogenic variants have been reported in COQ2 [75], COQ4 [76], COQ7 [77,78], and COQ9 [79]. Brain autopsies have shown neuronal loss with astrocytosis in the brainstem, basal ganglia, and thalami, features suggestive of Leigh disease, as well as damage to the cortex, cerebellum, and white matter [76,77] and lesions indicative of multifocal global ischemic events [79]. Antenatal presentations are typically associated with severe disease, not necessarily due to more deleterious variant types (e.g., nonsense versus missense), and often result in death during the neonatal period or early childhood.
Patients presenting symptoms in the neonatal period have been described with mutations in COQ2 [44,80,81], COQ4 [82,83,84], COQ6 [85], COQ7 [77,86], COQ9 [87,88], and HPDL [89,90,91,92,93]. These cases typically involve multisystemic disease with neurological features (hypotonia, epilepsy, dystonia, opisthotonos, encephalopathy), cardiac involvement (cardiomyopathy, cardiomegaly, bradycardia, tachycardia, cardiogenic shock), respiratory complications (apnea, respiratory distress), muscular contractures, and less frequently renal abnormalities (proteinuria, tubulopathy, edema). Feeding difficulties, microcephaly, and developmental delays are also common. These presentations are generally extremely severe, with reported deaths occurring from a few hours after birth to 3.5 years of age, although some children were still alive at the time of publication [85,92].
4.2. Involvement of the Central Nervous System
Damage to the central nervous system (CNS) is likely the most frequently reported manifestation in patients carrying pathogenic variants in HPDL, PDSS1, PDSS2, COQ2, COQ4, COQ5, COQ6, COQ7, COQ8A, and COQ9. The associated neurological symptoms vary widely and may occur in combination with one another or alongside involvement of other organ systems. Epilepsy, described under terms such as infantile spasms, jerks, myoclonus, or epileptic encephalopathy, is commonly observed in patients with mutations in COQ2 [80,81,94,95], COQ4 [76,82,83,84,96], COQ8A [97,98], COQ9 [87,88,99,100], and HPDL [89,90,91,92,93], and is reported less frequently in COQ5 [101], COQ6 [102], COQ7 [103], and PDSS1 [104]. Reported prevalence estimates include 32% for COQ8A, around 50% for HPDL [92], and more than 70% for COQ4, though these values vary depending on the gene and cohort size [84,97].
Epilepsy may appear as early as the neonatal period, as reported for COQ2 [80,81], COQ4 [76,83], COQ9 [100], and HPDL [93], or may manifest later, as observed in individuals with COQ6 mutations [102]. In some cases, seizures are resistant to antiepileptic drugs, such as in COQ9-related disease [87] and PDSS2 deficiency [105], and can contribute to early mortality [100]. Epilepsy is generally not an initial symptom in infantile or adult-onset forms associated with COQ4 [96], COQ7 [86], or COQ8A mutations [97], nor in cases where the CNS is not primarily affected, as shown for COQ2 [94].
Ataxia (also referred to as imbalance disorder) is the initial and predominant feature in patients with COQ8A mutations. It is present in all individuals with infantile-onset disease [97], with a moderate overall progression that leads to the need for walking aids or a wheelchair in approximately half of the patients. Additional neurological symptoms may accompany the ataxia. Cerebral imaging consistently shows cerebellar atrophy involving both the vermis and the hemispheres in nearly all affected individuals [97]. Ataxia has also been reported, though less frequently, in patients with other primary CoQ10 biosynthesis defects. This includes individuals with COQ2 mutations presenting with infantile-onset disease associated with tremor and cerebellar atrophy [95] or with adult-onset disease [106]; a young patient with a COQ4 mutation who developed a spastic-ataxic gait as the initial symptom [96]; three sisters carrying a COQ5 tandem duplication involving the last four exons, who exhibited non-progressive cerebellar ataxia with dysarthria, nystagmus, and mild cerebellar atrophy [101]; a patient with an infantile-onset COQ7 mutation [107]; and individuals with HPDL mutations, although in the latter ataxia is not a major feature [89].
Spastic paraplegia is a frequent manifestation in patients with HPDL mutations. It is typically accompanied by additional neurological features, including intellectual impairment, motor developmental delay, central respiratory failure, and epilepsy, and may present with neonatal, infantile, or juvenile onset. The clinical course is characterized by progressively worsening spasticity and evidence of brain or cortical atrophy, consistent with a neurodegenerative process [89,90,91,92]. Spasticity has been reported much less frequently in association with other primary CoQ10 biosynthesis defects. Cases include patients with COQ2 pathogenic variants, in whom neurological signs such as jerks and brisk reflexes occurred alongside hypertrophic cardiomyopathy [81]; individuals with COQ4 mutations presenting with infantile-onset disease where spastic paraplegia is the predominant feature [83,96,108]; patients with COQ7 mutations showing infantile [95] or juvenile onset accompanied by epilepsy and distal amyotrophy [103,109]; and two adult siblings with COQ9 mutations who developed pure spastic paraplegia with childhood onset [68].
Cervical or focal dystonia affecting the upper limbs has been reported in patients with COQ8A mutations. In the cohort described by Traschütz et al., dystonia occurred in approximately 30% of patients with ataxia and often represented the initial presenting symptom [97]. Dystonia has also been described in individuals with COQ2 mutations, including a pair of dizygotic twins in whom it was accompanied by additional neurological impairments [80].
Other neurological symptoms have been sporadically reported. Stroke-like episodes were described in a young patient with a COQ2 mutation who initially presented with proteinuria [94], and in 4 out of 59 patients with COQ8A mutations [97]. Motor delay, motor deterioration, or absence of psychomotor development has been frequently observed in individuals with HPDL mutations [89,91,92,93], in COQ8A deficiency [97], in patients with COQ7 mutations [77,78,95,103,107], with COQ5 mutations [101], and in one patient with a COQ4 mutation [83].
Cognitive symptoms, including cognitive deterioration, mild to moderate cognitive disability or delay, intellectual disability, cognitive impairment, mental retardation, language delay, tremor, migraine, and behavioral disorders, have also been reported in patients with COQ4 [83,96], COQ5 [101], COQ8A (affecting 25–50% of patients) [97], HPDL (affecting 50–65% of patients) [89,91,92], and PDSS1 mutations [110,111].
Encephalopathy has been described in both infantile- and adult-onset COQ2 deficiency [44], in neonatal-onset COQ4 deficiency [83], and in 35–65% of patients with HPDL mutations [89,90], with a predominance (up to 85%) in individuals presenting with a severe phenotype [89]. It has also been reported in a patient carrying both a deletion and a mutation in PDSS2 [112].
Brain imaging reveals a wide range of lesions and abnormalities affecting the CNS. Cerebellar atrophy or hypoplasia, often involving the vermis, is among the most frequently reported findings in patients with pathogenic variants in the CoQ10 biosynthetic pathway. It affects approximately 95% of individuals with COQ8A mutations [97], around 15% of those with HPDL mutations [89,91], and has also been described in patients with mutations in COQ2 [75,94,95,106], COQ4 [76,83,84], COQ5 [101], and COQ9 [87,99]. White matter abnormalities, described as white matter changes, leukomalacia, leukoencephalopathy, or delayed myelination, are also common across several genetic forms of primary CoQ10 deficiency. These findings have been reported in individuals with mutations in COQ2 [95], COQ4 [84], COQ6 [102], COQ7 [77,86,103,107], HPDL [89], PDSS1 [104,113,114]. In the cohort described by Wiessner et al., white matter abnormalities were present in approximately 40% of HPDL-mutated patients, predominantly among those with a severe phenotype [89]. Symmetrical lesions in the basal ganglia and brainstem, reminiscent of Leigh syndrome, have been reported in patients with mutations in COQ4 [84], COQ7 [77], COQ9 [88], HPDL [89,115], PDSS1 [104], and PDSS2 [105]. Additional reported abnormalities include agenesis or hypoplasia of the corpus callosum [78,89,99], brainstem hypoplasia [78,96,99], cortical abnormalities, and generalized cerebral atrophy [81,84,86,87,89,90,91,94].
4.3. Involvement of the Peripheral Nervous System
Peripheral polyneuropathy, or distal hereditary motor neuropathy, is frequently reported in patients with COQ7 mutations [57,77,109,116,117,118]. Symptoms typically begin in childhood or adolescence and manifest as difficulties with running or walking, muscle weakness, and frequent falls. These symptoms gradually worsen and progress toward amyotrophy. Foot deformities, such as pes cavus or hammer toes, are also observed. Deep tendon reflexes may be normal, reduced, or brisk. Nerve conduction studies usually show an axonal motor neuropathy, although sensory involvement has also been reported. Peripheral neuropathy has additionally been described in two siblings with a PDSS1 mutation [110] and in a patient with a COQ2 mutation [95]. In one case, sural nerve biopsy revealed mild mixed axonal and demyelinating degeneration [109].
4.4. Involvement of the Muscular System
Skeletal muscle involvement has been well documented in patients carrying mutations in COQ2 [80,81,94,95], COQ4 [76,82,83,84], COQ5 [119], COQ6 [102], COQ7 [78,86,107], COQ8A [97], COQ9 [87,88,99,100], HPDL [89], PDSS1 [113], and PDSS2 [105]. Muscle involvement is rarely isolated and more commonly occurs alongside neurological or cardiac manifestations. Although early signs may appear during the antenatal period, typically as decreased fetal movements [76], most symptoms have neonatal or infantile onset. In the neonatal period, hypotonia, when present, is frequently accompanied by respiratory difficulties or distress and feeding problems [76,80,81,83,84,86,87,88,113]. Additional findings reported at birth include arthrogryposis [83,100], reduced spontaneous movement, and progressive decline in muscle tone [82]. When muscle symptoms emerge during childhood or adolescence, they primarily present as muscle weakness [95,111,119], exercise intolerance [97], walking difficulties [107], or difficulty maintaining head control [105], with gradual progression over time. In late-onset cases, muscle involvement is rarely the initial symptom but may affect approximately 25% of individuals with COQ8A mutations [97]. Other less frequently reported manifestations include oculomotor abnormalities [89], dysphagia and ptosis [97], and elevated creatine phosphokinase (CPK) levels [95]. Histological and histo-enzymatic analyses have been performed in a limited number of studies using muscle biopsy samples and have shown heterogeneous findings. Reported abnormalities include lipid accumulation [78,120] and subsarcolemmal mitochondrial proliferation, identified using Gomori’s trichrome staining or succinate dehydrogenase labeling [78,94,105,120,121]. Cytochrome c oxidase–negative fibers have also been described [120,121]. In some cases, muscle biopsy results are normal [117] or reveal only subtle abnormalities, such as an increased proportion of type 2C fibers [101]. Electron microscopy may show mitochondria that are abnormal in size or structure or otherwise damaged [78,117].
4.5. Involvement of the Heart
Cardiac involvement has been reported in patients carrying mutations in COQ2, COQ4, COQ6, COQ7, COQ9, PDSS1, and PDSS2, with presentations occurring in the antenatal period [83,84,88], the neonatal period [76,77,78,79,81,82,83,84,86,100], or during infancy [99,107,111,112,113]. Cardiac manifestations are rarely isolated and instead typically occur within a multisystemic presentation that also involves the renal, neurological, muscular, ocular, and auditory systems. Echocardiographic findings include hypertrophic or dilated cardiomyopathy, systolic or diastolic dysfunction with reduced ejection fraction involving the right ventricle, the left ventricle, or both, left ventricular non-compaction cardiomyopathy, atrial or ventricular septal defects, tricuspid or mitral regurgitation, mitral dysplasia, and pulmonary hypertension. Cardiac rhythm disturbances, such as arrhythmia, bradycardia, and ventricular tachycardia, have also been reported. These abnormalities commonly progress to heart failure, cardiogenic shock, and early death in most cases. Autopsy findings, reported in a limited number of patients, include biventricular hypertrophy, left ventricular hypoplasia with septal hypertrophy, cardiomyocyte hypertrophy and vacuolization, necrosis, endocardial fibrosis, edema, and lymphocytic infiltration [76,82,83].
4.6. Involvement of the Kidneys
Interestingly, it is possible to distinguish isolated renal forms, seen almost exclusively in patients with COQ8B mutations [122,123,124,125,126], from multisystemic forms in which renal involvement co-occurs with abnormalities in other organs such as the brain, eyes, skeletal muscle, and heart. These multisystemic presentations are associated with mutations in COQ2 [44,81,94,127], COQ6 [85,102,128,129,130], COQ7 [77,78,86], COQ9 [79,87,99,100], PDSS1 [104,114], and PDSS2 [105,112], and frequently lead to a fatal outcome. Renal disease typically manifests as proteinuria of varying severity, sometimes associated with edema and arterial hypertension, tubulopathy, acute kidney injury, or a steroid-resistant nephrotic syndrome, which often progresses to end-stage renal failure and anuria. Although renal symptoms most commonly appear during childhood, adolescent- and adult-onset forms have also been reported. Earlier presentations include antenatal manifestations such as oligohydramnios and hyperechoic kidneys [78,79] and prenatal findings such as tubular dysfunction, hyperechoic kidneys, and renal cysts [87,100]. A large Chinese study of 120 children with proteinuria or focal segmental glomerulosclerosis associated with steroid-resistant nephrotic syndrome identified COQ8B as the most frequently mutated gene [124]. When kidney biopsy is performed, histological analysis almost invariably reveals focal segmental glomerulosclerosis [81,112,122,125,126,128,131], characterized by mesangial hypercellularity, expansion of the mesangial matrix, sclerosis of glomerular capillaries, thickening of the glomerular basement membrane, foot-process effacement, enlarged podocytes, and an increased number of swollen or structurally abnormal mitochondria.
4.7. Involvement of the Eyes
Eye involvement, although less frequently reported than other organ manifestations, has been described in patients with mutations in COQ2 [80,94,119,127,132], COQ4 [108,119], COQ5 [119], COQ6 [129], COQ8A [97], PDSS1 [110,111,113,119], and PDSS2 [112]. A wide spectrum of ophthalmological findings has been reported, including vision loss, night blindness, photophobia, optic disc pallor, central scotoma, abnormal color vision, cataract, retinal dystrophy, macular edema, pigmentary retinopathy, and optic atrophy. Among these, pigmentary retinopathy and optic atrophy are the most frequently observed and may occur together, as reported by Traschütz et al. in a patient with a COQ8A mutation [97]. Isolated ocular involvement is rare. One exception is the case described by Kurata et al., in which a 20-year-old patient presented with night blindness, photophobia, and progressive vision loss associated with pigmentary retinopathy, without another organ involvement [132]. In most other reports, eye abnormalities occur in the context of multisystem disease and are associated with neurological, renal, muscular, or cardiac manifestations, or with hearing loss. In such multisystemic cases, ocular symptoms are generally not the initial presentation and tend to develop during childhood, adolescence, or even adulthood.
4.8. Involvement of the Auditory System
Bilateral sensorineural hearing loss has been reported in patients with mutations in COQ6 [129,130], COQ7 [77,78,86,95], PDSS1 [110,111,113], and PDSS2 [112]. Although hearing loss is occasionally isolated [130], it is more commonly observed as part of a multisystemic presentation, associated with neurological, muscular, renal, cardiac, ophthalmological, or gastrointestinal involvement. Deafness may be detected at birth through neonatal hearing screening [112], during the neonatal period [77,78,86], or appear later in childhood [95,110,111,113,129,130]. Sensorineural impairment is documented using audiometry or brainstem auditory evoked response testing.
4.9. Involvement of Other Organs
Damage to other organs has been reported, although only in very isolated cases. Pulmonary arterial hypertension has been observed in patients with mutations in PDSS1 [110,113] and PDSS2 [112]. Regarding the digestive system, Pettenuzzo et al. described meconium peritonitis in a two-day-old newborn carrying mutations in the COQ7 gene, associated with intestinal atresia that required multiple surgical interventions. Hepatic involvement has also been reported [78]. Wang et al. described hepatomegaly as part of a multisystem presentation (cardiac, renal, and pulmonary involvement) in a 3-month-old infant with COQ6 mutations [102]. Additionally, Mollet et al. reported liver failure in a 2-day-old girl with PDSS1 mutations, associated with neurological and renal abnormalities [110].
5. Roles of Coenzyme Q10 and Pathophysiological Hypotheses
At first glance, it may seem surprising that the same biochemical abnormality, namely CoQ10 deficiency caused by pathogenic variants in genes involved in its biosynthesis, can result in a wide spectrum of clinical phenotypes, ranging from isolated organ involvement to multisystemic disease, despite the ubiquitous nature of CoQ10. In primary CoQ10 deficiency, a reduction in total cellular CoQ10 levels has been consistently demonstrated in patient-derived tissues, particularly muscle and fibroblasts, suggesting a global depletion affecting both mitochondrial and non-mitochondrial compartments; however, this has never been clearly demonstrated.
This observation raises the possibility that multiple cellular processes dependent on CoQ10 are disrupted and contribute to disease pathophysiology. However, an important question remains: why are certain tissues preferentially affected, whereas others appear relatively spared? One intuitive hypothesis is that tissues with high energy demand may be more vulnerable to CoQ10 depletion, given the central role of this cofactor in mitochondrial ATP production. Supporting this notion, pathogenic variants in COQ8B predominantly lead to renal manifestations such as proteinuria, steroid-resistant nephrotic syndrome, or focal segmental glomerulosclerosis (see Section 4.6). Nevertheless, this explanation alone is insufficient, as other highly energy-dependent organs, such as the heart, skeletal muscle, or central nervous system, are preserved in these isolated forms, even though they are commonly involved in mitochondrial disorders. This discrepancy suggests that the pathophysiological mechanisms underlying primary CoQ10 deficiencies cannot be fully explained by impaired energy production alone.
The following section details the various physiological functions of CoQ10 within both mitochondrial and non-mitochondrial compartments. Building on these pathways, we will categorize the putative pathophysiological mechanisms responsible for the tissue and organ alterations described in Section 4 in patients harboring deleterious variants in COQ genes. We have ranked these processes as major, moderate, or minor based on the volume of existing literature, the consistency of results across experimental models, and the successful reversal of anomalies through pharmacological or genetic interventions. Mechanisms are classified as “major” when they have been consistently observed across multiple experimental models, are supported by a substantial body of literature, and demonstrate reversibility upon the normalization of CoQ10 levels. Mechanisms were categorized as moderate if they had been demonstrated in only a single experimental model or if existing data remained contradictory. Finally, we defined mechanisms as minor when they were purely hypothetical or lacked support from robust experimental data in the literature.
Various experimental models have been utilized to characterize CoQ10 biosynthesis and the mechanisms underlying cellular alterations in primary deficiencies. While these models offer distinct advantages, they also present limitations regarding their translatability to human physiology and pathology. For instance, the yeast model is frequently used to identify biosynthetic enzymes due to the ease of gene inactivation and its clear phenotype. However, while most yeast Coq genes have mammalian homologs, some possess multiple counterparts, and the overall homology between yeast and human orthologs is relatively low. Conversely, patient-derived dermal fibroblasts are widely used to validate the pathogenicity of COQ variants and study cellular abnormalities. These provide a human tissue model that is easily cultured and obtained through minimally invasive skin biopsies. Furthermore, these models are highly amenable to the employed techniques, allowing for the modulation of protein activity or expression through both pharmacological and genetic approaches. While human tissues such as muscle, liver, and heart are used for diagnostic purposes, their utility in characterizing pathophysiological mechanisms is limited by small sample sizes and the requirement for immediate processing. To address these limitations, preclinical models, including knockout (KO) or knock-in (KI) mice, have been developed to simulate human mutations. These models offer the advantage of studying organ and cellular alterations within a complex, physiological environment that closely mirrors human pathology. By integrating these findings with clinical and biochemical data, it is possible to establish a framework for understanding the tissue specificity and phenotypic variability observed in primary CoQ10 deficiencies. Furthermore, induced pluripotent stem cells (iPSCs) represent a novel approach to studying mutations in a tissue-specific context. Derived from patient fibroblasts, iPSCs can be differentiated into neurons, cardiomyocytes, or myocytes and cultured in 2D or 3D systems to create complex organoid models. While this approach has been applied to mitochondrial diseases and specifically to COQ2 and COQ4 variants, some findings remain surprising [133]. For instance, Romero-Moya et al. observed cellular alterations in iPSC-derived neurons carrying a heterozygous COQ4 variant, which is unexpected given the autosomal recessive nature of CoQ10 deficiencies [134]. Similarly, Nakamoto et al. studied the impact of two COQ2 variants in iPSC-derived neurons, though one is classified as a common polymorphism in the Japanese population [135].
5.1. Involvement of Coenzyme Q10 in Energy Metabolism
5.1.1. Mitochondrial Respiration and ATP Production
Since its discovery in the 1960s, the best-characterized role of CoQ10 is its function as a mobile electron carrier within the MRC. CoQ10 shuttles electrons from complexes I and II, as well as from several other dehydrogenases, to complex III, thereby sustaining the proton motive force that drives ATP synthesis [136,137]. Complex I (NADH-CoQ oxidoreductase) is a flavoprotein that transfers two electrons from NADH to CoQ10 via flavin mononucleotide (FMN) and eight Fe–S clusters. This transfer is coupled to the translocation of protons across the IMM [138]. Complex II (succinate-CoQ oxidoreductase) participates in both the MRC and the Krebs cycle, where it catalyzes the oxidation of succinate to fumarate with the concomitant reduction of FAD to FADH2. The two electrons derived from this reaction are transferred to CoQ10, reducing it to CoQH2 via three Fe–S clusters. Unlike complex I, this process does not contribute directly to proton pumping [139]. Once reduced, CoQH2 diffuses freely within the lipid bilayer of the IMM to deliver its electrons to complex III (CoQ–cytochrome c oxidoreductase). Electron transfer through complex III follows a circular pathway known as the Q cycle, which ensures the reoxidation of CoQH2, the reduction in two cytochrome c molecules, and the net pumping of protons [140]. Complex IV (cytochrome c oxidase) catalyzes the terminal step of the MRC by transferring electrons from reduced cytochrome c to molecular oxygen, while concomitantly pumping additional protons across the IMM [141]. The resulting proton gradient powers complex V (ATP synthase), ensuring efficient ATP production (Figure 4) [142].
Figure 4.
Coenzyme Q10 in the mitochondrial respiratory chain. IMM: inner mitochondrial membrane; IMS: intermembrane space; I: complex I; II: complex II; III: complex III; Q: Ubiquinone; QH2: Ubiquinol. SQ: semi-quinone. Created in BioRender. https://BioRender.com/, accessed on 20 December 2025.
The precise organization underlying mitochondrial electron transfer has long been the subject of debate, gradually evolving from the classical “random collision model” toward more structured conceptual frameworks [143]. According to the random collision model, the entire CoQ10 pool functions as a homogeneous reservoir accessible to all mitochondrial respiratory complexes and dehydrogenases. This view is supported by evidence that the majority of mitochondrial CoQ10 (approximately 70–90%) is not tightly bound to membrane proteins. It posits that respiratory chain complexes, dehydrogenases, and CoQ10 diffuse freely and independently within the IMM, with electron transfer occurring through random collisions between CoQ10 and its enzymatic partners [144]. The subsequent discovery of respiratory supercomplexes (SCs) introduced a more organized paradigm, wherein individual complexes I, III, and IV can assemble into stable supramolecular entities, most prominently CI/CIII2, CIII2/CIV, and CI/CIII2/CIV [145]. In this model, each SC is proposed to sequester a specific subpopulation of CoQ10 molecules, thereby enhancing electron transfer efficiency through substrate channeling [146]. Indeed, isolated SCs have been shown to be catalytically competent, capable of sustaining electron transfer without requiring exogenous CoQ10. These findings gave rise to the contemporary “plasticity model,” which reconciles both perspectives by proposing a dynamic equilibrium between freely diffusing complexes and diverse SC assemblies [147]. Within this framework, the CoQ10 pool is no longer viewed as entirely homogeneous but rather as dynamically partitioned into at least two functionally distinct fractions: (1) a subset of CoQ10 molecules associated with or sequestered by SCs, facilitating efficient, channeled electron transfer from NADH (the CoQNADH pool); and (2) a freely diffusing pool within the IMM that serves complex II and other dehydrogenases (the CoQFADH2 pool) [143]. Despite this apparent compartmentalization, kinetic data indicate that these CoQ10 subpools remain interconnected, such that the overall CoQ10 population operates as a single functional continuum in which all dehydrogenases ultimately compete for the same redox mediator.
Given the role of CoQ10 in mitochondrial bioenergetics, a primary deficit of this cofactor produces a reduction in complexes I+III, II+III, and GPD (glycerol-3-phosphate dehydrogenase)+III activities, a decrease in oxygen consumption rate and variable impairments in ATP synthesis. Studies on tissues derived from patients carrying mutations in genes involved in CoQ10 biosynthesis (including COQ2, COQ4, COQ7, COQ8B, HPDL and PDSS1) have demonstrated variable impact on mitochondrial respiration and/or on ATP synthesis [57,80,83,90,101,107,122,148]; these differences in results are likely related to the varying impact of pathogenic variants, the level of CoQ10 depletion, and the tissues analyzed. On muscle biopsy, Jakobs and collaborators also demonstrated a decrease in pyruvate oxidation and in ATP production associated with CoQ10 depletion [80]. In fibroblasts, a correlation between CoQ10 level and the reduction in maximal mitochondrial respiration is observed among different patients [83]. Some studies observed that the decrease in CoQ10 fibroblast content only reduced the maximal respiration rate [83,107,122], while others showed that the basal respiration was also altered in lymphocytes [90] and in fibroblasts [57]; such differences can be explained by different techniques or experimental conditions used for these measurements. Alongside the decrease in CoQ10, a reduction in ATP synthesis is observed by some in muscle [80] and fibroblasts [57] but not by others [107]. These discrepancies can be explained by the ATP assay, which is not a robust technique, and by the use of different substrates to fuel the respiratory chain. It is also noteworthy that supplementation of patient’s fibroblasts with CoQ10 rescues mitochondrial respiration [57,68,107].
Experiments performed on patient-derived fibroblasts cultured in galactose medium, which forces reliance on oxidative phosphorylation for energy production, have shown a strong dependence of ATP levels on the severity of CoQ10 deficiency. While a major deficiency in CoQ10 (≤40% of normal values) leads to a significant decrease in ATP levels, this is not the case with moderate deficiency (up to 50% of normal values) [149]. This energy deficit could contribute, at least in part, to the multisystemic clinical manifestations characteristic of primary CoQ10 deficiencies.
In conclusion, based on the current evidence and numerous studies demonstrating a correlation between CoQ10 depletion and impaired mitochondrial respiration and ATP synthesis, disruption of energy metabolism appears to be a major contributor to the pathogenesis of primary CoQ10 deficiency, particularly in high-energy-demand organs such as the heart, liver, skeletal muscles, kidneys, and neurons. Overall, the severity of CoQ10 deficiency generally correlates with the degree of impairment in the respiratory chain and ATP production. In vitro supplementation of patient-derived cells with CoQ10 can often restore mitochondrial respiration and ATP synthesis.
5.1.2. Coenzyme Q10 in Mitochondrial β-Oxidation
Electron-transferring flavoprotein dehydrogenase (ETFDH), also known as ETF-QO (electron transfer flavoprotein–ubiquinone oxidoreductase), is a mitochondrial inner membrane enzyme that plays a pivotal role in funneling electrons into the CoQ10 pool (Figure 5). ETFDH receives electrons from electron-transfer flavoprotein (ETF), which in turn is reduced by at least nine distinct acyl-CoA dehydrogenases involved in mitochondrial β-oxidation of fatty acids and in the catabolism of branched-chain amino acids [150]. Pathogenic variants in ETFDH cause multiple acyl-CoA dehydrogenase deficiency (MADD), a disorder characterized by impaired fatty acid oxidation and prominent muscle manifestations, including fatigue, exercise intolerance, and myopathy without [151] or with CoQ10 deficiency [152].
Figure 5.
Major enzymatic reactions using coenzyme Q10 as an electron acceptor outside the mitochondrial respiratory chain. GPD2: Mitochondrial glycerol-3-phosphate dehydrogenase; ETFDH: Electron-transferring flavoprotein dehydrogenase (ETF–ubiquinone oxidoreductase); ETF: Electron-transferring flavoprotein; ACADS: Short-chain acyl-CoA dehydrogenase; DHODH: Dihydroorotate dehydrogenase; SQOR: Sulfide:quinone oxidoreductase; CHDH: Choline dehydrogenase; PRODH: Proline dehydrogenase. Created in BioRender. https://BioRender.com/, accessed on 20 December 2025.
Whether primary CoQ10 deficiencies directly impair the ETFDH pathway remains unclear. However, accumulating evidence suggests that CoQ10 deficiency is associated with a broader disruption of lipid metabolism. Patients carrying pathogenic variants in genes involved in CoQ10 biosynthesis, such as COQ2, PDSS2, and ADCK2, frequently display metabolic signatures reminiscent of MADD, including muscular impairment (see Section 4.4). In individuals with ADCK2 haploinsufficiency, as well as in the Adck2+/− mouse model, moderately increased plasma levels of saturated short- and medium-chain acylcarnitines have been reported, consistent with impaired fatty acid oxidation and reduced electron transfer to the CoQ10 pool. Adck2+/− mice also show significantly increased urinary excretion of adipic and ethylmalonic acids, together with reduced circulating β-hydroxybutyrate and free carnitine levels [65]. Alterations in urinary organic acids are commonly observed in mitochondrial diseases, including increased excretion of tricarboxylic acid (TCA) cycle intermediates, ethylmalonic acid, and 3-methylglutaconic acid [153]. A patient with a fatal neonatal COQ2 mutation displayed mild dicarboxylic aciduria and slightly elevated alanine [154]. Similarly, three individuals from unrelated families with pathogenic COQ4 variants showed elevated 2-hydroxyglutarate levels, supporting ETFDH deficiency [83]. A major consequence of these alterations is lipid accumulation in tissues with high energetic demand, particularly skeletal muscle. Lipid storage disorder has been documented in muscle biopsies from patients with neonatal-onset COQ2 deficiency and from individuals with ADCK2 haploinsufficiency, both displaying mitochondrial myopathy with prominent lipid droplets [155]. Lipid accumulation was also observed in patients with pathogenic variations in COQ7 [78] and COQ8A (see Section 4.4) [120]. These findings are recapitulated in the Adck2+/− mouse model, which exhibits marked lipid accumulation in skeletal muscle as well as hepatic steatosis, reflecting a systemic defect in lipid metabolism driven by insufficient CoQ10 availability [156]. In addition, Pdss2kd/kd mice show increased levels of short-chain acylcarnitines (C4–C6), which have been attributed to decreased activity of sulfide:quinone oxidoreductase (SQOR), another CoQ-dependent enzyme, although ETFDH function was not directly assessed in this model [157].
In conclusion, although primary CoQ10 deficiency may be associated with impaired fatty acid oxidation and lipid accumulation, particularly in muscle and liver, the evidence supporting a direct effect on the ETFDH pathway is limited and inconsistent. Thus, disruption of β-oxidation should be considered a minor contributor to the pathogenesis of primary CoQ10 deficiency. In addition, whether the observed lipid alterations primarily result from defective electron transfer through ETFDH, from secondary dysfunction of other CoQ-dependent enzymes such as SQOR, or from a combination of both mechanisms remains to be determined.
5.1.3. Glycerol-3-Phosphate Shuttle
Mitochondrial glycerol-3-phosphate dehydrogenase 2 (GPD2) is a flavin-dependent dehydrogenase that catalyzes the oxidation of glycerol-3-phosphate (G3P) to dihydroxyacetone phosphate (DHAP) while transferring electrons from FADH2 to CoQ10 (Figure 5). This enzyme functions together with the cytosolic glycerol-3-phosphate dehydrogenase 1 (GPD1) to form the glycerol-3-phosphate shuttle, which regenerates cytosolic NAD+ from glycolysis-derived NADH and delivers electrons to the electron transport chain via CoQ10. GPD2 is anchored to the inner mitochondrial membrane on the intermembrane-space side [158]. As a key component of intermediary metabolism, GPD2 links glycolysis and oxidative phosphorylation and triglyceride synthesis through the glycerol-3-phosphate shuttle. The activity of GPD2 associated with the respiratory chain is known to vary considerably between tissues. It is highly active in the brain, fibroblasts, and lymphocytes. In contrast, negligible glycerol-3-phosphate dehydrogenase activity has been observed in the heart, kidneys, and liver [158].
GPD2 has been little explored in the context of primary CoQ10 deficiency. Rötig et al. demonstrated that CoQ10 deficiency directly impairs GPD2 activity when functionally coupled to complex III, assessed as glycerol-3-phosphate:cytochrome c reductase (GPD2+III). In lymphocytes from two affected siblings, quinone-dependent activities (CII+III and GPD2+III) were at the lower interval of the control range, while activity ratios (CIV/CII+III and CIV/GPD2+III), which are suggested to be much more sensitive indicators of respiratory chain imbalance, were markedly increased. Addition of decylubiquinone or analogs (idebenone, CoQ4, CoQ6) led to substantial increases in GPD2+III activity in patient-derived fibroblasts. This quinone responsiveness decreased as mitochondrial CoQ10 levels were restored during treatment and increased again upon clinical deterioration. However, whether the CoQ10 deficiency is primary or secondary is not indicated by the authors [26].
In conclusion, while CoQ10 deficiency may impair GPD2 activity under specific experimental conditions, the available evidence is extremely limited, and the physiological relevance remains unclear. Therefore, alterations of the glycerol-3-phosphate shuttle should be considered a minor contributor to the pathogenesis of primary CoQ10 deficiencies.
5.2. Involvement of Coenzyme Q10 in Non-Bioenergetic Processes
5.2.1. Implication of Coenzyme Q10 in Anabolic Pathways
Lipids Metabolism
Given the role of CoQ10 in the degradation of fatty acids and the involvement of the mevalonate pathway in its synthesis, research has been conducted to better understand the impact of a CoQ10 deficiency on lipid metabolism. Lipidomic studies using induced-pluripotent stem cells (iPSC)-derived neurons harboring mutations in CoQ10 biosynthesis genes (COQ2 and PDSS2) demonstrate that severe CoQ10 depletion (≈12–14% residual levels) leads to a marked repression of mevalonate pathway activity, characterized by a reduced expression of key enzymes such as HMG-CoA reductase (HMGCR) and farnesyl diphosphate synthase (FPPS), along with a decreased availability of lipid precursors including farnesyl- and geranylgeranyl-pyrophosphate [159]. Conversely, moderate CoQ10 deficiency (≈80% residual), induced pharmacologically, does not affect enzyme expression of the mevalonate pathway but instead perturbs cholesterol trafficking and storage. These findings indicate that the consequences of CoQ10 loss on lipid metabolism depend on the severity of the deficit.
Neurons with CoQ10 depletion exhibit a reduction in cholesteryl esters, diacylglycerol, and glycosphingolipids; an increase in phosphatidylglycerol; and dysregulation of lipid efflux mechanisms [159]. Given that lipids play structural and functional roles, particularly in neurons, it is not surprising that the central and peripheral nervous systems are affected.
In conclusion, although CoQ10 deficiency was shown to affect lipid metabolism, the current available evidence indicates that these alterations represent a minor contributor to the overall pathogenesis of primary CoQ10 deficiencies. However, given the critical role of lipids in neuronal structure and function, disturbances in lipid homeostasis may play a more pronounced role in neurological manifestations, potentially contributing to the phenotypic variability observed among patients.
Pyrimidine Metabolism
Dihydroorotate dehydrogenase (DHODH) is a mitochondrial flavoprotein that catalyzes the oxidation of dihydroorotate to orotate (Figure 5), the fourth and rate-limiting step of the de novo pyrimidine biosynthesis pathway leading to the formation of uridine monophosphate (UMP), a precursor of RNA and DNA nucleotides (UTP, CTP, and dTMP) [160]. Located on the outer leaflet of the IMM, DHODH transfers electrons from dihydroorotate via the cofactor FMNH2 to CoQ, reducing it to CoQH2, which then feeds electrons into complex III of the MRC. This reaction directly couples pyrimidine synthesis to mitochondrial respiration [161].
Loss of respiratory chain function (as in ρ0 cells that are depleted in mitochondrial DNA (mtDNA) or in complex III-deficient cells) abolishes DHODH activity, leading to uridine auxotrophy since exogenous uridine bypasses the DHODH-dependent step in pyrimidine synthesis [162]. Similarly, CoQ10 deficiency could impair DHODH function by restricting the pool of oxidized CoQ10 as an electron acceptor. In line with this idea, fibroblasts harboring COQ2 mutations with a profound CoQ10 depletion (<20% residual CoQ10 content) exhibit growth defects that are rescued by exogenous CoQ10 or uridine supplementation; the stronger rescue with uridine suggests that impaired nucleotide synthesis, rather than reduced ATP production, is the primary vulnerability in these cells [163]. In galactose medium, the proliferation of fibroblasts from patients with pathogenic COQ7 and COQ9 variations was reduced and partially restored by CoQ10 supplementation [57,68]. Montero et al. also reported a secondary CoQ10 deficiency in both muscle and fibroblasts of a patient with a mtDNA depletion syndrome, suggesting a link between CoQ10 deficiency and mtDNA replication [164].
However, severely CoQ10-deficient models such as Coq7-knockout or Pdss2/Coq7 double-knockout mouse embryonic fibroblasts grow normally without uridine supplementation, implying that even minimal residual mitochondrial respiration (possibly supported by trace CoQ10 present in standard culture medium) is sufficient to maintain DHODH activity [165]. Interestingly, while DHODH mutations cause Miller syndrome with characteristic craniofacial and limb malformations, such developmental defects are not observed in primary CoQ10 deficiency. This discrepancy indicates that reduced CoQ10 availability impairs DHODH function metabolically but does not recapitulate the profound enzyme inactivation caused by monogenic DHODH loss [166]. Further studies will be needed to determine the extent to which CoQ10 deficiency compromises DHODH activity and nucleotide synthesis in different pathological contexts.
In conclusion, CoQ10 deficiency can impair DHODH-dependent pyrimidine synthesis, as demonstrated by functional studies in patient-derived fibroblasts, where uridine supplementation rescues growth defects. This position DHODH dysfunction as a moderate contributor to the pathogenesis of primary CoQ10 deficiencies. However, results from mouse embryonic fibroblast models suggest that the impact of this mechanism likely depends on the severity of CoQ10 depletion and the cellular context, and it may be more pronounced in certain cell types, potentially contributing to the phenotypic variability among patients.
Proline Metabolism
Another entry point for electrons into the CoQ10 pool involves proline metabolism, mediated by proline dehydrogenase 1 and 2 (PRODH1/2) (Figure 5). PRODH1 catalyzes the oxidation of L-proline to 1-pyrroline-5-carboxylate (P5C), with electrons being transferred directly to CoQ10. P5C is subsequently converted into glutamate and then glutamine. PRODH1 plays important roles in energy metabolism, mitochondrial ROS production, and signaling pathways involved in apoptosis and stress responses [167,168]. PRODH2, although closely related to PRODH1, shows a strong preference for trans-4-hydroxy-L-proline as its substrate, a metabolite derived from extracellular matrix collagen turnover. PRODH2 converts hydroxyproline into 3-hydroxy-1-pyrroline-5-carboxylate, which is further metabolized to glyoxylate and pyruvate [169]. Mutations in PRODH1 cause type I hyperprolinemia, an autosomal recessive disorder with highly variable clinical presentation, ranging from asymptomatic individuals to severe neurological and psychiatric manifestations. Hyperprolinemia has not previously been reported in patients with CoQ10 deficiency. However, it should be noted that amino acid chromatography is not routinely performed in individuals with primary CoQ10 deficiency. Further studies will be needed to determine whether impaired CoQ10 availability affects proline and hydroxyproline metabolism [170]. Based on the limited evidence currently available, alterations in proline metabolism should be considered a minor contributor to the pathogenesis of primary CoQ10 deficiencies.
Choline Metabolism
Choline is an essential nutrient in mammals that serves both as a precursor for the synthesis of membrane phospholipids (via the CDP-choline pathway that produces phosphatidylcholine) and sphingomyelin and for the biosynthesis of the neurotransmitter acetylcholine. A portion of the cellular choline pool is also directed toward the mitochondrial oxidative pathway, where choline dehydrogenase (CHDH), an enzyme located in the IMM and dependent on the CoQ10 pool, catalyzes its oxidation to betaine aldehyde, which is subsequently oxidized to betaine by betaine aldehyde dehydrogenase (BADH) (Figure 5) [171]. Betaine then functions as a methyl-group donor in the remethylation of homocysteine to methionine by betaine-homocysteine methyltransferase (BHMT), thereby directly linking choline metabolism to the methionine cycle and to the production of SAM, the universal methyl donor. This pathway is tightly interconnected with the folate cycle, which provides an alternative route for homocysteine remethylation through 5-methyl-THF, and it extends to the transsulfuration pathway, responsible for the synthesis of cysteine, glutathione, and other sulfur-containing metabolites [172]. Thus, through their role in betaine synthesis, choline and the activity of CHDH are involved in redox balance and one-carbon metabolism, and to a lesser extent in membrane integrity and neurotransmission with its implication in phosphatidylcholine and acetylcholine production. At present, it is difficult to conclude that CHDH dysfunction plays a significant role in the pathophysiology of primary CoQ10 deficiencies. Indeed, no specific clinical abnormalities attributable to CoQ10 deficiency–related CHDH impairment have been demonstrated. Based on the available data, a defect in the remethylation pathway appears more plausible; however, this alteration does not seem to be part of the recognized clinical spectrum of primary CoQ10 deficiencies [173]. Finally, CHDH has also been described as a mitophagy sensor [174]. Currently, there is no evidence supporting a reduction in CHDH expression or activity in this context (i.e., CoQ10 deficiency), making it difficult to infer an impact on mitophagy. Moreover, its role in mitophagy is independent of its catalytic activity and, therefore, of CoQ10 availability. Nonetheless, based on the current available evidence, CHDH-related choline metabolism should be considered a minor contributor to the pathogenesis of primary CoQ10 deficiencies while remaining an interesting area for future investigation.
5.2.2. Implication of Coenzyme Q10 in Sulfide Metabolism
Another CoQ10-linked enzyme is the sulfide:quinone oxidoreductase (SQOR). Sulfide metabolism in mammalian cells involves two main routes: (1) the trans-sulfuration pathway, which produces hydrogen sulfide (H2S) from cysteine or homocysteine, and (2) the mitochondrial H2S oxidation pathway, which converts H2S into sulfate ions (SO42−). In mammals, the sulfide oxidation pathway takes place within mitochondria [175]. SQOR, a flavoprotein anchored to the IMM, catalyzes the first and key step of this pathway by coupling the oxidation of H2S to the reduction in CoQ10. During this process, a persulfide intermediate (E–SSH) is generated on a catalytic cysteine residue of SQOR. This persulfide sulfur is then transferred to glutathione (GSH), the main physiological sulfane sulfur acceptor, yielding glutathione persulfide (GSSH) [176]. GSSH serves as a mobile sulfur carrier that undergoes further oxidation by the iron-dependent persulfide dioxygenase ETHE1, generating sulfite (SO32−) and reforming GSH. Alternatively, GSSH can react with sulfite through the sulfurtransferase rhodanese (thiosulfate sulfurtransferase, TST) to produce thiosulfate (S2O32−), while sulfite can be oxidized to sulfate by sulfite oxidase located in the intermembrane space (IMS) [177]. The final products of this pathway, thiosulfate and sulfate, are excreted, completing the detoxification of H2S while contributing to mitochondrial energy metabolism.
In primary CoQ10 deficiencies, reduced levels of residual CoQ10 destabilize SQOR, leading to its degradation and a marked reduction in enzyme activity [178]. This dose-dependent relationship has been demonstrated both in mammalian models and in human cellular systems. In patient-derived skin fibroblasts carrying pathogenic mutations in various CoQ10 biosynthetic genes (including COQ2, COQ4, COQ8A, COQ9, and PDSS2), a progressive decline in CoQ10 content correlates directly with reduced SQOR protein stability and impaired SQOR-dependent respiratory activity. Fibroblasts with residual CoQ10 levels below ~30% of normal exhibit the most severe functional impairment, with a marked decrease in oxygen consumption in response to hydrogen sulfide and a pronounced loss of detectable SQOR protein (reduced to ~25–27% of control levels). Conversely, fibroblasts maintaining ~50% of physiological CoQ10 show only a partial reduction in sulfide oxidation capacity, indicating that SQOR function is preserved until CoQ10 becomes critically limiting as an electron acceptor [157].
A similar threshold effect has been observed in various mouse models of primary CoQ10 deficiency, including Coq9R239X, Coq9Q95X, and Pdss2kd/kd. In these animals, the extent of SQOR depletion closely mirrors the local residual CoQ9 content and the severity of manifestations in the affected tissue. For instance, in Pdss2kd/kd mice, the kidney, where CoQ9 levels drop to ~15%, displays a dramatic reduction in SQOR protein (to ~16% of control) and a near-complete collapse of its activity, while the brain, retaining ~30% of CoQ9, maintains SQOR levels comparable to wild-type. Similar results were reported for the two other mouse models; in Coq9R239X, the very low level of CoQ9 content in different tissues (cerebellum, kidney and muscle) is associated with reduced level of SQOR protein level and activity. In Coq9Q95X, where muscles display the most profound CoQ9 deficiency by 80% compared to kidney or cerebellum (only 50%), a low SQOR protein content and activity is observed only in muscles [179]. These findings collectively support the existence of a CoQ10 threshold, below which SQOR becomes unstable and rapidly degraded. Under these conditions, the oxidation of the mitochondrial H2S oxidation pathway is compromised, setting the stage for pathological sulfide accumulation.
Excess H2S resulting from this metabolic failure would contribute directly to the cellular dysfunction associated with CoQ10 deficiency. H2S specifically targets the cytochrome c oxidase (COX) by binding directly to the heme-containing catalytic center that maintains the complex IV in a constant reduced state and accelerates long-term degradation of COX subunits, leading to inhibition of mitochondrial respiration [180]. Elevated sulfide also inhibits short-chain acyl-CoA dehydrogenase (SCAD), leading to impaired β-oxidation of short-chain fatty acids and increased levels of C4–C6 acylcarnitines [178]. Additionally, redox stress induced by H2S and oxidized sulfur species depletes antioxidant defenses, particularly glutathione (GSH), through sulfide autoxidation, reduced availability of precursors such as glutamate, and decreased activities of glutathione peroxidase and glutathione reductase [179]. Excess sulfide also enhances protein S-sulfhydration, altering diverse cellular functions, and feeds back on the transsulfuration pathway (modulating H2S biosynthesis) with broader consequences for carbon metabolism, including folate cycling, serine biosynthesis, and nucleotide metabolism [181].
Rescue interventions confirm that defective sulfide oxidation is directly caused by CoQ depletion: CoQ10 supplementation restores SQOR levels and SQOR-dependent respiration both in vitro in mutant fibroblasts and in vivo in Coq9R239X mice [157,179].
In conclusion, impaired sulfide oxidation due to SQOR instability represents an important and well-supported pathogenic mechanism in primary CoQ10 deficiencies. Its contribution appears to be highly dependent on the severity of CoQ10 depletion, with a clear threshold below which SQOR becomes unstable and rapidly degraded. Beyond the direct loss of sulfide detoxification capacity, excess H2S exerts secondary deleterious effects on mitochondrial respiration through inhibition of complex IV, impairs short-chain fatty acid oxidation via SCAD inhibition, and compromises antioxidant defenses by disrupting glutathione homeostasis. Collectively, these findings position defective sulfide metabolism as a moderate but multifaceted contributor to disease pathogenesis, amplifying mitochondrial dysfunction, particularly in tissues with profound CoQ10 depletion.
5.2.3. Implication of Coenzyme Q10 in Oxidative Stress
Reactive Oxygen Species (ROS), Oxidative Stress and Cellular Toxicity
Oxidative stress arises from an imbalance between the production of ROS, derived from oxygen, and the antioxidant defense systems. In aerobic metabolism, the principal ROS include the superoxide anion (O2−), hydrogen peroxide (H2O2), and the hydroxyl radical (HO°) [182]. The two main sources of ROS are mitochondria, as the predominant site of production, and NADPH oxidase in macrophages, which generates those species involved in antimicrobial defense [183,184]. ROS are highly reactive compounds, which interact with multiple cellular components (lipids, proteins, and DNA) and promote their damage, and have substantial cytotoxic effects [185,186,187]. Among all molecular targets, polyunsaturated fatty acids (PUFAs) in mitochondrial and cellular membranes are especially sensitive to oxidation through non-enzymatic lipid peroxidation directly driven by ROS [188]. This process occurs in three main steps:
- Initiation: highly reactive hydroxyl radicals (HO°), often produced via iron-dependent Fenton chemistry from hydrogen peroxide, abstract a hydrogen atom from PUFA chains, generating a lipid radical (L°).
- Propagation: the lipid radical rapidly reacts with molecular oxygen to form a lipid peroxyl radical (LOO°), which then attacks nearby lipids, creating new radicals and sustaining an amplifying chain reaction that produces lipid hydroperoxides (LOOH).
- Termination: the chain reaction stops when two radicals combine to form non-radical products, or when antioxidants such as glutathione break the cycle. The end of this cascade produces reactive secondary aldehydes, notably malondialdehyde (MDA) and 4-hydroxy-2-nonenal (4-HNE), which impair membrane integrity and can form adducts with proteins, DNA, and phospholipids, amplifying oxidative damage [188].
Mitochondrial membranes are especially susceptible to lipid peroxidation because they are enriched in polyunsaturated phospholipids, particularly cardiolipins [189]. Oxidation of cardiolipin alters cristae architecture, destabilizes respiratory SCs, and impairs oxidative phosphorylation, which further increases electron leakage and ROS generation [190]. ROS production triggers a vicious cycle that reinforces and amplifies its own generation. Moreover, it is well established in Barth syndrome that cardiolipin abnormalities promote dysfunction of the mitochondrial respiratory chain [191].
Ferroptosis, first described by Dixon et al. as a regulated, non-apoptotic form of cell death driven by iron-dependent lipid peroxidation, is marked by condensed and shrunken mitochondria, displaying increased membrane density and loss of cristae, while the outer membrane remains intact. Its execution reflects a disequilibrium between pro-oxidant mechanisms responsible for the accumulation of lipid hydroperoxides and the antioxidant systems that normally prevent their lethal conversion into toxic breakdown products [192]. Lyamzaev and colleagues showed a direct relationship between the peroxidation of mitochondrial phospholipids and ferroptosis; mitochondria-targeted antioxidants are powerful inhibitors of this form of cell death [193].
Proteins are also susceptible to oxidative modification that perturbs their structure and function. A predominant mechanism is carbonylation, an irreversible ROS-driven introduction of aldehyde or ketone groups into protein backbones, marking damaged proteins for degradation and contributing to loss of proteostasis when excessively accumulated. Additional modifications on cysteine and tyrosine residues can impair enzyme activity, disrupt redox signaling, and alter protein–protein interactions, ultimately compromising essential metabolic and regulatory pathways [194]. It has been demonstrated in experimental models that mitochondrial proteins undergo oxidative alterations that impair complex I activity and respiration [195]. Finally, ROS can cause extensive damage to the genome, affecting both nuclear and mitochondrial DNA. Oxidative base lesions are particularly frequent, with guanine oxidation producing 8-oxo-7,8-dihydroguanine (8-oxo-dG), a mutagenic lesion capable of inducing G → T transversions if unrepaired. ROS can also break the sugar–phosphate backbone and generate an abasic site through cleavage of the N-glycosidic bond [196]. Mitochondrial DNA, lacking histone protection and located near ROS-producing sites, exhibits especially high vulnerability, leading to mutations, impaired oxidative phosphorylation, and mitochondrial dysfunction. Moreover, secondary aldehydes generated by lipid peroxidation, such as MDA and 4-HNE, can form bulky DNA adducts that hinder replication and repair [197].
How Do Mitochondria Generate ROS?
The mitochondrial respiratory chain contains several major sites of ROS production, with complex I (CI) being one of the most prominent. Two ROS-generating sub-sites have been identified within CI: the FMN site and the ubiquinone (CoQ) binding pocket. During the normal oxidation of NADH, electrons are transferred to CoQ; however, a fraction of these electrons may prematurely reduce molecular oxygen to superoxide. This process is greatly amplified when electron flow through CI is restricted or reversed. Under specific metabolic conditions, including a highly reduced ubiquinol (QH2) pool coupled to an elevated proton-motive force, electrons can flow backward from QH2 to the NAD+/NADH pool in the matrix. This phenomenon, known as reverse electron transport (RET), is widely recognized as a potent source of ROS formation, particularly superoxide and its dismutation product, hydrogen peroxide [198,199]. In the present context (i.e., CoQ10 deficiency), this mechanism does not appear to be a major contributor, as total CoQ10 levels are decreased and the ETC activity is reduced.
Additional ROS originate from other ETC complexes. At complex II (CII), the IIF site of succinate dehydrogenase generally produces minimal ROS under physiological activity, but its contribution markedly increases during dysfunction or when electron flow is restricted. At complex III (CIII), the Qo site within the Q-cycle can generate superoxide through the semiquinone intermediate formed during electron transfer (Figure 4). Notably, superoxide produced at complex III can be released into both the mitochondrial matrix and the IMS. Importantly, the resulting CoQH2/CoQ10 ratio emerging from these redox interactions functions as a central sensor of respiratory chain activity. This ratio influences mitochondrial SC organization and can promote RET at complex I under highly reduced conditions, thereby amplifying ROS production. Collectively, these mechanisms underscore that CoQ10 is not merely a passive electron carrier but a dynamic redox hub that integrates electron flux, structural organization of the respiratory chain, and mitochondrial ROS signaling [200].
Within the IMS, superoxide is rapidly converted into hydrogen peroxide by the Cu/Zn-dependent superoxide dismutase (SOD1), and this hydrogen peroxide can freely diffuse into the cytosol, extending its signaling or damaging effects beyond mitochondria. In the mitochondrial matrix, superoxide is detoxified by the Mn-dependent superoxide dismutase (SOD2 or Mn-SOD), which catalyzes its conversion into hydrogen peroxide, thereby preventing the accumulation of superoxide and limiting oxidative stress within the mitochondrial compartment. In contrast, complex IV (CIV) contributes only marginally to ROS formation due to its high catalytic efficiency in reducing oxygen through a tightly controlled four-electron transfer, minimizing unintended electron leakage [199]. Under normal physiological conditions, the respiratory chain’s ROS output is tightly controlled by antioxidant systems, most notably SODs, which convert superoxide into the more stable and membrane-permeant hydrogen peroxide at moderate levels; H2O2 functions as a signaling molecule [201]. When an imbalance occurs and ROS production exceeds the capacity of antioxidant defense systems, these reactive species begin to accumulate and interact with cellular constituents and organelles. Under mild oxidative stress, damaged molecules can be repaired or eliminated through quality-control mechanisms, preserving cellular integrity. However, when oxidative damage becomes excessive or irreversible, ROS compromise essential cellular functions and trigger regulated cell death pathways, including apoptosis, necrosis, pyroptosis, and ferroptosis [201].
Antioxidant Systems
Cells maintain redox homeostasis through a coordinated set of antioxidant systems that neutralize ROS and prevent oxidative damage. The first line of defense is provided by SODs, which convert superoxide anion into hydrogen peroxide. H2O2 generated by SODs is then detoxified by glutathione-dependent enzymes [202].
The glutathione (GSH and GSSG) system constitutes a central axis of cellular antioxidant defense. Reduced glutathione (GSH), abundant in the cytosol and mitochondria, directly scavenges ROS and participates as a cofactor for glutathione peroxidases (GPX). GPXs form a family of selenium-dependent antioxidant enzymes that reduce hydrogen peroxide and organic hydroperoxides using glutathione as an electron donor to water or non-toxic alcohols [203]. Several isoforms coexist in mammalian cells with distinct subcellular localizations and functions: GPX1 is widely expressed in the cytosol and mitochondria and primarily detoxifies hydrogen peroxide; GPX2 is enriched in the gastrointestinal epithelium; GPX3 is secreted into the extracellular space and contributes to plasma antioxidant defense; and GPX4 is unique in its ability to directly reduce phospholipid hydroperoxides within biological membranes [204]. Importantly, GPX4 is the only GPX isoform capable of preventing the accumulation of membrane lipid peroxides, making it the sole member of the family essential for the suppression of ferroptosis [205]. It is worthy to note that the efficient GPX4 translation requires the isopentenylation of the selenocysteine tRNA[Ser]Sec, coupling the mevalonate pathway to the antioxidant system [206]. Thus, alteration of the mevalonate pathway could also reduce the efficacy of GPX4 (see Section Lipids Metabolism).
The pool of GSH is maintained by glutathione reductase (GR), ensuring continuous regeneration from oxidized glutathione (GSSG). Complementing this system, glutathione-S-transferases (GSTs) catalyze the conjugation of GSH to electrophilic compounds, including toxic lipid peroxidation products, thus facilitating their detoxification and export [207]. Together, these antioxidant systems provide overlapping layers of protection: SODs prevent superoxide accumulation, GPXs eliminate peroxides, GSH provides reducing power, and GR and GST remove oxidized by-products. This multilayered defense not only prevents ROS-induced macromolecular damage but also preserves signaling processes that rely on controlled redox balance.
Its ability to transport electrons also makes CoQ10 a strong candidate in the defense against oxidative stress, as it is capable of capturing electrons. Beyond its well-established function within the mitochondrial electron transport chain, CoQ10 participates in multiple antioxidant systems designed to counteract ROS. A central component of these systems is the plasma membrane redox system (PMRS), which transfers reducing equivalents from intracellular donors, primarily NADH and NADPH, to extracellular acceptors. Through this process, the PMRS contributes to maintaining the NAD(P)H/NAD(P)+ redox balance, a major determinant of metabolic fluxes, redox signaling, and cellular stress responses. Preserving this redox ratio prevents excess electron accumulation, limiting their diversion toward oxygen and thereby avoiding ROS generation [208].
The PMRS comprises several membrane-associated enzymes and small antioxidant molecules, including extramitochondrial CoQ10, vitamins C and E. Crucially, three enzymes directly depend on CoQ10 as their redox partner: NADH–cytochrome b5 reductase (CYB5R), NAD(P)H:quinone oxidoreductase 1 (NQO1), and ferroptosis suppressor protein 1 (FSP1) [209,210,211]. These enzymes, located on the inner leaflet of the plasma membrane, extract electrons from cytosolic NAD(P)H and transfer them to CoQ10 embedded in the bilayer [212]. The resulting QH2 can then donate electrons either to the tocopherol radical, suppressing lipid peroxidation, or to the monodehydroascorbate radical (MDHA), regenerating ascorbate. Through this dual antioxidant recycling mechanism, CoQ10 provides an additional layer of protection against oxidative stress and ferroptosis (Figure 6) [213]. Although GPX4, FSP1, and DHODH all contribute to ferroptosis suppression through the maintenance of reduced ubiquinol, DHODH represents the principal enzymatic defense against ferroptosis within mitochondria [214,215,216], while GPX4 and FSP1 predominantly act in non-mitochondrial membranes [217]. Therefore, ferroptosis protection depends not only on antioxidant activity but also on the compartmentalized reduction of CoQ10 into CoQH2.
Figure 6.
Schematic representation of ferroptosis and the role of coenzyme Q10 in its regulation. In the upper part of the diagram, the cellular protective system against ferroptosis is illustrated, involving CoQ10 in synergy with vitamin E or tocopherol (radical and reduced) and vitamin C (MDHA: monodehydroascorbate and ascorbate). CoQ10 exerts its protective function at two levels. First, in its reduced form (CoQH2), it donates electrons to regenerate tocopherol radical (VIT Eox) into tocopherol reduced (VIT E) with ascorbate. Second, it directly neutralizes lipid peroxyl radicals (LOO•), a process dependent on its reduction by the FSP1 pathway, which utilizes NADH. Another major anti-ferroptotic defense mechanism is mediated by GPX4, which uses glutathione to reduce lipid hydroperoxides (LOOH) and prevent the accumulation of oxidative lipid damage. In the lower part of the diagram, an analogous mechanism is depicted within mitochondria, where DHODH and/or SQOR provide an additional layer of protection by reducing mitochondrial CoQ10, thereby limiting the initiation of ferroptosis in this compartment. Created in BioRender. https://BioRender.com/, accessed on 20 December 2025.
Because CoQ10 participates in both mitochondrial and non-mitochondrial antioxidant protection, its loss may contribute to oxidative damage affecting multiple cellular membranes. Indeed, a marked increase in ROS production has been demonstrated in human fibroblasts carrying mutations in various genes involved in CoQ10 biosynthesis. The group of Quinzii et al. has extensively investigated this issue and observed no correlation between the level of CoQ10 depletion and ROS generation [149,218,219,220,221]. They rather showed that ROS overproduction is most pronounced in moderate deficiencies of CoQ10 levels by approximately 40% (Figure 7).
Figure 7.
Schematic representation of ROS production as a function of residual CoQ10 concentration. Adapted from López et al. [218].
The proposed explanation is that complete CoQ10 depletion markedly slows down the respiratory chain and shifts ATP production toward anaerobic glycolysis, whereas partial deficiencies allow for residual, yet dysfunctional, respiratory chain activity that produces higher levels of ROS. These findings, limited to fibroblast models, therefore indicate that ROS production is mainly secondary to respiratory chain dysfunction in the context of CoQ10 deficiency [149,219,220]. While a direct causal link between primary CoQ10 deficiency and ferroptosis has not yet been conclusively demonstrated, experimental disruption of CoQ10 transport from mitochondria to the plasma membrane was shown to markedly increase ferroptotic sensitivity [73]. In light of these findings on ROS production, it cannot be excluded that the oxidative stress and its associated damages would vary among cell types, which could explain why certain tissues are more susceptible to damage; this could explain why certain organs such as the brain, heart, or kidneys are more frequently affected in primary CoQ10 deficiencies. To further support this hypothesis, it would be of interest to investigate oxidative stress in tissues other than fibroblasts, using established markers of oxidative damage. These could include DNA oxidation products such as 8-oxo-dG, protein oxidation markers such as dityrosine, and indicators of lipid peroxidation such as isoprostanes.
In this context, the use of novel experimental models, such as iPSCs or organoid systems, could provide a particularly relevant approach. These models would allow the investigation of redox imbalance in a tissue-specific manner, better reflecting the cellular diversity of affected organs, and may help clarify the contribution of oxidative stress to the pathophysiology.
The link between primary CoQ10 deficiency and a reduction in these antioxidant functions has not been clearly demonstrated in humans. However, it is reasonable to assume that when the global CoQ10 pool decreases, not only are mitochondrial bioenergetics impaired, but also its antioxidant capacity may be compromised. In such a context, sustained oxidative stress, insufficiently counterbalanced by endogenous defense systems, could theoretically promote cell death pathways, including ferroptosis. This assumption is biologically consistent with the mechanisms previously discussed, which show that CoQH2 serves as a central lipid radical–trapping antioxidant, that its regeneration through enzymes such as FSP1 and DHODH constitutes a major ferroptosis-suppressive axis, and that mitochondrial complex I dysfunction can sensitize cells to ferroptosis by disturbing redox homeostasis and enhancing lipid peroxidation [193]. Thus, ferroptosis is likely to play a significant role in CoQ10 deficiencies. It may represent a major cell death pathway and could contribute to cellular damage, including cardiomyocyte necrosis [82] and neuronal loss associated with astrogliosis reported in COQ4 mutations [76,83].
In conclusion, numerous studies link CoQ10 depletion to ROS levels, suggesting that oxidative stress is a major contributor to CoQ10 deficiency, as suggested for other mitochondrial diseases. In these cases, antioxidant therapies have yet to show clear clinical benefits [222]. It is important to note that these observations are limited to the specific molecules and outcome measures studied to date, such as visual improvement in Leber hereditary optic neuropathy. Thus, while oxidative stress is likely central to the disease’s pathophysiology, robust clinical evidence for the success of targeting this pathway remains elusive.
ROS as a Key Trigger of Mitophagy
Mitophagy is an essential cellular process that regulates mitochondrial mass through the autophagy pathway. It occurs under both physiological conditions, such as the elimination of mitochondria during erythropoiesis, and pathological situations, where it serves to remove damaged mitochondria. If not eliminated, these dysfunctional organelles can release pro-apoptotic signals, most notably cytochrome c, leading to cell death. The mitophagy process unfolds in several coordinated steps. First, dysfunctional mitochondria are recognized through specific molecular cues, often associated with fragmentation of the mitochondrial network. Once identified, they are isolated and subsequently enclosed within a forming autophagosome. The autophagosome then fuses with a lysosome, resulting in the degradation of mitochondrial components and the prevention of apoptosis [223]. Mitophagy plays a crucial role in maintaining mitochondrial quality control and has been implicated in a wide range of diseases, including Parkinson’s disease [224], cardiovascular disorders [225], and ischemic stroke [226]. Two major pathways for mitophagy activation have been described:
- The PINK1/Parkin pathway. This pathway is triggered by a loss of mitochondrial membrane potential. PINK1 and Parkin act in concert to label mitochondrial outer membrane proteins with phosphorylated ubiquitin. This ubiquitin tag is recognized by the autophagic machinery, allowing the recruitment of mitochondria to microtubule-associated protein 1A/1B-light chain 3 (LC3) through adaptor proteins and their subsequent incorporation into autophagosomes [227].
- The receptor-mediated pathways. Certain mitochondrial receptors, such as FUNDC1 under ischemic conditions, expose an LC3-interacting region (LIR) motif upon activation. This motif directly binds LC3, forming a bridge between the mitochondrion and the autophagosome [228]. These receptors function in a context-dependent manner, responding to specific types of cellular stress or damage.
Few studies have investigated the relationship between CoQ10 deficiency and mitophagy. Nevertheless, this connection is biologically plausible, as several pathophysiological mechanisms observed in CoQ10 deficiency could also activate mitophagy. These include mitochondrial membrane depolarization, which may trigger the PINK1/Parkin pathway, and excessive oxidative stress leading to mitochondrial damage and mitophagy induction.
The first study to explore this relationship demonstrated a disruption of the mitochondrial network, a preliminary step required for the selective targeting of damaged mitochondria [149,229]. The authors analyzed fibroblasts from four patients carrying COQ gene mutations and observed decreased mitochondrial membrane potential (less polarized mitochondria), a key signal for mitophagy activation. Increased ROS production was also noted, further contributing to mitochondrial injury and mitophagy initiation. Consistent with this, expression of autophagy-related proteins (LC3, Beclin, and Atg12) was upregulated, lysosomal activity was enhanced, as evidenced by increased acidic vacuoles and lysotracker staining, and electron microscopy revealed autophagosomes containing mitochondria. Importantly, treatment with the antioxidant N-acetylcysteine (NAC) attenuated autophagy, confirming the role of oxidative stress as a trigger [229].
This study was the first to implicate mitophagy in the context of primary CoQ10 deficiency. The functional role of mitophagy in this setting remains to be fully defined. As demonstrated in other pathologies, mitophagy generally exerts a cytoprotective function by eliminating damaged mitochondria and preventing the release of pro-apoptotic factors. However, excessive or sustained activation may lead to mitochondrial depletion and impaired bioenergetic capacity, potentially worsening cellular dysfunction. Further studies focusing on the specific actors of mitophagy, particularly PINK1 and Parkin, are required to better characterize the mechanisms involved in CoQ10 deficiency. However, it has been demonstrated in certain mitochondrial diseases, such as Leber’s hereditary optic neuropathy, that mitophagy can become persistently activated and likely contributes to a profound depletion of mitochondrial mass, as it is not adequately compensated by mitobiogenesis, ultimately leading to neuronal degeneration. Mitophagy is therefore not inherently protective and may exacerbate the pathological condition when excessively sustained. Notably, interventions aimed at reducing mitophagy, such as supplementation with CoQ10 precursors to mitigate oxidative stress, have been shown to exert a beneficial effect on cellular survival. Together, these findings show that while mitophagy serves a protective function, its excessive activation can promote mitochondrial depletion and contribute to cell death [230].
Because this cellular mechanism is involved in the removal of damaged mitochondria, it is expected to be activated in the context of CoQ10 deficiency. While mitophagy is initially protective, its sustained or excessive activation may become deleterious, as it can lead to excessive mitochondrial depletion and consequently to cellular energy deficiency. The most important trigger for mitophagy activation appears to be the accumulation of ROS, suggesting that mitophagy represents a secondary mechanism downstream of oxidative stress. Based on the current body of evidence, this therefore supports the view that mitophagy constitutes a minor pathophysiological mechanism in CoQ10 deficiency rather than a primary driver of disease. However, the dynamics of mitophagy in CoQ10 deficiency remain insufficiently characterized. Many of the tools used in published studies rely on general autophagy markers, while relatively few directly assess the core components of the mitophagy machinery, such as PINK1 and Parkin. Further investigations are therefore required to better understand the role of mitophagy in primary CoQ10 deficiencies.
5.2.4. Role of Inflammation in Coenzyme Q10 Deficiency
Inflammation is a physiological process that contributes to host defense and the restoration of homeostasis in response to various insults. This tightly regulated system is initiated by specific sensing mechanisms, particularly in the context of tissue stress, where damage-associated molecular patterns (DAMPs), including those of mitochondrial origin, play a central role [231]. The onset of inflammation involves several classes of pattern recognition receptors (PRRs). These receptors detect pathogen-associated molecular patterns (PAMPs) and DAMPs released from stressed or damaged cells. Among extracellular PRRs, Toll-like receptors (TLRs) and C-type lectin receptors (CLRs) are key sensors. Intracellularly, other PRRs such as RIG-I-like receptors (RLRs), AIM2-like receptors (ALRs) and NOD-like receptors (NLRs) contribute to the detection of nucleic acids, lipids and other danger signals. Activation of membrane or endosomal PRRs typically engages the NF-κB pathway and induces the transcription of pro-inflammatory cytokines. Moreover, activation of cytosolic NLRs can lead to the assembly of inflammasomes, which activate caspase-1 and promote the maturation and secretion of IL-1β and IL-18, often associated with lytic forms of cell death such as pyroptosis [232].
Mitochondrial stress or damage can lead to the release of mtDNA into the cytosol or extracellular environment. Once outside the mitochondrial matrix, mtDNA behaves as a DAMP that is sensed by innate immune receptors. Cytosolic mtDNA may activate the cGAS–STING signaling pathway, triggering production of type I interferons and pro-inflammatory cytokines. In parallel, extracellular or endosomal mtDNA can engage receptors such as TLR9 or stimulate inflammasome complexes (e.g., NLRP3), leading to secretion of IL-1β and IL-18 and amplification of the inflammatory response. Thus, mitochondrial dysfunction, through mtDNA release, constitutes a mechanistic bridge between mitochondrial damage and sterile inflammation [233].
Indirect evidence suggests a link between CoQ10 and inflammation. Low CoQ10 levels are associated with NLRP3 activation in peripheral blood mononuclear cells obtained from patients affected by fibromyalgia, and supplementation by exogenous CoQ10 reverses these abnormalities [234]. In preclinical models, CoQ10 and its analogs (CoQ0) inhibit NLRP3 activation by reducing mitochondrial ROS, suppressing NF-κB signaling, and, in some cases, promoting autophagy [235,236]. Notably, interventions aimed at reducing autophagy reversed CoQ0-induced inhibition of inflammation. Together, these findings showed that in such a context, autophagy had a positive effect.
To date, no study has specifically and systematically characterized the inflammatory response in patients with primary CoQ10 deficiency. However, several mechanistic hypotheses can be proposed based on the known pathophysiology of CoQ10 deficiency and on general links between mitochondrial dysfunction and inflammation:
- ROS-mediated activation of inflammasome: increased ROS production, observed in primary CoQ10 deficiency, is a well-established trigger of inflammasome activation. In particular, ROS can promote dissociation of the thioredoxin (Trx)–thioredoxin-interacting protein (TXNIP) complex, allowing TXNIP to bind NLRP3 and drive NLRP3 inflammasome assembly, caspase-1 activation and IL-1β/IL-18 release [237].
- Role of Mitochondrial DAMPs in inflammasome activation: several mitochondrial components have been shown to trigger inflammatory responses through activation of the inflammasome [231]. Although a direct link between ferroptosis and the release of these mitochondrial danger signals has not yet been demonstrated, this remains a plausible scenario given the profound disruption of mitochondrial membranes during lipid peroxidation and the potential extrusion of pro-inflammatory factors such as oxidized cardiolipin [238].
- Altered sulfide oxidation and H2S accumulation: H2S has been identified as a mediator of inflammation, and several studies have reported a correlation between elevated H2S levels and the severity of inflammatory responses [239]. Therefore, in primary CoQ10 deficiency, where disturbances in H2S metabolism have been observed, it is plausible that altered H2S signaling represents a contributing mechanism to the associated inflammatory phenotype.
In conclusion, multiple lines converge toward a probable overactivation of inflammatory pathways in primary CoQ10 deficiencies, potentially driven by ROS-induced cellular damage, the release of DAMPs, and the disturbance in sulfide metabolism. However, the mechanism still requires further validation through additional experimental investigation, and its clinical relevance remains to be established through appropriately designed therapeutic studies. Based on the current evidence, we can therefore classify this pathophysiological mechanism as minor.
5.3. Physiopathological Hypothesis About Tissue Susceptibility
Primary CoQ10 deficiencies illustrate how disruption of a single metabolic hub can trigger a cascade of interconnected cellular dysfunctions. Although CoQ10 depletion is biochemically defined by impaired electron transfer within the MRC, the clinical and experimental evidence reviewed here clearly demonstrates that disease pathophysiology extends far beyond an isolated defect in ATP production. Conversely, CoQ10 deficiency triggers multiple interconnected pathways (Figure 8). Their varying contributions to the pathophysiology of these diseases collectively dictate tissue vulnerability, disease severity, and phenotypic expression.
Figure 8.
Main hypotheses and metabolic pathways that may explain the pathophysiological mechanisms of primary coenzyme Q10 deficiencies. The pathophysiological mechanisms are shown on a colored background according to their relative importance in the pathophysiology of primary CoQ10 deficiency. FAOD: Fatty acid oxidation disorder. Dotted arrows mean indirect pathophysiological mechanisms. Created in BioRender. https://BioRender.com/, accessed on 20 December 2025.
5.3.1. Differential Depletion of CoQ10 Among Tissues
While human data are limited due to the invasive nature of organ sampling, preclinical models with human COQ gene mutations demonstrate that CoQ10 depletion levels are both organ- and mutation-specific [240]. For instance, in Coq9Q95X mice, depletion is more severe in skeletal muscle than in the brain or cerebellum. Comparing the Coq9Q95X and Coq9R239X models reveals that the latter induces greater depletion across the brain, heart, liver, and kidneys, though not in skeletal muscle.
These distinct depletion profiles dictate the pathological outcome: partial deficiency primarily causes tissue damage through oxidative stress, due to the loss of radical scavenging and impaired antioxidant regeneration, rather than through primary energy failure (Figure 9). Elevated oxidative stress damages mitochondrial lipids, proteins, and DNA, further impairing mitochondrial function and creating a self-reinforcing loop of dysfunction. Persistent redox imbalance can activate apoptotic and necrotic cell death pathways, contributing to progressive tissue degeneration, particularly in post-mitotic tissues such as neurons and cardiomyocytes. In the case of a severe CoQ10 depletion leading primarily to ATP deficiency (Figure 9), numerous cellular dysfunctions occur, including a drastic reduction in muscle contraction, particularly cardiac contraction; the shutdown of ATP-dependent ion pumps both on the cell surface and in intracellular compartments, leading to a massive accumulation of calcium in the cytosol and mitochondria; and an accumulation of sodium and water inside the cell, leading to cell swelling and cell death by necrosis. The release of intracellular content into the extracellular environment will constitute an additional signal, thus creating inflammation in neighboring cells.
Figure 9.
Threshold-dependent effects of CoQ10 deficiency on mitochondrial metabolism and tissue vulnerability. Severe CoQ10 deficiency (<30–40% of normal) leads to a major decrease in ATP production, profound impairment of sulfide oxidation due to SQOR instability, and reduced DHODH-dependent pyrimidine synthesis, while ROS production remains moderately elevated. By contrast, moderate CoQ10 deficiency (≈40–60% of normal) causes a moderate decrease in ATP production, partial impairment of sulfide oxidation, and marked increases in ROS generation. Pyrimidine synthesis is largely preserved in this context. Arrow thickness represents the relative magnitude of pathway alterations, and color coding indicates the severity of dysfunction (red, severe; orange, moderate; green, preserved). Created in BioRender. https://BioRender.com/, accessed on 20 December 2025.
5.3.2. Energy Requirement
The most direct consequence of CoQ10 depletion is impaired electron transport between several mitochondrial dehydrogenases and complex III, leading to reduced respiratory chain efficiency and ATP synthesis. The severity of this energetic defect depends on residual CoQ10 levels (Figure 9) and on the degree to which tissues rely on oxidative phosphorylation. Experimental data from patient-derived cells show that mild to moderate CoQ10 depletion primarily limits maximal respiratory capacity, whereas severe deficiency compromises basal respiration, mitochondrial membrane potential, and ATP/ADP ratios, particularly under conditions that force reliance on oxidative metabolism. These findings would explain why organs with high and continuous energy demands, such as the brain, heart, skeletal muscle, and kidney, are preferentially affected. However, the existence of isolated organ phenotypes indicates that energy failure alone is insufficient to account for the full clinical spectrum.
5.3.3. Different Levels of Antioxidant Enzymes
Tissue susceptibility to oxidative stress is determined by the interplay of several factors: the expression of antioxidant enzymes or molecules, including CoQ10 concentrations; the prevalence of damage-prone structures like lipid-rich membranes; and the intrinsic rate of ROS production, which is closely linked to mitochondrial density and metabolic demand.
Within the superoxide dismutase family, SOD1 (cytosolic) and SOD2 (mitochondrial) are ubiquitously expressed. In contrast, SOD3 (extracellular) shows a more restricted distribution, peaking in vascular tissues, notably at the blood–brain barrier, where it likely maintains extracellular redox homeostasis [241]. Regarding systems more closely tied to CoQ10 metabolism, GPX4 is notably enriched in lipid-heavy organs such as the brain, liver, and heart, though exact quantitative expression is still being defined [205]. Conversely, FSP1 (AIFM2) is generally expressed at low levels, with only a slight predominance in the liver. Whether this profile indicates a true tissue-specific reliance on the FSP1–CoQ10 axis remains a subject for further study.
The brain serves as a primary example of high oxidative vulnerability. This sensitivity stems from its dense lipid composition, high energetic requirements, and heavy reliance on mitochondrial metabolism, all of which drive elevated ROS production. Furthermore, evidence suggests that the brain’s antioxidant defenses may be relatively sparse compared to other metabolically active tissues [242].
Collectively, these observations suggest that tissue-specific redox architecture may dictate differential vulnerability to ROS. This variation represents a significant, yet underexplored, factor in explaining the clinical heterogeneity of CoQ10 deficiency. However, direct evidence linking tissue-specific ROS susceptibility to clinical phenotypes remains sparse, necessitating further experimental validation.
5.3.4. Differential Pathways
As previously discussed, CoQ10 occupies a central position at the intersection of multiple metabolic pathways, meaning its depletion can trigger diverse cellular alterations depending on the specific requirements of the affected tissue. In energy-demanding cardiac and skeletal muscles, CoQ10 deficiency impairs electron transfer from ETFDH, thereby reducing mitochondrial β-oxidation. This metabolic block leads to lipid accumulation, myopathy, and cardiomyopathy, as documented in both clinical and preclinical models.
Furthermore, studies in iPSC-derived neurons indicate that CoQ10 loss disrupts the mevalonate pathway and cholesterol trafficking. Such perturbations in lipid homeostasis likely compromise membrane composition, which is particularly detrimental to neurons given their reliance on membrane dynamics for myelination and synaptic function.
Additionally, the tissue-specific expression of CoQ10-dependent enzymes explains varying organ susceptibility. For instance, SQOR is highly expressed in the kidneys and skeletal muscle. Under conditions of CoQ10 deficiency, SQOR is destabilized, which impairs mitochondrial hydrogen sulfide detoxification. The resulting accumulation of sulfide and sulfane sulfur species further inhibits respiratory complexes and β-oxidation while altering redox signaling. Much like ATP synthesis and ROS production, this pathway is highly sensitive to CoQ10 levels, potentially acting as a critical amplifier of mitochondrial dysfunction once a specific depletion threshold is reached.
5.3.5. Exogenous Intake of CoQ10
Another factor that could partly explain the differential damage to certain tissues compared to others is the contribution of exogenous CoQ10. While CoQ10 supplementation (200 mg) for 14 days in healthy human subjects does not increase the muscle concentration of this cofactor [243], oral supplementation (between 20 and 73 mg/kg/day) does increase CoQ10 concentrations measured in PBMCs from patients with primary deficiency [244]. It can therefore be assumed that, in physiological conditions, the contribution of exogenous CoQ10 to tissue concentrations is negligible, but that in pathological conditions (i.e., primary CoQ10 deficiency), this pathway would allow for an intake, albeit insufficient to enable subnormal cellular function. Given that exogenous CoQ10 is transported mainly by lipoproteins in the blood, HDL, LDL, and CD36 receptors could be involved in the tissue import of CoQ10, as suggested by preclinical studies [245]. However, this hypothesis has not been validated by the work of Saiki and colleagues on the Pdss2kd/kd mouse model. Although a reduction in proteinuria is observed after CoQ10 supplementation, no increase in this cofactor has been observed in the kidney [246].
5.4. Translational Implications
Primary CoQ10 deficiency is unique among mitochondrial diseases, as it is the only one considered treatable through cofactor supplementation. Theoretically, administering exogenous CoQ10 should bypass the metabolic block caused by pathogenic variants in COQ genes, restoring tissue levels and the biochemical reactions dependent on them. Indeed, the capacity to rescue these metabolic pathways is a key criterion for confirming the pathogenicity of newly identified variants.
Clinical outcomes, however, vary significantly. In a cohort of patients with ataxia caused by COQ8A mutations, Traschütz et al. found that approximately 50% responded positively to daily CoQ10 doses (2–40 mg/kg/day) with minimal side effects [97]. Interestingly, the response was independent of patient age, age of onset, or disease duration. Clinical improvements were confirmed through longitudinal assessments, where symptoms often worsened if treatment was discontinued. Recent systematic reviews also highlight the complexities of CoQ10 treatment efficacy. Wang and Hekimi analyzed 89 well-documented cases and found a responder rate of only 27% [247]. This low percentage may result from the difficulty of evaluating a positive response in patients affected by multi-systemic symptoms. However, they noted that the response was independent of dose or duration, with isolated renal forms and less severe phenotypes showing the best outcomes. In a critical review of over 330 patients harboring various COQ mutations, Mantle et al. highlighted the necessity of early CoQ10 supplementation to prevent irreversible tissue damage [248]. They found that therapeutic efficacy is highly gene-specific, showing significant success in COQ6-related nephropathy, but remains limited in treating CNS symptoms, likely due to the poor permeability of CoQ10 across the blood–brain barrier.
Mechanistically, cellular models suggest that the “dose–response” relationship is not uniform across all biological functions. Duberley et al. demonstrated that while low concentrations of CoQ10 can reduce superoxide production, significantly higher doses are required to restore mitochondrial membrane potential or to partially correct respiratory chain deficiencies [249]. This suggests that the clinical success of supplementation depends heavily on whether the exogenous cofactor can reach specific tissues and penetrate the relevant cellular compartments, such as the mitochondria.
These data underscore the necessity of early intervention and the use of objective criteria to monitor treatment efficacy in suspected primary CoQ10 deficiency. Future research has to focus on enhancing the bioavailability of CoQ10 and elucidating its transport mechanisms to different organs and intracellular spaces to more effectively target the pathophysiology of these deficiencies.
6. Conclusions
Ultimately, primary CoQ10 deficiencies transcend simple mitochondrial energy failure; they are multisystemic conditions driven by complex metabolic and redox imbalances. Clinical manifestations appear to be governed by tissue-specific vulnerability, likely dictated by varying degrees of residual CoQ10 and dysfunctions in cellular pathways. Nevertheless, certain questions remain unanswered and open up essential avenues of research for improving more effective and targeted therapeutic management of patients with primary deficiency.
6.1. Does the Efficacy of CoQ10 Supplementation Vary Across Different Organs?
Studies using 11C-labeled CoQ10 demonstrate preferential accumulation in the liver and heart, with significantly lower uptake in skeletal muscle and the brain. These distribution patterns suggest that while oral supplementation may effectively address cardiac or renal manifestations of primary CoQ10 deficiency, its efficacy for neurological symptoms remains limited. Consequently, future efforts must focus on enhancing CoQ10’s blood–brain barrier permeability or engineering therapies that target tissue-specific cellular dysfunction directly.
6.2. Does CoQ10 Supplementation in Patients with Primary Deficiency Correct Both Mitochondrial and Extramitochondrial Concentrations?
While CoQ10 is primarily localized within the mitochondrial fraction, it is also present in the non-mitochondrial pool, where it primarily serves as an antioxidant and ferroptosis inhibitor. No study has yet determined whether CoQ10 depletion in patients with biosynthesis defects affects the mitochondrial pool, the non-mitochondrial pool, or both. Furthermore, it remains to be determined whether exogenous CoQ10 supplementation can effectively or preferentially restore these specific cellular pools.
6.3. Is It Possible to Measure the Involvement of the Various Pathways or Reactions in Which CoQ10 Is Involved in Pathogenicity in Humans?
As previously noted, CoQ10 is involved in several biochemical pathways, such as pyrimidine synthesis and choline metabolism, whose roles in specific pathophysiological mechanisms remain unknown due to a lack of objective data. We propose that organoids derived from patient-specific iPSCs represent a promising experimental model to address this gap. Using these models, specialized biochemical assays could be developed to measure pathway-specific metabolites with greater precision. Furthermore, pharmacological interventions, specific gene expression or CRISPR-Cas9 gene editing could be employed to correct observed alterations, allowing for the evaluation of therapeutic outcomes at both the cellular and organoid levels.
6.4. Is There a Tissue-Specific Critical Threshold of CoQ10?
It is well admitted that the degree of CoQ10 depletion, which varies across different tissues, directly dictates cellular dysfunction and, consequently, clinical phenotype (as illustrated in Figure 8 and Figure 9). A critical consideration is that pathological thresholds for CoQ10 may be tissue-specific; investigating these distinct thresholds could provide an interesting insight into the underlying pathophysiological mechanisms of the disease.
6.5. Given That the Pathophysiological Mechanisms of Primary CoQ10 Deficiencies Are Complex and Involve Several Pathways, Would Combination Therapies Targeting These Different Pathways Be Effective?
Clinical outcomes for patients with mutations in CoQ10 biosynthesis genes remain inconsistent, as supplementation often fails to yield uniform benefits. This suggests that instead of focusing exclusively on restoring CoQ10 levels, therapeutic efforts should also expand to address secondary cellular disruptions, including neuroinflammation, oxidative stress, H2S metabolism, and cell death signaling. Integrating CoQ10 with specific modulators of these pathways may provide a more robust and effective therapeutic framework than monotherapy with the cofactor alone.
Author Contributions
F.F., R.P. and S.A.: writing—review and editing. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study.
Acknowledgments
We thank BioRender for providing the software used to generate several figures included in this publication.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| 8-oxo-dG | 8-oxo-2′-deoxyguanosine |
| 4-HBF | 4-hydroxybenzoylformate |
| 4-HB | 4-hydroxybenzoate |
| 4-HBz | 4-hydroxybenzaldehyde |
| 4-HMA | 4-hydroxymandelate |
| 4-HNE | 4-hydroxynonenal |
| 4-HPP | 4-hydroxyphenylpyruvate |
| AADAT | α-aminoadipate aminotransferase |
| ADCK | AarF domain-containing kinase |
| ADP | Adenosine diphosphate |
| ALDH3A1 | Aldehyde dehydrogenase 3 family member A1 |
| ALRs | AIM2-like receptors |
| ATP | Adenosine triphosphate |
| ATPase | adenosine triphosphatase |
| BADH | Betaine aldehyde dehydrogenase |
| BHMT | Betaine-homocysteine methyltransferase |
| CDP-choline | Cytidine diphosphate choline |
| CHDH | Choline dehydrogenase |
| CI | Mitochondrial respiratory chain complex I |
| CIV | Mitochondrial respiratory chain complex IV |
| CLRs | C-type lectin receptors |
| CNS | Central nervous system |
| CoQ | Coenzyme Q |
| CoQH2 | Ubiquinol |
| COX | Cytochrome c oxidase |
| Cryo-EM | Cryo-electron microscopy |
| CTP | Cytidine triphosphate |
| CYB5R | Cytochrome b5 reductase |
| DAMPs | Damage-associated molecular patterns |
| DDMQ | Demethoxy-demethyl-CoQ10 |
| DHAP | Dihydroxyacetone phosphate |
| DHODH | Dihydroorotate dehydrogenase |
| DMeQ | Demethyl-CoQ10 |
| DMAP | Dimethylallyl pyrophosphate |
| DMQ | Demethoxy-CoQ10 |
| DN | Deoxyribonucleic acid |
| D2HGDH | D-2-hydroxyglutarate dehydrogenase |
| ETC | Electron transport chain |
| ETF | Electron-transfer flavoprotein |
| ETFDH | Electron-transferring flavoprotein dehydrogenase |
| ETF-QO | Electron-transfer flavoprotein–ubiquinone oxidoreductase |
| ETHE1 | Ethylmalonic encephalopathy protein 1 |
| E–SSH | Protein persulfide |
| FAD | Flavin adenine dinucleotide |
| FADH2 | Reduced flavin adenine dinucleotide |
| FBS | Fetal bovine serum |
| FMN | Flavin mononucleotide |
| FMNH2 | Reduced flavin mononucleotide |
| FPPS | Farnesyl diphosphate synthase |
| FPP | Farnesyl pyrophosphate |
| FSP1 | Ferroptosis suppressor protein 1 |
| FUNDC1 | FUN14 domain-containing protein 1 |
| G3P | Glycerol-3-phosphate |
| GPX | Glutathione peroxidase |
| GPD1 | Glycerol-3-phosphate dehydrogenase 1 |
| GPD2 | Glycerol-3-phosphate dehydrogenase 2 |
| GPP | Geranyl pyrophosphate |
| GR | Glutathione reductase |
| GSH | Reduced glutathione |
| GSSH | Glutathione persulfide |
| GSTs | Glutathione-S-transferases |
| HDL | High-density lipoprotein |
| HEK293 | Human embryonic kidney 293 |
| HMGCR | 3-hydroxy-3-methylglutaryl-CoA reductase |
| HPDL | Hydroxyphenylpyruvate dioxygenase-like protein |
| IMS | Intermembrane space |
| IMM | Inner mitochondrial membrane |
| IPP | Isopentenyl pyrophosphate |
| iPSC | Induced pluripotent stem cells |
| IUGR | Intrauterine growth restriction |
| LC3 | Microtubule-associated protein 1 light chain 3 |
| LDHD | Lactate dehydrogenase D |
| LDL | Low-density lipoprotein |
| LIR | LC3-interacting region |
| MADD | Multiple acyl-CoA dehydrogenase deficiency |
| MDA | Malondialdehyde |
| MRC | Mitochondrial respiratory chain |
| mtDNA | Mitochondrial DNA |
| NAC | N-acetylcysteine |
| NAD+ | Nicotinamide adenine dinucleotide |
| NADH | Reduced nicotinamide adenine dinucleotide |
| NADP | Nicotinamide adenine dinucleotide phosphate |
| NF-κB | Nuclear factor kappa-B |
| NLRP3 | NLR family pyrin domain-containing 3 |
| NLRs | NOD-like receptors |
| NQO1 | NAD(P)H quinone dehydrogenase 1 |
| OMM | Outer mitochondrial membrane |
| PAH | Phenylalanine hydroxylase |
| PAMPs | Pathogen-associated molecular patterns |
| PBHQ | 3-polyprenyl-5-hydroxy-1,4-benzohydroquinone |
| PBQ | 3-polyprenyl-1,4-benzohydroquinone |
| PDSS1 | Decaprenyl diphosphate synthase subunit 1 |
| PDSS2 | Decaprenyl diphosphate synthase subunit 2 |
| PINK1 | PTEN-induced kinase 1 |
| PMRS | Plasma membrane redox system |
| PPDHB | 3-polyprenyl-4,5-dihydroxybenzoate |
| PPHB | 3-polyprenyl-4-hydroxybenzoate |
| PPMP | 2-polyprenyl-6-methoxyphenol |
| PPP | Polyprenyl pyrophosphate |
| PPVA | 3-polyprenylvanillic acid |
| PRRs | Pattern-recognition receptors |
| PRODH1 | Proline dehydrogenase 1 |
| PRODH2 | Proline dehydrogenase 2 |
| PUFAs | Polyunsaturated fatty acids |
| Q | Ubiquinone |
| QH2 | Ubiquinol |
| RET | Reverse electron transport |
| RIG-I | Retinoic acid-inducible gene I |
| RLRs | RIG-I-like receptors |
| RNA | Ribonucleic acid |
| ROS | Reactive oxygen species |
| SAM | S-adenosylmethionine |
| SCAD | Short-chain acyl-CoA dehydrogenase |
| SCs | Respiratory supercomplexes |
| SOD1 | Superoxide dismutase 1 |
| SOD2 | Superoxide dismutase 2 |
| SQ | Semiquinone |
| SQOR | Sulfide quinone oxidoreductase |
| SUOX | Sulfite oxidase |
| TAT | Tyrosine aminotransferase |
| TCA | Tricarboxylic acid |
| TLR9 | Toll-like receptor 9 |
| TLRs | Toll-like receptors |
| Trx | Thioredoxin |
| TST | Thiosulfate sulfurtransferase |
| TXNIP | Thioredoxin-interacting protein |
| UMP | Uridine monophosphate |
| UTP | Uridine triphosphate |
| VLDL | Very-low-density lipoprotein |
References
- Festenstein, G.N.; Heaton, F.W.; Lowe, J.S.; Morton, R.A. A constituent of the unsaponifiable portion of animal tissue lipids (lambda max. 272 m mu). Biochem. J. 1955, 59, 558–566. [Google Scholar] [CrossRef] [Scilit]
- Crane, F.L.; Hatefi, Y.; Lester, R.L.; Widmer, C. Isolation of a quinone from beef heart mitochondria. Biochim. Biophys. Acta 1957, 25, 220–221. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lester, R.L.; Crane, F.L.; Hatefi, Y. COENZYME Q: A NEW GROUP OF QUINONES1. J. Am. Chem. Soc. 1958, 80, 4751–4752. [Google Scholar] [CrossRef] [Scilit]
- Wolf, D.E.; Hoffman, C.H.; Trenner, N.R.; Arison, B.H.; Shunk, C.H.; Linn, B.O.; McPherson, J.F.; Folkers, K. COENZYME Q. I. STRUCTURE STUDIES ON THE COENZYME Q GROUP. J. Am. Chem. Soc. 1958, 80, 4752. [Google Scholar] [CrossRef] [Scilit]
- Aberg, F.; Appelkvist, E.L.; Dallner, G.; Ernster, L. Distribution and redox state of ubiquinones in rat and human tissues. Arch. Biochem. Biophys. 1992, 295, 230–234. [Google Scholar] [CrossRef] [Scilit]
- Denis, F.A.; D’Oultremont, P.A.; Debacq, J.J.; Cherel, J.M.; Brisou, J. [Distribution of ubiquinones (coenzyme Q) in Gram negative bacillae]. Comptes Rendus Seances Soc. Biol. Fil. 1975, 169, 380–383. [Google Scholar]
- Lester, R.L.; Crane, F.L. The natural occurrence of coenzyme Q and related compounds. J. Biol. Chem. 1959, 234, 2169–2175. [Google Scholar] [CrossRef] [Scilit]
- Turunen, M.; Olsson, J.; Dallner, G. Metabolism and function of coenzyme Q. Biochim. Biophys. Acta (BBA)-Biomembr. 2004, 1660, 171–199. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, Y.; Turunen, M.; Appelkvist, E.L. Restricted uptake of dietary coenzyme Q is in contrast to the unrestricted uptake of alpha-tocopherol into rat organs and cells. J. Nutr. 1996, 126, 2089–2097. [Google Scholar] [CrossRef] [Scilit]
- Tomasetti, M.; Alleva, R.; Solenghi, M.D.; Littarru, G.P. Distribution of antioxidants among blood components and lipoproteins: Significance of lipids/CoQ10 ratio as a possible marker of increased risk for atherosclerosis. BioFactors 1999, 9, 231–240. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lenaz, G.; Samorì, B.; Fato, R.; Battino, M.; Parenti Castelli, G.; Domini, I. Localization and preferred orientations of ubiquinone homologs in model bilayers. Biochem. Cell Biol. 1992, 70, 504–514. [Google Scholar] [CrossRef] [Scilit]
- Afri, M.; Ehrenberg, B.; Talmon, Y.; Schmidt, J.; Cohen, Y.; Frimer, A.A. Active oxygen chemistry within the liposomal bilayer. Part III: Locating Vitamin E, ubiquinol and ubiquinone and their derivatives in the lipid bilayer. Chem. Phys. Lipids 2004, 131, 107–121. [Google Scholar] [CrossRef] [Scilit]
- Kaurola, P.; Sharma, V.; Vonk, A.; Vattulainen, I.; Róg, T. Distribution and dynamics of quinones in the lipid bilayer mimicking the inner membrane of mitochondria. Biochim. Biophys. Acta (BBA)-Biomembr. 2016, 1858, 2116–2122. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Galassi, V.V.; Arantes, G.M. Partition, orientation and mobility of ubiquinones in a lipid bilayer. Biochim. Biophys. Acta (BBA)-Bioenerg. 2015, 1847, 1560–1573. [Google Scholar] [CrossRef] [Scilit]
- Sohal, R.S.; Forster, M.J. Coenzyme Q, oxidative stress and aging. Mitochondrion 2007, 7, S103–S111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Garrido-Maraver, J. Clinical applications of coenzyme Q10. Front. Biosci. 2014, 19, 619. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weber, C.; Bysted, A.; Hølmer, G. Coenzyme Q10 in the diet-daily intake and relative bioavailability. Mol. Asp. Med. 1997, 18, S251–S254. [Google Scholar] [CrossRef] [Scilit]
- Yubero, D.; Montero, R.; Artuch, R.; Land, J.M.; Heales, S.J.R.; Hargreaves, I.P. Biochemical diagnosis of coenzyme q10 deficiency. Mol. Syndromol. 2014, 5, 147–155. [Google Scholar] [CrossRef] [Scilit]
- Bhagavan, H.N.; Chopra, R.K. Coenzyme Q10: Absorption, tissue uptake, metabolism and pharmacokinetics. Free Radic. Res. 2006, 40, 445–453. [Google Scholar] [CrossRef] [Scilit]
- Miles, M.V. The uptake and distribution of coenzyme Q10. Mitochondrion 2007, 7, S72–S77. [Google Scholar] [CrossRef] [Scilit]
- Hosoe, K.; Kitano, M.; Kishida, H.; Kubo, H.; Fujii, K.; Kitahara, M. Study on safety and bioavailability of ubiquinol (Kaneka QH) after single and 4-week multiple oral administration to healthy volunteers. Regul. Toxicol. Pharmacol. RTP 2007, 47, 19–28. [Google Scholar] [CrossRef] [Scilit]
- Tomono, Y.; Hasegawa, J.; Seki, T.; Motegi, K.; Morishita, N. Pharmacokinetic study of deuterium-labelled coenzyme Q10 in man. Int. J. Clin. Pharmacol. 1986, 24, 536–541. [Google Scholar]
- Nakamura, T.; Ohno, T.; Hamamura, K.; Sato, T. Metabolism of coenzyme Q10: Biliary and urinary excretion study in guinea pigs. BioFactors 1999, 9, 111–119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bentinger, M.; Dallner, G.; Chojnacki, T.; Swiezewska, E. Distribution and breakdown of labeled coenzyme Q10 in rat. Free Radic. Biol. Med. 2003, 34, 563–575. [Google Scholar] [CrossRef] [Scilit]
- Paredes-Fuentes, A.J.; Montero, R.; Codina, A.; Jou, C.; Fernández, G.; Maynou, J.; Santos-Ocaña, C.; Riera, J.; Navas, P.; Drobnic, F.; et al. Coenzyme Q10 Treatment Monitoring in Different Human Biological Samples. Antioxidants 2020, 9, 979. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rötig, A.; Appelkvist, E.L.; Geromel, V.; Chretien, D.; Kadhom, N.; Edery, P.; Lebideau, M.; Dallner, G.; Munnich, A.; Ernster, L.; et al. Quinone-responsive multiple respiratory-chain dysfunction due to widespread coenzyme Q10 deficiency. Lancet 2000, 356, 391–395. [Google Scholar] [CrossRef] [Scilit]
- Stefely, J.A.; Pagliarini, D.J. Biochemistry of Mitochondrial Coenzyme Q Biosynthesis. Trends Biochem. Sci. 2017, 42, 824–843. [Google Scholar] [CrossRef] [Scilit]
- Nicoll, C.R.; Alvigini, L.; Gottinger, A.; Cecchini, D.; Mannucci, B.; Corana, F.; Mascotti, M.L.; Mattevi, A. In vitro construction of the COQ metabolon unveils the molecular determinants of coenzyme Q biosynthesis. Nat. Catal. 2024, 7, 148–160. [Google Scholar] [CrossRef] [Scilit]
- Pareek, V.; Sha, Z.; He, J.; Wingreen, N.S.; Benkovic, S.J. Metabolic channeling: Predictions, deductions, and evidence. Mol. Cell 2021, 81, 3775–3785. [Google Scholar] [CrossRef] [Scilit]
- Neupert, W.; Herrmann, J.M. Translocation of proteins into mitochondria. Annu. Rev. Biochem. 2007, 76, 723–749. [Google Scholar] [CrossRef] [Scilit]
- Guerra, R.M.; Pagliarini, D.J. Coenzyme Q biochemistry and biosynthesis. Trends Biochem. Sci. 2023, 48, 463–476. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aussel, L.; Pierrel, F.; Loiseau, L.; Lombard, M.; Fontecave, M.; Barras, F. Biosynthesis and physiology of coenzyme Q in bacteria. Biochim. Biophys. Acta (BBA)-Bioenerg. 2014, 1837, 1004–1011. [Google Scholar] [CrossRef] [Scilit]
- Awad, A.M.; Bradley, M.C.; Fernández-Del-Río, L.; Nag, A.; Tsui, H.S.; Clarke, C.F. Coenzyme Q10 deficiencies: Pathways in yeast and humans. Essays Biochem. 2018, 62, 361–376. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fernández-Del-Río, L.; Clarke, C.F. Coenzyme Q Biosynthesis: An Update on the Origins of the Benzenoid Ring and Discovery of New Ring Precursors. Metabolites 2021, 11, 385. [Google Scholar] [CrossRef] [Scilit]
- Banh, R.S.; Kim, E.S.; Spillier, Q.; Biancur, D.E.; Yamamoto, K.; Sohn, A.S.W.; Shi, G.; Jones, D.R.; Kimmelman, A.C.; Pacold, M.E. The polar oxy-metabolome reveals the 4-hydroxymandelate CoQ10 synthesis pathway. Nature 2021, 597, 420–425. [Google Scholar] [CrossRef] [Scilit]
- Stefely, J.A.; Kwiecien, N.W.; Freiberger, E.C.; Richards, A.L.; Jochem, A.; Rush, M.J.P.; Ulbrich, A.; Robinson, K.P.; Hutchins, P.D.; Veling, M.T.; et al. Mitochondrial protein functions elucidated by multi-omic mass spectrometry profiling. Nat. Biotechnol. 2016, 34, 1191–1197. [Google Scholar] [CrossRef] [Scilit]
- Xie, L.X.; Williams, K.J.; He, C.H.; Weng, E.; Khong, S.; Rose, T.E.; Kwon, O.; Bensinger, S.J.; Marbois, B.N.; Clarke, C.F. Resveratrol and para-coumarate serve as ring precursors for coenzyme Q biosynthesis. J. Lipid Res. 2015, 56, 909–919. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fernández-Del-Río, L.; Nag, A.; Gutiérrez Casado, E.; Ariza, J.; Awad, A.M.; Joseph, A.I.; Kwon, O.; Verdin, E.; de Cabo, R.; Schneider, C.; et al. Kaempferol increases levels of coenzyme Q in kidney cells and serves as a biosynthetic ring precursor. Free Radic. Biol. Med. 2017, 110, 176–187. [Google Scholar] [CrossRef] [Scilit]
- Tricarico, P.M.; Crovella, S.; Celsi, F. Mevalonate Pathway Blockade, Mitochondrial Dysfunction and Autophagy: A Possible Link. Int. J. Mol. Sci. 2015, 16, 16067–16084. [Google Scholar] [CrossRef] [Scilit]
- Ashby, M.N.; Edwards, P.A. Elucidation of the deficiency in two yeast coenzyme Q mutants. Characterization of the structural gene encoding hexaprenyl pyrophosphate synthetase. J. Biol. Chem. 1990, 265, 13157–13164. [Google Scholar] [CrossRef] [Scilit]
- Saiki, R.; Nagata, A.; Kainou, T.; Matsuda, H.; Kawamukai, M. Characterization of solanesyl and decaprenyl diphosphate synthases in mice and humans. FEBS J. 2005, 272, 5606–5622. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ashby, M.N.; Kutsunai, S.Y.; Ackerman, S.; Tzagoloff, A.; Edwards, P.A. COQ2 is a candidate for the structural gene encoding para-hydroxybenzoate:polyprenyltransferase. J. Biol. Chem. 1992, 267, 4128–4136. [Google Scholar] [CrossRef] [Scilit]
- Forsgren, M.; Attersand, A.; Lake, S.; Grünler, J.; Swiezewska, E.; Dallner, G.; Climent, I. Isolation and functional expression of human COQ2, a gene encoding a polyprenyl transferase involved in the synthesis of CoQ. Biochem. J. 2004, 382, 519–526. [Google Scholar] [CrossRef] [Scilit]
- Desbats, M.A.; Morbidoni, V.; Silic-Benussi, M.; Doimo, M.; Ciminale, V.; Cassina, M.; Sacconi, S.; Hirano, M.; Basso, G.; Pierrel, F.; et al. The COQ2 genotype predicts the severity of coenzyme Q10 deficiency. Hum. Mol. Genet. 2016, 25, 4256–4265. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Herebian, D.; Seibt, A.; Smits, S.H.J.; Rodenburg, R.J.; Mayatepek, E.; Distelmaier, F. 4-Hydroxybenzoic acid restores CoQ10 biosynthesis in human COQ2 deficiency. Ann. Clin. Transl. Neurol. 2017, 4, 902–908. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pierrel, F. Impact of Chemical Analogs of 4-Hydroxybenzoic Acid on Coenzyme Q Biosynthesis: From Inhibition to Bypass of Coenzyme Q Deficiency. Front. Physiol. 2017, 8, 436. [Google Scholar] [CrossRef] [Scilit]
- Jackman, L.M.; O’Brien, I.G.; Cox, G.B.; Gibson, F. Methionine as the source of methyl groups for ubiquinone and vitamin K: A study using nuclear magnetic resonance and mass spectrometry. Biochim. Biophys. Acta (BBA)-Gen. Subj. 1967, 141, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Alexander, K.; Young, I.G. Three hydroxylations incorporating molecular oxygen in the aerobic biosynthesis of ubiquinone in Escherichia coli. Biochemistry 1978, 17, 4745–4750. [Google Scholar] [CrossRef] [Scilit]
- Gin, P.; Hsu, A.Y.; Rothman, S.C.; Jonassen, T.; Lee, P.T.; Tzagoloff, A.; Clarke, C.F. The Saccharomyces cerevisiae COQ6 gene encodes a mitochondrial flavin-dependent monooxygenase required for coenzyme Q biosynthesis. J. Biol. Chem. 2003, 278, 25308–25316. [Google Scholar] [CrossRef] [Scilit]
- Pelosi, L.; Morbiato, L.; Burgardt, A.; Tonello, F.; Bartlett, A.K.; Guerra, R.M.; Ferizhendi, K.K.; Desbats, M.A.; Rascalou, B.; Marchi, M.; et al. COQ4 is required for the oxidative decarboxylation of the C1 carbon of coenzyme Q in eukaryotic cells. Mol. Cell 2024, 84, 981–989.e7. [Google Scholar] [CrossRef] [Scilit]
- Marbois, B.; Gin, P.; Gulmezian, M.; Clarke, C.F. The yeast Coq4 polypeptide organizes a mitochondrial protein complex essential for coenzyme Q biosynthesis. Biochim. Biophys. Acta (BBA)-Mol. Cell Biol. Lipids 2009, 1791, 69–75. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Casarin, A.; Jimenez-Ortega, J.C.; Trevisson, E.; Pertegato, V.; Doimo, M.; Ferrero-Gomez, M.L.; Abbadi, S.; Artuch, R.; Quinzii, C.; Hirano, M.; et al. Functional characterization of human COQ4, a gene required for Coenzyme Q10 biosynthesis. Biochem. Biophys. Res. Commun. 2008, 372, 35–39. [Google Scholar] [CrossRef] [Scilit]
- Acosta Lopez, M.J.; Trevisson, E.; Canton, M.; Vazquez-Fonseca, L.; Morbidoni, V.; Baschiera, E.; Frasson, C.; Pelosi, L.; Rascalou, B.; Desbats, M.A.; et al. Vanillic Acid Restores Coenzyme Q Biosynthesis and ATP Production in Human Cells Lacking COQ6. Oxidative Med. Cell. Longev. 2019, 2019, 3904905. [Google Scholar] [CrossRef] [Scilit]
- Marbois, B.N.; Clarke, C.F. The COQ7 gene encodes a protein in saccharomyces cerevisiae necessary for ubiquinone biosynthesis. J. Biol. Chem. 1996, 271, 2995–3004. [Google Scholar] [CrossRef] [Scilit]
- Stenmark, P.; Grünler, J.; Mattsson, J.; Sindelar, P.J.; Nordlund, P.; Berthold, D.A. A new member of the family of di-iron carboxylate proteins. Coq7 (clk-1), a membrane-bound hydroxylase involved in ubiquinone biosynthesis. J. Biol. Chem. 2001, 276, 33297–33300. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.; Smith, C.; Parboosingh, J.S.; Khan, A.; Innes, M.; Hekimi, S. Pathogenicity of two COQ7 mutations and responses to 2,4-dihydroxybenzoate bypass treatment. J. Cell. Mol. Med. 2017, 21, 2329–2343. [Google Scholar] [CrossRef] [Scilit]
- Jacquier, A.; Theuriet, J.; Fontaine, F.; Mosbach, V.; Lacoste, N.; Ribault, S.; Risson, V.; Carras, J.; Coudert, L.; Simonet, T.; et al. Homozygous COQ7 mutation: A new cause of potentially treatable distal hereditary motor neuropathy. Brain 2023, 146, 3470–3483. [Google Scholar] [CrossRef] [Scilit]
- Clarke, C.F.; Williams, W.; Teruya, J.H. Ubiquinone biosynthesis in Saccharomyces cerevisiae. Isolation and sequence of COQ3, the 3,4-dihydroxy-5-hexaprenylbenzoate methyltransferase gene. J. Biol. Chem. 1991, 266, 16636–16644. [Google Scholar] [CrossRef] [Scilit]
- Jonassen, T.; Clarke, C.F. Isolation and functional expression of human COQ3, a gene encoding a methyltransferase required for ubiquinone biosynthesis. J. Biol. Chem. 2000, 275, 12381–12387. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nguyen, T.P.T.; Casarin, A.; Desbats, M.A.; Doimo, M.; Trevisson, E.; Santos-Ocaña, C.; Navas, P.; Clarke, C.F.; Salviati, L. Molecular characterization of the human COQ5 C-methyltransferase in coenzyme Q10 biosynthesis. Biochim. Biophys. Acta (BBA)-Mol. Cell Biol. Lipids 2014, 1841, 1628–1638. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- He, C.H.; Xie, L.X.; Allan, C.M.; Tran, U.C.; Clarke, C.F. Coenzyme Q supplementation or over-expression of the yeast Coq8 putative kinase stabilizes multi-subunit Coq polypeptide complexes in yeast coq null mutants. Biochim. Biophys. Acta (BBA)-Mol. Cell Biol. Lipids 2014, 1841, 630–644. [Google Scholar] [CrossRef] [Scilit]
- Yen, H.-C.; Yeh, W.-Y.; Lee, S.-H.; Feng, Y.-H.; Yang, S.-L. Characterization of human mitochondrial PDSS and COQ proteins and their roles in maintaining coenzyme Q10 levels and each other’s stability. Biochim. Biophys. Acta (BBA)-Bioenerg. 2020, 1861, 148192. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yen, H.-C.; Liu, Y.-C.; Kan, C.-C.; Wei, H.-J.; Lee, S.-H.; Wei, Y.-H.; Feng, Y.-H.; Chen, C.-W.; Huang, C.-C. Disruption of the human COQ5-containing protein complex is associated with diminished coenzyme Q10 levels under two different conditions of mitochondrial energy deficiency. Biochim. Biophys. Acta (BBA)-Gen. Subj. 2016, 1860, 1864–1876. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reidenbach, A.G.; Kemmerer, Z.A.; Aydin, D.; Jochem, A.; McDevitt, M.T.; Hutchins, P.D.; Stark, J.L.; Stefely, J.A.; Reddy, T.; Hebert, A.S.; et al. Conserved Lipid and Small-Molecule Modulation of COQ8 Reveals Regulation of the Ancient Kinase-like UbiB Family. Cell Chem. Biol. 2018, 25, 154–165.e11. [Google Scholar] [CrossRef] [Scilit]
- Vázquez-Fonseca, L.; Schaefer, J.; Navas-Enamorado, I.; Santos-Ocaña, C.; Hernández-Camacho, J.D.; Guerra, I.; Cascajo, M.V.; Sánchez-Cuesta, A.; Horvath, Z.; Siendones, E.; et al. ADCK2 Haploinsufficiency Reduces Mitochondrial Lipid Oxidation and Causes Myopathy Associated with CoQ Deficiency. J. Clin. Med. 2019, 8, 1374. [Google Scholar] [CrossRef] [Scilit]
- Lohman, D.C.; Forouhar, F.; Beebe, E.T.; Stefely, M.S.; Minogue, C.E.; Ulbrich, A.; Stefely, J.A.; Sukumar, S.; Luna-Sánchez, M.; Jochem, A.; et al. Mitochondrial COQ9 is a lipid-binding protein that associates with COQ7 to enable coenzyme Q biosynthesis. Proc. Natl. Acad. Sci. USA 2014, 111, E4697–E4705. [Google Scholar] [CrossRef] [Scilit]
- Manicki, M.; Aydin, H.; Abriata, L.A.; Overmyer, K.A.; Guerra, R.M.; Coon, J.J.; Dal Peraro, M.; Frost, A.; Pagliarini, D.J. Structure and functionality of a multimeric human COQ7:COQ9 complex. Mol. Cell 2022, 82, 4307–4323.e10. [Google Scholar] [CrossRef] [Scilit]
- Fontaine, F.; Labalme, A.; Laurencin, C.; Theuriet, J.; Jacquier, A.; Lacoste, N.; Streichenberger, N.; Lesca, G.; Allouche, S. Homozygous COQ9 mutation: A new cause of potentially treatable hereditary spastic paraplegia. Eur. J. Hum. Genet. EJHG 2025, 33, 997–1005. [Google Scholar] [CrossRef] [Scilit]
- Tsui, H.S.; Pham, N.V.B.; Amer, B.R.; Bradley, M.C.; Gosschalk, J.E.; Gallagher-Jones, M.; Ibarra, H.; Clubb, R.T.; Blaby-Haas, C.E.; Clarke, C.F. Human COQ10A and COQ10B are distinct lipid-binding START domain proteins required for coenzyme Q function. J. Lipid Res. 2019, 60, 1293–1310. [Google Scholar] [CrossRef] [Scilit]
- Saito, Y.; Fukuhara, A.; Nishio, K.; Hayakawa, M.; Ogawa, Y.; Sakamoto, H.; Fujii, K.; Yoshida, Y.; Niki, E. Characterization of cellular uptake and distribution of coenzyme Q10 and vitamin E in PC12 cells. J. Nutr. Biochem. 2009, 20, 350–357. [Google Scholar] [CrossRef] [Scilit]
- Kashiba, M.; Oizumi, M.; Suzuki, M.; Sawamura, Y.; Nagashima, K.; Yoshimura, S.; Yamamoto, Y. Prosaposin regulates coenzyme Q10 levels in HepG2 cells, especially those in mitochondria. J. Clin. Biochem. Nutr. 2014, 55, 85–89. [Google Scholar] [CrossRef] [Scilit]
- Mugoni, V.; Postel, R.; Catanzaro, V.; De Luca, E.; Turco, E.; Digilio, G.; Silengo, L.; Murphy, M.P.; Medana, C.; Stainier, D.Y.R.; et al. Ubiad1 Is an Antioxidant Enzyme that Regulates eNOS Activity by CoQ10 Synthesis. Cell 2013, 152, 504–518. [Google Scholar] [CrossRef] [Scilit]
- Deshwal, S.; Onishi, M.; Tatsuta, T.; Bartsch, T.; Cors, E.; Ried, K.; Lemke, K.; Nolte, H.; Giavalisco, P.; Langer, T. Mitochondria regulate intracellular coenzyme Q transport and ferroptotic resistance via STARD7. Nat. Cell Biol. 2023, 25, 246–257. [Google Scholar] [CrossRef] [Scilit]
- Zhang, Y.; Rao, X.; Wang, J.; Liu, H.; Wang, Q.; Wang, X.; Hua, F.; Guan, X.; Lin, Y. Mitochondria-Associated Membranes: A Key Point of Neurodegenerative Diseases. CNS Neurosci. Ther. 2025, 31, e70378. [Google Scholar] [CrossRef] [Scilit]
- Rosado Santos, R.; Rodrigues, M.; Loureiro, T. Prenatal Diagnosis of Lissencephaly Associated with Biallelic Pathologic Variants in the COQ2 Gene. Acta Med. Port. 2023, 36, 428–431. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chung, W.K.; Martin, K.; Jalas, C.; Braddock, S.R.; Juusola, J.; Monaghan, K.G.; Warner, B.; Franks, S.; Yudkoff, M.; Lulis, L.; et al. Mutations in COQ4, an essential component of coenzyme Q biosynthesis, cause lethal neonatal mitochondrial encephalomyopathy. J. Med. Genet. 2015, 52, 627–635. [Google Scholar] [CrossRef] [Scilit]
- Fabra, M.A.; Paredes-Fuentes, A.J.; Torralba Carnerero, M.; Moreno Férnandez de Ayala, D.J.; Arroyo Luque, A.; Sánchez Cuesta, A.; Staiano, C.; Sanchez-Pintos, P.; Luz Couce, M.; Tomás, M.; et al. New variants expand the neurological phenotype of COQ7 deficiency. J. Inherit. Metab. Dis. 2024, 47, 1047–1068. [Google Scholar] [CrossRef] [Scilit]
- Pettenuzzo, I.; Carli, S.; Sánchez-Cuesta, A.; Isidori, F.; Montanari, F.; Grippa, M.; Lanzoni, G.; Ambrosetti, I.; Di Pisa, V.; Cordelli, D.M.; et al. COQ7 defect causes prenatal onset of mitochondrial CoQ10 deficiency with cardiomyopathy and gastrointestinal obstruction. Eur. J. Hum. Genet. 2024, 32, 938–946. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smith, A.C.; Ito, Y.; Ahmed, A.; Schwartzentruber, J.A.; Beaulieu, C.L.; Aberg, E.; Majewski, J.; Bulman, D.E.; Horsting-Wethly, K.; Koning, D.V.; et al. A family segregating lethal neonatal coenzyme Q10 deficiency caused by mutations in COQ9. J. Inherit. Metab. Dis. 2018, 41, 719–729. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jakobs, B.S.; Van Den Heuvel, L.P.; Smeets, R.J.P.; De Vries, M.C.; Hien, S.; Schaible, T.; Smeitink, J.A.M.; Wevers, R.A.; Wortmann, S.B.; Rodenburg, R.J.T. A novel mutation in COQ2 leading to fatal infantile multisystem disease. J. Neurol. Sci. 2013, 326, 24–28. [Google Scholar] [CrossRef] [Scilit]
- Scalais, E.; Chafai, R.; Van Coster, R.; Bindl, L.; Nuttin, C.; Panagiotaraki, C.; Seneca, S.; Lissens, W.; Ribes, A.; Geers, C.; et al. Early myoclonic epilepsy, hypertrophic cardiomyopathy and subsequently a nephrotic syndrome in a patient with CoQ10 deficiency caused by mutations in para-hydroxybenzoate-polyprenyl transferase (COQ2). Eur. J. Paediatr. Neurol. 2013, 17, 625–630. [Google Scholar] [CrossRef] [Scilit]
- Pan, P.; Zhou, N.; Sun, Y.; Chen, Z.; Han, J.; Zhou, W. The Spectrum of clinical manifestations in newborns with the COQ4 mutation: Case series and literature review. Front. Pediatr. 2024, 12, 1410133. [Google Scholar] [CrossRef] [Scilit]
- Brea-Calvo, G.; Haack, T.B.; Karall, D.; Ohtake, A.; Invernizzi, F.; Carrozzo, R.; Kremer, L.; Dusi, S.; Fauth, C.; Scholl-Bürgi, S.; et al. COQ4 Mutations Cause a Broad Spectrum of Mitochondrial Disorders Associated with CoQ10 Deficiency. Am. J. Hum. Genet. 2015, 96, 309–317. [Google Scholar] [CrossRef] [Scilit]
- Yu, M.H.-C.; Tsang, M.H.-Y.; Lai, S.; Ho, M.S.-P.; Tse, D.M.L.; Willis, B.; Kwong, A.K.-Y.; Chou, Y.-Y.; Lin, S.-P.; Quinzii, C.M.; et al. Primary coenzyme Q10 deficiency-7: Expanded phenotypic spectrum and a founder mutation in southern Chinese. npj Genom. Med. 2019, 4, 18. [Google Scholar] [CrossRef] [Scilit]
- Drovandi, S.; Lipska-Ziętkiewicz, B.S.; Ozaltin, F.; Emma, F.; Gulhan, B.; Boyer, O.; Trautmann, A.; Ziętkiewicz, S.; Xu, H.; Shen, Q.; et al. Variation of the clinical spectrum and genotype-phenotype associations in Coenzyme Q10 deficiency associated glomerulopathy. Kidney Int. 2022, 102, 592–603. [Google Scholar] [CrossRef] [Scilit]
- Kwong, A.K.-Y.; Chiu, A.T.-G.; Tsang, M.H.-Y.; Lun, K.-S.; Rodenburg, R.J.T.; Smeitink, J.; Chung, B.H.-Y.; Fung, C.-W. A fatal case of COQ7-associated primary coenzyme Q10 deficiency. JIMD Rep. 2019, 47, 23–29. [Google Scholar] [CrossRef] [Scilit]
- Duncan, A.J.; Bitner-Glindzicz, M.; Meunier, B.; Costello, H.; Hargreaves, I.P.; López, L.C.; Hirano, M.; Quinzii, C.M.; Sadowski, M.I.; Hardy, J.; et al. A Nonsense Mutation in COQ9 Causes Autosomal-Recessive Neonatal-Onset Primary Coenzyme Q10 Deficiency: A Potentially Treatable Form of Mitochondrial Disease. Am. J. Hum. Genet. 2009, 84, 558–566. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Danhauser, K.; Herebian, D.; Haack, T.B.; Rodenburg, R.J.; Strom, T.M.; Meitinger, T.; Klee, D.; Mayatepek, E.; Prokisch, H.; Distelmaier, F. Fatal neonatal encephalopathy and lactic acidosis caused by a homozygous loss-of-function variant in COQ9. Eur. J. Hum. Genet. 2016, 24, 450–454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wiessner, M.; Maroofian, R.; Ni, M.-Y.; Pedroni, A.; Müller, J.S.; Stucka, R.; Beetz, C.; Efthymiou, S.; Santorelli, F.M.; Alfares, A.A.; et al. Biallelic variants in HPDL cause pure and complicated hereditary spastic paraplegia. Brain J. Neurol. 2021, 144, 1422–1434. [Google Scholar] [CrossRef] [Scilit]
- Sun, Y.; Wei, X.; Fang, F.; Shen, Y.; Wei, H.; Li, J.; Ye, X.; Zhan, Y.; Ye, X.; Liu, X.; et al. HPDL deficiency causes a neuromuscular disease by impairing the mitochondrial respiration. J. Genet. Genomics 2021, 48, 727–736. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ghosh, S.G.; Lee, S.; Fabunan, R.; Chai, G.; Zaki, M.S.; Abdel-Salam, G.; Sultan, T.; Ben-Omran, T.; Alvi, J.R.; McEvoy-Venneri, J.; et al. Biallelic variants in HPDL, encoding 4-hydroxyphenylpyruvate dioxygenase-like protein, lead to an infantile neurodegenerative condition. Genet. Med. 2021, 23, 524–533. [Google Scholar] [CrossRef] [Scilit]
- Husain, R.A.; Grimmel, M.; Wagner, M.; Hennings, J.C.; Marx, C.; Feichtinger, R.G.; Saadi, A.; Rostásy, K.; Radelfahr, F.; Bevot, A.; et al. Bi-allelic HPDL Variants Cause a Neurodegenerative Disease Ranging from Neonatal Encephalopathy to Adolescent-Onset Spastic Paraplegia. Am. J. Hum. Genet. 2020, 107, 364–373. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baggiani, M.; Damiani, D.; Privitera, F.; Della Vecchia, S.; Tessa, A.; Santorelli, F.M. Generation and Characterization of hiPS Lines from Three Patients Affected by Different Forms of HPDL-Related Neurological Disorders. Int. J. Mol. Sci. 2024, 25, 10614. [Google Scholar] [CrossRef] [Scilit]
- Quinzii, C.; Naini, A.; Salviati, L.; Trevisson, E.; Navas, P.; DiMauro, S.; Hirano, M. A Mutation in Para-Hydroxybenzoate-Polyprenyl Transferase (COQ2) Causes Primary Coenzyme Q10 Deficiency. Am. J. Hum. Genet. 2006, 78, 345–349. [Google Scholar] [CrossRef] [Scilit]
- Hashemi, S.S.; Zare-Abdollahi, D.; Bakhshandeh, M.K.; Vafaee, A.; Abolhasani, S.; Inanloo Rahatloo, K.; DanaeeFard, F.; Farboodi, N.; Rohani, M.; Alavi, A. Clinical spectrum in multiple families with primary COQ10 deficiency. Am. J. Med. Genet. Part A. 2021, 185, 440–452. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Caglayan, A.O.; Gumus, H.; Sandford, E.; Kubisiak, T.L.; Ma, Q.; Ozel, A.B.; Per, H.; Li, J.Z.; Shakkottai, V.G.; Burmeister, M. COQ4 Mutation Leads to Childhood-Onset Ataxia Improved by CoQ10 Administration. Cerebellum 2019, 18, 665–669. [Google Scholar] [CrossRef] [Scilit]
- Traschütz, A.; Schirinzi, T.; Laugwitz, L.; Murray, N.H.; Bingman, C.A.; Reich, S.; Kern, J.; Heinzmann, A.; Vasco, G.; Bertini, E.; et al. Clinico-Genetic, Imaging and Molecular Delineation of COQ8A-Ataxia: A Multicenter Study of 59 Patients. Ann. Neurol. 2020, 88, 251–263. [Google Scholar] [CrossRef] [Scilit]
- Terracciano, A.; Renaldo, F.; Zanni, G.; D’Amico, A.; Pastore, A.; Barresi, S.; Valente, E.M.; Piemonte, F.; Tozzi, G.; Carrozzo, R.; et al. The use of muscle biopsy in the diagnosis of undefined ataxia with cerebellar atrophy in children. Eur. J. Paediatr. Neurol. 2012, 16, 248–256. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Olgac, A.; Öztoprak, Ü.; Kasapkara, Ç.S.; Kılıç, M.; Yüksel, D.; Derinkuyu, E.B.; Taşçı Yıldız, Y.; Ceylaner, S.; Ezgu, F.S. A rare case of primary coenzyme Q10 deficiency due to COQ9 mutation. J. Pediatr. Endocrinol. Metab. JPEM 2020, 33, 165–170. [Google Scholar] [CrossRef] [Scilit]
- Donis, R.; Al Badi, M.; Alhashmi, N.; Hattersley, A.T.; Flanagan, S.E.; De Franco, E. Two cases of neonatal hyperglycemia caused by a homozygous COQ9 stop-gain variant. J. Diabetes Investig. 2025, 16, 959–963. [Google Scholar] [CrossRef] [Scilit]
- Malicdan, M.C.V.; Vilboux, T.; Ben-Zeev, B.; Guo, J.; Eliyahu, A.; Pode-Shakked, B.; Dori, A.; Kakani, S.; Chandrasekharappa, S.C.; Ferreira, C.R.; et al. A novel inborn error of the coenzyme Q10 biosynthesis pathway: Cerebellar ataxia and static encephalomyopathy due to COQ5 C-methyltransferase deficiency. Hum. Mutat. 2018, 39, 69–79. [Google Scholar] [CrossRef] [Scilit]
- Wang, N.; Zheng, Y.; Zhang, L.; Tian, X.; Fang, Y.; Qi, M.; Du, J.; Chen, S.; Chen, S.; Li, J.; et al. A Family Segregating Lethal Primary Coenzyme Q10 Deficiency Due to Two Novel COQ6 Variants. Front. Genet. 2021, 12, 811833. [Google Scholar] [CrossRef] [Scilit]
- Sait, H.; Pandey, M.; Phadke, S.R. COQ7 splice site variant causing a spastic paraparesis phenotype in siblings. J. Genet. 2024, 103, 26. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Habib, C.; Tal, G.; Weiss, K.; Magen, D.; Pollack, S. PDSS1 mutations-associated steroid-resistant nephrotic syndrome: Case report and review of literature. Pediatr. Nephrol. 2025, 40, 1583–1589. [Google Scholar] [CrossRef] [Scilit]
- López, L.C.; Schuelke, M.; Quinzii, C.M.; Kanki, T.; Rodenburg, R.J.T.; Naini, A.; Dimauro, S.; Hirano, M. Leigh syndrome with nephropathy and CoQ10 deficiency due to decaprenyl diphosphate synthase subunit 2 (PDSS2) mutations. Am. J. Hum. Genet. 2006, 79, 1125–1129. [Google Scholar] [CrossRef] [Scilit]
- Mitsui, J.; Koguchi, K.; Momose, T.; Takahashi, M.; Matsukawa, T.; Yasuda, T.; Tokushige, S.-I.; Ishiura, H.; Goto, J.; Nakazaki, S.; et al. Three-Year Follow-Up of High-Dose Ubiquinol Supplementation in a Case of Familial Multiple System Atrophy with Compound Heterozygous COQ2 Mutations. Cerebellum 2017, 16, 664–672. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, Y.; Gumus, E.; Hekimi, S. A novel COQ7 mutation causing primarily neuromuscular pathology and its treatment options. Mol. Genet. Metab. Rep. 2022, 31, 100877. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wei, Q.; Yu, H.; Wang, P.-S.; Xie, J.-J.; Dong, H.-L.; Wu, Z.-Y.; Li, H.-F. Biallelic variants in the COQ4 gene caused hereditary spastic paraplegia predominant phenotype. CNS Neurosci. Ther. 2024, 30, e14529. [Google Scholar] [CrossRef] [Scilit]
- Qiu, Y.; Xiong, Y.; Wang, L.; Zhu, M.; Tan, D.; Hong, D. Homozygous variant in COQ7 causes autosomal recessive hereditary spastic paraplegia. Ann. Clin. Transl. Neurol. 2024, 11, 1067–1074. [Google Scholar] [CrossRef] [Scilit]
- Mollet, J.; Giurgea, I.; Schlemmer, D.; Dallner, G.; Chretien, D.; Delahodde, A.; Bacq, D.; de Lonlay, P.; Munnich, A.; Rötig, A. Prenyldiphosphate synthase, subunit 1 (PDSS1) and OH-benzoate polyprenyltransferase (COQ2) mutations in ubiquinone deficiency and oxidative phosphorylation disorders. J. Clin. Investig. 2007, 117, 765–772. [Google Scholar] [CrossRef] [Scilit]
- Nardecchia, F.; De Giorgi, A.; Palombo, F.; Fiorini, C.; De Negri, A.M.; Carelli, V.; Caporali, L.; Leuzzi, V. Missense PDSS1 mutations in CoenzymeQ10 synthesis cause optic atrophy and sensorineural deafness. Ann. Clin. Transl. Neurol. 2021, 8, 247–251. [Google Scholar] [CrossRef] [Scilit]
- Iványi, B.; Rácz, G.Z.; Gál, P.; Brinyiczki, K.; Bódi, I.; Kalmár, T.; Maróti, Z.; Bereczki, C. Diffuse mesangial sclerosis in a PDSS2 mutation-induced coenzyme Q10 deficiency. Pediatr. Nephrol. 2018, 33, 439–446. [Google Scholar] [CrossRef] [Scilit]
- Bellusci, M.; García-Silva, M.T.; Martínez de Aragón, A.; Martín, M.A. Distal phalangeal erythema in an infant with biallelic PDSS1 mutations: Expanding the phenotype of primary Coenzyme Q10 deficiency. JIMD Rep. 2021, 62, 3–5. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vasta, V.; Merritt, J.L., II; Saneto, R.P.; Hahn, S.H. Next-generation sequencing for mitochondrial diseases: A wide diagnostic spectrum. Pediatr. Int. 2012, 54, 585–601. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Numata-Uematsu, Y.; Uematsu, M.; Yamamoto, T.; Saitsu, H.; Katata, Y.; Oikawa, Y.; Saijyo, N.; Inui, T.; Murayama, K.; Ohtake, A.; et al. Leigh syndrome-like MRI changes in a patient with biallelic HPDL variants treated with ketogenic diet. Mol. Genet. Metab. Rep. 2021, 29, 100800. [Google Scholar] [CrossRef] [Scilit]
- Rebelo, A.P.; Tomaselli, P.J.; Medina, J.; Wang, Y.; Dohrn, M.F.; Nyvltova, E.; Danzi, M.C.; Garrett, M.; Smith, S.E.; Pestronk, A.; et al. Biallelic variants in COQ7 cause distal hereditary motor neuropathy with upper motor neuron signs. Brain 2023, 146, 4191–4199. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, X.; Wang, N.; Chen, Y.; Lv, W.; Hong, J.-M.; Xu, G.-R.; Zhou, L.-Y.; Chen, W.-J.; Fan, D.-S.; He, J. Biallelic variants in the COQ7 gene cause distal hereditary motor neuropathy in two Chinese families. Brain 2023, 146, e27–e30. [Google Scholar] [CrossRef] [Scilit]
- Zhang, X.-Y.; Dong, H.-L.; Wu, Z.-Y. Axonal Charcot-Marie-Tooth disease due to COQ7 mutation: Expanding the genetic and clinical spectrum. Brain 2023, 146, e117–e119. [Google Scholar] [CrossRef] [Scilit]
- Jurkute, N.; Cancellieri, F.; Pohl, L.; Li, C.H.Z.; Heaton, R.A.; Reurink, J.; Bellingham, J.; Quinodoz, M.; Yioti, G.; Stefaniotou, M.; et al. Biallelic variants in coenzyme Q10 biosynthesis pathway genes cause a retinitis pigmentosa phenotype. npj Genom. Med. 2022, 7, 60. [Google Scholar] [CrossRef] [Scilit]
- Horvath, R.; Czermin, B.; Gulati, S.; Demuth, S.; Houge, G.; Pyle, A.; Dineiger, C.; Blakely, E.L.; Hassani, A.; Foley, C.; et al. Adult-onset cerebellar ataxia due to mutations in CABC1/ADCK3. J. Neurol. Neurosurg. Psychiatry 2012, 83, 174–178. [Google Scholar] [CrossRef] [Scilit]
- Barca, E.; Musumeci, O.; Montagnese, F.; Marino, S.; Granata, F.; Nunnari, D.; Peverelli, L.; DiMauro, S.; Quinzii, C.M.; Toscano, A. Cerebellar ataxia and severe muscle CoQ10 deficiency in a patient with a novel mutation in ADCK3. Clin. Genet. 2016, 90, 156–160. [Google Scholar] [CrossRef] [Scilit]
- Ashraf, S.; Gee, H.Y.; Woerner, S.; Xie, L.X.; Vega-Warner, V.; Lovric, S.; Fang, H.; Song, X.; Cattran, D.C.; Avila-Casado, C.; et al. ADCK4 mutations promote steroid-resistant nephrotic syndrome through CoQ10 biosynthesis disruption. J. Clin. Investig. 2013, 123, 5179–5189. [Google Scholar] [CrossRef] [Scilit]
- Feng, C.; Wang, Q.; Wang, J.; Liu, F.; Shen, H.; Fu, H.; Mao, J. Coenzyme Q10 supplementation therapy for 2 children with proteinuria renal disease and ADCK4 mutation: Case reports and literature review. Medicine 2017, 96, e8880. [Google Scholar] [CrossRef] [Scilit]
- Wang, F.; Zhang, Y.; Mao, J.; Yu, Z.; Yi, Z.; Yu, L.; Sun, J.; Wei, X.; Ding, F.; Zhang, H.; et al. Spectrum of mutations in Chinese children with steroid-resistant nephrotic syndrome. Pediatr. Nephrol. 2017, 32, 1181–1192. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, J.; Yang, Y.; Hu, Z. A novel ADCK4 mutation in a Chinese family with ADCK4-Associated glomerulopathy. Biochem. Biophys. Res. Commun. 2018, 506, 444–449. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhai, S.; Zhang, L.; Sun, B.; Zhang, Y.; Ma, Q. Early-onset COQ8B (ADCK4) glomerulopathy in a child with isolated proteinuria: A case report and literature review. BMC Nephrol. 2020, 21, 406. [Google Scholar] [CrossRef] [Scilit]
- Abdelhakim, A.H.; Dharmadhikari, A.V.; Ragi, S.D.; de Carvalho, J.R.L.; Xu, C.L.; Thomas, A.L.; Buchovecky, C.M.; Mansukhani, M.M.; Naini, A.B.; Liao, J.; et al. Compound heterozygous inheritance of two novel COQ2 variants results in familial coenzyme Q deficiency. Orphanet J. Rare Dis. 2020, 15, 320. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gigante, M.; Diella, S.; Santangelo, L.; Trevisson, E.; Acosta, M.J.; Amatruda, M.; Finzi, G.; Caridi, G.; Murer, L.; Accetturo, M.; et al. Further phenotypic heterogeneity of CoQ10 deficiency associated with steroid resistant nephrotic syndrome and novel COQ2 and COQ6 variants. Clin. Genet. 2017, 92, 224–226. [Google Scholar] [CrossRef] [Scilit]
- Justine Perrin, R.; Rousset-Rouvière, C.; Garaix, F.; Cano, A.; Conrath, J.; Boyer, O.; Tsimaratos, M. COQ6 mutation in patients with nephrotic syndrome, sensorineural deafness, and optic atrophy. JIMD Rep. 2020, 54, 37–44. [Google Scholar] [CrossRef] [Scilit]
- Yuruk Yildirim, Z.; Toksoy, G.; Uyguner, O.; Nayir, A.; Yavuz, S.; Altunoglu, U.; Turkkan, O.N.; Sevinc, B.; Gokcay, G.; Kurkcu Gunes, D.; et al. Primary coenzyme Q10 Deficiency-6 (COQ10D6): Two siblings with variable expressivity of the renal phenotype. Eur. J. Med. Genet. 2020, 63, 103621. [Google Scholar] [CrossRef] [Scilit]
- Li, M.; Yue, Z.; Lin, H.; Wang, H.; Chen, H.; Sun, L. COQ2 mutation associated isolated nephropathy in two siblings from a Chinese pedigree. Ren. Fail. 2021, 43, 97–101. [Google Scholar] [CrossRef] [Scilit]
- Kurata, K.; Hosono, K.; Takayama, M.; Katsuno, M.; Saitsu, H.; Ogata, T.; Hotta, Y. Retinitis pigmentosa with optic neuropathy and COQ2 mutations: A case report. Am. J. Ophthalmol. Case Rep. 2022, 25, 101298. [Google Scholar] [CrossRef] [Scilit]
- Heiduschka, S.; Prigione, A. iPSC models of mitochondrial diseases. Neurobiol. Dis. 2025, 207, 106822. [Google Scholar] [CrossRef] [Scilit]
- Romero-Moya, D.; Castaño, J.; Santos-Ocaña, C.; Navas, P.; Menendez, P. Generation, genome edition and characterization of iPSC lines from a patient with coenzyme Q 10 deficiency harboring a heterozygous mutation in COQ4 gene. Stem Cell Res. 2017, 24, 144–147. [Google Scholar] [CrossRef] [Scilit]
- Nakamoto, F.K.; Okamoto, S.; Mitsui, J.; Sone, T.; Ishikawa, M.; Yamamoto, Y.; Kanegae, Y.; Nakatake, Y.; Imaizumi, K.; Ishiura, H.; et al. The pathogenesis linked to coenzyme Q10 insufficiency in iPSC-derived neurons from patients with multiple-system atrophy. Sci. Rep. 2018, 8, 14215. [Google Scholar] [CrossRef] [Scilit]
- Alcázar-Fabra, M.; Navas, P.; Brea-Calvo, G. Coenzyme Q biosynthesis and its role in the respiratory chain structure. Biochim. Biophys. Acta (BBA)-Bioenerg. 2016, 1857, 1073–1078. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bentinger, M.; Tekle, M.; Dallner, G. Coenzyme Q-biosynthesis and functions. Biochem. Biophys. Res. Commun. 2010, 396, 74–79. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wirth, C.; Brandt, U.; Hunte, C.; Zickermann, V. Structure and function of mitochondrial complex I. Biochim. Biophys. Acta (BBA)-Bioenerg. 2016, 1857, 902–914. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fullerton, M.; McFarland, R.; Taylor, R.W.; Alston, C.L. The genetic basis of isolated mitochondrial complex II deficiency. Mol. Genet. Metab. 2020, 131, 53–65. [Google Scholar] [CrossRef] [Scilit]
- Cramer, W.A.; Hasan, S.S.; Yamashita, E. The Q cycle of cytochrome bc complexes: A structure perspective. Biochim. Biophys. Acta (BBA)-Bioenerg. 2011, 1807, 788–802. [Google Scholar] [CrossRef] [Scilit]
- Kadenbach, B. Complex IV—The regulatory center of mitochondrial oxidative phosphorylation. Mitochondrion 2021, 58, 296–302. [Google Scholar] [CrossRef] [Scilit]
- Neupane, P.; Bhuju, S.; Thapa, N.; Bhattarai, H.K. ATP Synthase: Structure, Function and Inhibition. Biomol. Concepts 2019, 10, 1–10. [Google Scholar] [CrossRef] [Scilit]
- Enriquez, J.A.; Lenaz, G. Coenzyme Q and the Respiratory Chain: Coenzyme Q Pool and Mitochondrial Supercomplexes. Mol. Syndromol. 2014, 5, 119–140. [Google Scholar] [CrossRef] [Scilit]
- Hackenbrock, C.R.; Chazotte, B.; Gupte, S.S. The random collision model and a critical assessment of diffusion and collision in mitochondrial electron transport. J. Bioenerg. Biomembr. 1986, 18, 331–368. [Google Scholar] [CrossRef] [Scilit]
- Caruana, N.J.; Stroud, D.A. The road to the structure of the mitochondrial respiratory chain supercomplex. Biochem. Soc. Trans. 2020, 48, 621–629. [Google Scholar] [CrossRef] [Scilit]
- Genova, M.L.; Lenaz, G. Functional role of mitochondrial respiratory supercomplexes. Biochim. Biophys. Acta (BBA)-Bioenerg. 2014, 1837, 427–443. [Google Scholar] [CrossRef] [Scilit]
- Acin-Perez, R.; Enriquez, J.A. The function of the respiratory supercomplexes: The plasticity model. Biochim. Biophys. Acta (BBA)-Bioenerg. 2014, 1837, 444–450. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bravo-Alonso, I.; Navarrete, R.; Vega, A.I.; Ruíz-Sala, P.; García Silva, M.T.; Martín-Hernández, E.; Quijada-Fraile, P.; Belanger-Quintana, A.; Stanescu, S.; Bueno, M.; et al. Genes and Variants Underlying Human Congenital Lactic Acidosis—From Genetics to Personalized Treatment. J. Clin. Med. 2019, 8, 1811. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Quinzii, C.M.; López, L.C.; Gilkerson, R.W.; Dorado, B.; Coku, J.; Naini, A.B.; Lagier-Tourenne, C.; Schuelke, M.; Salviati, L.; Carrozzo, R.; et al. Reactive oxygen species, oxidative stress, and cell death correlate with level of CoQ10 deficiency. FASEB J. 2010, 24, 3733–3743. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Henriques, B.J.; Katrine Jentoft Olsen, R.; Gomes, C.M.; Bross, P. Electron transfer flavoprotein and its role in mitochondrial energy metabolism in health and disease. Gene 2021, 776, 145407. [Google Scholar] [CrossRef] [Scilit]
- Penicaud, R.; Ferron, J.; Valette, X.; Bauduin, P.; Faisant, M.; Schiff, M.; Nguyen, A.; Fontaine, F.; Allouche, S. Late-Onset Multiple Acyl-CoA Dehydrogenase Deficiency (MADD): A Case Report with a Complex Biochemical Profile. JIMD Rep. 2025, 66, e70035. [Google Scholar] [CrossRef] [Scilit]
- Gempel, K.; Topaloglu, H.; Talim, B.; Schneiderat, P.; Schoser, B.G.H.; Hans, V.H.; Pálmafy, B.; Kale, G.; Tokatli, A.; Quinzii, C.; et al. The myopathic form of coenzyme Q10 deficiency is caused by mutations in the electron-transferring-flavoprotein dehydrogenase (ETFDH) gene. Brain J. Neurol. 2007, 130, 2037–2044. [Google Scholar] [CrossRef] [Scilit]
- Turton, N.; Cufflin, N.; Dewsbury, M.; Fitzpatrick, O.; Islam, R.; Watler, L.L.; McPartland, C.; Whitelaw, S.; Connor, C.; Morris, C.; et al. The Biochemical Assessment of Mitochondrial Respiratory Chain Disorders. Int. J. Mol. Sci. 2022, 23, 7487. [Google Scholar] [CrossRef] [Scilit]
- Desbats, M.A.; Vetro, A.; Limongelli, I.; Lunardi, G.; Casarin, A.; Doimo, M.; Spinazzi, M.; Angelini, C.; Cenacchi, G.; Burlina, A.; et al. Primary coenzyme Q10 deficiency presenting as fatal neonatal multiorgan failure. Eur. J. Hum. Genet. EJHG 2015, 23, 1254–1258. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Trevisson, E.; DiMauro, S.; Navas, P.; Salviati, L. Coenzyme Q deficiency in muscle. Curr. Opin. Neurol. 2011, 24, 449–456. [Google Scholar] [CrossRef] [Scilit]
- Hernández-Camacho, J.D.; Vicente-García, C.; Ardila-García, L.; Padilla-Campos, A.; López-Lluch, G.; Santos-Ocaña, C.; Zammit, P.S.; Carvajal, J.J.; Navas, P.; Fernández-Ayala, D.J.M. Prenatal and progressive coenzyme Q10 administration to mitigate muscle dysfunction in mitochondrial disease. J. Cachexia Sarcopenia Muscle 2024, 15, 2402–2416. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ziosi, M.; Di Meo, I.; Kleiner, G.; Gao, X.-H.; Barca, E.; Sanchez-Quintero, M.J.; Tadesse, S.; Jiang, H.; Qiao, C.; Rodenburg, R.J.; et al. Coenzyme Q deficiency causes impairment of the sulfide oxidation pathway. EMBO Mol. Med. 2017, 9, 96–111. [Google Scholar] [CrossRef] [Scilit]
- Mráček, T.; Drahota, Z.; Houštěk, J. The function and the role of the mitochondrial glycerol-3-phosphate dehydrogenase in mammalian tissues. Biochim. Biophys. Acta (BBA)-Bioenerg. 2013, 1827, 401–410. [Google Scholar] [CrossRef] [Scilit]
- Pesini, A.; Barriocanal-Casado, E.; Compagnoni, G.M.; Hidalgo-Gutierrez, A.; Yanez, G.; Bakkali, M.; Chhonker, Y.S.; Kleiner, G.; Larrea, D.; Tadesse, S.; et al. Coenzyme Q10 deficiency disrupts lipid metabolism by altering cholesterol homeostasis in neurons. Free Radic. Biol. Med. 2025, 229, 441–457. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Löffler, M.; Jöckel, J.; Schuster, G.; Becker, C. Dihydroorotat-ubiquinone oxidoreductase links mitochondria in the biosynthesis of pyrimidine nucleotides. Mol. Cell. Biochem. 1997, 174, 125–129. [Google Scholar] [CrossRef] [Scilit]
- Boukalova, S.; Hubackova, S.; Milosevic, M.; Ezrova, Z.; Neuzil, J.; Rohlena, J. Dihydroorotate dehydrogenase in oxidative phosphorylation and cancer. Biochim. Biophys. Acta (BBA)-Mol. Basis Dis. 2020, 1866, 165759. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- King, M.P.; Attardi, G. Human cells lacking mtDNA: Repopulation with exogenous mitochondria by complementation. Science 1989, 246, 500–503. [Google Scholar] [CrossRef] [Scilit]
- López-Martín, J.M.; Salviati, L.; Trevisson, E.; Montini, G.; DiMauro, S.; Quinzii, C.; Hirano, M.; Rodriguez-Hernandez, A.; Cordero, M.D.; Sánchez-Alcázar, J.A.; et al. Missense mutation of the COQ2 gene causes defects of bioenergetics and de novo pyrimidine synthesis. Hum. Mol. Genet. 2007, 16, 1091–1097. [Google Scholar] [CrossRef] [Scilit]
- Montero, R.; Sánchez-Alcázar, J.A.; Briones, P.; Navarro-Sastre, A.; Gallardo, E.; Bornstein, B.; Herrero-Martín, D.; Rivera, H.; Martin, M.A.; Marti, R.; et al. Coenzyme Q10 deficiency associated with a mitochondrial DNA depletion syndrome: A case report. Clin. Biochem. 2009, 42, 742–745. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.; Hekimi, S. Minimal mitochondrial respiration is required to prevent cell death by inhibition of mTOR signaling in CoQ-deficient cells. Cell Death Discov. 2021, 7, 201. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van Roey, V.L.; Ombashi, S.; Kaymaz, I.; van Dooren, M.F.; Goverde, A.; Wolvius, E.B.; Mathijssen, I.M.J.; Versnel, S.L. Unveiling the Phenotypic Spectrum of Miller Syndrome: A Systematic Review. J. Craniofac. Surg. 2025, 36, e1243–e1247. [Google Scholar] [CrossRef] [Scilit]
- Servet, C.; Ghelis, T.; Richard, L.; Zilberstein, A.; Savoure, A. Proline dehydrogenase: A key enzyme in controlling cellular homeostasis. Front. Biosci. 2012, 17, 607–620. [Google Scholar] [CrossRef] [Scilit]
- Pallag, G.; Nazarian, S.; Ravasz, D.; Bui, D.; Komlódi, T.; Doerrier, C.; Gnaiger, E.; Seyfried, T.N.; Chinopoulos, C. Proline Oxidation Supports Mitochondrial ATP Production When Complex I Is Inhibited. Int. J. Mol. Sci. 2022, 23, 5111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Phang, J.M. The regulatory mechanisms of proline and hydroxyproline metabolism: Recent advances in perspective. Front. Oncol. 2022, 12, 1118675. [Google Scholar] [CrossRef] [Scilit]
- Baschiera, E.; Sorrentino, U.; Calderan, C.; Desbats, M.A.; Salviati, L. The multiple roles of coenzyme Q in cellular homeostasis and their relevance for the pathogenesis of coenzyme Q deficiency. Free Radic. Biol. Med. 2021, 166, 277–286. [Google Scholar] [CrossRef] [Scilit]
- Salvi, F.; Gadda, G. Human choline dehydrogenase: Medical promises and biochemical challenges. Arch. Biochem. Biophys. 2013, 537, 243–252. [Google Scholar] [CrossRef] [Scilit]
- Steane, S.E.; Kumar, V.; Cuffe, J.S.M.; Moritz, K.M.; Akison, L.K. Prenatal Choline Supplementation Alters One Carbon Metabolites in a Rat Model of Periconceptional Alcohol Exposure. Nutrients 2022, 14, 1874. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.; Shen, X.; Yang, X.; Lian, F.; Li, Y.; Li, J.; Huang, Y.; Shen, W.; Liu, H. CHDH, a key mitochondrial enzyme, plays a diagnostic role in metabolic disorders diseases and tumor progression. Front. Genet. 2023, 14, 1240650. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, S.; Choi, S.-G.; Yoo, S.-M.; Son, J.H.; Jung, Y.-K. Choline dehydrogenase interacts with SQSTM1/p62 to recruit LC3 and stimulate mitophagy. Autophagy 2014, 10, 1906–1920. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Libiad, M.; Yadav, P.K.; Vitvitsky, V.; Martinov, M.; Banerjee, R. Organization of the human mitochondrial hydrogen sulfide oxidation pathway. J. Biol. Chem. 2014, 289, 30901–30910. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jackson, M.R.; Melideo, S.L.; Jorns, M.S. Human sulfide:quinone oxidoreductase catalyzes the first step in hydrogen sulfide metabolism and produces a sulfane sulfur metabolite. Biochemistry 2012, 51, 6804–6815. [Google Scholar] [CrossRef] [Scilit]
- Hildebrandt, T.M.; Grieshaber, M.K. Three enzymatic activities catalyze the oxidation of sulfide to thiosulfate in mammalian and invertebrate mitochondria. FEBS J. 2008, 275, 3352–3361. [Google Scholar] [CrossRef] [Scilit]
- Quinzii, C.M.; Luna-Sanchez, M.; Ziosi, M.; Hidalgo-Gutierrez, A.; Kleiner, G.; Lopez, L.C. The Role of Sulfide Oxidation Impairment in the Pathogenesis of Primary CoQ Deficiency. Front. Physiol. 2017, 8, 525. [Google Scholar] [CrossRef] [Scilit]
- Luna-Sánchez, M.; Hidalgo-Gutiérrez, A.; Hildebrandt, T.M.; Chaves-Serrano, J.; Barriocanal-Casado, E.; Santos-Fandila, Á.; Romero, M.; Sayed, R.K.; Duarte, J.; Prokisch, H.; et al. CoQ deficiency causes disruption of mitochondrial sulfide oxidation, a new pathomechanism associated with this syndrome. EMBO Mol. Med. 2017, 9, 78–95. [Google Scholar] [CrossRef] [Scilit]
- Paul, B.D.; Snyder, S.H.; Kashfi, K. Effects of hydrogen sulfide on mitochondrial function and cellular bioenergetics. Redox Biol. 2021, 38, 101772. [Google Scholar] [CrossRef] [Scilit]
- Quinzii, C.M.; Lopez, L.C. Abnormalities of hydrogen sulfide and glutathione pathways in mitochondrial dysfunction. J. Adv. Res. 2021, 27, 79–84. [Google Scholar] [CrossRef] [Scilit]
- Filomeni, G.; De Zio, D.; Cecconi, F. Oxidative stress and autophagy: The clash between damage and metabolic needs. Cell Death Differ. 2015, 22, 377–388. [Google Scholar] [CrossRef] [Scilit]
- Mailloux, R.J. An Update on Mitochondrial Reactive Oxygen Species Production. Antioxidants 2020, 9, 472. [Google Scholar] [CrossRef] [Scilit]
- Rendra, E.; Riabov, V.; Mossel, D.M.; Sevastyanova, T.; Harmsen, M.C.; Kzhyshkowska, J. Reactive oxygen species (ROS) in macrophage activation and function in diabetes. Immunobiology 2019, 224, 242–253. [Google Scholar] [CrossRef] [Scilit]
- Imlay, J.A.; Linn, S. DNA damage and oxygen radical toxicity. Science 1988, 240, 1302–1309. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Halliwell, B. Biochemical mechanisms accounting for the toxic action of oxygen on living organisms: The key role of superoxide dismutase. Cell Biol. Int. Rep. 1978, 2, 113–128. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davies, K.J.; Lin, S.W.; Pacifici, R.E. Protein damage and degradation by oxygen radicals. IV. Degradation of denatured protein. J. Biol. Chem. 1987, 262, 9914–9920. [Google Scholar] [CrossRef] [Scilit]
- Gaschler, M.M.; Stockwell, B.R. Lipid peroxidation in cell death. Biochem. Biophys. Res. Commun. 2017, 482, 419–425. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, W.; Porter, N.A.; Schneider, C.; Brash, A.R.; Yin, H. Formation of 4-hydroxynonenal from cardiolipin oxidation: Intramolecular peroxyl radical addition and decomposition. Free Radic. Biol. Med. 2011, 50, 166–178. [Google Scholar] [CrossRef] [Scilit]
- Paradies, G.; Paradies, V.; Ruggiero, F.M.; Petrosillo, G. Oxidative stress, cardiolipin and mitochondrial dysfunction in nonalcoholic fatty liver disease. World J. Gastroenterol. 2014, 20, 14205–14218. [Google Scholar] [CrossRef] [Scilit]
- Ghosh, S.; Iadarola, D.M.; Ball, W.B.; Gohil, V.M. Mitochondrial dysfunctions in barth syndrome. IUBMB Life 2019, 71, 791–801. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dixon, S.J.; Lemberg, K.M.; Lamprecht, M.R.; Skouta, R.; Zaitsev, E.M.; Gleason, C.E.; Patel, D.N.; Bauer, A.J.; Cantley, A.M.; Yang, W.S.; et al. Ferroptosis: An iron-dependent form of nonapoptotic cell death. Cell 2012, 149, 1060–1072. [Google Scholar] [CrossRef] [Scilit]
- Lyamzaev, K.G.; Panteleeva, A.A.; Simonyan, R.A.; Avetisyan, A.V.; Chernyak, B.V. Mitochondrial Lipid Peroxidation Is Responsible for Ferroptosis. Cells 2023, 12, 611. [Google Scholar] [CrossRef] [Scilit]
- Garcia-Llorens, G.; El Ouardi, M.; Valls-Belles, V. Oxidative Stress Fundamentals: Unraveling the Pathophysiological Role of Redox Imbalance in Non-Communicable Diseases. Appl. Sci. 2025, 15, 10191. [Google Scholar] [CrossRef] [Scilit]
- Curtis, J.M.; Hahn, W.S.; Stone, M.D.; Inda, J.J.; Droullard, D.J.; Kuzmicic, J.P.; Donoghue, M.A.; Long, E.K.; Armien, A.G.; Lavandero, S.; et al. Protein carbonylation and adipocyte mitochondrial function. J. Biol. Chem. 2012, 287, 32967–32980. [Google Scholar] [CrossRef] [Scilit]
- Reddy, V.P. Oxidative Stress in Health and Disease. Biomedicines 2023, 11, 2925. [Google Scholar] [CrossRef] [Scilit]
- Han, Y.; Chen, J.Z. Oxidative stress induces mitochondrial DNA damage and cytotoxicity through independent mechanisms in human cancer cells. BioMed Res. Int. 2013, 2013, 825065. [Google Scholar] [CrossRef] [Scilit]
- Gibbs, E.T.; Lerner, C.A.; Watson, M.A.; Wong, H.-S.; Gerencser, A.A.; Brand, M.D. Site IQ in mitochondrial complex I generates S1QEL-sensitive superoxide/hydrogen peroxide in both the reverse and forward reactions. Biochem. J. 2023, 480, 363–384. [Google Scholar] [CrossRef] [Scilit]
- Zhao, R.-Z.; Jiang, S.; Zhang, L.; Yu, Z.-B. Mitochondrial electron transport chain, ROS generation and uncoupling (Review). Int. J. Mol. Med. 2019, 44, 3–15. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guarás, A.; Perales-Clemente, E.; Calvo, E.; Acín-Pérez, R.; Loureiro-Lopez, M.; Pujol, C.; Martínez-Carrascoso, I.; Nuñez, E.; García-Marqués, F.; Rodríguez-Hernández, M.A.; et al. The CoQH2/CoQ Ratio Serves as a Sensor of Respiratory Chain Efficiency. Cell Rep. 2016, 15, 197–209. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zorov, D.B.; Juhaszova, M.; Sollott, S.J. Mitochondrial reactive oxygen species (ROS) and ROS-induced ROS release. Physiol. Rev. 2014, 94, 909–950. [Google Scholar] [CrossRef] [Scilit]
- Birben, E.; Sahiner, U.M.; Sackesen, C.; Erzurum, S.; Kalayci, O. Oxidative Stress and Antioxidant Defense. World Allergy Organ. J. 2012, 5, 9–19. [Google Scholar] [CrossRef] [Scilit]
- Pei, J.; Pan, X.; Wei, G.; Hua, Y. Research progress of glutathione peroxidase family (GPX) in redoxidation. Front. Pharmacol. 2023, 14, 1147414. [Google Scholar] [CrossRef] [Scilit]
- Brigelius-Flohé, R.; Maiorino, M. Glutathione peroxidases. Biochim. Biophys. Acta (BBA)-Gen. Subj. 2013, 1830, 3289–3303. [Google Scholar] [CrossRef] [Scilit]
- Xie, Y.; Kang, R.; Klionsky, D.J.; Tang, D. GPX4 in cell death, autophagy, and disease. Autophagy 2023, 19, 2621–2638. [Google Scholar] [CrossRef] [Scilit]
- Fradejas, N.; Carlson, B.A.; Rijntjes, E.; Becker, N.-P.; Tobe, R.; Schweizer, U. Mammalian Trit1 is a tRNA([Ser]Sec)-isopentenyl transferase required for full selenoprotein expression. Biochem. J. 2013, 450, 427–432. [Google Scholar] [CrossRef] [Scilit]
- Vašková, J.; Kočan, L.; Vaško, L.; Perjési, P. Glutathione-Related Enzymes and Proteins: A Review. Molecules 2023, 28, 1447. [Google Scholar] [CrossRef] [Scilit]
- Ly, J.D.; Lawen, A. Transplasma membrane electron transport: Enzymes involved and biological function. Redox Rep. Commun. Free Radic. Res. 2003, 8, 3–21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Del Principe, D.; Avigliano, L.; Savini, I.; Catani, M.V. Trans-plasma membrane electron transport in mammals: Functional significance in health and disease. Antioxid. Redox Signal. 2011, 14, 2289–2318. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ross, D.; Siegel, D. The diverse functionality of NQO1 and its roles in redox control. Redox Biol. 2021, 41, 101950. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Santoro, M.M. The Antioxidant Role of Non-mitochondrial CoQ10: Mystery Solved! Cell Metab. 2020, 31, 13–15. [Google Scholar] [CrossRef] [Scilit]
- Merker, M.P.; Bongard, R.D.; Kettenhofen, N.J.; Okamoto, Y.; Dawson, C.A. Intracellular redox status affects transplasma membrane electron transport in pulmonary arterial endothelial cells. Am. J. Physiol. Lung Cell. Mol. Physiol. 2002, 282, L36–L43. [Google Scholar] [CrossRef] [Scilit]
- Hyun, D.-H.; Hernandez, J.O.; Mattson, M.P.; de Cabo, R. The plasma membrane redox system in aging. Ageing Res. Rev. 2006, 5, 209–220. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cao, J.; Chen, X.; Chen, L.; Lu, Y.; Wu, Y.; Deng, A.; Pan, F.; Huang, H.; Liu, Y.; Li, Y.; et al. DHODH-mediated mitochondrial redox homeostasis: A novel ferroptosis regulator and promising therapeutic target. Redox Biol. 2025, 85, 103788. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, J.; Roh, J.-L. Dihydroorotate Dehydrogenase in Mitochondrial Ferroptosis and Cancer Therapy. Cells 2025, 14, 1889. [Google Scholar] [CrossRef] [Scilit]
- Mao, C.; Liu, X.; Zhang, Y.; Lei, G.; Yan, Y.; Lee, H.; Koppula, P.; Wu, S.; Zhuang, L.; Fang, B.; et al. DHODH-mediated ferroptosis defence is a targetable vulnerability in cancer. Nature 2021, 593, 586–590. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ahola, S.; Langer, T. Ferroptosis in mitochondrial cardiomyopathy. Trends Cell Biol. 2024, 34, 150–160. [Google Scholar] [CrossRef] [Scilit]
- López, L.C.; Luna-Sánchez, M.; García-Corzo, L.; Quinzii, C.M.; Hirano, M. Pathomechanisms in Coenzyme Q10-Deficient Human Fibroblasts. Mol. Syndromol. 2014, 5, 163–169. [Google Scholar] [CrossRef] [Scilit]
- Quinzii, C.M.; López, L.C.; Von-Moltke, J.; Naini, A.; Krishna, S.; Schuelke, M.; Salviati, L.; Navas, P.; DiMauro, S.; Hirano, M. Respiratory chain dysfunction and oxidative stress correlate with severity of primary CoQ10 deficiency. FASEB J. 2008, 22, 1874–1885. [Google Scholar] [CrossRef] [Scilit]
- Quinzii, C.M.; Tadesse, S.; Naini, A.; Hirano, M. Effects of inhibiting CoQ10 biosynthesis with 4-nitrobenzoate in human fibroblasts. PLoS ONE 2012, 7, e30606. [Google Scholar] [CrossRef] [Scilit]
- Quinzii, C.M.; Garone, C.; Emmanuele, V.; Tadesse, S.; Krishna, S.; Dorado, B.; Hirano, M. Tissue-specific oxidative stress and loss of mitochondria in CoQ-deficient Pdss2 mutant mice. FASEB J. 2013, 27, 612–621. [Google Scholar] [CrossRef] [Scilit]
- Almannai, M.; El-Hattab, A.W.; Ali, M.; Soler-Alfonso, C.; Scaglia, F. Clinical trials in mitochondrial disorders, an update. Mol. Genet. Metab. 2020, 131, 1–13. [Google Scholar] [CrossRef] [Scilit]
- Ding, W.-X.; Yin, X.-M. Mitophagy: Mechanisms, pathophysiological roles, and analysis. Biol. Chem. 2012, 393, 547–564. [Google Scholar] [CrossRef] [Scilit]
- Malpartida, A.B.; Williamson, M.; Narendra, D.P.; Wade-Martins, R.; Ryan, B.J. Mitochondrial Dysfunction and Mitophagy in Parkinson’s Disease: From Mechanism to Therapy. Trends Biochem. Sci. 2021, 46, 329–343. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bravo-San Pedro, J.M.; Kroemer, G.; Galluzzi, L. Autophagy and Mitophagy in Cardiovascular Disease. Circ. Res. 2017, 120, 1812–1824. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, J.-L.; Mukda, S.; Chen, S.-D. Diverse roles of mitochondria in ischemic stroke. Redox Biol. 2018, 16, 263–275. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Han, R.; Liu, Y.; Li, S.; Li, X.-J.; Yang, W. PINK1-PRKN mediated mitophagy: Differences between in vitro and in vivo models. Autophagy 2023, 19, 1396–1405. [Google Scholar] [CrossRef] [Scilit]
- Liu, H.; Zang, C.; Yuan, F.; Ju, C.; Shang, M.; Ning, J.; Yang, Y.; Ma, J.; Li, G.; Bao, X.; et al. The role of FUNDC1 in mitophagy, mitochondrial dynamics and human diseases. Biochem. Pharmacol. 2022, 197, 114891. [Google Scholar] [CrossRef] [Scilit]
- Rodríguez-Hernández, Á.; Cordero, M.D.; Salviati, L.; Artuch, R.; Pineda, M.; Briones, P.; Gómez Izquierdo, L.; Cotán, D.; Navas, P.; Sánchez-Alcázar, J.A. Coenzyme Q deficiency triggers mitochondria degradation by mitophagy. Autophagy 2009, 5, 19–32. [Google Scholar] [CrossRef] [Scilit]
- Danese, A.; Patergnani, S.; Maresca, A.; Peron, C.; Raimondi, A.; Caporali, L.; Marchi, S.; La Morgia, C.; Del Dotto, V.; Zanna, C.; et al. Pathological mitophagy disrupts mitochondrial homeostasis in Leber’s hereditary optic neuropathy. Cell Rep. 2022, 40, 111124. [Google Scholar] [CrossRef] [Scilit]
- Grazioli, S.; Pugin, J. Mitochondrial Damage-Associated Molecular Patterns: From Inflammatory Signaling to Human Diseases. Front. Immunol. 2018, 9, 832. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gurung, P.; Lukens, J.R.; Kanneganti, T.-D. Mitochondria: Diversity in the regulation of the NLRP3 inflammasome. Trends Mol. Med. 2015, 21, 193–201. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hu, M.-M.; Shu, H.-B. Mitochondrial DNA-triggered innate immune response: Mechanisms and diseases. Cell. Mol. Immunol. 2023, 20, 1403–1412. [Google Scholar] [CrossRef] [Scilit]
- Cordero, M.D.; Alcocer-Gómez, E.; Culic, O.; Carrión, A.M.; de Miguel, M.; Díaz-Parrado, E.; Pérez-Villegas, E.M.; Bullón, P.; Battino, M.; Sánchez-Alcazar, J.A. NLRP3 Inflammasome Is Activated in Fibromyalgia: The Effect of Coenzyme Q10. Antioxid. Redox Signal. 2014, 20, 1169–1180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hseu, Y.-C.; Tseng, Y.-F.; Pandey, S.; Shrestha, S.; Lin, K.-Y.; Lin, C.-W.; Lee, C.-C.; Huang, S.-T.; Yang, H.-L. Coenzyme Q0 Inhibits NLRP3 Inflammasome Activation through Mitophagy Induction in LPS/ATP-Stimulated Macrophages. Oxidative Med. Cell. Longev. 2022, 2022, 4266214. [Google Scholar] [CrossRef] [Scilit]
- Liang, Y.; Han, Y.; Xiao, L.; Su, Y.; Bao, T.; Ji, X.; Jia, L.; Zhang, J. Coenzyme Q10 modulates the immunity by enhancing mononuclear macrophage, NK cell activity, and regulating gut microbiota. Front. Nutr. 2025, 12, 1504831. [Google Scholar] [CrossRef] [Scilit]
- Forrester, S.J.; Kikuchi, D.S.; Hernandes, M.S.; Xu, Q.; Griendling, K.K. Reactive Oxygen Species in Metabolic and Inflammatory Signaling. Circ. Res. 2018, 122, 877–902. [Google Scholar] [CrossRef] [Scilit]
- Chakraborty, K.; Raundhal, M.; Chen, B.B.; Morse, C.; Tyurina, Y.Y.; Khare, A.; Oriss, T.B.; Huff, R.; Lee, J.S.; St Croix, C.M.; et al. The mito-DAMP cardiolipin blocks IL-10 production causing persistent inflammation during bacterial pneumonia. Nat. Commun. 2017, 8, 13944. [Google Scholar] [CrossRef] [Scilit]
- Bhatia, M.; Gaddam, R.R. Hydrogen Sulfide in Inflammation: A Novel Mediator and Therapeutic Target. Antioxid. Redox Signal. 2021, 34, 1368–1377. [Google Scholar] [CrossRef] [Scilit]
- Luna-Sánchez, M.; Díaz-Casado, E.; Barca, E.; Tejada, M.Á.; Montilla-García, Á.; Cobos, E.J.; Escames, G.; Acuña-Castroviejo, D.; Quinzii, C.M.; López, L.C. The clinical heterogeneity of coenzyme Q10 deficiency results from genotypic differences in the Coq9 gene. EMBO Mol. Med. 2015, 7, 670–687. [Google Scholar] [CrossRef] [Scilit]
- Zelko, I.N.; Mariani, T.J.; Folz, R.J. Superoxide dismutase multigene family: A comparison of the CuZn-SOD (SOD1), Mn-SOD (SOD2), and EC-SOD (SOD3) gene structures, evolution, and expression. Free Radic. Biol. Med. 2002, 33, 337–349. [Google Scholar] [CrossRef] [Scilit]
- Cobley, J.N.; Fiorello, M.L.; Bailey, D.M. 13 reasons why the brain is susceptible to oxidative stress. Redox Biol. 2018, 15, 490–503. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cooke, M.; Iosia, M.; Buford, T.; Shelmadine, B.; Hudson, G.; Kerksick, C.; Rasmussen, C.; Greenwood, M.; Leutholtz, B.; Willoughby, D.; et al. Effects of acute and 14-day coenzyme Q10 supplementation on exercise performance in both trained and untrained individuals. J. Int. Soc. Sports Nutr. 2008, 5, 8. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wahedi, A.; Sudhakar, S.; Lam, A.; Ciancio, J.I.R.; Mills, P.; Gissen, P.; Gardham, A.; Kapadia, J.; Hassell, J.; Heales, S.; et al. Clinical Features, Biochemistry, Imaging, and Treatment Response in a Single-Center Cohort with Coenzyme Q10 Biosynthesis Disorders. Neurol. Genet. 2024, 10, e200209. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guile, M.D.; Jain, A.; Anderson, K.A.; Clarke, C.F. New Insights on the Uptake and Trafficking of Coenzyme Q. Antioxidants 2023, 12, 1391. [Google Scholar] [CrossRef] [Scilit]
- Saiki, R.; Lunceford, A.L.; Shi, Y.; Marbois, B.; King, R.; Pachuski, J.; Kawamukai, M.; Gasser, D.L.; Clarke, C.F. Coenzyme Q10 supplementation rescues renal disease in Pdss2kd/kd mice with mutations in prenyl diphosphate synthase subunit 2. Am. J. Physiol.-Ren. Physiol. 2008, 295, F1535–F1544. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.; Hekimi, S. The efficacy of coenzyme Q10 treatment in alleviating the symptoms of primary coenzyme Q10 deficiency: A systematic review. J. Cell. Mol. Med. 2022, 26, 4635–4644. [Google Scholar] [CrossRef] [Scilit]
- Mantle, D.; Millichap, L.; Castro-Marrero, J.; Hargreaves, I.P. Primary Coenzyme Q10 Deficiency: An Update. Antioxidants 2023, 12, 1652. [Google Scholar] [CrossRef] [Scilit]
- Duberley, K.E.; Heales, S.J.R.; Abramov, A.Y.; Chalasani, A.; Land, J.M.; Rahman, S.; Hargreaves, I.P. Effect of Coenzyme Q10 supplementation on mitochondrial electron transport chain activity and mitochondrial oxidative stress in Coenzyme Q10 deficient human neuronal cells. Int. J. Biochem. Cell Biol. 2014, 50, 60–63. [Google Scholar] [CrossRef] [Scilit]
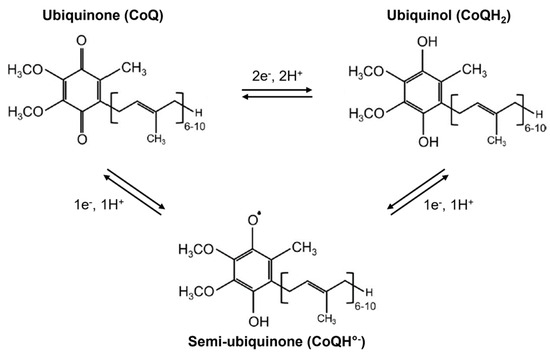
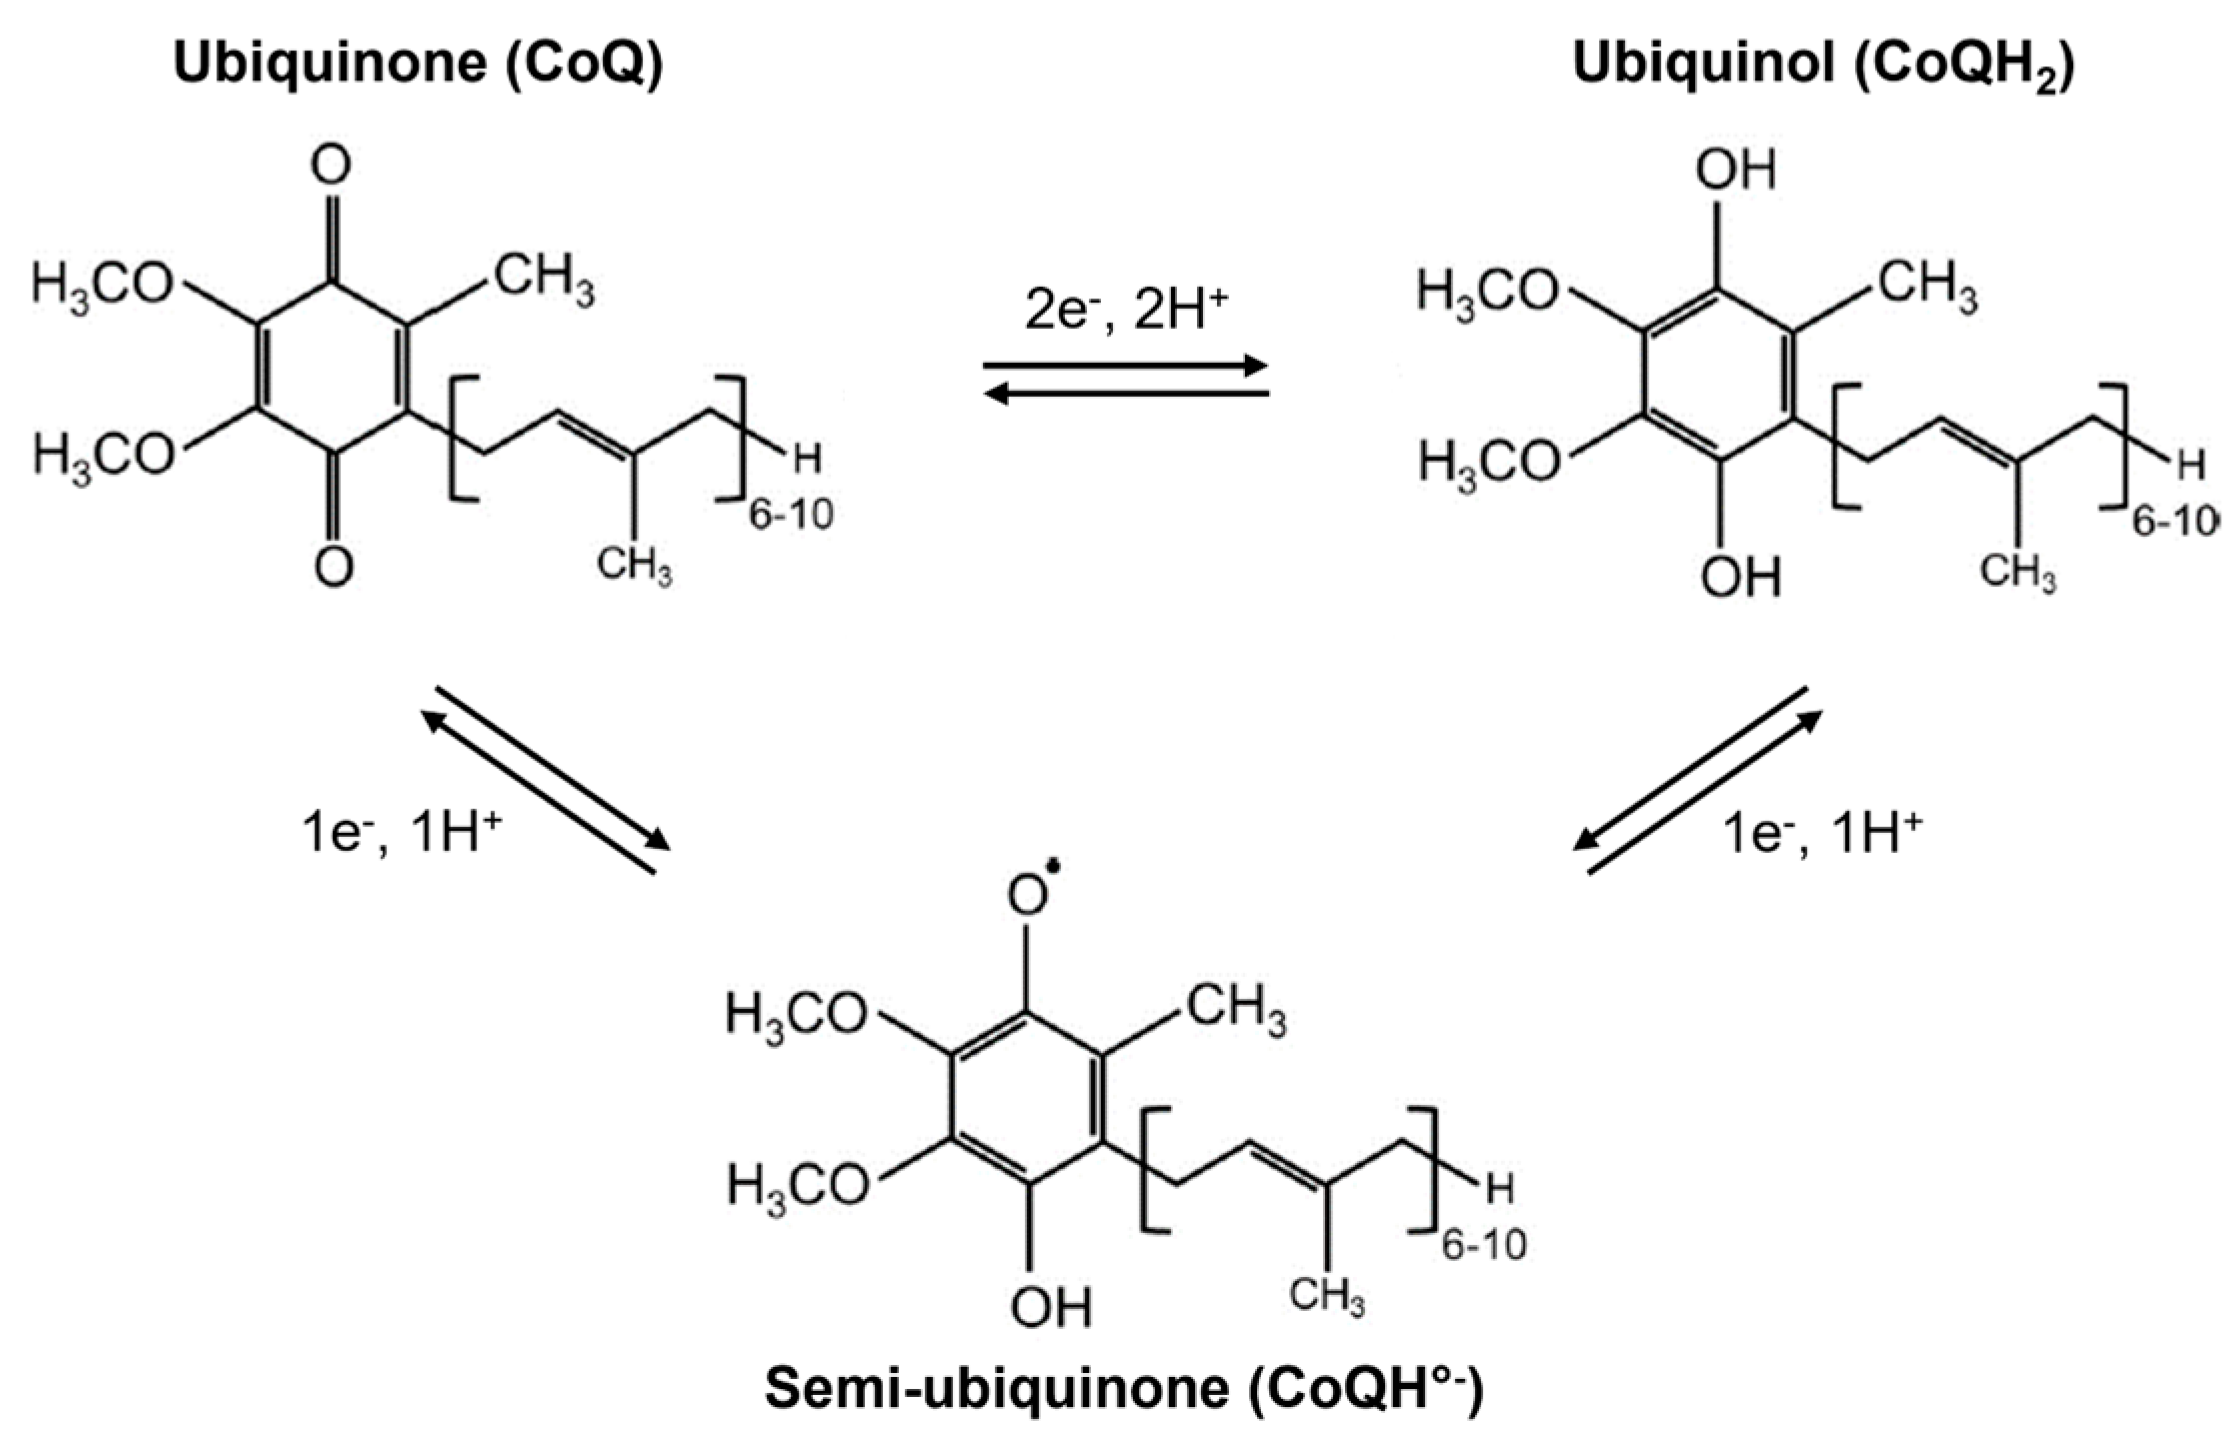
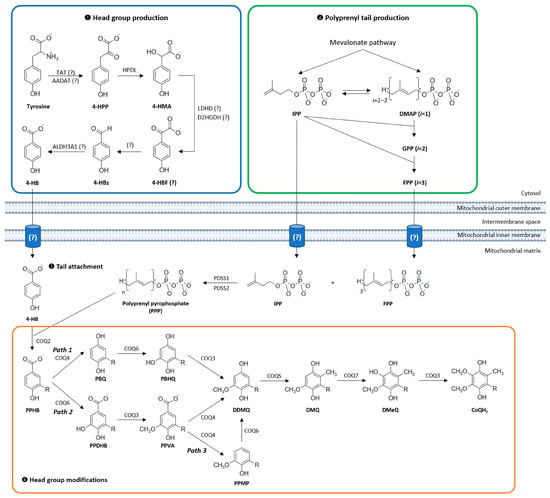
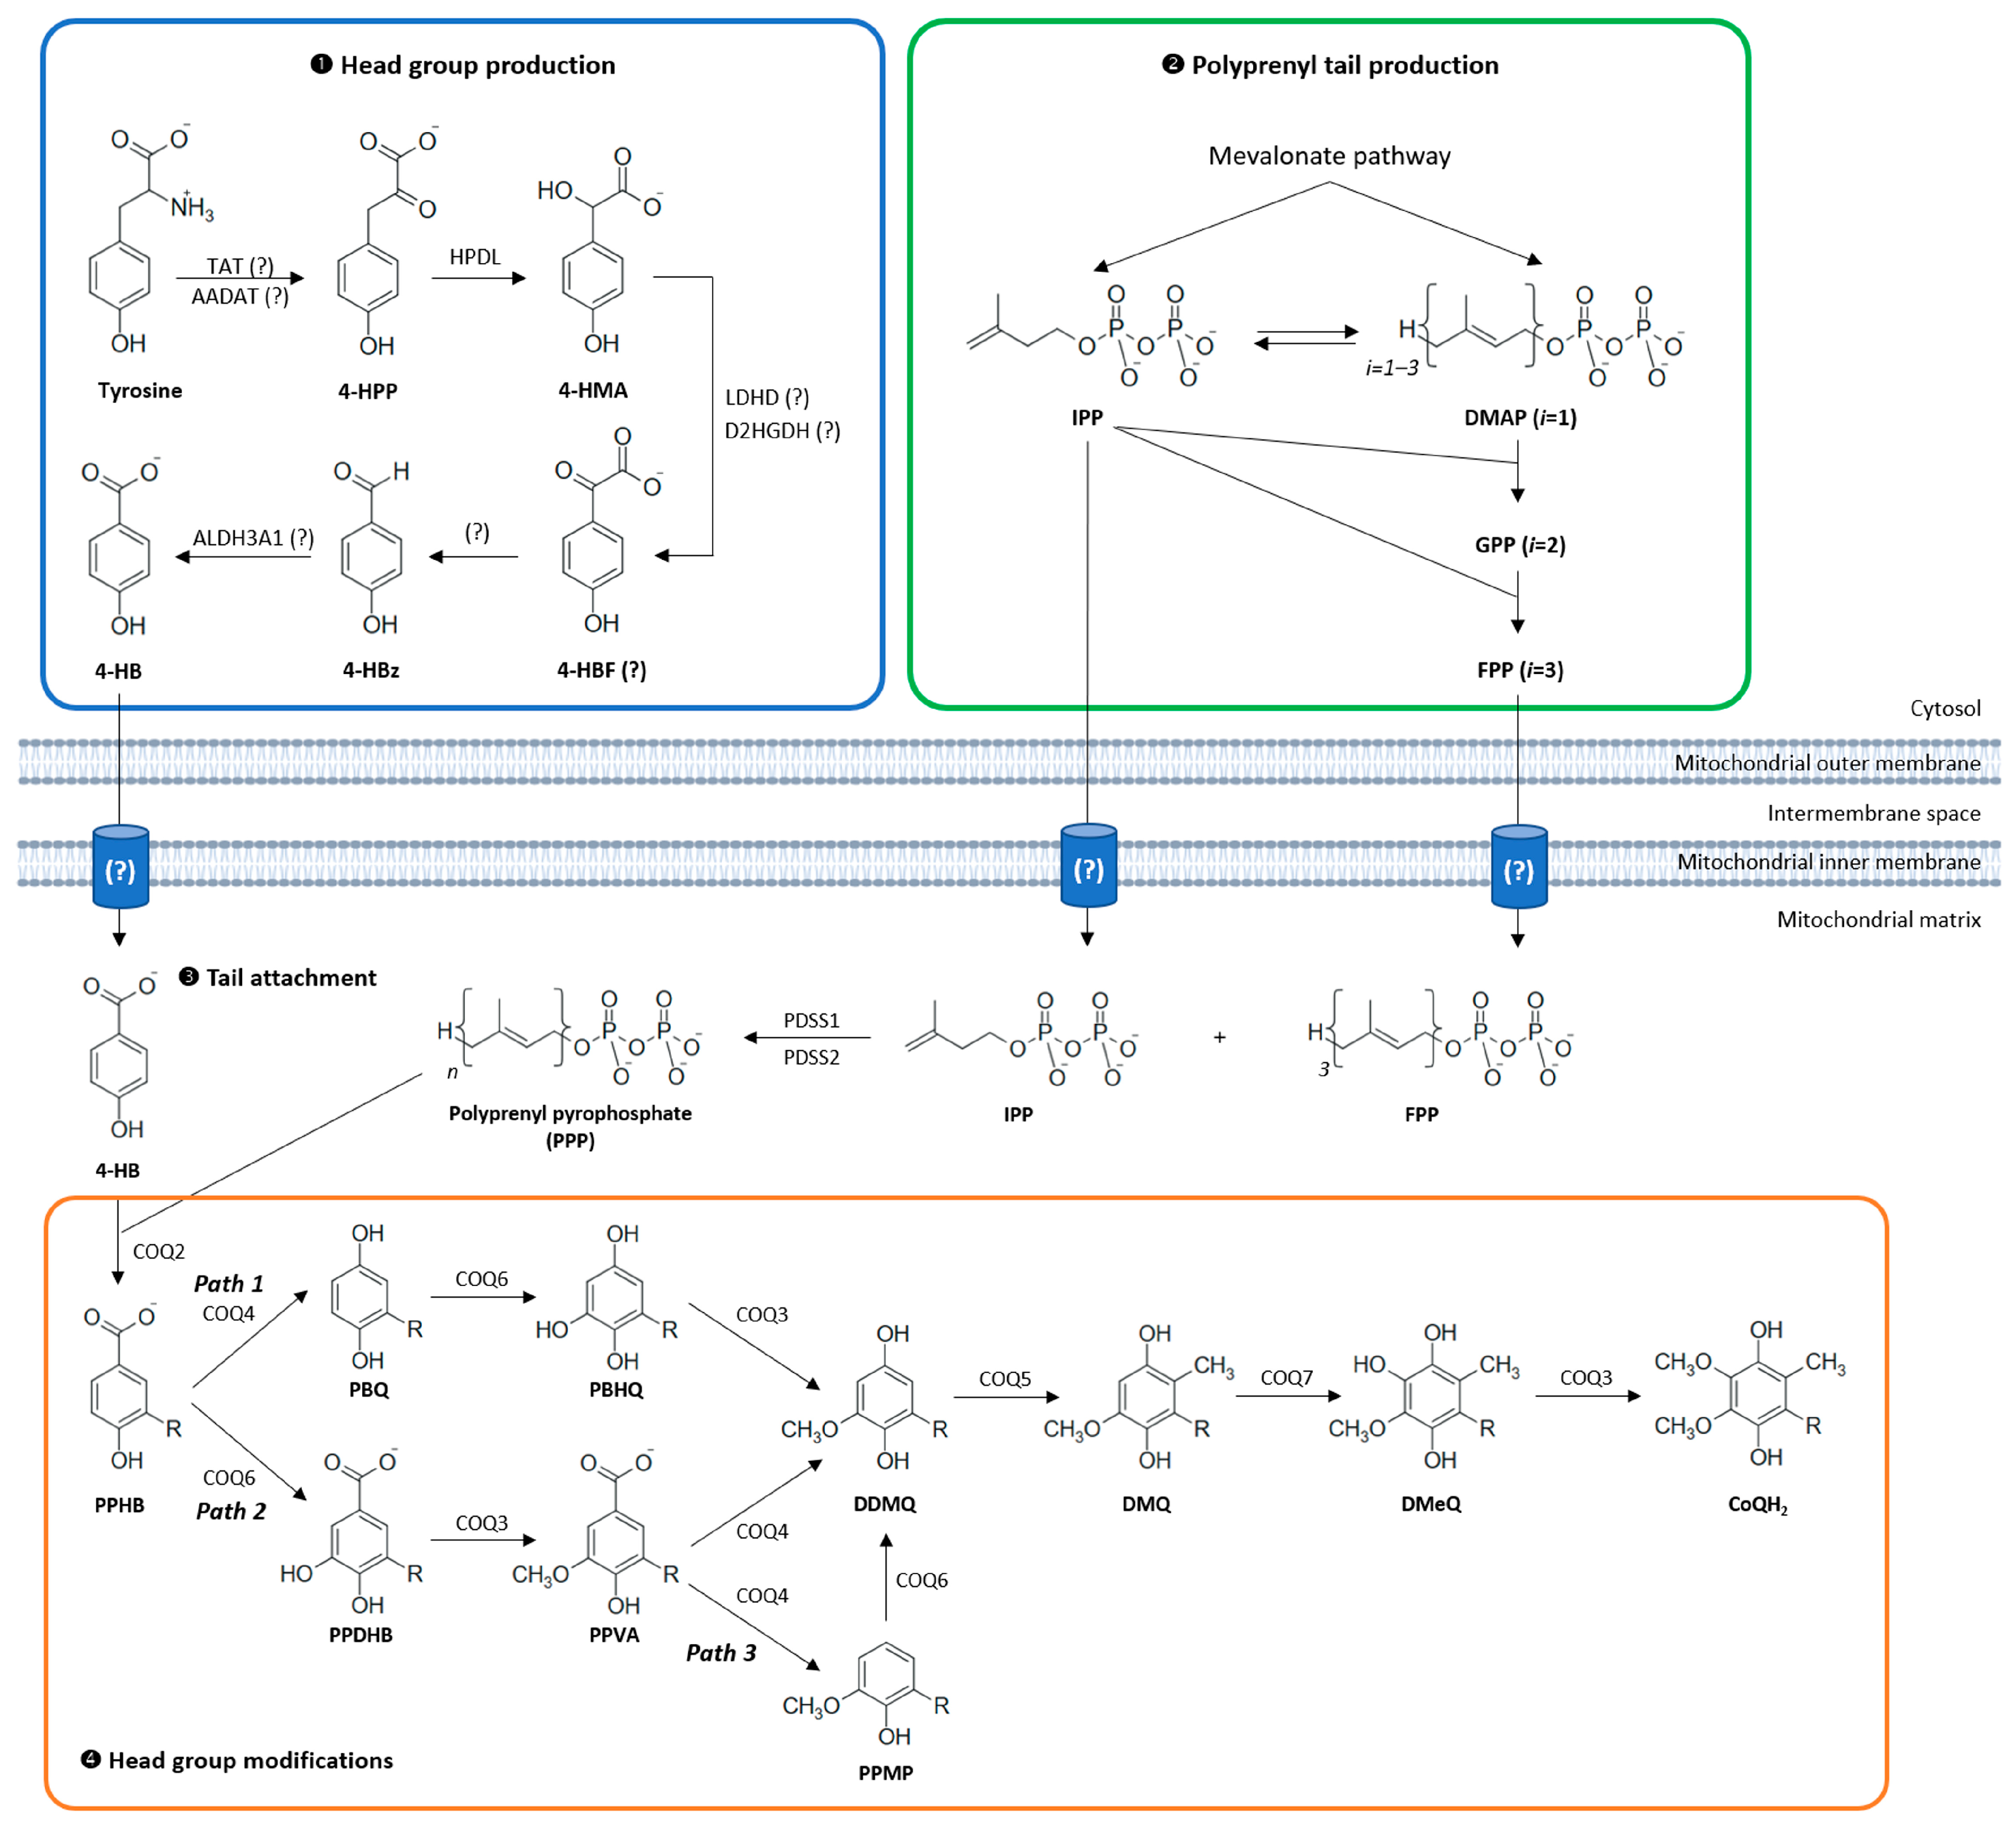
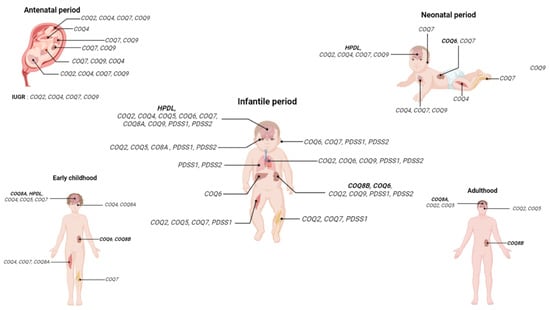
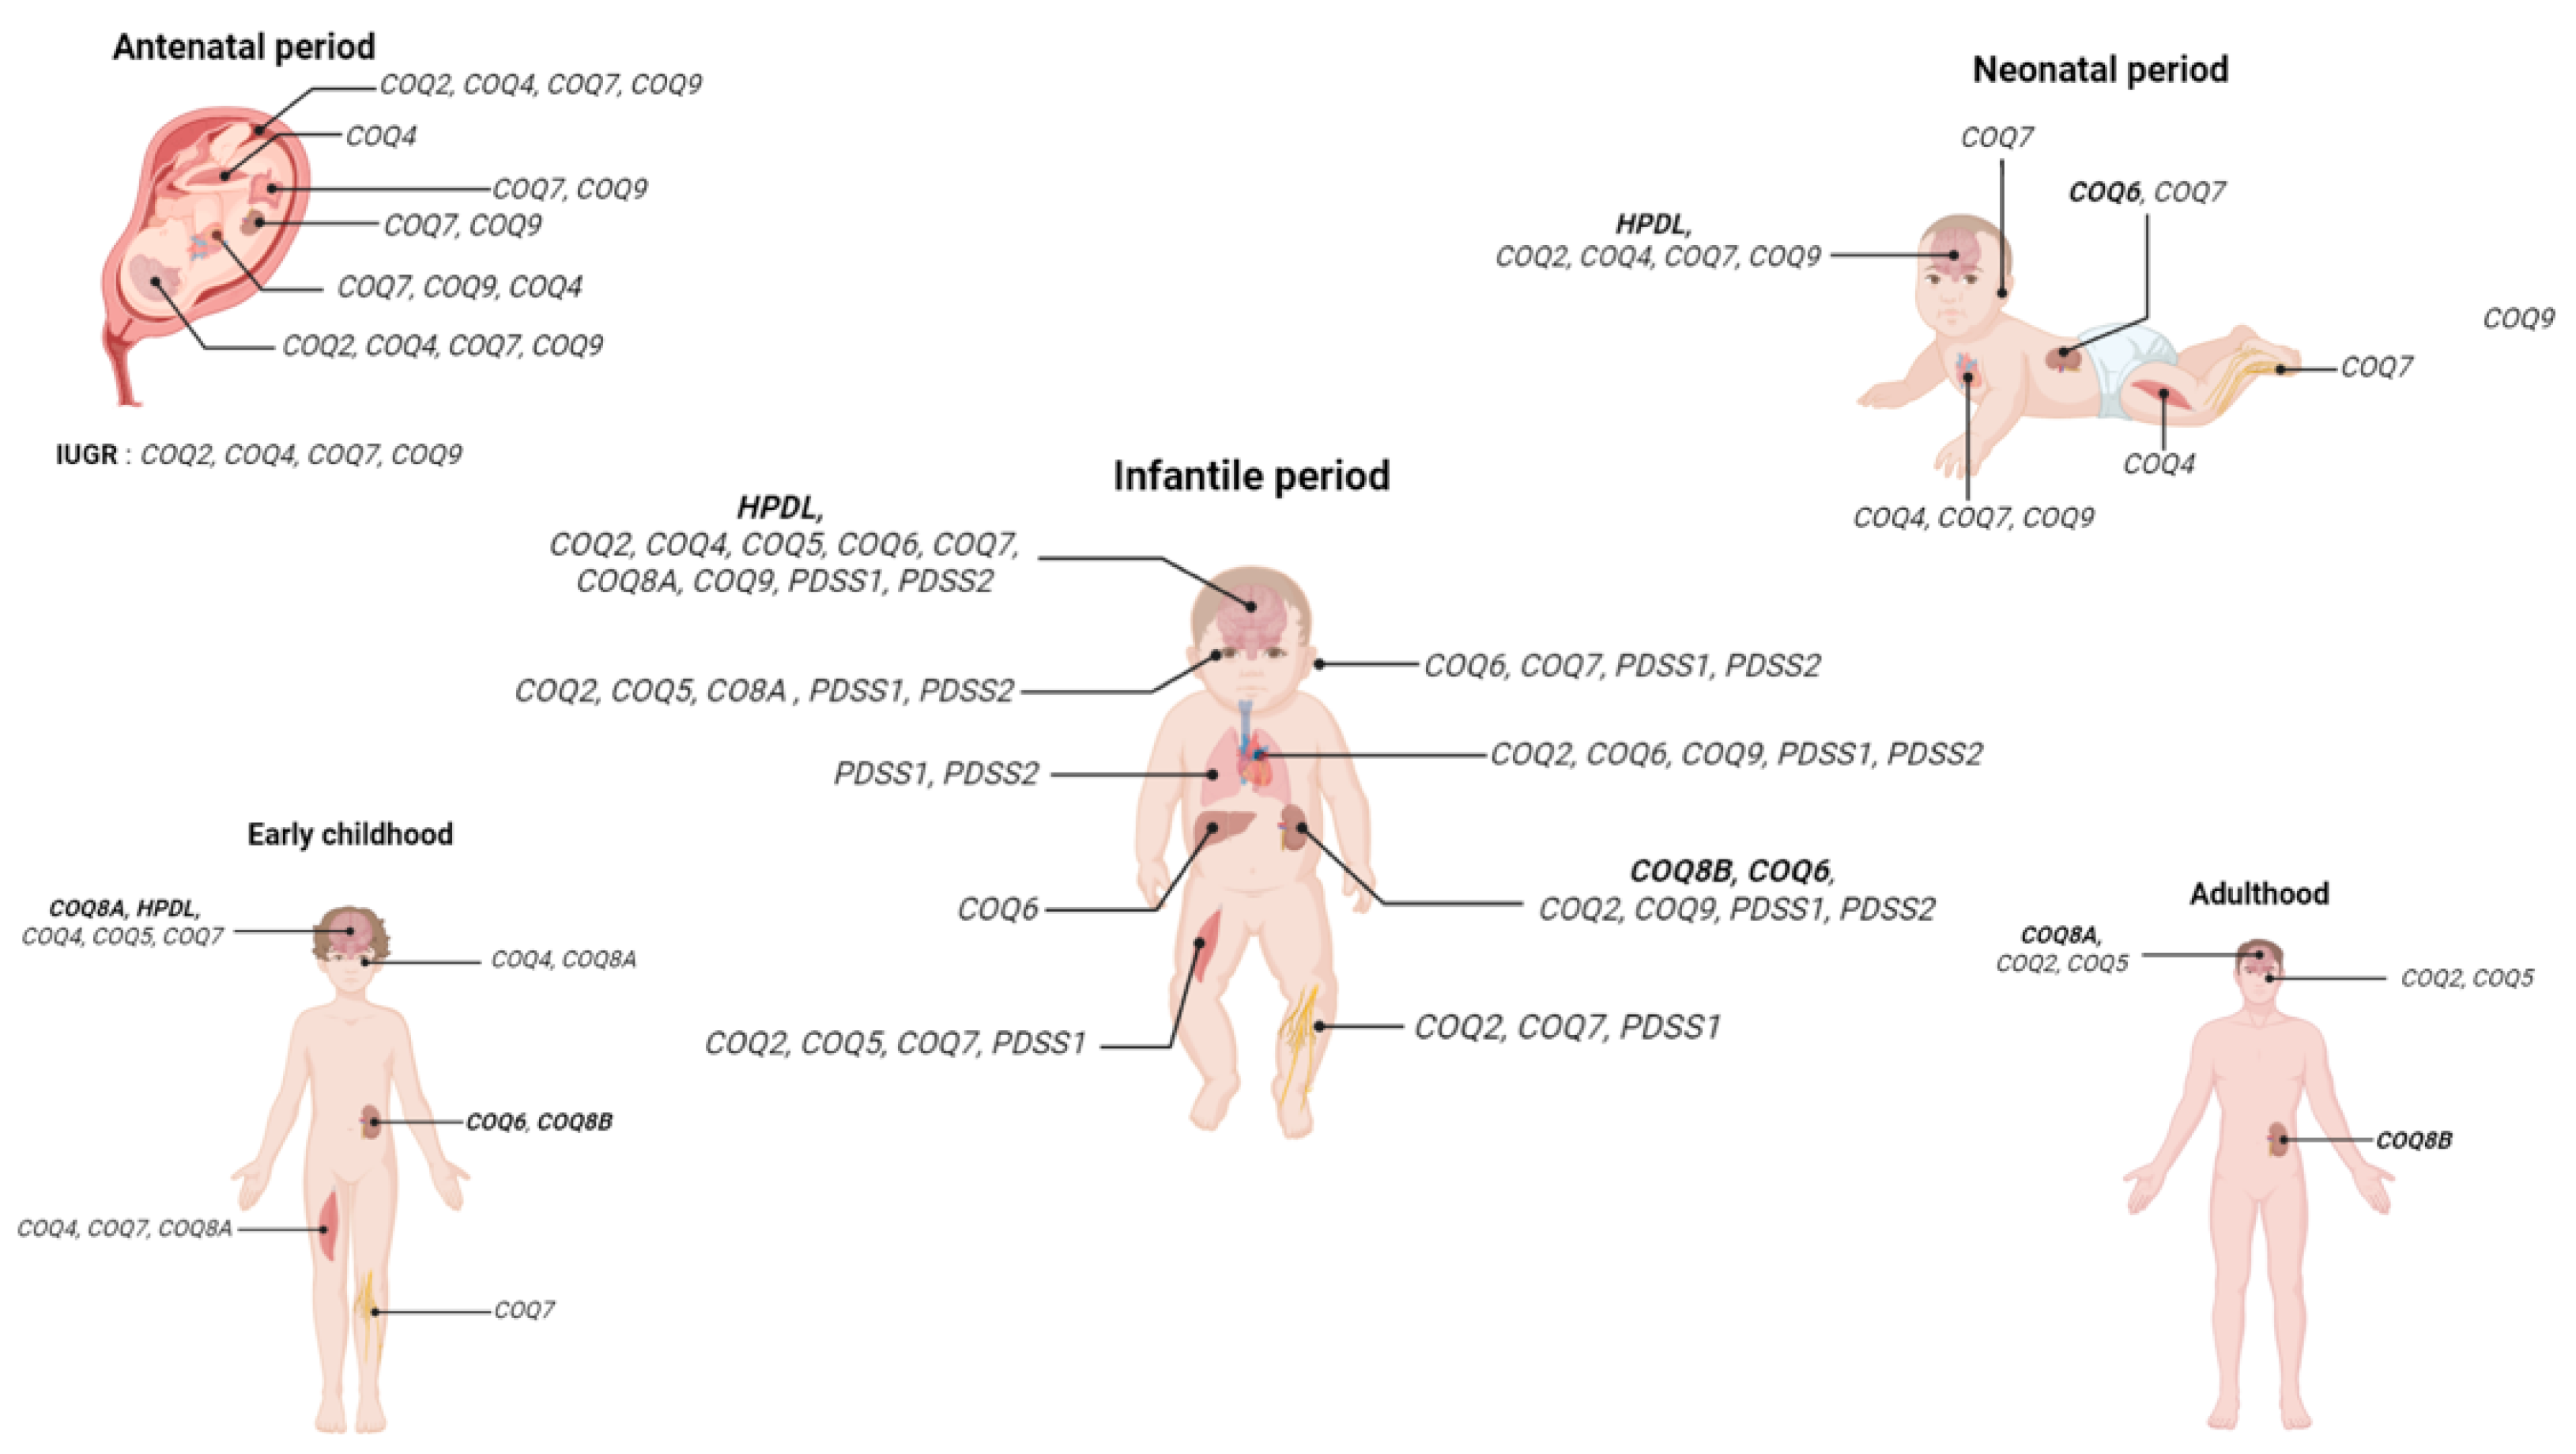
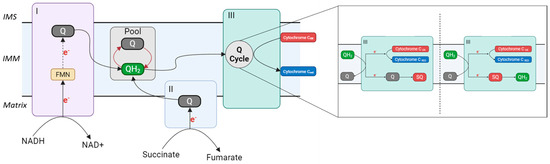
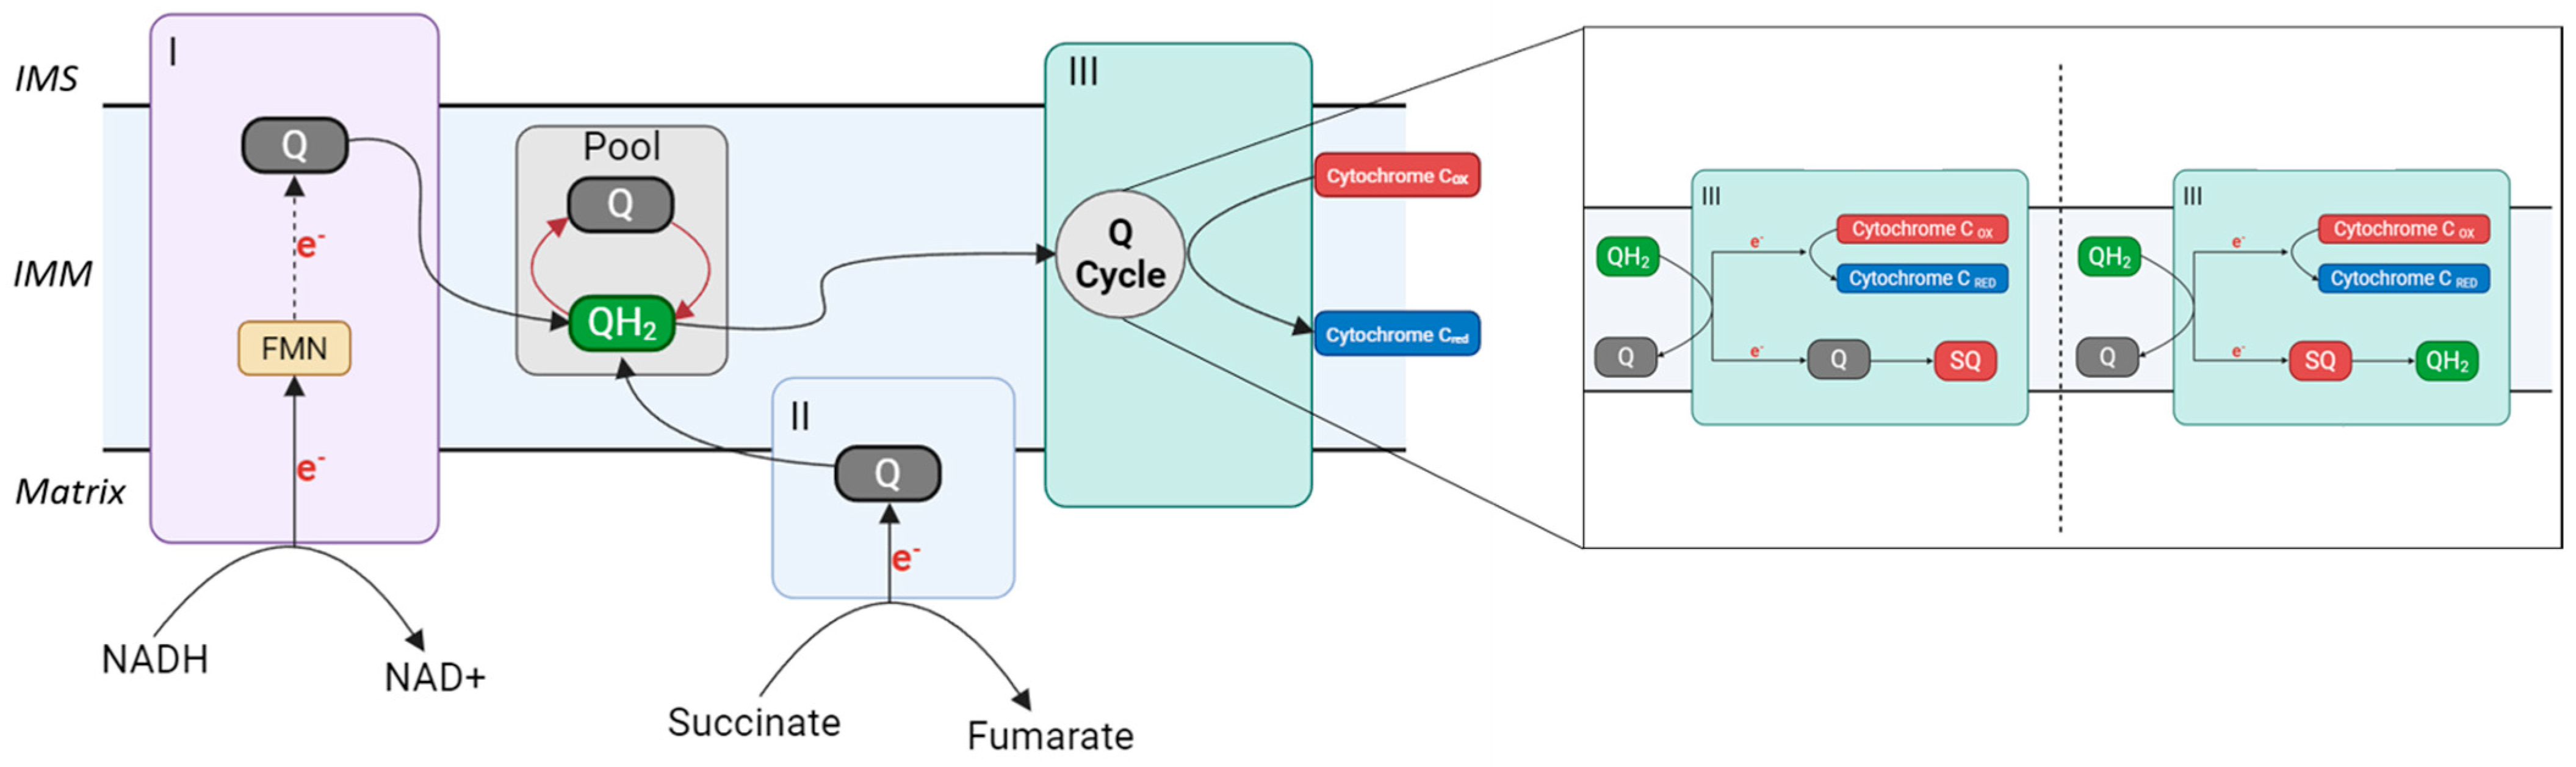
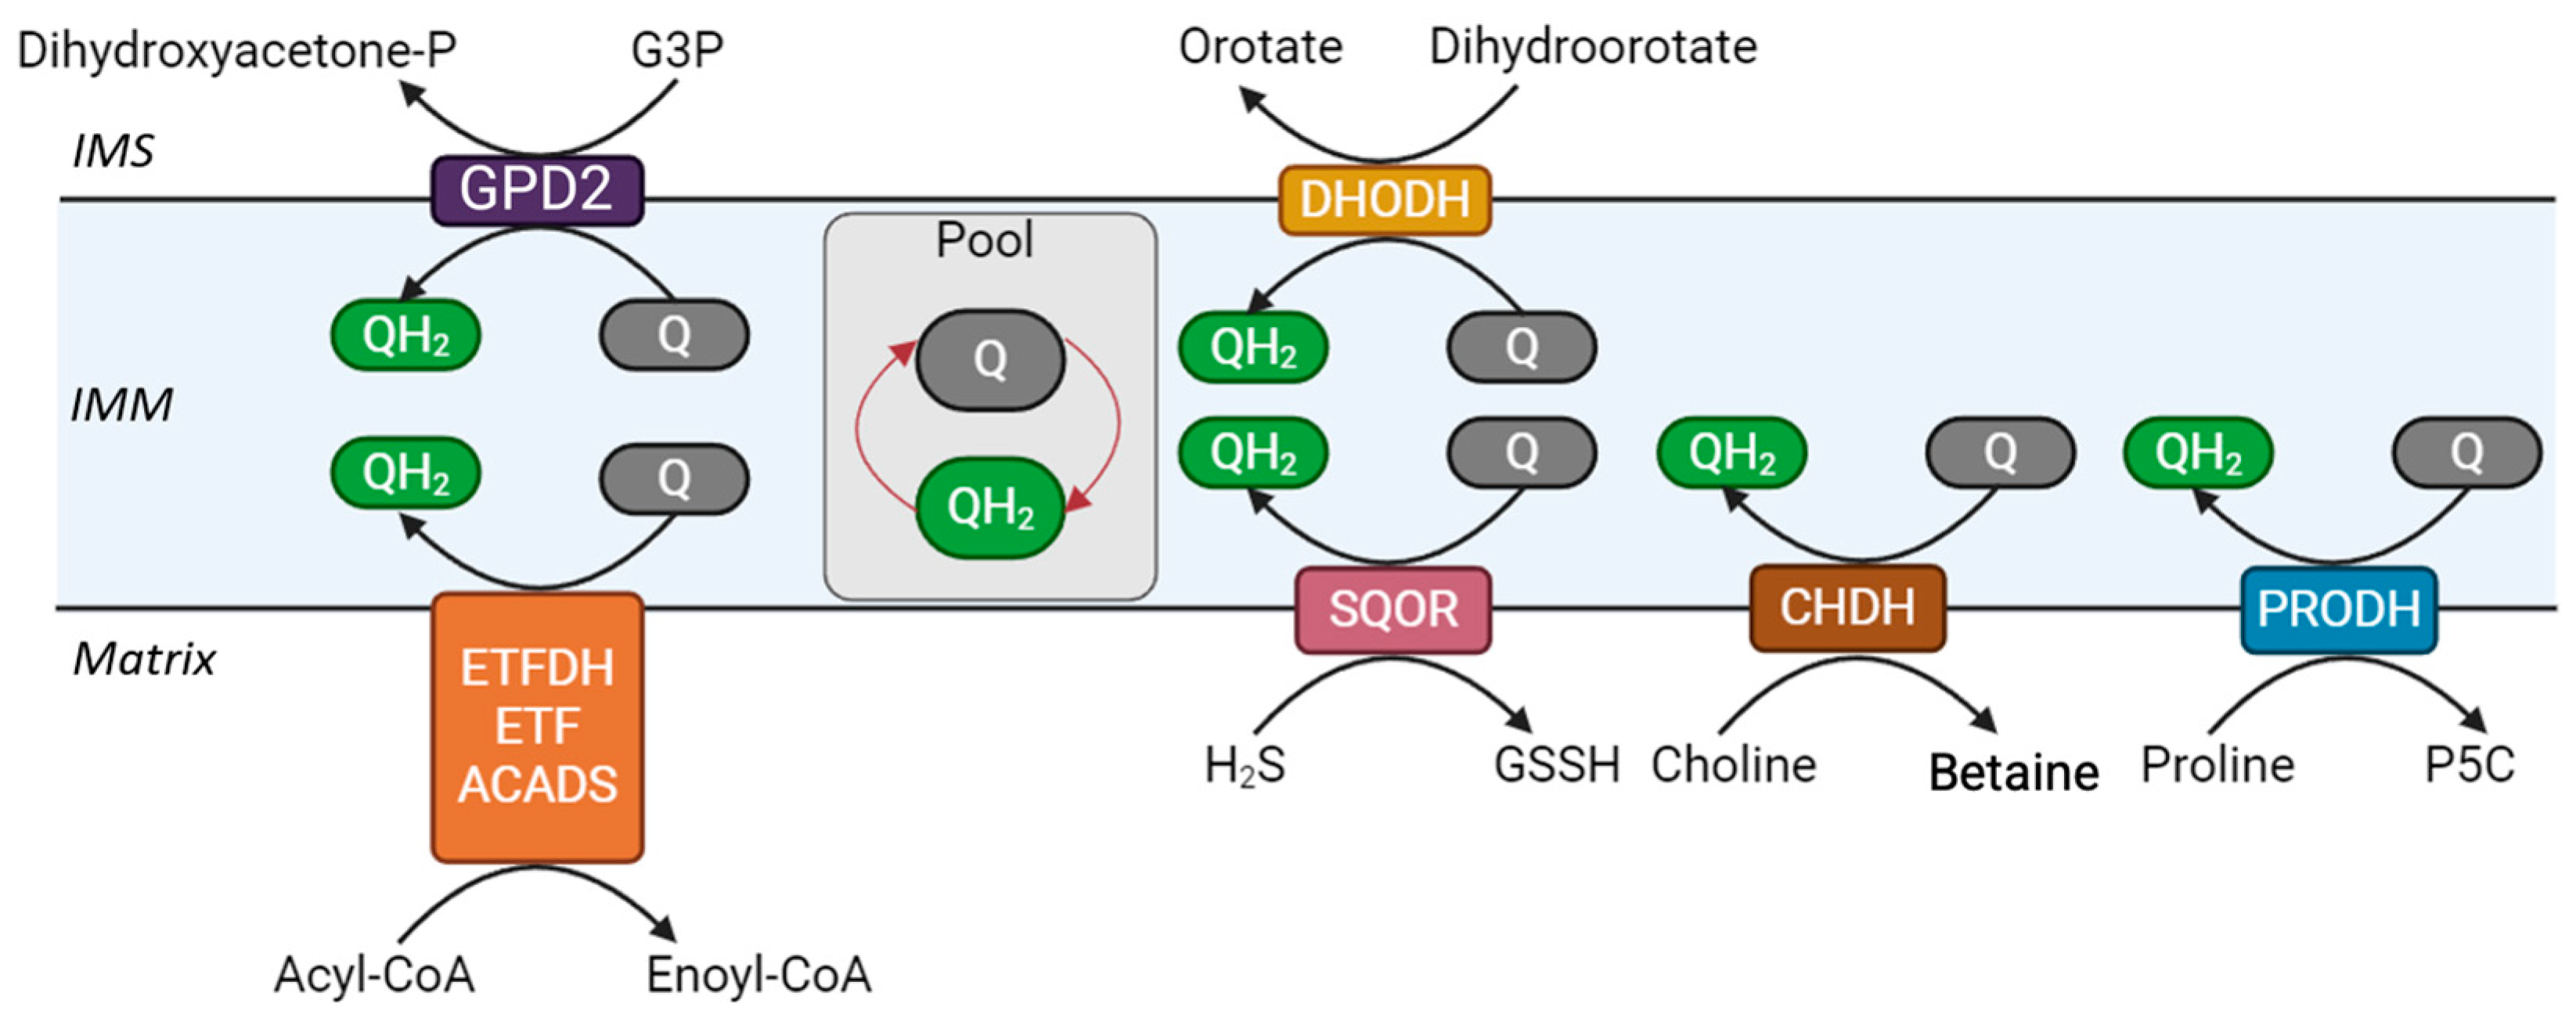
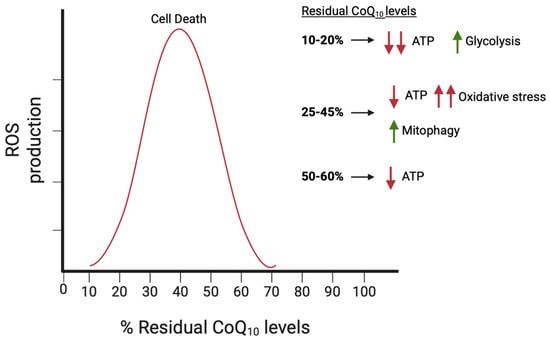
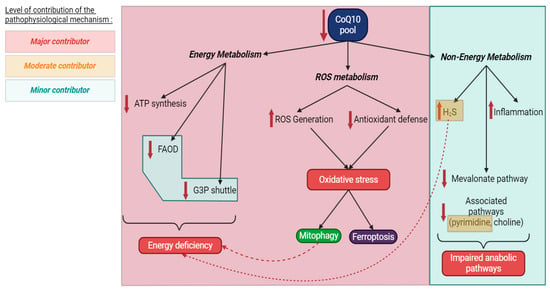
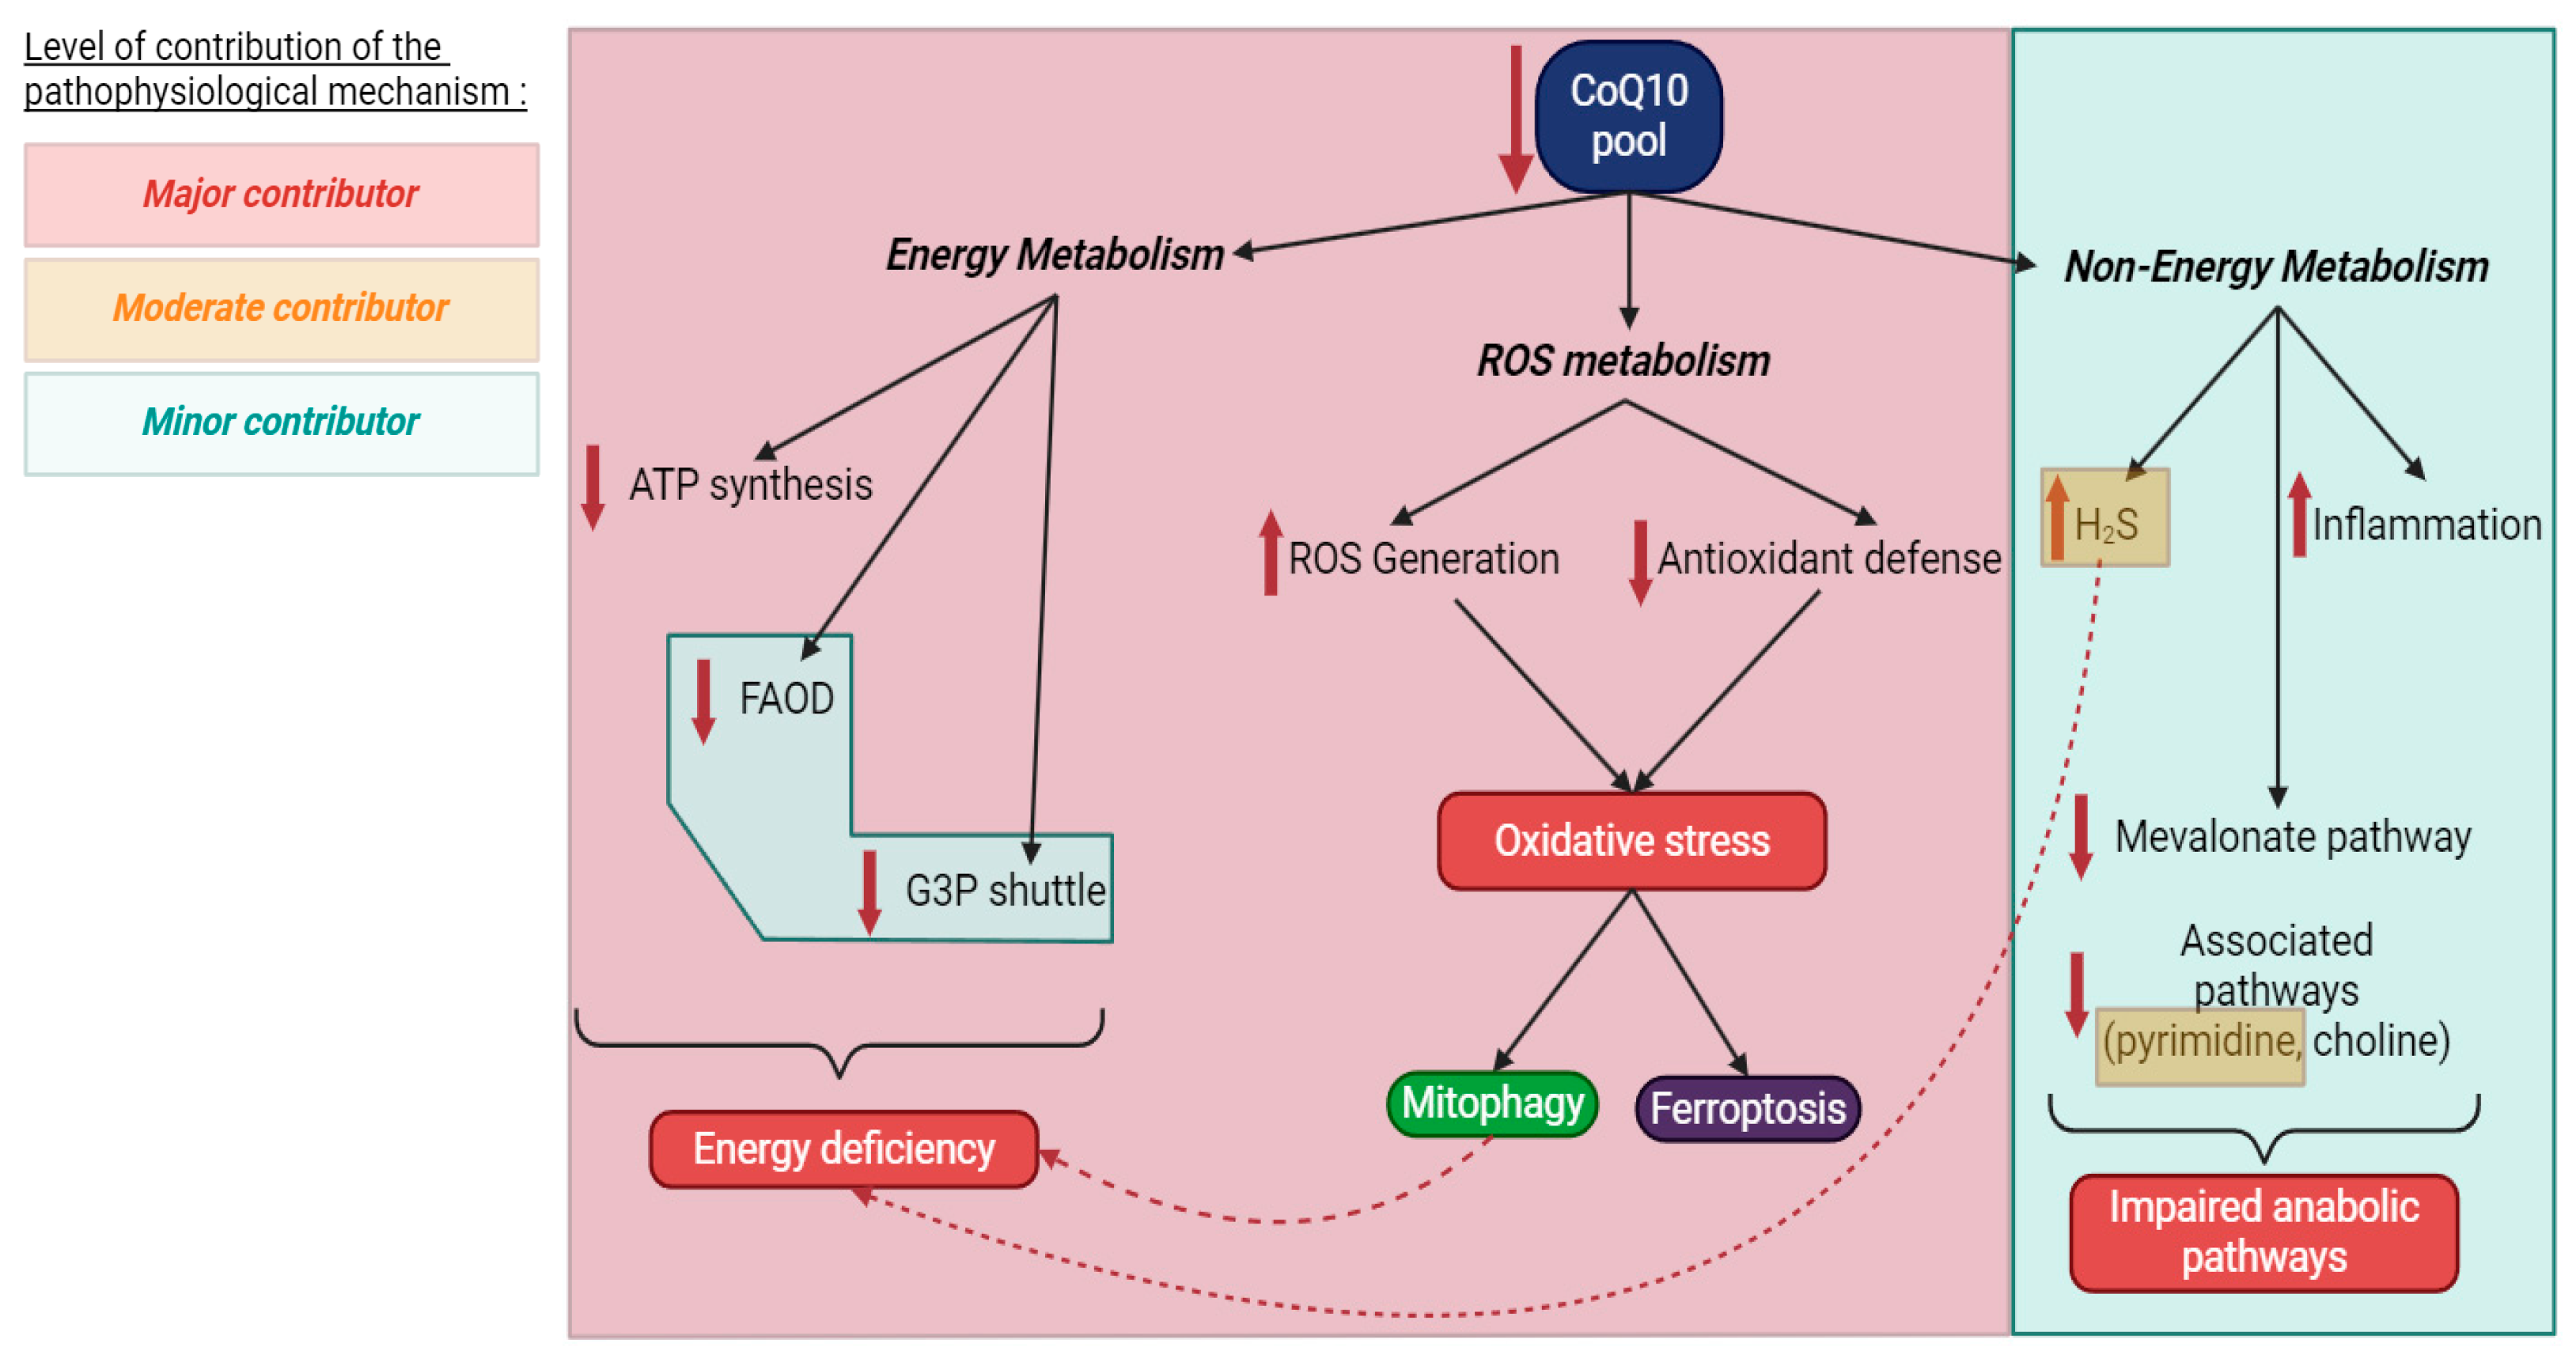
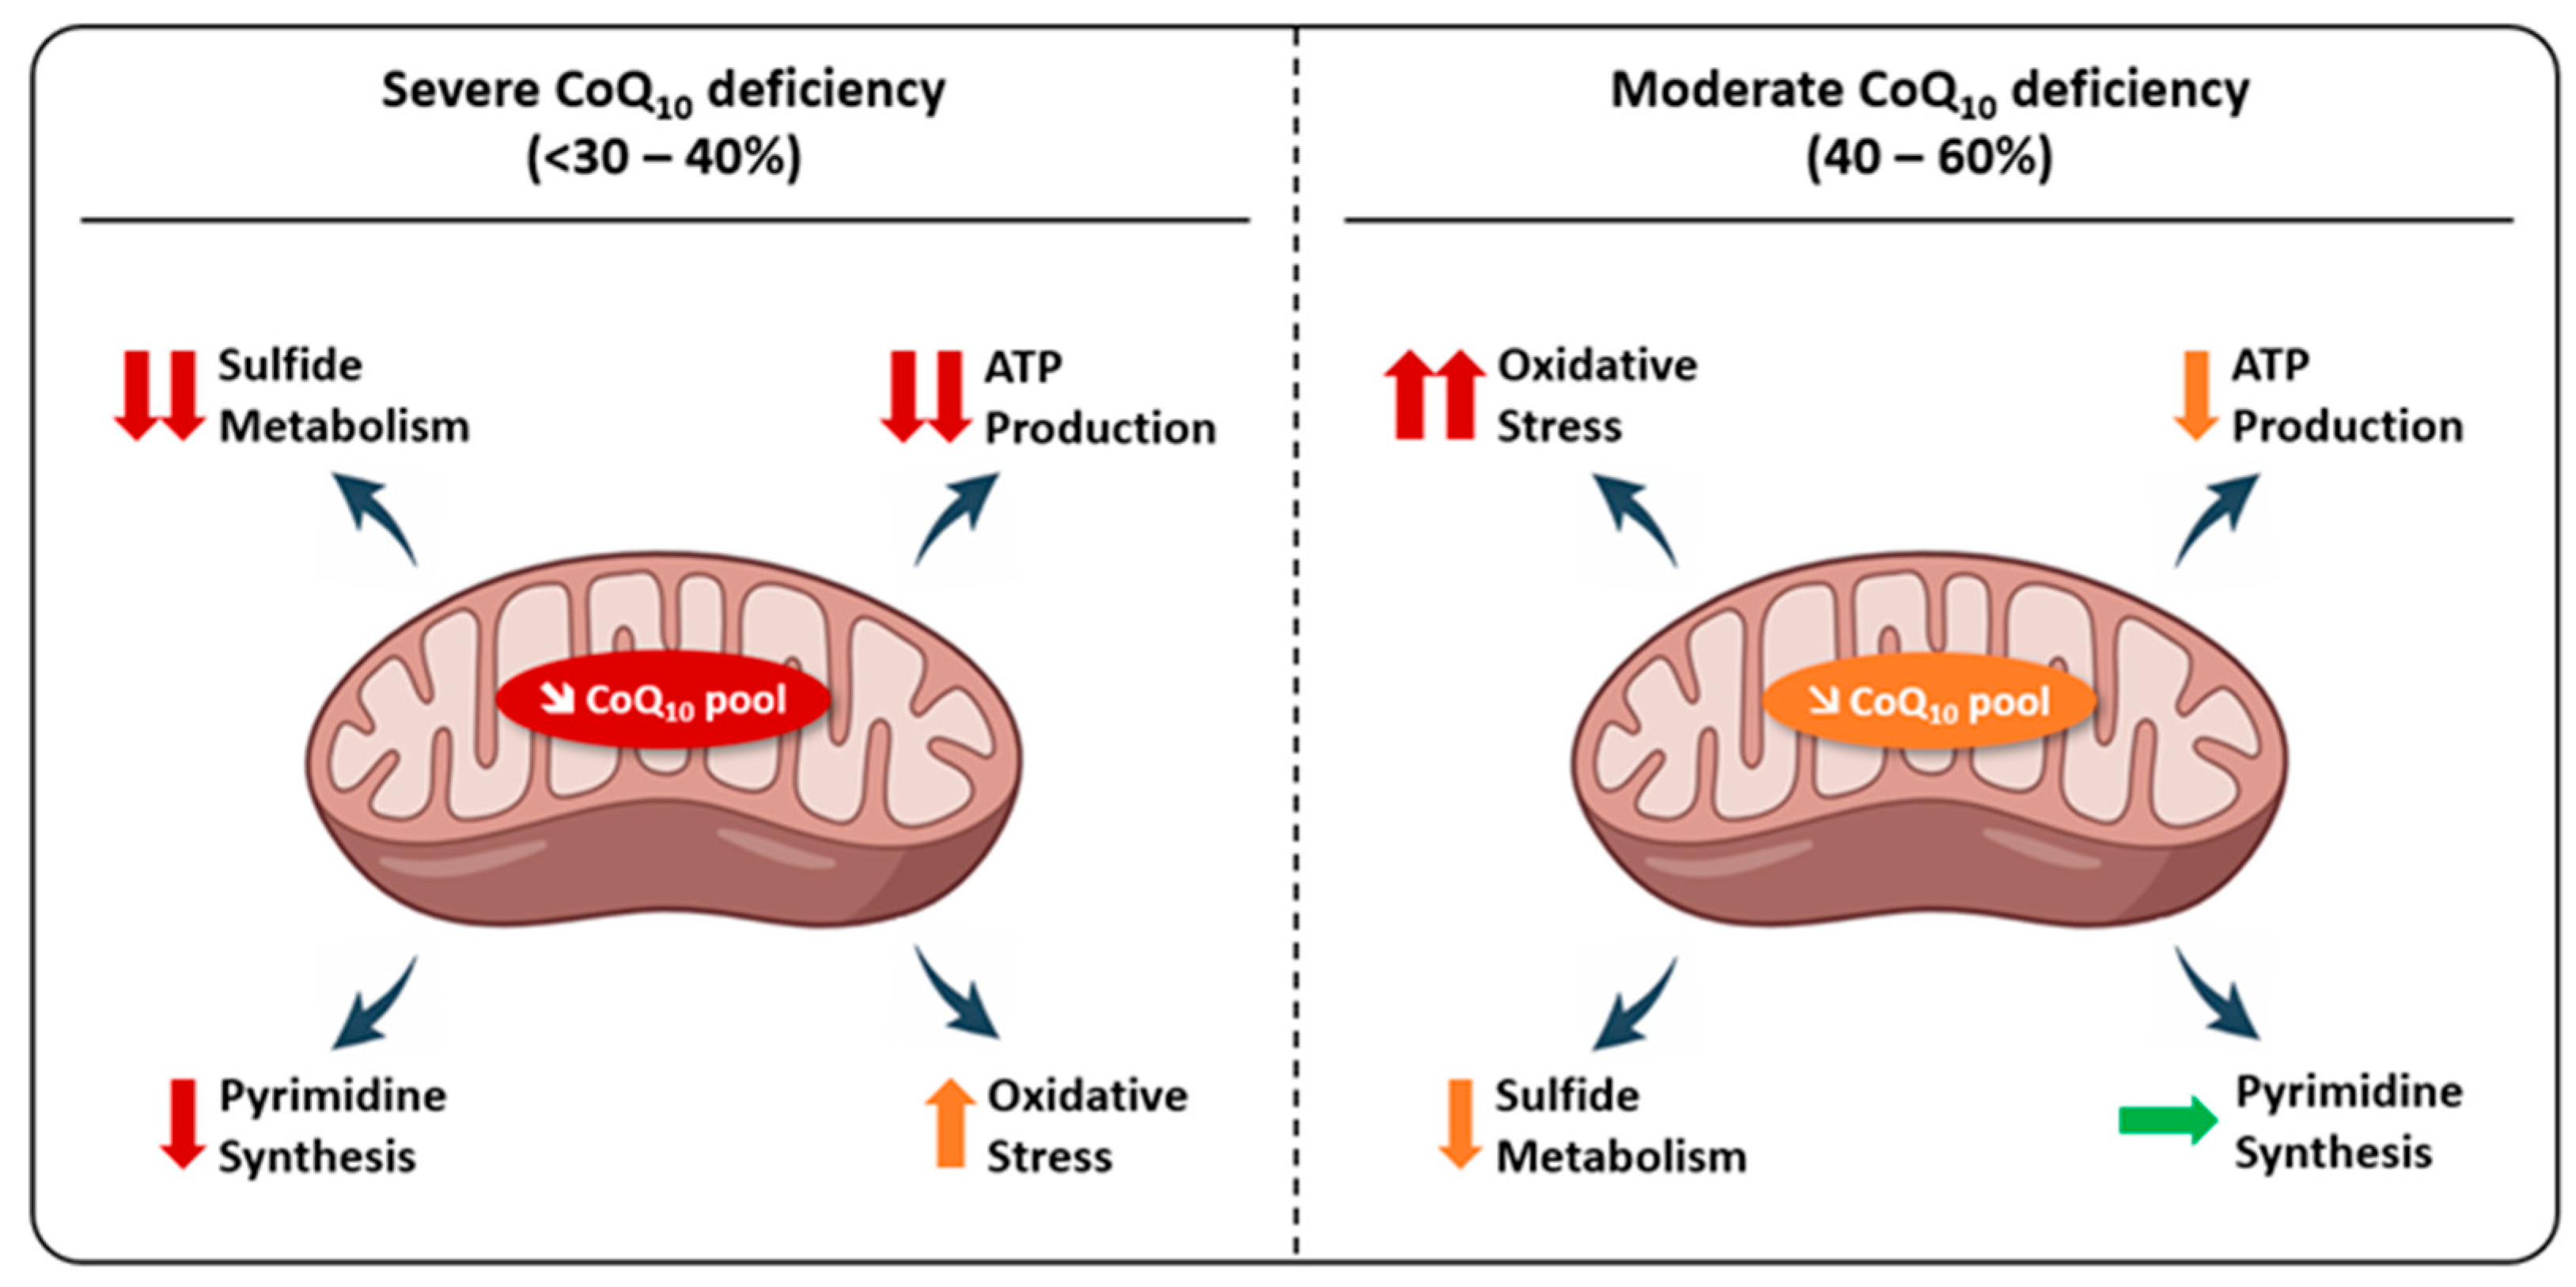
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.