


Abstract
Atopic dermatitis is a chronic and multifactorial inflammatory dermatosis. Recurrent eczematous lesions and intense pruritus very often reduce the quality of life of patients, affecting their mental health. For this reason, it is necessary to undertake treatment. Treatment should be characterized by an individual approach to the patient, taking into account the predominant pathogenetic factors in the development of atopic dermatitis and systematic skin care. Soothing the typical symptoms of AD, i.e., dry skin and persistent itching, involves emollients, which counteract xerosis and reduce the feeling of itching. Studies confirm that the regular use of emollients in patients with AD prolongs the period between relapses and alleviates the intensity of symptoms during periods of disease severity. This review paper aims to highlight the challenges that patients with atopic dermatitis face. This work will also present an indication of the rationale for the use of emollients in this condition, as well as an indication of the forms of their application in therapeutic and care preparations.
1. Introduction
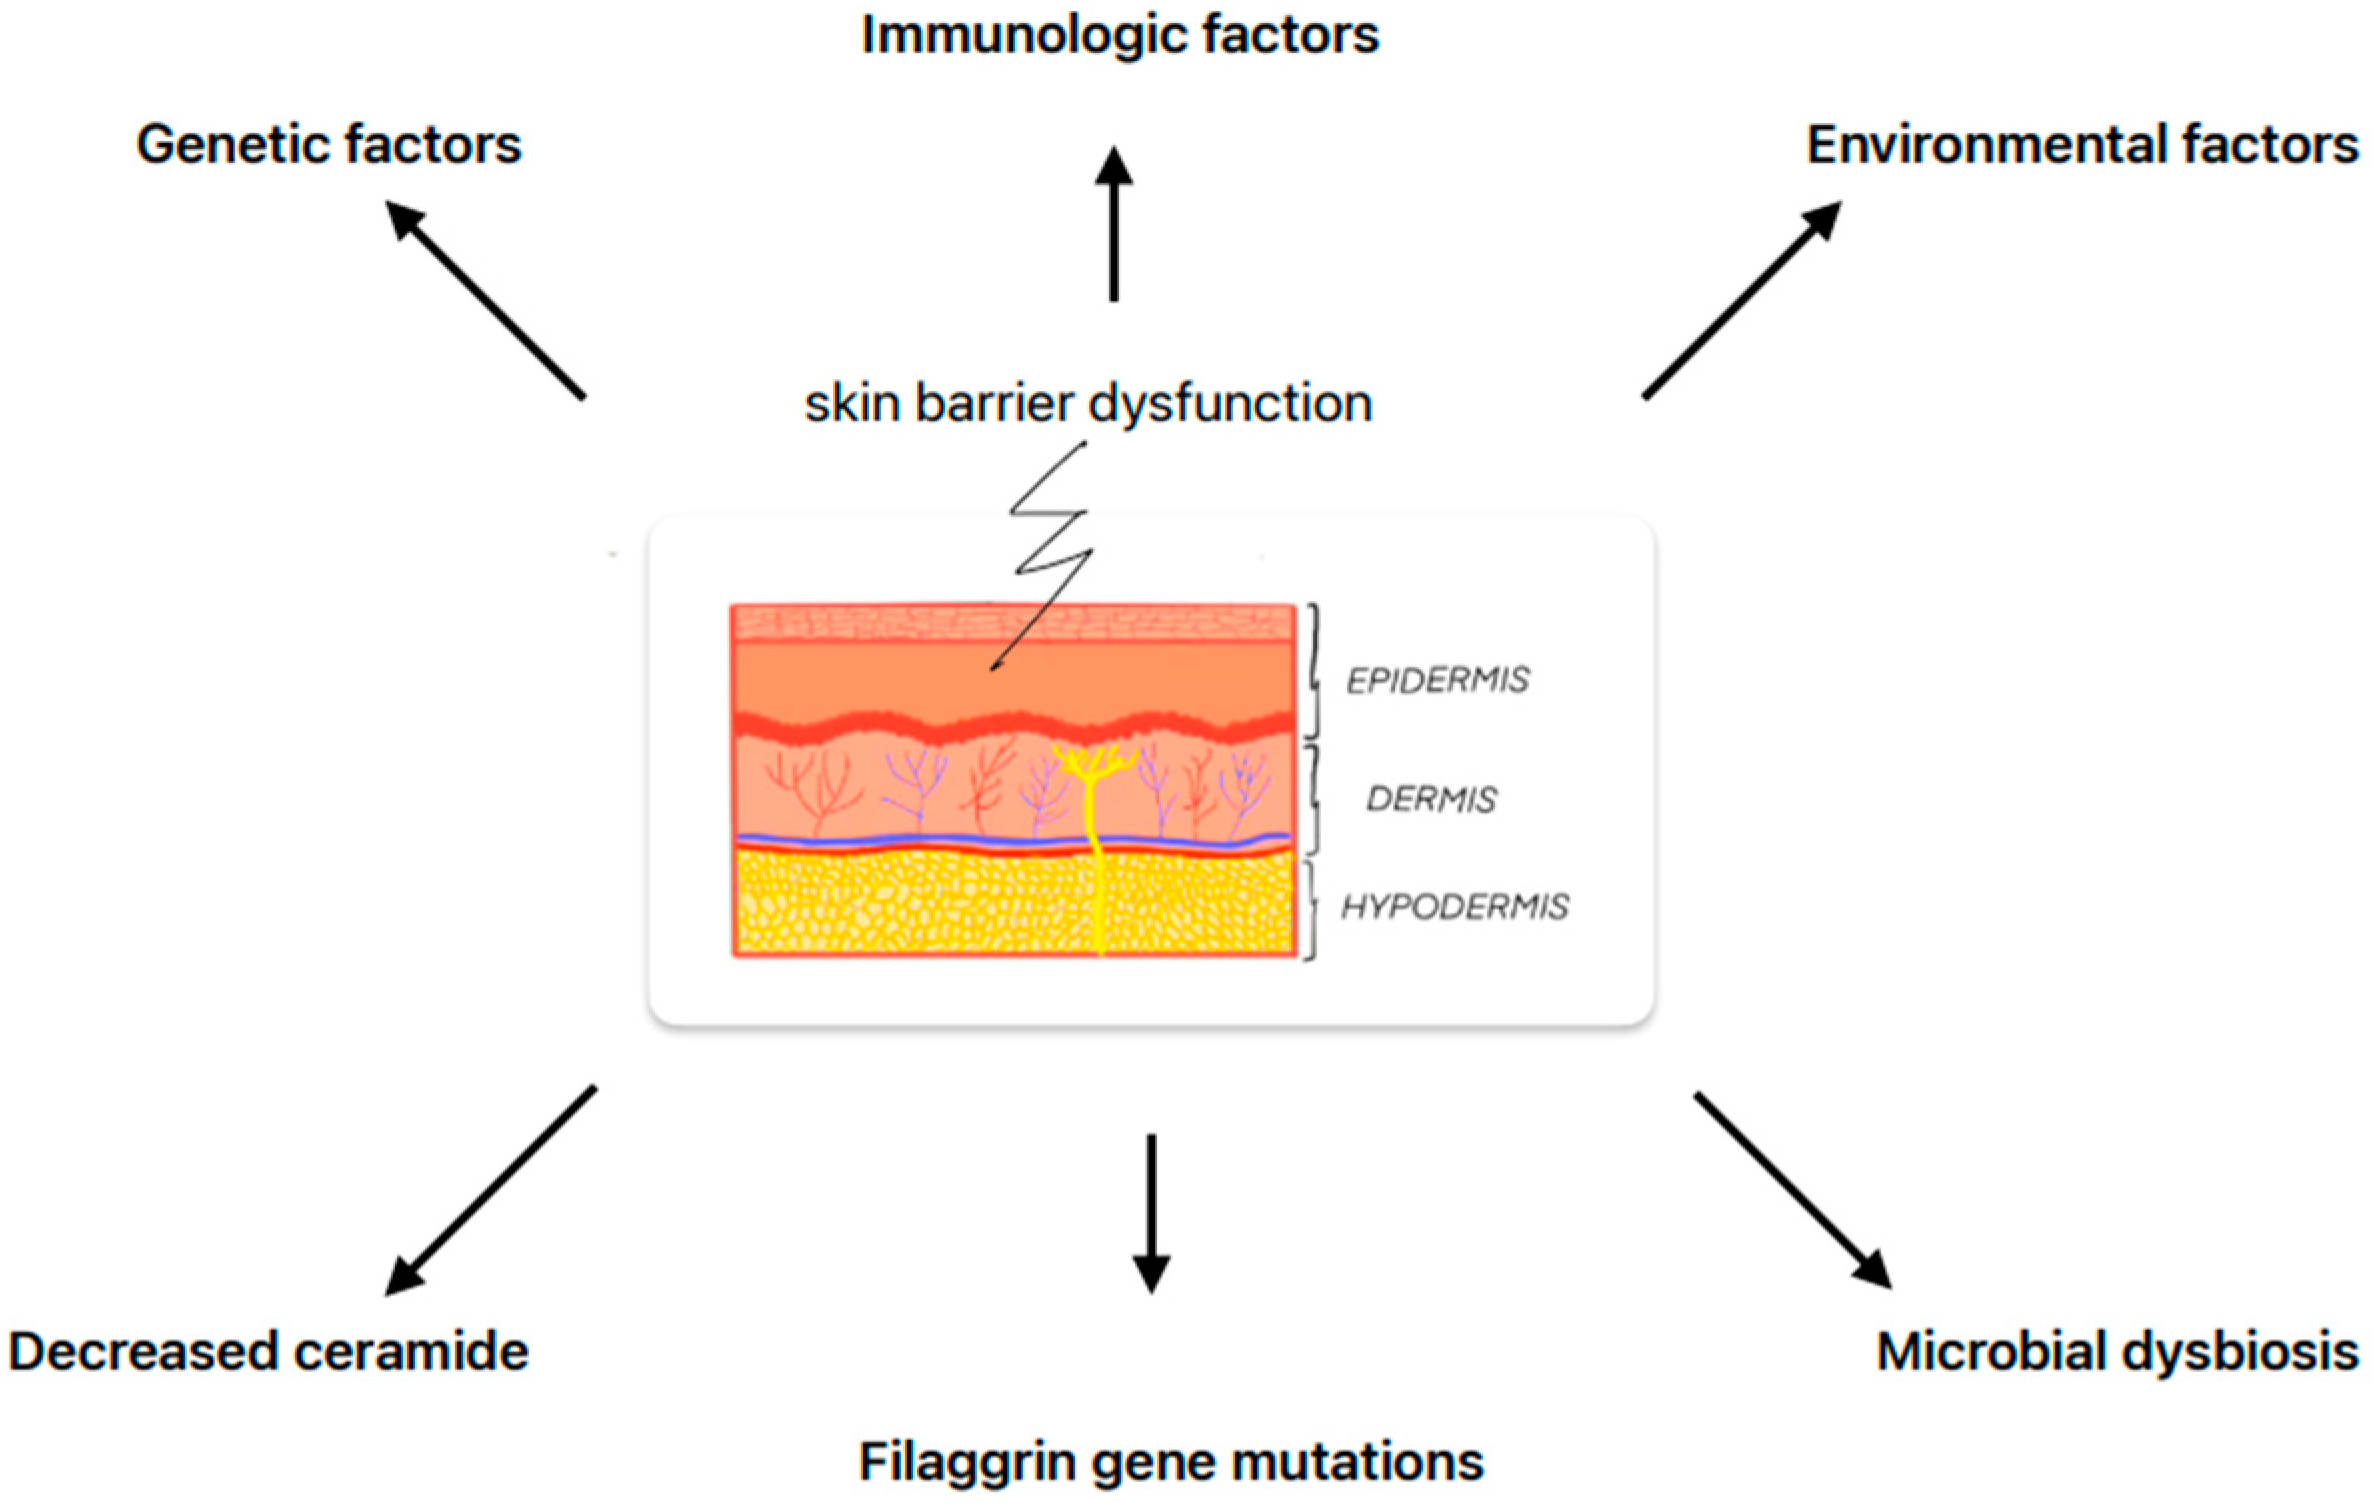
Atopic dermatitis (AD) is a chronic inflammatory dermatosis [1,2,3]. Damage to the epidermal barrier can occur for a variety of reasons, whether genetic, environmental or immunological [3,4,5] (Figure 1).
Figure 1.
Factors affecting skin barrier defect in atopic dermatitis based on [4,5,6,7].
Skin barrier defect is a key element in the course of atopic dermatitis [7]. It consists of abnormalities of the stratum corneum, disorders of tight junctions or antimicrobial peptides [7,8]. The aforementioned elements are responsible for the clinical manifestations of patients with AD such as dry skin. This parameter in turn generates increased transepidermal water loss (TEWL), facilitates the penetration of allergens and disrupts the microbial balance of the skin surface [7,8]. The genetic determinants of AD include a mutation of the filaggrin structural protein (FLG) [7]. The authors of [9] report that the effect of mutations in the filaggrin gene predisposing to atopic dermatitis was noted in 2006. The role of this protein is primarily based on maintaining the structure of the epidermis by synthesizing molecules that retain water. Filaggrin deficiency results in keratinocyte abnormalities and causes impairment of the epidermal barrier, which allows exogenous molecules to penetrate the epidermis [9]. Mutations in filaggrin occurring in C-terminal repeats cause a significant reduction in filaggrin in the epidermis of AD patients. This is because the C-terminal region is essential for the proper processing of profilaggrin into filaggrin [10]. Abnormalities in filaggrin synthesis reduce the amount of natural moisturizing factor and cause an increase in skin pH as a result of the decreased production of transurocapnic acid [11]. Another factor in the defect of the skin barrier is a decrease in cutaneous ceramides, which results in a decrease in TEWL and increases the possibility of allergens and microorganisms penetrating deep into the skin [6] (Figure 1).
According to statistics, the incidence of AD is steadily increasing [1]. According to the Global Report on Atopic Dermatitis 2022, about 223 million people worldwide struggle with AD [12]. Atopic dermatitis affects about 25% of children [11]. During the first years of a person’s life, the prevalence of the disease is comparable in both sexes; it is only after the age of six that the diagnosis of atopic dermatitis increases in females [11]. In a retrospective study that was conducted in South Korea, atopic dermatitis was diagnosed in 944,559 children and in more than one million adults (1,066,453) [2]. In contrast, according to a compilation of information in a publication [7], 3.91% of children in Poland suffer from AD.
The primary goals of treating atopic dermatitis are to reduce inflammation, decrease pruritus or redness and restore the normal skin barrier [13]. Therapeutic strategies in the treatment of AD target the skin—that is, skin care and topical medications, most commonly corticosteroids (ICS) or calcineurin inhibitors. The mainstay of atopic dermatitis treatment used for more than 60 years has been topical corticosteroids [14]. This is because they exhibit anti-inflammatory, antiproliferative and immunosuppressive effects, as well as antipruritic effects [11]. Medium- and high-potency steroids, such as triamcinolone acetonide 0.1%, are used to treat acute inflammatory lesions. In contrast, lower-potency steroids are used on areas covered by a thinner layer of skin, such as the eyelids, facial skin or genitals, because of the risk of atrophy. In a situation where skin lesions occupy more than 20%, general corticosteroid treatment is implemented [11,15,16]. As noted by the authors [17], long-term use of steroids has been associated with many side effects such as rosacea, acne-like rashes, skin atrophy and telangiectasias. A summary of various therapeutic strategies is presented in Table 1.
Table 1.
Summary of therapeutic strategies for atopic dermatitis for all age groups [18,19].
Products that reduce the use of steroids in the treatment of AD are emollients, which, according to the authors of [20], have significantly reduced the need for patients to use corticosteroids. The authors of [21] report that the use of emollients is associated with numerous beneficial effects, such as reducing the number of AD exacerbations, prolonging remission periods, reducing eczematous lesions and reducing the amount of corticosteroids needed to achieve a similar therapeutic effect. It has been confirmed that emollients in combination with active treatment (among other steroids) produce significantly better results than steroids alone [21]. Currently, the typical therapeutic strategy undertaken in patients with atopic dermatitis is the simultaneous use of glucocorticosteroids and emollients [21]. One method that combines emollients and steroids is the use of wet-wrap treatment. It involves applying two layers of dressings to the skin. The inner layer is saturated with emollients and a glucocorticosteroid, while the outer layer remains dry. Wet-wrap treatment reduces the sensation of pruritus, cools the skin and prolongs the sensation of hydration, while the use of topical glucocorticosteroids in wet dressings increases their absorption from the skin surface [10]. Emollients achieve the greatest efficacy in mild forms of AD [4,22]. Studies confirm that the concomitant use of glucocorticosteroids during exacerbations and maintenance of regular skin care with emollients can beneficially manage atopic dermatitis and prevent exacerbations [20]. Their action is based on restoring the integrity of the epidermal barrier, which counteracts xerosis and reduces persistent itching, which is one of the most troublesome symptoms. They are commonly used to treat various disorders such as psoriasis, keratosis disorders and xeroderma [4,22]. Emollients can be used either as creams, emulsions or lotions, or as a form of bath preparation as shower gels or shampoos [1].
The use of emollient-like ingredients has been popular since ancient times. The use of substances such as honeys or natural oils, among others, in treatment was already known in ancient Egypt, Rome and China [1,5]. Most likely, the first known description of a patient with AD was created by Gaius Svetonius Tranquillus, and the patient was the famous Emperor Octavian Augustus [5]. This information confirms that atopic dermatitis is a disease that people have faced since the dawn of time. It is for this reason that today, on the basis of accumulated knowledge, we are able to develop more and more targeted and effective therapy for patients with atopic dermatitis [1,5]. Previous studies confirm the effectiveness and safety of emollients for both children and adults. The systematic application of emollients to the skin can reduce the frequency of glucocorticosteroid applications in patients diagnosed with AD [1]. Numerous studies [4,23,24] also prove that the use of emollients from birth can have a preventive effect and thus prevent the development of atopic dermatitis in children with the aforementioned risk factors. The authors of [25] indicate that this risk is reduced by up to 50%. This is primarily due to the restoration of the epidermal barrier, which in turn results in reduced transepidermal water loss [25,26,27]. A parameter that has a beneficial effect on the skin after the use of emollients is the reduction in skin pH [28,29]. Studies have confirmed that acidic skin pH contributes to improved skin barrier function, and its higher values correlate with the course of AD [1,28,29]. For the above reason, the pH of washing products should be in the range of 5-6, since the acidic reaction of the preparations, as mentioned in the article, has a beneficial effect on the skin, without violating the skin barrier [24].
The physiological pH of the skin assumes values <5.0; this has a beneficial effect on the skin’s protective microbiota and supports the maintenance of a normal skin barrier [30]. In progressive AD, the skin barrier is often damaged, increasing the pH of the skin surface and facilitating the proliferation of pathogenic bacteria (such as Staphylococcus aureus) [30], which is highlighted in Figure 1 as a factor affecting skin barrier damage. In general, this is important in the context of the overall treatment of atopic dermatitis in the course of which there is a deficiency of valuable intercellular lipids of the stratum corneum, as well as defects in the filaggrin protein [24]. Any changes in this context in the aforementioned components result in increased transepidermal water loss [24]. The use of emollients should be a key and first line of treatment; it should also take into account the pathogenesis of AD and be a treatment that is clearly personalized and targeted to the individual patient [2,31].
2. Characteristics of Atopic Dermatitis: Types and Clinical Symptoms
Recent studies suggest that atopic dermatitis, as a heterogeneous and multifactorial disease, can be classified into different types. Taking into account all the classifications that have been created to group patients with AD, clinical features and the results of biochemical markers can be indicated as common criteria [2,12,32]. These include clinical symptoms, the state of the epidermal barrier, the level of IgE immunoglobulin in the blood and demographics such as age, gender or ethnicity [2,12,32].
The first such diagnostic criteria for AD were published by Hungarian dermatologist Georg Rajka [5]. Hanifin and Rajka’s criteria, which were published in 1980, are still widely used for diagnostic purposes [33]. They were developed based on clinical experience and the consensus of experienced dermatologists, but without objective clinical validation [34]. To diagnose atopic dermatitis in a patient, he or she should meet three of the four so-called “major” (main) criteria and three of the twenty-three “minor” (secondary) criteria [33] (Table 2).
Table 2.
Diagnostic criteria of atopic dermatitis according to Hanifin and Rajka based on [35].
It is noteworthy that only seven of the twenty-three minor criteria are due to immunological disorders, supporting the statement that atopic dermatitis is a multifactorial disease [33].
Currently, the most widely used scale that assesses both objective and subjective symptoms of atopic dermatitis is the SCORing Atopic Dermatitis Index (SCORAD) [36]. It was developed by the European Task Force on Atopic Dermatitis (ETFAD) in 1993. The severity of skin lesions is assessed based on six criteria: erythema, edema, oozing or scabs, lichenization and dry skin (ranging from 0, i.e., no lesions, to 3, i.e., the most severe lesions) [36]. Subjective symptoms (severity of pruritus and sleep disturbance), on the other hand, are assessed on an analog scale (0 to 10). Based on the above criteria, atopic dermatitis is assessed as mild (less than 25 points), moderate (25–50 points) and severe (>50 points) [36,37]. Numerous studies [36,37,38,39] on the validation of the SCORAD scale have confirmed that it is a reliable method in both clinical trials and daily medical practice. The SCORAD scale is sensitive to changes, easy to interpret and has good reproducibility in both the examination and diagnosis of children and adults with different courses of atopic dermatitis [36,37,38,39].
The classification distinguishes between external and internal subtypes of atopic dermatitis. The external subtype is characterized by high serum IgE levels and eosinophilia. In addition, there is an increase in the filaggrin mutation rate in the skin of these patients. The external subtype of AD often coexists with other allergic diseases [32,40]. In a study conducted by the authors [41], it was found that about 35% of children with moderate to severe atopic dermatitis also have another type of food allergy. In contrast, the intrinsic subtype of AD occurs with normal serum IgE levels. It is most common in women and has no atopic background [32,40].
Another classification can be a division that distinguishes between acute and chronic subtypes of AD. We can group atopic dermatitis by ethnic difference [40]. Tests have been conducted that analyzed the Asian endotype of atopic dermatitis. They showed increased TH17 levels in the blood and severe eczematous skin lesions in Japanese atopic dermatitis patients. The study [42] proved that TH17 lymphocytes were more markedly increased in acute eczematous lesions than in chronic conditions. In addition, TH17 lymphocytes were found to be the initial source of pro-inflammatory cytokines that led to eczematous skin lesions. In contrast, the European endotype showed no TH17 activation [40]. This indicates that Asian patients with atopic dermatitis are characterized by its unique subtype, which is based on immune dysfunction [40].
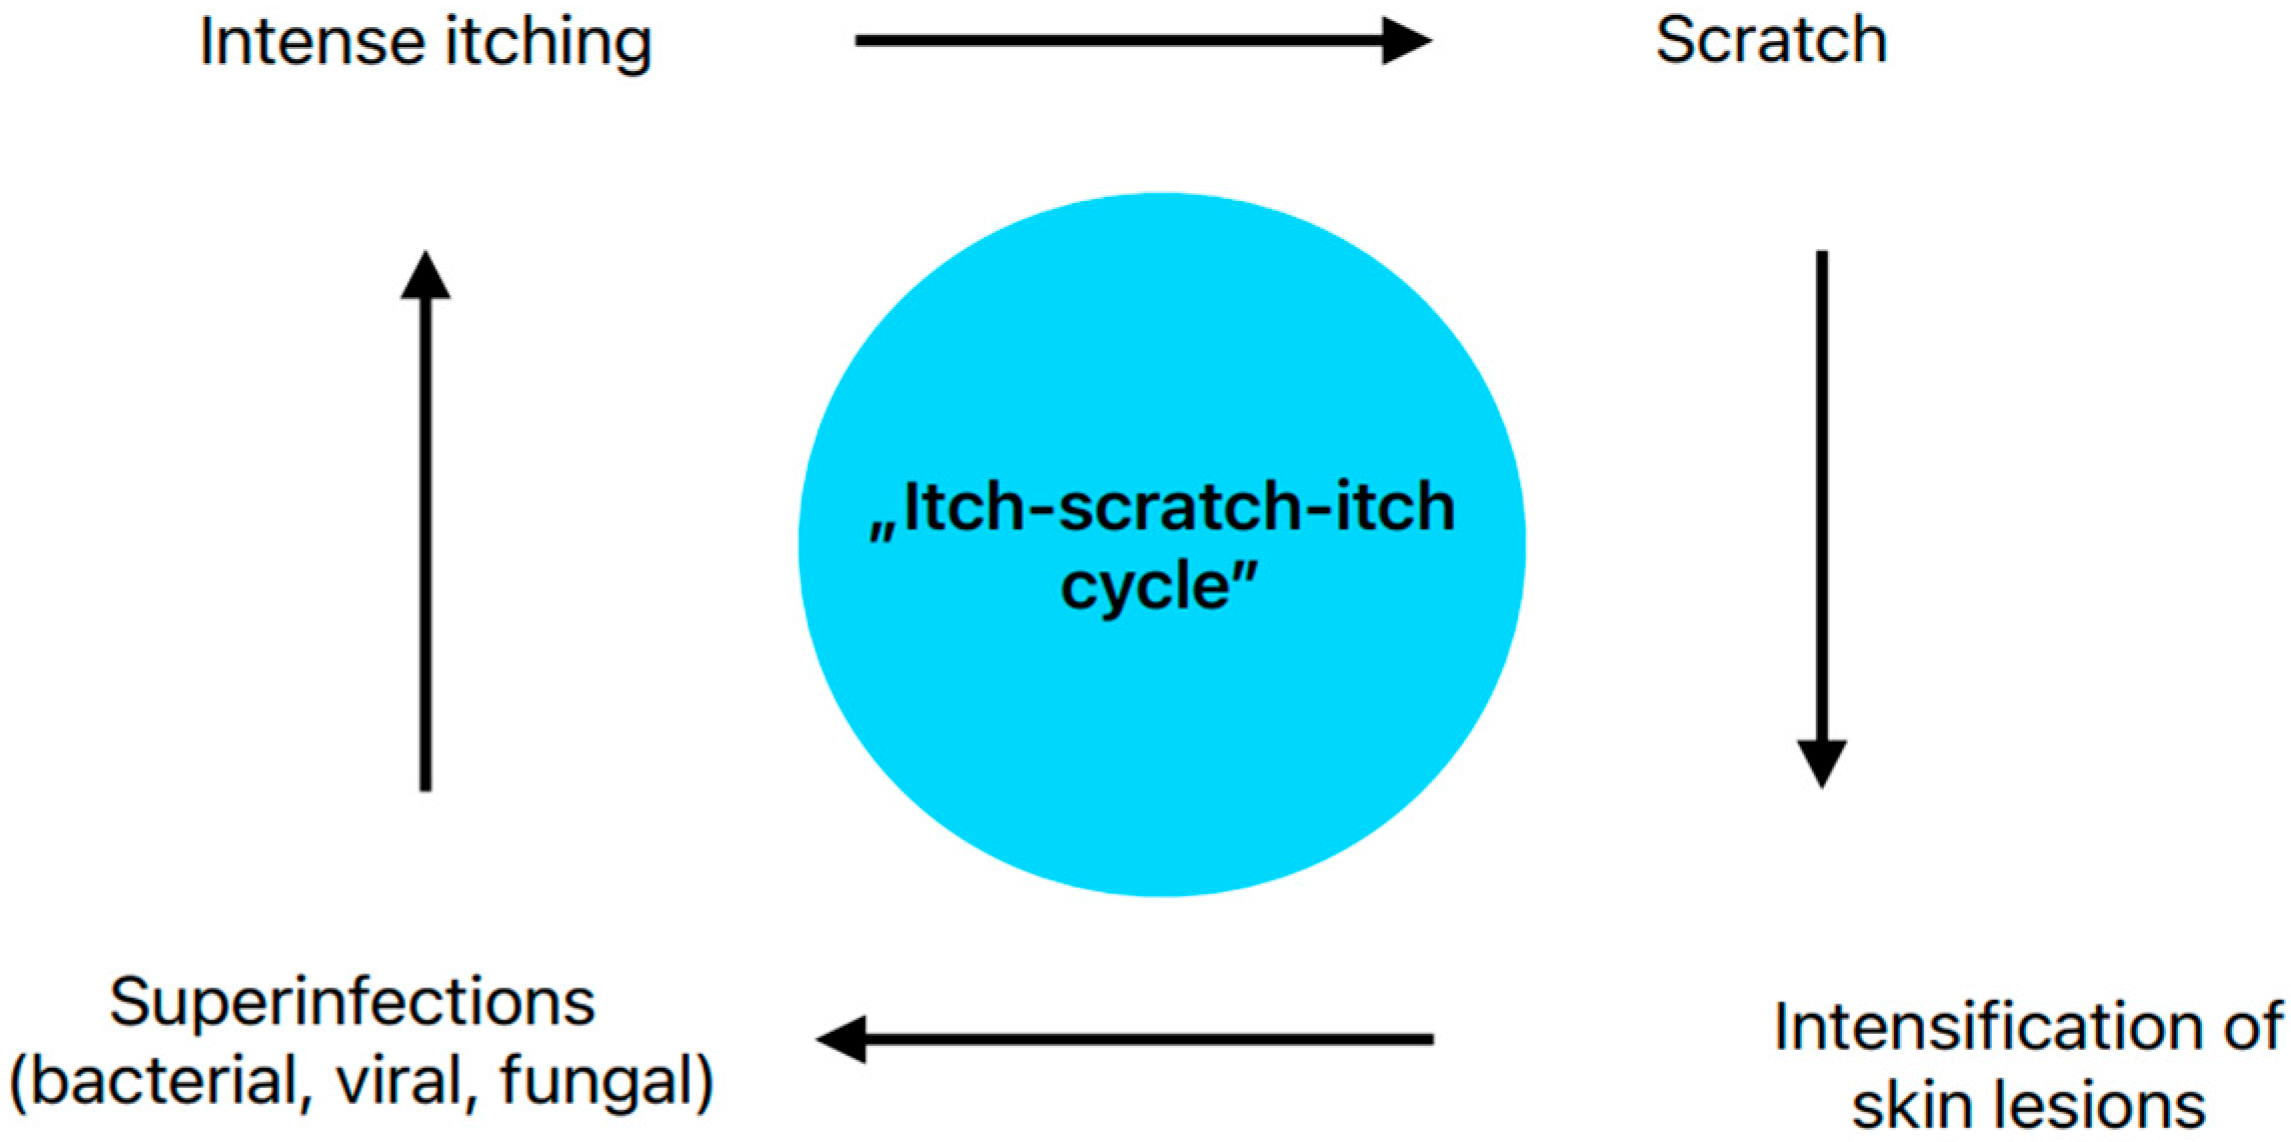
Determining a patient’s atopic dermatitis subtype is crucial to achieving favorable therapy outcomes. It also helps in the development of personalized treatment strategies [2,40]. Pruritus is a common and dominant feature of most subtypes of atopic dermatitis. It causes scratching, which worsens inflammation and can lead to bacterial superinfection, among other things. This condition is called the “Itch-scratch-itch cycle” [1,23,43,44,45] (Figure 2). Frequent bacterial or viral infections in AD patients are related to disorders of non-specific immunity, which are associated with a defective role of neutrophils [15].
Figure 2.
“Itch-scratch-itch cycle” in the course of atopic dermatitis based on [1,23,43,44,45].
Skin lesions in the course of atopic dermatitis are typically eczematous, characterized by papules, vesicles and sometimes scabs. The skin in the area is characterized by marked dryness and flaking [12,23].
3. Phenotypic and Endotypic Differences among Children and Adults with AD
The appearance of lesions and their localization in the course of atopic dermatitis varies depending on the age group. However, the basic features of AD—the presence of atopy and xerosis—are similar in both adults and children [46]. Most often, in infants and children, inflammation and lesions appear on the face, trunk and around the extensors of the lower and upper extremities, and in advanced cases even throughout the body. In adults, on the other hand, the lesions occur in the flexor region, neck, ears, around the eyes, and are more chronic in nature. A typical feature of the condition is dark red erythema on the face and neck [12,32,40]. From the data presented by the researchers in [47], it can be seen that 85% of AD cases manifest themselves before the age of five, thus indicating the greatest severity of symptoms among the younger population [47,48]. The data presented are consistent with population-based studies conducted in the United States, where the prevalence of atopic dermatitis in children was 10.7% and in adults 7.2% [48]. Atopic dermatitis can develop de novo in adulthood (about 25%), and in children AD can resolve before the age of five [11]. However, according to the authors [11,49], one in five pediatric patients with AD will develop symptoms of atopic dermatitis in adulthood. The authors of [32,40] report that a disorder of the immune system, which is not fully developed in the first weeks and months of life, is responsible for atopic lesions in younger patients. Initially, most T lymphocytes are immature and only gradually develop into memory cells [50]. Studies [50] show that immune changes, including T-cell activation and differentiation, occur more rapidly in children with AD. This indicates accelerated activation of these cells, faster differentiation into specific subsets (TH1, TH22, TH17) and the influence of environmental and genetic factors, as well as chronic skin inflammation [40,50,51]. Studies conducted to evaluate lymphocyte levels in newborns with atopic dermatitis have shown low levels of TH1 lymphocytes and high levels of TH2 in cord blood [40,51]. Epigenetic factors are responsible for the above condition, supporting the statement that atopic dermatitis is a typical multifactorial disease [40,51] (Figure 1).
Another study [40] on blood flow cytometry confirmed the delayed development of TH1 lymphocytes populating the skin of children with AD compared to healthy children. Increased blood concentrations of TH2 lymphocytes in both adults and children with AD are noted as a common feature [40].
The authors of [40] indicate that the number of tight junctions between epithelial cells in the skin is reduced and the expression of lipid barrier genes is decreased in children with AD. According to the authors of the above study, this has the effect of exacerbating the epidermal barrier defect in patients with atopic dermatitis despite normal levels of filaggrin protein in the skin [40]. A comparative study was conducted for three age groups (18–40, 41–60 and over 61) of atopic dermatitis patients [40]. The study observed that with age there is a decrease in TH2/TH22 levels with a concomitant increase in TH1/TH17, with a normalized epidermal barrier, which is a differentiating feature for AD occurring in adults compared to that in children [32,40]. Other differences in the course of AD in children and adults are presented in Table 3. The study [32,40] and also the study conducted by the authors of [51] indicated that therapy that is tailored to the age and specific stage of the disease is of great importance.
Table 3.
Endotypic and phenotypic and therapeutic differences in atopic dermatitis in children and adults based on [19,40,51,52].
4. Components of Emollients and Their Effect on the Changes That Occur in Atopic Dermatitis
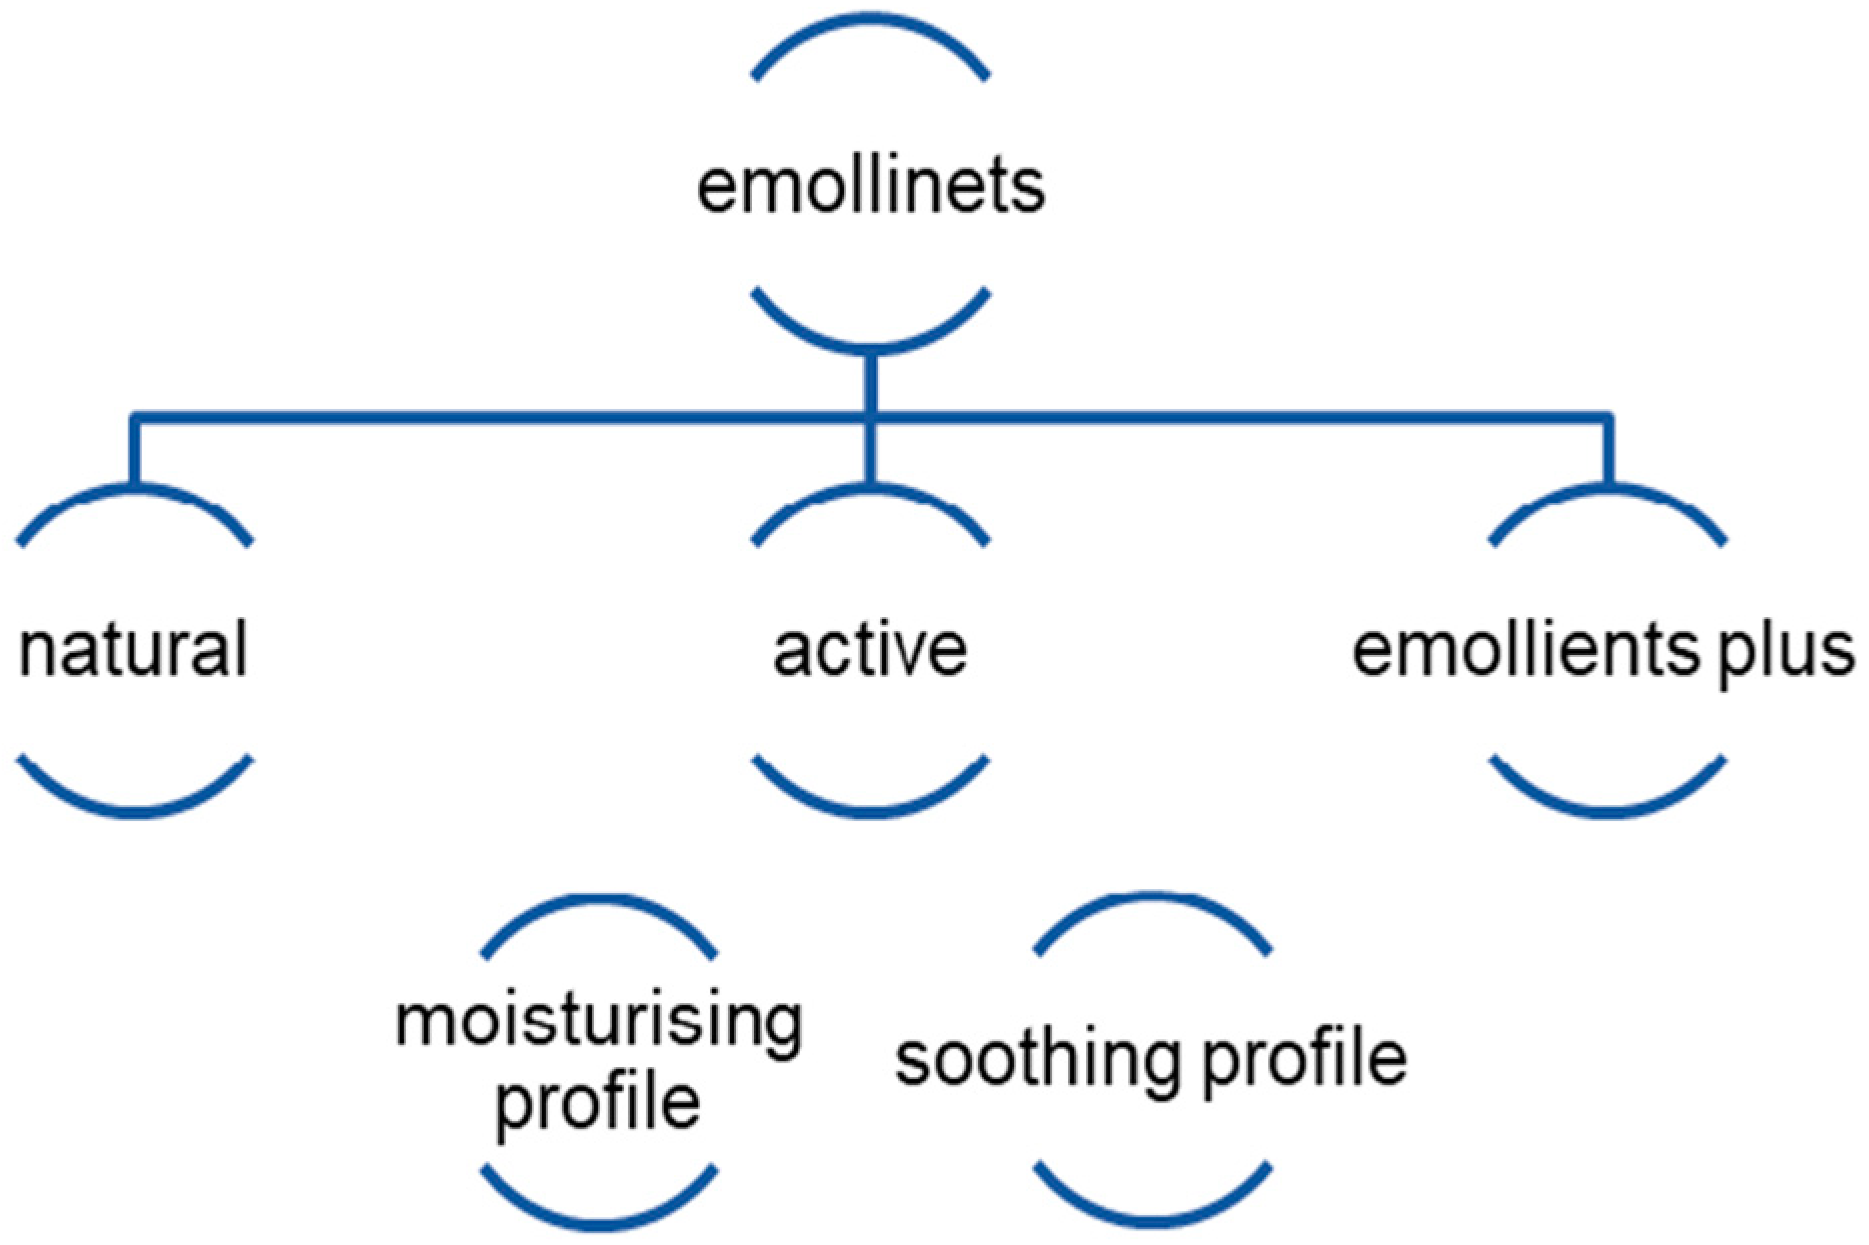
Most emollient products are based on humectants such as urea, glycerol or sorbitol. These ingredients promote hydration of the stratum corneum, reducing inflammation caused by AD [1,7,23,53]. Inherent in their composition is an occlusive substance, whose main function is to retain water, and prevent it from evaporating from the skin surface [1,23,53]. Occlusive ingredients in emollients, such as Vaseline, can improve skin barrier function and inhibit the production of pro-inflammatory cytokines [12,53]. Petrolatum, paraffin or mineral oils provide protection against adverse external factors and reduce TEWL [7]. Many emollients contain vegetable oils such as olive oil, coconut oil or avocado oil [53]. The authors of [7] state that components of emollients also include substances that seal the skin barrier, such as ceramides, cholesterol and fatty acids. Emollients by composition can be divided into two main groups: neutral emollients (containing only occlusive substances) and active emollients, which are divided by their profile of action—moisturizing and soothing [54]. Currently, an additional group of emollients is distinguished—emollient “plus”—which is included in the figure below [12,54] (Figure 3).
Figure 3.
Division of emollients based on [54].
Until recently, emollients did not contain additional active ingredients. Currently, “plus” emollients are used, whose composition is enriched with active ingredients [12]. The most commonly used active substances are as follows: flavonoids—saponins, riboflavin with extracts from young oat shoots and bacterial lysates from species such as Aquaphilus dolomiae or Viteoscilla filiformis [12,20,24]. There are also other substances that have beneficial effects on skin lesions in AD; for example, chamomile added to emollients has an anti-inflammatory effect due to the presence of apigenin, an ingredient that relieves symptoms of atopic dermatitis [53]. Emollients have anti-inflammatory properties if substances such as glycyrrhizinic acid, allantoin or D-panthenol are present in their formulation [19]. On the other hand, emollients with added camphor or menthol have antipruritic properties [19]. The authors of the papers [55,56] assure that the use of emollients with additives such as colloidal oats, avenanthramide or ceramides strengthens the skin barrier and is well tolerated in different age groups. Other researchers [20] emphasize that emollients “plus” restore normal microbial diversity in patients with mild to moderate AD. In their view, this is important because low microbial diversity and excessive colonization with Staphylococcus aureus leads to exacerbations and aggravation of atopic dermatitis. As evidenced by the studies [20,57], emollients supplemented with non-pathogenic Vitreoscilla filiformis bacteria reduce the severity of clinical symptoms as assessed by SCORAD, and also reduce pruritus in patients with AD. Another comparative study [58], which was conducted on a group of 60 patients with moderate AD, found that an emollient “plus” supplemented with Vitreoscilla filiformis bacteria normalized the skin microbiota and reduced the number and severity of eczematous lesions in AD compared to a traditional emollient. The authors of [57] confirm that Vitreoscilla filiformis is an extract that contains essential nutrients for cells and the skin microbiota. According to the aforementioned authors, it has optimal bio-affinity to the skin and mimics the action of beneficial skin microorganisms. Emollients that are enriched with certain vegetable oils—in particular sunflower, borage, corn or sea buckthorn—are beneficial due to the presence of essential fatty acids such as gamma-linolenic acid, linoleic acid, oleic acid, stearic acid, palmitic acid or medium-chain fatty acids (MCFA) in coconut oil [53,59]. The authors of [60] emphasize that natural oils such as sunflower oil, sesame oil and safflower seed oil have been used to restore skin barrier homeostasis. According to studies [7,53], they can improve skin barrier function, thereby reducing inflammation (by activating receptors through peroxisome proliferators). In addition, they help restore microbial homeostasis on the skin surface [7,53]. Restoring microbial balance is important because the stratum corneum is damaged in AD, which is caused by increased levels of endogenous and exogenous stratum corneum chymotryptase enzyme (SCCE), a protease produced by house dust mites or streptococci, among others [15]. This explains why the majority of patients with AD have a co-occurrence of IgE-mediated allergic reactions to airborne allergens which include house dust mites [15]. Table 4 summarizes most of the known and used active substances with proven therapeutic properties in AD.
Table 4.
Selected natural ingredients of emollients—action and their effectiveness.
Emollients “plus,” which typically contain allergenic ingredients such as plant proteins derived from peanuts or oats, should not be applied to the skin in children before the age of two, due to the intolerance and allergic properties of some ingredients [24].
Atopic skin, due to a defect in the epidermal barrier, is prone to irritation. For this reason, the authors of [18] recommend the use of emollients free of fragrances, preservatives and dyes.
A rare yet important component of emollients is substances of animal origin such as horse fat oil, which exhibits antimicrobial, anti-inflammatory and antipruritic effects [59]. The effect of horse oil on restoring the skin barrier was evaluated using a specially formulated dissolving microneedle patch (DMN). When applied transdermally, a significant improvement in the density of the epidermis and dermis, as well as an increase in skin elasticity and hydration were reported [59,84].
Another study in this area showed the anti-inflammatory effects of horse oil in reducing erythema and serum IgE immunoglobulin levels in contact hypersensitivity induced in mice. However, at this point, there are no ongoing and documented studies for the use of this oil in the treatment of patients with AD [59].
Another animal-derived ingredient mentioned by the authors [59,85] is lanolin, which is secreted from the sebaceous glands of sheep and obtained through wool processing. A study conducted to evaluate the effect of lanolin on the skin showed that daily use of an emollient with olive oil and lanolin (in a ratio of 30% olive oil and 70% lanolin) significantly improved skin condition compared to a water-in-oil emulsion used (containing neither olive oil nor lanolin) among a study population of newborns (without skin diseases) [86]. Lanolin and its derivatives are among the components of emollients that permanently restore the epidermal barrier, as its effects are longer lasting than those of occlusive emollients [1]. The authors point out that lanolin contained in cosmetics replenishes lipids in the stratum corneum reducing dryness of the skin, protects the skin from drying and cracking [52]. Lanolin is structurally similar to the structure of fetal synovial lipids, which is beneficial for restoring the epidermal barrier among newborns [1]. Until recently, lanolin was a common cause of allergy by the presence of fractions of free lanolin alcohols [1]. The above claims are explained by the concept of the lanolin paradox presented in 1986 by Wolf, who pointed out that lanolin is a component of drugs responsible for sensitization in a large number of patients, but at the same time is a safe compound in the general population [87]. According to the authors of [1], non-allergenic lanolin derivatives (liquid lanolin, as well as acetylated and ethoxylated lanolin alcohols) are currently in use.
Confirmation of the validity of the introduction of natural ingredients into the preparations used in the care of atopic skin was the work conducted by the authors [88,89,90,91]. The aforementioned authors confirmed the significant role of fats and oils in moisturizing the skin, specifically sheep tallow, hemp oil and walnut oil, while taking into account the benefit of introducing enzyme-modified fats into therapeutic preparations. They indicated that the model formulations they obtained may be used as moisturizing formulations and also as a preparation in the treatment of dry skin.
One of the commonly used ingredients of animal origin in emollients is honey [85,92]. Honey is a substance that deeply nourishes the epidermis and is rich in enzymes that naturally exfoliate the skin [85]. It is usually added to the formulation of cosmetics used at night and recommended for dry or mature skin [92]. Honey has humectant properties due to its high glucose and fructose content. Both of these substances can form hydrogen bridges with water [92]. According to the above authors, this increases water retention in the stratum corneum of the skin, which consequently increases hydration. Studies emphasize that honey’s moisturizing effect is also due to the presence of amino acids (proline, arginine, alanine, lysine, glycine, among others) and organic acids (gluconic acid, lactic acid, citric acid, succinic acid or acetic acid), which have corresponding functional groups (such as amine or carboxyl) [93]. They can form hydrogen bonds, enhancing the effect of water retention in the stratum corneum of the skin. According to the authors of [92,93], honey exerts a pH-regulating effect and prevents infections, due to its antimicrobial properties. Three factors contribute to this: the osmotic effect (allowing honey to interact strongly with water, leaving insufficient water for microorganisms), the acidic pH of honey and the release of hydrogen peroxide by the enzyme glucose oxidase.
One of the components of emollients is also ceramides, which, delivered in appropriate concentrations and proportions, improve the skin barrier and moisturize the skin [24,59]. They maintain the integrity of the skin barrier, which helps prevent water loss [24,59]. Studies have shown that the skin of patients with atopic dermatitis usually has reduced levels of ceramides [59]. However, in most cases, the ceramide content of over-the-counter remedies is too low to provide the above effects. When ceramides are provided without the addition of two other key lipids (cholesterol and at least one fatty acid), the epidermal barrier deteriorates [53]. Studies have confirmed that in order to restore normal skin barrier function, these three components should be supplied in a specific ratio [53]. One randomized study involving 100 patients divided into two groups evaluated the efficacy of a cream that contained ceramides and magnesium in the treatment of mild to moderate atopic dermatitis [94]. The authors of the above study compared the use of a cream with ceramides and magnesium to the effects of hydrocortisone and an emollient. After 6 weeks, the group that used ceramides and magnesium cream and hydrocortisone simultaneously showed a significant reduction in the intensity of clinical symptoms as assessed by the SCORAD scale and a reduction in TEWL. In contrast, the group that used ceramides and magnesium cream and an emollient at the same time had a higher score according to the SCORAD scale (indicating the severity of AD disease symptoms) and a higher TEWL. The study showed that all the above-described active ingredients improved the patients’ clinical condition after 6 weeks of use. However, only the simultaneous use of ceramides and magnesium cream in combination with applied hydrocortisone lowered SCORAD by 8.7 units [94].
In contrast, another study showed an increase in skin hydration and a significantly greater reduction in TEWL and a decrease in skin dryness in areas where the ceramide precursor moisturizer was applied, compared to skin to which it was not applied, after a 4-week application of the ceramide precursor moisturizer [95].
5. Use of Emollients in the Care of Skin with Atopic Dermatitis among Children and Adults
The use of emollients is the cornerstone of atopic dermatitis treatment. They help reduce the need for pharmacotherapy, including the use of glucocorticosteroids on the skin. Such management reduces the risk of side effects that follow steroid use, whose potential side effects include the development of Cushing’s syndrome, cataracts or whole-body endocrine disruption [12,17,31]. There are studies confirming that emollients reduce the severity of skin lesions in AD [31,96,97]. In clinical studies of so-called “plus” emollients, it has been noted that their use significantly reduces skin pruritus and improves skin hydration and epidermal barrier function [31]. One study on “plus” emollients, during which patients massaged the appropriate emollient twice a day onto clean and dry skin, showed that on day 21 of use there was a 115% increase in skin hydration and a 52% decrease in TEWL compared to baseline results for these parameters. Pruritus, erythema and exfoliation of the epidermis were reduced in those areas where application with emollient “plus” followed [96]. Another study confirmed that the use of emollients “plus” allowed a significant reduction in the amount of corticosteroids used compared to a control group using a classic emollient [97]. The same authors noted that after 28 days of its use, the skin showed improvement and thus the amount of corticosteroid treatment could be reduced. An additional added value in this study was the reduction in corticosteroid application to the skin in relation to the whole day.
The Cochrane Skin Group conducted a study during which the focus was on comparing the status of atopic dermatitis patients using moisturizers to control groups that did not use emollients with the active ingredients discussed earlier [98]. The study showed that patients were more likely to report an improvement in their skin condition when using a cream that contained urea in its formulation relative to patients using a placebo. It was confirmed that the urea-containing cream reduced skin dryness and reduced the number of recurrent lesions. Similar results were achieved in patients using moisturizing creams containing glycerol or oats [98]. Although there were fewer recurrences in the group using oat cream and the need for topical corticosteroids was reduced, there was a slight increase in the number of reported side effects such as burning, itching, erythema and folliculitis [98]. Nevertheless, study participants found moisturizing creams to be effective in reducing skin lesions and reducing pruritus compared to a control group that did not use emollients. And for allergic problems, the authors of [24,98] point to emollients with the simplest formulation with the least number of ingredients. On the other hand, the authors’ research led to the conclusion that ointments or creams containing 5–10% urea or 5–10% salicylic acid should be used in the chronic phase of atopic dermatitis [11].
The North American Contact Dermatitis Group conducted a study of three fragrance markers and six essential oils among them tea tree oil, which has anti-inflammatory effects on the skin lesions of AD patients [59]. The results of the above researchers confirmed the beneficial effect of tea tree oil on skin lesions in AD. Tea tree oil did not cause allergic reactions in 45% of patients allergic to other essential oils.
According to another study conducted by authors in a similar area, about one-third of adult patients developed contact allergies to the components of the emollients they used [24,59]. Most often, type IV sensitization appeared due to preservatives, fragrances or tocopherol included in emollients [24,59]. Another group of authors confirmed that the most common symptoms of type IV contact allergies included erythema, increased eczematous lesions and increased intensity of pruritus [23].
The authors of [53,99] emphasize that products should be chosen carefully, tailoring them to the needs of patients with atopic dermatitis. A 2017 study showed that topical application of moisturizers in mice, twice a day for 4 days, caused changes in the epidermis of varying severity. These changes included an increase in TEWL, an increase in skin surface pH and a decrease in skin hydration [53,99]. The same authors confirm that commercially available products may provide short-term relief, while if they exacerbate skin barrier disruption, they may initiate a vicious cycle (exacerbate skin dryness), requiring additional applications of skin care products. In contrast, other authors point out that one should be wary of over-the-counter emollients with a “dermatologically tested” label [97]. As it turned out, during a survey of companies, of the twenty-five companies that responded to the questionnaire, only four of them disclosed the number of people tested, and thirteen of them said that a dermatologist was present at one of the testing stages [59,97]. According to the authors of [59], such labeling can mislead patients, and skin care products that are widely available are not always safe.
6. Effect of Emollients on the Prevention of AD among Newborns and Children
Currently, we can distinguish three strategies in the prevention of atopic dermatitis: primary, secondary and tertiary prevention [23,100]. According to the recommendations of the Polish Dermatological Society, primary prophylaxis includes children at high risk but without disease symptoms. It involves prolonged breastfeeding (up to 4–6 months of age), limiting exposure to airborne allergens and using emollients from the first day of life [100]. Secondary prophylaxis of AD, on the other hand, applies to patients with fairly early symptoms of the disease, but without its advancement. It involves the introduction of appropriate care of the skin covered with lesions (use of emollients every 4–6 h) and avoidance of irritants, as well as elimination of allergens that exacerbate symptoms. And tertiary prevention, which applies to full-blown patients, focuses on reducing the severity of symptoms, preventing recurrence and the development of other allergic diseases. It is based on psychological counseling and patient education. Tertiary prophylaxis also includes the use of antihistamines and specific immunotherapy, which is used to prevent the development of symptoms from other organs [19,23,100,101].
More recently, emollients have been recommended for the prevention of primary atopic dermatitis in newborns. There are randomized trials that showed a 32% and 50% reduction in the risk of atopic dermatitis with regular use of emollients from birth in newborns with risk factors [24,25]. One study analyzed the effect of using emollients on improving the skin barrier and skin microbiota in 6-month-old infants with a positive family history of AD. According to the authors [28], reduced skin pH and increased Streptococcus salivarius in the skin microbiota after long-term use of emollients may have a preventive effect on the development of AD in children. The acidic pH of the skin counteracts the bacterial dysbiosis of the skin characteristic of atopic dermatitis [28]. Streptococcus salivarius strains have been shown to reduce the production of pro-inflammatory cytokines and chemokines interleukin-6 and interleukin-1 and -8 [28,102,103]. They also reduce TNF-alpha production in in vitro epithelial assays. S. salivarius stimulates TH1 lymphocytes and antagonizes TH2, and it is for this reason that its increased participation on the skin surface reduces inflammation initiated by TH2 lymphocytes in atopic dermatitis [28,102,103].
The Barrier Enhancement for Eczema Prevention study evaluated the impact of daily use of emollients during a child’s first year of life [104]. The study included 1394 infants with risk factors for developing AD. They were randomly divided into a group using emollients and a control group without the use of emollients [104]. According to the authors of the above study, the diagnosis of AD was made in 31% of infants in the group using emollients prophylactically and 28% of infants in the control group. Atopic dermatitis was diagnosed in these children between 12 and 60 months of age. The incidence of atopic dermatitis between the groups was thus comparable, and daily use of emollients in the first year of life did not significantly prevent the development of the disease. Similar results were obtained in a population-based study conducted at Oslo University Hospital and Ostfold Hospital Trust in Oslo and Karolinska University Hospital in Stockholm, which included 2397 newborns born between 2015 and 2017 [105]. They were assigned to four groups: a control group without skin care with infant feeding guidelines maintained, a group using skin softeners, a food intervention group (supplementing feeding with peanuts, cow’s milk, wheat and eggs) and a final group that combined skin and food interventions. As it turned out, AD was diagnosed in 8% of infants in the group with no skin or nutritional interventions, 11% of infants in the group that used emollients, 9% in the group that used supplemental feeding, and 5% in the group that combined skin and nutritional interventions. Thus, the introduction of emollients and appropriate supplemental nutrition did not reduce the development of atopic dermatitis for the infants studied.
7. Recommendations in the Use of Emollients in Atopic Dermatitis and Their Synergism with Other Behaviors and Therapies
Referring to the recommendations of dermatological societies in Europe (EADV, ETFAD) and in the United States (American Academy of Dermatology), it should be noted that they recommend the use of emollients in mild AD during periods of remission, while during exacerbations they indicate combining them with topical corticosteroids or calcineurin inhibitors [1]. The European Task Force on Atopic Dermatitis (ETFAD) recommends using large amounts of emollients in patients with AD—namely, a minimum of 30 g/day or 1 kg/month for an adult [24]. According to the European Academy of Dermatology and Venereology (EADV), on the other hand, the correct amount of emollient used per skin surface in children should be 150–200 g per week, while in adults it should be 500 g [1,106]. The authors of [23] do not recommend applying too many emollients to the skin, as a high frequency and large amounts can cause folliculitis or childhood seborrheic dermatitis. Also important in the application of emollients to the skin is the method of application, namely with clockwise circular motions [23].
Yet, in the context of the prevention of atopic dermatitis in newborns and children, the American College of Allergy, Asthma and Immunology says that further research is needed to evaluate the effect of emollients on the prevention of atopic dermatitis in newborns, as well as to determine whether the type of emollient applied, frequency, duration and age are relevant to the prevention of atopic dermatitis [107]. A similar position is represented by the European Task Force on Atopic Dermatitis, which does not provide recommendations for primary prevention of AD, as the quality and quantity of data in this area is not satisfactory [24].
The American Academy of Pediatrics recommends a skin care regimen based on the use of fragrance-free emollients after bathing [14]. The authors of [14] note that bathing in patients with AD can be carried out in lukewarm water for 10 to 15 min every 2 or 3 days. One randomized study evaluated the effect of bathing frequency on the severity of AD symptoms among 28 children (between 6 months and 10 years of age) [108]. Symptom improvement was measured using the SCORAD scale. As it turned out, bathing frequency had no significant effect on the course of AD. ETFAD recommends regular baths or showers in lukewarm 34–37 °C water from two to seven times a week using mild surfactants, and the preferred products should be galenic forms—syndets or emollients for washing based on softening oils. Bath emollients usually contain paraffin and synthetic fatty acid esters such as isopropyl myristate. These ingredients lubricate and soften the epidermis. At the same time, they are lightweight and allow oxygen and water exchange in the skin [1,18,24,109,110]. Sometimes emollients in the form of lotions, creams or cleansing products may contain antimicrobial ingredients (such as chlorhexidine) to limit the development of bacterial superinfections in AD [24,109,110]. Studies have proven that the use of harsh detergents and alkaline soaps adversely affected the skin lesions of patients with AD [23,24]. The ban on the use of soaps in atopic dermatitis is called the “Scholtz procedure” in the United States [18]. According to the authors of [111], it is extremely important to educate AD patients about skin care management especially in the context of children with atopic dermatitis. Unfortunately, studies continue to show that a significant percentage of patients with atopic dermatitis use soap for washing (about 40%) and do not use emollients after bathing (about 25%) [111].
In acute inflammation, topical anti-inflammatory treatment should be implemented first, followed by emollient care [24,53,112]. The authors of [10] emphasize that the application of emollients directly to acute inflammatory lesions may result in increased pruritus and burning of the skin. In acute inflammation, the so-called “wet-wrap” dressing is used, which involves bandaging the skin with moist compresses after applying emollients or anti-inflammatory drugs. This has an anti-inflammatory, antipruritic and cooling effect [18].
8. Conclusions
In summary, the above work aimed to indicate the validity of including emollients in therapy and skin care in atopic dermatitis. The meta-analysis we performed consistently set the direction of approach in this condition. We specifically focused on reports from the last few years to show the latest, least invasive behavior in this area. Therefore, taking into account the work of scientists and their guidelines, as well as the guidelines of health organizations from around the world on the treatment and care of skin with AD, it should be clearly stated that patients should use concomitant emollients along with anti-inflammatory drugs (if necessary). On the other hand, it should be noted that the choice of emollients should depend on the patient’s condition, the season or the area on the body affected by lesions. In general, it is worth noting that the minimization of the components of emollients in terms of coloring agents or fragrances, as well as their composition based on natural raw materials, brings the affinity of a given preparation to the skin of a healthy person closer, which thus affects the effectiveness and safety of the emollient.
Author Contributions
Conceptualization, S.M.O., Ł.B. and M.K.K.; formal analysis, M.K.K.; data curation, Ł.B. and S.M.O.; writing—original draft preparation, S.M.O., Ł.B. and M.K.K.; writing—review and editing, S.M.O., Ł.B. and M.K.K.; supervision, M.K.K. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Not applicable.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Kamińska, E. Rola Emolientów W Atopowym Zapaleniu Skóry U Dzieci. Dev. Period Med. 2018, 22, 396–403. [Google Scholar] [CrossRef] [PubMed]
- Garcia Gatmaitan, J.; Lee, J.H. Challenges and Future Trends in Atopic Dermatitis. Int. J. Mol. Sci. 2023, 24, 11380. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Torres, T.; Ferreira, E.O.; Gonçalo, M.; Mendes-Bastos, P.; Selores, M.; Filipe, P. Update on Atopic Dermatitis. Acta Médica Port. 2019, 32, 606. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salvati, L.; Cosmi, L.; Annunziato, F. From Emollients to Biologicals: Targeting Atopic Dermatitis. Int. J. Mol. Sci. 2021, 22, 10981. [Google Scholar] [CrossRef] [Scilit]
- Jaworek, A.K.; Wojas-Pelc, A. History of Atopic Dermatitis—A Short Review from Ancient to Modern Medicine. Dermatol. Rev. 2017, 104, 636–647. [Google Scholar] [CrossRef] [Scilit]
- Anania, C.; Brindisi, G.; Martinelli, I.; Bonucci, E.; D’Orsi, M.; Ialongo, S.; Nyffenegger, A.; Raso, T.; Spatuzzo, M.; De Castro, G.; et al. Probiotics Function in Preventing Atopic Dermatitis in Children. Int. J. Mol. Sci. 2022, 23, 5409. [Google Scholar] [CrossRef] [Scilit]
- Trzeciak, M.; Zysk, W.; Wolańska-Buzalska, D. “Emollients Plus” with Vitreoscilla Filiformis in Monotherapy and Adjunctive Therapy in Skin Diseases in Children. Dermatol. Rev. 2023, 110, 602–607. [Google Scholar] [CrossRef] [Scilit]
- Kim, J.; Kim, B.E.; Leung, D.Y.M. Pathophysiology of Atopic Dermatitis: Clinical Implications. Allergy Asthma Proc. 2019, 40, 84–92. [Google Scholar] [CrossRef] [Scilit]
- Moosbrugger-Martinz, V.; Leprince, C.; Méchin, M.-C.; Simon, M.; Blunder, S.; Gruber, R.; Dubrac, S. Revisiting the Roles of Filaggrin in Atopic Dermatitis. Int. J. Mol. Sci. 2022, 23, 5318. [Google Scholar] [CrossRef] [Scilit]
- Nowicki, R.; Grubska-Suchanek, E.; Trzeciak, M.; Wilkowska, A. Current Options and Perspectives for the Topical Treatment of Atopic Dermatitis. Dermatol. Rev. 2021, 108, 117–125. [Google Scholar] [CrossRef] [Scilit]
- Kanabaj, K.; Shawkat, S.; Kuźniak, A.; Adamski, Z.; Jenerowicz, D. Selected Clinical and Therapeutic Aspects of Atopic and Contact Dermatitis. Przegląd Dermatol. 2021, 108, 394–406. [Google Scholar] [CrossRef] [Scilit]
- Arents, B.; van Zuuren, E.; Fedorowicz, Z.; Hughes, O. Global Report on Atopic Dermatitis 2022 Atopicdermatitisatlas.org. 2022. Available online: https://www.eczemacouncil.org/assets/docs/global-report-on-atopic-dermatitis-2022.pdf (accessed on 17 October 2022).
- Clebak, K.T.; Helm, L.; Uppal, P.; Davis, C.R.; Helm, M.F. Atopic Dermatitis. Prim. Care Clin. Off. Pract. 2023, 50, 191–203. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Silverberg, N. Atopic Dermatitis Prevention and Treatment. Cutis 2017, 100, 173–177. [Google Scholar]
- Bartoszak, L.; Czarnecka-Operacz, M. Contact Allergy in Children with Atopic Dermatitis. Adv. Dermatol. Allergol. 2007, 24, 120–126. [Google Scholar]
- Murphy, P.B.; Hooten, J.N.; Atwater, A.R.; Gossman, W. Allergic Contact Dermatitis; StatPearls Publishing: Treasure Island, FL, USA, 2021. [Google Scholar]
- Abramovits, W.; Hung, P.; Tong, K.B. Efficacy and Economics of Topical Calcineurin Inhibitors for the Treatment of Atopic Dermatitis. Am. J. Clin. Dermatol. 2006, 7, 213–222. [Google Scholar] [CrossRef] [Scilit]
- Czarnecka-Operacz, M. Pielęgnacja Skóry Chorego Na Atopowe Zapalenie Skóry W Świetle Nowoczesnej Wiedzy Medycznej. Alergia 2015, 3, 24–28. [Google Scholar]
- Jurzak, M.; Rudyk, A. Składniki Aktywne Kosmetyków I Dermokosmetyków Stosowane W Pielęgnacji Skóry Z Atopowym Zapaleniem; Oficyna Wydawnicza: Warsaw, Poland, 2012. [Google Scholar]
- Zelenkova, H.; Kerob, D.; Salah, S.; Demessant-Flavigny, A.-L. Impact of Daily Use of Emollient “Plus” on Corticosteroid Consumption in Patients with Atopic Dermatitis: An Open, Randomized Controlled Study. J. Eur. Acad. Dermatol. Venereol. 2023, 37, 27–34. [Google Scholar] [CrossRef] [Scilit]
- Hlela, C.; Osei-Sekyere, B.; Yeboah Senyah, A. Emollients—Latest and Greatest Uses in Atopic Dermatitis. Curr. Allergy Clin. Immunol. 2022, 35, 2–5. [Google Scholar]
- Nola, I.; Kostović, K.; Kotrulja, L.; Lugović, L. The Use of Emollients as Sophisticated Therapy in Dermatology. Acta Dermatovenerol. Croat. 2003, 11, 80–87. [Google Scholar]
- Dębowska, D.; Monika Pasikowska-Piwko, N.; Katarzyna, N.; Kisiel, A. Terapia Emolientowa W Przebiegu Atopowego Zapalenia Skóry. Emollient Therapy in the Treatment of Atopic Dermatitis. Klin. Pediatryczna 2021, 29, 5028–5032. [Google Scholar]
- Wollenberg, A.; Christen-Zäch, S.; Taieb, A.; Paul, C.; Thyssen, J.P.; Bruin-Weller, M.; Vestergaard, C.; Seneschal, J.; Werfel, T.; Cork, M.J.; et al. ETFAD/EADV Eczema Task Force 2020 Position Paper on Diagnosis and Treatment of Atopic Dermatitis in Adults and Children. J. Eur. Acad. Dermatol. Venereol. 2020, 34, 2717–2744. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Simpson, E.L.; Chalmers, J.R.; Hanifin, J.M.; Thomas, K.S.; Cork, M.J.; McLean, W.H.I.; Brown, S.J.; Chen, Z.; Chen, Y.; Williams, H.C. Emollient Enhancement of the Skin Barrier from Birth Offers Effective Atopic Dermatitis Prevention. J. Allergy Clin. Immunol. 2014, 134, 818–823. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Simpson, E.L.; Berry, T.M.; Brown, P.A.; Hanifin, J.M. A Pilot Study of Emollient Therapy for the Primary Prevention of Atopic Dermatitis. J. Am. Acad. Dermatol. 2010, 63, 587–593. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Horimukai, K.; Morita, K.; Narita, M.; Kondo, M.; Kitazawa, H.; Nozaki, M.; Shigematsu, Y.; Yoshida, K.; Niizeki, H.; Motomura, K.; et al. Application of Moisturizer to Neonates Prevents Development of Atopic Dermatitis. J. Allergy Clin. Immunol. 2014, 134, 824–830.e6. [Google Scholar] [CrossRef] [Scilit]
- Glatz, M.; Jo, J.-H.; Kennedy, E.A.; Polley, E.C.; Segre, J.A.; Simpson, E.L.; Kong, H.H. Emollient Use Alters Skin Barrier and Microbes in Infants at Risk for Developing Atopic Dermatitis. PLoS ONE 2018, 13, e0192443. [Google Scholar] [CrossRef] [Scilit]
- Rippke, F.; Schreiner, V.; Doering, T.; Maibach, H.I. Stratum Corneum PH in Atopic Dermatitis. Am. J. Clin. Dermatol. 2004, 5, 217–223. [Google Scholar] [CrossRef] [Scilit]
- Capone, K.; Kirchner, F.; Klein, S.; Tierney, N. Effects of Colloidal Oatmeal Topical Atopic Dermatitis Cream on Skin Microbiome and Skin Barrier Properties. J. Drugs Dermatol. 2020, 19, 524–531. [Google Scholar] [CrossRef] [Scilit]
- Chandrashekar, B.S.; Luger, T.; Rajendran, S.C.; Parathasaradhi, A.; Thomas, J.; Ganjoo, A.; Sharma, D.; Damishetty, R.; Ruby, N.; Sujay, V.; et al. Role of Actives in Emollients in Atopic Dermatitis. J. Dermatol. Ski. Sci. 2024, 6, 16–23. [Google Scholar] [CrossRef] [Scilit]
- Tokura, Y.; Hayano, S. Subtypes of Atopic Dermatitis: From Phenotype to Endotype. Allergol. Int. 2021, 71, 14–24. [Google Scholar] [CrossRef] [Scilit]
- Marciniak, A.; Hasse-Cieślińska, M.; Jenerowicz, D.; Czarnecka-Operacz, M. The Role of Minor Hanifin and Rajka Criteria in Diagnosis of Atopic Dermatitis Patients. Post. Derm. Alerg. 2008, 25, 55–60. [Google Scholar]
- Brenninkmeyer, E.E.A. Atopic and Atopiform Dermatitis; University of Amsterdam: Amsterdam, The Netherlands, 2014. [Google Scholar]
- Fal, A. Alergia, Choroby Alergiczne, Astma; Medycyna Praktyczna: Cholerzyn, Poland, 2011. [Google Scholar]
- Bożek, A.; Reich, A. Assessment of the Severity of Atopic Dermatitis. Dermatol. Rev. 2016, 6, 479–485. [Google Scholar] [CrossRef] [Scilit]
- Oranje, A.P.; Glazenburg, E.J.; Wolkerstorfer, A.; de Waard-van der Spek, F.B. Practical Issues on Interpretation of Scoring Atopic Dermatitis: The SCORAD Index, Objective SCORAD and the Three-Item Severity Score. Br. J. Dermatol. 2007, 157, 645–648. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schmitt, J.; Langan, S.; Deckert, S.; Svensson, A.; von Kobyletzki, L.; Thomas, K.; Spuls, P. Assessment of Clinical Signs of Atopic Dermatitis: A Systematic Review and Recommendation. J. Allergy Clin. Immunol. 2013, 132, 1337–1347. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rehal, B.; Armstrong, A. Health Outcome Measures in Atopic Dermatitis: A Systematic Review of Trends in Disease Severity and Quality-of-Life Instruments 1985–2010. PLoS ONE 2011, 6, e17520. [Google Scholar] [CrossRef] [Scilit]
- Czarnowicki, T.; He, H.; Krueger, J.G.; Guttman-Yassky, E. Atopic Dermatitis Endotypes and Implications for Targeted Therapeutics. J. Allergy Clin. Immunol. 2019, 143, 1–11. [Google Scholar] [CrossRef] [Scilit]
- Kim, J.S. Pediatric Atopic Dermatitis: The Importance of Food Allergens. Semin. Cutan. Med. Surg. 2008, 27, 156–160. [Google Scholar] [CrossRef] [Scilit]
- Koga, C.; Kabashima, K.; Shiraishi, N.; Kobayashi, M.; Tokura, Y. Possible Pathogenic Role of Th17 Cells for Atopic Dermatitis. J. Investig. Dermatol. 2008, 128, 2625–2630. [Google Scholar] [CrossRef] [Scilit]
- Yosipovitch, G.; Papoiu, A.D.P. What Causes Itch in Atopic Dermatitis? Curr. Allergy Asthma Rep. 2008, 8, 306–311. [Google Scholar] [CrossRef] [Scilit]
- Hong, J.; Buddenkotte, J.; Berger, T.G.; Steinhoff, M. Management of Itch in Atopic Dermatitis. Semin. Cutan. Med. Surg. 2011, 30, 71–86. [Google Scholar] [CrossRef] [Scilit]
- Blume-Peytavi, U.; Metz, M. Atopic Dermatitis in Children: Management of Pruritus. J. Eur. Acad. Dermatol. Venereol. 2012, 26, 2–8. [Google Scholar] [CrossRef] [Scilit]
- Ramírez-Marín, H.A.; Silverberg, J.I. Differences between Pediatric and Adult Atopic Dermatitis. Pediatr. Dermatol. 2022, 39, 345–353. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brunner, P.M.; Israel, A.; Zhang, N.; Leonard, A.; Wen, H.-C.; Huynh, T.; Tran, G.; Lyon, S.; Rodriguez, G.; Immaneni, S.; et al. Early-Onset Pediatric Atopic Dermatitis Is Characterized by TH2/TH17/TH22-Centered Inflammation and Lipid Alterations. J. Allergy Clin. Immunol. 2018, 141, 2094–2106. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Avena-Woods, C. Overview of Atopic Dermatitis. Am. J. Manag. Care 2017, 23, S115–S123. [Google Scholar] [PubMed]
- Kowalska-Olędzka, E.; Czarnecka, M.; Baran, A. Epidemiology of Atopic Dermatitis in Europe. J. Drug Assess. 2019, 8, 126–128. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Esaki, H.; Czarnowicki, T.; Gonzalez, J.; Oliva, M.; Talasila, S.; Haugh, I.; Rodriguez, G.; Becker, L.; Krueger, J.G.; Guttman-Yassky, E.; et al. Accelerated T-Cell Activation and Differentiation of Polar Subsets Characterizes Early Atopic Dermatitis Development. J. Allergy Clin. Immunol. 2016, 138, 1473–1477.e5. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, L.; Leonard, A.; Pavel, A.B.; Malik, K.; Raja, A.; Glickman, J.; Estrada, Y.D.; Peng, X.; del Duca, E.; Sanz-Cabanillas, J.; et al. Age-Specific Changes in the Molecular Phenotype of Patients with Moderate-To-Severe Atopic Dermatitis. J. Allergy Clin. Immunol. 2019, 144, 144–156. [Google Scholar] [CrossRef] [Scilit]
- Śliwa, K.; Sikora, E.; Ogonowski, J. Kosmetyki Do Pielęgnacji Skóry Atopowej. Wiadomości Chem. 2011, 65, 651–673. [Google Scholar]
- Elias, P.M.; Wakefield, J.S.; Man, M.-Q. Moisturizers versus Current and Next-Generation Barrier Repair Therapy for the Management of Atopic Dermatitis. Ski. Pharmacol. Physiol. 2018, 32, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Grześk-Kaczyńska, M.; Petrus-Halicka, J.; Kaczyński, S.; Bartuzi, Z.; Ukleja-Sokołowska, N. Should Emollients Be Recommended for the Prevention of Atopic Dermatitis?—New Evidence and Current State of Knowledge. J. Clin. Med. 2024, 13, 863. [Google Scholar] [CrossRef] [Scilit]
- Fowler, J.F.; Nebus, J.; Wallo, W.; Eichenfield, L.F. Colloidal Oatmeal Formulations as Adjunct Treatments in Atopic Dermatitis. J. Drugs Dermatol. 2012, 11, 804–807. [Google Scholar]
- Fowler, J.; Silverberg, N. Active Naturals Have a Key Role in Atopic Dermatitis. Semin. Cutan. Med. Surg. 2008, 27, 8–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gueniche, A.; Liboutet, M.; Cheilian, S.; Fagot, D.; Juchaux, F.; Breton, L. Vitreoscilla Filiformis Extract for Topical Skin Care: A Review. Front. Cell. Infect. Microbiol. 2021, 11, 747663. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seite, S.; Zelenkova, H.; Martin, R. Clinical Efficacy of Emollients in Atopic Dermatitis Patients—Relationship with the Skin Microbiota Modification. Clin. Cosmet. Investig. Dermatol. 2017, 10, 25–33. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hon, K.L.; Kung, J.S.C.; Ng, W.G.G.; Leung, T.F. Emollient Treatment of Atopic Dermatitis: Latest Evidence and Clinical Considerations. Drugs Context 2018, 7, 1–14. [Google Scholar] [CrossRef] [Scilit]
- Lin, T.-K.; Zhong, L.; Santiago, J. Anti-Inflammatory and Skin Barrier Repair Effects of Topical Application of Some Plant Oils. Int. J. Mol. Sci. 2017, 19, 70. [Google Scholar] [CrossRef] [Scilit]
- Wyszkowska-Kolatko, M.; Koczurkiewicz, P.; Wójcik, K.; Pękala, E. Medicinal Plants Used in Skin Diseases Treatment. Postępy Fitoter. 2015, 3, 184–192. [Google Scholar]
- Shadi, T.Z.; Talal, A.Z. A Review of Four Common Medicinal Plants Used to Treat Eczema. J. Med. Plants Res. 2015, 9, 702–711. [Google Scholar] [CrossRef] [Scilit]
- Varma, S.R.; Sivaprakasam, T.O.; Arumugam, I.; Dilip, N.; Raghuraman, M.; Pavan, K.B.; Rafiq, M.; Paramesh, R. In Vitro Anti-Inflammatory and Skin Protective Properties of Virgin Coconut Oil. J. Tradit. Complement. Med. 2019, 9, 5–14. [Google Scholar] [CrossRef] [Scilit]
- Verallo-Rowell, V.M.; Dillague, K.M.; Syah-Tjundawan, B.S. Novel Antibacterial and Emollient Effects of Coconut and Virgin Olive Oils in Adult Atopic Dermatitis. Dermat. Contact Atopic Occup. Drug 2008, 19, 308–315. [Google Scholar] [CrossRef] [Scilit]
- Casetti, F.; Wölfle, U.; Gehring, W.; Schempp, C.M. Dermocosmetics for Dry Skin: A New Role for Botanical Extracts. Ski. Pharmacol. Physiol. 2011, 24, 289–293. [Google Scholar] [CrossRef] [Scilit]
- Danby, S.G.; AlEnezi, T.; Sultan, A.; Lavender, T.; Chittock, J.; Brown, K.; Cork, M.J. Effect of Olive and Sunflower Seed Oil on the Adult Skin Barrier: Implications for Neonatal Skin Care. Pediatr. Dermatol. 2012, 30, 42–50. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nadora, D.; Burney, W.; Chaudhuri, R.K.; Galati, A.; Min, M.; Fong, S.; Lo, K.; Chambers, C.J.; Sivamani, R.K. Prospective Randomized Double-Blind Vehicle-Controlled Study of Topical Coconut and Sunflower Seed Oil-Derived Isosorbide Diesters on Atopic Dermatitis. Dermatitis 2024, 35, S62–S69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eichenfield, L.F.; McCollum, A.; Msika, P. The Benefits of Sunflower Oleodistillate (SOD) in Pediatric Dermatology. Pediatr. Dermatol. 2009, 26, 669–675. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, J.-H.; Choi, D.-K.; Lee, S.-S.; Choi, S.J.; Kim, C.D.; Yoon, T.-J.; Lee, J.-H. Enhancement of Keratinocyte Differentiation by Rose Absolute Oil. Ann. Dermatol. 2010, 22, 255. [Google Scholar] [CrossRef] [Scilit]
- Puglia, C.; Bonina, F. In Vivo Spectrophotometric Evaluation of Skin Barrier Recovery after Topical Application of Soybean Phytosterols. J. Cosmet. Sci. 2008, 59, 217–224. [Google Scholar]
- Walczak-Zeidler, K.; Felczak-Guzik, A.; Nowak, I. Oleje Roślinne Stosowane Jako Surowce Kosmetyczne—Leksykon; Cursiva: Warsaw, Poland, 2013. [Google Scholar]
- Schäfer, N.; Sobczyk, M.; Burczyk, D.; Balwierz, R.; Skotnicka-Graca, U. Possibilities of Using Vegetable Oils in Acne Skin Care. Aesthetic Cosmetol. Med. 2022, 11, 49–54. [Google Scholar] [CrossRef] [Scilit]
- Awazuhara, H.; Kawai, H.; Baba, M.; Matsui, T.; Komiyama, A. Antigenicity of the Proteins in Soy Lecithin and Soy Oil in Soybean Allergy. Clin. Exp. Allergy 1998, 28, 1559–1564. [Google Scholar] [CrossRef] [Scilit]
- Bettzuege-Pfaff, B.I.; Melzer, A. Treating Dry Skin and Pruritus with a Bath Oil Containing Soya Oil and Lauromacrogols. Curr. Med. Res. Opin. 2005, 21, 1735–1739. [Google Scholar] [CrossRef] [Scilit]
- Kim, J.N.; Han, S.N.; Ha, T.J.; Kim, H.-K. Black Soybean Anthocyanins Attenuate Inflammatory Responses by Suppressing Reactive Oxygen Species Production and Mitogen Activated Protein Kinases Signaling in Lipopolysaccharide-Stimulated Macrophages. Nutr. Res. Pract. 2017, 11, 357. [Google Scholar] [CrossRef] [Scilit]
- Zielińska, A.; Nowak, I. Abundance of Active Ingredients in Sea-Buckthorn Oil. Lipids Health Dis. 2017, 16, 95. [Google Scholar] [CrossRef] [Scilit]
- Resich-Kozieł, L.; Niemyska, K. Zastosowanie Oleju Z Rokitnika W Kosmetologii. Kosmetol. Estet. 2020, 9, 187–191. [Google Scholar]
- Koskovac, M.; Cupara, S.; Kipic, M.; Barjaktarevic, A.; Milovanovic, O.; Kojicic, K.; Markovic, M. Sea Buckthorn Oil—A Valuable Source for Cosmeceuticals. Cosmetics 2017, 4, 40. [Google Scholar] [CrossRef] [Scilit]
- Kurek-Górecka, A.; Balwierz, R.; Mizera, P.; Nowak, M.; Żurawska-Płaksej, E. Znaczenie Terapeutyczne I Kosmetyczne Oleju Konopnego. Farm. Pol. 2018, 74, 704–708. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wydro, D. The Effect of Oral Supplementation with Omega-3 and 6 Acids on Skin Condition—Pilot Study. Acad. Aesthet. Anti-Aging Med. 2012, 4, 46–54. [Google Scholar]
- Callaway, J.; Schwab, U.; Harvima, I.; Halonen, P.; Mykkänen, O.; Hyvönen, P.; Järvinen, T. Efficacy of Dietary Hempseed Oil in Patients with Atopic Dermatitis. J. Dermatol. Treat. 2005, 16, 87–94. [Google Scholar] [CrossRef] [Scilit]
- Zielińska, A.; Nowak, I. Kwasy Tłuszczowe W Olejach Roślinnych I Ich Znaczenie W Kosmetyce. Chemik 2014, 68, 103–110. [Google Scholar]
- Chrząstek, L.; Dondela, B.; Deska, M. Safe Components of Cosmetics Lipids and Derivative. Pr. Nauk. Akad. Im Jana Długosza W Częstochowie Technol. Inform. Inżynieria Bezpieczeństwa 2015, 3, 9–27. [Google Scholar] [CrossRef] [Scilit]
- Lee, C.; Eom, Y.; Yang, H.; Jang, M.; Jung, S.; Park, Y.; Lee, S.; Jung, H. Skin Barrier Restoration and Moisturization Using Horse Oil-Loaded Dissolving Microneedle Patches. Ski. Pharmacol. Physiol. 2018, 31, 163–171. [Google Scholar] [CrossRef] [Scilit]
- Cristiano, L.; Guagni, M. Zooceuticals and Cosmetic Ingredients Derived from Animals. Cosmetics 2022, 9, 13. [Google Scholar] [CrossRef] [Scilit]
- Kiechl-Kohlendorfer, U.; Berger, C.; Inzinger, R. The Effect of Daily Treatment with an Olive Oil/Lanolin Emollient on Skin Integrity in Preterm Infants: A Randomized Controlled Trial. Pediatr. Dermatol. 2008, 25, 174–178. [Google Scholar] [CrossRef] [Scilit]
- Żmudzińska, M.; Czarnecka-Operacz, M. The Lanolin Paradox Phenomenon. Adv. Dermatol. Allergol. 2008, 25, 66–68. [Google Scholar]
- Kowalska, M.; Woźniak, M.; Paździor, M. Assessment of the Sensory and Moisturizing Properties of Emulsions with Hemp Oil. Acta Polytech. Hung. 2017, 14, 183–195. [Google Scholar] [CrossRef] [Scilit]
- Kowalska, M.; Mendrycka, M.; Zbikowska, A.; Kowalska, D. Assessment of a Stable Cosmetic Preparation Based on Enzymatic Interesterified Fat, Proposed in the Prevention of Atopic Dermatitis. Acta Pol. Pharm. 2017, 74, 465–476. [Google Scholar] [PubMed]
- Kowalska, M.; Żbikowska, A.; Woźniak, M.; Amanowicz, A. Quality of Emulsions Based on Modified Watermelon Seed Oil, Stabilized with Orange Fibres. Molecules 2022, 27, 513. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kowalska, M.; Woźniak, M.; Turek, P.; Żbikowska, A. New Fat Bases in Model Emulsion Systems in Physicochemical and Consumer Evaluation. Appl. Sci. 2024, 14, 3553. [Google Scholar] [CrossRef] [Scilit]
- Ab Hadi, H. Honey, a Gift from Nature to Health and Beauty: A Review. Br. J. Pharm. 2016, 1, 46–54. [Google Scholar] [CrossRef] [Scilit]
- Burlando, B.; Cornara, L. Honey in Dermatology and Skin Care: A Review. J. Cosmet. Dermatol. 2013, 12, 306–313. [Google Scholar] [CrossRef] [Scilit]
- Koppes, S.; Charles, F.; Lammers, L.; Frings-Dresen, M.; Kezic, S.; Rustemeyer, T. Efficacy of a Cream Containing Ceramides and Magnesium in the Treatment of Mild to Moderate Atopic Dermatitis: A Randomized, Double-Blind, Emollient- and Hydrocortisone-Controlled Trial. Acta Derm. Venereol. 2016, 96, 948–953. [Google Scholar] [CrossRef] [Scilit]
- Simpson, E.; Böhling, A.; Bielfeldt, S.; Bosc, C.; Kerrouche, N. Improvement of Skin Barrier Function in Atopic Dermatitis Patients with a New Moisturizer Containing a Ceramide Precursor. J. Dermatol. Treat. 2013, 24, 122–125. [Google Scholar] [CrossRef] [Scilit]
- Gasparri, F. Effects of a Novel Emollient Cream on Skin Moisture, Epidermal Barrier Function and Atopic Dermatitis Signs and Symptoms: Results from a Clinical Study. In Proceedings of the 24th World Congress of Dermatology, Milan, Italy, 10–15 June 2019. [Google Scholar]
- Dinani, N.; Patel, M.; George, S. ‘Dermatologically Tested’: What Does It Really Mean? Br. J. Dermatol. 2017, 177, 176. [Google Scholar]
- van Zuuren, E.J.; Fedorowicz, Z.; Lavrijsen, A.; Christensen, R.; Arents, B. Emollients and Moisturisers for Eczema. Cochrane DatabaseSyst.Rev. 2016, 2. [Google Scholar] [CrossRef] [Scilit]
- Li, Z.; Hu, L.; Elias, P.M.; Man, M.-Q. Skin Care Products Can Aggravate Epidermal Function: Studies in a Murine Model Suggest a Pathogenic Role in Sensitive Skin. Contact Dermat. 2017, 78, 151–158. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nowicki, R.; Trzeciak, M.; Kaczmarski, M.; Wilkowska, A.; Czarnecka-Operacz, M.; Kowalewski, C.; Rudnicka, L.; Kulus, M.; Mastalerz-Migas, A.; Peregud-Pogorzelski, J.; et al. Atopic Dermatitis. Interdisciplinary Diagnostic and Therapeutic Recommendations of the Polish Dermatological Society, Polish Society of Allergology, Polish Pediatric Society and Polish Society of Family Medicine. Part I. Prophylaxis, Topical Treatment and Phototherapy. Alergol. Pol. Pol. J. Allergol. 2019, 6, 69–80. [Google Scholar] [CrossRef] [Scilit]
- Hamelmann, E.; Herz, U.; Holt, P.; Host, A.; Lauener, R.P.; Matricardi, P.M.; Wahn, U.; Wickman, M. New Visions for Basic Research and Primary Prevention of Pediatric Allergy: An IPAC Summary and Future Trends. Pediatr. Allergy Immunol. 2008, 19, 4–16. [Google Scholar] [CrossRef] [Scilit]
- Kaci, G.; Goudercourt, D.; Dennin, V.; Pot, B.; Doré, J.; Ehrlich, S.D.; Renault, P.; Blottière, H.M.; Daniel, C.; Delorme, C. Anti-Inflammatory Properties of Streptococcus Salivarius, a Commensal Bacterium of the Oral Cavity and Digestive Tract. Appl. Environ. Microbiol. 2014, 80, 928–934. [Google Scholar] [CrossRef] [Scilit]
- Eyerich, K.; Novak, N. Immunology of Atopic Eczema: Overcoming the Th1/Th2 Paradigm. Allergy 2013, 68, 974–982. [Google Scholar] [CrossRef] [Scilit]
- Bradshaw, L.E.; Wyatt, L.A.; Brown, S.J.; Haines, R.H.; Montgomery, A.A.; Perkin, M.R.; Lawton, S.; Sach, T.H.; Chalmers, J.R.; Ridd, M.J.; et al. Emollients for Prevention of Atopic Dermatitis: 5-Year Findings from the BEEP Randomized Trial. Allergy 2022, 78, 995–1006. [Google Scholar] [CrossRef] [Scilit]
- Skjerven, H.O.; Rehbinder, E.M.; Vettukattil, R.; LeBlanc, M.; Granum, B.; Haugen, G.; Hedlin, G.; Landrø, L.; Marsland, B.J.; Rudi, K.; et al. Skin Emollient and Early Complementary Feeding to Prevent Infant Atopic Dermatitis (PreventADALL): A Factorial, Multicentre, Cluster-Randomised Trial. Lancet 2020, 395, 951–961. [Google Scholar] [CrossRef] [Scilit]
- Czarnecka-Operacz, M.; Sadowska-Przytocka, A. The Updated Knowlegde on Proper Skin Care Modalities in Patients with Atopic Dermatitis. Alergia 2015, 3, 24–26. [Google Scholar]
- Katibi, O.S.; Cork, M.J.; Flohr, C.; Danby, S.G. Moisturizer Therapy in Prevention of Atopic Dermatitis and Food Allergy: To Use or Disuse? Ann. Allergy Asthma Immunol. 2022, 128, 512–525. [Google Scholar] [CrossRef] [Scilit]
- Koutroulis, I.; Petrova, K.; Kratimenos, P.; Gaughan, J. Frequency of Bathing in the Management of Atopic Dermatitis. Clin. Pediatr. 2014, 53, 677–681. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tarr, A.; Iheanacho, I. Should We Use Bath Emollients for Atopic Eczema? BMJ 2009, 339, b4273. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gallard, S. Emollient Ingredients: Making the Best Clinical Choice for Older Patients. Dermatol. Nurs. 2022, 21, 27–30. [Google Scholar]
- Hon, K.L.E.; Leung, T.F.; Wong, Y.; So, H.K.; Li, A.M.; Fok, T.F. A Survey of Bathing and Showering Practices in Children with Atopic Eczema. Clin. Exp. Dermatol. 2005, 30, 351–354. [Google Scholar] [CrossRef] [Scilit]
- Wollenberg, A.; Kinberger, M.; Arents, B.; Aszodi, N.; Avila Valle, G.; Barbarot, S.; Bieber, T.; Brough, H.A.; Calzavara Pinton, P.; Christen-Zäch, S.; et al. European Guideline (EuroGuiDerm) on Atopic Eczema: Part I—Systemic Therapy. J. Eur. Acad. Dermatol. Venereol. 2022, 36, 1409–1431. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).