


Abstract
Permanent Supportive Housing (PSH) provides housing and supportive services for individuals experiencing homelessness, yet less is known about how the built environment can support residents’ dignity and well-being. This study assessed the feasibility of multimodal methods for examining Dignified Design in PSH using an interdisciplinary, in situ research approach. Nine methods were piloted, including four physiological measures (ActiGraph, Fibion, Upmood, and hormonal assay), two psychological methods (condensed photovoice and moving interviews), and three design-based approaches (Dignified Design Assessment Tool, Dignified Design Inventory, and space syntax analysis). Methods were evaluated based on feasibility, participant acceptance and burden, technical and logistical considerations, and researcher expertise. Most methods were generally feasible and appropriate for field-based research, although important differences emerged across approaches. Physiological measures presented technical challenges and variable data yield; psychological methods required greater participant engagement and introduced participant burden; and design-based methods required greater researcher expertise. Findings demonstrate the complementary strengths and limitations of different approaches and support the potential value of multimodal methods for examining relationships among the built environment, occupant experience, and dignity in PSH. This study contributes to methodological development for interdisciplinary research on design and occupant well-being in residential environments.
1. Introduction
1.1. Homelessness, Trauma, and the Built Environment
Homelessness is a persistent and growing problem despite ongoing efforts to reduce the number of unhoused people. According to the U.S. Department of Housing and Urban Development’s Annual Homeless Assessment Report (AHAR), the number of people experiencing homelessness reached an unprecedented 771,480 during the 2024 Point-in-Time count, representing an 18 percent increase from 2023 [1,2]. This means that nearly 23 out of every 10,000 Americans are sleeping in emergency shelters, safe havens, places deemed unfit for human habitation, or unsheltered locations [1]. Living without a home, or without shelter, is rife with traumatic experiences, including the physical and psychological stress and depression of searching for a home and shelter and exposure to exploitation by bad actors, as well as many others [2].
Permanent Supportive Housing (PSH) has emerged as a leading intervention for addressing chronic homelessness by combining affordable housing with on-site supportive services. However, providing PSH shelter and services alone may not be sufficient to promote health and healing for residents. The quality of the built environment is a critical yet often overlooked aspect of PSH. Design influences how residents experience comfort, safety, and self-worth. As a result, the environment can either facilitate or hinder the goals of PSH [3,4,5,6]. Unfortunately, we lack valid, acceptable measures of the PSH built environment to test its impact on residents. This paper tests the feasibility of measuring the PSH built environment using a Dignified Design framework.
1.2. Dignified Design as a Framework for Healing and Well-Being
Dignity is often discussed as a social or interpersonal construct; however, it is also embedded within the environments people inhabit [7,8]. The built environment can support or undermine an individual’s sense of worth, belonging, and agency through its tangible features and the opportunities these features afford or deny [7]. In this way, the physical environment serves as more than a backdrop to human experience; it is a participant and contributor to the promotion of dignity. Dignity, therefore, may be reflected both in the physical characteristics of the built environment and in the health and well-being outcomes of the individuals utilizing spaces.
The Dignified Design Model [9] is a maturing framework that illustrates how the built environment can provide more than basic shelter from the stress and trauma frequently associated with homelessness [10,11]. Drawing on principles of trauma-informed design, the model seeks to create environments that support health, healing, and dignity for individuals who have experienced homelessness, trauma, and social marginalization [11]. Despite growing interest in the Dignified Design framework, methods for assessing its presence and impacts within supportive housing environments remain underdeveloped. Existing studies have relied primarily on surveys, interviews, and architectural analyses, with limited exploration of multimodal approaches that integrate physiological, psychological, and environmental measures. Before implementing such approaches to evaluate Dignified Design outcomes, researchers must establish their feasibility within PSH settings.
2. Literature Review
2.1. The Dignified Design Conceptual Model
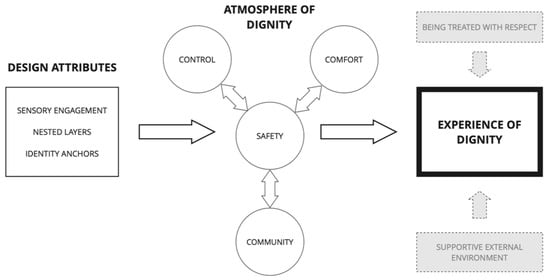
Dignified Design evolved from earlier models of trauma-informed care and trauma-informed design while intentionally expanding to assume a strength-based, salutogenic orientation that emphasizes the dynamic interplay between individuals and their environment [9]. Dignified Design is informed by empirical research in the social and cognitive sciences, as well as the lived expertise of building occupants [7,9]. The conceptual model of Dignified Design, shown in Figure 1, illustrates the relationships among the design attributes that constitute the physical environment, the intended affordances that shape occupants’ experience of safety, and how these experiences contribute to the expression of dignity [9].
Figure 1.
Conceptual Model of Dignified Design [9].
Comfort, community, control, and safety emerged as core principles of dignity in supportive housing settings, with safety revealed as an outcome of the interdependent experiences of comfort, community, and control [9]. The model suggests that design attributes and experiences support dignity, not directly but through the affordances they create, enabling occupants to experience greater comfort, develop meaningful social connections, exercise choice and personal agency, and, ultimately, feel safe within their environments. In this way, dignity emerges as an outcome of the dynamic interaction between individuals and the physical and social conditions of the spaces they inhabit.
2.2. Dignified Design in Permanent Supportive Housing
Although Dignified Design can be applied across a range of environments, it may be particularly relevant within Permanent Supportive Housing (PSH) settings. PSH serves individuals who have experienced homelessness and who have histories of trauma, chronic stress, social exclusion, mental illness, and physical health challenges [9,12]. Research suggests that the physical environment can influence residents’ safety, well-being, and community integration—all critical to housing stability and recovery [5]. Design features that support self-regulation, connection, and choice have been associated with improved mental health, reduced stress, and a stronger sense of belonging [5,13]. These findings suggest that the built environment is more than a backdrop for shelter and service delivery; it actively shapes occupants’ experiences, relationships, and view of self.
2.3. Challenges in Measuring Dignified Design
Because Dignified Design was recently developed and introduced to the broader scholarly and design community, no studies have yet examined its impact on the health and well-being of PSH residents. However, several studies have measured and evaluated earlier iterations of trauma-informed design (TID) and related human-centered, intentional design approaches. These studies have relied primarily on self-reported surveys, interviews, and other qualitative and computational methods, including photographic analysis, floor plan analysis, and space syntax, to assess the effects of the built environment and TID on occupant well-being [12,13,14,15,16,17,18]. Additional studies exploring TID or versions of intentional design outside of the PSH context also tend to use surveys and interviews to examine the impact of design on various health outcomes [19,20], with one study utilizing biometric measures [19]. Many of these studies were conducted in laboratory or virtual settings, which limits their ability to capture the realities and complexities of authentic lived experiences within actual spaces.
Another challenge lies in operationalizing what to measure when evaluating Dignified Design. Existing approaches tend to focus either on abstract attributes of buildings (e.g., visibility or permeability in space syntax analysis) or on the experiences and outcomes reported by building occupants (e.g., satisfaction surveys). We conclude that no single method can fully capture the nuanced qualities of a space or the mechanisms through which it influences occupants. This conclusion suggests that evaluating Dignified Design requires methods that assess environmental conditions, occupant experiences, and the outcomes associated with those conditions. Consequently, a multimodal approach is well-suited to capturing the complexity of dignity within supportive housing environments.
2.4. A Multimodal Approach to Measuring Dignified Design
Given our Model of Dignified Design (see Figure 1), in which comfort, community, control, and safety in the built environment ultimately scaffold experiences of dignity, we identified a number of ways to measure dignity and its component parts, as well as stress as a core physiological response to the built environment.
2.4.1. Psychological Methods
Psychological approaches typically rely on participants’ perceptions and self-reported experiences. For example, community is often operationalized as social connectedness and its inverse, isolation or loneliness, and is typically measured using subjective scales and self-report questionnaires [21,22,23,24,25]. Similarly, perceptions of safety, control, and autonomy are commonly assessed through surveys, questionnaires, interviews, and other subjective measures [26,27,28].
2.4.2. Physiological Methods
Physiological methods offer a complementary perspective by measuring objective indicators of stress and well-being. Research suggests that the built environment, including its design, layout, and sensory characteristics, can influence the body’s stress response in both regulatory and stimulatory ways [29]. Research in medicine, neuroscience, and public health has identified numerous physiological biomarkers associated with stress and well-being, including cortisol, dehydroepiandrosterone (DHEA), blood pressure, heart rate variability (HRV), and allostatic load [29,30,31].
2.4.3. Design and Environmental Methods
A third category of measurements focuses on the built environment itself. Methods such as space syntax, environmental monitoring (e.g., measuring humidity, noise levels, and air quality), and assessments of daylight and access to nature examine environmental factors that may contribute to experiences of comfort, community, control, and safety [32,33,34]. Unlike psychological and physiological measures, which assess human perceptions, experiences, or outcomes, design-focused methods evaluate the spatial and environmental conditions that may then elicit patterns of psychological responses, experiences, or behaviors.
3. Study Aim
Taken together, these approaches suggest that dignity may be best understood by integrating multiple complementary forms of evidence. However, the feasibility of administering these methods in PSH settings remains largely unknown. This study builds on the limited evidence of measuring the impacts and outcomes of Dignified Design by assessing the feasibility of implementing multiple potential Dignified Design measurement methods in PSH environments. Specifically, the study identifies: (1) which Dignified Design measurement methods are appropriate for assessing Dignified Design characteristics; (2) which Dignified Design measurement methods are feasibly administered in a PSH setting; (3) which Dignified Design measurement methods are acceptable to residents, staff, and researchers; and (4) which Dignified Design measurement methods have the greatest potential to validly measure key dimensions of the Dignified Design Model.
4. Methods
4.1. Study Design
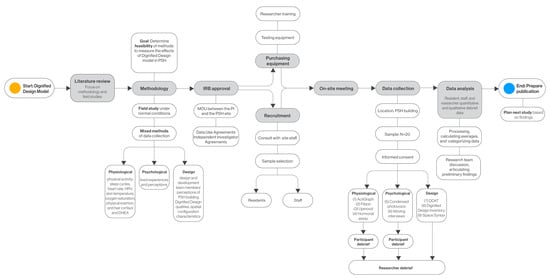
This study used a mixed-methods design to assess the feasibility of a multimodal approach to measuring Dignified Design in PSH. The primary objective was not to evaluate outcomes associated with Dignified Design itself but to assess the feasibility and overall fit of a diverse set of methods for future use in PSH settings. Nine methods across three complementary measurement domains—(1) physiological, (2) psychological, and (3) design—were tested. Together, these methods were selected to capture multiple dimensions of the built environment and its relationship to experiences of safety, comfort, community, control, and dignity. Feasibility was assessed through debrief interviews and surveys conducted by: (1) PSH residents; (2) staff in PSH; and (3) researchers participating in both data collection and facilitation. An overview of the research process is presented in Figure 2.
Figure 2.
Research Process Flowchart.
4.2. Study Setting
This study was conducted at a PSH site in the Mountain West region of the United States. The two-story building opened in 2024 with a total built area of 42,807 square feet and 54 one- and two-bedroom apartments for single adults and couples who previously experienced homelessness and a disabling condition. As a PSH site, the building is staffed by property management and maintenance personnel and a supportive services team, and includes dedicated spaces for case management, community gatherings, and other onsite programming. The site was selected because the architecture firm intentionally employed a Dignified Design approach and because the building’s recent completion reflected the latest application of Dignified Design principles. The study received Institutional Review Board (IRB) approval from the University of Denver. The researchers secured a Memorandum of Understanding (MOU) between the University of Denver and the PSH site. Additionally, the researchers secured Data Use Agreements and Independent Investigator Agreements with the institutions of all participating researchers, including Bryn Mawr College, Florida State University, and Shopworks Architecture.
4.3. Participants and Recruitment
Convenience and purposive sampling were used to recruit building residents and staff interested in participating in the study. The study sample (N = 20) included eight residents and two staff living and working at the PSH site, three members of the PSH site’s design and development team, and seven researchers (see Appendix A). Participants were recruited from March to May 2025. Site staff approached residents who they believed would be open to and capable of engaging with the various data collection methods being piloted. Given the exploratory nature of the study and the range of methods being tested in a PSH setting, inclusion criteria for resident participants required that they: (a) reside in the building; (b) be at least 18 years of age; and (c) demonstrate the mental and physical capacity necessary for study activities, including moving around the building, operating technology, and engaging in direct physical contact. Staff participants were recruited during a staff meeting by identifying individuals who were available and willing to participate on the scheduled on-site testing day. Residents and staff were recruited into one of two cohorts (morning or afternoon). To minimize fatigue and participant burden, each participant tested a total of two methods. The PSH site’s design and development team identified and contacted members directly to test a single method. Informed consent was obtained from all study participants prior to participation.
4.4. Study Procedures
This study tested the feasibility of nine individual methods. These methods were categorized according to whether they measured physiological responses, assessed psychological reactions, or evaluated design characteristics of the built environment. The methods assessed in this study were as follows: physiological methods—(1) ActiGraph (Ametris, FL, USA), (2) Fibion (Fibion, Jyväskylä, Finland), (3) Upmood (Taison Digital Limited, Hong Kong, China), and (4) hormonal assay; psychological methods—(5) condensed photovoice and (6) moving interviews; and design methods—(7) the Dignified Design Assessment Tool (DDAT), (8) Dignified Design Inventory, and (9) space syntax analysis.
The research team, consisting of seven researchers from the partner research institutions, facilitated study activities and participated in researcher-administered data collection. A lead and a support researcher were assigned to each method to oversee testing, which included purchasing and testing devices and equipment for collecting physiological data, preparing testing materials, training other researchers to assist with testing as needed, facilitating testing with participants, collecting relevant data, and leading analysis efforts.
In August 2025, before data collection began, the research team met with staff and residents at the study site to present study details and set participation expectations. The DDAT was also administered virtually to members of the design and development team who oversaw the project.
In September 2025, researchers conducted a full day of on-site testing, during which they piloted all physiological and psychological methods, as well as one design method (the Dignified Design Inventory). Participants in the morning cohort tested one of three wearable devices (Fibion, ActiGraph, or Upmood) as well as a condensed photovoice approach. Participants received the wearable devices on the on-site testing day and were instructed to wear them for the next seven days for electronic collection of biometric data. Actual wear time and the proportion of usable recordings were not quantified. Participants in the afternoon cohort completed moving interviews and a hormonal assay. After each activity, participants in both morning and afternoon sessions were individually debriefed by an assigned research team member. One week after the on-site testing day, researchers returned to the PSH site to retrieve the wearable devices and equipment and to conduct debrief interviews with participants who tested the wearable devices. Researchers also piloted the Dignified Design Inventory during the on-site testing day (Figure 3).
Figure 3.
Researchers on site completing the Dignified Design Inventory.
4.5. Multimodal Assessment Measures
4.5.1. Physiological Methods
ActiGraph. ActiGraph LEAP is a wearable tracking device that monitors a person’s physical activity, sleep cycles, and vital signs, including heart rate, heart rate variability (HRV), skin temperature, and oxygen saturation (all measured during the pilot). ActiGraph LEAP devices were paired with mobile phones provided to the participants, on which the device’s app was installed, enabling the devices to transmit data directly to participants’ accounts via Bluetooth. The pilot period began with participant orientation to discuss the device’s purpose, when and how to wear it, how to connect to the device’s app, and to answer any participant questions. Researchers conducted frequent remote device monitoring to check device activation and apparent use; these checks did not quantify wear time or establish continuous recording or signal quality. Researchers also checked in with participants by phone halfway through the pilot period. After testing, researchers downloaded data as CSV files from the cloud platform provided by the device supplier, Artemis, and consulted with Artemis staff to help interpret the data.
Fibion. Fibion Helix was piloted for interval-based monitoring of physical activity, sleep cycles, and vital signs, including heart rate, heart rate variability (HRV), and skin temperature. The research team initially envisioned using the device primarily to track sleep. Like the ActiGraph LEAP, the pilot period began with participant orientation to review device-use guidelines. The Fibion was also connected to a mobile phone for data transmission, and researchers monitored the data and checked in on the participant by phone halfway through the testing period. After data collection, researchers downloaded data from the application provided by Power Flow, a partner of the application and device provider, Fibion. These intended outputs should be distinguished from the data actually obtained: the expected HRV data were not recorded, and sleep recordings were too irregular or limited for confident analysis (Section 5.1.2).
Upmood. Upmood was piloted to collect biometric data, including heart rate, heart rate variability, and physical exertion. Notably, Upmood also estimates moment-to-moment affective states (i.e., valence and arousal), offering a proxy for an individual’s emotional state (i.e., anxious, sad, tense, happy, excited, unpleasant, calm, zen, pleasant, challenged, or confused) as well as a composite stress score [35]. Upmood devices were connected to mobile phones provided to participants via the Upmood app, enabling data from the PPG sensor to be transmitted via Bluetooth. Like ActiGraph LEAP and Fibion HELIX, the pilot period began with an overview of the equipment, and researchers conducted frequent remote monitoring to check device activation and apparent recording status; these checks did not establish continuous recording or quantify adherence. Researchers also checked in with participants halfway through the pilot period about device use. All data were transmitted to and stored on Upmood servers. Following the data collection phase, researchers received a data file from Upmood.
Hormonal Assay. Hair cortisol and DHEA samples were collected by cutting a small section of hair directly from the back of each participant’s head. Participants also completed a questionnaire about lifestyle factors known to affect hormone levels, including medications and hair treatments. Researchers mailed the samples and questionnaires to the Human & Animal Integrated Research (HAIR) Lab at the Yale Child Study Center within one week of data collection. The lab processed the samples, and the research team received cortisol results electronically in November 2025. After reviewing the results and consulting with the lab, researchers requested additional DHEA testing. The lab delivered those results in January 2026. The hormones tested in this study, cortisol and DHEA, were selected because they provide complementary information about an individual’s stress response. Cortisol reflects physiological stress activation, whereas DHEA serves as a counter-stress hormone [36].
4.5.2. Psychological Methods
Condensed Photovoice. Photovoice is a well-established community-based participatory research method that prompts participants to take photographs, which are then used to stimulate dialogue about their lived experiences from their own perspective [37,38]. This study piloted an abridged version of the traditional photovoice approach [39], condensing what would typically involve multiple engagement sessions into a single exercise. Participants received instructions on how to use a provided digital camera, along with written prompts to take photos of indoor and/or outdoor spaces within the PSH site where they felt safe or unsafe, comfortable or uncomfortable, in control or not in control, and connected or disconnected from the community, based on the core principles of Dignified Design. After approximately 20 min of photographing spaces throughout the property, each participant met with a researcher, who uploaded the photographs to a laptop computer. With the participant’s consent, the researcher audio-recorded the participant’s interpretations of each image. The recordings were then transcribed for analysis.
Moving Interviews. The researchers conducted moving interviews one-on-one with a resident or staff participant. The moving interview protocol was tailored to the unique PSH environment in which the study was conducted. Examples of questions included “Tell me about your experience in the building” and “Can you take me to a space where you connect most with staff, either most often or with the highest quality connection?” Each interview took approximately 30 min and was audio-recorded with the participant’s consent. The recordings were then transcribed for analysis.
4.5.3. Design Methods
Dignified Design Assessment Tool. The Dignified Design Assessment Tool (DDAT) [40] captures design and development team members’ perceptions of a project’s Dignified Design qualities. The DDAT assesses core concepts including safety, comfort, community, and control; end user engagement; external environmental conditions that influenced design decisions; and commitment to ongoing Dignified Design learning. Design and development team members are asked to write four separate one-hundred-word narratives describing the project’s Dignified Design process and resulting features. Completion of the DDAT yields a score between 0 and 16, with 0 indicating very low levels of Dignified Design and 16 indicating very high levels.
Dignified Design Inventory. The Dignified Design Inventory is a tool that documents the Dignified Design architectural elements both inside and outside a building based on the Dignified Design theoretical model, noting specific design affordances (safety, comfort, community, and control) and design attributes (sensory engagement, nested layers, and identity anchors). While moving through a building, researchers are encouraged to use a ‘note catcher’ to capture and document the affordances and attributes present or absent within each space, as well as their personal experience of the space. Researchers were trained in the use of the observation tool prior to data collection. At the PSH site, they received a 15-min guided tour of the building led by building management staff, followed by a 45-min self-guided observation and note-taking period. Researchers were also encouraged to photograph spaces and design elements referenced in their notes.
Space Syntax. Space syntax is a computational method for analyzing building configurations to identify the organizational hierarchies embedded in the design and to reveal potential navigational, communal, or segregational patterns. The space syntax approach uses visibility (what people can see from any point within a building) and permeability (where people can move from any point in a building) as measures for spatial analysis. For this study, a member of the research team analyzed architectural floor plans using the Isovist platform developed by McElhinney and Benedikt [41]. Researchers examined the visibility measures of mean visual depth (MVD), integration, intelligibility, overt control, and choice to map potential navigational, congregational, activity, and privacy patterns in the building configuration. In other words, these measures evaluate the spatial qualities of functional spaces in the building, including how well they are connected, their ease of access, and the location of key junction and control spaces. Before performing the analysis, the floor plans were linked in the Isovist application. For each measure, Isovist generated data in two complementary formats: visual floor plan graphs and numerical data in an Excel spreadsheet. Researchers then calculated averages and correlation coefficients as part of the analysis.
4.6. Data Collection
Two primary data sources captured detailed input on the feasibility of each method: resident and staff debrief reports and researcher debrief reports.
4.6.1. Resident and Staff Debriefs
After testing each method, residents and staff debriefed with a member of the research team. Debrief sessions lasted approximately 15 to 30 min, depending on the participant and method. For participants piloting wearable devices, researchers returned to the study site one week later to conduct individual debrief sessions. The debrief process included 15 scaled and open-ended questions assessing participant comprehension and perceptions of comfort and safety during testing of each method. Quantitative data reported participants’ perceptions of comfort, safety, and clarity on a five-point Likert-type scale, where 1 = not at all and 5 = extremely positive/negative.
4.6.2. Researcher Debriefs
Members of the research team also participated in a debrief process. After all methods had been tested, researchers were asked to complete a debrief form for each method in which they were involved, either as facilitators or as direct participants (as was the case for the Dignified Design Inventory and space syntax). The forms were tailored to each method’s specific requirements and included six to eight scaled and open-ended questions assessing perceptions of comfort and safety, ease of administration, appropriateness for measuring an atmosphere of dignity, and overall experience. Researchers also completed eight additional open-ended questions about the overall on-site testing day, including the most meaningful or actionable aspects, the most challenging aspects, ethical and privacy concerns, and potential improvements to the testing process. Quantitative data reported on researchers’ perceptions of comfort, safety, and overall experience for each tested method along a five-point Likert-type scale. For comfort and safety, 1 = not at all and 5 = extremely positive/negative. For overall experience, 1 = extremely negative and 5 = extremely positive. Researchers completed the debrief process within two weeks of the on-site testing day to ensure accurate and descriptive reporting. Researchers took 30 to 90 min to complete the full researcher debrief form.
4.7. Data Analysis
The primary objective of data analysis was to apply a structured evaluation framework to assess the feasibility of each of the nine tested methods for use in Dignified Design research within PSH settings. To do this, two researchers first independently analyzed the full collection of staff and resident debrief data, as well as researcher debrief data, to populate the first five categories of the feasibility assessment. Lead researchers were asked to review and add notes to the first five categories as well as complete the remaining six method-specific categories. For each method, the feasibility assessment scores were compiled to create an Average Assessment Score. The full research team then considered the implementation, usability, and perceived value of each method to arrive at an Overall Fit assessment.
4.7.1. Feasibility Assessment
Researchers evaluated each method across five implementation-focused domains using a three-point rating scale (1 = low, 2 = medium, and 3 = high). Researchers assigned ratings based on a synthesis of staff and resident quantitative and qualitative debrief responses, researcher quantitative and qualitative debrief responses, and first-hand implementation experience. Notes were documented alongside ratings to establish rationale and facilitate discussion among the research team.
- Viability: The extent to which the method could be successfully implemented to collect data.
- User Friendliness: The extent to which participants were able to complete research activities as intended.
- Researcher Facilitation: The ease with which researchers were able to administer the methods and carry out associated research activities.
- Logistics: The degree to which technical, technological, or spatial challenges affected setup, implementation, or data collection.
- Acceptability: The perceived appropriateness of administering the method in a PSH setting without placing unnecessary burden on participants or the resident and staff community.
4.7.2. Method-Specific Categories
Each method was also evaluated on additional technical features using the same three-point rating scale (1 = low, 2 = medium, 3 = high), with supporting narrative notes for further discussion.
- Adherence: This category applied only to wearable devices. Researchers’ qualitative assessment of device use was informed by remote monitoring, participant check-ins, debrief feedback, and a review of the downloaded data files. Wear time and adherence percentages were not quantified, and adherence ratings did not represent attainment of a prespecified wear-time threshold.
- Data Yield and Quality: This category applied only to wearable devices. Researchers’ qualitative assessment of recording completeness and the availability of the expected biometric data were informed by review of downloaded data files and technical issues encountered during testing. Valid recording hours, valid days, and percentages of usable data were not calculated.
- Content: This refers to the extent to which the method captured the intended information, experiences, or environmental characteristics it was designed to assess. For example, this criterion evaluated whether condensed photovoice elicited meaningful data related to Dignified Design affordances; whether the Dignified Design Inventory documented design attributes; or whether moving interviews generated relevant discussions of safety, comfort, community, and control.
- Relevance: This is the extent to which the method assessed key concepts of the Dignified Design Model.
- Depth/Breadth: This is the volume and richness of Dignified Design-related information collected by the method.
- Quality: This refers to the perceived accuracy, completeness, and overall integrity of the resulting data.
4.7.3. Average Assessment Score and Overall Fit
For each method, the team averaged ratings across the applicable domains to generate an Average Assessment Score, providing an overall indicator of feasibility and methodological performance. The research team then considered each method’s Average Assessment Score alongside all other available data to evaluate its overall suitability for assessing Dignified Design in PSH settings. This final analysis resulted in an Overall Fit assessment for each method on a rating scale of low to high (low, moderately low, medium, moderately high, high). The complete scoring framework and ratings for all methods are included in Appendix A.
5. Results
A summary of the Average Assessment Score and Overall Fit assessments for each of the nine methods is presented in Table 1.
Table 1.
Average assessment scores and overall fit assessments for the nine tested methods.
As shown in Table 1, ActiGraph, hormonal assay, condensed photovoice, and the Dignified Design Inventory received a high overall fit assessment, indicating strong feasibility for measuring Dignified Design in PSH settings. Moving interviews and space syntax received medium-high scores, while DDAT received a moderately low score. The remaining devices collecting physiological data—Fibion and Upmood—received low scores. The following sections provide a narrative summary of the assessment and scoring for each method. These summaries explain the ratings presented in Table 1, which reflect a synthesis of information captured in Appendix A.
5.1. Physiological Methods
The wearable-device findings below describe participant feedback, researcher assessments, and observed recording problems.
5.1.1. ActiGraph
ActiGraph received an Average Assessment Score of 2.73 and a high Overall Fit assessment. Researchers gave high ratings for the method’s overall experience (5.0), comfort (4.5), and safety (5.0). Participants also responded favorably, rating comfort (4.5), safety (5.0), and clarity (4.5) highly. Post-study feedback indicated that the device and app were relatively easy to use, though setup was challenging for researchers because of the complexity of configuring and syncing the devices with mobile phones. Participants reported that the device was comfortable and unobtrusive. When evaluating the measure’s implementation, researchers rated viability and user-friendliness as high, while logistics received a medium rating because of the initial setup challenges. Researchers recommend using ActiGraph companion hubs instead of smartphones in future studies to ease logistical burdens and prevent participants from feeling restricted.
5.1.2. Fibion
Unlike ActiGraph, Fibion received much lower scores, with an Average Assessment Score of 1.45 and a low Overall Fit assessment. Researchers gave high ratings for overall experience (5.0), comfort (4.0), and safety (5.0). Participants also rated comfort (5.0), safety (5.0), and clarity (5.0) highly. Post-study feedback indicated that the device and application were relatively easy to use, and the participant found the process accessible and straightforward. Researchers also found the remote data interface easy to use and interpret. However, researchers identified several logistical challenges. First, connecting the device application to the phone was cumbersome, and the initial set-up process was lengthy. Second, one of the two devices unexpectedly failed during on-site testing, so only one participant could pilot the method. Finally, the device did not track HRV as expected, and the sleep data were either too irregular or too limited for a confident analysis. Therefore, the favorable participant experience did not translate into reliable data collection. The device may have potential, but the hardware failure and poor data yield substantially reduced its feasibility for assessing the effects of the built environment in this context.
5.1.3. Upmood
Upmood received an Average Assessment Score of 1.45 and a low Overall Fit assessment. Researchers gave moderate-to-high ratings for the overall experience (4.0), comfort (3.5), and safety (5.0). Participants responded favorably to the instrument, rating comfort (4.5), safety (5.0), and clarity (5.0) highly. Post-study feedback indicated that the device and application were straightforward to use and that instructions were clear. Participants also appreciated the real-time feedback, which they felt could positively influence their mood. However, participants noted several issues with the process. Firstly, carrying the connecting phone with them at all times was burdensome. Second, they received regular prompts to resynchronize the device and were often unsure whether their data were being recorded. Researcher feedback suggested that the remote data interface was easy to interpret; however, connecting the application to the phone was cumbersome, the initial setup was lengthy, and the device required frequent synchronization. Finally, the device did not capture heart rate variability or emotion-related data as expected, and data collection was inconsistent across the seven-day period, ranging from 1 to 85 entries per day. Therefore, participant acceptability did not compensate for unreliable data yield, and researchers determined that Upmood was not feasible for future studies without more stable connectivity, clearer recording-status indicators, and a less burdensome synchronization process.
5.1.4. Hormonal Assay
The hormonal assay received an Average Assessment Score of 2.33 and a high Overall Fit assessment. All four hair samples submitted for testing were deemed viable and yielded results for both cortisol and DHEA levels. Participants rated comfort and clarity at an average of 3.8 and safety at 4.8. Researchers who administered the method rated it slightly higher, with an average comfort rating of 4 and overall experience and safety ratings in the high 4 range. Notably, this method required several time-consuming administrative activities before and after data collection, including signing contracts with the laboratory, preparing materials for specimen collection, packaging and mailing samples, and consulting with laboratory staff about technical results and their possible interpretation. Despite these logistical demands, the hormonal assay yielded high-quality, accurate, and compelling data with strong potential for measuring outcomes associated with Dignified Design.
Researchers noted that administering the hormonal assay process was similar to a doctor’s visit. Participants first completed paperwork with a researcher in the main room before transitioning to a separate private room, where a second researcher collected the hair sample. This approach appeared to promote comfort and privacy during sample collection. Researchers also noted that the method benefited significantly from efforts to build trust and rapport with participants prior to sample collection. These efforts included visiting the site before the study and openly discussing the hormonal assay procedures, which were anticipated to be among the most unfamiliar aspects of study participation. Such intentional, relationship-building practices were essential for ensuring a dignified and respectful sample collection experience.
5.2. Psychological Methods
5.2.1. Condensed Photovoice
Condensed photovoice received an Average Assessment Score of 2.67 and a high Overall Fit assessment. Researchers rated this method highly for overall experience (4.8), comfort (4.8), and safety (5). Researchers also expressed enthusiasm about the method’s ability to collect high-quality, meaningful, and engaging data as well as its ease of facilitation (Figure 4). However, average participant ratings were notably lower for comfort (3.8), safety (4.2), and clarity (4.6). Participants reported some uncertainty about the exercise objectives and insecurity about whether they were doing it correctly. While participants reported general comfort taking photos throughout the building, some indicated that discussing their photographs in a private setting would have been preferable to the crowded room where study activities largely took place. Training on the digital cameras was mostly straightforward; however, uploading the photographs to a laptop and facilitating a recorded dialogue introduced a modest learning curve and the potential for technical issues. Overall, the method was highly rated for its relevance to Dignified Design and ability to directly assess experiences of safety, comfort, community, and control within a PSH setting.
Figure 4.
An example of a photograph taken by one of the study participants testing condensed photovoice.
5.2.2. Moving Interviews
Moving interviews received an Average Assessment Score of 2.50 and a moderately high Overall Fit assessment. A total of five researcher–participant pairs completed the moving interviews and associated debrief forms. Researchers rated the overall experience, comfort, and safety of the method above 4.0. Participants similarly rated comfort and safety above 4.0 and clarity at 3.8. Resident debrief feedback revealed that some residents did not feel comfortable or safe going to some areas of the building during the interview process. Researchers suggested more thorough informed consent procedures and a more detailed explanation of the method before participation could improve participant comfort and overall feasibility.
5.3. Design Methods
5.3.1. Dignified Design Assessment Tool (DDAT)
The Dignified Design Assessment Tool received an Average Assessment Score of 2.39 and a moderately low Overall Fit assessment. Of the five forms distributed, three were completed and returned. Participants rated comfort, safety, clarity, and overall experience above 4.0. However, one participant expressed concerns about sharing negative feedback about the building if their design partners saw the responses, suggesting a strong social desirability bias. The research team also noted that administering the DDAT within the first few months after a building opens may be preferable, as team members reported difficulty recalling project-specific details after a longer period. Although the instrument was relatively easy to administer and generally well received, questions remained about its suitability as a stand-alone measure of Dignified Design in PSH settings. In particular, the researchers questioned whether the tool, in its current form, captures sufficient insight and detail about occupant experiences and perceptions of environmental conditions to assess Dignified Design thoroughly. Further refinement may be needed if the measure were to serve as a principal method for evaluating Dignified Design in PSH settings.
5.3.2. Dignified Design Inventory
The Dignified Design Inventory received an Average Assessment Score of 2.78 and a high Overall Fit assessment. Researchers assigned favorable feasibility scores for overall experience (4.0). Perceptions of safety were high, with researchers noting they felt secure in a group and with a member of the PSH staff. However, some researchers reported discomfort with conducting research in residents’ homes and felt somewhat rushed during the tour and observation period. Debrief data revealed that the activity was perceived as low-barrier, and the note-catcher was accessible and easy to use. However, researchers wanted more structured guidance and greater specificity in the observation prompts, particularly on how to distinguish between the quality and quantity of key design attributes and affordances.
5.3.3. Space Syntax
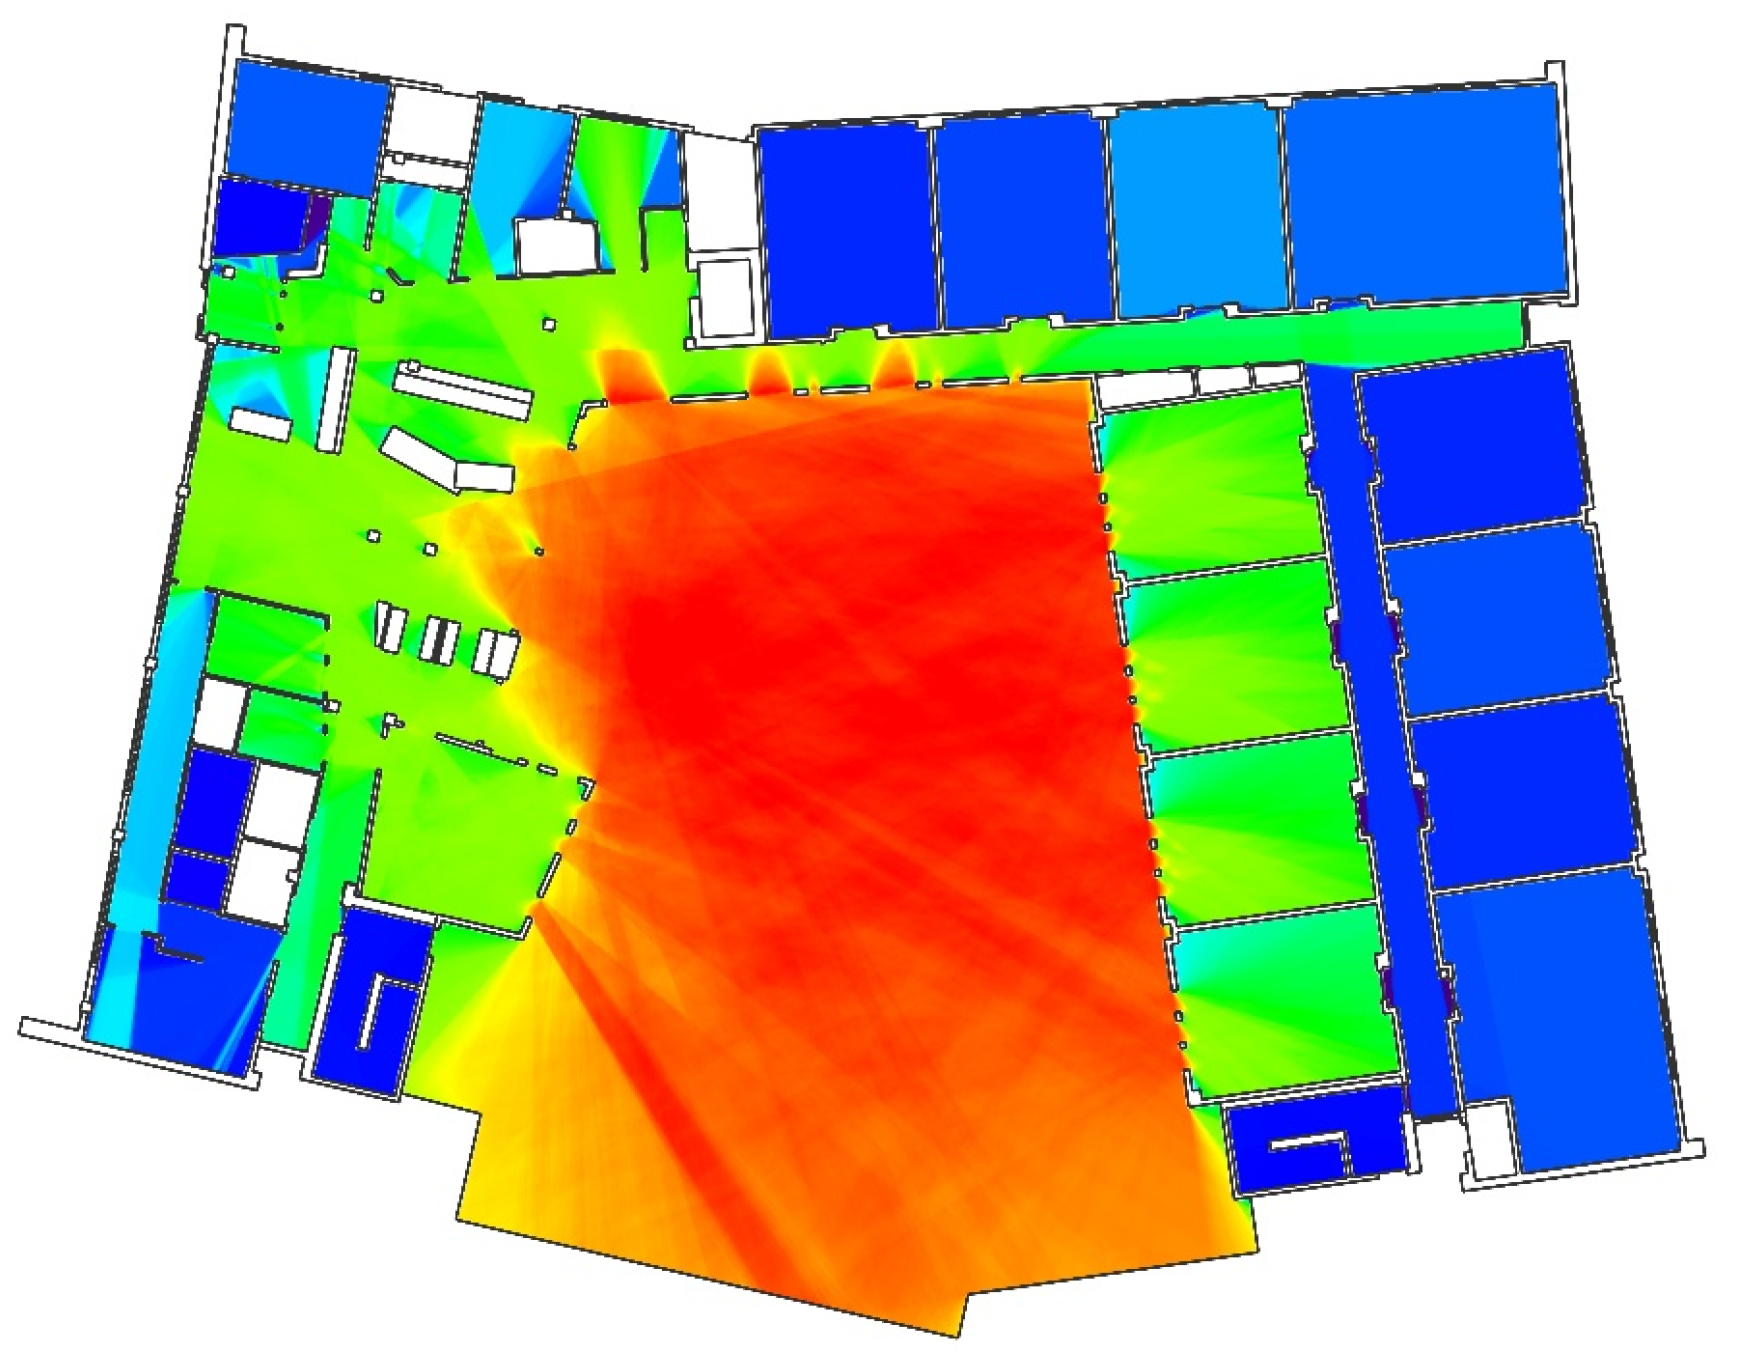
Space syntax received an Average Assessment Score of 2.69 and a moderately high Overall Fit assessment. Unlike most of the other methods tested, space syntax is a computational measure that does not require direct participant involvement or on-site data collection. Architectural floor plans and supporting photographs were sufficient to perform a baseline analysis of the building’s spatial configuration (Figure 5). However, researchers noted that successful implementation requires training and technical expertise with space syntax theory and methodology, as well as experience using the Isovist platform to prepare floor plans, generate visualizations, and interpret results. Only one member of the research team had the expertise necessary to conduct the space syntax analysis. As a stand-alone measure, the depth of information generated by space syntax was rated as moderate. However, when integrated with qualitative or physiological data, the measure was rated highly for both viability and acceptability.
Figure 5.
Space syntax analysis of the first floor displaying the integration measure. Red and orange areas are highly integrated, indicating that they are more easily accessible and likely to experience higher levels of movement and activity. Green and blue areas are more segregated, suggesting that they are less accessible, quieter, and potentially more private.
5.4. Overall Feasibility
In a review of the open-ended questions from the researcher debrief forms, researchers’ responses suggested broad acceptability of testing these methods in a PSH setting. However, the method-specific assessments did not support the conclusion that all methods were feasible. Fibion and Upmood received low overall fit assessments due to technical failures and recording limitations that compromised data collection, despite favorable participant feedback. Researchers identified condensed photovoice and moving interviews as generating the richest insights into participants’ experiences of the built environment and their perceptions of safety, comfort, community, control, and dignity. Condensed photovoice, in particular, was repeatedly described as revealing nuanced experiences that may not otherwise emerge through traditional interviews or surveys. The Dignified Design Inventory was viewed as the most valuable method for identifying environmental design affordances and attributes directly related to the Dignified Design Model.
Researchers reported that, although the physiological measures were recognized for their potential to provide objective indicators of stress and well-being, their contribution was considered more indirect and required substantial additional analysis. Further, wearable technologies were seen as having the greatest implementation challenges because of the complexity of device setup, participant instruction, and equipment failures. Although the hormonal assay generated enthusiasm among researchers as a novel and unexpectedly feasible method for implementation in PSH settings under the right conditions, collecting hair samples for cortisol and DHEA testing raised concerns related to participant screening and recruitment.
Across all responses, researchers said participants generally reported positive experiences with the study, highlighting high engagement, a willingness to share personal experiences, and appreciation for being invited to contribute. Ethical considerations centered primarily on privacy during in-person interviews and debrief discussions, as well as confidentiality concerns related to biomarker data. Overall, researchers concluded that a community-centered approach emphasizing partnership, transparency, kindness, trust-building, and respect for participant expertise contributed substantially to the study’s implementation success and perceived feasibility.
6. Discussion
The central aim of this study was to pilot and assess the feasibility of administering a range of methods intended to evaluate the various aspects of the Dignified Design Model in Permanent Supportive Housing (PSH) settings. Findings show that a diverse set of physiological, psychological, and design-based methods can be successfully administered within PSH environments and can collectively help explain how the built environment shapes experiences of safety, comfort, community, control, and dignity. Beyond evaluating individual methods, this study contributes to the emerging field of Dignified Design by demonstrating the value of a multidisciplinary, in situ approach to studying the relationship between architecture, human experience, and well-being.
6.1. Feasibility of a Multimodal Approach to Evaluating Dignified Design
The findings provide preliminary support for a multimodal approach to evaluating Dignified Design in PSH using selected methods with acceptable implementation characteristics. Importantly, no single method emerged as sufficient for capturing the full complexity of dignity within the built environment. Rather, various methods offered a unique perspective on the relationship between people and places, reinforcing the value of methodological triangulation.
The physiological methods contributed a distinct perspective by offering objective indicators of stress and well-being, but their field performance varied substantially. While the wearable devices were generally considered well tolerated by participants, logistical and technical challenges, including complex smartphone syncing requirements and inconclusive biometric data, limited their overall utility. Among the wearable devices, ActiGraph showed the most promise despite complex smartphone setup and synchronization requirements. In contrast, Fibion hardware failure reduced the planned number of participants; its available data did not include the expected HRV measures, and its sleep data was insufficient for confident analysis. Upmood was hindered by Bluetooth disconnections, equipment reliability issues, and synchronization demands that left participants uncertain whether recording was active and whether it produced consistent data across the pilot period. These unintended outcomes affected both data-collection quality and the practical feasibility of the wearable methods, even though participants found the devices acceptable. This points to the need to distinguish between participant acceptability and technical viability. In addition, it identifies specific refinements for future field studies, including testing equipment before use, ensuring a backup device, simplifying pairing procedures, and monitoring connections continuously.
In contrast, hormone assay testing through hair samples emerged as a particularly compelling measure. Although the administrative burden was substantial, it was more acceptable and feasible than anticipated and produced high-quality data. This suggests that physiological indicators remain valuable measures for future evaluations of Dignified Design when failure contingencies are addressed in advance.
Among the methods tested, psychological methods, such as condensed photovoice and moving interviews, generated the most direct and meaningful insights into participants’ lived experiences with dignity and their perceptions of safety, comfort, community, and control. These approaches allowed residents and staff to articulate how specific spaces shaped their daily experiences and revealed nuanced interpretations that a more structured method alone would likely miss. At the same time, both methods highlighted the importance of privacy, trust, and thoughtful facilitation in residential settings. Additionally, it is critical to note that condensed photovoice and moving interviews can bring residents physically to places that feel unsafe and trigger negative emotional responses.
The Dignified Design Inventory emerged as the strongest design-focused method for assessing and identifying environmental affordances and attributes associated with the Dignified Design Model. Researchers found the method accessible, practical, and highly relevant for documenting spatial conditions that may contribute to experiences of dignity. Similarly, space syntax provided a valuable systems-level understanding of how building configuration may support or constrain navigation, visibility, control, and social interaction. Although its application requires specialized expertise, space syntax complemented participant-centered methods by revealing spatial dynamics that building occupants may not consciously recognize. Additional design-based methods, such as DDAT and space syntax, contributed complementary context to the design’s intentions and outcomes. Each method strengthened the multimodal approach. However, researchers noted that future use of the Dignified Design Inventory and DDAT would benefit from clearer prompts and efforts to address potential participant biases.
Taken together, these findings suggest that the greatest strength lies not in any individual method but in integrating multiple approaches. By combining physiological, psychological, and design assessment strategies, researchers are better positioned to understand both the characteristics of dignified environments and the impacts those environments have on the people who inhabit them.
6.2. Conceptualizing and Measuring an Atmosphere of Dignity
Through the analysis process, the research team found that some methods assessed environmental characteristics and conditions that created an experiential atmosphere, while others assessed the physiological and psychological outcomes of inhabiting that atmosphere. In other words, some of the methods were better suited to assess an atmosphere of dignity (AOD), while others measured the outcomes of an AOD. Importantly, no single method adequately captured an atmosphere on its own. The experience of place emerged through the interaction between the physical and spatial elements of the built environment and the humans inhabiting the space, requiring a composite, multi-measurement tool to assess the atmosphere. This distinction provides a foundation for future research focused specifically on operationalizing an AOD tool.
Within this framework, the piloted methods fall into two categories. First, measures of AOD—including design and environmental methods such as the Dignified Design Inventory, DDAT, and Space Syntax—are intended to be executed together to characterize the environmental and experiential conditions that constitute an atmosphere of dignity. Second, AOD outcome measures—including physiological methods such as ActiGraph and Hormone Assay as well as psychological methods such as Condensed Photovoice and Moving Interview—can be executed independently or in combination to assess impacts associated with inhabiting dignified environments.
6.3. Limitations and Future Research
Several limitations should be considered when interpreting this study’s findings. First, the pilot was conducted within a single PSH site and involved a relatively small sample of residents, staff, and design and development team members. As a result, the findings should be viewed as preliminary and are not generalizable to other PSH settings, geographic regions, or housing models. Future studies should seek to replicate and extend these findings across multiple sites and larger, more diverse populations to better understand the applicability of these methods in varying contexts.
Second, the primary aim of this study was to assess the field feasibility of a range of methods for evaluating Dignified Design—the study accomplishes this objective. However, the study does not definitively assess the validity and reliability of the range of methods assessed, nor the psychometric properties of these approaches for measuring dignity-related constructs or generalizable clinical outcomes. Future research is needed to establish the reliability, validity, sensitivity, and overall measurement performance of these methods, both individually and within a broader multimodal assessment framework.
Wearable-device adherence and usable-data yield were not quantified. Remote monitoring, midpoint telephone check-ins, participant debriefs, and review of downloaded files provided qualitative information about device use and recording problems, but we did not establish valid wear hours, valid recording days, or the percentage of usable data. Consequently, the ordinal adherence and data-yield ratings should not be interpreted as quantitative performance estimates or evidence of continuous wear and recording. It is recommended that future studies prespecify participant wear-time and synching requirements, record reasons for missing data, and report adherence and usable-data yield separately.
Third, the study examined a selective subset of available methods and, therefore, does not represent the full range of approaches relevant to evaluating Dignified Design. Several potentially valuable methods, such as electroencephalography (EEG), functional magnetic resonance imaging (fMRI), the Visual Stress Analysis Tool (ViStA), Neuroception and Psychological Safety Scale (NPSS), and more extensive qualitative interviewing approaches, were excluded due to their feasibility constraints, resource limitations, specialized expertise required to administer the instruments, or previously assessed suitability. Future research should continue to explore and compare alternative methods across disciplines to determine their utility in capturing dimensions of dignity, well-being, and environmental experiences.
Importantly, the piloting process also identified several promising avenues for future investigation. These include tracking blood pressure as an additional physiological indicator of stress; utilizing Visibility Graph Analysis (VGA) as a spatial mapping tool; measuring environmental factors such as lighting, thermal, and noise quality and control; and developing a standardized dignity measurement scale tailored to housing environments. Such efforts could contribute to a more robust and comprehensive framework for assessing both atmospheres of dignity and their associated outcomes.
Finally, this study underscored the importance of balancing methodological rigor with ethical and relational considerations in housing research. Since participants were asked to engage in research within spaces that function as homes and workplaces, future studies must continue to prioritize privacy, autonomy, informed consent, and participant comfort. Community-centered approaches grounded in trust, transparency, and respect will remain essential to ensuring that efforts to measure human–environmental interactions and experiences are themselves conducted in a dignified manner.
7. Conclusions
Beyond informing future research, this study contributes to the growing body of knowledge linking architecture, health, and social well-being. By identifying feasible and acceptable methods for studying dignity in situ, this study lays the groundwork for future efforts to operationalize and measure atmospheres of dignity and to better understand how supportive housing design can promote health, well-being, and human flourishing among residents and staff alike. This study provides preliminary support for a multimodal approach to evaluating Dignified Design in PSH settings through the selection of complementary physiological, psychological, and design-based methods. Testing nine methods identified complementary approaches that capture environmental conditions, lived experiences, and potential outcomes associated with dignity in the built environment. While all methods were implementable within a PSH setting, notable differences emerged in their overall fit, logistical demands, and ability to assess key dimensions of the Dignified Design Model (i.e., safety, comfort, community, and control), highlighting promising opportunities for future research and implementation.
Author Contributions
Conceptualization, S.R.S., J.W., R.M., Y.M., B.M. and D.B.; methodology, S.R.S., J.W., R.M., Y.M., B.M. and D.B.; validation, S.R.S., J.W., R.M., Y.M., B.M. and D.B.; formal analysis, S.R.S., J.W., R.M., Y.M., B.M. and D.B.; investigation, S.R.S., J.W., R.M., Y.M., B.M. and D.B.; resources, S.R.S., J.W., R.M., Y.M., B.M. and D.B.; data curation, S.R.S., J.W., R.M., Y.M., B.M. and D.B.; writing—original draft preparation, S.R.S., J.W., R.M., Y.M., B.M. and D.B.; writing—review and editing, S.R.S., J.W., R.M., Y.M., B.M., J.B.B. and D.B.; visualization, S.R.S., J.W., R.M., Y.M., B.M. and D.B.; supervision, J.W., R.M., project administration, S.R.S., J.W., R.M., Y.M., B.M.; funding acquisition, J.W. and R.M. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by Shopworks Architecture, an architecture firm with an in-house research team that includes some of the authors of this paper. The authors’ professional affiliations with Shopworks Architecture are disclosed here to ensure transparency regarding the relationship between the funder and the research team.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki, and the study protocol was approved by the University of Denver Institutional Review Board (DU IRB) (Approval No. 2329525-1) on 22 August 2025.
Informed Consent Statement
Informed consent for participation was obtained from all subjects involved in the study.
Data Availability Statement
The original contributions presented in this study are included in the article. Further inquiries can be directed to the corresponding author.
Acknowledgments
We extend our sincere gratitude to all the participants who generously shared their time, experiences, and perspectives and made this research possible. We also thank the housing community and organizations that supported this work by facilitating access, collaborating with the research team, and helping create the conditions necessary for this project.
Conflicts of Interest
The authors declare no conflicts of interest.
Appendix A. Scoring Framework and Ratings for All Methods
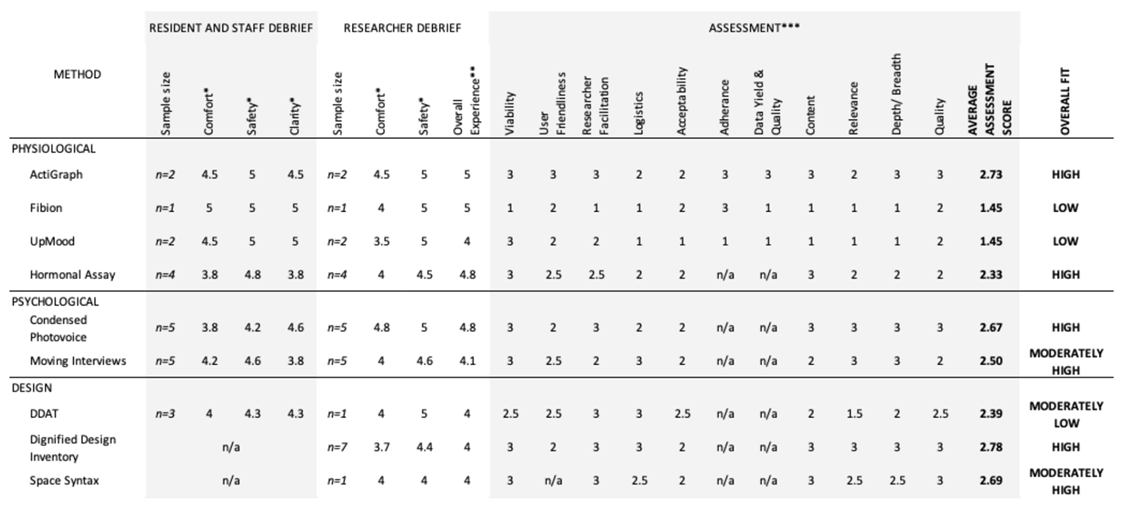
* Items on 5-point Likert-type scale with 1 = not at all and 5 = extremely positive/negative.
** Items on 5-point Likert-type scale with 1 = extremely negative and 5 = extremely positive.
*** Items on 3-point Likert-type scale with 1 = low, 2 = medium, and 3 = high.
References
- de Sousa, T.; Henry, M. The 2024 Annual Homelessness Assessment Report (AHAR) to Congress; U.S. Department of Housing and Urban Development: Washington, DC, USA, 2024. Available online: https://www.huduser.gov/portal/sites/default/files/pdf/2024-AHAR-Part-1.pdf (accessed on 1 August 2026).
- Soucy, D.; Hall, A.; Moses, J. State of Homelessness: 2025 Edition; National Alliance to End Homelessness: Washington, DC, USA, 2025; Available online: https://endhomelessness.org/state-of-homelessness/ (accessed on 1 August 2026).
- Devlin, A.S. Environmental Psychology and Human Well-Being: Effects of Built and Natural Settings; Academic Press: Cambridge, MA, USA, 2018. [Google Scholar]
- Pless, N.M.; Maak, T.; Harris, H. Art, ethics and the promotion of human dignity. J. Bus. Ethics 2017, 144, 223–232. [Google Scholar] [CrossRef] [Scilit]
- Rollings, K.A.; Bollo, C.S. Permanent supportive housing design characteristics associated with the mental health of formerly homeless adults in the U.S. and Canada: An integrative review. Int. J. Environ. Res. Public Health 2021, 18, 9588. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tucker, R.; Andrews, F.; Giles, D.B.; Vecchiet, B.; Sal Moslehian, A. A place to call home: Design characteristics for transitional housing supporting pathways out of homelessness in Australia. J. Hous. Built Environ. 2025, 41, 807–839. [Google Scholar] [CrossRef] [Scilit]
- Brisson, D.; Holtzinger, C.; Macur, R.; Otteson, T.; Rossbert, L.; Speer, R.; Twigg, S.; Wilson, J. Designing for Dignity: Elements of Practice; ORO Editions: Novato, CA, USA, 2025. [Google Scholar]
- Gallagher, A. Care environments that support dignity in care. In Dignity in Healthcare: A Practical Approach for Nurses and Midwives; Matiti, M.R., Baillie, L., Eds.; Routledge: London, UK, 2011; pp. 52–61. [Google Scholar]
- Wilson, J.; Bollo, C.; Macur, R.; Mann, B.; Metzger, M. A grounded theory of dignified design informed by residents and staff in permanent supportive housing. Enquiry 2025, 22, 80–94. [Google Scholar] [CrossRef] [Scilit]
- Justus, J.; Raghani, S. Trauma-informed design: Shelter homes for runaway children. Int. J. Adolesc. Youth 2025, 30, 2445053. [Google Scholar] [CrossRef] [Scilit]
- Owen, C.; Crane, J. Trauma-informed design of supported housing: A scoping review through the lens of neuroscience. Int. J. Environ. Res. Public Health 2022, 19, 14279. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brisson, D.; Macur, R.; Mann, B.; Wilson, J. Impact of trauma-informed design on health and well-being of people formerly experiencing homelessness in permanent supportive housing. Soc. Sci. 2025, 14, 417. [Google Scholar] [CrossRef] [Scilit]
- Bollo, C.; Donofrio, A. Trauma-informed design for permanent supportive housing: Four case studies from Seattle and Denver. Hous. Soc. 2022, 49, 229–250. [Google Scholar] [CrossRef] [Scilit]
- Ajeen, R.; Ajeen, D.; Wisdom, J.P.; Greene, J.A.; Lepage, T.; Sjoelin, C.; Melvin, T.; Hagan, T.E.; Hunter, K.F.; Peters, A.; et al. The impact of trauma-informed design on psychological well-being in homeless shelters. Psychol. Serv. 2023, 20, 680–689. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huffman, T. Built community: Architecture, community, and participation in a permanent supportive housing project. J. Soc. Distress Homeless. 2018, 27, 44–52. [Google Scholar] [CrossRef] [Scilit]
- McLane, Y.; Pable, J. Architectural design characteristics, uses, and perceptions of community spaces in permanent supportive housing. J. Inter. Des. 2020, 45, 33–52. [Google Scholar] [CrossRef] [Scilit]
- Perkins & Will. Healthy Affordable Housing: The Toolkit: Sharing Lessons Learned from the Pandemic to Improve Affordable Housing; American Society of Interior Designers: Washington, DC, USA, 2021; Available online: https://perkinswill.com/healthy-affordable-housing-the-toolkit/ (accessed on 1 August 2026).
- Preservation of Affordable Housing. What Is Trauma-Informed Housing? A Toolkit for Advancing Equity and Economic Opportunity in Affordable Housing. 2023. Available online: https://traumainformedhousing.poah.org/what-is-trauma-informed-housing/ (accessed on 1 August 2026).
- Huang, S.; Qi, J.; Li, W.; Dong, J.; van den Bosch, C.K. The contribution to stress recovery and attention restoration potential of exposure to urban green spaces in low-density residential areas. Int. J. Environ. Res. Public Health 2021, 18, 8713. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Peters, E.; Hovinga, D.; Maas, J.; Schuengel, C. Exposure to a natural environment to improve parental wellbeing in parents in a homeless shelter: A multiple baseline single-case intervention study. J. Soc. Distress Homeless. 2023, 32, 85–96. [Google Scholar] [CrossRef] [Scilit]
- De Jong Gierveld, J.; Van Tilburg, T. A 6-item scale for overall, emotional, and social loneliness: Confirmatory tests on new survey data. Res. Aging 2006, 28, 582–598. [Google Scholar] [CrossRef] [Scilit]
- Indianapolis Network Mental Health Study. Protocol—Social Networks. Institute for Social Research. 1991. Available online: https://www.phenxtoolkit.org/protocols/view/211101 (accessed on 1 August 2026).
- Lee, R.M.; Draper, M.; Lee, S. Social connectedness, dysfunctional interpersonal behaviors, and psychological distress: Testing a mediator model. J. Couns. Psychol. 2001, 48, 310–318. [Google Scholar] [CrossRef]
- Pasricha, P. Measuring Social Connection: The State of Affairs and the Path Forward; Foundation for Social Connectedness: Washington, DC, USA, 2023; Available online: https://www.socialconnectedness.org/wp-content/uploads/2023/11/Prachir-Pasricha_Final-Report.pdf (accessed on 1 August 2026).
- Watts, R.; Kettner, H.; Geerts, D.; Gandy, S.; Kartner, L.; Mertens, L.; Timmermann, C.; Nour, M.M.; Kaelen, M.; Nutt, D.; et al. The Watts Connectedness Scale: A new scale for measuring a sense of connectedness to self, others, and world. Psychopharmacology 2022, 239, 3461–3483. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ogden, J.; Daniells, E.; Barnett, J. The value of choice: Development of a new measurement tool. Br. J. Gen. Pract. 2008, 58, 614–618. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ruthig, J.; Chipperfield, J.; Perry, R.; Newall, N.; Swift, A. Comparative risk and perceived control: Implications for psychological and physical well-being among older adults. J. Soc. Psychol. 2007, 147, 345–369. [Google Scholar] [CrossRef] [PubMed]
- Sadeghi, S.A.; Karava, P.; Konstantzos, I.; Tzempelikos, A. Occupant interactions with shading and lighting systems using different control interfaces: A pilot field study. Build. Environ. 2016, 97, 177–195. [Google Scholar] [CrossRef] [Scilit]
- Valentine, C.; Mitcheltree, H.; Sjövall, I.A.K.; Khalil, M.H. Architecturally mediated allostasis and neurosustainability: A proposed theoretical framework for the impact of the built environment on neurocognitive health. Brain Sci. 2025, 15, 201. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beese, S.; Postma, J.; Graves, J.M. Allostatic load measurement: A systematic review of reviews, database inventory, and considerations for neighborhood research. Int. J. Environ. Res. Public Health 2022, 19, 17006. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- DeCaro, J.A.; Helfrecht, C. Applying minimally invasive biomarkers of chronic stress across complex ecological contexts. Am. J. Hum. Biol. 2022, 34, e23814. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Du, B.; Rey, J.F.; Cesari, M.; Roulet, C.-A.; Favreau, P.; Perret, V.; Suarez, G.; Hager Jörin, C.; Goyette Pernot, J.; Licina, D. Indoor air quality in Swiss primary schools: Impacts of mechanical ventilation and seasonal variation. Build. Environ. 2025, 280, 113146. [Google Scholar] [CrossRef] [Scilit]
- Guo, T.; Hu, S.; Li, Q. Experimental study on the effects of low pressure and acoustic characteristics on heart rate and acoustic comfort. Sci. Rep. 2025, 15, 29192. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tomasso, L.P.; Białowolski, P.; Spengler, J.D. Stress reduction from landscape painting and live nature viewing: A comparative experimental study. J. Glob. Health 2025, 15, 04146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Upmood. Upmood: Emotion Tracker & Mood Sensor—Wearable. 2023. Available online: https://www.upmood.com/ (accessed on 1 August 2026).
- Kamin, H.S.; Kertes, D.A. Cortisol and DHEA in development and psychopathology. Horm. Behav. 2017, 89, 69–85. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Catalani, C.; Minkler, M. Photovoice: A review of the literature in health and public health. Health Educ. Behav. 2010, 37, 424–451. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, C.; Burris, M.A. Photovoice: Concept, methodology, and use for participatory needs assessment. Health Educ. Behav. 1997, 24, 369–387. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, C.; Burris, M.A. Empowerment through photo novella: Portraits of participation. Health Educ. Q. 1994, 21, 171–186. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brisson, D.; Wilson, J.; Macur, R.; Mann, B.; Rossbert, L.; Holtzinger, C. Dignified design assessment tool. Front. Environ. Health 2025, 4, 1546442. [Google Scholar] [CrossRef] [Scilit]
- McElhinney, S.; Benedikt, M. Isovists.org. 2024. Available online: https://isovists.org/ (accessed on 1 August 2026).





Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.