


Highlights
What are the main findings?
- Hypertrophic cardiomyopathy (HCM) involves coordinated genetic, epigenetic, and immune remodeling, redefining it as an immunogenetic disorder rather than solely a sarcomeric disease.
- Key molecular drivers and immune cell shifts link RNA regulation, m6A methylation, and inflammatory pathways to myocardial fibrosis and diastolic dysfunction.
What are the implications of the main finding?
- Identified diagnostic gene panels and hub genes support transcriptome-based precision diagnostics for HCM.
- Immunometabolic drug targets and integration of biomarkers with imaging may guide personalized immunotherapy and risk stratification.
Abstract
Background: Hypertrophic cardiomyopathy (HCM) is increasingly recognized as a disorder shaped not only by sarcomeric mutations but also by complex immunogenetic and metabolic interactions. Emerging transcriptomic and single-cell analyses implicate immune dysregulation, RNA methylation, and necroptosis as critical modulators of myocardial remodeling. Objectives: This scoping review synthesizes bioinformatic, transcriptomic, and experimental data to delineate the immunogenetic architecture of HCM and identify candidate molecular targets for immune–metabolic modulation. Methods: Following Joanna Briggs Institute and PRISMA-ScR guidelines, we systematically searched PubMed, Embase, Web of Science, and GEO through September 2025 for studies evaluating immune infiltration, RNA regulation, and necroptosis in human HCM. Data were narratively synthesized across histologic, clinical, and multi-omics domains. Results: Among 8191 screened records, 25 studies met the inclusion criteria. Key immune–epigenetic regulators included the lncRNA–mRNA pair MIR210HG–BPIFC, m6A readers IGFBP3 and YTHDC1, and necroptosis gene JAK2. The HCM myocardium exhibited the depletion of reparative M2 macrophages and Tregs; enrichment of cytotoxic CD8+ T cells; and activation of the TNFα–NFκB, IL-6–JAK–STAT3, and PI3K–Akt pathways. Machine learning biomarkers (RASD1, FCN3, and PIK3R1) exhibited diagnostic accuracy (AUC > 0.85). Drug target predictions identified ruxolitinib and celecoxib as potential immunometabolic modulators (agents predicted to modulate both immune and metabolic pathways based on gene expression signatures). Conclusions: These findings support a hypothesis that HCM may involve immunogenetic mechanisms, rather than being exclusively sarcomeric in nature, although this remains to be validated. The integration of molecular and imaging biomarkers may enable precision immunotherapy, redefining HCM from a structural cardiomyopathy to a biologically stratified condition.
1. Introduction
Hypertrophic cardiomyopathy (HCM) is the most common form of inherited cardiomyopathy. It remains one of the principal causes of heart failure, atrial fibrillation, and sudden cardiac death in young and apparently healthy individuals [1,2,3]. Although traditionally defined as a primary disease of the sarcomere driven predominantly by pathogenic variants in MYBPC3 and MYH7, the clinical expression of HCM is remarkably heterogeneous, ranging from asymptomatic carriers to patients who present with progressive heart failure or malignant ventricular arrhythmias [4,5]. This heterogeneity cannot be explained solely by genetic factors. Indeed, even within families carrying the same variant, penetrance and phenotype vary considerably, suggesting the presence of additional molecular and environmental factors that influence disease trajectory [6,7].
Among these factors, immune activation and inflammation have recently been recognized as potential modifiers of HCM pathophysiology. It is well established that T cells play a key role in regulating myocardial remodeling in other forms of cardiovascular disease. Effector subsets, including cytotoxic CD8+ and pro-inflammatory CD4+ cells such as Th1 and Th17 cells, drive fibroblast proliferation and extracellular matrix expansion. In contrast, regulatory T cells (Tregs) counterbalance these processes by dampening inflammation and restraining maladaptive fibrosis [8,9,10]. The dynamic equilibrium between these opposing arms of the immune response appears to shape outcomes in ischemic and non-ischemic cardiomyopathies, suggesting that similar mechanisms may contribute to disease progression in HCM [11,12].
Evidence supporting this hypothesis is gradually increasing. Histological studies, although limited in scale, have consistently demonstrated lymphocytic infiltrates in the regions of myocardial disarray and fibrosis. Recent immunophenotyping studies have suggested that the balance between effector T cells and Tregs may be correlated with the extent of remodeling [13,14]. Clinical observations further support this concept: elevated circulating cytokine levels, including interleukin-6 and tumor necrosis factor-α, have been associated with diffuse myocardial fibrosis, as measured by cardiac magnetic resonance imaging, and with the occurrence of atrial and ventricular arrhythmias [15,16,17]. Moreover, transcriptomic and single-cell analyses have begun to delineate immune-fibrotic signaling networks, revealing the recurrent enrichment of pathways such as NF-κB, JAK/STAT, and interleukin-17 (IL-17) in myocardial samples from patients with HCM [18,19].
Most studies are small, use heterogeneous definitions of immune activation, and employ diverse endpoints, ranging from descriptive pathology to exploratory prognostic analyses. Consequently, it is difficult to ascertain whether T-cell activation in HCM is the primary driver of remodeling, a secondary bystander phenomenon, or a potential therapeutic target. Therefore, this scoping review aims to systematically map existing evidence linking immune and epigenetic mechanisms in HCM, identify consistent molecular mediators, and propose translational implications for precision therapy.
2. Methods
This scoping review was designed to systematically map current evidence describing immune, genetic, and epigenetic mechanisms in hypertrophic cardiomyopathy (HCM). This review followed the Joanna Briggs Institute (JBI) methodological framework for scoping reviews. It adhered to the Preferred Reporting Items for Systematic Reviews and Meta-Analyses extension for Scoping Reviews (PRISMA-ScR) guidelines, as shown in Supplementary Methods S1. A detailed protocol outlining the objectives, inclusion criteria, and analytic approach was prospectively registered on the Open Science Framework (OSF): doi.10.17605/OSF.IO/3NTUR.
2.1. Search Strategy
A comprehensive search strategy was developed in consultation with an experienced medical information specialist to capture the full breadth of the literature on immune and transcriptomic mechanisms in HCM. The following databases were searched from inception to 5 November 2025: PubMed/MEDLINE; Embase; Web of Science Core Collection; Cochrane Library; Gene Expression Omnibus (GEO) for transcriptomic datasets [20,21].
Search strings combined controlled vocabulary (MeSH and Emtree terms) with free-text keywords related to hypertrophic cardiomyopathy, T lymphocytes, macrophages, cytokines, fibrosis, epigenetics, lncRNA, m6A methylation, and immune infiltration. The complete search syntax for each database is provided in the Supplementary Materials to ensure reproducibility, as shown in Supplemental Methods S2.
2.2. Eligibility Criteria
Eligible studies met all the following criteria:
- Population: Human participants diagnosed with HCM confirmed by imaging, histopathology, or genotyping.
- Concept: Evaluation of immune activation, T-cell or macrophage subsets, cytokine expression, RNA modification, or necroptosis mechanisms.
- Context: Investigations using histological, clinical, bioinformatic, transcriptomic, or single-cell approaches.
- Publication characteristics: Peer-reviewed articles published in English.
We excluded the following: (i) animal or cell-only studies without human validation; (ii) case reports or series with fewer than five participants; (iii) conference abstracts, editorials, and gray literature; and (iv) studies without primary or integrative data on immune or molecular mechanisms.
2.3. Study Selection
All records were imported into EndNote X25 (Clarivate Analytics, 70 St Mary Axe, London, UK) for deduplication, then uploaded to Rayyan QCRI for blinded screening. Two independent reviewers screened titles and abstracts and evaluated the full texts of all potentially eligible studies. Discrepancies were resolved by discussion or consultation with a third senior reviewer.
2.4. Data Extraction
A standardized extraction template was piloted before implementation. The following data were systematically collected:
- Bibliographic details (author, year, and country);
- Study design and sample characteristics;
- Assessment modality (immunohistochemistry, flow cytometry, RNA-seq, single-cell profiling, or bioinformatics);
- Key immune or molecular findings (T-cell subsets, macrophage polarization, cytokine pathways, lncRNA–mRNA pairs, m6A readers, and necroptosis genes);
- Clinical correlates (fibrosis, arrhythmia, or outcomes);
- Main conclusions and limitations.
Data were independently extracted by two reviewers and cross-checked for accuracy.
2.5. Critical Appraisal of Evidence
Given the heterogeneity of study designs, a formal meta-analysis was not feasible. Instead, quality appraisal was conducted using validated instruments appropriate for each study type: AMSTAR 2 for systematic reviews; JBI critical appraisal tools for observational and biomarker studies; and evaluation of reproducibility, external validation, and biological plausibility for omics and single-cell datasets. Each study was categorized as having low, moderate, or high methodological strength, as shown in Supplemental Materials (Supplemental Tables S1A, S1B and S2).
2.6. Data Synthesis and Integration
The findings were synthesized narratively across four thematic domains:
- Histologic and biopsy-based studies;
- Clinical and biomarker cohorts;
- Transcriptomic and bioinformatic analyses;
- Translational and single-cell investigations.
To ensure analytical depth, recurring molecular pathways and immune signatures were tabulated and cross-validated across datasets. When available, GEO dataset identifiers (e.g., GSE36961 and GSE141910) were annotated to facilitate reproducibility. Molecular interactions and drug–target networks were further explored using STRING, Enrichr, and DrugBank databases to identify therapeutic candidates for immune–metabolic modulation.
2.7. Ethical Considerations
This study synthesized publicly available data and previously published reports; therefore, institutional ethics approval and informed consent were not required.
3. Results
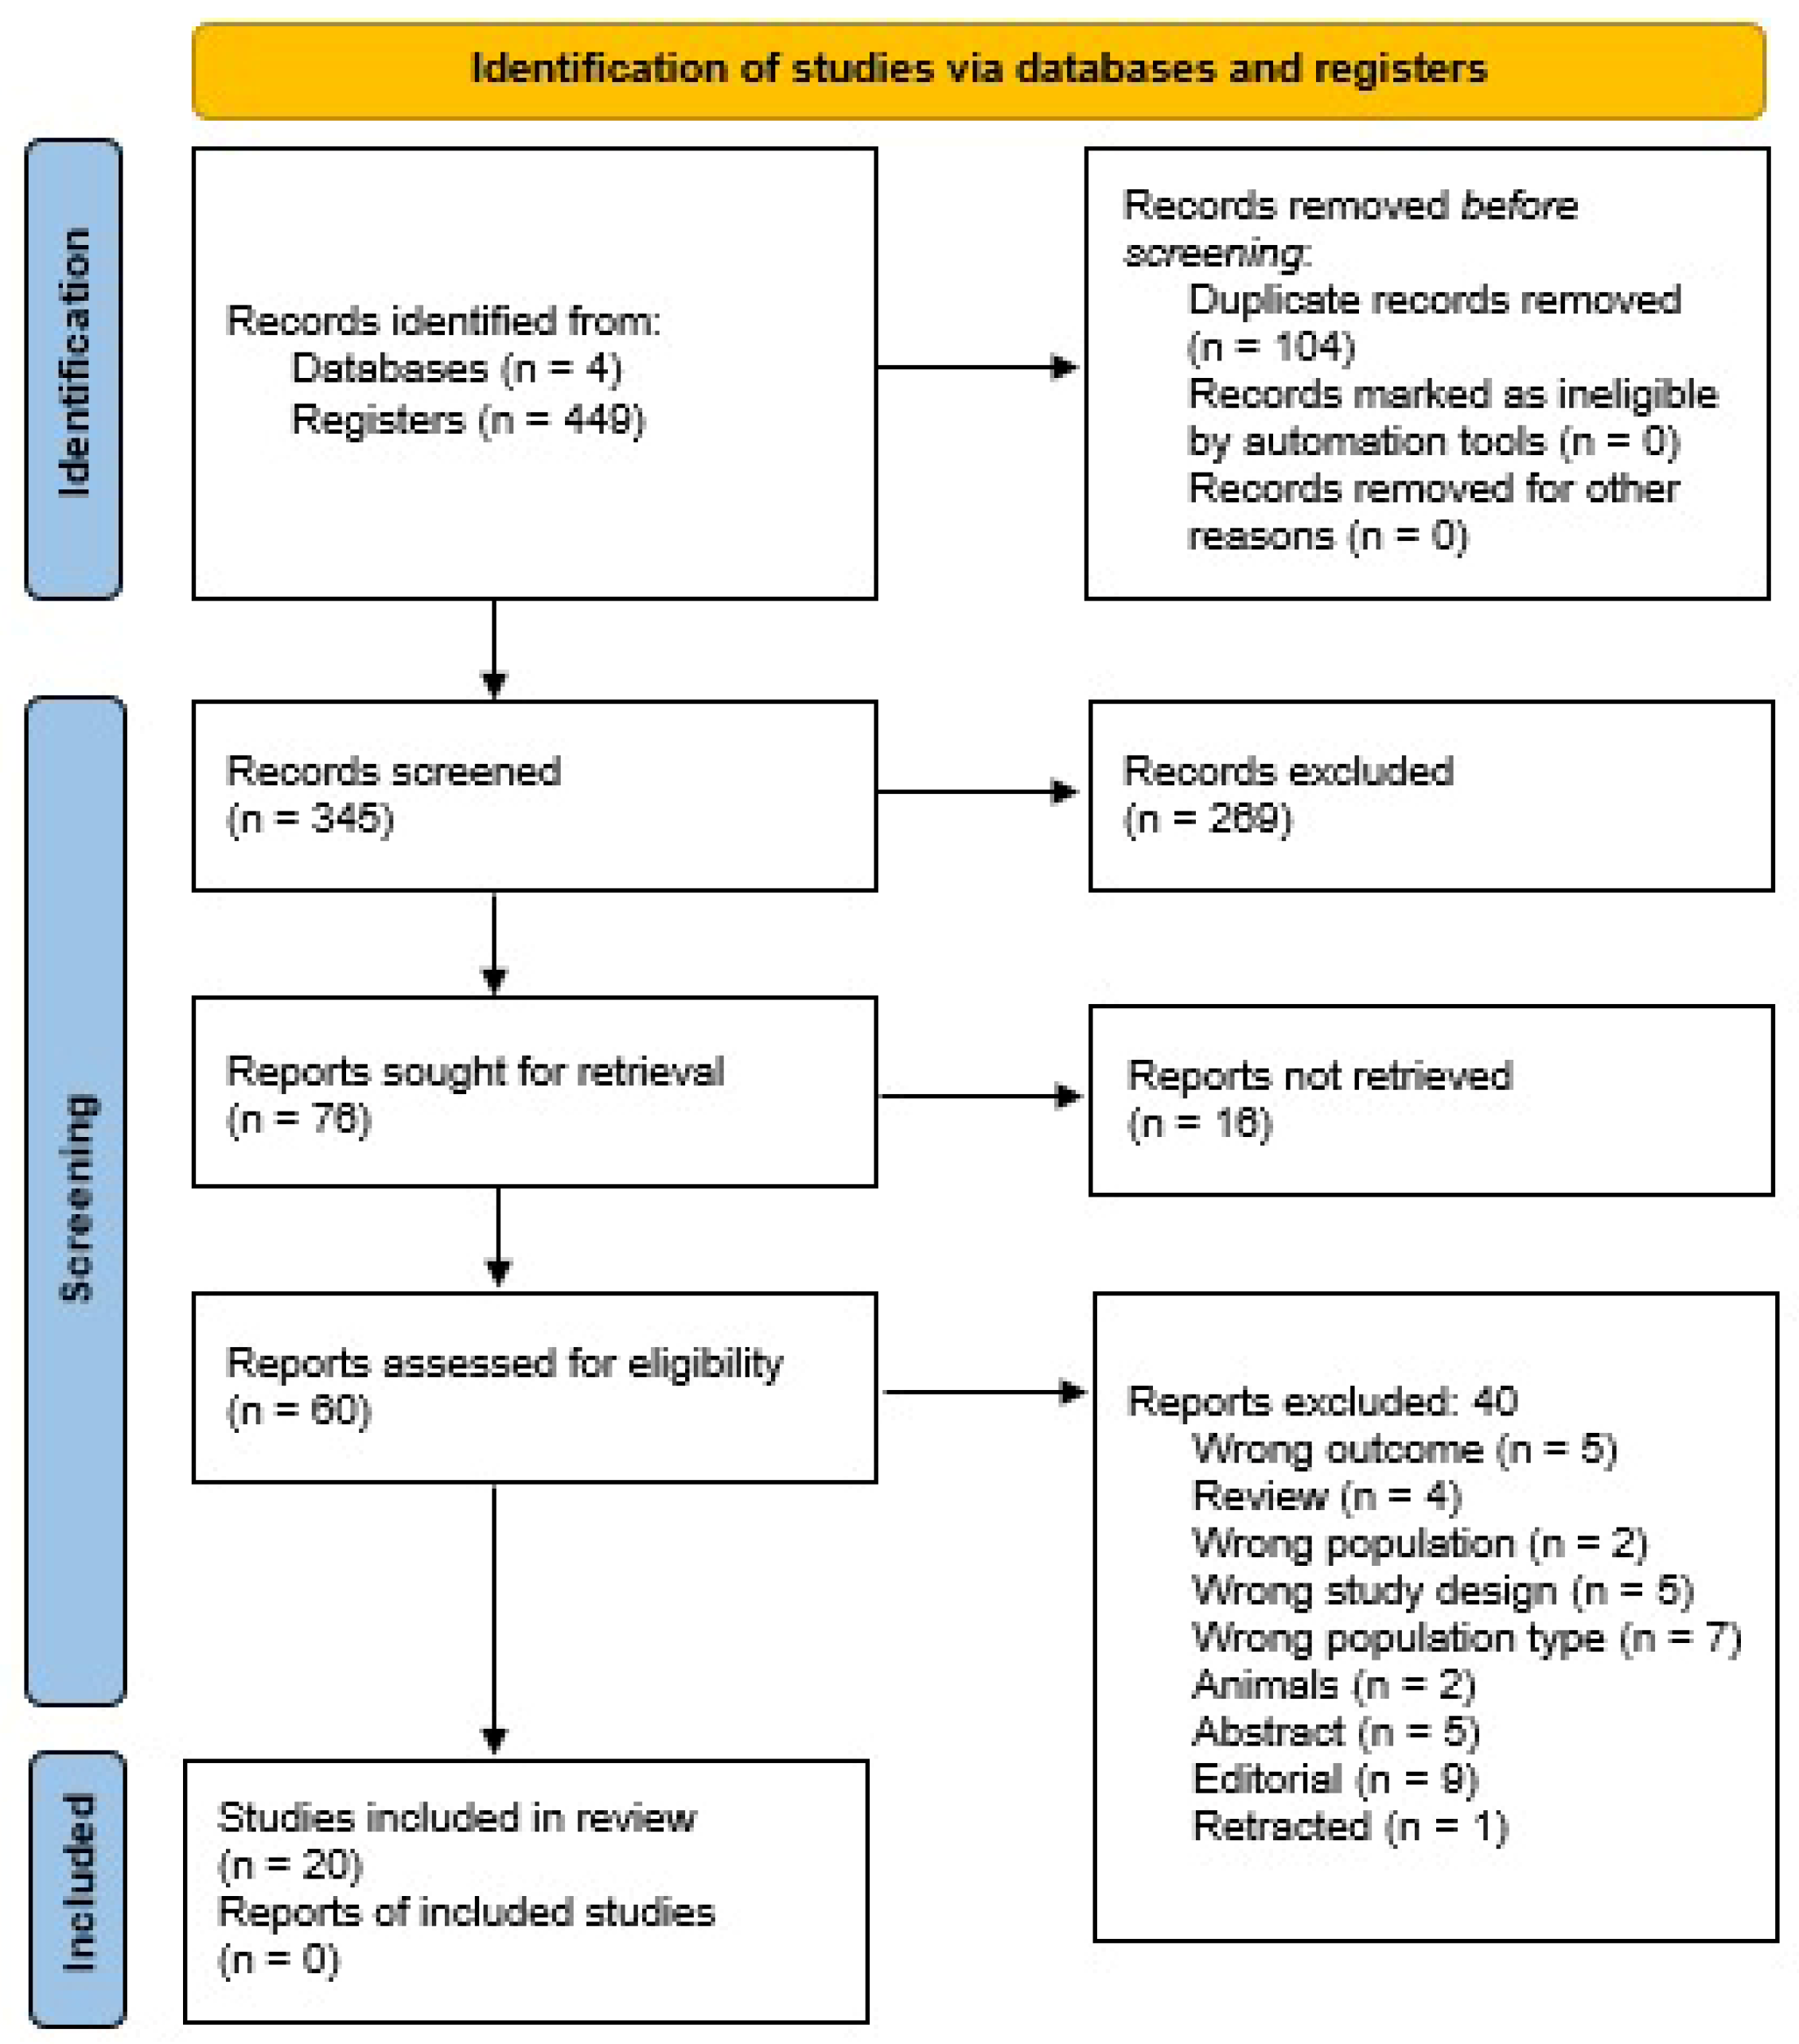
A total of 8191 prospective studies were identified in our scoping review, and 380 were included in the full-text review (Figure 1). A total of 25 studies were included in the analysis [22,23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41,42]. Following the analysis of the primary findings, we categorized the studies into several groups based on the research’s main features and results, as shown in Table 1.
Figure 1.
PRISMA Flowchart.
Table 1.
Demographic characteristics of selected studies.
3.1. Immune Dysregulation in Hypertrophic Cardiomyopathy
Recent studies using transcriptomic and bioinformatics analyses have identified a significant role for the immune system in the pathogenesis of HCM. The drug targets identified by network pharmacology lack sufficient dose–response data, on-target proof in HCM models, or safety assessments for the heart when used in combination with standard treatment, as shown in Supplementary Table S1A,B.
Specifically, changes in macrophage populations and T-cell subsets, along with the dysregulation of genes such as IGFBP3 and the lncRNA-mRNA pair MIR210HG-BPIFC, are central to these findings [22,23,24,25,26].
3.2. Immune–Epigenetic Crosstalk and Immune Cell Infiltration in Hypertrophic Cardiomyopathy
Recent transcriptomic and single-cell studies have uncovered a complex interplay between immune dysregulation and epigenetic regulation in hypertrophic cardiomyopathy (HCM). A central feature of the immune landscape in HCM is the marked imbalance of macrophage populations within the myocardium. Tissue analyses consistently show a significant reduction in LYVE1+CD163+ M2 macrophages, which are essential for maintaining tissue homeostasis and resolving inflammation, accompanied by an increase in pro-inflammatory M1 macrophages [25]. This macrophage polarization shift favors chronic inflammation and fibrotic remodeling, creating a microenvironment that promotes disease progression.
In parallel, T-cell dysregulation has emerged as another hallmark of the HCM immune profile. A notable reduction in naïve CD4+ T cells, together with an increase in cytotoxic CD8+ T cells, suggests an imbalance in adaptive immune activation [22]. Interestingly, the MIR210HG–BPIFC lncRNA–mRNA pair, which is downregulated in HCM, appears to modulate this process by influencing the infiltration and differentiation of these T-cell subsets [22]. This finding supports the notion that epigenetic control at the RNA level contributes to the remodeling of the myocardial immune microenvironment.
Comprehensive immune infiltration analyses further demonstrate a decreased representation of monocytes, dendritic cells, Th1 cells, and regulatory T cells (Tregs), indicating impaired adaptive immune surveillance in the hypertrophied myocardium [25]. Conversely, the increased infiltration of basophils and activated macrophages indicates sustained activation of the innate immune system, which perpetuates inflammatory signaling and contributes to interstitial fibrosis. Collectively, these cellular shifts depict an immune ecosystem skewed toward inflammation and tissue injury rather than repair.
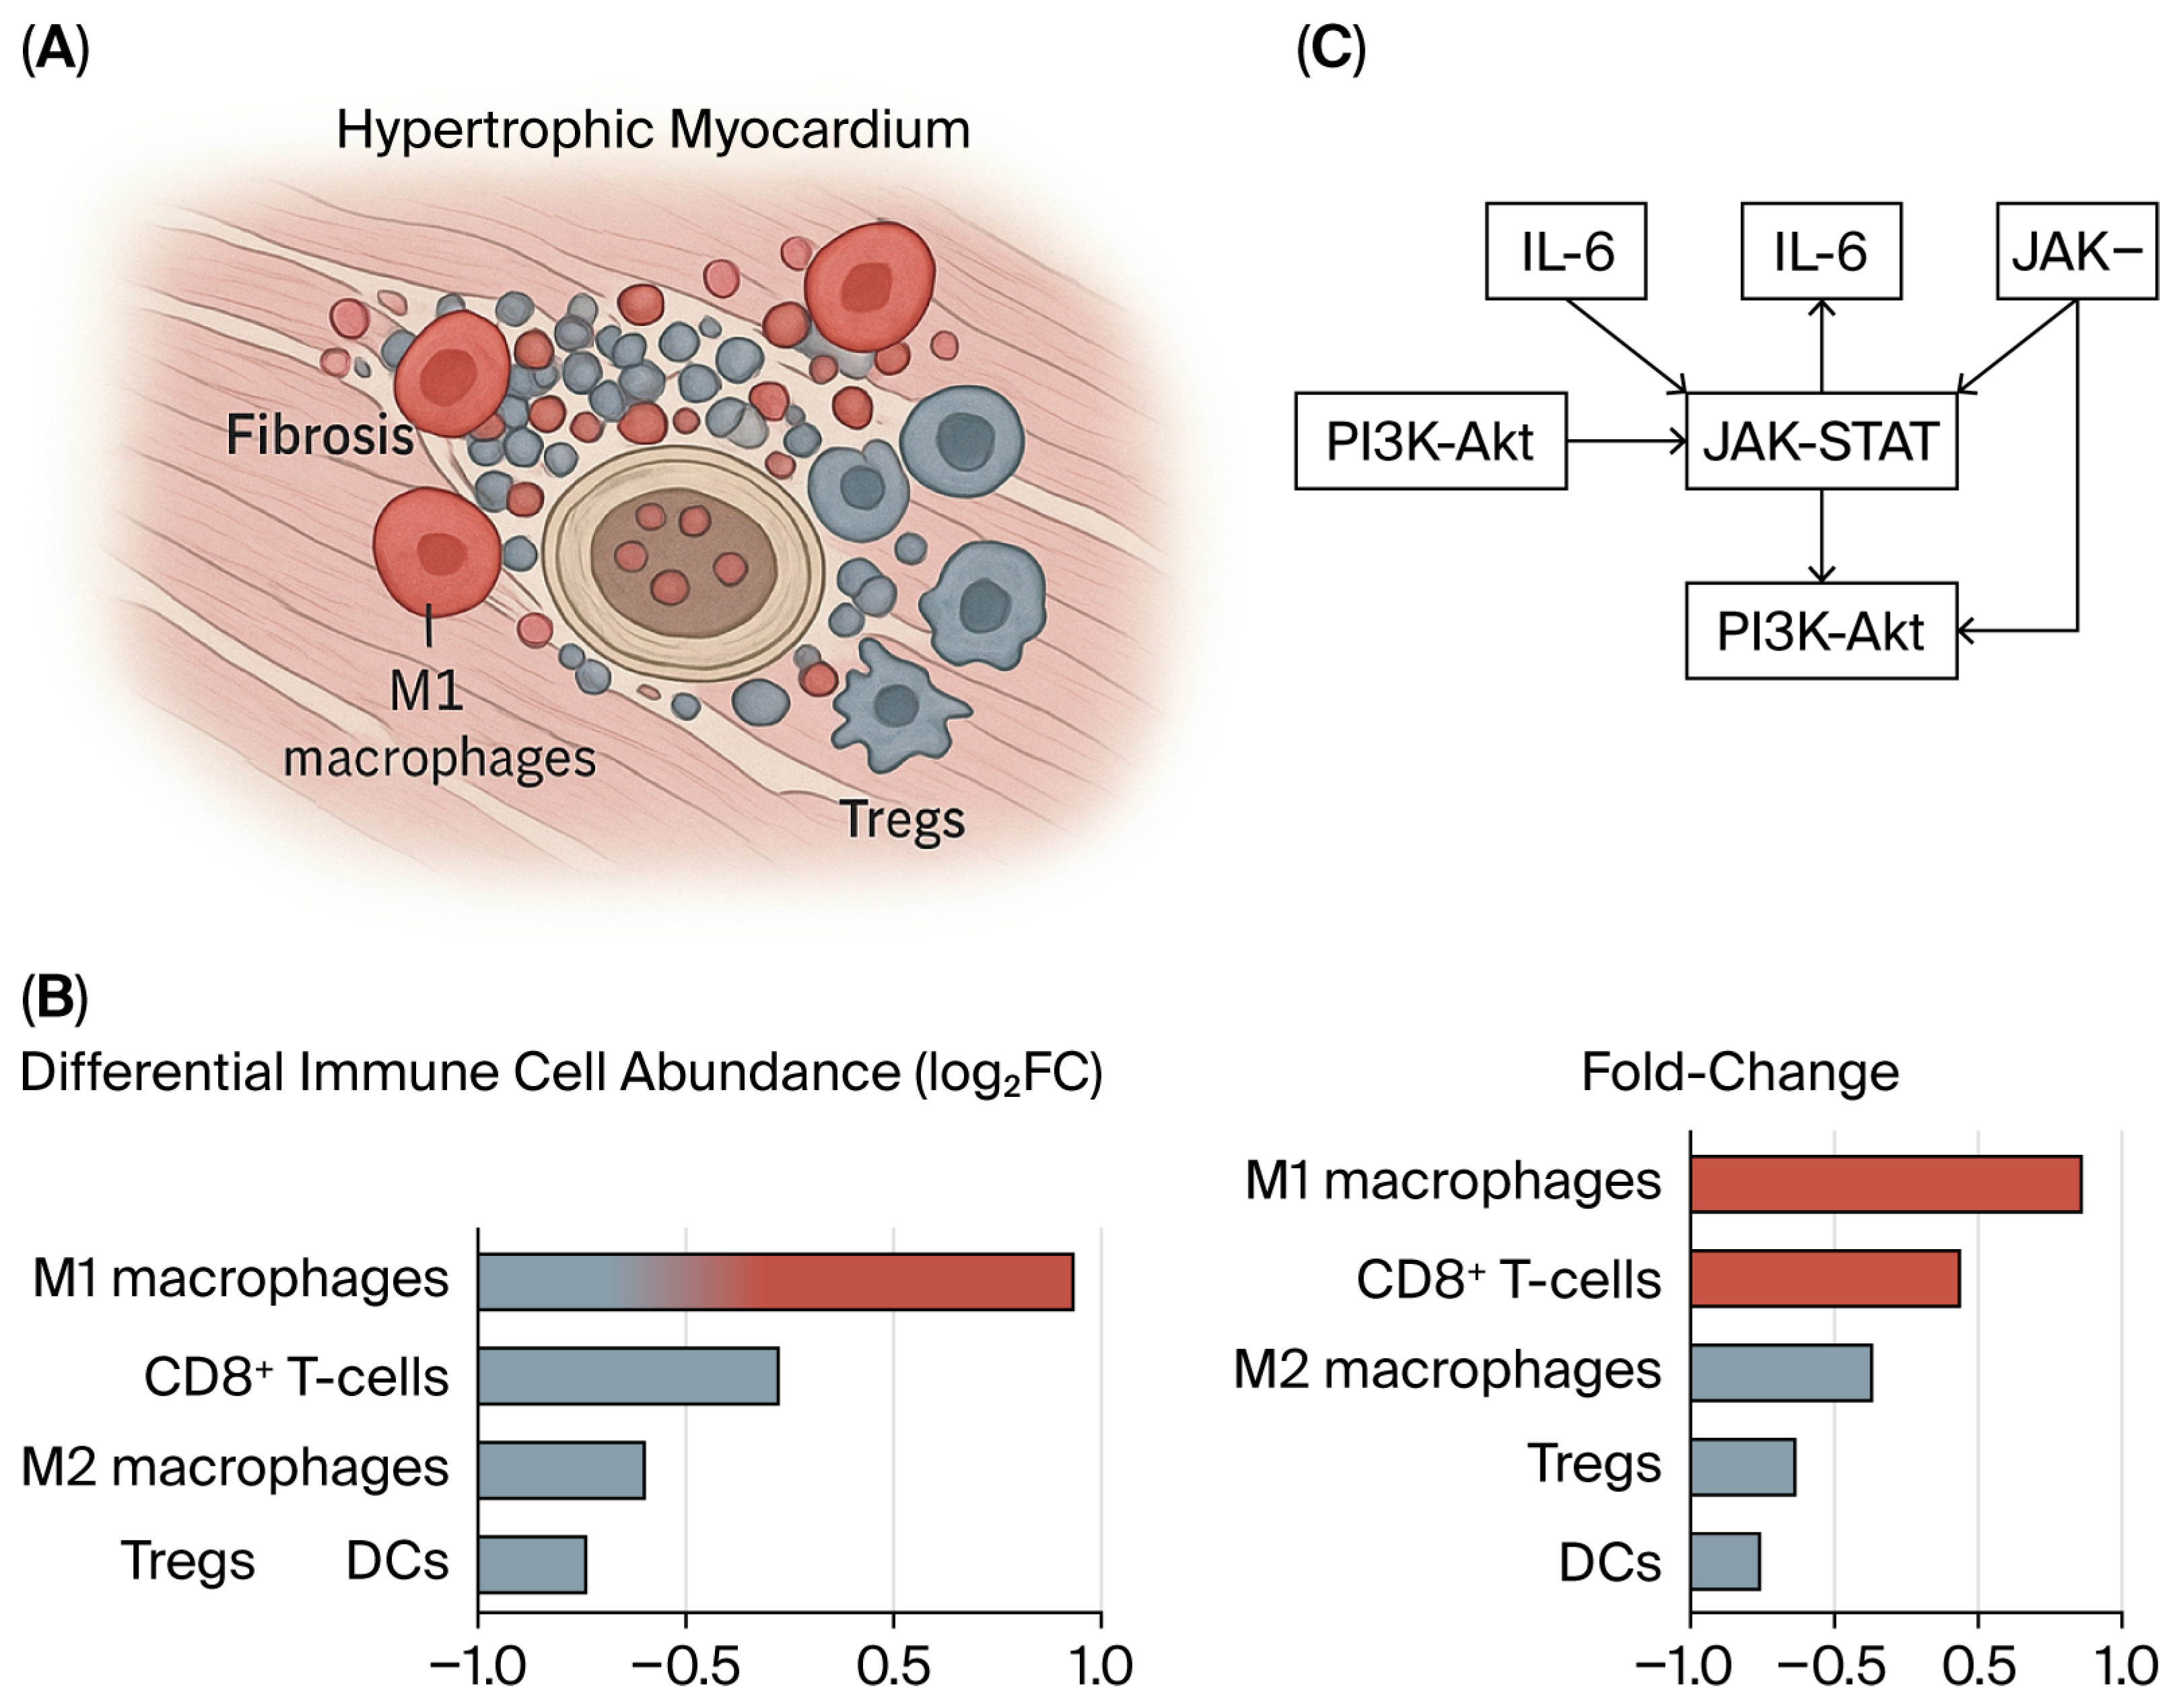
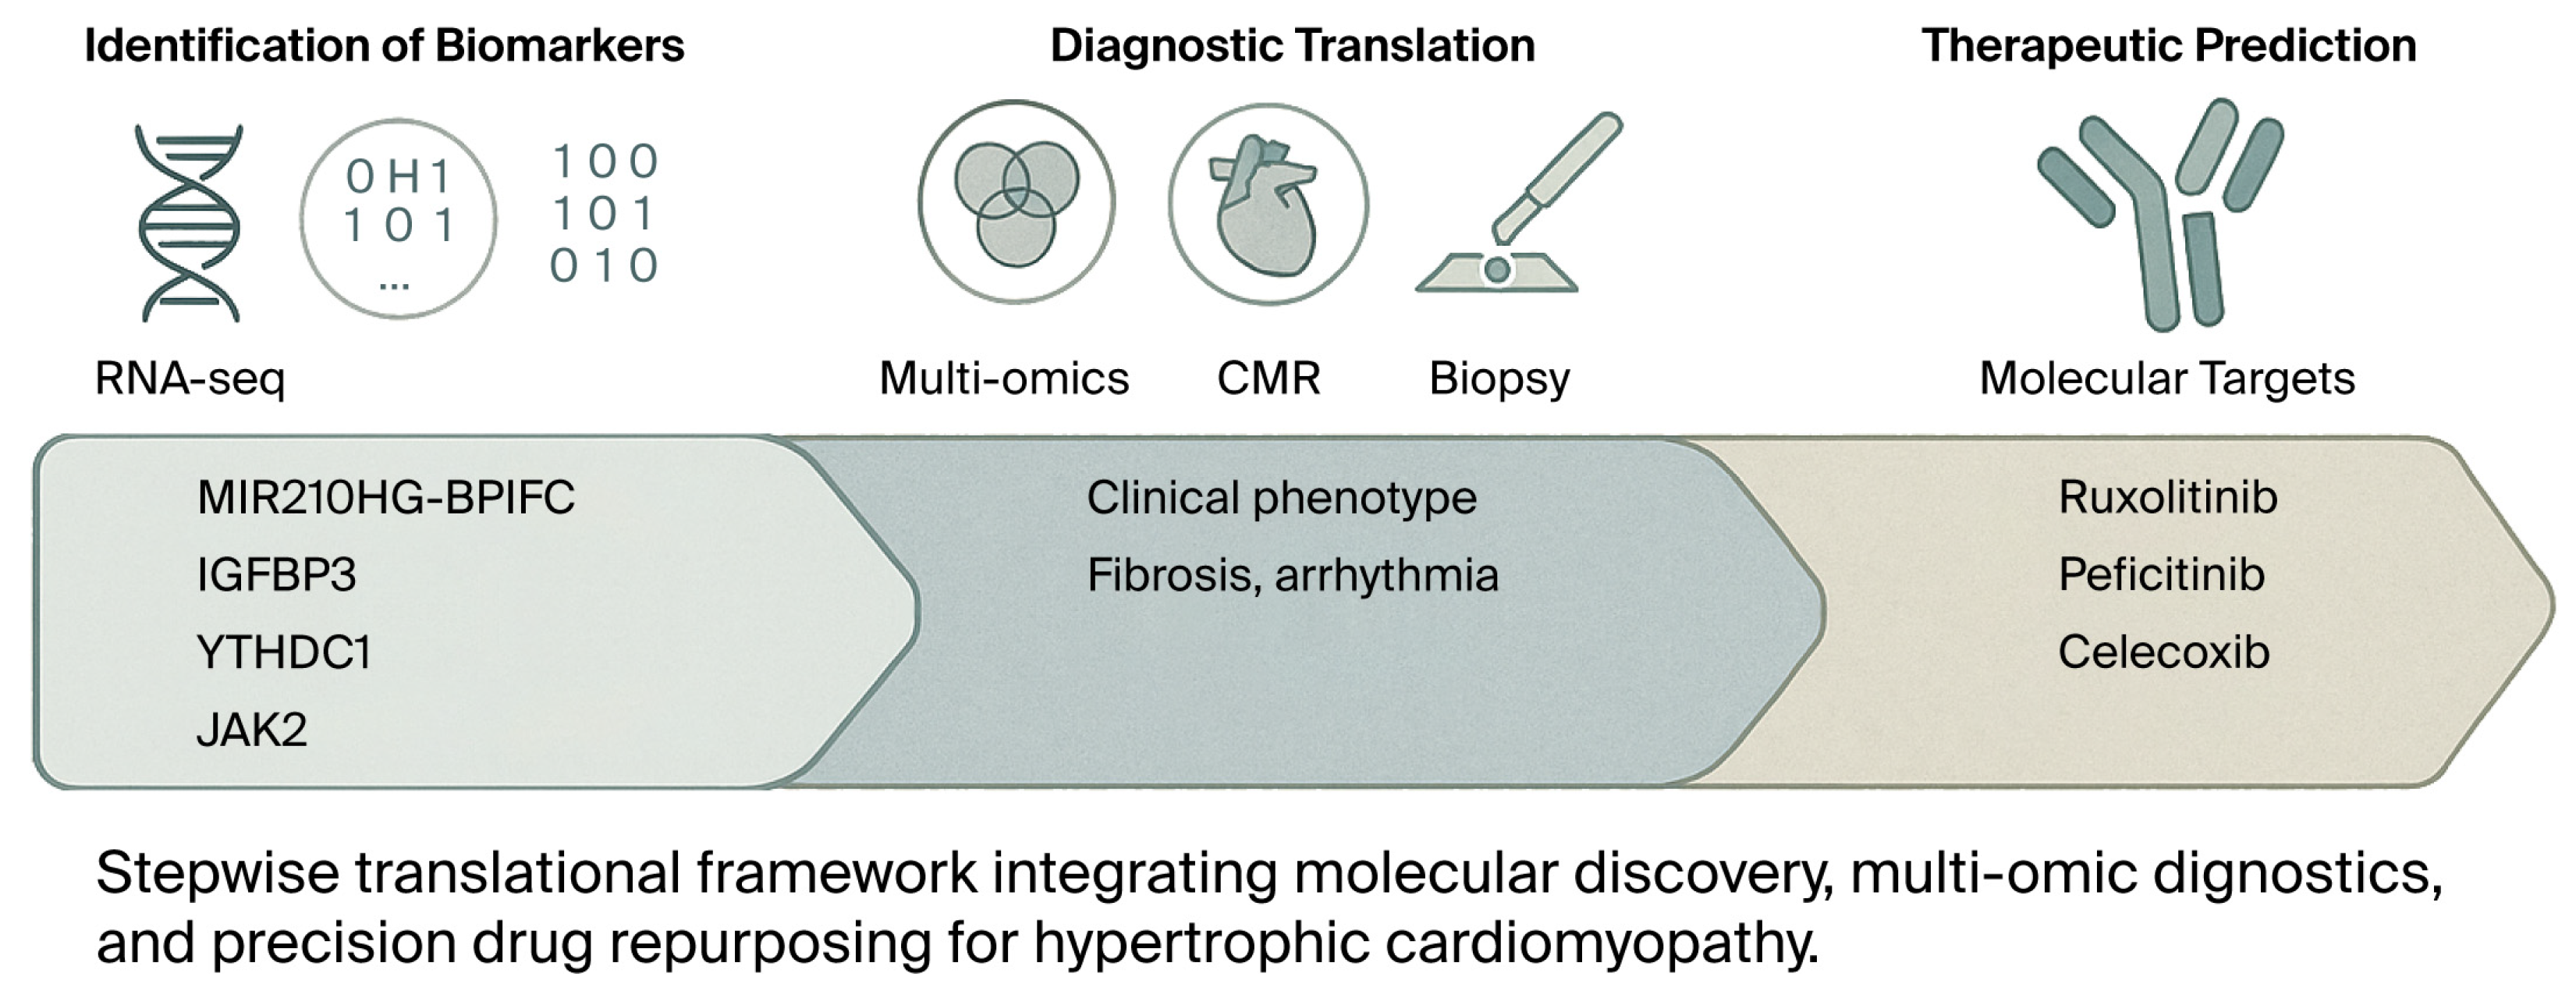
At the molecular level, epigenetic regulators are increasingly recognized as key orchestrators of this inflammatory milieu. The elevated expression of the m6A reader IGFBP3 has been linked to a highly enriched inflammatory state, marked by the increased infiltration of activated dendritic cells, macrophages, mast cells, and Tregs [23]. Pathway enrichment analyses revealed significant activation of TNFα signaling via NFκB and the IL6–JAK–STAT3 pathways in the high-IGFBP3 subgroup, underscoring the role of RNA methylation in amplifying cytokine-driven inflammatory remodeling [23] as shown in Figure 2 and Figure 3.
Figure 2.
Immune cell remodeling in hypertrophic cardiomyopathy (HCM). (A) Schematic representation of hypertrophic myocardium showing immune infiltration and microstructural remodeling, characterized by increased M1 macrophages and CD8+ T-cells, reduced T regulatory cells (Tregs), and relative depletion of M2 macrophages and dendritic cells (DCs). Fibrotic deposition and myocyte disarray are illustrated as hallmarks of HCM pathology. (B) Differential abundance of immune cell populations (log2 fold-change), demonstrating up-regulation of pro-inflammatory M1 macrophages and CD8+ T-cells, and down-regulation of reparative M2 macrophages, Tregs, and DCs in HCM myocardium. (C) Key inflammatory signaling pathways implicated in immune-mediated myocardial remodeling, including IL-6–mediated activation of the JAK–STAT and PI3K–Akt pathways, contribute to fibrotic and hypertrophic responses. Abbreviations: DCs—Dendritic cells; HCM—Hypertrophic cardiomyopathy; IL-6—Interleukin-6; JAK—Janus kinase; PI3K—Phosphoinositide 3-kinase; STAT—Signal transducer and activator of transcription; Tregs—Regulatory T cells (CD4+CD25+FoxP3+).
Figure 3.
From mechanistic insight to precision immunotherapy in hypertrophic cardiomyopathy (HCM). This figure illustrates a stepwise translational framework connecting molecular discovery, diagnostic integration, and therapeutic prediction in HCM. Identification of biomarkers begins with RNA-seq and multi-omic analyses, highlighting key immunogenetic drivers, including MIR210HG–BPIFC, IGFBP3, YTHDC1, and JAK2. These candidate biomarkers undergo diagnostic translation using multi-omic profiling, cardiovascular magnetic resonance (CMR), and myocardial biopsy to link molecular signatures with clinical phenotypes, including fibrosis and arrhythmia susceptibility. Finally, therapeutic prediction leverages these mechanistic insights to identify potential immunomodulatory drug targets. It proposes repurposed agents—such as ruxolitinib, peficitinib, and celecoxib—to modulate the JAK–STAT and inflammatory pathways implicated in HCM remodeling. Overall, the figure summarizes an integrated precision-medicine pipeline for advancing targeted immunotherapy in hypertrophic cardiomyopathy. Abbreviations: CMR—Cardiovascular magnetic resonance; HCM—Hypertrophic cardiomyopathy; RNA-seq—RNA sequencing.
Balancing transcriptomic data identified a cluster of downregulated hub genes with critical roles in immune function, including CD14, ITGB2, C1QB, CD163, HCLS1, ALOX5AP, PLEK, C1QC, FCER1G, and TYROBP. These genes are involved in pathways governing inflammatory and innate immune responses and JAK–STAT signaling [24,25,26]. In addition, the necroptosis pathway, a regulated form of programmed cell death, is significantly enriched and activated in HCM myocardial tissue. Core necroptosis-related genes, such as CYBB, BCL2, and JAK2, show strong correlations with M2 macrophage infiltration, linking maladaptive cell death mechanisms to immune remodeling [24].
Together, these findings suggest that immune–epigenetic interactions form a critical axis in the pathophysiology of HCM. Epigenetic modifications, including m6A methylation and lncRNA-mediated regulation, appear to shape immune cell composition and function, thereby perpetuating chronic inflammation and fibrotic transformation.
Bioinformatic analyses corroborate these insights, consistently showing that HCM is characterized by upregulated innate immune activity—including the expansion of M0 macrophages (They refer to undifferentiated monocytes before polarization into M1 or M2 phenotype), monocytes, and natural killer (NK) cells—and the downregulation of adaptive immune regulatory components, such as M2 macrophages, Tregs, and plasma cells. This immunological imbalance favors a pro-inflammatory and pro-fibrotic myocardial environment that underpins disease progression and clinical heterogeneity, as summarized in Table 2.
Table 2.
Integrated overview of immune infiltration, molecular pathways, and translational biomarkers in HCM.
3.3. Macrophage Heterogeneity and Remodeling in HCM
Macrophages play a central role in the immunopathology of hypertrophic cardiomyopathy (HCM), linking inflammation, fibrosis, and myocardial remodeling. Bioinformatic analyses of myocardial transcriptomes consistently reveal a profound imbalance between macrophage subtypes, characterized by a loss of reparative LYVE1+CD163+ M2 macrophages and an accumulation of pro-inflammatory M1 macrophages [25]. This polarization shift undermines tissue homeostasis and promotes fibrotic progression. Further, the absence of GATA3+ macrophages has been associated with improved myocardial function, suggesting that macrophage transcriptional phenotypes directly influence disease severity [28].
The differentiation of circulating monocytes into M1 and M2 macrophages appears to be dysregulated in HCM, shaping both inflammatory intensity and repair potential [27]. Interestingly, the results from different transcriptomic datasets are heterogeneous. While GSE32453 suggests increased macrophage, NK cell, and monocyte infiltration, GSE36961 and GSE141910 report the opposite pattern, with decreased macrophages and monocytes but increased CD8+ T cells, basophils, and fibroblasts [25]. These contrasting results likely reflect stage-dependent immune remodeling, in which immune overactivation and suppression may coexist across different disease contexts.
Histologically, CD68+ macrophages are enriched in fibrotic and necrotic regions, coordinating debris clearance and repair responses [27]. The upregulation of IGFBP3, an m6A RNA-binding protein, further correlates with the increased infiltration of macrophages, mast cells, and dendritic cells, linking metabolic and epigenetic signaling to immune activation [23]. Collectively, these findings support the view that HCM is not solely a structural or genetic disorder but also an immunologically dynamic disease, in which macrophage plasticity critically shapes fibrosis, ventricular compliance, and clinical outcomes.
Contrasting immune infiltration results—some reporting increased, others decreased macrophage/monocyte abundance—may reflect differences in sampling (e.g., myectomy vs. biopsy), disease stage, bioinformatic pipelines, or batch correction strategies. These variations underscore the need for standardized immune deconvolution methods and longitudinal sampling to define the trajectory of immune remodeling in HCM.
4. Discussion
Our scoping review, drawing on recent bioinformatic and experimental studies, identifies convergent genetic, epigenetic, and immunoregulatory signals that reshape current thinking on hypertrophic cardiomyopathy (HCM). Key candidates include the lncRNA–mRNA pair MIR210HG–BPIFC, the m6A readers IGFBP3 and YTHDC1, and the necroptosis-related kinase JAK2—each of which is emerging as a potential biomarker and therapeutic target. Moving forward, priorities include in vivo validation, mechanistic dissection, and clinical translation to improve diagnosis, risk stratification, and therapy [22,23,24,35,36,37]. While animal-only studies were excluded, findings from mouse models and iPSC-derived cardiomyocytes have informed our understanding of fibrosis, inflammation, and sarcomeric disarray. These models offer mechanistic insight into immune–fibrotic interactions and should be considered complementary to human data.
4.1. Genetic and Epigenetic Modulators of Immune Remodeling
Accumulating evidence indicates that non-coding RNA networks modulate myocardial inflammation and remodeling. The MIR210HG–BPIFC pair is downregulated in HCM and may shape immune cell infiltration—notably naïve CD4+ and CD8+ T cells—within the myocardium, implicating RNA-level control in disease progression [22]. At the epigenetic level, the m6A readers IGFBP3 and YTHDC1 are upregulated in HCM and, respectively, differentiate cases from controls with high accuracy, linking RNA methylation to immune activation and energy metabolism/mitophagy [23]. Together, these signals define a molecular axis linking transcriptional regulation with immune tone and metabolic stress [22,23,35,38,39,40,41,42].
4.2. Immunoregulation and Cell Infiltration
Across datasets, JAK–STAT appears among the most perturbed immune pathways—often enriched among downregulated genes—underscoring its role in maintaining immune balance in cardiac tissue [25,32,33]. Additional inflammation-linked pathways (e.g., MAPK, PI3K–Akt) accompany shifts in immune composition, highlighting complex immune dysregulation in HCM [25,28]. Functionally, IGFBP3-high tissues show activated dendritic cells, macrophages, mast cells, and Tregs, and the enrichment of TNFα–NFκB and IL6–JAK–STAT3 signaling—consistent with an inflamed myocardial microenvironment [23]. JAK2 also sits at the intersection of immune activation and necroptosis, correlating with macrophage phenotypes and linking cell death programs to fibrotic remodeling [24].
4.3. Biomarkers for Diagnosis and Risk Stratification
Multiple analytic strategies converge on promising diagnostic signatures. Machine learning analyses identify RASD1, CDC42EP4, MYH6, and FCN3 as strong classifiers of HCM vs. controls [29]. Independent analyses highlight a 10-gene hub panel—CD14, ITGB2, C1QB, CD163, HCLS1, ALOX5AP, PLEK, C1QC, FCER1G, and TYROBP—that is downregulated in myocardial tissue [26]. Gong et al. report eight additional candidates (FOS, CD86, CD68, BDNF, PIK3R1, PLEK, RAC2, and CCL2), each with an AUC > 0.8, reinforcing the diagnostic robustness of their approach [27]. Beyond expression panels, IGFBP3 and YTHDC1 (m6A readers) discriminate HCM and may bridge metabolic and immune dysregulation; IGFBP3 and JAK2 also associate with altered energy metabolism, strengthening their pathobiological relevance [23,28]. Clinically, these markers could improve differential diagnosis—particularly from hypertensive LVH—and refine risk stratification [23].
4.4. Integrated Model of Ischemia–Immune Interactions Driving Fibrosis in Hypertrophic Cardiomyopathy
Emerging data suggest that immune-mediated remodeling is not an isolated process; instead, it likely interacts with established ischemic mechanisms that have long been associated with hypertrophic cardiomyopathy. HCM is distinguished by microvascular dysfunction, which is caused by small-vessel thickening, a reduced capacity for vasodilation, and extravascular compression during diastole, the period when coronary perfusion should ideally occur. These pathological features result in recurrent supply–demand imbalances, focal ischemia, and myocyte necrosis, which subsequently elicit reparative fibrosis and contribute to the arrhythmogenic substrate. Furthermore, ischemic injury may also catalyze secondary immune activation, thereby facilitating macrophage recruitment, fibroblast proliferation, and cytokine-mediated extracellular matrix deposition.
Consequently, microvascular ischemia and immune remodeling should be considered synergistic processes, rather than mutually exclusive ones. Chronic ischemia initiates cellular damage and establishes a pro-inflammatory environment, thereby exacerbating the immunogenetic pathways discussed herein. This integrated perspective facilitates a more thorough comprehension of the multifaceted origins of fibrosis and electrical instability in HCM [43,44,45].
4.5. Therapeutic Targeting and Drug Repurposing
The same nodes that organize immune–metabolic crosstalk may be actionable. Bioinformatic predictions nominate ruxolitinib (JAK1/2) for JAK2 and celecoxib (COX-2) for IGFBP3 as candidates for targeted intervention; peficitinib (JAK1/2/3) has also been proposed to modulate JAK-dependent inflammation [28,30]. Pathway-level targets such as PIK3R1 (PI3K–Akt) suggest additional levers to limit hypertrophy and adverse remodeling [27]. These leads, while preliminary, support a precision immunometabolic therapeutic strategy anchored in patient-specific molecular profiles [22,23,24].
4.6. Targeted Candidates and Rationale (Concise)
JAK2 → ruxolitinib/peficitinib: These suppress cytokine-driven inflammation and have the potential to blunt JAK-STAT-linked remodeling [28,30]. IGFBP3 → celecoxib: These predict interactions in drug–target networks and may influence inflammation/fibrosis interfaces and metabolic signaling [23,28]. IGFBP3 and JAK2 co-expression: It is reproducibly higher across HCM datasets (e.g., GSE36961, GSE89714), strengthening its disease relevance [23,28]. These represent theoretical candidates for future exploration but lack direct testing in HCM models or clinical safety data in this context.
4.7. Imaging–Molecular Integration
CMR-LGE provides a robust, noninvasive assessment of fibrosis but may miss a subset of patients with histologically extensive fibrosis. EMB-derived collagen area fraction (CAF) and CD3+ T-cell counts independently predict adverse outcomes, and a combined high CAF/high CD3+ portends the worst prognosis [31]. Pairing CMR with genetic/epigenetic biomarkers (e.g., IGFBP3, YTHDC1, JAK2) could enhance phenotype discrimination and outcome prediction. At the same time, spatial transcriptomics suggests focal alterations in interferon signaling, mitochondrial metabolism, and ECM within disorganized regions that may be therapeutically exploitable [24,32,33].
4.8. Methodological Considerations When Aggregating Public Datasets
Leveraging multiple GEO and related datasets increases power, enables external validation, and improves model construction (e.g., integrating imaging features with clinical scores). Still, it introduces risks of dataset inconsistency, class imbalance, and overfitting. Findings must be confirmed in independent cohorts and, ultimately, via experimental validation in clinical samples and patient-derived cardiomyocytes [22,26,29,30,34].
Findings must be interpreted with caution, as several key analyses are derived from recurring GEO datasets (e.g., GSE36961, GSE141910). This may give the appearance of convergence, while in fact representing reanalyses of overlapping patient material. As such, it reduces the adequate sample size and limits the generalizability of findings across diverse cohorts.
4.9. Consolidated Outlook
Collectively, the evidence supports a genetic–epigenetic–immune axis in HCM: MIR210HG–BPIFC, IGFBP3, YTHDC1, and JAK2 link RNA regulation, immune activation, necroptosis, and metabolism, while hub and ML-derived genes (e.g., CD14, ITGB2, C1QB, CD163, FOS, PIK3R1, RAC2) expand the diagnostic toolkit [26,27,29]. The predicted agents (ruxolitinib, celecoxib, and peficitinib) exemplify a shift toward targeted immunometabolic therapy [28,30]. The next step is prospective, multimodal validation—melding omics, imaging, and pathology—to deliver molecularly guided diagnosis and treatment in HCM [22,23,24], as shown in Figure 3. The new evidence and clinical implications are presented in Supplemental Material Table S3.
4.10. Limitations
The current study has several limitations that should guide interpretation. This is a scoping synthesis that maps signals instead of counting them. Because there is no formal meta-analysis, we cannot estimate the effect size, quantify heterogeneity, or assess small-study and publication biases. Study identification was limited to peer-reviewed English-language publications, excluding non-English and gray sources that could skew biomarker results. There is substantial variety in the evidence base. The datasets include both bulk and single-cell platforms, including distinct preprocessing, normalization, and immune-deconvolution methods; cross-platform batch effects may be misinterpreted as biological concordance. GEO cohorts are often reanalyzed across different publications, which can create a false impression of reproducibility and effectively reduce the sample size. Tissue collection is variable (e.g., myectomy specimens, endomyocardial biopsy, and explant), and clinical confounders—such as genotype, disease stage, obstruction status, comorbidities, and concurrent cardiometabolic or disease-modifying therapies—are inconsistently recorded or managed. Most research is cross-sectional, which renders it difficult to draw causal conclusions. Different immune cell signals across datasets show how sensitive findings are to platform and cohort makeup. Translational assertions are still in their early stages. Pathway enrichment (e.g., IL-6/JAK-STAT, NF-κB, PI3K-Akt, and necroptosis) is mostly inferred in silico, supplemented with limited protein-level and phospho-signaling validation. Reported machine-learning biomarkers demonstrate promising discriminative performance, but without stringent external prospective validation, calibration, or decision-curve analysis. The drug targets identified by network pharmacology lack sufficient dose–response data, on-target proof in HCM models, or safety assessments for the heart when used with standard treatment. Lastly, molecular imaging integration is limited by the lack of studies combining patient-level omics with CMR (LGE/ECV), strain, or clinical outcomes. Moreover, there are too few pediatric cases, phenocopies, and individuals of diverse ancestries to make the results broadly generalizable. These limitations underscore the need for prospective, multicenter studies with standardized methodologies, high spatial resolution, protein-level validation, and early-phase, mechanism-informed trials before clinical implementation.
5. Conclusions
These findings support a hypothesis that HCM may involve immunogenetic mechanisms, rather than being exclusively sarcomeric in nature, although this remains to be validated. The convergence of evidence around MIR210HG–BPIFC, IGFBP3, YTHDC1, and JAK2 underscores an integrated axis linking RNA methylation, immune activation, necroptosis, and fibrosis. These molecules, together with downregulated or upregulated immune hub genes, form a promising foundation for biomarker-based diagnosis and targeted intervention.
Predicted pharmacologic modulators—such as ruxolitinib and celecoxib—illustrate the emerging feasibility of precision immunometabolic therapy in HCM. Future research should focus on validating these pathways in patient-derived cardiomyocytes, integrating imaging and molecular signatures, and testing targeted therapies in translational trials. Ultimately, this integrative framework bridges immunology, genetics, and therapeutics, offering a pathway toward individualized management and improved patient outcomes in hypertrophic cardiomyopathy. These predicted pharmacologic modulators, such as ruxolitinib and celecoxib, illustrate the theoretical potential of precision immunometabolic therapy but require rigorous preclinical evaluation.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/cells15010061/s1, Methods S1: PRISMA; Methods S2: Search Strategy; Table S1A: Characteristics of included studies evaluating T-cell immunity in hypertrophic cardiomyopathy (HCM); Table S1B: Characteristics of included studies evaluating T-cell immunity in hypertrophic cardiomyopathy (HCM); Table S2: Study Appraisal Summary (JBI Framework); Table S3: Translational Perspective.
Author Contributions
Conceptualization, A.d.S.M.J., I.J.W. and S.M.B.; methodology, A.d.S.M.J., I.J.W. and S.M.B.; software, H.L.d.O. and K.B.A.d.L.; validation, A.d.S.M.J.; formal analysis, A.d.S.M.J., I.J.W. and S.M.B.; investigation, A.d.S.M.J. and I.J.W.; resources, A.d.S.M.J.; data curation, A.d.S.M.J., H.L.d.O. and K.B.A.d.L.; writing—original draft preparation, A.d.S.M.J., I.J.W., S.M.B., H.L.d.O. and K.B.A.d.L.; writing—review and editing, A.d.S.M.J., I.J.W., S.M.B., H.L.d.O. and K.B.A.d.L.; visualization, A.d.S.M.J., H.L.d.O. and K.B.A.d.L.; supervision, A.d.S.M.J. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing does not apply to this study.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
| AF | Atrial fibrillation |
| ALOX5AP | Arachidonate 5-lipoxygenase-activating protein |
| AUC | Area under the curve |
| BCL2 | B-cell lymphoma 2 |
| BDNF | Brain-derived neurotrophic factor |
| BPIFC | Bactericidal/permeability-increasing fold-containing family C protein |
| CAF | Collagen area fraction |
| CD | Cluster of differentiation |
| CD14 | Cluster of differentiation 14 |
| CD68 | Cluster of differentiation 68 |
| CD86 | Cluster of differentiation 86 |
| CDC42EP4 | CDC42 effector protein 4 |
| C1QB | Complement component 1, q subcomponent, B chain |
| C1QC | Complement component 1, q subcomponent, C chain |
| CMR | Cardiac magnetic resonance |
| CYBB | Cytochrome b-245, beta chain |
| DC | Dendritic cell |
| ECM | Extracellular matrix |
| FCER1G | Fc fragment of IgE receptor Ig |
| FCN3 | Ficolin-3 |
| FOS | Fos proto-oncogene, AP-1 transcription factor subunit |
| GEO | Gene Expression Omnibus |
| HCM | Hypertrophic cardiomyopathy |
| HOCM | Hypertrophic obstructive cardiomyopathy |
| HCLS1 | Hematopoietic cell-specific Lyn substrate 1 |
| IGFBP3 | Insulin-like growth factor-binding protein 3 |
| IL | Interleukin |
| IL-6 | Interleukin-6 |
| IL-17 | Interleukin-17 |
| INF-γ | Interferon-gamma |
| ITGB2 | Integrin subunit beta 2 |
| JAK | Janus kinase |
| JAK-STAT | Janus kinase/signal transducer and activator of transcription |
| LGE | Late gadolinium enhancement |
| lncRNA | Long noncoding RNA |
| LV | Left ventricle |
| LVEF | Left ventricular ejection fraction |
| LYVE1 | Lymphatic vessel endothelial hyaluronan receptor 1 |
| M0/M1/M2 | Macrophage phenotypes (naïve/pro-inflammatory/reparative) |
| MAPK | Mitogen-activated protein kinase |
| m6A | N6-methyladenosine |
| ML | Machine learning |
| mRNA | Messenger RNA |
| MSC | Mesenchymal stem cell |
| MYBPC3 | Myosin-binding protein C, cardiac type |
| MYH6 | Myosin heavy chain 6 |
| MYH7 | Myosin heavy chain 7 |
| NF-κB | Nuclear factor kappa B |
| NK | Natural killer cell |
| PI3K–Akt | Phosphoinositide 3-kinase–protein kinase B |
| PIK3R1 | Phosphoinositide-3-kinase regulatory subunit 1 |
| PLEK | Pleckstrin |
| PRISMA-ScR | Preferred Reporting Items for Systematic Reviews and Meta-Analyses extension for Scoping Reviews |
| RASD1 | Ras-related dexamethasone-induced 1 |
| RNA-seq | RNA sequencing |
| scRNA-seq | Single-cell RNA sequencing |
| STAT3 | Signal transducer and activator of transcription 3 |
| ST2 | Suppression of tumorigenicity 2 (IL-33 receptor) |
| TGF-β | Transforming growth factor beta |
| Th | T helper |
| TNF-α | Tumor necrosis factor alpha |
| Treg | Regulatory T cell |
| TYROBP | TYRO protein tyrosine kinase-binding protein |
| WGCNA | Weighted gene co-expression network analysis |
| YTHDC1 | YTH domain-containing protein 1 |
References
- Maron, B.J.; Ommen, S.R.; Semsarian, C.; Spirito, P.; Olivotto, I.; Maron, M.S. Hypertrophic cardiomyopathy: Present and future, with translation into contemporary cardiovascular medicine. J. Am. Coll. Cardiol. 2014, 64, 83–99, Erratum in J. Am. Coll. Cardiol. 2014, 64, 1188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arbelo, E.; Protonotarios, A.; Gimeno, J.R.; Arbustini, E.; Barriales-Villa, R.; Basso, C.; Bezzina, C.R.; Biagini, E.; Blom, N.A.; De Boer, R.A.; et al. 2023 ESC Guidelines for the management of cardiomyopathies. Eur. Heart J. 2023, 44, 3503–3626. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Braunwald, E. Hypertrophic Cardiomyopathy: A Brief Overview. Am. J. Cardiol. 2024, 212, S1–S3. [Google Scholar] [CrossRef] [Scilit]
- Ho, C.Y.; Day, S.M.; Ashley, E.A.; Michels, M.; Pereira, A.C.; Jacoby, D.; Cirino, A.L.; Fox, J.C.; Lakdawala, N.K.; Ware, J.S.; et al. Genotype and Lifetime Burden of Disease in Hypertrophic Cardiomyopathy: Insights from the Sarcomeric Human Cardiomyopathy Registry (SHaRe). Circulation 2018, 138, 1387–1398. [Google Scholar] [CrossRef] [Scilit]
- Helms, A.S.; Tang, V.T.; O’Leary, T.S.; Friedline, S.; Wauchope, M.; Arora, A.; Wasserman, A.H.; Smith, E.D.; Lee, L.M.; Wen, X.W.; et al. Effects of MYBPC3 loss-of-function mutations preceding hypertrophic cardiomyopathy. J. Clin. Investig. 2020, 5, e133782. [Google Scholar] [CrossRef] [Scilit]
- Marian, A.J. Molecular Genetic Basis of Hypertrophic Cardiomyopathy. Circ. Res. 2021, 128, 1533–1553. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lillo, R.; Graziani, F.; Franceschi, F.; Iannaccone, G.; Massetti, M.; Olivotto, I.; Crea, F.; Liuzzo, G. Inflammation across the spectrum of hypertrophic cardiac phenotypes. Heart Fail. Rev. 2023, 28, 1065–1075. [Google Scholar] [CrossRef] [Scilit]
- Martín, P.; Sánchez-Madrid, F. T cells in cardiac health and disease. J. Clin. Investig. 2025, 135, e185218. [Google Scholar] [CrossRef] [Scilit]
- Xia, Y.; Gao, D.; Wang, X.; Liu, B.; Shan, X.; Sun, Y.; Ma, D. Role of Treg cell subsets in cardiovascular disease pathogenesis and potential therapeutic targets. Front. Immunol. 2024, 15, 1331609. [Google Scholar] [CrossRef] [Scilit]
- Yu, H.; Gu, L.; Du, L.; Dong, Z.; Li, Z.; Yu, M.; Yin, Y.; Wang, Y.; Yu, L.; Ma, H. Identification and analysis of key hypoxia- and immune-related genes in hypertrophic cardiomyopathy. Biol. Res. 2023, 56, 45. [Google Scholar] [CrossRef] [Scilit]
- Amara, M.; Stoler, O.; Birati, E.Y. The Role of Inflammation in the Pathophysiology of Heart Failure. Cells 2025, 14, 1117. [Google Scholar] [CrossRef] [Scilit]
- Borlaug, B.A.; Sharma, K.; Shah, S.J.; Ho, J.E. Heart Failure with Preserved Ejection Fraction: JACC Scientific Statement. J. Am. Coll. Cardiol. 2023, 81, 1810–1834. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.; Wang, C.; Shen, L.; Xu, D. The Role of Regulatory T Cells in Heart Repair After Myocardial Infarction. J. Cardiovasc. Transl. Res. 2023, 16, 590–597. [Google Scholar] [CrossRef] [Scilit]
- Zhuang, R.; Meng, Q.; Ma, X.; Shi, S.; Gong, S.; Liu, J.; Li, M.; Gu, W.; Li, D.; Zhang, X.; et al. CD4+FoxP3+CD73+ regulatory T cell promotes cardiac healing post-myocardial infarction. Theranostics 2022, 12, 2707–2721. [Google Scholar] [CrossRef] [Scilit]
- Zhuang, R.; Feinberg, M.W. Regulatory T cells in ischemic cardiovascular injury and repair. J. Mol. Cell Cardiol. 2020, 147, 1–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boothby, I.C.; Cohen, J.N.; Rosenblum, M.D. Regulatory T cells in skin injury: At the crossroads of tolerance and tissue repair. Sci. Immunol. 2020, 5, eaaz9631. [Google Scholar] [CrossRef] [Scilit]
- Skórka, P.; Piotrowski, J.; Bakinowska, E.; Kiełbowski, K.; Pawlik, A. The Role of Signaling Pathways in Myocardial Fibrosis in Hypertrophic Cardiomyopathy. Rev. Cardiovasc. Med. 2025, 26, 27152. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nollet, E.E.; Schuldt, M.; Sequeira, V.; Binek, A.; Pham, T.V.; Schoonvelde, S.A.C.; Jansen, M.; Schomakers, B.V.; van Weeghel, M.; Vaz, F.M.; et al. Integrating Clinical Phenotype with Multiomics Analyses of Human Cardiac Tissue Unveils Divergent Metabolic Remodeling in Genotype-Positive and Genotype-Negative Patients with Hypertrophic Cardiomyopathy. Circ. Genom. Precis. Med. 2024, 17, e004369. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.J.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMA-ScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit]
- Peters, M.D.J.; Marnie, C.; Tricco, A.C.; Pollock, D.; Munn, Z.; Alexander, L.; McInerney, P.; Godfrey, C.M.; Khalil, H. Updated methodological guidance for the conduct of scoping reviews. JBI Evid. Synth. 2020, 18, 2119–2126. [Google Scholar] [CrossRef] [Scilit]
- Shea, B.J.; Reeves, B.C.; Wells, G.; Thuku, M.; Hamel, C.; Moran, J.; Moher, D.; Tugwell, P.; Welch, V.; Kristjansson, E.; et al. AMSTAR 2: A critical appraisal tool for systematic reviews that include randomised or non-randomised studies of healthcare interventions, or both. BMJ 2017, 358, j4008. [Google Scholar] [CrossRef] [Scilit]
- Zhang, Y.; Zhao, J.; Jin, Q.; Zhuang, L. Transcriptomic Analyses and Experimental Validation Identified Immune-Related lncRNA-mRNA Pair MIR210HG-BPIFC Regulating the Progression of Hypertrophic Cardiomyopathy. Int. J. Mol. Sci. 2024, 25, 2816. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.; Zhang, W.; Dai, Y.; Chen, K. Identification and verification of IGFBP3 and YTHDC1 as biomarkers associated with immune infiltration and mitophagy in hypertrophic cardiomyopathy. Front. Genet. 2022, 13, 986995. [Google Scholar] [CrossRef] [Scilit]
- Hou, C.; Fei, S.; Jia, F. Necroptosis and immune infiltration in hypertrophic cardiomyopathy: Novel insights from bioinformatics analyses. Front. Cardiovasc. Med. 2024, 11, 1293786. [Google Scholar] [CrossRef] [Scilit]
- Zhang, X.Z.; Zhang, S.; Tang, T.T.; Cheng, X. Bioinformatics and Immune Infiltration Analyses Reveal the Key Pathway and Immune Cells in the Pathogenesis of Hypertrophic Cardiomyopathy. Front. Cardiovasc. Med. 2021, 8, 696321. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, S.; Ud Din, I.; Sadiq, F.M.; Abdel-Maksoud, M.A.; Haris, M.; Mubarak, A.; Farrag, M.A.; Alghamdi, S.; Almekhlafi, S.; Akram, M.; et al. Dysfunctional network of hub genes in hypertrophic cardiomyopathy patients. Am. J. Transl. Res. 2022, 14, 8918–8933. [Google Scholar] [PubMed]
- Gong, J.; Shi, B.; Yang, P.; Khan, A.; Xiong, T.; Li, Z. Unveiling Immune Infiltration Characterizing Genes in Hypertrophic Cardiomyopathy Through Transcriptomics and Bioinformatics. J. Inflamm. Res. 2024, 17, 3079–3092. [Google Scholar] [CrossRef] [Scilit]
- Cai, S.; Jin, T.; Liu, M.; Dai, Q. Identification of biomarkers associated with energy metabolism in hypertrophic cardiomyopathy and exploration of potential mechanisms of roles. Front. Cardiovasc. Med. 2025, 12, 1546865. [Google Scholar] [CrossRef] [Scilit]
- You, H.; Dong, M. Prediction of diagnostic gene biomarkers for hypertrophic cardiomyopathy by integrated machine learning. J. Int. Med. Res. 2023, 51, 03000605231213781. [Google Scholar] [CrossRef] [Scilit]
- Zhuo, J.; Ding, D.; Fan, M.; Lu, W.; Lu, X.; Yao, L.; Sheng, H. Identification of marker genes associated with oxidative stress in hypertrophic cardiomyopathy using bioinformatics analysis and experimental validation. Sci. Rep. 2025, 15, 28817. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shintani, Y.; Nakayama, T.; Masaki, A.; Yokoi, M.; Wakami, K.; Ito, T.; Goto, T.; Sugiura, T.; Inagaki, H.; Seo, Y. Clinical impact of the pathological quantification of myocardial fibrosis and infiltrating T lymphocytes using an endomyocardial biopsy in patients with hypertrophic cardiomyopathy. Int. J. Cardiol. 2022, 362, 110–117. [Google Scholar] [CrossRef] [Scilit]
- Laird, J.; Perera, G.; Batorsky, R.; Wang, H.; Arkun, K.; Chin, M.T. Spatial Transcriptomic Analysis of Focal and Normal Areas of Myocyte Disarray in Human Hypertrophic Cardiomyopathy. Int. J. Mol. Sci. 2023, 24, 12625. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.J.; Singh, K.; Lokman, A.B.; Deng, S.; Sunitha, B.; Coelho Lima, J., Jr.; Beglov, J.; Kelly, M.; Blease, A.; Fung, J.C.K.; et al. Regulatory T cells attenuate chronic inflammation and cardiac fibrosis in hypertrophic cardiomyopathy. Sci. Transl. Med. 2025, 17, eadq3516. [Google Scholar] [CrossRef] [Scilit]
- He, F.; Pi, Q.; Yang, J.; Wan, M.; Yu, J.; Yang, D.; Guo, Y.; Li, X. A causal association between immune cells and hypertrophic cardiomyopathy: A bidirectional Mendelian randomization study. Genes. Dis. 2025, 12, 101539. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cao, X.; Wang, H.; Hu, Z.; Ma, W.; Ding, P.; Sun, H.; Guo, X. Interplay of ST2 downregulation and inflammatory dysregulation in hypertrophic cardiomyopathy pathogenesis. Front. Cardiovasc. Med. 2025, 12, 1511415. [Google Scholar] [CrossRef] [Scilit]
- Marketou, M.E.; Parthenakis, F.I.; Kalyva, A.; Pontikoglou, C.; Maragkoudakis, S.; Kontaraki, J.E.; Zacharis, E.A.; Patrianakos, A.; Chlouverakis, G.; Papadaki, H.A.; et al. Circulating mesenchymal stem cells in patients with hypertrophic cardiomyopathy. Cardiovasc. Pathol. 2015, 24, 149–153. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Helms, A.S.; Alvarado, F.J.; Yob, J.; Tang, V.T.; Pagani, F.; Russell, M.W.; Valdivia, H.H.; Day, S.M. Genotype-Dependent and -Independent Calcium Signaling Dysregulation in Human Hypertrophic Cardiomyopathy. Circulation 2016, 134, 1738–1748. [Google Scholar] [CrossRef] [Scilit]
- Fang, L.; Beale, A.; Ellims, A.H.; Moore, X.L.; Ling, L.H.; Taylor, A.J.; Chin-Dusting, J.; Dart, A.M. Associations between fibrocytes and postcontrast myocardial T1 times in hypertrophic cardiomyopathy. J. Am. Heart Assoc. 2013, 2, e000270. [Google Scholar] [CrossRef] [Scilit]
- Kalyva, A.; Marketou, M.E.; Parthenakis, F.I.; Pontikoglou, C.; Kontaraki, J.E.; Maragkoudakis, S.; Petousis, S.; Chlouverakis, G.; Papadaki, H.A.; Vardas, P.E. Endothelial progenitor cells as markers of severity in hypertrophic cardiomyopathy. Eur. J. Heart Fail. 2016, 18, 179–184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tanaka, A.; Yuasa, S.; Mearini, G.; Egashira, T.; Seki, T.; Kodaira, M.; Kusumoto, D.; Kuroda, Y.; Okata, S.; Suzuki, T.; et al. Endothelin-1 induces myofibrillar disarray and contractile vector variability in hypertrophic cardiomyopathy-induced pluripotent stem cell-derived cardiomyocytes. J. Am. Heart Assoc. 2014, 3, e001263. [Google Scholar] [CrossRef] [Scilit]
- Ali, S.A.; Perera, G.; Laird, J.; Batorsky, R.; Maron, M.S.; Rivas, V.N.; Stern, J.A.; Harris, S.; Chin, M.T. Single Cell Transcriptomic Profiling of MYBPC3-Associated Hypertrophic Cardiomyopathy Across Species Reveals Conservation of Biological Process but Not Gene Expression. J. Am. Heart Assoc. 2025, 14, e035780. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ellims, A.H.; Iles, L.M.; Ling, L.H.; Hare, J.L.; Kaye, D.M.; Taylor, A.J. Diffuse myocardial fibrosis in hypertrophic cardiomyopathy can be identified by cardiovascular magnetic resonance and is associated with left ventricular diastolic dysfunction. J. Cardiovasc. Magn. Reson. 2012, 14, 76. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lu, Y.; Xue, Z.K.; Gao, W.; Bai, G.; Zhang, X.; Chen, K.Y.; Li, G. Microcirculatory dysfunction in hypertrophic cardiomyopathy with chest pain assessed by angiography-derived microcirculatory resistance. Sci. Rep. 2024, 14, 16977. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rehan, R.; Yong, A.; Ng, M.; Weaver, J.; Puranik, R. Coronary microvascular dysfunction: A review of recent progress and clinical implications. Front. Cardiovasc. Med. 2023, 10, 1111721. [Google Scholar] [CrossRef] [Scilit]
- Pelliccia, F.; Cecchi, F.; Olivotto, I.; Camici, P.G. Microvascular Dysfunction in Hypertrophic Cardiomyopathy. J. Clin. Med. 2022, 11, 6560. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.