


Simple Summary
This article reviews the impact of glioma diagnoses and treatments on patients’ quality of life. Because gliomas affect the brain, they can influence physical, cognitive, emotional, and social functioning in ways that extend beyond traditional clinical outcomes. Using the World Health Organization’s health-related quality-of-life framework, this review examines the multiple domains of life affected by gliomas and highlights opportunities to improve patient-centered outcomes through clinical care, care delivery, and broader health system and policy approaches.
Abstract
Health-related quality of life is a multidimensional concept used to describe one’s well-being in relation to their disease. Individuals with gliomas, the most commonly occurring malignant primary brain tumor, experience a multitude of symptoms due to their disease and treatments. Using the World Health Organization’s health-related quality-of-life model, we review the impact of this disease across each domain of the model. Furthermore, we summarize known sociodemographic disparities that contribute to inequities in health-related quality of life and highlight areas that require further investigation. Finally, we discuss potential areas for innovation to better address current gaps and inequities affecting the health-related quality of life of individuals with gliomas.
1. Introduction
Gliomas are the most common malignant primary brain tumors, with an estimated average age-adjusted annual incidence of 6 cases per 100,000 individuals [1]. Gliomas are classified into oligodendrogliomas, astrocytomas, and glioblastomas, with glioblastoma representing the most common subtype and having the poorest prognosis [1]. Prognosis varies widely across gliomas and depends on tumor type, grade, and molecular markers [2]. Individuals with lower-grade gliomas and/or favorable tumor markers such as isocitrate dehydrogenase (IDH) mutations may survive for years or decades, while those with glioblastoma, a high-grade glioma (HGG) that is IDH-wildtype, have a median overall survival of 15 months despite standard of care therapy [2]. Health outcomes for individuals with gliomas are also influenced by social determinants of health (SDOH), including economic, structural, and social conditions that shape access to and quality of care, which contribute to observed health disparities [3,4]. For example, patients who are uninsured or identify as Black or Latino are less likely to receive gross total resection, chemotherapy, or radiation therapy, treatments that have been shown to prolong overall survival in gliomas [5,6].
Individuals with gliomas experience a variety of presenting symptoms that depend on tumor location, with most tumors arising in the frontal, parietal, or temporal lobe [2]. Common presentations include headaches from mass effect or increased intracranial pressure, seizures, and focal neurological deficits, such as language impairment, motor or sensory deficits, or difficulties with cognitive functioning [2]. While surgical resection and anti-neoplastic therapy may alleviate symptoms, many individuals experience persistent or chronic symptoms requiring ongoing supportive management. Despite best supportive practices, individuals with gliomas report significant impairments in quality of life across physical, cognitive, and psychosocial domains, irrespective of tumor [7].
Health-related quality of life (HRQoL) is a subjective, multidimensional concept that captures an individual’s perception of their physical, psychological, and social well-being in the context of disease [8]. While HRQoL was historically less emphasized in clinical trials, advances in measurement tools, the emergence of more effective treatments, and the transformation of many diseases into more manageable or chronic conditions have led to its increased and appropriate incorporation as a patient-centered endpoint for evaluating the net benefit of therapies [9,10]. In response, the World Health Organization (WHO) developed a conceptual framework to standardize the assessment of HRQoL across diseases and cultural contexts. Within the WHO model, core domains of HRQoL include physical health, level of independence, psychological well-being, social relationships, environmental factors, and spirituality, religion, or personal beliefs (Table 1). Accordingly, this review applies the WHO HRQoL framework to examine quality of life and health disparities among individuals with gliomas.
Table 1.
A table summarizing the six domains of the World Health Organization’s (WHO) quality-of-life (QOL) model with contributing factors listed under each domain. This is an adaptation of the original work “WHOQOL User Manual.” Geneva: World Health Organization (WHO); 2012. License: CC BY-NC-SA 3.0 IGO.
2. Health-Related Quality of Life Among Individuals with Gliomas
2.1. Physical Capacity
Physical capacity is a core domain of HRQoL, reflecting an individual’s ability to engage in daily activities, which may be limited by pain, discomfort, fatigue, or impaired rest related to disease or its treatment [11]. More than 50% of individuals with gliomas experience pain or discomfort, most commonly headaches related to increased intracranial pressure or mass effect. These headaches are routinely managed with surgical resection or medications to reduce peri-tumoral edema, such as steroids or bevacizumab, a monoclonal antibody targeting vascular endothelial growth factor (VEGF). In other areas of neuro-oncology, studies have documented disparities in the recognition and management of symptom burden. For example, research shows that among individuals with brain metastases, racial and socioeconomic factors influence the use of supportive medications, including analgesics for headache [12]. However, it remains unclear whether similar disparities exist in the recognition and management of symptoms among individuals with gliomas. Notably, evidence suggests that Latino individuals are more likely to report unmanaged pain and sensory symptoms [13].
Studies have consistently documented racial and ethnic differences in pain management in other cancer populations [14]. Black patients are less likely to be prescribed opioids or referred to palliative care or hospice services and are more likely to report poorer pain control and lower HRQoL [15]. Within glioma populations, prior research has demonstrated racial, ethnic, age, and socioeconomic disparities in access to treatment, including differences in receipt of surgery, radiation therapy, and chemotherapy, suggesting that structural inequities in care delivery may also extend to supportive and symptom-directed [6,16,17]. Although disparities in pain management have not yet been consistently demonstrated among individuals with gliomas, these findings underscore the importance of standardized, proactive approaches to symptom management. One study demonstrates disparities in hospice enrollment, with non-White patients, individuals living in rural areas, men, and those with lower educational attainment experiencing lower hospice utilization [18]. Accordingly, we recommend routine consideration of palliative care referral for all patients with uncontrolled pain, as a strategy to improve symptom control and reduce the risk of inequities in care.
Fatigue, defined as tiredness, weakness, and lack of energy, is widely prevalent among individuals with gliomas, with estimates ranging from 20 to 76% [19,20]. The etiology of fatigue in this population is considered multifactorial, with contributing factors including tumor-related characteristics, comorbid conditions, psychological symptoms, and treatment-related side effects [21]. Contrary to common assumptions, studies evaluating tumor type and treatment modalities have not consistently identified differences in the prevalence or severity of fatigue [22]. These findings are corroborated across other cancer types and their related treatments [23]. Available evidence suggests that socioeconomic disadvantage, rather than tumor- or treatment-related factors, may be associated with worse patient-reported fatigue in individuals with glioma [24].
Studies evaluating associations between fatigue and clinical factors such as tumor location, use of antiepileptic drugs, and sex have yielded conflicting results [19,23,25]. While sedation is a well-known side effect of antiepileptic drugs, small studies evaluating fatigue among individuals with gliomas have yet to unequivocally establish an association between antiepileptic drugs and fatigue [19,23]. In contrast, psychosocial and functional factors, including depression, baseline preoperative fatigue, and physical functioning, have been more consistently identified as predictors of postoperative fatigue [23]. One proposed mechanism for fatigue in neurologic conditions is the increased cognitive or physical effort required to accomplish everyday tasks [26]. However, adults with gliomas appear to experience fatigue independently of neurocognitive impairment [27].
Efforts to mitigate fatigue among individuals with gliomas have had varying success. The National Comprehensive Cancer Network (NCCN) guidelines recommend evaluating for treatable contributing factors such as pain, emotional distress, physical deconditioning, sleep disturbances, and medication side effects [21]. After addressing contributing factors, both nonpharmacologic and pharmacologic interventions may be considered [21]. Regular physical activity is one nonpharmacologic strategy that has been associated with reductions in fatigue among individuals with gliomas [28,29]. However, disparities in the built environment may limit the feasibility of exercise for individuals from lower socioeconomic or marginalized communities, including reduced access to parks, green spaces, and fitness facilities, as well as financial barriers associated with gym membership and safe recreational spaces [30,31]. Meanwhile, pharmacologic interventions such as the use of armodafinil, a psychostimulant, have not been found to provide a meaningful benefit [32]. Similarly, trials of methylphenidate in individuals with ADHD have not shown consistent efficacy [33]. However, the NCCN recommendation for the management of fatigue is to trial a psychostimulant after addressing other contributing factors [21].
2.2. Psychological
Psychological factors influencing HRQoL include mood, self-perception, and cognition. A chief concern among individuals with gliomas is neurocognitive dysfunction, which commonly manifests as word-finding difficulties, short-term memory impairment, and difficulty completing complex tasks [34]. While radiation therapy can contribute to the development of cognitive changes, studies reveal that individuals with gliomas experience neurocognitive dysfunction independently of radiation exposure [35]. In one study using standardized neuropsychological testing, 74% of individuals with gliomas exhibited clinically significant impairment in at least one cognitive domain [34]. A meta-analysis evaluating cognitive impairment among individuals with gliomas revealed greater rates of cognitive impairment for high-grade gliomas compared to low-grade gliomas, affecting 68.9% and 31.1% of individuals, respectively [36]. Evaluation of sociodemographic factors suggests an association between cognitive impairment and lower educational achievement and non-White racial background [37]. However, more in-depth analyses of cognitive dysfunction are often limited by a heterogeneity of cognitive testing and a lack of sociodemographic diversity among participants.
Another common detriment to HRQoL for individuals with gliomas is mood disturbance. Studies indicate that 38–48% of individuals experience clinically significant symptoms of anxiety and/or depression during their disease [38,39]. These psychological stressors may be further influenced by treatment-related changes in physical appearance such as steroid-related weight changes, alopecia, and surgical scars. While sufficient data are not available to evaluate for racial or ethnic disparities among individuals with gliomas and depression, higher rates of depression have been observed among Black individuals with other cancers [40,41]. Additionally, Black individuals are less likely to be prescribed antidepressants [40]. Research demonstrates high rates of depressive symptoms in individuals with gliomas and identifies socioeconomic factors, including lower income and related sociodemographic variables, as risk factors for depression in this population. For example, a cross-sectional study of individuals with glioma found that lower household income, marital status, and sleep disturbances were independently associated with depression symptoms [42]. Furthermore, analyses of socioeconomic deprivation in primary malignant brain tumors show that greater deprivation is associated with worse emotional distress, including depression [24]. These findings parallel the broader literature on cancer survivorship, showing that social determinants and healthcare access disparities can affect mental health outcomes [43,44,45].
Other factors associated with mood disturbances in individuals with gliomas include female sex and a history of psychiatric illness [39,46]. Consistent with neuroanatomic vulnerability, individuals with gliomas involving their limbic system experience higher rates of severe depressive symptoms [47]. Evaluation of depression, fatigue, emotional distress, and existential problems among individuals with gliomas revealed that depressive symptoms emerged as the strongest independent predictor of HRQoL [38]. Despite the strong relationship between mood disturbances and HRQoL, there is no interrelationship between mood disorders and neurocognitive symptoms [48]. This dissociation emphasizes the importance of independent screening of psychological symptoms and cognitive impairment in both clinical care and clinical trials, rather than assuming overlap between these domains [48].
2.3. Level of Independence
Level of independence refers to an individual’s ability to perform activities of daily living (ADLs) and instrumental activities of daily living (IADLs) [49]. ADLs and IADLs include self-care, grooming, financial management, medication management, and employment. Given the central importance of maintaining independence, several functional measures, most notably the Karnofsky Performance Scale (KPS), were developed to assess functional status longitudinally in individuals with brain tumors [50,51]. Importantly, significant inter-rater variability exists among clinicians when measuring KPS among individuals with brain tumors [52]. Emerging evidence suggests that clinician-assigned performance status measures, including the Karnofsky Performance Scale (KPS), may be subject to bias, with Black individuals more likely to be rated as having lower performance status [53]. Such differences may influence treatment recommendations and eligibility for clinical trials, potentially contributing to the lack of diversity observed in glioma clinical [54]. In response to concerns about bias in clinical assessment and decision-making, the Society for Neuro-Oncology has emphasized the importance of bias-mitigation strategies, including the use of “nudges”—behavioral-economics-informed interventions designed to promote more equitable and consistent clinical decision-making [55].
Despite variability in KPS measurement, multiple studies have consistently found that functional independence declines with each tumor [56,57]. Consequently, innovations in glioma treatment have increasingly focused on delaying disease progression and preserving or restoring independence at tumor recurrence. An example of success in surgical innovation to preserve independence is the use of awake craniotomies to safely resect tumors near eloquent cortex [58]. Similarly, over half of individuals receiving chemotherapy for treatment of glioma recurrence experience stability or improvement in several measures of HRQOL, including physical function [59]. Unfortunately, significant disparities in access to high-volume medical centers with expertise in awake craniotomies and brain tumor care exist [60]. Individuals who identify as Latino, are uninsured, or come from a low-income household are less likely to receive care at a high-volume medical center [60], raising concern for disparities in functional outcomes related to these sociodemographic factors.
Employability represents another key metric of independence and is substantially affected among individuals diagnosed with gliomas. Return-to-work rates vary by tumor grade, with approximately half of individuals with low-grade gliomas returning to work after diagnosis compared to one-third of individuals with high-grade [61,62]. To date, limited data exist evaluating racial or ethnic disparities in return-to-work rates among individuals with gliomas. However, studies in other cancer populations have found that Black and Latino patients are less often able to return to work after a cancer diagnosis [63,64]. Additionally, a European population-based study found that individuals from lower socioeconomic backgrounds experience lower overall survival compared to individuals from higher socioeconomic backgrounds [65]. Although the mechanisms underlying this association are multifactorial, in the United States, the link between employment and health insurance may further amplify these disparities [66]. Therefore, employability serves a key role not only in HRQoL but also in associated health outcomes. The phenomenon of “job lock,” whereby patients or caregivers remain employed to maintain health insurance coverage, may exacerbate psychosocial stress and financial toxicity, particularly in the context of serious illness [67,68].
A greater extent of tumor resection predicts successful return to work [69]. Meanwhile, the development of acute postoperative motor, gait, or cognitive deficits reduce the likelihood of returning to work [62]. Even when individuals with low-grade gliomas return to work, many experience ongoing occupational difficulties related to their illness [61]. Limitations include cognitive difficulties such as concentration and speed of task completion [61]. These findings underscore the need for further innovation in glioma treatments and cognitive rehabilitation to help individuals with gliomas regain their independence and experience greater HRQoL.
2.4. Social Relationships
The ability to maintain and nourish social relationships is another key metric of HRQoL. Individuals with gliomas are particularly susceptible to disruptions in social relationships, given the cognitive, language, and communication impairments that may result from their disease or related treatments [70]. Poor social relationships and social isolation have been associated with worsening neurologic illness and functional decline, underscoring their importance in neurologic health more broadly [70,71]. Quantitative assessments of social networks and social isolation for individuals with gliomas remain limited, although recent pilot studies have begun to explore social network structure in this population [70]. In a small study of nine individuals with glioblastoma, 77% reported dissatisfaction with personal relationships. Similarly, a qualitative study exploring the challenges faced by individuals with glioblastoma identified social isolation as a prominent subtheme, with participants describing difficulty engaging in conversations due to cognitive or language changes, followed by progressive withdrawal from social circles and community life [72].
While research regarding racial disparities in social relationships for individuals with gliomas has yet to be performed, racial disparities have been observed among individuals with breast cancers. Notably, social network size, network density, and practical support have been associated with increased 5-year survival among individuals with breast cancers [73]. However, Black individuals with breast cancers were found to have smaller networks, lower network density, and greater geographical separation from support compared to their White counterparts [73]. Similar patterns have been observed in other areas of medicine; for example, strong social networks were identified as a protective factor during the COVID-19 pandemic, whereas limited access to social support among older adults and marginalized populations was thought to contribute, in part, to observed disparities in outcomes [74]. Given the substantial caregiving needs and social challenges faced by individuals with gliomas, further investigation into disparities in social networks would be helpful to inform future interventions.
Another important dimension of social relationships is sexual health. Sexual health is associated with better overall health, well-being, and enjoyment of life [75,76,77]. Meanwhile, sexual dysfunction can negatively affect interpersonal relationships and psychosocial functioning [77,78]. Among individuals with low-grade gliomas who are not receiving adjuvant therapy, 44–63% report sexual dysfunction, most commonly related to sexual drive and satisfaction [77,79,80]. As a consequence of decreased sexual arousal, sexual desire, and orgasms, women report lower levels of social well-being and quality of relationships [77,80]. Despite the high prevalence of sexual health concerns, screening and discussion of sexual dysfunction remain uncommon in neuro-oncology care, with 59% of neurosurgeons reporting never having discussed sexual health with their patients [81]. Routine assessment of sexual health should be performed among individuals with gliomas, particularly given the availability of effective interventions targeting sexual desire and satisfaction, including pharmacologic therapies and sexual aids [82,83].
2.5. Environment
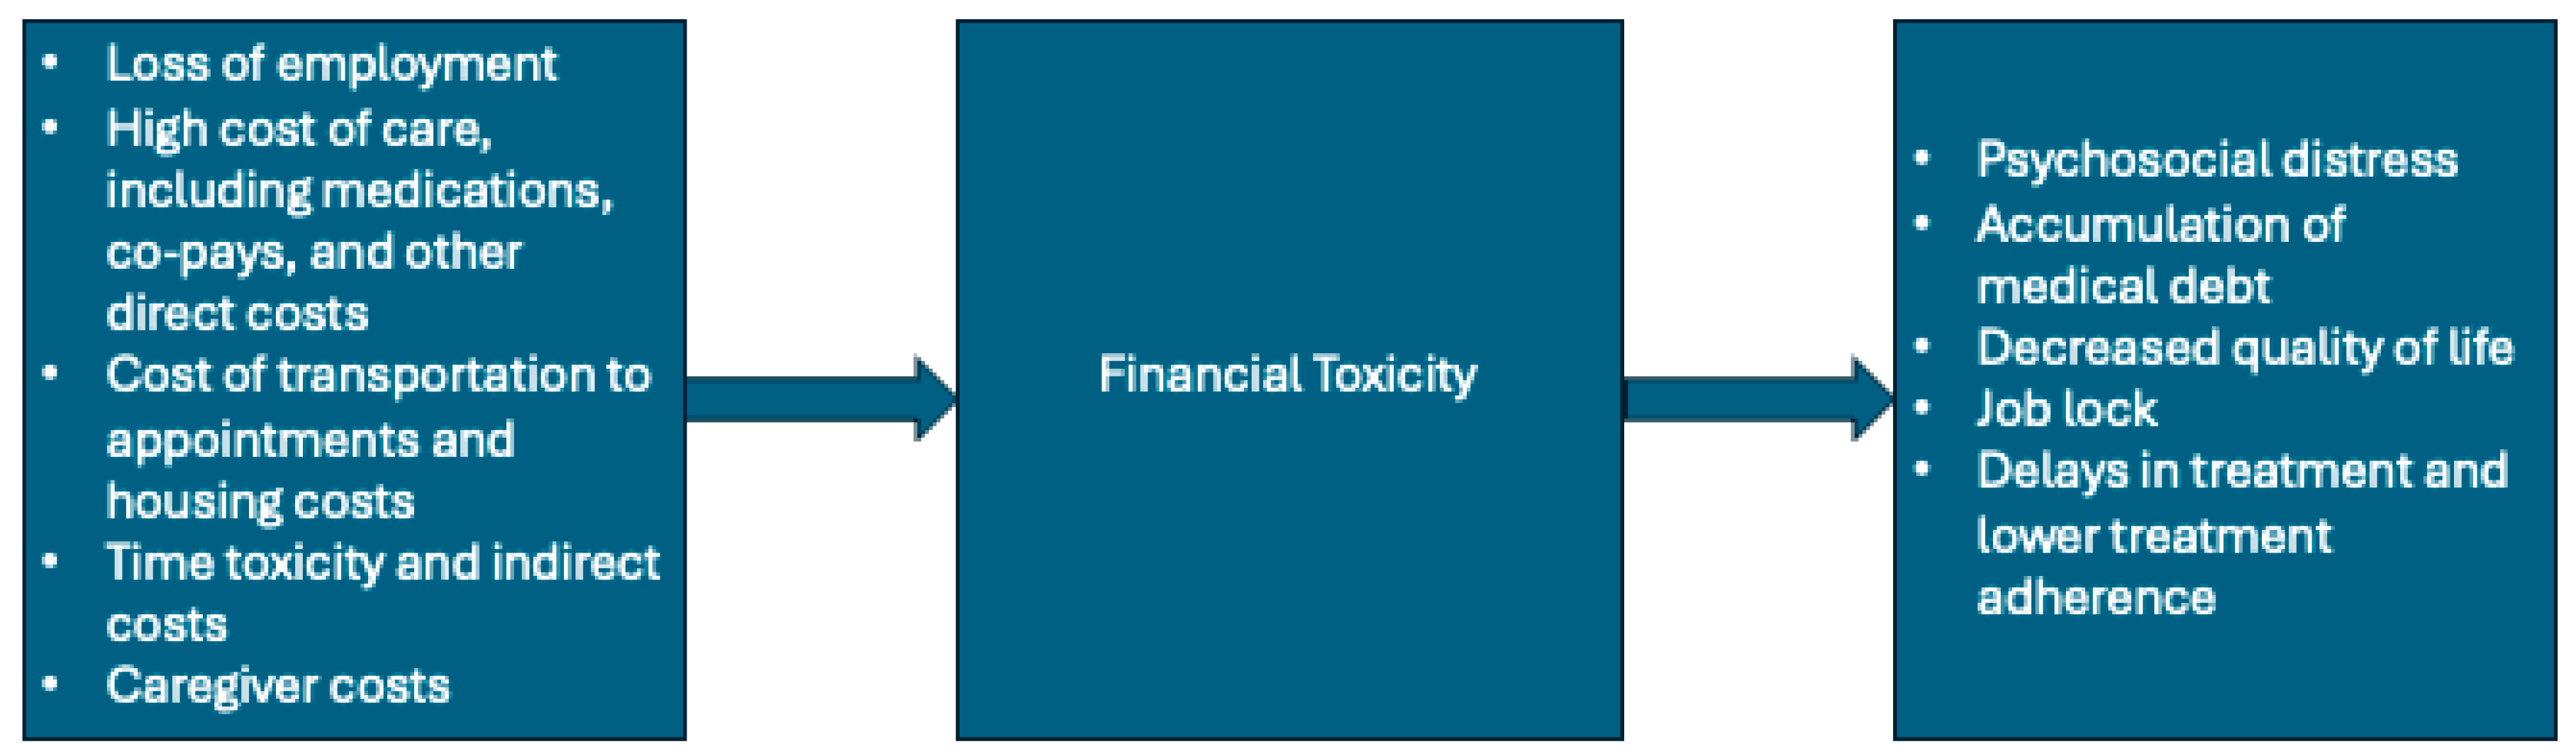
Environmental factors that influence one’s HRQoL include financial stability, physical safety, transportation, access to healthcare, and the ability to engage in leisurely activities. For individuals diagnosed with gliomas, financial toxicity represents a major environmental determinant of diminished quality of life. Financial toxicity encompasses the negative impact and economic burden of medical care, including but not limited to medical debt, loss of income, and the associated psychological distress [84,85]. Individuals with cancer often incur high out-of-pocket costs, many of which are not fully covered by insurance [85]. For example, one study found that 34% of individuals with glioblastoma and 54% of their caregivers spent more than $271 USD out-of-pocket per month on treatment [86]. A separate analysis reported that the mean per-patient per-month cost for individual with glioblastoma was $18,053 USD when including both in- and outpatient costs [87,88]. Even when patients have insurance coverage, co-pays for treatment can be substantial, ranging from $0–100 USD to >$1000 USD per chemotherapy prescription [89]. As neuro-oncology treatment paradigms evolve, including the introduction of targeted therapies such as isocitrate dehydrogenase (IDH) inhibitors, overall treatment costs may increase and be partially passed on to patients. With total annual costs that can exceed $300,000 USD, a portion of these expenses may be borne directly by patients through medication co-payments or indirectly through the healthcare system, potentially contributing to higher insurance premiums.
As a consequence of these cumulative costs, patients may acquire high medical debt across multiple points of care, including outpatient visits, which can force trade-offs between medical expenses and essential needs such as housing, food, and transportation [85,90]. Compounding these economic toxicities, individuals with gliomas face a high risk of unemployment or reduced work capacity due to disease-related disability, further limiting financial stability [84,85]. Additionally, these patients are at a high risk of transportation insecurity, which has been associated with missed appointments, treatment delays, and foregone cancer care, thereby exacerbating treatment inequities and ultimately overall survival [65,91]. Ultimately, limited financial resources can profoundly impair QoL and contribute to inequities in cancer treatment and outcomes (Figure 1).
Figure 1.
This figure summarizes the factors contributing to the development of financial toxicity and the repercussions of financial toxicity.
Another environmental challenge experienced by individuals with gliomas is the ability to participate in recreation and leisure activities, which may be limited by neurocognitive impairments related to disease or treatment. In addition to cognitive dysfunction, neurologic symptoms, including motor and sensory deficits, aphasia, seizures, and headaches, can interfere with occupational and leisure activities [85,92,93]. Low-grade gliomas are more likely to be epileptogenic, and as a result, individuals with gliomas are more likely to avoid activities that they previously enjoyed because of seizure risk [92,94]. One study found that nearly half (48%) of all individuals with gliomas surveyed reported moderate–severe activity-related interference, while another found that poor physical health among individuals with glioblastoma led to fewer outings, and, in turn, lower subjective well-being [56,95]. In sum, these findings highlight substantial barriers to participation in leisure activities and skill acquisition, which negatively impact overall HRQoL among individuals with glioma.
Sociodemographic factors further shape environmental influences on QoL. Individuals with gliomas who grew up in or currently reside in rural areas are more likely to experience moderate to severe activity interference related to their disease [56]. These individuals also tend to travel longer distances to receive care, resulting in significant time toxicity, defined as the time spent receiving medical care that displaces time otherwise available for work, caregiving, or leisure activities [91,96,97]. In urban settings, individuals from racial and ethnic minority groups, those with lower median household income, and individuals with public insurance are more likely to seek care through emergency departments, sometimes presenting with more advanced disease, due to barriers to continuity of outpatient care [98]. Addressing these environmental and structural disparities in care will require large-scale, system-level interventions to improve equitable access to care, treatment outcomes, and HRQoL [4].
2.6. Spirituality
Spirituality is defined as a personal quest for meaning and understanding in relation to existential questions about life and one’s connections to the sacred or transcendent [99,100]. While it is related to religiosity, spirituality is distinct in that religiosity emphasizes organized practices, beliefs, and worship [100]. Spirituality has been associated with more effective coping with chronic and serious illness, as well as improved cancer-related symptom control [101,102,103]. These associations are thought to underlie the positive relationship between spirituality and HRQOL [100]. Racial and ethnic differences in spirituality have been described among survivors of other cancers, with individuals who identify as Black or Latino reporting higher levels of meaning and peace, contributing to greater spiritual well-being [104]. Among individuals with gliomas, similar findings have been observed, with studies demonstrating a positive association between spirituality or religiosity and higher HRQoL, independent of performance status or tumor type [105]. Furthermore, individuals with glioblastoma who report higher spiritual well-being have also demonstrated greater resilience and longer survival [106]. Given the shortened life expectancy associated among individuals with gliomas, these findings emphasize the importance of acknowledging and supporting spirituality as part of comprehensive, patient-centered care throughout the disease course [105].
3. Discussion
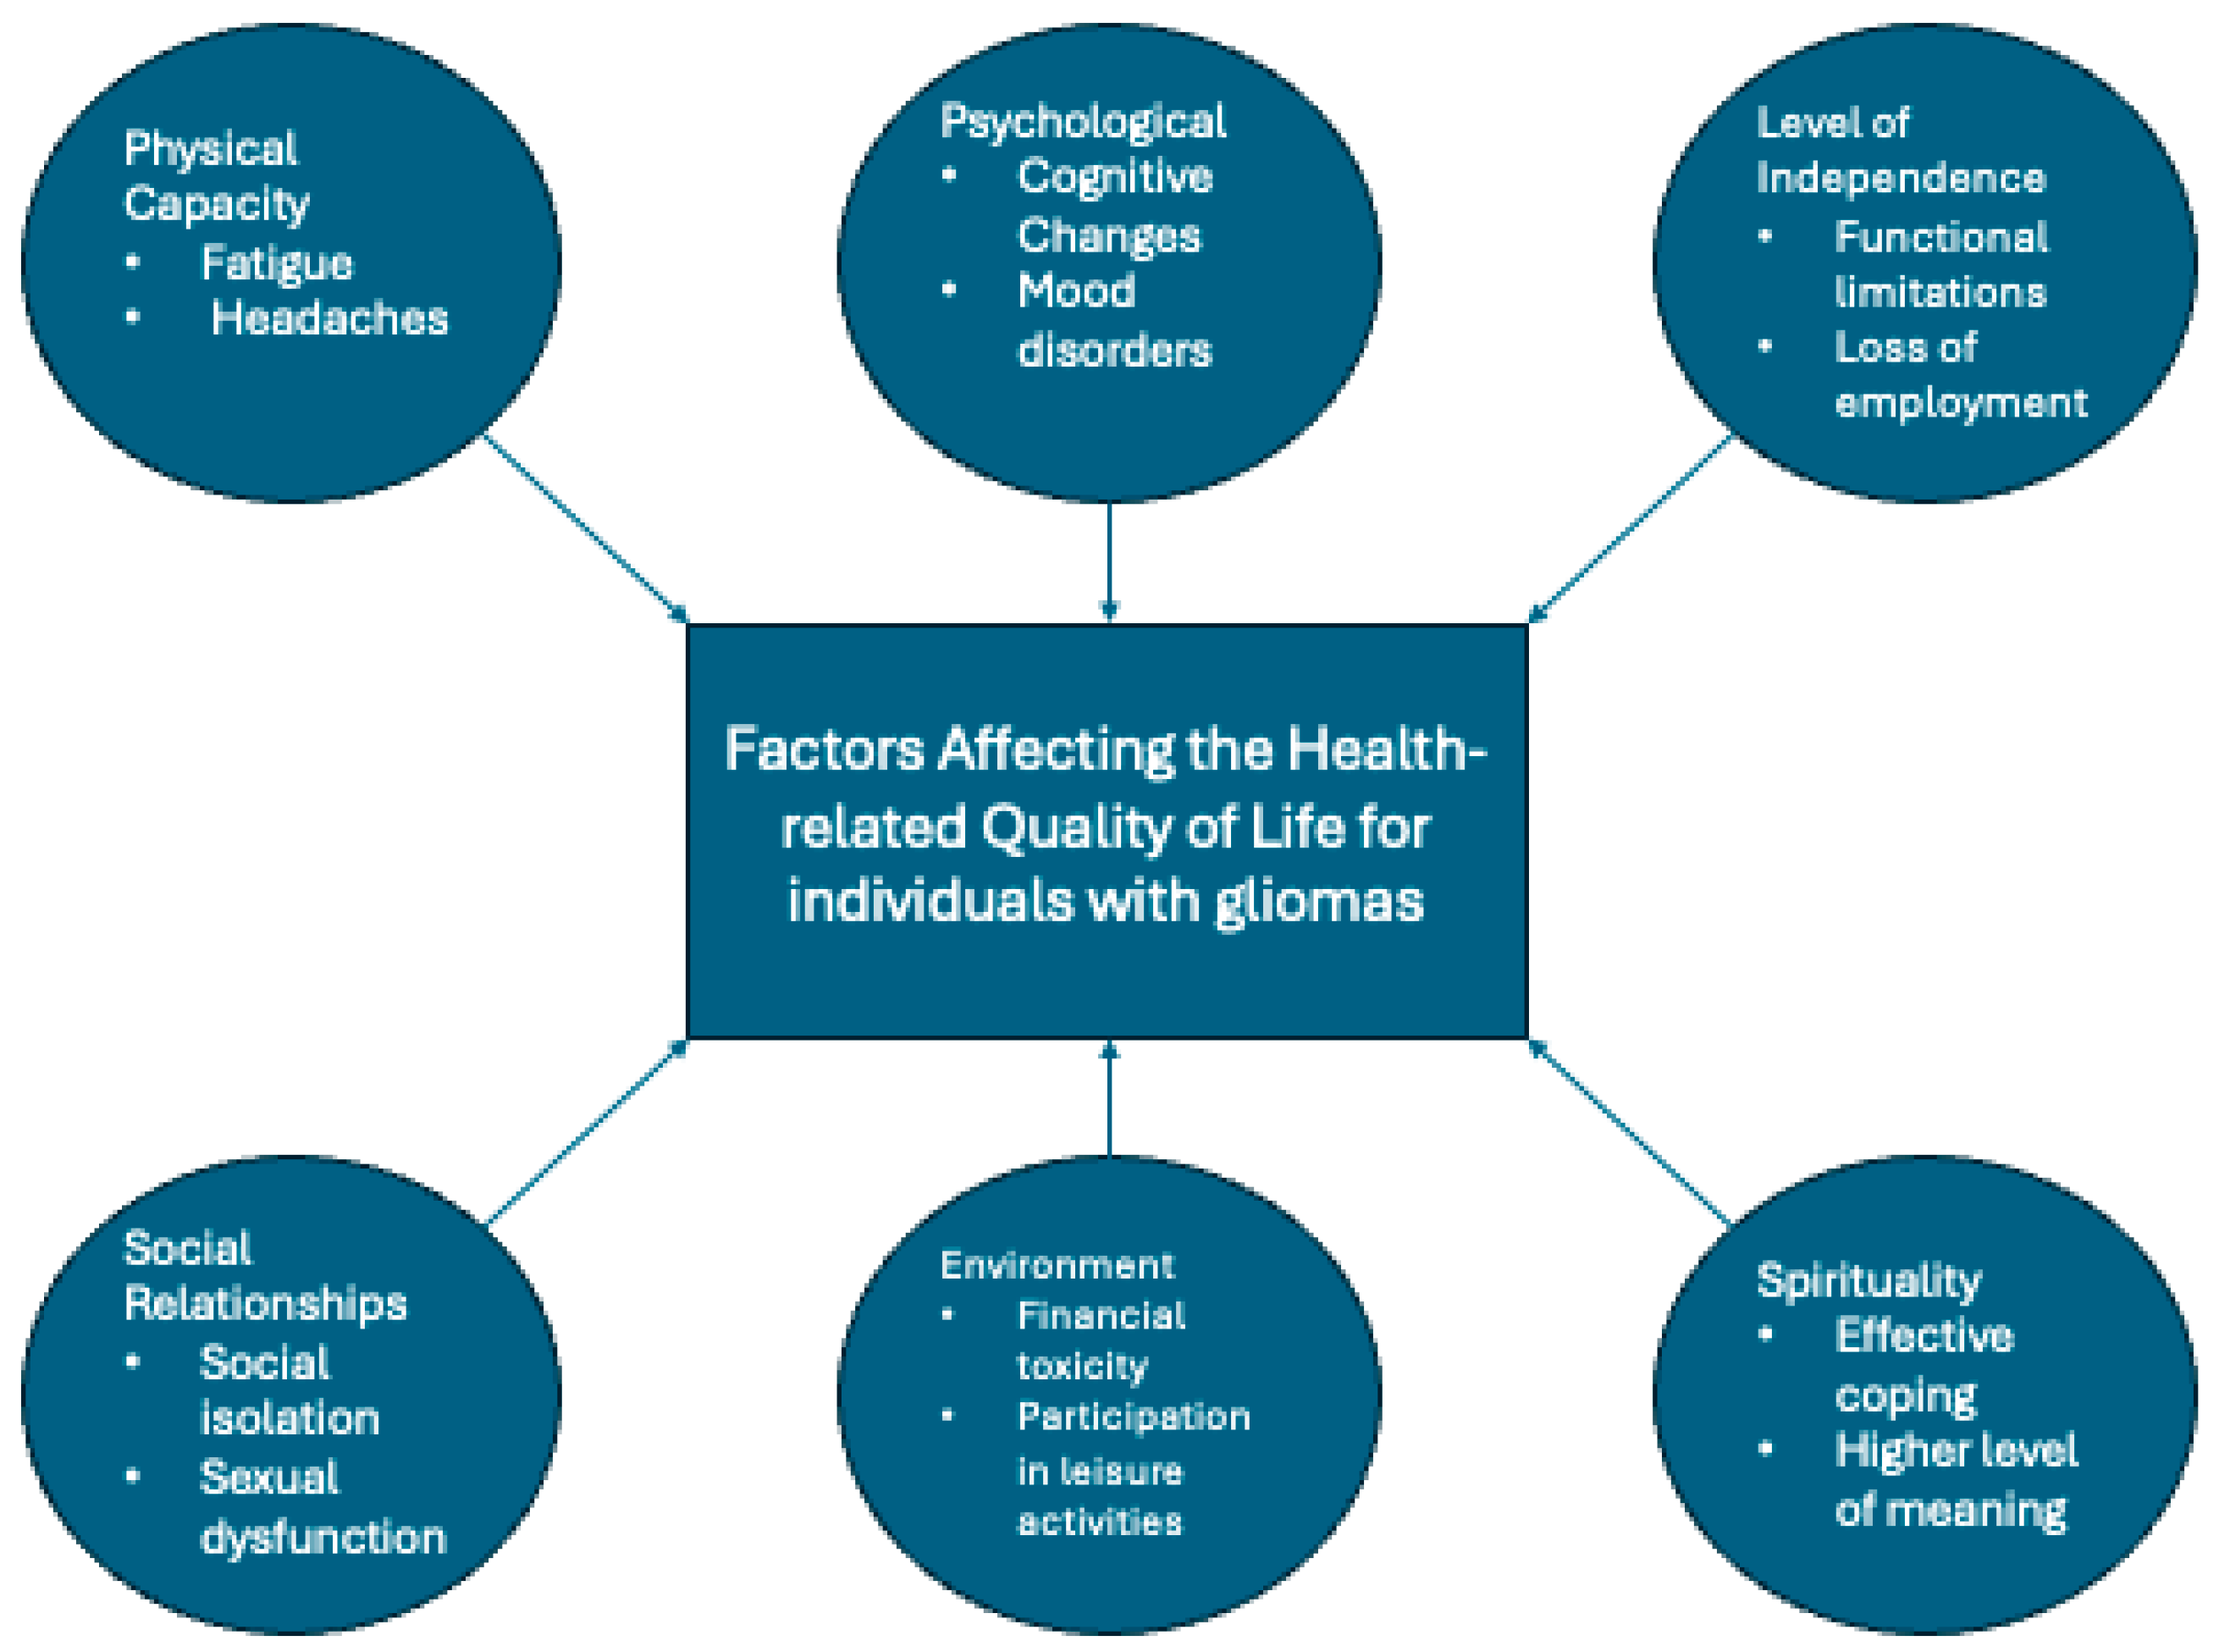
Gliomas affect individuals across all domains of HRQoL (Figure 2). The degree and nature of impact vary according to tumor grade, tumor location, and sociodemographic factors, with cognitive impairment, social isolation, financial toxicity, mood disturbances, and loss of independence emerging as key contributors to diminished HRQoL. Although these challenges are not unique to individuals with gliomas, addressing them requires targeted, equity-conscious interventions that account for the heterogeneity of patient experiences and the social determinants of health.
Figure 2.
A summary of the factors affecting the HRQoL among individuals with gliomas.
Several pragmatic opportunities exist to improve HRQoL in neuro-oncology care. Standardized, universal screening for common and impactful concerns, such as mood disturbances, financial hardship, and sexual health, followed by timely referral to appropriate specialists, may substantially improve patient well-being. Partnerships with physiatrists and physical therapy specialists also offer important opportunities to develop tailored rehabilitation programs to help restore and maintain independence and support patients’ individual goals. Additionally, expanded use of virtual care may improve access to specialized brain tumor centers for patients who face geographic, transportation, or mobility barriers.
Clinical trials and research represent another critical avenue for advancing understanding of HRQoL. Recent clinical trials, including those evaluating vorasidenib, have increasingly incorporated HRQoL and patient-reported outcomes as key outcomes alongside traditional clinical endpoints [107]. The European Organization for Research and Treatment of Cancer (EORTC) developed a validated HRQoL questionnaire specifically designed to assess the impact of tumors and treatments on patients’ well-being. Broader adoption of standardized instruments can facilitate cross-trial comparisons, inform clinical decision-making, and guide health policy [108]. Additionally, as clinical trials have historically lacked sociodemographic diversity, new guidance has emerged to improve recruitment of diverse participants [55]. Expanding participant diversity and routinely integrating HRQoL assessments into glioma trials will be essential to better characterize disparities and inform more equitable care.
Beyond traditional efficacy trials, pragmatic clinical trials and quality improvement initiatives will be essential for advancing HRQoL in neuro-oncology. Pragmatic trials are designed to evaluate interventions under real-world clinical conditions, emphasizing usual care settings, broad patient inclusion, and outcomes that are directly relevant to patients and health systems [109]. Such approaches allow evaluation of real-world interventions such as routine HRQoL screening, integrated supportive care, rehabilitation, and financial navigation within diverse care settings. Prioritizing pragmatic and implementation-focused research alongside randomized trials will be critical to translating therapeutic advances into meaningful improvements in HRQoL for individuals with gliomas and should be a central focus of the field moving forward.
Importantly, there are currently no widely adopted guidelines for the standardization of HRQoL measurement instruments in glioma research, highlighting an important opportunity for professional societies and research consortia to collaborate on the development and implementation of standardized, patient-centered assessment tools. For all the reasons outlined in this review, it is our belief that an invigorated focus on improving the HRQoL of individuals with gliomas is critical to unlocking the full benefit provided by any current and future treatments.
4. Conclusions
Gliomas impose a substantial and multifaceted burden on HRQoL that extends well beyond survival, affecting physical functioning, cognition, emotional well-being, social relationships, independence, environmental stability, and spirituality. While advances in surgical, medical, and targeted therapies have improved disease control for some individuals, these gains are often accompanied by persistent symptoms, functional limitations, and structural barriers that disproportionately affect socially and economically marginalized populations.
Improving HRQoL for individuals with gliomas will require moving beyond disease-directed treatment alone. Standardized screening for common quality-of-life challenges, integration of supportive and rehabilitative services, and intentional efforts to address financial, geographic, and structural barriers to care represent actionable opportunities to improve patient-centered outcomes. At the research level, broader incorporation of HRQoL and patient-reported outcomes into clinical trials, greater sociodemographic representation, and the development of standardized assessment tools are critical next steps.
Finally, prioritizing pragmatic clinical trials and quality improvement initiatives will be essential to translating therapeutic advances into meaningful improvements in daily functioning and well-being for individuals living with gliomas. An intentional, equity-focused emphasis on HRQoL should be a central goal of neuro-oncology care and research to ensure that progress in treatment is matched by progress in patients’ lived experience.
Author Contributions
M.A.P., D.C.R. and J.A.B. all contributed to the conception, research, writing, critical review, and preparation of this manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded in part through the NIH/NCI Cancer Center Support Grant P30 CA008748 (PI Vickers), K12 CA184746, and the Nicholls–Biondi Diversity Clinical Scientist Program at Memorial Sloan Kettering Cancer Center.
Institutional Review Board Statement
Not applicable.
Data Availability Statement
Not applicable.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Ostrom, Q.T.; Cote, D.J.; Ascha, M.; Kruchko, C.; Barnholtz-Sloan, J.S. Adult Glioma Incidence and Survival by Race or Ethnicity in the United States From 2000 to 2014. JAMA Oncol. 2018, 4, 1254–1262. [Google Scholar] [CrossRef] [Scilit]
- Schaff, L.R.; Mellinghoff, I.K. Glioblastoma and Other Primary Brain Malignancies in Adults: A Review. JAMA 2023, 329, 574–587. [Google Scholar] [CrossRef] [Scilit]
- Michaelson, N.M.; Watsula, A.; Bakare-Okpala, A.; Mohamadpour, M.; Chukwueke, U.N.; Budhu, J.A. Disparities in Neuro-Oncology. Curr. Neurol. Neurosci. Rep. 2023, 23, 815–825. [Google Scholar] [CrossRef] [Scilit]
- Budhu, J.A.; Mejia, N.I.; Saadi, A. Health Disparities in Neurology. Nat. Rev. Neurol. 2025, 21, 593–605. [Google Scholar] [CrossRef] [Scilit]
- Ostrom, Q.T.; Krebs, H.L.; Patil, N.; Cioffi, G.; Barnholtz-Sloan, J.S. Racial/Ethnic Disparities in Treatment Pattern and Time to Treatment for Adults with Glioblastoma in the US. J. Neuro-Oncol. 2021, 152, 603–615. [Google Scholar] [CrossRef] [Scilit]
- Dressler, E.V.; Liu, M.; Garcia, C.R.; Dolecek, T.A.; Pittman, T.; Huang, B.; Villano, J.L. Patterns and Disparities of Care in Glioblastoma. Neuro-Oncol. Pract. 2019, 6, 37–46. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Osoba, D.; Brada, M.; Prados, M.D.; Yung, W.K.A. Effect of Disease Burden on Health-Related Quality of Life in Patientswith Malignant Gliomas. Neuro-Oncology 2000, 2, 221–228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bonomi, A.E.; Patrick, D.L.; Bushnell, D.M.; Martin, M. Validation of the United States’ Version of the World Health Organization Quality of Life (WHOQOL) Instrument. J. Clin. Epidemiol. 2000, 53, 1–12. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pennacchini, M.; Bertolaso, M.; Elvira, M.M.; De Marinis, M.G. A Brief History of the Quality of Life: Its Use in Medicine and in Philosophy. Clin. Ter. 2011, 162, e99–e103. [Google Scholar]
- Strong, L.E. The Past, Present, and Future of Patient-Reported Outcomes in Oncology. Am. Soc. Clin. Oncol. Educ. Book 2015, 35, e616–e620. [Google Scholar] [CrossRef] [Scilit]
- Bakas, T.; McLennon, S.M.; Carpenter, J.S.; Buelow, J.M.; Otte, J.L.; Hanna, K.M.; Ellett, M.L.; Hadler, K.A.; Welch, J.L. Systematic Review of Health-Related Quality of Life Models. Health Qual. Life Outcomes 2012, 10, 134. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lamba, N.; Mehanna, E.; Kearney, R.B.; Catalano, P.J.; Haas-Kogan, D.A.; Alexander, B.M.; Cagney, D.N.; Lee, K.A.; Aizer, A.A. Racial Disparities in Supportive Medication Use among Older Patients with Brain Metastases: A Population-Based Analysis. Neuro-Oncology 2020, 22, 1339–1347. [Google Scholar] [CrossRef] [Scilit]
- Brady, K.; Cohen, A.L. Differences in Symptom Burden in Primary Brain Tumor Patients Based on Sex, Race, and Ethnicity: A Single-Center Retrospective Study. J. Racial Ethn. Health Disparities 2024, 11, 3029–3039. [Google Scholar] [CrossRef] [Scilit]
- Kim, S.J.; Retnam, R.P.; Sutton, A.L.; Edmonds, M.C.; Bandyopadhyay, D.; Sheppard, V.B. Racial Disparities in Opioid Prescription and Pain Management among Breast Cancer Survivors. Cancer Med. 2023, 12, 10851–10864. [Google Scholar] [CrossRef] [Scilit]
- Payne, R.; Medina, E.; Hampton, J.W. Quality of Life Concerns in Patients with Breast Cancer: Evidence for Disparity of Outcomes and Experiences in Pain Management and Palliative Care among African-American Women. Cancer 2003, 97, 311–317. [Google Scholar] [CrossRef] [Scilit]
- Estevez-Ordonez, D.; Abdelrashid, M.; Coffee, E.; Laskay, N.M.B.; Atchley, T.J.; Chkheidze, R.; Fiveash, J.B.; Markert, J.M.; Lobbous, M.; Maveal, B.M.; et al. Racial and Socioeconomic Disparities in Glioblastoma Outcomes: A Single-Center, Retrospective Cohort Study. Cancer 2023, 129, 3010–3022. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Burton, E.; Yusuf, M.; Gilbert, M.R.; Gaskins, J.; Woo, S. Failure to Complete Standard Radiation Therapy in Glioblastoma Patients: Patterns from a National Database with Implications for Survival and Therapeutic Decision Making in Older Glioblastoma Patients. J. Geriatr. Oncol. 2020, 11, 680–687. [Google Scholar] [CrossRef] [Scilit]
- Forst, D.; Adams, E.; Nipp, R.; Martin, A.; El-Jawahri, A.; Aizer, A.; Jordan, J.T. Hospice Utilization in Patients with Malignant Gliomas. Neuro-Oncology 2018, 20, 538–545. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Valko, P.O.; Siddique, A.; Linsenmeier, C.; Zaugg, K.; Held, U.; Hofer, S. Prevalence and Predictors of Fatigue in Glioblastoma: A Prospective Study. Neuro-Oncology 2015, 17, 274–281. [Google Scholar] [CrossRef] [Scilit]
- Van Coevorden-van Loon, E.M.P.; Coomans, M.B.; Heijenbrok-Kal, M.H.; Ribbers, G.M.; Van Den Bent, M.J. Fatigue in Patients with Low Grade Glioma: Systematic Evaluation of Assessment and Prevalence. J. Neuro-Oncol. 2017, 133, 237–246. [Google Scholar] [CrossRef] [Scilit]
- Berger, A.M.; Mooney, K.; Alvarez-Perez, A.; Breitbart, W.S.; Carpenter, K.M.; Cella, D.; Cleeland, C.; Dotan, E.; Eisenberger, M.A.; Escalante, C.P.; et al. Cancer-Related Fatigue, Version 2.2015. J. Natl. Compr. Cancer Netw. 2015, 13, 1012–1039. [Google Scholar] [CrossRef] [Scilit]
- Armstrong, T.S.; Cron, S.G.; Bolanos, E.V.; Gilbert, M.R.; Kang, D. Risk Factors for Fatigue Severity in Primary Brain Tumor Patients. Cancer 2010, 116, 2707–2715. [Google Scholar] [CrossRef] [Scilit]
- Röttgering, J.G.; Belgers, V.; De Witt Hamer, P.C.; Knoop, H.; Douw, L.; Klein, M. Toward Unraveling the Correlates of Fatigue in Glioma. Neuro-Oncol. Adv. 2022, 4, vdac169. [Google Scholar] [CrossRef] [Scilit]
- Sampath, S.G.; Manriquez, A.H.; Haile, H.; Botkiss, M.; Izima, C.; Adapa, A.R.; Shlobin, N.A.; Argenziano, M.G.; Leu, C.-S.; Gill, B.J.A. Socioeconomic Disparities in Patient-Reported Outcomes, Health Literacy, and Access to Care among Patients with Primary Brain Tumors: Findings from the All of Us Research Program. J. Neuro-Oncol. 2025, 176, 123. [Google Scholar] [CrossRef] [Scilit]
- Struik, K.; Klein, M.; Heimans, J.J.; Gielissen, M.F.; Bleijenberg, G.; Taphoorn, M.J.; Reijneveld, J.C.; Postma, T.J. Fatigue in Low-Grade Glioma. J. Neuro-Oncol. 2009, 92, 73–78. [Google Scholar] [CrossRef] [Scilit]
- Zedlitz, A.; Fasotti, L.; Geurts, A. Post-Stroke Fatigue: A Treatment Protocol That Is Being Evaluated. Clin. Rehabil. 2011, 25, 487–500. [Google Scholar] [CrossRef] [Scilit]
- Röttgering, J.G.; Taylor, J.W.; Brie, M.; Luks, T.; Hervey-Jumper, S.L.; Phan, S.; Bracci, P.M.; Smith, E.; De Witt Hamer, P.C.; Douw, L.; et al. Understanding the Association between Fatigue and Neurocognitive Functioning in Patients with Glioma: A Cross-Sectional Multinational Study. Neuro-Oncol. Pract. 2024, 11, 284–295. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Spencer, J.; Staffileno, B. Exercise Intervention: A Pilot Study to Assess the Feasibility and Impact on Cancer-Related Fatigue and Quality of Life Among Patients With High-Grade Glioma. Clin. J. Oncol. Nurs. 2021, 25, 194–200. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Miklja, Z.; Gabel, N.; Altshuler, D.; Wang, L.; Hervey-Jumper, S.L.; Smith, S. Exercise Improves Health-Related Quality of Life Sleep and Fatigue Domains in Adult High- and Low-Grade Glioma Patients. Support. Care Cancer 2022, 30, 1493–1500. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gordon-Larsen, P.; Nelson, M.C.; Page, P.; Popkin, B.M. Inequality in the Built Environment Underlies Key Health Disparities in Physical Activity and Obesity. Pediatrics 2006, 117, 417–424. [Google Scholar] [CrossRef] [Scilit]
- Laddu, D.; Paluch, A.E.; LaMonte, M.J. The Role of the Built Environment in Promoting Movement and Physical Activity across the Lifespan: Implications for Public Health. Prog. Cardiovasc. Dis. 2021, 64, 33–40. [Google Scholar] [CrossRef] [Scilit]
- Porter, A.B.; Liu, H.; Kohli, S.; Cerhan, J.L.; Sloan, J.; McMurray, R.P.; Le-Rademacher, J.; Loprinzi, C.L.; Villano, J.L.; Kizilbash, S.H.; et al. Efficacy of Treatment with Armodafinil for Cancer-Related Fatigue in Patients with High-Grade Glioma: A Phase 3 Randomized Clinical Trial. JAMA Oncol. 2022, 8, 259–267. [Google Scholar] [CrossRef] [Scilit]
- Gong, S.; Sheng, P.; Jin, H.; He, H.; Qi, E.; Chen, W.; Dong, Y.; Hou, L. Effect of Methylphenidate in Patients with Cancer-Related Fatigue: A Systematic Review and Meta-Analysis. PLoS ONE 2014, 9, e84391. [Google Scholar] [CrossRef] [Scilit]
- Noll, K.R.; Bradshaw, M.E.; Weinberg, J.S.; Wefel, J.S. Neurocognitive Functioning Is Associated with Functional Independence in Newly Diagnosed Patients with Temporal Lobe Glioma. Neuro-Oncol. Pract. 2018, 5, 184–193. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Taphoorn, M.J.; Klein, M. Cognitive Deficits in Adult Patients with Brain Tumours. Lancet Neurol. 2004, 3, 159–168. [Google Scholar] [CrossRef] [Scilit]
- Van Kessel, E.; Baumfalk, A.E.; Van Zandvoort, M.J.E.; Robe, P.A.; Snijders, T.J. Tumor-Related Neurocognitive Dysfunction in Patients with Diffuse Glioma: A Systematic Review of Neurocognitive Functioning Prior to Anti-Tumor Treatment. J. Neuro-Oncol. 2017, 134, 9–18. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Calvio, L.; Feuerstein, M.; Hansen, J.; Luff, G.M. Cognitive Limitations in Occupationally Active Malignant Brain Tumour Survivors. Occup. Med. 2009, 59, 406–412. [Google Scholar] [CrossRef] [Scilit]
- Pelletier, G.; Verhoef, M.J.; Khatri, N.; Hagen, N. Quality of Life in Brain Tumor Patients: The Relative Contributions of Depression, Fatigue, Emotional Distress, and Existential Issues. J. Neuro-Oncol. 2002, 57, 41–49. [Google Scholar] [CrossRef] [Scilit]
- Arnold, S.D.; Forman, L.M.; Brigidi, B.D.; Carter, K.E.; Schweitzer, H.A.; Quinn, H.E.; Guill, A.B.; Herndon, J.E.; Raynor, R.H. Evaluation and Characterization of Generalized Anxiety and Depression in Patients with Primary Brain Tumors. Neuro-Oncology 2008, 10, 171–181. [Google Scholar] [CrossRef] [Scilit]
- Parikh, R.B.; Gallo, J.J.; Cashy, J.; Robinson, K.W.; Narayan, V.; Wong, Y.-N.; Jayadevappa, R.; Chhatre, S. Racial Disparities in Depression Incidence, Management, and Mortality after Prostate Cancer Diagnosis. J. Clin. Oncol. 2021, 39, 201. [Google Scholar] [CrossRef] [Scilit]
- Kinlock, B.L.; Parker, L.J.; Howard, D.L.; Bowie, J.V.; LaVeist, T.A.; Thorpe, R.J. Prevalence and Correlates of Major Depressive Symptoms among Black Men with Prostate Cancer. Ethn. Dis. 2017, 27, 429–436. [Google Scholar] [CrossRef] [Scilit]
- Zheng, X.; Zhang, W.; Li, Y.; Lai, X.; Fan, Q.; Xu, Y.; Yin, X. Prevalence and Independent Risk Factors of Anxiety and Depression Symptoms in Glioma Patients: A Cross-Sectional Analysis. Psychiatry Clin. Psychopharmacol. 2025, 35, 155–164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Franco-Rocha, O.Y.; Fuentes-Balderrama, J.; Sun, B.; Smits, J.A.J.; Magnuson, A.; Kesler, S.R.; Van Dyk, K.; Moore, R.C.; Henneghan, A.M. The Impact of Social Determinants of Health on Mental and Behavioral Health Trajectories of Breast Cancer Survivors: A Longitudinal Cohort Study. Eur. J. Oncol. Nurs. Off. J. Eur. Oncol. Nurs. Soc. 2025, 80, 103036. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Badger, T.A.; Segrin, C.; Crane, T.E.; Chalasani, P.; Arslan, W.; Hadeed, M.; Sikorskii, A. Social Determinants of Health and Symptom Burden During Cancer Treatment. Nurs. Res. 2023, 72, 103–113. [Google Scholar] [CrossRef] [Scilit]
- Krok-Schoen, J.L.; Nikahd, M.; Hyer, M.; Felix, A.S.; Nolan, T.S.; Ridgway-Limle, E.A.; Xu, M.; Quick, A.M.; Paoletta, C.; Horn, M.; et al. Social Determinants of Health and Depressive Symptoms before and after Cancer Diagnosis. J. Women Aging 2024, 36, 398–409. [Google Scholar] [CrossRef] [Scilit]
- Acquaye, A.A.; Vera-Bolanos, E.; Armstrong, T.S.; Gilbert, M.R.; Lin, L. Mood Disturbance in Glioma Patients. J. Neuro-Oncol. 2013, 113, 505–512. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van Genderen, M.N.G.; Belgers, V.; Niers, J.M.; Douw, L.; Röttgering, J.G.; Gorter, M.; Blom, M.E.C.; Barkhof, F.; Klein, M.; Eijgelaar, R.S.; et al. Tumor Location Is Associated with Mood Dysfunction in Patients with Diffuse Glioma. Nat. Ment. Health 2024, 2, 853–864. [Google Scholar] [CrossRef] [Scilit]
- Noll, K.R.; Bradshaw, M.E.; Weinberg, J.S.; Wefel, J.S. Relationships between Neurocognitive Functioning, Mood, and Quality of Life in Patients with Temporal Lobe Glioma: Quality of Life and Temporal Lobe Glioma. Psycho-Oncology 2017, 26, 617–624. [Google Scholar] [CrossRef] [Scilit]
- on behalf of the EORTC Quality of Life Group; Oort, Q.; Dirven, L.; Sikkes, S.A.M.; Aaronson, N.; Boele, F.; Brannan, C.; Egeter, J.; Grant, R.; Klein, M.; et al. Development of an EORTC Questionnaire Measuring Instrumental Activities of Daily Living (IADL) in Patients with Brain Tumours: Phase I–III. Qual. Life Res. 2021, 30, 1491–1502. [Google Scholar] [CrossRef] [Scilit]
- Sacko, A.; Hou, M.-M.; Temgoua, M.; Alkhafaji, A.; Marantidou, A.; Belin, C.; Mandonnet, E.; Ursu, R.; Doridam, J.; Coman, I.; et al. Evolution of the Karnosky Performance Status throughout Life in Glioblastoma Patients. J. Neuro-Oncol. 2015, 122, 567–573. [Google Scholar] [CrossRef] [Scilit]
- Stark, A.M.; Stepper, W.; Mehdorn, H.M. Outcome Evaluation in Glioblastoma Patients Using Different Ranking Scores: KPS, GOS, mRS and MRC. Eur. J. Cancer Care 2010, 19, 39–44. [Google Scholar] [CrossRef] [Scilit]
- Frappaz, D.; Bonneville-Levard, A.; Ricard, D.; Carrie, S.; Schiffler, C.; Xuan, K.H.; Weller, M. Assessment of Karnofsky (KPS) and WHO (WHO-PS) Performance Scores in Brain Tumour Patients: The Role of Clinician Bias. Support. Care Cancer 2021, 29, 1883–1891. [Google Scholar] [CrossRef] [Scilit]
- Buzaglo, J.S.; Musallam, A.; Stepanski, E.; White, C.; Joiner, M.; Vanderwalde, A.M.; Decker, V. Racial Disparities in Performance Status among Cancer Patients at a Community Oncology Practice. J. Clin. Oncol. 2020, 38, 132. [Google Scholar] [CrossRef] [Scilit]
- Reihl, S.J.; Patil, N.; Morshed, R.A.; Mehari, M.; Aabedi, A.; Chukwueke, U.N.; Porter, A.B.; Fontil, V.; Cioffi, G.; Waite, K.; et al. A Population Study of Clinical Trial Accrual for Women and Minorities in Neuro-Oncology Following the NIH Revitalization Act. Neuro-Oncology 2022, 24, 1341–1349. [Google Scholar] [CrossRef] [Scilit]
- Budhu, J.A.; Chukwueke, U.N.; Jackson, S.; Lee, E.Q.; McFaline-Figueroa, J.R.; Willmarth, N.; Dalmage, M.; Kawachi, I.; Arons, D.; Chang, S.M.; et al. Defining Interventions and Metrics to Improve Diversity in CNS Clinical Trial Participation: A SNO and RANO Effort. Neuro-Oncology 2024, 26, 596–608. [Google Scholar] [CrossRef] [Scilit]
- McIver, B.A.; Davis, T.S.; Reinhart, K.; Vera, E.; Acquaye-Mallory, A.; Choi, A.; Kunst, T.; Johnson, M.; Grajkowska, E.; Miller, H.; et al. Evaluating Clinical and Sociodemographic Risk for Symptom Burden Associated Interference With Daily Functioning in the Primary Brain Tumor Patient Population. Cancer Med. 2025, 14, e70682. [Google Scholar] [CrossRef] [Scilit]
- Crooms, R.C.; Johnson, M.O.; Leeper, H.; Mehta, A.; McWhirter, M.; Sharma, A. Easing the Journey—An Updated Review of Palliative Care for the Patient with High-Grade Glioma. Curr. Oncol. Rep. 2022, 24, 501–515. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakajima, R.; Kinoshita, M.; Okita, H.; Yahata, T.; Nakada, M. Awake Surgery for Glioblastoma Can Preserve Independence Level, but Is Dependent on Age and the Preoperative Condition. J. Neuro-Oncol. 2019, 144, 155–163. [Google Scholar] [CrossRef] [Scilit]
- Dirven, L.; Van Den Bent, M.J.; Bottomley, A.; Van Der Meer, N.; Van Der Holt, B.; Vos, M.J.; Walenkamp, A.M.E.; Beerepoot, L.V.; Hanse, M.C.J.; Reijneveld, J.C.; et al. The Impact of Bevacizumab on Health-Related Quality of Life in Patients Treated for Recurrent Glioblastoma: Results of the Randomised Controlled Phase 2 BELOB Trial. Eur. J. Cancer 2015, 51, 1321–1330. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goyal, A.; Zreik, J.; Brown, D.A.; Kerezoudis, P.; Habermann, E.B.; Chaichana, K.L.; Chen, C.C.; Bydon, M.; Parney, I.F. Disparities in Access to Surgery for Glioblastoma Multiforme at High-Volume Commission on Cancer–Accredited Hospitals in the United States. J. Neurosurg. 2022, 137, 32–41. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Loon, E.; Ernens, W.; Heijenbrok-Kal, M.; Horemans, H.; Ribbers, G.; Bent, M. Long-Term Employment Status and the Association with Fatigue in Patients with Grade II Glioma. J. Rehabil. Med. 2021, 53, jrm00198. [Google Scholar] [CrossRef] [Scilit]
- Iyer, H.G.; Ariwodo, O.K.; Mckevitt, C.; Meade, P.S.; Marenco-Hillembrand, L.; Otamendi-Lopez, A.; De Macêdo Filho, L.J.M.; Rosenfeld, S.S.; Cordova, C.; Peterson, J.L.; et al. Predictors of Return to Work Following Surgery in Patients with Glioblastoma: A Retrospective Multicenter Study. J. Neuro-Oncol. 2025, 174, 381–389. [Google Scholar] [CrossRef] [Scilit]
- Blinder, V.S.; Patil, S.; Thind, A.; Diamant, A.; Hudis, C.A.; Basch, E.; Maly, R.C. Return to Work in Low-income Latina and non-Latina White Breast Cancer Survivors: A 3-year Longitudinal Study. Cancer 2012, 118, 1664–1674. [Google Scholar] [CrossRef] [Scilit]
- Ekenga, C.C.; Pérez, M.; Margenthaler, J.A.; Jeffe, D.B. Early-stage Breast Cancer and Employment Participation after 2 Years of Follow-up: A Comparison with Age-matched Controls. Cancer 2018, 124, 2026–2035. [Google Scholar] [CrossRef] [Scilit]
- Tosoni, A.; Gatto, L.; Franceschi, E.; Di Nunno, V.; Lodi, R.; Mura, A.; Di Battista, M.; Bartolini, S.; Brandes, A.A. Association between Socioeconomic Status and Survival in Glioblastoma: An Italian Single-Centre Prospective Observational Study. Eur. J. Cancer 2021, 145, 171–178. [Google Scholar] [CrossRef] [Scilit]
- Sohn, H. Racial and Ethnic Disparities in Health Insurance Coverage: Dynamics of Gaining and Losing Coverage Over the Life-Course. Popul. Res. Policy Rev. 2017, 36, 181–201. [Google Scholar] [CrossRef] [Scilit]
- Blinder, V.S.; Patil, S.; Finik, J.; Makower, D.; Muppidi, M.; Lichtenthal, W.G.; Parker, P.A.; Claros, M.; Suarez, J.; Narang, B.; et al. An Interactive Mobile Application versus an Educational Booklet to Promote Job Retention in Women Undergoing Adjuvant Chemotherapy for Breast Cancer: A Randomized Controlled Trial. Trials 2022, 23, 840. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kirchhoff, A.C.; Nipp, R.; Warner, E.L.; Kuhlthau, K.; Leisenring, W.M.; Donelan, K.; Rabin, J.; Perez, G.K.; Oeffinger, K.C.; Nathan, P.C.; et al. “Job Lock” Among Long-Term Survivors of Childhood Cancer: A Report from the Childhood Cancer Survivor Study. JAMA Oncol. 2018, 4, 707–711. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Starnoni, D.; Berthiller, J.; Idriceanu, T.-M.; Meyronet, D.; d’Hombres, A.; Ducray, F.; Guyotat, J. Returning to Work after Multimodal Treatment in Glioblastoma Patients. Neurosurg. Focus 2018, 44, E17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rhee, J.Y.; Mastrangelo, C.; Miller, P.J.; Youssef, G.; Tentor, Z.; Rothfeld-Wehrwein, Z.R.; Dhongade, V.A.; Nakhate, V.; Batchelor, T.; Dhand, A. A Pilot Study to Quantify and Describe Personal Social Networks in Patients with Glioblastoma. Neuro-Oncol. Pract. 2025, 12, 426–436. [Google Scholar] [CrossRef] [Scilit]
- Shen, C.; Rolls, E.T.; Cheng, W.; Kang, J.; Dong, G.; Xie, C.; Zhao, X.-M.; Sahakian, B.J.; Feng, J. Associations of Social Isolation and Loneliness with Later Dementia. Neurology 2022, 99, e164–e175. [Google Scholar] [CrossRef] [Scilit]
- Gately, L.; McLachlan, S.A.; Dowling, A.; Philip, J. Surviving Glioblastoma and a Sense of Disconnection. J. Clin. Neurosci. 2020, 81, 284–289. [Google Scholar] [CrossRef] [Scilit]
- Vijayasiri, G.; Molina, Y.; Chukwudozie, I.B.; Tejeda, S.; Pauls, H.A.; Rauscher, G.H.; Campbell, R.T.; Warnecke, R.B. Racial Disparities in Breast Cancer Survival: The Mediating Effects of Macro-Social Context and Social Network Factors. J. Health Disparities Res. Pract. 2018, 11, 6. [Google Scholar]
- Gauthier, G.R.; Smith, J.A.; García, C.; Garcia, M.A.; Thomas, P.A. Exacerbating Inequalities: Social Networks, Racial/Ethnic Disparities, and the COVID-19 Pandemic in the United States. J. Gerontol. B Psychol. Sci. Soc. Sci. 2021, 76, e88–e92. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Steptoe, A.; Deaton, A.; Stone, A.A. Subjective Wellbeing, Health, and Ageing. Lancet 2015, 385, 640–648. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, D.M.; Nazroo, J.; O’Connor, D.B.; Blake, M.; Pendleton, N. Sexual Health and Well-Being Among Older Men and Women in England: Findings from the English Longitudinal Study of Ageing. Arch. Sex. Behav. 2016, 45, 133–144. [Google Scholar] [CrossRef] [Scilit]
- Lombard, A.; Duffau, H. Sexual Dysfunction of Patients with Diffuse Low-Grade Glioma: A Qualitative Review of a Neglected Concern. Cancers 2022, 14, 3025. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morokqff, P.J.; Gillilland, R. Stress, Sexual Functioning, and Marital Satisfaction. J. Sex Res. 1993, 30, 43–53. [Google Scholar] [CrossRef] [Scilit]
- Finocchiaro, C.Y.; Petruzzi, A.; Fedeli, G.; Vistalli, M.G.; Innocenti, A.; Silvani, A.; Lamperti, E. Hidden Reality: Sexual Sphere in Brain Tumor Patients. Psychol. Health Med. 2017, 22, 370–380. [Google Scholar] [CrossRef] [Scilit]
- Boccia, M.L.; Anyanda, E.I.; Fonkem, E. A Preliminary Report on Quality of Life and Sexual Function in Brain Tumor Patients. J. Sex. Med. 2021, 18, 737–742. [Google Scholar] [CrossRef] [Scilit]
- Laldjising, E.; Sekercan, A.; Gadjradj, P.S. Neurosurgeons’ Opinions on Discussing Sexual Health among Brain Tumor Patients: Room for Improvement? J. Clin. Neurosci. 2021, 94, 292–297. [Google Scholar] [CrossRef] [Scilit]
- Hughes, M.K. Sexual Dysfunction and Brain Tumors: Why Address It? Neuro-Oncology 2015, 17, 483–484. [Google Scholar] [CrossRef] [Scilit]
- Bhinder, J.K.; Kennedy, S.K.F.; Faouk Al Aadah, C.; Al-Khaifi, M. 2024 SOGC, 2024 NCCN, 2022 ESO-ESMO, and 2018 ASCO: A Comparison of Female Cancer Survivorship Guidelines for the Management of Sexual Health Concerns. Support. Care Cancer 2025, 33, 584. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pisu, M.; Martin, M.Y. Financial Toxicity: A Common Problem Affecting Patient Care and Health. Nat. Rev. Dis. Primer 2022, 8, 7. [Google Scholar] [CrossRef] [Scilit]
- Elshiekh, C.; Rudà, R.; Cliff, E.R.S.; Gany, F.; Budhu, J.A. Financial Challenges of Being on Long-Term, High-Cost Medications. Neuro-Oncol. Pract. 2025, 12, i49–i58. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khanmohammadi, S.; Mobarakabadi, M.; Mohebi, F. The Economic Burden of Malignant Brain Tumors. In Human Brain and Spinal Cord Tumors: From Bench to Bedside; Springer International Publishing: Cham, Switzerland, 2023; pp. 209–221. [Google Scholar]
- Luttrell, J.; Lion, K.; Pinkham, M.B.; Collins, L.G.; Ownsworth, T. The Impact of Financial Toxicity on Quality of Life for Survivors of Primary Brain Tumour. J. Cancer Surviv. 2025; in press. [CrossRef] [Scilit]
- Pöhlmann, J.; Grabe-Heyne, K.; Krott-Coi, L.; Rabar, S.; Pollock, R. HSD15 The Economic and Humanistic Burden of Glioma in the United States and Canada. Value Health 2024, 27, S223. [Google Scholar] [CrossRef] [Scilit]
- Patel, M.P.; Affronti, M.L.; Buckley, E.D.; Herndon Ii, J.E.; Mackowsky, E.M.; Johnson, M.O.; Peters, K.B. Financial Toxicity of Oral Chemotherapy in Patients with Primary Brain Tumors. Neuro-Oncol. Pract. 2025, 12, 153–159. [Google Scholar] [CrossRef] [Scilit]
- Terrell, D.; Camarano, J.; Whipple, S.; Guthikonda, B.; Beyl, R.; Newman, W.C. Financial Toxicity in Patients with Glioblastoma. J. Neuro-Oncol. 2025, 171, 75–83. [Google Scholar] [CrossRef] [Scilit]
- Graboyes, E.M.; Chaiyachati, K.H.; Sisto Gall, J.; Johnson, W.; Krishnan, J.A.; McManus, S.S.; Thompson, L.; Shulman, L.N.; Yabroff, K.R. Addressing Transportation Insecurity Among Patients with Cancer. J. Natl. Cancer Inst. 2022, 114, 1593–1600. [Google Scholar] [CrossRef] [Scilit]
- Fauvet, C.; Villain, M.; Gatignol, P. Repeated Awake Surgery and Quality of Life in Patients with Diffuse Glioma: A Systematic Review and Meta-Analysis. Neurosurg. Rev. 2023, 46, 156. [Google Scholar] [CrossRef] [Scilit]
- Garcia Fox, R.; Chukwueke, U.N.; Sannes, T.; Miran, D.; Chiu, D.; Bagley, C.; Holmes, E.G.; Peirce, B.; Beroukhim, R.; Youssef, G.; et al. Glioma Resource Outreach with Support: A Program to Identify and Initiate Supportive Care Interventions for Unmet Needs among Adult Lower-Grade Glioma Patients. Neuro-Oncol. Pract. 2025, 12, 87–99. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rimmer, B.; Balla, M.; Dutton, L.; Williams, S.; Lewis, J.; Gallagher, P.; Finch, T.; Burns, R.; Araújo-Soares, V.; Menger, F.; et al. “It Changes Everything”: Understanding How People Experience the Impact of Living with a Lower-Grade Glioma. Neuro-Oncol. Pract. 2024, 11, 255–265. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakajima, R.; Kinoshita, M.; Okita, H.; Nakada, M. Postsurgical Motor Function and Processing Speed as Predictors of Quality of Life in Patients with Chronic-Phase Glioblastoma. Acta Neurochir. 2024, 166, 357. [Google Scholar] [CrossRef] [Scilit]
- Stockdill, M.L.; Vo, J.B.; Celiku, O.; Karim, Z.; Kim, Y.; Miller, H.; Vera, E.; Armstrong, T.S. Abstract 2155: The Impact of Urban Residence on Symptom Duration, Treatment Initiation, and Survival among Primary Brain Tumor Patients: A Large Cohort Analysis. Cancer Res. 2024, 84, 2155. [Google Scholar] [CrossRef] [Scilit]
- Gupta, A.; Eisenhauer, E.A.; Booth, C.M. The Time Toxicity of Cancer Treatment. J. Clin. Oncol. Off. J. Am. Soc. Clin. Oncol. 2022, 40, 1611–1615. [Google Scholar] [CrossRef] [Scilit]
- Asfaw, Z.K.; Young, T.; Durbin, J.; Tomalin, L.; Germano, I.M. Navigating the Crossroads: A 10-Year Population Study on Access to Care Among Patients With Brain Tumor. Neurosurgery 2025, 97, 884–892. [Google Scholar] [CrossRef] [Scilit]
- Koenig, H.G.; Larson, D.B.; Larson, S.S. Religion and Coping with Serious Medical Illness. Ann. Pharmacother. 2001, 35, 352–359. [Google Scholar] [CrossRef]
- Panzini, R.G.; Mosqueiro, B.P.; Zimpel, R.R.; Bandeira, D.R.; Rocha, N.S.; Fleck, M.P. Quality-of-Life and Spirituality. Int. Rev. Psychiatry 2017, 29, 263–282. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Skevington, S.M.; Gunson, K.S.; O’Connell, K.A. Introducing the WHOQOL-SRPB BREF: Developing a Short-Form Instrument for Assessing Spiritual, Religious and Personal Beliefs within Quality of Life. Qual. Life Res. 2013, 22, 1073–1083. [Google Scholar] [CrossRef] [Scilit]
- Coleman, D.; Hurtado-de-Mendoza, A.; Montero, A.; Sawhney, S.; Wang, J.H.; Lobo, T.; Graves, K.D. Stigma, Social Support, and Spirituality: Associations with Symptoms among Black, Latina, and Chinese American Cervical Cancer Survivors. J. Cancer Surviv. 2024, 18, 710–726. [Google Scholar] [CrossRef] [Scilit]
- Bai, J.; Brubaker, A.; Meghani, S.H.; Bruner, D.W.; Yeager, K.A. Spirituality and Quality of Life in Black Patients with Cancer Pain. J. Pain Symptom Manag. 2018, 56, 390–398. [Google Scholar] [CrossRef] [Scilit]
- Canada, A.L.; Fitchett, G.; Murphy, P.E.; Stein, K.; Portier, K.; Crammer, C.; Peterman, A.H. Racial/Ethnic Differences in Spiritual Well-Being among Cancer Survivors. J. Behav. Med. 2013, 36, 441–453. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Randazzo, D.M.; McSherry, F.; Herndon, J.E.; Affronti, M.L.; Lipp, E.S.; Miller, E.S.; Woodring, S.; Healy, P.; Jackman, J.; Crouch, B.; et al. Spiritual Well-Being and Its Association with Health-Related Quality of Life in Primary Brain Tumor Patients. Neuro-Oncol. Pract. 2021, 8, 299–309. [Google Scholar] [CrossRef] [Scilit]
- Dinapoli, L.; Caliandro, M.; Chiesa, S.; Marconi, E.; Capocchiano, N.D.; Mazzarella, C.; Bartoli, F.B.; Bracci, S.; Balducci, M.; Chieffo, D.P.R.; et al. Resilience and Spiritual Well-Being as Resources for Coping with Radiotherapy and Surviving in Patients with Glioblastoma. Palliat. Support. Care 2025, 23, e10. [Google Scholar] [CrossRef] [Scilit]
- Peters, K.; Mellinghoff, I.; Van Den Bent, M.; Blumenthal, D.; Touat, M.; Clarke, J.; Mendez, J.; Yust-Katz, S.; Mason, W.; Ducray, F.; et al. A Randomized, Double-Blind, Phase 3 Study of Vorasidenib Versus Placebo in Patients with Mutant IDH1/2 Diffuse Glioma (INDIGO): Analysis of Health-Related Quality of Life, Neurocognition and Seizures (PL5.003). Neurology 2024, 102, 5113. [Google Scholar] [CrossRef] [Scilit]
- Goonaratne, E.; McGrath, K.; Lee, S.F.; Bottomley, A.; Cella, D.; Soliman, H.; Chan, A.W.; Chang, E.; Rades, D.; Marta, G.N.; et al. Use of the EORTC QLQ-BN20 and the FACT-Br for the Assessment of Quality of Life in Patients with Brain Tumors: A Systematic Review of Prospective Clinical Studies. Curr. Opin. Support. Palliat. Care 2025, 19, 270–278. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ford, I.; Norrie, J. Pragmatic Trials. N. Engl. J. Med. 2016, 375, 454–463. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.