


Abstract
(1) Background: Native foods are essential for promoting health, sustainability, and the resilience of Indigenous communities. They contribute to biodiversity, are adapted to local ecosystems, and support cultural identity. This study aims to identify and describe strategies and health outcomes from programs and interventions using native foods to promote health or address food insecurity. (2) Methods: A scoping review was conducted using five databases, including studies that implemented interventions using native foods exclusively or combined with introduced foods (non-native). The review included studies involving human participants and reporting outcomes related to health, nutritional improvements, food security, or cultural impacts. (3) Results: Nineteen studies were included. Most interventions (n = 16) combined native foods with introduced healthy foods and implemented multicomponent strategies to promote their intake (n = 15), such as educational sessions, food distribution, gardening, cooking activities, community events, media campaigns, and policy changes. Of the 19 studies, 12 explicitly used a participatory method. Reported outcomes included improved dietary intake and nutrient intake, such as increased intake of vitamin A, calcium, and iron; enhanced knowledge about native foods and healthy eating; improved health; positive cultural impacts; and enhanced food security. (4) Conclusions: The results from this scoping review suggest that interventions using native foods show promising results in improving health, nutritional outcomes, cultural identity, and food security, highlighting their potential for broader public health applications and the value of participatory approaches for sustainable interventions.
1. Introduction
Native foods, recognised for their nutrient-rich properties, are vital for supporting biodiversity, sustainability, and the resilience of Indigenous communities [1]. Environmentally, native foods are adapted to local ecosystems, using less water and agricultural inputs such as fertilisers and pesticides, which helps mitigate climate change and promotes ecological balance [2]. From a health perspective, native foods are typically rich in essential nutrients, antioxidants, and phytochemicals, which are linked to preventing chronic diseases such as diabetes and cardiovascular diseases [1,2]. Additionally, these foods are minimally processed, which contributes to their nutrient-rich properties [2]. Indigenous communities apply traditional methods such as grinding seeds and cooking and leaching some nuts only for detoxification purposes and make foods more digestible and palatable [2].
Despite this recognition, there are still challenges to preserving and using native foods and the Indigenous food knowledge associated with them [3]. This has contributed to a rise in diet-related diseases and a significant loss of food diversity in Indigenous communities [4]. Indigenous peoples, who constitute only 5% of the global population, account for 15% of global poverty [5]. These communities represent a diversity of languages, cultures, and histories [6], yet share common challenges with socioeconomic status and health, experiencing significantly poorer health outcomes compared to non-Indigenous groups [7,8,9,10,11]. Additionally, systemic marginalisation and discrimination contribute to these health inequities [12].
A systematic review and meta-analysis by Shahunja et al. [7] found that Indigenous populations from countries such as Australia, the USA, Canada, New Zealand, and India have twice the likelihood of experiencing multimorbidity compared to non-Indigenous populations. Another systematic review focused on Canadian Indigenous peoples revealed a disproportionate impact of diabetes, with prevalence rates almost twice as high as in the general population [8]. In some remote Northern Territory communities in Australia, the prevalence of diabetes in adults was 28.6% in 2018–2019 [10]. Carman et al. [9] analysed a national survey of Australian individuals, finding that Aboriginal respondents had a two-fold higher prevalence of mental–physical multimorbidity (16.1% vs. 8.1%). Food insecurity also disproportionately affects Aboriginal and Torres Strait Islander peoples compared to non-Indigenous Australians (22% vs. 3.7%) [13]. In Canada, 52% of Inuit ages 25 and older experienced food insecurity in 2012 [14], and in 2017–2018, food insecurity rates were two to six times higher among Indigenous households than other Canadian households [15].
These health disparities are rooted in historical and systemic factors such as colonisation, displacement from traditional lands, and policies that disrupt Indigenous food systems [16]. The Australian Institute of Health and Welfare identifies numerous determinants impacting health disparities, including socioeconomic, environmental, health risk, and historical factors [11]. For example, employment rates are lower among First Nations peoples compared to non-Indigenous Australians (56% vs. 78%), which may directly affecting food security [11]. Colonisation is a historical factor that has deeply impacted the culture and health of First Nations communities [11]. Violence, epidemic diseases, and land occupation have caused a loss of cultural connections to land, food, family, and community, resulting in ongoing intergenerational trauma linked to poor physical and mental health outcomes [11,17,18,19]. In Australia, First Nations peoples were forcibly removed from their traditional lands and native foods when colonisers imposed Western diets consisting of flour, sugar, tea, and salted meats [20]. Suppression of native food consumption was part of broader assimilation policies that undermined food sovereignty, disrupted the transmission of traditional food knowledge, and led to a decline in health and wellbeing in these communities [20].
To address the impacts of social inequities, racism, and colonisation trauma, promoting cultural connectedness is essential for improving health outcomes [8,21]. Engaging community members in decision making, traditional practices, and contact with land through culturally safe approaches can strengthen cultural identity, connectedness, and community resilience [8,21]. Revitalising Indigenous food practices by incorporating native foods into community diets is a pathway to enhancing sustainability, food security, and health outcomes in these communities [1,2,4,22]. Egeland and Harrison [23] reviewed various programs and interventions integrating native foods and traditional food practices in Indigenous communities. They found that community-led initiatives and policies centred around native foods can support Indigenous sovereignty and self-determination, thereby addressing health disparities and improving food security [23].
Food sovereignty is the right of Indigenous peoples to define and control their own food systems and promote health through culturally relevant practices [24,25,26], ensuring democratic ownership of food resources [27]. This right is supported by the United Nations Declaration on the Rights of Indigenous Peoples (UNDRIP), which, since 2007, has recognised the importance of revitalising cultural practices and native foods and affirmed Indigenous peoples’ right to make decisions in all policies or research impacting their lives [28]. Since then, many research projects and policies involving Indigenous communities have employed participatory methods. Participatory approaches, such as Community-Based Participatory Research (CBPR), co-design, and co-production, involve researchers, policymakers, and community members working collaboratively and sharing power and decisions throughout the project—from design to implementation, evaluation, and dissemination of results [29,30]. This scoping review aims to identify and describe strategies and health outcomes from programs and interventions implemented using native foods to promote health or to address food insecurity.
The terms “traditional food,” “native food,” “Indigenous food,” and “local food” are frequently used in the context of health and sustainable food systems. While they share similarities, each has distinct meanings that reflect historical, cultural, and geographical contexts. Native food refers to plants and animals Indigenous to a specific region and adapted to local environments [31,32]. The term is sometimes used interchangeably with Indigenous food, but the latter encompasses broader cultural practices, including spiritual beliefs and ecological knowledge [33]. Traditional food refers to foods consumed over generations with specific preparation methods and cultural significance [34]. Local food emphasises geographic proximity and promotes consuming foods produced close to where they are grown to reduce the carbon footprint associated with transportation [35].
In this review, we predominantly use the term native food, as the interventions examined are based on Indigenous communities and involve foods native to their locations. However, considering the interchangeable nature of these concepts in the literature, we retained the terms used by each study in the summary table, with many using “traditional foods.” Similarly, we use the terms Indigenous and First Nations peoples to describe pre-colonial Indigenous countries with independent languages and identities. Within an Australian context, the term “Aboriginal” refers to all Indigenous peoples of mainland Australia and Tasmania, while “Torres Strait Islander” identifies those groups indigenous to Australia from the islands of the Torres Strait.
2. Materials and Methods
2.1. Study Design
This scoping review followed the Prisma Extension for Scoping Reviews (PRISMA-ScR) [36] and the five-stage framework developed by Arksey and O’Malley, which involves (1) defining the research question; (2) finding relevant studies; (3) selecting the studies according to the inclusion criteria; (4) organising and categorising the data by key themes; and (5) summarising and presenting the results [37]. The review was registered in PROSPERO (CRD42023463624).
2.2. Search Strategy
A search strategy was developed (Appendix A Table A1) to identify studies that assessed interventions using native foods to promote health. Five electronic databases were accessed to search for relevant studies, which included Scopus, Embase, Web of Science Core Collection, Medline, and PubMed. Key words were applied based on the two main concepts: native food and intervention. The search strategy used for all databases is shown in Table A1.
2.3. Eligibility—PICOS Criteria
The search was limited to results published in English and Portuguese, as we wanted to expand the scope of our review and capture a broader range of studies, considering that our two reviewers are proficient in these languages. No exclusion criteria were applied for the publication date. All peer-reviewed experimental studies on humans were included. Reviews and conference abstracts were excluded.
The PICOS criteria for inclusion and exclusion of studies were applied as follows: (1) Participants (P): studies were included if they presented the intervention on humans and excluded if the intervention was conducted on animals, such as lab interventions. No age or other specific criteria were applied. (2) Interventions (I): studies used any native food, exclusively or combined with introduced foods, and in different ways, such as nutrition education, cooking, or gardening, that aimed to promote or maintain health or address food insecurity. (3) Comparators (C): no intervention (control group) and the use of introduced foods were considered for inclusion. (4) Outcomes: the primary outcomes included the evaluation of actual or intended consumption, purchase or gardening of native foods, improvements in health and nutritional status, and impacts on food security. The secondary outcomes included the knowledge enhancement of native foods and their health benefits and perceptions of the intervention, including cultural impacts, providing qualitative insights into its effectiveness and acceptance.
2.4. Study Selection
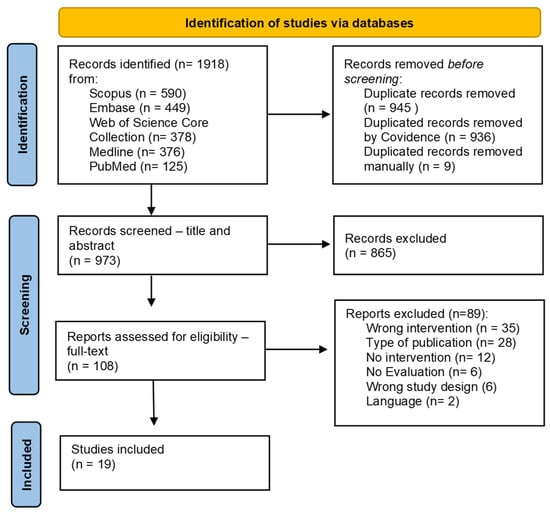
The Covidence platform was used for the study management process. Two authors (CL and JL) independently screened the references’ titles and abstracts. At the second stage, the authors evaluated the full texts according to the eligibility criteria. Any discrepancies between the two reviewers were resolved through consensus or a third reviewer. The flowchart in Figure 1 details the identification and screening process for including the papers.
Figure 1.
Flowchart of identification and screening process for selection of records assessing interventions and programs using native foods to promote health.
2.5. Data Extraction and Synthesis
Two researchers (CL and JL) independently extracted relevant data from the included papers using a template developed by the research team on Covidence, which included title, author(s), year of publication, country, aim of the study, study design, methods, intervention details, native food used, population description, inclusion and exclusion criteria, recruitment details, sample size, outcomes, and results. Disagreements were resolved by consensus or by consultation with a third researcher (SM). There was a substantial heterogeneity among the interventions and reported outcomes of the included studies, which made it challenging to conduct a quantitative synthesis or meta-analysis. This heterogeneity is particularly expected in the context of native foods, as there are limited studies available on this topic. Therefore, we opted to use a narrative synthesis to explore and describe the diversity of interventions and outcomes, offering an important first overview of the type of interventions and outcomes related to native foods.
To analyse whether the studies included a participatory approach, two researchers (CL and JL) independently extracted relevant data for explicit mention of Community-Based Participatory Research (CBPR), Community Advisory Boards (CABs), Community Advisory Groups (CAGs), co-design, or specific steps in the participatory approach. The studies were then classified into four categories: (1) those that clearly stated the use of CBPR, CABs, CAGs, or co-design or described the participatory steps; (2) those that mentioned participatory approaches without providing detailed information; (3) those that did not mention any participatory approach; and (4) studies conducted entirely by community members.
2.6. Quality Assessment
The Mixed Method Appraisal Tool (MMAT, Version 2018) [38] was applied for a qualitative assessment of all included studies by two reviewers (CL and JL). The MMAT was suitable for this review due to its versatility in appraising different study designs, including quantitative, qualitative, and mixed methods. The tool uses criteria related to the clarity of the research questions, appropriateness of the study design, representativeness of the sample, outcome data’s completeness, adherence to the intervention, and interpretation of the results [38].
3. Results
3.1. Study Selection
The search across all five databases resulted in 1918 studies, of which 945 duplicates were excluded. After screening the title and abstract, 865 records were excluded, resulting in 108 articles for full-text review. Of these, 19 met the inclusion criteria. Two authors (CL and JL) independently conducted the screening process, and conflicts were resolved by discussion and consensus.
3.2. Study Characteristics
Appendix B Table A2 presents the characteristics of the included studies.
3.2.1. Study Design
All papers included in this review were published in English. Studies used qualitative methods (n = 5) [39,40,41,42,43], quasi-experimental methods (n = 4) [44,45,46,47], mixed methods (n = 4) [48,49,50,51], non-RCT (n = 3) [52,53,54], RCT (n = 2) [55,56], and cross-sectional methods (n = 1). Most studies (n = 12) were conducted in North America—USA, Canada, and Greenland, followed by studies in Oceania—the Federated States of Micronesia (n = 3), Asia—India and Japan (n = 2), South Africa (n = 1), and South America—Ecuador (n = 1). Studies were published between 2001 and 2023; nine were published between 2010–2019, seven were published after 2020, and three studies were published before 2010.
3.2.2. Study Population and Sample
Sample sizes were generally small. Most studies (n = 11) had a sample smaller than 100 participants. The sample sizes ranged from 10 to 531; the mean was 132.9. All studies targeted First Nations populations and communities. Studies reported the participants’ ages differently, and some did not mention it (n = 5), which was a barrier to calculating the mean. The participants’ ages ranged from 6 months to 79 years old. Approximately half of studies (n = 10) had more than 50% female participants. However, six studies did not report gender.
3.2.3. Method—Participatory Approach
Appendix C Table A3 shows whether the study used any participatory approach to develop, implement, and evaluate the intervention. Out of 19 studies, 12 explicitly used Community-Based Participatory Research (CBPR) or clearly outlined steps of a participatory approach, such as co-design, shared decision making, or active involvement of community members throughout the research/intervention process. A total of three studies cited the use of a participatory approach but lacked specific details on how the community or participants were involved in the research/intervention process. The other three studies did not describe any participatory approach or involvement of community members in the research process. One intervention was initiated, designed, and conducted by community members, with the study merely assessing or evaluating the outcomes of this community-led initiative.
3.2.4. Quality Appraisal
The quality scores varied across the studies, with the lowest scoring study at 42.9% and the highest score at 100%, with an average of 77.3%. Overall, most studies (n = 12) received a high score—higher than 80%. However, two studies scored below 50%. The studies with low scores were due to a lack of details about sampling, statistical analyses, risk of bias, or the absence of some reported outcomes in the results (Appendix D Table A4).
3.3. Interventions’ Characteristics and Main Outcomes
3.3.1. Interventions’ Aims
Of the interventions, eight aimed to facilitate cultural reintegration, such as reconnecting with the traditional food system and increasing the intake of native foods [39,40,41,42,43,47,51,54]. Five interventions focused on improving diet and promoting healthy eating behaviours, including increasing FV intake and reducing unhealthy food consumption [46,47,48,49,53]. Four interventions aimed to enhance overall health and wellbeing [48,49,50,57], while another four aimed to improve access to healthy, local, and native foods [40,41,42,43], and four promoted physical activity [47,48,50,53]. Two interventions aimed to enhance food security or cultural food security [52,57]; two promoted dietary diversity and nutrient intake [44,52]; two focused on improving knowledge about nutrition, sustainability, and Indigenous foods [46,48]; and two supported local food production and consumption [49,50]. Furthermore, two targeted health promotion in specific conditions, such as diabetes and cardiovascular disease [55,56]. One intervention aimed to provide evidence of the importance of local food for food security and health [45]. Most interventions had multiple objectives, as detailed in Appendix B Table A2.
3.3.2. Interventions’ Duration and Target Population
The duration of interventions varied widely from 1 month to 15 years. Most interventions (n = 13) lasted one year or more, which aligns with the participatory approach previously described. All interventions focused on First Nations populations and communities, as described in Appendix B Table A2.
3.3.3. Interventions’ Activities
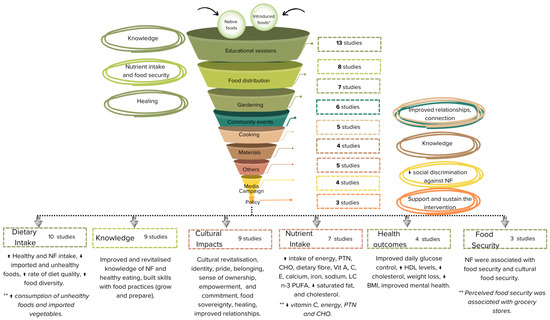
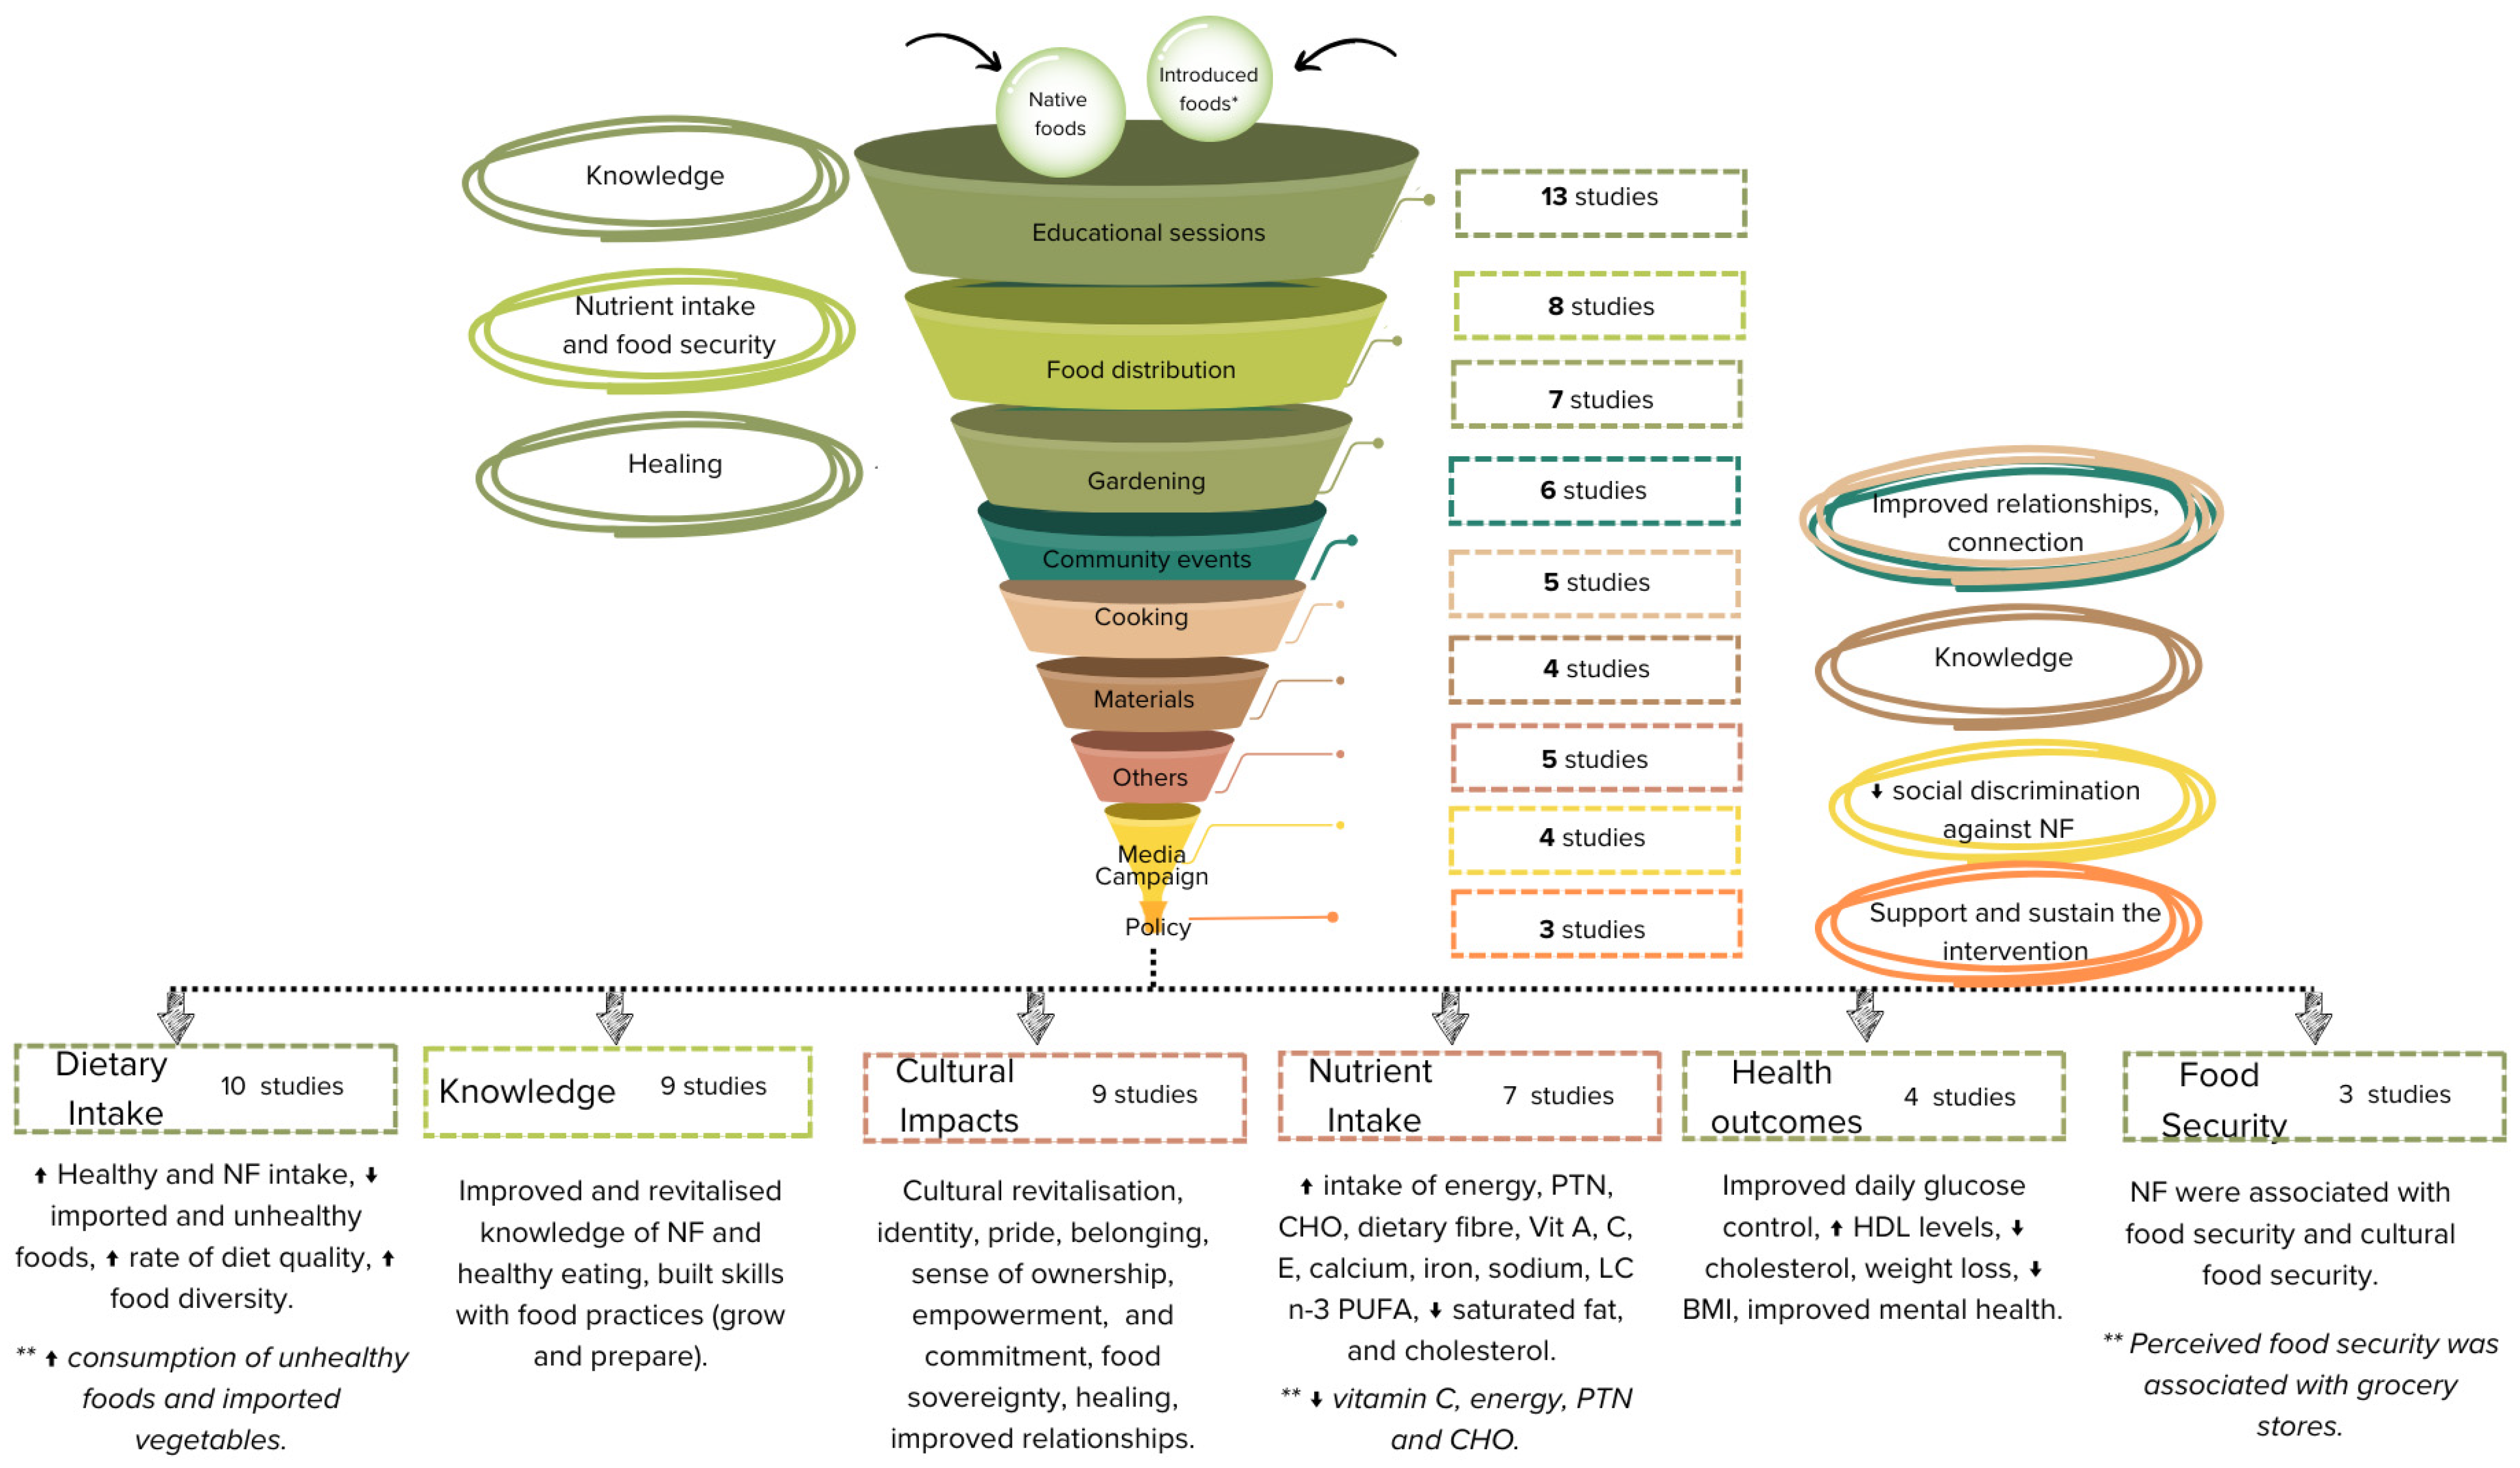
Appendix B Table A2 presents the detailed characteristics of the interventions, and Figure 2 shows a summary of the type of interventions. Most interventions (n = 16) combined native foods with other introduced healthy foods in their activities to achieve the previously outlined objectives. Interventions included a diverse combination of native foods, including animal-derived foods such as marine mammals and fish [44,53,54,55,56,57], as well as plant-based foods such as wild rice [48]; grains (kosayo—beans cooked with millet flour and berries) [39]; yams [44]; vegetables; and wild fruits such as perennial lily [39], yellow-fleshed banana [45,49], and breadfruit varieties [45,49,50]. Only three interventions focused exclusively on native foods in their activities, such as salmon [54,57] and some native greens and vegetables [51]. Overall, the majority of interventions (n = 15) integrated more than one category of activity. Two studies focused solely on activities related to food distribution [44,52], one study concentrated on educational sessions [46], and another focused exclusively on cooking activities [51].
Figure 2.
Distribution of intervention activities and main outcomes. * Introduced foods—non-native foods. ** Although studies showed improvements in various outcomes, they also reported mixed or unintended results, such as a reduction in specific nutrients (e.g., vitamin C) or associations of food security with grocery stores instead of native foods. NF—Native Foods; PTN—Protein; CHO—Carbohydrate; Vit—Vitamin; LC n-3 PUFA—Long-Chain Omega-3 Polyunsaturated Fatty Acid; HDL—High-Density Lipoprotein; BMI—Body Mass Index.
Thirteen studies incorporated educational sessions as part of their interventions [40,41,42,43,45,46,47,48,49,50,53,54,57]. These sessions covered different topics, such as healthy eating [53]; food skills [43]; the benefits of native foods [49]; and traditional food preparation methods such as using a charcoal oven [50], gardening, and harvesting. Some schools included lessons on healthy eating [46], the benefits of traditional methods and native foods, and dietary diversification [46,49]. In some cases, elders passed on knowledge to youth, covering traditional food methods, cultural values, and Indigenous language [40,41,47].
Eight studies included food distribution as a strategy to enhance access to native foods [39,42,43,44,52,54,56,57]. For example, the Local Food to School (LF2S) program in Canada used local food pantries to distribute local foods to schools (e.g., meals with native foods) and other public organisations [42,43]. Similarly, the Nega Elicarvigmun (Fish-to-School) program in the USA served locally caught salmon weekly to students, aiming to reconnect them with their traditional food system and increase native food consumption [54].
Activities focusing on how to grow and prepare native foods were also included in the studies. Gardening activities were included in seven interventions [40,41,42,43,47,48,50]. These activities often took place in school gardens with native foods, where students and elders combined scientific knowledge with Indigenous knowledge, using respectful harvesting and traditional protocols [40,41,42,43,47]. Five studies included cooking activities designed to build the capacity to prepare healthy meals using native foods, including participatory cooking sessions and recipes focusing on native foods [39,49,50,51,53]. Community events such as fairs [53], celebration days [42,43,54], and communal gatherings [39,57] were also used as a form of intervention in six studies.
To support knowledge transmission about native foods and traditional practices, four interventions also developed educational materials, such as guides, pamphlets, posters, recipe books, clipart, and storybooks [42,53,55,56]. Media campaigns were used in four studies to increase awareness and knowledge about native foods, including radio [53], newsletters and newspapers with recipes using native foods [39,53], posters [45], and the promotion of local foods through “Go Local” slogans [45,49]. For instance, Kaufer et al. [49] implemented the “Go local and Go Yellow” messages in some communities in Federated States of Micronesia to promote vitamin A-rich native foods.
Three studies included local and regional policies to promote native foods. Blanchet et al., using a participatory approach, included community members to participate and decide on water management to facilitate the inclusion and reproduction of Okanagan Sockeye Salmon in Canada. Cueva et al. [40,41] implemented school guidelines to promote healthy foods and beverages. Other activities included in five studies involved counselling [55], environmental changes (e.g., constructing fish passages to support salmon migration) [57], labelling dishes with their traditional names [39], youth drama club, games, planting competitions, charcoal oven development [45], and seed and plant distribution [50].
3.3.4. Outcomes
The main outcomes reported by the studies included improvements in dietary and nutrient intake, increased knowledge, improved health, positive cultural impacts, and enhanced food security.
Improvements in Dietary and Nutrient Intake
Dietary intake was analysed in 10 studies (52.6%) using Food Frequency Questionnaires (FFQs), 24-h recalls, or surveys. The improvements in dietary intake included increased native food consumption [45,49,50,51,53,54,55,56,57]; improved dietary diversity [45,49,51]; higher diet quality scores [54]; and reduced intake of unhealthy and less sustainable foods, such as imported meats, fruits, and added sugars [49,53,56]. Nine studies reported positive dietary outcomes, and eight studies incorporated educational sessions or materials in combination with other activities such as counselling, food distribution, cooking, community events, policy development, media campaigns, or gardening. One study [51] focused exclusively on cooking activities.
Eight studies showed significant improvements in dietary outcomes, including increased healthy and native food intake, reduced imported and unhealthy food intake, and increased rates of diet quality and food diversity [45,49,50,51,53,54,55,57]. For example, Kaufer et al. [49] in the Federated States of Micronesia used workshops, cooking activities, and media campaigns to promote local food production and consumption. The intervention resulted in a 475% increase in the consumption frequency of giant swamp taro and a 53% increase in the consumption of local bananas (p < 0.01). Similarly, Roche et al. [51] in Ecuador conducted a 12-day participatory cooking session intervention focusing on Stinging nettle (Urtica dioica), round-leaved dock (Rumex obtusifolius), and other native vegetables, which led to higher dietary diversity scores in the intervention group (IG: 15.0 ± 4.4) compared to the control group (CG: 13.4 ± 4.6). Furthermore, the likelihood of mothers in the intervention group feeding their children native leafy greens was almost 10 times greater than in the control group (adjusted odds ratio (aOR): 9.5; 95% CI: 4.37, 20.21; p < 0.001). Two studies that also used educational sessions associated with other activities as part of their positive dietary outcomes also presented an increased consumption frequency of imported drinks with sugar and flour products [49] and imported vegetables [50]. One study that used educational sessions in combination with gardening activities presented low self-rated consumed food such as blueberries (3.00 = occasionally), raspberries (2.72 = a little/occasionally), and fish (2.72 = a little/occasionally) [48].
Seven studies (36.8%) analysed nutrient intake using FFQ [51,53,56] or 24-h recall [44,52] or a combination of both [45,49], and all reported improvements in some nutrients, including carbohydrates; protein; dietary fibre; vitamins A, C, and E; calcium; iron; sodium; and long-chain omega-3 fatty acids, along with reduced saturated fats and cholesterol [44,45,49,51,52,53,56]. However, three studies [44,51,56] did not provide statistical analyses. Nevertheless, some studies observed decreases in certain nutrients, such as reduced vitamin C [52], protein, and carbohydrates [53]. Reductions in carbohydrates, saturated fat, and cholesterol were associated with decreased consumption of unhealthy foods which were de-promoted by some studies [49,53]. Different strategies were used in the interventions presenting nutrient intake improvements, with most studies using educational materials or sessions associated with other activities. However, it is also important to highlight that, from seven studies with nutrient improvements, three studies used food distribution as an activity [44,52,56].
Englberger et al. [45], utilising a combined intervention with workshops, media campaigns, and youth activities such as youth drama clubs to promote yellow native foods rich in vitamin A, such as yellow-fleshed banana, giant swamp taro, and breadfruit, demonstrated a significant increase in provitamin A carotenoid intake from 227 μg/person to 475 μg/person (p = 0.02), attributed to the increase consumption of these promoted native foods. Kaufer et al. [49] also showed that yellow-fleshed bananas, giant swamp taro, and breadfruit combined with other native vegetables contributed to 36–98% of overall micronutrient intake, including 97% of vitamin C, 44% of calcium, 36% of iron, and an increased in beta-carotene equivalents (BCEs), among community members in Pohnpeian, FSM. In Ecuador, the “Corazon en Familia” program—a 12-day cooking session involving mothers and Elders—revealed that native foods such as nettle and dock contributed significantly to the daily recommended intake of nutrients for their children, accounting for 6.7% of iron, 27.5% of folate, and 25.5% of magnesium [51].
The Dali Food System, a 15-year community-led initiative in India that distributes different native foods, such as sorghum, millet, pulses, and wild fruits, reported statistically significant improvements among mothers in the intervention group for energy intake (11,189 ± 3335 kJ vs. 10,193 ± 3738 kJ; p = 0.04), protein intake (68.9 ± 22.6 g vs. 60.4 ± 23.8 g; p < 0.01), dietary fibre (40.8 ± 19.6 g vs. 32.5 ± 19.3 g; p < 0.01), and iron intake (15.8 ± 6.6 mg vs. 13.7 ± 9.1 mg; p < 0.01) [52]. However, a significant reduction in vitamin C intake was also observed (19.7 ± 35.5 mg vs. 21.7 ± 26.1 mg; p = 0.04) [52].
Health Outcomes
Four studies (21.1%) reported some health outcomes. Two studies presented statistically significant positive impacts [53,56], one study reported positive impacts without statistics, and one found no significant improvements [45]. The randomised controlled trial by Lewis et al. [56], conducted among Greenlandic native communities, compared a traditional marine diet (due to their high protein and fat content alongside low carbohydrate levels) with a Western diet through native salmon distribution and educational materials. The intervention group consuming a traditional diet with native salmon for four weeks showed improved daily glucose control (mean daily blood glucose decrease of 0.17 mmol/L-95% CI 0.05, 0.29; p = 0.006; maximum daily blood glucose decrease of 0.26 mmol/L-95% CI 0.06, 0.46; p = 0.010), increased HDL levels, reduced cholesterol ratio by 4% (95% CI 1, 9; p = 0.018), and reduced weight (average weight loss of 0.5 kg; 95% CI 0.09, 0.90; p = 0.016). Kolahdooz et al. [53], in Canada, used a multi-component intervention for 12 months (educational sessions, cooking activities, community events, and media campaigns) to increase the visibility and accessibility of healthy foods, including native ones, such as some marine animals and local berries. The authors reported a reduction in BMI among the intervention group. Participants in a 2-year qualitative study in Canada reported that gardening activities contributed to their mental health [43].
Positive Cultural Impacts
Nine studies (47.4%) used interviews, focus groups, photovoice, observations, and surveys to capture participants’ perceptions and feelings about the interventions, and all of them presented some positive cultural impacts [39,40,41,42,43,48,49,51,54]. Participants in studies involving media campaigns reported a reduction in social discrimination and more positive attitudes toward native foods [39,49]. Land-based activities such as gardening and gathering native foods in the forest were linked to wellbeing, life satisfaction, and healing from past trauma [42,43,48].
Participatory approaches and culturally appropriate activities such as community events celebrating Indigenous culture and foods [39,43,54], incorporation of Indigenous languages in dishes and activities [39,43,51], and garden and kitchen activities led by elders sharing traditional knowledge [40,41,42,43,51] were associated with enhanced identity, pride, belonging, sense of ownership, empowerment, commitment, food sovereignty, healing, connection with the community, and improved relationships. Participants in the “Feast for the Future” program in the USA expressed a strong sense of ownership and commitment due to the community participatory approach used in the intervention [41]. In the “Local Food to School” program in Canada, participants noted that gardening activities and educational sessions on land management and traditional food practices on land contributed to healing from past traumas [43]. Participants from the “Learning Garden Program” also reported improvements in health, life satisfaction, and community connectedness through activities like harvesting and locating edible berries in the forest [48].
Increased Knowledge
Nine studies (47.4%) that reported knowledge improvements used educational sessions. Of those, eight studies associated it with other activities, such as community events, gardening, cooking activities, and others. The outcomes included improved traditional food knowledge, increased awareness of healthy eating, and skills for growing and preparing food [41,42,43,47,48,49,50,54]. Kindergarten students in the USA’s “Veggies for kids” program demonstrated significant improvements (p < 0.01) in identifying asparagus, squash, lemon, spinach, and blueberry and showed an increased willingness to try squash after the intervention, which included educational sessions and gardening activities.
Food Security
Three studies (15.8%) discussed food security outcomes. Two studies using food distribution in combination with other activities showed positive outcomes [42,57]. Blanchet et al. [57], in a cross-sectional study evaluating the Skaha Lake program in Canada, showed that 80.6% of participants considered traditional food important for household food security, and household access to salmon (p = 0.0216) and receiving salmon from a community member (p = 0.040) were significantly associated with cultural food security. McEachern et al. [42] highlighted that school food programs played a significant role in food security and sovereignty among participants, though without statistical support. However, Stroink and Nestor [48], using educational sessions with gardening activities, found that even though participants used their gardening skills to grow their own foods, perceived food security remained linked to the availability and affordability of food in grocery stores, rather than local food sources. Studies that incorporated decision making in local policies or guidelines aimed to support and sustain the interventions [40,41,57].
Challenges
All the studies underscored the benefits of incorporating native foods into community interventions. However, they also highlighted barriers such as limited access and knowledge about native foods due to the loss of family connection [57], challenges imposed by history and colonisation [41], seasonality, high cost, unreliable funding, food regulations that hinder the integration of native foods into current food systems [42], and a lack of space for cultivation [50].
4. Discussion
Findings from this scoping review highlight that native foods may play an important role in enhancing food security, nutrient intake, and promoting wellbeing in Indigenous communities. However, more details about their nutritional composition are needed to evaluate their real contributions to dietary quality. Except for three studies [45,49,55] that explicitly linked the nutritional composition of the native foods to the specific outcomes, such as vitamin A and omega-3 polyunsaturated fats, other studies did not provide detailed nutritional information about these foods, which limits the full assessment of their direct nutritional impacts. Moreover, studies reporting changes in nutrient intake applied different tools, such as FFQ and 24-h recalls, which can impact the consistency and comparability of the findings.
Self-reported health outcomes, such as the improvement in mental health reported in one study [43], could benefit from the use of validated assessment tools in future research to enhance the reliability of the findings. Two studies [44,54] that scored lower than 50% on the quality appraisal may have had some biases in their specific results. However, their inclusion did not interfere with the overall results of this scoping review, as the findings were also supported by other more rigorous studies included in this review—improvement in micronutrient intake, diet quality, and community engagement.
Previous research has also shown significant improvements in dietary and nutrient intake resulting from multicomponent interventions using native foods. Redmon et al. [58] conducted a randomised controlled trial in Native American communities to prevent obesity, employing cooking demonstrations, taste testing in local food stores, school lessons on native foods and traditional food practices, educational materials, and media campaigns. These interventions aimed to encourage the consumption of healthy foods, including native ones, while discouraging the consumption of ultra-processed foods like sweetened breakfast cereals. The study found a greater decrease in the carbohydrate, total fat, saturated fat, and monounsaturated fat intake in the intervention group (p < 0.05). However, there was no statistically significant reduction in total sugar intake. Other studies have also highlighted the importance of native foods for micronutrient intake, including iron, calcium [59], vitamin A, and zinc [60]. Gagné et al. [61] evaluated the impact of native food consumption on the nutrient intake of preschool Inuit children in Nunavik. They observed that, despite low native food consumption, children who consumed native foods had significantly (p < 0.05) higher intakes of protein, iron, zinc, copper, phosphorus, selenium, riboflavin, vitamin B12, niacin, and pantothenic acid, alongside lower intakes of energy and carbohydrates. These findings support the potential of native foods to contribute to healthier dietary patterns due to their nutrient density [1,2].
Similarly to this review, other studies also reported the significance of native foods in enhancing food security within Indigenous communities [62,63,64,65,66,67]. McKerchar et al. [68] highlighted the importance of native foods in supplying and providing income to Maori people, which enhanced food security. Ferguson et al. [69] reported that 40% of the 76% of food-insecure individuals from remote Aboriginal communities in the Northern Territory, Australia, consumed native foods during these periods of food insecurity. However, the literature also highlights that access to native foods is one of the most significant barriers to food security for First Nations peoples, stemming from colonisation, cultural loss, environmental degradation, and negligent policies [70]. This lack of access of native foods, mainly in urban areas [71], can be one of the causes of the perceived food security being still strongly associated with the availability and affordability of foods in grocery stores, found in one of the studies in this review [48]. Canada’s Indigenous Food Bank program used a food distribution intervention to make fruits and vegetables, including native ones, more accessible to Indigenous people living in urban areas [72]. Participants noted the importance of this type of program for food security and empowerment through culturally appropriate foods [72].
Findings from this scoping review also showed that interventions using native foods, which positively impact nutrient intake, can be linked to preventing chronic diseases such as diabetes and cardiovascular diseases [56] and improving mental health [43]. Similarly, Birch et al. [73] and Pour et al. [74] also suggested that some Australian native grains may prevent non-communicable diseases such as diabetes and heart disease due to their nutritional composition and bioactive compounds, such as phenolic and polyunsaturated fatty acids. Additional studies also showed that some traditional food practices such as gathering, fishing, hunting, and eating native foods can improve mental health, as they foster cultural identity, nutritional health, and holistic well-being among First Nations peoples [75,76]. Studies show that native foods can also promote sustainable practices and foster cultural identity, enhancing communities’ health, healing, and resilience [66,67].
Most studies in this review used multicomponent strategies, combining educational sessions with hands-on activities such as gardening and cooking, food distribution, community engagement, and media campaigns to increase knowledge and achieve nutritional and health outcomes. Similarly, Gumelar and Tangpukdee [77] used video recordings and booklets focused on local and native foods in Indonesia and reported a significant increase in mothers’ knowledge and improvements in children’s anthropometry after the intervention (p < 0.05). Lee et al. [78] support the idea that multicomponent interventions are necessary to enhance nutrition and health outcomes among First Nations peoples, including economic strategies, food supplementation, food supply, and community-directed programs. Browne et al. [79] analysed previous programs addressing diet-related health outcomes for Aboriginal and Torres Strait Islander peoples. They found that multicomponent interventions involving community members in the development, implementation, and evaluation stages are more likely to succeed.
All twelve studies using participatory methods in this review reported significant cultural impacts, such as cultural revitalisation, healing from past traumas, and improved relationships. Involving community members in all stages of the program or intervention—design, implementation, evaluation, and dissemination of results—fostered a sense of ownership, collaboration, respect, and reciprocity, leading to more sustainable nutritional and health outcomes [80,81]. Moreover, participatory methods can better address the community’s real needs through culturally relevant solutions [80,81].
Since 2007, the United Nations Declaration on the Rights of Indigenous Peoples (UNDRIP) has provided a framework to support the rights of First Nations peoples globally [82]. This foundational international human rights instrument emphasises Indigenous peoples’ rights to make decision in any research and policies that impact their lives [80,82,83,84]. Aligning programs and interventions with this framework allows these populations co-create knowledge and increase the effectiveness and relevance of policies and research [80].
In the context of integrating native foods into our food systems, particularly within Indigenous communities, several UNDRIP articles explicitly recognise Indigenous peoples’ rights in policies and research related to this topic [28]. Article 24 affirms their right to maintain their health systems and traditional plants [28]. Article 13 recognises Indigenous rights to revitalise and transmit their knowledge, supporting and promoting traditional food practices, including native foods [28]. These articles acknowledge the importance of traditional food practices among these communities in promoting health [28,80,84]. In terms of how it should be done, three other articles can guide research and policies regarding this topic. Articles 4 and 18 recognise Indigenous self-determination and the right to participate in any decision-making processes about their lives [28]. Article 26 asserts Indigenous rights to access all traditionally owned resources, such as land to manage sustainable and traditional practices and maintain food systems that align with their cultural values [28]. Finally, Article 31 emphasises the right of Indigenous peoples to control, protect, and develop their culture and traditional knowledge, which protects the intellectual property of Indigenous food-related knowledge and practices, ensuring that research and policies benefit communities while preserving their cultural integrity [28,84].
While all studies in this review aligned in some way with the UNDRIP by integrating native foods into communities’ diets, not all clearly stated the participatory approach used to ensure Indigenous self-determination and sovereignty. Barriers mentioned in the studies, such as loss of cultural connections and knowledge about these foods and lack of space to grow their foods, remain significant challenges to ensure more ethical integrity in programs and policies using native foods.
5. Strengths and Limitations
This review offers a comprehensive understanding of the diverse ways in which native foods have been integrated into health and nutrition interventions, showing their potential to improve health, enhance cultural identity, and address food security issues within Indigenous communities. This broad scope allows for a deeper understanding of the flexibility and adaptability of multicomponent interventions and their contributions to some specific outcomes, providing valuable guidance for future programs and policy development.
Our scoping review has highlighted some gaps in the existing literature that require further investigation. These include the need for more detailed information on the nutritional composition of native foods to better understand their contributions to nutrient intake improvements. Additionally, future research should aim to establish clearer links between specific activities within interventions and their outcomes. Addressing these gaps will provide a more comprehensive approach to how native foods can be effectively utilised to improve health outcomes, particularly in Indigenous communities. For practice, our scoping review offers valuable insights for health promotion officers and policymakers, for example, regarding the importance of media campaigns to reduce discrimination against these foods, food distribution to address food security, and culturally safe approaches for health promotion interventions involving Indigenous communities.
Nevertheless, the wide range of strategies included in the review also presented a significant limitation. The broad variety of activities, diverse outcomes, and study designs reported made it challenging to directly and statistically link specific strategies to specific outcomes. Therefore, the individual contribution of each activity to observed outcomes could not be clearly established. This complexity made it impractical to conduct a more detailed systematic review or meta-analysis, which would have provided a clearer understanding of the effectiveness of each strategy. Future research should consider focusing on more targeted interventions and utilising standardised outcome measures to better evaluate which specific activities lead to outcomes.
While every effort was made to conduct a comprehensive search, we may have missed some relevant studies, particularly those published in other languages or indexed in other databases.
6. Conclusions
The findings from this review show the potential of multicomponent interventions using native foods to support dietary improvements, health outcomes, and cultural revitalisation within Indigenous communities. Additionally, culturally safe interventions that actively involved elders and community members in all steps of the program foster food sovereignty and community empowerment. We acknowledge that the nutrient-rich properties of native foods are also attributed to their minimal processing, rather than solely to their origin. Moreover, it is important to note that the urban lifestyle, such as social interactions and physical activity levels, has profoundly impacted Indigenous health, highlighting the need for future research to explore its association with the consumption of native foods and its impacts. However, despite the reported benefits, significant barriers such as the loss of traditional knowledge, limited access to native foods, and lack of policy support continue being significant challenges. Aligning future programs with the United Nations Declaration on the Rights of Indigenous Peoples (UNDRIP) can promote greater Indigenous self-determination and sovereignty in food practices. Interventions must prioritise participatory approaches, ensuring Indigenous voices guide the design, implementation, and evaluation stages.
Author Contributions
Conceptualisation: C.V.A.L.; Data collection (screening and extraction): C.V.A.L. and J.L.d.S.A.N.; Data analysis: C.V.A.L.; Original draft: C.V.A.L.; Revision: S.M., R.R., J.H. and J.L.d.S.A.N. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Acknowledgments
The authors would like to thank the librarian Jeremy Cullis for his guidance and advice on this review. C.V.A.L. was supported by the International Macquarie University Research Excellence Scholarship (iMQRES) from Macquarie University.
Conflicts of Interest
The authors declare no conflicts of interest.
Appendix A. Search Strategy
Table A1.
Search strategy employed in the review.
Appendix B. Characteristics of Included Individual Studies
Table A2.
Characteristics of included individual studies (n = 19).
Appendix C. Participatory Approach Used by the Studies
Table A3.
Participatory approach used by the studies (n = 19).
Appendix D. Quality Assessment
Table A4.
Quality assessment based on Mixed Method Appraisal Tool—MMAT (n = 19).
References
- Akinola, R.; Pereira, L.M.; Mabhaudhi, T.; de Bruin, F.-M.; Rusch, L. A Review of Indigenous Food Crops in Africa and the Implications for more Sustainable and Healthy Food Systems. Sustainability 2020, 12, 3493. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lopes, C.V.A.; Mihrshahi, S.; Ronto, R.; Hunter, J. Aboriginal Food Practices and Australian Native Plant-Based Foods: A Step toward Sustainable Food Systems. Sustainability 2023, 15, 11569. [Google Scholar] [CrossRef] [Scilit]
- Kuhnlein, H.V.; Erasmus, B.; Spigelski, D. Indigenous Peoples’ Food Systems: The Many Dimensions of Culture, Diversity and Environment for Nutrition and Health; Food and Agriculture Organization of the United Nations: Rome, Italy, 2009; Available online: https://www.cabidigitallibrary.org/doi/full/10.5555/20093209327 (accessed on 10 November 2024).
- Sarkar, D.; Walker-Swaney, J.; Shetty, K. Food Diversity and Indigenous Food Systems to Combat Diet-Linked Chronic Diseases. Curr. Dev. Nutr. 2020, 4, 3–11. [Google Scholar] [CrossRef] [Scilit]
- Kuhnlein, H.V. Gender roles, food system biodiversity, and food security in Indigenous Peoples’ communities. Matern. Child Nutr. 2017, 13, e12529. [Google Scholar] [CrossRef] [Scilit]
- Kuhnlein, H.; Eme, P.; Larrinoa, Y.D. Indigenous food systems: Contributions to sustainable food systems and sustainable diets. In Sustainable Diets: Linking Nutrition and Food Systems; CABI: Wallingford, UK, 2019; pp. 64–78. [Google Scholar] [CrossRef] [Scilit]
- Shahunja, K.; Ushula, T.W.; Hussain, M.A.; Pati, S.; Mamun, A.A. Multimorbidity among the Indigenous population: A systematic review and meta-analysis. Ann. Epidemiol. 2024, 98, 8–17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cheran, K.; Murthy, C.; A Bornemann, E.; Kamma, H.K.; Alabbas, M.; Abid, N.; Manaye, S.; Venugopal, S.; Bornemann, E.A.; Elashahab, M. The Growing Epidemic of Diabetes Among the Indigenous Population of Canada: A Systematic Review. Cureus 2023, 15, e36173. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carman, W.; Ishida, M.; Trounson, J.S.; Mercer, S.W.; Anindya, K.; Sum, G.; Armstrong, G.; Oldenburg, B.; McPake, B.; Lee, J.T. Epidemiology of physical–mental multimorbidity and its impact among Aboriginal and Torres Strait Islander in Australia: A cross-sectional analysis of a nationally representative sample. BMJ Open 2022, 12, e054999. [Google Scholar] [CrossRef] [Scilit]
- Hare, M.J.L.; Zhao, Y.; Guthridge, S.; Burgess, P.; Barr, E.L.M.; Ellis, E.; Butler, D.; Rosser, A.; Falhammar, H.; Maple-Brown, L.J. Prevalence and incidence of diabetes among Aboriginal people in remote communities of the Northern Territory, Australia: A retrospective, longitudinal data-linkage study. BMJ Open 2022, 12, e059716. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Australian Institute of Health and Welfare (Canberra: AIHW). Determinants of Health for First Nations People; Australian Institute of Health and Welfare: Canberra, Australia, 2024. Available online: https://www.aihw.gov.au/reports/australias-health/social-determinants-and-indigenous-health (accessed on 10 November 2024).
- Cunningham, J.; Paradies, Y.C. Patterns and correlates of self-reported racial discrimination among Australian Aboriginal and Torres Strait Islander adults, 2008–2009: Analysis of national survey data. Int. J. Equity Health 2013, 12, 47. [Google Scholar] [CrossRef] [Scilit]
- Australian Bureau of Statistics (ABS Canberra). Australian Aboriginal and Torres Strait Islander health Survey: Nutrition Results–Food and Nutrients, 2012–2013; Australian Bureau of Statistics: Canberra, Australia, 2015. Available online: https://www.abs.gov.au/ausstats/abs@.nsf/Lookup/4727.0.55.005main+features12012-13 (accessed on 10 November 2024).
- Banerji, A.; Pelletier, V.A.; Haring, R.; Irvine, J.; Bresnahan, A.; Lavallee, B. Food insecurity and its consequences in indigenous children and youth in Canada. PLOS Glob. Public Health 2023, 3, e0002406. [Google Scholar] [CrossRef] [Scilit]
- Shafiee, M.; Keshavarz, P.; Lane, G.; Pahwa, P.; Szafron, M.; Jennings, D.; Vatanparast, H. Food Security Status of Indigenous Peoples in Canada According to the 4 Pillars of Food Security: A Scoping Review. Adv. Nutr. Int. Rev. J. 2022, 13, 2537–2558. [Google Scholar] [CrossRef] [Scilit]
- Gracey, M.; King, M. Indigenous Health Part 1: Determinants and Disease Patterns. Lancet 2009, 374, 65–75. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Paradies, Y.C.; Cunningham, J. The DRUID study: Racism and self-assessed health status in an indigenous population. BMC Public Health 2012, 12, 131. [Google Scholar] [CrossRef] [Scilit]
- Paradies, Y. Colonisation, racism and indigenous health. J. Popul. Res. 2016, 33, 83–96. [Google Scholar] [CrossRef] [Scilit]
- Dudgeon, P.; Blustein, S.; Bray, A.; Calma, T.; McPhee, R.; Ring, I. Connection between family, kinship and social and emotional wellbeing. In Produced for the Indigenous Mental and Suicide Prevention Clearninghouse; AIHW: Canberra, Australia, 2021. Available online: https://www.indigenousmhspc.gov.au/getattachment/e129c621-58a4-4966-8730-dcf6e3a533a8/dudgeon-et-al-2021-family-kinship-20210802.pdf (accessed on 10 November 2024).
- Newton, J. The Oldest Foods on Earth: A History of Australian Native Foods with Recipes; NewSouth: Sydney, Australia, 2016. [Google Scholar]
- Australian Government. Department of Health and Aged Care National Aboriginal and Torres Strait Islander Health Plan 2021–2031; Australian Government: Canberra, Australia, 2021.
- Bokelmann, W.; Huyskens-Keil, S.; Ferenczi, Z.; Stöber, S. The role of indigenous vegetables to improve food and nutrition security: Experiences from the project HORTINLEA in Kenya (2014–2018). Front. Sustain. Food Syst. 2022, 6, 806420. [Google Scholar] [CrossRef] [Scilit]
- Egeland, G.M.; Harrison, G.G. Health Disparities: Promoting Indigenous Peoples’ Health Through Traditional Food Systems and Self-Determination. In Indigenous Peoples’ Food Systems and Well-Being: Interventions and Policies for Healthy Communities; Food and Agriculture Organization of the United Nations: Rome, Italy, 2013. [Google Scholar]
- Jernigan, V.B.B.; Maudrie, T.L.; Nikolaus, C.J.; Benally, T.; Johnson, S.; Teague, T.; Mayes, M.; Jacob, T.; Taniguchi, T. Food Sovereignty Indicators for Indigenous Community Capacity Building and Health. Front. Sustain. Food Syst. 2021, 5, 704750. [Google Scholar] [CrossRef] [Scilit]
- Jernigan, V.B.B.; Taniguchi, T.; Nguyen, C.J.; London, S.M.; Henderson, A.; Maudrie, T.L.; Blair, S.; Clyma, K.R.; Lopez, S.V.; Jacob, T. Food Systems, Food Sovereignty, and Health: Conference Shares Linkages to Support Indigenous Community Health. Heal. Promot. Pract. 2023, 24, 1109–1116. [Google Scholar] [CrossRef] [Scilit]
- Ogundiran, A. Food Security, Food Sovereignty, and Indigenous Knowledge. Afr. Archaeol. Rev. 2019, 36, 343–346. [Google Scholar] [CrossRef] [Scilit]
- Weiler, A.M.; Hergesheimer, C.; Brisbois, B.; Wittman, H.; Yassi, A.; Spiegel, J.M. Food sovereignty, food security and health equity: A meta-narrative mapping exercise. Heal. Policy Plan. 2015, 30, 1078–1092. [Google Scholar] [CrossRef] [Scilit]
- United Nations General Assembly. Division for Inclusive Social Development (DISD). In United Nations Declaration on the Rights of Indigenous Peoples; United Nations: Rome, Italy, 2007; pp. 1–18. Available online: https://social.desa.un.org/issues/indigenous-peoples/united-nations-declaration-on-the-rights-of-indigenous-peoples (accessed on 10 November 2024).
- Macaulay, A.C. Participatory research: What is the history? Has the purpose changed? Fam. Pract. 2016, 34, 256–258. [Google Scholar] [CrossRef] [Scilit]
- Collins, S.E.; Clifasefi, S.L.; Stanton, J.; The Leap Advisory Board; Straits, K.J.E.; Gil-Kashiwabara, E.; Espinosa, P.R.; Nicasio, A.V.; Andrasik, M.P.; Hawes, S.M.; et al. Community-based participatory research (CBPR): Towards equitable involvement of community in psychology research. Am. Psychol. 2018, 73, 884–898. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Palma, M.A.; Collart, A.J.; Chammoun, C.J. Information Asymmetry in Consumer Perceptions of Quality-Differentiated Food Products. J. Consum. Aff. 2015, 49, 596–612. [Google Scholar] [CrossRef] [Scilit]
- Dissanayake, I.H.; Zak, V.; Kaur, K.; Jaye, K.; Ayati, Z.; Chang, D.; Li, C.G.; Bhuyan, D.J. Australian native fruits and vegetables: Chemical composition, nutritional profile, bioactivity and potential valorization by industries. Crit. Rev. Food Sci. Nutr. 2023, 63, 8511–8544. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maudrie, T.L.; Nguyen, C.J.; Wilbur, R.E.; Mucioki, M.; Clyma, K.R.; Ferguson, G.L.; Jernigan, V.B.B. Food Security and Food Sovereignty: The Difference Between Surviving and Thriving. Health Promot. Pract. 2023, 24, 1075–1079. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Galli, F. Traditional food: Definitions and nuances. In Case Studies in the Traditional Food Sector; Elsevier: Amsterdam, The Netherlands, 2018; pp. 3–24. [Google Scholar] [CrossRef] [Scilit]
- Bôto, J.M.; Rocha, A.; Miguéis, V.; Meireles, M.; Neto, B. Sustainability Dimensions of the Mediterranean Diet: A Systematic Review of the Indicators Used and Its Results. Adv. Nutr. Int. Rev. J. 2022, 13, 2015–2038. [Google Scholar] [CrossRef] [Scilit]
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.J.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMA-ScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit]
- Arksey, H.; O’Malley, L. Scoping studies: Towards a methodological framework. Int. J. Soc. Res. Methodol. 2005, 8, 19–32. [Google Scholar] [CrossRef] [Scilit]
- Hong, Q.N.; Fàbregues, S.; Bartlett, G.; Boardman, F.; Cargo, M.; Dagenais, P.; Gagnon, M.-P.; Griffiths, F.; Nicolau, B.; O’cathain, A.; et al. The Mixed Methods Appraisal Tool (MMAT) version 2018 for information professionals and researchers. Educ. Inf. 2018, 34, 285–291. [Google Scholar] [CrossRef] [Scilit]
- Iwasaki-Goodman, M. Transmitting Ainu traditional food knowledge from mothers to their daughters. Matern. Child Nutr. 2017, 13, e12555. [Google Scholar] [CrossRef] [Scilit]
- Cueva, K.; Speakman, K.; Neault, N.; Richards, J.; Lovato, V.; Parker, S.; Carroll, D.; Sundbo, A.; Barlow, A. Cultural Connectedness as Obesity Prevention: Indigenous Youth Perspectives on Feast for the Future. J. Nutr. Educ. Behav. 2020, 52, 632–639. [Google Scholar] [CrossRef] [Scilit]
- Cueva, K.; Lovato, V.; Carroll, D.; Richards, J.; Speakman, K.; Neault, N.; Barlow, A. A Qualitative Evaluation of a Community Based, Culturally Relevant Intervention to Promote Healthy Food Access in American Indian Communities. J. Community Health 2020, 45, 458–464. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McEachern, L.W.; Yessis, J.; Yovanovich, J.; Crack, S.; Zupko, B.; Valaitis, R.; Hanning, R.M. Implementation of the Learning Circle: Local Food to School Initiative in the Island Communities of Haida Gwaii, British Columbia, Canada—A Descriptive Case Study. Curr. Dev. Nutr. 2022, 6, nzac090. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McEachern, L.W.; Harris, S.; Valaitis, R.; Watson, A.; Yessis, J.; Zupko, B.; Hanning, R.M. Learning Circles: A Collaborative Approach to Enhance Local, Healthy and Traditional Foods for Youth in the Northerly Community of Hazelton/Upper Skeena, British Columbia, Canada. Int. J. Environ. Res. Public Health 2022, 19, 15878. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leslie, J.H. Uli’eo Koa Program: Incorporating a traditional Hawaiian dietary component. Pacific health dialog: A publication of the Pacific Basin Officers Training Program and the Fiji School of Medicine. Pac. Health Dialog 2001, 8, 401–406. [Google Scholar]
- Englberger, L.; Kuhnlein, H.V.; Lorens, A.; Pedrus, P.; Albert, K.; Currie, J.; Pretrick, M.; Jim, R.; Kaufer, L. Pohnpei, FSM case study in a global health project documents its local food resources and successfully promotes local food for health. Pac. Health Dialog 2010, 16, 129–136. [Google Scholar]
- Mbhatsani, V.H.; Mbhenyane, X.G.; Mabapa, S.N. Development and Implementation of Nutrition Education on Dietary Diversification for Primary School Children. Ecol. Food Nutr. 2017, 56, 449–461. [Google Scholar] [CrossRef] [Scilit]
- Emm, S.; Harris, J.; Halterman, J.; Chvilicek, S.; Bishop, C. Increasing Fruit and Vegetable Intake with Reservation and Off-reservation Kindergarten Students in Nevada. J. Agric. Food Syst. Community Dev. 2019, 9, 1–10. [Google Scholar] [CrossRef] [Scilit]
- Stroink, M.L.; Nelson, C.H. Aboriginal Health Learning in the Forest and Cultivated Gardens: Building a Nutritious and Sustainable Food System. J. Agromed. 2009, 14, 263–269. [Google Scholar] [CrossRef] [Scilit]
- Kaufer, L.; Englberger, L.; Cue, R.; Lorens, A.; Albert, K.; Pedrus, P.; Kuhnlein, H.V. Evaluation of a “traditional food for health” intervention in Pohnpei, Federated States of Micronesia. Pac. Health Dialog 2010, 16, 61–73. [Google Scholar]
- Hanson, M.; Englberger, L.; Duncan, B.; Taren, D.; Mateak, H.; Johnson, E. An evaluation of a nutrition intervention in Kapinga Village on Pohnpei, Federated States of Micronesia. Pac. Health Dialog. 2011, 17, 173–184. [Google Scholar]
- Roche, M.L.; Ambato, L.; Sarsoza, J.; Kuhnlein, H.V. Mothers’ groups enrich diet and culture through promoting traditional Quichua foods. Matern. Child Nutr. 2017, 13, e12530. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schmid, M.; Salomeyesudas, B.; Satheesh, P.; Hanley, J.; Kuhnlein, H.V. Intervention with traditional food as a major source of energy, protein, iron, vitamin C and vitamin A for rural Dalit mothers and young children in Andhra Pradesh, South India. Asia Pac. J. Clin. Nutr. 2007, 16, 84–93. [Google Scholar] [PubMed]
- Kolahdooz, F.; Pakseresht, M.; Mead, E.; Beck, L.; Corriveau, A.; Sharma, S. Impact of the Healthy Foods North nutrition intervention program on Inuit and Inuvialuit food consumption and preparation methods in Canadian Arctic communities. Nutr. J. 2014, 13, 68. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bersamin, A.; Izumi, B.T.; Nu, J.; O’brien, D.M.; Paschall, M. Strengthening adolescents’ connection to their traditional food system improves diet quality in remote Alaska Native communities: Results from the Neqa Elicarvigmun Pilot Study. Transl. Behav. Med. 2019, 9, 952–961. [Google Scholar] [CrossRef] [Scilit]
- Oppezzo, M.; Knox, M.; Skan, J.; Chieng, A.; Crouch, M.; Aikens, R.C.; Benowitz, N.L.; Schnellbaecher, M.; Prochaska, J.J. Traditional Heart-Healthy Diet and Medication Adherence in the Norton Sound Region: An 18-Month Telehealth Intervention. Int. J. Environ. Res. Public Health 2022, 19, 9885. [Google Scholar] [CrossRef] [Scilit]
- Lewis, J.I.; Lind, M.V.; Møller, G.; Hansen, T.; Pedersen, H.; Christensen, M.M.; Laursen, J.C.; Nielsen, S.; Ottendahl, C.B.; Larsen, C.V.; et al. The effect of traditional diet on glucose homoeostasis in carriers and non-carriers of a common TBC1D4 variant in Greenlandic Inuit: A randomised crossover study. Br. J. Nutr. 2023, 130, 1871–1884. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Blanchet, R.; Willows, N.; Johnson, S.; Okanagan Nation Salmon Reintroduction Initiatives; Batal, M. Enhancing cultural food security among the Syilx Okanagan adults with the reintroduction of Okanagan sockeye salmon. Appl. Physiol. Nutr. Metab. 2022, 47, 124–133. [Google Scholar] [CrossRef] [Scilit]
- Redmond, L.C.; Wensel, C.R.; Estradé, M.; Fleischhacker, S.E.; Poirer, L.; Jock, B.W.I.; Gittelsohn, J. Dietary Outcomes of a Multilevel, Multicomponent, Cluster Randomized Obesity Intervention in 6 Native American Communities in the Upper Midwest and Southwest United States. Curr. Dev. Nutr. 2023, 7, 100043. [Google Scholar] [CrossRef] [Scilit]
- Ghosh-Jerath, S.; Singh, A.; Lyngdoh, T.; Magsumbol, M.S.; Kamboj, P.; Goldberg, G. Estimates of Indigenous Food Consumption and Their Contribution to Nutrient Intake in Oraon Tribal Women of Jharkhand, India. Food Nutr. Bull. 2018, 39, 581–594. [Google Scholar] [CrossRef] [Scilit]
- Kasimba, S.; Covic, N.; Motswagole, B.; Laubscher, R.; Claasen, N. Consumption of Traditional and Indigenous Foods and Their Contribution to Nutrient Intake among Children and Women in Botswana. Ecol. Food Nutr. 2019, 58, 281–298. [Google Scholar] [CrossRef] [Scilit]
- Gagné, D.; Blanchet, R.; Lauzière, J.; Vaissière, E.; Vézina, C.; Ayotte, P.; Déry, S.; O’Brien, H.T. Traditional food consumption is associated with higher nutrient intakes in Inuit children attending childcare centres in Nunavik. Int. J. Circumpolar Health 2012, 71, 18401. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Elliott, B.; Jayatilaka, D.; Brown, C.; Varley, L.; Corbett, K.K. “We Are Not Being Heard”: Aboriginal Perspectives on Traditional Foods Access and Food Security. J. Environ. Public Health 2012, 2012, 130945. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smith, E.; Ahmed, S.; Dupuis, V.; Crane, M.R.; Eggers, M.; Pierre, M.; Flagg, K.; Shanks, C.B. Contribution of Wild Foods to Diet, Food Security, and Cultural Values Amidst Climate Change. J. Agric. Food Syst. Community Dev. 2019, 9, 191–214. [Google Scholar] [CrossRef] [Scilit]
- Walch, A.; Loring, P.; Johnson, R.; Tholl, M.; Bersamin, A. Traditional Food Practices, Attitudes, and Beliefs in Urban Alaska Native Women Receiving WIC Assistance. J. Nutr. Educ. Behav. 2019, 51, 318–325. [Google Scholar] [CrossRef] [Scilit]
- Davies, A.; Gwynn, J.; Allman-Farinelli, M.; Flood, V.; Dickson, M.; Turner, N.; Porykali, B.; Ngiyampaa, M.L. Programs Addressing Food Security for First Nations Peoples: A Scoping Review. Nutrients 2023, 15, 3127. [Google Scholar] [CrossRef] [Scilit]
- Domingo, A.; Charles, K.-A.; Jacobs, M.; Brooker, D.; Hanning, R.M. Indigenous Community Perspectives of Food Security, Sustainable Food Systems and Strategies to Enhance Access to Local and Traditional Healthy Food for Partnering Williams Treaties First Nations (Ontario, Canada). Int. J. Environ. Res. Public Heal. 2021, 18, 4404. [Google Scholar] [CrossRef] [Scilit]
- Kuhnlein, H.V.; Fediuk, K.; Nelson, C.; Howard, E.; Johnson, S. The legacy of the Nuxalk food and nutrition program for food security, health and well-being of indigenous peoples in British Columbia. BC Stud. Br. Columbian Q. 2013, 179, 159–167. [Google Scholar]
- McKerchar, C.; Bowers, S.; Heta, C.; Signal, L.; Matoe, L. Enhancing Māori food security using traditional kai. Glob. Health Promot. 2015, 22, 15–24. [Google Scholar] [CrossRef] [Scilit]
- Ferguson, M.; Brown, C.; Georga, C.; Miles, E.; Wilson, A.; Brimblecombe, J. Traditional food availability and consumption in remote Aboriginal communities in the Northern Territory, Australia. Aust. New Zealand J. Public Health 2017, 41, 294–298. [Google Scholar] [CrossRef] [Scilit]
- Gurney, R.M.; Caniglia, B.S.; Mix, T.L.; Baum, K.A. Native American Food Security and Traditional Foods: A Review of the Literature. Sociol. Compass 2015, 9, 681–693. [Google Scholar] [CrossRef] [Scilit]
- Skinner, K.; Pratley, E.; Burnett, K. Eating in the City: A Review of the Literature on Food Insecurity and Indigenous People Living in Urban Spaces. Societies 2016, 6, 7. [Google Scholar] [CrossRef] [Scilit]
- Richmond, C.; Dokis, B. “We Make It Work Because We Must”: Narrating the Creation of an Urban Indigenous Food Bank in London, Ontario, Canada. Land 2023, 12, 2028. [Google Scholar] [CrossRef] [Scilit]
- Birch, J.; Benkendorff, K.; Liu, L.; Luke, H. The nutritional composition of Australian native grains used by First Nations people and their re-emergence for human health and sustainable food systems. Front. Sustain. Food Syst. 2023, 7, 1237862. [Google Scholar] [CrossRef] [Scilit]
- Pour, T.; Binge, H.; Cross, R.; Moore, K.; Pattison, A.; Brand-Miller, J.; Atkinson, F.; Bell-Anderson, K. Australian native grain reduces blood glucose response and Glycemic Index. Proc. Nutr. Soc. 2024, 83, E48. [Google Scholar] [CrossRef] [Scilit]
- Kuhnlein, H.V.; Receveur, O.; Chan, H.M. Traditional food systems research with Canadian Indigenous Peoples. Int. J. Circumpolar Health 2001, 60, 112–122. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dudgeon, P.; Walker, R.; Scrine, C.; Shepherd, C.; Calma, T.; Ring, I. Effective Strategies to Strengthen the Mental Health and Wellbeing of Aboriginal and Torres Strait Islander People; Australian Government: Canberra, Australia, 2014. Available online: https://www.aihw.gov.au/reports/indigenous-australians/strategies-to-strengthen-mental-health-wellbeing/summary (accessed on 10 November 2024).
- Gumelar, W.R.; Tangpukdee, J. The Effect of Nutrition Education Based on Local Foods on Mothers’ Knowledge and Anthropometry of Malnutrition Children Aged 6 to 21 Months. Malays. J. Nurs. 2022, 14, 53–58. [Google Scholar] [CrossRef] [Scilit]
- Lee, A.J.; Leonard, D.; A Moloney, A.; Minniecon, D.L. Improving Aboriginal and Torres Strait Islander nutrition and health. Med. J. Aust. 2009, 190, 547–548. [Google Scholar] [CrossRef] [Scilit]
- Browne, J.; Adams, K.; Atkinson, P.; Gleeson, D.; Hayes, R. Food and nutrition programs for Aboriginal and Torres Strait Islander Australians: An overview of systematic reviews. Aust. Health Rev. 2017, 42, 689–697. [Google Scholar] [CrossRef] [Scilit]
- Ignace, L.; Burton, L.; Mynott, S.; Meehan, M.; Olson, E.; Steel, J.; Ojeda, J.; Harper, S.; Ramirez, L.; Baker, D.; et al. Researchers’ responsibility to uphold Indigenous rights. Science 2023, 381, 129–131. [Google Scholar] [CrossRef] [Scilit]
- Cunningham, C.; Mercury, M. Coproducing health research with Indigenous peoples. Nat. Med. 2023, 29, 2722–2730. [Google Scholar] [CrossRef] [Scilit]
- Stephens, C.; Porter, J.; Nettleton, C.; Willis, R. UN Declaration on the Rights of Indigenous Peoples. Lancet 2007, 370, 1756. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mazel, O. Indigenous Health and Human Rights: A Reflection on Law and Culture. Int. J. Environ. Res. Public Health 2018, 15, 789. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oldham, P.; Frank, M.A. ‘We the peoples…’: The United Nations Declaration on the rights of indigenous peoples. Anthropol. Today 2008, 24, 5–9. [Google Scholar] [CrossRef] [Scilit]
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).