


Abstract
Somatic genome editing may provide durable treatment for selected cardiovascular diseases, but its translational maturity is organ-dependent. This narrative review compares CRISPR-Cas nucleases, base editors, and prime editors across liver-directed and direct myocardial applications, with emphasis on target biology, delivery, genomic integrity, clinical evidence, and long-term governance. Liver-directed editing of PCSK9, ANGPTL3, and TTR has produced sustained pharmacodynamic effects after one administration in early clinical studies; these findings establish target engagement, not yet reductions in cardiovascular events, reversal of amyloid cardiomyopathy, or lifelong safety. Direct myocardial editing remains preclinical. MYH7 and MYBPC3 studies demonstrate variant-specific disease prevention in selected neonatal or presymptomatic models, but do not establish reversal of mature hypertrophy, fibrosis, dysfunction, or arrhythmia in adult human myocardium. The principal translational divide therefore reflects the convergence of validated target direction, accessible delivery, measurable systemic output, and tolerable editing heterogeneity in the liver, versus the need for allele-selective, spatially distributed correction in an electrically and mechanically coupled heart. We propose an organ-specific translational evidence framework that separates evidence required before first-in-human administration from evidence generated during clinical development. Progress will depend on clinically meaningful outcomes, cell- and region-resolved editing, product-specific genomic safety, credible management of persistent harm, and durable surveillance.
1. Introduction
Cardiovascular diseases (CVDs) remain the leading cause of death and disability-adjusted life-year (DALY) burden worldwide, accounting for an estimated 19.2 million deaths and 437 million DALYs in 2023 [1]. Elevated low-density lipoprotein cholesterol (LDL-C) remains a major modifiable contributor to this burden, accounting for an estimated 3.6 million deaths and 90.7 million DALYs worldwide in 2023 [2]. Although age-standardized LDL-C-attributable mortality and DALY rates have declined substantially since 1990, the absolute burden attributable to elevated LDL-C has continued to increase, largely driven by population growth and aging [2]. These data underscore the persistent need for effective and durable strategies to reduce cardiovascular risk.
Established prevention of atherosclerotic cardiovascular disease (ASCVD) generally requires sustained treatment [3]. The SECURE trial showed that simplifying secondary prevention with a polypill reduced major cardiovascular events after myocardial infarction [4], whereas FOURIER demonstrated that intensive lipid lowering does not eliminate residual risk [5]. Inclisiran reduces dosing frequency and lowers LDL-C by approximately 50%, but still requires repeated administration [6]. These limitations motivate interest in one-time interventions that maintain a biological effect after the therapeutic components have cleared [3].
Therapeutic genome editing offers a fundamentally different approach by permanently modifying an endogenous genomic locus rather than supplying an exogenous gene or transiently inhibiting its transcript [3]. Nuclease-based, base-editing, and prime-editing approaches enable targeted genomic modification through distinct molecular mechanisms [7,8,9,10]. Current clinical development focuses on somatic genome editing rather than intentional modification of the human germline [11]. The permanence of genomic modification is both its principal therapeutic advantage and a major challenge: unlike conventional pharmacological therapies, the effect cannot readily be titrated, withdrawn, or reversed if an unintended genomic alteration produces harm [3]. Accordingly, the therapeutic potential of cardiovascular genome editing depends not only on editing efficiency but also on target selection, tissue specificity, delivery, editing precision, and long-term safety.
The rationale for cardiovascular genome editing is strongest when the intended direction of effect is supported by human genetics. Heterozygous loss-of-function variants in PCSK9 and ANGPTL3 are associated with lifelong reductions in atherogenic lipids and lower coronary risk [12,13]. These natural experiments support target direction, but they do not reproduce a therapeutic exposure that begins in adulthood, may edit hepatocytes unevenly, and creates a product-specific mixture of intended, unintended, and unedited alleles. For TTR, therapeutic disruption is supported by the pathogenic role of circulating transthyretin and by the clinical efficacy of reversible TTR-lowering therapies, rather than by a directly analogous lifelong protective genotype [14]. Thus, human genetics and pharmacology justify target selection, while the safety and benefit of adult somatic editing must be established independently for PCSK9, ANGPTL3, and TTR.
This concept has translated most rapidly into clinical development for liver-directed applications. Early clinical studies of CRISPR-Cas9 editing of hepatic TTR and ANGPTL3, as well as adenine base editing of PCSK9, have demonstrated substantial reductions in circulating disease-related biomarkers following a single administration, with effects persisting during available follow-up [14,15,16]. These studies provide pharmacodynamic proof of concept that liver-directed genome editing can achieve durable modification of clinically validated cardiovascular targets in humans, although cardiovascular-outcome benefit and lifelong safety remain unresolved [3].
In contrast, direct myocardial genome editing remains predominantly preclinical and presents distinct biological and delivery challenges [3]. Experimental studies have demonstrated that AAV-mediated base editing can correct pathogenic variants associated with hypertrophic cardiomyopathy in cardiomyocytes and improve disease-related phenotypes in humanized models [17,18]. However, these studies also highlight the challenges of achieving efficient and selective editing across sufficient numbers of cardiomyocytes while limiting unintended editing and tissue-level toxicity [17]. Unlike the liver, where hepatocytes can be efficiently targeted and secreted proteins provide readily measurable pharmacodynamic readouts, the myocardium represents a substantially more complex target for permanent genome modification. This divergence between liver-directed and myocardial applications represents a central translational question for cardiovascular genome editing.
The 2026 American College of Cardiology scientific statement provides a comprehensive overview of genome-editing platforms, cardiovascular targets, delivery systems, and clinical, regulatory, and ethical considerations [3]. The present review adds a focused analytical question: why have liver-directed programs reached human testing while direct myocardial editing remains preclinical? We compare the biological determinants of these trajectories—target dispensability, disease mechanism, target-cell accessibility, acceptable allelic heterogeneity, spatial coverage, measurable pharmacodynamics, and rescue options after harm—and distinguish established evidence, emerging hypotheses, and our proposed criteria for clinical readiness. Figure 1 summarizes this organ-specific perspective.
Figure 1.
Somatic genome editing in cardiovascular disease: platforms, targets, delivery systems, safety challenges, and the translational path. The conceptual illustration was generated with Microsoft Copilot 365 (GPT-5 Chat model); the authors independently verified all scientific terms and representations and remain responsible for the final figure.
Scope and Literature Selection
This is a structured narrative review of somatic in vivo genome editing relevant to cardiovascular disease; germline editing and ex vivo cell editing are outside its scope. Targeted searches of PubMed/MEDLINE, ClinicalTrials.gov, FDA guidance pages, and reference lists of eligible primary studies and major cardiovascular statements were performed from database inception through 22 October 2026. Search concepts combined “CRISPR”, “genome editing”, “base editing”, or “prime editing” with “cardiovascular”, “heart”, “myocardium”, “cardiomyopathy”, “PCSK9”, “ANGPTL3”, “TTR”, “MYH7”, “MYBPC3”, “delivery”, “off-target”, “genomic integrity”, “clinical trial”, or “guidance”.
We prioritized peer-reviewed primary human studies, disease-relevant animal studies that reported a molecular and functional outcome, and authoritative regulatory or trial-registry documents. Mechanistic and delivery studies were included when they directly informed organ-specific translation. Gene-addition or RNA-silencing studies were used only as procedural or biological comparators. Conference reports, sponsor communications, and securities filings were considered only for developments not yet available in peer-reviewed form and are explicitly labeled as preliminary or sponsor-reported. Study selection was purposive rather than exhaustive; no meta-analysis was attempted because platforms, models, denominators, doses, and endpoints were heterogeneous.
2. The Gene-Editing Toolkit in Cardiology
The principal genome-editing platforms differ in the genomic outcomes they produce, the cellular repair processes they recruit, and the therapeutic objectives for which those outcomes are acceptable. In cardiovascular applications, this distinction is decisive. Gene disruption may be appropriate for a dispensable hepatic protein whose reduced expression is beneficial, whereas an inherited cardiomyopathy caused by a dominant-negative allele may require precise, allele-selective correction. Platform selection should therefore begin with the intended biological effect and then account for the sequence context, target cell, and tolerable spectrum of editing products [3]. Section 3 applies these mechanistic distinctions to hepatic and myocardial targets and reviews current clinical and preclinical evidence. Section 4 examines organ-specific delivery, and Section 5 addresses genomic, clinical, regulatory, and ethical risk.
2.1. CRISPR-Cas Nuclease Editing
CRISPR-Cas nuclease editing couples a programmable guide RNA to a Cas nuclease, most commonly Cas9. Guide-RNA hybridization to a complementary DNA sequence adjacent to a compatible protospacer-adjacent motif activates site-specific cleavage of both DNA strands [7]. Repair by non-homologous or microhomology-mediated end joining then generates a distribution of insertions and deletions. When these alterations shift the reading frame, disrupt a splice site, or introduce a premature termination signal, the net result can be durable loss of target-gene function [7].
This outcome is well aligned with cardiovascular targets for which reduced protein production is the therapeutic objective. The first clinical liver-directed programs targeting TTR and ANGPTL3, for example, use nuclease editing to convert transient exposure to editing machinery into sustained suppression of a circulating pathogenic or risk-associated protein [14,15]. In this setting, edited hepatocytes need not carry an identical sequence change, provided that the aggregate population of editing products reliably reduces functional protein expression. Homology-directed repair can, in principle, install a defined sequence in the presence of a donor template, but its dependence on repair pathways that are inefficient in nondividing cells limits its practicality in adult cardiomyocytes [3].
For nuclease editing, the intended event and unintended structural outcomes must be separated explicitly. The intended therapeutic product is a distribution of small end-joining insertions or deletions that inactivate the target gene. The same programmed double-strand break can also generate large deletions, complex local rearrangements, vector capture, or chromosome-scale damage such as chromothripsis [19,20]. These outcomes differ in biological consequence and assay requirements; a high percentage of small loss-of-function alleles does not establish genomic integrity. Nuclease editing is therefore best matched to a dispensable target for which heterogeneous loss-of-function products are acceptable, and is less suited to precise correction of an essential sarcomeric gene when disruption of the normal allele could add a second pathogenic mechanism [17].
2.2. Base Editing
Base editors replace the nuclease-induced double-strand break with chemically directed nucleotide conversion. A catalytically impaired Cas protein exposes a short segment of single-stranded DNA within the RNA-DNA complex, and a tethered deaminase modifies a susceptible nucleotide within that editing window. A nick in the opposite DNA strand biases repair toward retention of the edited base [8,9]. Cytosine and adenine base editors consequently enable complementary transition mutations while avoiding a programmed double-strand break and donor DNA [8,9].
This mechanism supports two cardiovascular strategies: correction of a compatible transition mutation, as in preclinical MYH7 models [17,18], or deliberate creation of a splice-disrupting or stop-generating change, as in the clinical PCSK9 program VERVE-102 [16]. Base editing may yield a more uniform molecular product than end-joining-mediated disruption only for a specific editor, target sequence, strand orientation, protospacer-adjacent motif, and editing window. Nearby susceptible nucleotides can undergo bystander conversion, and treated cells may contain intended edits, bystander edits, unedited alleles, and small insertions or deletions [17]. Guide-independent DNA or RNA deamination also depends on editor architecture [21,22]. Consequently, the complete product distribution must be measured for each editor-guide-delivery combination rather than inferred from the platform name.
2.3. Prime Editing
Prime editing combines a Cas9 nickase with a reverse transcriptase and a prime-editing guide RNA (pegRNA). In addition to specifying the genomic target, the pegRNA contains a primer-binding sequence and a reverse-transcription template encoding the intended alteration. After one DNA strand is nicked, the reverse transcriptase copies the template into the target locus, and cellular processing resolves the edited and unedited DNA flaps [10]. Because the replacement sequence is templated rather than generated by a deaminase, prime editing can install all base substitutions as well as selected small insertions and deletions without a donor DNA molecule or programmed double-strand break [10].
This broader sequence scope is relevant to cardiomyopathies, in which many pathogenic variants are not compatible with cytosine or adenine base editing. However, sequence flexibility is accompanied by greater molecular complexity. Editing efficiency depends on pegRNA stability, primer-binding and reverse-transcription-template design, local DNA repair, and coordinated delivery of a comparatively large editor and guide system. Manipulating mismatch-repair determinants and stabilizing the pegRNA have substantially improved prime-editing efficiency in experimental systems [23,24]. Even so, performance remains highly locus- and cell-dependent.
Cardiovascular prime-editing evidence remains preclinical. Dual-AAV delivery produced up to 11% editing in bulk mouse heart tissue [25], whereas plasmid delivery and enrichment of edited cells yielded 34.8% correction of homozygous RBM20 p.P633L alleles in cultured human induced-pluripotent-stem-cell-derived cardiomyocytes, with restoration of RBM20 localization and splicing [26]. These percentages have different denominators, delivery contexts, and selection pressures and are not directly comparable. Greater sequence flexibility therefore does not imply superior therapeutic performance: the multicomponent payload, locus-dependent efficiency, incomplete or heterogeneous products, and need for broad adult myocardial delivery remain unresolved [3,25,26].
2.4. Selecting a Platform for the Therapeutic Objective
No platform is uniformly superior. Nuclease editing offers the most direct route to gene inactivation when heterogeneous loss-of-function alleles are acceptable [14,15,19,20]. Base editing is preferable when a compatible transition can create a defined therapeutic allele without a programmed double-strand break, provided that bystander and deaminase-associated products remain acceptable [8,9,16,17,18,21,22]. Prime editing offers the broadest sequence scope but currently carries the greatest payload and implementation burden [10,23,24,25,26]. The clinically relevant comparison is therefore not simply editing efficiency; it is the proportion of target cells that acquire an acceptable functional outcome, the distribution of unintended products, the durability of the phenotype, and the consequences of residual unedited or incorrectly edited cells [3]. These criteria become especially important when the therapeutic target shifts from a secreted hepatic protein to an essential component of the cardiac sarcomere. Table 1 summarizes the mechanistic suitability and cardiovascular maturity of genome-editing platforms [3,14,15,16,17,18,25,26].
Table 1.
Mechanistic fit and cardiovascular maturity of genome-editing platforms.
3. Primary Therapeutic Targets and Clinical Progress
The cardiovascular field has advanced along two biologically distinct paths. Liver-directed programs modify hepatocytes to reduce a circulating protein that drives systemic lipid risk or cardiac amyloid deposition [14,15,16,27,28,29,30]. Direct myocardial programs instead seek to correct or silence a pathogenic allele within cardiomyocytes [17,18,26,27,28]. The first strategy can benefit from partial editing of a large secretory cell population and can be monitored through a circulating biomarker, whereas the second must contend with an essential, largely nonrenewing target tissue in which spatially heterogeneous editing may itself have functional consequences [3,14,15,16,17,18,27,28]. This organ-specific distinction, more than target prominence alone, explains the present gap between clinical and preclinical development.
3.1. Liver-Directed Clinical Translation
Human studies have concentrated on PCSK9, ANGPTL3, and TTR [14,15,16,29,30]. Each is expressed predominantly in hepatocytes and encodes a circulating protein that can be measured after treatment. Table 2 standardizes the available peer-reviewed evidence by dose, cohort size, follow-up, endpoint definition, pharmacodynamic result, and safety numerator. The studies establish target engagement and early durability, but their small uncontrolled designs and nonuniform assays preclude comparative efficacy claims or conclusions about uncommon adverse events.
Table 2.
Peer-reviewed human studies of in vivo liver-directed cardiovascular genome editing. Cross-trial comparisons are descriptive only; populations, dose-escalation rules, endpoint definitions, background therapy, and follow-up differ.
3.1.1. PCSK9: Reproducing a Naturally Protective Lipid Phenotype
PCSK9 has unusually strong directional validation: naturally occurring heterozygous loss-of-function variants are associated with lifelong reductions in LDL-C and coronary disease risk [12]. Therapeutic editing is not equivalent to that exposure. It begins after decades of cumulative risk, may create mosaic hepatocyte editing, and can produce unintended alleles not present in variant carriers. In nonhuman primates, one systemic PCSK9 base-editor administration produced approximately 66% bulk-liver editing, reduced circulating PCSK9 by about 90% and LDL-C by about 60%, and remained pharmacodynamically stable for at least eight months [31]. These results bridge target biology to in vivo editing but do not by themselves establish clinical benefit or lifelong genomic safety.
VERVE-102 and YOLT-101 provide independent evidence that adenine base editing can suppress PCSK9 and LDL-C after one administration [16,29]. The relevant efficacy question is whether this produces fewer myocardial infarctions, ischemic strokes, coronary revascularizations, and cardiovascular deaths in addition to optimized background therapy. Because outcome benefit depends on achieved absolute LDL-C, baseline risk, adherence to concomitant therapy, and duration of exposure, a percentage LDL-C change cannot be converted directly into a predictable event reduction. Definitive evaluation will require adequately powered randomized, event-driven trials with multi-year follow-up; there is no scientifically defensible universal minimum duration independent of accrued events. Longer surveillance will still be required for delayed editing-related harm after the outcome trial ends.
3.1.2. ANGPTL3: Simultaneous Reduction of Atherogenic Lipoproteins and Triglycerides
Loss-of-function variants in ANGPTL3 are associated with lower triglyceride and LDL-C concentrations and reduced coronary artery disease risk [13]. Because the intended therapeutic outcome is loss of protein function rather than correction of a specific pathogenic variant, nuclease-mediated disruption is a logical platform choice. CTX310 produced dose-dependent reductions in circulating ANGPTL3, LDL-C, and triglycerides in its first-in-human study, including marked lipid reductions at the highest tested dose [15].
CTX310 broadens editing beyond a single-lipid pathway, but its present evidence remains pharmacodynamic [15]. Lifelong heterozygous ANGPTL3 loss of function supports the direction of effect, whereas adult nuclease editing may generate a wider and more heterogeneous spectrum of null alleles. Clinical benefit should therefore be tested using major adverse cardiovascular events and pancreatitis-relevant outcomes in appropriate hypertriglyceridemic populations, while monitoring fat-soluble nutrients, hepatic effects, and other consequences of sustained ANGPTL3 suppression. As for PCSK9, an event-driven design and multi-year follow-up are more informative than an arbitrary fixed “minimum” interval.
3.1.3. TTR: Reducing the Precursor of Cardiac Amyloid
Transthyretin editing differs from lipid-risk modification because the objective is to reduce production of a pathogenic precursor rather than recreate a population-level protective lipid phenotype. Nexiguran ziclumeran achieved rapid and sustained suppression of circulating transthyretin in patients with ATTR-CM [14]. ART001 subsequently demonstrated durable transthyretin reduction in a small hereditary ATTR cohort, providing additional evidence that the target class is editable in humans, although that study predominantly involved polyneuropathy and cannot be interpreted as evidence of cardiac efficacy [30].
Suppression of circulating transthyretin is necessary but does not directly demonstrate removal of established myocardial amyloid or recovery of cardiac function. Meaningful ATTR-CM endpoints include all-cause mortality, recurrent cardiovascular hospitalization, functional capacity, symptoms and health status, and serial measures of myocardial structure and amyloid burden [14,32]. These endpoints evolve on different time scales: early biomarker and imaging trends can support biological activity, but morbidity and survival require randomized follow-up measured in years. ART001 should be interpreted separately because its cohort predominantly had hereditary polyneuropathy rather than ATTR-CM [30]. The ongoing MAGNITUDE trial is designed to test clinical outcomes; until those data are available, TTR editing has demonstrated durable target suppression, not reversal of cardiomyopathy or improved survival [32].
3.2. Direct Myocardial Editing
Direct myocardial editing poses a distinct therapeutic problem. Sarcomeric cardiomyopathies can reflect dominant-negative proteins, haploinsufficiency, splice defects, or other mechanisms, so the required fraction and type of corrected cells will differ. Allele-selective correction may be necessary for dominant-negative MYH7 disease, whereas restoration above a functional protein threshold may suffice for some MYBPC3 haploinsufficiency. The editor must reach enough appropriately distributed cardiomyocytes, preserve the normal allele when required, and avoid deleterious products. A “toxic myocardial mosaic” remains a biologically plausible concern rather than an established human observation. No peer-reviewed clinical trial has yet demonstrated direct in vivo editing of human cardiomyocytes [3,17,18,26,27,28].
3.2.1. MYH7: Allele-Specific Correction of a Dominant-Negative Variant
Two complementary studies have established proof of concept for correcting the hypertrophic cardiomyopathy-associated MYH7 p.R403Q variant. Reichart and colleagues used an adenine base editor in a humanized mouse model, whereas Chai and colleagues combined patient-derived cardiomyocytes with a separate humanized mouse model [17,18]. Together, the studies showed that precise correction can preserve or rescue cardiac structure and function while avoiding indiscriminate suppression of the normal MYH7 allele [17,18]. This is an important conceptual advantage for a dominant-negative disease in which the wild-type protein remains necessary.
The MYH7 studies define both proof of concept and its boundary. Animals were treated at birth or at 10–13 days of age, before hypertrophy, fibrosis, dysfunction, or arrhythmia was established [17,18]. They therefore demonstrate prevention of disease emergence, not reversal of mature cardiomyopathy. Human extrapolation is limited by differences in myocardial maturation, heart size, disease duration, cardiomyocyte turnover, fibrosis, immune exposure, and genetic background. Variant specificity narrows the eligible population; dual-AAV delivery requires co-transduction; ventricular and atrial coverage differed; an additional dose increased bystander editing; and nuclease-mediated allele inactivation showed dose-dependent toxicity [17]. Adult studies should begin after documented hypertrophy or dysfunction and prespecify which abnormalities—wall thickness, fibrosis, strain, arrhythmia burden, exercise capacity, or survival—are expected to improve rather than merely stop progressing.
3.2.2. MYBPC3: Restoring Function Across Distinct Variant Mechanisms
MYBPC3 provides a complementary mechanism because many pathogenic variants cause haploinsufficiency. In a homozygous p.W1098X neonatal rat model, retro-orbital delivery on postnatal day 3 of 5 × 10¹¹ vector genomes each of SpCas9-AAV9 and guide/donor-AAV9 yielded 3.56% correction among bulk-tissue mutant alleles and MYBPC3 protein equal to 2.12% of wild-type abundance at six months, while preventing a severe hypertrophic phenotype [27]. The denominators are not interchangeable: allele correction in homogenized tissue, protein abundance in tissue lysate, and the fraction and spatial distribution of corrected cardiomyocytes answer different questions. The result may indicate biological amplification from a small corrected pool, but cell-resolved distribution and independent dose–response replication were not established. Neonatal delivery, a homozygous null-like genotype, efficient developmental remodeling, and HDR in a growing heart limit extrapolation to heterozygous adult disease with established fibrosis.
A later study used base editing to correct the MYBPC3 c.772G>A splice-site mutation in humanized mice and reported attenuation of hypertrophy, fibrosis, and dysfunction [28]. This supports mechanism-matched editing but does not provide a mutation-agnostic solution. Across MYH7 and MYBPC3, the available in vivo studies primarily intervene before or near disease onset; evidence that editing reverses established hypertrophy, mature fibrosis, sustained dysfunction, or arrhythmia is absent. Adult, large-animal models with clinically recognizable disease and longitudinal electrophysiological and mechanical phenotyping are therefore a prerequisite for stronger clinical inference.
3.3. Why Hepatic Translation Leads Myocardial Translation
The relative maturity of liver-directed programs is not simply a consequence of earlier investment. PCSK9, ANGPTL3, and TTR are secreted proteins with validated directional effects: lower expression is the intended outcome and circulating protein or lipid concentrations provide rapid measures of target engagement. Partial editing across hepatocytes can aggregate into a therapeutically relevant systemic effect, while heterogeneous loss-of-function alleles may still converge on the same phenotype [3,14,15,16]. These properties permit early trials to test biological activity before enough cardiovascular events accrue for efficacy analysis.
Myocardial targets offer fewer such margins. MYH7 and MYBPC3 encode essential sarcomeric proteins, pathogenic mechanisms vary by allele, and the clinical consequence of nonuniform editing must be understood at the level of the whole organ. A mean editing percentage can obscure regional underexposure, differential editing of the normal and mutant alleles, or small subsets of cardiomyocytes carrying deleterious products. Preclinical success must therefore encompass not only sequence correction but also durable contractile rescue, electrical stability, absence of adverse remodeling, and performance in established disease [3,17,18,27,28].
Table 3 makes the translational divide quantitative without implying direct equivalence among heterogeneous experiments. Hepatic studies report bulk-liver allelic editing linked to a circulating output, whereas myocardial studies use bulk tissue, chamber-specific RNA, or isolated cardiomyocyte nuclei and largely assess prevention in young animals. These denominator and disease-stage differences preclude a universal editing threshold.
Table 3.
Selected quantitative preclinical studies illustrating the hepatic–myocardial translational divide. Values are study-specific and should not be compared as if they shared a common denominator.
4. Delivery Systems: Reaching the Target Tissue
For in vivo genome editing, delivery is part of the therapeutic mechanism. Reports should distinguish at least four denominators: (i) bulk-tissue allelic editing, which mixes cardiomyocyte and noncardiomyocyte DNA; (ii) editing measured in purified cardiomyocytes or cardiomyocyte nuclei; (iii) the fraction of cardiomyocytes carrying at least one acceptable edit; and (iv) editing of mutant versus wild-type alleles in heterozygous disease. Cardiomyocyte multinucleation and polyploidy further prevent a simple conversion from edited alleles to corrected cells. Sampling location also matters: one ventricular specimen may not represent other walls, the septum, atria, or conduction tissue. Spatial in situ sequencing confirms that similar tissue-level means can conceal different cellular and regional distributions [34].
4.1. Lipid Nanoparticles and the Hepatic Delivery Advantage
Lipid nanoparticles (LNPs) are the most clinically advanced vehicles for in vivo cardiovascular editing. They can co-deliver editor messenger RNA and guide RNA, protect these cargos during systemic administration, and generate a finite interval of intracellular editor production [14,15,16,29,30]. In mice, LNP-mediated co-delivery of Cas9 messenger RNA and an ANGPTL3-directed guide produced liver-restricted editing and durable lipid lowering, establishing that transient exposure to editing machinery can generate a persistent hepatic phenotype [33]. The human TTR, ANGPTL3, and PCSK9 programs described in Section 3 apply the same broad principle, although the lipid composition, guide, cargo architecture, and dose are product specific [14,15,16,29,30].
The hepatic advantage reflects anatomy as well as formulation biology. Fenestrated hepatic sinusoids facilitate particle access, and many ionizable LNPs acquire apolipoproteins after intravenous administration and enter hepatocytes through receptor-mediated pathways. Productive editing nevertheless requires a sequence of additional events such as cellular uptake, endosomal escape, cargo release, editor translation, guide availability, and nuclear access, so organ accumulation alone does not demonstrate delivery of an active editing complex [33,35]. Receptor-directed ligands can strengthen this chain. In low-density lipoprotein receptor-deficient nonhuman primates, incorporation of N-acetylgalactosamine (GalNAc), which engages the hepatocyte asialoglycoprotein receptor (ASGPR), increased ANGPTL3 base editing from approximately 5% to 61%; the pharmacodynamic effect persisted for six months in wild-type nonhuman primates [35]. VERVE-102 extends this strategy to humans through a GalNAc-containing LNP intended to preserve hepatocyte uptake when low-density lipoprotein receptor function is impaired [16].
LNPs offer two further advantages for permanent editing: they can accommodate RNA cargos larger than a single adeno-associated viral vector can package, and they limit the duration of editor expression. A short editing pulse may narrow the interval during which exposure-dependent bystander or off-target products can accumulate, but it does not reverse a genomic change that has already occurred [11]. Moreover, “LNP” is not a biodistribution category. Lipid composition, particle size, surface chemistry, cargo ratio, dose, and route can alter uptake by hepatocytes, Kupffer cells, endothelial cells, and extrahepatic tissues [33,35]. Delivery performance must therefore be established for the final LNP-editor–guide combination rather than inferred from another formulation.
4.2. Adeno-Associated Viral Vectors and the Myocardial Payload Problem
Adeno-associated viral (AAV) vectors remain prominent in preclinical myocardial editing because selected capsids can transduce nondividing cardiomyocytes and sustain transgene expression [36,37]. Persistence is advantageous for gene addition but is not inherently desirable for an editor that needs only a finite period of activity. The limited AAV payload is an additional constraint: the base editor used in the MYH7 hypertrophic cardiomyopathy model and the prime-editing systems evaluated in mice required dual vectors [17,25]. Productive editing then depends on co-transduction of the same cardiomyocyte and successful intracellular reconstitution. Detection of vector genomes or one payload component in cardiac tissue therefore does not establish delivery of a complete editing system.
Cardiac tropism is conditional rather than a fixed rank order among capsids. Engineered AAV2 variants improved the cardiac-to-hepatic transduction ratio relative to AAV9 in mice [36]. In a separate comparison, AAV6 produced greater transduction than AAV9 after intramyocardial administration across rodent and porcine hearts, human induced pluripotent stem cell-derived cardiomyocytes, and human atrial tissue slices [37]. These studies justify capsid engineering and screening in human cardiac systems, but neither demonstrates homogeneous transduction after systemic administration to an adult human heart. Species, route, dose, disease state, pre-existing immunity, and promoter design remain components of the delivery phenotype [3,36,37].
Cardiac gene-addition studies provide useful procedural precedents while also defining the limit of extrapolation. In swine with ischemic heart failure, temporary coronary artery and coronary sinus occlusion with mechanical circulatory support increased AAV6 cardiac uptake and transgene expression compared with conventional intracoronary infusion [38]. A phase 1 study subsequently delivered the cardiotropic AAV2i8 gene-addition therapy AB-1002 by antegrade coronary infusion to 11 patients with nonischemic cardiomyopathy, demonstrating catheter-based procedural feasibility [39]. Neither study evaluated genome editing. Their relevance is narrower but important: capsid, route, vascular dwell time, and procedural conditions jointly determine myocardial exposure, and systemic dose escalation cannot be assumed to compensate for inefficient cardiac delivery [38,39].
4.3. Administration Route and Spatial Coverage
Administration route determines distribution, invasiveness, and redosing options. Peripheral intravenous delivery is operationally simple and supports broad exposure, but conventional LNPs are diverted to the liver and systemic AAV increases extra-cardiac exposure and immune burden. Direct intramyocardial injection creates high local concentration with focal coverage and procedural injury; in mice, modified-mRNA LNPs predominantly transfected fibroblasts, endothelial cells, and epicardial cells rather than cardiomyocytes [40]. Intracoronary delivery can expose a larger perfused territory at a lower systemic dose, but requires catheterization and depends on coronary flow, vascular dwell time, endothelial transit, and regional disease. None of these routes permit redosing to be assumed: anti-capsid immunity strongly constrains repeat AAV, whereas repeat LNP administration remains formulation- and immune-response-specific.
Reporter delivery must remain distinct from delivery of a complete editor. A 2026 LNP screen transfected 36% of cardiomyocytes at an injection site and 13% at distal sites in reporter mice, while substantial uptake persisted in noncardiomyocytes [41]. The formulation also delivered adenine-base-editor components, but editing was demonstrated in the injected left ventricle rather than throughout the myocardium. Reporter expression, one editor component, and permanent genomic editing therefore represent successive and noninterchangeable levels of evidence. Most such studies remain rodent based; large-animal support is stronger for catheter delivery and AAV gene addition than for complete myocardial genome editing [38,39].
Intracoronary administration seeks a compromise between systemic simplicity and focal injection. In normal and ischemia–reperfusion rabbit hearts, intracoronary reporter-mRNA LNPs produced broader expression than intravenous dosing and a less focal pattern than intramyocardial injection, but exposed cardiomyocytes, endothelial cells, smooth-muscle cells, and fibroblasts [42]. Stop-flow and recirculation strategies may improve myocardial contact yet make the procedure part of the product: exposure depends on perfusion pressure, vector dwell time, collateral flow, and regional tissue state [38]. Preclinical evaluation must therefore reproduce the intended clinical route and report functional editing by chamber, region, and cell type.
4.4. Emerging Transient Delivery Systems
The preferred long-term profile for myocardial editing would combine cardiac tropism, sufficient whole-organ coverage, and brief intracellular editor exposure. Cardiotropic LNPs may eventually meet that profile, but current evidence is dominated by reporter cargos, RNA interference, local administration, and small-animal models [40,41,42,43]. Engineered virus-like particles offer a complementary DNA-free strategy by packaging editor proteins and guide RNAs as transient ribonucleoprotein complexes. Prime-editor virus-like particles have achieved therapeutically relevant editing in noncardiac mouse models, but adult myocardial tropism, whole-heart coverage, scalable manufacture, and clinical biodistribution remain unestablished [44].
Transient delivery is also expanding the cargo that can be carried nonvirally. An optimized three-component prime-editing LNP achieved a mean 49% edit frequency in bulk mouse liver after one dose and corrected a phenylketonuria model, while producing a shorter exposure profile than AAV delivery [45]. This result is a liver proof of concept, not evidence that the same formulation can reach cardiomyocytes. Its translational value lies in showing that molecular complexity does not require a persistent viral vector. Future myocardial systems will have to combine comparable cargo coordination with cardiac-selective uptake and spatially adequate organ coverage.
4.5. Defining Adequate Organ-Specific Delivery
Delivery adequacy cannot be reduced to a highest mean percentage, and current evidence does not define a minimum corrected-cardiomyocyte threshold for human benefit. The required level is mechanism specific. Dominant-negative disease may require correction or selective silencing across enough cells to prevent continued incorporation of toxic protein, while preserving the normal allele. Haploinsufficiency may improve once aggregate protein exceeds a functional threshold, even if many cells remain uncorrected. Cell-autonomous defects may require broader coverage than mechanisms with paracrine or tissue-level compensation. Any threshold must also incorporate regional distribution, because the same bulk percentage could represent diffuse low-level correction or a highly edited local cluster. A liver-derived benchmark cannot be transferred to the heart.
An adequate delivery package should establish the proportion and identity of cells reached, regional distribution of acceptable edits, duration of editor exposure, full allelic product spectrum, and permanent editing in non-target organs [11,34]. Liver-directed programs have met enough of these conditions to justify human dose escalation, although clinical-outcome benefit and lifelong safety remain unproven [14,15,16,29,30]. Myocardial programs have rescued disease phenotypes in selected models but have not shown scalable, sufficiently uniform editing of the adult human heart [17,18,27,28]. Delivery is therefore the principal mechanistic explanation for the current organ-specific translational divide, not a downstream engineering detail. Table 4 summarizes the organ-specific criteria used to assess delivery adequacy in cardiovascular genome editing.
Table 4.
Organ-specific criteria for judging delivery adequacy in cardiovascular genome editing. The table distinguishes evidence of carrier or reporter delivery from functional delivery of the complete editing system and from therapeutic efficacy.
5. Safety and Translational Challenges
Permanence changes the standard by which safety must be judged. An infusion reaction may resolve as a carrier is cleared, whereas an intended or unintended genomic alteration may persist for the life of the edited cell [11]. Early tolerability therefore cannot establish long-term safety, and a high on-target percentage cannot compensate for an inadequately characterized product spectrum. The relevant evidence must connect molecular integrity to organ function, dose irreversibility, patient selection, clinical benefit, manufacturing control, and durable governance.
5.1. Genomic Integrity and Product Characterization
“Off target editing” is not a single event. Guide-dependent modification at a homologous locus, guide-independent deaminase activity, bystander conversion within the intended editing window, and unintended products at the target locus arise through different mechanisms and require different assays [19,20,21,22,23,24]. Nuclease-induced double-strand breaks can produce large deletions, complex rearrangements, and chromothripsis at the intended locus [19,20]. Base editors can generate guide-independent DNA or RNA changes depending on their architecture, whereas prime editors can generate partial edits and competing repair products despite avoiding a programmed double-strand break [21,22,23,24]. When AAV and a nuclease are present in the same cell, vector sequences may also be captured at the induced break [46]. Reporting the intended edit and a short list of predicted off-target sites is therefore insufficient.
The unit of characterization is the final editor-guide-delivery product. A practical preclinical package should combine unbiased nomination (for example, genome-wide cleavage or binding assays appropriate to the platform), targeted deep sequencing in multiple human donors, short-read quantification of small variants, and long-read or orthogonal structural assays for large deletions, inversions, translocations, and vector capture when mechanistically plausible [19,20,47]. Base editors additionally require target-window bystander analysis and guide-independent DNA/RNA assessment; prime editors require intended, partial, scaffold-derived, and competing repair products. Assays should include the intended human cell type and tissues exposed by biodistribution, use multiple biological replicates, approximate proposed on-target activity, and state variant-allele-frequency and structural-event detection limits. FDA’s 2026 document is draft, nonbinding guidance rather than a legally fixed checklist [47].
Human genetic diversity belongs within this strategy. A naturally occurring variant can create or remove a protospacer-adjacent motif and thereby change an individual’s off-target landscape. Cancellieri and colleagues demonstrated variant-enabled allele-specific off-target editing and a chromosomal inversion for a therapeutically relevant guide [48]. A reference genome alone cannot therefore represent all clinically relevant genomes. Candidate nomination and confirmation should incorporate population variation, relevant haplotypes, and donor cells spanning the ancestries expected in the treated population [47,48].
Detection must be followed by biological interpretation. Frequency alone is insufficient: a rare alteration in a growth-regulatory gene or an essential sarcomeric allele may matter more than a frequent neutral edit. Risk assessment should integrate genomic context, cell identity, allelic state, persistence, clonal potential, and organ consequence [11,47]. Negative results establish only that no event was detected in the assayed material above the stated limit; they cannot prove absence in an unsampled liver clone, a focal myocardial region, or a rare long-lived cell population. Human liver biopsies sample little tissue and myocardial biopsy is still more limited, so nonclinical biodistribution, spatial assays, circulating biomarkers, and longitudinal organ surveillance must be interpreted as complementary rather than substitutable evidence.
5.2. Organ-Level, Immune, and Dose-Related Safety
For liver-directed therapy, suppression of a circulating protein confirms target engagement but does not exclude injury in cell populations that encountered the product. The published TTR, ANGPTL3, and PCSK9 studies reported predominantly mild-to-moderate infusion reactions and transient laboratory abnormalities, but their small cohorts cannot exclude uncommon severe events [14,15,16,29,30]. Clinical interpretation should preserve timing, dose relationship, inflammatory context, intervention, recurrence, and resolution rather than grouping all aminotransferase changes as a uniform platform effect.
The later development of nexiguran ziclumeran illustrates why readiness assessment must be dynamic. The peer-reviewed phase 1 report describes the 36-patient ATTR-CM cohort through its prespecified data cutoff [14]. Separately, a March 2026 sponsor Form 8-K reported an FDA clinical hold on MAGNITUDE and MAGNITUDE-2 after grade 4 aminotransferase elevations and increased bilirubin in a MAGNITUDE participant; this disclosure was not a peer-reviewed causal analysis [49]. The hold was lifted after intensified liver-function monitoring, short-term corticosteroid guidance, revised hepatic and cardiovascular eligibility criteria, and explicit interruption rules [49]. These observations do not establish whether the event was caused by nexiguran ziclumeran, was product specific, or reflected a broader mechanism. They nevertheless lower confidence in readiness until exposure, host factors, recurrence, and mitigation are better defined, and they show that favorable pharmacodynamics cannot freeze a program’s benefit–risk assessment.
Myocardial editing requires a different organ-level safety program. Editing mosaicism has not been shown to be intrinsically arrhythmogenic in humans; concern is mechanistic, based on electrical and mechanical coupling across regions with different allelic products. Evaluation should pair cell- and region-resolved sequencing with serial 12-lead ECG, continuous or implantable rhythm monitoring, programmed electrical stimulation, conduction-velocity and optical-mapping studies where feasible, echocardiographic strain, pressure–volume analysis, exercise or pharmacological stress testing, chamber-specific histopathology, fibrosis mapping, and assessment of conduction tissue in adult disease models. Observed findings—such as dose-dependent nuclease toxicity in MYH7 mice—should be reported separately from hypothesized mosaic hazards [17].
Immune risks should be separated by mechanism. Pre-existing antibodies or T-cell responses to bacterial Cas proteins may eliminate edited cells or cause inflammation [50]. Anti-AAV capsid immunity affects eligibility, tissue exposure, and the feasibility of redosing [51]. LNPs can cause complement- or innate-immune-mediated infusion reactions and transient hepatic inflammation that depend on lipid composition, RNA cargo, dose, and premedication. Product-specific screening, acute monitoring, longitudinal immunomonitoring, and treatment algorithms are therefore required. Clearance of a carrier or editor cannot terminate an established edit, and increasing dose may broaden coverage while also increasing immune activation, non-target exposure, bystander editing, or normal-allele disruption [17].
First-in-human studies should use sequential enrollment, staggered escalation, prespecified pausing criteria, and sufficient observation between cohorts to identify early signals before additional participants receive an irreversible intervention [11]. For PCSK9, ANGPTL3, or TTR disruption, dose selection should seek the lowest exposure that produces a stable, clinically credible pharmacodynamic effect. For myocardial correction, dose must be interpreted against the proportions and spatial distribution of correctly edited, incorrectly edited, and unedited alleles; a higher total percentage may conceal a less favorable product distribution [17,18].
Patient selection should align target validation, disease severity, biological reversibility, alternatives, and the consequences of treatment failure. Severe familial hypercholesterolemia with persistent LDL-C elevation despite optimized therapy offers strong target validation and measurable residual risk, but also effective reversible alternatives. Progressive ATTR-CM has high morbidity and mortality despite stabilizers or silencers, yet TTR reduction may not remove established amyloid. Genetically defined cardiomyopathy offers etiologic precision but usually involves small variant-specific populations, difficult myocardial delivery, and fibrosis that may be irreversible. These populations therefore cannot share one acceptable-risk threshold. Initial use is most defensible where untreated or residual risk is high, the edit has a clear mechanistic advantage, and conventional therapy remains available if suppression is incomplete.
Inherited myocardial disease adds a narrower eligibility chain: a pathogenic or likely pathogenic variant, a mechanism compatible with the proposed edit, an editable sequence context, preservation of the normal allele when required, and enough viable myocardium for correction to change the trajectory [3,17,18,27,28]. A variant of uncertain significance cannot justify permanent editing. Timing is also critical: advanced disease strengthens unmet need but may leave fibrosis and remodeling that correction of the initiating variant cannot reverse. Preclinical studies and early protocols must distinguish prevention of disease from treatment of established cardiomyopathy.
Long-term follow-up should be mechanism based rather than defined only by duration. FDA guidance describes risk-based observation that may extend to 15 years for gene-therapy products with plausible delayed effects [52]. Liver-directed surveillance should address persistent hepatic injury and biologically credible consequences of unintended edits; myocardial surveillance should include new arrhythmia, ventricular dysfunction, and structural progression.
Registries can extend observation beyond the original trial, but they require stable funding, interoperable outcomes, participant retention, and transfer plans if a sponsor or center ceases participation. Liver-directed follow-up should include serial liver chemistry, synthetic function, imaging when indicated, metabolic consequences of target loss, and evaluation of clonal or malignant signals. Myocardial follow-up should include rhythm surveillance, ventricular function, remodeling, heart-failure events, and sudden-death outcomes. Surveillance intensity may differ, but both products require long-term linkage between molecular exposure, organ findings, and clinical events.
There is currently no clinically validated method to reverse a distributed somatic DNA edit. Immediate management can stop further dosing, treat infusion or immune-mediated injury, and support the affected organ, but it cannot remove an established genomic change. Persistent consequences may require conventional add-on therapy: lipid-lowering drugs after incomplete PCSK9 or ANGPTL3 suppression; vitamin A management and ATTR-directed care after TTR disruption; antiarrhythmic drugs, ablation, pacing or defibrillation, heart-failure therapy, mechanical support, or transplantation after myocardial harm. Excessive pathway suppression may sometimes be countered pharmacologically or by protein replacement, but feasibility is target specific. A second “rescue edit” is theoretical and would introduce additional delivery and genomic risk. Consent, stopping rules, referral pathways, and long-term monitoring should therefore be designed before dosing rather than after toxicity appears.
5.3. Clinical Translation and Governance
Biomarkers should be interpreted according to their causal position. PCSK9, LDL-C, ANGPTL3, triglycerides, and TTR establish target engagement but do not themselves demonstrate fewer cardiovascular events, improved function, or longer survival [14,15,16,29,30]. Myocardial allele correction or improved imaging likewise supports biological activity without proving net clinical benefit. Later trials should use indication-specific endpoints meaningful to patients: major cardiovascular events for lipid-risk programs; mortality, recurrent hospitalization, function, symptoms, and amyloid progression for ATTR-CM; and rhythm burden, functional capacity, remodeling, heart failure, and survival for cardiomyopathy. Background therapy should be optimized and recorded because editing may complement rather than replace conventional treatment.
The regulated product is the complete combination of editor, guide, delivery system, manufacturing process, dose, and route. Changing a guide can alter potency and off-target sites; changing a lipid, capsid, or process can alter cell exposure, impurities, particle attributes, and biological activity [11,47]. Chemistry, manufacturing, and controls must therefore connect identity and purity to a potency assay that reflects the intended mechanism in a relevant human cell system. Split-vector products additionally require control of component ratio and evidence that release testing captures productive co-delivery rather than the presence of each component in isolation.
Regulatory sources should be separated by status. FDA’s 2020 long-term follow-up document is final, nonbinding guidance describing the agency’s current recommendations [52]. The 2026 documents on next-generation sequencing safety assessment and leveraging prior knowledge are draft, nonbinding recommendations that may change before finalization [47,53]. Neither is a statute or a validated universal standard. Our framework below is an author-proposed analytical tool. Prior platform knowledge may reduce redundant manufacturing or nonclinical work when comparability is demonstrated, but guide-specific potency, on-target products, off-target assessment, biodistribution, and organ consequences remain necessary—particularly for variant-specific myocardial products.
Valid consent must explain that administration may be brief while the genomic effect may be lifelong, that long-term risks cannot yet be quantified precisely, and that withdrawal from follow-up cannot reverse the edit [11,54]. Governance should preserve the boundary between treatment and enhancement and apply a stricter benefit-risk threshold as development moves from severe disease toward common asymptomatic risk states. Transparent trial registration, independent oversight, and public reporting of serious signals are particularly important when early biomarker success creates pressure for rapid expansion [54].
Equity begins with evidence generation. Under-representation in genomic datasets and donor-cell panels can leave population-specific off-target sites undetected [47,48]. Trial eligibility based on AAV antibodies, comorbidity, proximity to specialist centers, or capacity for years of follow-up may further narrow representation [51,54]. Protocols should report who is screened out and why, and genomic safety panels should reflect the diversity of the intended population.
A single administration may reduce the burden of chronic dosing while still requiring complex manufacture, specialized infusion or catheter-delivery centers, acute monitoring, and long-term surveillance. Claims of broad cost-effectiveness or equitable access should therefore follow evidence of durable clinical benefit and a credible implementation model. Access is not solely a post-approval pricing question; it shapes trial participation, external validity, and the social legitimacy of exposing participants to irreversible risk [54].
5.4. Proposed Translational Evidence Framework
The central question is whether a clinically meaningful effect can be pursued with a sufficiently characterized genomic product, bounded tissue exposure, acceptable organ risk, and a surveillance and management plan for persistent harm. Table 5 is a proposed conceptual framework, not an established regulatory standard or universally applicable minimum. It separates evidence expected before first-in-human administration from evidence that can reasonably mature during clinical development and requires organ-specific interpretation.
Table 5.
Proposed translational evidence framework for cardiovascular genome editing. This is an author-proposed conceptual framework rather than an established or validated regulatory standard.
Before first-in-human dosing, essential evidence includes validated target direction, a final-product genomic-integrity package with prespecified detection limits, clinically intended delivery in relevant models, dose-linked organ safety, a credible starting dose and stopping rules, a high-risk population with meaningful unmet need, and feasible long-term follow-up. Early and later clinical development must then establish durability, rare and delayed harms, patient-important outcomes, and whether conventional treatment remains necessary. These are progression criteria, not numeric universal cutoffs: acceptable unintended products and adequate myocardial coverage depend on genomic context, disease mechanism, spatial distribution, and the severity of the condition being treated.
Progress should be judged by convergence across the framework rather than maximal editing efficiency. A program should not advance when a plausible high-consequence product remains inadequately assayed, clinically intended delivery has not been demonstrated, organ dysfunction lacks a management pathway, or the proposed population has effective lower-risk alternatives that make residual uncertainty unacceptable.
6. Future Directions and Conclusions
The next stage of cardiovascular genome editing is defined by five prioritized questions: whether durable biomarker suppression improves patient outcomes; whether sufficient adult myocardial coverage can be achieved with the complete editor; how editing mosaicism and allelic product mixtures affect organ function; how rare and delayed genomic harms can be detected despite limited tissue sampling; and which patients have sufficient unmet need to justify an irreversible intervention. Liver-directed programs can answer the first and fifth questions in ongoing clinical development, while myocardial programs must first resolve the second through fourth in adult disease-relevant models.
For liver-directed PCSK9 and ANGPTL3 editing, randomized event-driven trials should test cardiovascular outcomes on optimized background therapy. For TTR editing, circulating suppression must be linked to mortality, recurrent hospitalization, function, symptoms, and myocardial disease progression. For direct myocardial editing, cell- and region-resolved maps must be linked to rhythm, contractility, remodeling, and stress performance after treatment of established disease—not only neonatal or presymptomatic prevention. Large-animal studies should use the intended cargo, route, dose, and surveillance strategy.
Cardiotropic LNPs and engineered virus-like particles may separate permanent editing from persistent vector exposure, but homogeneous adult myocardial editing has not been demonstrated [41,44]. Platform reuse may reduce redundant development, yet each guide and target still require product-specific potency, allelic product, off-target, biodistribution, and organ-safety evidence [45,53,55].
Long-term evidence infrastructure must precede broad adoption. Trials and registries should harmonize definitions of genomic findings, hepatic injury, arrhythmia, ventricular function, hospitalization, and patient-reported outcomes; preserve follow-up when sponsors or centers change; and report genomic diversity and enrollment exclusions transparently [48,54]. Technical feasibility alone is insufficient to justify treatment, particularly as programs move from severe inherited disease toward common cardiovascular risk.
Cardiovascular genome editing will progress from molecular proof of concept to demonstrable clinical benefit only when an acceptable edited organ can be produced: the intended genomic outcome in the necessary cells and regions, with bounded unintended products, preserved organ function, a credible response to persistent harm, durable surveillance, and patient-important benefit that justifies irreversibility.
Author Contributions
Conceptualization, J.D. and A.B.; methodology, J.D. and G.K.; writing—original draft preparation, J.D. and G.K.; writing—review and editing, A.B., M.P., and F.G. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Acknowledgments
The authors used Microsoft Copilot 365 to prepare the conceptual graphical figure and GPT-5 to assist with language editing. The authors independently verified all scientific content, terminology, references, and visual representations; no generative AI tool was credited as an author, and the authors remain fully responsible for the manuscript.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| AAV | Adeno-associated virus/viral |
| ACC | American College of Cardiology |
| ANGPTL3 | Angiopoietin-like protein 3 |
| ASCVD | Atherosclerotic cardiovascular disease |
| ASGPR | Asialoglycoprotein receptor |
| ATTR-CM | Transthyretin amyloid cardiomyopathy |
| CAD | Coronary artery disease |
| Cas | CRISPR-associated |
| CRISPR | Clustered regularly interspaced short palindromic repeats |
| CVDs | Cardiovascular diseases |
| DALY | Disability-adjusted life-year |
| DNA | Deoxyribonucleic acid |
| ECG | Electrocardiography |
| FDA | Food and Drug Administration |
| GalNAc | N-Acetylgalactosamine |
| LDL-C | Low-density lipoprotein cholesterol |
| LNPs | Lipid nanoparticles |
| MYBPC3 | Myosin-binding protein C3 |
| MYH7 | Myosin heavy chain 7 |
| PCSK9 | Proprotein convertase subtilisin/kexin type 9 |
| pegRNA | Prime-editing guide RNA |
| RNA | Ribonucleic acid |
| TTR | Transthyretin |
References
- Global Burden of Cardiovascular Diseases and Risks 2023 Collaborators. Global, regional, and national burden of cardiovascular diseases and risk factors in 204 countries and territories, 1990–2023. J. Am. Coll. Cardiol. 2025, 86, 2167–2243. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- GBD 2023 LDL Cholesterol Collaborators. Global burden of elevated LDL-C: Findings from the Global Burden of Disease Study 2023. JAMA 2026, 336, 1072. [PubMed]
- Ambardekar, A.V.; Bhatt, A.; Hoekstra, M.; Kelly, M.A.; Musunuru, K.; Natarajan, P. Gene editing therapy in cardiovascular disease: 2026 ACC scientific statement: A report of the American College of Cardiology. J. Am. Coll. Cardiol. 2026, 87, 3185–3206. [Google Scholar]
- Castellano, J.M.; Pocock, S.J.; Bhatt, D.L.; Quesada, A.J.; Owen, R.; Fernandez-Ortiz, A.; Sanchez, P.L.; Marin Ortuño, F.; Vazquez Rodriguez, J.M.; Domingo-Fernández, A.; et al. Polypill strategy in secondary cardiovascular prevention. N. Engl. J. Med. 2022, 387, 967–977. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sabatine, M.S.; Giugliano, R.P.; Keech, A.C.; Honarpour, N.; Wiviott, S.D.; Murphy, S.A.; Kuder, J.F.; Wang, H.; Liu, T.; Wasserman, S.M.; et al. Evolocumab and clinical outcomes in patients with cardiovascular disease. N. Engl. J. Med. 2017, 376, 1713–1722. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ray, K.K.; Wright, R.S.; Kallend, D.; Koenig, W.; Leiter, L.A.; Raal, F.J.; Bisch, J.A.; Richardson, T.; Jaros, M.; Wijngaard, P.L.J.; et al. Two phase 3 trials of inclisiran in patients with elevated LDL cholesterol. N. Engl. J. Med. 2020, 382, 1507–1519. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cong, L.; Ran, F.A.; Cox, D.; Lin, S.; Barretto, R.; Habib, N.; Hsu, P.D.; Wu, X.; Jiang, W.; Marraffini, L.A.; et al. Multiplex genome engineering using CRISPR/Cas systems. Science 2013, 339, 819–823. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Komor, A.C.; Kim, Y.B.; Packer, M.S.; Zuris, J.A.; Liu, D.R. Programmable editing of a target base in genomic DNA without double-stranded DNA cleavage. Nature 2016, 533, 420–424. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gaudelli, N.M.; Komor, A.C.; Rees, H.A.; Packer, M.S.; Badran, A.H.; Bryson, D.I.; Liu, D.R. Programmable base editing of A·T to G·C in genomic DNA without DNA cleavage. Nature 2017, 551, 464–471. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Anzalone, A.V.; Randolph, P.B.; Davis, J.R.; Sousa, A.A.; Koblan, L.W.; Levy, J.M.; Chen, P.J.; Wilson, C.; Newby, G.A.; Raguram, A.; et al. Search-and-replace genome editing without double-strand breaks or donor DNA. Nature 2019, 576, 149–157. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- U.S. Food and Drug Administration. Human Gene Therapy Products Incorporating Human Genome Editing: Guidance for Industry; U.S. Food and Drug Administration: Silver Spring, MD, USA, 2024. Available online: https://www.fda.gov/media/156894/download (accessed on 13 August 2026).
- Cohen, J.C.; Boerwinkle, E.; Mosley, T.H., Jr.; Hobbs, H.H. Sequence variations in PCSK9, low LDL, and protection against coronary heart disease. N. Engl. J. Med. 2006, 354, 1264–1272. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dewey, F.E.; Gusarova, V.; Dunbar, R.L.; O’Dushlaine, C.; Schurmann, C.; Gottesman, O.; McCarthy, S.; Van Hout, C.V.; Bruse, S.; Dansky, H.M.; et al. Genetic and pharmacologic inactivation of ANGPTL3 and cardiovascular disease. N. Engl. J. Med. 2017, 377, 211–221. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fontana, M.; Solomon, S.D.; Kachadourian, J.; Walsh, L.; Rocha, R.; Lebwohl, D.; Smith, D.; Täubel, J.; Gane, E.J.; Pilebro, B.; et al. CRISPR-Cas9 gene editing with nexiguran ziclumeran for ATTR cardiomyopathy. N. Engl. J. Med. 2024, 391, 2231–2241. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Laffin, L.J.; Nicholls, S.J.; Scott, R.S.; Clifton, P.M.; Baker, J.; Sarraju, A.; Singh, S.; Wang, Q.; Wolski, K.; Xu, H.; et al. Phase 1 trial of CRISPR-Cas9 gene editing targeting ANGPTL3. N. Engl. J. Med. 2025, 393, 2119–2130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vafai, S.B.; Täubel, J.; Ashdown, T.; Patel, R.S.; Diamondali, S.; Cegla, J.; Soran, H.; Bashir, B.; Abitbol, A.; Gaudet, D.; et al. In vivo base editing of PCSK9 with VERVE-102 for hypercholesterolemia. N. Engl. J. Med. 2026, 395, 648–659. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reichart, D.; Newby, G.A.; Wakimoto, H.; Lun, M.; Gorham, J.M.; Curran, J.J.; Raguram, A.; DeLaughter, D.M.; Conner, D.A.; Marsiglia, J.D.C.; et al. Efficient in vivo genome editing prevents hypertrophic cardiomyopathy in mice. Nat. Med. 2023, 29, 412–421. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chai, A.C.; Cui, M.; Chemello, F.; Li, H.; Chen, K.; Tan, W.; Atmanli, A.; McAnally, J.R.; Zhang, Y.; Xu, L.; et al. N Base editing correction of hypertrophic cardiomyopathy in human cardiomyocytes and humanized mice. Nat. Med. 2023, 29, 401–411. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kosicki, M.; Tomberg, K.; Bradley, A. Repair of double-strand breaks induced by CRISPR-Cas9 leads to large deletions and complex rearrangements. Nat. Biotechnol. 2018, 36, 765–771. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leibowitz, M.L.; Papathanasiou, S.; Doerfler, P.A.; Blaine, L.J.; Sun, L.; Yao, Y.; Zhang, C.Z.; Weiss, M.J.; Pellman, D. Chromothripsis as an on-target consequence of CRISPR-Cas9 genome editing. Nat. Genet. 2021, 53, 895–905. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grünewald, J.; Zhou, R.; Iyer, S.; Lareau, C.A.; Garcia, S.P.; Aryee, M.J.; Joung, J.K. Transcriptome-wide off-target RNA editing induced by CRISPR-guided DNA base editors. Nature 2019, 569, 433–437. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Doman, J.L.; Raguram, A.; Newby, G.A.; Liu, D.R. Evaluation and minimization of Cas9-independent off-target DNA editing by cytosine base editors. Nat. Biotechnol. 2020, 38, 620–628. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, P.J.; Hussmann, J.A.; Yan, J.; Knipping, F.; Ravisankar, P.; Chen, P.F.; Chen, C.; Nelson, J.W.; Newby, G.A.; Sahin, M.; et al. Enhanced prime editing systems by manipulating cellular determinants of editing outcomes. Cell 2021, 184, 5635–5652.e29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nelson, J.W.; Randolph, P.B.; Shen, S.P.; Everette, K.A.; Chen, P.J.; Anzalone, A.V.; An, M.; Newby, G.A.; Chen, J.C.; Hsu, A.; et al. Engineered pegRNAs improve prime editing efficiency. Nat. Biotechnol. 2022, 40, 402–410. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davis, J.R.; Banskota, S.; Levy, J.M.; Newby, G.A.; Wang, X.; Anzalone, A.V.; Nelson, A.T.; Chen, P.J.; Hennes, A.D.; An, M.; et al. Efficient prime editing in mouse brain, liver and heart with dual AAVs. Nat. Biotechnol. 2024, 42, 253–264. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roman, A.; Zimmer, A.; Gotthardt, M.; Steinmetz, L.M.; Kühn, R.; Dang, T. Prime editing corrects the dilated cardiomyopathy-causing RBM20-P633L mutation in human cardiomyocytes. Mol. Ther. Nucleic Acids 2025, 36, 102734. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nie, J.; Han, Y.; Jin, Z.; Hang, W.; Shu, H.; Wen, Z.; Ni, L.; Wang, D.W. Homology-directed repair of an MYBPC3 gene mutation in a rat model of hypertrophic cardiomyopathy. Gene Ther. 2023, 30, 520–527. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, Y.; Jiao, S.; Yang, G.; Wang, J.; Yang, X.; Li, Z. Correction of MYBPC3 c.772G>A splice-site mutation by base editing ameliorates hypertrophic cardiomyopathy in humanized mice. Circ. Res. 2026, 138, e327443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wan, P.; Tang, S.; Lin, D.; Lu, Y.; Long, M.; Xiao, L.; Jiang, Y.; Liao, J.; Ma, X.; Liu, Y.; et al. In vivo base editing gene therapy for heterozygous familial hypercholesterolemia: A phase 1 trial. Nat. Med. 2026, 32, 1045–1051. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jiang, Y.; Huang, L.; Qiu, H.; Yang, S.; Tao, J.; Chen, R.; Hao, Y. Clinical safety and tolerability of in vivo gene editing drug ART001 for ATTR amyloidosis. Front. Med. 2026, 13, 1783921. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Musunuru, K.; Chadwick, A.C.; Mizoguchi, T.; Garcia, S.P.; DeNizio, J.E.; Reiss, C.W.; Wang, K.; Iyer, S.; Dutta, C.; Clendaniel, V.; et al. In vivo CRISPR base editing of PCSK9 durably lowers cholesterol in primates. Nature 2021, 593, 429–434. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- ClinicalTrials.gov. A Study to Evaluate Nexiguran Ziclumeran in Participants with Transthyretin Amyloidosis with Cardiomyopathy (MAGNITUDE); NCT06128629; National Library of Medicine: Bethesda, MD, USA, 2026. Available online: https://clinicaltrials.gov/study/NCT06128629 (accessed on 13 August 2026).
- Qiu, M.; Glass, Z.; Chen, J.; Haas, M.; Jin, X.; Zhao, X.; Rui, X.; Ye, Z.; Li, Y.; Zhang, F.; et al. Lipid nanoparticle-mediated codelivery of Cas9 mRNA and single-guide RNA achieves liver-specific in vivo genome editing of Angptl3. Proc. Natl. Acad. Sci. USA 2021, 118, e2020401118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Janjuha, S.; Haenggi, T.; Chamberlain, T.C.; Rothgangl, T.; Kissling, L.; Wilhelm, M.; Mathis, N.; Boeck, D.; Marquart, K.; Ioannidi, E.; et al. Spatial profiling of gene editing by in situ sequencing in mice and macaques. Nat. Biomed. Eng. 2026, 10, 968–979. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kasiewicz, L.N.; Biswas, S.; Beach, A.; Ren, H.; Dutta, C.; Mazzola, A.M.; Rohde, E.; Chadwick, A.; Cheng, C.; Garcia, S.P.; et al. GalNAc-lipid nanoparticles enable non-LDLR dependent hepatic delivery of a CRISPR base editing therapy. Nat. Commun. 2023, 14, 2776. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rode, L.; Bär, C.; Groß, S.; Rossi, A.; Meumann, N.; Viereck, J.; Abbas, N.; Xiao, K.; Riedel, I.; Gietz, A.; et al. AAV capsid engineering identified two novel variants with improved in vivo tropism for cardiomyocytes. Mol. Ther. 2022, 30, 3601–3618. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, J.; Jonker, T.; Cervera-Barea, A.; Dong, Z.; Visser, R.N.; Birza, E.E.; Boender, A.R.; Klerk, M.; Yang, Y.; Visser, J.; et al. AAV6 vectors provide superior gene transfer compared to AAV9 vectors following intramyocardial administration. Mol. Ther. Methods Clin. Dev. 2025, 33, 101532. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mazurek, R.; Tharakan, S.; Mavropoulos, S.A.; Singleton, D.T.; Bikou, O.; Sakata, T.; Kariya, T.; Yamada, K.; Kohlbrenner, E.; Liang, L.; et al. AAV delivery strategy with mechanical support for safe and efficacious cardiac gene transfer in swine. Nat. Commun. 2024, 15, 10450. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Henry, T.D.; Chung, E.S.; Alvisi, M.; Sethna, F.; Murray, D.R.; Traverse, J.H.; Roessig, L.; Roberts, L.; Reddy, S.; Chen, Y.; et al. Cardiotropic AAV gene therapy for heart failure: A phase 1 trial. Nat. Med. 2025, 31, 3845–3852. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Labonia, M.C.I.; Estapé Senti, M.; van der Kraak, P.H.; Brans, M.A.D.; Dokter, I.; Streef, T.J.; Smits, A.M.; Deshantri, A.K.; de Jager, S.C.A.; Schiffelers, R.M.; et al. Cardiac delivery of modified mRNA using lipid nanoparticles: Cellular targets and biodistribution after intramyocardial administration. J. Control. Release 2024, 369, 734–745. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sun, Y.; Pien, Y.C.; Xiao, Y.; Tan, W.; Sanchez-Ortiz, E.; Durbacz, M.Z.; Chen, Z.; McAnally, J.R.; Zhang, Y.; Li, H.; et al. A human cardiomyocyte screen identifies optimized lipid nanoparticles for in vivo cardiac gene editing. Proc. Natl. Acad. Sci. USA 2026, 123, e2528477123. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Handa, K.; Kawamura, M.; Sasai, M.; Matsuzaki, T.; Harada, A.; Fujimura, L.; Whitehouse, J.; Saito, S.; Komukai, S.; Kitamura, T.; et al. Effective transcatheter intracoronary delivery of mRNA-lipid nanoparticles targeting the heart. J. Control. Release 2025, 381, 113623. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shuvaev, V.V.; Tam, Y.K.; Lee, B.W.; Myerson, J.W.; Herbst, A.; Kiseleva, R.Y.; Glassman, P.M.; Parhiz, H.; Alameh, M.G.; Pardi, N.; et al. Systemic delivery of biotherapeutic RNA to the myocardium transiently modulates cardiac contractility in vivo. Proc. Natl. Acad. Sci. USA 2025, 122, e2409266122. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- An, M.; Raguram, A.; Du, S.W.; Banskota, S.; Davis, J.R.; Newby, G.A.; Chen, P.Z.; Palczewski, K.; Liu, D.R. Engineered virus-like particles for transient delivery of prime editor ribonucleoprotein complexes in vivo. Nat. Biotechnol. 2024, 42, 1526–1537. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jiang, A.Y.; Cristian, A.; Brooks, D.L.; Feierman, E.R.; Chen, P.Z.; Whittaker, M.N.; Pierce, S.E.; Sakai, H.A.; Chen, H.; Liu, D.; et al. Efficient prime editing in vivo and in vitro using lipid nanoparticles. Nat. Nanotechnol. 2026, 21, 1022–1035. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hanlon, K.S.; Kleinstiver, B.P.; Garcia, S.P.; Zaborowski, M.P.; Volak, A.; Spirig, S.E.; Muller, A.; Sousa, A.A.; Tsai, S.Q.; Bengtsson, N.E.; et al. High levels of AAV vector integration into CRISPR-induced DNA breaks. Nat. Commun. 2019, 10, 4439. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- U.S. Food and Drug Administration. Safety Assessment of Genome Editing in Human Gene Therapy Products Using Next-Generation Sequencing: Draft Guidance for Industry; U.S. Food and Drug Administration: Silver Spring, MD, USA, 2026. Available online: https://www.fda.gov/media/191966/download (accessed on 13 August 2026).
- Cancellieri, S.; Zeng, J.; Lin, L.Y.; Tognon, M.; Nguyen, M.A.; Lin, J.; Bombieri, N.; Maitland, S.A.; Ciuculescu, M.F.; Katta, V.; et al. Human genetic diversity alters off-target outcomes of therapeutic gene editing. Nat. Genet. 2023, 55, 34–43. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Intellia Therapeutics, Inc. Current Report (Form 8-K), Filed 2 March 2026; U.S. Securities and Exchange Commission: Washington, DC, USA, 2026. Available online: https://www.sec.gov/Archives/edgar/data/1652130/000119312526084309/d101756d8k.htm (accessed on 13 August 2026).
- Charlesworth, C.T.; Deshpande, P.S.; Dever, D.P.; Camarena, J.; Lemgart, V.T.; Cromer, M.K.; Vakulskas, C.A.; Collingwood, M.A.; Zhang, L.; Bode, N.M.; et al. Identification of preexisting adaptive immunity to Cas9 proteins in humans. Nat. Med. 2019, 25, 249–254. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pabinger, I.; Ayash-Rashkovsky, M.; Escobar, M.; Konkle, B.A.; Mingot-Castellano, M.E.; Mullins, E.S.; Negrier, C.; Pan, L.; Rajavel, K.; Yan, B.; et al. Multicenter assessment and longitudinal study of the prevalence of antibodies and related adaptive immune responses to AAV in adult males with hemophilia. Gene Ther. 2024, 31, 273–284. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- U.S. Food and Drug Administration. Long Term Follow-Up After Administration of Human Gene Therapy Products: Guidance for Industry; U.S. Food and Drug Administration: Silver Spring, MD, USA, 2020. Available online: https://www.fda.gov/media/113768/download (accessed on 13 August 2026).
- U.S. Food and Drug Administration. Leveraging Prior Knowledge in the Development of Human Gene Therapy Products Incorporating Genome Editing: Draft Guidance for Industry; U.S. Food and Drug Administration: Silver Spring, MD, USA, 2026. Available online: https://www.fda.gov/media/192810/download (accessed on 13 August 2026).
- World Health Organization. Human Genome Editing: Recommendations; World Health Organization: Geneva, Switzerland, 2021; Available online: https://www.who.int/publications/i/item/9789240030381 (accessed on 13 August 2026).
- Musunuru, K.; Grandinette, S.A.; Wang, X.; Hudson, T.R.; Briseno, K.; Berry, A.M.; Hacker, J.L.; Hsu, A.; Silverstein, R.A.; Hille, L.T.; et al. Patient-specific in vivo gene editing to treat a rare genetic disease. N. Engl. J. Med. 2025, 392, 2235–2243. [Google Scholar] [CrossRef] [Scilit] [PubMed]
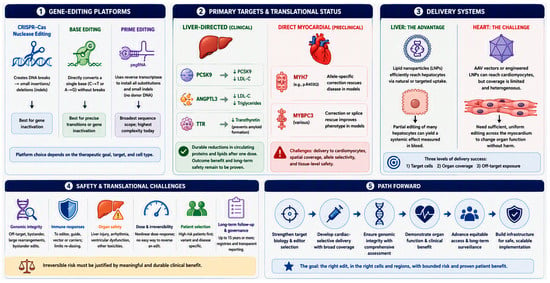
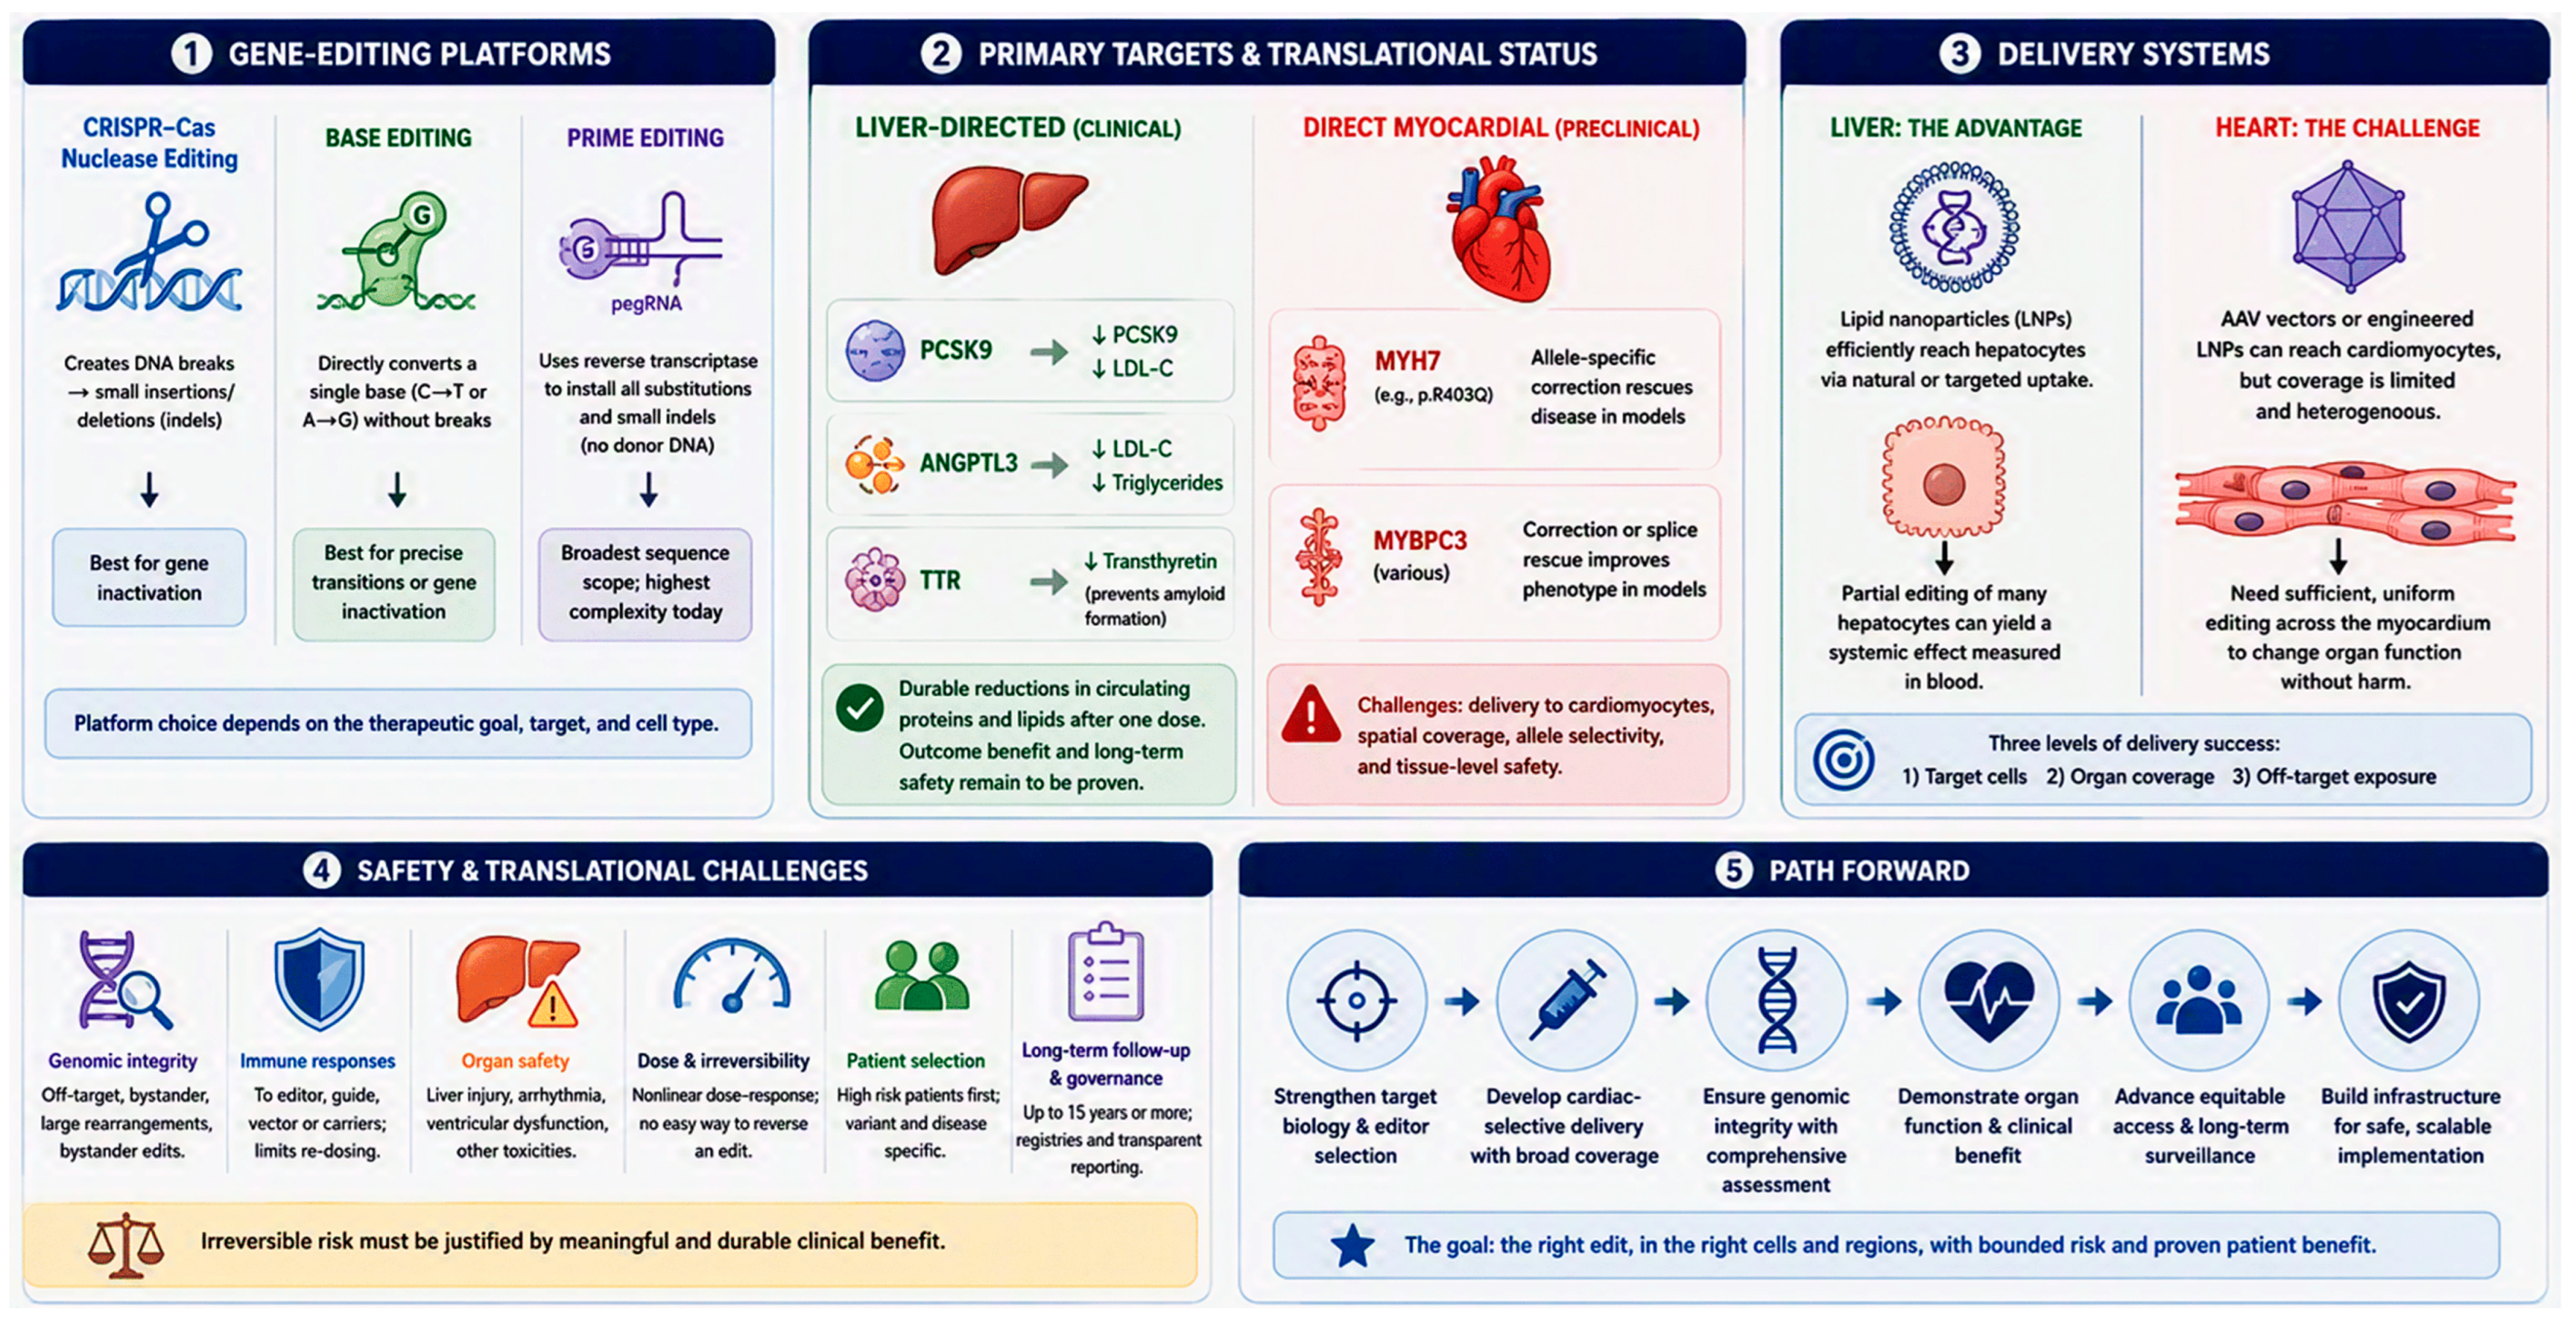

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.