


Abstract
We describe a case of maxillofacial trauma in a pediatric patient in whom the mandibular condyle was superolaterally displaced into the temporal fossa, medial to the zygomatic arch which was intact. In addition, there was an associated mandibular symphyseal fracture. To our knowledge, this case is the first of its kind to be reported in the literature. We also observed a complication in the form of development of ankylosis in the involved joint which required another surgery.
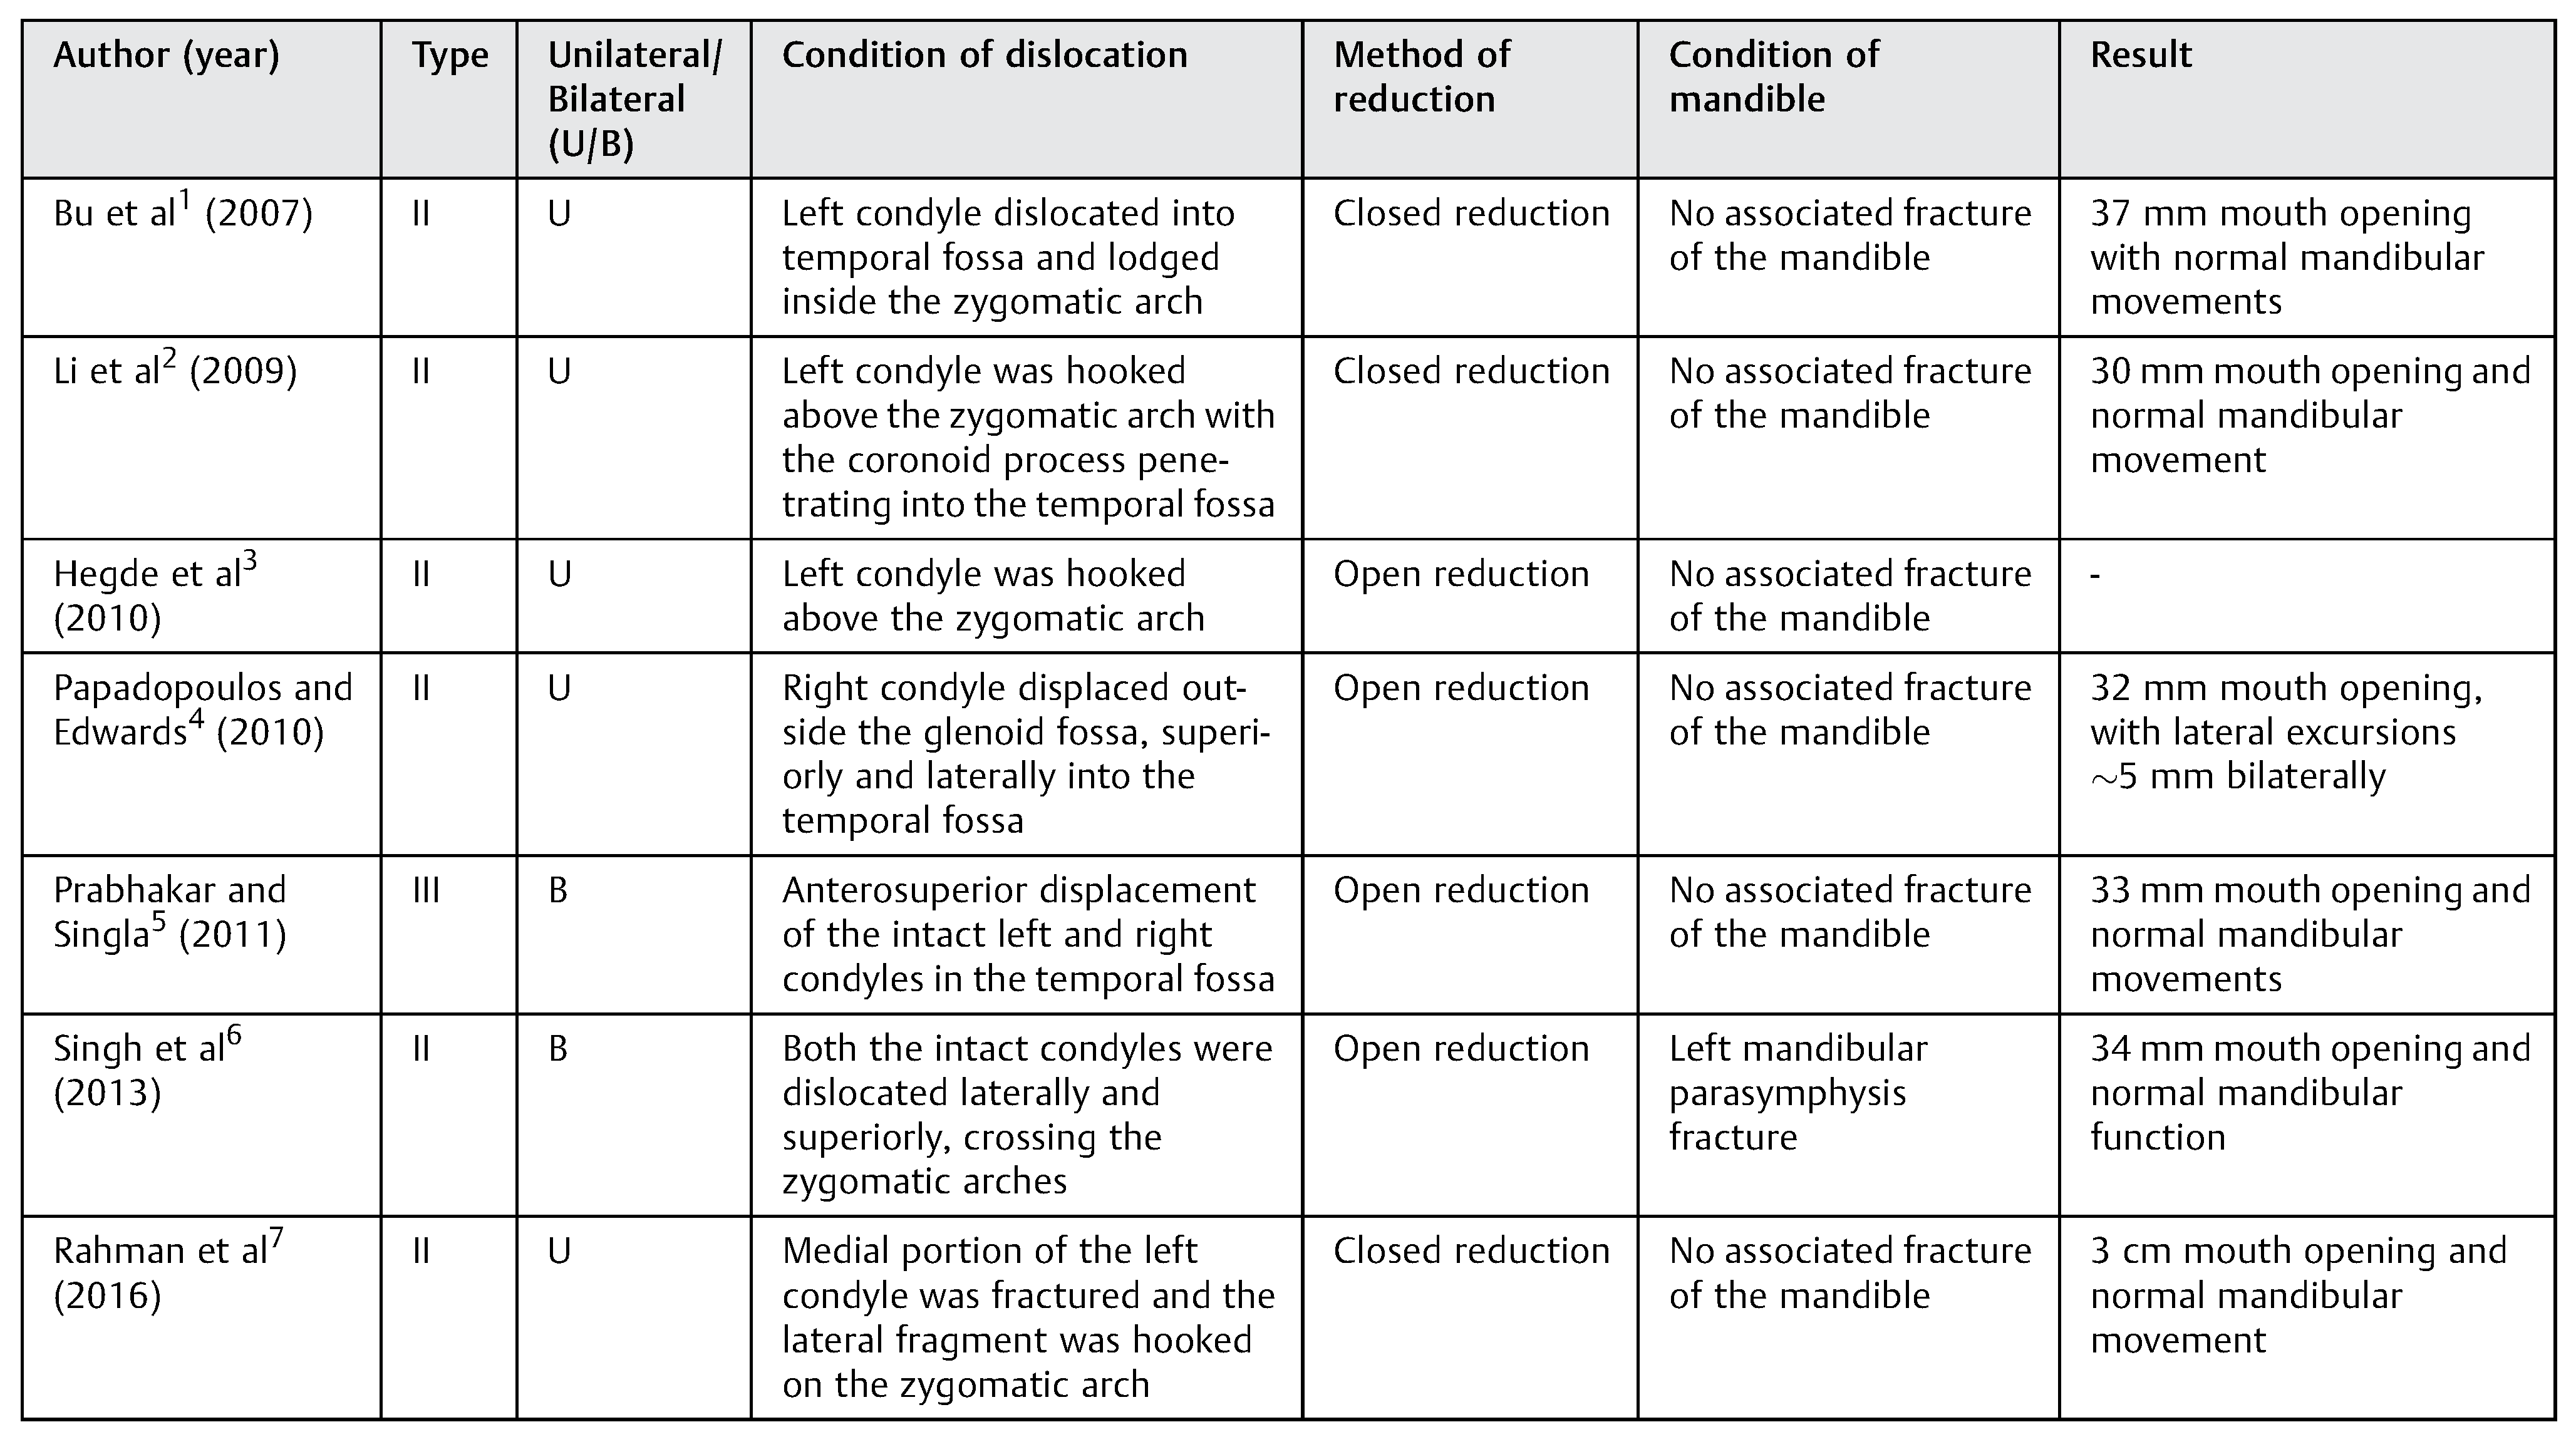
Superolateral dislocation of the intact mandibular condyle occurs very rarely. Only a handful of such cases are reported in the literature [1,2,3,4,5,6,7] (Table 1). The rarity of these dislocations can be attributed to the varying anatomy of the condyle, the direction of pull of muscles attached to the condyle, and position of the jaw at the time of impact. Superolateral dislocation of the intact condyle into temporal fossa is often overlooked and requires a thorough clinical and radiographic examination for correct diagnosis. In addition, there is a need for prompt management, as delay leads to imperfect reduction of the condyle due to trauma-induced fibrosis in glenoid fossa. We describe a case in which the patient reported late for treatment leading to ankylosis after successful reduction of the condyle into its anatomic position.
Case Report
A 7-year-old female reported to our OPD with the chief complaint of pain in lower jaw and facial deviation. History revealed that she sustained facial injuries 12 days back when she fell from a swing while playing. She had fractured right femur for which she was operated at a private hospital. After discharge, she reported to us.
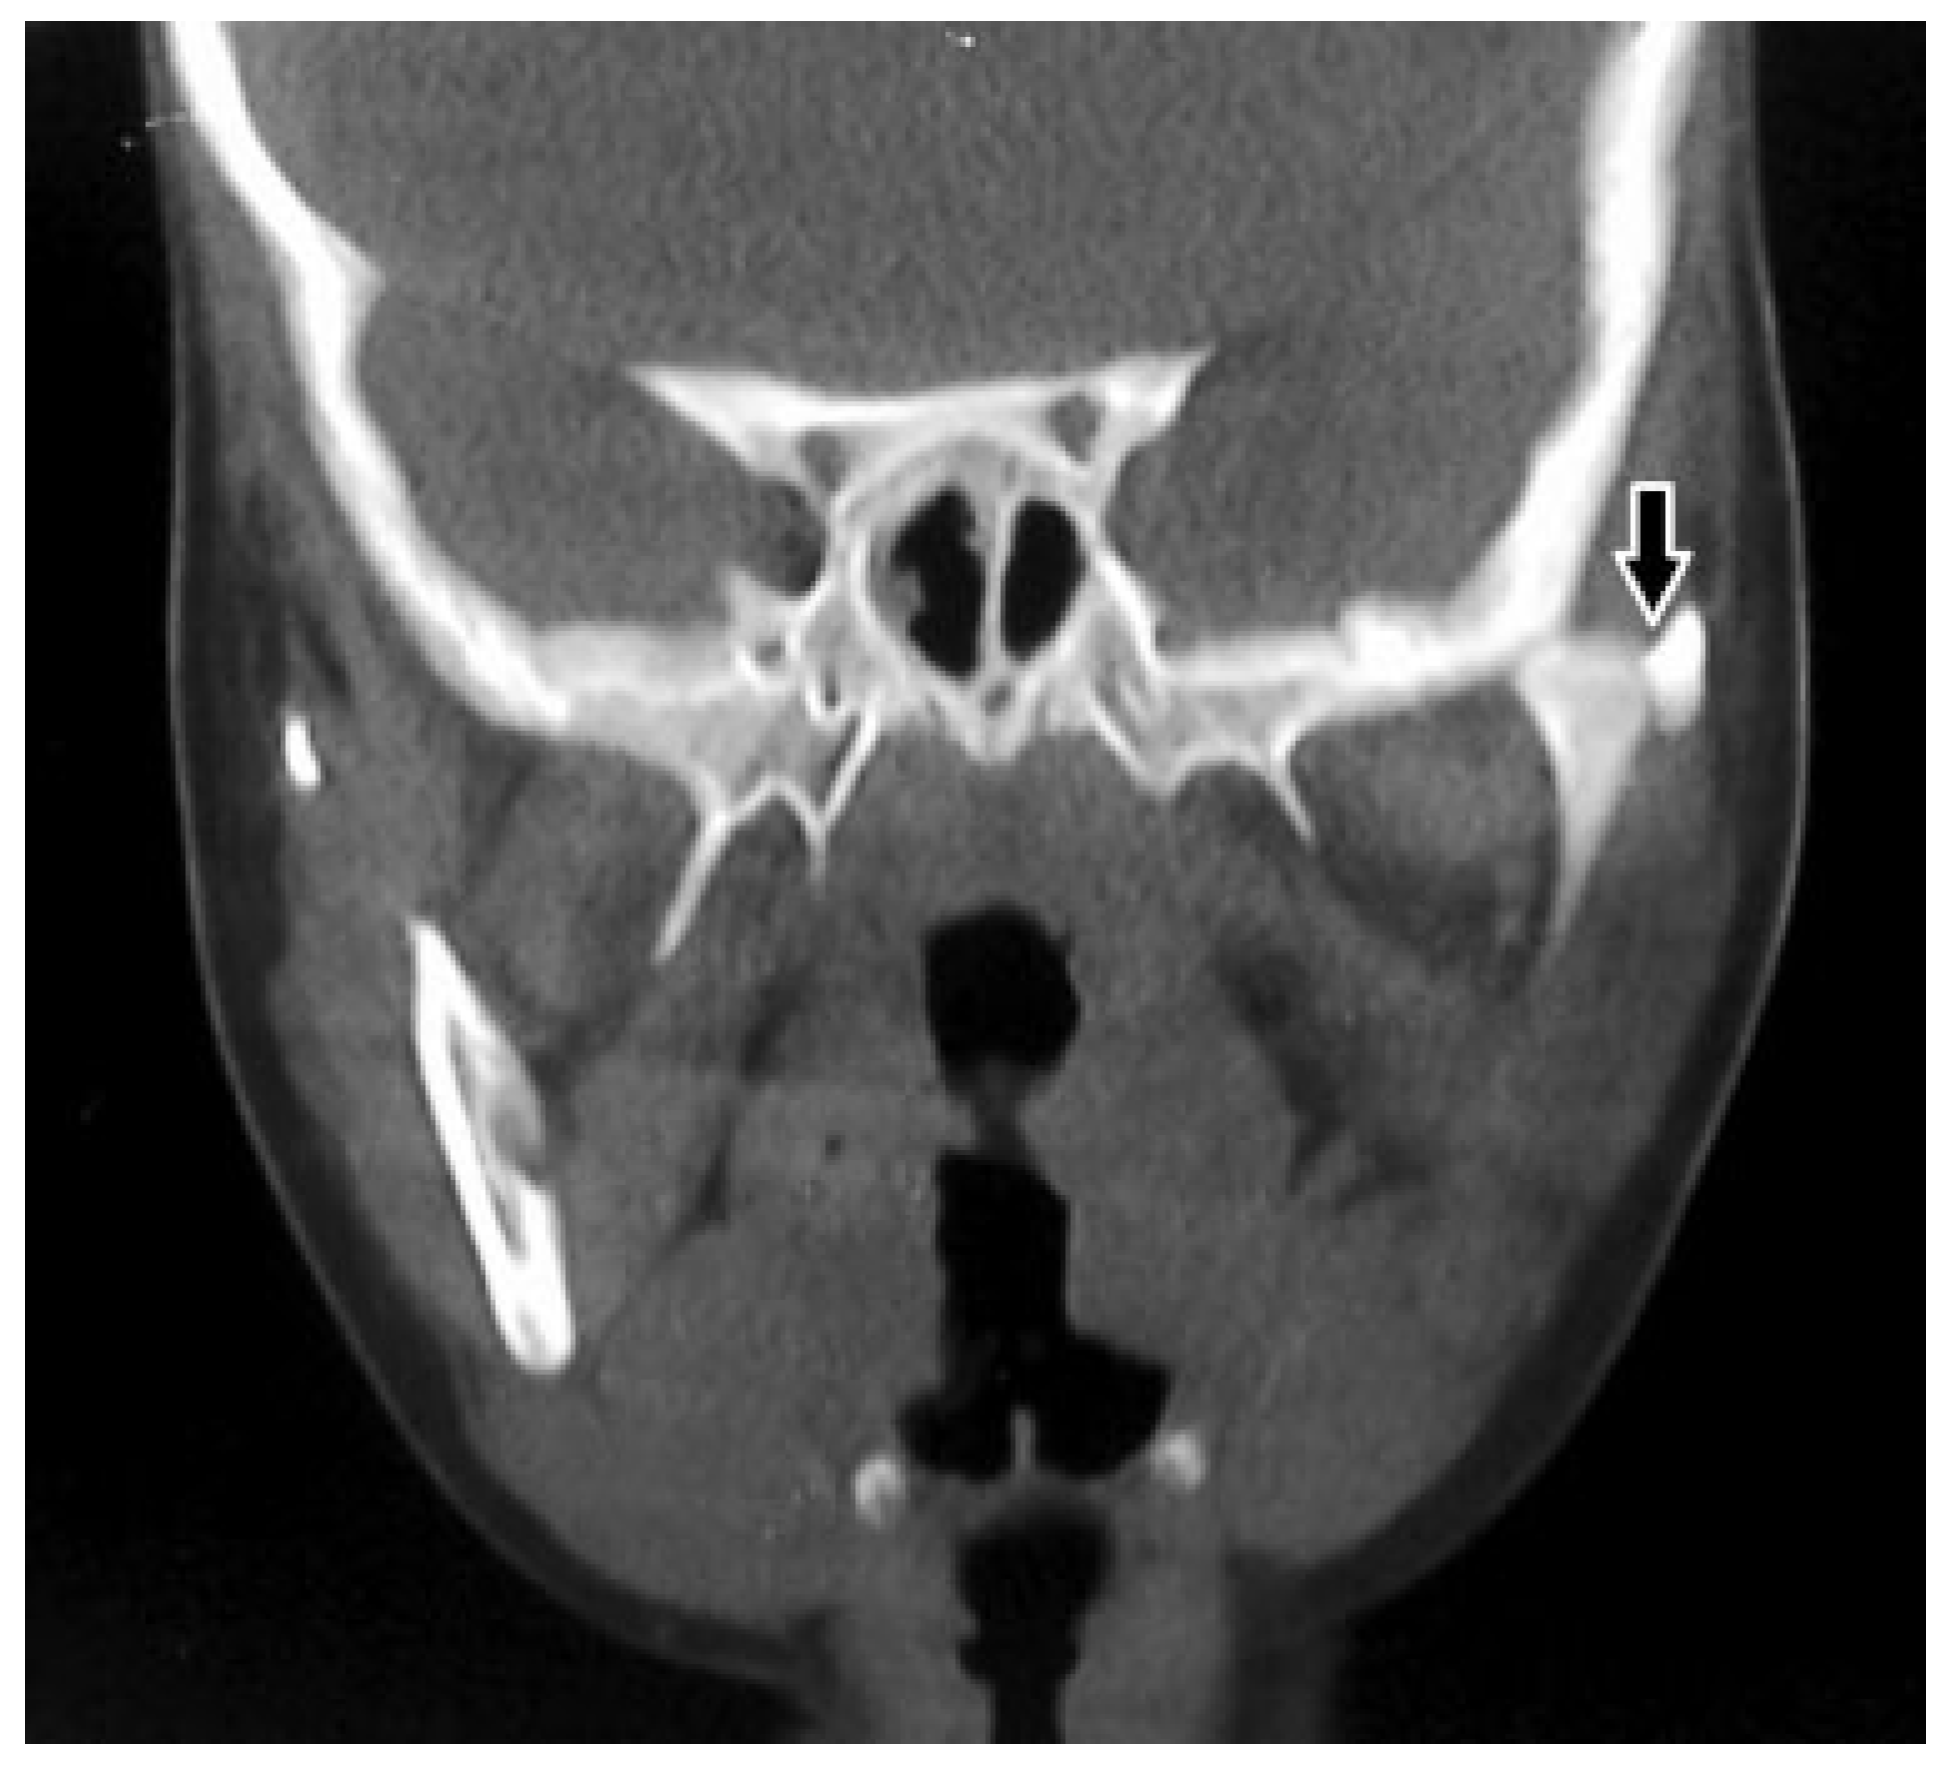
On examination, the jaw movements were severely restricted by pain with chin deviated toward right. The patient was unable to bring the teeth into occlusion. Left preauricular tenderness was apparent. Intraorally, permanent lower central and lateral incisor and deciduous upper right central incisor were missing and fracture was evident in the mandibular symphyseal region. A computed tomography (CT) was ordered which revealed that left mandibular condyle was dislodged from glenoid fossa into the temporal fossa deep to the zygomatic arch which was intact (Figure 1 and Figure 2).
We decided to reduce the condyle under general anesthesia. A mouth gag was placed between left posterior teeth and rotated clockwise to reduce the left condyle back into its normal position. The symphyseal fracture was reduced and fixed using 2.0-mm four hole miniplates. Mandibular movements and occlusion were verified and patient was extubated. The patient was discharged on the third postoperative day with intermaxillary fixation (IMF) for 10 days to prevent the reduced condyle from returning to the preoperative position. Thereafter, IMF was released and aggressive physiotherapy was advised. On follow-up, the patient exhibited continuously decreasing mouth opening with restriction of left temporomandibular joint (TMJ) movements and bony protuberance in left preauricular region. CTscan was ordered which confirmed ankylosis of left TMJ. Extended preauricular incision was given on the left side and interpositional arthroplasty was done using dermal fat from abdominal region after achieving an intraoperative mouth opening of 3.8 cm, and upon recovering the patient was discharged with instructions for aggressive physiotherapy. Patient was followed up till 6 months after which she was noncompliant to the follow-up schedule. The mouth opening measured at last follow-up appointment was 3.1 cm which was considered satisfactory.
Table 1.
Review of literature.
Discussion
Allen and Young [8] classified lateral dislocations of the mandibular condyle into type I (lateral subluxation) and type II (complete dislocation), in which the condyle is forced laterally and then superiorly. Type II dislocations were further subclassified by Satoh [9] et al. into type IIA (where the condyle is not hooked above the zygomatic arch); type IIB (where the condyle is hooked above the zygomatic arch); and type IIC (where the condyle is lodged inside the zygomatic arch, which is fractured). Allen and Young also suggested that an associated fracture of the anterior mandible is necessary for a type II dislocation. Our case had a unique presentation in a way that the intact condyle was dislodged inside the zygomatic arch, but the arch itself was intact. However, an associated symphyseal fracture was present. Bu [1] et al. reported a similar case but with anterior dislocation of right condyle and without any associated mandibular fracture.
Figure 1.
Three-dimensional computed tomographic image showing the displaced condyle and the intact zygomatic arch.
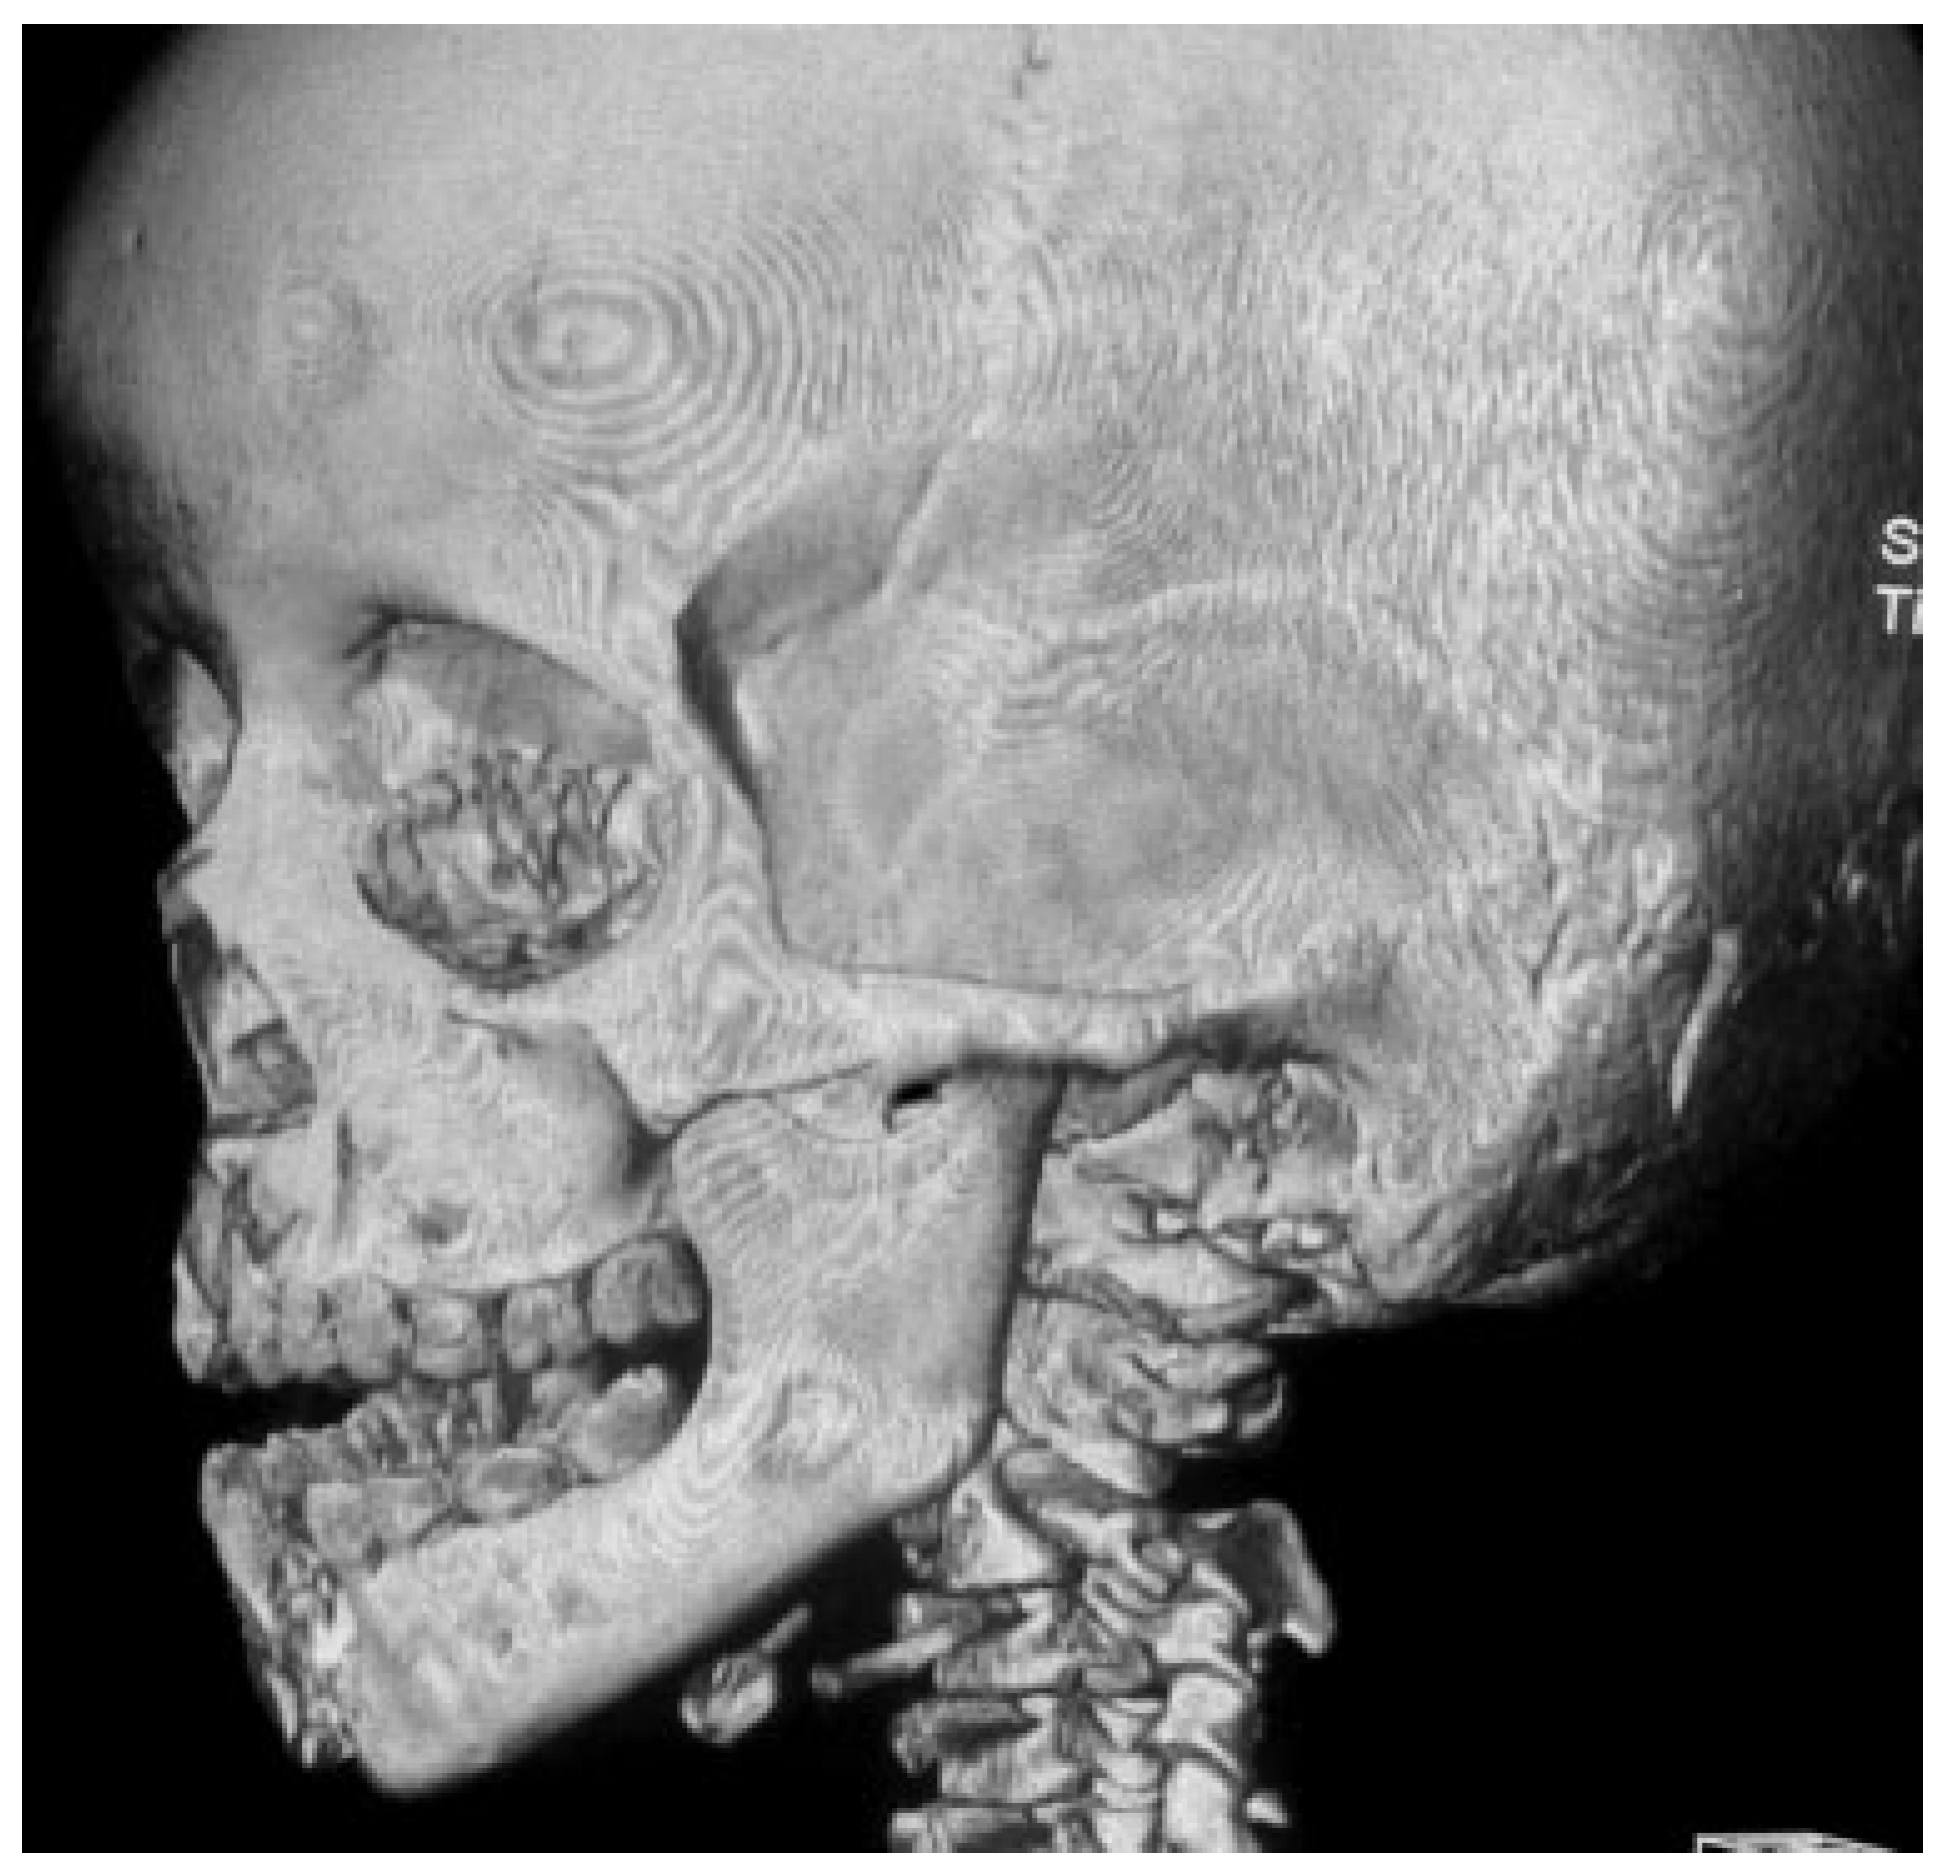
Figure 2.
Coronal section of computed tomographic image demonstrating the displaced condyle lying medial to the arch (arrow).
Worthington’s [10] criteria for diagnosis of these types of dislocation include malocclusion persisting after the jaw fracture was reduced, persistence of an open bite, persistent restriction of mandibular movement, an apparent loss of ramus height with elevation of the ramus fragment, and facial asymmetry.
CT scan proves very handy in diagnosing such conditions, as it can demonstrate the dislocated condyle, dislocation type, and whether or not there is a fracture,; which is evident in our case. Open traction with closed reduction should be attempted at the earliest if manual reduction or closed reduction under general anesthesia is unsuccessful. [9,10,11] In our case, the presence of symphyseal fracture facilitated easy reduction of the dislodged condyle. However, we believe that the ankylosis resulted from imperfect reduction of the condyle due to possible fibrosis of glenoid fossa caused by the delay in treatment.
References
- Bu, S.S.; Jin, S.L.; Yin, L. Superolateral dislocation of the intact mandibular condyle into the temporal fossa: Review of the literature and report of a case. Oral Surg Oral Med Oral Pathol Oral Radiol Endod 2007, 103, 185–189. [Google Scholar] [PubMed]
- Li, Z.; Li, Z.B.; Shang, Z.J.; Wu, Z.X. An unusual type of superolateral dislocation of mandibular condyle: Discussion of the causative mechanisms and clinical characteristics. J Oral Maxillofac Surg 2009, 67, 431–435. [Google Scholar] [PubMed]
- Hegde, S.; Kamath, V.V.; Deepa, M.; Priya, A. Superolateral dislocation of the mandibular condyle not associated with fracture: A case report. J Maxillofac Oral Surg 2010, 9, 424–427. [Google Scholar] [PubMed]
- Papadopoulos, H.; Edwards, R.S. Superolateral dislocation of the condyle: Report of a rare case. Int J Oral Maxillofac Surg 2010, 39, 508–510. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Prabhakar, V.; Singla, S. Bilateral anterosuperior dislocation of intact mandibular condyles in the temporal fossa. Int J Oral Maxillofac Surg 2011, 40, 640–643. [Google Scholar] [PubMed]
- Singh, V.; Gupta, P.; Khatana, S.; Bhagol, A. Superolateral dislocation of bilateral intact condyles-an unusual presentation: Report of a case and review of literature. Craniomaxillofac Trauma Reconstr 2013, 6, 205–210. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rahman, T.; Hashmi, G.S.; Ansari, M.K. Traumatic superolateral dislocation of the mandibular condyle: Case report and review. Br J Oral Maxillofac Surg 2016, 54, 457–459. [Google Scholar] [PubMed]
- Allen, F.J.; Young, A.H. Lateral displacement of the intact mandibular condyle. A report of five cases. Br J Oral Surg 1969, 7, 24–30. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Satoh, K.; Suzuki, H.; Matsuzaki, S. A type II lateral dislocation of bilateral intact mandibular condyles with a proposed new classification. Plast Reconstr Surg 1994, 93, 598–602. [Google Scholar] [PubMed]
- Worthington, P. Dislocation of the mandibular condyle into the temporal fossa. J Maxillofac Surg 1982, 10, 24–27. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kallal, R.H.; Gans, B.J.; Lagrotteria, L.B. Cranial dislocation of mandibular condyle. Oral Surg Oral Med Oral Pathol 1977, 43, 2–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
© 2017 by the author. The Author(s) 2017.