


Abstract
Chronic otitis media (COM) has been considered as a localized disease, and its systemic impact is poorly understood. Whether COM-induced inflammation could be associated with systemic bone loss and hip fracture is unknown at present. Our study tried to determine the risk of hip fracture among COM patients. We selected the comparison individuals without the COM coding and paired the controls with COM patients by gender, age, and comorbidities (including osteoporosis) by about a one-to-two ratio. Our study showed that the incidence of hip fracture was 4.48 and 3.92 per 1000 person-years for comparison and COM cohorts respectively. The cumulative incidence of hip fracture is higher in the COM cohort (p < 0.001). After adjustment for gender, age, and comorbidities, the COM patients had a 1.11-fold (aHR = 1.11; 95% CI = 1.05–1.17) risk of hip fracture than the control subjects. Among COM patients, a history of hearing loss is associated with higher (aHR = 1.21; 95% CI = 1.20–1.42) fracture risk. Our study showed that COM patients, especially those with hearing loss, are susceptible to a higher risk for hip fracture.
1. Introduction
Chronic otitis media (COM) is manifested by inflammation of the middle ear due to infectious or non-infections processes, resulting in pathologic changes in the tympanic membrane [1]. The pathologic changes of the tympanic membrane secondary to COM include atelectasis, perforation, retraction, tympanosclerosis, and cholesteatoma [1,2]. COM is also an important etiology of acquired hearing loss and is the main disease in the field of otolaryngology [1]. COM can lead to potentially deadly complications such as mastoiditis, petrositis, labyrinthitis, meningitis, brain abscess, and thrombophlebitis [1]. Despite the potentially fatal nature of the complications mentioned above, these complications are local in nature and the systemic effects of COM are unknown currently.
Bone loss is a recognized consequence of systemic inflammatory processes, which could be explained by the perspective of evolution, disturbed energy expenditure and storage, and immunologic as well as neuroendocrine factors [3]. There is also a genetic linkage between auditory tract disease and bone loss. For example, FBXO11 is associated with the susceptibility to otitis media and affects osteoblastogenesis [4,5,6]. The correlations between inflammation, shared genetic factors, and the impact of COM on bone metabolism have not been rigorously determined.
The most devastating complication secondary to bone loss is hip fracture [7]. Hip fractures are accountable for 25% of geriatric fractures mandating hospitalization with high morbidity and mortality [8]. There is no available evidence demonstrating whether COM-induced inflammation could be associated with systemic bone loss and hip fracture. In our study, we want to investigate the incidence of hip fracture among subjects with COM. We thus conducted a nationwide population-based study, attempting to unravel the association between COM and hip fracture. We hypothesize that COM patients might be predisposed to a higher risk of hip fracture.
2. Materials and Methods
The Longitudinal Health Insurance Database (LHID) of the National Health Insurance Research Database (NHIRD) was employed for our study under the approval of the Institutional Review Board of China Medical University, Taichung, Taiwan (CMUH104-REC2–115). The LHID is composed of the registry data for the beneficiaries, inpatient and outpatient files, and the registry for drug prescriptions as well as medical services. The history of medical comorbidities of the insured individuals was retrieved from the inpatient and outpatient files. The International Classification of Diseases, 9th Revision, Clinical Modification (ICD-9-CM) system was applied as the disease-coding system in NHIRD. The original identification numbers were eliminated to safeguard the privacy of the insured citizens, and a scrambled number was offered to correlate the claim data to each individual before releasing the data for research purposes.
A population-based cohort study was established to determine the incidence of hip fracture (ICD-9-CM code 820.x) among the subjects with COM. All of the patients who were coded with COM (ICD-9-CM code 382.1–382.9) first in their lifetime from 1 January 2000 to 31 December 2013, were assessed. The date when the diagnosis of COM was initially coded was defined as the index date. The comparison individuals without the diagnostic coding of COM were chosen from the LHID and paired with COM patients by gender, age (exact year), and the coding of osteoporosis (ICD-9-CM 733.0 and 733.1) at the index date by about a one-to-two ratio. The comparison subjects were recruited on the same date as the paired COM patients. All of the enrolled individuals were followed until the withdrawal from the insurance, the advent of hip fracture, or until 31 December 2013. The comorbidities analyzed in our study included hypertension (ICD-9-CM code 401–405), diabetes (ICD-9-CM code 250), epilepsy (ICD-9-CM code 345, A225), ischemic heart disease (ICD-9-CM code 410–414), chronic obstructive pulmonary disease (COPD, ICD-9-CM code 491, 492, 493 and 496), stroke (ICD-9-CM code 430–438), liver cirrhosis (ICD-9-CM code 571 and 572), osteoporosis (ICD-9-CM code 733) and end-stage renal disease (ICD-9-CM code 585.6). The impact of hearing loss (ICD-9-CM code 389), vertigo (ICD-9-CM code 386), and tinnitus (ICD-9-CM code 388.3) on the occurrence of hip fractures among COM patients were also analyzed.
The incidence rate of hip fracture was expressed as events per 1,000 person-years. The chi-square test for categorical variables and the two-sample t-test for continuous variables were applied for between-group comparisons. The Kaplan–Meier method was utilized to plot the cumulative incidence of hip fractures, and the log-rank test was employed to determine the significance of between-group differences [9,10]. To demonstrate the risk of hip fracture for the COM and control cohorts, the crude and adjusted hazard ratios (cHRs and aHRs) and 95% confidence intervals (CIs) were calculated by employing the single- and multi-variable Cox proportional hazard models [11]. The SAS 9.4 software (SAS Institute, Cary, NC, USA) was applied for data analysis and the R software (R Foundation for Statistical Computing, Vienna, Austria) was employed to plot the incidence curves.
3. Results
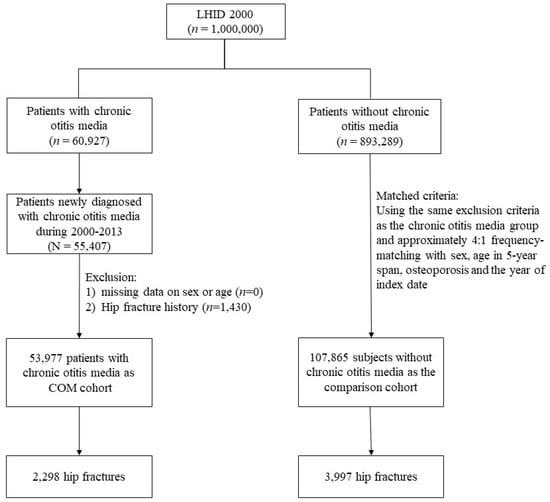
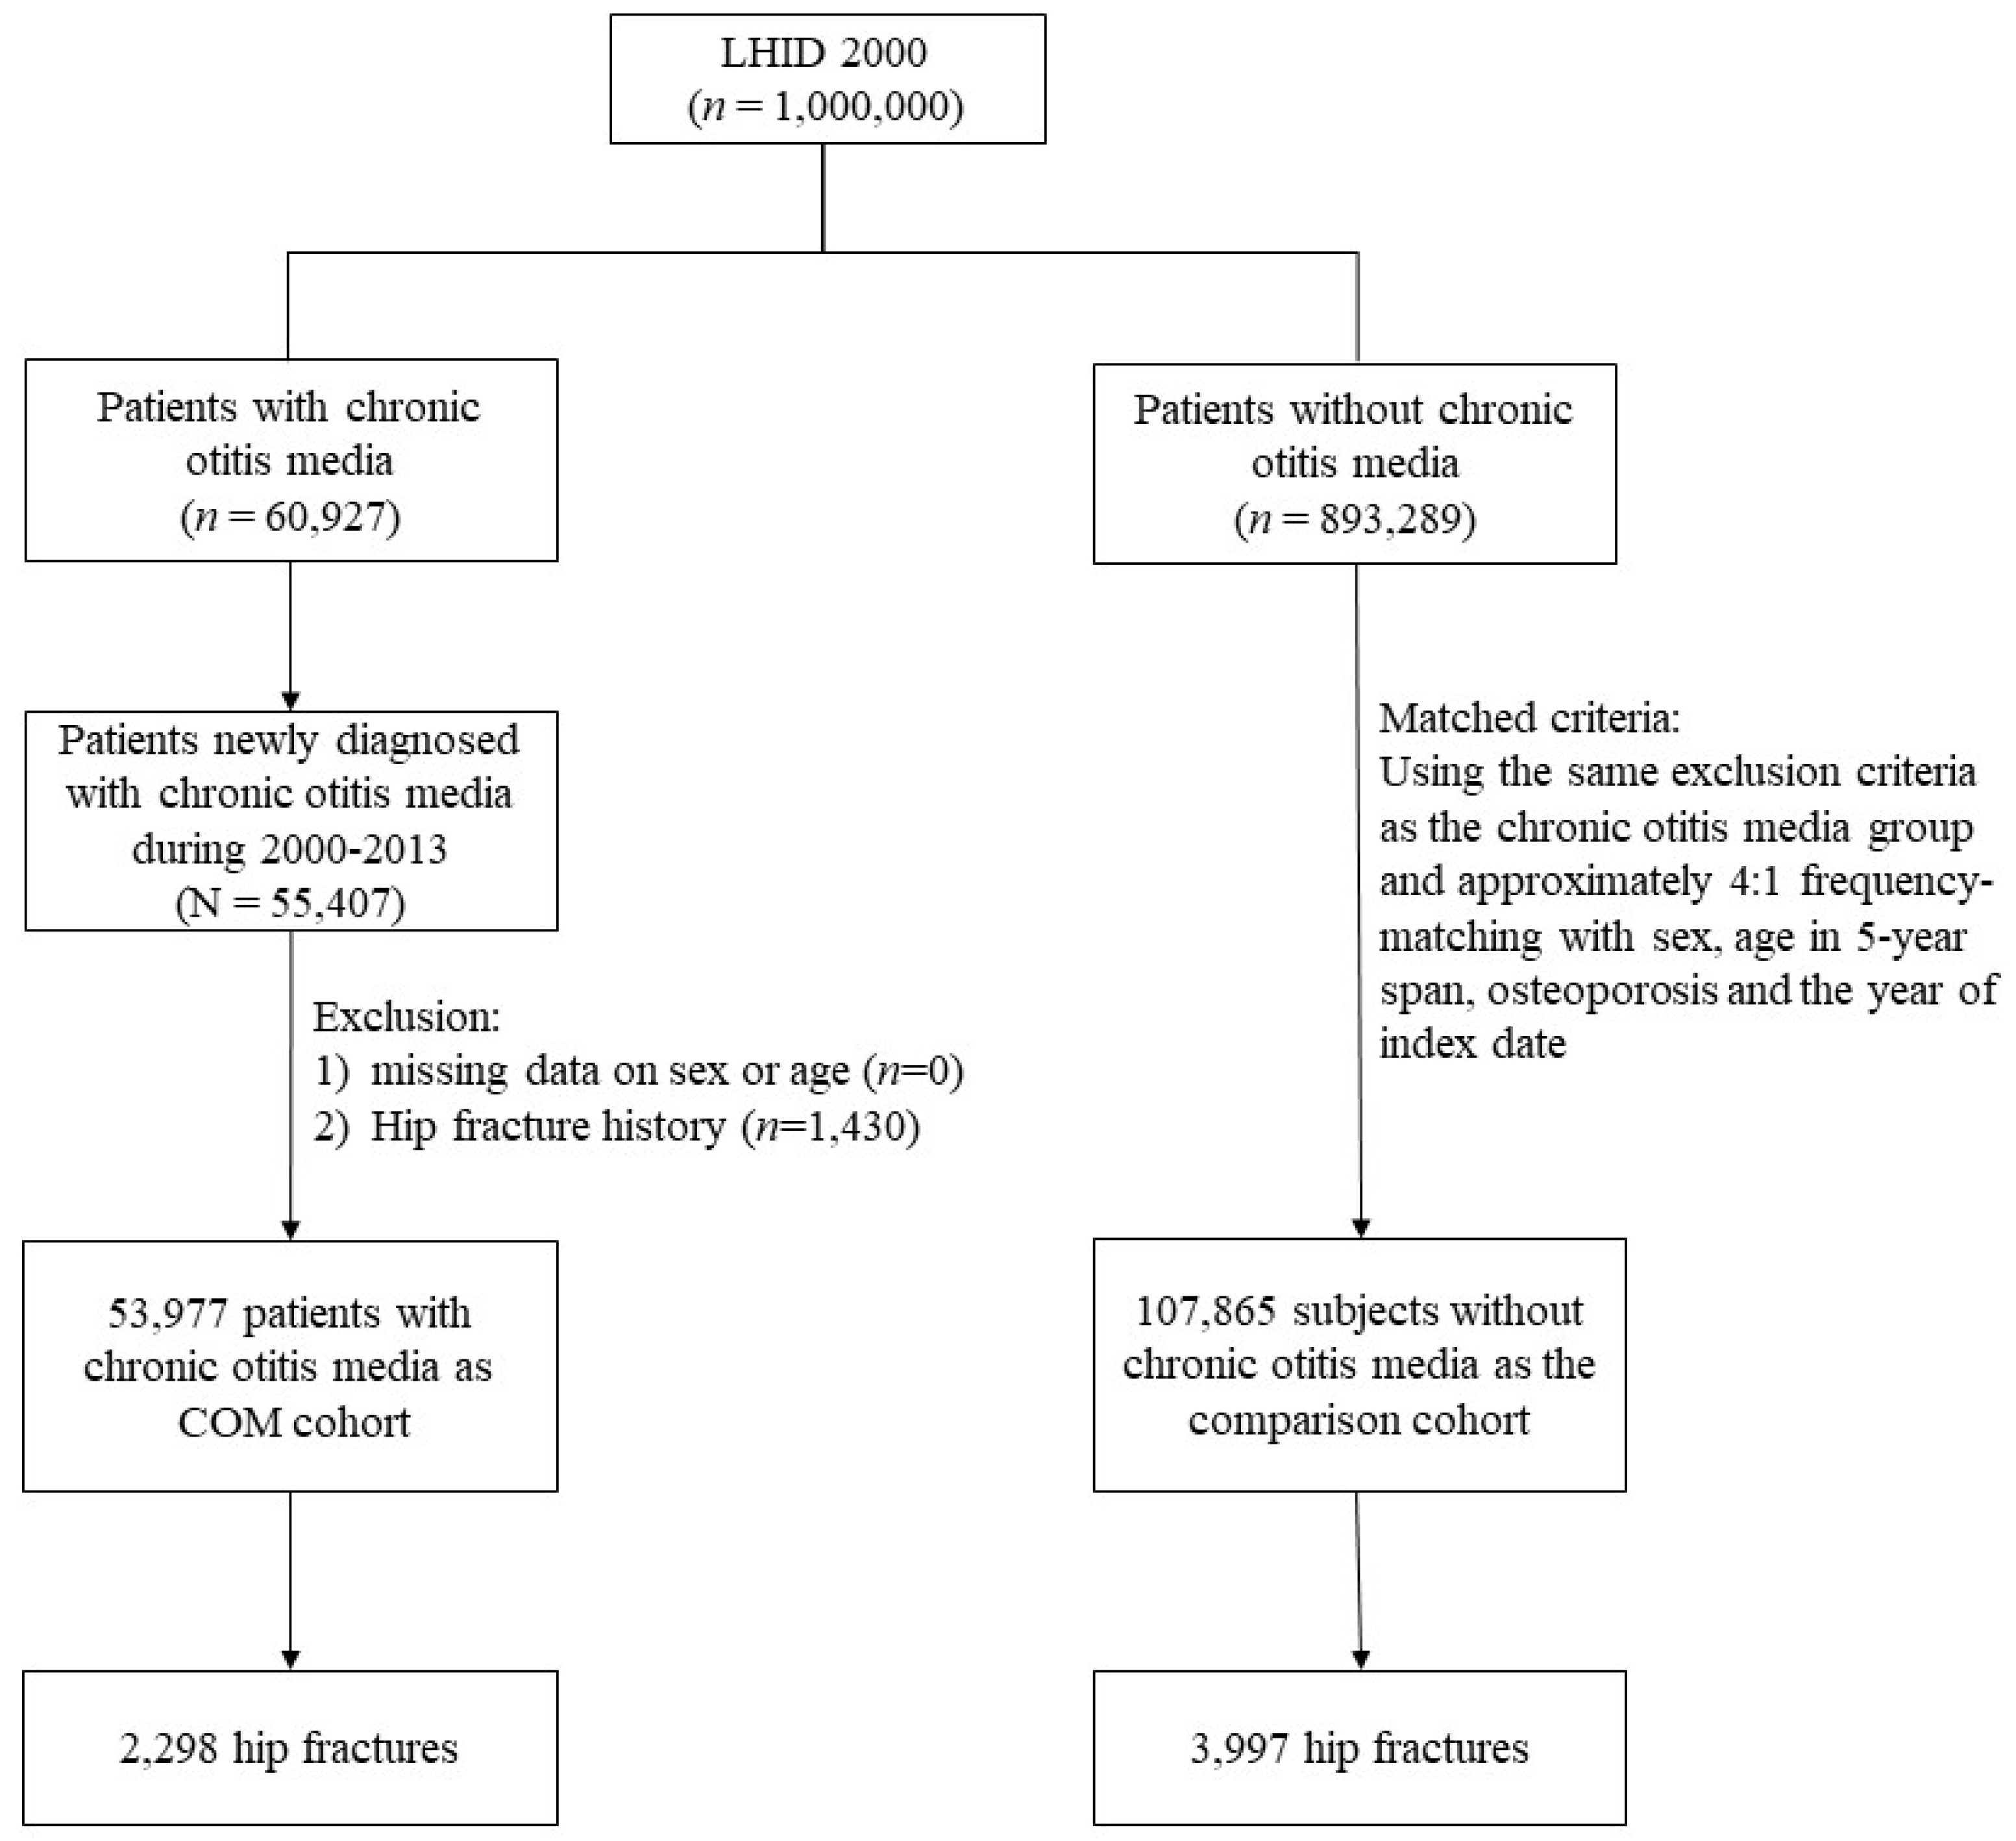
There were 53,997 patients in the COM cohort and 107,865 individuals in the comparison cohort. The distribution of gender, age, and the percentage with the initial diagnosis of osteoporosis were comparable between the two cohorts. The mean age of COM and comparison cohorts were 27.8 ± 86.0 and 28.1 ± 84.4 years, respectively (Table 1). The prevalence of hypertension, diabetes, epilepsy, ischemic heart disease, chronic obstructive pulmonary disease, stroke, and liver cirrhosis were all higher in the COM cohort (all p < 0.001). The follow-up duration was 9.49 ±3.7 years for the COM cohort and 9.43 ± 3.7 years for the comparison cohort. The flow diagram for the subject recruitment process was shown in Figure 1.
Table 1.
Demographic profiles for the COM and comparison cohorts.
Figure 1.
The flow diagram of the recruitment process.
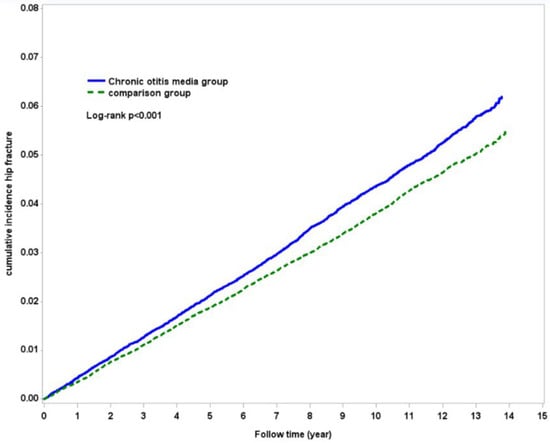
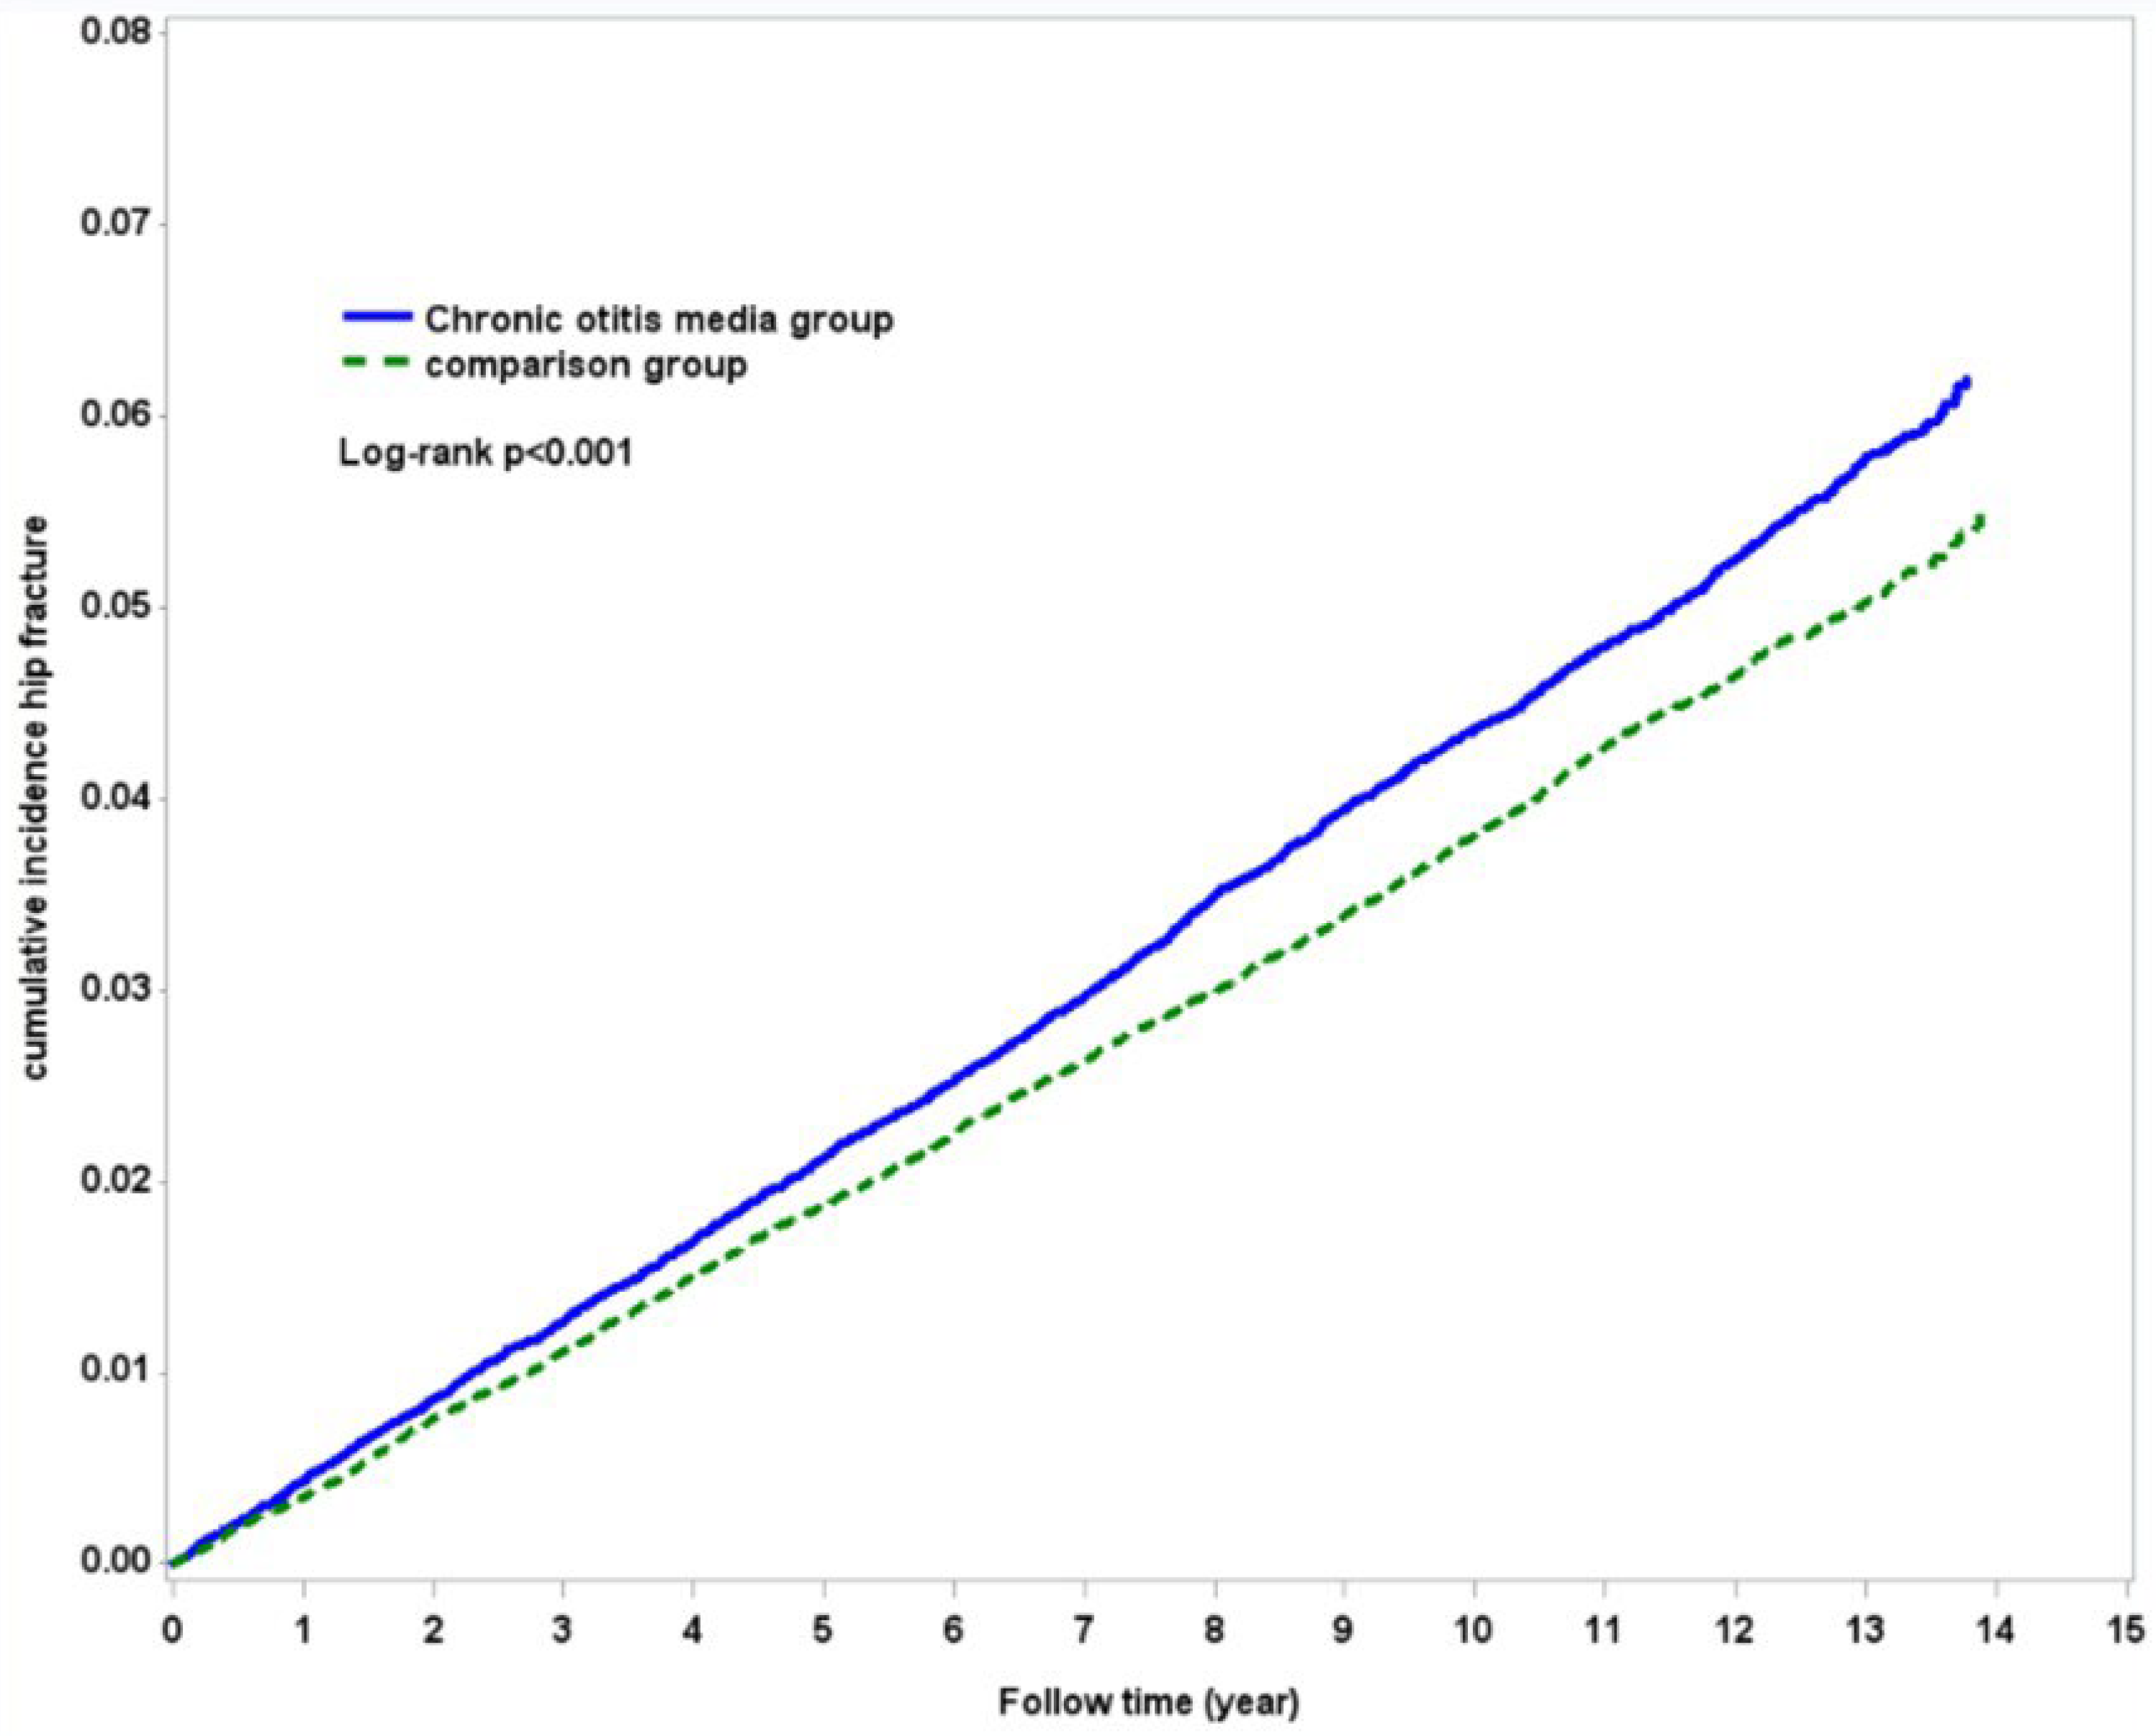
There were 2298 hip fractures in the COM cohort with an incidence density of 4.48 per 1000 person-years. As for the comparison cohort, 3997 individuals suffered from hip fractures with an incidence density of 3.92 per 1000 person-years (Table 2). The cumulative incidence of hip fracture was higher in the COM cohort than in the comparison cohort (Figure 2, p < 0.001 for log-rank test). After adjustment for gender, age, and all of the enlisted comorbidities, the subjects in the COM cohort had a 1.11-fold risk of hip fracture than the individuals in the comparison cohort (aHR = 1.11; 95% CI = 1.05–1.17). Age, gender, hypertension, diabetes, epilepsy, chronic obstructive pulmonary disease, stroke, and osteoporosis were also associated with a higher incidence of hip fracture in our model.
Table 2.
The incidence density of hip fracture stratified by the history of chronic otitis media, gender, age, and comorbidities.
Figure 2.
The incidence of hip fracture among COM and comparison cohorts. The dashed line indicates the comparison cohort, and the solid line indicates the COM cohort.
Table 3 showed that the impact of COM and on the risk of hip fracture was more pronounced among subjects with female gender (aHR = 1.17; 95% CI = 1.09–1.26), hypertension (aHR = 1.14; 95% CI = 1.05–1.24), diabetes (aHR = 1.19; 95% CI = 1.07–1.32), ischemic heart disease (aHR = 1.15; 95% CI = 1.00–1.33), and chronic obstructive pulmonary disease (aHR = 1.14; 95% CI = 1.02–1.27).
Table 3.
Differential incidence rate and hazard ratio of hip fracture among the subjects with and without chronic otitis media stratified by gender, age, and comorbidities.
Among the COM patients, a history of hearing loss is associated with a higher (aHR = 1.21; 95% CI = 1.20–1.42) risk of hip fracture (Table 4).
Table 4.
The subgroup analysis risk of hip fractures among the COM patients.
4. Discussion
COM has been considered as a localized disease, and its systemic impact is poorly understood. In our study, we showed that the COM patients were subject to 1.11-fold the risk of suffering from hip fracture than the comparison individuals (95% CI = 1.05–1.17). The impact of COM was more prominent among the subjects of female gender, hypertension, diabetes, ischemic heart disease, and chronic obstructive pulmonary disease. Among the COM patients, the history of hearing loss furtherly increased the risk of hip fracture. These results indicate that COM is not merely a “localized” disease.
The pathophysiologic linkage between COM and osteoporotic hip fracture is not clear at present. However, the inflammation and genetic factor could potentially be the pathophysiologic linkage between COM and hip fracture.
As for inflammation, the “three-pillar theory” has been proposed to account for the bone loss under inflammation, including evolution, disturbed energy expenditure and storage, and immunologic as well as endocrine factors [3]. Inflammation has been shown to be involved in the pathogenesis of both auditory tract disease and systemic bone loss. Wang et al. have shown that the osteoporosis cohort displayed a 1.32-fold risk to suffer from acquired cholesteatoma compared with the control cohort (aHR = 1.32; 95% CI = 1.11–1.57), thus suggesting that otolaryngologists should examine the middle ear of osteoporotic patients [12]. Additionally, cholesteatoma is characterized by bone erosion in the middle ear, and increased expression of receptor activator for nuclear factor-κB ligand (RANKL) and osteoprotegerin (OPG) is found in tissues of cholesteatoma [13,14,15]. These results nicely demonstrated the correlation between bone loss and the inflammation of the auditory tract. In our study, we demonstrated that the COM patients had 1.11 times the risk of suffering from hip fracture when compared with the paired comparison individuals. Our study supplemented the previous publications in bridging the association between the inflammation of the auditory tract and bone disease.
A shared genetic factor could be the potential nexus between COM and systemic bone loss. Otitis media (recurrent acute otitis media, chronic otitis media with effusion) is largely associated with genetic susceptibility (40–70%) [16]. Mahmood et al. demonstrated the association between COM and the genetic loci of FBXO11 and TGIF1, both of which are involved in the transforming growth factor -beta (TGF-β) signaling via regulating the Smad proteins [17]. Smad proteins are involved in osteoclastogenesis via the RANKL–RANK interplay [18]. FBXO11 can inhibit the transcriptional activity of the p53 gene via promoting its neddylation as a function of Nedd8-ligase and affects its synergistic cooperation with phospho-Smad2 protein on TGF-β signaling [19]. Phospho-Smad2 could enhance the gene expression specific to osteoclast, resulting in inflammatory bone destruction [18]. Furthermore, p53 itself also suppresses osteoblastogenesis and thus results in reduced bone formation [6,20]. As for TGIF1, it has also been shown that TGIF1 knockout mice could develop COM with suppressed Smad expression in middle ear epithelial cells [21]. Vertigo and dizziness are the clinical manifestations of COM, and a previous study revealed that they could increase the risk of falling [22]. The associations between genetic factors, COM, precipitation to falling, and hip fracture warrant further investigations.
We also displayed that the history of hearing loss coincided with a higher risk of hip fracture among the COM patients. Previous studies have shown that osteoporosis was associated with decreased ossicle mass, decreased bone density of the cochlea, and disturbed sound transmission to the cochlea, which end up having a higher incidence of a sensorineural type of hearing loss [23,24]. Yoo et al. analyzed 2588 women and 2273 men aged over 50 years to determine the correlation between senile hearing loss and osteoporosis. The authors demonstrated that individuals with decreased femoral neck bone mineral density could sustain a 1.7-fold risk of suffering from hearing loss (p < 0.01) [20]. In our study, the history of hearing loss is associated with a higher (aHR = 1.21; 95% CI = 1.20–1.42) risk of suffering from hip fracture among COM patients. The shown impact of hearing loss on the onset of hip fracture among COM patients in our study supplemented the knowledge concerning the correlation between hearing loss and bone disease.
Our study is not free from limitations. First, the NHIRD did not include all the known risk factors for hip fracture. Some important risk factors, such as vitamin D deficiency and family history, could not be retrieved from the NHIRD. In fact, it is impossible and not necessary to include every known risk factor of hip fracture for analysis. The optimal way to determine the impact of COM on the occurrence of hip fracture was propensity score matching. The absence of propensity score matching would raise the concern that the association between COM and hip fracture might be secondary to the un-recognized medical comorbidities associated with COM. However, excessive matching could skew the generalizability of our findings, so we only paired the coding of osteoporosis in this study and rigorously adjusted all the retrieval comorbidity factors in our regression model instead. Our group has been dedicated to unraveling the association between diseases that can stimulate inflammatory responses and hip fracture. Our future work will continue to unravel more disease entities that could predispose patients to hip fracture. We hope that our work can help in optimizing the risk prediction of, or even prevent, hip fracture.
5. Conclusions
- ✓
- The incidence of hip fracture was 4.48 and 3.92 per 1000 person-years for comparison and COM cohorts respectively. After adjustment for gender, age, and comorbidities, the COM patients had a 1.11-fold (aHR = 1.11; 95% CI = 1.05–1.17) risk of hip fracture than the control subjects.
- ✓
- The cumulative incidence of hip fracture is higher in the COM cohort (p < 0.001) than in the comparison cohort.
- ✓
- Among the COM patients, a history of hearing loss is associated with higher (aHR = 1.21; 95% CI = 1.20–1.42) fracture risk.
Author Contributions
Conceptualization, S.-J.K. and S.-L.H.; methodology, S.-J.K. and P.-S.L.; software, Y.-C.Y.; validation, P.-S.L., C.-C.C. and Y.-H.F.; formal analysis, Y.-H.F., C.-C.H. and K.-F.L.; investigation, S.-J.K., K.-F.L. and Y.-C.Y.; resources, S.-J.K., Y.-C.Y. and S.-L.H.; data curation, P.-S.L. and C.-C.C.; writing—original draft preparation, Y.-H.F., C.-C.H., and K.-F.L.; writing—review and editing, P.-S.L., C.-C.C. and S.-J.K.; visualization, S.-L.H.; supervision, S.-J.K. and S.-L.H.; project administration, P.-S.L. and C.-C.C.; funding acquisition, S.-J.K. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by the Ministry of Health and Welfare Clinical Trial Center, Taiwan (MOHW109-TDU-B-212-114004), the Minister of Science and Technology, Taiwan (MOST 109-2314-B-039-018-MY3, MOST 108-2622-E-039-002-CC1, MOST 109-2321-B-039-002, and MOST 108-2221-E-039-006-MY3), China Medical University (CMU109-MF-82), and China Medical University Hospital (DMR-110-111, DMR-110-222, DMR-110-224, DMR-111-114, and DMR-111-230), and Tseng-Lien Lin Foundation, Taichung, Taiwan.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki, and approved by the Institutional Review Board of China Medical University, Taichung, Taiwan (CMUH104-REC2-115 (CR4), date of approval: 5 July 2019).
Informed Consent Statement
Patient consent was waived under the agreement of the Institutional Review Board of China Medical University, Taichung, Taiwan because the identify of the subjects could not be identified.
Data Availability Statement
The data presented in this study are available on request from the corresponding author.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Park, M.; Lee, J.S.; Lee, J.H.; Oh, S.H.; Park, M.K. Prevalence and risk factors of chronic otitis media: The Korean National Health and Nutrition Examination Survey 2010–2012. PLoS ONE 2015, 10, e0125905. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nadol, J.B., Jr. Revision mastoidectomy. Otolaryngol. Clin. N. Am. 2006, 39, 723–740. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Straub, R.H.; Cutolo, M.; Pacifici, R. Evolutionary medicine and bone loss in chronic inflammatory diseases—A theory of inflammation-related osteopenia. Semin. Arthritis Rheum. 2015, 45, 220–228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Segade, F.; Daly, K.A.; Allred, D.; Hicks, P.J.; Cox, M.; Brown, M.; Hardisty-Hughes, R.E.; Brown, S.D.; Rich, S.S.; Bowden, D.W. Association of the FBXO11 gene with chronic otitis media with effusion and recurrent otitis media: The Minnesota COME/ROM Family Study. Arch. Otolaryngol. Head Neck Surg. 2006, 132, 729–733. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rye, M.S.; Wiertsema, S.P.; Scaman, E.S.; Oommen, J.; Sun, W.; Francis, R.W.; Ang, W.; Pennell, C.E.; Burgner, D.; Richmond, P.; et al. FBXO11, a regulator of the TGFbeta pathway, is associated with severe otitis media in Western Australian children. Genes Immun. 2011, 12, 352–359. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, X.; Kua, H.Y.; Hu, Y.; Guo, K.; Zeng, Q.; Wu, Q.; Ng, H.H.; Karsenty, G.; de Crombrugghe, B.; Yeh, J.; et al. p53 functions as a negative regulator of osteoblastogenesis, osteoblast-dependent osteoclastogenesis, and bone remodeling. J. Cell Biol. 2006, 172, 115–125. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Metcalfe, D. The pathophysiology of osteoporotic hip fracture. McGill J. Med. 2008, 11, 51–57. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carpintero, P.; Caeiro, J.R.; Carpintero, R.; Morales, A.; Silva, S.; Mesa, M. Complications of hip fractures: A review. World J. Orthop. 2014, 5, 402–411. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lai, S.W.; Liao, K.F.; Lin, C.L.; Lin, C.C.; Lin, C.H. Longitudinal data of multimorbidity and polypharmacy in older adults in Taiwan from 2000 to 2013. Biomedicine 2020, 10, 1–4. [Google Scholar] [CrossRef] [Scilit]
- Lai, S.W.; Liao, K.F.; Lin, C.L.; Lin, C.H. Association between Parkinson’s disease and proton pump inhibitors therapy in older people. Biomedicine 2020, 10, 1–4. [Google Scholar] [CrossRef] [Scilit]
- Chiang, C.H.; Li, C.Y.; Hu, K.C.; Fu, Y.H.; Chiu, C.C.; Hsia, C.C.; Kuo, S.J.; Hung, C.H. The Association between Iron-Deficiency Anemia (IDA) and Septic Arthritis (SA): The Real-World Data. Medicina 2022, 58, 617. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, T.C.; Lin, C.C.; Lin, C.D.; Chung, H.K.; Wang, C.Y.; Tsai, M.H.; Kao, C.H. Increased Acquired Cholesteatoma Risk in Patients with Osteoporosis: A Retrospective Cohort Study. PLoS ONE 2015, 10, e0132447. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amar, M.S.; Wishahi, H.F.; Zakhary, M.M. Clinical and biochemical studies of bone destruction in cholesteatoma. J. Laryngol. Otol. 1996, 110, 534–539. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kuczkowski, J.; Sakowicz-Burkiewicz, M.; Izycka-Swieszewska, E. Expression of the receptor activator for nuclear factor-kappaB ligand and osteoprotegerin in chronic otitis media. Am. J. Otolaryngol. 2010, 31, 404–409. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jung, J.Y.; Chole, R.A. Bone resorption in chronic otitis media: The role of the osteoclast. ORL J. Otorhinolaryngol. Relat. Spec. 2002, 64, 95–107. [Google Scholar] [CrossRef] [Scilit]
- Rye, M.S.; Blackwell, J.M.; Jamieson, S.E. Genetic susceptibility to otitis media in childhood. Laryngoscope 2012, 122, 665–675. [Google Scholar] [CrossRef] [Scilit]
- Bhutta, M.F.; Lambie, J.; Hobson, L.; Goel, A.; Hafren, L.; Einarsdottir, E.; Mattila, P.S.; Farrall, M.; Brown, S.; Burton, M.J. A mouse-to-man candidate gene study identifies association of chronic otitis media with the loci TGIF1 and FBXO11. Sci. Rep. 2017, 7, 12496. [Google Scholar] [CrossRef] [Scilit]
- Fennen, M.; Pap, T.; Dankbar, B. Smad-dependent mechanisms of inflammatory bone destruction. Arthritis Res. Ther. 2016, 18, 279. [Google Scholar] [CrossRef] [Scilit]
- Tateossian, H.; Hardisty-Hughes, R.E.; Morse, S.; Romero, M.R.; Hilton, H.; Dean, C.; Brown, S.D. Regulation of TGF-beta signalling by Fbxo11, the gene mutated in the Jeff otitis media mouse mutant. Pathogenetics 2009, 2, 5. [Google Scholar] [CrossRef] [Scilit]
- Abida, W.M.; Nikolaev, A.; Zhao, W.; Zhang, W.; Gu, W. FBXO11 promotes the Neddylation of p53 and inhibits its transcriptional activity. J. Biol. Chem. 2007, 282, 1797–1804. [Google Scholar] [CrossRef] [Scilit]
- Tateossian, H.; Morse, S.; Parker, A.; Mburu, P.; Warr, N.; Acevedo-Arozena, A.; Cheeseman, M.; Wells, S.; Brown, S.D. Otitis media in the Tgif knockout mouse implicates TGFbeta signalling in chronic middle ear inflammatory disease. Hum. Mol. Genet. 2013, 22, 2553–2565. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schlick, C.; Schniepp, R.; Loidl, V.; Wuehr, M.; Hesselbarth, K.; Jahn, K. Falls and fear of falling in vertigo and balance disorders: A controlled cross-sectional study. J. Vestib. Res. 2016, 25, 241–251. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yoo, J.I.; Park, K.S.; Seo, S.H.; Park, H.W. Osteoporosis and hearing loss: Findings from the Korea National Health and Nutrition Examination Survey 2009–2011. Braz. J. Otorhinolaryngol. 2020, 86, 332–338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kahveci, O.K.; Demirdal, U.S.; Yucedag, F.; Cerci, U. Patients with osteoporosis have higher incidence of sensorineural hearing loss. Clin. Otolaryngol. 2014, 39, 145–149. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).