Skip to Content
You are currently on the new version of our website. Access the old version .
  • 25 days
    Submission to First Decision
  • 21 days
    Acceptance to Publication

Journal of Dementia and Alzheimer's Disease

Journal of Dementia and Alzheimer's Disease is an international, peer-reviewed, open access journal on all types of dementia, with particular interest on Alzheimer’s disease, published quarterly online by MDPI. The Panhellenic Federation of Alzheimer's Disease and Related Disorders (PFADRD) is affiliated with the JDAD and its members receive a discount on the article processing charges.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (110)

  • Perspective
  • Open Access

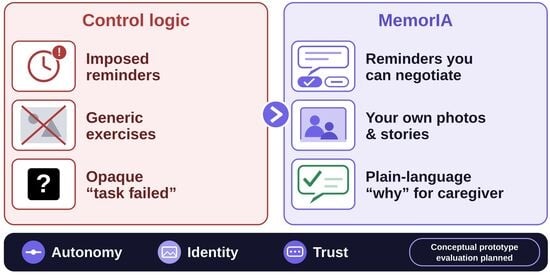
Dementia progressively erodes autonomy, personal identity, and the ability to manage everyday life, placing growing demands on the people who provide care. Many AI-based assistive tools respond to this challenge by prioritizing what the algorithm can do, while giving less attention to the autonomy, dignity, and lived experience of the person with dementia. This paper presents MemorIA, a static interface prototype based on the “Technology as Care” paradigm, in which the person’s autonomy, identity, and well-being are the primary goals and visual accessibility is the means to reach them. Three principles guide the prototype: Dynamic Autonomy, Authenticity, and Ethical Transparency. In the interface, these take the form of high colour contrast, simplified typography, brief wording, step-by-step interactions, and pictograms paired with personal photographs. A conversational onboarding phase is designed to calibrate the level of support, while a dedicated caregiver dashboard renders simulated decision rationales through narrative visualisations grounded in Explainable AI principles. An author-conducted, literature-informed design review examined the consistency of the proposed solutions with accessibility and care principles; the prototype has not yet been tested with end users, and an eye-tracking study is planned as a subsequent empirical step. Overall, the prototype argues that ethical AI in dementia care must serve the person before the task.

Conversational onboarding interface (prototype shown in English, the application’s native language for its target English-speaking users). The chatbot (left-aligned bubbles) opens with a welcome message personalised with the user’s name and photograph (right-aligned bubbles), emphasising user agency (“Remember, today you are in charge”). It then negotiates the desired support level (“Adjust your support”), asking the user to choose between Low (“I want autonomy”), Medium (“Balanced”), or High (“I need support”), with an explanatory note clarifying that a Low setting means the system will always ask permission before intervening. This single-decision, high-contrast dialogue format operationalises the Dynamic Autonomy pillar (Section 3.2), letting the user set their own support level rather than having it imposed. Icons and avatars provided by the Genially platform library (Genially Web S.L.).
  • Article
  • Open Access

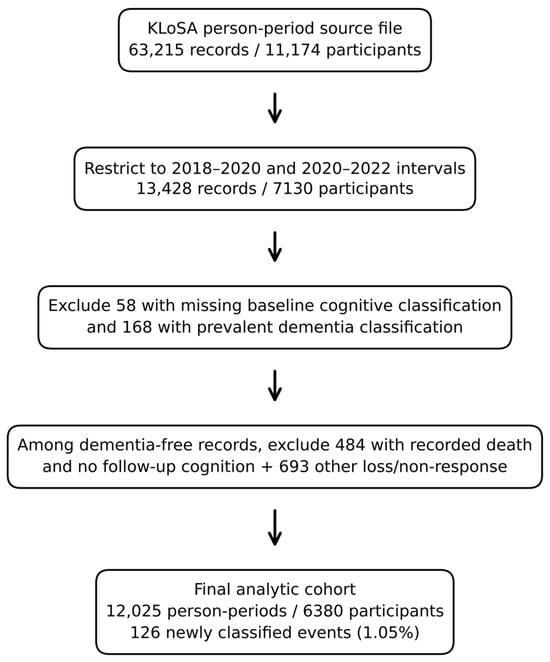
Background/Objectives: Population-based risk stratification for dementia is increasingly important in rapidly ageing societies. Developing prediction models for incident dementia using longitudinal survey data remains challenging because new events are uncommon, observations are repeatedly collected from the same individuals, and predictor variables span multiple health and social domains. This study aimed to develop and compare machine learning models for predicting the two-year risk of newly meeting a survey-derived dementia classification among community-dwelling older adults using longitudinal data from the Korean Longitudinal Study of Aging. Methods: We analysed 12,025 person-period observations from 6380 participants across the 2018–2020 and 2020–2022 intervals after explicitly restricting the risk set to records with known baseline cognition, no baseline dementia classification, and observed follow-up cognition. Sixty baseline predictors were evaluated with eight algorithms using 5-fold participant-level grouped cross-validation and temporally separated validation trained on 2018–2020 and tested on 2020–2022. Performance was assessed using the area under the receiver operating characteristic curve (ROC-AUC), the area under the precision-recall curve (AUPRC), Brier score, calibration, participant-cluster bootstrap confidence intervals (CIs), and top 5%, 10%, and 20% risk-group yield. Results: The survey-derived dementia classification was newly met in 126 of 12,025 person-period observations (1.05%). In grouped cross-validation, CatBoost achieved ROC-AUC 0.890 (95% CI, 0.869–0.910) and AUPRC 0.119 (95% CI, 0.081–0.179); XGBoost achieved ROC-AUC 0.877 and AUPRC 0.113. In temporally separated validation, CatBoost achieved the highest ROC-AUC (0.874); AUPRC values were uniformly low (0.048–0.087) with widely overlapping confidence intervals, so no algorithm was superior for precision-recall performance. The top 10% CatBoost risk group contained 60.3% of incident events in grouped cross-validation and 56.4% in temporal validation, with approximately 6-fold and 5.6-fold enrichment, respectively. Age remained the dominant predictor. Baseline mild cognitive impairment (MCI) was uncommon (39 observations) but strongly enriched for subsequent classification (12 events; 30.8%). Conclusions: Routinely collected longitudinal survey variables supported useful population-level risk ranking for subsequent transition to a survey-derived dementia classification, but absolute case-finding performance remained modest in this rare-event setting. The results support prioritisation for follow-up rather than diagnosis. Sensitivity analyses showed that performance was essentially unchanged after removing baseline survey year or highly missing predictors, whereas excluding baseline MCI reduced precision-recall performance. External validation, recalibration, and prospective evaluation remain necessary before implementation.

Study design and analytic cohort flow.
  • Systematic Review
  • Open Access

Background: The clinical adoption of anti-amyloid monoclonal antibodies, including lecanemab and donanemab, has changed Alzheimer’s disease management from primarily symptomatic care toward biologically targeted intervention. This transition supports renewed evaluation of diagnostic and monitoring practices. Although amyloid positron emission tomography (PET) and blood-based biomarkers often show high baseline concordance, recent clinical trial data suggest that these modalities can differ in their timing and magnitude of change during active treatment. This review examines fluid and imaging biomarker trajectories and proposes a practical framework for multimodal monitoring during immunotherapy. Methods: A comprehensive review was conducted in accordance with PRISMA 2020 guidelines to synthesize current evidence on biomarker kinetics during anti-amyloid immunotherapy. The literature search focused on studies published between January 2020 and February 2026. Priority was given to landmark Phase 3 interventional trials of lecanemab (CLARITY AD) and donanemab (TRAILBLAZER-ALZ 2). Additionally, the review examined large-scale observational cohorts for head-to-head biomarker validation (BioFINDER-2) and preclinical concordance (A4, AHEAD 3-45). Results: Baseline diagnostic concordance between plasma phosphorylated tau at threonine 217 (p-tau217) and amyloid PET appears robust in several cohorts, with reported area under the curve values often exceeding 0.90. Yet, fluid and imaging biomarkers may show different temporal profiles during treatment. These kinetic profiles are derived from separate trials using different assays, PET tracers, populations, and dosing paradigms, rather than head-to-head comparisons. Moreover, the specific magnitude and timing of biomarker change should be regarded as trial-specific rather than generalizable across therapies. Notably, change in plasma p-tau217 correlates only moderately with change in amyloid PET at the individual level (r = 0.484), so its kinetics should not be assumed to mirror amyloid PET within individuals. Even though plasma microtubule-binding region tau 243 may provide complementary information about neurofibrillary tangle burden, it requires further validation for treatment monitoring. Conclusions: Fluid and imaging biomarkers can provide complementary information during anti-amyloid immunotherapy. Blood biomarkers may support early pharmacodynamic monitoring. However, they should not be used alone to confirm individual amyloid clearance. Amyloid PET remains important for confirming amyloid pathology and may help assess treatment-specific clearance endpoints when clinically indicated. A multimodal monitoring framework should be applied with attention to assay platform, PET tracer, disease stage, and treatment protocol.

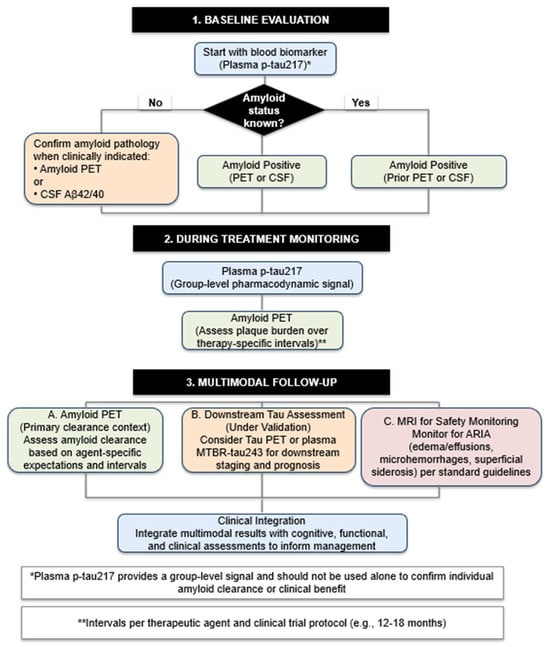
Proposed multimodal framework for monitoring anti-amyloid immunotherapy. (1) Baseline evaluation may begin with a blood biomarker (plasma p-tau217), followed by confirmatory amyloid PET or CSF Aβ42/40 testing when amyloid status is not already known or is otherwise clinically indicated. (2) During treatment, plasma p-tau217 provides a group-level pharmacodynamic signal and should not be used alone to confirm individual amyloid clearance or clinical benefit, while amyloid PET assesses plaque burden over therapy-specific intervals (e.g., commonly 12–18 months). (3) Multimodal follow-up may incorporate amyloid PET for therapy-specific clearance contexts, tau PET or plasma MTBR-tau243 for downstream staging and prognosis (under validation), and MRI for ARIA safety monitoring. Treatment response should be interpreted in the context of the specific therapeutic agent, assay platform, PET tracer, and dosing paradigm, alongside multimodal results integrated with cognitive, functional, and clinical assessments to inform management. ARIA, amyloid-related imaging abnormalities; Aβ, amyloid-beta; CSF, cerebrospinal fluid; MRI, magnetic resonance imaging; MTBR-tau243, microtubule-binding region tau 243; PET, positron emission tomography; p-tau217, plasma phosphorylated tau at threonine 217.
  • Article
  • Open Access

Health Inequalities Within Memory Services—The Need for Service Standards

  • Hari Subramaniam,
  • Shahbaz Abdullah and
  • Mohan Bhat
  • + 3 authors

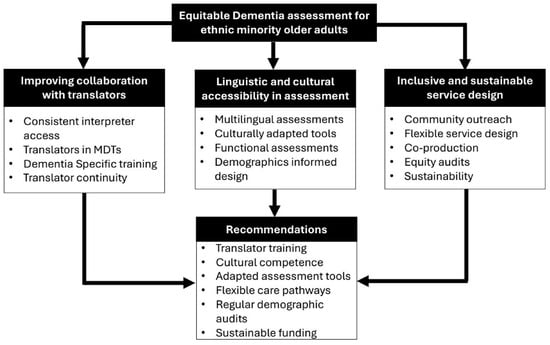
Background/Objectives: Healthcare systems worldwide face challenges regarding dementia diagnosis and offered care. The focus within services has been on diagnosis and waiting times monitored through key centralised performance metrics. However, inequalities persist in memory service pathways, disproportionately affecting people from ethnic minority (EM) backgrounds. EM groups encounter language barriers, access difficulties, culturally inappropriate diagnostic tools and misconceptions about dementia. These factors contribute to diagnosis delays, missed and under-diagnosis and negative health outcomes. We aim to develop recommendations to address these issues. Methods: To explore these inequalities, the Royal College of Psychiatrists Old Age (OA) faculty undertook a UK-wide survey of its membership as a College Quality Improvement initiative, alongside the Memory Services National Accreditation Program (MSNAP), in which variability, accessibility and availability of tailored services were examined. The experiences and understanding of health inequalities of professional mental health staff were studied. Following the survey, a facilitated discussion group explored the survey findings, and a thematic analysis of discussions and themes arising in this group was undertaken. Results: Recommendations to improve standards within memory services included specialized translator training, the integration of translators into multidisciplinary teams, enhancing staff cultural competence, the use of linguistic and culturally adapted tools, the provision of tailored and flexible services, the engagement of community in the coproduction of service initiatives and systematic auditing and monitoring. It was emphasized that the initiatives should be sustainable in the long term. Conclusions: The findings highlight the need for key standards to address health inequalities among elders accessing memory services. Clinical awareness is needed to actively recognise these health inequalities and their impact on clinical presentations; this requires additional resources and training.

Thematic framework figure for equitable dementia assessment for ethnic minority (EM) groups.

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
J. Dement. Alzheimer's Dis. - ISSN 3042-4518