


Abstract
Cognitive frailty combines physical frailty with cognitive impairment without dementia, identifying older adults vulnerable to adverse outcomes. Candidate microbiome-related pathways in cognitive frailty include dysfunction of the intestinal epithelial and blood–brain barriers, altered microbial metabolites, systemic and vascular inflammation, anabolic resistance, and neuroinflammation. However, direct evidence is scarce, and most findings derive from physical frailty, sarcopenia, mild cognitive impairment, or Alzheimer’s disease, inviting overinterpretation. This review integrates a multi-database evidence map with a domain-based synthesis of phenotypes, mechanisms, biomarkers, confounding, interventions, and clinical translation. Conducted up to 31 July 2026, the search identified one eligible primary human study directly examining the gut microbiome in cognitive frailty. Its small sample, age and educational imbalances, 16S-based resolution, and lack of external validation preclude clinical biomarker claims despite apparent discrimination. Larger metagenomic frailty studies report lower microbial diversity, gene richness, and butyrate-production capacity, with partial cross-population replication. Dietary, prebiotic, and probiotic trials demonstrate microbiome target engagement and report selected physical or cognitive benefits, but these outcomes are inconsistent, rarely assessed together, and not established as microbiome-mediated; fecal microbiota transplantation remains experimental. The microbiome should be considered a potential component of multidomain risk models rather than a stand-alone biomarker. Translation requires standardized phenotyping, longitudinal multi-omics, causal diagrams, external validation, and trials with concurrent physical and cognitive endpoints.
1. Introduction
Cognitive frailty was introduced to describe the simultaneous presence of physical frailty and cognitive impairment in older adults without established dementia [1]. The construct was intended to capture a clinically vulnerable but potentially modifiable state in which deteriorating physiological reserve and declining cognition reinforce one another before irreversible dependence becomes established. Subsequent models distinguished potentially reversible cognitive frailty, generally defined by physical frailty and mild cognitive impairment, from reversible cognitive frailty, in which pre-frailty or frailty coexists with subjective cognitive decline [2]. Despite rapid growth of the field, cognitive frailty remains operationally heterogeneous. Published studies have combined different frailty instruments, cognitive tests, thresholds, and exclusion criteria, producing prevalence estimates and risk associations that are not directly interchangeable [3,4].
This heterogeneity is clinically important. Older adults with both physical frailty and cognitive impairment generally experience worse outcomes than those with either deficit alone, including greater risks of disability, hospitalization, dementia, and mortality [3,5]. Yet cognitive frailty is not a single disease entity. It may arise from neurodegenerative, vascular, inflammatory, nutritional, metabolic, medication-related, sensory, affective, or social pathways, often in combination. The concept is therefore most useful when it prompts a multidimensional search for reversible contributors rather than when it is treated as a uniform biological diagnosis.
The gut microbiota has become an attractive candidate mechanism because it intersects several processes common to physical and cognitive decline. Aging-related changes in diet, dentition, gastrointestinal motility, intestinal permeability, immune regulation, medication exposure, and living environment can reshape microbial communities. In turn, altered microbial functions may influence systemic and endothelial inflammation, amino-acid availability, short-chain fatty acid production, bile-acid transformation, tryptophan metabolism, mitochondrial function, muscle anabolism, cerebral perfusion, blood–brain barrier integrity, and microglial activation. These pathways provide a plausible microbiota–gut–muscle–brain framework for cognitive frailty [6,7,8,9].
In this review, older adults primarily denotes people aged 65 years or older. A study was classified as mixed-age when its reported eligibility criteria or participant age range included individuals younger than 65 years. In the absence of a separate estimate for participants aged 65 years or older, it was classified as indirect adjacent evidence and was not used to support age-specific or cognitive-frailty-specific conclusions. We use dysbiosis to mean a population- and context-dependent deviation in microbial ecology or function associated with an adverse host state. The term does not imply a universal normal microbiome, disease specificity, or a causal direction. Because these assumptions are central to interpretation, the title uses the more neutral term gut microbiome.
Plausibility, however, does not establish clinical validity. A 2018 systematic review found substantial mechanistic support in animal models but very limited human evidence directly relevant to cognitive frailty [6]. Subsequent systematic reviews synthesized physical frailty or age-related cognitive decline separately [10,11,12], and a broad 2026 comprehensive review summarized the gut–brain–muscle axis [7]. Since 2018, the primary literature has advanced through larger human cohorts, shotgun metagenomics, metabolomics, longitudinal outcome assessment, and randomized dietary or prebiotic interventions. Direct evidence nevertheless remains extremely limited. We identified one full-length primary human study specifically comparing older adults with and without cognitive frailty through the prespecified cutoff; it was published in 2026 and included 35 participants per group [13]. Most available data still originate from adjacent phenotypes: physical frailty, sarcopenia, mild cognitive impairment (MCI), Alzheimer’s disease, or cognitive performance measured in otherwise unselected cohorts.
A further reason for caution is that microbiome signals are highly context-dependent. Age, geography, diet, malnutrition, bowel transit, oral health, physical activity, multimorbidity, medication exposure, and residential setting influence both the microbiota and the probability of being classified as cognitively frail. These variables are not merely statistical nuisances. They may be upstream causes, mediators, consequences of frailty, or all three. Cross-sectional adjustment can therefore attenuate a genuine pathway, leave residual confounding, or create misleading independence depending on the causal structure.
A more methodologically explicit synthesis became urgent after a broad 2026 review had already summarized the principal mechanisms and interventions along the gut–brain–muscle axis [7]. The present review is differentiated by five linked tasks: it separates direct from adjacent evidence; applies structured methodological appraisal to the central human studies; tests biomarker claims against analytical, predictive, and clinical-validity requirements; treats geriatric confounding and reverse causation as core causal problems; and specifies an applied assay pathway and target product profile. The aim of this comprehensive review is to determine what the current evidence supports regarding the microbiome–cognitive frailty relationship; integrate the principal mechanistic, biomarker, intervention, and geriatric-context domains; identify barriers to causal and clinical interpretation; and define minimum requirements for future translational studies. Table 1 positions these contributions against the principal prior reviews.
Table 1.
How the present comprehensive review differs from major prior syntheses.
2. Review Methodology and Evidence-Mapping Approach
2.1. Review Design and Scope
This article is a domain-based review with a structured evidence-mapping component. It integrates seven prespecified domains: cognitive-frailty definition and phenotyping; direct and adjacent human evidence; biological mechanisms; biomarker development and validity; geriatric confounding and technical heterogeneity; microbiota-modulating interventions; and prospects for clinical translation. The direct cognitive-frailty evidence block was searched and screened exhaustively across the named sources. The larger adjacent literatures were searched broadly and synthesized using predefined thematic and methodological prioritization criteria. The breadth of the review refers to integration across these domains and does not imply exhaustive capture of every eligible publication in the adjacent literatures. Accordingly, the review is not presented as a systematic review, scoping review, meta-analysis, or exhaustive synthesis of each adjacent domain. This design was selected because the review had two complementary objectives: exhaustive identification of evidence directly evaluating cognitive frailty and critical integration of heterogeneous adjacent literatures to assess biological plausibility, methodological constraints, and translational requirements. A formal scoping review across this full breadth would have required exhaustive screening and charting of all eligible records in every adjacent domain; that was neither the objective nor the procedure used.
2.2. Information Sources and Search Date
On 3 August 2026, PubMed/MEDLINE, Europe PMC, and OpenAlex were searched from inception to a publication-date cutoff of 31 July 2026. PubMed supplied controlled biomedical indexing; Europe PMC added grant-linked and early-access biomedical coverage; and OpenAlex broadened discovery across disciplines and document types. The sources overlap and were not treated as statistically independent. ClinicalTrials.gov was searched for active or recruiting microbiota-modulating studies with aging-relevant physical or cognitive outcomes. Retrieval was supplemented by targeted searches of journal and publisher platforms, backward and forward citation tracking of included articles and major reviews, and related-record inspection. The final update checked records dated up to 31 July 2026, including online-first publications.
2.3. Search Blocks, Reproducibility, and Retrieval Counts
Four complementary concept blocks were used because a single query either missed studies indexed under adjacent phenotypes or obscured the exceptionally small direct-evidence core: direct cognitive frailty; physical frailty or sarcopenia; cognitive impairment, MCI, or dementia; and microbiota-modulating interventions. Syntax was translated to each database while preserving the phenotype, microbiome, date, and, where relevant, intervention concepts. DOI, PMID, and normalized title were used sequentially for cross-source deduplication. Phenotype terms in the two adjacent disease blocks were searched in titles and abstracts rather than titles alone; the cognitive block explicitly included cognitive impairment, dementia, and Alzheimer disease to align retrieval with the eligibility criteria. Complete source-specific strings, the direct-block record inventory, and the structured adjacent-evidence inventory are provided in Supplementary File S1.
Targeted supplementary searches paired specific mechanisms or methods with the phenotype blocks, including short-chain fatty acids, tryptophan, indoles, bile acids, trimethylamine N-oxide, intestinal permeability, endothelial dysfunction, cerebral small-vessel disease, blood–brain barrier, inflammation, mitochondrial function, mucosal microbiota, virome, mycobiome, compositional data, absolute microbial load, prediction models, and external validation. These searches supported mechanistic and methodological interpretation and were not counted as additional direct clinical evidence.
The retrieval counts for the four concept blocks are summarized in Table 2.
Table 2.
Multi-database evidence-map retrieval up to 31 July 2026.
2.4. Eligibility and Evidence Strata
Human studies were eligible for the principal synthesis when they examined gut microbial composition or function, microbially related metabolites, or a microbiota-modulating intervention in aging-relevant adults and reported a physical, cognitive, frailty, sarcopenia, or dementia-related phenotype. Direct evidence required an explicit cognitive frailty definition combining physical frailty and objective cognitive impairment without established dementia. The operational age target was 65 years or older. A study was classified as mixed-age when its reported eligibility criteria or participant age range included individuals younger than 65 years. When age-stratified results were available, only the estimate for participants aged 65 years or older was treated as age-specific evidence. When such estimates were unavailable, the study was eligible only as indirect adjacent evidence, irrespective of its overall mean or median age, and only when it informed a prespecified mechanistic, methodological, or translational domain. Mixed-age studies without age-stratified results were not used to support age-specific or cognitive-frailty-specific conclusions. Adjacent evidence was retained when it clarified a component of the integrated syndrome, a candidate mechanism, an assay limitation, or a translational pathway. Studies limited to non-gut microbial sites, unrelated disease populations without an aging-relevant outcome, and purely descriptive taxon reports without a relevant host phenotype were not used to support clinical conclusions. Conference abstracts were excluded from the principal synthesis irrespective of the amount of methodological information reported. Only full reports were eligible as completed-study evidence; registry entries were used solely to describe ongoing protocols and were not treated as evidence of efficacy.
Evidence was mapped into four prespecified human strata: direct cognitive frailty; physical frailty or sarcopenia; adjacent cognitive evidence, within which MCI or non-dementia cognitive decline and established Alzheimer’s disease or other dementia were interpreted as distinct subgroups; and microbiota-modulating interventions. Throughout this review, only studies that explicitly combined physical frailty and objective cognitive impairment while excluding established dementia were classified as direct cognitive-frailty evidence. Studies of physical frailty or sarcopenia alone; MCI, cognitive decline, or established dementia without the combined phenotype; and interventions that did not assess cognitive frailty were classified as adjacent evidence. These adjacent strata were used to examine biological plausibility, methodological constraints, and translational hypotheses, but not to infer cognitive-frailty-specific associations or clinical validity. For the structured core, we extracted population, age, design, phenotype, sample size, assay, covariates, quantitative effect, internal or external validation, and principal limitations. Systematic reviews were used to identify primary studies and characterize consistency, but original studies were prioritized for quantitative details. Preclinical experiments were included only when they tested a defined causal or mechanistic step and were not treated as evidence of human efficacy. Registry status was verified at the cutoff date; an active protocol was not treated as an efficacy result.
Adjacent-study prioritization followed a two-stage process. First, a record had to address at least one prespecified review domain and provide human evidence on the microbiome, microbiome-related metabolites, or a microbiota-modulating intervention relevant to a physical or cognitive component of cognitive frailty. Second, a record was retained in the structured human-evidence core when it contributed at least one of the following: a large or multicenter sample relative to its design class; longitudinal or randomized evidence; shotgun-metagenomic, measured-metabolomic, or multi-omic resolution; external replication or validation; validated physical or cognitive outcomes with relevant geriatric covariates; or direct information on target engagement, assay validity, or clinical implementation. Recent systematic reviews and seminal primary studies were retained when needed to contextualize an otherwise underrepresented domain. No fixed sample-size cutoff or numerical quality score was applied, and no study was excluded solely on the basis of sample size, because the designs, phenotypes, and analytical dimensionality were not commensurable. Sample size was therefore interpreted relative to study design, assay complexity, and phenotype specificity. For all 26 central human studies and active protocols, Table S3 in Supplementary File S1 records the evidence stratum, design or status, inclusion rationale, and role in the synthesis.
The final structured core comprised 26 items: one direct study and 25 adjacent items, including three observational physical-frailty or sarcopenia studies, six observational cognitive studies, ten completed intervention studies, and six active protocols. For the adjacent evidence maps, full-text screening was not recorded as a formal eligibility stage; therefore, these figures describe the retained core rather than systematic full-text-assessment denominators.
2.5. Structured Critical Appraisal and Synthesis
Interpretive weight was assigned according to relevance to cognitive frailty, temporal design, sample size, phenotype quality, geriatric covariate coverage, assay resolution, functional confirmation, statistical appropriateness, and validation. Longitudinal human data, shotgun metagenomics, measured metabolomics, repeated biosampling, absolute-load or compositional methods, prespecified outcomes, and independent replication were weighted more strongly than small cross-sectional 16S classifiers. Microbiome-method reporting was evaluated with STORMS principles [14]. TRIPOD+AI [15], which updates and replaces the original TRIPOD statement [16], was used solely as a reporting benchmark for studies making multivariable prediction or classification claims. We examined whether reports described the target population, predictors, outcome, model-development procedures, performance measures, validation, and intended use; no TRIPOD adherence score was calculated, and incomplete reporting was not itself treated as a risk-of-bias judgment. PROBAST+AI [17], which updates the original PROBAST tool [18], was applied separately to prediction-model claims. Its model-development component informed judgments of development quality and applicability, whereas its model-evaluation component informed risk-of-bias and applicability judgments for reported performance estimates across the participants and data sources, predictors, outcome, and analysis domains.
Central randomized trials were appraised using RoB 2 domains [19]; observational studies were appraised with design-appropriate JBI items [20]; and microbial-classifier studies received the applicable PROBAST+AI appraisal for model development, model evaluation, or both. Tool-specific assessments were used to inform interpretation. RoB 2 and PROBAST+AI categories were retained as defined by the respective instruments, whereas JBI checklist items were considered individually and were not converted into non-standard overall risk categories. The structured appraisals present concise, result-specific methodological limitations rather than formal certainty-of-evidence grades. Because appraisal and selection were performed for a comprehensive synthesis rather than by two independent systematic reviewers, these interpretations are reported transparently.
Quantitative pooling was not appropriate because the target phenotype, microbial assays, exposures, outcomes, and interventions were not commensurable. The direct target-phenotype block was exhaustively inspected, but the much larger adjacent blocks were used as structured discovery maps rather than PRISMA screening denominators. Accordingly, the review does not claim systematic or scoping-review completeness; this boundary is examined explicitly in Section 12.
Initial study prioritization and data charting were conducted by C.R.N. and O.L.B.; L.B. verified the search and eligibility decisions, and A.M.M.S. reviewed the central human evidence. Methodological or interpretative differences were resolved by consensus among all authors. Independent duplicate screening and extraction were not performed, consistent with the non-systematic evidence-mapping design.
3. Cognitive Frailty: Definitions and Phenotypic Heterogeneity
3.1. The Original Construct and Subsequent Operational Models
The 2013 IANA/IAGG consensus defined cognitive frailty through the coexistence of physical frailty and cognitive impairment, with exclusion of Alzheimer’s disease and other dementias [1]. This definition contains three separable decisions: how physical frailty is measured, how cognitive impairment is established, and how dementia is excluded. Each decision changes the population classified as cognitively frail.
Accordingly, established Alzheimer’s disease or another dementia was an exclusion criterion for the direct cognitive-frailty stratum in this review. Studies of MCI or cognitive decline without established dementia and studies of established Alzheimer’s disease or other dementia were retained only as two distinct adjacent cognitive subgroups. When a study included more than one cognitive stage, findings were interpreted within the reported phenotype-specific comparisons and were not pooled across MCI and dementia or attributed to cognitive frailty.
Physical frailty may be operationalized using the Fried phenotype, a deficit-accumulation frailty index, the Clinical Frailty Scale, the Edmonton Frail Scale, or other multidomain instruments. These tools are related but not equivalent. The Fried phenotype emphasizes weight loss, weakness, exhaustion, slowness, and low activity. A frailty index quantifies accumulated deficits. Multidomain tools may include cognition, mood, medication use, social support, and functional dependence. When a scale already contains a cognitive item, combining it with a separate cognitive test can partially embed cognition in both sides of the cognitive frailty definition.
Cognitive impairment has likewise been defined using global screening instruments, domain-specific neuropsychological testing, MCI criteria, or subjective cognitive decline. A single universal cutoff on the Montreal Cognitive Assessment (MoCA) can misclassify individuals when education, language, sensory impairment, or cultural context are not adequately considered. Conversely, very low cognitive scores may identify participants whose impairment is more severe than the intended “without dementia” stage. Exclusion of dementia through a screening score alone is less robust than an expert clinical diagnosis supported by functional assessment and, when relevant, neuroimaging or biomarkers.
The Ruan model expanded the construct by distinguishing potentially reversible cognitive frailty from reversible cognitive frailty [2]. This distinction is clinically attractive because it recognizes a continuum, but it increases heterogeneity if studies pool subjective decline, objective MCI, pre-frailty, and established frailty. For microbiome research, these groups should be analyzed separately whenever possible. Otherwise, a microbial pattern associated with malnutrition and advanced physical frailty may be mistaken for a signature of early cognitive vulnerability.
For clarity, these terms are not treated as interchangeable or as a validated linear progression. In this review, reversible cognitive frailty denotes prefrailty or frailty accompanied by subjective cognitive decline or pre-MCI; potentially reversible cognitive frailty denotes physical frailty accompanied by MCI; the broader original IANA/IAGG construct combines physical frailty with objective cognitive impairment in the absence of established dementia; and established dementia lies outside the direct phenotype used in this review.
3.2. Why Phenotype Definition Matters for Microbiome Studies
Microbiome associations can be distorted when cases and controls occupy very different regions of the aging spectrum. Chronological age is one of the strongest determinants of multimorbidity, medication exposure, diet, bowel function, immune state, and residential dependency. Education influences cognitive test performance and is also associated with socioeconomic position, diet, healthcare access, and lifetime exposures. Physical activity and nutritional status affect both frailty classification and gut ecology. If these factors are strongly imbalanced, a classifier may discriminate the recruitment structure rather than cognitive frailty itself.
This problem is not fully solved by adding many covariates to a regression model. Small studies cannot reliably estimate numerous correlated effects, and adjustment for consequences or mediators of frailty can remove part of the biological signal under investigation. A defensible design begins with careful matching or restriction, prespecifies a causal model, and then uses parsimonious adjustment supported by adequate sample size. Repeated sampling is also important because a single stool specimen may not represent the participant’s longer-term ecological state.
Table 3 summarizes the principal cognitive frailty models and their implications for microbiome research.
Table 3.
Operational models of cognitive frailty and implications for microbiome research.
4. Architecture of the Available Human Evidence
4.1. Direct Evidence in Cognitive Frailty
We identified one full-length primary human study meeting the operational criteria for direct cognitive-frailty evidence up to 31 July 2026. Wen and colleagues recruited 70 community-dwelling older adults in Shanghai: 35 with cognitive frailty and 35 controls [13]. Cognitive frailty was operationalized using an Edmonton Frail Scale score of at least 5, a MoCA score below 26, and a Clinical Dementia Rating score of 0.5. Fecal communities were profiled using 16S rRNA V4 sequencing. Beta diversity differed between groups, and several taxa were differentially abundant. Cognitive frailty was associated with higher abundance of taxa including Escherichia–Shigella and with lower abundance of Roseburia and Haemophilus. A 35-genus model yielded an area under the receiver operating characteristic curve of 0.92.
The study is an important proof of concept, but the reported discrimination should not be interpreted as validation of a cognitive frailty biomarker. Cases were, on average, approximately 17 years older than controls (84.3 versus 66.8 years), markedly less educated, less physically active, more often unmarried, and had poorer sleep, nutritional status, and fiber intake. Mean MoCA scores were 12.7 in cases and 25.8 in controls, indicating an unusually wide cognitive separation for a construct intended to exclude dementia. The report also described controls as requiring a MoCA score above 26, which is internally inconsistent with the reported control-group mean of 25.8 and complicates exact phenotype reproduction. The Edmonton Frail Scale contains a cognitive domain, creating potential overlap between the physical and cognitive components. Although multivariable analyses were performed for selected community metrics, the small sample cannot support stable control of this degree of imbalance or the development and evaluation of a high-dimensional classifier in the same dataset.
Additional limitations include genus-level resolution, absence of measured microbial metabolites or inflammatory markers, a single geographic setting, cross-sectional sampling, and no external validation. The AUC therefore quantifies apparent discrimination in the derivation sample rather than transportable diagnostic performance. The appropriate conclusion is that a cognitive-frailty-associated microbial pattern may exist and merits confirmation in age- and education-balanced cohorts using a non-overlapping physical frailty definition, formal clinical adjudication of cognitive status, shotgun metagenomics, and independent validation.
An independent commentary published on 31 July 2026 reached a similar interpretation: the 35-genera signature was considered exploratory, and the authors specifically called for age-matched, longitudinal cohorts and external validation before clinical application [21]. The commentary also emphasized a question central to the present review: whether the reported taxa are specific to cognitive frailty or instead reflect aging, inflammation, nutritional vulnerability, and accumulated multimorbidity. This distinction cannot be resolved within the current derivation sample.
4.2. Evidence from Physical Frailty
Physical frailty provides the largest adjacent human evidence base. Early studies linked frailty to lower microbial diversity and reduced representation of health-associated commensals, but many were limited by small samples, 16S sequencing, and cross-sectional design [22,23,24,25,26]. The direction of individual taxonomic associations has varied across cohorts, reflecting differences in geography, diet, residence, frailty definition, sequencing region, and analysis. Consistency is generally stronger at the level of ecological function than at the level of a single genus.
Recent metagenomic studies materially improve this evidence. Pu and colleagues analyzed 1821 adults aged 62–96 years using a 33-item frailty index, shotgun metagenomics, and plasma metabolomics [27]. Eighteen microbial species and 17 circulating metabolites varied with frailty severity, and associations for nine species were reproduced in two external populations. A composite microbial score predicted two-year mortality, while glycerol, white blood cell count, and kidney function partially mediated selected associations. This study supports reproducibility and clinical relevance, although it addresses multidimensional physical frailty rather than cognitive frailty.
In July 2026, Vilar Geraldi and colleagues reported metagenomic data from 2081 Swedish women aged 75–80 years, with replication in 1448 older Chinese adults [28]. Higher frailty-mortality index scores were associated with lower Shannon diversity, reduced gene richness, diminished predicted functional capacity, and adverse outcomes over a median follow-up of 7.9 years. Frailty explained a statistically significant but modest proportion of overall compositional variation (approximately 0.6%). Species within Faecalibacterium and other potential butyrate-producing groups were inversely associated with frailty, whereas severe frailty was linked to altered amino-acid degradation, trimethylamine-related functions, anaerobic respiration, and reduced carbohydrate-derived butyrate-production potential. Cross-population replication is a major strength, but the derivation cohort included only women within a narrow age band and used a newly developed frailty-mortality index rather than a standard cognitive frailty phenotype.
Other recent studies reinforce the shift from taxonomic lists to functional interpretation. Jarmukhanov and colleagues used metagenomics in 158 adults across frailty severity categories and identified reduced diversity together with pathway differences involving cobalamin, arginine, one-carbon metabolism, and nucleotide biosynthesis [29]. Barberá and colleagues combined 16S and metagenomic analyses in 203 older adults and found taxonomic and functional patterns associated with frailty and related comorbidities, while also showing that age and diabetes acted as important confounders [30]. Across studies, loss of ecological richness, reduced abundance of selected butyrate-producing organisms, and altered metabolic capacity appear more reproducible than any universal “frailty taxon.”
4.3. Evidence from Sarcopenia and the Gut–Muscle Axis
Sarcopenia studies provide a mechanistic bridge to the physical component of cognitive frailty. The BIOSPHERE study combined microbial, inflammatory, amino-acid, and functional measures in 35 older adults with or without physical frailty and sarcopenia [25]. Its multimarker model classified participants accurately within the small derivation sample, but the absence of external validation and the high ratio of predictors to participants limit biomarker interpretation. Kang and colleagues reported reduced diversity and depletion of several butyrate-producing genera in participants with sarcopenia, together with predicted reductions in nutrient-transport and aromatic-amino-acid pathways and enrichment of lipopolysaccharide biosynthesis [31].
Systematic reviews confirm substantial heterogeneity in individual taxa but support a plausible gut–muscle relationship involving inflammation, microbial metabolites, nutrient utilization, and anabolic resistance [10,32]. A 2026 translational study added species-level evidence: Roseburia inulinivorans abundance was associated with several strength measures in younger and older adults, and supplementation increased grip strength and altered muscle metabolic pathways and fiber phenotype in antibiotic-treated mice [33]. This triangulation is mechanistically informative, but it is not yet a human treatment trial and does not show an effect on cognition. These findings can inform mechanisms of cognitive frailty, but they cannot establish that the same microbial features jointly drive cognitive impairment. Sarcopenia, physical frailty, and cognitive frailty overlap without being synonymous.
4.4. Adjacent Evidence from MCI, Cognitive Decline, and Established Dementia
All studies discussed in this subsection were treated as adjacent rather than direct cognitive-frailty evidence. Findings from MCI or non-dementia cognitive decline were interpreted separately from findings in established Alzheimer’s disease or other dementia.
Human studies of MCI and cognitive decline are more numerous than direct cognitive frailty studies, but results remain inconsistent. Verdi and colleagues evaluated 1551 adults and found that associations between microbiome diversity and cognitive performance changed after accounting for physical frailty, diet, proton pump inhibitor exposure, and antibiotics [34]. The study illustrates a central problem: physical health can explain or modify apparent microbiome–cognition associations and should be measured rather than treated as background noise.
Shotgun metagenomic studies offer improved species and functional resolution. Li and colleagues analyzed 516 community-dwelling older adults and identified microbial species and pathways related to cognitive performance, including functions involving short-chain fatty acids and lactate [35]. In 2025, Fan and colleagues examined 119 participants with MCI and 320 cognitively normal controls using shotgun metagenomics, amyloid positron emission tomography, plasma pTau181, APOE genotype, neuropsychological testing, and neuroimaging [36]. They identified 59 species linked to MCI or Alzheimer’s disease biomarkers and showed that species within the same genus could have opposing associations. This observation cautions against genus-level labels such as “beneficial Bacteroides” or “harmful Ruminococcus.”
Smaller 16S studies have reported classifiers with apparently high discrimination. For example, Fan and colleagues found an AUC of 0.84 for a genera-based MCI model in 31 cases and 65 controls [37]. As in cognitive frailty, internal AUCs from high-dimensional derivation samples should be viewed as hypothesis-generating. Differences in geography, cognitive criteria, diet, medication exclusions, sequencing pipelines, and statistical methods reduce portability.
Metabolomics may provide a more functionally meaningful layer. Wu and colleagues compared 22 participants with amnestic MCI, 27 with Alzheimer’s disease, and 28 controls and found group differences in tryptophan metabolites, short-chain fatty acids, and lithocholic acid [38]. Tryptophan-related alterations were already present in MCI, while several short-chain fatty acids declined across the cognitive spectrum. Such data support host–microbe metabolic crosstalk, but small cross-sectional samples cannot determine whether these metabolites are causes, consequences, dietary correlates, or markers of disease-related behavioral change.
4.5. Intervention Evidence and the Problem of Discordant Endpoints
Intervention trials demonstrate microbiome target engagement and, in some studies, improvement in selected geriatric outcomes; they do not establish that those benefits were microbiome-mediated or constitute an effective treatment for cognitive frailty. The NU-AGE study associated one year of Mediterranean-diet adherence with microbiome changes linked to lower frailty, better cognitive measures, and lower inflammatory markers in 612 non-frail or pre-frail older adults across five European countries [39]. Because dietary interventions alter many biological pathways simultaneously, microbiome mediation requires careful analysis and cannot be assumed from parallel change.
Yang and colleagues combined a large observational program with a multicenter randomized trial of 200 prefrail or frail older adults [40]. A 12-week inulin–oligofructose intervention improved several frailty-related measures, including walking speed and grip strength, and altered microbial and metabolic profiles. Cognitive outcomes were not the central target. Conversely, the PROMOTe trial randomized 36 twin pairs to a prebiotic or placebo while both groups received resistance exercise and branched-chain amino acids [41]. The prebiotic increased Bifidobacterium and improved a composite cognitive factor but did not improve the primary physical endpoint, chair-rise time. This divergence is particularly informative for cognitive frailty: an intervention cannot be assumed to modify the integrated syndrome because it benefits only one component.
Trials in MCI or cognitively vulnerable older adults have reported signals for Mediterranean-ketogenic diets and selected probiotic strains [42,43,44]. However, studies differ in strain, dose, duration, baseline cognitive status, cognitive tests, diet, and microbiome assessment. Positive secondary outcomes or subgroup findings should not be equated with prevention of dementia or reversal of cognitive frailty. Future trials should prespecify concurrent physical and cognitive primary or key secondary outcomes, confirm target engagement, and test whether microbiome change mediates clinical benefit.
Figure 1 summarizes this deliberately asymmetric evidence architecture. The narrow direct-evidence core should govern cognitive-frailty-specific claims, while the larger adjacent and preclinical literatures define hypotheses, mechanisms, and trial priorities rather than substitute for direct evidence.
Figure 1.
Evidence architecture and evidence-status key relevant to cognitive frailty. Direct human evidence is shown in the central red box; adjacent human evidence is represented by the physical-frailty or sarcopenia, cognitive, and intervention boxes; preclinical/mechanistic evidence is shown in blue; and arrows connecting these sources to cognitive frailty represent hypothesis or inference rather than established target-phenotype causation. MCI, mild cognitive impairment.
5. Structured Appraisal: What the Current Evidence Can—And Cannot—Support
The available evidence supports three cautious conclusions. First, gut microbial composition and function are associated with physical frailty and cognitive impairment in humans. Second, some ecological and functional features—particularly lower gene richness, loss of selected butyrate-producing capacity, and altered inflammatory or amino-acid-related metabolism—recur across independent frailty cohorts. Third, diet, prebiotics, and probiotics can achieve microbiome target engagement and may independently improve selected physical or cognitive outcomes, but microbiome-mediated clinical efficacy has not been demonstrated.
The evidence does not yet support a diagnostic microbial signature for cognitive frailty, a causal claim that dysbiosis initiates the syndrome in humans, or a clinical recommendation for a specific probiotic, prebiotic, postbiotic, or fecal microbiota transplantation protocol. Direct cognitive frailty evidence is too sparse, taxonomic signals are not sufficiently reproducible, and intervention trials rarely assess both components of the phenotype.
Table 4 provides the structured core-study inventory underlying these conclusions. The appraisal is deliberately result-specific. For example, a well-randomized trial may still carry some concerns for a microbiome-mediated cognitive claim when cognition was secondary, the microbiome analysis used a selected subset, or multiple endpoints were explored. Conversely, external replication can materially strengthen an observational association without converting it into causal evidence. Prediction-model claims are judged separately because a biologically informative association study can remain at high risk of bias when used to derive a classifier. Table 4 provides the structured core-study inventory underlying these conclusions.
Table 4.
Structured appraisal of central human studies relevant to cognitive frailty.
6. Biological Pathways Connecting Dysbiosis to Cognitive Frailty
6.1. A Bidirectional, Multi-Hit Framework
The microbiota–gut–muscle–brain axis should not be represented as a single causal chain in which dysbiosis independently produces cognitive frailty. A more defensible model is a bidirectional, multi-hit system. Aging, diet, disease, medication exposure, low physical activity, impaired oral health, and altered bowel transit can shift the intestinal ecosystem. Microbial functions may then modify barrier integrity, immune tone, metabolite availability, muscle anabolism, and neural homeostasis. Declining mobility, cognition, and independence feed back by changing food choice, meal regularity, medication use, social exposure, and gastrointestinal motility. Cognitive frailty may therefore both influence and be influenced by the microbiome.
This distinction matters because the evidence supporting each arrow is unequal. Human cohort studies support associations between frailty and microbial ecological or functional features [27,28,30], and between cognitive impairment and microbial or metabolic profiles [35,36,37,38]. Randomized interventions show that the microbiome can be modified and that selected physical or cognitive outcomes may improve [39,40,41,42,43,44]. By contrast, direct mediation of the combined cognitive frailty phenotype has not been demonstrated. Transfer experiments and pathway studies provide stronger causal evidence in animals, but their relevance to heterogeneous, multimorbid older adults remains inferential [47,48,49,50].
Accordingly, the mechanistic sections use four evidence-status categories: direct human evidence, adjacent human evidence, preclinical or mechanistic evidence, and hypothesis. No pathway currently has direct human mediation evidence for cognitive frailty; each subsection therefore begins with a concise evidence-status label identifying the highest available level of support.
Figure 2 depicts this framework as a feedback system rather than a unidirectional causal cascade. The diagram also separates measured or potentially measurable mediators from upstream geriatric exposures and from reverse pathways created by the syndrome itself.
Figure 2.
Bidirectional microbiota-gut-muscle-brain framework in cognitive frailty. Geriatric exposures shape microbial ecology and candidate barrier, metabolic, inflammatory, muscular, and neural pathways. Cognitive frailty can then feed back through mobility, diet, medication, and residential changes. The arrows indicate hypotheses of unequal evidential strength and should not be interpreted as established human causal effects. The colors distinguish conceptual domains rather than levels of evidence: gray indicates geriatric exposures; green, the microbial state; orange, the barrier pathway; purple, metabolic and brain pathways; blue, the muscle pathway; and red, immune/endothelial, cognitive-frailty, and reverse-feedback components. BBB, blood–brain barrier; SCFAs, short-chain fatty acids; TMAO, trimethylamine N-oxide.
6.2. Intestinal Barrier Dysfunction, Endotoxemia, and Inflammaging
Evidence status: Adjacent human and preclinical/mechanistic evidence; cognitive-frailty-specific mediation through intestinal barrier dysfunction and endotoxemia remains a hypothesis. Aging can be accompanied by reduced mucus protection, altered epithelial tight-junction regulation, immunosenescence, and impaired resilience after dietary, infectious, or pharmacological perturbation. Loss of obligate anaerobes and expansion of aerotolerant or pro-inflammatory organisms may further destabilize the mucosal environment. If microbial products such as lipopolysaccharide enter the circulation, activation of Toll-like receptor 4 and downstream NF-κB signaling can increase cytokine production and reinforce low-grade systemic inflammation.
The clearest causal evidence for this sequence remains preclinical. In aged mice, Thevaranjan and colleagues linked dysbiosis with increased intestinal permeability, circulating microbial products, systemic inflammation, and macrophage dysfunction; microbial depletion or germ-free conditions attenuated parts of the phenotype [47]. Human frailty cohorts also report combinations of depleted butyrate-associated organisms, inflammatory markers, altered amino-acid profiles, and poorer physical performance [25,27,28,30]. These observations are compatible with a barrier–inflammation pathway but do not prove that permeability precedes frailty.
Inflammation provides a biologically plausible bridge between physical and cognitive decline. Persistent IL-6, TNF-α, and related signaling can promote muscle proteolysis, impair insulin and anabolic signaling, reduce appetite, worsen fatigue, and alter endothelial and neural function. The same inflammatory background may increase blood–brain barrier vulnerability and prime microglia. However, circulating cytokines and endotoxin-related markers are not specific to microbial origin and are affected by adiposity, periodontal disease, infection, renal dysfunction, cardiometabolic disease, and medication use. Studies should therefore measure microbial exposure, host response, and relevant competing sources rather than use C-reactive protein alone as evidence of a microbiota-mediated mechanism.
6.3. Short-Chain Fatty Acids: Function Is More Informative than a Taxon List
Evidence status: Adjacent human and intervention evidence; cognitive-frailty-specific mediation remains a hypothesis.
Acetate, propionate, and butyrate are produced through microbial fermentation of dietary substrates, particularly fermentable fiber and resistant starch. They participate in epithelial energy supply, mucus and tight-junction regulation, immune signaling, glucose and lipid metabolism, and communication with peripheral tissues. Butyrate is especially relevant to the proposed axis because it supports colonocyte metabolism and can influence regulatory immune responses, while SCFA receptors and histone-deacetylase inhibition offer routes through which microbial metabolism could affect muscle and neural cells.
Frailty studies repeatedly report lower abundance of selected organisms with butyrate-producing potential and, more recently, reduced gene modules related to carbohydrate-derived butyrate production [28]. The NU-AGE intervention linked Mediterranean-diet-associated microbiome changes with lower inflammatory markers and better frailty-related outcomes [39]. PROMOTe demonstrated substantial bifidogenic target engagement but no benefit for the primary physical endpoint, illustrating that a taxonomic shift does not guarantee downstream functional or clinical benefit [41].
Interpretation of SCFA measurements requires care. A low fecal concentration can reflect low production, efficient host absorption, slower transit, or altered substrate availability; a high concentration can reflect increased production or impaired uptake. Stool consistency and transit strongly influence community structure and microbial growth [51]. Consequently, predicted pathway abundance from 16S data, fecal SCFA concentration, plasma SCFA exposure, and host receptor signaling are related but non-equivalent measures. Future cognitive frailty studies should combine measured diet, stool form and transit, metagenomic pathway capacity, targeted metabolomics, and host-response markers.
6.4. Tryptophan, Indole Derivatives, and Neuroendocrine Signaling
Evidence status: Adjacent human and mechanistic evidence; the cognitive-frailty-specific pathway remains a hypothesis.
Tryptophan metabolism is distributed across host and microbial pathways. Host enzymes direct tryptophan toward serotonin or the kynurenine pathway, whereas gut microbes generate indole and multiple indole derivatives capable of influencing epithelial integrity, aryl hydrocarbon receptor signaling, immune regulation, and, indirectly, neural function. Systemic inflammation can increase indoleamine 2,3-dioxygenase activity and shift metabolism toward kynurenine. Downstream metabolites may have neuroactive, neuroprotective, or neurotoxic properties depending on the pathway, concentration, tissue, and clinical context.
Small human metabolomic studies in amnestic MCI and Alzheimer’s disease have identified differences in tryptophan-related metabolites alongside SCFAs and bile acids [38]. These findings support pathway plausibility but are not specific to cognitive frailty and do not establish microbial origin. Tryptophan metabolism is also shaped by protein intake, liver and kidney function, inflammation, antidepressants, and other medications. A mechanistically informative study must therefore distinguish microbial indole products from host kynurenine metabolites and evaluate them with diet, renal function, inflammatory status, and medication exposure.
Neural communication through the vagus nerve and enteroendocrine system adds another route, but direct evidence in human cognitive frailty is lacking. Microbial metabolites may alter enteroendocrine secretion and afferent signaling; conversely, autonomic dysfunction and stress can modify motility, secretion, and barrier function. At present, these pathways should be presented as components of biological plausibility rather than as established clinical mechanisms.
6.5. Bile Acids, Trimethylamine N-Oxide, and Other Circulating Metabolites
Evidence status: Adjacent human and preclinical/mechanistic evidence; cognitive-frailty-specific mediation through bile-acid, TMAO, and other circulating-metabolite pathways remains a hypothesis. Primary bile acids synthesized by the host are transformed by intestinal microbes into secondary bile acids that signal through receptors including FXR and TGR5. These pathways influence glucose and lipid metabolism, inflammation, barrier function, and energy expenditure. In the Alzheimer’s Disease Neuroimaging Initiative, altered primary-to-secondary bile-acid ratios and individual bile acids were associated with MCI or Alzheimer’s disease and with neuroimaging or cerebrospinal-fluid biomarkers [52]. The study provides important human evidence for host–microbe co-metabolism, although the signals are not diagnostic of microbial causation and may reflect hepatic, dietary, metabolic, or medication-related effects.
Trimethylamine N-oxide (TMAO) illustrates the same interpretive challenge. Microbial metabolism of choline, phosphatidylcholine, and carnitine produces trimethylamine, which is oxidized in the liver to TMAO. Cerebrospinal-fluid TMAO has been reported to be higher in Alzheimer’s disease and associated with markers of neuronal injury and pathology [53]. Experimental work suggests that TMAO can promote neuroinflammation and age-related cognitive dysfunction [54]. Yet circulating TMAO is strongly affected by diet and renal clearance, both of which differ systematically in frail older adults. It is therefore better viewed as a host–microbe co-metabolite with possible mechanistic relevance than as a stand-alone microbiome biomarker.
Large multi-omics frailty studies reinforce the value of measuring metabolites rather than inferring them solely from taxonomy. Pu and colleagues identified circulating metabolomic signatures that accompanied microbial features and found partial mediation for selected frailty associations [27]. Vilar Geraldi and colleagues reported functional changes involving amino-acid degradation and trimethylamine-related pathways [28]. These results support integrated functional models, but mediation in observational data remains vulnerable to unmeasured confounding and reverse causation.
6.6. Vascular and Endothelial Pathways
Evidence status: Adjacent human evidence; the cognitive-frailty-specific vascular pathway remains a hypothesis.
A vascular route may connect microbiome-related exposures with both components of cognitive frailty. Systemic inflammation, insulin resistance, altered bile-acid signaling, and host–microbe co-metabolites can influence endothelial nitric-oxide bioavailability, arterial stiffness, thrombosis, and microvascular integrity. Reduced muscle perfusion can worsen exercise tolerance and anabolic response, while cerebral endothelial dysfunction and small-vessel disease can impair white-matter networks that support processing speed, executive function, and gait. This pathway is especially relevant because cognitive frailty frequently contains mixed vascular, metabolic, and neurodegenerative substrates rather than a purely Alzheimer-type process.
Human TMAO data illustrate both plausibility and non-specificity. Among 351 patients with acute ischemic stroke, higher TMAO was associated with greater white-matter-hyperintensity volume after vascular-risk adjustment (β = 0.14, 95% CI 0.00–0.29) and with lacunar stroke (adjusted OR 1.67, 95% CI 1.05–2.66) [55]. These cross-sectional associations support a link with cerebral small-vessel disease but do not establish that microbial TMA production caused the lesions. In the population-based Rotterdam Study, plasma TMAO was not associated overall with cognition, neuroimaging, or incident dementia; choline showed more consistent adverse associations, and TMAO predicted dementia only among participants with impaired renal function (HR 1.73, 95% CI 1.16–2.60) [56]. Renal clearance can therefore modify both exposure concentration and outcome risk.
Future studies should integrate blood pressure, orthostatic change, diabetes and insulin resistance, lipid and vascular disease, kidney function, carotid or arterial-stiffness measures, and brain small-vessel imaging. Endothelial or perfusion markers should be positioned as candidate mediators only when temporal sampling supports that role. Without these measurements, a microbial metabolite associated with cognitive frailty may simply index diet, cardiorenal disease, or reduced clearance.
6.7. Anabolic Resistance, Mitochondrial Function, and the Gut–Muscle Interface
Evidence status: Adjacent human and preclinical/mechanistic evidence; cognitive-frailty-specific mediation through anabolic resistance, mitochondrial dysfunction, and the gut–muscle interface remains a hypothesis.The physical component of cognitive frailty may be influenced through several convergent gut–muscle pathways. Reduced energy and protein intake, altered microbial amino-acid utilization, impaired epithelial absorption, insulin resistance, and systemic inflammation can limit the anabolic response to dietary protein and exercise. Frailty and sarcopenia cohorts have reported changes in amino-acid-related pathways, cobalamin and one-carbon metabolism, lipopolysaccharide biosynthesis, and butyrate-producing potential [25,27,28,29,31]. No single pathway has yet been shown to mediate cognitive frailty in humans.
Animal experiments demonstrate biological capacity. Germ-free mice display altered skeletal muscle mass, metabolic pathways, and physical function, with partial restoration after microbial colonization or metabolite supplementation [50]. Such experiments support a causal gut–muscle connection but do not reproduce the polypharmacy, multimorbidity, malnutrition, inactivity, and chronic inflammation characteristic of geriatric frailty.
Mitochondrial dysfunction may connect both sides of the phenotype. Impaired muscle mitochondrial energetics can reduce endurance and increase fatigability, while oxidative stress and mitochondrial injury in microglia or neurons may contribute to cognitive decline. Mossad and colleagues showed in mice that an age-associated microbial metabolite, N6-carboxymethyllysine, promoted oxidative stress and mitochondrial damage in microglia [49]. This is a compelling example of a defined microbial product acting on an aging-relevant neural pathway, but corresponding exposure–response evidence in cognitively frail humans is not yet available.
Skeletal muscle is also an endocrine organ. Exercise-induced myokines and other exerkines can affect metabolism, inflammation, vascular function, and neuroplasticity. In the opposite direction, inactivity reduces anabolic stimulation and changes intestinal transit, diet, and microbial ecology. Because physical activity sits both upstream and downstream of frailty, observational adjustment for activity can either reduce confounding or remove part of the pathway of interest. Longitudinal sampling before and after objectively measured changes in activity is more informative than a single questionnaire collected at the time of stool sampling.
6.8. Blood–Brain Barrier Vulnerability, Microglial Activation, and Reverse Causation
Evidence status: Predominantly preclinical/mechanistic evidence with adjacent human contextual support; the cognitive-frailty-specific pathway remains a hypothesis.
Systemic inflammation and microbial metabolites may affect cerebral endothelial function, blood–brain barrier permeability, glial activation, and synaptic plasticity. Fecal transfer from aged donor mice to young recipients impaired spatial learning and altered hippocampal proteins involved in synaptic plasticity and neurotransmission [48]. Other preclinical models link microbiota-derived products to microglial oxidative stress and mitochondrial dysfunction [49]. Together, these experiments demonstrate that age-associated microbial communities can carry biologically active signals capable of altering brain function.
They do not show that the same sequence explains human cognitive frailty. Cognitive decline itself can reshape the microbiome through dietary simplification, reduced shopping and cooking ability, medication non-adherence, sleep disruption, depression, institutionalization, and loss of mobility. Neurodegenerative or vascular pathology may precede stool collection by many years. A cross-sectional microbial signature can therefore be a cause, mediator, consequence, or correlate of cognitive deterioration.
The strongest future test is not another case–control classifier. It is a longitudinal design in which a standardized physical and cognitive phenotype, repeated stool and blood measures, diet, medication, oral health, transit, physical activity, and clinical outcomes are collected together. Temporal ordering, within-person change, and mediation can then be assessed, followed by interventions that demonstrate target engagement and improvement in both physical and cognitive domains.
7. Microbial and Metabolic Biomarkers: From Discovery to Clinical Validity
7.1. Biomarker Identity Begins with Intended Use
The term “biomarker” is often applied too early in microbiome research. A statistically different genus, a pathway associated with frailty, and a model that separates cases from controls in its training sample are discovery signals, not automatically clinical biomarkers. Clinical evaluation requires a defined intended use: diagnosis of current cognitive frailty, prediction of incident cognitive frailty, prognosis among affected patients, stratification for an intervention, or monitoring of treatment response. Each use requires a different population, outcome, time horizon, comparator, and performance threshold.
For current diagnosis, a microbiome test would need to add meaningful information beyond direct assessment of physical frailty and cognition—the two components that already define the syndrome. This makes a purely diagnostic use difficult to justify. More promising roles may be prediction before both components are clinically evident, identification of biologically distinct subgroups, or enrichment of trials for participants likely to respond to a microbiota-targeted intervention. Even these uses require evidence that the test improves decisions or outcomes rather than merely correlating with risk.
7.2. Taxonomic Signatures and the Problem of Non-Uniqueness
Individual taxa are attractive because they are easy to name and visualize, but several features limit their portability. The same genus can contain species or strains with opposing functions [36]. Different organisms can perform overlapping metabolic tasks, and the same organism can change function according to diet and ecological context. Oral organisms can also appear in fecal data when resident gut communities are depleted, so an apparent increase in an oral taxon may represent loss of colonization resistance rather than expansion of a disease-specific organism [57].
More fundamentally, there is no universal taxonomic definition of a healthy adult gut microbiome [58]. Population-scale studies show strong effects of diet, environment, cohabitation, medication, and other exposures [59,60,61], and explicit age adjustment can materially change disease-associated signals [62]. Age-associated uniqueness has predicted survival in some cohorts [63], whereas frailty cohorts frequently show loss of richness or butyrate-related capacity [27,28,30]. These observations can coexist: healthy aging may involve an increasingly individualized but functionally resilient ecosystem, while frailty may involve loss of ecological and metabolic reserve. A universal cognitive-frailty genus panel is therefore less plausible than a functionally anchored, population-calibrated model.
7.3. Analytical Validity: What Was Actually Measured?
Analytical validity requires that a feature be measured reproducibly across collection kits, storage conditions, DNA-extraction batches, sequencing platforms, library preparation, and bioinformatic pipelines. Both marker-gene and shotgun sequencing contain systematic, taxon-specific biases that can persist even when technical replicates are internally consistent [64]. Batch randomization, negative controls, positive mock communities, standardized metadata, and blinded processing are therefore essential.
Relative abundance data are compositional: an apparent increase in one taxon can arise because another taxon decreased, even when the absolute quantity of the first organism did not change [65]. Differential-abundance methods can produce markedly different results when applied to the same datasets [66]. Absolute microbial load, quantitative PCR, spike-in standards, or carefully selected log-ratio approaches can reduce misinterpretation. Preprocessing, feature filtering, normalization, and taxonomic database version should be prespecified and reported.
Metabolites create additional challenges. A circulating molecule may be produced by microbes, host tissues, or both; fecal concentrations may not reflect systemic exposure; and untargeted metabolomic annotations vary in confidence. Candidate biomarkers should therefore be confirmed with targeted assays, stable analytical procedures, and, where possible, isotope or pathway evidence supporting source attribution.
7.4. Biological-Compartment Validity: Stool Is Not the Whole Gut
Most human aging studies use fecal specimens because collection is scalable, repeatable, and acceptable outside hospital. Feces primarily sample the distal luminal ecosystem and do not directly represent communities attached to the mucus layer, interacting with epithelium, or located in the small intestine. This distinction is mechanistically important for permeability, epithelial immune signaling, nutrient absorption, oxygen gradients, and local metabolite exposure. It is therefore possible for a fecal biomarker to predict a host state while remaining an imperfect measure of the biological compartment proposed to cause it.
In a shotgun-metagenomic analysis of 1397 paired stool, rectal-swab, and mucosal-tissue samples from 240 participants, stool and swab profiles were more similar to one another than either was to mucosal tissue; mucosal communities retained distinct taxonomic and functional features [67]. The study was not conducted in cognitive frailty, but it demonstrates that specimen type is a biological design choice rather than a neutral container. Small-intestinal ecology is even less accessible and may be especially relevant to protein, micronutrient, and bile-acid handling.
Routine biopsy is neither necessary nor proportionate for most geriatric cohorts. A pragmatic design can use standardized repeated stool sampling for population-scale discovery while embedding mucosal, rectal-swab, or small-intestinal substudies in clinically indicated endoscopy or carefully selected mechanistic cohorts. Investigators should state the intended compartment, avoid equating fecal abundance with epithelial exposure, and align metabolite measurements with the site and time at which the proposed pathway operates.
7.5. Beyond Bacteriocentrism and Genus-Level Inference
The evidence base is predominantly bacteriocentric because 16S rRNA workflows capture bacteria and archaea unevenly while excluding viruses and fungi, and many analyses stop at genus level. This leaves the gut virome and bacteriophages, mycobiome, archaeome, and cross-kingdom ecological interactions largely unmeasured. Strain-level differences can also change metabolic capacity, colonization behavior, and safety within the same named species.
Human studies show that these omitted domains are measurable and aging-relevant. Multi-omic profiling has mapped determinants and metabolic correlates of the gut mycobiome in middle-aged and older adults [68]. Trans-kingdom analysis has identified combined bacterial, fungal, and viral features associated with cognitive decline [69], and a 2024 study reported virome and phage–bacteriome signatures linked to cognitive impairment in older adults [70]. These studies are adjacent rather than direct cognitive-frailty evidence and should not be used to nominate clinical markers, but they demonstrate that a bacterial taxon list is biologically incomplete.
Future discovery should use assay designs capable of strain-resolved bacterial profiling and, where justified, viral and fungal characterization. Functional validation remains essential because database incompleteness, low biomass, reagent contamination, transient food-associated organisms, and uncertain viral host assignment can generate unstable cross-kingdom signals.
7.6. Clinical Validity: Discrimination Is Only One Requirement
The prediction-model limitations of the only direct study are detailed in Section 4.1 and Table 4 [13]; its reported discrimination should therefore be considered exploratory rather than clinically validated.
Discrimination alone is insufficient. A model can rank cases above controls yet provide poorly calibrated probabilities. Future studies should report calibration plots and intercept/slope, sensitivity and specificity at prespecified thresholds, positive and negative predictive values in clinically relevant prevalence settings, and uncertainty intervals. Prediction-model studies should follow TRIPOD+AI for transparent reporting and use PROBAST+AI to assess model-development quality, risk of bias in performance estimates, and applicability [15,16,17,18].
External validation should be deliberately demanding. Temporal validation in the same center tests drift; geographic validation tests transportability; and validation across community, outpatient, and residential settings tests spectrum effects. If performance falls, recalibration may be reasonable, but extensive feature reselection creates a new model that requires new validation. Models should also be compared against a simple clinical baseline containing age, sex, education, nutrition, medications, physical performance, and cognitive score.
7.7. Incremental Value and Clinical Utility
The decisive question is whether microbial information changes management. A model that modestly improves AUC but does not change risk classification, referral, prevention, or treatment has limited clinical utility. Incremental value should be evaluated through likelihood-based comparison, change in calibration and explained variation, prespecified reclassification measures where appropriate, and decision-curve analysis across plausible thresholds.
For cognitive frailty, the most credible near-term biomarker may be a composite rather than an isolated organism. A model could integrate metagenomic pathways, measured metabolites, inflammatory and nutritional markers, and conventional geriatric variables. This approach may improve biological interpretability and robustness because function can be conserved across different taxonomic communities. It also increases dimensionality and overfitting risk, demanding larger samples, locked analysis plans, and independent replication.
Biomarker development should be separated into discovery, assay verification, clinical validation, and utility. Each stage needs a frozen feature definition and explicit success criteria. At present, no microbial or metabolic candidate has completed this sequence for cognitive frailty. Table 5 summarizes the candidate biomarker layers, their principal strengths and limitations, and their current translational readiness.
Table 5.
Candidate biomarker layers and readiness for cognitive frailty translation.
8. Geriatric Confounders and Sources of Heterogeneity
8.1. Confounding Is Part of the Biology, Not Merely a Statistical Inconvenience
Research in cognitive frailty is especially vulnerable to confounding because the exposures that shape the gut microbiome are also determinants or consequences of physical and cognitive decline. Chronological age, education, diet, malnutrition, multimorbidity, medication use, mobility, bowel transit, oral health, sleep, depression, renal function, and residential setting form an interconnected system. Labeling each variable as a generic covariate and entering all of them into one regression model does not solve the problem. Some factors are upstream common causes, some are mediators through which dysbiosis could act, and others are consequences of emerging cognitive frailty. Their role depends on the specific causal question.
For example, if the target is the total effect of a low-fiber diet on incident cognitive frailty, microbial composition may be a mediator and should not be adjusted away. If the target is the association between a microbial pathway and cognitive frailty independent of diet, detailed dietary measurement is essential. Physical activity may confound a cross-sectional microbiome–frailty association, mediate an intervention effect, or fall after frailty develops. A causal diagram specified before analysis is therefore more informative than automated covariate selection. Sensitivity analyses should show how estimates change under a minimal confounder set, an extended set, and plausible alternative causal structures.
8.2. Age, Sex, Education, Geography, and Socioeconomic Context
Age is a major threat to cognitive-frailty comparisons because it shapes microbial ecology through immunosenescence, gastrointestinal physiology, disease burden, medication exposure, diet, mobility, and living arrangement, while also determining frailty and cognitive performance. Statistical adjustment cannot repair extreme age non-overlap. Discovery cohorts should therefore use age-overlapping recruitment or matching, and validation cohorts should test performance across age bands rather than assume a linear age effect.
Sex-related biology and gendered exposures may influence body composition, immune responses, medication use, diet, social isolation, and care pathways. Studies should report sex-stratified distributions and test interaction only when sample size supports it. Education, literacy, language, sensory impairment, and cognitive reserve affect screening scores and can generate apparent case–control separation unrelated to neurobiology. Cognitive classification therefore requires education-sensitive interpretation and, ideally, domain-level assessment rather than a single uncorrected threshold.
Population-scale studies show that geography, household environment, diet, medications, and many other host variables explain measurable microbiome variation [59,60,71,72]. A signature discovered in one country or recruitment setting should not be called universal. Multi-country validation is necessary, but simple replication of identical taxa may be an unrealistic standard because different communities can preserve similar functions. Functional pathways and measured metabolites may travel better than fixed genus panels, provided analytical procedures are harmonized.
8.3. Diet, Nutritional Status, Dentition, and the Oral–Gut Interface
Diet is simultaneously a determinant of microbial substrate availability, a component of healthy-aging behavior, and a consequence of disability or cognitive decline. A short food-frequency questionnaire may miss the dimensions most relevant to microbial metabolism: total energy, fiber quantity and diversity, resistant starch, protein source, fermented foods, artificial sweeteners, alcohol, and recent dietary change. At minimum, studies should combine a validated dietary instrument with a brief recent-intake record and document supplements. When feasible, food-based variables should be linked to objective nutritional markers rather than reduced to a single “healthy diet” score.
Malnutrition and unintentional weight loss can alter intake, gut physiology, immune function, muscle mass, and frailty classification. They may also arise because cognitive decline impairs shopping, cooking, swallowing, or meal regularity. Body mass index alone is inadequate: recent weight change, Mini Nutritional Assessment or an equivalent validated tool, appetite, protein intake, and oral or swallowing problems should be measured. Analyses should distinguish low intake preceding the microbial change from low intake caused by the phenotype.
Dentition, periodontal disease, xerostomia, dysphagia, and oral hygiene influence food choice and the organisms entering the gastrointestinal tract. Oral taxa may become more detectable in faeces when resident gut communities are depleted rather than because a specific oral organism causes disease [57]. Recording dental status, periodontal disease, oral hygiene, swallowing difficulty, and recent dental treatment is therefore relevant to both confounding and biological interpretation.
8.4. Bowel Transit, Constipation, and Specimen Timing
Stool consistency and colonic transit are among the strongest technical–biological determinants of fecal microbiome composition [51]. Constipation is common in frail older adults because of low fluid and fiber intake, immobility, autonomic dysfunction, neurologic disease, and medication exposure. It can also increase fecal microbial density and change measured metabolite concentrations. Diarrhoea, laxative use, recent bowel preparation, and acute gastrointestinal illness create different distortions.
Each sample should be linked to Bristol Stool Form Scale, bowel-movement frequency, laxative use, and time since the previous bowel movement. Recent constipation or diarrhoea should be handled through prespecified exclusion, stratification, or sensitivity analysis rather than ignored. A single sample is particularly vulnerable to short-term perturbation. Repeated specimens collected under comparable conditions can separate stable between-person differences from transient within-person variation and can reduce regression dilution.
8.5. Multimorbidity, Polypharmacy, and Renal Function
Multimorbidity is not captured adequately by a disease count. Diabetes, chronic kidney disease, heart failure, cerebrovascular disease, chronic inflammatory disorders, and gastrointestinal disease can influence microbial composition, circulating metabolites, physical performance, and cognition through distinct pathways. Disease severity and control matter: treated stable diabetes is not equivalent to poorly controlled disease, and estimated glomerular filtration rate is essential when interpreting renally cleared co-metabolites such as TMAO.
Medication exposure is one of the most important and frequently undermeasured sources of heterogeneity. Antibiotics can cause large, prolonged ecological perturbations. Proton pump inhibitors facilitate oral–gut transfer and are repeatedly associated with compositional changes. Metformin, laxatives, antidepressants, antipsychotics, anticholinergics, opioids, non-steroidal anti-inflammatory drugs, iron, and nutritional supplements can each affect gut ecology, transit, inflammation, or cognition [59,60,61]. Polypharmacy itself is associated with multimorbidity and frailty, creating confounding by indication.
Studies should record generic name, dose, duration, indication, adherence, and changes during follow-up, not simply “medication: yes/no.” Recent antibiotics should trigger a prespecified exclusion or recovery window, while chronic drugs should be modeled individually when prevalence and sample size permit. Medication burden and anticholinergic or sedative exposure should also be represented because they can influence the cognitive outcome independently of the microbiome.
8.6. Physical Activity, Sleep, Mood, and Residential Setting
Physical activity affects muscle anabolism, insulin sensitivity, inflammation, gut transit, social participation, and dietary behavior. It also declines as frailty progresses. Objective accelerometry is preferable to a single self-report item, with sedentary time and intensity considered separately. A 2026 controlled bed-rest study provides a useful human model showing that enforced inactivity can alter gut and oral microbiome features over a short period, supporting bidirectionality between mobility and microbial ecology [73]. Such experimental models strengthen plausibility but do not reproduce the complexity of chronic cognitive frailty.
Sleep disturbance, depression, anxiety, loneliness, and stress influence cognition, appetite, autonomic function, medication use, and health behaviors. They should be measured with validated scales and interpreted as potential causes, mediators, or consequences. Sensory impairment is likewise important because hearing and vision affect cognitive testing, activity, diet, and social engagement.
Community residence, assisted living, and nursing-home residence represent different ecological and clinical environments. Institutionalization changes meals, medication administration, antibiotic exposure, contact networks, mobility, and dependency. The landmark older-adult cohort by Claesson and colleagues showed that diet and residence tracked closely with microbiota and health [22]. Residential setting should therefore be incorporated at the design stage; statistical adjustment after recruiting fundamentally different populations may leave severe residual confounding.
8.7. Pre-Analytical, Analytical, and Computational Heterogeneity
Pre-analytical and computational variation—including collection and storage, extraction, sequencing, batch allocation, reference databases, and bioinformatic workflows—can materially alter results. Studies should report appropriate negative and positive controls and follow STORMS [14], while analytical plans should address compositionality, zero inflation, multiple testing, batch effects, and absolute microbial load [64,65,66]. Raw reads, metadata, code, software versions, and frozen model specifications should be shared under appropriate governance.
8.8. A Time-Ordered DAG for Analysis Planning
Figure 2 is a biological feedback model; it is intentionally cyclic and therefore is not an analysis DAG. Figure 3 provides a separate, time-ordered directed acyclic graph for a prospective question: whether baseline microbial functional state contributes to incident cognitive frailty. Upstream sociodemographic and clinical factors influence modifiable exposures, the microbiome, and outcomes. Diet, medication and healthcare exposure, activity, and bowel transit shape the measured microbial state. Barrier dysfunction, metabolites, inflammation, and endothelial effects are candidate mediators rather than default adjustment variables. Physical and cognitive components are measured separately before the combined outcome is assigned.
Figure 3.
Time-ordered directed acyclic graph for analysis of incident cognitive frailty. The focal pathway runs from baseline microbial functional state through barrier, metabolic, inflammatory, and endothelial mediators to the physical and cognitive components of the incident phenotype. Dashed paths represent competing direct effects and reverse causation encoded by preclinical disease already present at baseline. The graph should be adapted to the prespecified estimand and should not be interpreted as a universal adjustment set. The colors distinguish node domains rather than levels of evidence: blue denotes upstream common causes and the physical component; green, modifiable exposures and the microbial state; gray, preclinical disease; orange, candidate mediators; purple, the cognitive component; and red, incident cognitive frailty. SES, socioeconomic status; t0, baseline; t1, intermediate time; t2, outcome time.
Reverse causation is represented without drawing a backward arrow: subclinical brain or muscle disease already present at baseline can alter diet, activity, medication, transit, and the microbiome before cognitive frailty is diagnosed. For the total effect of a microbial functional exposure, the minimally sufficient adjustment set would target measured common causes and avoid conditioning on proposed mediators or on consequences of subclinical disease. For a mediation estimand, additional assumptions and time-specific confounder measurement are required. The DAG must be adapted to each question; it is a starting causal model, not a universal adjustment recipe. Table 6 summarizes the principal geriatric confounding domains, their potential effects on observed associations, and the corresponding minimum measurement and design responses.
Table 6.
Minimum geriatric confounder framework for cognitive-frailty microbiome studies.
9. Therapeutic Modulation: Evidence, Limits, and Clinical Meaning
9.1. Dietary Patterns and Fermentable Substrates
Throughout this section, three evidential claims are distinguished. Microbiome target engagement denotes a prespecified change in microbial composition, function, or a microbially related metabolite. Clinical efficacy denotes improvement in a prespecified patient-relevant outcome relative to the comparator, regardless of mechanism. Microbiome-mediated clinical efficacy requires evidence that the microbial change lies on the causal pathway to the clinical benefit, including appropriate temporal ordering and mediation analysis.
Diet is the most clinically accessible route to microbiome modulation and the intervention with the strongest broader evidence for healthy aging. The one-year NU-AGE Mediterranean-style intervention demonstrated that sustained dietary change in older adults can alter microbial profiles in parallel with lower inflammatory markers and favorable frailty-related and cognitive measures [39]. Its multicountry design supports feasibility and ecological relevance. However, the intervention changed fiber, fat quality, micronutrients, food structure, and overall dietary pattern simultaneously. Microbiome change may mediate part of the benefit, mark adherence, or occur alongside host effects that do not require microbial mediation.
Prospective evidence published in 2025 further connected Mediterranean-diet adherence and a 20-taxon microbial score with slower cognitive decline over six years in 746 adults with overweight or obesity and metabolic syndrome [74]. This strengthens temporal evidence on the cognitive side, but it remains observational and population-specific. The microbial score requires external validation, and baseline diet may represent many correlated lifestyle advantages.
For cognitive frailty, a Mediterranean-style, plant-diverse pattern is more defensible than isolated “microbiome superfoods.” Intervention studies should quantify achieved fiber diversity, protein adequacy, energy sufficiency, and weight change. In a malnourished or sarcopenic participant, indiscriminately increasing bulky fiber while compromising protein or energy intake could be counterproductive. Dietary microbiome strategies must therefore be integrated with geriatric nutritional goals rather than applied as a separate supplement protocol.
9.2. Prebiotics
Prebiotics provide a more defined microbial substrate than whole-diet interventions, but product composition and background diet remain critical. In a 2016 double-blind trial of 60 frail older adults, 13 weeks of inulin plus fructooligosaccharides improved exhaustion and handgrip strength but did not change overall frailty rate, cognitive or functional behavior, or sleep [45]. The larger 2024 trial by Yang and colleagues randomized 200 prefrail or frail participants and reported improvements in several physical frailty measures together with microbiome and metabolomic change after an inulin–oligofructose mixture [40]. Cognition was not the central endpoint.
PROMOTe is particularly informative because it measured both sides of the proposed syndrome. Thirty-six twin pairs received a prebiotic or placebo while both groups undertook resistance exercise and branched-chain amino-acid supplementation [41]. The intervention increased Bifidobacterium and improved a composite cognitive factor, yet did not improve the primary physical endpoint of chair-rise time. This result is neither a simple success nor failure: it shows target engagement and possible domain-specific benefit, but not reversal of cognitive frailty.
Future prebiotic trials should prespecify the exact compound, dose, tolerability thresholds, habitual fiber intake, and adherence. Bloating, diarrhoea, constipation, appetite reduction, and interaction with fluid intake are clinically relevant in frail participants. A product that changes stool taxa but reduces dietary intake or adherence has limited geriatric value.
9.3. Probiotics, Synbiotics, and Postbiotics
Probiotic effects are strain-specific and cannot be generalized across a genus or commercial category. Kim and colleagues reported improved cognitive flexibility and stress-related outcomes with a defined probiotic formulation in community-dwelling older adults [43]. A randomized trial of Lacticaseibacillus rhamnosus GG in 200 middle-aged and older adults found a larger cognitive improvement in a cognitively impaired subgroup, but the subgroup definition and attrition make the finding exploratory [75]. Subsequent work linking probiotics, MCI, and microbiome change also suggested cognitive benefit, without establishing efficacy in cognitive frailty [44].
In 2025, a small randomized crossover study in 30 healthy older adults reported an acute improvement in reaction time under high executive demand and changes in selected mood-related cognitive biases after a multistrain product [76]. The modest sample, multiple outcomes, healthy population, and industry involvement reinforce the need for replication. These trials demonstrate that cognitive outcomes can be studied alongside microbiome target engagement; they do not identify a class effect or a clinically indicated probiotic for cognitive frailty.
Synbiotics combine organisms with a substrate intended to support them, while postbiotics deliver inactivated microorganisms, components, or defined metabolites. Both approaches may improve standardization relative to fecal community transfer. Yet no replicated trial has shown that a synbiotic or postbiotic improves both validated physical frailty and cognitive outcomes in a cognitively frail population. Until that evidence exists, recommendations should remain product-specific, trial-specific, and cautious.
9.4. Exercise–Nutrition–Microbiome Combinations
Exercise is already a core intervention for frailty and is biologically capable of changing insulin sensitivity, inflammation, muscle-derived signaling, transit, and microbial substrate use. Combining resistance and aerobic exercise with adequate protein and fiber is therefore more clinically coherent than treating the microbiome in isolation. The challenge is attribution: if mobility and cognition improve, the microbiome may be a mediator, a marker of adherence, or an unrelated parallel response.
Factorial or sequential trial designs can separate these possibilities. A pragmatic design could compare optimized geriatric care alone with exercise–nutrition, microbiota-targeted supplementation, and their combination. Repeated microbiome and metabolite sampling would test target engagement and mediation, while dual physical and cognitive endpoints would determine whether the integrated phenotype changes. The bed-rest experiment [73] also suggests that activity manipulation can be used as a mechanistic perturbation, although short-term enforced inactivity is not a therapeutic analogue.
9.5. Fecal Microbiota Transplantation and Next-Generation Microbial Therapeutics
Fecal microbiota transplantation (FMT) offers a strong ecological perturbation but remains experimental for cognitive aging. A 2023 single-arm pilot administered fecal microbiota capsules to only five adults with cognitive impairment, two of whom had MCI; microbiome and serum-metabolomic changes accompanied stable or improved cognitive scores in the MCI participants [46]. The absence of a control group, the very small and heterogeneous sample, and limited follow-up preclude efficacy claims. A published report of cognitive improvement after FMT for Clostridioides difficile infection is a single case and is highly susceptible to recovery effects, practice effects, and concurrent clinical change [77].
The 2026 ARMOR protocol is therefore notable: it will test encapsulated FMT from young physically active donors in community-dwelling adults aged 65–84 years, with safety, functional autonomy, muscle strength, metagenomics, metabolism, and cognition included in the design [78]. The protocol is aligned with the integrated gut–muscle–brain question, but results were not available at the search cutoff. It should be regarded as an important ongoing test rather than evidence of benefit.
Safety is central in frail, multimorbid, or immunocompromised older adults. Donor-derived extended-spectrum beta-lactamase-producing Escherichia coli caused invasive infections and one death in recipients of investigational FMT [79]. Pathogen transmission, antimicrobial-resistance genes, uncertain durability, donor dependence, and regulatory complexity make FMT unsuitable for routine cognitive-frailty treatment outside a properly governed trial. Defined microbial consortia or metabolite-based interventions may eventually offer greater reproducibility, but they require the same sequence of target validation, dose finding, safety evaluation, and clinical efficacy testing as other biological therapeutics.
9.6. What Constitutes a Positive Trial?
A convincing cognitive-frailty trial must show more than a statistically significant taxon. First, it should demonstrate target engagement using a prespecified microbial, functional, or metabolite measure. Second, it should improve a validated physical endpoint and a validated cognitive endpoint or a rigorously defined composite that does not allow improvement in one domain to conceal worsening in the other. Third, benefit should exceed that achieved by optimized nutrition, exercise, medication review, and management of reversible contributors. Fourth, adverse gastrointestinal effects, falls, delirium, infection, weight loss, and treatment burden should be reported.
Mediation is supportive only when temporal ordering is established and assumptions are explicit. A treatment can work without the measured microbiome feature mediating benefit, and microbiome change can occur without clinical benefit. Trials should therefore avoid presenting parallel changes as proof of mechanism. Table 7 summarizes the completed human microbiota-modulating interventions relevant to cognitive frailty, including target engagement, physical and cognitive outcomes, and syndrome-specific interpretation.
Table 7.
Human microbiota-modulating interventions relevant to cognitive frailty.
9.7. Ongoing Registered Studies and Durability of the Evidence Map
ClinicalTrials.gov searches identified several active studies that could materially change the adjacent evidence base (Table 8). None used an explicitly adjudicated cognitive-frailty phenotype as its primary outcome at the cutoff. Their value lies in complementary pieces of the translational pathway: long-term frailty outcomes after oral FMT, cognitive and imaging outcomes after defined prebiotics, combined diet–exercise manipulation, muscle-focused nutrition with microbiome measures, and integrated FMT assessment of strength and cognition.
Registry entries are protocols, not peer-reviewed efficacy evidence, and status can change. Their inclusion makes the review updateable: results should be incorporated only after prespecified outcomes, attrition, harms, and analysis populations can be compared with the registered plan. PRECODE has a published protocol describing its four-arm, double-blind design in 164 adults aged 60–79 years with subjective cognitive decline plus additional risk factors [80], while ARMOR has a peer-reviewed protocol [78].
Table 8.
Selected ongoing microbiota-related studies with aging-relevant physical or cognitive outcomes up to 31 July 2026.
10. From Association to Causality
10.1. Define the Causal Question Before Selecting the Analysis
“Does the microbiome cause cognitive frailty?” is too broad to identify a study design. A useful question specifies the exposure, intervention analogue, population, time zero, comparator, outcome, and follow-up. Examples include whether sustained loss of butyrate-production capacity predicts incident cognitive frailty over three years; whether a defined prebiotic reduces progression from prefrailty plus subjective cognitive decline to objective cognitive frailty; or whether improvement in a microbial functional pathway mediates part of the effect of a Mediterranean-style intervention.
Each question implies a different estimand. For prognosis, prediction performance and calibration may be sufficient without a causal claim. For treatment selection, the relevant quantity is differential treatment benefit, not disease association. For mediation, exposure–mediator, mediator–outcome, and exposure–outcome confounding must be addressed, and exposure-induced mediator–outcome confounders create additional difficulties. Authors should state whether they seek total, direct, indirect, prognostic, or predictive effects.
10.2. Longitudinal Cohorts with Repeated Phenotyping and Biosampling
The minimum advance beyond current evidence is temporal ordering. Participants free of cognitive frailty at baseline should undergo standardized physical and cognitive assessment, repeated stool and blood sampling, diet and medication characterization, and adjudication of incident outcomes. At least two baseline stool samples can improve exposure classification, with additional collection after major antibiotic courses, hospitalizations, or dietary or treatment changes where feasible.
Within-person analyses can reduce stable confounding, whereas mixed-effects or joint models can address trajectories, informative dropout, and death. Sampling protocols should remain feasible for older adults; home-based collection and proxy-supported logistics can reduce selective attrition and preserve the inclusion of vulnerable participants.
10.3. Triangulation Across Complementary Designs
No single design can resolve the whole pathway. Prospective cohorts establish temporality but remain confounded. Human perturbation studies can show that diet, activity, or a microbial product changes both microbiome function and host physiology. Randomized trials provide the strongest evidence for an intervention but may not reveal which microbial feature mediated benefit. Animal transfer experiments test biological capacity but may not represent heterogeneous aging. Concordance across these designs is more persuasive than repeated cross-sectional classifiers.
Mendelian randomization may contribute when robust genetic instruments exist for a well-defined microbial feature, but weak instruments, taxonomic instability, population specificity, horizontal pleiotropy, and the difference between lifelong genetic propensity and a modifiable treatment limit interpretation. It should be one component of triangulation rather than a substitute for longitudinal human data or randomized intervention.
Negative controls can expose residual bias. A microbial signature claimed to be specific to cognitive frailty should be tested against physical frailty without cognitive impairment, MCI without frailty, depression, malnutrition, and similarly medicated controls. Negative-control outcomes unlikely to be influenced by the proposed pathway and technical negative controls can further reveal hidden structure. Specificity need not be absolute, but overlap must be quantified rather than ignored.
10.4. Mediation, Multi-Omics, and Functional Confirmation
Multi-omics is useful only when layers are connected by a prespecified biological question. Shotgun metagenomics can measure functional potential; metatranscriptomics or metaproteomics can indicate activity; targeted stool and plasma metabolomics can measure products and host exposure; inflammatory and nutritional markers can characterize response. Timing is critical because a mediator must be measured after intervention or exposure and before the outcome change it is proposed to explain.
Observational mediation estimates require strong assumptions and should be presented with sensitivity analyses rather than as proof of mechanism. In randomized trials, treatment assignment protects the treatment–outcome comparison but does not automatically randomize the mediator. A useful sequence is: randomized treatment changes the prespecified microbial function; change in that function predicts later host-response change; host-response change predicts later physical and cognitive improvement; and the indirect effect is consistent across sensitivity analyses. Functional confirmation with targeted assays or ex vivo experiments strengthens source attribution.
10.5. Randomized Trials with Dual-Domain Endpoints
Trials should recruit a clearly defined stage of cognitive frailty and avoid mixing subjective decline, MCI, advanced dementia, prefrailty, and disability without stratification. Standard care must be optimized and described. Randomization should be stratified by key determinants such as site, frailty severity, cognitive stage, and recent antibiotic exposure when relevant. Blinding is feasible for capsules or supplements but more difficult for dietary patterns; blinded outcome assessment remains important.
The endpoint architecture should reflect the syndrome. A hierarchical approach could test safety and adherence, then a prespecified physical endpoint such as gait speed or Short Physical Performance Battery, then a cognitive composite with education-sensitive norms. Alternatively, a global rank or responder definition could require clinically meaningful improvement in both domains without major deterioration in either. Multiplicity, practice effects, missing data, and death must be planned prospectively. Follow-up should be long enough to distinguish transient microbial engraftment or short-term test learning from durable clinical benefit.
11. A Translational Research Framework
11.1. Standardize the Phenotype Without Erasing Clinical Heterogeneity
A core cognitive-frailty definition should use a physical instrument without embedded cognition, a validated multidomain cognitive assessment or adjudicated MCI diagnosis, and explicit exclusion of established dementia based on function and clinical evaluation rather than a screening score alone. Pre-frailty plus subjective decline should be reported as a separate early phenotype. Vascular, neurodegenerative, depressive, sensory, nutritional, and medication-related contributors should be characterized, not assumed away.
Standardization does not require pretending that all cases share one mechanism. Etiological subtyping may eventually be the main clinical value of microbiome-related data. A metabolically inflamed, malnourished, constipation-predominant subgroup may differ from a vascular, well-nourished subgroup with preserved mobility. Discovery studies should therefore retain rich geriatric phenotyping and test whether functional microbial patterns cluster with clinically interpretable pathways.
11.2. Use a Minimum Common Dataset
Cross-cohort synthesis requires a common core collected with harmonized definitions. The core should include physical phenotype and performance, cognitive domains and functional status, education and sensory function, diet and nutrition, complete medication exposure, bowel function, oral health, multimorbidity and renal function, activity, sleep and mood, residence, recent healthcare exposures, and complete specimen metadata. Optional modules can add neuroimaging, amyloid or tau biomarkers, metabolomics, immune profiling, and muscle imaging.
The dataset should be designed for older participants. Home collection, proxy-supported scheduling, large-font instructions, and transport-stable collection materials can reduce exclusion of frailer individuals. Inclusion of residential-care populations is important, but analyses should preserve setting rather than pool it invisibly with independent community living.
11.3. Separate Discovery, Validation, Utility, and Implementation
As detailed in Section 7, translation should proceed sequentially from discovery and analytical verification to independent clinical validation, incremental value beyond a geriatric baseline, and clinical utility. Candidate features and thresholds should be frozen before external testing.
Implementation studies must evaluate feasibility, turnaround time, cost, patient burden, interpretability, and equity. A technically impressive multi-omics panel that cannot be obtained from a frail participant or does not change management is not clinically useful. The likely near-term value of microbiome testing is research stratification and mechanistic enrichment of trials, not routine diagnosis.
Figure 4 converts these requirements into a gated translational pathway. Failure at analytical verification, external transportability, incremental value, or intervention-linked utility should return the candidate to discovery rather than permit premature clinical labeling.
Figure 4.
Gated translational pathway for a cognitive-frailty microbiome biomarker. A candidate should advance only after analytical verification, locked internal validation, independent external validation, and demonstration of incremental value. Clinical utility additionally requires target engagement and meaningful benefit across the physical and cognitive domains of the syndrome.
11.4. Target Product Profile for an Applied Biomarker
A practical translational framework should link minimum study standards with the additional requirements of an applied biomarker. The most defensible initial use is not stand-alone diagnosis, because physical and cognitive assessment already defines the syndrome, but prognostic stratification, trial enrichment, or monitoring in older adults with early multidomain vulnerability.
Table 9 consolidates these requirements into a single framework. The second column defines minimum standards for evidence generation, whereas the third specifies the additional steps needed for applied translation. Numerical thresholds should be prespecified and refined with clinicians, patients, laboratories, regulators, and payers before pivotal validation.
Table 9.
Minimum standards for future cognitive-frailty microbiome studies and applied translation.
12. Limitations of the Review
This review was designed to be comprehensive in scientific scope and methodological depth, but it is not a systematic or scoping review. The direct cognitive-frailty block was searched across three sources and inspected exhaustively, whereas the much larger adjacent blocks were used as structured breadth maps from which methodologically informative studies were prioritized. Consequently, the retrieval counts in Table 2 must not be interpreted as a PRISMA study-selection flow, and selection bias through the omission of eligible adjacent studies cannot be excluded.
PubMed/MEDLINE, Europe PMC, and OpenAlex provide broad, overlapping coverage but do not reproduce proprietary indexing in Embase, Scopus, or Web of Science. Database-specific syntax and document-type coverage differed, particularly in OpenAlex, which explains the larger intervention retrieval. Searches were performed in English and the synthesis emphasizes full reports available in English; language and publication bias are therefore possible. Conference abstracts were excluded from the principal synthesis, whereas registry entries were used only to describe ongoing protocols and not as evidence of efficacy. This conservative approach protects interpretability but may delay recognition of emerging null or positive results.
Study selection, extraction, and structured appraisal were conducted for this comprehensive review and were not duplicated by two independent systematic reviewers. RoB 2 and PROBAST+AI categories in Table 4 are tool-specific judgments; JBI-informed observations are reported as item-level, result-specific limitations rather than non-standard overall ratings. No GRADE assessment was applied, and statistical pooling was inappropriate because cognitive-frailty definitions, populations, specimen types, assays, outcomes, and interventions were not sufficiently commensurable.
The underlying evidence imposes additional limits on any synthesis. Direct human evidence consists of one small case–control report meeting our operational definition. Most studies use a single fecal sample, emphasize bacteria, and lack mucosal, viral, fungal, strain-level, absolute-load, or repeated functional measurements. Adjacent physical and cognitive phenotypes cannot be assumed to combine biologically, and microbially related metabolites often have substantial dietary, hepatic, renal, and host sources. Preclinical transfer studies demonstrate biological capacity but not clinical efficacy in multimorbid older adults.
Finally, the cutoff of 31 July 2026 creates rapid obsolescence in a fast-moving field. The active protocols in Table 8 and emerging reports should be checked immediately before submission and in any future update. These limitations constrain claims of exhaustiveness and causality, but they do not alter the central conclusion that the direct evidence gap and the validation gap are themselves clinically important findings.
13. Prioritized Future Directions
The first priority is a prospective, multicenter inception cohort recruiting age-overlapping robust, prefrail, physically frail, cognitively impaired, and cognitively frail groups with harmonized criteria. Repeated stool and blood sampling, time-varying diet and medication data, and adjudicated incident cognitive frailty should establish whether microbial functional change precedes the integrated phenotype and adds prediction beyond routine geriatric assessment.
Second, a candidate functional panel should be frozen before external testing. It should combine only features supported across physical and cognitive cohorts, then undergo analytical verification, absolute-load or log-ratio analysis, targeted metabolite confirmation, and temporal and geographic validation according to the integrated framework in Table 9. Another internally optimized genus AUC would add little.
Third, mechanism-informed trials should test optimized protein and energy intake, Mediterranean-style fiber diversity, and progressive exercise with or without a defined microbiota-targeted component. Trials should report microbiome target engagement and clinical efficacy separately and should claim microbiome-mediated clinical efficacy only when temporally ordered mediation analyses support it; clinically meaningful benefit should require concurrent improvement or protection in prespecified physical and cognitive outcomes without unacceptable treatment burden.
Fourth, nested mechanistic studies should address the evidence that stool cannot provide: mucosa-associated ecology, small-intestinal or bile-acid biology where feasible, strain-level function, phage–bacterial dynamics, and fungal or archaeal contributions. These modules should remain linked to the same geriatric phenotype and causal timeline rather than becoming disconnected omics surveys.
Finally, consortia should adopt the minimum common dataset and reporting standards summarized in Table 9, together with shared reference materials, analytical benchmarks, and federated validation protocols. Results from STEP-aging, PRECODE, ARMOR, and the other trials in Table 8 should be interpreted against their registered endpoints and used to refine, rather than bypass, the validation pathway.
14. Conclusions
Direct human evidence linking the gut microbiome to cognitive frailty is currently limited to one small case–control study and does not establish a validated biomarker. The larger literatures on physical frailty or sarcopenia and on MCI, cognitive decline, or Alzheimer’s disease are treated in this review only as adjacent evidence. These literatures support biological plausibility and help define candidate mechanisms and research priorities, but they cannot establish microbiome associations specific to the combined cognitive-frailty phenotype and should not be interpreted as interchangeable with direct evidence.
The principal translational obstacle is not an absence of plausible mechanisms. It is the combination of phenotype heterogeneity, geriatric confounding, technical variation, cross-sectional design, and validation failure. Age, education, diet, malnutrition, medication exposure, transit, activity, renal function, oral health, and residential setting can shape both the microbiome and the probability of being classified as cognitively frail. They must be incorporated into design and causal reasoning, not appended mechanically to a regression model.
Dietary, prebiotic, and probiotic trials demonstrate microbiome target engagement and report selected geriatric benefits, but physical and cognitive outcomes are inconsistent and microbiome-mediated clinical efficacy has not been established. FMT is an experimental research strategy with unresolved efficacy and material safety concerns. No microbiota-targeted intervention can currently be recommended specifically to diagnose, prevent, or treat cognitive frailty.
The field should move from isolated taxa and internally optimized AUCs toward longitudinal, functionally anchored, externally validated multidomain models. A useful biomarker must add value beyond conventional geriatric assessment, and a useful intervention must demonstrate target engagement together with clinically meaningful physical and cognitive benefit. Until those standards are met, microbiome findings should inform mechanism, stratification, and trial design rather than routine clinical decision-making.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/applbiosci5040089/s1, Supplementary File S1: Search Log, Direct-Evidence Record Inventory, and Structured Core Matrix. References cited in Supplementary File S1 correspond to references [13,27,28,33,34,35,36,37,38,39,40,41,42,43,44,45,46,74,75,76,78,80,81,82,83,84] in the main text.
Author Contributions
Conceptualization, C.R.N. and O.L.B.; methodology, C.R.N., O.L.B. and L.B.; investigation, C.R.N., O.L.B., L.B. and A.M.M.S.; data curation, O.L.B., L.B. and A.M.M.S.; validation, L.B. and A.M.M.S.; visualization, O.L.B. and L.B.; writing—original draft preparation, C.R.N. and O.L.B.; writing—review and editing, C.R.N., O.L.B., L.B. and A.M.M.S.; supervision, C.R.N. and O.L.B.; project administration, O.L.B. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Data Availability Statement
No new primary datasets were generated for this review. The search strategies, direct-evidence record inventory, and structured adjacent-evidence inventory supporting the review are provided in Supplementary File S1. Data discussed in the manuscript are available in the cited publications and public registries.
Acknowledgments
During the preparation of this manuscript, the authors used ChatGPT (OpenAI, GPT-5 model, web version, accessed July 2026) solely for translation and language polishing. The tool was not used to generate scientific content or conclusions. The authors reviewed and edited all AI-assisted text and take full responsibility for the content of the publication.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Kelaiditi, E.; Cesari, M.; Canevelli, M.; van Kan, G.A.; Ousset, P.-J.; Gillette-Guyonnet, S.; Ritz, P.; Duveau, F.; Soto, M.E.; Provencher, V.; et al. Cognitive frailty: Rational and definition from an (I.A.N.A./I.A.G.G.) international consensus group. J. Nutr. Health Aging 2013, 17, 726–734. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ruan, Q.; Yu, Z.; Chen, M.; Bao, Z.; Li, J.; He, W. Cognitive frailty, a novel target for the prevention of elderly dependency. Ageing Res. Rev. 2015, 20, 1–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Panza, F.; Lozupone, M.; Solfrizzi, V.; Sardone, R.; Dibello, V.; Di Lena, L.; D’URso, F.; Stallone, R.; Petruzzi, M.; Giannelli, G.; et al. Different cognitive frailty models and health- and cognitive-related outcomes in older age: From epidemiology to prevention. J. Alzheimer’s Dis. 2018, 62, 993–1012. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qiu, Y.; Li, G.; Wang, X.; Zheng, L.; Wang, C.; Wang, C.; Chen, L. Prevalence of cognitive frailty among community-dwelling older adults: A systematic review and meta-analysis. Int. J. Nurs. Stud. 2022, 125, 104112. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, X.M.; Wu, X.J.; Cao, J.; Jiao, J.; Chen, W. Association between cognitive frailty and adverse outcomes among older adults: A meta-analysis. J. Nutr. Health Aging 2022, 26, 817–825. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ticinesi, A.; Tana, C.; Nouvenne, A.; Prati, B.; Lauretani, F.; Meschi, T. Gut microbiota, cognitive frailty and dementia in older individuals: A systematic review. Clin. Interv. Aging 2018, 13, 1497–1511. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Taslim, N.A.; Sibarani, J.N.; Alfaray, R.I.; Mayulu, N.; Mustika, A.; Kumalawati, D.A.; Permatasari, H.K.; Tjandrawinata, R.R.; Nurkolis, F. The gut–brain–muscle axis: Microbial regulation of neuromuscular aging and cognitive frailty. Microorganisms 2026, 14, 1366. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ghosh, T.S.; Shanahan, F.; O’Toole, P.W. The gut microbiome as a modulator of healthy ageing. Nat. Rev. Gastroenterol. Hepatol. 2022, 19, 565–584. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baptista, L.C.; Sun, Y.; Carter, C.S.; Buford, T.W. Crosstalk between the gut microbiome and bioactive lipids: Therapeutic targets in cognitive frailty. Front. Nutr. 2020, 7, 17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Almeida, H.M.; Sardeli, A.V.; Conway, J.; Duggal, N.A.; Cavaglieri, C.R. Comparison between frail and non-frail older adults’ gut microbiota: A systematic review and meta-analysis. Ageing Res. Rev. 2022, 82, 101773. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coradduzza, D.; Sedda, S.; Cruciani, S.; De Miglio, M.R.; Ventura, C.; Nivoli, A.; Maioli, M. Age-related cognitive decline, focus on microbiome: A systematic review and meta-analysis. Int. J. Mol. Sci. 2023, 24, 13680. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wen, N.N.; Sun, L.W.; Geng, Q.; Zheng, G.H. Gut microbiota changes associated with frailty in older adults: A systematic review of observational studies. World J. Clin. Cases 2024, 12, 6815–6825. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wen, N.; Zhang, Y.; Sun, L.; He, J.; Zheng, G. Correlation between the gut microbiota composition and cognitive frailty: A case–control study in community-dwelling older adults. Front. Nutr. 2026, 12, 1709481. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mirzayi, C.; Renson, A.; Genomic Standards Consortium; Massive Analysis and Quality Control Society; Furlanello, C.; Sansone, S.-A.; Zohra, F.; Elsafoury, S.; Geistlinger, L.; Kasselman, L.J.; et al. Reporting guidelines for human microbiome research: The STORMS checklist. Nat. Med. 2021, 27, 1885–1892. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Collins, G.S.; Moons, K.G.M.; Dhiman, P.; Riley, R.D.; Beam, A.L.; Van Calster, B.; Ghassemi, M.; Liu, X.; Reitsma, J.B.; van Smeden, M.; et al. TRIPOD+AI statement: Updated guidance for reporting clinical prediction models that use regression or machine learning methods. BMJ 2024, 385, e078378, Correction in BMJ 2024, 385, q902. https://doi.org/10.1136/bmj.q902. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Collins, G.S.; Reitsma, J.B.; Altman, D.G.; Moons, K.G.M. Transparent reporting of a multivariable prediction model for individual prognosis or diagnosis (TRIPOD): The TRIPOD statement. BMJ 2015, 350, g7594. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moons, K.G.M.; Damen, J.A.A.; Kaul, T.; Hooft, L.; Navarro, C.A.; Dhiman, P.; Beam, A.L.; Van Calster, B.; Celi, L.A.; Denaxas, S.; et al. PROBAST+AI: An updated quality, risk of bias, and applicability assessment tool for prediction models using regression or artificial intelligence methods. BMJ 2025, 388, e082505. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wolff, R.F.; Moons, K.G.M.; Riley, R.D.; Whiting, P.F.; Westwood, M.; Collins, G.S.; Reitsma, J.B.; Kleijnen, J.; Mallett, S.; for the PROBAST Group. PROBAST: A tool to assess the risk of bias and applicability of prediction model studies. Ann. Intern. Med. 2019, 170, 51–58. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sterne, J.A.C.; Savović, J.; Page, M.J.; Elbers, R.G.; Blencowe, N.S.; Boutron, I.; Cates, C.J.; Cheng, H.Y.; Corbett, M.S.; Eldridge, S.M.; et al. RoB 2: A revised tool for assessing risk of bias in randomised trials. BMJ 2019, 366, l4898. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aromataris, E.; Lockwood, C.; Porritt, K.; Pilla, B.; Jordan, Z. (Eds.) JBI Manual for Evidence Synthesis; JBI: Adelaide, Australia, 2024. [Google Scholar] [CrossRef] [Scilit]
- Georgiadou, N.; Sultan, O.; Harris, B.H.L.; Koizia, L.J. Commentary: Correlation between the gut microbiota composition and cognitive frailty: A case-control study in community-dwelling older adults. Front. Nutr. 2026, 13, 1929141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Claesson, M.J.; Jeffery, I.B.; Conde, S.; Power, S.E.; O’Connor, E.M.; Cusack, S.; Harris, H.M.B.; Coakley, M.; Lakshminarayanan, B.; O’Sullivan, O.; et al. Gut microbiota composition correlates with diet and health in the elderly. Nature 2012, 488, 178–184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jackson, M.A.; Jeffery, I.B.; Beaumont, M.; Bell, J.T.; Clark, A.G.; Ley, R.E.; O’toole, P.W.; Spector, T.D.; Steves, C.J. Signatures of early frailty in the gut microbiota. Genome Med. 2016, 8, 8, Erratum in Genome Med. 2016, 8, 21. https://doi.org/10.1186/s13073-016-0275-2. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lim, M.Y.; Hong, S.; Kim, J.H.; Nam, Y.D. Association between gut microbiome and frailty in the older adult population in Korea. J. Gerontol. A Biol. Sci. Med. Sci. 2021, 76, 1362–1368. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Picca, A.; Ponziani, F.R.; Calvani, R.; Marini, F.; Biancolillo, A.; Coelho-Júnior, H.J.; Gervasoni, J.; Primiano, A.; Putignani, L.; Del Chierico, F.; et al. Gut microbial, inflammatory and metabolic signatures in older people with physical frailty and sarcopenia: Results from the BIOSPHERE Study. Nutrients 2020, 12, 65. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, Y.; Wang, Y.; Li, H.; Dai, Y.; Chen, D.; Wang, M.; Jiang, X.; Huang, Z.; Yu, H.; Huang, J.; et al. Altered fecal microbiota composition in older adults with frailty. Front. Cell. Infect. Microbiol. 2021, 11, 696186. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pu, Y.; Sun, Z.; Zhang, H.; Huang, Q.; Wang, Z.; Mei, Z.; Wang, P.; Kong, M.; Yang, W.; Lin, C.; et al. Gut microbial features and circulating metabolomic signatures of frailty in older adults. Nat. Aging 2024, 4, 1249–1262. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vilar Geraldi, M.; Dwibedi, C.; Jaiswal, R.; Gregori, G.; Zhou, X.; Lv, B.; Zheng, Y.; Wang, X.; Wu, H.; Axelsson, K.F.; et al. Gut microbiota associates with frailty in older women. Nat. Commun. 2026, 17, 5925. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jarmukhanov, Z.; Mukhanbetzhanov, N.; Vinogradova, E.; Kozhakhmetov, S.; Kushugulova, A. Gut metagenomic features of frailty. Front. Cell. Infect. Microbiol. 2024, 14, 1486579. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barberá, A.; Ortolá, R.; Sotos-Prieto, M.; Rodríguez-Artalejo, F.; Moya, A.; Ruiz-Ruiz, S. The role of the gut microbiome in the complex network of frailty syndrome and associated comorbidities in aging. Aging Cell 2026, 25, e70365. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kang, L.; Li, P.; Wang, D.; Wang, T.; Hao, D.; Qu, X. Alterations in intestinal microbiota diversity, composition, and function in patients with sarcopenia. Sci. Rep. 2021, 11, 4628. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, C.; Cheung, W.H.; Li, J.; Chow, S.K.; Yu, J.; Wong, S.H.; Ip, M.; Sung, J.J.Y.; Wong, R.M.Y. Understanding the gut microbiota and sarcopenia: A systematic review. J. Cachexia Sarcopenia Muscle 2021, 12, 1393–1407. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Martinez-Tellez, B.; Schönke, M.; Kovynev, A.; Garcia-Dominguez, E.; Ortiz-Alvarez, L.; Verhoeven, A.; Gacesa, R.; Vila, A.V.; Ducarmon, Q.R.; Jimenez-Pavon, D.; et al. Roseburia inulinivorans increases muscle strength. Gut 2026. Epub ahead of printing. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Verdi, S.; Jackson, M.A.; Beaumont, M.; Bowyer, R.C.E.; Bell, J.T.; Spector, T.D.; Steves, C.J. An investigation into physical frailty as a link between the gut microbiome and cognitive health. Front. Aging Neurosci. 2018, 10, 398. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, J.; Zhu, S.; Wang, Y.; Fan, M.; Dai, J.; Zhu, C.; Xu, K.; Cui, M.; Suo, C.; Jin, L.; et al. Metagenomic association analysis of cognitive impairment in community-dwelling older adults. Neurobiol. Dis. 2023, 180, 106081. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fan, K.C.; Lin, C.C.; Chiu, Y.L.; Koh, S.-H.; Liu, Y.-C.; Chuang, Y.-F. Compositional and functional gut microbiota alterations in mild cognitive impairment: Links to Alzheimer’s disease pathology. Alzheimer’s Res. Ther. 2025, 17, 122. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fan, K.C.; Lin, C.C.; Liu, Y.C.; Chao, Y.-P.; Lai, Y.-J.; Chiu, Y.-L.; Chuang, Y.-F. Altered gut microbiota in older adults with mild cognitive impairment: A case-control study. Front. Aging Neurosci. 2023, 15, 1162057. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, L.; Han, Y.; Zheng, Z.; Peng, G.; Liu, P.; Yue, S.; Zhu, S.; Chen, J.; Lv, H.; Shao, L.; et al. Altered gut microbial metabolites in amnestic mild cognitive impairment and Alzheimer’s disease: Signals in host–microbe interplay. Nutrients 2021, 13, 228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ghosh, T.S.; Rampelli, S.; Jeffery, I.B.; Santoro, A.; Neto, M.; Capri, M.; Giampieri, E.; Jennings, A.; Candela, M.; Turroni, S.; et al. Mediterranean diet intervention alters the gut microbiome in older people reducing frailty and improving health status: The NU-AGE 1-year dietary intervention across five European countries. Gut 2020, 69, 1218–1228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, J.; Hou, L.; Wang, A.; Shang, L.; Jia, X.; Xu, R.; Wang, X. Prebiotics improve frailty status in community-dwelling older individuals in a double-blind, randomized, controlled trial. J. Clin. Investig. 2024, 134, e176507. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ni Lochlainn, M.; Bowyer, R.C.E.; Moll, J.M.; García, M.P.; Wadge, S.; Baleanu, A.-F.; Nessa, A.; Sheedy, A.; Akdag, G.; Hart, D.; et al. Effect of gut microbiome modulation on muscle function and cognition: The PROMOTe randomised controlled trial. Nat. Commun. 2024, 15, 1859, Correction in Nat. Commun. 2025, 16, 3393. https://doi.org/10.1038/s41467-025-58771-w. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nagpal, R.; Neth, B.J.; Wang, S.; Craft, S.; Yadav, H. Modified Mediterranean-ketogenic diet modulates gut microbiome and short-chain fatty acids in association with Alzheimer’s disease markers in subjects with mild cognitive impairment. eBioMedicine 2019, 47, 529–542. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, C.S.; Cha, L.; Sim, M.; Jung, S.; Chun, W.Y.; Baik, H.W.; Shin, D.-M.; Cha, L. Probiotic supplementation improves cognitive function and mood with changes in gut microbiota in community-dwelling older adults: A randomized, double-blind, placebo-controlled, multicenter trial. J. Gerontol. A Biol. Sci. Med. Sci. 2021, 76, 32–40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aljumaah, M.R.; Bhatia, U.; Roach, J.; Gunstad, J.; Azcarate-Peril, M.A. The gut microbiome, mild cognitive impairment, and probiotics: A randomized clinical trial in middle-aged and older adults. Clin. Nutr. 2022, 41, 2565–2576. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Buigues, C.; Fernández-Garrido, J.; Pruimboom, L.; Hoogland, A.J.; Navarro-Martínez, R.; Martínez-Martínez, M.; Verdejo, Y.; Carmen Mascarós, M.; Peris, C.; Cauli, O. Effect of a prebiotic formulation on frailty syndrome: A randomized, double-blind clinical trial. Int. J. Mol. Sci. 2016, 17, 932. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, X.; Zhang, W.; Lin, Z.; Zheng, C.; Chen, S.; Zhou, H.; Liu, Z. Preliminary evidence for developing safe and efficient fecal microbiota transplantation as potential treatment for aged related cognitive impairments. Front. Cell. Infect. Microbiol. 2023, 13, 1103189. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thevaranjan, N.; Puchta, A.; Schulz, C.; Naidoo, A.; Szamosi, J.; Verschoor, C.P.; Loukov, D.; Schenck, L.P.; Jury, J.; Foley, K.P.; et al. Age-associated microbial dysbiosis promotes intestinal permeability, systemic inflammation, and macrophage dysfunction. Cell Host Microbe 2017, 21, 455–466.e4, Correction in Cell Host Microbe 2018, 23, 570. https://doi.org/10.1016/j.chom.2018.03.006. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- D’Amato, A.; Di Cesare Mannelli, L.; Lucarini, E.; Man, A.L.; Le Gall, G.; Branca, J.J.V.; Ghelardini, C.; Amedei, A.; Bertelli, E.; Regoli, M.; et al. Faecal microbiota transplant from aged donor mice affects spatial learning and memory via modulating hippocampal synaptic plasticity- and neurotransmission-related proteins in young recipients. Microbiome 2020, 8, 140. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mossad, O.; Batut, B.; Yilmaz, B.; Dokalis, N.; Mezö, C.; Nent, E.; Nabavi, L.S.; Mayer, M.; Maron, F.J.M.; Buescher, J.M.; et al. Gut microbiota drives age-related oxidative stress and mitochondrial damage in microglia via the metabolite N6-carboxymethyllysine. Nat. Neurosci. 2022, 25, 295–305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lahiri, S.; Kim, H.; Garcia-Perez, I.; Reza, M.M.; Martin, K.A.; Kundu, P.; Cox, L.M.; Selkrig, J.; Posma, J.M.; Zhang, H.; et al. The gut microbiota influences skeletal muscle mass and function in mice. Sci. Transl. Med. 2019, 11, eaan5662. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vandeputte, D.; Falony, G.; Vieira-Silva, S.; Tito, R.Y.; Joossens, M.; Raes, J. Stool consistency is strongly associated with gut microbiota richness and composition, enterotypes and bacterial growth rates. Gut 2016, 65, 57–62. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nho, K.; Kueider-Paisley, A.; MahmoudianDehkordi, S.; Arnold, M.; Risacher, S.L.; Louie, G.; Blach, C.; Baillie, R.; Han, X.; Kastenmüller, G.; et al. Altered bile acid profile in mild cognitive impairment and Alzheimer’s disease: Relationship to neuroimaging and CSF biomarkers. Alzheimer’s Dement. 2019, 15, 232–244. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vogt, N.M.; Romano, K.A.; Darst, B.F.; Engelman, C.D.; Johnson, S.C.; Carlsson, C.M.; Asthana, S.; Blennow, K.; Zetterberg, H.; Bendlin, B.B.; et al. The gut microbiota-derived metabolite trimethylamine N-oxide is elevated in Alzheimer’s disease. Alzheimer’s Res. Ther. 2018, 10, 124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brunt, V.E.; LaRocca, T.J.; Bazzoni, A.E.; Sapinsley, Z.J.; Miyamoto-Ditmon, J.; Gioscia-Ryan, R.A.; Neilson, A.P.; Link, C.D.; Seals, D.R. The gut microbiome-derived metabolite trimethylamine N-oxide modulates neuroinflammation and cognitive function with aging. GeroScience 2021, 43, 377–394. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kijpaisalratana, N.; Ament, Z.; Bevers, M.B.; Bhave, V.M.; Guarniz, A.-L.G.; Couch, C.A.; Irvin, M.R.; Kimberly, W.T. Trimethylamine N-oxide and white matter hyperintensity volume among patients with acute ischemic stroke. JAMA Netw. Open 2023, 6, e2330446. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yaqub, A.; Vojinovic, D.; Vernooij, M.W.; Slagboom, P.E.; Ghanbari, M.; Beekman, M.; van der Grond, J.; Hankemeier, T.; van Duijn, C.M.; Ikram, M.A.; et al. Plasma trimethylamine N-oxide (TMAO): Associations with cognition, neuroimaging, and dementia. Alzheimer’s Res. Ther. 2024, 16, 113. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liao, C.; Rolling, T.; Djukovic, A.; Fei, T.; Mishra, V.; Liu, H.; Lindberg, C.; Dai, L.; Zhai, B.; Peled, J.U.; et al. Oral bacteria relative abundance in faeces increases due to gut microbiota depletion and is linked with patient outcomes. Nat. Microbiol. 2024, 9, 1555–1565. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van Hul, M.; Cani, P.D.; Petitfils, C.; de Vos, W.M.; Tilg, H.; El-Omar, E.M. What defines a healthy gut microbiome? Gut 2024, 73, 1893–1908. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vujkovic-Cvijin, I.; Sklar, J.; Jiang, L.; Natarajan, L.; Knight, R.; Belkaid, Y. Host variables confound gut microbiota studies of human disease. Nature 2020, 587, 448–454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gacesa, R.; Kurilshikov, A.; Vich Vila, A.; Sinha, T.; Klaassen, M.A.Y.; Bolte, L.A.; Andreu-Sánchez, S.; Chen, L.; Collij, V.; Hu, S.; et al. Environmental factors shaping the gut microbiome in a Dutch population. Nature 2022, 604, 732–739. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vich Vila, A.; Collij, V.; Sanna, S.; Sinha, T.; Imhann, F.; Bourgonje, A.; Mujagic, Z.; Jonkers, D.M.A.E.; Masclee, A.A.M.; Fu, J.; et al. Impact of commonly used drugs on the composition and metabolic function of the gut microbiota. Nat. Commun. 2020, 11, 362. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ghosh, T.S.; Das, M.; Jeffery, I.B.; O’Toole, P.W. Adjusting for age improves identification of gut microbiome alterations in multiple diseases. eLife 2020, 9, e50240. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wilmanski, T.; Diener, C.; Rappaport, N.; Patwardhan, S.; Wiedrick, J.; Lapidus, J.; Earls, J.C.; Zimmer, A.; Glusman, G.; Robinson, M.; et al. Gut microbiome pattern reflects healthy ageing and predicts survival in humans. Nat. Metab. 2021, 3, 274–286, Correction in Nat. Metab. 2021, 3, 586. https://doi.org/10.1038/s42255-021-00377-9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McLaren, M.R.; Willis, A.D.; Callahan, B.J. Consistent and correctable bias in metagenomic sequencing experiments. eLife 2019, 8, e46923. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gloor, G.B.; Macklaim, J.M.; Pawlowsky-Glahn, V.; Egozcue, J.J. Microbiome datasets are compositional: And this is not optional. Front. Microbiol. 2017, 8, 2224. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nearing, J.T.; Douglas, G.M.; Hayes, M.G.; MacDonald, J.; Desai, D.K.; Allward, N.; Jones, C.M.A.; Wright, R.J.; Dhanani, A.S.; Comeau, A.M.; et al. Microbiome differential abundance methods produce different results across 38 datasets. Nat. Commun. 2022, 13, 342, Correction in Nat. Commun. 2022, 13, 777. https://doi.org/10.1038/s41467-022-28401-w. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sun, S.; Zhu, X.; Huang, X.; Murff, H.J.; Ness, R.M.; Seidner, D.L.; Sorgen, A.A.; Blakley, I.C.; Yu, C.; Dai, Q.; et al. On the robustness of inference of association with the gut microbiota in stool, rectal swab and mucosal tissue samples. Sci. Rep. 2021, 11, 14828. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shuai, M.; Fu, Y.; Zhong, H.L.; Gou, W.; Jiang, Z.; Liang, Y.; Miao, Z.; Xu, J.-J.; Huynh, T.; Wahlqvist, M.L.; et al. Mapping the human gut mycobiome in middle-aged and elderly adults: Multiomics insights and implications for host metabolic health. Gut 2022, 71, 1812–1820. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chaudhari, D.S.; Jain, S.; Yata, V.K.; Mishra, S.P.; Kumar, A.; Fraser, A.; Kociolek, J.; Dangiolo, M.; Smith, A.; Golden, A.; et al. Unique trans-kingdom microbiome structural and functional signatures predict cognitive decline in older adults. GeroScience 2023, 45, 2819–2834. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- James, A.S.; Adil, N.A.; Goltz, D.; Tangudu, D.; Chaudhari, D.S.; Shukla, R.; Kumar, V.; Kumar, A.; Masternak, M.M.; Holland, P.; et al. Abnormalities in gut virome signatures linked with cognitive impairment in older adults. Gut Microbes 2024, 16, 2431648. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Falony, G.; Joossens, M.; Vieira-Silva, S.; Wang, J.; Darzi, Y.; Faust, K.; Kurilshikov, A.; Bonder, M.J.; Valles-Colomer, M.; Vandeputte, D.; et al. Population-level analysis of gut microbiome variation. Science 2016, 352, 560–564. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhernakova, A.; Kurilshikov, A.; Bonder, M.J.; Tigchelaar, E.F.; Schirmer, M.; Vatanen, T.; Mujagic, Z.; Vila, A.V.; Falony, G.; Vieira-Silva, S.; et al. Population-based metagenomics analysis reveals markers for gut microbiome composition and diversity. Science 2016, 352, 565–569. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alvaro-Fuss, M.; DeClercq, V.; Blodgett, J.M.; Theou, O.; Langille, M.G.I.; Beiko, R.G. Effect of bedrest on the human gut and oral microbiome: Implications for frailty. Exp. Gerontol. 2026, 216, 113079. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ni, J.; Hernández-Cacho, A.; Nishi, S.K.; Babio, N.; Belzer, C.; Konstati, P.; Vioque, J.; Corella, D.; Castañer, O.; Vidal, J.; et al. Mediterranean diet, gut microbiota, and cognitive decline in older adults with obesity/overweight and metabolic syndrome: A prospective cohort study. BMC Med. 2025, 23, 669. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sanborn, V.; Azcarate-Peril, M.A.; Updegraff, J.; Manderino, L.; Gunstad, J. Randomized clinical trial examining the impact of Lactobacillus rhamnosus GG probiotic supplementation on cognitive functioning in middle-aged and older adults. Neuropsychiatr. Dis. Treat. 2020, 16, 2765–2777. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eastwood, J.; van Hemert, S.; Stolaki, M.; Williams, C.; Walton, G.; Lamport, D. Exploring the acute and chronic effects of a multistrain probiotic supplement on cognitive function and mood in healthy older adults: A randomized controlled trial. Am. J. Clin. Nutr. 2025, 121, 1268–1280. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, S.H.; Lee, J.H.; Shin, J.; Kim, J.-S.; Cha, B.; Lee, S.; Kwon, K.S.; Shin, Y.W.; Choi, S.H. Cognitive function improvement after fecal microbiota transplantation in Alzheimer’s dementia patient: A case report. Curr. Med. Res. Opin. 2021, 37, 1739–1744. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Astudillo-Guerrero, C.; Garrido, Á.; Masferrer, D.; Sepúlveda, C.; Olavarría, L.; Del Campo, R.; Bravo-Sagua, R.; Cubero, F.J.; Salech, F.; Thumala-Dockendorff, D.; et al. Randomized, double-blind, placebo-controlled trial of fecal microbiota transplantation from young physically active donors to promote resilient aging: Clinical trial protocol (ARMOR study). BMC Geriatr. 2026, 26, 271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- DeFilipp, Z.; Bloom, P.P.; Torres Soto, M.; Mansour, M.K.; Sater, M.R.A.; Huntley, M.H.; Turbett, S.; Chung, R.T.; Chen, Y.-B.; Hohmann, E.L. Drug-resistant E. coli bacteremia transmitted by fecal microbiota transplant. N. Engl. J. Med. 2019, 381, 2043–2050. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kruger, K.; van der Veen, H.; Beigy, M.; O’DOnovan, S.D.; van Riel, N.; Remie, L.B.; Aarts, E.; Steegenga, W.; Smeets, P.A.M.; van Trijp, M.P.H.; et al. Gut-brain health effects of PREbiotics in older adults with suspected COgnitive DEcline: Design of the PRECODE randomised placebo-controlled trial. Front. Nutr. 2026, 13, 1738622. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- ClinicalTrials.gov. Effect of Gut Microbiome Intervention on Aging via Oral FMT (STEP-Aging), NCT05598112. Available online: https://clinicaltrials.gov/study/NCT05598112 (accessed on 31 July 2026).
- ClinicalTrials.gov. Cognition, Flavonoids, Exercise, Gut Microbiome, NCT06495190. Available online: https://clinicaltrials.gov/study/NCT06495190 (accessed on 31 July 2026).
- ClinicalTrials.gov. The Effect of Pectin Supplementation on Geriatric with Frailty: A Randomised Placebo-Controlled Dietary Intervention Study, NCT06955975. Available online: https://clinicaltrials.gov/study/NCT06955975 (accessed on 31 July 2026).
- ClinicalTrials.gov. Effect of the Consumption of Cookies Enriched with Plant Proteins and of a Vitamin D Supplement on the Progression of Sarcopenia in the Elderly, NCT07356440. Available online: https://clinicaltrials.gov/study/NCT07356440 (accessed on 31 July 2026).
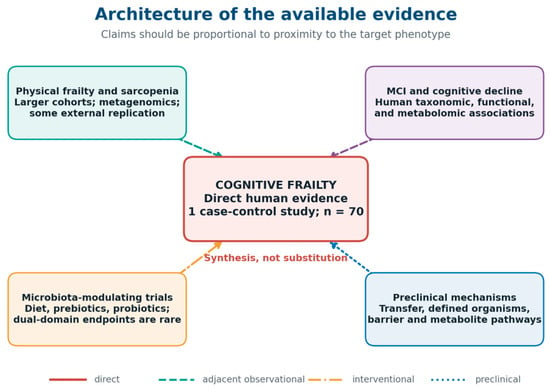
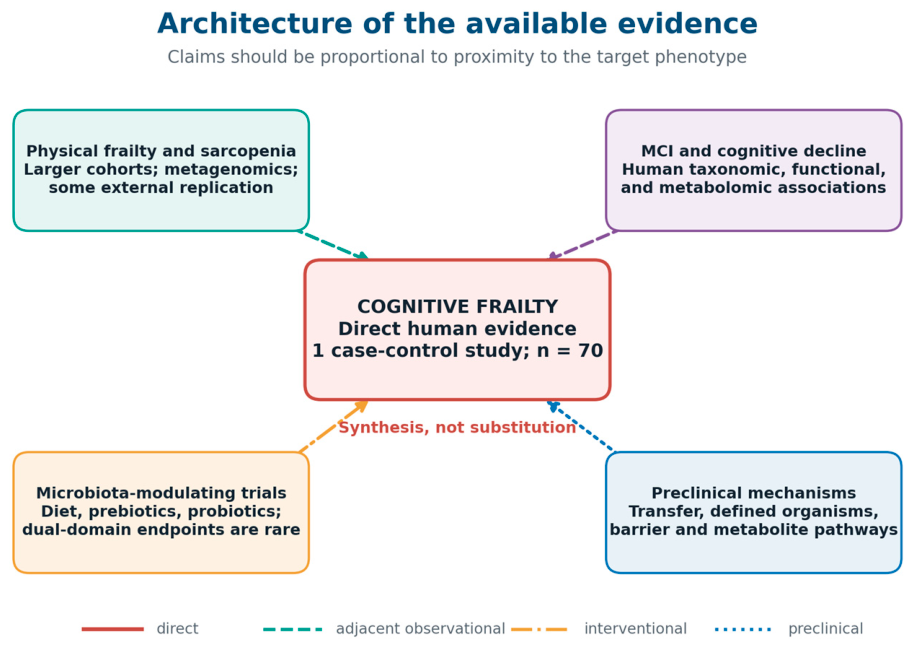
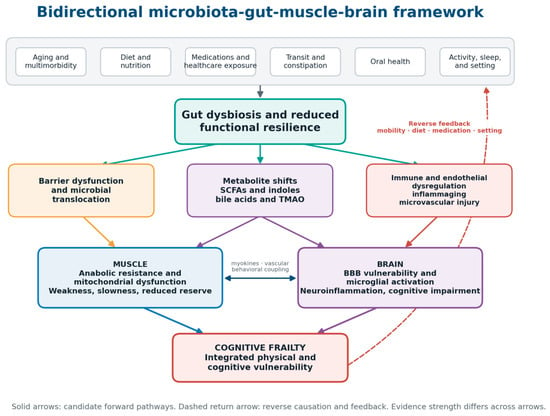
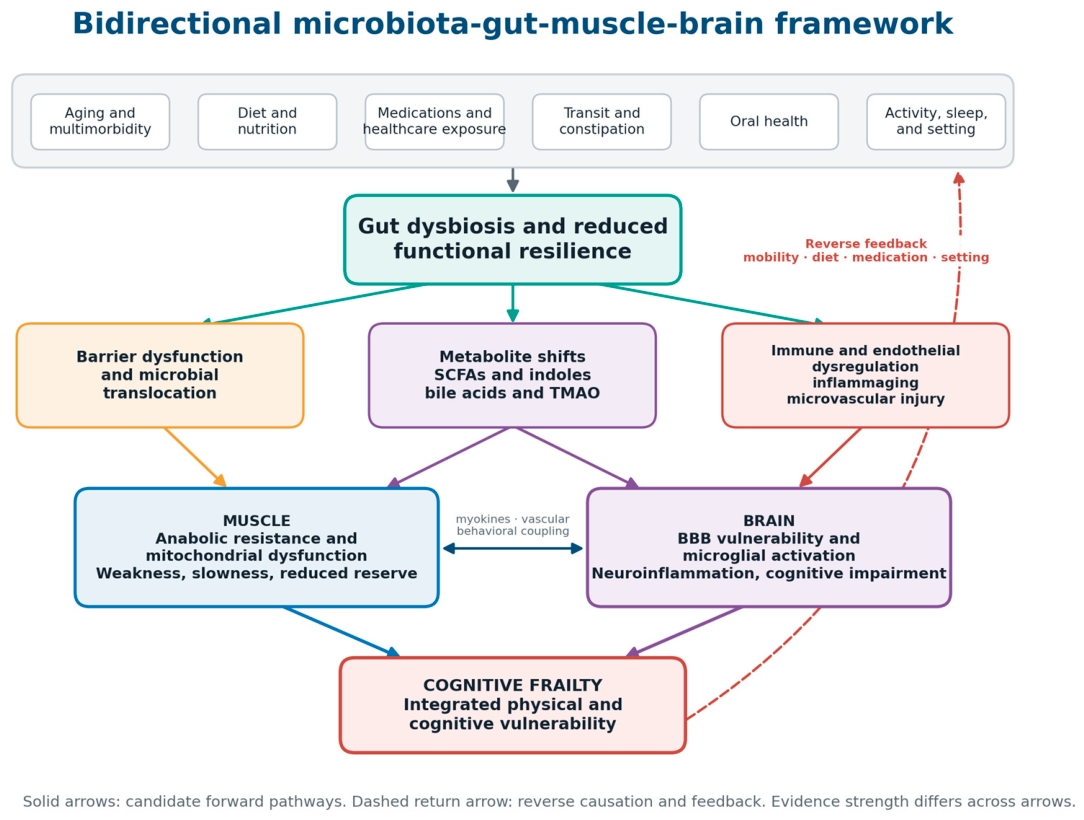
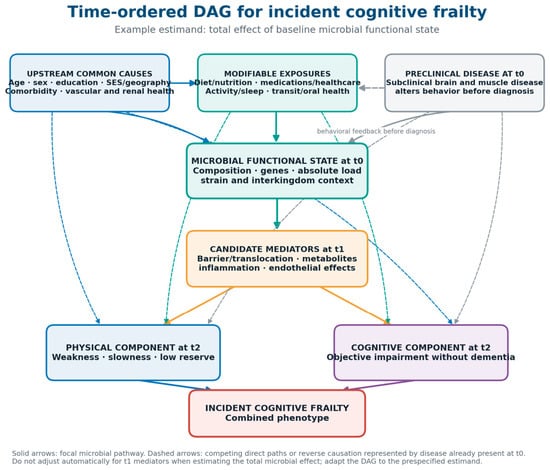
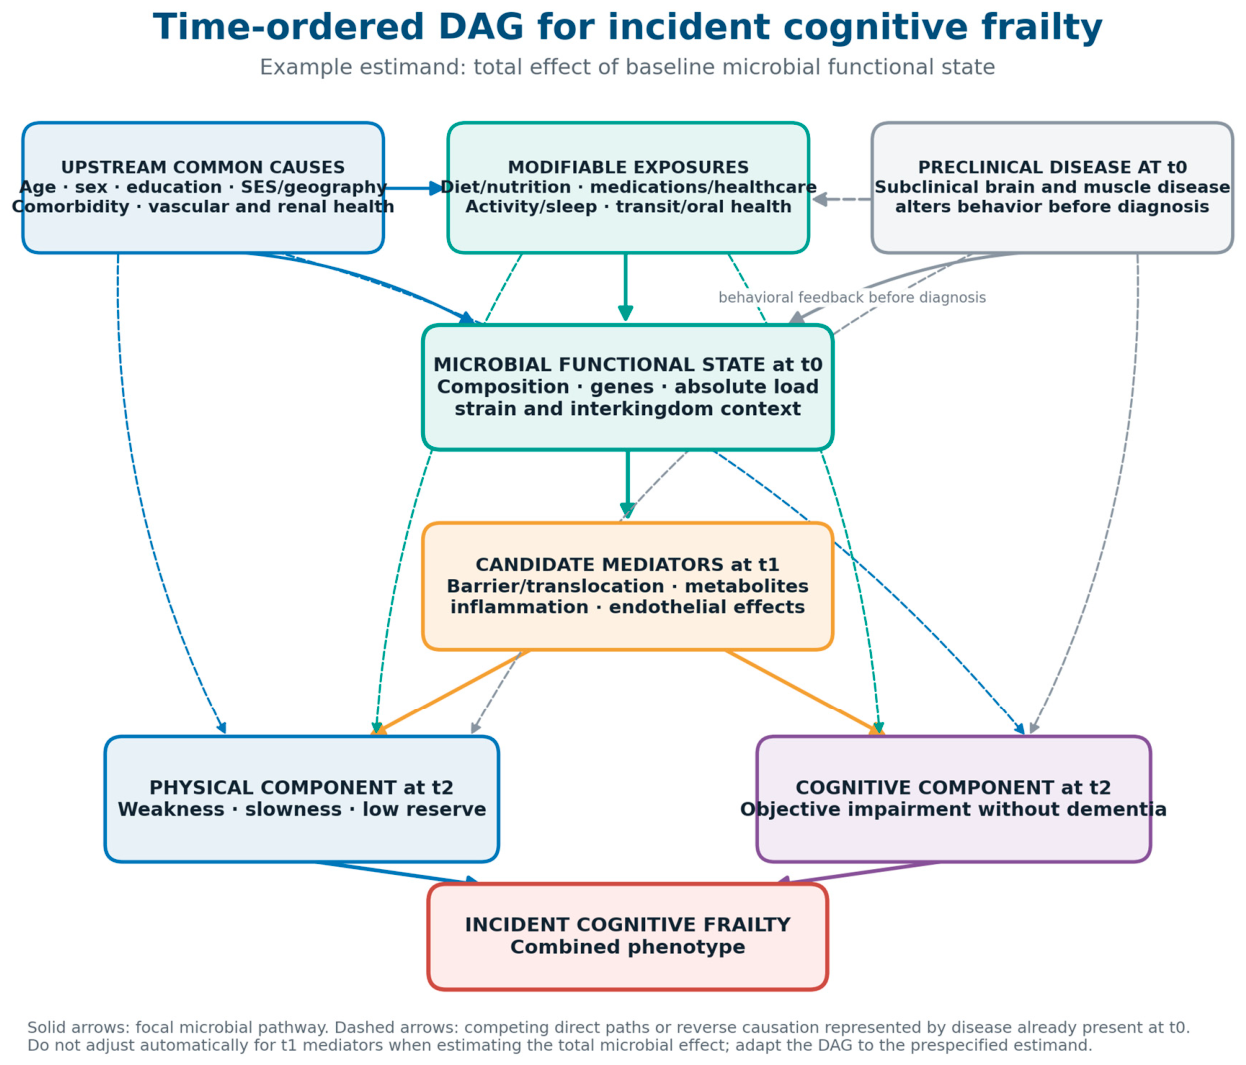
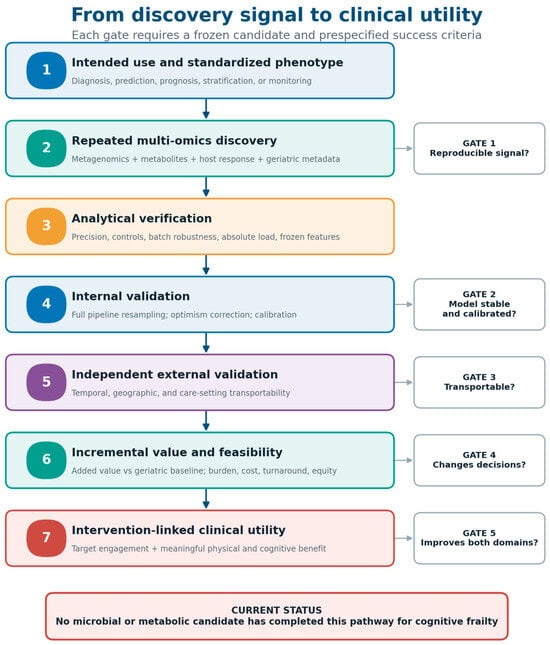
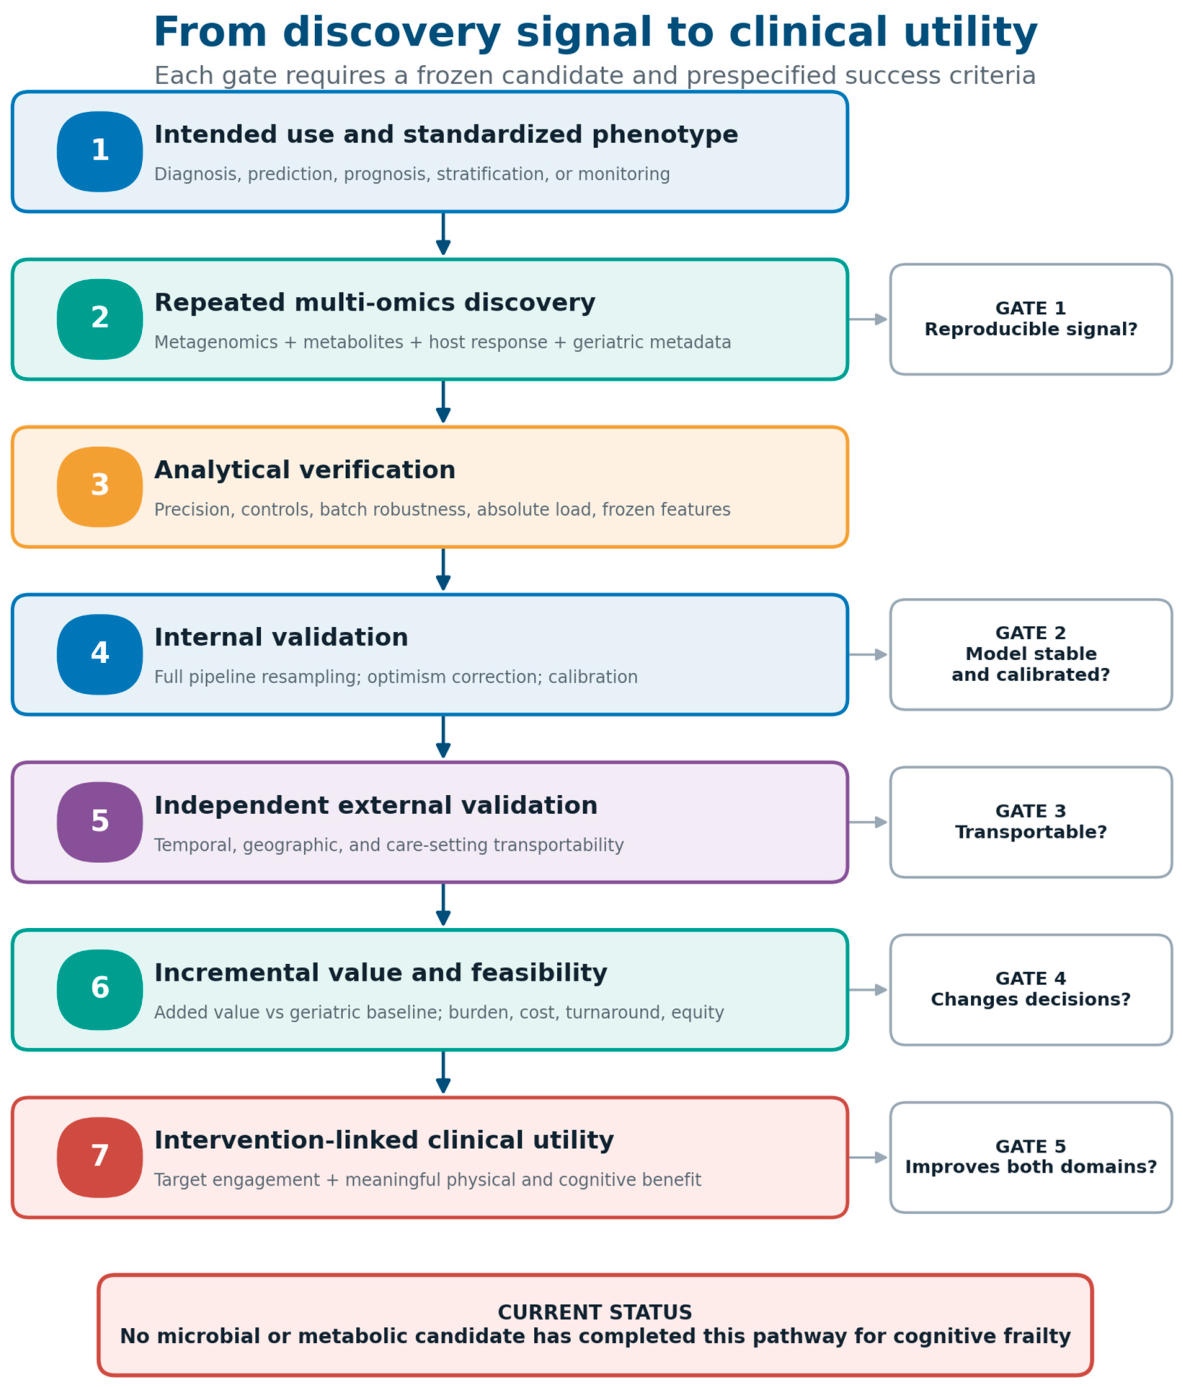

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.