Article

Neuroimmune Organoid Models Early Glioblastoma Establishment and the Invasive Niche

1
Stem Pharm, Incorporated, 2935 S Fish Hatchery Road PMB #235, Madison, WI 53711, USA
2
Department of Neurological Surgery, School of Medicine & Public Health, UW Carbone Cancer Center, University of Wisconsin, Madison, WI 53792, USA
*
Author to whom correspondence should be addressed.
Organoids 2026, 5(3), 23; https://doi.org/10.3390/organoids5030023
Submission received: 23 June 2026 / Revised: 27 July 2026 / Accepted: 30 July 2026 / Published: 2 August 2026

Abstract

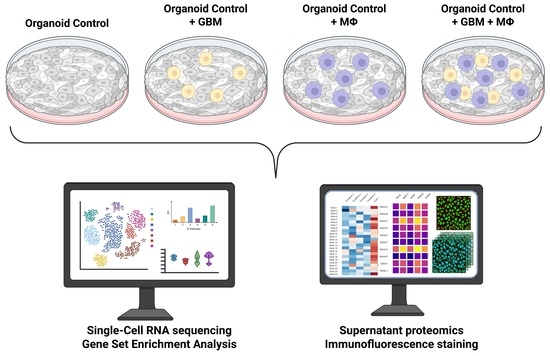
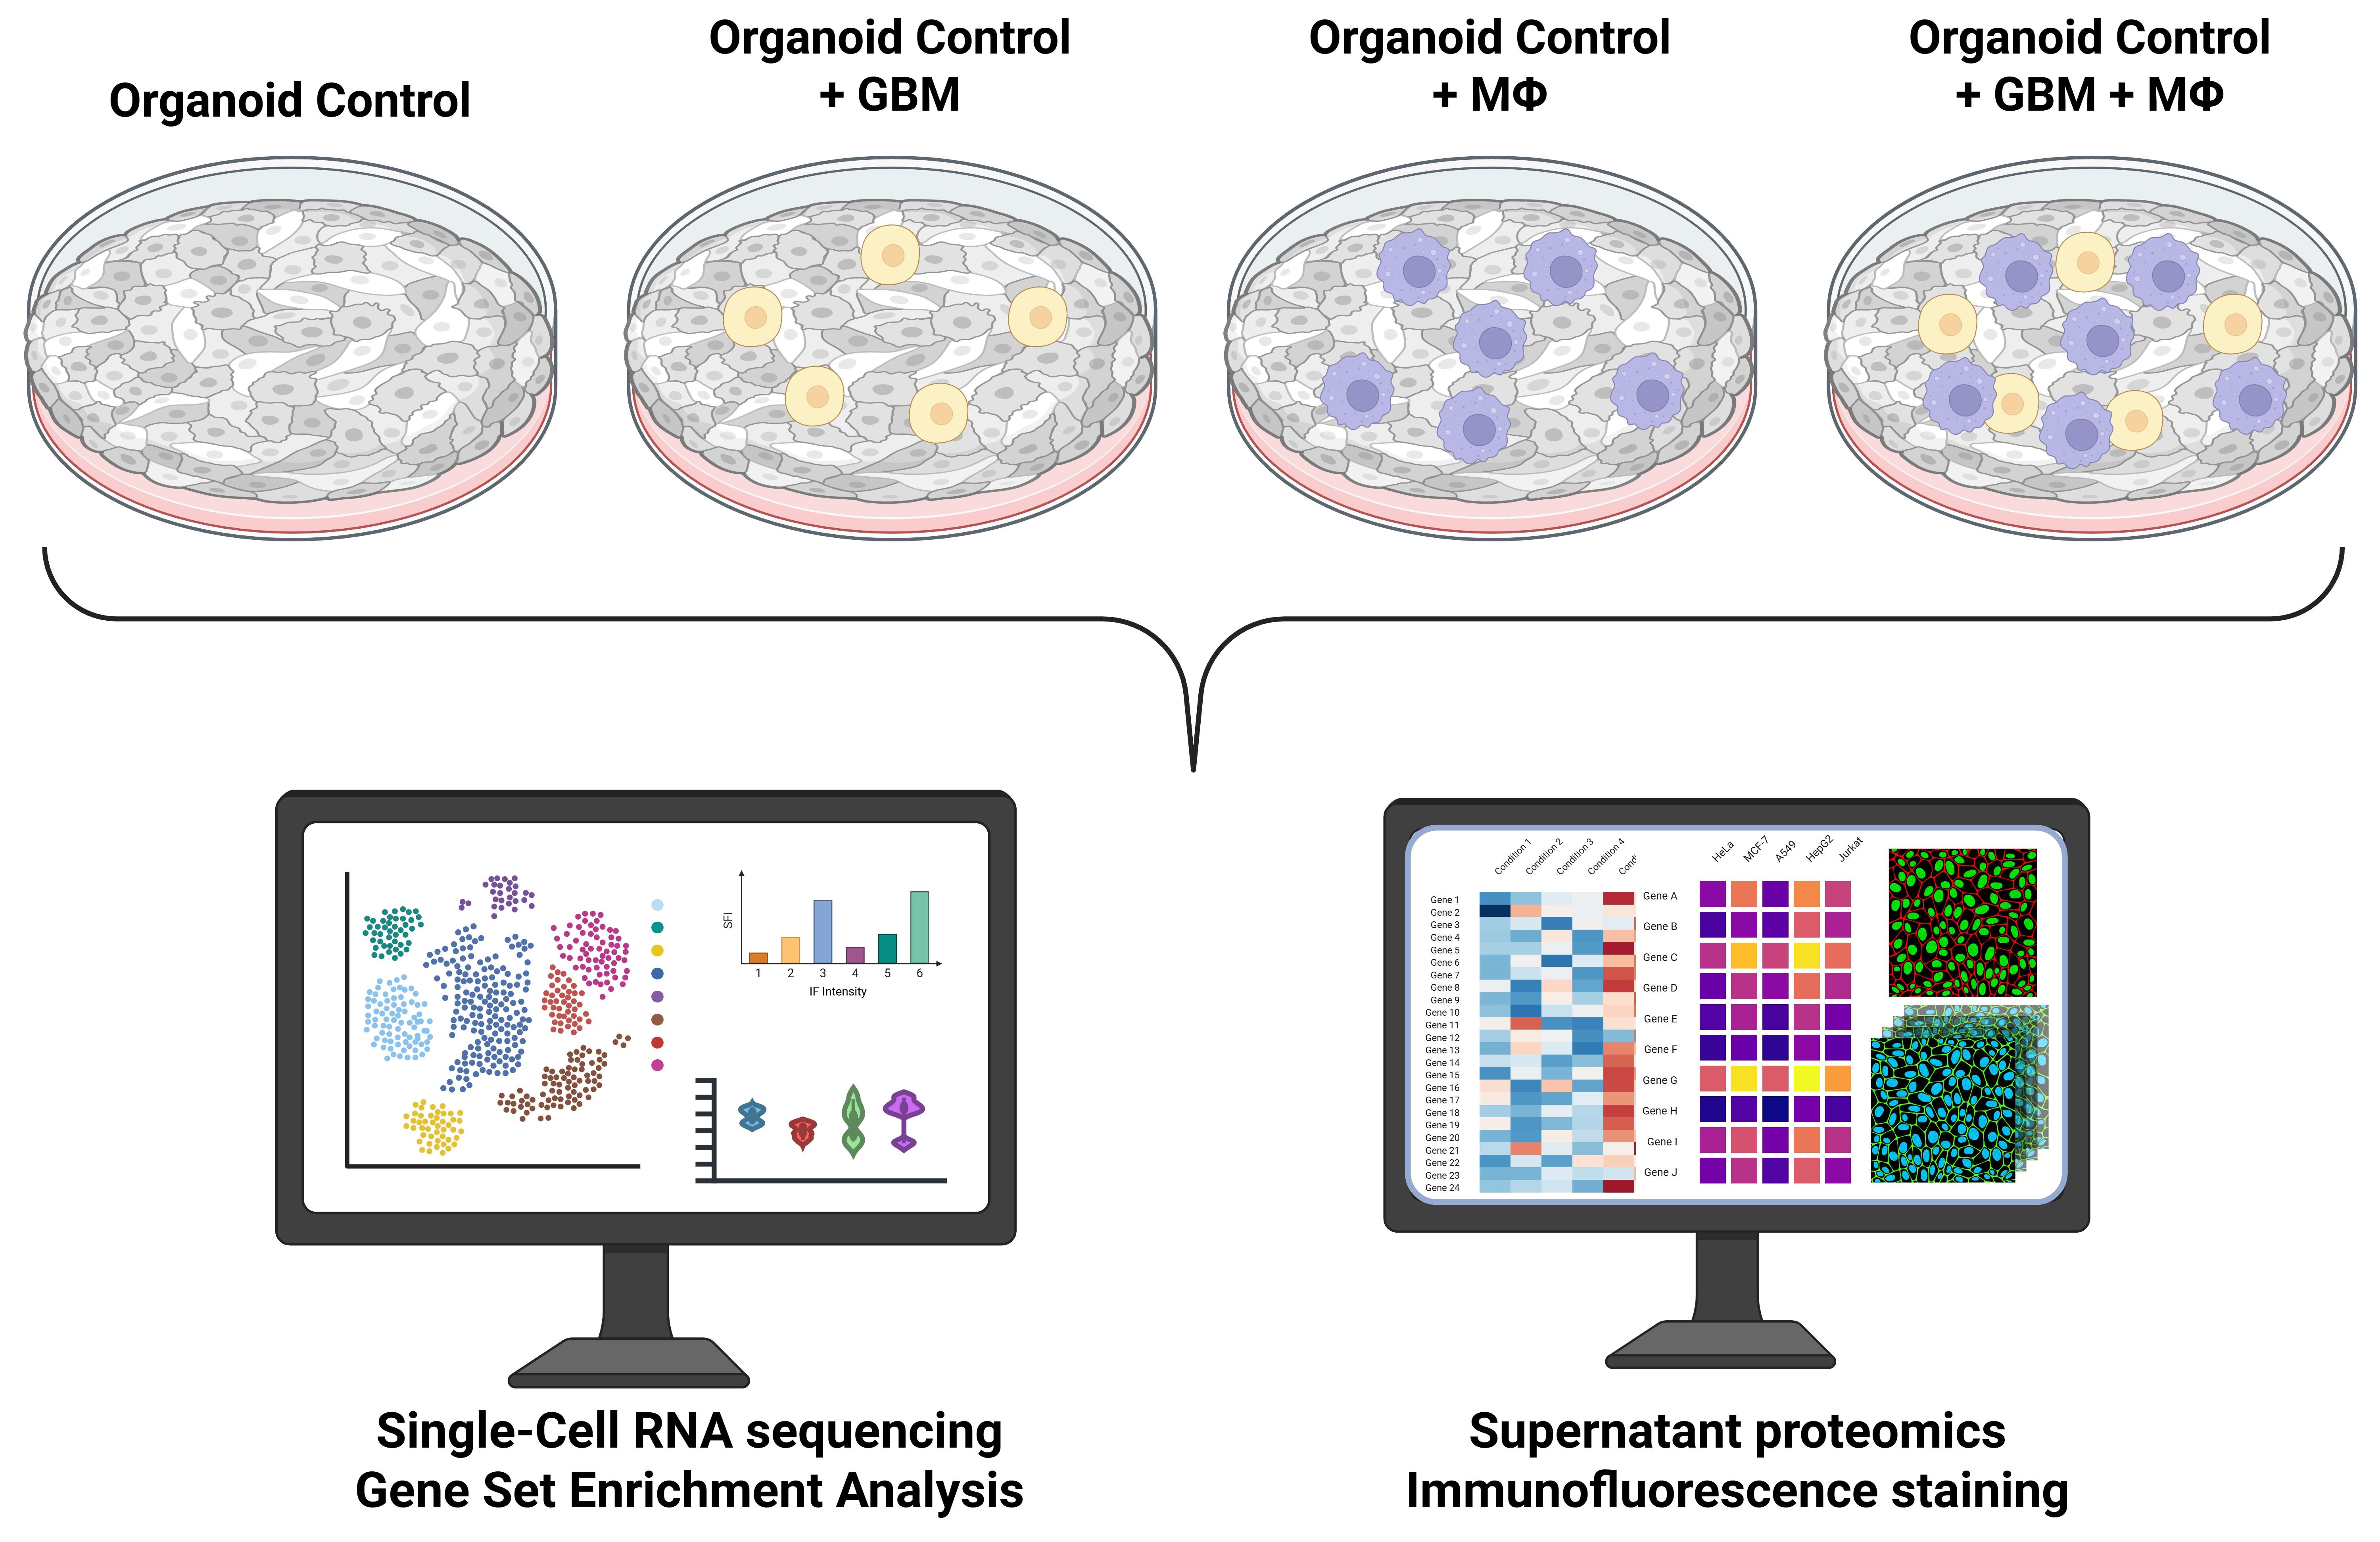
Glioblastoma (GBM) is a highly aggressive malignant brain tumor accounting for 15% of all brain tumors and 50% of all gliomas. The exact cause of GBM is not fully understood but risk factors include age, genetic mutations, exposure to ionizing radiation, and certain genetic disorders. Symptoms of GBM include headaches, seizures, cognitive impairment, and weaknesses on one side of the body. Myeloid cells account for 30–50% of the tumor mass and are instrumental in shaping the complex tumor microenvironment (TME). Inflammation in the TME is an important driver of tumor growth and invasion; however, as the environment evolves, the immunosuppressive TME poses a significant hurdle as it hinders the immune-mediated killing of tumor cells. Our work utilizes neuroimmune organoids containing neurons, astrocytes, microglia, and vascular-like cells, to which we add patient-derived GBM cells and/or iPSC-derived macrophages to model the GBM TME. Model characterization was performed using single-cell RNA sequencing and supernatant proteomics to determine cell-specific changes during coculturing. Our findings are consistent with this 7-day coculture model recapitulating key aspects of GBM early tumor establishment and immune activation, with transcriptomic and secretome signatures suggestive of an emerging immune evasion phenotype.

Graphical Abstract

1. Introduction

Glioblastoma (GBM) is the most aggressive and common malignant primary tumor affecting the central nervous system (CNS), with an incidence rate of 3 per 100,000 people [1]. Treatment involves maximal surgical resection and radiation followed by temozolomide-based chemotherapy. However, despite this standard of care, the five-year survival rate is around 6%, with a median survival of 12–16 months [2,3,4,5,6,7], with additional tumor-treating field radiotherapy extending median survival to 20.9 months [7]. One of the central challenges in treating GBM is the diffuse infiltration of the tumor into surrounding brain tissue, preventing complete surgical resection, as well as the cellular plasticity and rapid lineage switching of GBM that prevents effective eradication [8]. Consequently, virtually all patients experience recurrence, with over 80–90% arising at the edge of the resection cavity, typically within 6 to 9 months of completing treatment [9,10,11,12,13].
Of the glioma subtypes, isocitrate dehydrogenase (IDH) wild-type GBM represents the most aggressive form [14] and exhibits a more heterogeneous immune landscape enriched with microglia and macrophages [15,16]. These tumor-associated macrophages and microglia constitute up to 40–50% of cells in the tumor mass [15,17,18]. Due to this heterogeneity, in vitro 2D monocultures of patient-derived glioma stem cells (GSCs) do not faithfully reproduce tumor cell behavior and their interactions with surrounding normal tissue. Advances in single-cell RNA sequencing (scRNAseq) have revealed that GBM tumor cells exhibit transcriptional signatures resembling neural progenitor cells (NPC-like), oligodendrocyte precursor cells (OPC-like), astrocyte (AC-like), and mesenchymal (MES-like) cells [19]. Recent work in neural organoid models shows increased complexity in the plasticity of GSCs and cell state dynamics influenced by the tumor microenvironment (TME); however, these models often lack astrocyte, vascular, and microglial cells [20,21,22,23]. We have developed a multicellular neuroimmune planar organoid model [24] containing neurons, astrocytes, radial glia, vascular-like, and microglia cells. Using this model, we added patient-derived GSCs to host organoids with or without the addition of iPSC-derived macrophages (MΦ) and used single-cell RNA sequencing (scRNAseq) and supernatant proteomics for analysis. Overall, these data reveal the crosstalk between tumor and normal cells with differential cellular responses within the host organoid, the GSCs, and the immune cells. These models have the potential to provide valuable insight into the TME immune-related mechanisms underlying tumor invasion, treatment resistance, and recurrence.

2. Materials and Methods

2.1. Cell Culture

iPSC-derived human neural progenitor cells (NPCs) from an apparently healthy male donor were acquired from FUJIFILM Cellular Dynamics (FCDI, Madison, WI, USA) and were maintained in complete STEMdiff Neural Progenitor Medium (NPM), prepared by adding 1 mL of the Neural Progenitor Supplement A (STEMCELL Technologies 05836, Vancouver, BC, Canada) and 50 μL of the Neural Progenitor Supplement B (STEMCELL Technologies 05837) to 50 mL of Neural Progenitor Basal Medium (STEMCELL Technologies 05834). The iPSC line used to derive these cells is registered with the name CDIi001-A (RRID:CVCL_IT57) or 01279 in the European hPSCreg database, which documents informed consent. When thawing, 10 μM Y27632 (Rock inhibitor; Chemdea NC0407157, Med Chem Express, Monmouth Junction, NJ, USA) was included in the medium and removed day 1 post thawing. NPCs were cultured on Geltrex (Gibco A1413302, Thermo Fisher Scientific, Waltham, MA, USA) diluted 1:100 with DMEM/F12 (Gibco 11330032). Cells were cultured at 37 °C and 5% CO2 atmosphere, and passaged at 95% confluent with StemPro Accutase (Gibco A1110501) diluted 1:1 with Dulbecco’s Phosphate-Buffered Saline (D-PBS) (Gibco 14190094). NPCs were assessed for expression of NPC markers SOX2, Ki67 and Nestin by immunofluorescence (IF) analysis and were used within 5 passages of the original cell banking.
Human iPSC-derived iCell endothelial cells (ECs), a general/pan-endothelial cell line, were purchased from FUJIFILM Cellular Dynamics (FCDI C1114, Madison, WI, USA), donor 01434, and cultured according to the supplier’s recommendations using VascuLife Basal Medium (LifeLine LL-0003, LifeLine Cell Technologies, Frederick, MD, USA) with VascuLife VEGF LifeFactors. The iPSC line used to derive these cells is registered with the name CDIi002-A (RRID:CVCL_VC63) or 01434 in the European hPSCreg database, which documents informed consent. Heat-Inactivated FBS (HyClone SH30071.03HI, Hyclone, Logan, UT, USA) was added to the complete media at 10% in place of the supplied FBS. The supplied antimicrobial supplement was not added to the complete media. ECs were maintained on a coating of 3 μg/cm2 Fibronectin (Sigma FC010, Sigma Aldrich, St. Louis, MO, USA). Cells were cultured at 37 °C and 5% CO2 atmosphere, and passaged at 80% confluent with TrypLE Express (Gibco 12605028). Cells were used within 5 passages of receipt from the supplier.
Human iPSC-derived iCell mesenchymal stem cells (MSCs) were purchased from FUJIFILM Cellular Dynamics (FCDI R1098), donor 01279, and cultured in complete MSC medium composed of 0.25× Ham’s F-12 (Gibco 11765054), 0.75× IMDM (Gibco 12440046), 50 μg/mL Ascorbic Acid (Sigma A8960), 0.5× B-27 Supplement Minus Vitamin A (Gibco 12587010), 50 ng/mL bFGF (R&D Systems 233-FB, Minneapolis, MN, USA), 0.05% BSA (Gibco 15260037), 1× GlutaMAX (Gibco 35050061), 450 μM MTG (Sigma M6145), 0.5× N-2 Supplement (Gibco 17502048), and 50 ng/mL PDGF-BB (PeproTech 100-14B, Cranbury, NJ, USA). MSCs were cultured on a coating of 5 μg/mL Fibronectin (Sigma FC010) and 10 μg/mL Collagen I, (Gibco A1048301). Cells were cultured at 37 °C and 5% CO2 atmosphere, and passaged at 80% confluent with TrypLE Express (Gibco 12605028). Cells were used within 5 passages of receipt from the supplier.
Patient-derived GBM cells were generously provided by Dr. Mahua Dey. Protocols were approved and patients consented under IRB 2019-1308, approved by the University of Wisconsin. After surgical resection, tissue samples were removed from the operating room and taken to the lab where they were digested using collagenase (Gibco 17018029) for 30 min, filtered through a 70-micron mesh, and passed serially through pipette tips for further mechanical dissociation prior to cryopreservation. Cell lines were maintained through serial passage of flank tumor xenografts in immunocompromised nude mice (Charles River, NU(NCr)-Foxn1nu, Wilmington, MA, USA) as previously described [25,26], using protocols approved by the Office of Laboratory Animal Welfare of the University of Wisconsin–Madison. Briefly, hind flank xenograft tumors were resected, processed as described above, and cryopreserved. Single-cell suspensions were cultured on low-attachment 6-well plates (Stem Cell Technologies 100-0083) and cultured in neurobasal base media (Gibco 21103049) supplemented with 1× N2 (Gibco 17502048), 1× B27 (1× Gibco 17504044), EGF (20 ng/mL) and bFGF (20 ng/mL), and passaged using Accutase (Invitrogen 00-4555-56, Thermo Fisher Scientific).

2.2. Organoid Generation and Culturing

Human neuroimmune organoids were generated from NPCs, microglia, ECs, and MSCs. Except for the microglia, cells were cultured per the cell supplier’s instructions prior to plating onto a polyethylene glycol (PEG)-based hydrogel optimized for this application (proprietary formulation, Stem Pharm, Madison, WI, USA). Human iPSC-derived iCell Microglia 121 (MG), donor 01279, were purchased from FUJIFILM Cellular Dynamics and were added directly to organoids from cryopreservation. The generation of planar neural organoids has previously been described [24,27,28]. Briefly, the hydrogel was polymerized in μ-Plate 96 Well 3D plates (Ibidi 89646, Fitchburg, WI, USA) and equilibrated overnight in D-PBS and then in NMM prior to plating NPCs. NPCs, MSCs, ECs and MG were plated in serum-free medium at the following time points; NPCs day 0 (25 K/well), MSCs and ECs day 3 (18 K and 1.8 K/well respectively), and MG day 14 (12.5 K/well). Organoids were maintained in Neural Maintenance Medium (NMM): DF3S (DMEM/F12 (Gibco 11330032) supplemented with 64 μg/mL L-ascorbic acid-2-phosphate magnesium (Sigma A8960), 14 ng/mL Sodium Selenium (Sigma S5261), 543 μg/mL Sodium Bicarbonate (Gibco 25080-094) supplemented with 1× B-27 Supplement (Gibco 17504044), 1× N-2 Supplement (Gibco, 17502048), 1× GlutaMAX (Gibco 35050061), 1× MEM NEAA (Gibco 11140050), and 1× Penicillin–Streptomycin (Gibco 15140122). NMM was supplemented with 5 ng/mL Heat-Stable bFGF (Gibco PHG0367) on days 0–5 and 100 ng/mL VEGF (R&D Systems 293-VE) on days 3–13. Cultures were fed daily, with 50% of medium removed and fresh medium added back, and cultured at 37 °C and 5% CO2 atmosphere. The organoids were cultured until day 22 post plating with NMM prior to the addition of GBM and macrophage cells.

2.3. GBM Neuroimmune Organoid Generation

Day 22 organoids were seeded with 25,000 GBM cells and/or 12,500 macrophage cells in suspension. Human iPSC-derived macrophages (MΦ) (FCDI R1186), donor 01279, were purchased from FUJIFILM Cellular Dynamics and were added directly to organoids from cryopreservation. All organoids, controls and cocultures, were cultured in NMM supplemented with EGF and bFGF (20 ng/mL). Cultures were fed daily with 50% medium exchange and maintained at 37 °C and 5% CO2 atmosphere.

2.4. Immunofluorescence Imaging

Organoids were fixed with 4% paraformaldehyde in D-PBS for 1 h and stored in D-PBS at 4 °C. Organoid samples were permeabilized and blocked with D-PBS containing 10% Donkey Serum (Sigma D9663), 0.3% TritonX-100 (Sigma T9284) and 0.02% Sodium Azide (Fisher S227I, Fisher Scientific, Pittsburgh, PA, USA) (Antibody Incubation Solution, AIS) for 1 h. Primary antibodies were incubated overnight at 4 °C in AIS and washed three times in D-PBS, followed by the addition of secondary antibodies in AIS for incubation overnight at 4 °C and washing three times in D-PBS. Alexa Fluor 647 conjugated anti-GFAP (1:200, Abcam ab302828, Waltham, MA, USA), SOX10 (1:200, Proteintech 66786-1-Ig, Thermo Fisher Scientific), and Donkey anti-Mouse Alexa Fluor 488 (1:500, Thermo A32766, Thermo Fisher Scientific) were used for this study. Z-stack images were captured on a Nikon AX R confocal microscope with a 10× magnification. Image processing was performed in Nikon NIS-Elements. Maximum-intensity projection images are presented in representative images. For imaging, one biological replicate was assessed for each condition, one organoid per biological replicate.

2.5. Organoid Dissociation for scRNAseq

Six neuroimmune organoids (day 29) per condition (Table 1) were dissociated using a modified protocol from the Papain Digestion Kit (Worthington Biochemical Corp. LK003150, Lakewood, NJ, USA) and fixation protocols from 10x Genomics (Pleasanton, CA, USA). Organoids were washed with LINC wash buffer (1% Pluronic F-68 (Gibco 24040032) and 0.04% BSA (Gibco 15260037) in D-PBS) in the culture well. The organoids were pooled per condition and transferred to a round-bottom tube containing the dissociation solution (63% TrypLE Express (Gibco 12605010), 27% Papain (Worthington LK003150), 4.5% DNase (Worthington LK003150), 2 U/μL Protector RNAse (Roche 3335399001, Indianapolis, IN, USA), 5 μg/mL actinomycin D (Sigma A1410), 10 μM triptolide (Sigma T3652), and 27 μg/mL anisomycin (Sigma A9789)). Samples were placed at 37 °C for 40 min with titration every 10 min to dissociate. The samples were centrifuged at 300× g for 5 min. The dissociation solution was aspirated, and samples were washed with LINC wash buffer. Samples were passed through a 100 μM cell strainer and centrifuged at 500× g for 5 min at 4 °C. The wash buffer was aspirated and cells resuspended in LINC wash buffer. Samples were counted and checked for viability. Cells were fixed with 2% paraformaldehyde (EMS 15710, Electron Microscopy Sciences, Ambler, PA, USA) for 1 h at room temperature. Equal parts LINC quenching solution (0.1% TRIS; Fisher BP2471500) and LINC wash buffer were added to the fixed cells. Samples were centrifuged at 500× g for 5 min at 4 °C. The solution was aspirated and the samples resuspended in wash buffer then counted. Samples were centrifuged at 500× g for 5 min at 4 °C. Wash buffer was aspirated and samples resuspended in LINC freezing buffer (5% DMSO; Sigma D2650), 10% Glycerol (Sigma G5516), and 0.2 U/μL SUPERaseIN RNase Inhibitor (Invitrogen AM2694) in LINC wash buffer. Samples were frozen at −80 °C for 24 h prior to moving to liquid nitrogen for long-term storage.

2.6. scRNA-Seq

scRNA-seq was performed at the University of Wisconsin Biotechnology Gene Expression Center. Seurat (v5.3.0) [29] was used for quality control, normalization, sample integration, cell clustering, and visualization. Cells were filtered for features > 3000 and <15,000, transcripts < 140,000, and mitochondrial percent < 10%. Clustering was performed using UMAP. Cell clusters were annotated based on the expression of key marker genes identified for each target cell type. The scRNA-seq data for each cluster was first collapsed using the AggregateExpression() function in Seurat [29], generating bulk-like profiles that represented the pooled expression of all cells in each cluster. The median expression of marker genes associated with each target cell type was then calculated from these bulk-like profiles. Each cluster was subsequently assigned to the cell type with the highest median expression score for its corresponding marker genes. The list of target cell types and their associated marker genes included astrocytes (AQP4), excitatory (BDNF, SLC17A6, and TLX3), inhibitory (SLC32A1, DLX5, and GAD1), immature inhibitory (LDX5), radial glia (GBX2), dividing cells (MKI67), vascular-related like (DCN and COL5A3), microglia (C1QA and CX3CR1), macrophages (CHIT1), and GBM (PMP2 and CDKN2C). 10x Genomics Loupe Browser v8.1.2 was used for visualization and differential expression analysis to assist with marker gene identification. Differential gene expression between clusters was calculated in the Loupe Browser, which applies the same statistical method as Cell Ranger: an exact negative binomial test based on the sSeq method, switching to the fast asymptotic negative binomial test (as implemented in edgeR) for large UMI counts. The resulting p-values were adjusted for multiple testing using the Benjamini–Hochberg procedure. GO terms from GO Biological Process (GO:BP) were used to generate enrichment analysis using the gProfiler2 package in R, querying significantly upregulated and downregulated gene sets (padj < 0.05) for results and interpretation. To provide additional pathway-level validation, differentially expressed genes were further analyzed using Hallmark, KEGG, and Reactome gene set enrichment via the clusterProfiler package and ReactomePA packages in R (padj < 0.05) (data shown in Supplemental Figure S7). For further information on the methods used for analysis and interpretation, please refer to published reviews [30,31,32]. GBM meta-module scoring was performed as previously described [19]. Briefly, six meta-modules (MES1-2-like, NPC1-2-like, AC-like, and OPC-like) were used to score and assign cells into groups using Seurat’s AddModuleScore() function on the RNA assay. Cell cycle status was scored using the G1/S and G2/M meta-modules, and cells were classified as cycling if either module score exceeded 0.5 and colored for visualization based on density as described in [19]. Analysis and scoring for the modules were performed in R (v4.5.0) using Seurat (v5.4.0) and ggplot2 for visualization. Copy number variation (CNV) was inferred using inferCNV package in R (cutoff of 0.1 for 10x Genomics data). Astrocytes, microglia, macrophages, excitatory, inhibitory, immature inhibitory, and vascular-related like groups were designated as the reference group, with the GBM-annotated cluster serving as the observation group. Dividing cells and radial glia populations were excluded from the reference group due to potential overlap with proliferative and progenitor-like malignant cell states. Gene genomic coordinates were obtained from the GENCODE v19 (GRCh37/hg19) gene position reference.

2.7. Biochemical Assays

Cell supernatant was collected daily in half-medium changes (50%) or at the experimental endpoint (100%). The collected supernatant was frozen at −80 °C prior to proteomic analysis. Supernatant from the endpoint was analyzed with the Human Cytokine/Chemokine 71-Plex Discovery Assay® Array (HD71) (Eve Technologies, Calgary, AB, Canada). Cell culture supernatant from GBM, macrophages, and GBM and macrophage cocultures on the above-mentioned synthetic hydrogel for 7 days was collected and measured for comparison. For visualization, measurements were normalized to the highest value across all conditions and across the organoid-only conditions. Measurements below the limit of detection were entered as zero. Three biological replicates were assessed for each condition, one organoid per biological replicate.

3. Results

We generated four experimental growth conditions to model GBM: Organoid, Organoid + GBM, Organoid + MΦ, and Organoid + GBM + MΦ (Table 1). Host organoids were cultured as previously described, with the addition of mitogenic growth factors EGF and bFGF for the four conditions. Patient-derived GSCs (+GBM) and/or iPSC monocyte-derived macrophages (+MΦ) were added into day 22 organoids and cultured for seven days (day 29) prior to collection for scRNAseq.
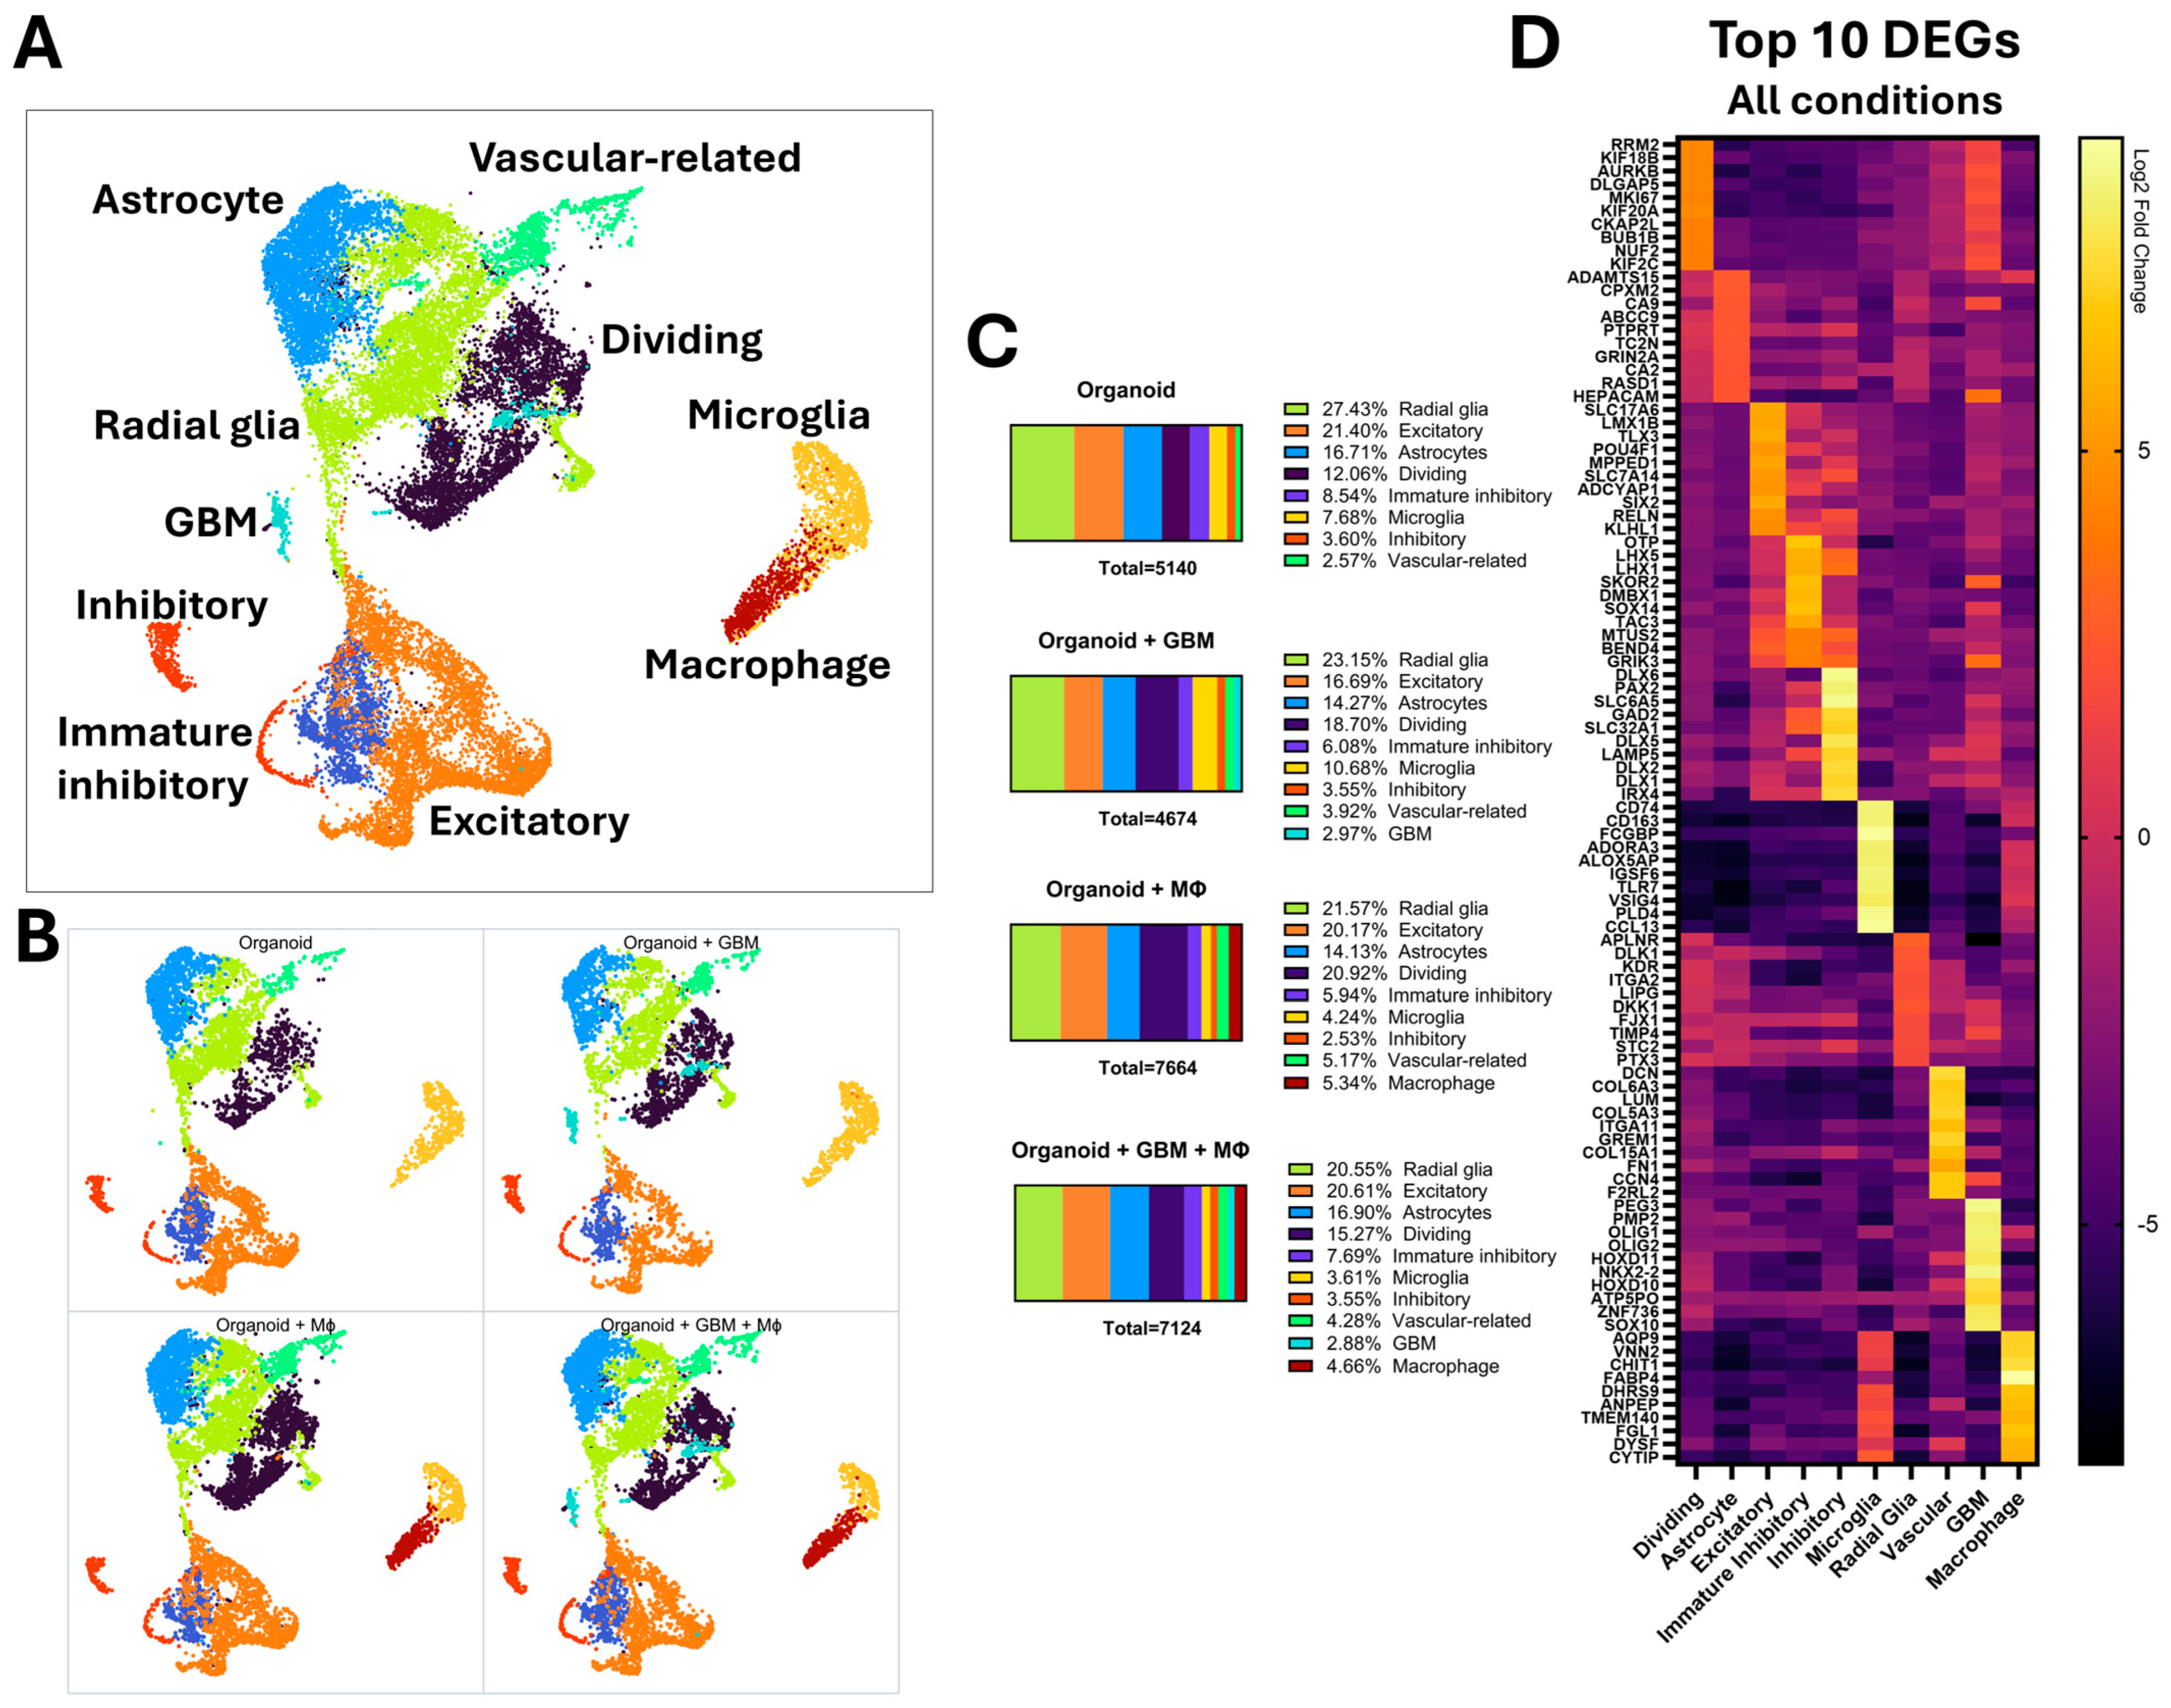
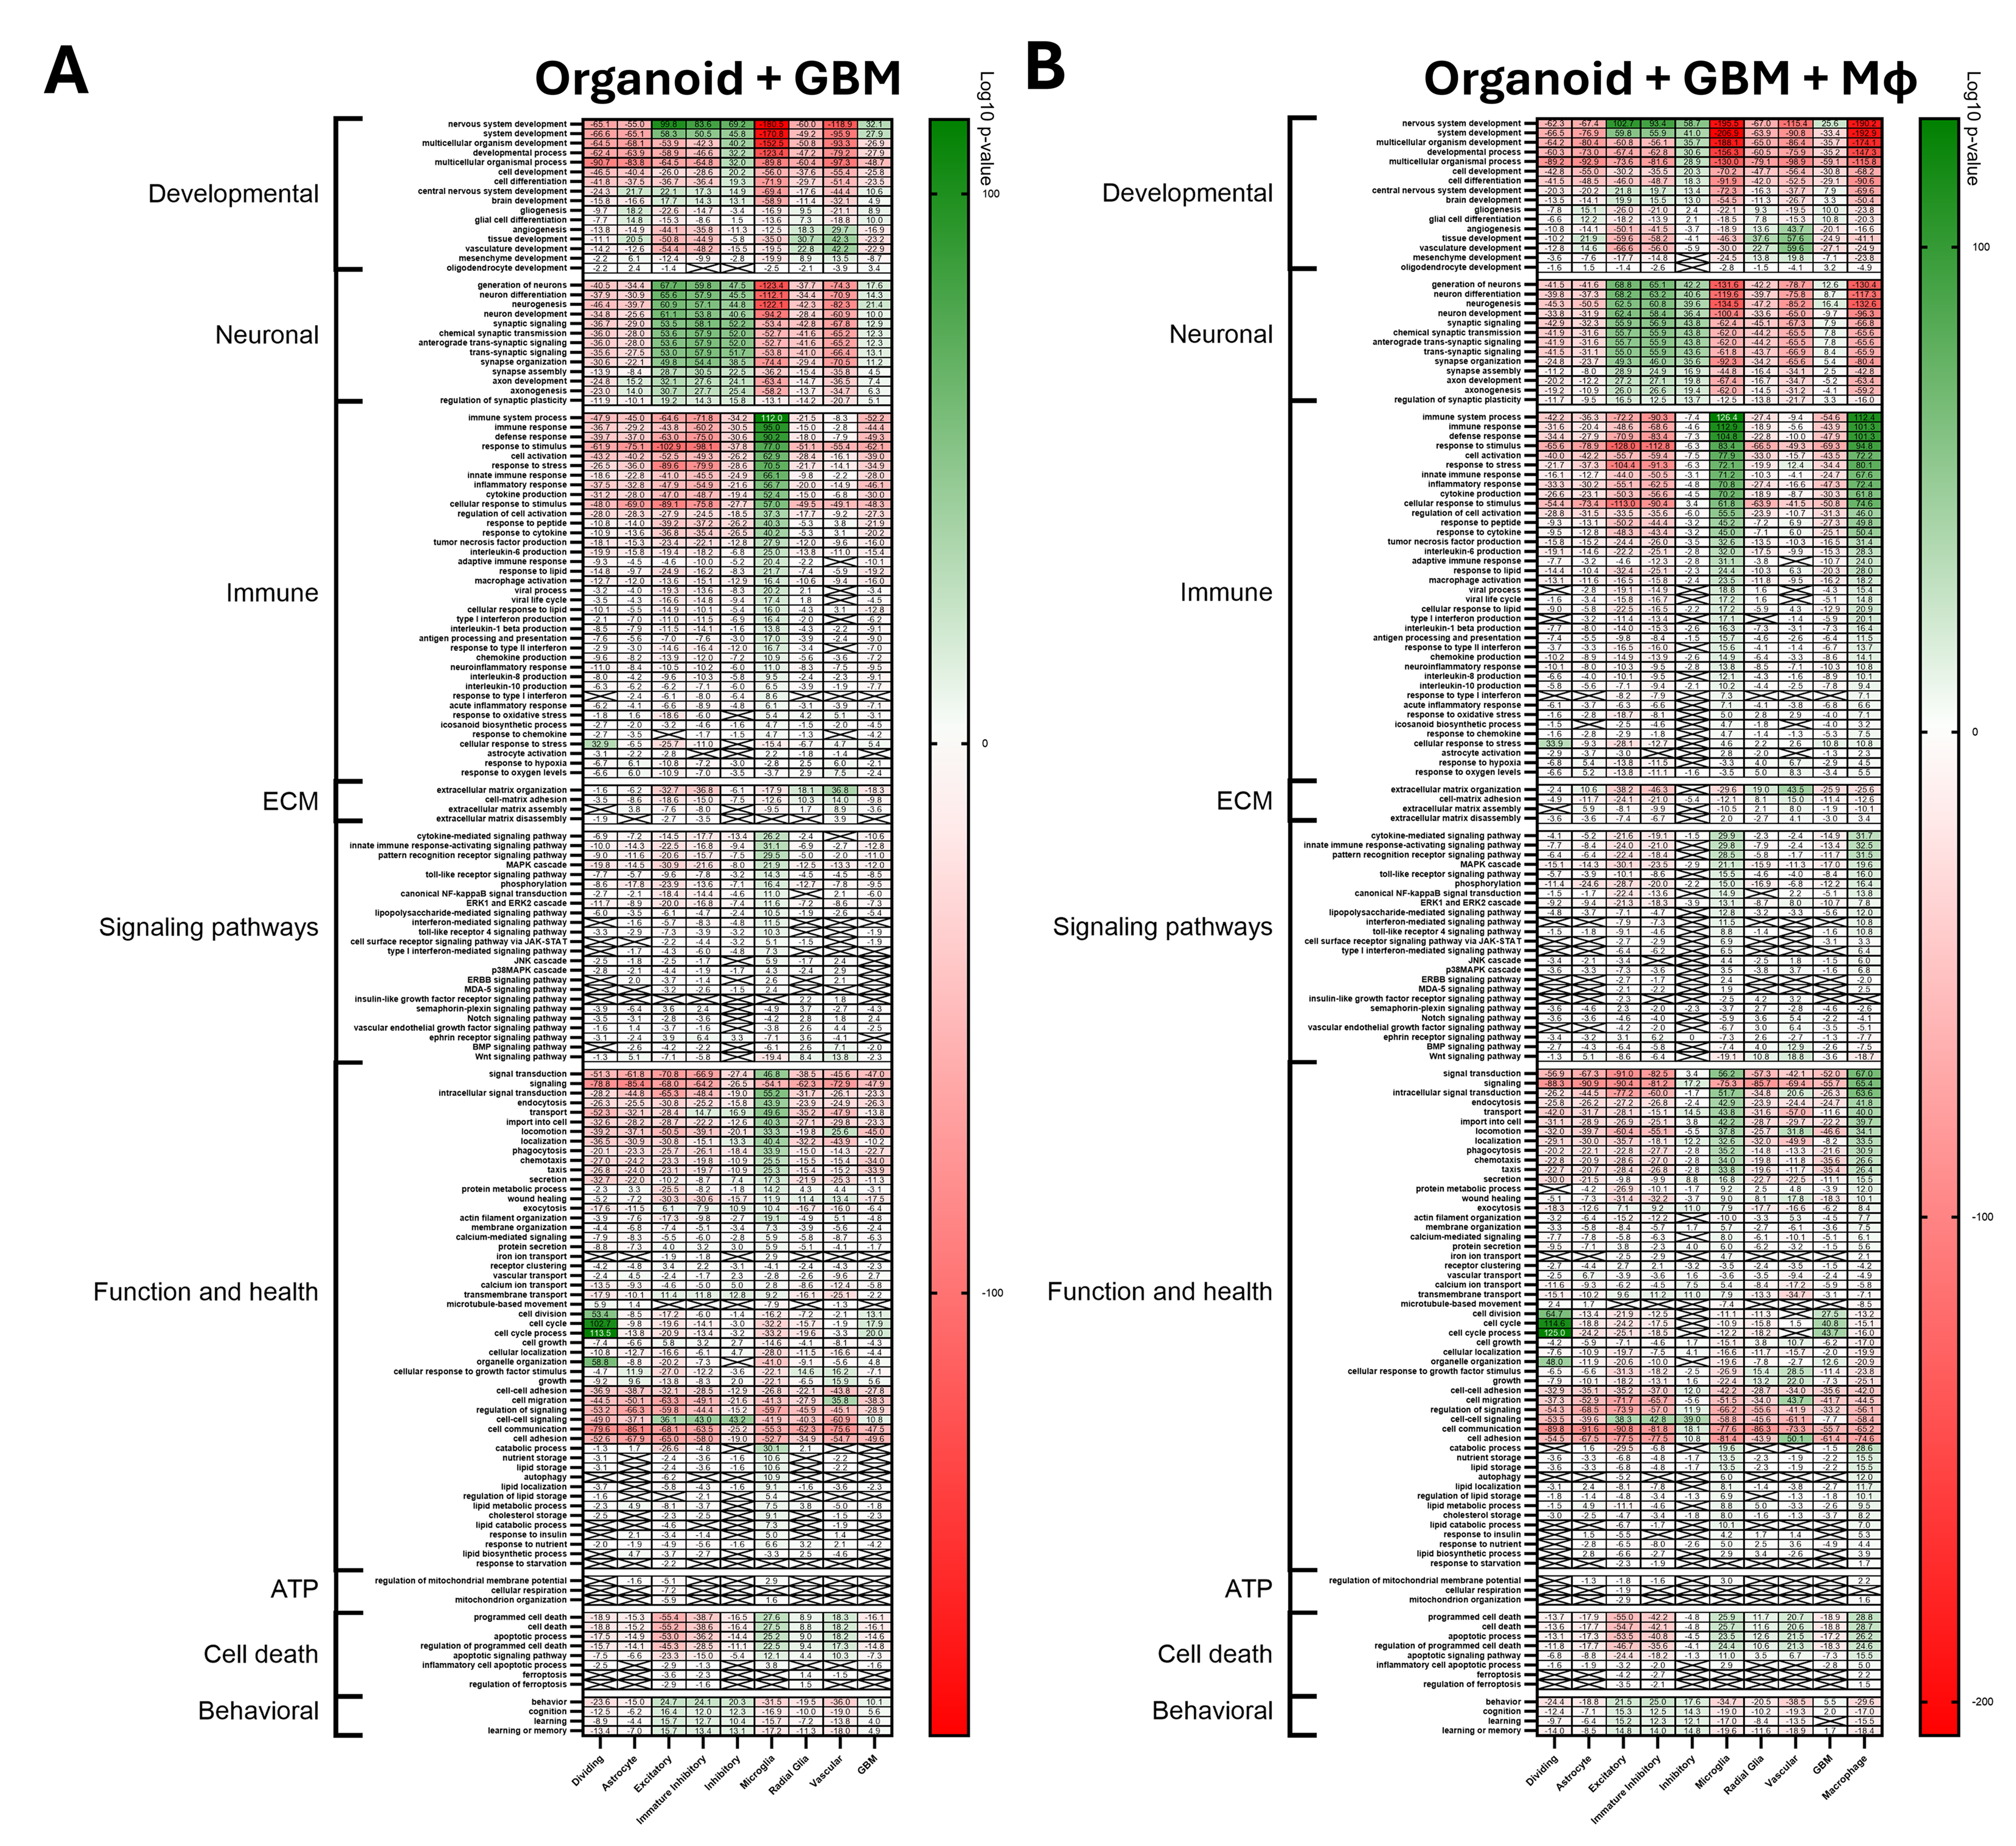
Organoids were harvested and the singularized cells were fixed and frozen prior to being subjected to the 10x Genomics Flex protocol. Figure 1A represents UMAP visualization of scRNA-seq data of the aggregated data from the four experimental growth conditions, and Figure 1B shows the UMAP separated by condition. Cell types were clustered and annotated based on canonical genes described in the figure legend. Relative cell population distributions between the four conditions are shown in Figure 1C, with the top 10 differentially expressed genes (DEGs) in each of the respective cell populations shown in Figure 1D. In the UMAP, the integrated GBM cells split into two distinct groups most closely clustering to the dividing and the radial glia cell populations (Figure 1A,B). The patient-derived GBM cells had a high relative gene expression of OPC-related markers OLIG1, OLIG2, and SOX10. Interestingly, we found that paternally expressed gene-3 (PEG3) could be used to identify the GBM population as this gene is developmentally repressed and epigenetically regulated (Supplemental Figure S1A) [33,34]. However, PMP2 was used for annotation based on previously published GBM scRNAseq datasets [35], while CDKN2C was used to distinguish proliferating GBM cells from native dividing organoid cells (Supplemental Figure S1B). Annotation was further confirmed using CNV inference (Supplemental Figure S8). Sequencing of the patient-sampled tumor detected the presence of TERT promoter mutation and loss of CDKN2A/B, both of which lead to aggressive tumor behavior with enhanced immortalization and proliferation [36]. Highly proliferative GSCs are primarily linked to NPC- and OPC-like cell states [19], with the expression of OLIG1/2 found to be a major driver of GBM proliferation [37]. The comparison of the expression distribution of GBM cell state-associated gene markers across all identified cell types further reveals heightened relative expression levels for OPC- and NPC-like genes in the GBM cluster (Supplementary Figure S2), supporting that the tumor cells favor an NPC- and OPC-like cell state in the organoid. To validate the annotation, we performed transcriptomic gene set enrichment analysis on the cell populations in the GBM-containing experimental conditions. We found that relative to the other cell populations, GBM was enriched for terms related to neuronal, glial, and oligodendrocyte development, as well as cell cycle and division pathways, in both the Organoid + GBM (Figure 2A) and the Organoid + GBM + MΦ condition (Figure 2B).
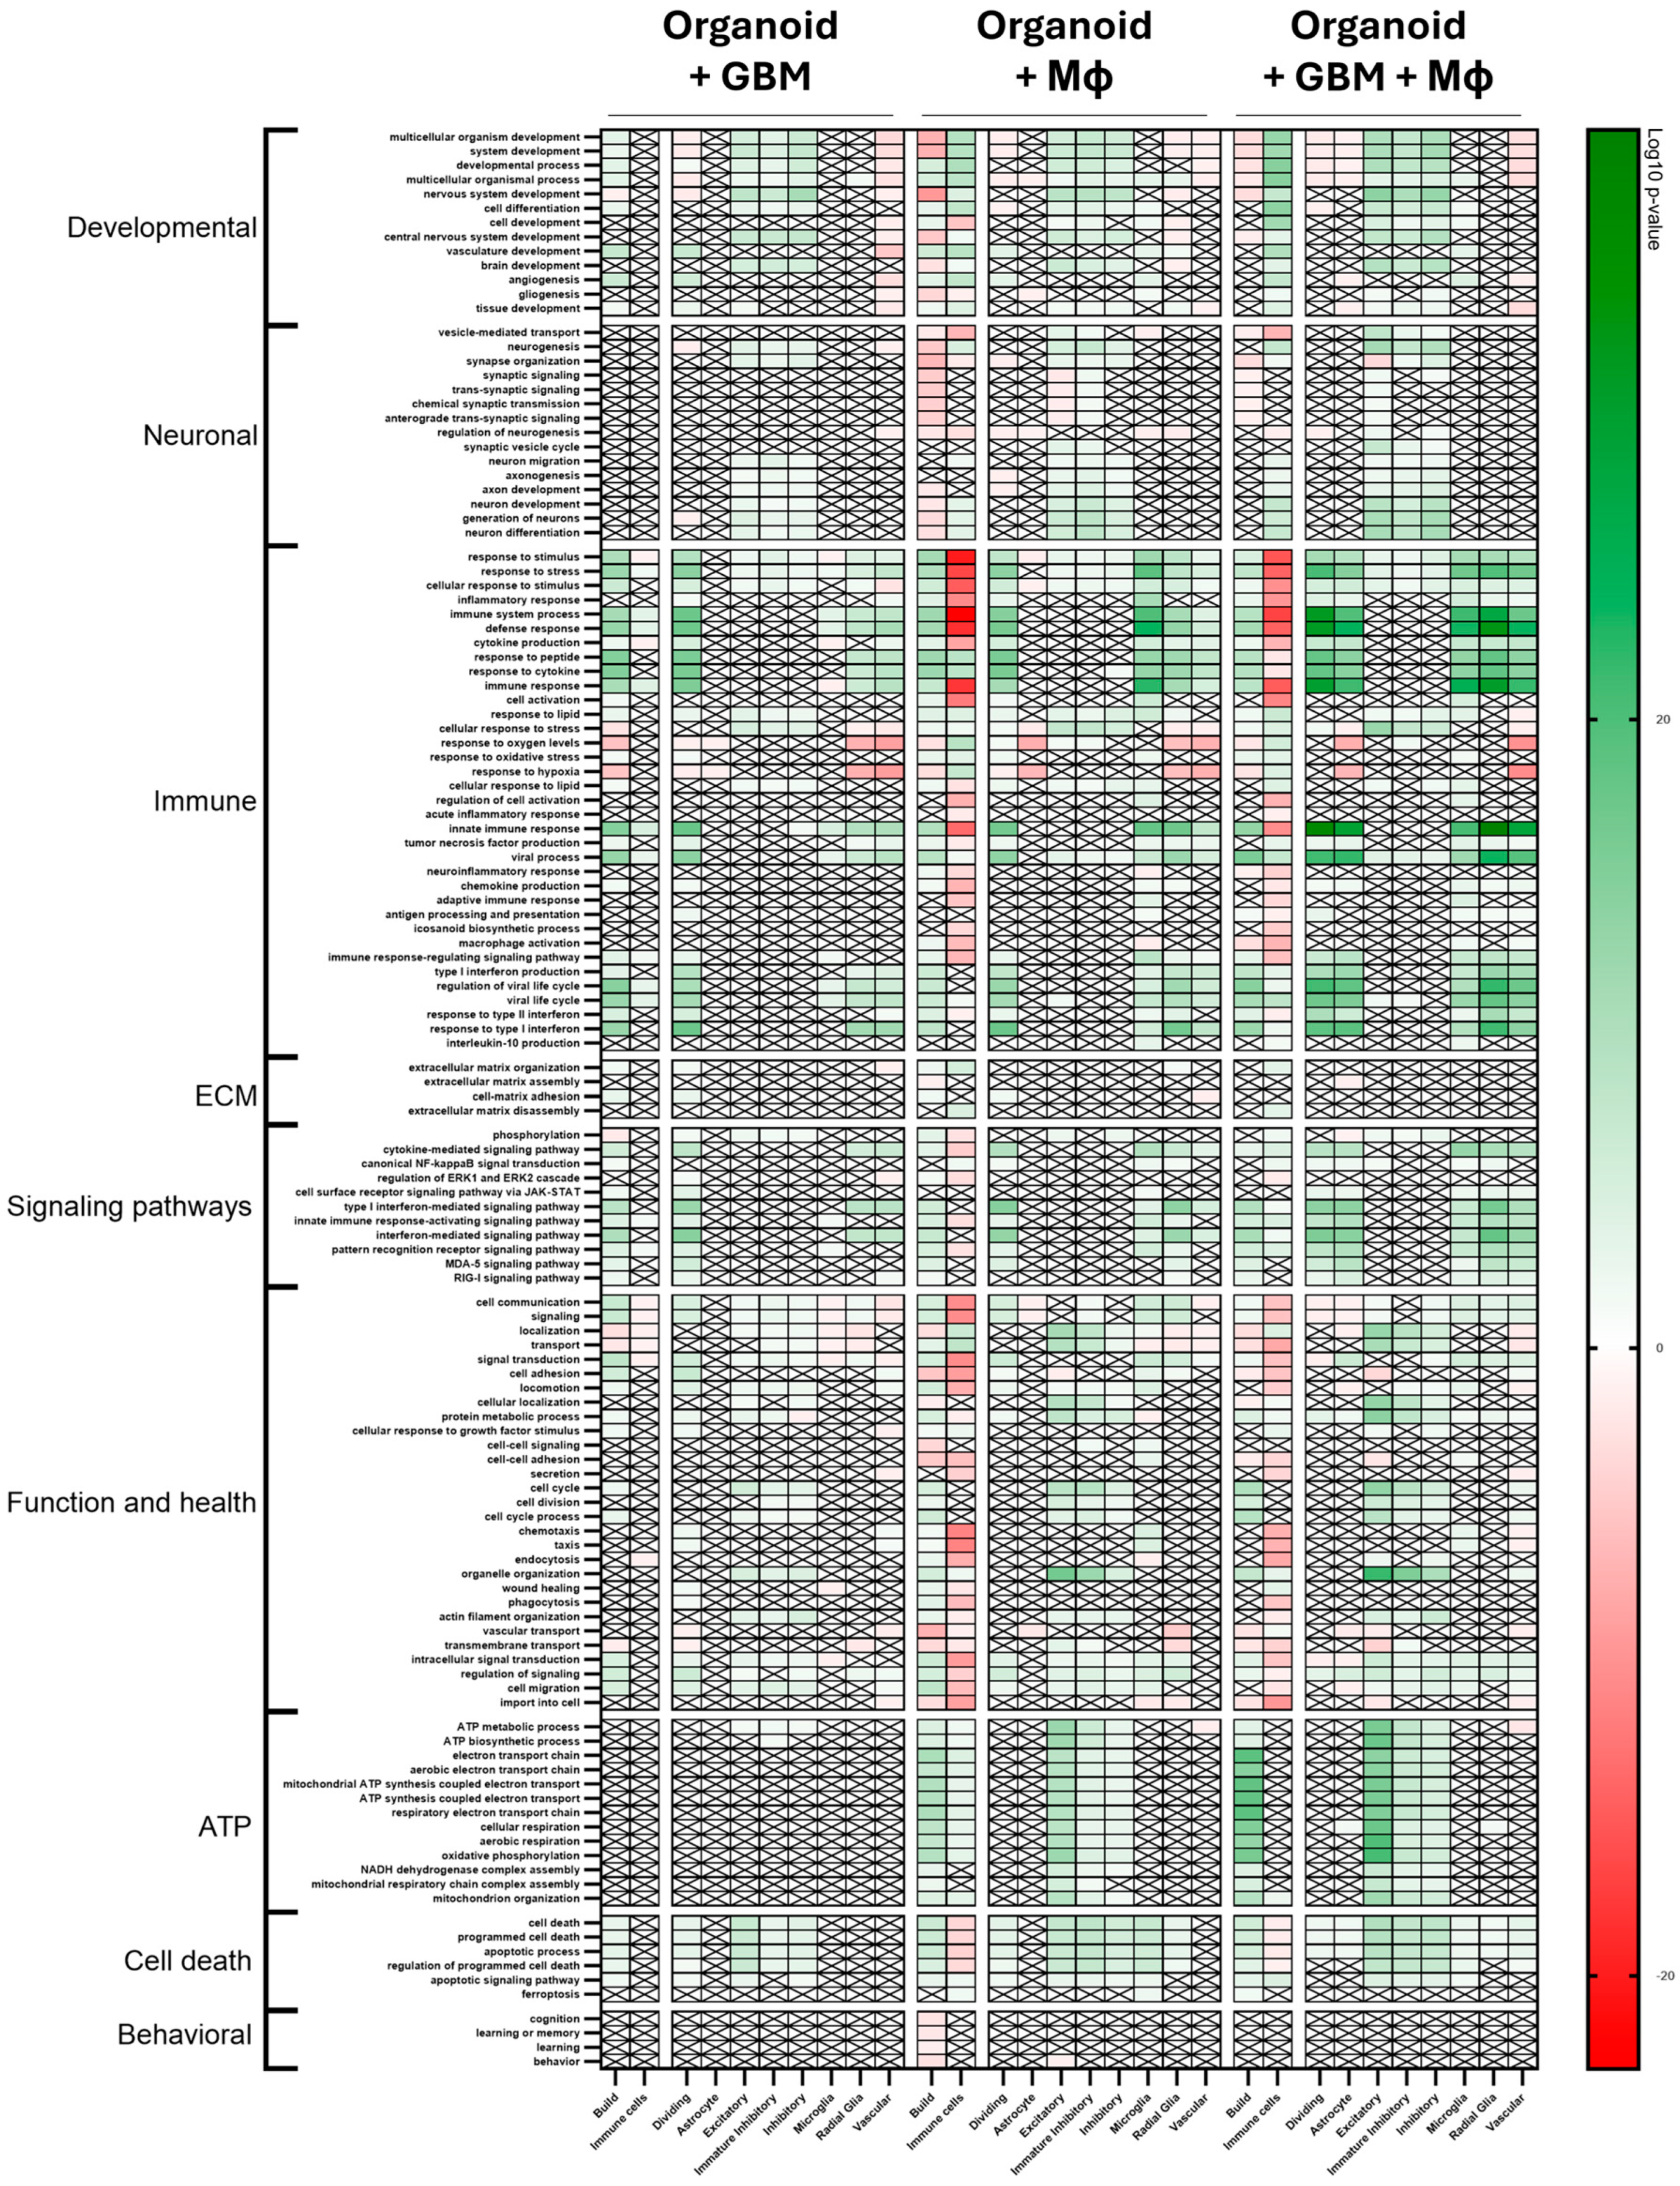
Enrichment analysis between the experimental conditions was performed between the cell populations using the cell populations in the control Organoid dataset (Figure 3). To account for the absence of GBM in the Organoid control, the aggregated cell populations in each condition was pooled as a general build (all cells) and compared between the different conditions. Likewise, to quantify macrophage contributions to the organoid-only control, microglia and macrophages were pooled as a general Immune Cell category. Between the builds in the Organoid + GBM, we see an increase in immune signaling pathways, particularly virally related interferon (IFN) signaling arising from the dividing, radial glia, microglia, and vascular cells, while the neuronal cell populations were enriched for terms related to neurogenesis and cell death. In the Organoid + MΦ condition, the addition of the macrophages in the Immune Cell population causes downregulation of immune related terms; however, a comparison within the microglia population alone shows the upregulation of these pathways. Similar to the Organoid + GBM, we see glial enrichment for IFN-related pathways and neuronal enrichment for cell death pathways. In addition, we see neuronal-specific upregulation of ATP and oxidative phosphorylation-related pathways. Finally, in the Organoid + GBM + MΦ conditions, we observe similar enrichment for glial IFN-related pathways and neuronal enrichment for cell death and ATP-related pathways, with an increased enrichment for immune response and signal transduction pathways in the dividing, astrocyte, microglia, radial glia, and vascular-related cells.
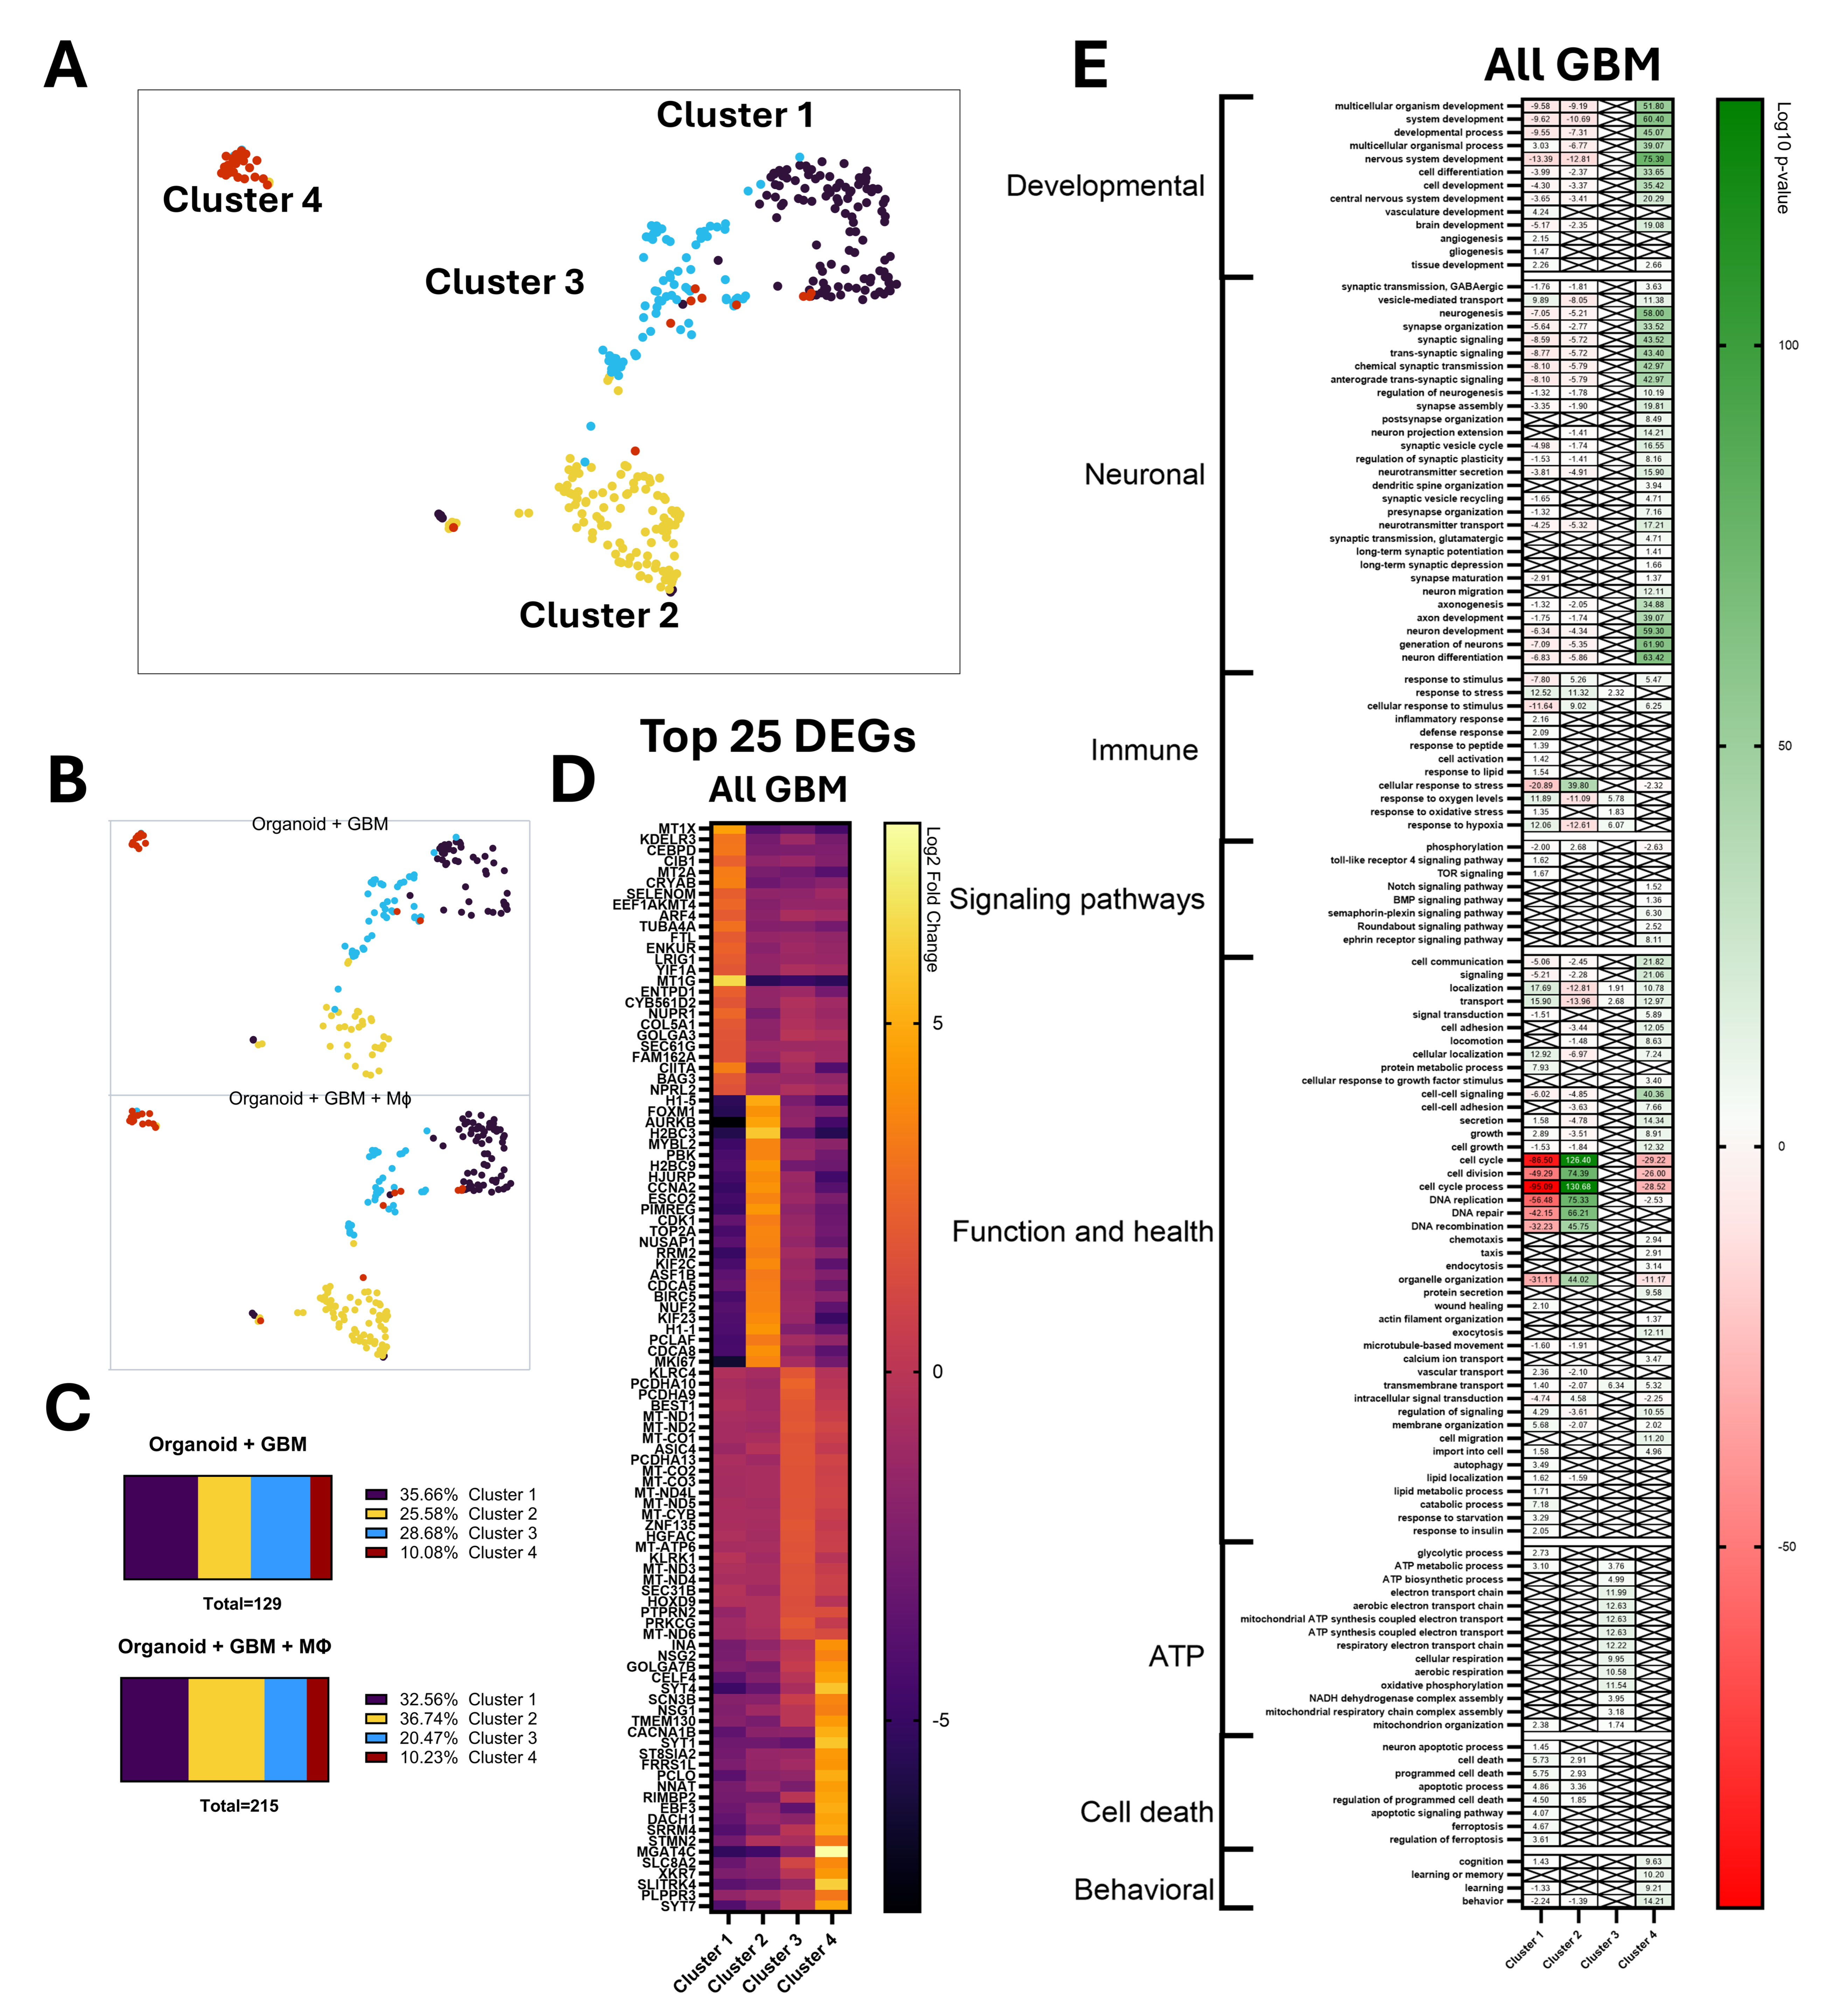
To determine alterations in the GBM cell population, we performed unbiased subclustering on the GBM cells alone and identified four different subclusters. UMAPs of the aggregated GBM cells (Figure 4A) and by experimental condition (Figure 4B) show that the addition of macrophages increases the relative cell population of Cluster 2. The top 25 DEGs (Figure 4D) and enrichment analysis (Figure 4E) show the differential gene and pathway regulation of the different clusters. Cluster 1 GBM cells are enriched for glial and vascular transport-related pathways and glycolytic and hypoxia-related terms while Cluster 2 GBM cells are enriched for cell cycle terms. Cluster 3 demonstrated upregulation of transport and ATP and oxidative phosphorylation-related pathways while Cluster 4 exhibited highly significant enrichment for neuronal and signaling pathways. Comparison of the expression distribution of GBM cell state-associated gene markers across the GBM subclusters (Supplementary Figure S3) supports that Cluster 1 represents an MES- or AC-like population, found primarily in hypoxic tumor cores [38], while Cluster 2 represents an OPC- and NPC-like population, found primarily in tumor bulk and leading edge, and Cluster 3 represents a energetically transitional state previously reported as a mitochondrial substate [35]. Interestingly, Cluster 4 had heightened expression of NPC-like markers and synaptic-related genes and was enriched for neuronal signaling and transport pathways, which has previously been described in the infiltrative cells mediating neuron–tumor crosstalk [35,39] and which facilitates tumor integration into the neural circuits [40]. Comparison of the expression distribution of GBM cell state-associated gene markers across the GBM-containing conditions with or without macrophages shows that macrophages induce higher OPC- and MES-like gene expression (Supplementary Figure S3). Furthermore, as confirmation of the heightened presence of OPC-like and NPC-like GBM cell state in our organoids, we performed GBM cell state mapping via meta-module scoring previously established from patient tumor samples [19]. These Neftel star plots further highlight the heightened occurrence of OPC-like and NPC-like GBM cells in the organoid, which is exacerbated in the presence of macrophages (Supplemental Figure S4).
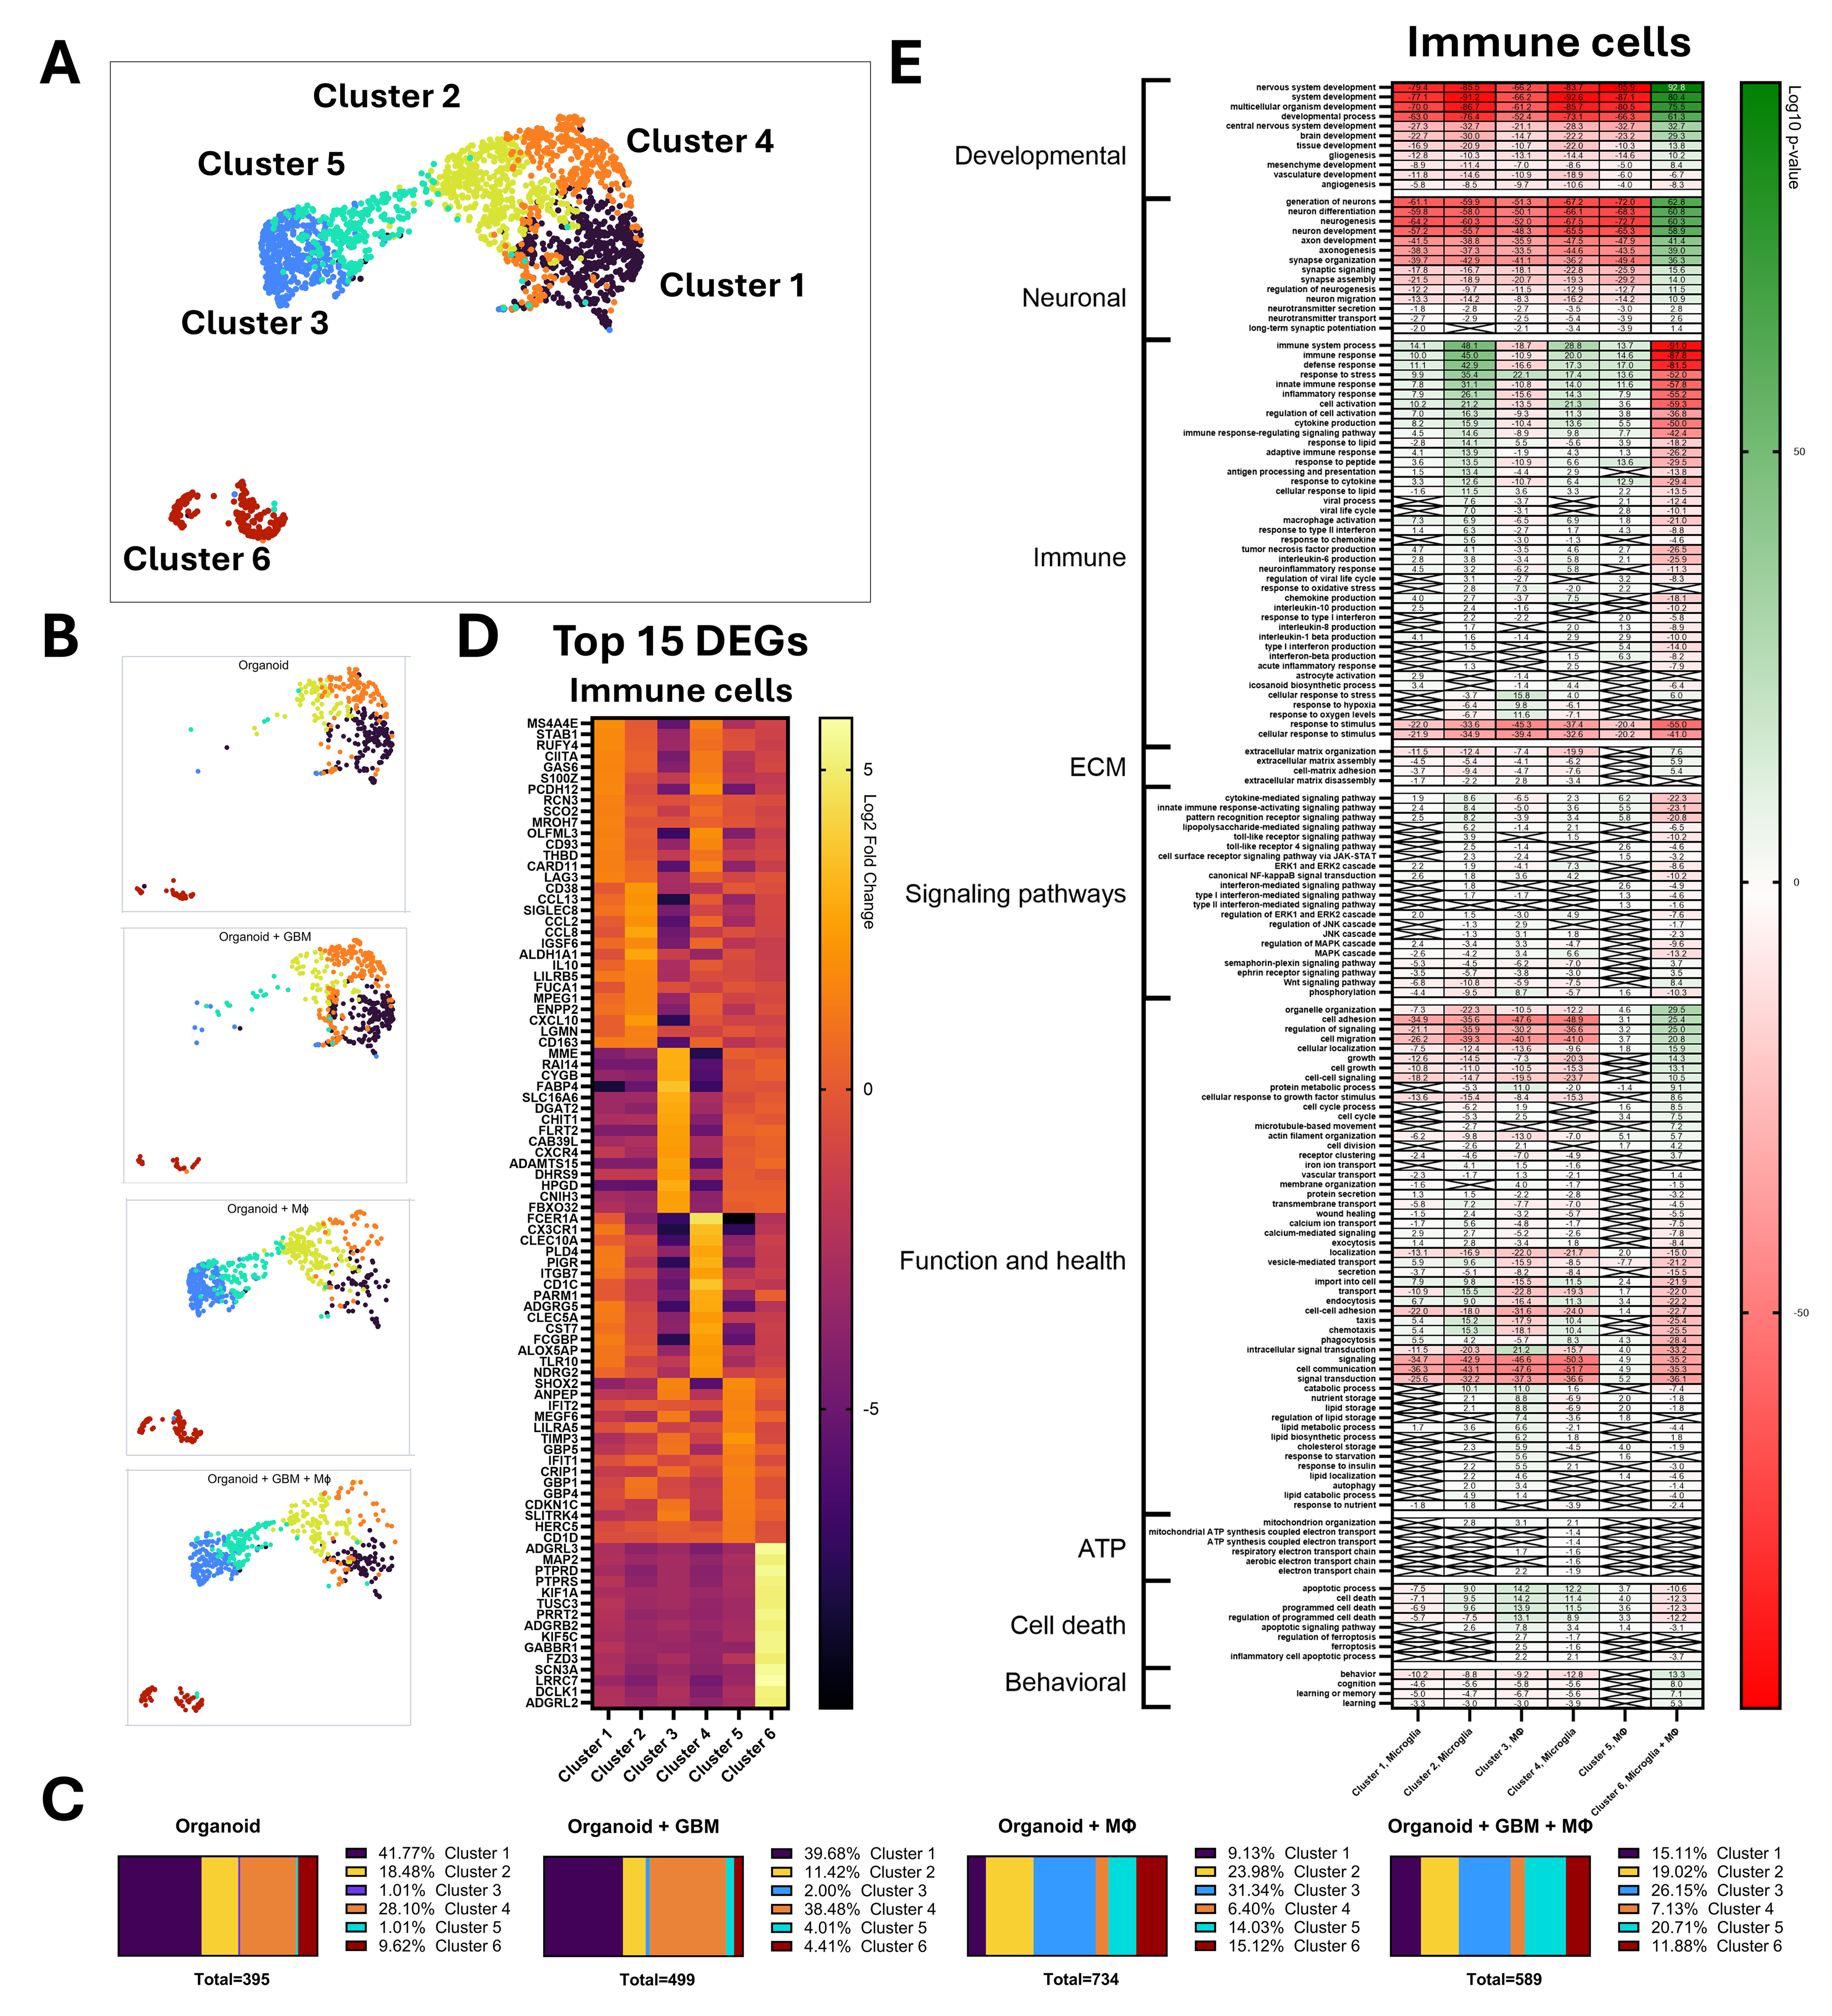
Unbiased subclustering of the immune cells encompassing both microglia and monocyte-derived macrophages identified six different subclusters. UMAPs of the aggregated immune cells (Figure 5A) and by experimental condition (Figure 5B) show that Cluster 3 and 5 are largely composed of macrophages while Clusters 1, 2, and 4 are largely microglial (Supplementary Figure S5). The top 15 DEGs (Figure 5D) and enrichment analysis (Figure 5E) show the differential gene and pathway regulation of the different clusters. Cluster 1 microglia demonstrate more significant enrichment for IL-1B production, astrocyte activation, and TNF production while Cluster 2 microglia demonstrate highly significant enrichment for immune response including IFN signaling, chemotaxis, and wound healing. Cluster 4 microglia are more significantly enriched in phagocytosis, MAPK and ERK signaling, and IL-6 production. Cluster 3 macrophages show enrichment for lipid-related processes, intracellular signal transduction, and hypoxia while Cluster 5 macrophages are enriched for IFN production and response related pathways. These two populations of macrophages, IFN-associated and lipid metabolism-associated, have been previously reported in GBM TME [41]. Cluster 6 was composed of both microglia and macrophages and had relatively higher enrichment of neuronal-related pathways, which may point to contamination or detection of engulfed transcripts, as has been frequently reported in transcriptomic profiling in microglia [42,43]. Of all the subclusters, only Cluster 1 and Cluster 2 microglia showed significant enrichment for IL-10 production. Among the immune cells, microglia exhibited higher expression of TGFB1 while macrophages had minimally higher expression of TGFB2.
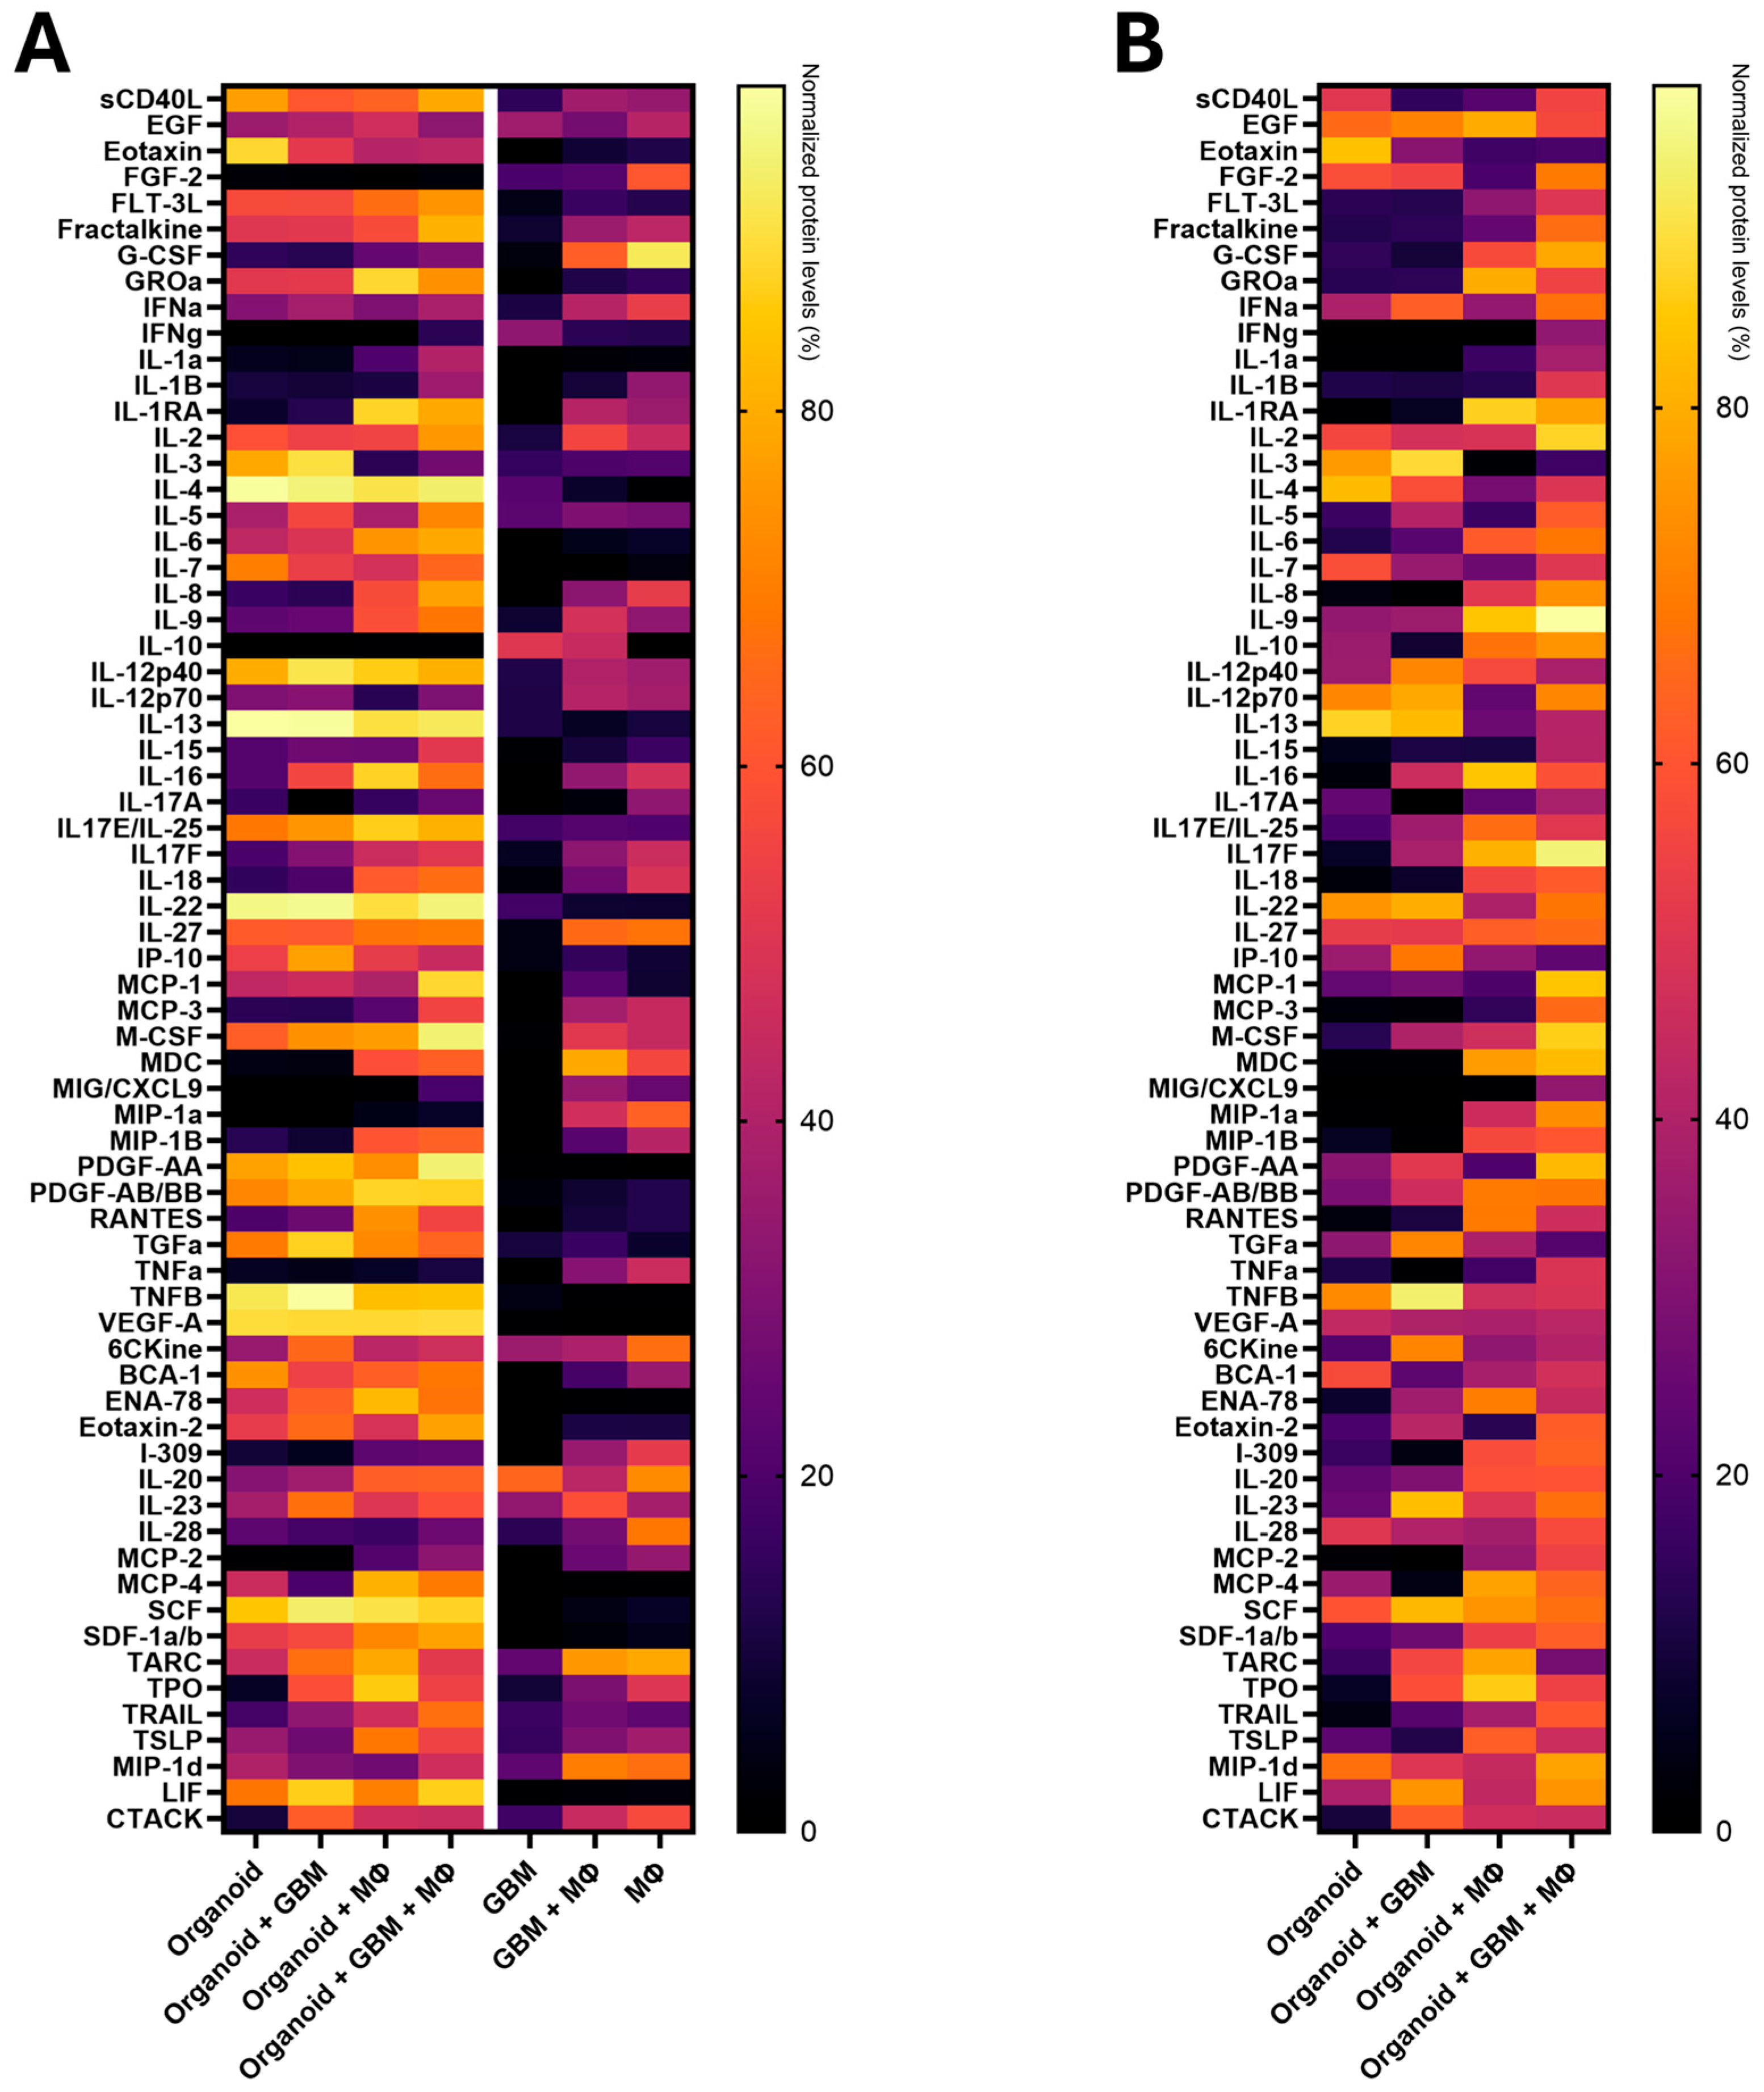
Cell culture supernatants collected from day 29 were analyzed via proteomic multiplex and compared to media from cultures containing GBM alone, GBM + MΦ, and MΦ alone. Measurements were normalized across all datasets (Figure 6A) and across the organoid-alone conditions (Figure 6B). Interestingly, we found the highest secretion of IL-10 in cultures of GBM-alone while in the organoid conditions, levels were highest in Organoid + GBM + MΦ, indicating that the GBM secretome is altered when cultured in a neuroimmune organoid model compared to when in monoculture or simple coculture systems. Additionally, several proteins that have been implicated in GBM progression were found specifically upregulated in the GBM-containing organoids vs. in monoculture and coculture conditions including IFNα, IL-17E/IL-25, MCP-3, MIP-1B, PDGF-AA, VEGF, and LIF [44,45,46,47,48,49,50]. Comparative coculturing reveals that MCP-3 and MIP-1B were primarily secreted by macrophages, while IFNα was secreted by both microglia and macrophages. In contrast, IL-17E/IL-25, PDGF-AA, VEGF-A and LIF were secreted at low levels in the GBM, MΦ, and GBM + MΦ cultures and were predominantly derived from the organoid (Figure 6A,B).
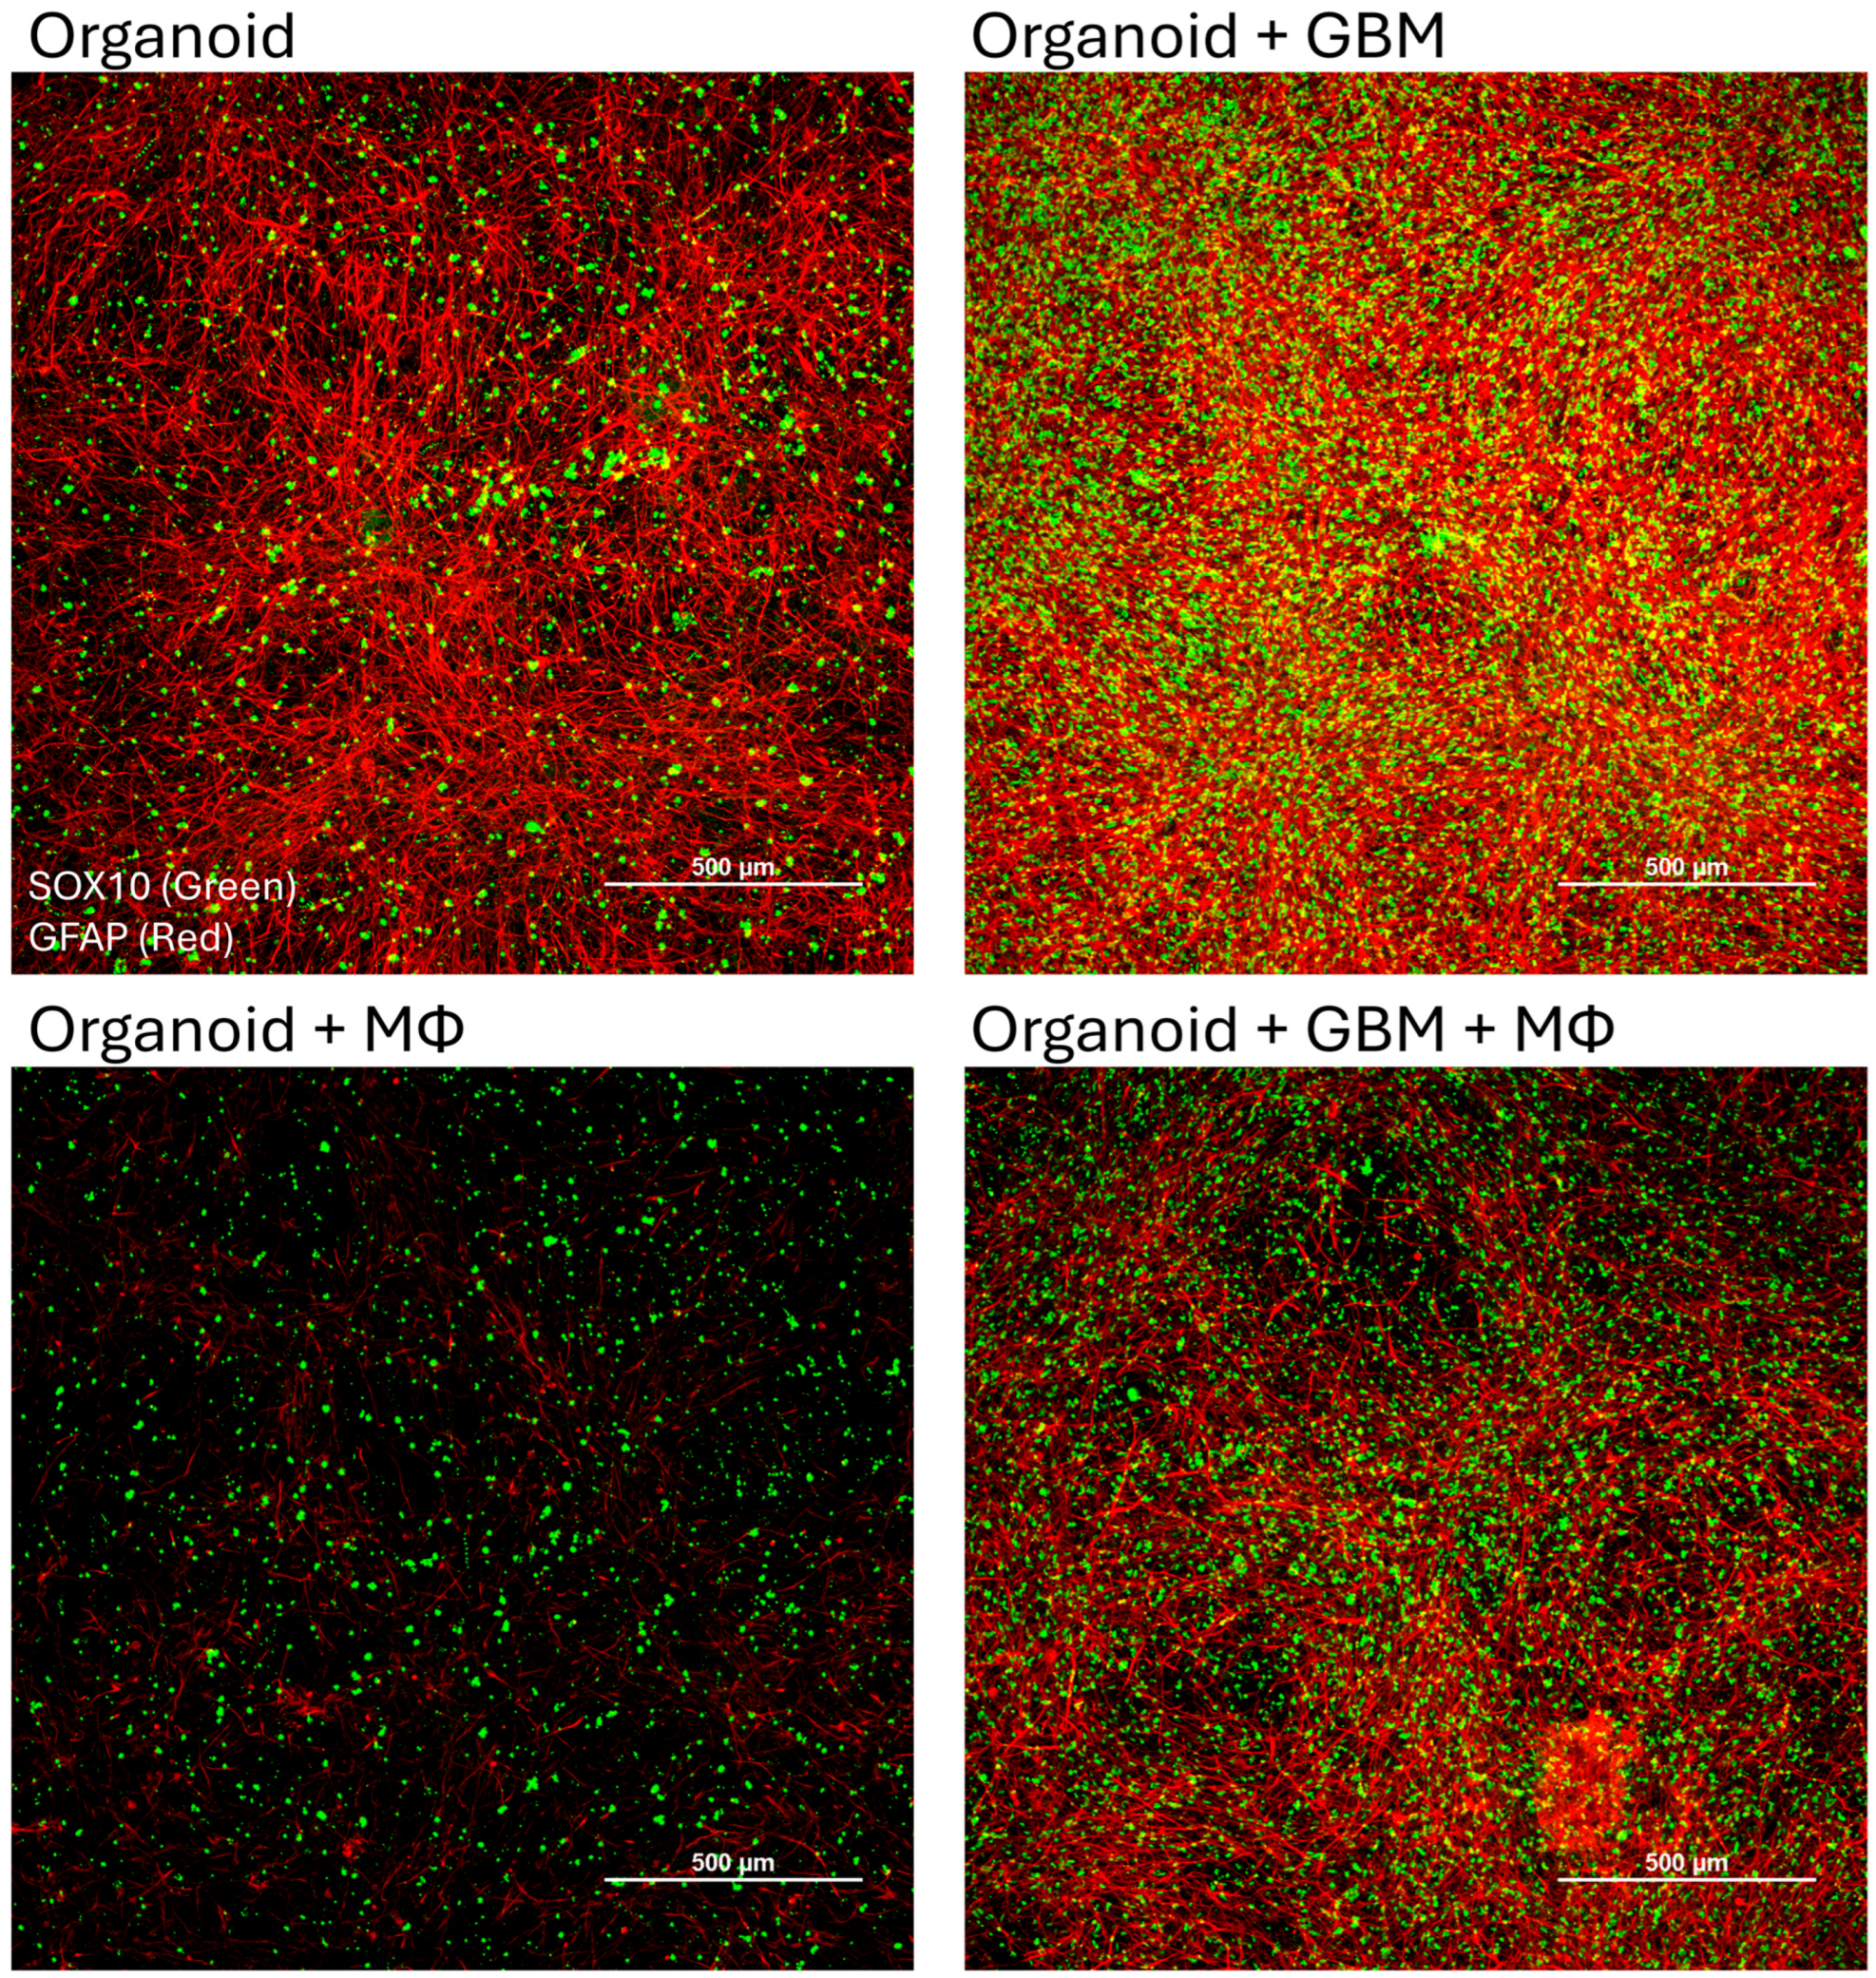
As proof of concept, based on transcriptional expression, organoids were stained using SOX10 to identify GBM cells and validate tumor cell integration while GFAP, which was found in relatively low abundance in the GBM cells (Supplementary Figure S2D), was used to stain astrocytes in the host organoid (Figure 7). The SOX10+ cells were diffuse and distributed throughout the organoid, consistent with the transcriptional and proteomic analysis. Control organoids without GBM cells also contained SOX10+ cells, indicating early development of native OPCs in the organoid model which we have previously detected via scRNAseq in D28 organoids [51]. Interestingly, GBM appeared to increase GFAP+ staining in the organoid while macrophages decreased staining. However, quantification was not performed, and additional future characterization via IF is required.

4. Discussion

GBM is an incurable malignant brain tumor with a 6% five-year survival rate that has remained largely unchanged for decades [52], underscoring the need for more effective treatments to enhance patient outcomes. Understanding the mechanism of infiltration and immunosuppression in the TME is essential in identifying the processes underlying treatment resistance and recurrence. Using scRNAseq, we identified and compared patient-derived GBM cells to iPSC-derived host organoid cells and found specific cellular alterations in the various cell populations in the GSCs versus the surrounding organoid populations. Gene set enrichment analysis (Figure 3) between the cell populations indicates increased NF-kB and IL6/JAK/STAT3 activation in the host organoid glial cells; both have been implicated in tumoral growth and invasiveness in the GBM TME [53,54]. The robust IFN response elicited in the glial cells of the organoid after the addition of the patient-derived GSCs is in line with the early-phase activation of anti-tumoral immunosurveillance by recognition of DNA, RNA, and damage-associated molecular patterns (DAMPs) [55], which is eventually downregulated in the hypoxic TME [56]. When analyzing immune cells together rather than by macrophages and microglia, we see decreased immune activation (Figure 3). However, when comparing the microglial groups alone, we see an upregulation in immune activation, suggesting that the macrophages are responsible for the downregulatory signal. Subclustering the immune cells (Figure 5) reveals that a cluster of chemotactic microglia (Immune Cluster 2) associated with IFN response and immunosuppressive IL-10 increase after macrophages are introduced into the system. In parallel, subclustering of the GBM population (Figure 4) shows that a dividing cell NPC- and OPC-like GSC population (GBM Cluster 2) increases in the presence of macrophages. This would suggest that the presence of macrophages, with or without GBM, shapes the immune response in a way that facilitates the stemness of GSCs. Similar findings have been reported in GBM organoids cocultured with peripheral blood mononuclear cells [23]. NPC-/OPC-like programs are associated with the infiltrating tumor, leading edge, and cellular tumor regions of glioblastoma [38]. In contrast, MES-/AC-like programs are enriched in the regions of the pseudopalisading cells around necrosis [38], which corresponds to GBM Cluster 1’s enrichment in glial and vascular transport, low cell division, and hypoxic stress [57]. These MES-like states are believed to have higher therapy resistance and to be involved in the reinitiation of tumor re-expansion [57]. However, it should be noted that the general expression of NPC- and OPC-like features in our GBM population was high, corroborating our sequencing results as well as recently published findings on the heightened NPC-/OPC-like cellular states relative to lower MES-like cells present in the glioblastoma cerebral organoid model (GLICO [58]), the human organoid tumor transplantation model (HOTT [22]) and patient peritumoral zones in GBM [39].
The shifts in the microglia population to a more immunosuppressive subtype (Cluster 2) in the presence of macrophages is intriguing. However, it should be noted that the presence of the GBM cells slightly decreased Cluster 2 while increasing IFN-signaling Cluster 5 monocytes. This immune response, as well as the high expression of infiltration-associated expression of NPC- and OPC-like features in our GBM population, suggests early anti-tumoral processes. In line with these observations, naïve microglia reduce the sphere-forming ability of human GSCs to suppress glioma growth, while microglia and macrophages cultured from glioma patients have lost this anti-tumorigenic potential [59]. In response, the GBM population shifts to a more NPC- and OPC-like progenitor state to increase infiltration and proliferation. Differences in the milieu between the cultures also suggest early anti-tumoral IFNα, as well as immune-recruiting IL-25, MCP-3, and MIP-1B, in addition to pro-tumoral PDGF-AA, VEGF, and LIF secretion. The comparison of the neuroimmune organoid secretome to monocultures and GBM + MΦ coculture experiments overlooks this multifaceted CNS glial signaling.
The pro- or anti-tumorigenic role of type I interferon signaling in GBM is complex. However, a number of studies suggest that the acute and robust type I IFN responses have beneficial outcomes while chronic and weak signaling is detrimental and may lead to therapy-resistant phenotypes (reviewed in [60,61]). In particular, IFN signaling participates in the inflammatory reprogramming of macrophages in the TME [61], and IFN-mediated crosstalk between myeloid cells and T cells has been implicated in PD-L1 therapy resistance [41]. Immune checkpoint blockade has revolutionized the cancer oncology field by blocking inhibitory signals of T cell activation. However, its utility in GBM has had minimal success due to the “immune-cold” or immunosuppressive microenvironment which hampers effective anti-tumor immune response [62]. Type I IFN production has been shown to be crucial in eliciting anti-tumor immune responses against GBM and increases the effectiveness of anti-PD1 treatment [41]. As type I IFN can be produced by virtually all nucleated cells and IFNAR is ubiquitously expressed on nearly all immune cells, investigation into this heterogenous cell signaling in the TME is complex and challenging to monitor over time. Longer experiments that allow for GBM hypoxic and necrotic core development would be necessary to facilitate the immunosuppressive macrophage phenotype that defines the GBM TME. It has been shown that microglia are enriched at the invasive edge while macrophages are enriched in core regions (reviewed in [63]). Seeding of a single GSC neurosphere instead of a GSC cell suspension, while increasing cell culture duration, would more effectively mimic the formation of a hypoxic tumor core environment and create conditions to further induce GSC mesenchymal transition [64] and prompt myeloid accumulation and enhanced immunosuppression in the TME [65,66]. Alternatively, using a different GBM cell donor that better exhibits the formation of large neurospheres, rather than diffuse infiltration, would also facilitate modeling this cell state [67]. Later resection or removal of the GBM neurosphere from the host organoid in combination with therapeutics could offer an accessible model of tumor recurrence and provide further insight into treatment strategies, such as increasing IFN signaling to enhance anti-PD1 treatment. Furthermore, as it is known that the MES-like transition is accomplished through gradients of cytokines [68], additional integration of TME-associated immune cells such as neutrophils and T-cells into the GBM organoid environment would further our understanding of how the TME develops and the effects of these cells on the myeloid populations.
Using neuroimmune organoid models to investigate GBM development offers a more human-relevant model of the TME with greater clinical translation and mirrors transcriptional and proteomic changes found in patient tissues [22,23,58,67]. Furthermore, drug screening in neuroimmune organoids has replicated heightened clinical resistance to chemotherapy and allows the assessment of therapeutics and radiotherapy on healthy surrounding tissue [67]. As the malignant cells in GBM exist in a limited set of cellular states, therapeutic development focused on these cell states will inform the design of more effective treatments. A major limitation of our study was the use of a single patient-derived GBM line. It has been shown that different patient-derived lines exhibit strikingly different phenotypes when cultured in organoids under the same conditions [67]. Further experiments using a wider variety of patient-derived cells are critical in replicating the heterogeneity of tumors that are clinically observed in GBM patients. Another limitation of our model is the incorporation of general endothelial cells rather than brain microvascular endothelial cells, which more accurately recapitulates the CNS-specific environment. Additionally, our study did not include direct functional validation (invasion assays, T cell-mediated cytotoxicity, etc.), and future studies incorporating functional immune and invasion assays would be necessary to establish causal mechanisms underlying the phenotypes. Finally, the number of GBM cells isolated in the scRNAseq was low (<3%; Figure 1C), relative to the rest of the organoid, limiting the number of identifiable cell clusters during analysis. Further optimization on the initial seeding number of GBM cells, longer coculturing times, and optimization of the scRNAseq harvesting method to allow for analysis of more incorporated GBM cells should be performed to enhance yields. In this study, we utilized GBM cells without strong specific cell state driver mutations that yielded high NPC- and OPC-like gene expression. This cell state has a key role in mediating the diffuse infiltrative nature of GBM [39,69], which is a major obstacle for complete surgical resection. However, the transition of these cells to a more mesenchymal cell state underlies the aggressive and treatment-resistant phenotype of recurring GBM. Further modeling, using GBM cells that contain CDK4, PDGFRA, EGFR or NF1 mutations that favor a particular cell state (NPC-like, OPC-like, AC-like, and MES-like) or combinations thereof, would provide insight into the dynamics of lineage switching and potential strategies to restrict cell state plasticity in GBM. Numerous studies have suggested that the MES-like cell state is characterized by high resistance to standard treatment and increased tumor recurrence, with a median survival time of 1.2 years [70]. Additionally, MES-like GBMs show the highest percentage of microglia, macrophage, and lymphocyte infiltration, which is also correlated with worse prognosis [71]. Pseudotime analyses have shown that MES-like cells appear later while NPC- and OPC-like cells are found earlier during disease progression [72]. Likewise, primary tumors are enriched with NPC-like and OPC-like cells, while immunotherapy-treated relapse tumors are enriched with MES-like tumor cells [72]. Similarly, it has been found that microglia are prominent in newly diagnosed GBM while macrophages prevail in recurrent GBM [73]. Further investigation into the interactions between the tumor and its microenvironment may provide greater insight into tumor biology and reveal new therapeutic strategies.
In conclusion, further study and comparison using these complex neuroimmune organoid models, particularly for GBM favoring the MES-like cell state, have the potential to provide valuable insight into mechanisms of tumor evasion, expansion, and recurrence. Inquiry into how these finite GBM cell states can be restricted or switched to a more favorable cell state could be leveraged for treatment. This avenue of GBM research promotes the development of personalized therapeutics targeting specific cell states and subtypes. Understanding the genetic and cellular mechanisms of the TME in the different GBM cell states over time is essential to the development and expansion of treatment options and the potential discovery of novel biomarkers associated with unfavorable cell state trajectories. As it stands, our OPC-/NPC-like GBM organoid model described herein can facilitate the discovery of compounds preventing tumor invasion. Focused development to recreate MES-like GBM organoids is necessary to enable therapeutic discovery targeting immunosuppression and tumor recurrence. Further model development and in-depth characterization in this area is critical in enhancing patient outcomes for this deadly condition.

5. Conclusions

  • Patient-derived GBM cells seeded into organoids exhibit infiltration and proliferation-related OPC- and NPC-like cell states corresponding to early tumor establishment.
  • Macrophage cells increase the actively proliferating GBM subpopulation within the neuroimmune organoid.
  • Both microglia and macrophages retain subpopulations of IFN-related cells, and the presence of macrophages increases IFN-related microglia and anti-inflammatory processes.
  • Neuroimmune organoids seeded with GBM cells and cultured for 7 days with or without macrophages demonstrate diffuse infiltration and early anti-tumoral processes corresponding to early primary tumor establishment.

Supplementary Materials

The following supporting information can be downloaded at https://www.mdpi.com/article/10.3390/organoids5030023/s1, Figure S1: Expression distribution of paternally expressed Gene-3 (PEG3) in the annotated cell population in the aggregated scRNAseq conditions; Figure S2: Expression distribution of GBM cell state associated gene markers for the annotated cell population in the aggregated scRNAseq conditions; Figure S3: Expression distribution of GBM cell state associated gene markers in the GBM cell population by condition (Organoid ± MΦ) and individual GBM clusters in the aggregated GBM scRNAseq conditions; Figure S4: Two-dimensional representation of cellular states from scRNAseq assigned to the six meta-modules defined by Neftel et al. 2019 [19]; Figure S5: UMAP representation of the immune cells (microglia and macrophage populations, n = 2217) from scRNAseq after quality control and batch correction showing the annotated cell populations in the subclustering; Figure S6: Expression distribution of SOX10 in the annotated cell population in the aggregated scRNAseq conditions; Figure S7: Gene Ontology enrichment analysis of differentially expressed genes in Organoid + GBM + Macrophage (GBM4) vs Organoid only control (GBM1); Figure S8: Copy number variation (CNV) inference supports malignant identity of the GBM-annotated cluster.

Author Contributions

Conceptualization, N.Y.Y., J.A.Z., M.D., and C.S.L.; methodology, N.Y.Y., W.D.R., K.T.P., K.G., J.S., L.Z., and C.S.L.; software, J.A.Z., K.T.P., and N.Y.Y.; validation, N.Y.Y., W.D.R., K.T.P., M.D., and C.S.L.; formal analysis, N.Y.Y., K.T.P., M.D., and C.S.L.; investigation, N.Y.Y., W.D.R., K.T.P., K.G., J.A.Z., J.S., L.Z., M.D., and C.S.L.; resources, M.D. and C.S.L.; data curation N.Y.Y., K.T.P., and C.S.L.; writing—original draft preparation, N.Y.Y.; writing—review and editing, N.Y.Y., W.D.R., K.T.P., J.S., L.Z., M.D., and C.S.L.; visualization, N.Y.Y. and K.T.P.; supervision, M.D. and C.S.L.; project administration, M.D. and C.S.L.; funding acquisition, M.D. and C.S.L. All authors have read and agreed to the published version of the manuscript.

Funding

This work has been supported by NIH SBIR and STTR grants R44ES029898 and R41CA281533.

Institutional Review Board Statement

De-identified patient-derived GBM cells were obtained, and patients consented under IRB 2019-1308, approved by the University of Wisconsin (approval date: 1 July 2020) and renewed yearly. Cells were maintained through serial passage of flank tumor xenografts in immunocompromised nude mice using protocols approved by the Office of Laboratory Animal Welfare of the University of Wisconsin–Madison (approval date: 21 October 2022; approval code: M006254-RO1).

Informed Consent Statement

The cells used for the generation of the organoids were from a commercial supplier that verified informed consent of the donor for research use. Consent is documented via hpscreg. Donor consent restrictions require that omics data can be made available only through a secure access-controlled database that restricts use to Research Use Only and explicitly prohibits re-identification of the donor or donor relatives. Patient-derived GBM cells were collected under IRB 2019-1308, approved by the University of Wisconsin with patient consent.

Data Availability Statement

Data are available upon request. scRNA-seq datasets generated and analyzed during the current study are not publicly available. As a privately held biotechnology company, the authors consider these datasets and associated metadata to contain proprietary information and trade secrets that support ongoing research and commercial development activities. Reasonable requests for access to specific data may be considered on a case-by-case basis, subject to evaluation of the scientific purpose, protection of confidential and proprietary information, and the execution of appropriate confidentiality and data use agreements. Donor consent restrictions require that omics data can be made available only through a secure access-controlled database that restricts use to Research Use Only and explicitly prohibits re-identification of the donor or donor relatives. Requests should be directed to the corresponding author.

Acknowledgments

We thank Steven Visuri and Ryan Gordon for their contributions in reviewing data and this manuscript. The authors utilized the University of Wisconsin–Madison Biotechnology Center Gene Expression Center (Research Resource Identifier—RRID:SCR_017757) and the Biotechnology Center DNA Sequencing Facility (Research Resource Identifier—RRID:SCR_017759 for scRNA-seq library prep and sequencing, and the University of Wisconsin–Madison Biotechnology Center Bioinformatics Core Facility (Research Resource Identifier—RRID:SCR_017799) for initial analysis of scRNA-seq data and data export. Confocal imaging was performed at the University of Wisconsin–Madison Optical-Imaging Core.

Conflicts of Interest

The authors declare the following financial interests/personal relationships which may be considered as potential competing interests: Nina Y. Yuan, William D. Richards, and Connie S. Lebakken are employees of Stem Pharm, Inc. and have stock options. Connie S. Lebakken is a stockholder of Stem Pharm.

Abbreviations

The following abbreviations are used in this manuscript:
GBMGlioblastoma
GSCGlioma stem cell
CNSCentral nervous system
D-PBSDulbecco’s phosphate-buffered saline
AISAntibody incubation solution
ECEndothelial cell
OPCOligodendrocyte precursor cell
ACAstrocyte
NPCNeural precursor cell
MESMesenchymal
TMETumor microenvironment
Macrophage
iPSCInduced pluripotent stem cell
MGMicroglia
DEGDifferentially expressed gene
IFNInterferon
IFImmunofluorescence
scRNAseqSingle-cell RNA sequencing

References

  1. Ostrom, Q.T.; Price, M.; Neff, C.; Cioffi, G.; Waite, K.A.; Kruchko, C.; Barnholtz-Sloan, J.S. CBTRUS Statistical Report: Primary Brain and Other Central Nervous System Tumors Diagnosed in the United States in 2015–2019. Neuro. Oncol. 2022, 24, v1–v95. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  2. Ostrom, Q.T.; Gittleman, H.; Farah, P.; Ondracek, A.; Chen, Y.; Wolinsky, Y.; Stroup, N.E.; Kruchko, C.; Barnholtz-Sloan, J.S. CBTRUS statistical report: Primary brain and central nervous system tumors diagnosed in the United States in 2006–2010. Neuro. Oncol. 2013, 15, ii1–ii56. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  3. Ostrom, Q.T.; Patil, N.; Cioffi, G.; Waite, K.; Kruchko, C.; Barnholtz-Sloan, J.S. CBTRUS Statistical Report: Primary Brain and Other Central Nervous System Tumors Diagnosed in the United States in 2013–2017. Neuro. Oncol. 2020, 22, iv1–iv96. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Price, M.; Ballard, C.A.P.; Benedetti, J.R.; Kruchko, C.; Barnholtz-Sloan, J.S.; Ostrom, Q.T. CBTRUS Statistical Report: Primary Brain and Other Central Nervous System Tumors Diagnosed in the United States in 2018–2022. Neuro. Oncol. 2025, 27, iv1–iv66. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Stupp, R.; Hegi, M.E.; Mason, W.P.; van den Bent, M.J.; Taphoorn, M.J.; Janzer, R.C.; Ludwin, S.K.; Allgeier, A.; Fisher, B.; Belanger, K.; et al. Effects of radiotherapy with concomitant and adjuvant temozolomide versus radiotherapy alone on survival in glioblastoma in a randomised phase III study: 5-year analysis of the EORTC-NCIC trial. Lancet Oncol. 2009, 10, 459–466. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. Sipos, D.; Raposa, B.L.; Freihat, O.; Simon, M.; Mekis, N.; Cornacchione, P.; Kovacs, A. Glioblastoma: Clinical Presentation, Multidisciplinary Management, and Long-Term Outcomes. Cancers 2025, 17, 146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Stupp, R.; Taillibert, S.; Kanner, A.; Read, W.; Steinberg, D.; Lhermitte, B.; Toms, S.; Idbaih, A.; Ahluwalia, M.S.; Fink, K.; et al. Effect of Tumor-Treating Fields Plus Maintenance Temozolomide vs Maintenance Temozolomide Alone on Survival in Patients with Glioblastoma: A Randomized Clinical Trial. JAMA 2017, 318, 2306–2316. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. De Silva, M.I.; Stringer, B.W.; Bardy, C. Neuronal and tumourigenic boundaries of glioblastoma plasticity. Trends Cancer 2023, 9, 223–236. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. McDonald, M.F.; Gopakumar, S.; Juratli, T.A.; Eyupoglu, I.Y.; Rao, G.; Mandel, J.J.; Jalali, A. Discontiguous recurrences of IDH-wildtype glioblastoma share a common origin with the initial tumor and are frequently hypermutated. Acta Neuropathol. Commun. 2025, 13, 9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  10. Weller, M.; van den Bent, M.; Preusser, M.; Le Rhun, E.; Tonn, J.C.; Minniti, G.; Bendszus, M.; Balana, C.; Chinot, O.; Dirven, L.; et al. EANO guidelines on the diagnosis and treatment of diffuse gliomas of adulthood. Nat. Rev. Clin. Oncol. 2021, 18, 170–186. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Vaz-Salgado, M.A.; Villamayor, M.; Albarran, V.; Alia, V.; Sotoca, P.; Chamorro, J.; Rosero, D.; Barrill, A.M.; Martin, M.; Fernandez, E.; et al. Recurrent Glioblastoma: A Review of the Treatment Options. Cancers 2023, 15, 4279. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. De Bonis, P.; Anile, C.; Pompucci, A.; Fiorentino, A.; Balducci, M.; Chiesa, S.; Lauriola, L.; Maira, G.; Mangiola, A. The influence of surgery on recurrence pattern of glioblastoma. Clin. Neurol. Neurosurg. 2013, 115, 37–43. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Ammirati, M.; Galicich, J.H.; Arbit, E.; Liao, Y. Reoperation in the treatment of recurrent intracranial malignant gliomas. Neurosurgery 1987, 21, 607–614. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Louis, D.N.; Perry, A.; Wesseling, P.; Brat, D.J.; Cree, I.A.; Figarella-Branger, D.; Hawkins, C.; Ng, H.K.; Pfister, S.M.; Reifenberger, G.; et al. The 2021 WHO Classification of Tumors of the Central Nervous System: A summary. Neuro. Oncol. 2021, 23, 1231–1251. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Poon, C.C.; Gordon, P.M.K.; Liu, K.; Yang, R.; Sarkar, S.; Mirzaei, R.; Ahmad, S.T.; Hughes, M.L.; Yong, V.W.; Kelly, J.J.P. Differential microglia and macrophage profiles in human IDH-mutant and -wild type glioblastoma. Oncotarget 2019, 10, 3129–3143. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Klemm, F.; Maas, R.R.; Bowman, R.L.; Kornete, M.; Soukup, K.; Nassiri, S.; Brouland, J.P.; Iacobuzio-Donahue, C.A.; Brennan, C.; Tabar, V.; et al. Interrogation of the Microenvironmental Landscape in Brain Tumors Reveals Disease-Specific Alterations of Immune Cells. Cell 2020, 181, 1643–1660.e17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Miller, T.E.; El Farran, C.A.; Couturier, C.P.; Chen, Z.; D’Antonio, J.P.; Verga, J.; Villanueva, M.A.; Gonzalez Castro, L.N.; Tong, Y.E.; Saadi, T.A.; et al. Programs, origins and immunomodulatory functions of myeloid cells in glioma. Nature 2025, 640, 1072–1082. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  18. Badie, B.; Schartner, J.M. Flow cytometric characterization of tumor-associated macrophages in experimental gliomas. Neurosurgery 2000, 46, 957–961; discussion 961–962. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Neftel, C.; Laffy, J.; Filbin, M.G.; Hara, T.; Shore, M.E.; Rahme, G.J.; Richman, A.R.; Silverbush, D.; Shaw, M.L.; Hebert, C.M.; et al. An Integrative Model of Cellular States, Plasticity, and Genetics for Glioblastoma. Cell 2019, 178, 835–849.e21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  20. Weth, F.R.; Peng, L.; Paterson, E.; Tan, S.T.; Gray, C. Utility of the Cerebral Organoid Glioma ‘GLICO’ Model for Screening Applications. Cells 2022, 12, 153. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. da Silva, B.; Mathew, R.K.; Polson, E.S.; Williams, J.; Wurdak, H. Spontaneous Glioblastoma Spheroid Infiltration of Early-Stage Cerebral Organoids Models Brain Tumor Invasion. SLAS Discov. 2018, 23, 862–868. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  22. Ge, W.; Kan, R.L.; Yilgor, C.; Fazzari, E.; Nano, P.R.; Azizad, D.J.; Shinglot, H.; Li, M.; Ito, J.Y.; Tse, C.; et al. Human organoid tumor transplantation identifies functional glioblastoma-microenvironment communication mediated by PTPRZ1. Cell Rep. 2026, 45, 116848. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Baisiwala, S.; Fazzari, E.; Li, M.X.; Martija, A.; Azizad, D.J.; Sun, L.; Herrera, G.; Phan, T.; Monteleone, A.; Kan, R.L.; et al. A human tumor-immune organoid model of glioblastoma. Cell Rep. 2026, 45, 116790. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Yuan, N.Y.; Richards, W.D.; Parham, K.T.; Clark, S.G.; Greuel, K.; Polzin, B.; Smith, S.W.; Lebakken, C.S. Neural organoids incorporating microglia to assess neuroinflammation and toxicities induced by known developmental neurotoxins. Curr. Res. Toxicol. 2025, 9, 100252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Shireman, J.M.; Atashi, F.; Lee, G.; Ali, E.S.; Saathoff, M.R.; Park, C.H.; Savchuk, S.; Baisiwala, S.; Miska, J.; Lesniak, M.S.; et al. De novo purine biosynthesis is a major driver of chemoresistance in glioblastoma. Brain 2021, 144, 1230–1246. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Carlson, B.L.; Pokorny, J.L.; Schroeder, M.A.; Sarkaria, J.N. Establishment, maintenance and in vitro and in vivo applications of primary human glioblastoma multiforme (GBM) xenograft models for translational biology studies and drug discovery. Curr. Protoc. Pharmacol. 2011, 52, 14.16.1–14.16.23. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Schwartz, M.P.; Hou, Z.; Propson, N.E.; Zhang, J.; Engstrom, C.J.; Santos Costa, V.; Jiang, P.; Nguyen, B.K.; Bolin, J.M.; Daly, W.; et al. Human pluripotent stem cell-derived neural constructs for predicting neural toxicity. Proc. Natl. Acad. Sci. USA 2015, 112, 12516–12521. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  28. Majumder, J.; Torr, E.E.; Aisenbrey, E.A.; Lebakken, C.S.; Favreau, P.F.; Richards, W.D.; Yin, Y.; Chang, Q.; Murphy, W.L. Human induced pluripotent stem cell-derived planar neural organoids assembled on synthetic hydrogels. J. Tissue Eng. 2024, 15, 20417314241230633. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Hao, Y.; Stuart, T.; Kowalski, M.H.; Choudhary, S.; Hoffman, P.; Hartman, A.; Srivastava, A.; Molla, G.; Madad, S.; Fernandez-Granda, C.; et al. Dictionary learning for integrative, multimodal and scalable single-cell analysis. Nat. Biotechnol. 2024, 42, 293–304. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  30. Xu, S.; Hu, E.; Cai, Y.; Xie, Z.; Luo, X.; Zhan, L.; Tang, W.; Wang, Q.; Liu, B.; Wang, R.; et al. Using clusterProfiler to characterize multiomics data. Nat. Protoc. 2024, 19, 3292–3320. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  31. Subramanian, A.; Tamayo, P.; Mootha, V.K.; Mukherjee, S.; Ebert, B.L.; Gillette, M.A.; Paulovich, A.; Pomeroy, S.L.; Golub, T.R.; Lander, E.S.; et al. Gene set enrichment analysis: A knowledge-based approach for interpreting genome-wide expression profiles. Proc. Natl. Acad. Sci. USA 2005, 102, 15545–15550. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  32. Chicco, D.; Agapito, G. Nine quick tips for pathway enrichment analysis. PLoS Comput. Biol. 2022, 18, e1010348. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  33. Takikawa, S.; Ray, C.; Wang, X.; Shamis, Y.; Wu, T.Y.; Li, X. Genomic imprinting is variably lost during reprogramming of mouse iPS cells. Stem Cell Res. 2013, 11, 861–873. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  34. Theka, I.; Sottile, F.; Aulicino, F.; Garcia, A.C.; Cosma, M.P. Reduced expression of Paternally Expressed Gene-3 enhances somatic cell reprogramming through mitochondrial activity perturbation. Sci. Rep. 2017, 7, 9705. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Nomura, M.; Spitzer, A.; Johnson, K.C.; Garofano, L.; Nehar-Belaid, D.; Galili Darnell, N.; Greenwald, A.C.; Bussema, L.; Oh, Y.T.; Varn, F.S.; et al. The multilayered transcriptional architecture of glioblastoma ecosystems. Nat. Genet. 2025, 57, 1155–1167. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  36. Yuile, A.; Satgunaseelan, L.; Wei, J.Q.; Rodriguez, M.; Back, M.; Pavlakis, N.; Hudson, A.; Kastelan, M.; Wheeler, H.R.; Lee, A. CDKN2A/B Homozygous Deletions in Astrocytomas: A Literature Review. Curr. Issues Mol. Biol. 2023, 45, 5276–5292. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  37. Tian, Y.; Wang, Z.; Sun, M.; Li, J.; Zheng, W.; Yang, F.; Zhang, Z. Olig1/2 Drive Astrocytic Glioblastoma Proliferation Through Transcriptional Co-Regulation of Various Cyclins. Genes 2025, 16, 573. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  38. Eberhart, C.G.; Bar, E.E. Spatial enrichment of cellular states in glioblastoma. Acta Neuropathol. 2020, 140, 85–87. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  39. Wu, Y.; Wu, B.Z.; Ellenbogen, Y.; Kant, J.B.Y.; Yu, P.; Li, X.; Caloren, L.; Sotov, V.; Tran, C.; Restrepo, M.; et al. Neurodevelopmental hijacking of oligodendrocyte lineage programs drives glioblastoma infiltration. Dev. Cell 2025, 60, 2420–2433.e12. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  40. Li, J.; Xu, Y.; Zhu, H.; Wang, Y.; Li, P.; Wang, D. The dark side of synaptic proteins in tumours. Br. J. Cancer 2022, 127, 1184–1192. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  41. Lim, J.; La, J.; Kim, H.C.; Kang, I.; Kang, B.H.; Ku, K.B.; Kim, Y.; Kwon, M.S.; Lee, H.K. Type I interferon signaling regulates myeloid and T cell crosstalk in the glioblastoma tumor microenvironment. iScience 2024, 27, 110810. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  42. Guvenek, A.; Parikshak, N.; Zamolodchikov, D.; Gelfman, S.; Moscati, A.; Dobbyn, L.; Stahl, E.; Shuldiner, A.; Coppola, G. Transcriptional profiling in microglia across physiological and pathological states identifies a transcriptional module associated with neurodegeneration. Commun. Biol. 2024, 7, 1168. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  43. Patel, T.; Carnwath, T.P.; Wang, X.; Allen, M.; Lincoln, S.J.; Lewis-Tuffin, L.J.; Quicksall, Z.S.; Lin, S.; Tutor-New, F.Q.; Ho, C.C.G.; et al. Transcriptional landscape of human microglia implicates age, sex, and APOE-related immunometabolic pathway perturbations. Aging Cell 2022, 21, e13606. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  44. Khan, S.; Mahalingam, R.; Sen, S.; Martinez-Ledesma, E.; Khan, A.; Gandy, K.; Lang, F.F.; Sulman, E.P.; Alfaro-Munoz, K.D.; Majd, N.K.; et al. Intrinsic Interferon Signaling Regulates the Cell Death and Mesenchymal Phenotype of Glioblastoma Stem Cells. Cancers 2021, 13, 5284. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  45. Han, X.; Ye, J.; Huang, R.; Li, Y.; Liu, J.; Meng, T.; Song, D. Pan-cancer analysis reveals interleukin-17 family members as biomarkers in the prediction for immune checkpoint inhibitor curative effect. Front. Immunol. 2022, 13, 900273. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  46. Okada, M.; Saio, M.; Kito, Y.; Ohe, N.; Yano, H.; Yoshimura, S.; Iwama, T.; Takami, T. Tumor-associated macrophage/microglia infiltration in human gliomas is correlated with MCP-3, but not MCP-1. Int. J. Oncol. 2009, 34, 1621–1627. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  47. Lyu, T.J.; Wang, J.; Zhao, F.; Sun, K.; Zhao, Z.; Tian, R.; Guo, Z.; Wang, H.; Zhao, X.; Ma, W.; et al. CCL4 as a potential serum factor in differential diagnosis of central nervous system inflammatory diseases and gliomas. Front. Immunol. 2024, 15, 1461450. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  48. Zhang, X.; Li, X.; Cui, R.; Yu, X.; Zhang, Z.; Luo, Z.; Chen, G.; Lin, S. Disrupting PDGFRA-driven immune evasion in glioma: Vaccine-based strategies on the horizon. Front. Oncol. 2026, 16, 1666612. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  49. Xie, H.; Jiang, Y.; Xiang, Y.; Wu, B.; Zhao, J.; Huang, R.; Wang, M.; Wang, Y.; Liu, J.; Wu, D.; et al. Super-enhancer-driven LIF promotes the mesenchymal transition in glioblastoma by activating ITGB2 signaling feedback in microglia. Neuro. Oncol. 2024, 26, 1438–1452. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  50. Bao, S.; Wu, Q.; Sathornsumetee, S.; Hao, Y.; Li, Z.; Hjelmeland, A.B.; Shi, Q.; McLendon, R.E.; Bigner, D.D.; Rich, J.N. Stem cell-like glioma cells promote tumor angiogenesis through vascular endothelial growth factor. Cancer Res. 2006, 66, 7843–7848. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  51. Yuan, N.Y.; Richards, W.D.; Parham, K.T.; Clark, S.G.; Greuel, K.; Polzin, B.; Smith, S.W.; Lebakken, C.S. Stimulus-Based ApoE Alzheimer’s Disease Induction Model Using Microglia-Containing Brain Organoids for Drug Discovery. Cells 2026, 15, 1266. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  52. Tan, A.C.; Ashley, D.M.; Lopez, G.Y.; Malinzak, M.; Friedman, H.S.; Khasraw, M. Management of glioblastoma: State of the art and future directions. CA Cancer J. Clin. 2020, 70, 299–312. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  53. Ramar, V.; Guo, S.; Wang, G.; Liu, M. The Pivotal Role of NF-kappaB in Glioblastoma: Mechanisms of Activation and Therapeutic Implications. Int. J. Mol. Sci. 2025, 26, 7883. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  54. Fu, W.; Hou, X.; Dong, L.; Hou, W. Roles of STAT3 in the pathogenesis and treatment of glioblastoma. Front. Cell Dev. Biol. 2023, 11, 1098482. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  55. Lim, J.; Kang, I.; La, J.; Ku, K.B.; Kang, B.H.; Kim, Y.; Park, W.H.; Lee, H.K. Harnessing type I interferon-mediated immunity to target malignant brain tumors. Front. Immunol. 2023, 14, 1203929. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  56. Miar, A.; Arnaiz, E.; Bridges, E.; Beedie, S.; Cribbs, A.P.; Downes, D.J.; Beagrie, R.A.; Rehwinkel, J.; Harris, A.L. Hypoxia Induces Transcriptional and Translational Downregulation of the Type I IFN Pathway in Multiple Cancer Cell Types. Cancer Res. 2020, 80, 5245–5256. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  57. Tejero, R.; Huang, Y.; Katsyv, I.; Kluge, M.; Lin, J.Y.; Tome-Garcia, J.; Daviaud, N.; Wang, Y.; Zhang, B.; Tsankova, N.M.; et al. Gene signatures of quiescent glioblastoma cells reveal mesenchymal shift and interactions with niche microenvironment. EBioMedicine 2019, 42, 252–269. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  58. Pine, A.R.; Cirigliano, S.M.; Nicholson, J.G.; Hu, Y.; Linkous, A.; Miyaguchi, K.; Edwards, L.; Singhania, R.; Schwartz, T.H.; Ramakrishna, R.; et al. Tumor Microenvironment Is Critical for the Maintenance of Cellular States Found in Primary Glioblastomas. Cancer Discov. 2020, 10, 964–979. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  59. Sarkar, S.; Doring, A.; Zemp, F.J.; Silva, C.; Lun, X.; Wang, X.; Kelly, J.; Hader, W.; Hamilton, M.; Mercier, P.; et al. Therapeutic activation of macrophages and microglia to suppress brain tumor-initiating cells. Nat. Neurosci. 2014, 17, 46–55. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  60. Ruiz-Iglesias, A.; Guilbaud, E.; Galluzzi, L.; Manes, S. Context-dependent impact of type I interferon signaling in cancer. Mol. Cancer 2025, 24, 275. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  61. Chadwick, T.B.; So, J.; Hertzog, P.J.; Haynes, N.M.; Parker, B.S. Striking the right balance with type I interferon signalling in cancer. Nat. Rev. Cancer 2026, 26, 391–414. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  62. Zoi, V.; Galani, V.; Sioka, C.; Alexiou, G.A.; Kyritsis, A.P. Immunotherapy for Glioblastoma: A Focus on PD-1/PD-L1 Inhibitors. Cancers 2025, 17, 3777. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  63. Cheng, Y.; Zhao, W.; Xie, M.; Zheng, X.; Ding, F.; Du, J. Decoding myeloid heterogeneity in glioblastoma: Spatial insights from transcriptomics. J. Transl. Med. 2026, 24, 432. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  64. Joseph, J.V.; Conroy, S.; Pavlov, K.; Sontakke, P.; Tomar, T.; Eggens-Meijer, E.; Balasubramaniyan, V.; Wagemakers, M.; den Dunnen, W.F.; Kruyt, F.A. Hypoxia enhances migration and invasion in glioblastoma by promoting a mesenchymal shift mediated by the HIF1alpha-ZEB1 axis. Cancer Lett. 2015, 359, 107–116. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  65. Rahimi Koshkaki, H.; Minasi, S.; Ugolini, A.; Trevisi, G.; Napoletano, C.; Zizzari, I.G.; Gessi, M.; Giangaspero, F.; Mangiola, A.; Nuti, M.; et al. Immunohistochemical Characterization of Immune Infiltrate in Tumor Microenvironment of Glioblastoma. J. Pers. Med. 2020, 10, 112. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  66. Chen, Z.; Feng, X.; Herting, C.J.; Garcia, V.A.; Nie, K.; Pong, W.W.; Rasmussen, R.; Dwivedi, B.; Seby, S.; Wolf, S.A.; et al. Cellular and Molecular Identity of Tumor-Associated Macrophages in Glioblastoma. Cancer Res. 2017, 77, 2266–2278. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  67. Linkous, A.; Balamatsias, D.; Snuderl, M.; Edwards, L.; Miyaguchi, K.; Milner, T.; Reich, B.; Cohen-Gould, L.; Storaska, A.; Nakayama, Y.; et al. Modeling Patient-Derived Glioblastoma with Cerebral Organoids. Cell Rep. 2019, 26, 3203–3211.e5. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  68. Liu, F.; Chen, J.; Yu, M.; Liu, Y.; Wang, W.; Pei, Y.; Yang, S.; Yu, W. Targeting immune microenvironment-mediated mesenchymal transition in glioblastoma: Molecular mechanisms and translational strategies. Neurooncol. Adv. 2026, 8, vdag075. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  69. Garcia-Diaz, C.; Poysti, A.; Mereu, E.; Clements, M.P.; Brooks, L.J.; Galvez-Cancino, F.; Castillo, S.P.; Tang, W.; Beattie, G.; Courtot, L.; et al. Glioblastoma cell fate is differentially regulated by the microenvironments of the tumor bulk and infiltrative margin. Cell Rep. 2023, 42, 112472. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  70. Yoon, S.J.; Shim, J.K.; Chang, J.H.; Moon, J.H.; Roh, T.H.; Sung, K.S.; Lee, J.H.; Kim, E.H.; Kim, S.H.; Hong, Y.K.; et al. Tumor Mesenchymal Stem-Like Cell as a Prognostic Marker in Primary Glioblastoma. Stem Cells Int. 2016, 2016, 6756983. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  71. Martinez-Lage, M.; Lynch, T.M.; Bi, Y.; Cocito, C.; Way, G.P.; Pal, S.; Haller, J.; Yan, R.E.; Ziober, A.; Nguyen, A.; et al. Immune landscapes associated with different glioblastoma molecular subtypes. Acta Neuropathol. Commun. 2019, 7, 203. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  72. Hendriksen, J.D.; Locallo, A.; Maarup, S.; Debnath, O.; Ishaque, N.; Hasselbach, B.; Skjoth-Rasmussen, J.; Yde, C.W.; Poulsen, H.S.; Lassen, U.; et al. Immunotherapy drives mesenchymal tumor cell state shift and TME immune response in glioblastoma patients. Neuro. Oncol. 2024, 26, 1453–1466. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  73. Ismailov, A.; Spallone, A.; Belogurov, A., Jr.; Herbert, A.; Poptsova, M. Molecular biology of the deadliest cancer—Glioblastoma: What do we know? Front. Immunol. 2025, 16, 1530305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Figure 1. ScRNAseq data of neuroimmune organoid builds constructed with or without GBM and/or macrophages demonstrate that GBM cells exhibit gene expression distinct from other cell types and splits into two separate groups most closely clustering to the dividing and radial glia cell populations. (AD) Mapping of scRNAseq data from Stem Pharm’s neuroinflammatory organoid model (day 29) illustrates distinct CNS-type cell types. (A) Annotated UMAP representation of all cells (n = 24,602) from scRNAseq after quality control and batch correction. Organoids from a total of four conditions were sequenced: control Organoid, Organoid + GBM, Organoid + Mϕ, and Organoid + GBM + Mϕ. GBM and/or macrophages were added on day 22 and cultured for seven days before processing. Cells are colored by cell type annotation. Assigned cell types are annotated by distinguishing genes as follows: astrocytes (AQP4), excitatory (BDNF, SLC17A6, and TLX3), inhibitory (SLC32A1, DLX5, and GAD1), immature inhibitory (LDX5), radial glia (GBX2), dividing cells (MKI67), vascular-related (DCN and COL5A3), microglia (C1QA and CX3CR1), macrophages (CHIT1), and GBM (PMP2 and CDKN2C). (B) UMAPs separated by experimental condition. (C) Relative distribution of cell types detected in the organoid and annotated by scRNAseq. Values shown are percentages of the total amount of cells analyzed per condition. (D) Top 10 significant DEGs per annotated cell population, visualized in a heatmap colored by Log2 fold change.
Organoids 05 00023 g001
Figure 2. Transcriptomic pathway analysis between organoids containing GBM shows NPC-like, AC-like, and OPC-like traits relative to the other cell populations. Pathway analysis by Gene Ontology enrichment of significantly modulated gene transcriptional changes in annotated scRNAseq data. Organoids (day 29) in the (A) Organoid + GBM (n = 4674 cells) and the (B) Organoid + GBM + Mϕ (n = 7124 cells) conditions show expression of the different cell types relative to other cell types in each condition. Representative subset of significantly modulated pathways (p ≤ 0.05) altered by conditions, visualized in a heatmap colored by Log10 p-value (value inset) between the other cell populations in the analyzed condition; only statistically significant (≥1.3) Log10 p-values are colored, and those that did not reach statistical significance are indicated with an X.
Organoids 05 00023 g002
Figure 3. Transcriptomic pathway analysis between the organoids containing GBM and/or Mϕ shows microglia-specific immune upregulation but an overall immune downregulation in the presence of macrophages. Pathway analysis by Gene Ontology enrichment of significantly modulated gene transcriptional changes in the annotated scRNAseq data. Organoids (day 29) in the Organoid + GBM (n = 4674 cells), Organoid + Mϕ (n = 7664 cells), and the Organoid + GBM + Mϕ (n = 7124 cells) conditions show expression of the different cell types relative to respective cell types in the control Organoid condition. Representative subset of significantly modulated pathways (p ≤ 0.05) altered by conditions, visualized in a heatmap colored by Log10 p-value (value inset) between the other cell populations in the analyzed condition; only statistically significant (≥1.3) Log10 p-values are colored, and those that did not reach statistical significance are indicated with an X.
Organoids 05 00023 g003
Figure 4. GBM cells cluster into four distinct groupings and exhibit differential pathway enrichment, which demonstrates that the addition of macrophages in the GBM-containing organoids increases the relative cell population of cell cycle-related Cluster 2 GBM. (A) UMAP representation of the GBM cells (n = 344 cells) from scRNAseq after quality control and batch correction reveals four clusters. (B) UMAP representation of the GBM cells separated by experimental condition. (C) Relative distribution of cluster types detected in the GBM-containing organoid conditions. Values shown are percentages of the total amount of cells analyzed per condition. (D) Top 25 significant DEGs per GBM cell cluster compared between themselves and visualized in a heatmap colored by Log2 fold change. (E) Pathway analysis by Gene Ontology enrichment of significantly modulated gene transcriptional changes in the GBM of the scRNAseq dataset between the four clusters. Representative subset of significantly modulated pathways (p ≤ 0.05), visualized in a heatmap colored by Log10 p-value (value inset) between the analyzed clusters; only statistically significant (≥1.3) Log10 p-values are colored, and those that did not reach statistical significance are indicated with an X.
Organoids 05 00023 g004
Figure 5. Immune cells cluster into six distinct groupings and exhibit differential pathway enrichment, which demonstrates that IFN- and lipid-related macrophages reduce phagocytic and surveilling Cluster 4 microglia while increasing immunosuppressive Cluster 2 microglia. (A) UMAP representation of the immune cells (microglia and macrophage populations, n = 2217) from scRNAseq after quality control and batch correction. (B) UMAP representation of the immune cells separated by experimental condition. (C) Relative distribution of cluster types detected in the organoid conditions. Values shown are percentages of the total amount of cells analyzed per condition. (D) Top 15 significant DEGs per GBM cell cluster compared between themselves and visualized in a heatmap colored by Log2 fold change. (E) Pathway analysis by Gene Ontology enrichment of significantly modulated gene transcriptional changes in the immune cells of the scRNAseq data between the six clusters. Representative subset of significantly modulated pathways, (p ≤ 0.05), visualized in a heatmap colored by Log10 p-value (value inset) between the analyzed clusters; only statistically significant (≥1.3) Log10 p-values are colored, and those that did not reach statistical significance are indicated with an X.
Organoids 05 00023 g005
Figure 6. Multiplex organoid supernatant analysis reveals differential secreted proteins dependent on the presence of the host neuroimmune organoid. The human cytokine multiplex array was performed using a Luminex panel. For visualization, measurements were normalized to the highest value across all conditions (A) as well as in the organoid-only conditions (B). Measurements below the limit of detection were entered as zero; n = 3 per condition.
Organoids 05 00023 g006
Figure 7. Representative staining of patient-derived GBM cells stained using SOX10. Organoids were stained using GFAP (red) and SOX10 (green) antibodies to visualize native organoid astrocytes and patient-derived GBM cells. Proof of concept staining; n = 1 per condition; quantification was not performed. Images shown are maximum-intensity projections of 10× magnification on a confocal microscope; scale bar = 500 µm.
Organoids 05 00023 g007
Table 1. ScRNAseq sample sets and conditions. Identity of the sample condition with relevant statistics. Average RNA transcripts sequenced per cell and average number of genes detected per cell were calculated and extracted using Seurat.
NameIdentityAve Transcripts Sequenced/CellAve Genes/Cell
GBM1Organoid28,0666533
GBM2Organoid + GBM33,0936982
GBM3Organoid + Mϕ40,1617398
GBM4Organoid + GBM + Mϕ 39,8837424
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.