


Abstract
Background/Objectives: A complex karyotype (CK) in acute myeloid leukemia (AML) and myelodysplastic syndromes (MDSs) is defined as the presence of three or more unrelated chromosomal abnormalities in the absence of defining core-binding factor translocations. Losses/Deletions on chromosomes 5, 7 and 17 are frequently observed. It is heavily associated with TP53 mutations, with 70–80% of CK cases in MDS/AML harboring TP53 mutations. Methods: An extensive literature search of the studies carried out in the last two decades has shown a consistent development of experimental and clinical studies aiming to characterize the biological properties and clinical features of AML and MDS bearing CK and TP53 mutations. Results: These studies have greatly contributed to identifying as separate entities AML and MDS bearing CK and or TP53 alterations. Particularly, the improvement in the methods of detection of chromosome aberrations has contributed to defining the specific nature of the various chromosome abnormalities and to deciphering the mechanisms of catastrophic events leading to gene rearrangements. Two types of CK were identified in AML and MDS, one more frequently associated with TP53 mutations (with poor prognosis) and another less frequently without TP53 mutations (with relatively better prognosis). Conclusions: The treatment of AML and MDS with CK and/or TP53 mutations alterations remains extremely challenging, and the prognosis of these patients is dismal. The main aim of the various induction treatments explored in these patients is to bridge patients to allo-HSCT, the only therapeutic approach able to improve the survival of at least a part of these patients.
1. Introduction
Conventional cytogenetic analysis is fundamental in the diagnosis and/or prognosis of many hematological malignancies, including myelodysplastic syndrome (MDS), acute myeloid leukemia (AML), chronic lymphocytic leukemia (CLL), chronic myeloid leukemia (CML) and multiple myeloma (MM). Cytogenetic abnormalities of leukemias involve acquired chromosome changes, such as translocations (balanced and unbalanced), deletions, gains, duplications and inversions; these abnormalities are frequently observed and are different in the various leukemias. Deletions and gains may involve a part of a chromosome or a whole chromosome.
Complex karyotype (CK) is a cytogenetic classification in hematologic malignancies defined by the presence of three or more (sometimes ≥ 5) independent chromosome abnormalities (structural or numerical) in a single clone [1]. It is a marker of poor prognosis, indicating high genetic instability and resistance to therapy in some hematologic malignancies, including myelodysplastic syndromes (MDSs), acute myeloid leukemia (AML), acute lymphoid leukemia (ALL) and chronic lymphocytic leukemia (CLL). CK is strongly associated with TP53 gene alterations, thus explaining the aggressive clinical phenotype and the poor response to current treatments [1]. Some classifications distinguish two types of CK: CK1, containing balanced translocations/deletions; and CK2 containing only unbalanced chromosome aberrations, like structural imbalances, ring chromosomes and marker chromosomes. Cases of CK2 are associated with a higher genetic instability than CK1.
The definition of CK may change for the various hematological diseases; thus, while CK in MDS, AML, CLL and MM has been generally classified as based on the presence of ≥3 chromosome abnormalities, the definition of CK in B-ALL is based on the presence of ≥5 chromosome abnormalities.
CK in MDS and AML is defined by three or more unrelated chromosome abnormalities and is strongly associated with poor prognosis and high treatment resistance. Occurring in 10–15% of AML and 10–30% of MDS cases, CK is frequently accompanied by TP53 mutations (50–80% of cases). Frequent unbalanced chromosomal abnormalities observed in MDS and AML CK are represented by deletions of chromosomes 5 or 7 or 17, del(5q), del(7q), del(17p). CK is frequently observed in therapy-related myeloid neoplasms.
Typical features of CK-MDS and CK-AML are represented by their higher frequency in therapy-related MDS and AML compared with de novo MDS and AML and by their strong association with TP53 mutations (TP53 mutations, deletions or loss of heterozygosity) and with monosomal karyotype (MK, defined as the presence of two autosomal monosomies or of a single monosomy associated with at least one structural alteration) [1]. CK-AML cases are less frequent in pediatric patients (3–5%), and their frequency sharply increases with age, reaching a frequency of 20% and more in elderly AML patients over the age of 60.
The aim of this study is to provide an overview of recent progresses made in the characterization of CK and TP53 alterations in MDS and AML. Studies carried out in the last two decades have consistently contributed to better defining MDS and AML with CK and TP53 alterations as a separate entity with peculiar biological and clinical features.
2. Methodologies Used for the Detection of Chromosomal Aberrations
Detecting chromosome abnormalities in MDS and AML is critical for accurate diagnosis, disease classification and prognostic risk stratification. Several methodologies are routinely used in clinical laboratories ranging from traditional microscopy to advanced genomic mapping. (Table 1).
Table 1.
Main techniques used for the detection and characterization of chromosomal abnormalities in MDS and AML.
The gold standard of conventional cytogenetics is based on karyotyping. This technique evaluates bone marrow cells arrested in metaphase under a microscope to identify the main numerical (trisomies or monosomies) or structural (translocations, deletions, inversions) features. The advantage of this technique consists in providing a comprehensive, genome-wide view of chromosome health in a single test; its main limitations are that it requires dividing cells and can miss subtle, sub-microscopic cryptic aberrations due to resolution limits [2,3].
Fluorescence in situ hybridization (FISH) is a targeted method that uses fluorescently labeled DNA probes to bind to specific chromosomal regions of specific interest. The main advantage of this technique is that is highly sensitive, fast and does not require actively dividing cells and can be performed in interphase cells; its main limitations are that it detects only one single chromosomal abnormality dependent on the DNA probe used and cannot scan the whole genome for unknown or rare abnormalities.
Chromosome microarray analysis (CMA) is based on two techniques such as array-CGH (comparative genomic hybridization) and SNP array (single nucleotide polymorphism) that analyze DNA to detect copy number variations (gains or losses). The advantage of these techniques is that they offer markedly more resolution than standard karyotyping and can detect abnormalities such as “uniparental disomy” (UDP, when patients inherit two copies of a chromosome from one parent but none from the other); their main limitation is that they cannot reliably identify balanced translocations, where genetic material is rearranged without any loss or gain [2,3].
Optical genome mapping (OGM) is a next generation cytogenomic technology that detects structural and copy number variants across the entire genome in a single assay. In hematological malignancies, it provides a significantly higher resolution than traditional karyotyping, revealing cryptic fusions, complex chromosomal events and abnormalities missed by traditional karyotyping or fluorescence in situ hybridization (FISH) [4]. OGM allows the detection of all major classes of structural variants including translocations and inversions, deletions and duplications and ploidy changes [4]. A limitation of OGM is related to the requirement of a DNA fragment length longer than that obtained using routine molecular testing such as sequencing; therefore, most archival DNA specimens are not amenable to OGM [5].
Next generation sequencing (NGS) is primarily used to detect gene mutations but can be combined with bioinformatics tools to infer copy number alterations and structural abnormalities across target genes. The main advantages of sequencing-based technologies over conventional cytogenetic methods consist of higher resolution and general wide detection of chromosomal aberrations, with improved sensitivity that can detect mutations or alterations that are present in only 1% of the cells; the main limitations are represented by the high cost and the complex requirements for bioinformatic analysis.
3. Classification of AML and MDS with TP53 Alterations and CK
Mutated TP53 has been incorporated into both International Consensus Classification (ICC) and World Health Organization (WHO) classifications for AML and MDS due to its association with poor prognosis. ICC defined: (i) AML with mutated TP53 as those with >20% of blasts and TP53 mutation with VAF > 10%; (ii) MDS with mutated TP53 as multi-hit TP53 or TP53 mutation with VAF > 10% plus complex karyotype; and (iii) MDS/AML with mutated TP53 as those with 10–19% blasts and TP53 mutation > 10% [6]. The WHO 5th edition defined MDS with biallelic TP53 mutation as those with <20% blasts with two or more TP53 mutations, or one mutation plus TP53 copy number loss or copy-neutral loss of heterozygosity (cnLOH) [7]. (Figure 1).
Figure 1.
Different criteria adopted by the International Consensus Classification, WHO 5th Edition, and harmonized classification for the classification of mTP53-mutated myeloid neoplasms.
Thus, great differences exist between these two classification systems. AML with mutated TP53 is recognized as a distinct sub-entity by the ICC, but not by the WHO-5. Both ICC and WHO-5 consider the poor outcomes associated with multi-hit TP53-mutant and have excluded single-hit TP53-mutant MDS. However, a different cut-off is proposed by the two classification systems for multi-hit MDS: in the WHO-5, MDS with biallelic inactivation is considered a single entity irrespective of blast percentages, whereas cases with monoallelic TP53 inactivation in MDS (BM blasts < 20%) are completely excluded from this category. However, in the ICC, TP53-mutant MDS/AML (BM or PD blasts 10–19%) are included irrespective of hit status, whereas only multi-hit TP53-mutant MDS (BM or PB blasts 0–9%) are included in TP53-mutant myeloid neoplasms. Furthermore, the ICC differs from WHO-5 in the inclusion of additional criteria, such as the VAF threshold of TP53 mutations of ≥10% and the presence of CK in the context of one TP53 mutation as a “multi-hit equivalent”. (Figure 1).
The International Consortium for Myelodysplastic Syndromes (ICMS) adopted a data-driven approach to attempt a harmonization between these two classification systems. The analysis of 7017 MDS cases showed a discordance in 45.6% of cases between WHO and ICC criteria of MDS classification in terms of assigning participants to specific clinical entities. Importantly, discordant classification was observed in 35% of 657 participants with MDS syndromes with TP53 mutations [8]. To harmonize the classification of TP53-mutant MDS, a new classification of these tumors was proposed. TP53-mutated MDS with biallelic TP53 inactivation were included into cluster 2 of the ICMS classification; cluster 2 was characterized by TP53 mutations related to biallelic inactivation of the gene. A total of 77.9% of patients included in this cluster had a TP53 variant allele frequency of at least 10% and 70.1% had CK. Assignment to this cluster was irrespective of blast count. Patients with monoallelic TP53 inactivation were segregated into two different clusters: cluster 1, including MDS patients with mutated SF3B1 and concurrent higher risk mutations, and cluster 8, including MDS with del(5q) [8]. (Figure 1).
These classifications, although useful in improving the classification of TP53-mutant myeloid neoplasms, displayed many limitations, as has emerged from many recent studies. Stengel et al. reported the analysis of 178 TP53-mutant myeloid neoplasms, 83 AML and 95 MDS. MDS patients were subdivided into blast percentages (<5%, >5%/<10%, >10%/<20%) [9]. The frequency of double-hit TP53 alterations as well as of CK consistently changed in these four groups of patients (for double-hit TP53 alterations: 24% for MDS < 5%, 67% for MDS > 5%, 91% for MDS > 10% and 71% for AML; for CK: 24% for MDS < 5%, 70% for MDS > 5%, 91% for MDS > 10% and 64% for AML) [9] (Figure 2). At the level of outcomes, MDS with <5% of blasts showed the best outcome, followed by MDS with blasts > 5%, MDS with blasts > 10% and AML; the same hierarchy was observed when each subgroup was divided according to TP53 single-hit and TP53 double-hit; patients with TP53 double-hit have a dismal outcome in all subgroups [9]. The negative prognostic role of a CK was particularly evident for MDS cases with <5% blasts [9]. From this study, it emerged also that many cases of TP53-mutant MDS or AML cannot be classified as TP53-mutant myeloid neoplasms following the WHO-5 or ICC classification criteria.
Figure 2.
Top panel—Frequency of CK and TP53 double-hit alterations in TP53-mutated MDS patients subdivided into three groups according to the percentage of BM blasts (<5%, >5% and >10%) and AML patients. Original data are reported in Stengel et al. [6]. Bottom panel—Frequency of CK, MK and TP53 double-hit alterations in TP53-mutated MDS patients subdivided into three groups—MDS-LB (<5% BM blasts), MDS-EB1 (5–9% BM blasts) and MDS-EB2 (10–19% BM blasts)—and in AML patients. Original data are reported in Shah et al. [10].
Shah et al. have evaluated a group of 580 patients with TP53-mutant myeloid neoplasms, including: 219 AML, 194 MDS-LB (defined as MDS with <2% PB or <5% BM blasts), 92 MDS-EB1 (defined as MDS with 2–4% PB and 5–9% BM blasts) and 75 MDS-EB2 (defined as MDS with 5–19% PB and 10–19% BM blasts); TP53-mutant VAF significantly increased from MDS-LB (31%) to MDS-EB1 (37%), MDS-EB2 (36%) and AML (42%) [10]. Similarly, biallelic TP53 inactivation increased from MDS-LB to AML, with 63%, 73%, 78% and 86% of cases of MDS-LB, MDS-EB1, MDS-EB2 and AML presenting biallelic TP53 inactivation [10]. The frequency of CK and MK was lower in MDS-LB compared with other MDS groups (for CK: 63.5% in MDS-LB patients, compared with 84%, 92% and 01% in MDS-EB1, MDS-EB2 and AML; for MK: 56% in MDS-LB patients compared with 80%, 83% and 81% in MDS-EB1, MDS-EB2 and AML, respectively) [10] (Figure 2). The median OS observed in the four groups of TP53-mutant patients was significantly different: 14.9 months for MDS-LB, 9.7 months for MDS-EB1, 7.4 months for MDS-EB2 and 4.1 months for AML [10]. In MDS-LB patients, biallelic TP53 inactivation (63.5% of cases) was associated with significantly poor prognosis compared with monoallelic inactivation (36.5% of cases) (mOS 12.7 months vs. 23.6 months, respectively); the mOS of monoallelic TP53 inactivation without CK was superior to the monoallelic TP53 inactivation with CK (34.8 months vs. 13.0 months, respectively); MDS-LB with TP53 < 10% VAF less frequently have biallelic TP53 inactivation and CK and have a better mOS compared with those with TP53 VAF > 10% [10]. In MDS-EB1, MDS-EB2 and AML patients, two groups of patients were identified according to TP53 VAF < 10% or >10%. Patients with VAF < 10% are a distinct group with mOS longer than the corresponding patients with VAF > 10%; within this group with VAF < 10%, the presence of CK was associated with a significantly poor prognosis compared with those without CK [10]. TP53-mutant MDS-EB1 and MDS-EB2 with VAF > 10% have comparable biological properties and similar survival [10]. AML with VAF > 10% form a group with extremely poor survival; the presence of CK did not affect the outcomes of these patients [10].
In a subsequent study, Shah et al. have retrospectively applied WHO-5 and ICXC to 603 TP53-mutant myeloid neoplasms (TP53 mutants VAF ≥ 2%). WHO-5 and ICC could not classify 64% and 20% of these cases as TP53-mutant myeloid neoplasms [11]. Furthermore, of those classified, 67.5% would be classified discrepantly. The reasons for these discrepancies were related to prognostic importance of TP53-mutant AML; intersection of the blast percentage and allelic status; 17p deletion detected by cytogenetics; CK as multi-hit equivalent; and the TP53 mutant VAF threshold [11]. The analysis of the survival outcome of the various groups of TP53-mutant patients showed that AML was associated with poor survival compared with TP53-WT AML, myelodysplasia-related (4.7 vs. 18.3 months, respectively), thus supporting its inclusion within TP53-mutant myeloid neoplasms as a distinct entity; the survival of TP53-mutant MDS with 10–19% blasts was poor regardless of the TP53 allelic status; for cases with a single TP53 mutation with VAF < 50%, del(17p) or CK serve as surrogates of biallelic inactivation; and TP53-mutant AML, MDS multi-hit/multi-hit equivalent with VAF < 10% had significantly poorer survival compared with TP53 mutant without CK or del(17p) and were comparable with those with VAF ≥ 10% (14.1 vs. 48.8 vs. 7.8 months, respectively) [11]. These studies support the view that future classification of TP53-mutant MDS/AML should include all patients who have a biallelic inactivation of TP53, CK, >5% of blasts and/or TP53-mutant VAF > 10%. These observations may provide useful criteria for a revision of the WHO and ICC classifications.
Hart and coworkers have analyzed a cohort of 188 patients of TP53-mutated myeloid disease to evaluate at what extent diagnoses and outcomes differ between the ICC and WHO-5 classifications [12]. The overall analysis showed that 64% of cases were classified differentially by the ICC and WHO-5, including 30% of cases with <20% of blasts. A main reason for this discrepancy was related to the inclusion of CK as a surrogate for biallelic TP53 inactivation only in the ICC [12]. In fact, the analysis of patients showed that there are no significant differences in clinicopathologic characteristics or in OS between cases categorized as TP53-mutated disease by both classifications and those with a single TP53 mutation associated with CL, thus supporting that the presence of CK is a key parameter for identifying TP53-mutant cases with biallelic TP53 inactivation [12]. A total of 94% of cases of TP53-mutant AML are discrepantly classified between the ICC and WHO-5 because AML with mutated TP53 is recognized as a distinct category only in ICC; in fact, according to WHO-5, these cases are diagnosed as AML with myelodysplasia-related changes (AML-MR). However, the analysis of AML-MR patients without TP53 mutations clearly showed that they form a group distinct from TP53-mutated AML for their different genetic profiles and outcomes, a finding strongly supporting the inclusion of TP53-mutant AML as a distinct entity [12]. Another element of great discrepancy between the two classification systems is related to the significance of TP53 VAF, where the WHO-5 includes VAF criteria with respect to TP53 mutations, while the ICC required TP53 VAF > 10% to diagnose TP53-mutated cases. However, the observations made in this study showed that TP53 VAF < 10% is frequently associated in both MDS and AML patients with equal or worse outcomes compared with those observed with VAF > 10% [12].
Recent studies have evaluated the difficulties related to the classification of the heterogeneous group of MDS with isolated del(5q). Montero and coworkers have explored a large cohort of 682 MDS patients with isolated del(5q) (MDS-del(q)); a total of 18.9% of these patients displayed TP53 mutations, and 76% of these mutations were TP53 monoallelic and 24% were multi-hit [13]. Considering the whole group of TP53-mutant patients, their OS was similar to that observed for TP53-WT patients; however, TP53-mutant patients had a significantly increased incidence of AML transformation compared with TP53-WT patients [13]. Concerning patients with monoallelic TP53 alterations, their outcomes were related to the VAF: patients with TP53 monoallelic mutations, and VAF > 20% presented outcomes equivalent to TP53 multi-hit patients [12]. Importantly, 48% of TP53-monoallelic MDS-del(5q) had a TP53-mutant VAF < 20% and 52% had a VAF > 20% [13].
In a recent study, the same authors explored a group of 43 patients with MDS with isolated del(5q) harboring TP53 multi-hit alterations (MDS-del(5q) TP53 multi-hit) and compared these MDSs with 68 patients with low-blast MDS with TP53 multi-hit and without isolated del(5q) (MDS-LB TP53 multi-hit) [14]. By definition, patients with MDS-del(5q) TP53 multi-hit do not have CK, while 76% of MDS-LB TP53 multi-hit have CK. Patients with MDS-del(5q) TP53 multi-hit more frequently had SF3B1 mutations, were less frequently classified as high-risk by IPSS and had significantly better outcomes than patients with MDS-LB TP53 multi-hit (OS 70.2 vs. 13.9 months and time to AML progression of 31.9 vs. 7.2, respectively) [14]. Importantly, the outcomes of MDS-del (5q) TP53OK multi-hit persisted significantly better even when compared with MDS-LB TP53 multi-hit without CK (OS 70.2 vs. 39.9 months and time to AML progression 31.9 vs. 11.4 months, respectively) [14].
MDS with >5% BM blasts and a TP53 mutation indicates a highly aggressive disease. This combination defines a distinct clinical entity that behaves similarly to AML and is associated with a poor overall prognosis. A recent study reported the characterization of a large cohort of 587 MDS patients with >5% BM blasts and TP53 mutations: a total of 87.7% of these patients had monosomy 5 or del(5q), and 12.3% of patients were without these chromosomal alterations [15]. The group with chromosome 5 aberrations, compared with the group without chromosome 5 aberrations, had more CK (908.3% vs. 61.1%), chromosome 7 (65% vs. 37.5%), del(17p) (59.4% vs. 30.6%), TP53 multi-hit alterations (88.3% vs. 56.9%) and less co-alterations (48.2% vs. 76.4%) [15]. Presence of −5/5q was associated with a shorter 24-month OS (7.8 months vs. 11.2 months), an effect restricted to some patient subgroups, including patients with <20% BM blasts, absent chromosome 7 abnormalities and WHO-5-defined TP53 single-hit allelic state [15]. Finally, the presence of −5/5q predicted significantly shorter OS post-HSCT [15].
4. Main Characteristics of CK in MDS and AML
CK includes different types of chromosomal abnormalities, such as aneuploidy (monosomies, trisomies), large deletions (such as the loss of the 5q or 7q or 17p arms), ring chromosomes, marker chromosomes and unbalanced translocations. Karyotype complexity has a major prognostic role in MDS and AML. Although there is no consensus in the definition of a CK, a CK is based on the presence of at least three independent chromosomal abnormalities in MDS or AML patients. The Francophone Group of Hematological Cytogenetics proposed a definition of CK according to the number of chromosome abnormalities: low CK having three chromosome abnormalities (CK3); intermediate CK having four chromosome abnormalities (CK4); and highly complex karyotype as having five or more chromosome abnormalities (CK5) [1].
Stolzel and coworkers reported the characterization of AML with CK in a group of 3526 de novo AML patients. In this large cohort of AML, patients with CK numbered 417 and were classified into six different subgroups: patients with hyperdiploidy (HDK, 4.8%), patients with t(9;11) (t(9;11) 2.4%), patients with CK3 without adverse risk aberrations (CK3, 4.6%), patients with CK4 without adverse risk aberrations (CK4, 8.4%) and patients with CK3 + CK4 with adverse risk aberrations (CK + ADV, 79.8%) [16]. Adverse risk aberrations are defined as −5, del(5q), −7, del(7q), −17, del(17p), add(5q) and add(7q) [16]. Pure HDK was rare and was associated with a reduced OS compared with AML with normal karyotype [16]. CK3 and CK4 patients were subdivided into four subgroups: CK3 + MK (monosomal karyotype), CK3-MK, CK4 + MK and CK4-MK; patients with CK3 and CK4 either without or with MK have a markedly shorter OS compared with AML with normal karyotype [16]. It is important to note that CK4 has a higher frequency of adverse risk aberrations (82% vs. 54%, respectively) and MK (65% vs. 34%) than CK3 [16].
A recent study reported an extensive molecular characterization of CK in AML and MDS in a cohort of 939 patients (429 MDS and 510 AML) [17]. The most frequent mutation was TP53 (MDS 79% and AML 70%). Chromosomal abnormalities were not random: the most frequently affected chromosomes were Chr 5 (77%), Chr 7 (58%) and Chr 17 (46%); Chr 10, Chr 2 and sex chromosomes were the less frequently affected; with Chr 5, the most frequent abnormalities were del(5q) (59% of all CK); within Chr 7, the most frequent abnormalities were monosomy 7 (29%) and del(7q) (28%); within Chr 17, the most frequent were del(17p) (21%) and monosomy 17 (17%); and other recurrent monosomies involved Chr 16, Chr 18 and Chr 20 [17]. Hierarchical clustering showed the existence of two clusters: a major cluster (cluster 1, 787 patients) segregated patients with Chr 5 abnormalities and TP53 mutations, with frequent del(7q) and del(17p) and monosomy 17; a smaller cluster (cluster 2, 152 patients) segregated patients with Chr 7 abnormalities and Chr 8 trisomy [17]. Patients in cluster 1 had worse OS than those in cluster 2 [14]. In cluster 1, all patients had a poor survival, with the exception of Chr 5 normal/TP53-WT with a relatively better survival [14]. These observations suggest that chromosome 5 abnormalities and TP53 mutations contribute to chromoanagenesis genetic instability and confer worse outcome.
5. Hyperdiploid Complex Karyotype
HDK AML represents a rare cytogenetic subgroup of AML, characterized by a modal number of 49–65 chromosomes; extra copies of chromosomes 8, 13 and 21 are the most frequently observed aberrations. According to Chilton et al., HDK can be subdivided into three different subgroups: HDK numerical (HDK-NUM), with only numerical chromosome aberrations; HDK adverse (HDK-ADV), with numerical and with chromosome aberrations associated with adverse outcomes, such as −5, del(5q), −7 and −17; and HDK structural (HDK-STR), with additional structural chromosome abnormalities [18]. These three HDK subgroups differ also for their mutational profile in that TP53 mutations are frequent in the HDK-ADV group (64%) but are rare or absent in the HDK-STR and HDK-NUM subgroups; DNMT3A and TET2 mutations are more frequent in HDK-STR and HDK-NUM than in HDK-ADV subgroups [19]. The outcomes of the three different HDK subgroups are different in that the survival of HDK-NUM patients is better than that of HDK-STR and particularly of HDK-ADV [19].
It is important to note that HDK-AML with only numerical changes without structural abnormalities was not considered as CK and has been reclassified into an intermediate risk group in the 2022 European Leukemia Net (ELN) risk classification, while it has been historically classified as an adverse risk group [20]. The observations made in the study of Hzaveh et al. on a cohort of 124 AML patients support this conclusion and also suggest that HDH-STR and HDK-ADV should be included in the adverse risk group [19].
However, a study carried out on 133 Chinese AML patients with HDK showed non-statistically significant differences for OS in the subgroups NUM, STR and ADV and suggested that all these three subgroups should be assigned to the adverse cytogenetic risk group of AML [21].
Poiré et al. have analyzed the EBMT registry and identified 236 HDK patients defined as pure HDK (pHDK, corresponding to HDK-NUM) and HDK with other cytogenetic abnormalities (HDK+, corresponding to HDK-STR and HDK-ADV) and observed 2-year probability of OS better for pHDK than for HDK+ (57% vs. 36%, respectively), as well as a lower cumulative incidence of relapse for pHDK than for HDK+ (22% vs. 44%, respectively) [22]. According to these findings, they concluded that pHDK may represent a distinct cytogenetic entity from HDK+ [22].
In conclusion, HDK AML is a rare and heterogeneous subgroup characterized by the presence of 49 to 65 chromosomes. Cases associated with pure numerical changes (HDK-NUM) are classified under intermediate risk; cases that also include high-risk markers like chromosome 5 or 7 losses carry a poorer prognosis.
6. Typical and Atypical Complex Karyotype
In CK-AML, the most frequent chromosome abnormalities are represented by unbalanced abnormalities, the most frequent being loss of the long arm of chromosome 5 5/5q, deleted in about 80% of cases, followed by loss of material from 7q and 17, each occurring in about 50% of cases. Abnormalities of 5q, 7q and 17p often occur together and are present in about 85% of CK-AML patients; this observation was the rationale for subdividing CK-AML into typical and atypical, with typical being CK-AML with ≥3 abnormalities that include 5q, 7q and/or 17p loss and atypical being those without these abnormalities [23]. (Figure 3).
Figure 3.
Subgroups of CK-AML patients subdivided into two main groups of unbalanced and balanced CK according to the type of chromosome alterations; unbalanced CK are subdivided into two groups, typical and atypical CK; typical CK are subdivided into two subgroups according to the presence or not of TP53 mutations; atypical CK are subdivided into numerical and other abnormalities according to the type of chromosome aberrations.
Typical and atypical CK-AMLs differed for cytogenetic and mutational abnormalities. Thus, atypical and typical CK-AML differed not only for the presence of 5q, 7q and 17p but also for the complexity of karyotype more complex in typical than atypical cases (median nine vs. four abnormalities) [14]. The mutational profile of typical and atypical CK-AML is markedly different in typical and atypical CK-AML, with TP53 mutations being markedly more frequent in typical than atypical cases (67% vs. 10%, respectively), while other gene mutations (TET2, NRAS, NF1, FLT3-ITD, FLT3-TKD, DHF6, ZRSR2, MED12 and NPM1) are more frequent in atypical than typical cases [23] (Figure 4).
Figure 4.
Main gene mutations observed in typical and atypical CK-AML. Top panel: frequency of the main individual gene mutations observed in typical and atypical CK-AML. Bottom panel: Main gene mutations observed in typical and atypical CK-AML subdivided according to structural–functional pathway.
At the clinical level, patients with atypical CK-AML had higher WBCs, higher percentages of BM and PB blasts. Although treatment outcomes were poor for these two groups of patients, atypical CK-AML patients had higher CR rates and a trend towards longer DFS and OS than typical CK-AML patients [23]. Both typical and atypical CK-AML are heterogeneous. In fact, about one third of typical CK-AML cases do not harbor TP53 mutations. The typical TP53-mut CK-AML had more complex karyotypes and more often harbored 5q and 17p abnormalities than the CK-AML TP53-WT; patients with typical CK-AML TP53-WT more often carry BCOR mutations and are the only ones with SMARCA2 and PLCG2 mutations [23]. Atypical CK-AML can be subdivided into two subgroups: one with only numerical chromosomal abnormalities (characterized by RUNX1, ASXL1, SRSF2, KRAS and STAG2 mutations) and the second with other chromosome abnormalities that are not numerical (representing only the atypical CK-AML with TP53 mutations in 16% of cases, while in the numerical subgroup, they are absent) [23].
In typical CK-AML, an additional factor of heterogeneity is related to the number and to the type of 5q, 7q and 17p abnormalities present, with the most frequent combinations being represented by 5q, 7q and 17p, 7q and 17p but not 7q, 7q but not 5q or 17p and 5q and 7q but not 17p [20]. The 7q but not 5q or 17p subgroup differs from the other typical CK-AML subgroups for fewer chromosome abnormalities, lower frequency of TP53 mutations (18% vs. 74%) and higher frequency of FLT3-ITD, BCOR, WT1, DNMT3A, NPM1 and RUNX1; patients in this subset had longer OS than other patients with typical CK-AML, and this may be related to the lower frequency of TP53 mutations [23]. A third group of CK-AML is represented by CK-AML balanced and characterized by the presence of ≥3 chromosome abnormalities, where one or more are balanced arrangements, such as translocations. Two subgroups of balanced CK-AML were identified: one subgroup with the presence of a rare recurrent balanced chromosome abnormality (characterized by paucity of gene mutations, with only recurrent TP53 mutations in 33% of cases), and another subgroup characterized by the presence of unique balanced aberrations (characterized by more frequent gene mutations, including 60% of TP53 mutations, and by the presence of very complex karyotypes and abnormalities of 5q, 17p and/or 7q in 75% of cases) [23].
Ussman and coworkers analyzed 263 patients with adverse risk according to ELN 2022 who underwent HSCT. A total of 105 of these patients had CK-AML (17% a balanced CK-AML and 83% an unbalanced CK-AML) [24]. Following allo-HSCT, patients with CK-AML had a shorter EFS than the other adverse risk AML patients; EFS was similar for both typical and atypical CK-AML patients [24]. In multivariate analysis, ≥5 cytogenetic aberrations as well as no CR/CRi at HSCT were adverse factors for RFS [21].
Interestingly, the combination of sparse whole genome sequencing with machine learning of AML genomes applied to over 600 AML patient samples revealed novel genetic, biologic and clinical correlates in AML patients. Particularly, two molecular novel subgroups were identified: a group of patients exhibiting focal and cryptic hemizygous deletions at 17p, 21q and 3p in otherwise diploid genomes, associated with inferior survival compared with other patients; and a group of patients within the adverse risk category group that lack deletions on chromosomes 5, 7 and 17 and that fare better than the rest of the adverse risk patients with CK-AML, likely reflecting previously identified atypical CK-AML patients [25].
Yoshida et al. reported the clinical features of 115 CK-AML patients, 77 with typical and 38 with atypical disease [26]. The chromosomal abnormalities and the mutational profile observed in this study in typical and atypical CK-AML were similar to those reported by Mrozek et al. [23]. Following intensive chemotherapy treatment, typical and atypical CK-AML achieved a similar CR rate (55.6% vs. 70.8%, respectively) but a significantly shorter OS (143 days for typical and 369 days for atypical) [26]. For atypical CK-AML patients, TP53 mutations observed in 33% of cases were associated with poor outcomes (mOS 77.5 days for patients with TP53 mutations and 574 days for those without TP53 mutations) [26].
In conclusion, typical and atypical in AML are defined by the presence of three or more chromosome abnormalities, distinguished by the presence or absence of specific core losses on chromosome arms 5q, 7q and/or 17p. Typical CK is strongly linked to high rates of TP53 mutations and MK; patients with typical CK are usually older at diagnosis and experience a very poor prognosis and shorter OS than atypical CK patients.
7. Monosomal Karyotype in the Context of a Complex Karyotype
Monosomal karyotype (MK) is defined by the presence of a single autosomal monosomy, along with an additional autosomal monosomy or a structural chromosomal abnormality. Monosomy 5 (−5), monosomy 7 (−7) and monosomy 17 (−17) are among the most frequently observed in MDS and AML patients. MK is present in 10–15% of MDS and AML, and >90% of MK cases also qualify as a CK. MKs are subdivided into two subgroups: MK1 defined as one single autosomal monosomy with structural abnormalities and MK2 defined as two or more distinct autosomal monosomies [27]. AML patients with MK have a poor prognosis; however, the survival of MK1 patients is significantly better than that of MK2 patients after allo-HSCT in patients in CR at transplantation [28].
In both MDS and AML patients, MK is strongly associated with CK (about 90%). In about 10–15% of cases, a CK without MK is observed, referring to a genetic profile with multiple chromosomal abnormalities (three or more) without the complete loss of any single autosomal chromosome. Some studies suggest that patients with a CK without MK may have a better OS than those with CK and MK [27,29]. On the other hand, studies in MDS patients showed the presence of MK in 16% of patients, most of whom associated with CK (88% of cases); in these patients, the presence of MK in the context of a CK, but not MK alone, was associated with shorter OS and increased incidence of AML transformation [30].
At variance with MDS, in AML both MK and CK are associated with poor prognosis, but the negative prognostic effect is more pronounced in patients who concomitantly have MK and CK. Thus, Jo and coworkers explored the registry database of adult AML patients who underwent allo-HSCT between 2000 and 2019 in Japan; among 16,094 patients, they identified 3345 patients with poor cytogenetic risk, mostly including patients with MK and CK: a total of 34.8% of patients had CK−/MK−, 32.4% CK+/MK−, 3.3% CK−/MK+ and 29.5% CK+/MK+ [31]. The results of this analysis showed: concerning OS, 5-year OS was 37.1%, 27.7%, 25.5% and 10.4% for patients with CK−/MK−, CK−/MK+, CK+/MK− and CK+/MK+; concerning cumulative incidence of relapse, the 5-year CIR was 40.6%, 54.1%, 52.5% and 61.9% for patients with CK−/MK−, CK−/MK+, CK+/MK− and CK+/MK+, respectively; and concerning DFS, the 5-year DFS was 33.6%, 22.3%, 22.3% and 9.9% for patients with CK−/MK−, CK−/MK+, CK+/MK− and CK+/MK+, respectively [31]. In line with these observations, Jeyakumar et al. analyzed the outcomes of 67 consecutive AML-MDS patients who underwent HSCT at Stanford University: a total of 16% of these patients were TP53-mutated only, 30% had CK/MK and 54% had TP53-mutated/CK/MK [29]. Following HSCT, patients with only TP53 mutations had better survival and a lower 1-year cumulative incidence of relapse compared with the other two groups of patients with CK/MK [32].
In conclusion, MK is defined by two or more distinct autosomal monosomies or one single monosomy combined with at least one structural chromosome defect. Very frequently, MK predicts very low OS and rapid transition from MDS to AML.
8. TP53 Alterations in CK-AML
As above mentioned, there is a strong association and pathogenetic relationship between CK and TP53 gene alterations both in MDS and AML patients. According to the ICC 2022 classification, multi-hit TP53 signifies the presence of two or more distinct TP53 mutations, each with VAF ≥ 10%; a single TP53 mutation with VAF ≥ 50%; and a single TP53 mutation with VAF ≥ 10% accompanied by a cytogenetically apparent del (17p13.1), copy-neutral loss of heterozygosity (LOH) at the 19p TP53 locus or in the absence of LOH information, CK [7].
Most of the TP53 mutations observed in MDS and AML patients are missense mutations occurring within the DNA-binding domain; these mutations have important functional consequences impairing the transcriptional activation of TP53 target genes [33]. Many missense mutations impair the transcriptional activity of mutant p53 protein through mechanisms either due to a disruption of the residues involved in DNA contact or due to the induction of conformational changes of the p53 protein, preventing promoter binding. However, TP53 missense mutations often act as dominant-negative. In fact, since the p53 suppressor protein functions as a tetramer, a mutant p53 protein may bind to WT p53 subunits to form a mixed tetramer, thus inactivating residual WT p53 [34]. This mechanism may lead to a full TP53 inactivation, even in conditions in which only one TP53 allele is affected [34]. Many missense TP53 mutants do not just block WT p53 but also acquire active, pro-oncogenic behaviors promoting altered transcriptional programs. Thus, hotspot mutations involving residues R175, YY220, G245, R248, R273 and R282 represent about 35% of all TP53 missense mutations in AML/MDS; these hotspot mutations may have dominant-negative or gain-of-function properties [35].
Jambhekar and coworkers have analyzed TP53 mutations in four different myeloid neoplasm subtypes (MDS, AML, AML with myelodysplasia-related changes (AML-MRC) and therapy-related AML (t-AML)) and identified significant differences in mutation types, spectrum and hotspots [33]. Missense mutations represented the most frequent type of TP53 mutations in all types of myeloid neoplasms; however, missense mutations were enriched in MDS and splice mutations depleted in MDS compared with AML-MRC [30]. Missense mutations mostly occurred at the level of DBD of the TP53 gene; however, DBD enrichment was significantly higher in MDS than in AML or AML-MRC [30]. Of the seven most common mutations found in human cancers, six were identified as hotspot peaks in AML (R175, Y220, G245, R248, R273 and R282) [30]. Contact mutations (R248Q, R273H and R282W) were more common in AML-MRC than in either AML or MDS, while conformational mutations (R175H, Y220C, G245S and R249S) occurred with similar frequencies in the different myeloid neoplasms [33]. Importantly, among myeloid neoplasms, MDS and AML-MRC displayed the highest differences in terms of TP53 mutation types, distributions and predicted transcriptional activities of TP53 mutations. Missense mutations, particularly those retaining higher levels of transcriptional activity, are overrepresented in MDS, while mutations inducing a complete loss of expression or transcriptional activity of p53 protein are overrepresented in AML-MRC, thus suggesting that TP53 missense mutations may play a more active role on initiation of MDS, seemingly by acquiring gain-of-function properties, while p53 inactivation is sufficient for promoting progression in AML-MRC [33].
A pivotal study by Rucker and coworkers evaluated the frequency and the clinical–biological characteristics of CK-AML with TP53 alterations [30]. In this study, 234 CK-AMLs were evaluated, with TP53 mutations in 60% of cases and TP53 losses in 40% of cases for a total of 70% of cases with TP53 alterations; TP53 mutations were localized in the sequence-specific DNA-binding domain of TP53, and the large majority were missense mutations, followed by deletions/insertions [36]. It was estimated that at least 71% of TP53-mutant CK-AML had TP53 biallelic inactivation. TP53-altered CK-AMLs were characterized by a higher degree of genomic complexity (14.3 chromosomic alterations in TP53-mutant vs. 6.16 in TP53-WT) and a higher frequency of specific copy number alterations such as −5q, −7q, −16q and −18q [36]. TP53-altered CK-AML more frequently displayed a monosomal karyotype compared with TP53-WT CK-AML. TP53-altered CK-AML patients were older and had significantly lower CR rates, inferior EFS, relapse-free survival and OS than TP53-WT AML patients [36].
A more recent study evaluated a large cohort of 299 CK-MDS (155 patients) and CK-AML (144 patients); a total of 83% of these patients had TP53 gene alterations, and for the allelic status, 64% of MDS and 83% of AML patients had multi-hit alterations [37]. Patients with TP53 alterations had older age, lower hemoglobin and BM blasts compared with patients with CK and TP53-WT [37]. Compared with patients with TP53-WT, CK-TP53-mutated patients had more chromosome alterations (median eight vs. four) and were enriched in abnormalities of chromosome 5 (86% vs. 45%), chromosome 7 (60% vs. 43%) and chromosome 17p (42.5 vs. 15.6%). In all patients, TP53-WT patients had a mOS of 33.9 months, compared with 12.5 months and 9.2 months in those with monoallelic or multi-hit TP53-mutated patients; the difference in mOS between TP53-WT and both monoallelic or multi-hit TP53-mutated patients was highly significant, while the difference between monoallelic and multi-hit TP53-mutant patients showed a trend toward worse outcomes for multi-hit patients [37]. Multivariable analysis identified the presence of multi-hit TP53 alterations as the strongest predictor of a worse outcome, while neither a diagnosis of AML vs. MDS nor therapy relatedness independently influenced OS [37]. This study also included a group of therapy-related MDS and AML: these cases displayed a higher frequency of TP53 mutations, with a trend for worse survival in therapy-related patients as compared with de novo disease, and within the therapy-related group, the presence of TP53 mutations strongly predicted for worse outcome [37].
Grob et al. reported the molecular characterization of 230 TP53-mutant AML (186 patients) and MDS-EB (with excess of blasts, 44 patients); the median VAF of TP53 mutations was 47%, and biallelic mutant TP53 status was observed in 76% of these patients; multiple TP53 mutations were observed in 215 of patients [38]. A total of 84% of patients with mutant TP53 have CK; CK was detected in most patients with biallelic TP53 mutant (97%), in patients with multiple TP53 mutations (94%) and in patients with larger TP53 clones (94% in VAF > 40%) [38]. Both AML and MDS-EB patients with TP53 mutations have a poor outcome with a 2-year OS of 12.8% [38]. Patients with CK associated with TP53 mutations have a particularly poor survival; patients with CK without TP53 mutations have a survival similar to that of TP53-mutant patients without CK [38]. Patients with monoallelic hit TP53 mutations had a dismal survival as well as those with multi-hit TP53 alterations. Clonal size was not significantly associated with survival [38].
Fedenko and coworkers have explored the temporal order of mutations and karyotype aberrations in CK-AML [36]. These authors have performed whole exome sequencing and CNV of 33 CK-AML, 17 TP53-mutant and 16 TP53-WT cases; OS was significantly better in TP53-WT than in TP53-mutant patients, and among TP53-mutant patients, high VAF values were associated with a worse outcome [39]. The TP53-mutant CK-AML group had few mutations outside the tumor suppressor gene category, while the TP53-WT CK-AML group had mutations in epigenetic modifiers, DNA damage repair component genes and the signaling pathway gene [39]. The most frequent copy number aberrations in the TP53-mutant group were −5q, −7q, −17p, −16q and +11q; the most frequent copy number aberrations in the TP53-WT group were +8, −7q and 11q23 translocations corresponding to the KMT2A locus [36]. More than half of TP53-WT CK-AML have atypical karyotypes without −5q, −7q and −17p [39]. A total of 16 of 17 TP53-mutant CK-AML had the TP53 gene biallelically inactivated. The analysis of TP53 mutational VAF and the clonal fraction of CNV supported the conclusion that TP53 mutations can arise in any sequence relative to other driver mutations but are rapidly followed by the loss of the second TP53 allele and subsequent karyotype decline [39]. Thus, TP53 mutations are dominant-negative in CK-AML [39].
Haase et al. reported the characterization of 339 MDS patients with CK, and 55% of these patients were TP53-mut and 45% were TP53-WT; TP53-mut CK has less mutations than TP53-WT CK-MDS (ASXL1 5% vs. 15%; U2AF1 3% vs. 11%; RUNX1 0.5% vs. 9%) [40] (Figure 5).
Figure 5.
Most recurrent karyotype abnormalities (top panel) and somatic gene mutations (bottom panel) observed in 153 TP53-WT and 186 TP53-mut CK-MDS patients. Data are reported in Haase et al. [40].
Some remarkable differences have also been observed in the frequencies of chromosome abnormalities between TP53-mut and TP53-MDS, with chromosome 5 and 17 and monosomal aberrations being particularly frequent in TP53-mut CK-MDS [34]. The OS of TP53-mut CK-MDS was significantly lower than that of TP53-WT CK-MDS (mOS 0.6 years vs. 1.5 years, respectively); the TP53-mutant VAF negatively affected OS (VAF > 0.4 had OS of 0.6 years and VAF < 0.4 had OS of 1.1 years) [40]. In the whole CK group, the presence of five or more chromosome abnormalities and the presence of monosomal karyotype was associated with poor outcomes; the combined presence of monosomal karyotype and TP53 mutations was associated with a particularly poor prognosis [40].
A pivotal study by Bernard and coworkers evaluated the role of TP53 allelic state in MDS and its relationship with chromosome abnormalities. In this study, 3324 MDS patients were explored for TP53 mutations and allelic state; a total of 378 patients displayed at least one TP53 mutation, and 24 patients displayed alterations of TP53 locus without TP53 mutations [35]. Evaluating both TP53 mutations and allelic imbalances, four subgroups of TP53-mutated patients were identified: monoallelic TP53 mutation (33% of cases), multiple mutations without deletion or cnLOH (22% of cases), mutations and concomitant deletions (22% of cases) and mutations and concomitant cnLOH (21% of cases) [41]. Subgroup 1 corresponded to a mono-hit subgroup, while subgroups 2 to 4 corresponded to multi-hit subgroups. The mono-hit and multi-hit subgroups greatly differed for associated chromosomal abnormalities, with del (5q) and CK being much more frequent in multi-hit than mono-hit TP53-mutant MDS (85% vs. 34% and 91% vs. 13%, respectively) [41] (Figure 6), and they also differed for driver mutations different from TP53 mutations, being more frequent in the monoallelic state compared with the multi-hit subgroups [41] (Figure 6).
Figure 6.
Frequency of CK and the main chromosomic abnormalities (top panel) and the more recurrent gene mutations (bottom panel) in TP53-mutated MDS subdivided according to allelic status into TP53 mono-hit and TP53 multi-hit. Original data are reported in Bernard et al. [41].
Overall survival and the rate of AML transformation were significantly different between TP53 allelic states: in the multi-hit state, the mOS was 8.7 months, whereas it was 2.5 years for monoallelic patients; the 5-year cumulative incidence of AML transformation in the multi-hit and monoallelic states was, respectively, 44% and 21% [38]. In multivariate analysis, multi-hit TP53 and CK, but not monoallelic TP53, were independent predictors of adverse outcome [41].
The association between TP53 VAF and disease outcomes was investigated in many studies. Lu et al. reported the evolution of 160 TP53-mutant AML, and 23 of these patients (14.4%) had a VAF < 10%; at the molecular level, these AMLs with VAF < 10% compared with the rest of TP53-mutant AMLs had lower PB blast percentages at diagnosis (2% vs. 22.5%, respectively), lower frequency of CK (31.8% vs. 77.9%, respectively), lower frequency of CK (31.8% vs. 77.9%, respectively), lower incidence of monosomy 7 (4.5% vs. 27.2%, respectively), lower frequency of monosomy 5/del(5q) (4.5% vs. 54.4%, respectively), a higher frequency of ASXL1 mutations (30.4% vs. 10.2%, respectively) and SRFSF2 mutations (26.1% vs. 2.9%, respectively) [42]. The majority of these patients were treated with VEN + HMA, and although patients with TP53-mut VAF < 10% displayed a trend toward a higher rate of CR (69.2% vs. 44%), they had an OS comparable with that observed for the rest of TP53-mutant AML patients [42].
In conclusion, TP53 alterations strongly associate with CK, appearing in 70% to 80% of these cases; they drive genomic instability, multi-chromosomal chaos and very poor clinical outcomes. In CK-AML patients, TP53 alterations are typically dominant-negative and rapidly followed by the loss of the other allele (multi-hit TP53 alterations) and overall karyotype degeneration.
9. Mechanisms of CK Development
The mechanisms of CK development in AML and MDS are highly interconnected with the loss of critical DNA repair and tumor suppressor pathways. The main drivers include: TP53 gene mutations and deletions causing genomic instability; chromothripsis and chromoplexy, underlying the generation of multiple chromosomal aberrations via catastrophic, single-event genomic crises; events underlying a karyotype decline related to the acquisition of multiple genetic alterations of TP53 gene alleles; and generation of events of unbalanced chromosomal rearrangements, leading to net loss of genetic material with consequent loss of heterozygosity or events of complete loss of a whole chromosome (monosomies).
CK development, currently defined by the presence of three or more chromosome abnormalities with a single clone, usually arises from events of strong genetic instability, frequently by a combination of events such as catastrophic cellular events and stepwise accumulation of genetic errors. The catastrophic events are collectively known as chromoanagenesis, a collective term indicating a set of catastrophic, single-cell cycle mechanisms that create complex structural abnormalities, The term, derived from the ancient Greek word “chromo” meaning chromosome and “anagenesis” indicating rebirth, describes a “rebirth” of chromosomes where chromosomes shatter and rearrange, contributing to the development of multiple chromosome abnormalities, determining cancer progression and rapid cancer evolution [43]. Chromoanagenesis determines large-scale genomic rearrangements, occurs suddenly and induces genomic catastrophic events characterized by extensive and chaotic chromosome rearrangements and copy number alterations [43]. Chromothripsis was discovered by Stephens et al., who used NGS to identify chromothripsis in a CLL patient with 42 rearrangements involving the log arm of chromosome 4; it was proposed that massive genomic rearrangements discovered in this patient could derive from a single catastrophic event: chromothripsis [44].
Rausch first reported in 2012 the occurrence of chromothripsis in AML. In this pivotal study, chromothripsis was commonly detected in TP53-mutant AML patients (47.1% of cases); furthermore, chromothripsis was associated with cases of CK-AML (39.3% of positivity) rather than in cases with non-CK (0% of cases) [45]. Fontana and coworkers explored 395 de novo AML patients and reported evidence of chromothripsis in 6.6% of these patients [43]. Patients with chromothripsis (CT) had higher age, ELN high risk, lower white blood cells, TP53 loss and/or mutations (observed in 23/26 patients) and CK, while FLT3 and NPM1 mutations were absent in these patients [46]. CT-positive patients had worse OS compared with high-risk AML patients [43]. CT-positive AML patients had typical features of chromosome instability, including TP53 alterations, 5q deletion, CK, high number of CNAs, alterations in DNA repair and cell cycle and focal deletions on chromosomes 4, 7, 12, 16 and 17 [46].
Rucker et al. reported the evaluation of 112 CK-AML patients, and 39 of these patients were CT-positive [44]. The comparison of CT-positive and CT-negative CK-AML patients showed that CT-positive patients have more chromosome losses or gains than CT-negative patients, have more genomic aberrations and significantly more abnormalities of chromosomes 5, 7, 12, 16 and 17, more MK than CT-negative patients [47] (Figure 7). CT-positive patients had a significantly lower OS than CT-negative patients [47].
Figure 7.
Main chromosome alterations, monosomal karyotype and TP53 alterations in a group of CK-AML patients subdivided into two subgroups according to the presence or not of chromothripsis (CT). Data are reported in Rucker et al. [47].
Nacheva et al. have analyzed 87 MDS and AML patients with CK using chromosome G-banding, FISH, chromosome microarray analysis and targeted NGS; these samples were analyzed according to ISCN 2020, and CT was defined according to alternating disomy and heterozygous loss along a chromosome or chromosomal segment, while chromoanasynthesis (CHA) was defined according to deletions and one or two copy number gains in a single chromosome or chromosome region including copy number variants without the clustered breakpoints of CT [48]. CK harboring CT- and CHA-type aberrations were detected in 65 out of 727 AML and 22 out of 1779 MDS samples; CT events were observed alongside CHA in 67% of cases and rarely presented as a sole abnormality (2% of cases), while CHA alone was found in 31% of samples [45]. CT was most frequently mapped at chromosomes 21, 7, 17, 19 and 5; CHA alterations in most instances followed the genome location of CT [48]. Only cases harboring 5q deletions showed a significant association with TP53 status [48].
Abel and coworkers explored 29 AML and 13 TP53 mutations by whole genome sequencing and reported a total incidence of 59.5% CT in the whole cohort of patients; among AML patients, 58.6% had CT and 90% had CK; among MDS patients, 61.5% had CT and 100% had CK [49].
Wei et al. have reported the analysis of chromoanagenesis (CAG) in a group of 410 AML patients (292 newly diagnosed and 118 R/R) using optical genome mapping (OGM) [50]. CAG was identified in 16% of patients (14% of ND AML and 20% of R/R AML), which is higher than the reports for CT using array-based assays. In this study, CAG was identified by the presence of clusters, with 10 or more breakpoints of structural abnormalities and/or segmental copy number alterations within one or more chromosomal regions [50]. Compared with patients without CAG, patients with CAG showed markedly higher frequencies of CK (92% vs. 11%), monosomal karyotype (88% vs. 12%), marked clonal heterogeneity (75% vs. 7%), gene amplification (49% vs. 1%) and TP53 abnormalities [50]. Among patients with ND AML, patients with CAG had a significantly shorter OS than those without CAG [50].
Bochtler et al. have explored the presence of marker chromosomes in AML patients [47]. Marker chromosomes are defined as chromosomes that are rearranged to a level that prevents their allocation to 1 of the 23 chromosomes. In two large cohorts of adult AML patients, a frequency of marker chromosomes ranging from 4.5% and 7.4% was observed [51]. Marker chromosomes were frequently observed in adverse risk AML (26.5%) and were associated with CK (40.3%), monosomal karyotype (50.2%) and with abnormalities of chromosomes 5, 7 and 17 [50]. Marker chromosomes are rare in AML with recurrent translocations, as well as in FLT3-mutant or NPM1-mutant AML [51]. A total of 38% of AML patients with marker chromosomes display CT, and the subgroup of patients with marker chromosomes and CT display a significantly higher frequency of multiple chromosome abnormalities (100% of CK) compared with the subgroup with marker chromosomes without CT [51]. The prognosis of patients with both marker chromosomes and CT is particularly poor [51]. The presence of marker chromosomes in AML patients was associated with a particularly poor prognosis after allo-HSCT with a markedly reduced OS compared with the rest of adverse risk AML patients without marker chromosomes [52].
Klever et al. reported the analysis of 11 CK-AML patients using an integrative workflow for the detection of structural variants based on Oxford Nanopore genome DNA long-read sequencing and high-throughput chromosome conformation to capture identified regions with an extreme density of structural variations [53]. These rearrangements consisted to a large degree of focal amplifications enriched in the proximity of mammalian-wide interspersed repeat elements, resulting in oncogenic fusion transcripts or the deregulation of oncogenic driver gene; this phenomenon of genomic rearrangement was defined as chromocataclysm [53]. A total of 6 of 11 (54.5%) of these patients displayed CT [53].
All these studies leave open an important question about the temporal relationship between CAG or CT and TP53 loss/mutation events: is it TP53 mutation/loss to predispose patients to CAG/CT or CAG/CT that contributes to TP53 inactivation? The double-hit TP53 pattern observed in CAG-positive patients is compatible with the hypothesis that an initial TP53 mutation/loss (first-hit) may predispose to CAG/CT development, which in turn amplifies the genomic instability, leading to a second-hit and inducing a clinically aggressive phenotype [39]. This interpretation is supported by the finding that most TP53 mutations in CK-AML are dominant-negative, and only these mutations drive loss of the remaining allele, facilitate subsequent karyotype aberrations and promote disease progression [39].
The study of MDS with del(5q) suggests the existence of two different genetic pathways that can lead to CK development. Del(5q) is a common alteration of MDS, detected in 10–20% of cases, with a higher frequency in TP53-mutated than in TP53-WT cases (55% vs. 15%) [54]. Del(5q) is observed in MDS in two different molecular types: (i) an isolated type in which del(5q) is present in MDS with low blast counts, in association with at most one additional cytogenetic aberration other than monosomy 7 or del(7q) being present and no biallelic TP53 inactivation being found; 10–20% of these cases may be associated with single-hit TP53 alterations; and (ii) a form in which del(5q) is found in the context of numerous other cytogenetic abnormalities (such as monosomy 7 or del(7q) and del(17p)) and very frequently in association with multi-hit TP53 alterations (80–90% of cases) [54]. Using genetic hierarchy analysis, it was explored whether MDS with CK, including del(5q), may arise from cases where del(5q) is the primary abnormality. To this end, Huber and coworkers analyzed a cohort of 729 MDS patients harboring a del(5q): a total of 42% of these patients had an isolated del(5q), 50% had CK, and 8% had a different condition. TP53 mutations were more frequent in CK-MDS than in MDS iso5q (87% vs. 20%, respectively) and were also more commonly multi-hit in CK-MDS compared with MDS iso5q (73% vs. 19%); additional gene mutations (such as DNMT3A, SF3B1, TET2 and ASXL1) were more frequent in MDS iso5q than in CK-MDS [54]. In these patients, there was a strong association between multi-hit TP53 alterations and CK (91% of cases) [54]. Hierarchy clonal analysis showed that most MDS-iso5q displayed del(5q) within the ancestral clone (48% of cases) and less frequently TP53 mutations in the ancestral clone (20% of cases); an opposite situation was observed for CK-MDS in which in most instances TP53 mutations are present in the ancestral clone (46% of cases) and only rarely in a del(5q) clone (6% of cases) [54]. The serial study of patients with MDS-iso5q undergoing treatment with lenalidomide showed that 24% of patients developed CK with the acquisition of TP53 alterations (in 50% of these patients had multi-hit alterations), while 69% remained with a stable karyotype without acquired TP53 alterations [54]. These observations support the existence of two separate pathways that may lead to the development of CK in MDS with del(5q): one route deriving from MDS-iso5q, which main harbors del(5q) within the ancestral clone and acquires TP53 during the evolution of the disease; and a second route arising from clones with a TP53 mutation as the ancestral abnormality, acquired later during the course of disease del(5q) in the context of a genomic instability [54].
The MyeloMATCH Molecular Diagnostic Network recently reported the characterization of 95 AML/MDS patients with CK: 72% of these patients had del(5q); 51% of these CK-del(5q) cases showed del(17p); only 15% of CK non-del(5q) showed del(17p); biallelic TP53 alterations were observed in 85% of CK-del(5q) but only in 25% of CK non-del(5q); and in CK-del(5q) cases without del(17p), biallelic and double TP53 aberrations were observed in 33.3 and 36.4%, respectively [55]. These observations showed that TP53 alterations and double TP53 mutations were predominant among AML/MDS patients with CK-del(5q), accounting for 78% of cases compared with 3.8% among those with CK-non del(5q) and 0% among those without a CK [55]. These observations further support the hypothesis that 5q loss cooperates with TP53 mutations to drive evolution to CK. Studies in an experimental model of CK-AML development supported this hypothesis. Thus, Creamer et al. have established induced pluripotent stem cells lines (iPSC) from TP53+/− and TP53+/− with del(5q) (TP53/del(5q)) preleukemic clones reprogrammed from an AML-CK patient [55]. Treatment of these clones with mitotic checkpoint inhibitors showed that TP53/del(5q) but not TP53+/− clones progressively evolved to different CK conditions, thus supporting that 5q loss cooperates with TP53 mutations to drive evolution to CK [56]. Clonal evolution of aneuploid clones was marked by stepwise acquisition of numerical and structural chromosomal changes, with some abnormalities conferring fitness advantage with consequent clonal expansion [57]. Interestingly, iPSC-derived HSPCs and primary CK-AML samples display a common conserved gene expression signature marked by upregulation of PTEN, cohesins and anti-apoptotic factor BCL2 [57].
Fernandes and coworkers have retrospectively analyzed a cohort of 25 MDS (17 patients) and AML (8 patients) with mono-hit TP53 mutations, assessed for outcome, rate of complete TP53 loss and associated with acquisition of CK and therapeutic modalities associated with this process. These patients had TP53 VAF < 40%, absent CK and alterations in 17/17p [58]. These patients received various treatments (with genotoxic and with non-genotoxic drugs), and 10 patients underwent allo-HSCT. Following their treatment, five patients developed CK, three AML and two MDS; three of these patients developed CK at relapse after allo-HSCT and two patients at relapse after first-line therapy. A total of 80% of patients who developed CK received genotoxic therapy during their treatment [58]. In total, 33.3% of patients who received genotoxic therapy developed CK disease compared with 7.7% among those who did not receive genotoxic therapy [58]. The karyotype of each of the five patients who developed CK disease showed at least seven chromosome abnormalities, and 60% displayed loss of 17/17p; the remaining 40% of patients had a significant increase in their mutational burden to >50% VAF, indicating a copy number loss of heterozygosity or microdeletion of the TP53-WT allele [58]. The OS of patients who developed CK was significantly shorter with respect to patients not developing CK. These observations suggest that MDS/AML patients with TP53 single-hit mutation have a considerable risk of progression to CK disease when treated with genotoxic agents.
Leppa and coworkers have explored intra-tumor heterogeneity by single-cell multiomics analysis in eight patients with primary CK-AML, five patient-derived matched xenografts and two matched relapse or refractory samples. The results of this analysis showed a complex structural variant landscape with a strong intra-tumor heterogeneity characterized by an average of 18.9 chromosomal alterations per cell, with interstitial structural variants, terminal gains and losses, whole chromosome aneuploidies, balanced structural variants and complex chromosomal rearrangements [59]. In each patient with CK-AML, 3–12 chromosomes harbored at least one chromosome alteration present at high cell fraction (>80%) [56]. An analysis of structural variant subclonality showed three distinct subclonal growth patterns: monoclonal; linear growth; and branched polyclonal growth. In monoclonal growth, a single subclone was dominant, while in the linear and branched samples, multiple oligoclonal or polyclonal subclones were present [59]. Samples with branched growth exhibited the highest degree of intra-tumor heterogeneity [59].
The karyotype evolution of TP53-mutated MDS and AML showed highly complex patterns of evolution. In most instances, the initial routes of tumor evolutionary branches had −5/5q and −7/7q in common and the evolution routes are very complex with karyotype evolutions involving combined branched, linear, parallel and macro-evolution; in this evolutionary process, chromosome loss was more common than chromosome gain [60].
10. Complex Karyotype in Therapy-Related Myeloid Neoplasia
Cancer patients treated with many types of cytotoxic treatment may develop secondary therapy-related tumors. One of the most frequent types of second primary cancer is represented by therapy-related myeloid neoplasms (t-MNs), which can present either as therapy-related MDS (t-MDS) or therapy-related AML (t-AML) [58]. The prognosis of t-MN is dismal due to their aggressive clinical phenotype and resistance to all current treatments, including HSCT [61].
Two initial studies showed that there are several features that distinguish t-MDS and t-AML from de novo MDS and AML, including a higher incidence of TP53 mutations, abnormalities of chromosomes 5 and 7, complex cytogenetics, and resistance to chemotherapy [62]. A pivotal study by Wong et al. provided evidence that cytotoxic therapy does not directly induce TP53 mutations but determines the expansion of pre-existing clones with TP53 mutations that are resistant to chemotherapy and expand preferentially after treatment [52]. Singhal et al. reported the analysis of mutational profile of 128 t-MN patients, compared with 108 primary MDS patients. The cytogenetic profile of t-MDS displayed several differences compared with that of p-MDS: del7/yq (18.4% vs. 6.5%), CK (28.8% vs. 8.3%), MK (28.8% vs. 8.3%), chromosomal translocations (39.2% vs. 10.2%), MK (26.4% vs. 4.6%) and marker chromosomes (20.8% vs. 1.9%) [63]. The overall mutational frequency was similar in p-MMDS and t-MDS, with some remarkable differences in the frequency of some mutations, particularly for the TP53 gene being more mutated in t-MDS than in p-MDS (29.5% vs. 7.0%, respectively); in contrast, SF3B1, U2AF1, CBL and JAK2 were more frequently mutated in p-MDS than in t-MDS [63]. The presence of TP53 mutations in t_MDS was strongly associated with CK: patients with TP53 VAF > 20% had a higher CK frequency compared with patients with TP53 VAF < 20% (83% vs. 43%, respectively) [63]. At the level of t-MDS patients, the mutational profiles of TP53-mut and TP53-WT were highly different, with frequent TET2, ASXL1, DNMT3A, SRFS2, RUNX1, KRAS and NRAS mutations among TP53-WT patients [60]. In TP53-mutated t-MDS patients, those with VAF > 20% had a lower OS than those with VAF < 20% [63]. Interestingly, in contrast to p-MDS, the ring sideroblastic phenotype was not associated with better survival in t-MN due to genetic association with TP53 mutations; in fact, TP53 mutations were detected in 92% of t-MDS with >15% of ring sideroblasts and SF3B1-WT cases [63].
Hiwase and coworkers reported the characterization of an international cohort of 377 t-MN patients (245 f-MDS and 132 t-AML); a total of 35% of these patients had TP53 mutations [61] (8.3 months vs. 21.6 months, respectively). While the survival was in line with previous studies, TP53-mut and TP53-WT patients markedly differed for their cytogenetic changes, with CK and MK being much more frequent in TP53-mut than in TP53-WT (88.6% vs. 11.5% for CK; 82.1% vs. 14.9% for MK) [64]. The comparison of cytogenetic changes among TP53-mutant patients subdivided into single-hit and multi-hit showed no significant difference [61]. The results of the analysis of the relationship between TP53 mutation parameters and clinical outcomes showed that neither the allelic status nor the BM blast percentages of t-MN provided significant prognostic information and that TP53 VAF of 10% represents a clinically useful threshold to identify patients with poor survival [64]. In a more extensive study on 488 t-MN patients by the same authors, including 182 patients TP53-mut; TP53-mut had a VAF > 10% in 88.2% of these patients [64]. TP53-mut t-MN with VAF > 10% had a distinct cytogenetic and mutational profile and clinical phenotype compared with both TP53-mut VAF < 10% and TP53-WT cases [64] (Figure 8). Importantly, TP53-mut VAF > 10% had a significantly shorter OS compared with TP53-WT (8.3 months vs. 21.6 months, respectively), while the survival of TP53-mut VAF < 10% was comparable with that of TP53-WT [65]. In the cohort of TP53-mut VAF > 10% patients, the inferior outcomes were not significantly influenced by single- or multi-hit status, co-mutation status, cytogenetic abnormalities or type of treatments received [65]. It is of interest to note that, at variance with de novo MDS, in t-MDS there was no significant difference in the cytogenetic and mutational profile between single- and multi-hit TP53 status [65]. Furthermore, the OS was not significantly different between the mono-hit and multi-hit TP53 [65]. The frequency of TP53 mutations in t-MN markedly increased with burden of chromosomal aberrations from 4.5% in normal karyotype cases to 17.3% in cases with two chromosomal alterations and 76.8% in vases with CK [65]. Even in the context of CK group, TP53-mutant cases displayed a significant increase in the number of chromosomal aberrations compared with CK-TP53-WT; more than 80% of TP53-mutant cases were segregated in t-MN with >4 cytogenetic abnormalities [65] (Figure 8). Furthermore, TP53-mutant were significantly enriched in typical compared with atypical-CK [65]. CK is associated with poor survival in t-MN patients, and the presence of TP53 mutations does not further stratify these patients, with a similar survival for CK-TP53-mut compared with CK-TP53-WT (7.7 months vs. 8.3 months) [65].
Figure 8.
Chromosome aberrations and gene mutations in t-MN patients. T-MN patients have been subdivided into three subgroups, TP53-WT, TP53-mut VAF < 10% and TP53-mut VAF > 10%, and analyzed for chromosomal aberrations (top panel) and most recurrent gene mutations (top-middle panel). Analysis of chromosome aberrations in t-MN patients have subdivided according to the presence of either multi-hit or mono-hit TP53 alterations (bottom middle panel). Analysis of chromosome aberrations into two subgroups of t-MN patients subdivided according to the presence of CK associated or not associated with TP523 mutations (bottom panel). Original data are reported in Singhal et al. [65].
Bao and coworkers reported a detailed molecular and clinical analysis of 138 L-MDS patients compared with 157 primary MDS (p-MDS) patients. The analysis of the mutational profile showed that t-MDS displayed more frequent TP53 and PPM1D mutations than p-MDS (for TP53: 32.6% vs. 9.6%; for PPM1D: 8.5% vs. 0.5%); in contrast, ASXL1, U2AF1 and SRSF2 mutations are less frequent in t-MDS than in p-MDS (for ASXL1: 7% vs. 22%; for U2AF1: 6% vs. 23.5%; for SRSF2: 0% vs. 6.5%) [66]. TP53 mutations in t-MDS were found in larger clone sizes compared with p-MDS (46.2% vs. 32.2%); this difference was particularly pronounced in single-hit cases (33% vs. 14.6%) but was also detectable in multi-hit cases (57.7% vs. 45%) [66]. A clonal hierarchy evaluation based on the analysis of TP53-mutant VAF showed that in t-MDS, TP53-mutations were almost exclusively observed in ancestral clones (99.5%), but less frequently in p-MDS (77.6%) [63]. Interestingly, in p-MDS, cases with ancestral TP53 mutations had a significantly shorter OS compared with those with non-ancestral TP53 mutations [66]. As observed in other studies, TP53 mutations identified a subset of t-MDS with great genetic instability (as evidenced by the high rate of numerous karyotypic abnormalities, including CK) and by a clearly shorter OS compared with TP53-WT cases (6 vs. 23 months, respectively) [63]. For t-MDS, the inferior outcomes of TP53-mutant MDS persisted across all the BM blasts categories (<5%, 5–10% and >10%) and all treatment types [66]. In t-MDS patients, single-hit and multi-hit TP53-mutant patients displayed similar clinical parameters, cytogenetic profiles and co-mutation patterns; furthermore, unlike p-MDS, single-hit TP53-mutant t-MDS cases had equally poor survival compared with multi-hit cases (6 months vs. 5 months, respectively) [66].
Shah and coworkers have explored the cellular origin of t-MDS from clonal cytopenias of undetermined significance (CCUS). CCUS is defined by the presence of somatic driver mutations/copy number alterations in hematopoietic cells, in patients with unexplained cytopenia in one or more peripheral blood cell lineages, in the absence of overt morphological dysplasia, excess blasts and MDS-defining chromosomal abnormalities. CCUS as well as clonal hematopoiesis of indeterminate potential (CHIP) are associated with an increased risk developing subsequent hematologic malignancies. Characterization of patients with CCUS has shown that a part of these patients can be defined as CCUS, while another part may be defined as low-risk MDS; at the molecular level, for patients with CCUS and LR-MDS, 78% of CCUS patients had ≥ 1 somatic mutation, 11% had clonal cytogenetic abnormality and only 11% had both somatic and clonal cytogenetic abnormality [67]. The mutational spectrum was similar in CCUS and LR-MDS patients, with the exception of a higher mutational rate SF3B1 in LR-MRD and a higher mutational frequency of ZRSF2 in CCUS [64]. Also, at the clinical level, there is a consistent overlap between CCUS and LR-MDS [67].
Shah et al. have identified and explored a group of patients who received DNA-damaging therapy and developed unexplained cytopenia with clonal abnormalities without morphological evidence of a myeloid neoplasm; this condition can be considered a therapy-induced CCUS (t-CCUS) [68]. In a first study, these authors compared the clinical–biological properties of CCUS, t-CCUS and t-MDS. The study of 33 t-CCUS patients showed in these patients a shorter interval from primary diagnosis to t-CCUS than to t-MDS (34.4 months vs. 79.8 months, respectively) [68]. t-CCUS patients had a lower level of abnormal cytogenetics (24.2% vs. 84.9%), CK (0% vs. 52.3%) and MK (0% vs. 50.9%) compared with t-MDS [65]. A total of 96% of t-CCUS had at least one mutation at diagnosis with a mVAF of 35%; TP53 mutations were more frequent in t-MDS than in t-CCUS (40.9% vs. 7.4%), while TET2 and DNMT3A mutations were more frequent in t-CCUS than in t-MDS (37% vs. 8% for TET2 and 14% vs. 6% for DNMT3A). The follow-up in the time of patients with t-CCUS showed an incidence of t-MN of 13%, 23% and 50% at 6 months, 1 year and 5 years, respectively [64]. The cumulative incidence of t-MN transformation was markedly lower in patients with normal cytogenetics compared with those with altered cytogenetics and with DTA (DNMT3A, TET2, ASXL2) mutations compared with those with no-DTA mutations [68]. Serial studies in t-CCUS patients progressing to t-MN showed clonal evolution with the acquisition of new cytogenetic abnormalities or new gene mutations [68]. A second study largely confirmed these findings, showing that patients with t-CCUS have a greatly increased tendency to t-MN transformation (with a follow-up of two years, 26% in t-MN compared with 15% in de novo-CCUS) [69]. Univariable and multivariable time-to-event analyses showed that exposure to cytotoxic therapy independently accounted for inferior PFS and OS of t-CCUS patients [69].
The pathogenesis of TP53-mutant MDS/AML particularly with respect to the role of TP53 allelic state (monoallelic or biallelic) and its prognostication role remained unclear and a matter of consistent discrepancies in the various studies on this topic. A recent study attempted to clarify this controversial issue through the development of novel in vitro and in vivo mouse models to investigate the role of monoallelic or biallelic TP53 mutations in the clonal expansion and leukemic progression from CHIP/CCUS to t-MDS/AML [67]. These studies provided evidence that while HSPCs with monoallelic TP53 mutations gain clonal fitness and undergo expansion but maintain genomic integrity upon chemo- or radiation therapy, HSPCs with biallelic TP53 mutations display consistent genetic instability and promote leukemic development [70]. The findings observed in these experimental models strongly support the need of biallelic TP53 inactivation to promote the genetic instability typically observed in TP53-mutant t-MDS/AML. However, these findings cannot explain the occurrence of clinical cases with only monoallelic mutations but with clinical–genomic features typical of biallelic TP53 inactivation, such as CK and poor prognosis. Thus, Fullin et al. have proposed three different explanations for these apparently paradoxical observations. First, in some instances, the accurate evaluation of TP53 allelic state could be not appropriate, particularly in conditions of subclonal biallelic inactivation though cnLOH, requiring whole genome sequencing for its optimal assessment. Second, non-mutational inactivation of TP53 though overexpression of negative regulators of p53 such as MDM2 and MDM4 could explain some cases of monoallelic TP53 inactivation that resemble the biallelic state clinico-genomically. In line with this hypothesis, recent studies have provided evidence of: MDM2 overexpression in AML samples retains WT TP53 alleles, associated with poor prognosis [71]; a defective TP53-mediated apoptosis is a subset of AML with WT TP53, associated with dismal outcomes [72]; and 5% of MDS display TP53-WT and hyperexpression of abnormal protein, associated with upstream p53 signaling aberrations in PI3K, RAS, WNT and NFkB pathways or MDM2 gene amplification and with poor survival comparable with that observed for MDS patients with biallelic TP53 mutations [73]. Third, AML/MDS cases where TP53 mutations are subclonal in the context of preceding recurrent AML/MDS initiating lesions might mimic some of the clinical–genomic features of true biallelic AML-MDS evolving from TP53-mutant clonal hematopoiesis [70]. According to the results of these studies, Fullin and coworkers propose that chemotherapy or radiation therapy through their DNA-damaging mechanisms do not directly induce TP53 mutations in hematopoietic stem/progenitor cells but promote clonal expansion and leukemia progression of pre-existing HSC/HPCs that have randomly acquired TP53 mutations during a process of naturally occurring mutagenesis related to ageing [70].
11. Treatment of MDS and AML with TP53 Mutations and/or CK
11.1. Induction Chemotherapy
There is no single universally accepted standard of care for TP53-mutant MDS and AML because they are notoriously resistant to conventional therapies and carry a very poor prognosis. Treatment approaches are primarily divided by a patient’s fitness for an allogeneic hematopoietic cell transplant (HSCT), which remains the only potentially curative approach.
For TP53-mutant MDS and AML patients, particularly those with biallelic alterations, standard therapies, including cytarabine-based regimens, as well as hypomethylating agents (HMA), such as azacytidine (AZA) or decitabine (DEC), with or without venetoclax (VEN) all lead to a similar and dismal median survival of 6–9 months. Clinical studies in primary AML patients treated with standard induction regimens, including 7 + 3 chemotherapy regimen or FLAG-IDA showed a low rate of CR, a high rate of relapse and a short OS in TP53-mutant AML, which are in large part associated with CK [74,75]. The presence of TP53 mutations in AML and MDS patients was associated with inferior OS and reduced DFS, irrespective of the associated cytogenetic abnormalities [74,75].
Both typical and atypical CK-AML displayed a poor response to standard induction chemotherapy, regardless of TP53 mutation status; in the whole population of CK-AML patients, mOS was significantly shorter for TP53-mutant compared with TP53-WT patients; and in atypical CK-AML patients, mOS was similar for both TP53-mutant and TP53-WT patients, while in atypical CK-AML patients TP53-WT had better mOS compared with TP53-mutant patients [26]. AMLs displaying the association of CK with mono-hit TP53 alteration have a shorter OS following 7 + 3 chemotherapy, similar to that observed for AMLs with multi-hit TP53 alterations [76].
Similarly to 7 + 3 chemotherapy regimen, FLAG + IDA or CPX-351 failed to significantly improve the outcomes of AML patients with TP53 mutations or with CK. Since a phase III study showed better efficacy in patients aged from 60 to 75 years in t-AML and in AML with antecedent MDS or with MDS-related cytogenetic abnormalities and since these AMLs contain a significant fraction of TP53-mutant cases, a possible efficacy of CPX-351 in the treatment of TP53-mutant AML was hypothesized. However, a careful DNA sequencing analysis and molecular reclassification of the patients treated in the context of the phase III registrational study showed that while AML-MR cases exhibit a significant benefit deriving from CPX-351 treatment, TP53-mutant cases failed to show any significant benefit related to CPX-351 treatment; TP53-multi-hit showed a worse survival with respect to TP53 mono-hit (3.8 vs. 7.0 months, respectively), but without any significant benefit of CPX-351 over 7 + 3 chemotherapy [77]. In line with these findings, Chiusolo et al. recently reported the retrospective study of 60 AML patients with t-AML or with AML-MR and observed that in these patients, the presence of CK was associated with a markedly reduced rate of responses and of OS [78].
11.2. Hypomethylating Agents and Venetoclax
AZA or DEC are currently used for the treatment of elderly AML patients or of MDS patients. In higher-risk MDS patients, AZA showed superiority compared with conventional care regimens and was approved for the treatment of these patients. However, only 30–40% of TP53-mutant MDS patients respond to AZA, with only 15–20% of CER and with a short OS, ranging from 5 to 11 months. Azacitidine alone showed very low anti-leukemic activity in TP53-mutant AMLs. DEC is another HMA currently used for the treatment of MDS patients. A single-center non-randomized clinical study showed a 100% rate of responses in 21 TP53-mutant MDS and AML patients treated with a 10-day DEC regimen compared with a rate of response of 41% in TP53-WT patients, with a mOS of 12.7 months in TP53-mutant patients compared with 15.4 months in TP53-WT patients [79]. However, these results failed to be confirmed in other studies. Thus, in a phase II trial comparing 5-day and 10-day DEC regimens, in TP53-mutant AML, the ORR was 29% and 47%, respectively, with a mOS of 5.5 and 4.9 months, respectively [80]. Similarly, Montalba-Bravo reported the response to treatment with HMAs, including DEC, in 261 MDS patients with TP53 mutations [81]. In patients treated with DEC, the ORR was 40% and 62% in those treated with AZA or guadecitabine, respectively [81]. Only 16% of patients treated with DEC achieved a CR [78]. MDS patients responding to the treatment with HMAs displayed a significant decrease in TP53 VAF following treatment, while non-responders showed either no change or increase in TP53 VAF following treatment [81].
Decitabine-cedazuridine is a combination of DEC and cedazuridine (CED), a cytidine deaminase inhibitor. DEC-CED was approved in 2020 by the FDA for the treatment of MDS. A recent study specifically evaluated the response of 180 MDS patients, including 73 (40.5%) TP53-mutant patients [79]. In this study, TP53-mut patients were classified according to WHO criteria as TP53-WT, TP53 single-hit and TP53 multi-hit [82]. The patients received 7.5 cycles of DEC-CED therapy and showed the following outcomes: the CR rates were 22.4%, 14% and 21.7% in TP53-WT, TP53 single-hit and TP53 multi-hit, respectively; the median time to loss of response was 459 days, 401 days and 249 days for TP53-WT, TP53 single-hit and TP53 multi-hit, respectively [82]. These results suggest that the TP53 status does not impact the response rate but affects the relapse rate [82]. mOS was 31.7 months, 22.1 months and 11.5 months in TP53-WT, TP53 single-hit and TP53 multi-hit, respectively [82]. A propensity-matched comparison with an institutional group of TP53-mutant MDS showed a mOS of 13.1 months for DEC-CED and 8.0 months for HMA monotherapy [82].
Two studies have evaluated the efficacy of AZA in combination with lenalidomide for the treatment of high-risk MDS, including TP53-mutant MDS. In this context, a randomized phase II study failed to show any better efficacy of AZA + lenalidomide compared with AZA alone; in this study, it was also shown that TP53 multi-hit MDS patients had a markedly reduced mOS compared with TP53-WT patients [83]. In a more recent study, Yan et al. reported the outcomes of 16 TP53-mutant MDS patients treated with AZA plus lenalidomide: the response rate for patients with CK and TP53 mutations was 46% and 56%, respectively; responding patients showed a marked decline of TP53 VAF in response to the treatment [84].
VEN and AZA are the current standard of care for patients with treatment-naïve AML who are not eligible for intensive chemotherapy, such as elderly AML patients. The outcomes of treatment-naïve AML patients harboring poor-risk cytogenetics, with or without TP53 alterations, who are unfit for intensive chemotherapy due to age ≥ 75 years and/or morbidities and who were treated with VEN + AZA or AZA alone [85]. Patients with poor-risk cytogenetics without TP53 mutations (CK 31.8–50%; 17pdel 0–4%) and patients with poor-risk cytogenetics with TP53 mutations (CK 90.7–94.4%; 17pdel 22.2–24.1%) have the following responses to treatment with VEN + AZA and AZA alone, respectively: for poor-risk cytogenetics + TP53-WT, 70% vs. 23% for CR, 18.4 vs. 8.5 months for DoR and 23.4 vs. 11.3 months for mOS; and for poor-risk cytogenetics + TP53-mutant, 41% vs. 17% for CR, 6.5 vs. 6.7 months for DoR and 5.2 vs. 4.9 months for mOS [85]. Therefore, in TP53-mutant AML patients, VEN + AZA improves CR rate but not mOS compared with AZA alone [85].
Goldfinger et al. have evaluated once weekly a metronomic schedule of DEC and VEN in patients with MDS and AML and have explored the safety and the efficacy of this regimen in a cohort of 40 TP53-mutant MDS and AML patients; a total of 70% of these patients had CK and 82% had biallelic TP53 alterations [86]. The ORR for AML was 70% and 57% for MDS; with a follow-up of 12.9 months, the mOS was 11.3 months and 10.4 months for the biallelic TP53-mutated patients [83]. These observations supported a low toxicity profile of a metronomic dosing schedule of DEC and VEN, associated with a better profile in terms of OS compared with standard VEN + AZA. Zheng et al. have explored another regimen based on cycles of 9–14 days of VEN, associated with 3-day DEC in a group of 23 TP53-mutant AML patients; a total of 86.9% of patients had multi-hit TP53 alterations [86]. The ORR was 78%, with a CR rate of 73.9%; mOS was 8 months [86].
Other studies have explored the efficacy of VEN added to chemotherapy regimens. DiNardo and coworkers have explored the safety and the efficacy of VEN added to FLAG-IDA in ND and R/R AML patients [87]. In the whole population of 77 ND AML patients the CR rate was 95%, with a 3-year OS of 66%. Among the ND cohort, six patients had TP53 mutations; a total of 100% of these patients achieved a CR, but with a short DoR of 8 months and a mOS of 13 months (compared with a mOS not reached in TP53-WT ND AML patients) [88]. In the R/R cohort of 61 patients, among TP53-WT patients, the 3-year OS was 51%, while among TP53-mutant patients, the 3-year OS was only 13% [85]. Ruhnke et al. have evaluated the safety and the efficacy of VEN plus high-dose cytarabine and mitoxantrone as salvage treatment for R/R AML patients, also including 11% of TP53-mutant patients [86]. Patients with TP53 mutations or CK with or without TP53 mutations had a markedly reduced mOS compared with patients without TP53 mutations and/or CK [89].
A recent study phase I/II study explored DEC-CED in combination with VEN in 60 high-risk MDS and nine CMML patients; a total of 25% of these patients had TP53 mutations, mostly being multi-hit TP53 (15/17). Patients with TP53 mutations had a mOS of 17 months, compared with a mOS of 31 months for TP53-WT patients [90]. The combination of DEC-CED with VEN seems to be a feasible combination with a high rate of responses in high-risk MDS.
Eprenetapopt (APR-246) is a first-in-class small molecule that reactivates p53 and targets cellular redox balance, inducing apoptosis and ferroptosis in TP53-mutNT cancer cells. APR-246 acts as a prodrug that needs to be converted to methylene quinuclidinone, a compound that binds to cysteine residues in mutant p53, inducing thermodynamic stabilization of the p53 protein and shifting its conformation to a functional protein. APR-246 synergistically with AZA induces apoptosis of TP53-mutant MDS/AML cells, and thus, this drug combination was evaluated into two parallel phase II clinical studies [91,92]. A recent study reported the combined analysis of these two trials involving a total of 100 TP53-mutant MDS and AML patients, showing the following results: an ORR of 69% and 41% CR, mOS of 11.8 months and a mDoR of 10.2 months [93]. Patients who achieved MRD negativity (TP53 VAF < 0.1%) had a 2-year OS of 33% compared with 19% in patients without MRD negativity [89]. mOS was significantly improved early in patients who underwent HSCT in CR or MRD negativity compared with those who underwent HSCT with active disease (mOS 26.7 months vs. 9.1 months, respectively) [93].
11.3. Mechanisms of Resistance to Venetoclax
In TP53-mutant MDS and AML, resistance to venetoclax is a major clinical challenge. While about half of these patients may show initial responses, remissions are typically brief, and the median overall survival remains poor, around 6 to 8 months.
Emerging evidence suggests that TP53 mutations promote venetoclax resistance through multiple mechanisms, including apoptotic dysregulation, metabolic reprogramming, enhancement of leukemic stem cell properties and epigenetic remodeling, with a relative major contribution of apoptotic deregulation. Studies in experimental models of TP53-mutant AML cells showed that resistance to venetoclax resulted from an inability to execute apoptosis driven by BAX loss, decreased expression of BCL2 and/or reliance on alternative BCL2 family member, such as BCL-XL; resistance was accompanied by changes in mitochondrial homeostasis and cellular metabolism [94]. A recent study provided evidence that resistance to venetoclax is primarily driven by a post-mitochondrial block where TP53-mutant AML cells experience defective caspase-3/-7 activation [95]. AML cells exhibit selective failure in apoptosis induction. Despite inhibition of pro-apoptotic BAX and selective enrichment in TP53-mutant AML cells, compensatory upregulation of BIM preserved a functional capacity to induce mitochondrial outer membrane permeabilization (MOMP); however, TP53-mutant AML cells exhibited a complete incapacity to activate executioner caspase-3/-7 and, through this mechanism, evade apoptosis after venetoclax-azacitidine, decoupling the mitochondrial and executioner phases of apoptosis [95]. Thus, this study showed a critical post-mitochondrial defect in TP53-mutant cells as a key driver of leukemia chemoresistance.
11.4. Factors Predicting the Response to Induction Treatment
In CK or TP53-mutant MDS or AML patients, there are not well-established pre-therapy prognostic indicators of the response to induction therapy with chemotherapy or with HMAs. Some studies have identified some predictors of CR and 25-month OS. Thus, Kaur et al. explored a group of 242 patients with TP53-mutated MN ≥ 10% of blasts receiving frontline therapy with IC (26%) or HMA + VEN (74%). The overall CR rate was 25.6%; pre-therapy factors predictive of inferior CR included ≥2 autosomal monosomies, −17/17p, multi-hit TP53 allelic state and CUX1 gene co-mutations; predictive factors for shorter OS24 were ≥2 autosomal monosomies and TP53 VAF > 25% [96]. In a subgroup analysis of patients treated with HMA + VEN, TP53 VAF and monosomies did not impact OS24 [96]. Mutations/Deletions at the level of CUX1, U2AF1, EZH2, TET2, CBL and KRAS (EP6 signature) predicted inferior OS24 [96]. A multivariable, age-adjusted analysis extended to a cohort of 325 TP53-mutated MN patients with >10% of blasts showed that EP16 signature was predictive of OS24 in the whole cohort, as well as in patients treated with HMA + VEN [96]. A more recent study by the same authors extended the analysis to 495 TP53-mutated MN patients, including all the groups of MDS patients, also comprising those with <5% BM blasts (29% MDS and 71% AML). In the analysis of predictors of response to induction treatment, a new parameter was also included: the analysis of the proportion of clonal cells in the karyotype, independent of specific genetic alterations, with a cut-off of 50% to distinguish <50% CK from >50% CK [97]. The analysis of baseline characteristics of all these TP53-mutated MN patients showed that CK < 50 differed from CK > 50 mostly for CK, −17/17p loss and TP53 VAF, but also for blast number, −5/5q [98]. Among patients uniformly treated with HMA-based regimens, only higher CK50 predicted a reduced CR rate, while among patients treated with IC, neither CK50 nor blast counts predicted frontline response [98]. For patients who underwent allo-HSCT, outcomes were similar for CK < 50 and CK > 50 [95]. In the OS24 analysis, blast cell counts stratified at a 20% cut-off were only marginally associated with worse OS24, while CK and CK50 predicted significantly shorter outcomes; OS was significantly superior for the TP53 single-hit allelic state compared with TP53 multi-hit allelic state (9.7 months vs. 7.3 months, respectively) [98]. In a multivariable analysis including all TP53 allelic state determinants, only CK50 and CK remained relevant for predicting adverse outcomes [98].
A recent study retrospectively compared the response to induction IC or HMA regimens in a cohort of 358 AML patients with very-high risk cytogenetics (CK or MK) [96]. Cytogenetic features of these patients included CK in 90.2%, MK in 64% and inv(3;3)/t(3;3) in 9.8% of cases; TP53 was mutated in 51% of these patients [99]. Frontline therapy was IC in 40% and HMA + VEN in 60% of cases [93]. Median OS for these patients was 8 months compared with 31 months in an AML group without high-risk cytogenetics [99]. No overall survival differences were observed by frontline treatment (for the whole cohort, CR rate with IC and HMA + VEN was 55% vs. 54%, respectively; mOS 7.7 months vs. 6.6 months; for TP53-mutated AML, mOS was 8.1 months vs. 5.8 months; after allo-HSCT, mOS was 35 months vs. 25 months) [99]. Furthermore, no significant OS difference was seen between IC and HMA + VEN among patients aged 60–75 years [99]. Therefore, given equivalent efficacy and similar early mortality, HMA + VEN represents a reasonable frontline option for patients aged 60–75 years with high-risk cytogenetics or with TP53 mutations [99].
11.5. Allo-HSCT
Allogeneic hematopoietic stem cell transplantation (allo-HSCT) is the only potentially curative treatment strategy for patients with TP53-mutant MDS or AML. Various studies have provided evidence that allo-HSCT may improve outcomes of TP53-mutant MDS and AML patients compared with those of patients not undergoing HSCT. Thus, Badar et al. reported the survival of 68 TP53-mutant AML patients who underwent allo-HSCT after first induction or after salvage therapy; a total of 43% of these patients received myeloablative conditioning and 57% received reduced-intensity conditioning [100]. The mEFS was 12.4 months and mOS 24.5 months; patients who received allo-HSCT in CR after first induction had better outcomes compared with those who underwent allo-HSCT after salvage therapy [97]. These observations suggest that allo-HSCT offers the best opportunity to improve long-term outcomes among patients with TP53-mutant AML. A retrospective study at MD Anderson Cancer Center, Texas, USA, on 122 MDS and 291 TP53-mutant patients confirmed that allo-HSCT significantly improved OS compared with patients not receiving allo-HSCT both in MDS and AML patients [101]. The OS post-allo-HSCT was markedly longer for MRD-negative compared with MRD-positive patients at transplantation [98]. In line with these observations, Bewersdorf et al. reported the clinical experience of a single center in the treatment of a cohort of 83 TP53-mutated AML patients [102]. In this study, 11 patients underwent allo-HSCT and had a significantly longer median OS compared with patients treated with intensive chemotherapy or other lower-intensity treatments [102].
However, the presence of CK, found in most TP53-mutant myeloid neoplasms, was enriched with considerably shortened OS. Thus, Yoshizato and coworkers in a large cohort of 797 MDS patients who underwent allo-HSCT showed that the presence of CK clearly reduced OS of both TP53-WT and TP53-mutated patients with respect to the corresponding patients without CK due to a very high rate of relapse, which was particularly elevated in TP53-mutant/CK patients [100]. Importantly, the OS observed for TP53-mutated patients without CK was comparable with that observed for TP53-WT patients [103]. A similar conclusion was reached by Loke et al., who reported the outcomes of a cohort of 780 AML patients who underwent allo-HSCT: in the 179 TP53-mutant AML patients, the 2-year OS was significantly reduced compared with TP53-WT patients (35.1% vs. 64%, respectively) [104]. In patients with TP53-mutated AML with no evidence of either chromosome 17p loss and/or CK, the 2-year OS was comparable with that observed for TP53-WT patients [104]. These observations suggest that the adverse prognostic effect of TP53-alterations on allo-HSCT requires the concomitant presence of either 17p loss and/or CK [104].
Baranwat and coworkers have reported the results observed in a multicenter study on 134 TP53-mutant MN who underwent allo-HSCT, 80% harbored CK; 94% of TP53 mutant variants were localized to the DBD [105]. Overall survival at 1 year, 2 years and 3 years was 51.4%, 35.1% and 25.1%, respectively [105]. Only 76.9% (103 cases) of these met the ICC criteria for MN with TP53-mutations; the 3-year OS of ICC-defined TP53-mutated MN was markedly shorter in comparison with the other TP53-mutant cases excluded by the ICC [102]. In both MDS and AML patients, allo-HSCT significantly improved mOS compared with patients who did not undergo allo-HSCT [105]. The mOS of TP53-mutated AML patients who underwent allo-HSCT with MRD negative status was significantly longer compared with TP53-mutated AML patients transplanted with an MRD-positive condition; this observation was also confirmed in a subpopulation of TP53-mutated high-risk patients (TP53-mutated multi-hit) [105]. In multivariate analysis, TP53-mutated AML patients defined as “low-risk” (single TP53 mutation, VAF < 40%) had significantly better survival post-HSCT compared with patients defined as “high-risk” (with >1 TP53 mutation, one mutation plus allelic deletion or a single mutation with VAF > 40%) [105]. The presence of CK negatively affected survival of AML patients [105].
Lontos et al. explored the factors associated with clinical benefit in a cohort of 240 TP53-mutated MDS (114) and AML (126) who underwent allo-HSCT; a total of 71% of these patients had CK, 69% had multi-hit TP53 on mono-hit allelic status, respectively, and 50% and 50% of patients had TP53-mutated with VAF < 59% or >50% [106]. The most favorable prognostic factors for PFS were absence of CK, 5q deletion, 7q deletion, a lower VAF, a mono-hit status and use of a matched-related donor for HSCT [106]. VAF and cytogenetics were the two most important prognostic factors: TP53-muant VAF > 50% had a 2-year PFS of 3%; patients with VAF < 50% and CK/5q/7q cytogenetic abnormalities had a 2-year PFS of 22%; and patients with VAF < 50% and without CK/5q/7q cytogenetic abnormalities had a 2-year PFS of 60% [106].
In a retrospective analysis on 66 TP53-mutant MDS and AML patients who underwent allo-HSCT, it was shown that the presence of <2 myeloid gene co-mutations was strongly associated with poor outcomes, particularly in patients who combine this property with CK and/or 17p deletion [107].
The Consortium on Myeloid Malignancies and Neoplastic Diseases (COMMAND) evaluated the prognostic impact of multi-hit (MH) versus single-hit (SH) TP53 alterations in 3872 MN patients [108]. A total of 55 of these patients underwent allo-HSCT and showed that allo-HSCT improves OS in both SH and MH patients; in SH patients, the benefit deriving from HSCT was more pronounced in patients without CK [108].
Gomez-Arteaga et al. have used the CIBMTR Registry to investigate outcomes of AML patients with TP53 alterations undergoing HSCT; these patients were subdivided into three groups: group 1 (TP53-mutated/TP53-deleted, CK 61%), group 2 (TP53-deleted, CK 54%) and group 3 (TP53-mutated, CK 6%) [109]. The results of these analyses showed that in group 1, 2 and 3 of TP53-mutated patients, the OSs were 18%, 18% and 35% [106]. In multivariate analysis, TP53 deletion was independently associated with higher relapse risk and shorter OS [109]. Li et al. have used the EBMT registry to explore the outcomes of 185 TP53-mutant AML patients who underwent allo-HSCT with active disease at transplantation [110]. With a median follow-up of 3 years, the 2-year OS was 20.5% and was not significantly improved among different types of donors [107]. Thus, allo-HSCT for AML patients with active disease confers a modest survival benefit [110].
An extensive meta-analysis based on 33 studies involving 2526 MDS patients undergoing allo-HSC showed that both TP53 mutation status (single-hit, multi-hit) and TP53-mutant VAF (<30% or >30%) predicted poorer outcomes in MDS patients recipient of allo-HSCT [111].
A recent retrospective study by Bazinet and coworkers reported the analysis of outcomes of 427 high-risk MDS patients undergoing allo-HSCT. By multivariate analysis, TP53 status resulted as the most important predictor of post-HSCT OS: patients with TP53-WT had an OS of 69% at 5 years, and the mOS was not reached; patients with monoallelic TP53 alterations had a mOS of 9.1 months and those with biallelic alterations a mOS of 6.8 months [112]. Importantly, when TP53-mutant patients were stratified by cytogenetic complexity, those without CK had a mOS of 123.1 months compared with a mOS of 8.3 months in those with CK [112].
Many TP53-mutant MDS and AML patients do not achieve a CR following induction treatment with intensive chemotherapy or with venetoclax-based regimens. Few studies have evaluated the feasibility and the outcomes for TP53-mutant MDS and AML patients not transplanted at CR. Steiner et al. reported the results of a retrospective analysis on 81 patients with TP53-mutated MDS or AML (30 with single-hit and 51 with multi-hit mutations) who underwent allo-HSCT at the University of Hamburg, Germany [113]. In the whole cohort of patients, the 3-year OS and LFS were 25% and 23% for patients with AML and 43% and 30% for patients with MDS [113]. Interestingly, the 3-year OS (34% vs. 28% vs. 42%) and LFS (32% vs. 26% vs. 26%) rates were comparable among patients transplanted in CR, in non-CR and in those untreated at allo-HSCT, respectively [113]. Patients with single-hit TP53 mutations had OS comparable with those with multi-hit TP53 mutations but had a higher LFS rate [113]. Thus, this study suggests that TP53-mutant AML and MDS patients should be considered as transplant candidates even if they are not in CR.
The administration of post-transplant maintenance therapy, with the capacity of either enhancing a graft-versus-leukemia or delivering anti-leukemic activity after transplantation, represents a promising strategy to try to improve outcomes of allo-HSCT in MDS and AML patients. The administration of HMAs, such as AZA, post-transplant as maintenance therapy in MDS/AML patients yielded conflicting results. AZA maintenance after HSCT produced unsatisfactory results in a phase III clinical trial, showing no improvement in OS and RFS in patients receiving AZA post-transplant compared with controls [114]. However, a retrospective-matched study showed benefit deriving from AZA maintenance post-transplant in high-risk MDS/AML patients, including some TP53-mutant patients with MRD-positive disease [115].
A phase I clinical study evaluated the safety and the efficacy of prophylactic maintenance therapy with VEN and AZA for patients with high-risk MDS/AML patients undergoing reduced-intensity allo-HSCT after VEN and fludarabine/busulfan conditioning (VEN/FluBu2 allo-HSCT) [116]. A total of 22 MDS/AML patients received this treatment and 16 had TP53-mutant disease, and all patients were in CR at transplantation. In the 22 treated patients, the 2-year OS, PFS, non-relapse mortality and cumulative incidence of relapse rates were 67%, 59%, 0% and 41% [116]. A total of 52% of TP53-mutant patients were MRD-positive at transplantation. Among the 16 patients with TP53 mutations, 9 relapsed and 7 remained in remission; in the seven patients in remission, MRD negativity was reached by day +100 in four cases and after day +100 in three cases, suggesting that in some patients the conditioning regimen was sufficient to suppress clone expansion after HSCT, while in other patients maintenance therapy contributed to eradication after HSCT [116]. In a more recent study, the same authors have investigated 30 high-risk MDS/AML patients undergoing VEN/FluBu2 allo-HSCT, followed by maintenance therapy using VEN + DEC-CED; a total of 63% of these patients had TP53 patients (15/19 had TP53 multi-hit state) [117]. The 2-year OS was 77%, 56% and 31% for TP53-WT, TP53 single-hit and TP53 multi-hit patients, respectively [117]. OS of TP53-mutant patients with MRD-negative at day 100 post-HSCT was markedly better compared with MRD-positive patients at day 100 post-HSCT; in 50% of TP53-mutated patients positive at day 1000 post-HSCT, TP53 mutation clearance was obtained at 6 and 12 months of maintenance therapy [117].
Sallman and coworkers evaluated AZA + APR-246 as maintenance therapy in 14 TP53-mutant AML patients undergoing allo-HSCT [118]. A total of 57% of these patients were MRD-positive at the first evaluation post-HSCT; achieving MRD negativity at any time post-HSCT was predictive of RFS and EFS but not OS; The MRD evaluation after the end of maintenance therapy was the strongest predictor of outcomes; a total of 75% of the four patients negative at the end of maintenance therapy did not relapse [118].
A recent study reported the cases of three patients with TP53-mutated MN who achieved durable CR after a sequential strategy consisting of limited pre-transplant therapy, prompt allo-HSCT after reduction of the TP53-positive clone, and early dose-adjusted AZA maintenance [119]. According to these results, it was suggested that in TP53-mutated MN, pre-transplant therapy should be considered as a bridge to allo-HSCT that should be performed early when the TP53-positive clone has decreased, rather than prolonging the noncurative induction therapy; AZA maintenance therapy should be initiated early after HSCT [119].
The studies carried out in MDS and AML patients with CK and/or TP53 mutations have shown that a minority of these patients may greatly benefit from allo-HSCT; however, it remains to be determined how to prospectively select this minority of patients whom it might benefit. Therefore, dedicated prospective randomized trials are required to provide criteria for selecting TP53-mutated MDS/AML patients who may derive a consistent benefit for allo-HSCT.
12. Conclusions
A CK in MDS and AML is defined by the presence of three or more unrelated chromosomal abnormalities in the absence of favorable, recurring translocations. Recent studies have defined CK in AML and MDS not as a simple count of ≥3 chromosome abnormalities but a heterogeneous disease frequently driven by TP53 mutations and massive structural catastrophes, such as chromothripsis. The mechanisms of CK development in MNs was only in part elucidated and is highly interconnected with the loss of critical DNA repair mechanisms and tumor suppressor pathways. The main drivers of CK development include TP53 gene mutations and deletions, causing loss of cell cycle checkpoint control and genomic instability. The genomic instability promotes gross chromosomal rearrangements, such as chromothripsis and chromoplexy, underlying the generation of multiple chromosomal aberrations via catastrophic, single-event genomic crises.
These studies have clearly shown that CK-AML and MDS without (less frequent) and with (more frequent) TP53 mutations represent two groups with a clearly poorer prognosis for the TP53-mutant group compared with the TP53-WT group. Models of leukemogenesis have suggested a specific sequence of events, characterized first by events of TP53 mutations (dominant-negative TP53 mutations), followed by the deletion or loss of the remaining WT allele, and once the two copies of TP53 alleles are functionally lost, genomic instability is generated with a cascade of karyotypic abnormalities.
This advancement in the understanding the mechanisms of TP53 alterations and CK development were not accompanied by an improvement in the treatment of TP53-mutated MNs, whose prognosis remains dismal. These clinical studies have clearly shown that the main aim of induction treatment of TP53-mutant MNs is represented by a bridge to allo-HSCT. Consistent efforts have been made in the development of drugs able to target mutant p53, but at the moment they are associated with very limited therapeutic success.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The author declares no conflict of interest.
References
- Nguyen-Khac, F.; Bidet, A.; Daudignon, A.; Lafage-Pochitaloff, M.; Ameye, G.; Bilhou-Nabéra, C.; Chapiro, E.; Collonge-Rame, M.A.; Cuccuini, W.; Couet-Guilbert, N.; et al. The complex karyotype in hematological malignancies: A comprehensive overview by the Francophone group of Hematologica Cytogenetics (FFCH). Leukemia 2022, 36, 1451–1456. [Google Scholar] [CrossRef] [Scilit]
- Song, Q.; Peng, M.; Chu, Y.; Huang, S. Techniques for detecting chromosomal aberrations in myelodysplastic syndromes. Oncoatrget 2017, 8, 62716–62729. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smith, O.; Poveda-Rogers, C.; Laczko, D.; Yang, G.; Morrissette, J. Cytogenetics and genomics of acute myeloid leukemia. Best Pract. Res. Clin. Hematol. 2024, 37, 101533. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Torres-Hernandez, N.; Mora, E.; Gracia-Ruiz, C.; Diaz-Gonzalez, A.; Avetisyan, G.; Martinez-Campusano, D.; Berenguer-Rubio, A.; Botella, C.; Benet, C.; Gomez-Catalan, I.; et al. Optical genome mapping as a high-resolution tool for uncovering cytogenetic complex and cryptic alterations in a cohort of patients with MDS and AML. npj Precis. Oncol. 2026, 10, 85. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Levy, B.; Burnside, R.D.; Akkari, Y. Optical genome mapping: A new tool for cytogenomic analysis. Genes 2025, 16, 924. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khoury, J.D.; Solary, E.; Abla, O.; Akkari, Y.; Alaggio, R.; Apperley, J.F.; Bejar, R.; Berti, E.; Busque, L.; Chan, J.; et al. The 5th edition of the World Health Organization classification of hematolymphoid tumors: Myeloid and histiocytic/dendritic neoplasms. Leukemia 2022, 36, 1703–1719. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arber, D.A.; Orazi, A.; Hasserjian, R.P.; Borowitz, M.J.; Clavo, K.R.; Kwanisnicka, H.M.; Wang, S.A.; Bagg, A.; Barbui, T.; Branford, S.; et al. International consensus classification of myeloid neoplasms and acute leukemias: Integrating morphologic, clinical, and genomic data. Blood 2022, 140, 1200–1228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Komrokji, R.S.; Lanino, L.; Ball, S.; Bewersdorf, J.; Marchetti, M.; Maggioni, G.; Travaglino, E.; Al Ali, N.; Fenaux, P.; Platzbecker, U.; et al. Data-driven, harmonised classification system for myelodysplastic syndromes: A consensus paper from the International Consortium for Myelodysplastic Syndromes. Lancet Oncol. 2024, 11, e862–e872. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stengel, A.; Meggendorfer, M.; Walter, W.; Baer, C.; Nadarajah, N.; Hutter, S.; Kern, W.; Haferlach, T.; Haferlach, C. Interplay of TP53 allelic state, blast count, and complex karyotype on survival of patients with AML and MDS. Blood Adv. 2023, 7, 5540–5548. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shah, M.V.; Hung, K.; Baranwal, A.; Kutyna, M.M.; Al-Kali, A.; Toop, C.; Greipp, P.; Brown, A.; Shah, S.; Khanna, S.; et al. Evidence-based risk stratification of myeloid neoplasms harboring TP53 mutations. Blood Adv. 2025, 9, 3370–3380. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shah, M.V.; Hung, K.; Baranwal, A.; Wexhalekar, G.; Al-Kali, A.; Toop, C.; Greipp, P.; Kutyna, M.M.; Matin, A.; Ladon, D.; et al. Validation of the 5th edition of the World Health Organization and International Consensus Classification guidelines for TP53-mutated myeloid neoplasm in an independent international cohort. Blood Cancer J. 2025, 15, 88. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hart, S.A.; Lee, L.A.; Seegmiller, A.C.; Mason, E.F. Diagnosis of TP53-mutated myeloid disease by the ICC and WHO fifth edition classification. Blood Adv. 2025, 9, 445–454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Montoro, M.J.; Palomo, L.; Haferlach, C.; Acha, P.; Chan, O.; Navarro, V.; Kubota, Y.; Schulz, F.I.; Meggendorfer, M.; Briski, R.; et al. Influence of TP53 gene mutations and their allelic status in myelodysplastic syndromes with isolated 5q deletion. Blood 2024, 144, 1722–1731. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Montoro, M.J.; Acha, P.; Haferlach, C.; Chan, O.; Navarro, V.; Kubota, Y.; Schulz, F.I.; Briski, R.; Al Ali, N.; Xicoy, B.; et al. How should myelodysplastic neoplasms with isolated deletion of 5q and TP53 multihit alterations be classified? Leukemia 2026, 40, 1448–1453. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yasin, I.; Stengel, A.; Shao, H.; Kaur, A.; Mason, E.F.; Patwardhan, P.P.; Bailey, N.G.; Ghosh, S.; Inamdar, K.V.; Patel, A.A.; et al. Characterization of chromosome 5 aberrations in TP53 mutated myeloid neoplasms with >5% blasts: An international TP53 investigators network (iYiN) study. Cancer 2026, 132, e70210. [Google Scholar] [PubMed]
- Stolzel, F.; Mohr, B.; Oelschlagel, U.; Botchler, T.; Berdel, W.E.; Kaufmann, M.; Bladus, C.D.; Schafer-Eckart, K.; Struhlmann, R.; Einsele, H.; et al. Karyotype complexity and prognosis in acute myeloid leukemia. Blood Cancer J. 2016, 6, e386. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bataller, A.; Bazinet, A.; Montalban-Bravo, G.; Chien, K.; Hammond, D.; Bouligny, I.; Senapati, J.; Sasaki, K.; Issa, G.; Short, N.; et al. Complex cytogenetic in myeloid malignancies: A deconstruction analysis redefining complex karyotypes. Blood 2025, 146, 5641–5642. [Google Scholar] [CrossRef] [Scilit]
- Chilton, L.; Hills, R.K.; Harrison, C.J.; Burnett, A.K.; Grimwade, D.; Moorman, A.V. Hyperploidy with 49-65 chromosome represents a heterogeneous cytogenetic subgroup of acute myeloid leukemia with differential outcomes. Leukemia 2014, 28, 321–328. [Google Scholar] [PubMed]
- Hezaveh, E.B.; Yan, J.; Zhao, D.; Wangulu, C.; Lo, W.; Wei, C.; Chang, H. Genetic landscape and risk stratification of AML with hyperdiploid karyotype. Eur. J. Haematol. 2025, 115, 165–175. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dohner, H.; Wei, A.H.; Appelbaum, F.R.; Craddock, C.; Di Nardo, C.D.; Dombret, H.; Ebert, B.L.; Fenaux, P.; Godley, L.A.; Hasserjian, R.P.; et al. Diagnosis and management of AML in adults: 2022 recommendations from an international expert panel on behalf of the ELN. Blood 2022, 140, 1345–1377. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, Z.; Fu, C.; Sun, Y.; Liu, Y.; Wang, Q.; Yan, W.; Wu, C.; Wang, Q.; Zeng, Z.; Wen, L.; et al. High hyperdiploid karyotype with ≥49 chromosomes represents a heterogeneous subgroup of acute myeloid leukemia with differential TP53 mutation status and prognosis: A single-center study from Chine. Ann. Hematol. 2024, 103, 2337–2346. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Poiré, X.; Labopin, M.; Polge, E.; Gnaser, A.; Socié, G.; Gedde-Dahl, T.; Forcade, E.; Finke, J.; Chalandon, Y.; Bulabois, C.E.; et al. Allogeneic hematopoietic cell transplantation for acute myeloid leukemia with hyperdiploid complex karyotype. Bone Marrow Transplant. 2024, 59, 264–269. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mroçzek, K.; Eisfeld, A.K.; Kohlschmidt, J.; Carroll, A.; Walker, C.; Nicolet, D.; Blachly, J.; Bill, M.; Papaioannu, D.; Wang, E.; et al. Complex karyotype in de novo acute myeloid leukemia: Typical and atypical subtypes differ molecularly and clinically. Leukemia 2019, 33, 1620–1634. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ussmann, J.; Weigwert, A.; Bischof, L.; Brauer, D.; Backaus, D.; Diener, C.; Merz, M.; Vucinic, V.; Metzler, K.H.; Platzbecker, K.H.; et al. Impact of typical and atypical complex karyotype subgroups on outcome of AML patients undergoing allogeneic stem cell transplantation. Blood 2023, 142, 2244–2245. [Google Scholar] [CrossRef] [Scilit]
- Baslan, T.; Belleau, P.; Dschenes, A.; Zhang, Y.; Sun, Z.; Garett-Bakelman, F.; Kleppe, M.; Paietta, E.; Cripe, L.; Fernandez, U.; et al. Sparse whole genome sequencing and machine learning of AML genomes reveals novel, clinically relevant genetics. Blood 2025, 146, 5263–5264. [Google Scholar] [CrossRef] [Scilit]
- Yoshida, S.; Onozawa, M.; Miyashita, N.; Kimura, H.; Takahashi, S.; Yokoyama, S.; Matukawa, T.; Hirabayashi, S.; Mori, A.; Hidaka, D.; et al. Clinical features of complex karyotype in newly diagnosed acute myeloid leukemia. Int. J. Hematol. 2023, 117, 544–552. [Google Scholar] [PubMed]
- Breems, D.A.; Van Putten, W.; De Greef, G.; Van Zelderen-Bhola, S.; Gressen-Schoorl, K.; Mellink, K.; Nieuwint, A.; Jotterand, M.; Hagerneijer, A.; Beverloo, B.; et al. Monosomal karyotype in acute myeloid leukemia: A better indicator of poor prognosis than a complex karyotype. J. Clin. Oncol. 2008, 26, 4791–4797. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yokoyama, H.; Yanada, M.; Mizuno, S.; Uchida, N.; Shigai, N.; Fukuda, T.; Tanaka, M.; Yoshihara, S.; Nishida, T.; Sawa, M.; et al. Prognostic factors influencing outcomes of allogeneic HCT for AML with monosomal karyotype. Int. J. Hematol. 2026, 123, 746–753. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Patnaik, M.M.; Hanson, C.A.; Hodnefield, J.M.; Knudson, R.; Van Dyke, D.L.; Tefferi, A. Monosomal karyotype in myelodysplastic syndromes, with or without monosomy 7 or 5, is prognostically worse that in otherwise complex karyotype. Leukemia 2011, 25, 266–270. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vlacarcel, D.; Ademà, V.; Solé, F.; Ortega, M.; Nomdedeu, B.; Sanz, G.; Luno, E.; Canizo, C.; de la Serna, J.; Ardanaz, M.; et al. Complex, non monosomal, karyotype is the cytogenetic maker of poorest prognosis in patients with primary myelodysplostic syndrome. J. Clin. Oncol. 2013, 31, 916–922. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jo, T.; Arai, Y.; Oshima, S.; Kondo, T.; Harada, K.; Uchida, N.; Goki, N.; Fukuda, T.; Tanaka, M.; Ozawa, Y.; et al. Prognostic impact of complex/or monosomal karyotypes in post-transplant poor cytogenetic acute myeloid leukemia; a quantitative analysis. Br. J. Haematol. 2023, 202, 356–368. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jeyakumar, N.; Torres, N.; Godbole, S.; Yamamoto, F.; Zhang, B.; Arai, S.; Bharadwaj, S.; Dahiya, S.; Elmariah, H.; Frank, M.; et al. Patients with TP53-mutated AML/MDS without complex or monosomal karyotype can achieve durable survival benefits with allogeneic HCT. Blood 2025, 146, 2525–2526. [Google Scholar] [CrossRef] [Scilit]
- Jambhekar, A.; Ackerman, E.E.; Alpay, B.A.; Lahav, G.; Lovitch, S.B. Comparison of TP53 mutations in myelodysplasia and acute leukemia suggests divergent roles in initiation and progression. Blood Neoplasia 2024, 1, 100004. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boettcher, S.; Miller, P.G.; Sharma, R.; McConkey, M.; Leventhal, M.; Krivstov, A.; Giacomelli, A.; Wong, W.; Kim, J.; Chao, S.; et al. A dominant-negative effect drives selection of TP53 missense mutations in myeloid malignancies. Science 2019, 365, 599–604. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wong, T.N.; Link, D.C. Are TP53 mutations all alike? ASH Educ. Program 2024, 2024, 321–325. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rucker, F.; Schlenk, R.; Bullinger, L.; Kayser, S.; Telaenu, V.; Kett, H.; Habdank, M.; Kugler, C.M.; Holzmann, K.; Gaidzik, V.; et al. TP53 alterations in acute myeloid leukemia with complex karyotype correlated with specific copy number alterations, monosomal karyotype, and dismal outcome. Blood 2012, 119, 2114–2121. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weinberg, O.; Siddon, A.; Madanat, Y.; Gagan, J.; Arber, D.A.; DalCin, P.; Narayan, D.; Ouseph, M.; Kurzer, J.; Hasserjian, R. TP53 mutation defines a unique subgroup within complex karyotype de novo and therapy-related MDS/AML. Blood Adv. 2022, 6, 2847–2853. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grob, T.; Al Hinai, A.; Sanders, M.; Kavelaars, F.; Rijken, M.; Grodowska, P.; Biemond, B.; Breems, D.; Maertens, J.; Van Marwijk, M.; et al. Molecular characterization of mutant TP53 acute myeloid leukemia and high-risk myelodysplastic syndrome. Blood 2022, 139, 2347–2354. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fedenko, A.; Czapinska, H.; Kramer, A.; Stolzel, F.; Bochtler, T.; Bochtler, M. Etiology of TP53 mutated complex karyotype acute myeloid leukemia. Leukemia 2026, 40, 444–448. [Google Scholar] [PubMed]
- Haase, D.; Stevenson, K.; Neuberg, D.; Maciejewski, J.P.; Nazha, A.; Sekeres, M.; Ebert, B.; Garcia-Manero, G.; Haferlach, C.; Haferlach, T.; et al. TP53 mutation status divides myelodysplastic syndromes with complex karyotypes into distinct prognostic subgroups. Leukemia 2019, 33, 1747–1758. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bernard, E.; Nannya, Y.; Hasserjian, R.; Devlin, S.; Tuechler, H.; Medina-Martinez, J.; Yoshizato, T.; Shiozawa, Y.; Saiki, R.; Malcovati, L.; et al. Implications of TP53 allelic state for genome stability, clinical presentation and outcomes in myelodysplastic syndromes. Nat. Med. 2020, 26, 1549–1556. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lu, X.; Ma, X.; Zhang, K.; Zhang, S.; Wei, F.; Jiang, H.; Jiang, Q.; Chang, Y.; Huang, X.; Zhao, X. Low-VAF-mutated AML displays distinct biological features in a single-center cohort. Biomedocones 2026, 14, 180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pellenter, F.; Gaillard, J.B.; Puechberty, J.; Gatinois, V. Chromoanagenesis, the mechanism of a genomic chaos. Semin. Cell Dev. Biol. 2022, 123, 90–99. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stephens, P.J.; Greenman, C.D.; Fu, B.; Yang, F.; Bignell, G.R.; Mudie, L.J. Massive genomic rearrangement acquired in a single catastrophic event during cancer development. Cell 2011, 144, 27–40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rausch, T.; Jones, D.T.; Zapatka, M.; Srtutz, A.M.; Zicher, T.; Weischenfeldt, J. Genome sequencing of pediatric medulloblastoma links catastrophic DNA rearrangements with TP53 mutations. Cell 2012, 148, 59–71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fontana, M.C.; Marconi, G.; Milosevic Feenstra, J.; Fonzi, E.; Papayannidis, C.; Luserna di Rorà, A.G.; Padella, A.; Solli, V.; Franchini, E.; Ottaviani, E.; et al. Chromothripsis in acute myeloid leukemia: Biological features and impact on survival. Leukemia 2018, 32, 1609–1620. [Google Scholar] [CrossRef] [PubMed]
- Rucker, F.; Dolnik, A.; Blatte, T.; Teleanu, V.; Ernst, A.; Thol, F.; Heuser, M.; Gnaser, A.; Dohner, H.; Döhner, K.; et al. Chromothripsis is linked to TP53 alteration, cell cycle impairment, and dismal outcome in acute myeloid leukemia with complex karyotype. Haematologica 2018, 103, e17–e20. [Google Scholar] [PubMed]
- Nacheva, E.; Boneva, T.; O’Nions, J.; Wilson, A.J.; Xu, K.; Baker, R.; Gupta, R. Chromoanagenesis in hematological malignancy: Review of samples from patients with acute leukemia and MDS. Blood 2023, 142, 1564–1565. [Google Scholar] [CrossRef] [Scilit]
- Abel, H.; Oetjien, K.; Miller, C.; Ramakrishnan, S.; Day, R.; Helton, N.; Fronick, C.; Fulton, R.; Heath, S.; Tarnawski, S.; et al. Genomic landscape of TP53-mutated myeloid malignancies. Blood Adv. 2023, 7, 4586–4598. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wei, Q.; Hu, S.; Loghavi, S.; Toruner, G.; Ravandi-Kashanani, F.; Tang, Z.; Li, S.; Xu, J.; Daver, N.; Medeiros, J.; et al. Choromoanagenesis iof frequently associated with highly complex karyotypes, extensive clonal heterogeneity, and treatment refractoriness in acute myeloid leukemia. Am. J. Hematol. 2025, 100, 417–426. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bochtler, T.; Granzow, M.; Stolzel, F.; Kunk, C.; Mohr, B.; Kartal-Kaess, M.; Hinderhofer, K.; Heilig, C.; Kramer, M.; Thiede, C.; et al. Marker chromosomes can arise from chromothripsis and predict adverse prognosis in acute myeloid leukemia. Blood 2017, 129, 1333–1342. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fuse, K.; Tanaka, T.; Shibasaki, Y.; Furukawa, T.; Narita, M.; Sino, H.; Masuko, M. Marker chromosome is a strong poor prognosis factor after allogeneic HSCT for adverse-risk AML patients. Eur. J. Hematol. 2020, 105, 616–625. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Klever, M.K.; Starng, E.; Hetzel, S.; Jungnitsch, J.; Dolnik, A.; Schopflin, R.; Schrezenmeier, J.F.; Schick, F.; Blau, O.; Westermann, J.; et al. AML with complex karyotype: Extreme genomic complexity revealed by combined long-read sequencing and Hi-C technology. Blood Adv. 2023, 7, 6520–6531. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huber, S.; Hutter, S.; Baer, C.; Meggendorfer, M.; Hoermann, G.; Kern, W.; Haferlach, T.; Haferlach, C. Two ways to complex karyotype in MDS-the role of del(5q) and TP53. Leukemia 2025, 15, 96. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fang, M.; Othus, M.; Kropeger, K.; Ngueyn, T.; Qu, X.; Wood, B.; Harris, L.; Erba, H.; Radich, J.; Little, R.; et al. Biallelic TP53 aberrations and double TP53 mutations are prevalent in AML/MDS patients with del(5q) complex karyotype-an NCI myelomatch and SWOG report. Blood 2025, 146, 5276. [Google Scholar] [CrossRef] [Scilit]
- Creamer, J.P.; Ray, S.; Stewart, S.; Appelbaum, J.S.; Fang, M.; Swisher, E.; Doulatov, S. Loss of 5q drives evolution to aneuploidy in an iPSC model of complex karyotype AML. Blood 2024, 144, 629–630. [Google Scholar] [CrossRef] [Scilit]
- Creamer, J.P.; Ray, S.; Stewart, S.; Gulsuner, S.; Saliba, A.; Wu, J.; Huang, F.; Leppa, A.M.; Wang, B.; Abbas, H.; et al. Chromosome 5q deletion drives evolution of aneuploidy in myeloid neoplasms with complex karyotype. Leukemia, 2026; in press. [CrossRef] [Scilit] [PubMed]
- Fernandes, P.; Pasca, S.; Jain, T.; Levis, M.; Ambinder, A.; Walsh, L.; Gojo, I.; Smith, D.; Webster, J.; Ghiaur, G.; et al. Evolution to complex karyotype disease in mono-allelic TP53-mutated myelodysplastic syndrome/acute myeloid leukemia: A cohort study. Haematologica, 2026; in press. [CrossRef] [Scilit] [PubMed]
- Leppa, A.M.; Grimes, K.; Jeong, H.; Huang, F.; Andrades, A.; Waclawiczek, A.; Boch, T.; Jauch, A.; Renders, S.; Stelman, P.; et al. Single-cell multiomics analysis reveals dynamic clonal evolution and targetable phenotypes in acute myeloid leukemia with complex karyotype. Nat. Genet. 2024, 56, 2790–8203. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Matsumoto, Y.; Kato, D.; Muramatsu, A.; Sugitani, M.; Kobayashi, T.; Iwai, T.; Mori, M.; Motooka, D.; Nakata, J.; Ogawa, S.; et al. Karyotype evolution of myelodysplastic syndrome and acute myeloid leukemia with TP53 mutations. Int. J. Hematol. 2025, 121, 792–800. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Singhal, D.; Kutyna, M.; Shah, M.Y.; Hiwase, D. Therapy-related myeloid neoplasms: Complex interactions among cytotoxic therapies, genetic factors, and aberrant microenvironment. Blood Cancer Discov. 2024, 5, 400–416. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wong, T.; Ramsimngh, G.; Young, A.; Miller, C.A.; Touma, W.; Welch, J.S.; Lamprecht, T.; Shen, D.; Hundal, J.; Fulton, R.S.; et al. Role of TP53 mutations in the origin and evolution of therapy-related acute myeloid leukemia. Nature 2015, 518, 552–557. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Singhal, D.; Wee, L.W.; Kutyna, M.; Chhetri, R.; Gheogegan, J.; Schreiber, A.; Feng, J.; Wang, P.; Babic, M.; Parker, W.; et al. The mutational burden of therapy-related myeloid neoplasms is similar to primary myelodysplastic syndrome had a distinctive distribution. Leukemia 2019, 33, 2842–2853. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hiwase, D.; Hahn, C.; Tran, E.; Chhetri, R.; Baranwal, A.; Al_Kali, A.; Sharplin, K.; Ladon, D.; Hollins, R.; Greipp, P.; et al. TP53 mutation in therapy-related myeloid neoplasm defines a distinct molecular subtype. Blood 2023, 141, 1087–1091. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shah, M.V.; Tran, E.; Shah, S.; Cchetri, R.; Baranwal, A.; Ladon, D.; Shultz, C.; Al_kali, A.; Brown, A.L.; Ceng, D.; et al. TP53 mutation variant allele frequency of ≥10% is associated with poor prognosis in therapy-related myeloid neoplasms. Blood Cancer J. 2023, 13, 51. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bao, Z.; Li, B.; Qin, T.; Xu, Z.; Qu, S.; Jia, Y.; Li, C.; Pan, L.; Gao, Q.; Jiao, M.; et al. Molecular characteristics and clinical implications of TP53 in therapy-related myelodysplastic syndromes. Blood Cancer J. 2025, 15, 58. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, M.; Binder, M.; Ferrer, A.; Gangat, N.; Al-Kali, A.; Mangaonkar, A.; Eliott, M.; Litzow, M.; Hogan, W.; Pardanani, A.; et al. Clinical, molecular, and prognostic comparisons between CCUS and lower-risk MDS: A study of 187 molecularly annotated patients. Blood Adv. 2021, 5, 2272–2278. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shah, M.V.; Mangaonkar, A.A.; Begna, K.H.; Alòkhateeb, H.B.; Greipp, P.; Nanaa, A.; Elliott, M.A.; Hogan, W.J.; Litzow, M.R.; McCullough, K.; et al. Therapy-related clonal cytopenia as a precursor to therapy-related myeloid neoplasms. Blood Cancer J. 2022, 12, 106. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, M.; Baranwal, A.; Gurney, M.; Shah, S.N.; Al_kali, A.; Alkhateeb, H.; Foran, J.; Yi, C.A.; Ongle, L.; Chen, D.; et al. The impact of cytotoxic therapy on the risk of progression and death in clonal cytopenias of undetermined significance. Blood Adv. 2024, 8, 3130–3139. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fullin, J.; Topcu, E.; Zielinska, K.; Schimmer, R.R.; Klemm, N.; Koch, C.; Caiado, F.; Lock, M.; Doederlmann, C.; Buhler, M.; et al. The pathogenesis of therapy-related myeloid neoplasms from TP53-mutant clonal hematopoiesis. Leukemia 2026, 40, 279–292. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Quintàs-Cardana, A.; Hu, C.; Qutub, A.; Qiu, Y.; Zhang, X.; Post, S.M.; Zhang, N.; Coomber, K.; Kornblau, S.M. p53 pathwayy dysfunction is highly prevalent in acute myeloid leukemia independent of TP53 mutational status. Leukemia 2017, 31, 1296–1305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dubois, J.; Palmer, A.; King, D.; Rizk, M.; Bedi, K.; Shedden, K.; Malek, S. Patients with AML, with WT TP53 but defective TP53-mediated apoptosis have a dismal survival. JCI Insight 2026, 11, e197261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zampini, M.; Riva, E.; Lanino, L.; Sauta, E.; Dos Reis, R.; Ejarque, R.M.; Maggioni, G.; Termanini, A.; Meriott, A.; Campagna, A.; et al. Characterization and clinical implications of p53 dysfunction in patients with myelodysplastic syndromes. J. Clin. Oncol. 2025, 43, 2069–2083. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bowen, D.; Groves, M.J.; Burnett, A.K.; Patel, Y.; Allen, C.; Green, C.; Gale, R.E.; Hills, R.; Linch, D.C. TP53 gene mutation is frequent iFallinn patients with acute myeloid leukemia and complex karyotype and is associated with very poor prognosis. Leukemia 2009, 23, 203–206. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seifert, H.; Mohr, B.; Thiede, C.; Oelschlagel, U.; Schakel, U.; Illmer, T.; Soucek, S.; Ehninger, G.; Schaich, M. The prognostic impact of 17p (pp53) deletion in 2272 adults with acute myeloid leukemia. Leukemia 2009, 23, 656–663. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rausch, C.; Rothenbrg-Thuley, M.; Dufour, A.; Schneider, S.; Gittimger, H.; Sauerland, C.; Gorlich, D.; Krug, U.; Berdell, W.; Woermann, B.E.; et al. Complex karyotype is an independent risk factor in TP53-mutated AML. HemaSphere 2023, 7, 753–759. [Google Scholar] [CrossRef] [Scilit]
- Shimony, S.; Murdock, H.M.; Keating, J.; Tsai, H.; Sasi, A.; Gibson, C.; Faderl, S.; Wagner, A.; Dronaramju, N.; Lin, T.; et al. CPX-351 selectively benefits patients with AML with myelodysplasia-related mutations in the pivotal randomized trial. Blood Adv. 2026, 10, 2854–2864. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chiusolo, P.; Fianchi, L.; Frioni, F.; Giammarco, S.; Metafuni, E.; Limongiello, M.A.; Quattrone, M.; Criscuolo, M.; Giordano, A.; Sica, S.; et al. Determinants of survival in patients treated with CPX-351 for acute myeloid leukemia. Front. Oncol. 2026, 16, 1813333. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Welch, J.S.; Petti, A.A.; Miller, C.A.; Fronick, C.C.; Laughlin, M.; Fulton, R.S.; Wilson, R.K.; Baty, J.D.; Duncavage, E.J.; Tandon, B.; et al. TP53 and decitabine in acute myeloid leukemia and myelodysplastic syndromes. N. Engl. J. Med. 2016, 375, 2023–2036. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Short, N.J.; Kantarjian, H.M.; Loghavi, S.; Huang, X.; Qiao, W.; Borthakur, G.; Kadia, T.M.; Daver, N.; Ohanian, M.; DiNardo, C.D.; et al. Treatment with a 5-day versus a 10-day schedule of decitabine in older patients with newly diagnosed acute myeloid leukemia: A ranodmised phase 2 trial. Lancet Hematol. 2019, 6, e29–e37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Montalban-Bravo, G.; Kanagal-Shamanna, R.; Benton, C.B.; Class, C.A.; Chien, K.S.; Sasaki, K.; Naqvi, K.; Alvarado, Y.; Kadia, T.M.; Ravandi, F.; et al. Genomic context and TP53 allele frequency define clinical outcomes in TP53-mutated myelodysplastic syndromes. Blood Adv. 2020, 4, 482–493. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Urrutia, S.; Sasaki, K.; Bataller, A.; Kantarjian, H.; Montalban-Bravo, G.; McCloskeyy, J.; Griffiths, E.A.; Yee, K.; Zeidan, A.; Savona, M.; et al. Decitabine-cedazuridine in patients with MDS and TP53 mutations. Blood Adv. 2026, 10, 881–886. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rasmussen, B.; Gohring, G.; Bernard, E.; Nilsson, L.; Tobiasson, M.; Jadersten, M.; Garelius, H.; Dibedai, I.; Grenbaek, K.; Ejerblad, E.; et al. Randomized phase II study of azacytidine ± lenalidomide in higher-risk myelodysplastic syndromes and acute myeloid leukemia with a karyotype including Del(5q). Leukemia 2022, 36, 1436–1438. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yan, X.; Song, C.; Ge, Z. High efficacy of azacytidine combined with lenalidomide in TP53 mutation-positive and other high-risk myelodysplastic neoplasms. Blood 2025, 146, 2082–2083. [Google Scholar] [CrossRef] [Scilit]
- Pollyea, D.A.; Pratz, K.W.; Wei, A.H.; Pullarkat, V.; Jonas, B.A.; Recher, C.; Babu, S.; Schuh, A.C.; Dail, M.; Sun, Y.; et al. Outcomes in patients with poor-risk cytogenetics with or without TP53 mutations treated with venetoclax and azacytidine. Clin. Cancer Res. 2022, 28, 5272–5279. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goldfinger, M.; Mantzaris, I.; Shastri, A.; Rockwell, B.; Saunthararajah, Y.; Yin, S.; Levitz, D.; Gritsman, K.; Sica, A.R.; Kornblum, N.; et al. Treatment of TP53-mutated myelodysplastic syndrome and acute myeloid leukemia with low intensity metronomic decitabine and venetoclax. Haematologica, 2026; in press. [CrossRef] [Scilit] [PubMed]
- Zheng, F.; Suo, X.; Liu, J.; Zhao, L.; Bai, G.; Zhao, X.; Bai, Y.; Wang, D.; Mi, Y.; Liu, K. Venetoclax combined with three-day multi-frequency decitabine (DEC3-VEN) as induction treatment in newly diagnosed acute myeloid leukemia with TP53-mutation. Blood 2025, 146, 3395–3396. [Google Scholar] [CrossRef] [Scilit]
- DiNardo, C.D.; Jen, W.Y.; Takahashi, K.; Kadia, T.; Loghavi, S.; Daver, N.G.; Xiao, L.; Reville, P.K.; Issa, G.C.; Short, N.J.; et al. Long term results of venetoclax combined with FLAG-IDA induction and consolidation for newly diagnosed and relapsed or refractory acute myeloid leukemia. Leukemia 2025, 39, 854–863. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ruhnke, L.; Schliemann, C.; Milkersch, J.H.; Stelljes, M.; Fransecky, L.; Steffen, B.; Kaufmann, M.; Burchert, A.; Rank, A.; Hanoun, M.; et al. Ventoclax plus high-dose cytarabine and mitoxantrone as salvage treatment for relapsed or refractory acute myeloid leukemia/RELAX): A multicenter, single-arm, phase ½ trial. Lancet Hematol. 2026, 13, e157–e168. [Google Scholar]
- Bataller, A.; Bouligny, I.; Bazinet, A.; Montalban-Bravo, G.; Chien, K.; Hammond, D.; Sasaki, K.; Valero, Y.A.; Issa, G.; Short, N.; et al. Oral decitabine/cedazuridine in combination with venetoclax in treatment-naïve high-risk myelodysplastic syndrome or chronic myelomonocytic leukemia: Updates of a phase ½ clinical trial. Blood 2025, 146, 237–238. [Google Scholar] [CrossRef] [Scilit]
- Cluzeau, T.; Sebert, M.; Rahmé, R.; Cuzzubbo, S.; Lehman-Che, J.; Madelaine, I. Eprenetapopt plus azatididine in TP53-mutated myelodysplastic syndromes and acute myeloid leukemia: A phase II study by the group francophone des myelodysplasies (GFM). J. Clin. Oncol. 2021, 39, 1575–1583. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sallman, D.A.; DeZern, A.E.; Garcia-Manero, G.; Steensma, D.P.; Roboz, G.; Sekeres, M.A. Eprenetapopt (APR-246) and azcitidine in TP53-mutant myelodysplastic syndromes. J. Clin. Oncol. 2021, 39, 1584–1594. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sallman, D.A.; Kromrokji, R.S.; Dezern, A.E.; Sebert, M.; Garcia-Manero, G.; Rahmé, R.; Winer, E.S.; Lehmann-Che, J.; Roboz, G.; Madelaine, I.; et al. Long-term follow-up and combined phase 2 results of eprenetapopt and azacytidine in patients with TP53 mutant MDS/AML. HemaSphere 2025, 9, e70164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nechiporuk, T.; Kurtz, S.E.; Nikolova, O.; Liu, T.; Jones, C.; D’Alessandro, A.; Culp-Hill, R.; D’Almeida, A.; Joshi, S.K.; Rosenberg, M.; et al. The TP53 apoptotic network is a primary mediator of resistance to BCL2 inhibition in AML cells. Cancer Discov. 2019, 9, 910–925. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mmadouh, A.; Olesinki, E.; Lim, F.; Jasdanwala, S.; Mi, Y.; Lin, N.; Liang, D.; Chitkara, N.; Hogdal, L.; Lindsley, C.; et al. TP53 mutations drive therapy resistance via post-mitochondrial caspase blockade. bioRxiv 2025. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kaur, A.; Rojek, A.; Symes, E.; Nawas, M.T.; Patel, A.A.; Patel, J.L.; Sojitra, P.; Aqil, B.; Sukhanova, M.; McNerney, M.; et al. Real world predictors of response and 24-month survival in high-grede TP53-mutated myeloid neoplasms. Blood Cancer J. 2024, 14, 99. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Symes, E.; Wang, P.; Sojitra, P.; Menon, M.; Patel, A.A.; Hasan, F.; Ghosh, S.; Roloff, G.W.; Zhou, Q.; Findley, A.; et al. Somatic co-alteration signatures are prognostic in high-grade TP53-mutated myeloid neoplasms. Br. J. Haematol. 2025, 206, 1103–1108. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pandiri, M.; Stengel, A.; Zhang, J.; Wang, P.; Shao, H.; Velmurugan, S.; Jacob, A.; Symes, E.; Kaur, A.; Rojek, A.; et al. Karyotypic clonal fraction predicts adverse outcome in TP53-mutated myeloid neoplasms: An international TP53 investigators network (iTiN) study. J. Clin. Pathol. 2025, 78, 629–635. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aguirre, L.E.; Bewersdof, J.P.; Liu, Y.Y.; Shallis, R.; Boussi, L.; Zucenka, A.; Garciaz, S.; Bystrom, R.; DeAngelo, D.; Stone, R.M.; et al. Comparative effectiveness of HMA with venetoclax vs intensive chemotherapy in AML with very high-risk cytogenetics. Blood Neoplasia 2026, 3, 100201. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Badar, T.; Atallah, E.; Shallis, R.; Saliba, A.N.; Patel, A.; Bewrsdorf, J.; Grenet, J.; Stahl, M.; Duvall, A.; Burkart, M.; et al. Survival of TP53-mutated acute myeloid leukemia patients receiving allogeneic stem cell transplantation after first induction or salvage therapy: Results from the Consortium on myeloid malignancies and neoplastic diseases (COMMAND). Leukemia 2023, 37, 799–806. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Senapati, J.; Loghavi, S.; Garcia-Manero, G.; Tang, G.; Kadia, T.; Short, N.J.; Abbas, H.A.; Arani, N.; DiNardo, C.D.; Bothakur, G.; et al. Clinical interrogation of TP53 aberrations and its impact on survival in patients with myeloid neoplasms. Hematologica 2025, 110, 1304–1315. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bewersdorf, J.P.; Shallis, R.M.; Gowda, L.; Wei, W.; Hager, K.; Isufi, I.; Kim, T.K.; Pillai, M.; Seropian, S.; Podoltsev, N.A.; et al. Clinical outcomes and characteristics of patients with TP53-mutated acute myeloid leukemia or myelodysplastic syndrome. A single center experience. Leuk. Lymphoma 2020, 61, 2180–2190. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yoshizato, T.; Nannya, Y.; Atsuta, Y.; Shiozawa, Y.; Lijima-Yamashita, Y.; Yoshida, K.; Shiraishi, Y.; Suzuki, H.; Nagata, Y.; Sato, Y.; et al. Genetic abnormalities in myelodysplasia and secondary acute myeloid leukemia: Impact on outcome of atem cell transplantation. Blood 2017, 129, 2347–2358. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Loke, J.; Labopin, M.; Craddock, C.; Cornelissen, J.J.; Labussiere-Wallet, H.; Wagner-Drouet, E.M.; Van Gorkom, G.; Schaap, N.; Kroger, N.; Veelken, J.H.; et al. Additional cytogenetic features determine outcome in patients allografted for TP53 mutant acute myeloid leukemia. Cancer 2022, 128, 2922–2931. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baranwal, A.; Langer, K.J.; Gannamani, V.; Rud, D.; Cibich, A.; Saygin, C.; Nawas, M.; Badar, T.; Kharfan-Dabaja, M.A.; Ayala, E.; et al. Factors associated with survival after allogeneic transplantation for myeloid neoplasms harboring TP53 mutations. Blood Adv. 2025, 9, 3395–3407. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lontos, K.; Saliba, R.M.; Kanagal-Shamanna, R.; Ozcan, G.; Ramdial, J.; Chen, G.; Kadia, T.; Short, N.J.; Daver, N.G.; Kantarjian, H.; et al. TP53-mutant variant allele frequency and cytogenetics determine prognostic groups in MDS/AML for transplantation. Blood Adv. 2025, 9, 2845–2853. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sun, Y.; Qin, S.; Wang, L.; Yi, H.; Ding, L.; Cai, B.; Liu, N.; Li, Y.Y.; Hu, J.; Qiao, Z.; et al. The prognostic impact of myeloid co-mutation burden in TP53-mutated AML/MDS after allogeneic stem cell transplantation: A multicenter retrospective analysis. Ann. Hematol. 2026, 105, 168. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Badar, T.; Nanaa, A.; Atallah, E.; Shallis, R.M.; Craver, E.C.; Li, Z.; Goldberg, A.; Saliba, A.; Patel, A.; Bewersdorf, J.; et al. Prognostic impact of multi-hit versus single-hit TP53 alteration in patients with acute myeloid leukemia: Results from the consortium for myeloid malignancies and neoplastic diseases. Haematologica 2024, 109, 3533–3545. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gomez-Arteaga, A.; Shallis, R.; Nawas, M.; Guo, L.; Oloyede, T.; Ahn, K.W.; Bachanova, V.; Byerne, M.; Girallt, S.; Gowda, L.; et al. Acute myeloid leukemia (AML) with TP53 alterations and outcomes after aloogeneic hematopoietic tsem cell transplantation: A CIBMTR registry study. Blood 2025, 146, 1060–1061. [Google Scholar] [CrossRef] [Scilit]
- Li, L.; Ye, Y.; Thibeault Ferhat, A.; Kroger, N.; Schroeder, T.; Stelljes, M.; Blau, I.-W.; Zeiser, R.; Passweg, J.; Bethge, W.; et al. Allogeneic hematopoietic cell transplantation in TP53-mutated acute myeloid leukemia patients with active disease: A study from the global committee and the acute leukemia working party of the EBMT. Blood 2025, 146, 2523–2524. [Google Scholar] [CrossRef] [Scilit]
- Park, D.; Sanders, J.; Khattra, M.; Miles, K.; Demardenosian, A.; Woan, W.; Tam, E.; Yaghmour, G. Prognostic impact of TP53 mutation status and variant allele frequency in myelodysplastic syndromes: A meta-analysis of prognosis and transplant outcomes. Blood 2025, 146, 7393. [Google Scholar] [CrossRef] [Scilit]
- Bazinet, A.; Bataller, A.; Chien, K.; Sasaki, K.; Montablan-Bravo, G.; Hammond, D.; Bouligny, I.; Swaminathan, M.; Jen, W.Y.; Kugler, E.; et al. Impact of allogeneic stem cell transplantation in patients with higher risk myelodysplastic syndromes. Blood Cancer J. 2026, 16, 48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Steiner, N.; Klyuchnikov, E.; Badbaran, A.; Massoud, R.; Gagelmann, N.; Rudolph, I.; Heidenreich, S.; Wolf, D.; Zeck, G.; Lueck, C.; et al. Remission status prior to allogeneic stem cell transplantation in acute myeloid leukemia/myelodysplastic syndrome patients harboring single-hit or multi-hit p53 mutations does not impact outcome. Transplant. Cell Ther. 2026, 32, 182–190. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oran, B.; de Lima, M.; Garcia-Manero, G.; Thall, P.F.; Lin, R.; Popat, U.; Alousi, A.M.; Hosing, C.; Giralt, S.; Rondon, G.; et al. A phase I randomized study of 5-azacitidine maintenance vs observation after transplant in high-risk AML and MDS patients. Blood Adv. 2020, 4, 5580–5588. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Paskovsky, O.; Saliba, R.M.; Popat, U.; Alousi, A.; Mehta, R.; Yeh, J.; Al-Atrash, G.; Adeel, M.; Ramdial, J.; Marin, D.; et al. Azacitidine post-transplant maintenance improves disease progression in high-risk acute myeloid leukemia and myelodysplastic syndrome. Clin. Lymphoma Myeloma Leuk. 2024, 24, e196–e204. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Garcia, J.S.; Kim, H.T.; Murdock, H.M.; Ansuinelli, M.; Brock, J.; Cutler, C.S.; Goopptu, M.; Ho, V.T.; Koreth, J.; Nikiforow, S.; et al. Prophylactic maintenance with venetoclax/azacytidine after reduced intensity conditioning allogeneic transplant for high-risk MDS and AML. Blood Adv. 2024, 8, 978–990. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Garcia, J.S.; Kim, H.T.; Murdock, H.M.; Bosch-Vilaseca, A.; Panaro, K.M.; Lim, F.; Fiorilla, J.; Auriemma, E.; Brock, J.; Goopptu, M.; et al. Venetoclax/FluBu2 RIC transplant followed by all oral venetoclax/decitabine maintenance for poor-risk MDS/AML. Blood Adv. 2026, 10, 1548–1558. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sallman, D.A.; McLemore, A.; Komrokji, R.; Elmariah, H.; Kuykendall, A.T.; Bejanyayn, N.; Chan, O.; Faramand, R.; Pidala, J.; Yoder, S.J.; et al. Posttransplant MRD monitoring by TP53 duplex sequencing with APR-246+azacytidine maintenance predicts outcomes. Blood Adv. 2026, 10, 1053–1056. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yamagata, F.; Yoshihara, K.; Nannya, Y.; Samori, M.; Takahashi, S.; Kumamoto, T.; Fujita, Y.; Utsunomiya, N.; Yoshihara, S. Ealy transplantation after pretransplant reduction of TP53-altered clones and prolonged dose-adjusted azacytidine maintenance: A three-case series. Eur. J. Hematol. 2026, 7, e70315. [Google Scholar]

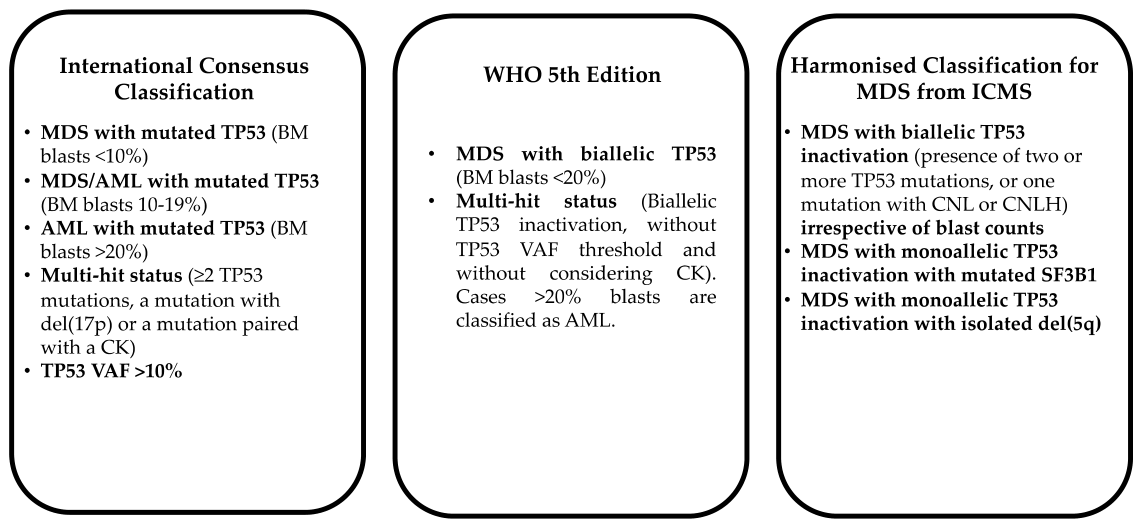
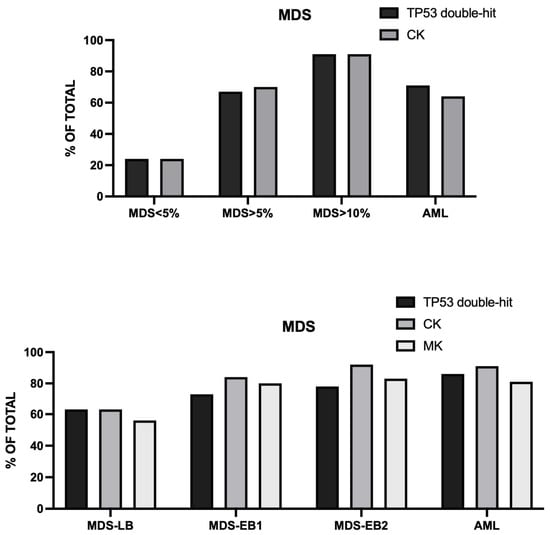
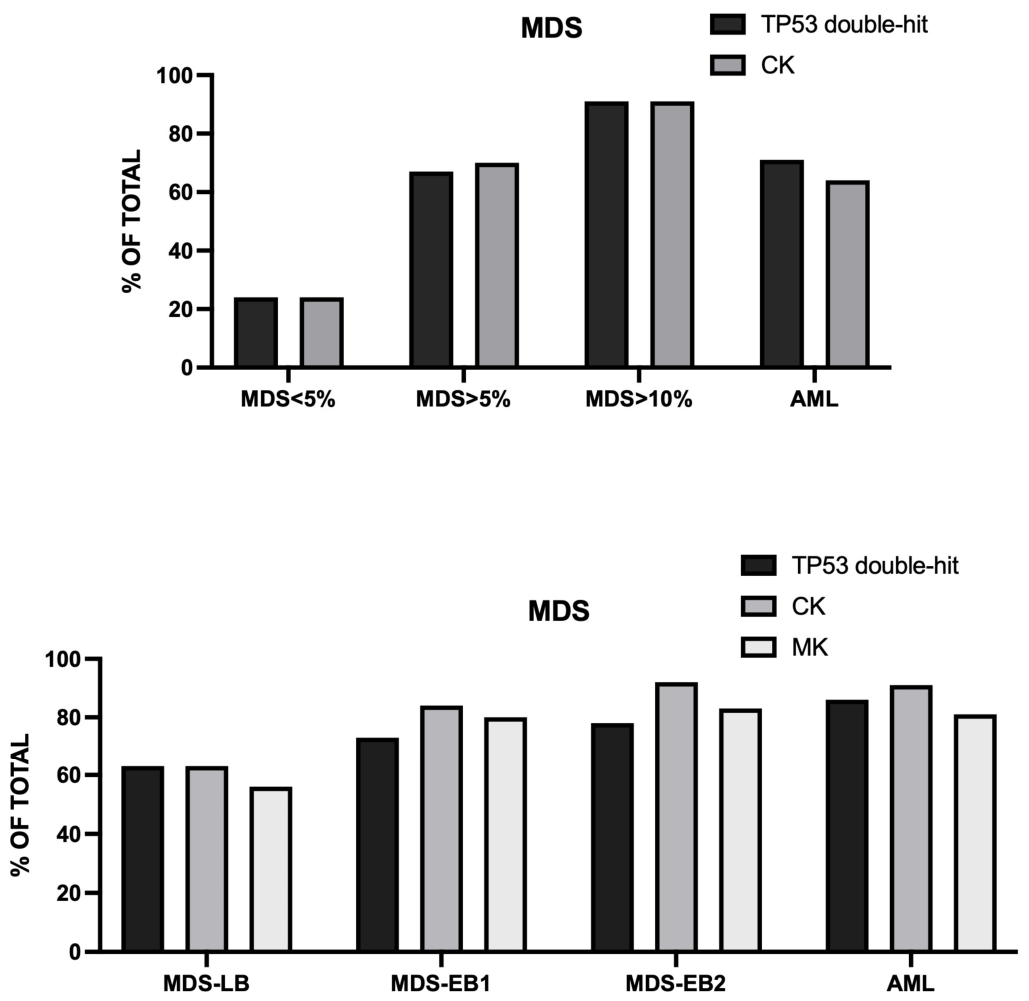
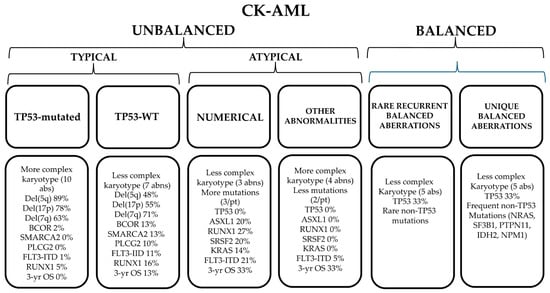
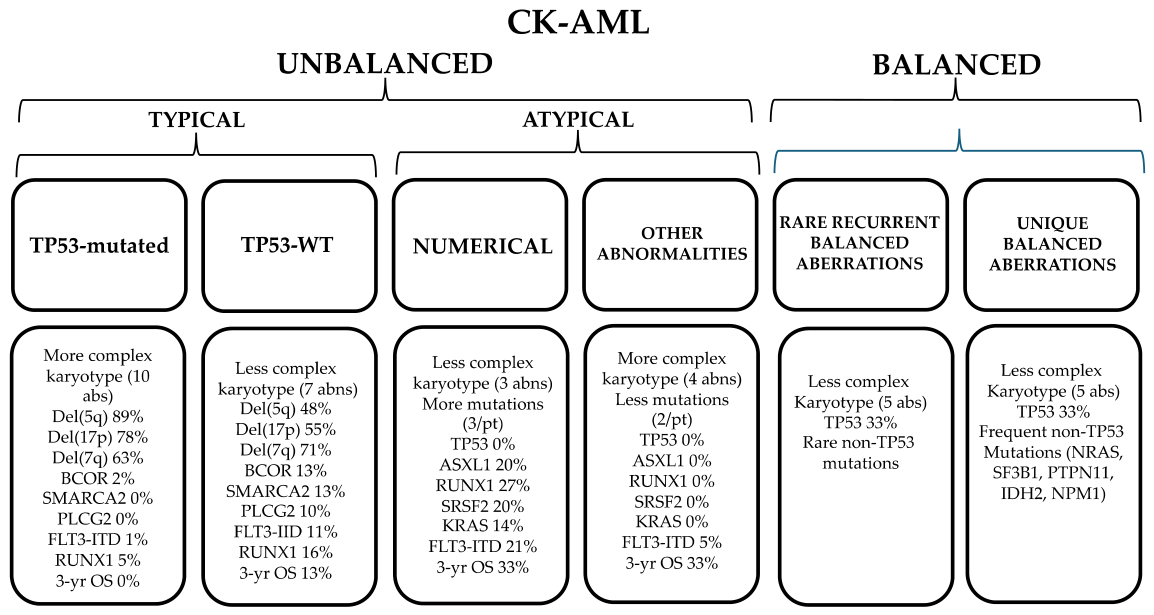
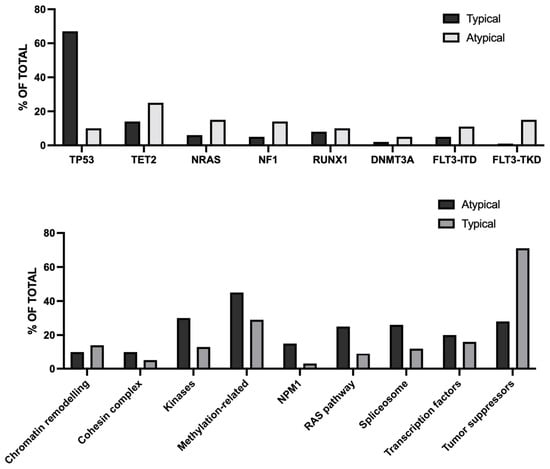
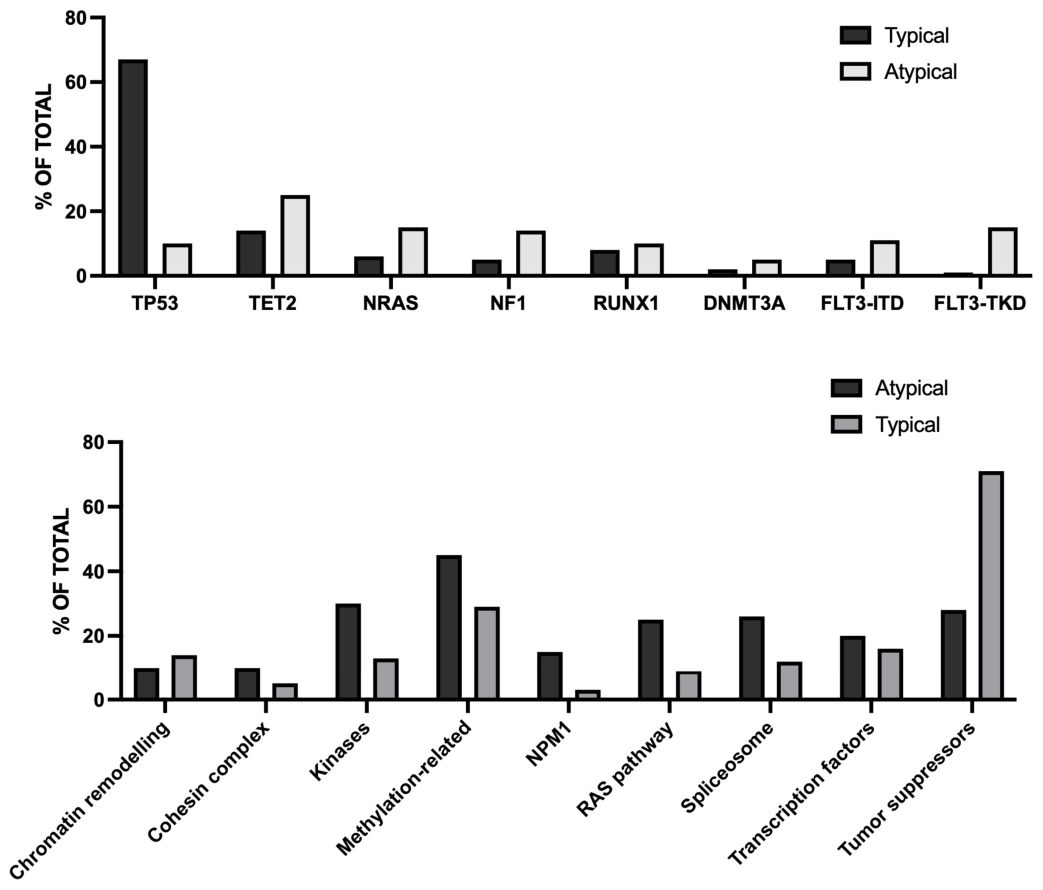
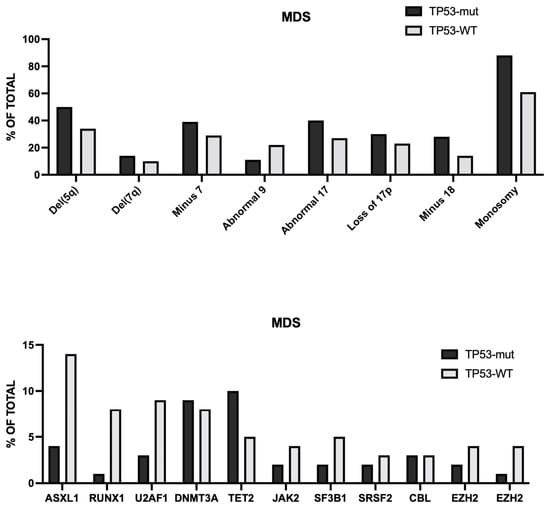
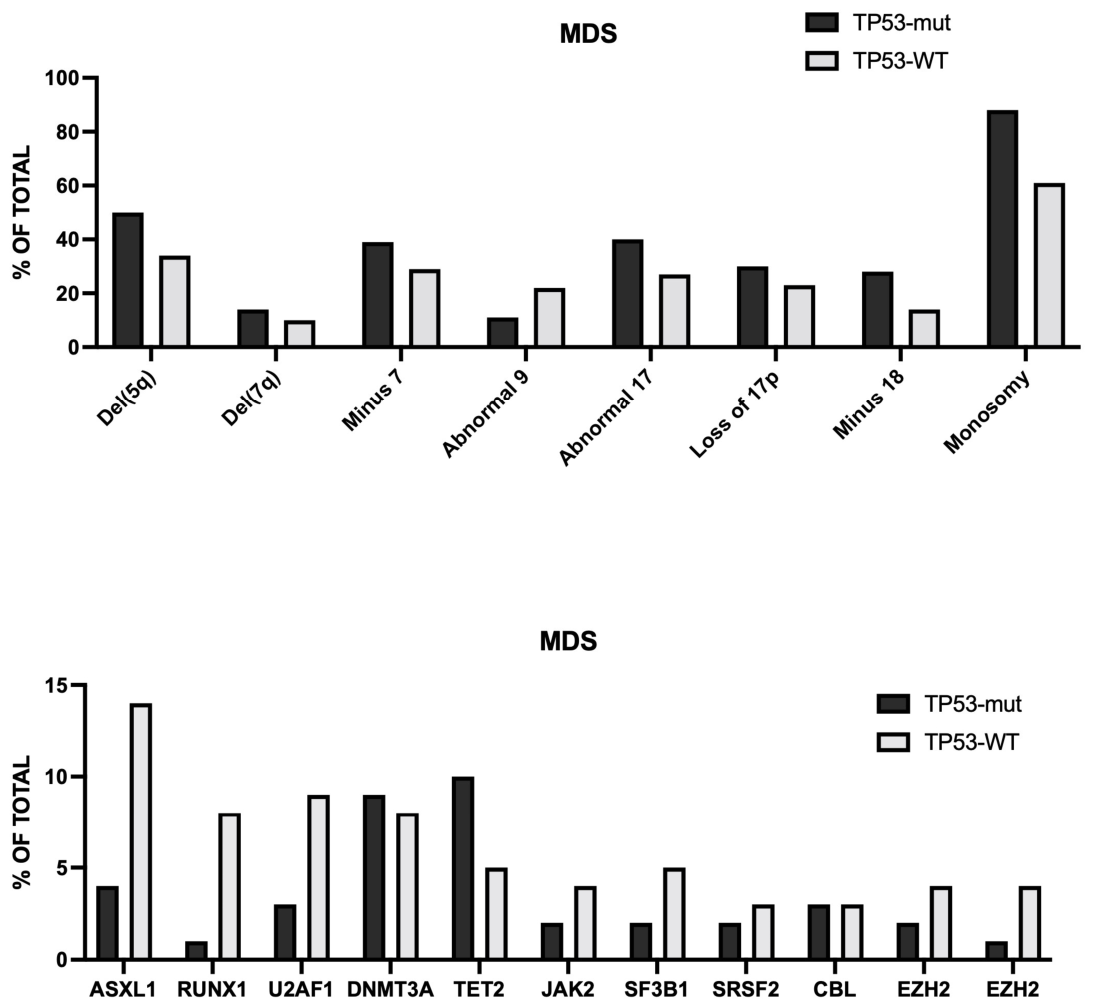
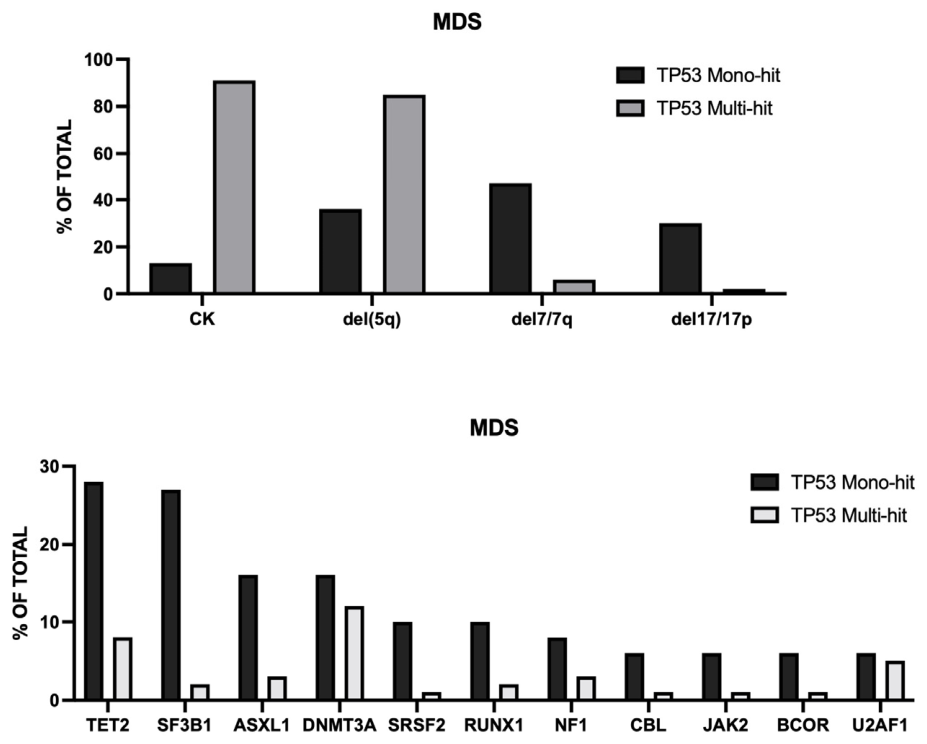
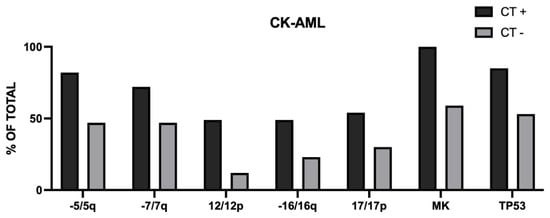
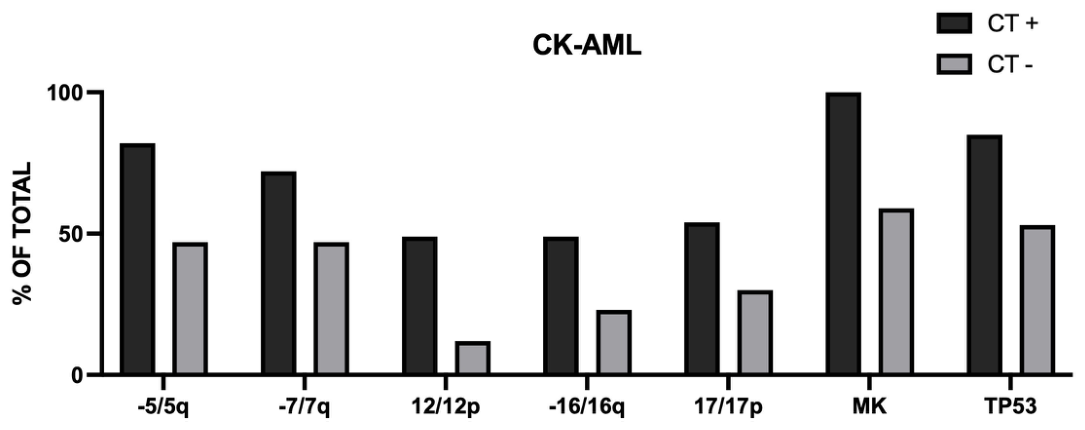
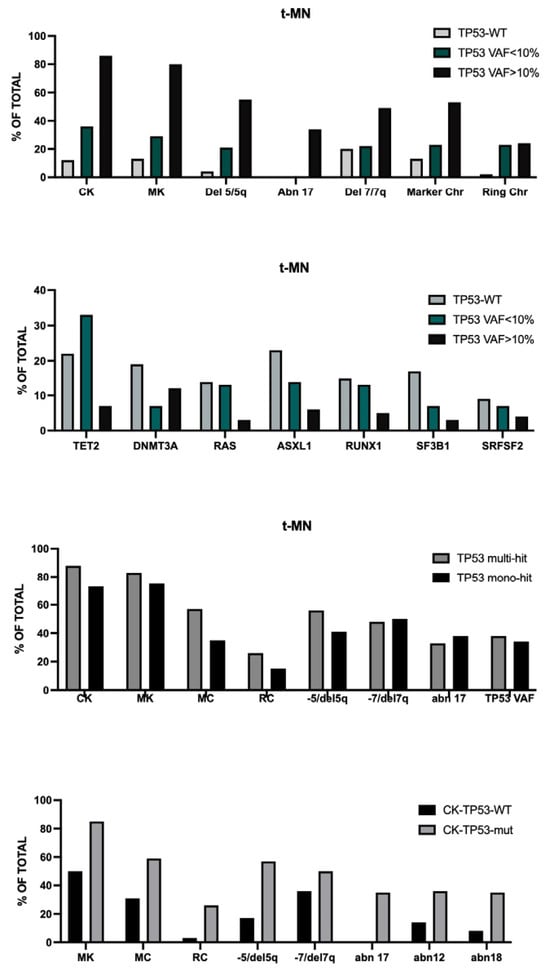
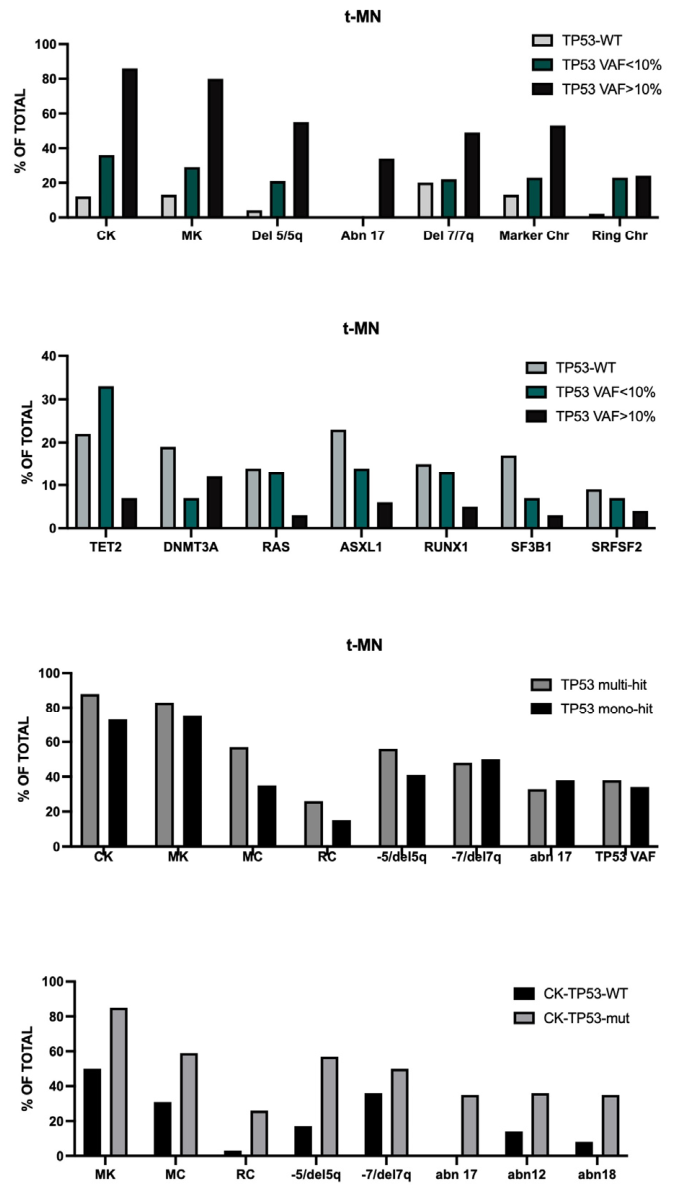

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the author. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.