


Abstract
Background/Objectives: The objective of this study was to test the accuracy of two sound-based voided volume measurement applications compared to voided volume based on the measurement of pre- and post-void weight using a high-resolution scale. Methods: Seven male and four female volunteers participated. Male and female volunteers used the proudP and Healthy Bladder-Voiding Diary mobile apps, respectively, to measure sound-based voided volume (SVV). The difference between pre- and post-void weight was calculated and converted to mL to be the true voided volume (TVV) using a high-resolution scale. Pearson correlation coefficients were calculated, and paired t-tests were completed. Results: Eighty-one voids were recorded (42M/39F). The median male participant age was 25 years. Male SVV ranged from 42 to 790 mL, and TVV ranged from 61 to 880 mL. The mean difference was 39 mL (95% CI, 18–59 mL). SVV and TVV comparison revealed a strong correlation (r = 0.977, p < 0.0001). Bland–Altman analysis revealed a mean bias of 39 mL. The median female participant age was 25 years. Female SVV ranged from 32 to 440 mL, and TVV ranged from 20 to 682 mL. The mean difference was 55 mL (95% CI, 23–88 mL). SVV and TVV comparison revealed a correlation (r = 0.882, p < 0.0001). Bland–Altman analysis demonstrated a mean bias of 55 mL. Conclusions: In this pilot study, we found that the male and female apps have a strong correlation to true voided volume (male > female app) and can be used by patients to track voided volume at home. The male app accurately measures voided volume within 60 mL from the TVV; however, the female app is less accurate. These preliminary findings warrant validation in larger prospective cohorts.
1. Introduction
Lower urinary tract symptoms (LUTSs) are predicted to affect nearly half the world’s population, with many studies reporting a disproportionate prevalence of greater than 60% in older men and women [1,2,3]. LUTSs are divided into three categories—storage, voiding, and postmicturition symptoms—and include concerns from urinary urgency and incontinence to incomplete emptying and postmicturition dribble [4]. LUTSs have a significant disease burden and commonly impact men with benign prostatic hyperplasia and women with overactive bladder [5,6]. LUTSs are linked to increased anxiety and depressive symptoms, as well as reduced quality of life, particularly due to decreased vitality and impaired ability to work and perform daily activities [7]. Accurate and timely symptomatic management is important for the effective treatment of LUTSs.
Uroflowmetry is widely used for the initial non-invasive evaluation of LUTSs due to its simplicity and broad availability and can be helpful in arriving at a diagnosis [8]. However, due to the burden, stress, and inconvenience of conventional uroflowmetry (since patients normally need to physically come to the clinic with a full bladder at their appointment time to urinate into a conventional uroflowmeter), there is growing interest in measuring urinary flows with voiding acoustics, also known as “sono-uroflowmetry,” as an alternative to uroflowmetry. Sono-uroflowmetry converts acoustic recordings of the sound generated by urine hitting the toilet bowl water when a patient voids to standard uroflow parameters including voided volume, and there are studies showing the promising potential of using sound-based uroflowmetry to detect abnormal urinary flow patterns [9]. This technology could allow for the home-based monitoring of multiple urinary flows, as opposed to a single office-based uroflow that may not accurately depict a patient’s true voiding patterns.
There is a need to investigate the accuracy of these new home-based measurement tools for LUTSs across men and women before they are widely adopted and used in clinical practice. This pilot study sought to evaluate the accuracy of two freely available sound-based smartphone apps from Soundable Health, Inc., Healthy Bladder and proudP, in measuring sound-based voided volume compared to true voided volume based on the measurement of pre- and post-void weight using a high-resolution scale.
The two smartphone applications evaluated in this pilot study are part of the rapidly expanding field of mobile health (mHealth), which encompasses smartphones, tablets, and wearable technologies. Within this domain, smartphones are increasingly being utilized for patient education, disease prevention, medical diagnosis, and ongoing health monitoring. As mHealth technologies continue to evolve, smartphone applications offer significant potential to enhance wellness and promote healthy behaviors, improve disease prevention and management, and increase access to health information and healthcare resources [10].
One of the greatest strengths of mHealth is its ability to facilitate healthcare delivery beyond geographical, temporal, and organizational constraints. By leveraging scalable digital solutions, such as online platforms accessible through widely available devices like smartphones, mHealth has the potential to improve access to care while reducing healthcare costs; however, a notable limitation is that relatively few mHealth applications have undergone rigorous scientific evaluation or received regulatory approval from agencies such as the U.S. Food and Drug Administration (FDA) or the European Medicines Agency [11].
In 2022, the FDA issued “Policy for Device Software Functions and Mobile Medical Applications”, which contained nonbinding recommendations. In it they defined a mobile application or “mobile app” as “a software application that can be executed (run) on a mobile platform (i.e., a handheld commercial off-the-shelf computing platform, with or without wireless connectivity), or a web-based software application that is tailored to a mobile platform but is executed on a server.” They defined a “mobile medical app” as a mobile app that “incorporates device software functionality that meets the definition of a device in section 201 (h) of the FD&C Act” and is “intended to be used as an accessory to a regulated medical device; or to transform a mobile platform into a regulated medical device.” Per the policy, the FDA intends to “apply its regulatory oversight to only those software functions that are medical devices and whose functionality could pose a risk to a patient’s safety if the device were to not function as intended.” [12].
Smartphone technology and smartphone applications represent a rapidly evolving area with significant potential to enhance urological care, patient engagement, and medical education. Through widely accessible devices, these technologies can improve healthcare delivery, facilitate patient monitoring, and support the self-management of urological conditions. Despite this promise, the marketplace remains largely self-regulated. A review by Tapiero et al. [10] highlighted the lack of high-quality, adequately powered clinical trials evaluating smartphone-based interventions in urology, limiting the ability to determine their true clinical value. Consequently, only a small number of available applications can currently be considered evidence-based or validated for routine use.
Concerns regarding the quality and reliability of urology-related smartphone applications are further supported by research showing that of the apps aimed at the general public, only 13% involved healthcare professionals and 2% involved urological associations in their development [13]. The absence of standardized quality criteria and comprehensive regulatory oversight for most health-related mobile applications raises important questions about their accuracy, safety, and clinical credibility. Against this backdrop, the present pilot study seeks to contribute to the growing body of evidence by evaluating two smartphone applications designed to estimate voided volume using sound analysis. It is hoped that the findings will provide valuable preliminary data regarding the accuracy and potential clinical utility of these applications.
2. Materials and Methods
2.1. Study Design and Study Population
This was a pilot study conducted to determine whether a larger investigation with a substantially greater number of participants would be feasible, practical, and methodologically sound. Through this preliminary work, we hoped to determine that recruitment and data collection were manageable and that the operational workflow, including the use of the high-resolution scale, was feasible. Another aim of this pilot study was to find insights to refine sample size calculations and anticipated statistical power for future studies. Soundable Health, Inc. had no role in this study’s data collection, statistical analysis, manuscript preparation, or the decision to submit this manuscript for publication.
In this prospective, single-center, within-subjects, open-label trial, we sought to determine the accuracy of the sound-based voided volume measurements from two smartphone applications, proudP and Healthy Bladder Voiding Diary. The Healthy Bladder Voiding Diary app was rebranded as Bladderly in June 2023. While both proudP and Healthy Bladder Voiding Diary were free to use at the time of this study, the company has since made both apps subscription-based. This study was approved by the Institutional Review Board at Penn State University before beginning recruitment and measuring voided volume in participants. At the time of this study, the two smartphone apps were available only for iPhones; however, since then the apps have become available for Android devices.
2.2. Inclusion and Exclusion Criteria
Healthy male and female volunteers were recruited. To be eligible for recruitment, participants needed to have a body weight of less than 150 kg and the ability to stand independently and use the toilet without assistance, and males needed to be able to urinate while standing. Exclusion criteria included the inability to stand or use the toilet independently, the inability to follow verbal instructions independently, and a history of any urologic condition or voiding dysfunction. A total of seven male and four female participants were recruited for this validation pilot study. Each participant provided multiple voids during the study period. Please refer to Table 1 for the demographics of the study volunteers.
Table 1.
Summary of participants.
2.3. Study Protocol
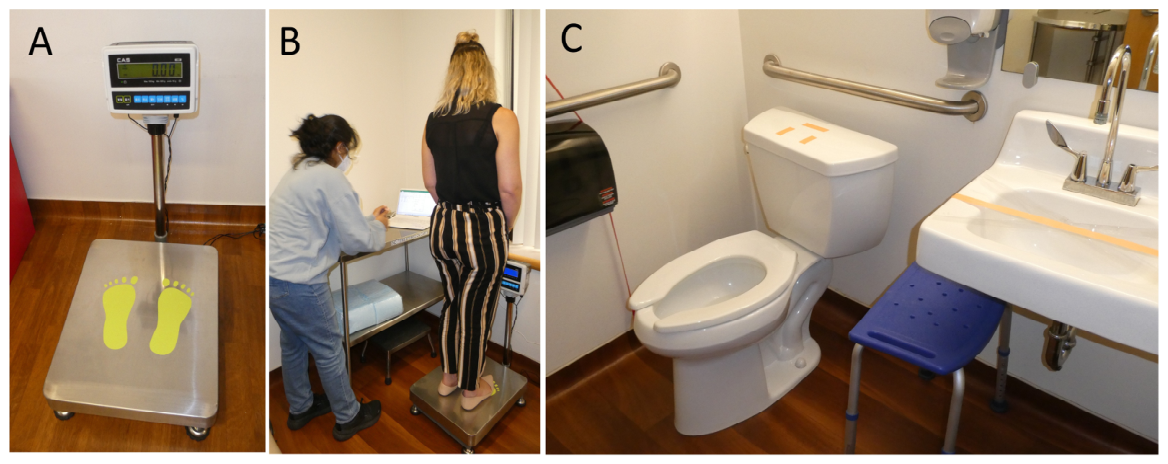
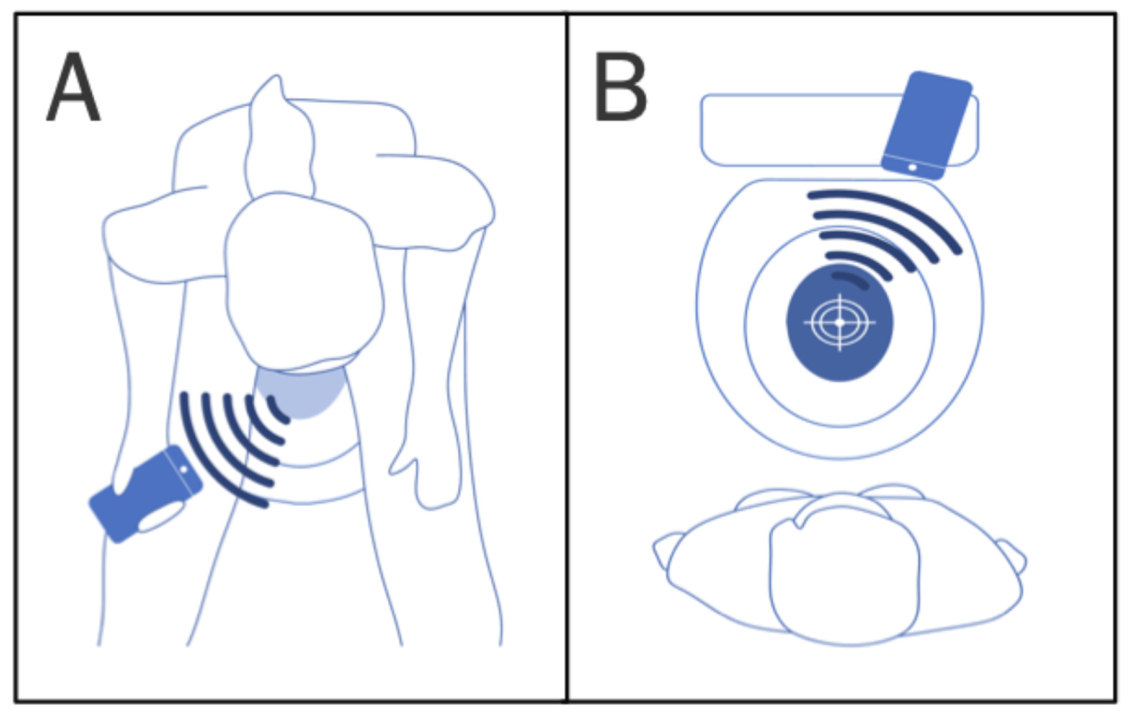
Participants’ voided volumes were measured between 22 September 2022 and 23 October 2022. Male participants used the proudP app, iOS v2.1.0 (Soundable Health, San Francisco, CA, USA), and female participants used the Healthy Bladder Voiding Diary app, iOS v1.2.1 (Soundable Health, San Francisco, CA, USA), to measure sound-based voided volume (SVV). Before measuring the SVV, participants’ pre-void weight was calculated using an HB-150 high-resolution electronic scale within 5 min of the void. The HB-150 high-resolution scale (Figure 1A,B) reported weight in kilograms with 10 g sensitivity, allowing for precise measurements of pre- and post-void weights. The measurement of SVV was done in a quality-controlled, single-user restroom (Figure 1C). This allowed for noise control to prevent acoustic background noise which would interfere with the SVV measurement. SVV for male participants was measured as described in Kim et al. [10]. To record SVV for female participants, prior to initiating a void, the participants rested a smartphone device on their mid-thigh with the bottom of the phone pointed towards the opening of the toilet bowl (Figure 2). All measurements were performed using the same toilet and restroom environment, and participants were instructed to position the smartphone according to the manufacturer’s instructions for each application.
Figure 1.
(A). HB-150 high-resolution electronic scale. (B). Volunteer being weighed on scale. (C). Restroom with toilet used for this study.
Figure 2.
Sound-based void volume collection method for female (A) and male participants (B). Reproduced with permission from Soundable Heath, Inc.
Before beginning to void, the participants pressed the start button on the smartphone application. The Healthy Bladder Voiding Diary (for females) and the proudP app (for males) recorded the sound of voiding and saved the data. Upon the completion of void, male and female participants were weighed on the HB-150 high-resolution scale to record post-void weight. The difference between pre- and post-void weight was determined. The difference in weight was then converted into the true voided volume (TVV). Urine specific gravity generally ranges from 1.005 to 1.030, and within this range, the weight difference in grams will reflect the volume in mL within 0.05%, so the weight difference was used as the true voided volume.
SVV measurements that were interrupted due to an unexpected noise occurrence during the void were excluded. TVVs less than 20 mL were also excluded from analysis as 20 g was the threshold required for a reliable weight measurement. Please refer to Table 2 for a summary of the voided volume measurements.
Table 2.
Summary of voided volume (VV) measurements from 11 participants.
2.4. Statistical Analysis
This study was designed as a pilot validation study intended to assess feasibility and generate preliminary estimates of agreement SVV and TVV. This study was designed as a pilot feasibility and validation study. Accordingly, no formal sample size calculation was performed, and the smaller number of participants and voided volumes was intended to provide preliminary estimates of agreement and feasibility data to inform future larger studies. Descriptive statistics were used to summarize participant characteristics and voided volumes. Agreement between SVV and TVV was assessed using Bland–Altman analysis, with mean bias and 95% limits of agreement reported. Pearson correlation coefficients were calculated to evaluate the relationship between SVV and TVV. Mean differences and corresponding 95% confidence intervals were calculated. Statistical analyses were performed using GraphPad Prism 9, and statistical significance was defined as p < 0.05.
3. Results
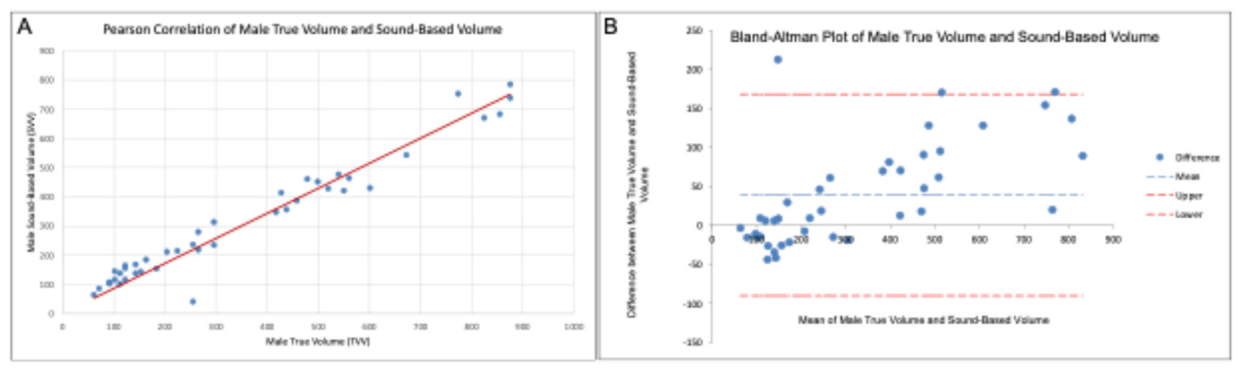
A total of eighty-one voids were recorded (42M/39F). The median male participant age was 25 years. Of the 42 voids from male participants, the SVV ranged from 42 to 790 mL, and TVV ranged from 61 to 880 mL. The mean difference between all voids was 39 mL (95% CI, 18–59 mL). SVV and TVV comparison (Figure 3A) revealed a strong correlation (r = 0.977, p < 0.0001). Bland–Altman analysis (Figure 3B) revealed a mean bias of 39 mL, indicating that the SVVs were lower than the TVVs on average. The 95% limits of agreement ranged from −91 to 168 mL. The majority of measurements fell within these limits, although some differences appeared to increase with increasing volume, suggesting potential bias at higher volumes. At higher voided volumes, the proudP app appeared to underestimate the TVV.
Figure 3.
Male participants’ true vs. sound-based voided volume. (A) Pearson correlation. Red line indicates perfect correlation. (B) Bland–Altman plot.
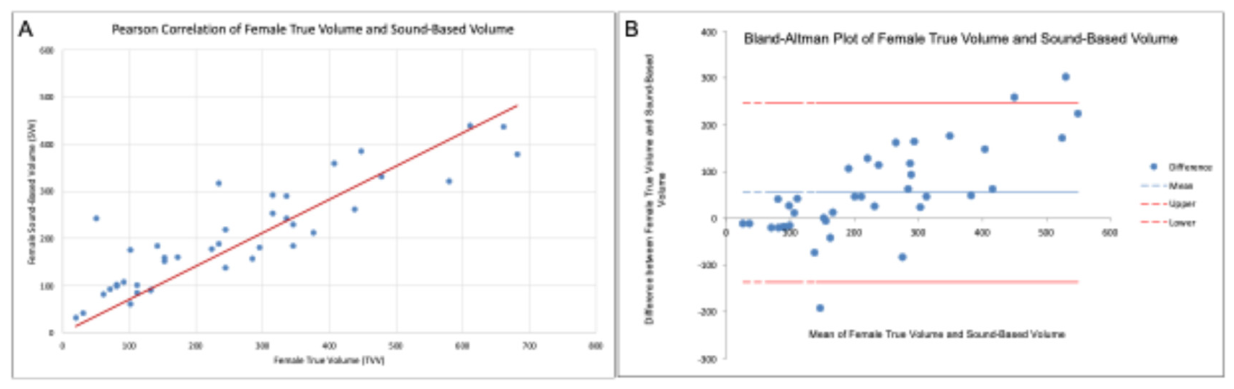
The median female participant age was 25 years. Of the 39 voids from female participants, SVV ranged from 32 to 440 mL, and TVV ranged from 20 to 682 mL. The mean difference was 55 mL (95% CI, 21–89 mL). SVV and TVV comparison (Figure 4A) revealed a correlation (r = 0.882, p < 0.0001). Bland–Altman analysis (Figure 4B) revealed a mean bias of 55 mL, indicating that the SVV estimates were lower than the TVVs on average. The 95% limits of agreement were −137 to 247 mL. While most of the observations fell within these limits, the spread of differences increased with increasing mean volume, suggesting reduced agreement at higher volumes. Similarly to the male version of the app, the female version (Healthy Bladder Voiding Diary) at higher volumes appeared to underestimate the TVV.
Figure 4.
Female participants’ true vs. sound-based voided volume. (A) Pearson correlation. Red line indicates perfect correlation. (B) Bland–Altman plot.
4. Discussion
This institutional pilot study validates the relative accuracy of two freely available sound-based smartphone apps from Soundable Health, Inc., Healthy Bladder Voiding Diary and proudP in healthy volunteers. Both the female app, Healthy Bladder Voiding Diary, and the male app, proudP, showed a significant correlation between SVV and TVV (r = 0.977, p < 0.0001 and r = 0.882, p < 0.0001, respectively).
Bland–Altman analysis was used to assess agreement between TVV and SVV. While both applications demonstrated strong correlations with TVV, the Bland–Altman plots revealed variability between individual measurements, with disagreement tending to increase at higher voided volumes. Specifically, both applications generally underestimated larger voided volumes, suggesting the presence of proportional bias. Although the mean bias was relatively small compared with the overall range of voided volumes measured, the observed variability and wider limits of agreement indicate that measurements, particularly at higher voided volumes, should be interpreted with caution. Nevertheless, our findings support the potential utility of the applications for monitoring overall voiding patterns and trends over time.
The female application exhibited wider limits of agreement than the male application, indicating greater variability in volume estimation and suggesting that the further refinement of the underlying acoustic algorithms may be necessary. The lower accuracy observed in the female application may reflect differences in voiding position, variation in smartphone placement (with the smartphone positioned on the lap; Figure 2), and differences in the acoustic characteristics of urine entering the toilet bowl. These factors may introduce greater variability into the sound-processing algorithms and contribute to the wider limits of agreement observed in female participants. Overall, these findings support the feasibility of sound-based voided volume estimation while highlighting the need for validation in larger, more diverse populations and real-world home settings.
These results suggest that sound-based smartphone applications are capable of accurately measuring voided volume, which is in line with the findings of other validation studies of iOS-based uroflow applications [14,15]. For patients, these results are significant as this means that voided volumes can easily be tracked in the privacy of their home. This study only assessed the accuracy of the voided volume calculated by the app and no other parameters such as the maximum flow rate and average flow rate, which the proudP app also calculates. A sound-based mobile phone application would also make monitoring symptom progression easier than it being monitored infrequently at clinic visits. Studies have also shown that tracking voided volumes via mobile-based applications are preferred by patients over paper methods [16]. Urologists would also benefit from the use of sound-based mobile phone applications to record voided volumes as they allow for an accurate report of the specific volumes and number of voids from their patients. This may allow for the improved monitoring of symptoms and treatment responses for those with LUTSs.
This study is not without limitations. Every effort was made to eliminate or decrease extraneous noise in the restroom during this study; however, ambient noise was inevitably present within the room and could have caused minor variations in the SVV reported. In addition to potential errors due to ambient noise, if the assumption made for converting the weight of urine to volume was inaccurate, minor differences in the TVV may be present. There are also limitations in how the apps generate the SVV. The app makes measurements based on the sound created when urine hits the water of the toilet bowl. However, the sound generated by urine hitting the sides of the toilet is different than that of it hitting the water, accounting for some potential inaccuracies despite every effort to control them. Our study enrolled seven healthy volunteers who completed a total of 42 voids for the male app and 39 voids for the female app. A wide range of sample volumes was collected, but consideration should be given to whether a larger number of participants would be needed to report the accuracy between SVV and TVV. That said, studies with a greater number of participants and measured voids had similar results [14,15,16].
Ongoing advancements in algorithm development are expected to further enhance performance. Future research is needed to investigate the accuracy of sound-based mobile applications in patients with LUTSs. The proudP app also calculates the maximum flow rate and average flow rate and generates a uroflow curve, just like the standard uroflow machines in most urology clinics, and future research is planned to determine the accuracy of these additional parameters.
5. Conclusions
In this initial cohort, both the male and female apps demonstrated positive correlation with true voided volume, with the male application showing stronger performance. The male application measured voided volume within 60 mL of the true voided volume (TVV), whereas the female application showed lower accuracy. If these early findings are confirmed and validated in larger, more diverse populations, these mobile apps may offer patients a practical means of tracking urinary voided volume using only their smartphones.
Author Contributions
Conceptualization, J.Y.C. and Z.C.; methodology, Z.C., A.R., K.S., B.A. and J.Y.C.; software, J.Y.C. and Z.C.; validation, J.Y.C. and Z.C.; formal analysis, J.Y.C. and Z.C.; investigation, Z.C., A.R., K.S., B.A. and J.Y.C.; resources, J.Y.C. and Z.C.; data curation, J.Y.C. and Z.C.; writing—original draft preparation, Z.C.; writing—review and editing, J.Y.C., A.R. and Z.C.; visualization, J.Y.C. and Z.C.; supervision, J.Y.C.; project administration, Z.C., A.R., K.S., B.A. and J.Y.C. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
This study was conducted in accordance with the Declaration of Helsinki and approved by the Institutional Review Board of Penn State University (STUDY00020244 and date of approval: 16 June 2022); this initial approved study was a prospective, multi-center trial that accrued 540 patients with an incentive given to each volunteer; however, due to funding restrictions, a modification was requested for a smaller single-center pilot trial without an incentive offered to volunteers. Verbal permission was given to start this trial pending the modification to the protocol, and the official modified protocol (MOD00034550) was received on 3 November 2022.
Informed Consent Statement
Implied or verbal consent was obtained from all subjects involved in this study as the IRB felt there was no more than a minimal risk of harm to subjects and involved no procedures for which written consent is normally required outside of the research context.
Data Availability Statement
The original contributions presented in this study are included in the article. Further inquiries can be directed to the corresponding author.
Acknowledgments
The authors thank Soundable Health, Inc. for permission to reproduce Figure 2. This abstract was presented at the Mid-Atlantic Section of the American Urological Association’s Annual Meeting at a Moderated Poster Session (BPH, Voiding Dysfunction, Female Urology), 20 October 2023, in Williamsburg, Virginia.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| SVV | sound-based voided volume |
| TVV | true voided volume |
| LUTSs | lower urinary tract symptoms |
| mHealth | mobile health |
| FDA | Food and Drug Administration |
References
- Zhang, A.Y.; Xu, X. Prevalence, Burden, and Treatment of Lower Urinary Tract Symptoms in Men Aged 50 and Older: A Systematic Review of the Literature. SAGE Open Nurs. 2018, 4, 2377960818811773. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Przydacz, M.; Golabek, T.; Dudek, P.; Lipinski, M.; Chlosta, P. Prevalence and bother of lower urinary tract symptoms and overactive bladder in Poland, an Eastern European Study. Sci. Rep. 2020, 10, 19819. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Irwin, D.E.; Milsom, I.; Kopp, Z.; Abrams, P.; Artibani, W.; Herschorn, S. Prevalence, severity, and symptom bother of lower urinary tract symptoms among men in the EPIC study: Impact of overactive bladder. Eur. Urol. 2009, 56, 14–20. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Irwin, D.E.; Milsom, I.; Hunskaar, S.; Reilly, K.; Kopp, Z.; Herschorn, S.; Coyne, K.; Kelleher, C.; Hampel, C.; Artibani, W.; et al. Population-based survey of urinary incontinence, overactive bladder, and other lower urinary tract symptoms in five countries: Results of the EPIC study. Eur. Urol. 2006, 50, 1306–1315. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Egan, K.B. The Epidemiology of Benign Prostatic Hyperplasia Associated with Lower Urinary Tract Symptoms: Prevalence and Incident Rates. Urol. Clin. N. Am. 2016, 43, 289–297. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wennberg, A.L.; Molander, U.; Fall, M.; Edlund, C.; Peeker, R.; Milsom, I. A longitudinal population-based survey of urinary incontinence, overactive bladder, and other lower urinary tract symptoms in women. Eur. Urol. 2009, 55, 783–791. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Welch, G.; Weinger, K.; Barry, M.J. Quality-of-life impact of lower urinary tract symptom severity: Results from the Health Professionals Follow-up Study. Urology 2002, 59, 245–250. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sinha, S. The Use of Uroflowmetry as a Diagnostic Test. Curr. Urol. Rep. 2024, 25, 99–107. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rangganata, E.; Rahardjo, H.E.; Rasyid, N.; Widia, F.; Murwantara, I.M.; Yugopuspito, P.; Gemilang, B.; Nasher, F.Z.; Syadza, Y.Z.; Yonathan, K.; et al. Comparative study of mobile acoustic uroflowmetry and conventional uroflowmetry: A systematic review and meta analysis. Neurourol. Urodyn. 2024, 43, 694–702. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tapiero, S.; Yoon, R.; Jefferson, F.; Sung, J.; Limfueco, L.; Cottone, C.; Lu, S.; Patel, R.M.; Landman, J.; Clayman, R.V. Smartphone technology and its applications in urology: A review of the literature. World J. Urol. 2020, 38, 2393–2410. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pereira Azevedo, N.; Gravas, S.; de la Rosette, J. Mobile Health in Urology: The Good, the Bad and the Ugly. J. Clin. Med. 2020, 9, 1016. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- US Food and Drug Administration. Policy for Device Software Functions and Mobile Medical Applications: Guidance for Industry and Food and Drug Administration Staff; FDA: Silver Spring, MD, USA, 2022. Available online: https://www.fda.gov/regulatory-information/search-fda-guidance-documents/policy-device-software-functions-and-mobile-medical-applications (accessed on 5 July 2026).
- Pereira-Azevedo, N.; Carrasquinho, E.; Cardoso de Oliveira, E.; Cavadas, V.; Osório, L.; Fraga, A.; Castelo-Branco, M.; Roobol, M.J. mHealth in Urology: A Review of Experts’ Involvement in App Development. PLoS ONE 2015, 10, e0125547. [Google Scholar] [CrossRef] [Scilit] [PubMed][Green Version]
- Kim, H.; Ye, C.; Jung, G.; Ryu, H.; Lee, J.W.; Jeong, S.J.; Lee, S. Validation of acoustic voided volume measure: A pilot prospective study. World J. Urol. 2023, 41, 509–514. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jung, G.; Ryu, H.; Lee, J.W.; Jeong, S.J.; Margolis, E.; Grover, N.; Lee, S. Validation of an algorithm for sound-based voided volume estimation. Sci. Rep. 2024, 14, 138. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, J.K.; Kim, H.; Ho, J.N.; Jeong, S.J.; Lee, S. A Novel Acoustic Uroflowmetry-Based Mobile App Voiding Diary: Comparison with Conventional Paper-Based Voiding Diary. BioMed Res. Int. 2022, 2022, 3390338. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.