


Abstract
Wilson’s disease (WD) is traditionally known as a monogenic disorder of copper transport, but immune activation is now being increasingly recognized in a subset of patients. In a single-center retrospective cohort study of 86 treatment-naïve WD patients who were rigorously diagnosed using the Leipzig score, Jiang et al. systematically evaluated the prevalence, clinical impact, and prognostic significance of autoimmune phenomena (AP), defined by autoantibody positivity and/or elevated immunoglobulin G (IgG). They found that 55.8% of patients met the criteria for AP, with about half showing at least one autoantibody, primarily low-titer antinuclear antibodies (ANAs), indicating that immune activation is common in newly diagnosed WD. Notably, patients with WD and AP (AP-WD) had more advanced hepatic dysfunction at baseline, including higher bilirubin levels, worse synthetic function, greater cirrhosis and ascites burden, and higher composite liver scores, as well as increased urinary copper excretion. Histological analysis in a subset of patients who underwent biopsy showed more intense portal inflammation and plasma cell infiltration in AP-WD, suggesting a distinct immunopathological phenotype. Over a 60-month period, AP-WD patients had a higher incidence of liver-related adverse events (death or liver transplantation), with a nearly fourfold increased hazard compared to patients without AP. Collectively, these findings support AP as a clinically significant modifier of disease expression and outcome in WD, emphasizing the importance of routine assessment of autoantibodies and IgG at diagnosis to improve risk stratification and guide follow-up care.
1. Autoimmune Markers in Wilson’s Disease: What Does the Study Add?
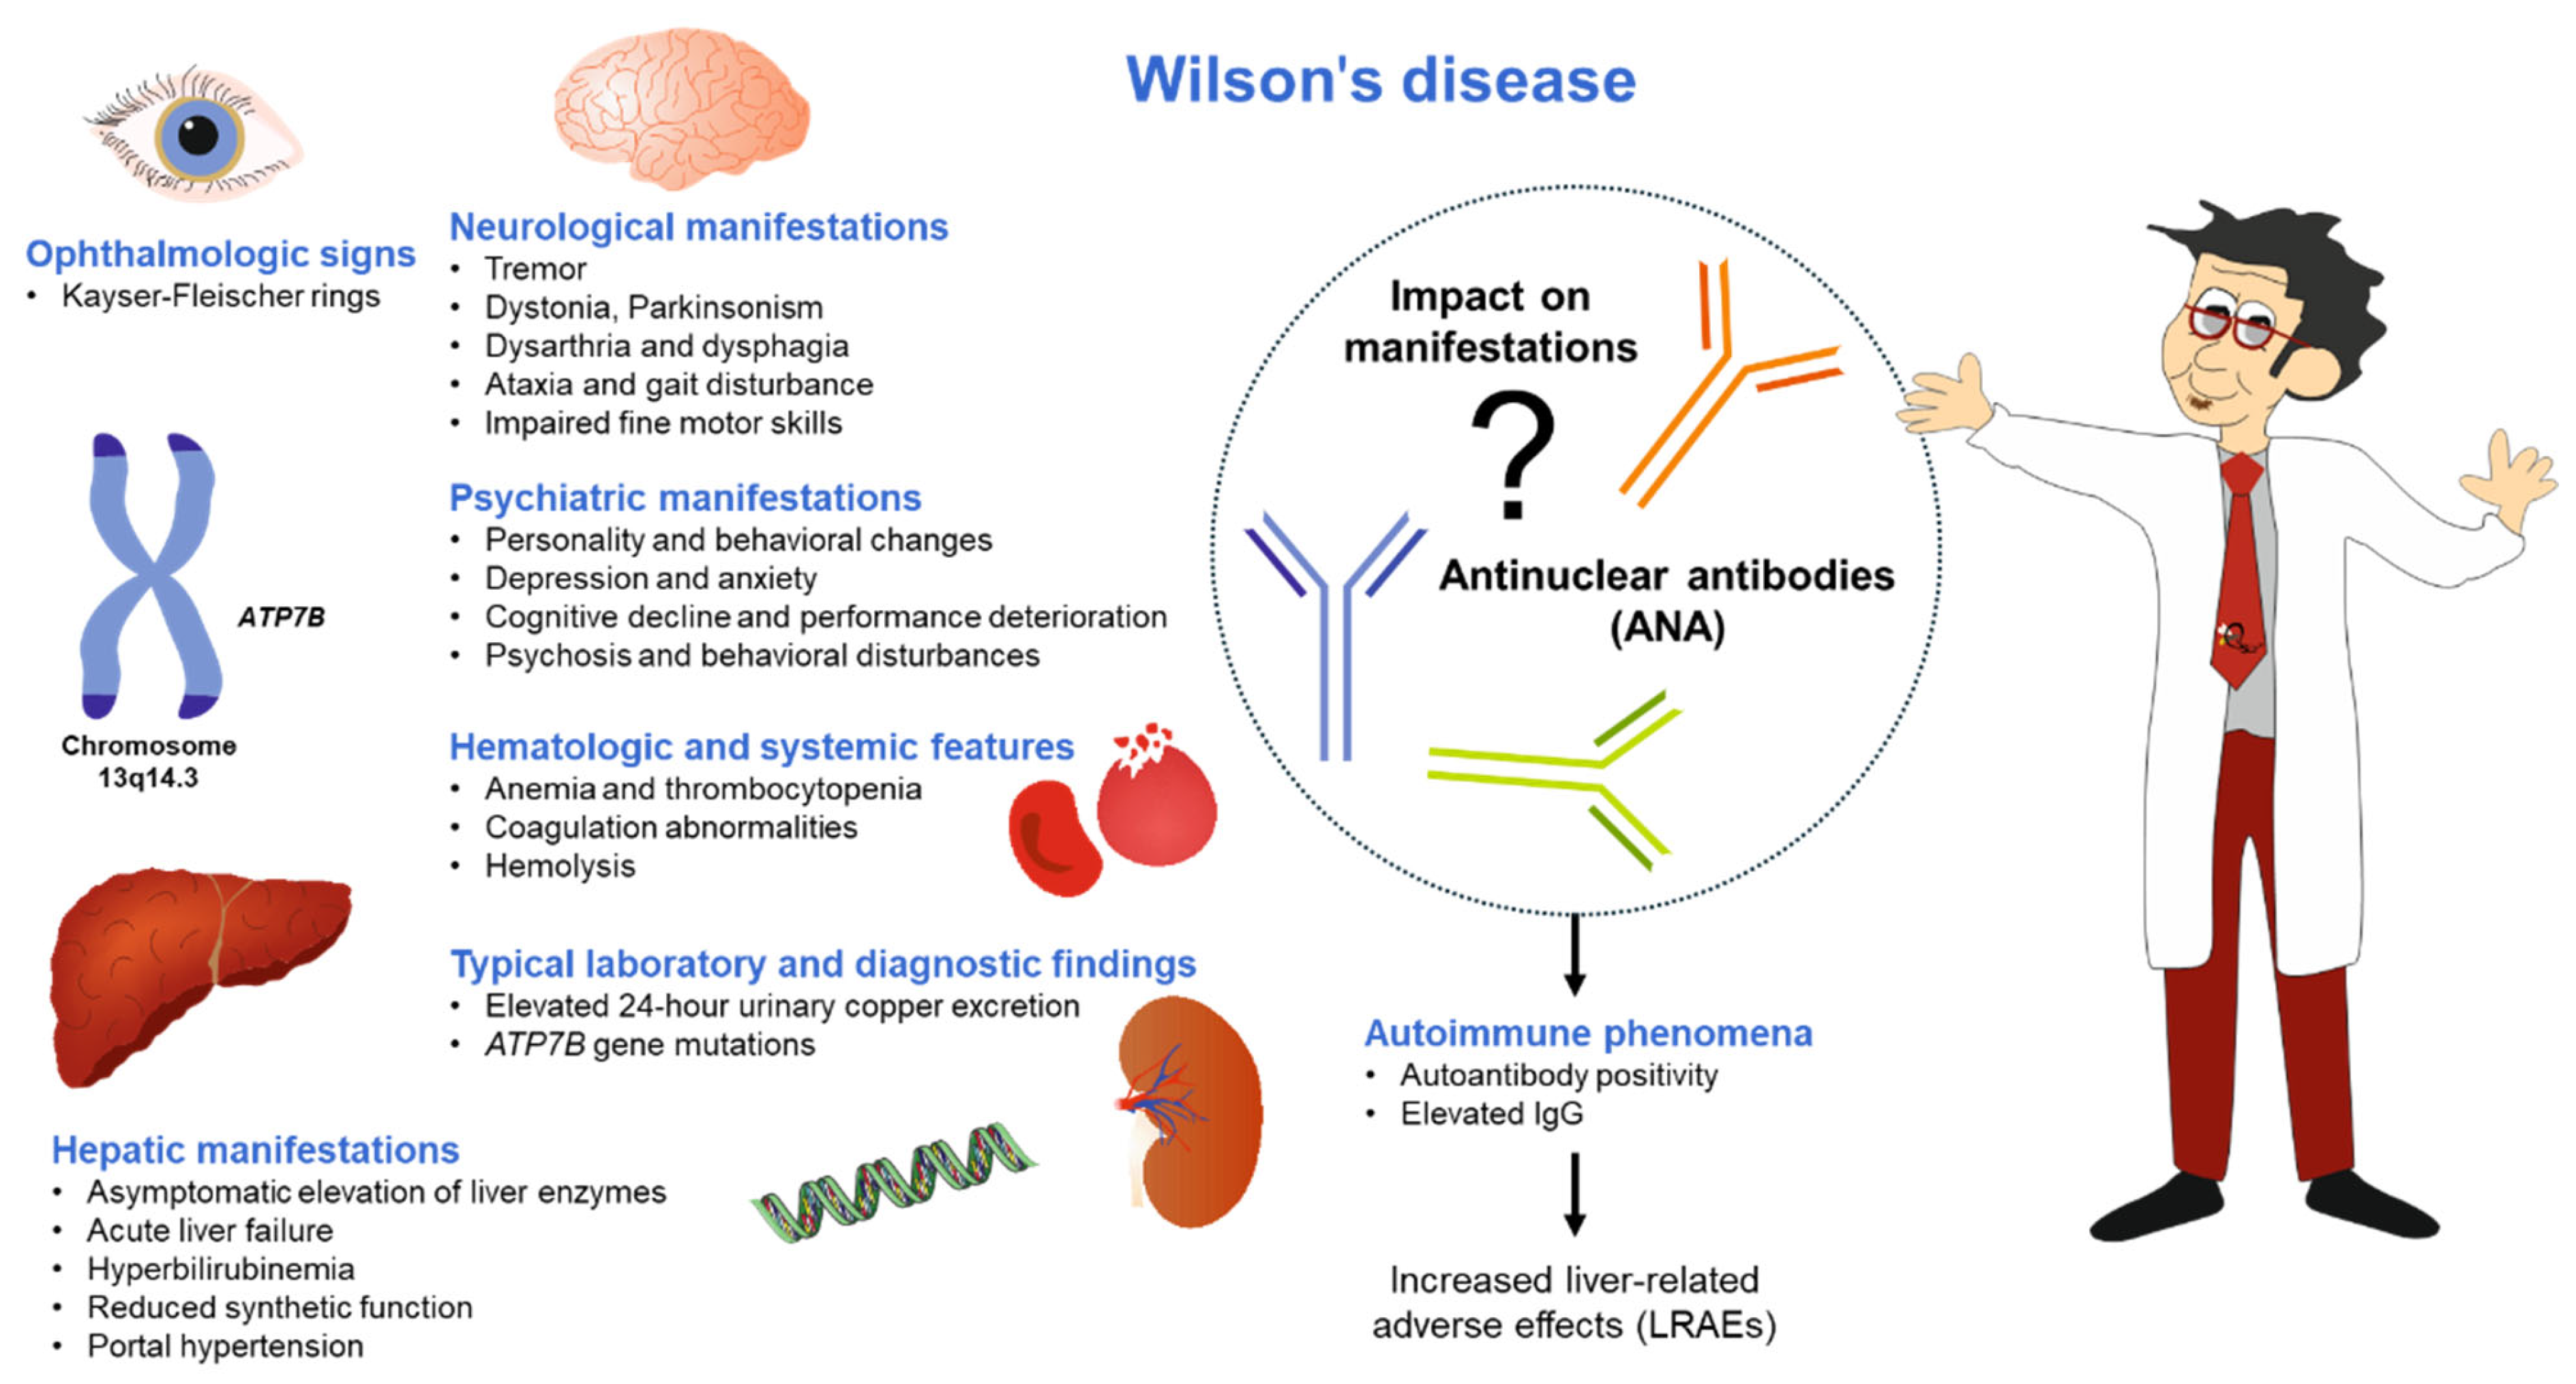
Wilson’s disease (WD) is a rare autosomal recessive disorder of copper metabolism caused by pathogenic variants in the ATP7B gene (Online Mendelian Inheritance in Man (OMIM): 606882) on chromosome 13q14.3, which encodes a copper-transporting P-type ATPase [1]. Impaired incorporation of copper into ceruloplasmin and defective biliary copper excretion lead to progressive systemic copper accumulation, predominantly in the liver, brain, and kidneys [2]. Clinically, WD ranges from asymptomatic elevation of liver enzymes to chronic liver disease, cirrhosis, acute liver failure, and diverse neurological and psychiatric manifestations, most often presenting in children and young adults. Early diagnosis and timely initiation of anti-copper therapy are crucial to prevent irreversible organ damage and to improve long-term outcomes [3]. A schematic overview linking ATP7B mutations on chromosome 13q14.3 to the hepatic, neurological, psychiatric, ophthalmologic, hematologic, and biochemical manifestations of the disease is shown in Figure 1. It highlights how autoantibody positivity and elevated IgG cluster with increased liver-related adverse events. However, the direct impact of antinuclear antibodies (ANAs) on individual manifestations remains unclear.
Figure 1.
Schematic overview of the clinical spectrum of Wilson’s disease and the potential role of autoimmune phenomena. Mutations in ATP7B on chromosome 13q14.3 result in Wilson’s disease, which is characterized by hepatic, neurological, psychiatric, ophthalmologic, hematologic/systemic, and typical laboratory features such as elevated 24 h urinary copper excretion and detectable ATP7B gene alterations. Autoimmune phenomena, indicated by autoantibody positivity and/or elevated IgG levels, are frequently observed and are linked to more advanced liver dysfunction and an increased risk of liver-related adverse events (LRAEs). However, the direct influence of antinuclear antibodies (ANA) on specific clinical manifestations remains uncertain. The arrows illustrate associations reported in clinical studies rather than proven causal relationships. The schematic is intended to highlight potential links between autoimmune phenomena and disease severity in Wilson’s disease without implying direct mechanistic causality.
In a recent article published in Metabolism and Target Organ Damage (MTOD), Jiang et al. reported on a retrospective single-center cohort study of 86 treatment-naïve patients with WD who were hospitalized over a 16-year period at Beijing YouAn Hospital [4]. All patients met the cut-off criteria of a Leipzig score ≥ 4 [1], and ATP7B mutations were confirmed through next-generation sequencing, ensuring strong diagnostic certainty for WD. Autoimmune phenomena (AP) were strictly defined as the presence of at least one autoantibody at a titer ≥1:100 and/or serum IgG levels above the upper limit of normal (17.4 g/L), resulting in two groups: WD with AP (AP-WD, n = 48) and WD without AP (NAP-WD, n = 38). Autoantibody testing was conducted in 81 out of 86 patients, with 41 (50.6%) testing positive for autoantibodies, which significantly exceeded the 10–20% seropositivity reported in healthy populations. ANAs were the most common, accounting for 40 out of 41 autoantibody-positive cases, with most patients showing isolated, low-titer patterns. These findings support the idea that immune activation is not an uncommon side effect but rather a common occurrence in WD during the initial presentation, especially in a tertiary liver center cohort. This study builds upon previous pediatric and mixed-phenotype series by focusing solely on treatment-naïve patients and incorporating both serologic and histologic markers of immune activity.
2. Baseline Phenotype: Autoimmune Phenomena as a Marker of More Advanced Liver Disease
One of the most striking observations is the consistently more severe hepatic phenotype in AP-WD compared with NAP-WD at baseline. Despite similar age and sex distributions, AP-WD patients had lower hemoglobin, red blood cell, and platelet counts, along with more pronounced coagulopathy (prolonged prothrombin time and activated partial thromboplastin time, higher International Normalized Ratio (INR), and reduced prothrombin time activity and fibrinogen). They also showed higher total and direct bilirubin concentrations, reduced albumin and cholinesterase, and higher Aspartate Aminotransferase to Platelet Ratio Index (APRI), Child-Pugh, and Model for End-Stage Liver Disease (MELD)/Pediatric End-Stage Liver Disease (PELD) scores.
Clinically, AP-WD patients more frequently presented with cirrhosis (75.0% vs. 44.7%), ascites (54.2% vs. 23.7%), and Kayser–Fleischer rings, further supporting an association between AP and advanced structural and functional liver damage. Interestingly, 24 h urinary copper excretion was also higher in AP-WD, suggesting that AP may cluster with greater systemic copper burden, although causality remains unresolved. An alternative explanation for the observed association between AP and more advanced liver disease deserves consideration. Autoantibody positivity and hypergammaglobulinemia are frequently detected in patients with cirrhosis of various etiologies and are often interpreted as secondary manifestations of immune dysregulation accompanying chronic liver injury [5,6]. In this context, elevated IgG levels or the presence of ANAs in AP-WD patients could partly reflect the immunological consequences of advanced hepatic dysfunction rather than a primary pathogenic driver. Consequently, the cross-sectional association between AP and cirrhosis observed by Jiang et al. cannot distinguish whether immune activation contributes to disease progression or arises as a downstream effect of severe liver damage. Prospective studies assessing the temporal evolution of immune markers in relation to disease stage will be required to clarify this relationship.
Jiang et al. further analyzed whether autoantibody titers themselves stratified severity, but they found no meaningful differences across titer subgroups in key clinical or biochemical markers. This supports the authors’ conclusion that the presence of AP, rather than the magnitude of autoantibody titers, appears to be the clinically relevant discriminator.
Beyond dichotomous AP status, the authors explored the relationship between serum IgG and functional liver parameters. IgG correlated inversely with albumin and cholinesterase and positively with INR, indicating that higher IgG levels track with impaired hepatic synthetic and coagulation function in WD. This pattern aligns more closely with immune-mediated liver injury than with isolated cholestasis and strengthens the argument that immunologic activation is entwined with disease severity.
3. Histopathology: A Distinct Immunopathological Signature?
A notable strength of this study is the inclusion of liver histology in 17 treatment-naïve WD patients, allowing a direct comparison of inflammatory architecture between AP-WD and NAP-WD. Although the biopsy subset is small, several trends are informative.
Compared with NAP-WD, AP-WD biopsies showed significantly greater plasma cell infiltration and higher inflammatory activity in portal tracts, features reminiscent of autoimmune hepatitis (AIH). Rosette-like hepatocellular arrangements were more frequent in AP-WD (50% vs. 9.1%), albeit without reaching statistical significance, while fibrosis stage and non-alcoholic fatty liver disease activity scores were broadly similar across groups.
It is important to note that several of these histological features are not specific to AIH. Portal plasma cell infiltration, interface activity and hepatocellular rosette formation can occur in various inflammatory liver diseases and metabolic disorders associated with chronic hepatocellular injury. Therefore, although the plasmacytic inflammatory pattern observed in AP-WD can resemble AIH, histological findings alone are insufficient for this diagnosis. Accurate differentiation requires the integration of parameters of copper metabolism, genetic testing for ATP7B variants, and considering the overall clinical context. This diagnostic overlap highlights the importance of systematically ruling out WD in patients with suspected AIH, particularly in younger individuals.
The findings of the study by Jiang et al. suggest that AP-WD is associated with a qualitatively different inflammatory milieu, more plasmacytic and portal-predominant, without necessarily corresponding to more advanced fibrosis at the time of biopsy. This raises the possibility that immune activation may contribute to ongoing necroinflammation superimposed on copper-induced injury, potentially influencing disease trajectory even when structural damage appears comparable.
However, caution is required in interpreting these histologic data: biopsies were available for only 17 patients, and selection for biopsy in a real-world setting is seldom random, with more severe or diagnostically uncertain cases more likely to undergo sampling. Larger, prospectively collected biopsy cohorts are needed to confirm whether AP-WD represents a reproducible immunopathological subtype of WD.
4. Prognostic Impact: Are Autoimmune Phenomena Simply Epiphenomena?
The central clinical question addressed by Jiang et al. is whether AP has prognostic relevance beyond being a cross-sectional marker of severe liver disease. Among 66 patients with longitudinal data and up to 60 months of administratively censored follow-up, 15 experienced liver-related adverse events (LRAEs), defined as liver transplantation or death. LRAEs occurred far more frequently in AP-WD (12 events; 7 deaths and 5 transplants) than in NAP-WD (3 deaths), translating into a significantly higher cumulative risk of LRAEs in Kaplan–Meier analysis. In univariable Cox proportional hazards modeling, AP-WD conferred a hazard ratio of 3.932 (95% CI: 1.106–13.976) for LRAEs compared with NAP-WD.
At face value, these data position AP as a clinically meaningful predictor of adverse hepatic outcomes in WD. Yet, an important nuance is that the reported Cox model is univariable. AP-WD is strongly correlated with established prognostic markers such as Child-Pugh class, MELD/PELD, degree of coagulopathy, and presence of ascites. Without multivariable adjustment, it remains uncertain whether AP independently contributes prognostic information beyond these conventional indicators, or whether it is largely a surrogate of more advanced disease. These considerations highlight that AP may currently be best interpreted as markers of disease severity rather than definitive mechanistic drivers of adverse outcomes.
Nevertheless, from a pragmatic standpoint, the message to clinicians is clear: WD patients who present with AP constitute a high-risk group that warrants intensified surveillance and early discussion of transplant candidacy, especially when combined with other markers of decompensation. Whether AP will ultimately be incorporated into formal prognostic models for WD will depend on replication in larger, externally validated cohorts with multivariable analyses.
5. Clinical Implications: Diagnostic and Therapeutic Considerations
The intersection of WD and autoimmune markers presents both diagnostic challenges and therapeutic dilemmas. Previous case reports and series have shown instances of WD mimicking AIH, with elevated IgG levels, positive ANA or smooth muscle antibodies, and interface hepatitis, leading to misdiagnosis and delayed chelation therapy [7,8,9]. Interestingly, previous studies have shown that patients treated with D-penicillamine develop ANA positivity more frequently than healthy individuals, whereas zinc sulfate-treated patients have significantly higher levels of anti-neutrophil cytoplasmic antibodies (ANCAs), neuronal surface antibodies (NSAbs), and onconeural antibodies (ONAs) [10].
From a broader hepatological perspective, the occurrence of autoimmune serological markers is not unique to WD. Similar observations have been reported in other metabolic liver disorders, including hereditary hemochromatosis [11], α-1 antitrypsin deficiency [12,13], and non-alcoholic steatohepatitis [14], where IgG elevations may accompany chronic hepatic inflammation. In such settings, autoimmune markers are generally interpreted as secondary epiphenomena rather than evidence of primary autoimmune liver disease. Recognizing this broader context may help clinicians avoid overinterpreting autoantibody positivity in WD and highlight the need for a comprehensive diagnostic evaluation.
Nevertheless, Jiang et al. confirmed that AIH-like serologic and histologic features are relatively common in WD and stressed the importance of ruling out WD in patients suspected of having autoimmune liver disease, especially younger individuals. The authors found that in their retrospective cohort, treatment approaches did not significantly differ between AP-WD and NAP-WD. All patients received standard anti-copper therapy following guidelines, with minimal use of immunosuppression reported for AP alone. International recommendations also do not advise routine immunosuppression for WD based on autoantibody positivity or elevated IgG levels without a confirmed AIH diagnosis [2,15]. However, this study does not determine whether a subset of AP-WD patients may benefit from additional immunomodulatory therapy, as it was not designed for that purpose.
Importantly, there are rare clinical scenarios in which Wilson’s disease (WD) coexists with AIH [16,17]. In such cases, if the established diagnostic criteria for AIH are met and inflammatory activity persists despite adequate anti-copper treatment, immunosuppressive therapy may be considered. However, evidence supporting this approach is currently limited to case reports and small case series, and careful diagnostic reassessment is essential before initiating immunosuppression. Currently, routine immunomodulatory therapy cannot be recommended based solely on autoantibody positivity or elevated IgG levels in WD. Cases in which WD, AIH and hereditary haemochromatosis occur simultaneously are even more challenging to diagnose [18]. A case report of a 55-year-old patient presenting with this combination of diseases revealed that therapeutic attempts to treat hereditary haemochromatosis and WD with chelating agents had failed until the course of treatment with immunosuppressants targeting components of the AIH-related immune system was completed [18].
Future research should investigate how the different pharmacological agents for anti-copper treatments available interact with autoimmune markers and patient outcomes, considering the potential of D-penicillamine, trientine, tetrathiomolybdate, and other agents to modulate immune responses [19].
6. Mechanistic Questions and Research Agenda
Jiang et al. speculate on various mechanistic links between chronic copper overload and the development of AP, suggesting that copper-driven oxidative stress, increased exposure to autoantigens, danger-associated molecular patterns (DAMPs), and dysregulated T- and B-cell activation may contribute to the production of autoantibodies. While these ideas are consistent with general models of autoimmunity, direct mechanistic evidence in WD is still limited. Therefore, this study lays a solid clinical foundation for future mechanistic research. Key areas for further investigations include:
- Conducting longitudinal immunophenotyping to monitor changes in autoantibody profiles, IgG levels, and lymphocyte subsets following chelation or zinc therapy, and assessing whether immunologic remission correlates with improvements in biochemical and clinical outcomes.
- Incorporating neurological phenotyping, which was not consistently available in this study, to determine if AP/AIH is primarily associated with LRAEs or if it also affects neurological or psychiatric functions.
- Enrolling larger multicenter cohorts with standardized biopsy procedures to validate portal-plasmacytic signatures and identify whether specific histological patterns can predict treatment response or the risk of disease progression.
- Developing precise definitions of AP/AIH that consider autoantibody specificity, IgG subclasses (including immunoglobulin G4 (IgG4), and emerging neuronal surface antibodies, which may be especially relevant for the neuropsychiatric aspects of WD.
- Integrating findings on autoimmune occurrence and autoantibody specificity into existing advanced algorithms and machine learning techniques to improve personalized medicine in diagnosis and management of WD [20].
Ultimately, combining thorough clinical phenotyping, as demonstrated by Jiang et al., with detailed immunological investigations will be crucial in determining whether AP/AIH in WD is a consequence of copper toxicity, a significant factor in disease progression, or a targetable driver of worsening symptoms in certain patients.
7. Strengths and Limitations of the Study
The study has several notable strengths. First, the focus on treatment-naïve patients minimizes confounding by prior chelation, which can significantly alter both liver biochemistry and immune parameters. Second, the investigators implemented a comprehensive work-up including autoantibodies, immunoglobulins, copper indices, and cross-sectional imaging in all included patients, and they supplemented this with histology where available. Third, the follow-up duration of up to 60 months provides meaningful mid-term outcome data in a rare disease context.
At the same time, the limitations acknowledged by the authors are important for contextualizing the findings. This was a single-center cohort from a tertiary liver disease referral hospital in China, enriched for hepatic presentations with limited systematic neurological assessment, which may not fully represent the global WD population or those with predominantly neurological phenotypes. Immune markers were measured at a single time point, precluding assessment of dynamics, and only 17 patients had biopsy material, introducing potential selection bias and limiting histologic power. The administrative censoring at 60 months, applied for comparability between groups, inevitably constrains insights into very long-term risk. Finally, the reliance on univariable survival analyses leaves open the question of whether AP adds independent prognostic information beyond conventional scores.
8. Conclusions: Toward Immune-Informed Risk Stratification in Wilson’s Disease
Jiang et al. convincingly demonstrate that AP are common in treatment-naïve WD and are associated with more advanced hepatic dysfunction, a distinct inflammatory pattern on liver biopsy, and an increased risk of LRAEs over 5 years. Their work highlights the value of incorporating autoantibodies and IgG into the initial evaluation of WD, not to reclassify these patients as having primary autoimmune liver disease, but to flag a subgroup with heightened vulnerability who may benefit from more intensive monitoring and earlier referral for transplantation assessment. Accordingly, AP should presently be regarded as a clinically useful risk marker rather than a proven causal driver of adverse outcomes. As precision medicine increasingly penetrates the management of rare metabolic diseases, immune-informed stratification may emerge as an important layer atop genetic and biochemical profiling in WD. The study by Jiang et al. represents a substantial step toward this goal and should stimulate both mechanistic investigations and prospective, multicenter validation efforts to clarify how best to translate autoimmune markers into individualized care pathways for patients with WD.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Acknowledgments
The authors of this commentary thank the investigators and participants of the original study by Jiang et al. for their important contributions to advancing the understanding of immune phenomena in Wilson’s disease. Moreover, the author is grateful to Sabine Weiskirchen (IFMPEGKC) for preparing the figure for this commentary.
Conflicts of Interest
The author is an “Associate Editor of Livers” but was not involved in the peer-review or editorial decision-making process for this manuscript. I declare that I have no other competing interests.
Abbreviations
The following abbreviations are used in this manuscript:
| AIH | Autoimmune hepatitis |
| ANAs | Antinuclear antibodies |
| ANCAs | anti-neutrophil cytoplasmic antibodies |
| AP | Autoimmune phenomena |
| AP-WD | Patients with WD and AP |
| APRI | Aspartate Aminotransferase to Platelet Ratio Index |
| DAMPs | Danger-associated molecular patterns |
| IgG | Immunoglobulin G |
| INR | International Normalized Ratio |
| LRAEs | Liver-related adverse events |
| MELD | Model for End-Stage Liver Disease |
| NAP-WD | Patient with WD without AP |
| NSAbs | Neuronal surface antibodies |
| OMIM | Online Mendelian Inheritance in Man |
| ONAs | Onconeural antibodies |
| PELD | Pediatric End-Stage Liver Disease |
| WD | Wilson’s disease |
References
- Ferenci, P.; Caca, K.; Loudianos, G.; Mieli-Vergani, G.; Tanner, S.; Sternlieb, I.; Schilsky, M.; Cox, D.; Berr, F. Diagnosis and phenotypic classification of Wilson disease. Liver Int. 2003, 23, 139–142. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- European Association for the Study of the Liver. EASL-ERN Clinical Practice Guidelines on Wilson’s disease. J. Hepatol. 2025, 82, 690–728. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roberts, E.A.; Schilsky, M.L. Current and emerging issues in Wilson’s disease. N. Engl. J. Med. 2023, 389, 922–938. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jiang, H.; Tang, S.; Liang, C.; Liu, H.; Yu, H.; Zhang, S.; Li, M.; Wang, Y.; Hou, W.; Zheng, S. Impact of autoimmune phenomena on the clinical presentation and prognosis of Wilson’s disease: A retrospective cohort study. Metab. Target Organ Damage 2026, 6, 6. [Google Scholar] [CrossRef] [Scilit]
- Fallatah, H.I.; Akbar, H.O. Elevated serum immunoglobulin G levels in patients with chronic liver disease in comparison to patients with autoimmune hepatitis. Libyan J. Med. 2010, 5, 4857. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- European Association for the Study of the Liver. EASL Clinical Practice Guidelines on the management of autoimmune hepatitis. J. Hepatol. 2025, 83, 453–501. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stremmel, W.; Longerich, T.; Liere, R.; Vacata, V.; van Helden, J.; Weiskirchen, R. Wilson disease—The impact of hyperimmunity on disease activity: A case report. World J. Clin. Cases 2021, 9, 1386–1393. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jańczyk, W.; Bierła, J.B.; Trojanowska, I.; Wierzbicka-Rucińska, A.; Cukrowska, B.; Socha, P. Prevalence and significance of autoantibody seropositivity in children with Wilson’s disease. Diagnostics 2023, 13, 768. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sallam, D.E.; Guergues, G.T.; Samak, N.M.; Eladawy, M.; Mohammed, S.G.; Agour, A.M. A diagnostic dilemma in a child with Wilson’s disease. Pediatr. Nephrol. 2026; epub ahead of print. [CrossRef] [Scilit] [PubMed]
- Antczak-Kowalska, M.; Członkowska, A.; Eyileten, C.; Palejko, A.; Cudna, A.; Wolska, M.; Piechal, A.; Litwin, T. Autoantibodies in Wilson disease: Impact on clinical course. JIMD Rep. 2022, 63, 508–517. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barton, J.C.; Barton, J.C.; Bertoli, L.F.; Acton, R.T. IgG subclass levels in referred hemochromatosis probands with HFE p.C282Y/p.C282Y. PLoS ONE 2024, 19, e0302817. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Czaja, A.J. Frequency and significance of phenotypes for alpha1-antitrypsin deficiency in type 1 autoimmune hepatitis. Dig. Dis. Sci. 1998, 43, 1725–1731. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Phung, N.D.; Kubo, R.T.; Spector, S.L. Alpha 1-antitrypsin deficiency and common variable hypogammaglobulinemia in a patient with asthma. Chest 1982, 81, 112–115. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- De Roza, M.A.; Lamba, M.; Goh, G.B.; Lum, J.H.; Cheah, M.C.; Ngu, J.H.J. Immunoglobulin G in non-alcoholic steatohepatitis predicts clinical outcome: A prospective multi-centre cohort study. World J. Gastroenterol. 2021, 27, 7563–7571. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schilsky, M.L.; Roberts, E.A.; Bronstein, J.M.; Dhawan, A.; Hamilton, J.P.; Rivard, A.M.; Washington, M.K.; Weiss, K.H.; Zimbrean, P.C. A multidisciplinary approach to the diagnosis and management of Wilson disease: 2022 Practice Guidance on Wilson disease from the American Association for the Study of Liver Diseases. Hepatology 2025, 82, E41–E90. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thomas, G.; Koshy, A.; Mukkada, R.J.; Chettupuzha, A.; Peethambaran, M.; Paul, S.; Mathew, P.G.; Joseph, J.A.; Thomas, E.; Hari, M.; et al. Navigating complexity: A case with overlapping features of autoimmune hepatitis and Wilson’s Disease. J. Clin. Exp. Hepatol. 2024, 14, S19–S20. [Google Scholar]
- Gimiga, N.; Păduraru, G.; Bozomitu, L.I.; Ghiga, G.; Pânzaru, M.C.; Butnariu, L.I.; Scurtu, A.M.; Cojocaru, E.; Lupu, V.V.; Trandafir, L.M. Wilson’s Disease with Autoimmune Hepatitis Manifestation in a Pediatric Patient: A Case Report and Literature Review. J. Clin. Med. 2025, 14, 8798. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fatemi, R.; Movassagh-Koolankuh, S.; Mosadeghi, N. Simultaneous Occurrence of Wilson’s Disease, Autoimmune Hepatitis, and Hereditary Hemochromatosis: A Diagnostic Challenge. Middle East J. Dig. Dis. 2024, 16, 64–68. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weiskirchen, R. Comprehensive pharmacological management of Wilson’s disease: Mechanisms, clinical strategies, and emerging therapeutic innovations. Sci 2025, 7, 94. [Google Scholar] [CrossRef] [Scilit]
- Stremmel, W.; Weiskirchen, R. An initiative to promote the integration of artificial intelligence in transforming the diagnosis and management of Wilson disease in the 21st century. Metab. Target Organ Damage 2025, 5, 9. [Google Scholar] [CrossRef] [Scilit]
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the author. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.