


Abstract
Hypertension remains the leading preventable cause of cardiovascular disease and premature death worldwide. In the hypertensive state, renal and cardiovascular dysfunctions become entrenched in a self-perpetuating feedback loop, with immune cells emerging as central coordinators of this pathological crosstalk. This narrative review examines the mechanisms by which immune cells integrate signals from high salt, the renin–angiotensin–aldosterone system (RAAS), and the sympathetic nervous system (SNS) to drive chronic inflammation and end-organ damage. We highlight the salt-dendritic cell-isolevuglandin (IsoLG)-T cell axis as a critical pathway linking dietary sodium to immune activation and hypertension. We also explore bidirectional interactions between immune cells and RAAS components, as well as neuro-immune crosstalk that amplifies sympathetic outflow. Counter-regulatory mechanisms, including the ACE2/Ang-(1-7)/Mas axis, the kallikrein–kinin system, Urodilatin, Klotho, and renalase, provide endogenous braking signals that limit inflammation. Finally, we discuss emerging immunomodulatory therapeutic strategies and identify key unanswered questions for future research. Understanding immune cells as central coordinators of cardiorenal communication offers new opportunities for precision medicine approaches to hypertension.
1. Introduction
Hypertension, affecting approximately one-third of adults (more than1.3 billion people) worldwide, is the most common risk factor contributing to the global burden of cardiovascular morbidity and mortality [1]. Effectively managing hypertension significantly could avert millions of cardiovascular disease-related deaths annually [2]. The kidney and heart work together intimately to maintain blood pressure stability and their dysfunctions play inextricable roles in the development of hypertension [3,4].
Cardiovascular dysfunction and renal dysfunction are deeply interconnected. Impairment in one organ quickly creates a cascading negative impact on the other, often referred to as Cardiorenal Syndrome or Cardiovascular–Kidney–Metabolic (CKM) Syndrome [3,5]. Renal dysfunction is highly prevalent in cardiovascular disease (CVD), affecting approximately half of patients with cardiac conditions [6]. Cardiac dysfunction is highly prevalent in patients with kidney disease. About half of all patients with chronic kidney disease (CKD) stage 4/5 experience cardiovascular disease, and cardiovascular complication is the leading cause of death for CKD patients [7,8]. Cardiovascular and renal dysfunctions trigger chronic systemic high blood pressure through a self-perpetuating spiral of damage. Beyond hemodynamic factors, the renin–angiotensin–aldosterone system (RAAS) and sympathetic nervous system (SNS) play central roles in the cardiorenal connections underlying hypertension.
A large body of evidence demonstrated that hypertension is a state of chronic immune activation and low-grade systemic inflammation [9]. Immune cells interact closely with RAAS and SNS, forming a self-amplifying cycle that drives hypertension, chronic inflammation, tissue fibrosis, and progressive cardiorenal organ damage. Despite extensive research into the complex pathology of hypertension and the development of numerous effective medications, more than half of patients still have poorly controlled blood pressure [10]. Exploring the precise interconnected immune cells pathway in the cardiorenal axis is critically needed for developing better diagnostics and targeted therapies.
In this review we focus on the cardiorenal connections in hypertension and the central coordinator role of immune cells in this process (Figure 1). We provide a comprehensive synthesis of how immune cells sense hypertensive stimuli, integrate signals from RAAS and SNS, and amplify inflammation and tissue injury. We also highlight the emerging concept of neuro-immune circuits that link the brain, kidney, and cardiovascular system. Finally, we discuss the translational potential of immunomodulatory strategies and identify key unresolved questions that should guide future research.
Figure 1.
Immune cells act as central coordinators of cardiorenal crosstalk in hypertension. Immune cells integrate signals from hemodynamic stress, high salt, the renin–angiotensin–aldosterone system (RAAS), and the sympathetic nervous system (SNS) to disrupt the normal cardiorenal communication in blood pressure management. The dysregulated cardiorenal communication drives chronic inflammation, fibrosis and end-organ damage in cardiorenal system, causing progressive hypertension.
This narrative review was informed by searches of PubMed conducted through January 2026 to August 2026. Search terms included “Inflammation and Cardiorenal Syndrome”. Publications were selected for their relevance to immune mechanisms of hypertension and cardiovascular–renal communication, with attention to mechanistic studies, counter-regulatory pathways, and findings that differed across experimental settings. The literature was synthesized narratively; formal systematic-review screening and risk-of-bias assessment were not performed.
2. Pathophysiology of Cardiorenal Connections in Hypertension
Blood pressure is fundamentally determined by the product of cardiac output (CO) and systemic vascular resistance (SVR). The kidneys regulate systemic blood pressure by dynamically controlling blood volume and vascular tone, primarily through the renin–angiotensin–aldosterone system (RAAS) and the sympathetic nervous system (SNS) [11,12,13]. In turn, the heart provides hormonal signals, including atrial natriuretic peptide (ANP) and B-type natriuretic peptide (BNP), as well as neural inputs that regulate blood pressure by modulating vascular tone and renal sodium handling [14,15].
High dietary salt intake is one of the most common factors that directly increases blood volume, thereby elevating CO [16]. Elevated blood pressure increases glomerular hydrostatic pressure, resulting in a transient increase in the glomerular filtration rate (GFR) [17]. Increased renal blood flow suppresses the activity of sodium transporters, including the Na+/K+-ATPase and Na+/H+ exchangers, along the renal tubules [18]. Under physiological conditions, elevated systemic blood pressure suppresses SNS activity and renin release while stimulating the production of renal vasodilators through multiple counter-regulatory mechanisms [19,20]. In hypertension, however, this finely coordinated feedback system becomes disrupted because of renal and/or cardiovascular dysfunction, resulting in persistent elevation of blood pressure.
Endothelial dysfunction, vascular remodeling, and fibrosis are the major pathological processes responsible for vascular lumen narrowing and increased arterial stiffness, both of which elevate systemic blood pressure [21]. Endothelial dysfunction is characterized by impaired endothelial function, with reduced bioavailability of vasodilators, including nitric oxide, prostaglandins, and kinins, together with increased production of vasoconstrictors such as endothelin-1, vasopressin, and angiotensin II [22]. Nitric oxide is the principal endogenous vasodilator and promotes vascular smooth muscle relaxation through the cyclic guanosine monophosphate (cGMP) signaling pathway [23]. Oxidative stress and inflammatory cytokines are the primary drivers of impaired nitric oxide bioavailability [24]. Endothelin-1 (ET-1), primarily produced by the kidney and vascular endothelial cells, is the most potent endogenous vasoconstrictor. Binding to receptors on vascular smooth muscle cells, ET-1 triggers intracellular calcium influx, producing sustained vasoconstriction and increasing systemic vascular resistance [25,26].
In hypertension, renal and cardiovascular dysfunction establish a self-perpetuating vicious cycle that further increases CO and/or SVR. Prolonged systemic hypertension causes hypertensive nephropathy by damaging the glomerular microvasculature. Impaired renal filtration promotes sodium retention, fluid overload, and chronic inflammation, all of which contribute to sustained elevations in blood pressure [12]. Injured kidneys also release vasoactive mediators that promote vasoconstriction, vascular remodeling, and arterial stiffening, further exacerbating hypertension [27]. Sustained hypertension imposes chronic pressure overload on the heart, ultimately leading to adverse cardiovascular remodeling, including left ventricular hypertrophy (LVH), arterial injury, and eventually heart failure [28,29]. As cardiac function declines, reduced cardiac output diminishes renal perfusion and lowers effective arterial pressure [30]. The resulting renal hypoperfusion activates the RAAS, further increasing blood pressure and accelerating progressive injury to both the heart and kidneys [3,31]. In addition, impaired cardiac function elevates central venous pressure, causing renal venous congestion that further compromises renal function and perpetuates cardiorenal injury [32].
3. The Inflammatory Paradigm in Hypertension
Hypertension is increasingly recognized as a chronic systemic inflammatory condition. Excess sodium accumulation in tissues, hormones like angiotensin II (Ang II) and aldosterone, and overactive SNS are the most common factors that stimulate immune cell activation and infiltration into the heart, blood vessels, and kidneys [9,33]. Circulating monocytes and recruited T cells and macrophages infiltrate into the vessel walls, creating a chronic inflammatory cycle that accelerates arterial stiffening and vascular dysfunction [34,35]. The inflammatory immune cells accumulated in kidney produce pro-inflammatory cytokines and ROS, causing kidney injury, driving sodium retention and blood volume expansion [33,36]. On the other hand, once the blood pressure is elevated, immune cells can sense the mechanical stretch and amplify the inflammatory cycle. Mechanical stretch from high blood pressure triggers the bone marrow to release more inflammatory monocytes into the bloodstream [37]. High blood pressure physically stretches the endothelial cells, triggering the release of pro-inflammatory cytokines and reactive oxygen species, which recruit immune cells into the walls of blood vessels [38]. Mechanical stretching of high blood pressure triggers neutrophils to release reactive oxygen species (ROS) and neutrophil extracellular traps (NETs) through influx of calcium by activation of TRPV4 and PIEZO1 channels [39,40].
The immune cells integrate signals from high salt, the RAAS, and the SNS to drive chronic inflammation and cardiorenal system end-organ damage. Figure 2 illustrates how immune cells integrate signals from the cardiovascular and renal systems to influence blood pressure regulation. Depending on their phenotype and the physiological context, immune cells may support homeostasis or amplify inflammation and tissue injury. Hypertension can develop when maladaptive immune–cardiorenal interactions overwhelm counter-regulatory mechanisms.
Figure 2.
Schematic illustration of the role of immune cells in cardiorenal communication. The balance of pro-inflammatory and anti-inflammatory immune cells determines the blood pressure health status. In healthy bodies, blood pressure is maintained stably through normal cardiorenal communication and multiple counter-regulatory mechanisms. Dysregulated cardiorenal communication disrupts the immune cell balance, promoting renal dysfunction and cardiovascular dysfunction. Sustained sodium retention and vascular stiffening lead to hypertension.
4. Salt-Mediated Immunologic Response as a Link Between Renal Dysfunction and Hypertension
High dietary salt levels have been associated with hypertension. To keep the blood pressure stable, the kidneys actively maintain sodium and water balance through pressure natriuresis [41]. In hypertensive individuals, renal inflammation, ROS, and hyperactive sodium channels impair pressure natriuresis, resulting in sodium retention [42,43]. Continued research has shown that excess Na+ accumulates in the skin, skeletal muscle and interstitium rather than just circulating in the bloodstream [44,45,46]. Furthermore, patients that demonstrate limited therapeutic response to hypertension treatment have higher tissue sodium levels [47,48]. The role of tissue sodium storage in causing hypertension is related to both innate immune cells and adaptive immune cells, like T cells, dendritic cells and macrophages [31,49,50].
4.1. T Lymphocytes in Salt-Sensitive Hypertension
Accumulating evidence suggests that T lymphocytes are important drivers of salt-sensitive hypertension [51,52]. Guzik and colleagues demonstrated that RAG-1-deficient mice, which lack T and B lymphocytes, were protected against DOCA-salt- and Ang II-induced hypertension. However, transfer of T cells, but not B cells, restored the hypertensive response, highlighting the central role of T cells in blood pressure regulation [51]. The role of B cells in hypertension shows contradictory results and requires further investigation [53,54]. Further studies indicate activated pro-inflammatory T cells (including Th17, Th1, CD8+ T cells, γδ T Cells) infiltrate into the kidneys and blood vessels, leading to hypertension. In the kidneys, they release inflammatory substances such as IL-17A and TNF-α, which increase sodium reabsorption, promote inflammation and fibrosis, and impair kidney function [55,56]. In blood vessels, they release IL-17A, IFN-γ, and reactive oxygen species, leading to inflammation, reduced nitric oxide, poor blood vessel relaxation, and increased stiffness [31,57]. Together, these kidney and blood vessel changes increase blood pressure and contribute to salt-sensitive hypertension.
Exposure to high salt environments has been found to suppress Treg and promote Th17 [49,58]. The relationship between high salt intake, immune cell activation, and hypertension is illustrated in Figure 3. Tregs are a specialized subset of CD4+ T cells that express the transcription factor forkhead box protein 3 (FOXP3). Regulatory T cells suppress excessive immune responses and maintain immune tolerance. Their protective effects in experimental hypertension include IL-10-mediated suppression of inflammation, although the effects of IL-10 on blood pressure and renal injury depend on the experimental context [59]. Both the number and function of regulatory Tregs are reduced in people and animal models with hypertension [60,61]. High salt exposure further impairs their suppressive function by activating serum/glucocorticoid-regulated kinase 1 (SGK1), which reduces FOXP3 expression and increases interferon-gamma (IFN-γ) secretion [58]. Reduced IFN-γ may restore some of the immune-suppressive activity of these Tregs [58]. At the same time, high salt promotes differentiation of naïve T cells into Th17 cells through the p38/MAPK pathway involving NFAT5 and SGK1. Inhibiting p38/MAPK, NFAT5, or SGK1 prevents high salt-induced Th17-cell development [49]. This shifts from protective Treg responses to inflammatory Th17 contributes to kidney and vascular injury, sodium retention, and ultimately salt-sensitive hypertension.
Figure 3.
High salt diet drives immune activation and salt-sensitive hypertension. Salt accumulation increases intracellular Na+ in dendritic cells, leading to ROS production. ROS increases the isolevuglandin (IsoLG)-protein adducts. The IsoLG-protein adducts act as antigens, driving naïve T cells to differentiate into pro-inflammatory T17 cells, producing IL-17A, IFN-γ, and TNF-α. At the same time, high salt suppresses Treg cells, decreasing IL-10 production. High salt concentrations trigger macrophages by shifting them into M1 phenotype while suppressing their M2 phenotype. Pro-inflammatory Th17 cells and M1 macrophages drive vascular dysfunction and kidney dysfunction, leading to the development of SSBP. In some conditions, high salt intake decreases renal TNF-α production, which lowers the natriuretic function of TNF-α in the kidney through TNFR1 activation.
4.2. Dendritic Cells and Antigen Presentation in Hypertension
Our work demonstrated that dendritic cells (DCs) play a critical role as professional antigen-presenting cells (APCs) through a specific pathway: ROS lead to lipid peroxidation of arachidonic acid, forming immunogenic IsoLG-protein adducts [62]. ENaC is a constitutively active channel that allows Na+ influx; in renal epithelium it reabsorbs Na+, regulating BP and volume [63]. ENaC serves as a direct route for extracellular sodium entry when tissue sodium levels rise. ENaC α- and γ-subunits are present on DCs of mice, while human APCs express ENaC α- and δ-subunits [64,65]. A process regulated by SGK1 increases ENaC α- and γ-subunit expression in mouse APCs [66]. In vivo models with ENaC α-subunit knockout or pharmacological inhibition show decreased salt-induced DC activation, reduced inflammasome signaling, and lowered hypertensive responses [67].
Sodium-hydrogen exchanger 1 (NHE1) exchanges an intracellular H+ for an extracellular Na+ to maintain cell pH. NHE1 was identified as a part of a dual sodium influx transport system alongside ENaC in dendritic cells. Inhibition of NHE1 with a selective inhibitor or NHE1 siRNA hindered a key step of NADPH oxidase activation that involves the association of p47phox with gp91phox [64]. As a key producer of ROS, NADPH oxidase is directly involved in the activation of dendritic cells and subsequent immune responses that lead to hypertension [64]. It has been demonstrated across multiple studies that excess intracellular sodium in DCs converges onto the activation of NADPH oxidase complexes. This enzyme system is assembled via a Ca2+/protein kinase C (PKC)-mediated phosphorylation of p47phox, which then associates with gp91phox and starts rapidly generating superoxides (O2−), a type of reactive oxygen species [64]. Generation of superoxides leads to superoxide-driven lipid peroxidation, ultimately causing the formation of IsoLGs. These are highly reactive γ-ketoaldehydes that form noncovalent adducts with lysine residues on proteins [68]. The IsoLG-protein adduct is presented to DCs as a neo-antigen that converts DCs into a hyperinflammatory phenotype. Furthermore, the accumulations of IsoLGs promote the secretion of pro-inflammatory cytokines from DCs, such as IL-1β [64]. Upon activation by IsoLGs, NLRP3 assembles with apoptosis-associated speck-like protein (ASC) and caspase-1 in DCs, which results in the cleavage of pro-IL-1β into its active IL-1β form [67]. Through IL-1β release, APCs promote T cell release of cytokines IL-17A and IFN-γ. IL-17A and IFN-γ are the most notorious pro-inflammatory drivers that directly promote vascular damage and renal damage, exacerbating high blood pressure. IL-17A contributes to hypertension by driving vascular oxidative stress and endothelial dysfunction while enhancing the renal sodium retention via SGK1 mediated transport [69]. Experimental models have shown that blocking NADPH oxidase reduces IsoLG-adduct formation, subsequently decreasing T cell activation and blood pressure elevation [70]. A recent study by our group showed that Janus kinase 2 (JAK2) in CD11c+ cells play critical roles in this progress [71]. Janus kinase 2 (JAK2), signal transducer and activator of transcription 3 (STAT3), and SMAD family member 3 (SMAD3) participate in signaling mechanisms that regulate immune function [71]. Salt loading upregulates the JAK2/STAT3/SMAD3 signaling in APCs from patients with salt-sensitive hypertension, while simultaneously suppressing the suppressor of cytokine signaling (SOCS) proteins that downregulate JAK signaling. This increases immunologic response conditions that lead to hypertension. Additionally, mouse model testing suggests that JAK2 expression in CD11c+ myeloid cells is necessary for salt-induced hypertension, for a conditional knockout of JAK2 protected mice from developing hypertension and they displayed normal renal responses to volume expansion [71].
4.3. Macrophages in Hypertension
In response to hypertensive stimuli, circulating monocytes transmigrate through the blood vessel walls and transform into inflammatory macrophages, releasing damaging cytokines (such as TNF-α, IL-1b and TGF-β) which promote inflammation and fibrosis, increasing peripheral resistance [31,72,73]. De Ciuceis et al. found homozygous osteopetrotic mice, lacking normal macrophage activity due to deficient macrophage colony-stimulating factor (m-CSF), were protected from BP elevation and vascular damage [74]. Infiltration of macrophages into the renal interstitium causes local renal injury and fibrosis, which directly impairs sodium handling [75]. The accumulation of macrophages in the heart promotes pathological cardiac hypertrophy and progressive myocardial dysfunction [76]. In addition, macrophages release cytokines that trigger further recruitment of adaptive immune cells to the cardiorenal system, creating a vicious cycle of inflammation that raises blood pressure [31].
High salt concentrations trigger macrophages by shifting them into M1 phenotype while suppressing their M2 phenotype through p38 MAPK, NFAT5 and SGK1 pathways [50,77,78]. Pro-inflammatory M1 macrophage buildup in the kidney and cardiovascular system releases ROS and pro-inflammatory cytokines, which trigger chronic oxidative stress and inflammation [79]. Conversely, M2 macrophages produce anti-inflammatory cytokines, such as IL-10 and TGF-β. Macrophages with reparative or immunoregulatory phenotypes can suppress inflammation and support tissue repair [72]. However, macrophage functions extend beyond the conventional M1/M2 classification, and their effects on blood pressure depend on the tissue environment and signaling pathways engaged.
4.4. Context-Dependent Roles of Cytokines in Hypertension
The roles of immune cells in blood pressure control are complex. Typically, pro-inflammatory cytokines were believed to drive hypertension via chronic, low-grade inflammation, while anti-inflammatory cytokines act as a counterregulatory mechanism to suppress this damage. However, this classic notion is challenged by some evidence from recent studies. For example, when TNF-α binds to TNF receptor 1 (TNFR1) in the kidney, it triggers a natriuretic and diuretic response to lower blood pressure [80,81]. In some conditions, high salt intake decreases renal TNF-α production, suggesting the natriuretic function of TNF-α in the kidney [82]. A meta-analysis showed anti-TNF agents may increase the risk of developing hypertension in rheumatoid arthritis patients, again suggesting diverse roles of TNF-α in blood pressure control [83]. As a typical anti-inflammatory cytokine, Il-10 may also play a pro-inflammatory role in certain conditions, such as Ang II-induced salt-sensitive hypertension [84].
4.5. Endothelin Signaling in Immune–Cardiorenal Crosstalk
High salt intake increases ET-1 production in the kidney, as well as non-renal tissues such as blood vessels and skin [85,86]. As a well-known potent vasoconstrictor, ET-1 may also act locally in the kidneys or skin to maintain sodium homeostasis [87,88]. ETA receptors and ETB receptors are the two main receptors of ET-1. When ET-1 binds to the ETA receptor on vascular smooth muscle cells, it triggers strong vasoconstriction and inflammation, while activation of ETB receptors in the kidney and skin promotes sodium secretion [87,88,89]. Disruption of the ETB receptor may cause severe salt-sensitive hypertension [89,90]. Both ETA and ETB receptors are expressed in various immune cells, including T lymphocytes, B lymphocytes, neutrophils, monocytes, macrophages, and dendritic cells [91,92]. Some immune cells produce their own ET-1, such as monocytes, macrophages, and dendritic cells, suggesting the important role of the endothelin system in immune cells communication in the pathogenesis of hypertension [92,93]. Czopek et al. demonstrated that macrophages internalize ET-1 through ETB receptor-mediated endocytosis, providing a clearance mechanism that can limit its hypertensive effects [94]. Our previous study showed that a high-sodium environment stimulates IsoLG formation in DCs, which promotes the production of Endothelin 3 (ET-3). ET-3 interacts with ETB receptors on renal lymphatic endothelial cells, altering their pumping dynamics. This results in renal lymphangiogenesis, immune cell infiltration and activation, kidney injury, and elevated blood pressure [95].
4.6. Gut Microbiota and Hypertension
High dietary salt intake may alter gut microbial composition and host–microbial interactions, potentially contributing to immune dysregulation and elevated blood pressure [96,97]. High dietary salt levels in both humans and mice change the gut microbial composition, specifically increasing Firmicutes, Proteobacteria, and Prevotella, but depleting beneficial bacteria like Lactobacillus. A high salt diet in mice induces systemic inflammation in vascular tissues such as the mesenteric arteries and aorta, enhancing susceptibility to Ang II. When transferring fecal matter, hence microbiota, from high salt-fed mice to germ-free mice, it predisposed them to increased inflammation and hypertension phenotypes [98].
Emerging evidence indicates that microbial metabolites, particularly short-chain fatty acids (SCFAs) like butyrate and propionate, play protective roles by promoting Treg differentiation and reducing inflammation. Conversely, dysbiosis leads to reduced SCFA production and increased levels of pro-inflammatory metabolites [99,100]. Gut-derived signals also influence kidney function, sympathetic outflow and renin release [101]. These findings open the possibility for microbiome-targeted interventions such as probiotics, prebiotics, or dietary fiber supplementation as adjunctive therapies in hypertension.
5. Renin–Angiotensin–Aldosterone System (RAAS) and Immune Cell Interactions
5.1. Overview of RAAS in Hypertension
The renin–angiotensin–aldosterone system (RAAS) is a central hormone system that regulates blood pressure. Chronic activation of the RAAS causes excessive vasoconstriction and sodium retention, which leads to hypertension [102]. Multiple mechanisms are involved in elevating blood pressure in the RAAS. Renin is released by renal juxtaglomerular cells in response to reduced renal perfusion pressure, decreased NaCl delivery to the macula densa, or sympathetic stimulation. Renin acts upon angiotensinogen, converting it into Angiotensin I (Ang I). Angiotensin-converting enzyme (ACE) converts Ang I into Ang II, which is the primary effector peptide acting on the AT1 receptor (AT1R) to constrict arterioles. Ang II triggers the adrenal glands to release aldosterone, which activates ENaC and SGK1, prompting the kidneys to retain sodium. Ang II signals the pituitary gland to release antidiuretic hormone (ADH), which further increases water reabsorption in the kidneys. In addition to circulating Ang II, locally generated intrarenal Ang II activates AT1 receptors, promoting renal sodium reabsorption and vasoconstriction [13,103]. Furthermore, both Ang II and aldosterone act on the brain to stimulate thirst and salt appetite, driving a subsequent expansion of total blood volume [104].
RAAS is a crucial survival mechanism in evolutionary history and remains functional in specific situations in modern ages, such as severe trauma and dehydration [105]. Chronic hyperactivation of the RAAS is highly prevalent in contemporary populations, primarily driven by environmental and lifestyle stressors. This continuous upregulation establishes a destructive cycle of vasoconstriction, oxidative stress, and inflammation. Bidirectional communication between immune cells and RAAS is shown in Figure 4.
Figure 4.
Bidirectional communication between immune cells and renin–angiotensin–aldosterone system (RAAS). The major RAAS components, including renin, Ang II and aldosterone, are bidirectionally communicated with immune cells. They interact with various immune cells to balance the inflammation status and blood pressure. Multiple counter-regulatory mechanisms are involved to provide endogenous braking signals that limit inflammation, including ACE2, kallikrein–kinin system (KSS), and kidney released Urodilatin, Klotho, and endothelin system. Impaired communication between immune cells and RAAS interrupts the balance, leading to hypertension. Pharmacological blockades of this communication, such as angiotensin-converting enzyme inhibitors (ACEIs), angiotensin receptor blockers (ARBs) and endothelin receptor antagonists (ERAs), are promising immunomodulatory strategies for managing hypertension.
5.2. Bidirectional Communication Between Immune Cells and RAAS
Pro-inflammatory cytokines secreted from immune cells bind to receptors on juxtaglomerular cells, altering intracellular cyclic AMP (cAMP) levels driving renin gene transcription and releasing of stored renin [106,107]. Oh et al. demonstrated that renal macrophages can directly promote juxtaglomerular cells to secrete renin, through their increased release of miR-106b-5p [108]. On the other hand, renin triggers inflammatory pathways in immune cells. Renin activates (pro)renin receptor expressed in monocytes and T cells, triggering intracellular ERK1/2 phosphorylation, enhancing the secretion of cytokines like IL-6, TNF-α, and inflammatory mediators like cyclooxygenase-2 [109,110,111].
Pro-inflammatory cytokines stimulate hepatocytes and renal cells to upregulate angiotensinogen (AGT) production, accelerating Ang II formation [112,113]. A study by Lai et al. demonstrated that cytokine IL-6 drives angiotensinogen expression in the liver through activation of JAK/STAT3 and JAK/p38/NF-kB signaling pathways [114]. While systemic AGT is primarily synthesized in the liver, localized renal inflammation triggers intrarenal AGT production, leading to localized Ang II spikes, promoting vasoconstriction, ROS production, and fibrosis [115]. In the kidney, IL-6 acts directly on renal proximal tubules to initiate angiotensinogen (AGT) transcription through the NF-κB and JAK-STAT pathways [116,117].
Ang II functions as an inflammatory mediator by activating the Ang II receptors expressed in immune cells, such as T lymphocytes, dendritic cells, macrophages, and neutrophils [118]. At the same time, inflammatory conditions upregulate the angiotensin receptors (particularly the AT1R subtype), increasing the immune cell’s sensitivity to Ang II [119]. Ang II binds to AT1Rs on native Cd4+ T cells, activating naive CD4+ T cells to pro-inflammatory Th1/Th17 cells while suppressing the master regulator of regulatory T cells (Tregs) [120,121].
Activation of AT1Rs on T cells activates the PKA–proteasome pathway, promoting the degradation of IkBa and MKP-1. Degradation of these inhibitory proteins upregulates NF-kB and STAT1, triggering the production of Th1 cytokines such as IFN-γ and TNF-α, suppressing FoxP3 expression [120,121,122,123]. AT1R activation enhances T cell responsiveness to inflammatory cytokines (like IL-6 and IL-12), activating STAT3 and RORgt, driving naïve T cells to differentiate into the Th17 [120,121,124]. With the presence of Ang II, TGF-β signaling acts to disrupt immune tolerance by shifting the differentiation of naïve T cells diverted away from the Treg pathway and into the pro-inflammatory Th17 pathway [121,125]. The accumulation of activated Th1/Th17 T cells in kidneys and blood vessels secretes cytokines that increase inflammation, contributing significantly to high blood pressure and vascular remodeling [51,126,127]. Moreover, Ang II acts as a co-stimulatory molecule binding to AT1R on CD8+ T cells to synergize with the T cell receptor (TCR) and enhance T cell proliferation and differentiation [119]. NK cells are also fully equipped with RAAS elements. They produce and deliver Ang II to localized sites of inflammation, which triggers the maturation of other innate immune cells, like dendritic cells and macrophages [124,128].
Type 1 angiotensin receptors expressed on CD11c+ dendritic cells act as an immune-regulatory brake. They suppress dendritic cell maturation and constrain T cell activation, limiting pro-inflammatory cytokine release and fluid retention [129]. Ang II causes vascular smooth muscle cells, endothelial cells, and macrophages to release Monocyte Chemoattractant Protein-1 (MCP-1) [130,131,132]. Ang II binds to the AT1R, stimulates NADPH oxidase, resulting in a rapid increase in intracellular ROS. The ROS production and G protein signaling activate several mitogen-activated protein kinase (MAPK) pathways, specifically ERK1/2 and p38 MAPK. The activated MAPKs, alongside calcium signaling, stimulate the translocation of the Nuclear Factor kappa-light-chain-enhancer of activated B cells (NF-κB) transcription factor to the nucleus, promoting the MCP-1 gene expression [132,133,134]. MCP-1 binds to CCR2 on monocytes, drawing them into the arterial wall, heart and kidneys where they turn into macrophages and contribute to hypertension [135]. The activation of NF-κ B also upregulates adhesion molecule gene expression on endothelial cells, such as ICAM-1, VCAM-1, and E-selectin, which promotes the infiltration of immune cells including T cells, macrophages, and neutrophils into vessel walls and kidneys [34,130,136]. Ang II prompts endothelial cells to release inflammatory chemokines (such as IL-8), which rapidly recruit neutrophils to sites of injury [137]. Similarly, Ang II stimulates neutrophils to produce high amounts of ROS [138]. Ang II triggers neutrophils to release neutrophil extracellular traps (NETs) that can cause blood clots and vascular inflammation [139]. While Ang II stimulates neutrophils, activated neutrophils can also release proteases (such as cathepsin G) that convert Ang I directly into Ang II, sustaining local inflammation [137,140]. Ang II stimulates B cells to differentiate into plasma cells that secrete large amounts of Immunoglobulin G (IgG). These antibodies accumulate in the walls of blood vessels, promoting structural remodeling and stiffness. The deposition of IgG triggers the recruitment of pro-inflammatory macrophages and T cells to the vascular wall, which worsens endothelial dysfunction and increases oxidative stress [54,141]. Recruitment and activation of immune cells, including T cells, macrophages, neutrophils, and B cells, within the kidneys, heart, and vasculature can contribute to renal dysfunction, vascular remodeling, and sustained hypertension. The consequences depend on the recruited cell populations, their activation states, and the affected tissue [111,142]. Angiotensin-converting enzyme inhibitors (ACEIs) and angiotensin receptor blockers (ARBs) modulate the immune system by blocking pro-inflammatory AT1Rs. This suppresses leukocyte recruitment, reduces the secretion of pro-inflammatory cytokines, and mitigates long-term tissue damage [113,120,142].
In addition, Ang II may interact with immune cells indirectly to regulate blood pressure through other pathways. For example, Ang II stimulates endothelial and smooth muscle cells to express ET-1, which mediates vasoconstriction and immune cell activation, ultimately driving vascular inflammation [143]. It is worth noting that our previous study found that acute dietary salt changes do not alter the expression of RAAS-related genes in human myeloid cells. This result suggests that high salt exposure activates ENaC in APCs not through the RAAS, but relying on alternative pathways [144].
5.3. Aldosterone and Mineralocorticoid Receptor Signaling
Aldosterone drives inflammation by activating mineralocorticoid receptors (MRs) on dendritic cells, T cells, and macrophages. Aldosterone activates dendritic cells, triggering the release of pro-inflammatory cytokines like IL-6 and TGF-β, and downregulates programmed death-ligand 1 (PD-L1) [145,146]. Through dendritic cell interactions, aldosterone polarizes CD4+ T cells toward a Th17 phenotype and activates CD8+ cytotoxic T cells [147]. MR signaling alters the distribution of T cells, reducing circulating naive T cell counts in the blood while upregulating migration markers like CXCR4, causing them to accumulate in the kidneys and aorta [148]. Once MR is activated by aldosterone, T cells are differentiated into subsets Th1 and Th17 phenotypes while suppressing anti-inflammatory regulatory T cells (Tregs) [149]. MR activation regulates CD8+ and CD4+ T cells, driving the secretion of IFN-γ, a cytokine that promotes superoxide generation and inflammation [150,151]. Aldosterone triggers monocytes and macrophages to release inflammatory cytokines like IL-6 and TGF-β1, promoting migration into vascular walls, leading to tissue remodeling, plaque instability, and fibrosis [145,152]. Mineralocorticoid receptor antagonists (MRAs), like spironolactone and finerenon, have been shown to reduce the polarization of inflammatory Th17 cells by monocyte-derived dendritic cells [153,154].
5.4. Counter-Regulatory Mechanisms of RAAS
Multiple intrinsic counter-regulatory pathways are employed to mitigate hyperactivation of RAAS and maintain blood pressure homeostasis (Figure 4). Renin is the initiating and rate-limiting enzyme of RAAS. Live-tissue mapping showed that high Ang II triggers rapid calcium oscillations across neighboring juxtaglomerular cells. This calcium surge acts as a physical biological brake to shut down renin overproduction [155,156]. Urodilatin, synthesized in the distal tubules of the kidney, inhibits renin secretion and blocks aldosterone releasing [157]. In addition, Urodilatin binds to Natriuretic Peptide Receptor A (NPR-A) receptors in the renal medullary collecting ducts, increasing cyclic GMP (cGMP). Elevated cGMP activates protein kinase G (PKG) and inhibits sodium (Na+) entry via apical amiloride-sensitive sodium channels and suppresses water reabsorption [157]. Urodilatin also exhibits anti-inflammatory effects by modulating the function of immune cells, including neutrophils and macrophages, and inhibited the generation ROS, suppressing pro-inflammatory cytokines like TNF-α and IL-6 [158,159].
The ACE2/Ang-(1-7)/Mas receptor axis is “counter-regulatory” arm of the RAAS. Angiotensin-converting enzyme 2 (ACE2) breaks down the Ang II into Angiotensin-(1-7) [160]. Ang-(1-7) binds to the Mas G protein-coupled receptor to trigger cellular responses, such as promotion of nitric oxide synthesis, inhibition of pro-inflammatory cytokines, suppression of fibrogenesis, and prevention of oxidative stress and NLRP3 inflammasome [161]. Activation of the Mas receptor in macrophages suppresses the pro-inflammatory M1 state and drives their polarization toward an anti-inflammatory M2 -like phenotype [162].
The kallikrein–kinin system (KKS) is an important hormonal system that counteracts RAAS and lowers blood pressure [163]. The enzyme kallikrein acts on kininogens to generate kinins (mainly bradykinin), which bind to the B2 receptor on kidneys and blood vessels, promoting sodium excretion and stimulating the release of vasodilators, such as nitric oxide and prostaglandins [164,165]. Bradykinin plays a critical role in immune homeostasis [166]. Bradykinin suppresses the Type I Interferon (IFN) responses by inhibiting the phosphorylation of STAT2, preventing excessive inflammation [167]. Experimental approaches delivering the kallikrein gene were developed to combat hypertension [168]. ACE inhibitors not only reduce the production of the Ang II, but also prevent the breakdown of bradykinin simultaneously [163,165]. Angiotensin receptor blockers (ARBs) block the angiotensin type 1 receptors directly. Blocking AT1, the excess Ang II is diverted to act on AT2 receptors. AT2 receptor stimulation activates the tyrosine phosphatase SHP-1, which subsequently upregulates prolylcarboxypeptidase (PRCP). PRCP acts as a catalyst that converts plasma prekallikrein into active plasma kallikrein, activating KKS [169,170].
5.5. The FGF23–Klotho Axis in Hypertension
The FGF23–Klotho axis is another important hormonal pathway interconnected with RAAS to manage blood pressure [171]. Fibroblast Growth Factor 23 (FGF23) is a hormone secreted primarily by osteocytes in response to rising phosphate levels or active vitamin D (1,25-dihydroxyvitamin D). FGF23 is massively elevated in hypertension patients with CKD. FGF23 suppresses the synthesis of active vitamin D in the kidneys by downregulating the expression of the enzyme 1α-hydroxylase (CYP27B1). Simultaneously, it stimulates the enzyme 24-hydroxylase (CYP24A1), which breaks down active vitamin D into inactive metabolites [172]. Vitamin D is a potent inhibitor of renin and its deficiency leads to increased renin biosynthesis, effectively upregulating RAAS [173]. In addition, FGF23 promotes sodium reabsorption by upregulating the sodium/chloride co-transporter (NCC) on the distal convoluted tubule of the kidney through the ERK1/2 and SGK1 pathways [174]. FGF23 promotes sympathetic overactivity by activating FGFR4-calcineurin signaling [175]. Ang II directly stimulates FGF-23 production in osteocytes and FGF-23 suppresses Ace2 in the kidney, preventing the breakdown of Ang II [176,177]. Aldosterone interacts with mineralocorticoid receptors (MRs) in osteoblasts and osteocytes, stimulating the expression of the FGF23 gene [178]. Ang II and aldosterone upregulate FGF23 production but act directly to reduce renal expression of Klotho on renal tubules [171].
Klotho, a crucial anti-aging protein highly expressed in all major tubular segments of kidneys, functions as an obligatory co-receptor of FGF23 to regulate the production of active vitamin D and signal the kidneys to excrete excess phosphate [179]. In CKD patients, their kidneys lose the ability to produce the Klotho protein. Klotho suppresses RAAS activity through the Wnt/β-catenin signaling pathway [180]. The Wnt/β-catenin pathway positively regulates the transcription of multiple RAS genes [181]. Klotho binds directly to Wnt proteins (such as Wnt1, Wnt4, and Wnt7a), blocking β-catenin activation and its entry into the cell nucleus [180]. Klotho inhibits vascular smooth muscle cells (VSMCs) from transforming into osteoblast-like cells, directly stopping arterial stiffening [182]. Klotho shields cardiomyocytes from structural remodeling, preventing left ventricular hypertrophy (LVH) by reducing systemic oxidative stress and limiting abnormal cellular signaling (such as the p38 and ERK pathways) [183,184].
During periods of severe systemic inflammation, activated macrophages produce FGF23 locally. The locally produced FGF23 interacts with FGFRs to directly stimulate the expression of pro-inflammatory cytokines like TNF-α and inhibit anti-inflammatory-like Arginase-1 [185,186]. High circulating levels of FGF23 bind to FGFR2 on neutrophils, impairing the ability to navigate to sites of inflammation [187]. FGF23 acts to suppress active vitamin D production in the kidneys, which exaggerates inflammatory responses and impaired infection clearance [185,188]. Research suggests that elevated FGF23 could be a novel marker for identifying individuals at higher risk for developing high blood pressure [189].
The Klotho protein acts as a systemic anti-inflammatory factor by suppressing pathways such as NF-kB and the NLRP3 inflammasome, ultimately reducing the production of active inflammatory cytokines [190]. Klotho directly limits the production of pro-inflammatory cytokines like IFN-γ, TNF-α, and IL-6 from T cells, suppressing the differentiation of Th1 and Th17 cells while promoting the activity of Tregs [188,191]. Klotho protects monocytes from DNA damage and stress-induced senescence, reducing the secretion of pro-inflammatory cytokines while boosting anti-inflammatory markers like IL-10 [192]. It actively shifts macrophages away from the pro-inflammatory M1 type and toward the anti-inflammatory M2 type [188]. Preclinical studies indicate that restoring Klotho levels can stop further increases in blood pressure and mitigate end-organ damages in the cardiorenal system [171,184,193].
6. Sympathetic Nervous System (SNS) and Immune Interactions
6.1. SNS Overactivation in Hypertension
Acute sympathetic activation raises blood pressure to support perfusion during physical stress or threat. Sustained sympathetic activation, however, can contribute to hypertension through persistent vascular, renal, and immune effects [194]. Chronic overactivation of SNS continuously releases norepinephrine, which binds to b1 adrenergic receptors in the heart. This accelerates heart rate and increases myocardial contractility. It acts on vascular a1 receptors to constrict blood vessels and increase arterial stiffness, which elevates systemic blood pressure and increases the heart’s workload [195]. In the kidney, sympathetic signals constrict the renal arteries, reducing renal blood flow and the Glomerular Filtration Rate (GFR), which limits the kidney’s ability to excrete sodium and water properly [196]. Increased SNS releases norepinephrine, which binds to a-adrenergic and b-adrenergic receptors on the basolateral membranes of tubular cells, stimulating Na and K-ATPase activity, directly driving the proximal tubule to absorb more sodium and water [197].
Norepinephrine released from renal sympathetic nerves binds directly to b1-adrenoceptors on juxtaglomerular (JG) granular cells, activating the cAMP pathway. Elevated intracellular cAMP levels activate protein kinase A (PKA), triggering the phosphorylation and exocytosis of renin into the bloodstream [198]. On the other hand, sustained sympathetic overactivity leads to cardiac hypertrophy and renal disfunction, which in turn trigger sensory afferent nerves that signal the brain and central sympathetic outflow [199,200].
6.2. Neuro-Immune Crosstalk
The SNS directly innervates primary and secondary lymphoid organs, including bone marrow, thymus, spleen, and lymph nodes [201]. For example, sympathetic nerve activation significantly drives the mobilization and release of hematopoietic stem and progenitor cells (HSPCs) from the bone marrow into the peripheral circulation, thereby influencing the systemic immune repertoire [202]. As shown in Figure 5, SNS overactivation stimulates immune cells (such as T cells, macrophages, and neutrophils) to release pro-inflammatory cytokines, causing arterial stiffening, endothelial dysfunction, and fluid retention. Research by Marvar et al. demonstrated that noradrenaline can activate T cells and promote their infiltration into blood vessel walls, leading to peripheral vascular inflammation [203]. Increasing evidence showed that elevated norepinephrine from nerve terminals activates adrenergic receptors on T cells, promoting their accumulation in the kidneys and blood vessels and creating a feedforward mechanism that raises blood pressure [204,205,206]. Catecholamines (noradrenaline and adrenaline) activate α and β adrenergic receptors expressed on macrophages, creating antagonistic effects [207]. When catecholamines bind to α1 adrenergic receptors on macrophages, this massively increases the secretion of proinflammatory mediators, such as IL-1β, by the protein kinase C (PKC) and p38 mitogen-activated protein kinase (p38 MAPK) pathways [208]. β2AR is generally expressed at higher levels than the other subtypes on macrophages. When NE binds to β2-ARs, it activates adenylate cyclase, increasing intracellular cyclic AMP (cAMP) levels. Elevated cAMP activates PKA, which prevents the pro-inflammatory transcription factor NF-κB from entering the cell nucleus. By blocking NF-κB, NE inhibits the transcription and release of pro-inflammatory cytokines like TNF-α, IL-6, and IL-8, while promoting the production of anti-inflammatory IL-10, which drives fibrosis instead of inflammation [209,210]. NE decreases the expression of the CCR2 chemokine receptor, which reduces the ability of macrophages to migrate out of the bloodstream and into inflamed tissues [211]. Renal nerves contribute to the migration of CD161a+/CD68+ macrophages to the renal medulla, where they contribute to increased renal expression of NKCC2, promoting water and sodium reabsorption [212,213].
Figure 5.
Sympathetic overactivation drives hypertension through neuro-renal-immune amplification. Chronic stress, high salt and obesity cause sympathetic nervous system (SNS) overactivation. SNS nerve terminals release norepinephrine (NE) and ATP. NE stimulates immune cells (such as T cells, macrophages, and neutrophils) to release pro-inflammatory cytokines (such as IL-6, IL-1β, TNF-α), causing inflammation, arterial stiffening, cardiorenal damage, and hypertension. As a sympathetic cotransmitter, ATP binds to P2X7 receptors on immune cells, triggering the release of potent pro-inflammatory cytokines. In return, pro-inflammatory cytokines communicate back to the brain, further amplifying SNS output. Renal denervation is a validated immunomodulatory therapeutic approach to reduce sympathetic drive in patients with hypertension.
SNS directly affects immune cell behaviors. In return, active immune cells release pro-inflammatory cytokines (such as IL-1b, IL-6, and TNF-α) that communicate back to the brain and activate microglia in the hypothalamus and brainstem, further amplifying SNS output (Figure 5) [214]. Sympathetic ganglia contain resident macrophages that directly interact with neuronal cell bodies, modulating neurotransmitter release and neuronal excitability [215]. This neuro-immune crosstalk creates a powerful, self-sustaining bio-loop, amplifying the chronic inflammation condition [216]. Spiral catheter technology disrupts overactive nerves lining the kidney arteries, which effectively reduces blood pressure in experimental models and humans [217]. Renal denervation has been shown to lower inflammation by decreasing the activation of monocytes, dendritic cells, and T cells [204,218,219].
6.3. Purinergic Signaling and Immune Activation
When the SNS is activated in hypertension, it releases ATP alongside norepinephrine from nerve terminals into the kidneys [220,221]. As a sympathetic cotransmitter, ATP binds to P2 receptors (such as P2X1) on vascular smooth muscle cells, triggering an influx of calcium, causing blood vessels to constrict and increasing peripheral vascular resistance [222]. Disruption of some P2 receptors (such as P2Y2, P2X4) can impair sodium excretion, leading to salt-resistant arterial hypertension [223,224]. Recently P2 receptors are increasingly recognized as a vital communication bridge between the immune system and the development of hypertension [225,226]. A recent study by Shokoples et al. demonstrated that elevated extracellular ATP acts as a damage-associated molecular patterns (DAMPs) in hypertension [227]. Excess ATP binds to P2X7 receptors on immune cells, activating the NLRP3 inflammasome, and amplifies Ca2+ influx during T cell activation, which triggers the release of potent pro-inflammatory cytokines like IL-1β and IL-18 [228,229,230]. Disruption of P2RX7 could reduce the infiltration of activated T cells and blunt Ang II-induced BP elevation [227]. When the P2RX7 receptor is activated by excess ATP on Tregs, it promotes a significant loss of FOXP3 and drives their conversion into pro-inflammatory Th17-like cells [231].
6.4. Renalase: A Counter-Regulatory Hormone
Renalase is a kidney-secreted hormone that decreases sympathetic nerve activity by metabolizing circulating adrenaline, noradrenaline and their precursors. Deficiency in renalase, often in CKD patients, is strongly associated with increased sympathetic activity and high blood pressure [232,233]. Renalase deficiency promotes a systemic and local proinflammatory state by triggering a significant upregulation of cytokines like TNF-α and MCP-1 [234]. Renalase functions as a cytokine that activates PI3K/AKT, JAK/STAT, and the MAPK pathways, driving the differentiation of macrophages toward the anti-inflammatory M2 phenotype. Exposure of activated M1 macrophages to renalase blocks inflammasome activation and production of IL6 and IL1β [235]. Proper renalase has been shown to protect the kidney and heart from ischaemic injuries and fibrosis by suppressing oxidative stress [236,237]. Exogenous renalase could potentially be developed as a new treatment for managing hypertension by dampening severe inflammation, especially in CKD patients [234,236,238].
7. Therapeutic Implications and Future Perspectives
7.1. Current Pharmacological Approaches
Because the heart and kidneys operate in a continuous, intertwined loop in hypertension, hypertension should be treated as a disorder of dysregulated cardiorenal communication. Effectively managing hypertension requires a coordinated approach that addresses both organs. In recent years, a combination of SGLT2 inhibitors and GLP-1 receptor agonists has been developed as foundational treatments for cardiovascular-kidney diseases as well as hypertension [239]. SGLT2 inhibitors lower blood sugar and blood pressure by causing the kidneys to excrete excess glucose and sodium, reducing sympathetic tone [240]. GLP-1 receptor agonists significantly reduce appetite and promote substantial weight loss. They reduce systemic inflammation and oxidative stress, protecting kidney function and lowering the risk of major adverse cardiovascular events [241]. When taken together, SGLT2 inhibitors and GLP-1 receptor agonists provide synergistic, complementary benefits [240]. To reduce adverse renal outcomes, ERAs and RAAS inhibitors are increasingly combined with SGLT2 inhibitors to maximally protect kidney function while managing hypertension [242]. Blocking the endothelin system by endothelin receptor antagonist (ERAs), such as Aprocitentan, has emerged as a novel therapeutic approach which significantly lowers blood pressure and protects kidney function in resistant hypertension patients with chronic kidney disease [243,244].
7.2. Emerging Immunomodulatory Strategies
Interventions targeting immune processes show potential in reducing cardiorenal damage and mitigating hypertension [245]. Some studies are looking at the use of anti-inflammatory agents like colchicine and methotrexate to curb hypertension-induced inflammation [245,246]. Drugs have been investigated for their ability to neutralize inflammatory cytokines (IL-17A, IL-1B, TNF-α) that contribute to hypertension [35]. Pre-clinical models showed that specific IsoLG scavengers like 2-hydroxybenzylamine (2-HOBA) intercept and neutralize highly reactive IsoLGs, protecting immune cells from dysfunction and significantly lowering blood pressure [247,248]. NLRP3 inhibitors are being studied for their potential to treat hypertension and its associated organ damage [249,250]. SGK1 inhibitors are an emerging class of experimental therapeutics being investigated for salt-sensitive hypertension and metabolic syndrome [66,251,252]. Regulatory T cells (Tregs) help suppress immune responses and reduce inflammation, acting to protect the vascular system and lower blood pressure [253,254]. Because of this crucial connection, modulating the immune response and balancing T cell subtypes are active areas of clinical research for novel, immune-regulatory treatments for hypertension [255]. For example, Srinivas et al. demonstrated that deletion of the STIM1 gene in Tregs blocks destructive calcium signaling, which restores redox balance and protects against hypertension and its cardiovascular complications [256]. Interventions that shift the balance away from M1 macrophages and toward M2 macrophages may help suppress chronic inflammation and lower blood pressure in hypertension [257].
7.3. Future Directions and Unanswered Questions
Immune cells play a central coordinator role in dysregulated cardiorenal communication in hypertension. Immune cells sense hypertensive stimuli, like high salt, Ang II, aldosterone, and sympathetic neurotransmitters, integrate with signals from the RAAS, SNS, cardiovascular and renal systems, and amplify inflammation and tissue injury, driving persistent hypertension. Although significant work has been done, some questions remain poorly understood. Which immune cell subtypes and pathways are the best targets for hypertension treatment that benefits the whole cardiorenal system? Discrete neuro-immune circuits that link the brain, kidney, and cardiovascular system in hypertension have been identified. However, the complexity of these circuits and the potential for off-target effects require careful preclinical and clinical evaluation. These interconnected circuits provide multiple nodes for therapeutic intervention. Targeting brain–immune interactions, for example, with drugs that cross the blood–brain barrier or with vagal nerve stimulation, represents a promising frontier in hypertension management. The clinical translation of microbiome-targeted interventions remains in early stages, and the causal relationships between specific microbial taxa and BP regulation require further elucidation. The etiology and pathogenesis of hypertension are highly heterogeneous, especially immune cells. With the unprecedented advances of high-throughput molecular technologies, including single-cell RNA sequencing, spatial transcriptomics, proteomics, and metabolomics, coupled with artificial intelligence, new opportunities are created to develop personalized interventions to better prevent hypertension and improve patient-specific cardiovascular outcomes.
Author Contributions
Conceptualization: Y.W. and A.K.; validation: Y.W., S.K.M., J.C. and A.K.; writing—original draft preparation: Y.W., J.C., S.K.M. and A.K.; writing—review and editing: Y.W., J.C., S.K.M., M.S. and A.K.; visualization: Y.W. and S.K.M.; supervision: A.K.; project administration: A.K.; funding acquisition: A.K. All authors have read and agreed to the published version of the manuscript.
Funding
This work was funded by grants from the National Institutes of Health (NIH) grant R01HL144941 (A.K.).
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors declare no conflicts of interest. The figures were created with BioRender.com.
References
- Dominiczak, A.F.; Delles, C. Hypertension in 2025: Are we ready for bold precision public health approaches worldwide? Nat. Rev. Cardiol. 2025, 22, 607–608. [Google Scholar] [CrossRef] [Scilit]
- Collaborators, G.R.F. Global burden of 87 risk factors in 204 countries and territories, 1990–2019: A systematic analysis for the global burden of disease study 2019. Lancet 2020, 396, 1223–1249. [Google Scholar] [CrossRef] [Scilit]
- Rangaswami, J.; Bhalla, V.; Blair, J.E.A.; Chang, T.I.; Costa, S.; Lentine, K.L.; Lerma, E.V.; Mezue, K.; Molitch, M.; Mullens, W.; et al. Cardiorenal syndrome: Classification, pathophysiology, diagnosis, and treatment strategies: A scientific statement from the american heart association. Circulation 2019, 139, e840–e878. [Google Scholar] [CrossRef] [Scilit]
- Schefold, J.C.; Filippatos, G.; Hasenfuss, G.; Anker, S.D.; von Haehling, S. Heart failure and kidney dysfunction: Epidemiology, mechanisms and management. Nat. Rev. Nephrol. 2016, 12, 610–623. [Google Scholar] [CrossRef] [Scilit]
- Marassi, M.; Fadini, G.P. The cardio-renal-metabolic connection: A review of the evidence. Cardiovasc. Diabetol. 2023, 22, 195. [Google Scholar] [CrossRef] [Scilit]
- Deferrari, G.; Cipriani, A.; La Porta, E. Renal dysfunction in cardiovascular diseases and its consequences. J. Nephrol. 2021, 34, 137–153. [Google Scholar] [CrossRef] [Scilit]
- Jankowski, J.; Floege, J.; Fliser, D.; Böhm, M.; Marx, N. Cardiovascular disease in chronic kidney disease: Pathophysiological insights and therapeutic options. Circulation 2021, 143, 1157–1172. [Google Scholar]
- Schuett, K.; Marx, N.; Lehrke, M. The cardio-kidney patient: Epidemiology, clinical characteristics and therapy. Circ. Res. 2023, 132, 902–914. [Google Scholar] [CrossRef] [Scilit]
- Harrison, D.G.; Patrick, D.M. Immune mechanisms in hypertension. Hypertension 2024, 81, 1659–1674. [Google Scholar] [CrossRef] [Scilit]
- Benson, L.N.; Guo, Y.; Deck, K.; Mora, C.; Liu, Y.; Mu, S. The link between immunity and hypertension in the kidney and heart. Front. Cardiovasc. Med. 2023, 10, 1129384. [Google Scholar] [CrossRef] [Scilit]
- Evans, R.G.; Bie, P. Role of the kidney in the pathogenesis of hypertension: Time for a neo-guytonian paradigm or a paradigm shift? Am. J. Physiol. Regul. Integr. Comp. Physiol. 2016, 310, R217–R229. [Google Scholar] [CrossRef] [Scilit]
- Hall, J.E.; Granger, J.P.; do Carmo, J.M.; da Silva, A.A.; Dubinion, J.; George, E.; Hamza, S.; Speed, J.; Hall, M.E. Hypertension: Physiology and pathophysiology. Compr. Physiol. 2012, 2, 2393–2442. [Google Scholar] [CrossRef] [Scilit]
- Coffman, T.M. The inextricable role of the kidney in hypertension. J. Clin. Investig. 2014, 124, 2341–2347. [Google Scholar] [CrossRef] [Scilit]
- García-Donaire, J.A.; Ruilope, L.M. Cardiovascular and renal links along the cardiorenal continuum. Int. J. Nephrol. 2011, 2011, 975782. [Google Scholar] [CrossRef] [Scilit]
- Viswanathan, G.; Gilbert, S. The cardiorenal syndrome: Making the connection. Int. J. Nephrol. 2010, 2011, 283137. [Google Scholar] [CrossRef] [Scilit]
- Bailey, M.A.; Dhaun, N. Salt sensitivity: Causes, consequences, and recent advances. Hypertension 2024, 81, 476–489. [Google Scholar] [CrossRef] [Scilit]
- Rossitto, G.; Maiolino, G.; Lerco, S.; Ceolotto, G.; Blackburn, G.; Mary, S.; Antonelli, G.; Berton, C.; Bisogni, V.; Cesari, M.; et al. High sodium intake, glomerular hyperfiltration, and protein catabolism in patients with essential hypertension. Cardiovasc. Res. 2021, 117, 1372–1381. [Google Scholar] [CrossRef] [Scilit]
- Mori, T. Renal venous hypertension to the regulation of pressure natriuresis in heart failure. Hypertens. Res. 2024, 47, 1081–1083. [Google Scholar] [CrossRef] [Scilit]
- Armando, I.; Villar, V.A.; Jose, P.A. Dopamine and renal function and blood pressure regulation. Compr. Physiol. 2011, 1, 1075–1117. [Google Scholar] [CrossRef] [Scilit]
- Baek, E.J.; Kim, S. Current understanding of pressure natriuresis. Electrolytes Blood Press. 2021, 19, 38–45. [Google Scholar] [CrossRef] [Scilit]
- Herzog, M.J.; Müller, P.; Lechner, K.; Stiebler, M.; Arndt, P.; Kunz, M.; Ahrens, D.; Schmeißer, A.; Schreiber, S.; Braun-Dullaeus, R.C. Arterial stiffness and vascular aging: Mechanisms, prevention, and therapy. Signal Transduct. Target. Ther. 2025, 10, 282. [Google Scholar] [CrossRef] [Scilit]
- Gallo, G.; Volpe, M.; Savoia, C. Endothelial dysfunction in hypertension: Current concepts and clinical implications. Front. Med. 2021, 8, 798958. [Google Scholar] [CrossRef] [Scilit]
- Ahmad, A.; Dempsey, S.K.; Daneva, Z.; Azam, M.; Li, N.; Li, P.L.; Ritter, J.K. Role of nitric oxide in the cardiovascular and renal systems. Int. J. Mol. Sci. 2018, 19, 2605. [Google Scholar] [CrossRef] [Scilit]
- Förstermann, U.; Xia, N.; Li, H. Roles of vascular oxidative stress and nitric oxide in the pathogenesis of atherosclerosis. Circ. Res. 2017, 120, 713–735. [Google Scholar] [CrossRef] [Scilit]
- Kohan, D.E. Endothelin, hypertension and chronic kidney disease: New insights. Curr. Opin. Nephrol. Hypertens. 2010, 19, 134–139. [Google Scholar] [CrossRef] [Scilit]
- Schroeder, A.C.; Imig, J.D.; LeBlanc, E.A.; Pham, B.T.; Pollock, D.M.; Inscho, E.W. Endothelin-mediated calcium signaling in preglomerular smooth muscle cells. Hypertension 2000, 35, 280–286. [Google Scholar] [CrossRef] [Scilit]
- Xanthopoulos, A.; Papamichail, A.; Briasoulis, A.; Loritis, K.; Bourazana, A.; Magouliotis, D.E.; Sarafidis, P.; Stefanidis, I.; Skoularigis, J.; Triposkiadis, F. Heart failure in patients with chronic kidney disease. J. Clin. Med. 2023, 12, 6105. [Google Scholar] [CrossRef] [Scilit]
- Izzo, J.L.; Gradman, A.H. Mechanisms and management of hypertensive heart disease: From left ventricular hypertrophy to heart failure. Med. Clin. N. Am. 2004, 88, 1257–1271. [Google Scholar] [CrossRef] [Scilit]
- Wu, S.; Li, M.; Lu, J.; Tang, X.; Wang, G.; Zheng, R.; Niu, J.; Chen, L.; Huo, Y.; Xu, M.; et al. Blood pressure levels, cardiovascular events, and renal outcomes in chronic kidney disease without antihypertensive therapy: A nationwide population-based cohort study. Hypertension 2023, 80, 640–649. [Google Scholar] [CrossRef] [Scilit]
- Mocan, D.; Lala, R.I.; Puschita, M.; Pilat, L.; Darabantiu, D.A.; Pop-Moldovan, A. The congestion “Pandemic” In acute heart failure patients. Biomedicines 2024, 12, 951. [Google Scholar] [CrossRef] [Scilit]
- Nguyen, B.A.; Alexander, M.R.; Harrison, D.G. Immune mechanisms in the pathophysiology of hypertension. Nat. Rev. Nephrol. 2024, 20, 530–540. [Google Scholar] [CrossRef] [Scilit]
- Mocan, D.; Jipa, R.; Jipa, D.A.; Lala, R.I.; Rasinar, F.C.; Groza, I.; Sabau, R.; Sulea Bratu, D.; Balta, D.F.; Cioban, S.T.; et al. Unveiling the systemic impact of congestion in heart failure: A narrative review of multisystem pathophysiology and clinical implications. J. Cardiovasc. Dev. Dis. 2025, 12, 124. [Google Scholar] [CrossRef] [Scilit]
- Guzik, T.J.; Nosalski, R.; Maffia, P.; Drummond, G.R. Immune and inflammatory mechanisms in hypertension. Nat. Rev. Cardiol. 2024, 21, 396–416. [Google Scholar] [CrossRef] [Scilit]
- Dos Passos, R.R.; Santos, C.V.; Priviero, F.; Briones, A.M.; Tostes, R.C.; Webb, R.C.; Bomfim, G.F. Immunomodulatory activity of cytokines in hypertension: A vascular perspective. Hypertension 2024, 81, 1411–1423. [Google Scholar] [CrossRef] [Scilit]
- Fu, M.; Lv, M.; Guo, J.; Mei, A.; Qian, H.; Yang, H.; Wu, W.; Liu, Z.; Zhong, J.; Wei, Y.; et al. The clinical significance of t-cell regulation in hypertension treatment. Front. Immunol. 2025, 16, 1550206. [Google Scholar] [CrossRef] [Scilit]
- Lu, X.; Crowley, S.D. Actions of immune cells in the hypertensive kidney. Curr. Opin. Nephrol. Hypertens. 2020, 29, 515–522. [Google Scholar] [CrossRef] [Scilit]
- Loperena, R.; Van Beusecum, J.P.; Itani, H.A.; Engel, N.; Laroumanie, F.; Xiao, L.; Elijovich, F.; Laffer, C.L.; Gnecco, J.S.; Noonan, J.; et al. Hypertension and increased endothelial mechanical stretch promote monocyte differentiation and activation: Roles of stat3, interleukin 6 and hydrogen peroxide. Cardiovasc. Res. 2018, 114, 1547–1563. [Google Scholar] [CrossRef] [Scilit]
- Anwar, M.A.; Shalhoub, J.; Lim, C.S.; Gohel, M.S.; Davies, A.H. The effect of pressure-induced mechanical stretch on vascular wall differential gene expression. J. Vasc. Res. 2012, 49, 463–478. [Google Scholar] [CrossRef] [Scilit]
- Krishnan, J.; Hennen, E.M.; Ao, M.; Kirabo, A.; Ahmad, T.; de la Visitación, N.; Patrick, D.M. Netosis drives blood pressure elevation and vascular dysfunction in hypertension. Circ. Res. 2024, 134, 1483–1494. [Google Scholar] [CrossRef] [Scilit]
- Zhao, W.; Wang, J. Mechanotransduction in neutrophil: Mechanosensing and immune function regulation. Mechanobiol. Med. 2025, 3, 100157. [Google Scholar] [CrossRef] [Scilit]
- Guyton, A.C.; Coleman, T.G.; Cowley, A.V.; Scheel, K.W.; Manning, R.D.; Norman, R.A. Arterial pressure regulation. Overriding dominance of the kidneys in long-term regulation and in hypertension. Am. J. Med. 1972, 52, 584–594. [Google Scholar]
- Siakabanze, C.; Luwaya, E.; Muchaili, L.; Siame, L.; Sibbenga, F.; Tande, M.; Shawa, C.; Masenga, S.K.; Liweleya, S. Integrated mechanisms linking sodium-potassium imbalance to salt-sensitive hypertension. Physiol. Rep. 2025, 13, e70715. [Google Scholar] [CrossRef] [Scilit]
- Bachlitzanaki, M.; Aletras, G.; Bachlitzanaki, E.; Vasilaki, N.; Lydakis, C.; Petrakis, I.; Foukarakis, E.; Stylianou, K. Beyond blood pressure: Salt sensitivity as a cardiorenal phenotype-a narrative review. Life 2026, 16, 247. [Google Scholar] [CrossRef] [Scilit]
- Titze, J.; Lang, R.; Ilies, C.; Schwind, K.H.; Kirsch, K.A.; Dietsch, P.; Luft, F.C.; Hilgers, K.F. Osmotically inactive skin na+ storage in rats. Am. J. Physiol. Ren. Physiol. 2003, 285, F1108–F1117. [Google Scholar] [CrossRef] [Scilit]
- Titze, J.; Bauer, K.; Schafflhuber, M.; Dietsch, P.; Lang, R.; Schwind, K.H.; Luft, F.C.; Eckardt, K.U.; Hilgers, K.F. Internal sodium balance in doca-salt rats: A body composition study. Am. J. Physiol. Ren. Physiol. 2005, 289, F793–F802. [Google Scholar] [CrossRef] [Scilit]
- Olde Engberink, R.H.G.; Selvarajah, V.; Vogt, L. Clinical impact of tissue sodium storage. Pediatr. Nephrol. 2020, 35, 1373–1380. [Google Scholar] [CrossRef] [Scilit]
- Kopp, C.; Linz, P.; Dahlmann, A.; Hammon, M.; Jantsch, J.; Müller, D.N.; Schmieder, R.E.; Cavallaro, A.; Eckardt, K.U.; Uder, M.; et al. 23na magnetic resonance imaging-determined tissue sodium in healthy subjects and hypertensive patients. Hypertension 2013, 61, 635–640. [Google Scholar] [CrossRef] [Scilit]
- Liu, J.; Shelton, E.L.; Crescenzi, R.; Colvin, D.C.; Kirabo, A.; Zhong, J.; Delpire, E.J.; Yang, H.C.; Kon, V. Kidney injury causes accumulation of renal sodium that modulates renal lymphatic dynamics. Int. J. Mol. Sci. 2022, 23, 1428. [Google Scholar] [CrossRef] [Scilit]
- Kleinewietfeld, M.; Manzel, A.; Titze, J.; Kvakan, H.; Yosef, N.; Linker, R.A.; Muller, D.N.; Hafler, D.A. Sodium chloride drives autoimmune disease by the induction of pathogenic th17 cells. Nature 2013, 496, 518–522. [Google Scholar] [CrossRef] [Scilit]
- Machnik, A.; Neuhofer, W.; Jantsch, J.; Dahlmann, A.; Tammela, T.; Machura, K.; Park, J.K.; Beck, F.X.; Müller, D.N.; Derer, W.; et al. Macrophages regulate salt-dependent volume and blood pressure by a vascular endothelial growth factor-c-dependent buffering mechanism. Nat. Med. 2009, 15, 545–552. [Google Scholar] [CrossRef] [Scilit]
- Guzik, T.J.; Hoch, N.E.; Brown, K.A.; McCann, L.A.; Rahman, A.; Dikalov, S.; Goronzy, J.; Weyand, C.; Harrison, D.G. Role of the t cell in the genesis of angiotensin ii induced hypertension and vascular dysfunction. J. Exp. Med. 2007, 204, 2449–2460. [Google Scholar] [CrossRef] [Scilit]
- Zhang, J.; Crowley, S.D. Role of T lymphocytes in hypertension. Curr. Opin. Pharmacol. 2015, 21, 14–19. [Google Scholar] [CrossRef] [Scilit]
- Chen, Y.; Dale, B.L.; Alexander, M.R.; Xiao, L.; Ao, M.; Pandey, A.K.; Smart, C.D.; Davis, G.K.; Madhur, M.S. Class switching and high-affinity immunoglobulin G production by B cells is dispensable for the development of hypertension in mice. Cardiovasc. Res. 2021, 117, 1217–1228. [Google Scholar] [CrossRef] [Scilit]
- Chan, C.T.; Sobey, C.G.; Lieu, M.; Ferens, D.; Kett, M.M.; Diep, H.; Kim, H.A.; Krishnan, S.M.; Lewis, C.V.; Salimova, E.; et al. Obligatory role for b cells in the development of angiotensin ii-dependent hypertension. Hypertension 2015, 66, 1023–1033. [Google Scholar] [CrossRef] [Scilit]
- Basile, D.P.; Ullah, M.M.; Collet, J.A.; Mehrotra, P. T helper 17 cells in the pathophysiology of acute and chronic kidney disease. Kidney Res. Clin. Pract. 2021, 40, 12–28. [Google Scholar] [CrossRef] [Scilit]
- Norlander, A.E.; Saleh, M.A.; Kamat, N.V.; Ko, B.; Gnecco, J.; Zhu, L.; Dale, B.L.; Iwakura, Y.; Hoover, R.S.; McDonough, A.A.; et al. Interleukin-17a regulates renal sodium transporters and renal injury in angiotensin ii-induced hypertension. Hypertension 2016, 68, 167–174. [Google Scholar] [CrossRef] [Scilit]
- DeConne, T.M.; Buckley, D.J.; Trott, D.W.; Martens, C.R. The role of T cells in vascular aging, hypertension, and atherosclerosis. Am. J. Physiol. Heart Circ. Physiol. 2024, 327, H1345–H1360. [Google Scholar] [CrossRef] [Scilit]
- Hernandez, A.L.; Kitz, A.; Wu, C.; Lowther, D.E.; Rodriguez, D.M.; Vudattu, N.; Deng, S.; Herold, K.C.; Kuchroo, V.K.; Kleinewietfeld, M.; et al. Sodium chloride inhibits the suppressive function of FOXP3+ regulatory t cells. J. Clin. Investig. 2015, 125, 4212–4222. [Google Scholar] [CrossRef] [Scilit]
- Rudensky, A.Y. Regulatory T cells and FOXP3. Immunol. Rev. 2011, 241, 260–268. [Google Scholar] [CrossRef] [Scilit]
- Alexander, M.R.; Dale, B.L.; Smart, C.D.; Elijovich, F.; Wogsland, C.E.; Lima, S.M.; Irish, J.M.; Madhur, M.S. Immune profiling reveals decreases in circulating regulatory and exhausted T cells in human hypertension. JACC Basic Transl. Sci. 2023, 8, 319–336. [Google Scholar] [CrossRef] [Scilit]
- Katsuki, M.; Hirooka, Y.; Kishi, T.; Sunagawa, K. Decreased proportion of FOXP3+ CD4+ regulatory t cells contributes to the development of hypertension in genetically hypertensive rats. J. Hypertens. 2015, 33, 773–783; discussion 783. [Google Scholar] [CrossRef] [Scilit]
- Kirabo, A.; Fontana, V.; de Faria, A.P.; Loperena, R.; Galindo, C.L.; Wu, J.; Bikineyeva, A.T.; Dikalov, S.; Xiao, L.; Chen, W.; et al. Dc isoketal-modified proteins activate t cells and promote hypertension. J. Clin. Investig. 2014, 124, 4642–4656. [Google Scholar] [CrossRef] [Scilit]
- Hanukoglu, I.; Hanukoglu, A. Epithelial sodium channel (ENaC) family: Phylogeny, structure-function, tissue distribution, and associated inherited diseases. Gene 2016, 579, 95–132. [Google Scholar] [CrossRef] [Scilit]
- Barbaro, N.R.; Foss, J.D.; Kryshtal, D.O.; Tsyba, N.; Kumaresan, S.; Xiao, L.; Mernaugh, R.L.; Itani, H.A.; Loperena, R.; Chen, W.; et al. Dendritic cell amiloride-sensitive channels mediate sodium-induced inflammation and hypertension. Cell Rep. 2017, 21, 1009–1020. [Google Scholar] [CrossRef] [Scilit]
- Ertuglu, L.A.; Pitzer Mutchler, A.; Jamison, S.; Laffer, C.L.; Elijovich, F.; Saleem, M.; Blackwell, D.J.; Kryshtal, D.O.; Egly, C.L.; Sahinoz, M.; et al. Eicosanoid-regulated myeloid ENaC and isolevuglandin formation in human salt-sensitive hypertension. Hypertension 2024, 81, 516–529. [Google Scholar] [CrossRef] [Scilit]
- Van Beusecum, J.P.; Barbaro, N.R.; McDowell, Z.; Aden, L.A.; Xiao, L.; Pandey, A.K.; Itani, H.A.; Himmel, L.E.; Harrison, D.G.; Kirabo, A. High salt activates CD11c+ antigen-presenting cells via SGK (serum glucocorticoid kinase) 1 to promote renal inflammation and salt-sensitive hypertension. Hypertension 2019, 74, 555–563. [Google Scholar] [CrossRef] [Scilit]
- Pitzer, A.; Elijovich, F.; Laffer, C.L.; Ertuglu, L.A.; Sahinoz, M.; Saleem, M.; Krishnan, J.; Dola, T.; Aden, L.A.; Sheng, Q.; et al. Dc enac-dependent inflammasome activation contributes to salt-sensitive hypertension. Circ. Res. 2022, 131, 328–344. [Google Scholar] [CrossRef] [Scilit]
- Xiao, L.; Patrick, D.M.; Aden, L.A.; Kirabo, A. Mechanisms of isolevuglandin-protein adduct formation in inflammation and hypertension. Prostaglandins Other Lipid Mediat. 2018, 139, 48–53. [Google Scholar] [CrossRef] [Scilit]
- Davis, G.K.; Fehrenbach, D.J.; Madhur, M.S. Interleukin 17a: Key player in the pathogenesis of hypertension and a potential therapeutic target. Curr. Hypertens. Rep. 2021, 23, 13. [Google Scholar] [CrossRef] [Scilit]
- Ruggeri Barbaro, N.; Van Beusecum, J.; Xiao, L.; do Carmo, L.; Pitzer, A.; Loperena, R.; Foss, J.D.; Elijovich, F.; Laffer, C.L.; Montaniel, K.R.; et al. Sodium activates human monocytes via the NADPH oxidase and isolevuglandin formation. Cardiovasc. Res. 2021, 117, 1358–1371. [Google Scholar] [CrossRef] [Scilit]
- Saleem, M.; Aden, L.A.; Mutchler, A.L.; Basu, C.; Ertuglu, L.A.; Sheng, Q.; Penner, N.; Hemnes, A.R.; Park, J.H.; Ishimwe, J.A.; et al. Myeloid-specific JAK2 contributes to inflammation and salt sensitivity of blood pressure. Circ. Res. 2024, 135, 890–909. [Google Scholar] [CrossRef] [Scilit]
- Harwani, S.C. Macrophages under pressure: The role of macrophage polarization in hypertension. Transl. Res. 2018, 191, 45–63. [Google Scholar] [CrossRef] [Scilit]
- Wenzel, P. Monocytes as immune targets in arterial hypertension. Br. J. Pharmacol. 2019, 176, 1966–1977. [Google Scholar] [CrossRef] [Scilit]
- De Ciuceis, C.; Amiri, F.; Brassard, P.; Endemann, D.H.; Touyz, R.M.; Schiffrin, E.L. Reduced vascular remodeling, endothelial dysfunction, and oxidative stress in resistance arteries of angiotensin ii-infused macrophage colony-stimulating factor-deficient mice: Evidence for a role in inflammation in angiotensin-induced vascular injury. Arterioscler. Thromb. Vasc. Biol. 2005, 25, 2106–2113. [Google Scholar]
- da Silva, C.H.N.D.; Guedes, I.H.L.; de Lima, J.C.S.; Sobrinho, J.M.D.R.; dos Santos, A.A. Responses triggered by the immune system in hypertensive conditions and repercussions on target organ damage: A review. Curr. Cardiol. Rev. 2023, 19, e200922208959. [Google Scholar] [CrossRef] [Scilit]
- Feng, H.; Hu, W.; Liu, Y.; Xu, X.; Zhou, P.; Qu, C.; Liu, Z. Macrophages in ventricular remodeling and heart failure: Orchestrators of inflammation and repair. Front. Immunol. 2025, 16, 1682294. [Google Scholar] [CrossRef] [Scilit]
- Zhang, W.C.; Zheng, X.J.; Du, L.J.; Sun, J.Y.; Shen, Z.X.; Shi, C.; Sun, S.; Zhang, Z.; Chen, X.Q.; Qin, M.; et al. High salt primes a specific activation state of macrophages, M(Na). Cell Res. 2015, 25, 893–910. [Google Scholar] [CrossRef] [Scilit]
- Min, B.; Fairchild, R.L. Over-salting ruins the balance of the immune menu. J. Clin. Investig. 2015, 125, 4002–4004. [Google Scholar] [CrossRef] [Scilit]
- Peter, J.K.; Umene, R.; Wu, C.H.; Nakamura, Y.; Washimine, N.; Yamamoto, R.; Muriuki, D.; Ngugi, C.; Linge, K.; Kweri, J.K.; et al. Macrophage depletion lowers blood pressure and reduces renal fibrosis progression in existing hypertension mice model. J. Physiol. Sci. 2025, 75, 100049. [Google Scholar] [CrossRef] [Scilit]
- Chen, C.C.; Pedraza, P.L.; Hao, S.; Stier, C.T.; Ferreri, N.R. Tnfr1-deficient mice display altered blood pressure and renal responses to ang ii infusion. Am. J. Physiol. Ren. Physiol. 2010, 299, F1141–F1150. [Google Scholar] [CrossRef] [Scilit]
- Mehaffey, E.; Majid, D.S.A. Tumor necrosis factor-α, kidney function, and hypertension. Am. J. Physiol. Ren. Physiol. 2017, 313, F1005–F1008. [Google Scholar] [CrossRef] [Scilit]
- Singh, P.; Stephenson, R.; Castillo, A.; Majid, D.S.A. High-salt intake reduces renal tissue levels of inflammatory cytokines in mice. Physiol. Rep. 2021, 8, e14621. [Google Scholar] [CrossRef] [Scilit]
- Zhao, Q.; Hong, D.; Zhang, Y.; Sang, Y.; Yang, Z.; Zhang, X. Association between anti-TNF therapy for rheumatoid arthritis and hypertension: A meta-analysis of randomized controlled trials. Medicine 2015, 94, e731. [Google Scholar]
- Singh, P.; Castillo, A.; Islam, M.T.; Majid, D.S.A. Evidence for prohypertensive, proinflammatory effect of interleukin-10 during chronic high salt intake in the condition of elevated angiotensin ii level. Hypertension 2017, 70, 839–845. [Google Scholar] [CrossRef] [Scilit]
- Tsai, Y.H.; Ohkita, M.; Gariepy, C.E. Chronic high-sodium diet increases aortic wall endothelin-1 expression in a blood pressure-independent fashion in rats. Exp. Biol. Med. 2006, 231, 813–817. [Google Scholar]
- Brooks, A.J.; Gallego-López, M.D.C.; De Miguel, C. Endothelin-1 signaling in the kidney: Recent advances and remaining gaps. Am. J. Physiol. Ren. Physiol. 2025, 328, F815–F827. [Google Scholar] [CrossRef] [Scilit]
- Speed, J.S.; Heimlich, J.B.; Hyndman, K.A.; Fox, B.M.; Patel, V.; Yanagisawa, M.; Pollock, J.S.; Titze, J.M.; Pollock, D.M. Endothelin-1 as a master regulator of whole-body Na+ homeostasis. FASEB J. 2015, 29, 4937–4944. [Google Scholar] [CrossRef] [Scilit]
- De Miguel, C.; Speed, J.S.; Kasztan, M.; Gohar, E.Y.; Pollock, D.M. Endothelin-1 and the kidney: New perspectives and recent findings. Curr. Opin. Nephrol. Hypertens. 2016, 25, 35–41. [Google Scholar]
- Schiffrin, E.L.; Pollock, D.M. Endothelin system in hypertension and chronic kidney disease. Hypertension 2024, 81, 691–701. [Google Scholar] [CrossRef] [Scilit]
- Johnston, J.G.; Speed, J.S.; Jin, C.; Pollock, D.M. Loss of endothelin B receptor function impairs sodium excretion in a time- and sex-dependent manner. Am. J. Physiol. Ren. Physiol. 2016, 311, F991–F998. [Google Scholar] [CrossRef] [Scilit]
- Elisa, T.; Antonio, P.; Giuseppe, P.; Alessandro, B.; Giuseppe, A.; Federico, C.; Marzia, D.; Ruggero, B.; Giacomo, M.; Andrea, O.; et al. Endothelin receptors expressed by immune cells are involved in modulation of inflammation and in fibrosis: Relevance to the pathogenesis of systemic sclerosis. J. Immunol. Res. 2015, 2015, 147616. [Google Scholar] [CrossRef] [Scilit]
- Guruli, G.; Pflug, B.R.; Pecher, S.; Makarenkova, V.; Shurin, M.R.; Nelson, J.B. Function and survival of dendritic cells depend on endothelin-1 and endothelin receptor autocrine loops. Blood 2004, 104, 2107–2115. [Google Scholar] [CrossRef] [Scilit]
- Divino, J.N.; Chawla, K.S.; da Silva, C.M.; Bjorge, A.M.; Brittingham, A. Endothelin-1 production by the canine macrophage cell line DH82: Enhanced production in response to microbial challenge. Vet. Immunol. Immunopathol. 2010, 136, 127–132. [Google Scholar] [CrossRef] [Scilit][Green Version]
- Czopek, A.; Moorhouse, R.; Guyonnet, L.; Farrah, T.; Lenoir, O.; Owen, E.; van Bragt, J.; Costello, H.M.; Menolascina, F.; Baudrie, V.; et al. A novel role for myeloid endothelin-B receptors in hypertension. Eur. Heart J. 2019, 40, 768–784. [Google Scholar] [CrossRef] [Scilit]
- Mutchler, A.L.; Zhong, J.; Yang, H.C.; Zhao, S.; Crescenzi, R.; Taylor, S.; Rao, R.L.; Shelton, E.L.; Kirabo, A.; Kon, V. ET-3/ETBR Mediates Na+-Activated Immune Signaling and Kidney Lymphatic Dynamics. Circ. Res. 2025, 136, 194–208. [Google Scholar] [CrossRef] [Scilit]
- Elijovich, F.; Laffer, C.L.; Sahinoz, M.; Pitzer, A.; Ferguson, J.F.; Kirabo, A. The gut microbiome, inflammation, and salt-sensitive hypertension. Curr. Hypertens. Rep. 2020, 22, 79. [Google Scholar] [CrossRef] [Scilit]
- Mattson, D.L.; Dasinger, J.H.; Abais-Battad, J.M. Gut-immune-kidney axis: Influence of dietary protein in salt-sensitive hypertension. Hypertension 2022, 79, 2397–2408. [Google Scholar] [CrossRef] [Scilit]
- Ferguson, J.F.; Aden, L.A.; Barbaro, N.R.; Van Beusecum, J.P.; Xiao, L.; Simmons, A.J.; Warden, C.; Pasic, L.; Himmel, L.E.; Washington, M.K.; et al. High dietary salt-induced dendritic cell activation underlies microbial dysbiosis-associated hypertension. JCI Insight 2019, 5, e126241. [Google Scholar] [CrossRef] [Scilit]
- Du, Y.; He, C.; An, Y.; Huang, Y.; Zhang, H.; Fu, W.; Wang, M.; Shan, Z.; Xie, J.; Yang, Y.; et al. The role of short chain fatty acids in inflammation and body health. Int. J. Mol. Sci. 2024, 25, 7379. [Google Scholar] [CrossRef] [Scilit]
- Pang, A.; Pu, S.; Pan, Y.; Huang, N.; Li, D. Short-chain fatty acids from gut microbiota restore Th17/Treg balance in rheumatoid arthritis: Mechanisms and therapeutic potential. J. Transl. Autoimmun. 2025, 11, 100316. [Google Scholar] [CrossRef] [Scilit]
- Yang, T.; Richards, E.M.; Pepine, C.J.; Raizada, M.K. The gut microbiota and the brain-gut-kidney axis in hypertension and chronic kidney disease. Nat. Rev. Nephrol. 2018, 14, 442–456. [Google Scholar] [CrossRef] [Scilit]
- Te Riet, L.; van Esch, J.H.; Roks, A.J.; van den Meiracker, A.H.; Danser, A.H. Hypertension: Renin-angiotensin-aldosterone system alterations. Circ. Res. 2015, 116, 960–975. [Google Scholar] [CrossRef] [Scilit]
- Rianto, F.; Hoang, T.; Revoori, R.; Sparks, M.A. Angiotensin receptors in the kidney and vasculature in hypertension and kidney disease. Mol. Cell Endocrinol. 2021, 529, 111259. [Google Scholar] [CrossRef] [Scilit]
- Gasparini, S.; Melo, M.R.; Nascimento, P.A.; Andrade-Franzé, G.M.F.; Antunes-Rodrigues, J.; Yosten, G.L.C.; Menani, J.V.; Samson, W.K.; Colombari, E. Interaction of central angiotensin II and aldosterone on sodium intake and blood pressure. Brain Res. 2019, 1720, 146299. [Google Scholar] [CrossRef] [Scilit]
- Hoh, B.P.; Abdul Rahman, T.; Yusoff, K. Natural selection and local adaptation of blood pressure regulation and their perspectives on precision medicine in hypertension. Hereditas 2019, 156, 1. [Google Scholar] [CrossRef] [Scilit]
- Sequeira Lopez, M.L.; Gomez, R.A. Novel mechanisms for the control of renin synthesis and release. Curr. Hypertens. Rep. 2010, 12, 26–32. [Google Scholar] [CrossRef] [Scilit]
- Gomez, R.A.; Sequeira-Lopez, M.L.S. Renin cells in homeostasis, regeneration and immune defence mechanisms. Nat. Rev. Nephrol. 2018, 14, 231–245. [Google Scholar] [CrossRef] [Scilit]
- Oh, J.; Matkovich, S.J.; Riek, A.E.; Bindom, S.M.; Shao, J.S.; Head, R.D.; Barve, R.A.; Sands, M.S.; Carmeliet, G.; Osei-Owusu, P.; et al. Macrophage secretion of miR-106b-5p causes renin-dependent hypertension. Nat. Commun. 2020, 11, 4798. [Google Scholar] [CrossRef] [Scilit]
- Ramkumar, N.; Kohan, D.E. The (pro)renin receptor: An emerging player in hypertension and metabolic syndrome. Kidney Int. 2019, 95, 1041–1052. [Google Scholar] [CrossRef] [Scilit]
- Narumi, K.; Hirose, T.; Sato, E.; Mori, T.; Kisu, K.; Ishikawa, M.; Totsune, K.; Ishii, T.; Ichihara, A.; Nguyen, G.; et al. A functional (pro)renin receptor is expressed in human lymphocytes and monocytes. Am. J. Physiol. Ren. Physiol. 2015, 308, F487–F499. [Google Scholar] [CrossRef] [Scilit]
- Geisberger, S.; Maschke, U.; Gebhardt, M.; Kleinewietfeld, M.; Manzel, A.; Linker, R.A.; Chidgey, A.; Dechend, R.; Nguyen, G.; Daumke, O.; et al. New role for the (pro)renin receptor in T-cell development. Blood 2015, 126, 504–507. [Google Scholar] [CrossRef] [Scilit]
- Satou, R.; Gonzalez-Villalobos, R.A.; Miyata, K.; Ohashi, N.; Katsurada, A.; Navar, L.G.; Kobori, H. Costimulation with angiotensin II and interleukin 6 augments angiotensinogen expression in cultured human renal proximal tubular cells. Am. J. Physiol. Ren. Physiol. 2008, 295, F283–F289. [Google Scholar] [CrossRef] [Scilit]
- Satou, R.; Penrose, H.; Navar, L.G. Inflammation as a regulator of the renin-angiotensin system and blood pressure. Curr. Hypertens. Rep. 2018, 20, 100. [Google Scholar] [CrossRef] [Scilit]
- Lai, H.S.; Lin, W.H.; Lai, S.L.; Lin, H.Y.; Hsu, W.M.; Chou, C.H.; Lee, P.H. Interleukin-6 mediates angiotensinogen gene expression during liver regeneration. PLoS ONE 2013, 8, e67868. [Google Scholar] [CrossRef] [Scilit]
- Navar, L.G.; Prieto, M.C.; Satou, R.; Kobori, H. Intrarenal angiotensin II and its contribution to the genesis of chronic hypertension. Curr. Opin. Pharmacol. 2011, 11, 180–186. [Google Scholar] [CrossRef] [Scilit]
- Gubernatorova, E.O.; Samsonov, M.Y.; Drutskaya, M.S.; Lebedeva, S.; Bukhanova, D.; Materenchuk, M.; Mutig, K. Targeting inerleukin-6 for renoprotection. Front. Immunol. 2024, 15, 1502299. [Google Scholar] [CrossRef] [Scilit]
- Satou, R.; Gonzalez-Villalobos, R.A.; Miyata, K.; Ohashi, N.; Urushihara, M.; Acres, O.W.; Navar, L.G.; Kobori, H. Il-6 augments angiotensinogen in primary cultured renal proximal tubular cells. Mol. Cell. Endocrinol. 2009, 311, 24–31. [Google Scholar] [CrossRef] [Scilit]
- Ruiz-Ortega, M.; Lorenzo, O.; Suzuki, Y.; Rupérez, M.; Egido, J. Proinflammatory actions of angiotensins. Curr. Opin. Nephrol. Hypertens. 2001, 10, 321–329. [Google Scholar] [CrossRef] [Scilit]
- Silva-Filho, J.L.; Caruso-Neves, C.; Pinheiro, A.A. Angiotensin II type-1 receptor (AT1R) regulates expansion, differentiation, and functional capacity of antigen-specific CD8+ T cells. Sci. Rep. 2016, 6, 35997. [Google Scholar] [CrossRef] [Scilit]
- Haliga, R.E.; Cojocaru, E.; Sîrbu, O.; Hrițcu, I.; Alexa, R.E.; Haliga, I.B.; Șorodoc, V.; Coman, A.E. Immunomodulatory effects of RAAS inhibitors: Beyond hypertension and heart failure. Biomedicines 2025, 13, 1779. [Google Scholar] [CrossRef] [Scilit]
- Zhang, S.; Gang, X.; Yang, S.; Cui, M.; Sun, L.; Li, Z.; Wang, G. The alterations in and the role of the Th17/Treg balance in metabolic diseases. Front. Immunol. 2021, 12, 678355. [Google Scholar] [CrossRef] [Scilit]
- Karin, N.; Wildbaum, G. The role of chemokines in adjusting the balance between CD4+ effector T cell subsets and FOXP3-negative regulatory T cells. Int. Immunopharmacol. 2015, 28, 829–835. [Google Scholar] [CrossRef] [Scilit]
- Hinshaw, D.C.; Benavides, G.A.; Metge, B.J.; Swain, C.A.; Kammerud, S.C.; Alsheikh, H.A.; Elhamamsy, A.; Chen, D.; Darley-Usmar, V.; Rathmell, J.C.; et al. Hedgehog signaling regulates Treg to Th17 conversion through metabolic rewiring in breast cancer. Cancer Immunol. Res. 2023, 11, 687–702. [Google Scholar] [CrossRef] [Scilit]
- Chang, Y.; Wei, W. Angiotensin ii in inflammation, immunity and rheumatoid arthritis. Clin. Exp. Immunol. 2015, 179, 137–145. [Google Scholar] [CrossRef] [Scilit]
- Lohr, J.; Knoechel, B.; Caretto, D.; Abbas, A.K. Balance of Th1 and Th17 effector and peripheral regulatory T cells. Microbes Infect. 2009, 11, 589–593. [Google Scholar] [CrossRef] [Scilit]
- Rudemiller, N.P.; Crowley, S.D. Interactions between the immune and the renin-angiotensin systems in hypertension. Hypertension 2016, 68, 289–296. [Google Scholar] [CrossRef] [Scilit]
- Harrison, D.G.; Guzik, T.J. Studies of the T-cell angiotensin receptor using Cre-Lox technology: An Unan-T-Cellpated result. Circ. Res. 2012, 110, 1543–1545. [Google Scholar] [CrossRef] [Scilit]
- Jurewicz, M.; McDermott, D.H.; Sechler, J.M.; Tinckam, K.; Takakura, A.; Carpenter, C.B.; Milford, E.; Abdi, R. Human t and natural killer cells possess a functional renin-angiotensin system: Further mechanisms of angiotensin ii-induced inflammation. J. Am. Soc. Nephrol. 2007, 18, 1093–1102. [Google Scholar]
- Lu, X.; Zhang, J.; Wen, Y.; Ren, J.; Griffiths, R.; Rudemiller, N.P.; Ide, S.; Souma, T.; Crowley, S.D. Type 1 angiotensin receptors on CD11c-expressing cells protect against hypertension by regulating dendritic cell-mediated t cell activation. Hypertension 2022, 79, 1227–1236. [Google Scholar] [CrossRef] [Scilit]
- Carter, K.; Shah, E.; Waite, J.; Rana, D.; Zhao, Z.Q. Pathophysiology of angiotensin ii-mediated hypertension, cardiac hypertrophy, and failure: A perspective from macrophages. Cells 2024, 13, 2001. [Google Scholar] [CrossRef] [Scilit]
- Yang, X.F.; Wang, H.; Huang, Y.; Huang, J.H.; Ren, H.L.; Xu, Q.; Su, X.M.; Wang, A.M.; Ren, F.; Zhou, M.S. Myeloid angiotensin ii type 1 receptor mediates macrophage polarization and promotes vascular injury in DOCA/salt hypertensive mice. Front. Pharmacol. 2022, 13, 879693. [Google Scholar] [CrossRef] [Scilit]
- Chen, X.L.; Tummala, P.E.; Olbrych, M.T.; Alexander, R.W.; Medford, R.M. Angiotensin ii induces monocyte chemoattractant protein-1 gene expression in rat vascular smooth muscle cells. Circ. Res. 1998, 83, 952–959. [Google Scholar] [CrossRef] [Scilit]
- Zhuo, J.L. Monocyte chemoattractant protein-1: A key mediator of angiotensin ii-induced target organ damage in hypertensive heart disease? J. Hypertens. 2004, 22, 451–454. [Google Scholar]
- Barhoumi, T.; Todryk, S. Role of monocytes/macrophages in renin-angiotensin system-induced hypertension and end organ damage. Front. Physiol. 2023, 14, 1199934. [Google Scholar] [CrossRef] [Scilit]
- Ishibashi, M.; Hiasa, K.; Zhao, Q.; Inoue, S.; Ohtani, K.; Kitamoto, S.; Tsuchihashi, M.; Sugaya, T.; Charo, I.F.; Kura, S.; et al. Critical role of monocyte chemoattractant protein-1 receptor CCR2 on monocytes in hypertension-induced vascular inflammation and remodeling. Circ. Res. 2004, 94, 1203–1210. [Google Scholar] [CrossRef] [Scilit]
- Oates, J.C.; Russell, D.L.; Van Beusecum, J.P. Endothelial cells: Potential novel regulators of renal inflammation. Am. J. Physiol. Ren. Physiol. 2022, 322, F309–F321. [Google Scholar] [CrossRef] [Scilit]
- Nabah, Y.N.; Mateo, T.; Estellés, R.; Mata, M.; Zagorski, J.; Sarau, H.; Cortijo, J.; Morcillo, E.J.; Jose, P.J.; Sanz, M.J. Angiotensin ii induces neutrophil accumulation in vivo through generation and release of CXC chemokines. Circulation 2004, 110, 3581–3586. [Google Scholar] [CrossRef] [Scilit]
- El Bekay, R.; Alvarez, M.; Monteseirín, J.; Alba, G.; Chacón, P.; Vega, A.; Martin-Nieto, J.; Jiménez, J.; Pintado, E.; Bedoya, F.J.; et al. Oxidative stress is a critical mediator of the angiotensin II signal in human neutrophils: Involvement of mitogen-activated protein kinase, calcineurin, and the transcription factor NF-κB. Blood 2003, 102, 662–671. [Google Scholar] [CrossRef] [Scilit]
- Chrysanthopoulou, A.; Gkaliagkousi, E.; Lazaridis, A.; Arelaki, S.; Pateinakis, P.; Ntinopoulou, M.; Mitsios, A.; Antoniadou, C.; Argyriou, C.; Georgiadis, G.S.; et al. Angiotensin ii triggers release of neutrophil extracellular traps, linking thromboinflammation with essential hypertension. JCI Insight 2021, 6, e148668. [Google Scholar] [CrossRef] [Scilit]
- Snyder, R.A.; Kaempfer, C.E.; Wintroub, B.U. Chemistry of a human monocyte-derived cell line (U937): Identification of the angiotensin i-converting activity as leukocyte cathepsin G. Blood 1985, 65, 176–182. [Google Scholar] [CrossRef] [Scilit][Green Version]
- Xia, N.; Hasselwander, S.; Reifenberg, G.; Habermeier, A.; Closs, E.I.; Mimmler, M.; Jung, R.; Karbach, S.; Lagrange, J.; Wenzel, P.; et al. B lymphocyte-deficiency in mice causes vascular dysfunction by inducing neutrophilia. Biomedicines 2021, 9, 1686. [Google Scholar] [CrossRef] [Scilit]
- Crowley, S.D.; Rudemiller, N.P. Immunologic effects of the renin-angiotensin system. J. Am. Soc. Nephrol. 2017, 28, 1350–1361. [Google Scholar] [CrossRef] [Scilit]
- Hong, H.J.; Chan, P.; Liu, J.C.; Juan, S.H.; Huang, M.T.; Lin, J.G.; Cheng, T.H. Angiotensin ii induces endothelin-1 gene expression via extracellular signal-regulated kinase pathway in rat aortic smooth muscle cells. Cardiovasc. Res. 2004, 61, 159–168. [Google Scholar] [CrossRef] [Scilit]
- Ertuglu, L.A.; Pitzer Mutchler, A.; Elijovich, F.; Laffer, C.L.; Sheng, Q.; Wanjalla, C.N.; Kirabo, A. Regulation of human salt-sensitivite hypertension by myeloid cell renin-angiotensin-aldosterone system. Front. Physiol. 2023, 14, 1208270. [Google Scholar] [CrossRef] [Scilit]
- Ferreira, N.S.; Tostes, R.C.; Paradis, P.; Schiffrin, E.L. Aldosterone, inflammation, immune system, and hypertension. Am. J. Hypertens. 2021, 34, 15–27. [Google Scholar] [CrossRef] [Scilit]
- Gorini, S.; Marzolla, V.; Mammi, C.; Armani, A.; Caprio, M. Mineralocorticoid receptor and aldosterone-related biomarkers of end-organ damage in cardiometabolic disease. Biomolecules 2018, 8, 96. [Google Scholar] [CrossRef] [Scilit]
- Herrada, A.A.; Campino, C.; Amador, C.A.; Michea, L.F.; Fardella, C.E.; Kalergis, A.M. Aldosterone as a modulator of immunity: Implications in the organ damage. J. Hypertens. 2011, 29, 1684–1692. [Google Scholar]
- Besedovsky, L.; Linz, B.; Born, J.; Lange, T. Mineralocorticoid receptor signaling reduces numbers of circulating human naïve t cells and increases their CD62L, CCR7, and CXCR4 expression. Eur. J. Immunol. 2014, 44, 1759–1769. [Google Scholar] [CrossRef] [Scilit]
- Bene, N.C.; Alcaide, P.; Wortis, H.H.; Jaffe, I.Z. Mineralocorticoid receptors in immune cells: Emerging role in cardiovascular disease. Steroids 2014, 91, 38–45. [Google Scholar] [CrossRef] [Scilit]
- Sun, X.N.; Li, C.; Liu, Y.; Du, L.J.; Zeng, M.R.; Zheng, X.J.; Zhang, W.C.; Zhu, M.; Kong, D.; Zhou, L.; et al. T-cell mineralocorticoid receptor controls blood pressure by regulating interferon-gamma. Circ. Res. 2017, 120, 1584–1597. [Google Scholar] [CrossRef] [Scilit]
- Barbaro, N.R.; Kirabo, A.; Harrison, D.G. A new role of mister (MR) T in hypertension: Mineralocorticoid receptor, immune system, and hypertension. Circ. Res. 2017, 120, 1527–1529. [Google Scholar]
- Brown, N.J. Contribution of aldosterone to cardiovascular and renal inflammation and fibrosis. Nat. Rev. Nephrol. 2013, 9, 459–469. [Google Scholar] [CrossRef] [Scilit]
- Mikolajczyk, T.P.; Śliwa, T.; Guzik, T.J. Immunometabolic switch in hypertension: How dendritic cell mineralocorticoid receptors drive Th17 polarization and blood pressure control. Eur. Heart J. 2025, 46, 1352–1354. [Google Scholar] [CrossRef] [Scilit]
- Higaki, A.; Mogi, M. Dendritic cells as potential initiators of immune-mediated hypertensive disorders. Hypertens. Res. 2022, 45, 527–529. [Google Scholar] [CrossRef] [Scilit]
- Werner, M.; Joulia, H.; Pussard, E.; Bergis, B.; Leblanc, P.E.; Wildenberg, L.; Huertas, A.; Vigué, B.; Duranteau, J.; Harrois, A. Hormonal response following hemorrhage after severe trauma: An observational prospective study. Crit. Care 2025, 30, 14. [Google Scholar] [CrossRef] [Scilit]
- Beierwaltes, W.H. The role of calcium in the regulation of renin secretion. Am. J. Physiol. Ren. Physiol. 2010, 298, F1–F11. [Google Scholar] [CrossRef] [Scilit]
- Forssmann, W.; Meyer, M.; Forssmann, K. The renal urodilatin system: Clinical implications. Cardiovasc. Res. 2001, 51, 450–462. [Google Scholar] [CrossRef] [Scilit]
- Toney, A.M.; Fox, D.; Chaidez, V.; Ramer-Tait, A.E.; Chung, S. Immunomodulatory role of urolithin a on metabolic diseases. Biomedicines 2021, 9, 192. [Google Scholar] [CrossRef] [Scilit]
- Groesdonk, H.V.; Bauer, A.; Kreft, B.; Heringlake, M.; Paarmann, H.; Pagel, H. Urodilatin and pentoxifylline prevent the early onset of escherichia coli-induced acute renal failure in a model of isolated perfused rat kidney. Kidney Blood Press Res. 2009, 32, 81–90. [Google Scholar] [CrossRef] [Scilit]
- Simões e Silva, A.C.; Silveira, K.D.; Ferreira, A.J.; Teixeira, M.M. ACE2, angiotensin-(1-7) and mas receptor axis in inflammation and fibrosis. Br. J. Pharmacol. 2013, 169, 477–492. [Google Scholar] [CrossRef] [Scilit]
- Cai, S.M.; Yang, R.Q.; Li, Y.; Ning, Z.W.; Zhang, L.L.; Zhou, G.S.; Luo, W.; Li, D.H.; Chen, Y.; Pan, M.X.; et al. Angiotensin-(1-7) improves liver fibrosis by regulating the nlrp3 inflammasome via redox balance modulation. Antioxid. Redox Signal 2016, 24, 795–812. [Google Scholar] [CrossRef] [Scilit]
- Hammer, A.; Yang, G.; Friedrich, J.; Kovacs, A.; Lee, D.H.; Grave, K.; Jörg, S.; Alenina, N.; Grosch, J.; Winkler, J.; et al. Role of the receptor mas in macrophage-mediated inflammation in vivo. Proc. Natl. Acad. Sci. USA 2016, 113, 14109–14114. [Google Scholar] [CrossRef] [Scilit]
- Regoli, D.; Gobeil, F. Kallikrein-kinin system as the dominant mechanism to counteract hyperactive renin-angiotensin system. Can. J. Physiol. Pharmacol. 2017, 95, 1117–1124. [Google Scholar] [CrossRef] [Scilit]
- Carretero, O.A. Vascular remodeling and the kallikrein-kinin system. J. Clin. Investig. 2005, 115, 588–591. [Google Scholar] [CrossRef]
- Madeddu, P.; Emanueli, C.; El-Dahr, S. Mechanisms of disease: The tissue kallikrein-kinin system in hypertension and vascular remodeling. Nat. Clin. Pract. Nephrol. 2007, 3, 208–221. [Google Scholar] [CrossRef] [Scilit]
- Szaryńska, M.; Olejniczak-Kęder, A. The immunomodulatory potential of bradykinin signaling in autoimmune conditions. Front. Immunol. 2026, 17, 1740800. [Google Scholar] [CrossRef] [Scilit]
- Seliga, A.; Lee, M.H.; Fernandes, N.C.; Zuluaga-Ramirez, V.; Didukh, M.; Persidsky, Y.; Potula, R.; Gallucci, S.; Sriram, U. Kallikrein-kinin system suppresses type I interferon responses: A novel pathway of interferon regulation. Front. Immunol. 2018, 9, 156. [Google Scholar] [CrossRef] [Scilit]
- Yayama, K.; Wang, C.; Chao, L.; Chao, J. Kallikrein gene delivery attenuates hypertension and cardiac hypertrophy and enhances renal function in Goldblatt hypertensive rats. Hypertension 1998, 31, 1104–1110. [Google Scholar] [CrossRef] [Scilit]
- Regoli, D.; Gobeil, F. Critical insights into the beneficial and protective actions of the kallikrein-kinin system. Vasc. Pharmacol. 2015, 64, 1–10. [Google Scholar] [CrossRef] [Scilit]
- Zhu, L.; Carretero, O.A.; Xu, J.; Wang, L.; Harding, P.; Rhaleb, N.E.; Yang, J.J.; Sumners, C.; Yang, X.P. Angiotensin II type 2 receptor-stimulated activation of plasma prekallikrein and bradykinin release: Role of SHP-1. Am. J. Physiol. Heart Circ. Physiol. 2012, 302, H2553–H2559. [Google Scholar] [CrossRef] [Scilit]
- Freundlich, M.; Gamba, G.; Rodriguez-Iturbe, B. Fibroblast growth factor 23—Klotho and hypertension: Experimental and clinical mechanisms. Pediatr. Nephrol. 2021, 36, 3007–3022. [Google Scholar] [CrossRef] [Scilit]
- Liu, S.; Tang, W.; Zhou, J.; Stubbs, J.R.; Luo, Q.; Pi, M.; Quarles, L.D. Fibroblast growth factor 23 is a counter-regulatory phosphaturic hormone for vitamin D. J. Am. Soc. Nephrol. 2006, 17, 1305–1315. [Google Scholar] [CrossRef] [Scilit]
- Dörr, K.; Kammer, M.; Reindl-Schwaighofer, R.; Lorenz, M.; Marculescu, R.; Poglitsch, M.; Beitzke, D.; Oberbauer, R. The effect of FGF23 on cardiac hypertrophy is not mediated by systemic renin-angiotensin-aldosterone system in hemodialysis. Front. Med. 2022, 9, 878730. [Google Scholar] [CrossRef] [Scilit]
- Andrukhova, O.; Slavic, S.; Smorodchenko, A.; Zeitz, U.; Shalhoub, V.; Lanske, B.; Pohl, E.E.; Erben, R.G. FGF23 regulates renal sodium handling and blood pressure. EMBO Mol. Med. 2014, 6, 744–759. [Google Scholar] [CrossRef] [Scilit]
- Kim, H.K.; Moe, O.W.; Vongpatanasin, W. High-phosphate-induced hypertension: The pathogenic role of fibroblast growth factor 23 (FGF23) signaling in sympathetic nervous system activation. Int. J. Mol. Sci. 2026, 27, 1138. [Google Scholar] [CrossRef] [Scilit]
- Dai, B.; David, V.; Martin, A.; Huang, J.; Li, H.; Jiao, Y.; Gu, W.; Quarles, L.D. A comparative transcriptome analysis identifying FGF23 regulated genes in the kidney of a mouse CKD model. PLoS ONE 2012, 7, e44161. [Google Scholar] [CrossRef] [Scilit]
- Fajol, A.; Chen, H.; Umbach, A.T.; Quarles, L.D.; Lang, F.; Föller, M. Enhanced FGF23 production in mice expressing PI3K-insensitive GSK3 is normalized by β-blocker treatment. FASEB J. 2016, 30, 994–1001. [Google Scholar] [CrossRef] [Scilit]
- Zhang, B.; Umbach, A.T.; Chen, H.; Yan, J.; Fakhri, H.; Fajol, A.; Salker, M.S.; Spichtig, D.; Daryadel, A.; Wagner, C.A.; et al. Up-regulation of FGF23 release by aldosterone. Biochem. Biophys. Res. Commun. 2016, 470, 384–390. [Google Scholar] [CrossRef] [Scilit]
- Ding, H.Y.; Ma, H.X. Significant roles of anti-aging protein klotho and fibroblast growth factor23 in cardiovascular disease. J. Geriatr. Cardiol. 2015, 12, 439–447. [Google Scholar]
- Zhou, L.; Mo, H.; Miao, J.; Zhou, D.; Tan, R.J.; Hou, F.F.; Liu, Y. Klotho ameliorates kidney injury and fibrosis and normalizes blood pressure by targeting the renin-angiotensin system. Am. J. Pathol. 2015, 185, 3211–3223. [Google Scholar] [CrossRef] [Scilit]
- Zhou, L.; Liu, Y. Wnt/β-catenin signaling and renin-angiotensin system in chronic kidney disease. Curr. Opin. Nephrol. Hypertens. 2016, 25, 100–106. [Google Scholar] [CrossRef] [Scilit]
- Yu, L.; Li, M. Roles of klotho and stem cells in mediating vascular calcification. Exp. Ther. Med. 2020, 20, 124. [Google Scholar] [CrossRef] [Scilit]
- Olejnik, A.; Franczak, A.; Krzywonos-Zawadzka, A.; Kałużna-Oleksy, M.; Bil-Lula, I. The biological role of klotho protein in the development of cardiovascular diseases. Biomed. Res. Int. 2018, 2018, 5171945. [Google Scholar] [CrossRef] [Scilit]
- Hajare, A.D.; Dagar, N.; Gaikwad, A.B. Klotho antiaging protein: Molecular mechanisms and therapeutic potential in diseases. Mol. Biomed. 2025, 6, 19. [Google Scholar] [CrossRef] [Scilit]
- Fitzpatrick, E.A.; Han, X.; Xiao, Z.; Quarles, L.D. Role of fibroblast growth factor-23 in innate immune responses. Front. Endocrinol. 2018, 9, 320. [Google Scholar] [CrossRef] [Scilit]
- Han, X.; Li, L.; Yang, J.; King, G.; Xiao, Z.; Quarles, L.D. Counter-regulatory paracrine actions of FGF-23 and 1,25(OH)2D in macrophages. FEBS Lett. 2016, 590, 53–67. [Google Scholar] [CrossRef] [Scilit]
- Rossaint, J.; Oehmichen, J.; Van Aken, H.; Reuter, S.; Pavenstädt, H.J.; Meersch, M.; Unruh, M.; Zarbock, A. FGF23 signaling impairs neutrophil recruitment and host defense during CKD. J. Clin. Investig. 2016, 126, 962–974. [Google Scholar] [CrossRef] [Scilit]
- Zhao, X.; Han, D.; Zhao, C.; Yang, F.; Wang, Z.; Gao, Y.; Jin, M.; Tao, R. New insights into the role of klotho in inflammation and fibrosis: Molecular and cellular mechanisms. Front. Immunol. 2024, 15, 1454142. [Google Scholar] [CrossRef] [Scilit]
- Akhabue, E.; Montag, S.; Reis, J.P.; Pool, L.R.; Mehta, R.; Yancy, C.W.; Zhao, L.; Wolf, M.; Gutierrez, O.M.; Carnethon, M.R.; et al. FGF23 (fibroblast growth factor-23) and incident hypertension in young and middle-aged adults: The cardia study. Hypertension 2018, 72, 70–76. [Google Scholar] [CrossRef] [Scilit]
- Zeng, Y.; Xu, G.; Feng, C.; Cai, D.; Wu, S.; Liu, Y.; Chen, Y.; Ma, W. Klotho inhibits the activation of nlrp3 inflammasome to alleviate lipopolysaccharide-induced inflammatory injury in a549 cells and restore mitochondrial function through sirt1/nrf2 signaling pathway. Chin. J. Physiol. 2023, 66, 335–344. [Google Scholar] [CrossRef] [Scilit]
- Kaszubowska, L.; Foerster, J.; Kaczor, J.J.; Karnia, M.J.; Kmieć, Z. Anti-inflammatory klotho protein serum concentration correlates with interferon gamma expression related to the cellular activity of both NKT-like and t cells in the process of human aging. Int. J. Mol. Sci. 2023, 24, 8393. [Google Scholar] [CrossRef] [Scilit]
- Mytych, J.; Romerowicz-Misielak, M.; Koziorowski, M. Klotho protects human monocytes from LPS-induced immune impairment associated with immunosenescent-like phenotype. Mol. Cell. Endocrinol. 2018, 470, 1–13. [Google Scholar] [CrossRef] [Scilit]
- Takenaka, T.; Kobori, H.; Inoue, T.; Miyazaki, T.; Suzuki, H.; Nishiyama, A.; Ishii, N.; Hayashi, M. Klotho supplementation ameliorates blood pressure and renal function in DBA/2-pcy mice, a model of polycystic kidney disease. Am. J. Physiol. Ren. Physiol. 2020, 318, F557–F564. [Google Scholar] [CrossRef] [Scilit]
- Bruno, R.M.; Ghiadoni, L.; Seravalle, G.; Dell’oro, R.; Taddei, S.; Grassi, G. Sympathetic regulation of vascular function in health and disease. Front. Physiol. 2012, 3, 284. [Google Scholar] [CrossRef] [Scilit]
- Sakitani, N. The sympathetic nervous system in the pathophysiology of hypertension: Mechanistic insights and therapeutic implications. Hypertens. Res. 2026, 49, 1324–1328. [Google Scholar] [CrossRef] [Scilit]
- DiBona, G.F. Sympathetic nervous system and the kidney in hypertension. Curr. Opin. Nephrol. Hypertens. 2002, 11, 197–200. [Google Scholar] [CrossRef] [Scilit]
- Azzam, Z.S.; Adir, Y.; Crespo, A.; Comellas, A.; Lecuona, E.; Dada, L.A.; Krivoy, N.; Rutschman, D.H.; Sznajder, J.I.; Ridge, K.M. Norepinephrine increases alveolar fluid reabsorption and Na,K-ATPase activity. Am. J. Respir. Crit. Care Med. 2004, 170, 730–736. [Google Scholar] [CrossRef] [Scilit]
- Friis, U.G.; Madsen, K.; Stubbe, J.; Hansen, P.B.; Svenningsen, P.; Bie, P.; Skøtt, O.; Jensen, B.L. Regulation of renin secretion by renal juxtaglomerular cells. Pflug. Arch. 2013, 465, 25–37. [Google Scholar] [CrossRef] [Scilit]
- DiBona, G.F. The sympathetic nervous system and hypertension: Recent developments. Hypertension 2004, 43, 147–150. [Google Scholar]
- Chavan, S.S.; Pavlov, V.A.; Tracey, K.J. Mechanisms and therapeutic relevance of neuro-immune communication. Immunity 2017, 46, 927–942. [Google Scholar] [CrossRef] [Scilit]
- Singh, M.V.; Chapleau, M.W.; Harwani, S.C.; Abboud, F.M. The immune system and hypertension. Immunol. Res. 2014, 59, 243–253. [Google Scholar] [CrossRef] [Scilit]
- Katayama, Y.; Battista, M.; Kao, W.M.; Hidalgo, A.; Peired, A.J.; Thomas, S.A.; Frenette, P.S. Signals from the sympathetic nervous system regulate hematopoietic stem cell egress from bone marrow. Cell 2006, 124, 407–421. [Google Scholar] [CrossRef] [Scilit]
- Marvar, P.J.; Thabet, S.R.; Guzik, T.J.; Lob, H.E.; McCann, L.A.; Weyand, C.; Gordon, F.J.; Harrison, D.G. Central and peripheral mechanisms of T-lymphocyte activation and vascular inflammation produced by angiotensin ii-induced hypertension. Circ. Res. 2010, 107, 263–270. [Google Scholar] [CrossRef] [Scilit]
- Gauthier, M.M.; Hayoz, S.; Banek, C.T. Neuroimmune interplay in kidney health and disease: Role of renal nerves. Auton. Neurosci. 2023, 250, 103133. [Google Scholar] [CrossRef] [Scilit]
- Touyz, R.M. The neuroimmune axis in the kidney: Role in hypertension. Circ. Res. 2015, 117, 487–489. [Google Scholar]
- Boahen, A.; Hu, D.; Adams, M.J.; Nicholls, P.K.; Greene, W.K.; Ma, B. Bidirectional crosstalk between the peripheral nervous system and lymphoid tissues/organs. Front. Immunol. 2023, 14, 1254054. [Google Scholar] [CrossRef] [Scilit]
- Freire, B.M.; de Melo, F.M.; Basso, A.S. Adrenergic signaling regulation of macrophage function: Do we understand it yet? Immunother. Adv. 2022, 2, ltac010. [Google Scholar] [CrossRef] [Scilit]
- Grisanti, L.A.; Woster, A.P.; Dahlman, J.; Sauter, E.R.; Combs, C.K.; Porter, J.E. A1-adrenergic receptors positively regulate toll-like receptor cytokine production from human monocytes and macrophages. J. Pharmacol. Exp. Ther. 2011, 338, 648–657. [Google Scholar] [CrossRef] [Scilit]
- Gosain, A.; Muthu, K.; Gamelli, R.L.; DiPietro, L.A. Norepinephrine suppresses wound macrophage phagocytic efficiency through alpha- and beta-adrenoreceptor dependent pathways. Surgery 2007, 142, 170–179. [Google Scholar] [CrossRef] [Scilit]
- Thoppil, J.; Mehta, P.; Bartels, B.; Sharma, D.; Farrar, J.D. Impact of norepinephrine on immunity and oxidative metabolism in sepsis. Front. Immunol. 2023, 14, 1271098. [Google Scholar] [CrossRef] [Scilit]
- Xiu, F.; Stanojcic, M.; Jeschke, M.G. Norepinephrine inhibits macrophage migration by decreasing CCR2 expression. PLoS ONE 2013, 8, e69167. [Google Scholar] [CrossRef] [Scilit]
- Itoh, K.; Izumi, Y.; Inoue, T.; Inoue, H.; Nakayama, Y.; Uematsu, T.; Fukuyama, T.; Yamazaki, T.; Yasuoka, Y.; Makino, T.; et al. Expression of three isoforms of Na-K-2Cl cotransporter (NKCC2) in the kidney and regulation by dehydration. Biochem. Biophys. Res. Commun. 2014, 453, 356–361. [Google Scholar] [CrossRef] [Scilit]
- Raikwar, N.; Braverman, C.; Snyder, P.M.; Fenton, R.A.; Meyerholz, D.K.; Abboud, F.M.; Harwani, S.C. Renal denervation and CD161a immune ablation prevent cholinergic hypertension and renal sodium retention. Am. J. Physiol. Heart Circ. Physiol. 2019, 317, H517–H530. [Google Scholar] [CrossRef] [Scilit]
- Liu, Y.; Jiang, Q.; Huang, Y.; Zhang, X.; Kang, H.; Yu, C.; Xia, Y.; Zhang, H. Hypothalamic microglia as dual hubs orchestrating local and systemic homeostasis in the periphery-central-periphery axis. Cells 2025, 14, 1780. [Google Scholar] [CrossRef] [Scilit]
- Du, J.; Yang, Y.; Rao, J.; Ma, X.; Tang, S.; Liu, J.; Liu, Y.; Liu, S.; Li, G.; Liang, S.; et al. Resident macrophages in the cervical sympathetic ganglia participate in P2Y12 receptor mediated diabetic cardiac autonomic neuropathy. Mol. Neurobiol. 2025, 62, 9744–9758. [Google Scholar] [CrossRef] [Scilit]
- Pongratz, G.; Straub, R.H. Chronic effects of the sympathetic nervous system in inflammatory models. Neuroimmunomodulation 2023, 30, 113–134. [Google Scholar] [CrossRef] [Scilit]
- Feriozzi, S.; Battaglia, Y.; Cirami, C.L.; Gangemi, C.; La Manna, G.; Gesualdo, L.; Muiesan, M.L.; Pani, A.; Pieruzzi, F.; Ribichini, F.; et al. The role of renal denervation for the treatment of hypertension in patients with chronic kidney disease: A position paper of the Italian society of nephrology. J. Nephrol. 2025, 38, 2053–2065. [Google Scholar] [CrossRef] [Scilit]
- Xiao, L.; Kirabo, A.; Wu, J.; Saleh, M.A.; Zhu, L.; Wang, F.; Takahashi, T.; Loperena, R.; Foss, J.D.; Mernaugh, R.L.; et al. Renal denervation prevents immune cell activation and renal inflammation in angiotensin ii-induced hypertension. Circ. Res. 2015, 117, 547–557. [Google Scholar] [CrossRef] [Scilit]
- Zaldivia, M.T.; Rivera, J.; Hering, D.; Marusic, P.; Sata, Y.; Lim, B.; Eikelis, N.; Lee, R.; Lambert, G.W.; Esler, M.D.; et al. Renal denervation reduces monocyte activation and monocyte-platelet aggregate formation: An anti-inflammatory effect relevant for cardiovascular risk. Hypertension 2017, 69, 323–331. [Google Scholar]
- Vallon, V.; Unwin, R.; Inscho, E.W.; Leipziger, J.; Kishore, B.K. Extracellular nucleotides and p2 receptors in renal function. Physiol. Rev. 2020, 100, 211–269. [Google Scholar] [CrossRef] [Scilit]
- Geerling, J.J.; Boon, M.R.; Kooijman, S.; Parlevliet, E.T.; Havekes, L.M.; Romijn, J.A.; Meurs, I.M.; Rensen, P.C. Sympathetic nervous system control of triglyceride metabolism: Novel concepts derived from recent studies. J. Lipid Res. 2014, 55, 180–189. [Google Scholar] [CrossRef] [Scilit]
- Inscho, E.W.; Cook, A.K.; Clarke, A.; Zhang, S.; Guan, Z. P2X1 receptor-mediated vasoconstriction of afferent arterioles in angiotensin II-infused hypertensive rats fed a high-salt diet. Hypertension 2011, 57, 780–787. [Google Scholar] [CrossRef] [Scilit]
- Soares, A.G.; Contreras, J.; Mironova, E.; Archer, C.R.; Stockand, J.D.; Abd El-Aziz, T.M. P2Y2 receptor decreases blood pressure by inhibiting ENAC. JCI Insight 2023, 8, e167704. [Google Scholar] [CrossRef] [Scilit]
- Li, X.; Zhu, L.J.; Lv, J.; Cao, X. Purinoceptor: A novel target for hypertension. Purinergic Signal. 2023, 19, 185–197. [Google Scholar] [CrossRef] [Scilit]
- Zhao, T.V.; Li, Y.; Liu, X.; Xia, S.; Shi, P.; Li, L.; Chen, Z.; Yin, C.; Eriguchi, M.; Chen, Y.; et al. ATP release drives heightened immune responses associated with hypertension. Sci. Immunol. 2019, 4, eaau6426. [Google Scholar] [CrossRef] [Scilit]
- Babou Kammoe, R.B.; Hamoudi, C.; Aoudjit, F. Role of nucleotide P2 receptors in the immune system: Focus on effector T cells. Cells 2025, 14, 1467. [Google Scholar] [CrossRef] [Scilit]
- Shokoples, B.G.; Berillo, O.; Comeau, K.; Chen, H.Y.; Higaki, A.; Caillon, A.; Ferreira, N.S.; Engert, J.C.; Thanassoulis, G.; Paradis, P.; et al. P2RX7 gene knockout or antagonism reduces angiotensin II-induced hypertension, vascular injury and immune cell activation. J. Hypertens. 2023, 41, 1701–1712. [Google Scholar] [CrossRef] [Scilit]
- Turner, C.M.; Elliott, J.I.; Tam, F.W. P2 receptors in renal pathophysiology. Purinergic Signal. 2009, 5, 513–520. [Google Scholar] [CrossRef] [Scilit]
- Menzies, R.I.; Tam, F.W.; Unwin, R.J.; Bailey, M.A. Purinergic signaling in kidney disease. Kidney Int. 2017, 91, 315–323. [Google Scholar] [CrossRef] [Scilit]
- Junger, W.G. Immune cell regulation by autocrine purinergic signalling. Nat. Rev. Immunol. 2011, 11, 201–212. [Google Scholar] [CrossRef] [Scilit]
- Schenk, U.; Frascoli, M.; Proietti, M.; Geffers, R.; Traggiai, E.; Buer, J.; Ricordi, C.; Westendorf, A.M.; Grassi, F. ATP inhibits the generation and function of regulatory t cells through the activation of purinergic p2x receptors. Sci. Signal. 2011, 4, ra12. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.; Chen, C.; Hu, G.L.; Chu, C.; Zhang, X.Y.; Du, M.F.; Zou, T.; Zhou, Q.; Liao, Y.Y.; Ma, Q.; et al. Associations of renalase with blood pressure and hypertension in Chinese adults. Front. Cardiovasc. Med. 2022, 9, 800427. [Google Scholar] [CrossRef] [Scilit]
- Vijayakumar, A.; Mahapatra, N.R. Renalase: A novel regulator of cardiometabolic and renal diseases. Hypertens. Res. 2022, 45, 1582–1598. [Google Scholar] [CrossRef] [Scilit]
- Guo, X.; Wang, L.; Velazquez, H.; Safirstein, R.; Desir, G.V. Renalase: Its role as a cytokine, and an update on its association with type 1 diabetes and ischemic stroke. Curr. Opin. Nephrol. Hypertens. 2014, 23, 513–518. [Google Scholar]
- Pointer, T.C.; Gorelick, F.S.; Desir, G.V. Renalase: A multi-functional signaling molecule with roles in gastrointestinal disease. Cells 2021, 10, 2006. [Google Scholar] [CrossRef] [Scilit]
- Lee, H.T.; Kim, J.Y.; Kim, M.; Wang, P.; Tang, L.; Baroni, S.; D’Agati, V.D.; Desir, G.V. Renalase protects against ischemic AKI. J. Am. Soc. Nephrol. 2013, 24, 445–455. [Google Scholar] [CrossRef] [Scilit]
- Du, M.; Huang, K.; Huang, D.; Yang, L.; Gao, L.; Wang, X.; Li, X.; Wang, C.; Zhang, F.; Wang, Y.; et al. Renalase is a novel target gene of hypoxia-inducible factor-1 in protection against cardiac ischaemia-reperfusion injury. Cardiovasc. Res. 2015, 105, 182–191. [Google Scholar] [CrossRef] [Scilit]
- Serban-Feier, L.F.; Cuiban, E.; Gogosoiu, E.B.; Stepan, E.; Radulescu, D. Renalase potential as a marker and therapeutic target in chronic kidney disease. Biomedicines 2024, 12, 1715. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.; He, X.; Li, X. Sodium-glucose transporter 2 inhibitors and cardiovascular-kidney-metabolic syndrome: A narrative review. Front. Endocrinol. 2025, 16, 1554637. [Google Scholar] [CrossRef] [Scilit]
- Gajjar, A.; Raju, A.K.; Menon, M.; Shah, S.A.Y.; Dani, S.; Weinberg, A. SGLT2 inhibitors and GLP-1 receptor agonists in cardiovascular-kidney-metabolic syndrome. Biomedicines 2025, 13, 1924. [Google Scholar] [CrossRef] [Scilit]
- Hartsell, S.E.; Wei, G.; Singh, R.; Throolin, M.; Nevers, M.R.; Sarwal, A.; Derington, C.G.; Curtis, C.; Boucher, R.E.; Shen, J.; et al. Comparative effectiveness of SGLT2 inhibitor and GLP-1 receptor agonist on kidney and cardiovascular outcomes by kidney failure risk. J. Am. Soc. Nephrol. 2026, 37, 1733–1747. [Google Scholar] [CrossRef] [Scilit]
- Wehbe, F.; Elliott, M.; Levin, A. CKDS at the crossroads: From failures to future therapies. Kidney Int. Rep. 2025, 10, 4145–4161. [Google Scholar] [CrossRef] [Scilit]
- Rossignol, P.; Clozel, M.; Dreier, R.F.; Flack, J.M.; Flamion, B.; Mann, J.; Narkiewicz, K.; Sassi-Sayadi, M.; Wang, J.G.; Weber, M.A.; et al. Aprocitentan in patients with chronic kidney disease and resistant hypertension. Hypertension 2026, 83, e25563. [Google Scholar] [CrossRef] [Scilit]
- Heidari Nejad, S.; Azzam, O.; Schlaich, M.P. Dual endothelin antagonism with aprocitentan as a novel therapeutic approach for resistant hypertension. Curr. Hypertens. Rep. 2023, 25, 343–352. [Google Scholar] [CrossRef] [Scilit]
- RMuralitharan, R.; Marques, F.Z.; O’Donnell, J.A. Recent advancements in targeting the immune system to treat hypertension. Eur. J. Pharmacol. 2024, 983, 177008. [Google Scholar] [CrossRef] [Scilit]
- Vinh, A.; Drummond, G.R.; Sobey, C.G. Immunity and hypertension: New targets to lighten the pressure. Br. J. Pharmacol. 2019, 176, 1813–1817. [Google Scholar] [CrossRef] [Scilit]
- Tao, H.; Huang, J.; Yancey, P.G.; Yermalitsky, V.; Blakemore, J.L.; Zhang, Y.; Ding, L.; Zagol-Ikapitte, I.; Ye, F.; Amarnath, V.; et al. Scavenging of reactive dicarbonyls with 2-hydroxybenzylamine reduces atherosclerosis in hypercholesterolemic Ldlr−/− mice. Nat. Commun. 2020, 11, 4084. [Google Scholar] [CrossRef] [Scilit]
- Shang, L.; Weng, X.; Wang, D.; Yue, W.; Mernaugh, R.; Amarnath, V.; Weir, E.K.; Dudley, S.C.; Xu, Y.; Hou, M.; et al. Isolevuglandin scavenger attenuates pressure overload-induced cardiac oxidative stress, cardiac hypertrophy, heart failure and lung remodeling. Free Radic. Biol. Med. 2019, 141, 291–298. [Google Scholar] [CrossRef] [Scilit]
- Pasqua, T.; Pagliaro, P.; Rocca, C.; Angelone, T.; Penna, C. Role of NLRP-3 inflammasome in hypertension: A potential therapeutic target. Curr. Pharm. Biotechnol. 2018, 19, 708–714. [Google Scholar] [CrossRef] [Scilit]
- Mo, B.; Ding, Y.; Ji, Q. Nlrp3 inflammasome in cardiovascular diseases: An update. Front. Immunol. 2025, 16, 1550226. [Google Scholar] [CrossRef] [Scilit]
- Du, Y.N.; Tang, X.F.; Xu, L.; Chen, W.D.; Gao, P.J.; Han, W.Q. SGK1-FOXO1 signaling pathway mediates Th17/Treg imbalance and target organ inflammation in angiotensin ii-induced hypertension. Front. Physiol. 2018, 9, 1581. [Google Scholar] [CrossRef] [Scilit]
- Norlander, A.E.; Saleh, M.A.; Pandey, A.K.; Itani, H.A.; Wu, J.; Xiao, L.; Kang, J.; Dale, B.L.; Goleva, S.B.; Laroumanie, F.; et al. A salt-sensing kinase in T lymphocytes, SGK1, drives hypertension and hypertensive end-organ damage. JCI Insight 2017, 2, e92801. [Google Scholar] [CrossRef] [Scilit]
- Trott, D.W.; Thabet, S.R.; Kirabo, A.; Saleh, M.A.; Itani, H.; Norlander, A.E.; Wu, J.; Goldstein, A.; Arendshorst, W.J.; Madhur, M.S.; et al. Oligoclonal CD8+ T cells play a critical role in the development of hypertension. Hypertension 2014, 64, 1108–1115. [Google Scholar] [CrossRef] [Scilit]
- Norlander, A.E.; Madhur, M.S.; Harrison, D.G. The immunology of hypertension. J. Exp. Med. 2018, 215, 21–33. [Google Scholar] [CrossRef] [Scilit]
- Barhoumi, T.; Kasal, D.A.; Li, M.W.; Shbat, L.; Laurant, P.; Neves, M.F.; Paradis, P.; Schiffrin, E.L. T regulatory lymphocytes prevent angiotensin ii-induced hypertension and vascular injury. Hypertension 2011, 57, 469–476. [Google Scholar] [CrossRef] [Scilit]
- Srinivas, B.; Alluri, K.; Fortuno, P.; Matrougui, K. Stim1 deletion in regulatory t cells restores redox balance and protects against hypertension-induced cardiovascular complications. Transl. Res. 2026, 290, 50–60. [Google Scholar] [CrossRef] [Scilit]
- Navaneethabalakrishnan, S.; Goodlett, B.L.; Smith, H.L.; Cardenas, A.; Montalvo, R.A., II; Peterson, G.C.; Mitchell, B.M. Blood pressure reduction and anti-inflammatory macrophage augmentation attenuate uterine immune dysregulation and inflammation in mice with salt-sensitive hypertension. Clin. Sci. 2025, 139, 1629–1642. [Google Scholar] [CrossRef] [Scilit]
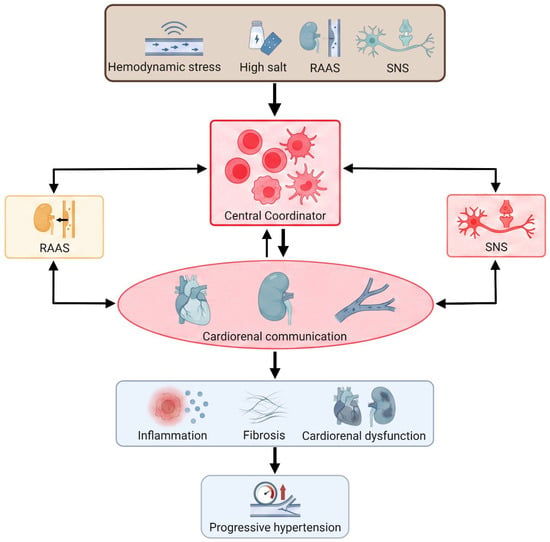
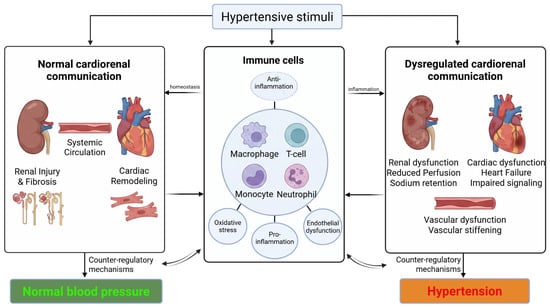
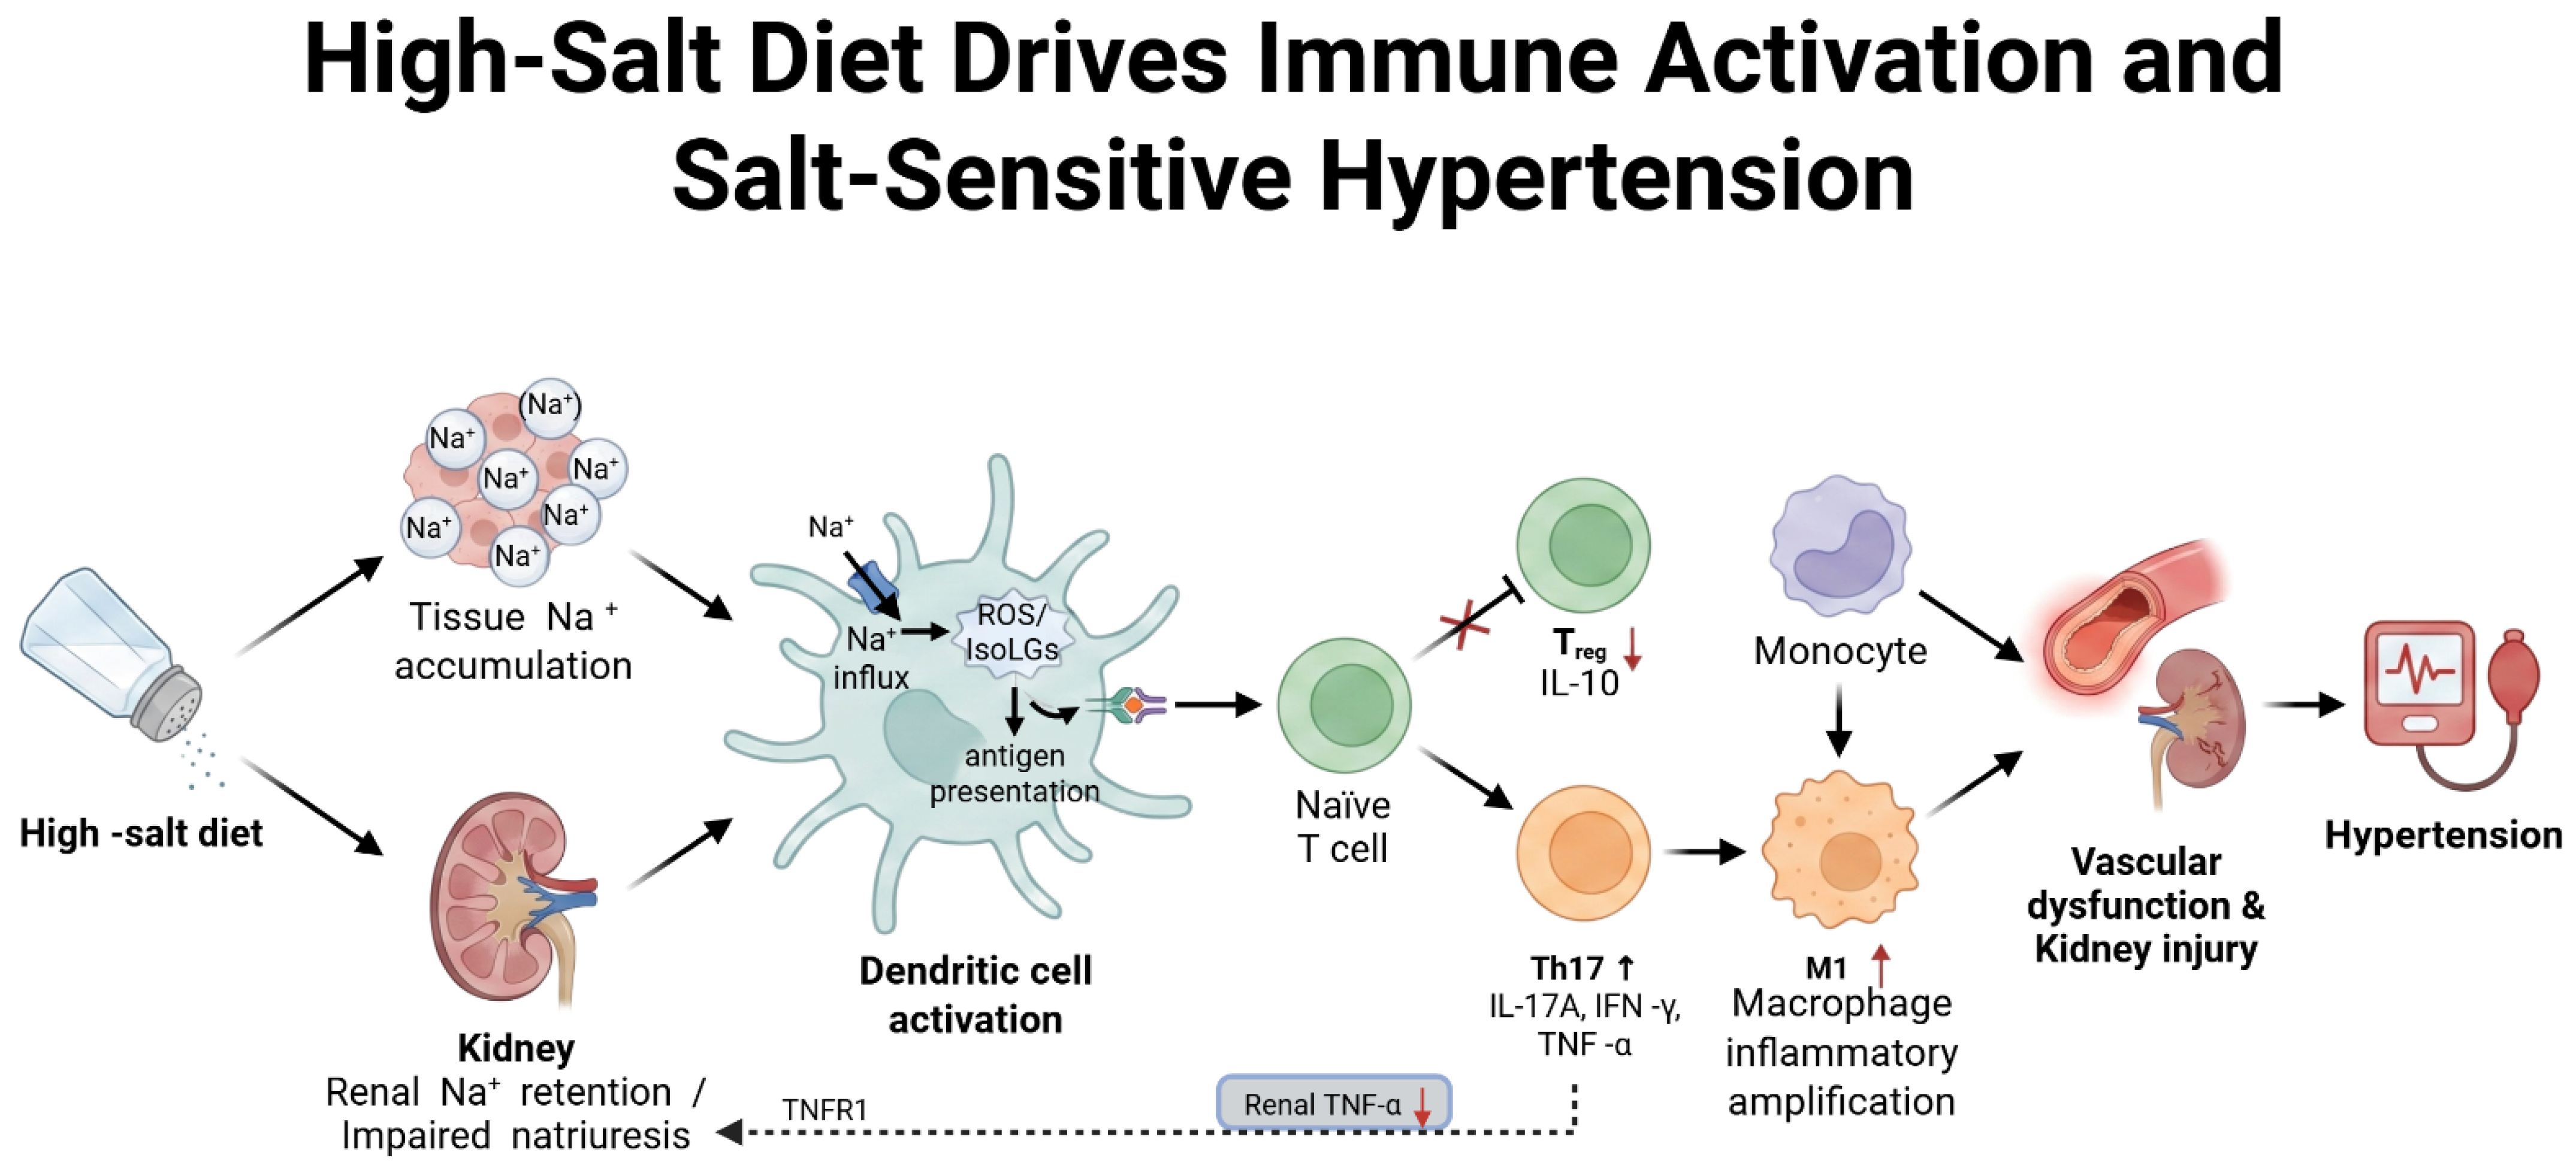
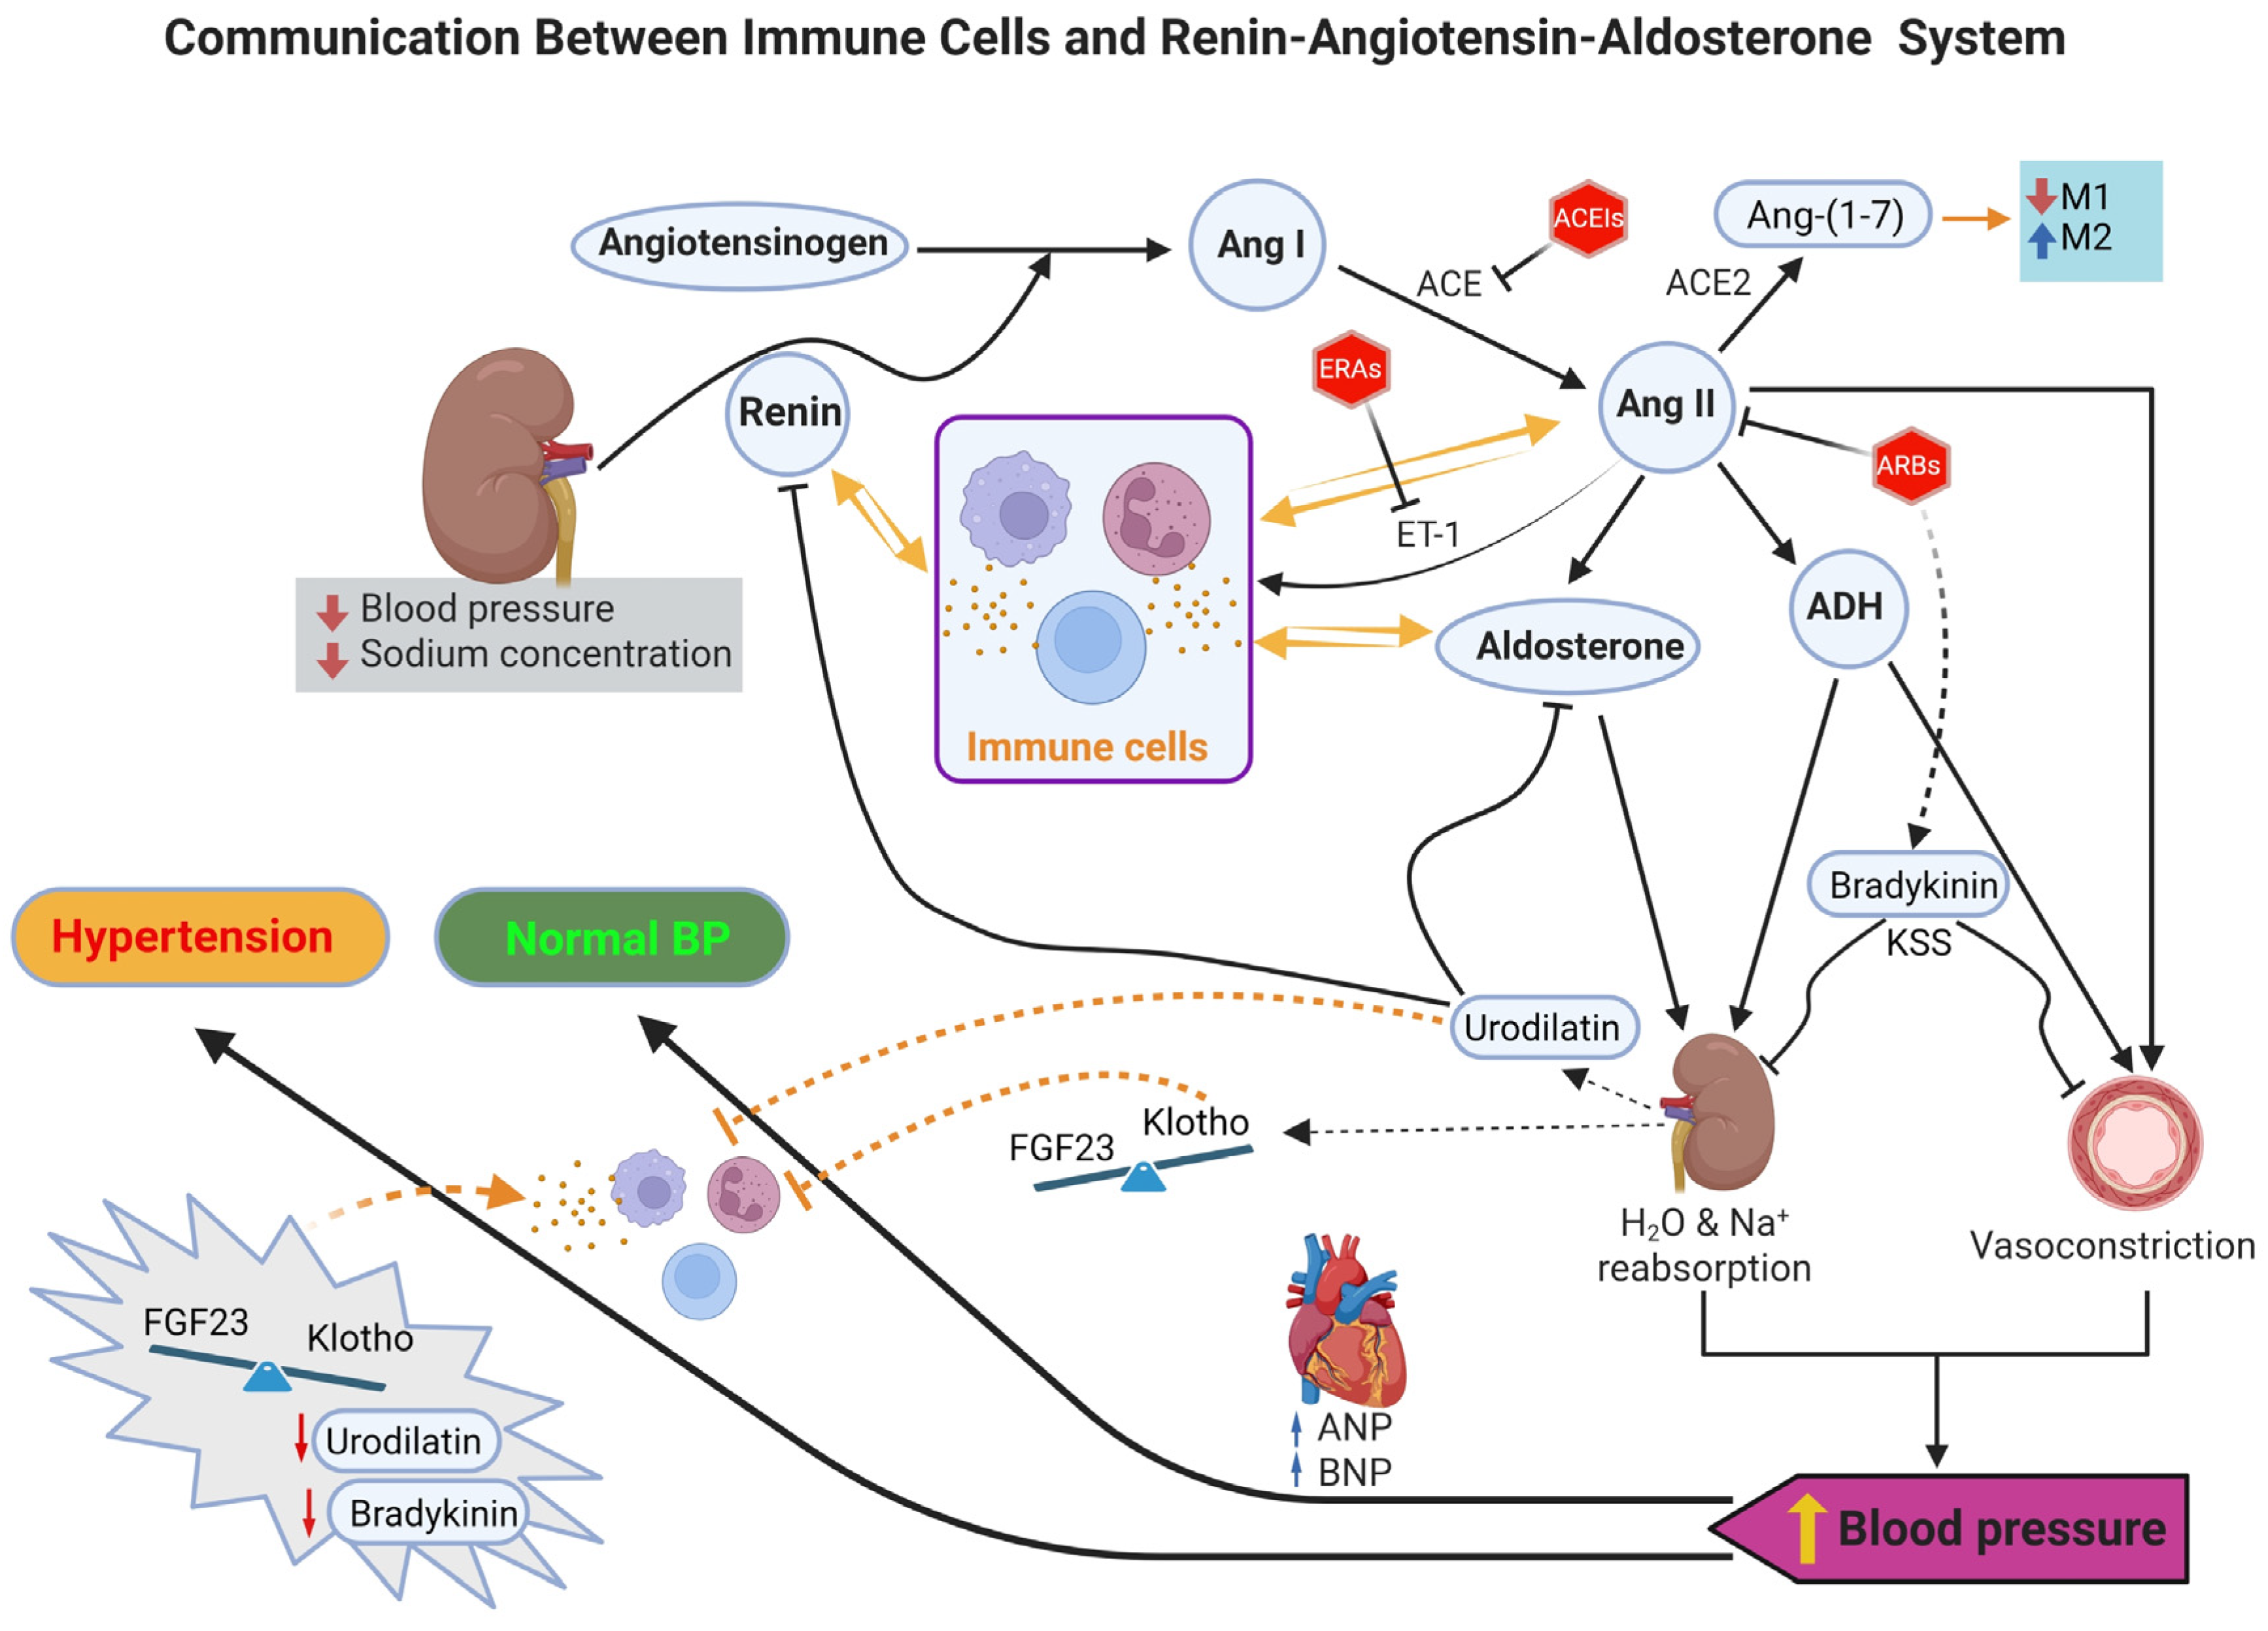
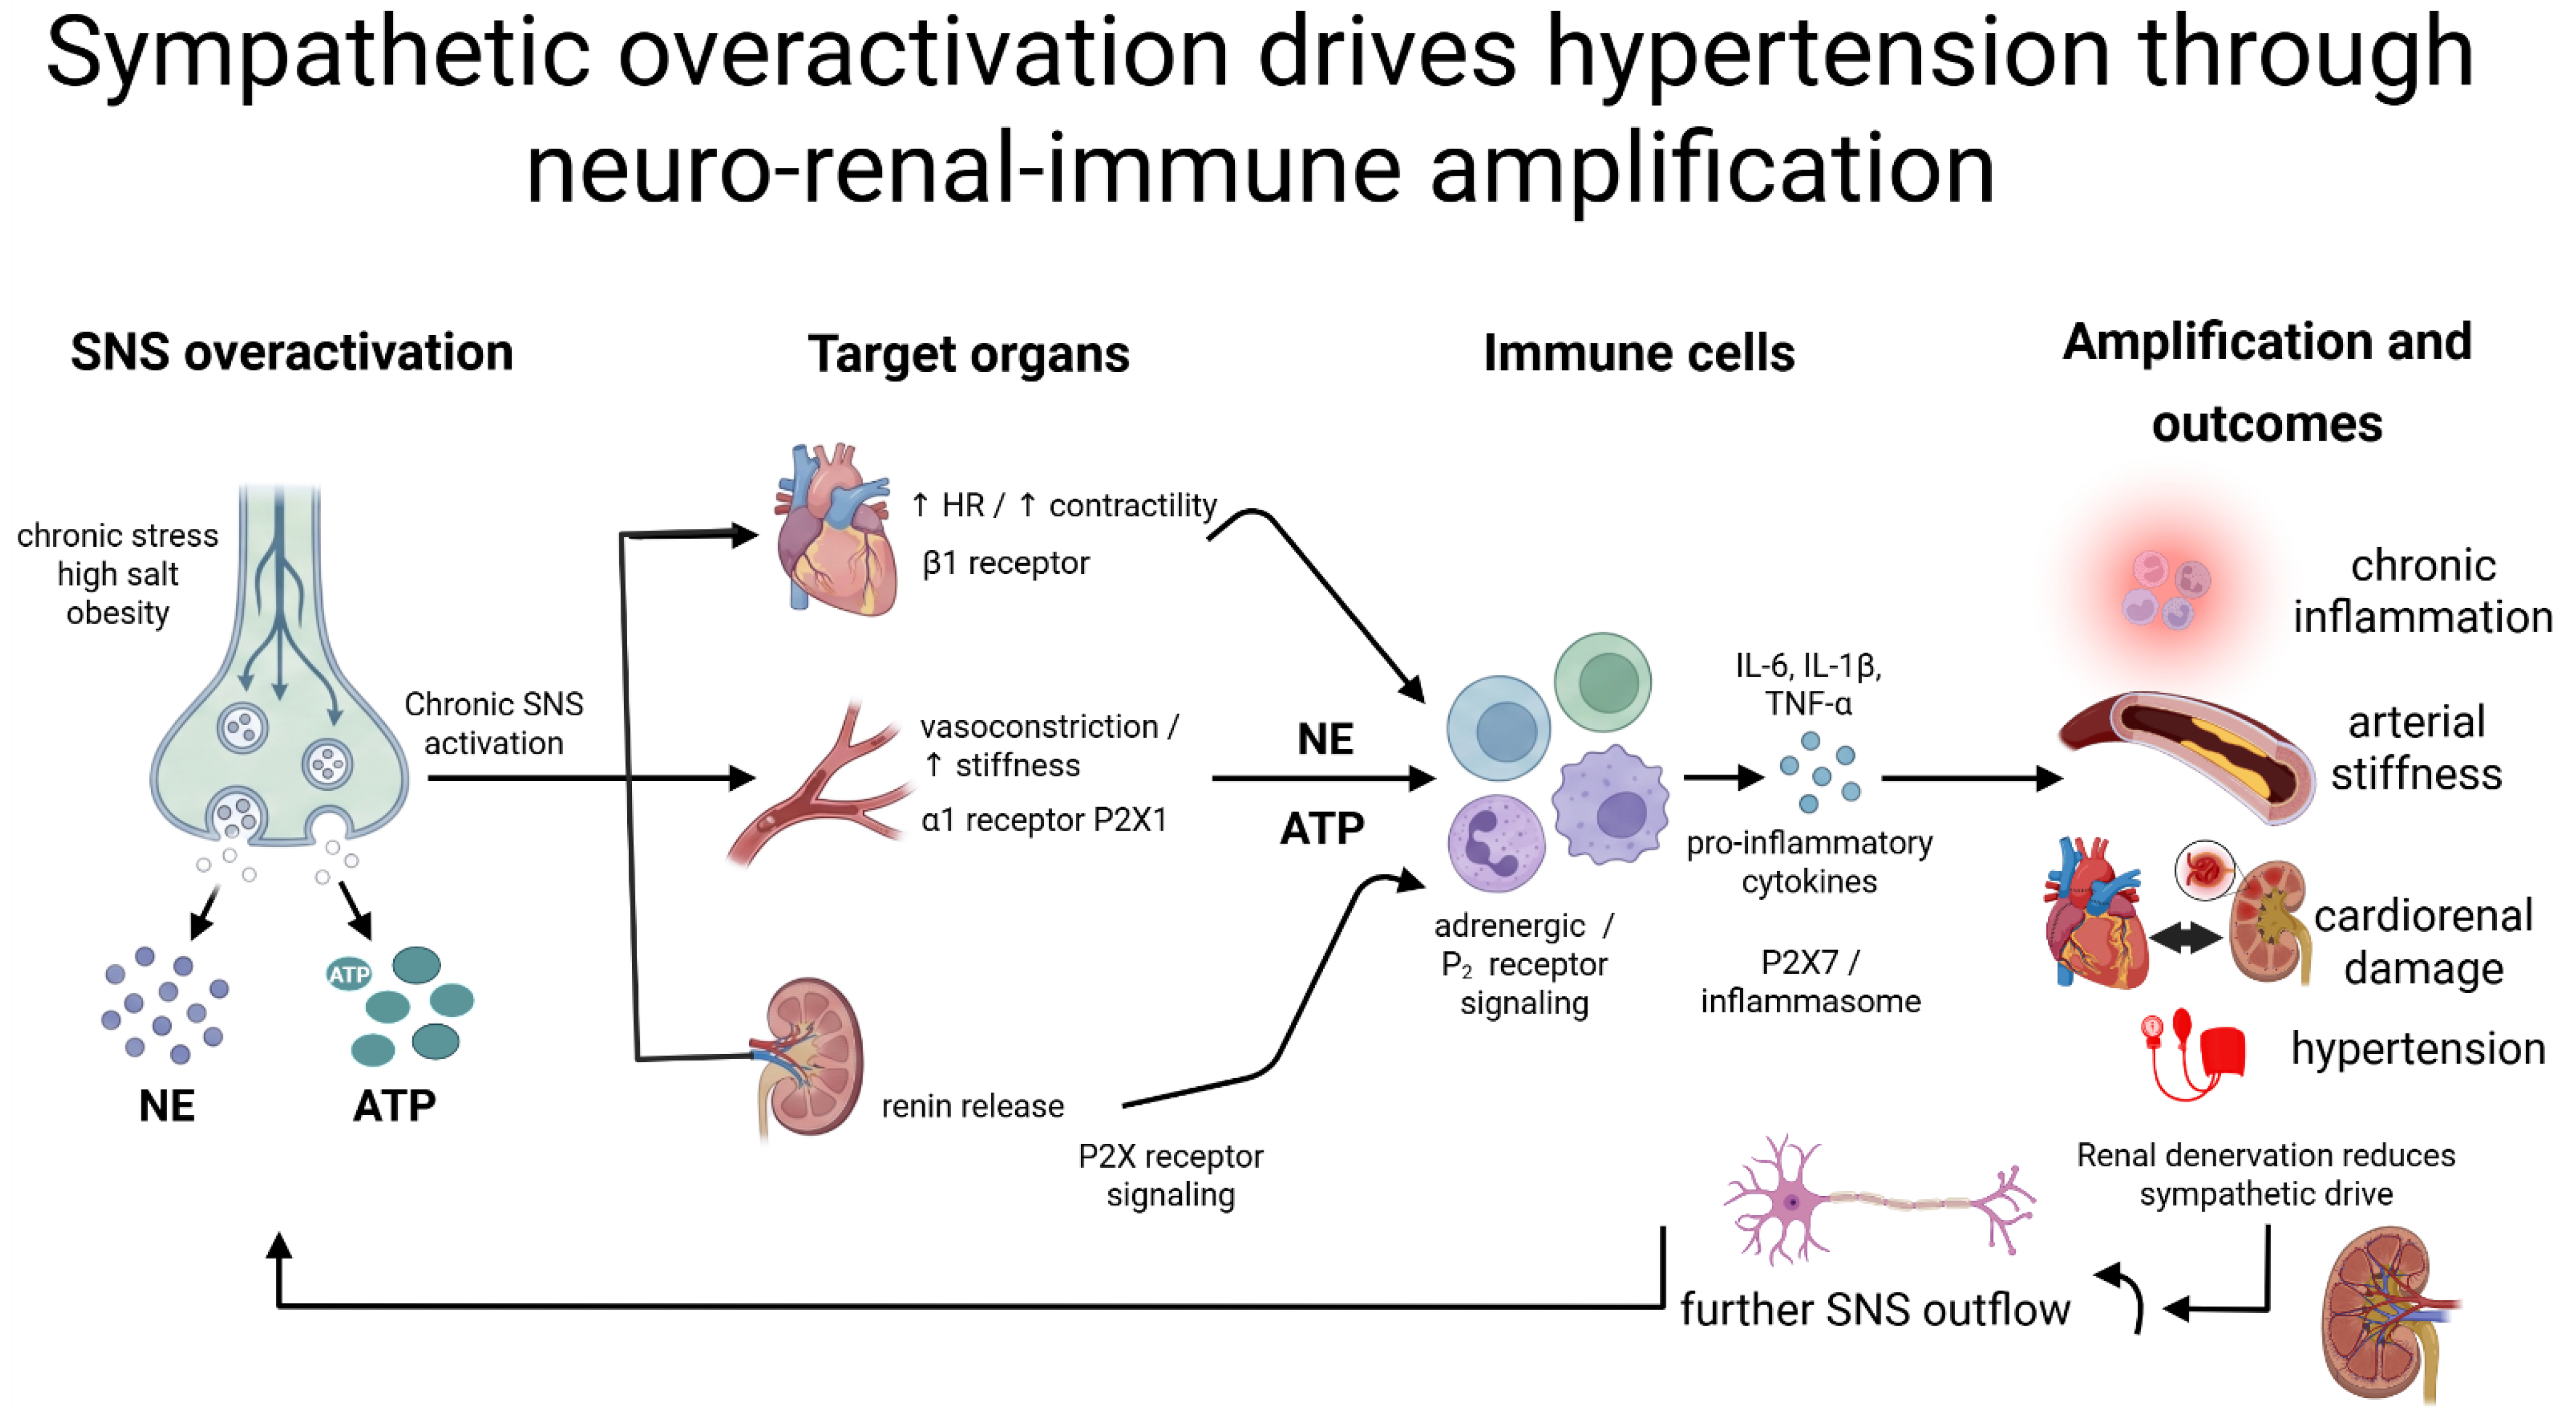
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.