


Abstract
Background/Objectives: Bone grafting is fundamental in oral implantology in order to achieve appropriate esthetic and functional results. One of the options for bone grafting is the use of allografts, which can be produced using femoral heads removed during orthopedic surgeries in accordance with the principles of the circular economy. The aim of this study is to examine the environmental impacts of the production of cancellous block and granulates of bone graft materials produced in this way. Methods: The cradle-to-gate life cycle assessment was performed at the Petz Aladár University Teaching Hospital Tissue Bank Department, Győr, Hungary, with the system boundaries defined and the bone graft material produced during a production process defined as a functional unit. The environmental impacts were determined with the OpenLCA v2.5.0. software, using the ReCiPe v1.03 2016 midpoint (H) and endpoint (H) assessment methods. Results: During the production process, 500 g of bone graft material is produced in both forms, packaged as 1 g. The carbon footprint of the production of the cancellous bone block was 88,972 kgCO2-Eq, while that of the bone granulates was 100,033 kgCO2-Eq, to which the chemicals used for the degreasing and deantigenization of the bone tissue contributed the most. Within the impact categories, the material resources of metals–minerals, terrestrial ecotoxicity and climate change contributed the most to the environmental impacts. Within most impact categories, electricity was the most significant influencing factor. Conclusions: The environmental impact of the production of bone substitute granulates is greater than that of the bone block, to which the packaging of the products contributes primarily.
1. Introduction
Environmental sustainability is of paramount importance for the future of humanity, as increasing industrialization and human activities are causing significant damage to the planet, including human health [1,2]. Healthcare also contributes to greenhouse gas emissions [3,4]. Sustainable solutions are essential to ensure that future generations can meet their needs [5].
Generating significant amounts of waste in healthcare, including infectious and hazardous waste, increases environmental pollution and public health risks. Therefore, the application of sustainable and regulated waste management is of outstanding importance [6,7,8]. Medical waste must be managed according to strict regulations to avoid health risks and environmental pollution [1,7]. The environmental and health risks of waste and the shortcomings of current disposal methods increase the need for recycling and reuse in the healthcare sector. This procedure helps to reduce the use of natural resources [9].
The circular economy is an economic model in which waste is treated as a valuable raw material, material and energy consumption is minimized, and products are recycled whenever possible, thus facilitating the implementation of the “zero waste” principle [1,7,10,11].
Recycling medical waste can be an environmentally friendly solution, for example by autoclaving infectious materials and then safely recycling them [9,11]. In addition, the processing and recycling of used medical devices and materials can also contribute to reducing waste and reducing environmental burdens [9,12].
The femoral head removed during orthopedic surgery, which contains a high quality and quantity of trabecular tissue, has the potential to be recycled for the production of bone substitutes, transforming this tissue, previously treated as medical waste, into a valuable raw material [13,14].
In dentistry and oral surgery, bone grafting is of paramount importance for the optimal rehabilitation of edentulous patients, given the fact that an adequate quantity and quality of alveolar bone is essential for the placement of stable implants. Bone loss can occur for various reasons, such as tooth extraction, trauma, infection or congenital anomalies, and therefore bone grafting procedures are often necessary [15,16,17,18,19,20,21]. During these procedures, bone is replaced with natural or synthetic graft materials and various regeneration techniques to ensure the long-term stability of implants [10,22]. In modern oral surgery and dentistry, bone grafting offers significant advantages not only from a functional but also from an esthetic point of view [23,24,25].
Allografts are excellent bone substitutes in dentistry and orthopedics, as their natural structure promotes bone formation and provides a secure base for implantation. Thus, they easily contribute to the stability and esthetic restoration of the maxillary bones [13,17,19,22]. They are also suitable for personalized bone replacement, as they are available in different sizes and shapes and can be customized to the needs of the given patient through their processing [13,14].
The role of tissue banks, among others, is to produce bone allografts, for which incoming tissues are collected, processed, tested, stored and safely transported to the site of use [13,14,26]. Their presence facilitates the development of modern reconstructive surgery, as they provide a quick and safe solution for complex orthopedic and dental procedures [14].
Tissue banks in the European Union must comply with strict legal and quality requirements covering the collection, processing, storage and use of tissues. The aim of this regulation is to preserve the biological properties of the grafts, guarantee their microbiological safety, and thus ensure the effective and safe use of transplants for patients [14,17,26,27,28].
From the perspective of sustainability, it is highly recommended to assess the environmental impacts of a product or process; life cycle assessment (LCA) is necessary, which provides an opportunity to compare different solutions from a sustainability perspective [8].
Life cycle assessment is an internationally recognized method that aims to assess the full environmental impact of a product or process during production, use, and disposal. The ISO 14040 and 14044 standards define the main steps of the process, including goal and scope definition, inventory analysis, impact category analysis, and interpretation of the results [7,8,11,29]. Impact categories may include global warming potential, human toxicity, and impacts on aquatic ecosystems and soil, which can be used to more accurately assess environmental burdens [3,30]. The midpoint categories of the life cycle impact assessment can be harmful to human health, the results of which can be aggregated through damage pathways in the endpoint category, determining DALYs [31,32]. This is a special morbidity indicator that can be used to quantify the global burden of premature death or disability due to diseases and injuries, thus making it possible to compare diseases that cause premature death with those that cause disability [3,32,33].
The femoral heads removed during orthopedic surgeries are considered medical waste, but it is also a valuable raw material, from which the production of bone graft material fits into the principles of the circular economy, and its processing can help make healthcare and dentistry more environmentally conscious. The aim of this study is to perform a life cycle assessment on allografts produced by processing femoral heads removed during orthopedic surgeries at the West Hungarian Regional Tissue Bank within the Petz Aladár University Teaching Hospital, Győr, Hungary, in the framework of a methodological LCA case study. During this process the investigation of the environmental impacts of the allograft block and bone granulates manufacturing process in the midpoint and endpoint impact categories, identification of the factors with the greatest contribution, and analysis of how the modification of their parameters affects the results was performed. It was also essential to assess the environmental impacts of incinerating bone as medical waste by determining the potential environmental benefits of implementing a circular economy.
2. Materials and Methods
The present study was approved by the Legal and Ethics Committee of Petz Aladár University Teaching Hospital (Approval no. 9/485-1/2025).
Life cycle assessment is the gold standard for examining and understanding the environmental impacts of a product or process [29]. The method is also used to measure the environmental impacts of healthcare activities [8]. According to the International Standards Organization (ISO) series 14040:2006 protocol and its 2020 amendment, there are 4 phases to perform an LCA analysis: (1) definition of the scope, functional unit and system boundaries; (2) analysis of the Life Cycle Inventory via databases, like Ecoinvent; (3) impact assessment using 18 impact categories; (4) interpretation of results [8,32,34]. LCA modeling can be done from cradle to gate, i.e., from raw materials to the pre-use stage, or from cradle to grave, which covers the entire life cycle of the product [29,35].
2.1. Objective and Scope
Goal and scope:
The aim of the study was to assess the environmental impact of the manufacturing process of allografts produced from femoral heads removed during orthopedic surgeries. Since the analysis was limited to the manufacturing phase only, the applied LCA approach follows the cradle-to-gate model. In order to better understand the environmental impacts, the amount of CO2 emitted during manufacturing was compared with the potential CO2 emissions that would be generated when the femoral heads were disposed of as infectious medical waste, primarily by incineration, given that this is the most commonly used disposal method, in accordance with the principles of the circular economy.
Functional unit:
The functional unit defines the specific product or service whose life cycle assessment is being examined. Several type of bone substitutes can be produced from the processing of femoral heads, which have different indications and areas of use. Since cancellous or cortico-cancellous blocks or bone granules are most commonly used in dental implantology, the production process of each of them was meant to be the functional unit to serve as a representative case for methodological demonstration.
System boundaries:
The definition of system boundaries is a key element in the life cycle assessment, as it identifies the raw materials, inputs, processes, outputs and waste streams that belong to the examined functional unit. An accurate and transparent definition of system boundaries is essential to ensure comparability of the results of different life cycle assessments. In this study, a cradle-to-gate approach was used; the system boundaries cover only the production processes and do not include the transport, clinical use or waste management of the finished bone substitute materials. Cradle-to-gate system boundaries are used for the life cycle assessment of the manufacturing process to ensure comparability with other manufacturing processes. In addition, the use of bone grafts can be diverse and, in some cases, difficult to track, but the values can serve as a building block for further LCA analysis of their use.
Since the removal of femoral heads during orthopedic surgeries takes place in the same institution where they are processed, the transport of raw materials was excluded from the examined model. However, the system that includes the chemical substances does include disposable materials, for which energy consumption is necessary for the processing and waste management, but does not include the travel of personnel or the maintenance of the equipment used in the process. The system boundaries of the LCA analysis lack the processes of screening donor samples, or hematological and microbiological tests, as these are merely related to the allograft production process. Serological and microbiological analyses are performed outside the manufacturing process, not within the Tissue Bank. These tests are not necessary for the fulfillment of the functional unit, as they only provide information on the safety of the product.
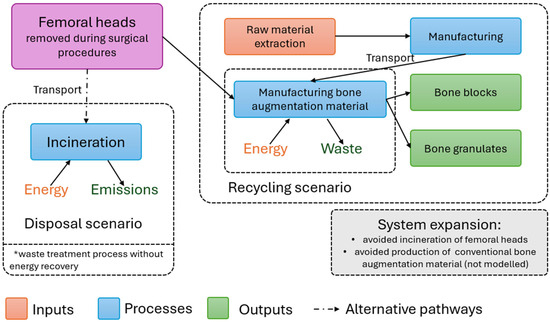
For a more reliable assessment of the environmental impacts of the recycling process, a system expansion method was used. The system expansion also considered the potential alternative pathway, namely the incineration of the femoral heads as medical waste. The bone graft materials produced during the process displaced the function of conventional bone graft materials. Due to the lack of available data in the literature and the scope of the current study, the conventional production process was not explicitly modeled.
The disposal scenario of the incineration of femoral heads was included within the framework of the system expansion. By applying the system expansion, the aim of the LCA analysis was to assess more accurately the environmental impacts, especially with regard to the benefits of applying a circular economy. According to the methodology, in addition to calculating the carbon dioxide emissions generated during the production of allografts, the value of the environmental load that would arise if the unprocessed femoral heads were incinerated as medical waste was also compared. The process of incinerating femoral heads as medical waste has been modeled based on the literature data (AP 42, Fifth Edition, Volume I, Chapter 2: Solid Waste Disposal, and the data found on the website of the local medical waste incinerator). The system boundaries included the packaging of medical waste, its transportation from the hospital to the incinerator, and its incineration in a rotary drum incinerator furnace [36,37].
The system boundaries are shown in Figure 1.
Figure 1.
System boundaries. *: Waste incineration can be carried out either in a conventional manner or with recovery of generated heat for energy production. In the present study, the energy produced during the incineration process was not taken into account.
2.2. Analysis of the Life Cycle Inventory
Data collection:
The primary data collection was carried out at the West Hungarian Regional Tissue Bank within the framework of the Petz Aladár University Teaching Hospital. The determination of the amount of materials and tools was based on observations and measurements.
The assumptions are based on empirical observations and years of professional experience of the Tissue Bank.
The following assumptions have been made regarding the calculations:
List of assumptions:
- During a processing cycle, an average of 24 femoral heads are processed, with a total weight of approximately 2720 g.
- Each work process is performed by one person wearing full protective equipment, including a sterile surgical gown, surgical mask, hair net and foot bag.
- Allografts are manipulated under sterile conditions in sterile fields.
- Bone waste generated during bone cutting and grinding cannot be reused due to metallic contamination and is therefore disposed of as infectious waste.
- The femoral heads received after surgeries are stored in a freezer for an average of 21 days until the 24 pieces are collected to start the processing process.
- The degreasing process takes an average of 28 days, during which the solution is changed initially every two days and then every three days; 2 L of methanol–chloroform solution is used at one time.
- Deantigenization lasts two days, during which the container containing the allografts is placed in a thermostat, and the process is carried out with 2 L of sodium azide-iodoacetic acid solution.
- Bleaching lasts one day, for which 2 L of hydrogen peroxide solution is used.
- During the transitions between the different chemical solutions, the bones are rinsed with distilled water.
- In the case of bone granules, the different size fractions are separated by sieving and then packaged according to size categories.
- The instruments used during production are not part of the system boundaries because they were few and need to be re-sterilized several times for different production processes, so their environmental impact is not significant.
- To ensure the sterility of the allografts, the entire batch is first sterilized in an ethylene oxide sterilizer, then lyophilization and individual packaging are carried out in a separate, sterile room under sterile conditions.
- The lyophilization process is a one-day long process.
- The packaging materials used for the final packaging of the allografts are sterilized in an autoclave to ensure sterility for all the completed allografts at the same time.
- Equipment maintenance activities are not included in the system boundaries, as they occur with a low frequency compared to the total production volume of the manufacturing processes examined, so their environmental impact over the entire life cycle can be considered less important.
- Personnel-related activities are not included in the system boundaries, as the scope of activities of the personnel involved in the Tissue Bank is diverse and cannot be exclusively linked to the production process of the bone grafts. As a result, the allocation of the environmental burden of personnel resources reduced to the production process of the bone grafts would have been methodologically uncertain. Furthermore, the production process under study consists of several steps that are functionally and temporally distinct, which can further complicate the reliable attribution of personnel-related impacts.
- An average of 500 units of 1 g bone substitute preparation can be produced during one processing cycle.
Life Cycle Inventory:
During the Life Cycle Inventory (LCI), each step of the allograft production process was mapped out minutiously in order to determine the carbon emissions of the production and the environmental impact of each process. The production processes of cancellous or cortico-cancellous blocks and bone granule allografts were included in the study, and consist of receiving and freezing the bone; cutting, degreasing, deantigenization, and bleaching of the bone; and grinding and sieving in the case of bone granule production. Additional processing phases included sterilization, lyophilization and packaging of the allografts.
The necessary materials and instruments were assigned to each step, but only the most necessary ones were considered. The materials used are broken down into their components and their exact mass is determined on an analytical balance. The information related to the composition and packaging materials is recorded based on the manufacturer’s data. Ten pieces of materials and instruments were examined and the considered weight was determined from the average weight values. The environmental impact of the materials is considered for each processing step.
The energy consumption of the devices was estimated based on their performance and operating time (Table 1).
Table 1.
Devices used in the process.
The waste generated during the process was classified into separate categories: bone residues generated during bone cutting and grinding were classified as medical waste, the chemicals used were classified as hazardous waste, while the remaining, non-hazardous waste was classified as municipal solid waste. The hospital took care of their collection, transportation and disposal.
The femoral heads are processed only after the patient’s written informed consent has been obtained, which allows the bone removed during surgeries to be used for the production of allografts.
To ensure the quality and safety of allografts, donors undergo a rigorous selection and screening process, which includes serological testing. Negative results for HIV-1/2, HBsAg, HBcoreAg, HCV and Treponema pallidum (lues) are essential during testing. In order to control the manufacturing process, bone samples are microbiologically tested after lyophilization but before packaging to ensure that no contamination has occurred during processing. When selecting donors, the medical history questionnaire includes, among other things, medical history, presence of infectious diseases and other health risk factors. The donor selection criteria are in accordance with EACTB principles (Guide to the safety and quality of tissues and cells for human application, 5th edition).
2.3. Assessing the Life Cycle Impact
In order to determine the environmental impacts of the allograft manufacturing procedure, a life cycle assessment (LCA) was performed using the openLCA software, based on the merged bioenergiedat_18; elcd_3_2_greendelta_v2_18_correction; needs_18; OzLCI2019, worldsteel_2020, exiobase 3.9.4. and USDA_1901009 and BAFU-2025_LCI DB_17Dec25 databases. To quantify the impacts of the process, the ReCiPe v1.03 2016 midpoint (H) method was used, which evaluates life cycle impacts in 18 environmental impact categories, including greenhouse gas emissions (kg CO2-eq), ozone depletion (kg CFC-11-eq), acidification (mol H+-eq) and eutrophication (kg N-eq, kg P-eq) and ReCiPe v1.03 2016 endpoint (H) method to calculate Disability Adjusted Life Years (DALYs).
The LCIA analysis makes it possible to compare the environmental impacts of different processes and leads to the identification of the points where the greatest efficiency gains or emission reductions can be achieved. Thus, more sustainable manufacturing strategies can be obtained. To perform the uncertainty analysis, lognormal uncertainty distributions were assigned to the most influential input parameters, and Monte Carlo simulation was performed with 5000 iterations LCA studies are based on estimates and assumptions. As part of the sensitivity analysis, the following scenarios were modeled to assess the robustness of the results: (i) in the case of energy use, reducing or increasing energy use by 20%, replacing conventional energy with green energy from wind power, or examining the impact of the storage time of the thigh heads in the freezer before processing on the environmental impact, considering 0 or 6 weeks of storage instead of the original 3 weeks; (ii) in the case of chemical use, a ±20% variation in the amount of chemical substances, or replacing them with chemical solutions that have a lower or higher environmental impact; (iii) replacing the quantity of disposable materials by ±20% or optimizing the packaging, in which bulk packaging was examined (packaging 5 g or 10 g of product in one unit instead of 1 g in the reference—these packaging formats are mainly used in orthopedics).
3. Results
This section presents the results of the process-based life cycle assessments performed for the two systems analyzed in the methodological case study. The process results in 500 g of bone graft material, which can be bone granulates or bone blocks depending on the processing process.
Supplementary Material S2 contains the results of the uncertainty and sensitivity analysis.
Table 2 contains the results of the LCIA analysis in the ReCiPe v1.03 midpoint (H) impact categories.
Table 2.
Life cycle impact results. The total burden on environment caused by production of bone substitutes: on demand calculation type.
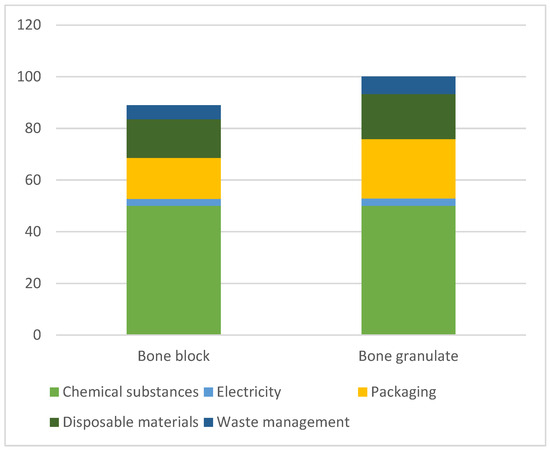
Bar charts showing the contribution of major contributors to the total carbon footprint values of cortico-cancellous or cancellous bone blocks and none granulates (expressed in kg CO2-eq) are presented in Figure 2 side-by-side. The figure shows data related to the production process. The clinical function and use of bone blocks and granulates are not the same, so the comparison is only based on weight.
Figure 2.
Component-wise comparison of greenhouse gas (GHG) emissions for the two products (kg CO2-eq).
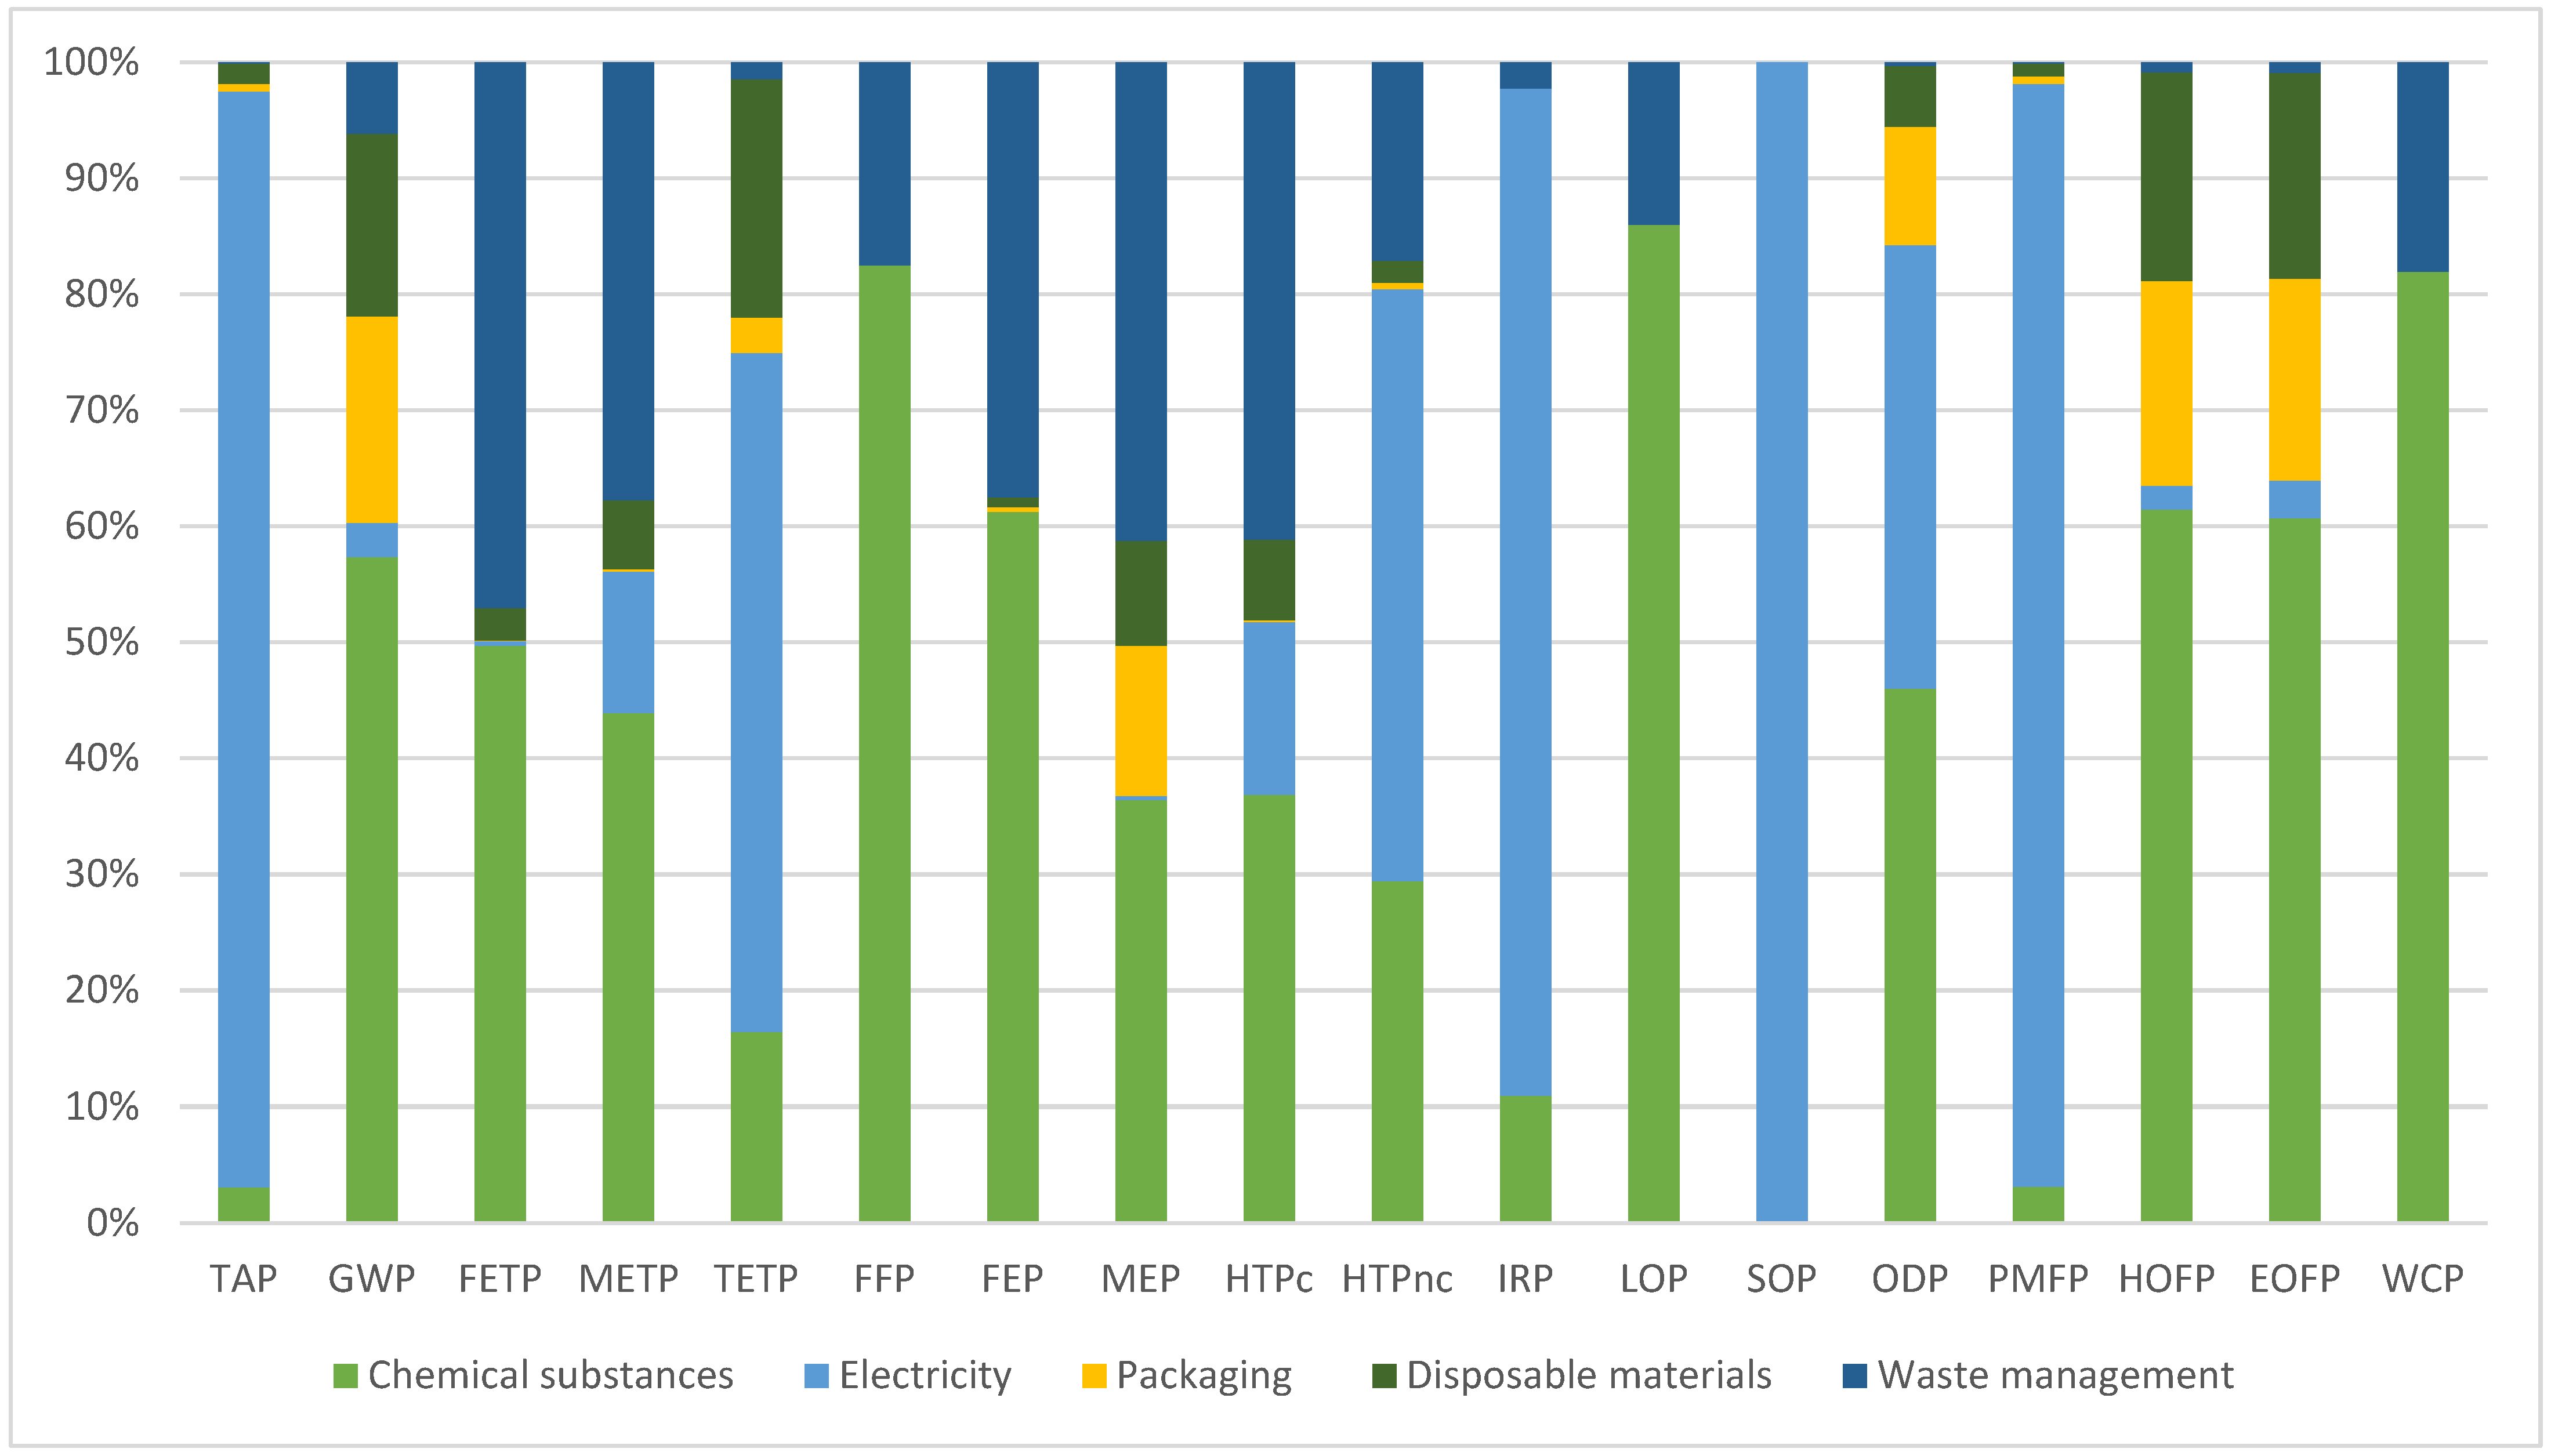
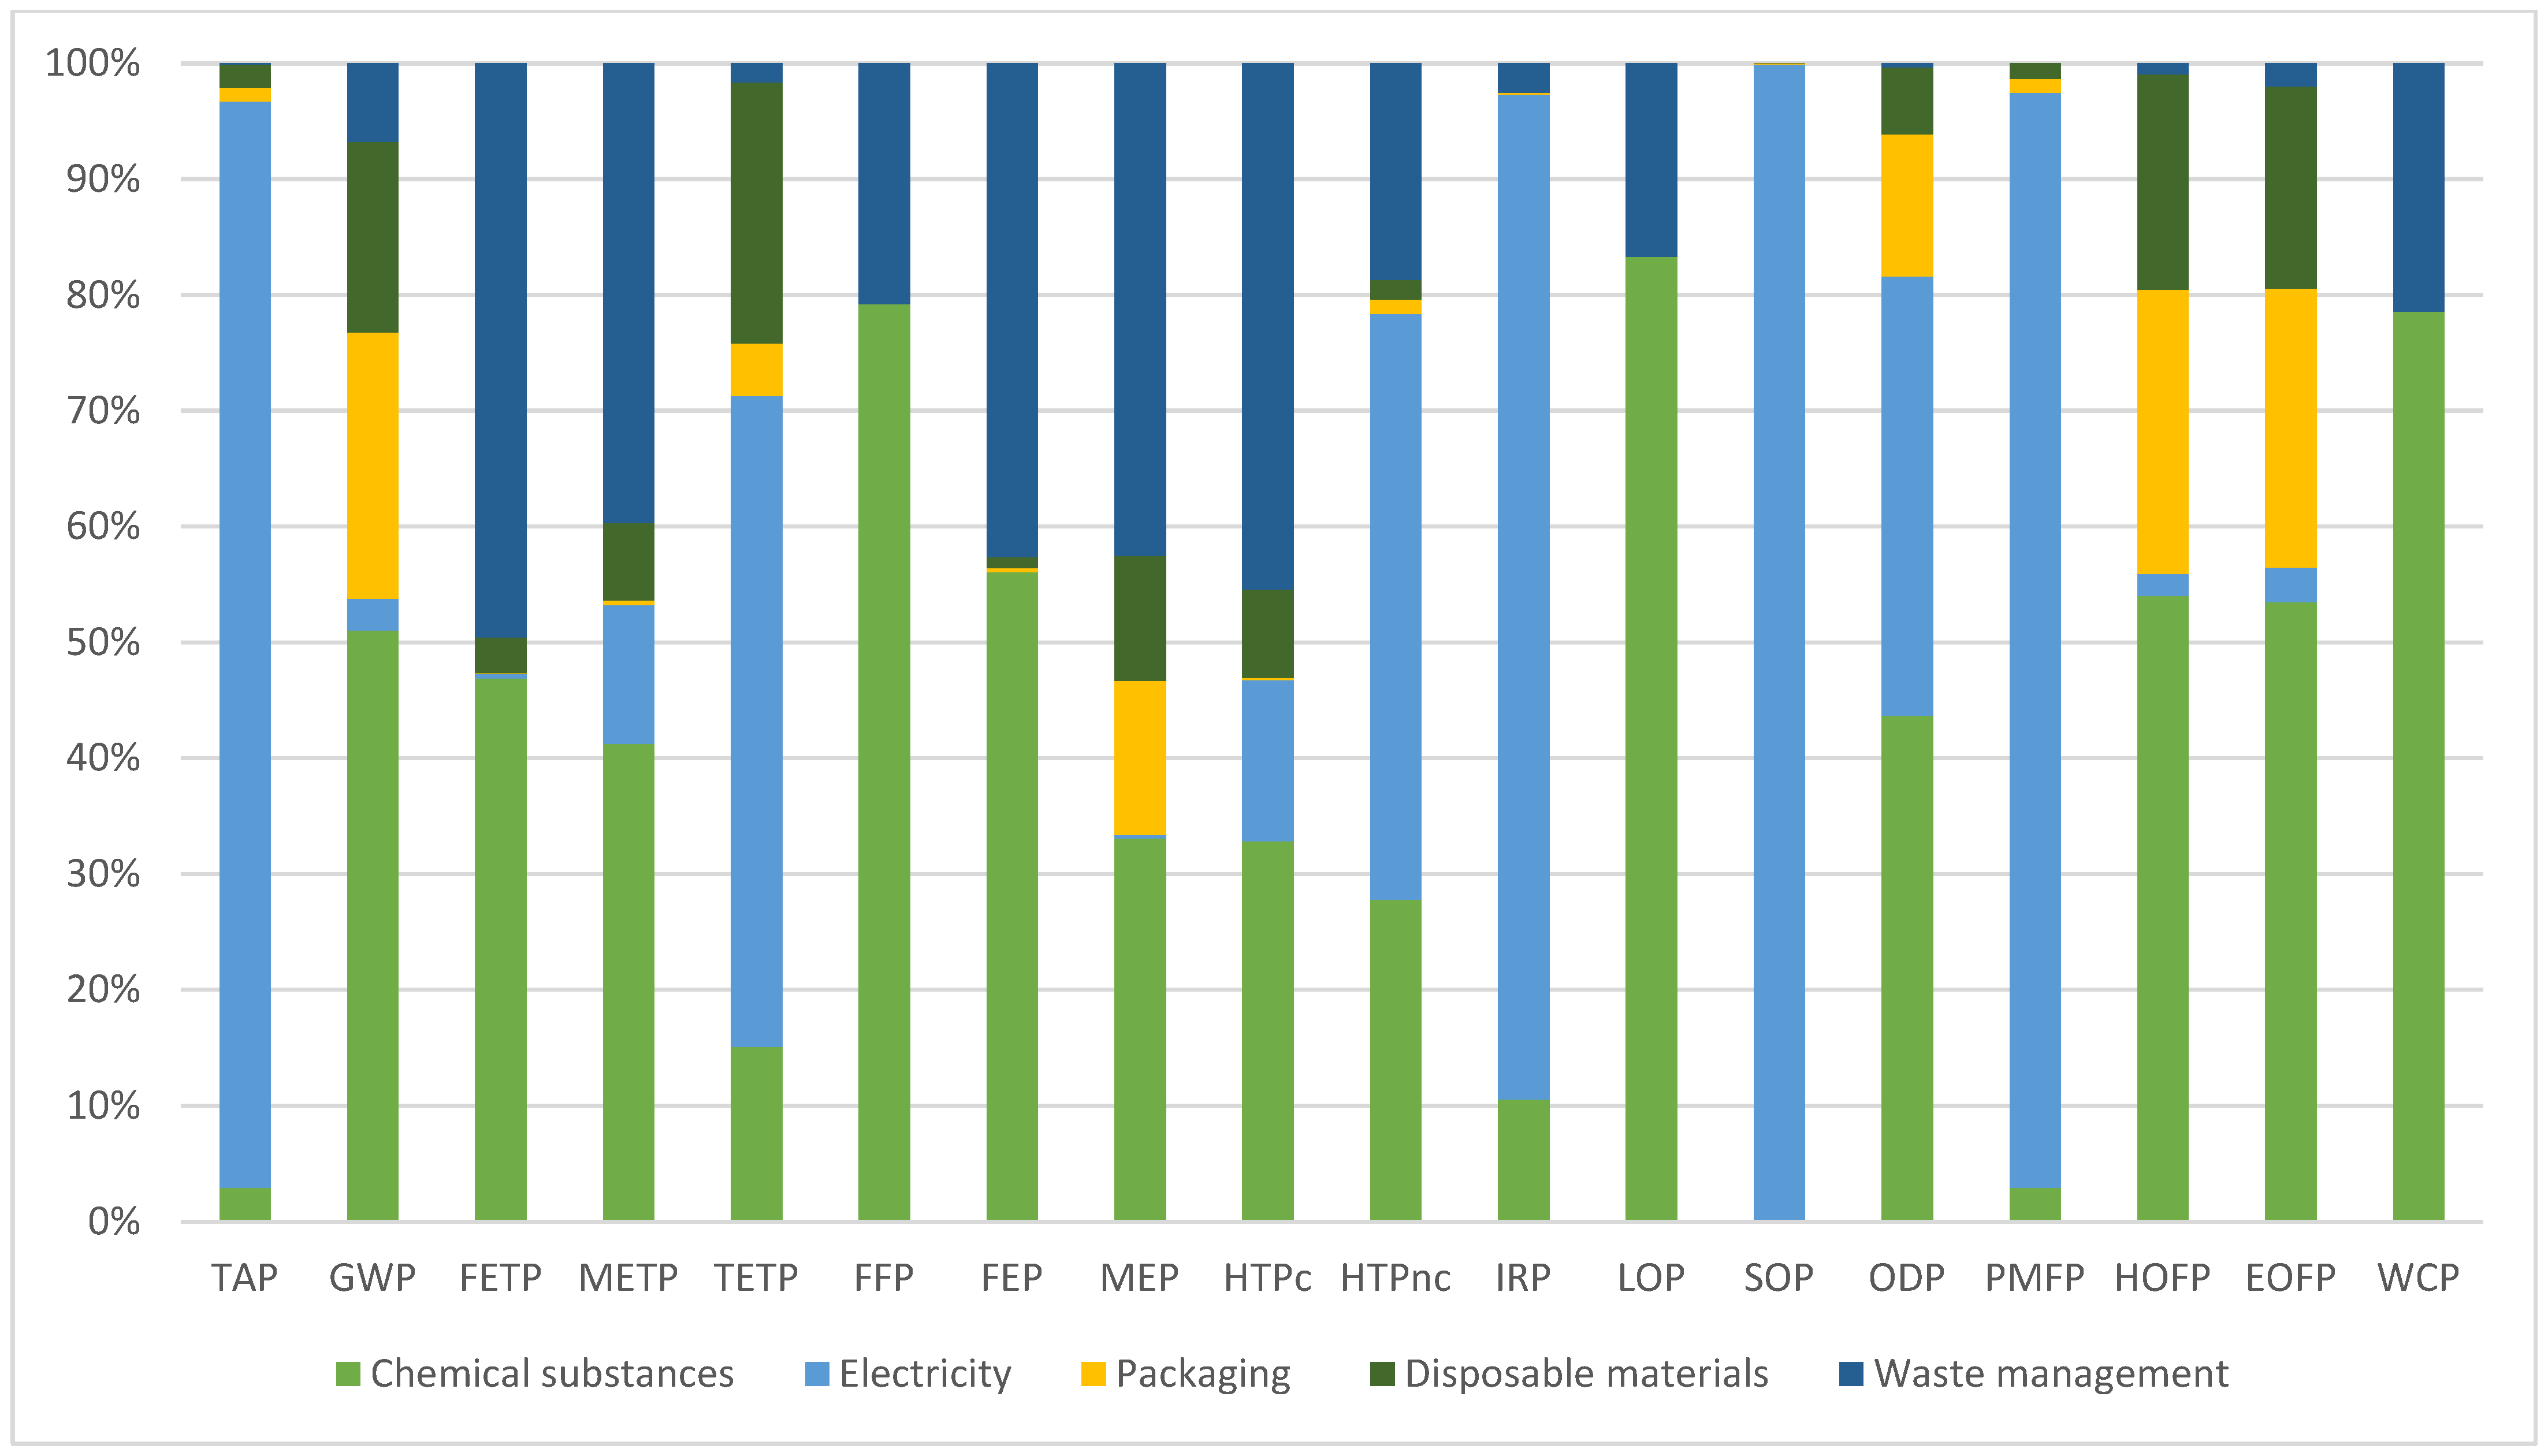
Figure 3 and Figure 4 show the environmental impacts of bone granulates and bone block in the ReCiPe v1.03 2016 midpoint (H) impact categories broken down into contributing elements. In the case of single-use devices, the impact includes the transport of materials from the country of origin to the area of use.
Figure 3.
Breakdown of contribution to environmental impacts in 18 impact categories—relative role of individual factors (chemical substances, electricity, packaging of the final product, disposable materials and waste management) of bone granulates.
Figure 4.
Breakdown of contribution to environmental impacts in 18 impact categories—relative role of individual factors (chemical substances, electricity, packaging of the final product, disposable materials and waste management) of bone blocks.
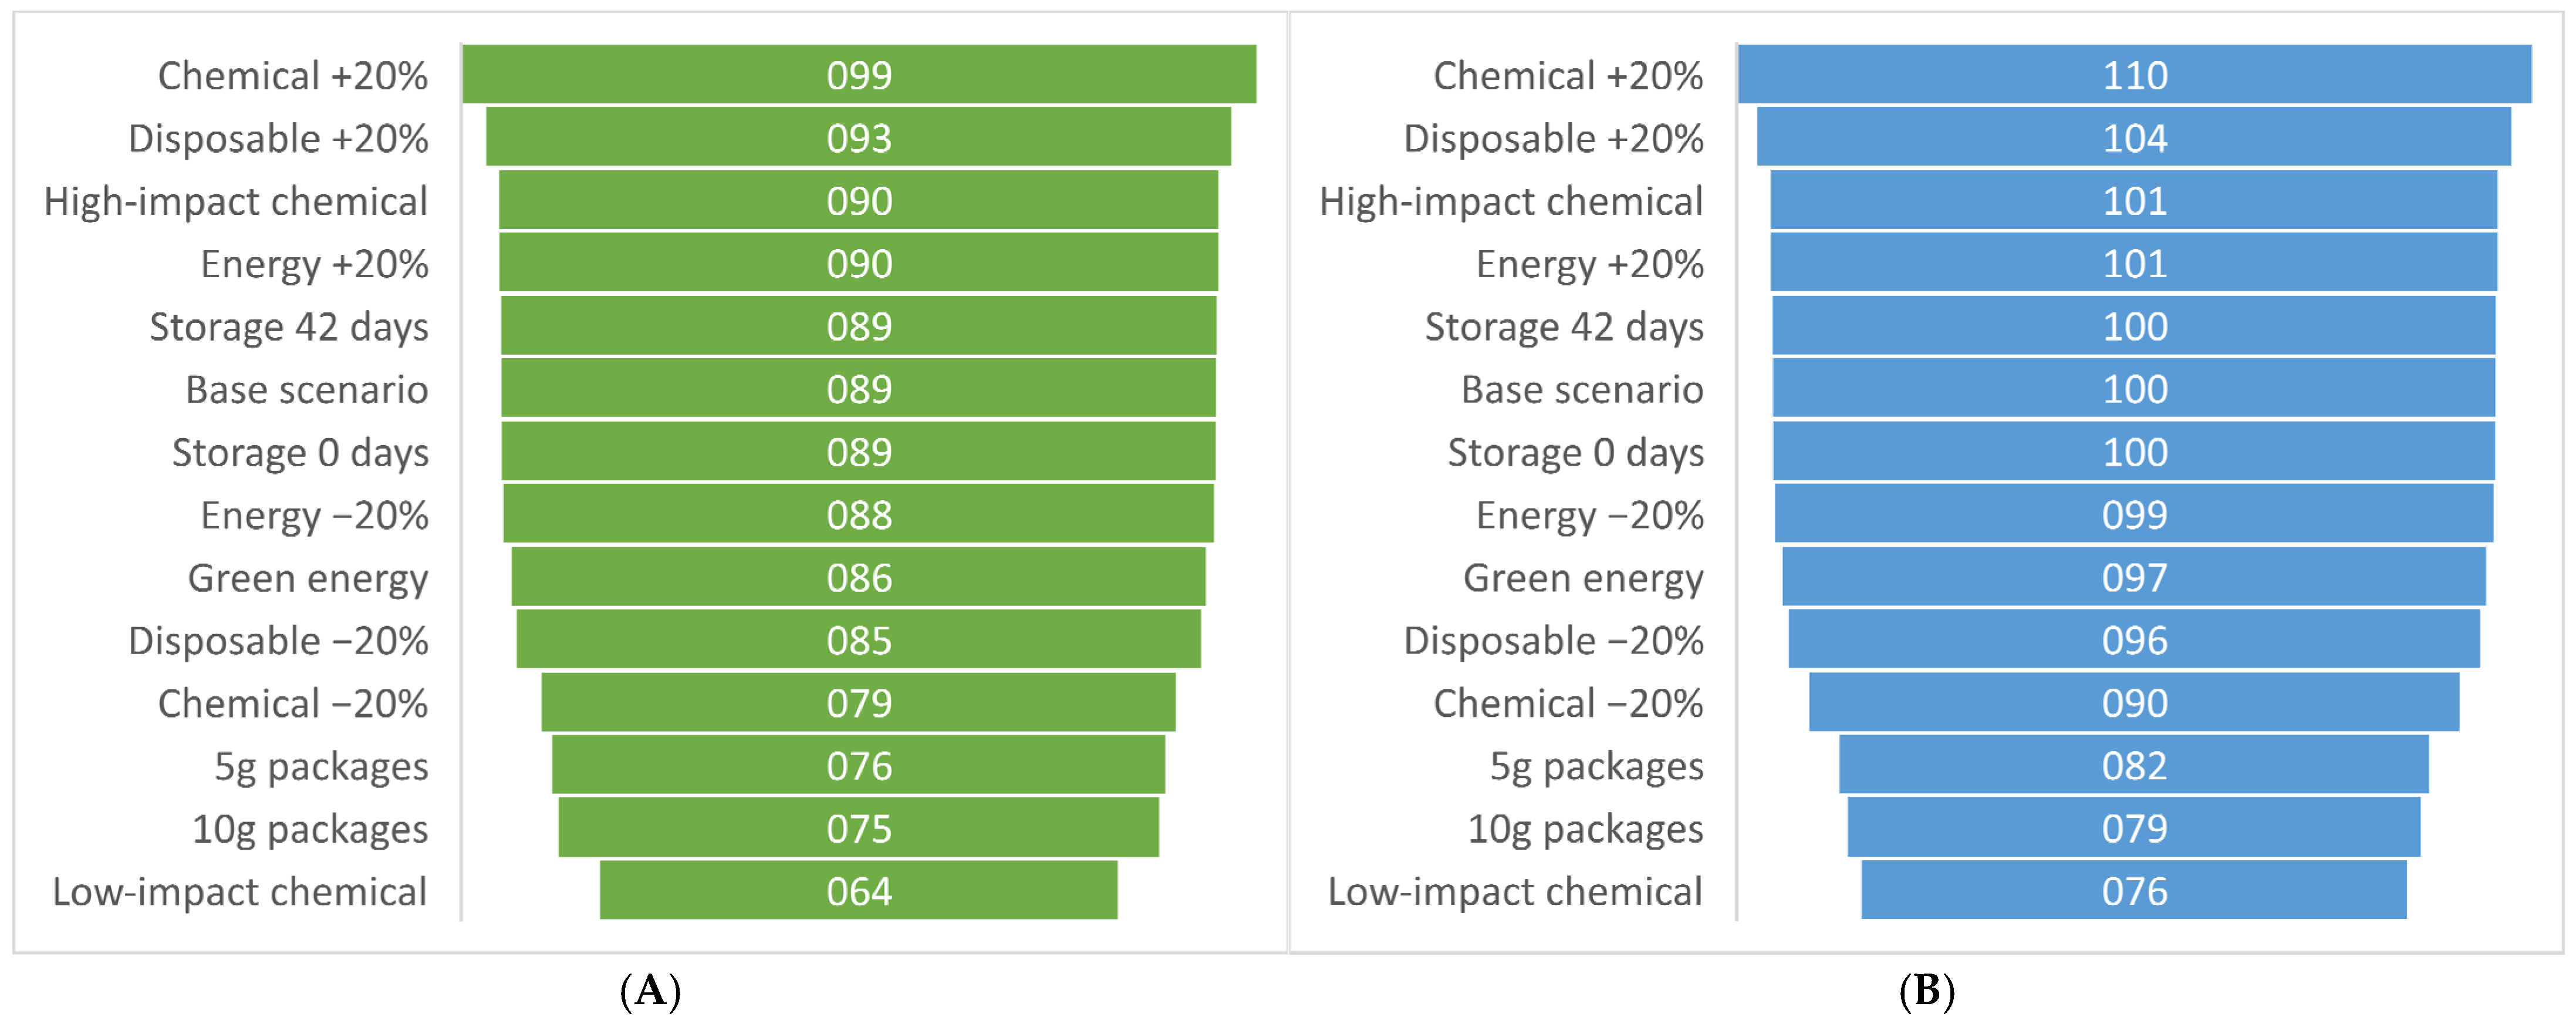
Figure 5A,B present the results of the sensitivity analysis for the climate change impact category when it comes to bone blocks(Figure 5A) and bone granulates (Figure 5B). Supplementary Material S1 provides tabular results of the additional impact categories for both bone substitute materials and scenarios where the femoral heads are processed immediately or when they are refrigerated for twice the originally estimated time before starting the manufacturing process.
Figure 5.
Results of sensitivity analysis in the climate change impact category when it comes to bone blocks (A) and bone granulates (B)—showing the base scenario and thirteen alternative scenarios. Descriptions for all alternative scenarios are presented in the figures.
The carbon footprint of incinerating 2720 g of femoral heads as medical waste based on the incineration scenario modeling would be 12.724 kg CO2-equivalent.
Table 3 contains the DALY values determined by the ReCiPe v1.03 2016 endpoint (H) method for the environmental impacts of the manufacturing processes.
Table 3.
Summary of DALY values per manufacturing process (500 g of bone substitute material).
4. Discussion
Implantation is the optimal solution for solving the functional and esthetic problems caused by tooth loss [15,23]. Bone grafting may often be necessary to perform the procedure, fill the gaps or promote osseointegration [14,17,38]. To optimize the regenerative process, it is necessary for the bone graft material to highly match the bone tissue in composition, morphology, structure, crystallinity and biological properties [39]. To achieve successful bone grafting, it is necessary to understand its biological function (osteogenesis, osteoinduction, and osteoconduction) [22].
A variety of materials and surgical techniques, such as onlay/inlay graft, guided bone regeneration, and distraction osteogenesis, exist to enable implantation in atrophied bone [20,21,23,40]. The choice of material depends on many factors: the size, extent and shape of the defect; the patient’s condition; and the availability, handling, biological properties and biomechanics of the material [22].
The ideal bone substitute material promotes osteogenesis, is osteoinductive and osteoconductive, does not induce an immune response, is easily accessible, and does not compromise the donor site [22,39]. Several types of bone substitute materials are available: autologous bone (harvested from a donor site), allografts (derived from individuals within the same species), xenografts (animal-derived, with a composition similar to human bone), or synthetic materials [21,22].
Autologous bone is considered the gold standard in implantology [10,14,16,24,41,42], due to its osteoinductive, osteoconductive and osteogenetic effects [41,42,43,44]. It has the additional advantage of being structurally stable and having a low immunological response [42]. Autologous bone can be harvested from a variety of sources [10,41,45], and the donor sites can be either endochondral (iliac crest, tibia, or ribs) or intramembranous (maxilla, mandible, or calvaria) [23,43]. An intramembranous, autologous bone is preferred because it is less resorbable [38,43,45]. In this case the disadvantages can be its limited availability, inevitable resorption and the possibility of donor site defects [24,46]. Bone harvesting is an invasive procedure, therefore preoperative screening is necessary [16]. Even so, the surgery can lead to several complications: postoperative pain [10,21,41,42], nerve injury (e.g., lateral femoral cutaneous nerve in the case of the iliac crest) [10,17,41], hematoma, seroma formation [16,17,39], gait disturbances [16,35,37], donor site deformity (especially in the case of the calvaria) [39,41], wound superinfection [17,39], donor bone fracture [16,39], soft tissue injury [39], development of a keloid scar [16,41], wound dehiscence [17], or hemorrhage [10].
An alternative can be the use of allografts, which overcome the complications caused by surgical intervention [13,17,26,46] and even allow the production of bone blocks with a predetermined shape and composition [13,17]. Allografts can be derived from living donors or cadavers [21,22,39]. They stimulate bone formation, are osteoconductive and may contain bone morphogenic proteins, which make them osteoinductive [13,19,22]. Their disadvantages include limited availability, high production costs, and religious issues regarding their acceptance [22,39]. The risk of immunorejection is low and, unlike other transplants, immunosuppressive treatment is not required [22,26,39]. The risk of spreading infections is also low, as tissue banks follow strict international standards, thus guaranteeing the safety of the bone substitutes produced [17,24].
Xenografts are often used in dentistry and can have bovine, porcine, or equine origin, or be derived from a coral exoskeleton, or eggshell [21,22]. Their structure resembles human bone, with a Ca/P ratio approaching 1.67. They are osteoconductive, but may contain bone morphogenic protein, making them osteoinductive. Their advantages include low cost and wide availability, but they also pose a risk of infection and may raise ethical and religious concerns [22].
Synthetic materials are widely used materials; one of the application areas is bone augmentation [39,47]. These can be ceramics, synthetic hydroxyapatites, bioactive glasses, polymers, and are also available in granulates, block and injectable forms [21,22,39,47]. Their composition is similar to the bone; they are biocompatible, easy to handle and osteoconductive (they release substances that contribute to bone formation); but they do not have an osteoinductive effect [22,47]. To improve their osteogenic properties, growth factors, for example, can be added to their composition [22].
Bone substitutes can be in the form of bone granulates or bone blocks [24]. The advantage of bone blocks over particulate-containing materials is that they can be cut to size and can be easily and stably fixed using osteosynthesis screws [16,21]. In addition, according to the present study, the production of cancellous and cortico-cancellous bone blocks from the femoral head has a lower environmental impact than that of bone granulates. However, it should be noted that the results are based on mass. A clinical comparison between the two types of bone substitutes would be necessary to determine how much bone substitute is needed from one or the other material under the same circumstances, and based on this, it would be possible to more accurately determine which one has a lower environmental impact.
Organ and tissue transplantations cover a wide spectrum of medical interventions, from life-saving interventions to those aimed at improving the quality of life [10]. The aim of tissue donation is to provide high-quality, safe transplants [27]. Tissue banks are responsible for the collection, testing, preparation, packaging, storage and distribution of bone grafts [14,26,28]. Tissue transplantation is a highly regulated procedure due to ethical considerations and the risk of spreading infections and malignancies. There are standards for human allografts in the European Union set out in national legislation [28].
In the case of transplants produced in the West Hungarian Regional Tissue Bank, living donors are pre-screened in accordance with EACTB principles and also undergo serological tests against HIV-1/2, HBsAg, HBcoreAg, HCV and Treponema pallidum (lues). The production process is strictly controlled and aseptic, and bone grafts also undergo ethylene oxide sterilization. The prepared bone graft materials are also subjected to microbiological tests after lyophilization but also before packaging, thus ensuring that they have not been contaminated during the processing procedure. The packaging of the produced bone substitute materials is marked with a barcode, which ensures the traceability of the grafts. Every origin and step during the production process is documented in detail and accurately. The label also contains the production and expiration dates.
Ethylene oxide sterilization has been used since the 1950s to sterilize heat- and moisture-sensitive medical devices [48,49]. The ethylene oxide sterilization of bone grafts ensures the safe use of bone grafts without destroying their composition and thus conserving their osteoinductive properties.
The femoral head is a high-quality trabecular bone that is often removed during orthopedic procedures [13]. Patients undergoing surgery for degenerative diseases can donate the removed bone for the production of allografts, thereby making medical waste useful [14]. Recycling is a process in which waste is converted into another valuable material and makes it possible to reduce the carbon footprint that would be caused by the incineration of waste [50]. The aim of the “circular economy” is to significantly reduce waste by reducing environmental damage, and to create sustainable, low-carbon technologies [10,11].
Medical waste is either landfilled or incinerated [1]. Incineration is an engineering process that destroys the organic components of waste through thermal oxidation at very high temperatures (800–1200 °C) [7,11]. Landfills pollute groundwater, while incineration releases hazardous gases [1]. Thus, waste incineration is a better method of waste management than landfills; however, it results in high carbon emissions [5]. Medical waste can be hazardous if it is not properly managed, can be harmful to health, and pollutes the environment, so an environmentally conscious approach to waste management is important [6,7,9]. The success of medical waste management is to achieve a circular economy [7]. The potential impact of waste incineration can be reduced by recycling, composting and preventing waste (avoided production) [5].
The environmental burden of the recycling process is 88,972 kg CO2Eq in the case of bone blocks and 100,033 kg CO2Eq in the case of bone granulates, compared to 12,724 kg CO2Eq for incineration. Environmental gain can be determined using the following formula: environmental gain = impact of incineration − impact of recycling. If the result is positive, recycling is the better option [51]. Although the recycling scenario shows a higher direct climate impact than incineration, it generates a functional bone graft material. However, environmental benefits can still be achieved if the environmental burden of recycling is less than the environmental burden of waste incineration and raw material production, according to the formula: net environmental impact = environmental burden of the waste treatment option—avoided burden credit of the waste treatment option [52]. The environmental impacts of the production of femoral head allografts in the context of a circular economy can only be fully assessed if LCA data for the production of conventional bone substitutes are also available. However, these are beyond the scope of this study, which focuses exclusively on the life cycle assessment of the allograft production process from medical waste and rather aims to illustrate guidelines for making bone substitute production more environmentally friendly and to highlight the importance of recycling medical waste.
The indication areas of bone blocks and particulate bone substitutes may differ. The use of bone granulates is primarily recommended for the replacement of smaller defects, as they show faster integration with the host bone tissue due to their larger surface area. In contrast, bone blocks are primarily suitable for the reconstruction of larger defects, where they provide structural support due to their mechanical stability. However, in clinical practice, the combined use of the two graft types is also common [53]. In terms of the effectiveness of bone substitute interventions, the determining factor is not primarily the amount of graft initially implanted, but the amount of bone remaining after the integration process, which is significantly influenced by the graft resorption rate. Based on the literature, bone blocks generally have a lower resorption rate than particulate grafts. However, the results of different studies are not uniform: some studies have shown a statistically significant difference between the two graft types, while others have not [54,55]. It should also be noted that statistically significant differences can also be detected between the resorption rates of bone blocks of different origins, such as grafts derived from endochondral and intramembranous bone [23,43,56]. Accordingly, clinical decision-making when choosing a bone substitution procedure is a complex process, during which several factors must be taken into account, and the environmental awareness of bone substitute materials could be a new aspect.
An important step in the production process of bone substitutes is the defatting and deantigenization of bone tissue. Its aim is to remove cellular elements and reduce antigenicity without changing the mechanical and biological properties of the bone [13]. Different processes exist for deantigenization, such as mechanical (lyophilization), chemical (oxidizing agents such as hydrogen peroxide) and enzymatic (e.g., trypsin) methods [13,14]. The use of protective equipment (surgical gown, hairnet, mask, and shoe covers) is essential during the production processes [28]. From the perspective of environmental awareness, the most significant problem is not waste management, but the use of disposable medical equipment and energy consumption [8]. The use of plastic significantly increases the amount of environmentally harmful waste [1,57]; therefore, more environmentally friendly solutions should be adopted in the field of protective equipment [57].
Within the ReCiPe v1.03 2016 midpoint (H) impact categories of the life cycle assessment of the manufacturing process applied at the West Hungarian Regional Tissue Bank, chemical substances contributed most to the environmental impacts, followed by electricity. Chemical substances contributed greatly to climate change (57.35% for bone blocks and 51.01% for bone granulates), and their greatest impact was on non-renewable fossil energy resources (82.52% for bone blocks and 79.21% for bone granulates). Electricity contributed mostly to terrestrial acidification (94.40% for bone blocks and 93.81% for bone granulates), ionizing radiation (86.79% for bone blocks and 86.75% for bone granulates), particulate matter formation (95.03% for bone blocks and 94.52% for bone granulates), and metal/mineral resource use (99.99% for bone blocks and 99.89% for bone granulates).
Based on the results of the Monte Carlo simulations, the system under study shows consistent and balanced results across several impact categories. The closeness of the mean and median values and the moderate range of values observed in most categories, including global warming potential, indicate that the applied model adequately handles input uncertainties. The methodology allows for the identification of critical impact categories while clearly separating stable results that are directly suitable for decision support from indicators with greater uncertainty. The statistical characteristics of the output distributions can be found in Supplementary Material S2.
Environmental impacts can be considered in midpoint and endpoint categories. The number of impact categories is significantly reduced in endpoint categories, which facilitates the interpretation of the results. DALY is an endpoint indicator of environmental impacts on human health in LCA analysis. Its application enables a consistent and harmonized comparison of different environmental impacts (e.g., air pollution, ozone layer depletion, climate change, and toxicity) at the level of human health [58,59]. The aggregated DALY results indicate that in the modeled processes the environmental burden on health per functional unit is dominated by particulate matter formation. The values expressed in units of time show the health burden at the population level associated with the manufactured bone substitute materials. To accurately determine the environmental benefits of recycling femoral heads within the circular economy, it would be appropriate to apply the DALY metric, as it is suitable for this purpose and may also support clinical decision-making.
To make the production of allografts more environmentally friendly, it would be necessary to optimize the production process. To achieve a reduction in energy use, energy-saving devices should be used during the production process and the use of energy from renewable energy sources should be preferred. Chemical substances should be replaced by new alternatives that successfully perform bone defatting and deantigenization and are less harmful to the environment. It is also necessary to reduce the use of single-use materials. A solution could be, for example, the reuse of surgical gowns used during the packaging of bone substitute materials when cutting and grinding the bones. In this case they would primarily protect the worker from contamination from the bones while working with the bones, not the bone substitutes from contamination. Furthermore, it would be useful to selectively collect the waste generated and apply the principles of the circular economy here as well, by recycling as much as possible. When purchasing materials, attention should also be paid to the environmental awareness of the materials.
Based on the results of the sensitivity analysis, the use of chemical substances proved to be the most decisive factor influencing the carbon footprint for both bone substitute materials. Accordingly, reducing the number of chemical components or replacing them with more environmentally friendly alternatives can result in the greatest environmental benefit. Energy consumption is not the dominant factor in the development of the carbon footprint; however, the use of renewable energy sources has a positive effect on the results, especially in those impact categories where energy consumption is the main contributor. The storage time of the femoral heads before processing resulted in only minor differences across the examined impact categories. Increasing the packaging unit size has a noticeable effect on the carbon footprint and in several other environmental impact categories; however, the context of use must be taken into account when interpreting these results: while in orthopedic applications larger packaging units can be considered justified, in dental implantology, if used in excess of the necessary amount, they can lead to material loss and potential waste. Detailed results for additional impact categories are included in Supplementary Material S2.
These results should be compared with the results of life cycle assessments for other bone substitute materials. Some studies have investigated the environmental impacts of 3D-printed, tissue-engineered bone substitutes using GaBi software [60,61,62]. The carbon footprint of 1 kg of bone tissue scaffold manufactured using 3D Digital Light Processing is 1.335 kg CO2-eq, of which 78.127% is attributable to electricity use [60]. Another study investigated the environmental impacts of a bone tissue scaffold made of polyethylene glycol diacrylate (PEGDA), dissolved in dimethyl sulfoxide (DMSO) and diphenyl (2,4,6-trimethylbenzoyl) phosphine oxide (TPO) as a photoinitiator, which resulted in 1.94731 kg CO2-equivalent. Since 3D printing is an energy-intensive process, electricity also contributed significantly; however, ethylene glycol and toluene contributed the most to the results [61]. One kilogram of a 3D gel-printed bone tissue scaffold emits 3.07 kg CO2-eq, resulting from the aggregation of emissions to air, freshwater, seawater, and industrial soil [62]. Based on the presented results, the 3D-printed engineered bone tissue scaffold appears to be an environmentally conscious alternative for bone substitute production; however, such a comparison also requires consideration of the circumstances of clinical use.
Healthcare LCA is an online database that collects the results of life cycle analyses related to healthcare interventions [63]. A search was performed in the database using the keywords bone augmentation, bone substitution, bone surgery, implantology, dental implant and bone graft, but none yielded any results.
Sustainability is a critical responsibility for the future of humanity, and all areas of healthcare therefore need to be environmentally conscious [1,10]. In implantology, there is ongoing research and development of new materials and a great emphasis is laid on [46]. The challenge for bioeconomy is to produce materials that can sustainably and economically meet the needs of a growing population. The development of new solutions based on biomaterials and biopolymers can bring benefits in the field of environmental protection [1]. Scaffolds based on natural polymers can be produced from proteins such as silk, collagen, gelatin, fibrin, soy, or polysaccharides such as cellulose, chitosan, or alginate [39]. Another solution for the production of bone tissue is to grow bone in cell cultures or, for example, from dental tissue or periodontal ligaments [25,42].
Limitations of the Study
There are a few limitations that may affect the validity of the results of the life cycle assessment. The values may vary depending on the manufacturing processes and location of the materials used. It was not necessarily possible to find conversion factors specific to Hungary in the databases, in which case global averages were used. The data in the databases are based on older data collections, and these values may have changed since then, because the manufacturing processes of more sustainable technologies have been used lately.
Another relevant limitation is the exclusion of immunogenicity testing, which may affect the comparability of the study. Further limitation is the omission of the downstream processes. When evaluating the results, it must be considered that factors omitted from the system boundaries may influence the environmental impact. Moreover, due to the limited data available in the literature, the environmental superiority of allograft production from medical waste cannot be clearly stated, therefore further studies are necessary.
5. Conclusions
Within healthcare, an environmentally conscious approach to implantology is essential for a more sustainable dental practice. Recycling the femoral heads removed during orthopedic surgeries to produce allografts, which can be used in both oral surgery and orthopedics, has the potential to contribute to this. Allografts, which can even have an osteoinductive effect, are a suitable material for bone augmentation procedures. To make allograft production more environmentally conscious, it would be necessary to optimize energy use, reduce the use of single-use materials and packaging, and find more environmentally conscious alternatives for the deantigenization of bone tissue. Future research could extend this methodological framework to additional bone augmentation materials through further case studies.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/prosthesis8020014/s1, Supplementary Material S1: Life Cycle Inventory; Supplementary Material S2: Uncertainty and sensitivity analysis.
Author Contributions
Conceptualization, S.K.V. and B.K.-M.; methodology: S.K.V. and L.C.; software: S.K.V.; validation: B.K.-M.; writing—original draft preparation: S.K.V.; writing—review and editing: B.B.B., M.S. and L.C. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The present study was approved by the Legal and Ethics Committee of Petz Aladár County University Hospital (Approval no. 9/485-1/2025 and date of approval 26 March 2025).
Informed Consent Statement
Patient consent was waived due to the aim of this study is to perform a life cycle assessment of allografts produced by processing femoral heads removed during orthopedic surgeries at the West Hungarian Regional Tissue Bank within the Petz Aladár University Teaching Hospital, Győr, Hungary. During the study, we did not come into direct contact with the patients or the bone removed during the surgery, our study consisted of processing the data of the Tissue Bank. The informed consent form sent was signed by the patients before the surgery for the purpose of bone donation. We requested permission from the Petz Aladár University Teaching Hospital to process the data of the Tissue Bank, which was signed by the hospital’s lawyer.
Data Availability Statement
Data presented are available upon request from the corresponding author.
Acknowledgments
Erasmus mobility grant for PhD students provided to S.K.V. by George Emil Palade University of Medicine, Pharmacy, Science, and Technology of Targu Mures, Romania, is highly acknowledged.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| LCA | Life Cycle Assessment |
| ISO | International Organization for Standardization |
| CO2 | carbon dioxide |
| LCI | Life Cycle Inventory |
| LCIA | Life Cycle Impact Assessment |
| HIV | Human Immunodeficiency Virus |
| AIDS | Acquired immunodeficiency syndrome |
| HBsAg | Hepatitis B surface Antigen |
| HBcoreAg | Hepatitis B core Antigen |
| HCV | Hepatitis C Virus |
| GHG | greenhouse gases |
References
- Dziuba, R.; Kucharska, M.; Madej-Kiełbik, L.; Sulak, K.; Wiśniewska-Wrona, M. Biopolymers and Biomaterials for Special Applications within the Context of the Circular Economy. Materials 2021, 14, 7704. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Abed, R.; Ashley, P.; Duane, B.; Crotty, J.; Lyne, A. An environmental impact study of inter-dental cleaning aids. J. Clin. Periodontol. 2023, 50, 2–10. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Almutairi, W.; Saget, S.; Mc Donnell, J.; Tarnowski, A.; Johnstone, M.; Duane, B. The planetary health effects of COVID-19 in dental care: A life cycle assessment approach. Br. Dent. J. 2022, 233, 309–316. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Suresh, P.; Crotty, J.; Tesanovic, S.; Alaweed, O.; Doyle, S.; Kiandee, M.; Hayes, E.; Umeh, V.; Khalilinejad, B.; Duane, B. A life cycle analysis of the environmental impact of procurement, waste and water in the dental practice. Br. Dent. J. 2024, 236, 545–551. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Borglin, L.; Pekarski, S.; Saget, S.; Duane, B. The life cycle analysis of a dental examination: Quantifying the environmental burden of an examination in a hypothetical dental practice. Community Dent. Oral Epidemiol. 2021, 49, 581–593, Erratum in Community Dent. Oral Epidemiol. 2024, 52, 613–617. https://doi.org/10.1111/cdoe.12952. PMID: 33686705. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ferawati, U.; Nuraini, N.; Fitria, A. Analysis of Medical Waste Management at UPTD Datu Beru Takengon Hospital. PROMOTOR 2025, 8, 586–591. [Google Scholar] [CrossRef] [Scilit]
- Attrah, M.; Elmanadely, A.; Akter, D.; Rene, E.R. A Review on Medical Waste Management: Treatment, Recycling, and Disposal Options. Environments 2022, 9, 146. [Google Scholar] [CrossRef] [Scilit]
- Pollice, B.; Thiel, C.L.; Baratz, M.E. Life Cycle Assessment in Orthopedics. Oper. Tech. Orthop. 2022, 32, 100998. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Kheirabadi, S.; Sheikhi, A. Recent advances and challenges in recycling and reusing biomedical materials. Curr. Opin. Green Sustain. Chem. 2022, 38, 100695. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Gallego, L.; Harvey, K.; Pevida, M.; García-Consuegra, L.; García-Suárez, O.; Meana, Á.; Alvarez-Viejo, M.; Junquera, L. From Waste to Innovation: A Circular Economy Approach for Tissue Engineering by Transforming Human Bone Waste into Novel Collagen Membranes. Biomolecules 2025, 15, 132. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Kumar, V.; Khan, V.; Gaurav, G. Environmental and Healthcare Issues of Medical Waste. Int. J. Environ. Sci. 2025, 11, 1093–1101. [Google Scholar] [CrossRef] [Scilit]
- Smith, L.; Ali, M.; Agrissais, M.; Mulligan, S.; Koh, L.; Martin, N. A comparative life cycle assessment of dental restorative materials. Dent. Mater. 2023, 39, 13–24. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Prinz, R.A.D.; da Rocha, L.R.; Eirado, T.P.; da Silva Pinto, J.; Guimarães, J.A.M.; Fogagnolo, F.; Dias, R.B. Biological parameters for quality evaluation of allografts from the Brazilian National Institute of Traumatology and Orthopedics tissue bank. Cell Tissue Bank. 2024, 25, 625–632. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ostojić, M.; Bulj, Z.; Kordić, D.; Šunjić, D.; Buntić, A.; Juka, K.; Bliznac, I.; Topić, A.; Ostojić, Z.; Rotim, K.; et al. Establishment of the Bone Tissue Bank at Mostar University Clinical Hospital. Acta Clin. Croat. 2019, 58, 571–575. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Jack, G.Z. Use of Autogenous Bone Graft from the Iliac Crest to Restore an Atrophic Maxilla with Implant-Retained Prosthesis. J. Can. Dent. Assoc. 2006, 72, 521–524. [Google Scholar]
- Freilich, M.M.; Sándor, G.K. In-office iliac crest bone harvesting for peri-implant jaw reconstruction. J. Can. Dent. Assoc. 2006, 72, 543–547. [Google Scholar] [PubMed]
- Pereira, E.; Messias, A.; Dias, R.; Judas, F.; Salvoni, A.; Guerra, F. Horizontal Resorption of Fresh-Frozen Corticocancellous Bone Blocks in the Reconstruction of the Atrophic Maxilla at 5 Months. Clin. Implant. Dent. Relat. Res. 2015, 17, e444–e458. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Sethi, A.; Kaus, T.; Cawood, J.I.; Plaha, H.; Boscoe, M.; Sochor, P. Onlay bone grafts from iliac crest: A retrospective analysis. Int. J. Oral Maxillofac. Surg. 2020, 49, 264–271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Csönge, L.; Bozsik, Á.; Tóth-Bagi, Z.; Gyuris, R.; Kónya, J. Regenerative medicine: Characterization of human bone matrix gelatin (BMG) and folded platelet-rich fibrin (F-PRF) membranes alone and in combination (sticky bone). Cell Tissue Bank. 2021, 22, 711–717. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Sheikh, Z.; Sima, C.; Glogauer, M. Bone Replacement Materials and Techniques Used for Achieving Vertical Alveolar Bone Augmentation. Materials 2015, 8, 2953–2993. [Google Scholar] [CrossRef] [Scilit] [PubMed Central]
- Kim, N.H.; Yang, B.E.; On, S.W.; Kwon, I.J.; Ahn, K.M.; Lee, J.H.; Byun, S.H. Customized three-dimensional printed ceramic bone grafts for osseous defects: A prospective randomized study. Sci. Rep. 2024, 14, 3397. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Ferraz, M.P. Bone Grafts in Dental Medicine: An Overview of Autografts, Allografts and Synthetic Materials. Materials 2023, 16, 4117. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Ma, G.; Wu, C.; Shao, M. Simultaneous implant placement with autogenous onlay bone grafts: A systematic review and meta-analysis. Int. J. Implant. Dent. 2021, 7, 61. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Lehmijoki, M.; Holming, H.; Thorén, H.; Stoor, P. Rehabilitation of the severely atrophied dentoalveolar ridge in the aesthetic region with corticocancellous grafts from the iliac crest and dental implants. Med. Oral Patol. Oral Cir. Bucal 2016, 21, e614–e620. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Matichescu, A.; Ardelean, L.C.; Rusu, L.C.; Craciun, D.; Bratu, E.A.; Babucea, M.; Leretter, M. Advanced Biomaterials and Techniques for Oral Tissue Engineering and Regeneration—A Review. Materials 2020, 13, 5303. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Dutra Roos, B.; Valdomiro Roos, M.; Camisa Júnior, A.; Moreno Ungaretti Lima, E.; Noshang Pereira, R.; Luciano Zangirolami, M.; de Machado Albuquerque, G. Prevalence of microbiological markers in bone tissue from live and cadaver donors in the musculoskeletal tissue bank of Passo Fundo. Rev. Bras. Ortop. 2014, 49, 386–390. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Braun, C.; Löwel, M.; Heuer, M.; Pruß, A.; Schulz, T. Bioburden of postmortem bone tissues with a procurement time exceeding 36 h. Cell Tissue Bank. 2025, 26, 27. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Van Rompaey, V.; Vandamme, W.; Muylle, L.; Van de Heyning, P.H. Temporal bone bank: Complying with European Union directives on human tissue and cells. Cell Tissue Bank. 2012, 13, 231–240. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ip, V.H.Y.; Sherman, J.; Eckelman, M.J. Building a sustainable future in health care: Collaboration and framework for meaningful life cycle assessment. Can. J. Anaesth. 2024, 71, 1441–1446. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wood, N. Environmental sustainability in dentistry: A call for ethical and eco-conscious practices. S. Afr. Dent. J. 2023, 78, 287–289. [Google Scholar] [CrossRef] [Scilit]
- Huijbregts, M.A.J.; Steinmann, Z.J.N.; Elshout, P.M.F.; Stam, G.; Verones, F.; Vieira, M.; Zijp, M.; Hollander, A.; van Zelm, R. ReCiPe2016: A harmonised life cycle impact assessment method at midpoint and endpoint level. Int. J. Life Cycle Assess. 2017, 22, 138–147. [Google Scholar] [CrossRef] [Scilit]
- Brett, D. Sustainable Dentistry Making a Difference; Springer: Berlin/Heidelberg, Germany, 2022. [Google Scholar] [CrossRef] [Scilit]
- Gold, M.R.; Stevenson, D.; Fryback, D.G. HALYS and QALYS and DALYS, Oh My: Similarities and differences in summary measures of population Health. Annu. Rev. Public Health 2002, 23, 115–134. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Winter, S.; McDonagh, G.; Lappin, D.; Smith, A.J. Assessing the efficacy and cost of detergents used in a primary care automated washer disinfector. Br. Dent. J. 2018, 225, 315–319. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Künzle, P.; Frank, A.C.; Paris, S. Environmental Impact of a Tooth Extraction: Life Cycle Analysis in a University Hospital Setting. Community Dent. Oral Epidemiol. 2026, 54, 30–39. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- AP42, Fifth Edition, Volume I Chapter 2.3: Solid Waste Incineration, Book. 2025. Available online: https://www.epa.gov/sites/default/files/2020-10/documents/c02s03.pdf (accessed on 2 January 2026).
- Győri Hulladékégető Kft. Available online: https://www.gyhk.hu/index.php?m=artalmatlanitas (accessed on 2 January 2026).
- Akintoye, S.O.; Giavis, P.; Stefanik, D.; Levin, L.; Mante, F.K. Comparative osteogenesis of maxilla and iliac crest human bone marrow stromal cells attached to oxidized titanium: A pilot study. Clin. Oral Implant. Res. 2008, 19, 1197–1201. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Mishchenko, O.; Yanovska, A.; Kosinov, O.; Maksymov, D.; Moskalenko, R.; Ramanavicius, A.; Pogorielov, M. Synthetic Calcium-Phosphate Materials for Bone Grafting. Polymers 2023, 15, 3822. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Naujokat, H.; Loger, K.; Gülses, A.; Flörke, C.; Acil, Y.; Wiltfang, J. Effect of enriched bone-marrow aspirates on the dimensional stability of cortico-cancellous iliac bone grafts in alveolar ridge augmentation. Int. J. Implant. Dent. 2022, 8, 34. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Wortmann, D.E.; van Minnen, B.; Delli, K.; Schortinghuis, J.; Raghoebar, G.M.; Vissink, A. Harvesting anterior iliac crest or calvarial bone grafts to augment severely resorbed edentulous jaws: A systematic review and meta-analysis of patient-reported outcomes. Int. J. Oral Maxillofac. Surg. 2023, 52, 481–494. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bhumiratana, S.; Bernhard, J.C.; Alfi, D.M.; Yeager, K.; Eton, R.E.; Bova, J.; Shah, F.; Gimble, J.M.; Lopez, M.J.; Eisig, S.B.; et al. Tissue-engineered autologous grafts for facial bone reconstruction. Sci. Transl. Med. 2016, 8, 343ra83. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Wortmann, D.E.; Klein-Nulend, J.; van Ruijven, L.J.; Schortinghuis, J.; Vissink, A.; Raghoebar, G.M. Incorporation of anterior iliac crest or calvarial bone grafts in reconstructed atrophied maxillae: A randomized clinical trial with histomorphometric and micro-CT analyses. Clin. Implant. Dent. Relat. Res. 2021, 23, 492–502. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Peeva-Petreska, M.; Veleska-Stevkovska, D.; Cucchi, A.; Perale, G.; Viktor, S. Jaw’s Bone Augmentation with New Generation of Bone Composite Substitute Materials. ECRONICON 2019, 18, 1818–1829. [Google Scholar]
- Monje, A.; Monje, F.; Galindo-Moreno, P.; Montanero-Fernandez, J.; Suarez, F.; Wang, H.L. Microstructural and densiometric analysis of extra oral bone block grafts for maxillary horizontal bone augmentation: A comparison between calvarial bone and iliac crest. Clin. Oral Implant. Res. 2014, 25, 659–664. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, Y.K.; Kim, S.G.; Byeon, J.H.; Lee, H.J.; Um, I.U.; Lim, S.C.; Kim, S.Y. Development of a novel bone grafting material using autogenous teeth. Oral Surg. Oral Med. Oral Pathol. Oral Radiol. Endodontol. 2010, 109, 496–503. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chaair, H.; Labjar, H.; Britel, O. Synthesis of β-tricalcium phosphate. Morphologie 2017, 101, 120–124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Patiño-Marín, N.; Villa García, L.D.; Aguirre López, E.C.; Medina-Solís, C.E.; Martínez Zumarán, A.; Martínez Rider, R.; Márquez Preciado, R.; Rosales García, P.; Salas Orozco, M.F. Sterilization and Disinfection: Ensuring Infection Control in Dental Practices. Cureus 2025, 17, e79041. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Ionut-Daniel, G.G.; Maria-Alexandra, M.; Oana, B.; IrisMalina, M.; Ana-Emanuela, B.; Doinita, T.O.; Ionut-Catalin, B.; Carmen Elena, C. Efficiency of disinfection and sterilization in dental medicine practice. Rom. J. Med. Dent. Educ. 2023, 12, 45–50. [Google Scholar]
- Ma, Y.; Han, S. Carbon Neutral Hand Surgery: Simple Changes to Reduce Carbon Footprint. Plast. Surg. 2024, 32, 108–112. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Ekvall, T.; Gottfridsson, M.; Nellström, M.; Nilsson, J.; Rydberg, M.; Rydberg, T. Modelling incineration for more accurate comparisons to recycling in PEF and LCA. Waste Manag. 2021, 136, 153–161. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kabir, M.; Young, M.H.; Gülen, G.; Singh, S. Assessing Avoided Burden and Net Environmental Impact by Recycling and Repurposing of Retiring Wind Turbines. Environments 2025, 12, 396. [Google Scholar] [CrossRef] [Scilit]
- Huang, L.R.; Zhong, Y.J.; Zhang, X.Q.; Feng, Z.R.; Lai, Y.C.; Wu, H.K.; Mo, A.C. Comparative evaluation of allograft particulate bone and cortical bone blocks combined with xenograft bone for labial bone defects in the aesthetic zone: A prospective cohort study. BMC Oral Health 2025, 25, 137. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Pisoni, L.; Lucchi, A.; Persia, M.; Marchi, O.; Ordesi, P.; Siervo, S. Sinus lift: 3 years follow up comparing autogenous bone block versus autogenous particulated grafts. J. Dent. Sci. 2016, 11, 231–237. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Dasmah, A.; Thor, A.; Ekestubbe, A.; Sennerby, L.; Rasmusson, L. Particulate vs. block bone grafts: Three-dimensional changes in graft volume after reconstruction of the atrophic maxilla, a 2-year radiographic follow-up. J. Cranio-Maxillofac. Surg. 2012, 40, 654–659. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Koo, H.; Hwang, J.; Choi, B.J.; Lee, J.W.; Ohe, J.Y.; Jung, J. Comparison of vertical bone resorption following various types of autologous block bone grafts. Maxillofac. Plast. Reconstr. Surg. 2023, 45, 38. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Snigdha Hiloidhari, M.; Bandyopadhyay, S. Environmental footprints of disposable and reusable personal protective equipment—A product life cycle approach for body coveralls. J. Clean. Prod. 2023, 394, 136166. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Kobayashi, Y.; Peters, G.M.; Ashbolt, N.J.; Shiels, S.; Khan, S.J. Assessing burden of disease as disability adjusted life years in life cycle assessment. Sci. Total Environ. 2015, 530–531, 120–128. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- De Schryver, A.M.; Brakkee, K.W.; Goedkoop, M.J.; Huijbregts, M.A. Characterization factors for global warming in life cycle assessment based on damages to humans and ecosystems. Environ. Sci. Technol. 2009, 43, 1689–1695. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Senusi, F.; Mahmood, S. Application of GaBi software in identifying potential environmental impacts in fabrication of 3D bone tissue engineering. In Proceedings of the ICE-SEAM 2021: Special Edition; UTeM Press: Melaka, Malaysia, 2022. [Google Scholar]
- Senusi, F.; Mahmood, S. Environmental Impact for 3D Bone Tissue Engineering Scaffolds Life Cycle: An Assessment. Biointerface Res. Appl. Chem. 2021, 12, 6504–6515. [Google Scholar] [CrossRef] [Scilit]
- Tajurahim, N.; Mahmood, S.; Saman, M.; Ngadiman, N. Life Cycle Assessment of 3D-Printed Bone Tissue Engineering Scaffolds. Research Square 2021, preprint. [Google Scholar] [CrossRef] [Scilit]
- HealthcareLCA. Available online: https://healthcarelca.com (accessed on 14 January 2026).

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.