


Abstract
Background: Among the complications caused directly or indirectly by the Human Immunodeficiency Virus (HIV) are alterations in the auditory system. Children who are HIV-exposed but uninfected (HEU) appear to have a higher risk of hearing loss (HL) compared to their unexposed peers, but a lower risk than those infected with HIV. However, the literature remains inconclusive regarding this association. This study aims to evaluate the hearing function of HEU infants during the first months of life and to correlate these findings with maternal, gestational, and neonatal variables. Methods: This prospective cohort study included all HIV-exposed infants born in a quaternary hospital in southern Brazil between 2021 and 2023. Maternal, gestational, and neonatal data were collected, as well as the results of neonatal auditory screening. At approximately 6 months of age, otolaryngological and audiological assessments were performed, including wideband tympanometry and electrophysiological evaluation using Auditory Brainstem Response with frequency-specific stimuli. The prevalence of hearing loss refers to the number of infants affected. Results: Thirty-eight infants, with a mean age of 8 months (±3.3), completed the study. Of these, 1 (2.6%) presented with bilateral sensorineural HL, and 13 (34.2%) presented with conductive HL, with 6 cases being unilateral and 7 bilateral. No associations were found between hearing loss and maternal, gestational, or neonatal variables, except for maternal CD4 count, where higher CD4 cell counts were associated with an increased risk of conductive HL. Conclusion: The findings provide relevant data on auditory alterations in HEU infants, demonstrating a high prevalence of conductive HL. These results highlight the importance of monitoring the hearing of these children during the first years of life.
1. Introduction
Human Immunodeficiency Virus (HIV) represents a serious global public health issue [1]. Once inside the body, HIV affects the immune system, making the individual susceptible to opportunistic diseases. Due to the progressive impairment of the immune system, HIV infection constitutes a chronic health condition with social and economic impacts [2]. Over the past few decades, effective intervention strategies, such as global access to antiretroviral therapy (ART), safe childbirth and breastfeeding practices, and post-exposure prophylaxis administered to newborn (NBs), have successfully reduced HIV transmission from mother to fetus and newborn [3]. As a result, there has been a significant reduction in the rates of children infected through vertical transmission (VT), despite intrauterine exposure to the virus [1,4]. In Brazil, the HIV detection rate among pregnant women in 2022 was 3.1 per 1000 live births (LBs), with the Southern region accounting for 28.7% of all cases in the country. Rio Grande do Sul has the second highest detection rate of HIV in pregnancy (12% of all cases nationwide), with a rate of 7.9 cases per 1000 LBs. The city of Porto Alegre, the capital of Rio Grande do Sul, exhibits the highest detection rate among Brazilian capitals, at 17 per 1000 LBs, almost six times the national rate [5]. Children born to HIV-positive mothers but without HIV infection through VT are considered HIV-exposed but uninfected (HEU). According to data from the Joint United Nations Program on HIV/AIDS (UNAIDS), the cumulative global population of HEU in 2022 was estimated at approximately 16 million [6].
For a long time, researchers have sought to understand the impacts of HIV on the lives of infected children. Currently, with the growing population of HEU, efforts have focused on understanding how intrauterine exposure to the virus, maternal antiretroviral therapy (ART), and an immunologically adverse intrauterine environment may affect these children during the first months and years of life [4,7]. Recent studies suggest that intrauterine exposure to HIV can have negative repercussions throughout development into adulthood. Compared to unexposed children, HEU have a higher risk of morbidity and mortality, as well as impairments in growth and neurodevelopment, affecting motor, language, cognition, and behavior areas [8,9,10,11,12,13].
Among the numerous complications caused, either directly or indirectly, by HIV, alterations in the auditory system stand out. According to several studies, there appears to be an association between auditory abnormalities and HIV infection in the pediatric population, with hearing loss (HL) rates ranging from 24 to 39%, primarily conductive HL [9,14]. Most of these patients present with middle ear pathologies, such as otalgia, tympanic membrane perforations and otorrhea, with otitis media being the most common finding [15]. However, regarding HL in HEU children, the literature remains controversial. These children appear to have a higher risk of HL compared to their unexposed peers, but a lower risk than those infected with HIV [16]. It remains unclear how exposure to HIV and ART may impact the auditory system of these children [17].
Early diagnosis of HL in childhood is highly desirable, as its occurrence during the first years of life may lead to significant limitations in speech and language acquisition. Long-lasting conductive HL may have negative impacts on child development [18]. Moreover, without appropriate auditory rehabilitation, HL may result in adverse effects on psychomotor, cognitive, and educational development [9,19].
Despite this, there is no consensus regarding the need to monitor these children. The Joint Committee on Infant Hearing (JCIH) does not list HIV as an Indicator of Risk for Hearing Loss (IRHL) [20]. In Brazil, however, the Multiprofessional Committee on Auditory Health (COMUSA) includes HIV exposure in the list of RIHL and recommends monitoring auditory function until the third year of life [21]. Nevertheless, this regular follow-up is not implemented in the vast majority of health services in Brazil, despite public health policies on auditory health and existing national recommendations, thereby justifying initiatives that contribute to a better understanding of the audiological findings in this population. This study aims to evaluate the hearing function of HEU infants during the first months of life and to correlate these findings with maternal, gestational, and neonatal variables.
2. Materials and Methods
This was a prospective study, conducted at a public, university-based quaternary hospital in southern Brazil, which is a reference center for prenatal and neonatal care for HIV-positive pregnancies and HIV-exposed newborns (NBs). The sample was recruited based on convenience, including all live births (LBs) from HIV-positive mothers at the institution between May 2021 and March 2023, who continued follow-up after discharge at the institution’s Pediatric Infectious Disease Outpatient Clinic during the first year of life. Management of these newborns and their follow-up in the outpatient clinic were conducted according to the institution’s protocol.
Newborns with coexisting congenital infections (rubella, toxoplasmosis, cytomegalovirus [CMV], and syphilis), major congenital anomalies, or genetic syndromes that could result in hearing impairment were excluded. Preterm NBs with a gestational age (GA) of less than 34 weeks, patients who presented with perinatal asphyxia, hyperbilirubinemia at levels requiring exchange transfusion, and those who received ototoxic medications during the neonatal period (furosemide, vancomycin, or aminoglycosides) or required admission to the Intensive Care Unit for 5 days or longer were also excluded. Our institution has a quaternary Neonatal Intensive Care Unit with a genetic service that is a reference for the entire country, providing staff, imaging and laboratory exams capable of diagnosing and managing most genetic syndromes and congenital anomalies.
After birth, eligible NBs were identified, and their parents were invited to participate in the study. A urine sample from each newborn was collected for polymerase chain reaction (PCR) testing for cytomegalovirus (CMV) infection to avoid misattributing any HL due to CMV to HIV.
Maternal and gestational data related to HIV infection and treatment were collected through electronic medical record review. Data related to pregnancy, delivery and perinatal variables were also collected, along with information on neonatal hearing screening (NHS). According to the institution’s protocol, HIV-exposed NBs underwent a transient evoked otoacoustic emissions (TEOAE) before hospital discharge. As these newborns had no other indicators of risk for IRHL, auditory brainstem response (ABR) testing was only performed in cases where TEOAE failed.
All NBs received ART prophylaxis for 28 days, in accordance with the guidelines of the Brazilian Ministry of Health (MoH) [7,22]. After discharge, they were referred to the Pediatric Infectious Disease Outpatient Clinic of the same hospital for routine clinical and laboratory follow-up.
The risk of VT was considered “high” or “low” according to the Ministry of Health (MoH) protocol [7,22]. NBs were classified as low risk for VT when their mothers used ART regularly, with good adherence, had initiated treatment during the first half of pregnancy, and had an undetected viral load (VL) in the third trimester. All other pregnancy scenarios were classified as high risk for VT. ART prophylaxis for the NBs was given according to the VT risk [7,22].
Newborns were also classified as appropriate for gestational age (AGA), small for gestational age (SGA), or large for gestational age (LGA), according to the INTERGROWTH-21st standards [23]. According to the routine outpatient follow-up, the infants entered the second phase of the study, which was conducted at a private clinic, where they were referred for the following procedures. The audiologic tests were blind, conducted without knowledge of maternal and perinatal data:
- Otolaryngological evaluation, including a focused history related to the otolaryngological physical examination;
- Audiological evaluation, including wideband tympanometry and auditory brainstem response (ABR) using frequency-specific stimuli (FS-ABR);
- Wideband tympanometry was performed using Titan equipment from Interacoustics. Tympanometric curves with probe tones of 1000 Hz and 226 Hz were analyzed according to age-specific recommendations. For the 1000 Hz probe, curves were classified as normal or abnormal [24]. When using the 226 Hz probe, based on the values found for compliance and tympanometric gradient, the responses were classified as type A, B, or C curves [25]. Additionally, acoustic reflexes were assessed and classified as “present” or “absent” based on the automatic analysis of the equipment.
Frequency-specific auditory brainstem response (FS-ABR) was conducted using the Eclipse EP25 equipment (Interacoustics) and included assessment of auditory pathway integrity and electrophysiological threshold estimation. Tests were conducted during natural sleep, with the infant positioned on the lap of the mother or caregiver. Electrodes were placed on the forehead (Fz [frontal—zero degrees—midline] and Fpz [pre-frontal—zero degrees—midline]) and on the right (A2) and left (A1) mastoids, according to the institution’s protocols.
The integrity of the auditory pathway was assessed using a click stimulus in alternating polarity and filters set from 100 to 3000 Hz. A total of 2000 stimuli were presented at a rate of 27.1 per second, at an intensity of 80 dB nHL in monaural mode through insert earphones. The absolute latencies of waves I, III, and V were analyzed, as well as the interpeak latencies I-III, III-V, and I-V. The electrophysiological threshold estimation was performed with the NB CE-Chirp LS® stimulus and alternating polarity at frequencies of 500, 1000, 2000, and 4000 Hz via air conduction. The electrophysiological threshold was considered the lowest intensity at which wave V was present, observed in at least two recordings to ensure replicability. Thresholds of 35, 30, 30, and 25 dB HL, respectively, were considered normal.
In cases of abnormal electrophysiological thresholds via air conduction, bone conduction testing was performed using the B71 bone transducer at frequencies of 2000 and 500 Hz in an ascending manner, starting at 30 and 20 dB nHL, respectively. The electrophysiological threshold was considered the lowest value at which wave V was present.
After the evaluations were concluded, findings were classified as normal hearing (when tympanometry and air and bone conduction were normal), conductive abnormality (when tympanometry and air conduction were altered, but bone conduction was normal) or sensorineural abnormality (when there was normal tympanometry but altered air and bone conduction).
All 38 infants were classified as HIV-uninfected after three undetectable VL tests during the first year of life, along with a nonreactive chemiluminescence serological test at 12–18 months of age [7].
Data were entered into an Excel spreadsheet and subsequently analyzed using the Statistical Package for the Social Science (SPSS) version 29.0. Quantitative variables with a symmetric distribution were described using mean and standard deviation, whereas those with an asymmetric distribution were described using the median and interquartile range. Categorical variables were analyzed using absolute and relative frequencies. To evaluate the association between HL and maternal, gestational, and neonatal variables, a bivariate analysis was conducted. A significance level of 5% (p < 0.05) was adopted. The project was approved by the institution’s Research Ethics Committee (Number 2021-0130), and all mothers or legal guardians provided written informed consent.
3. Results
3.1. Sample Characterization
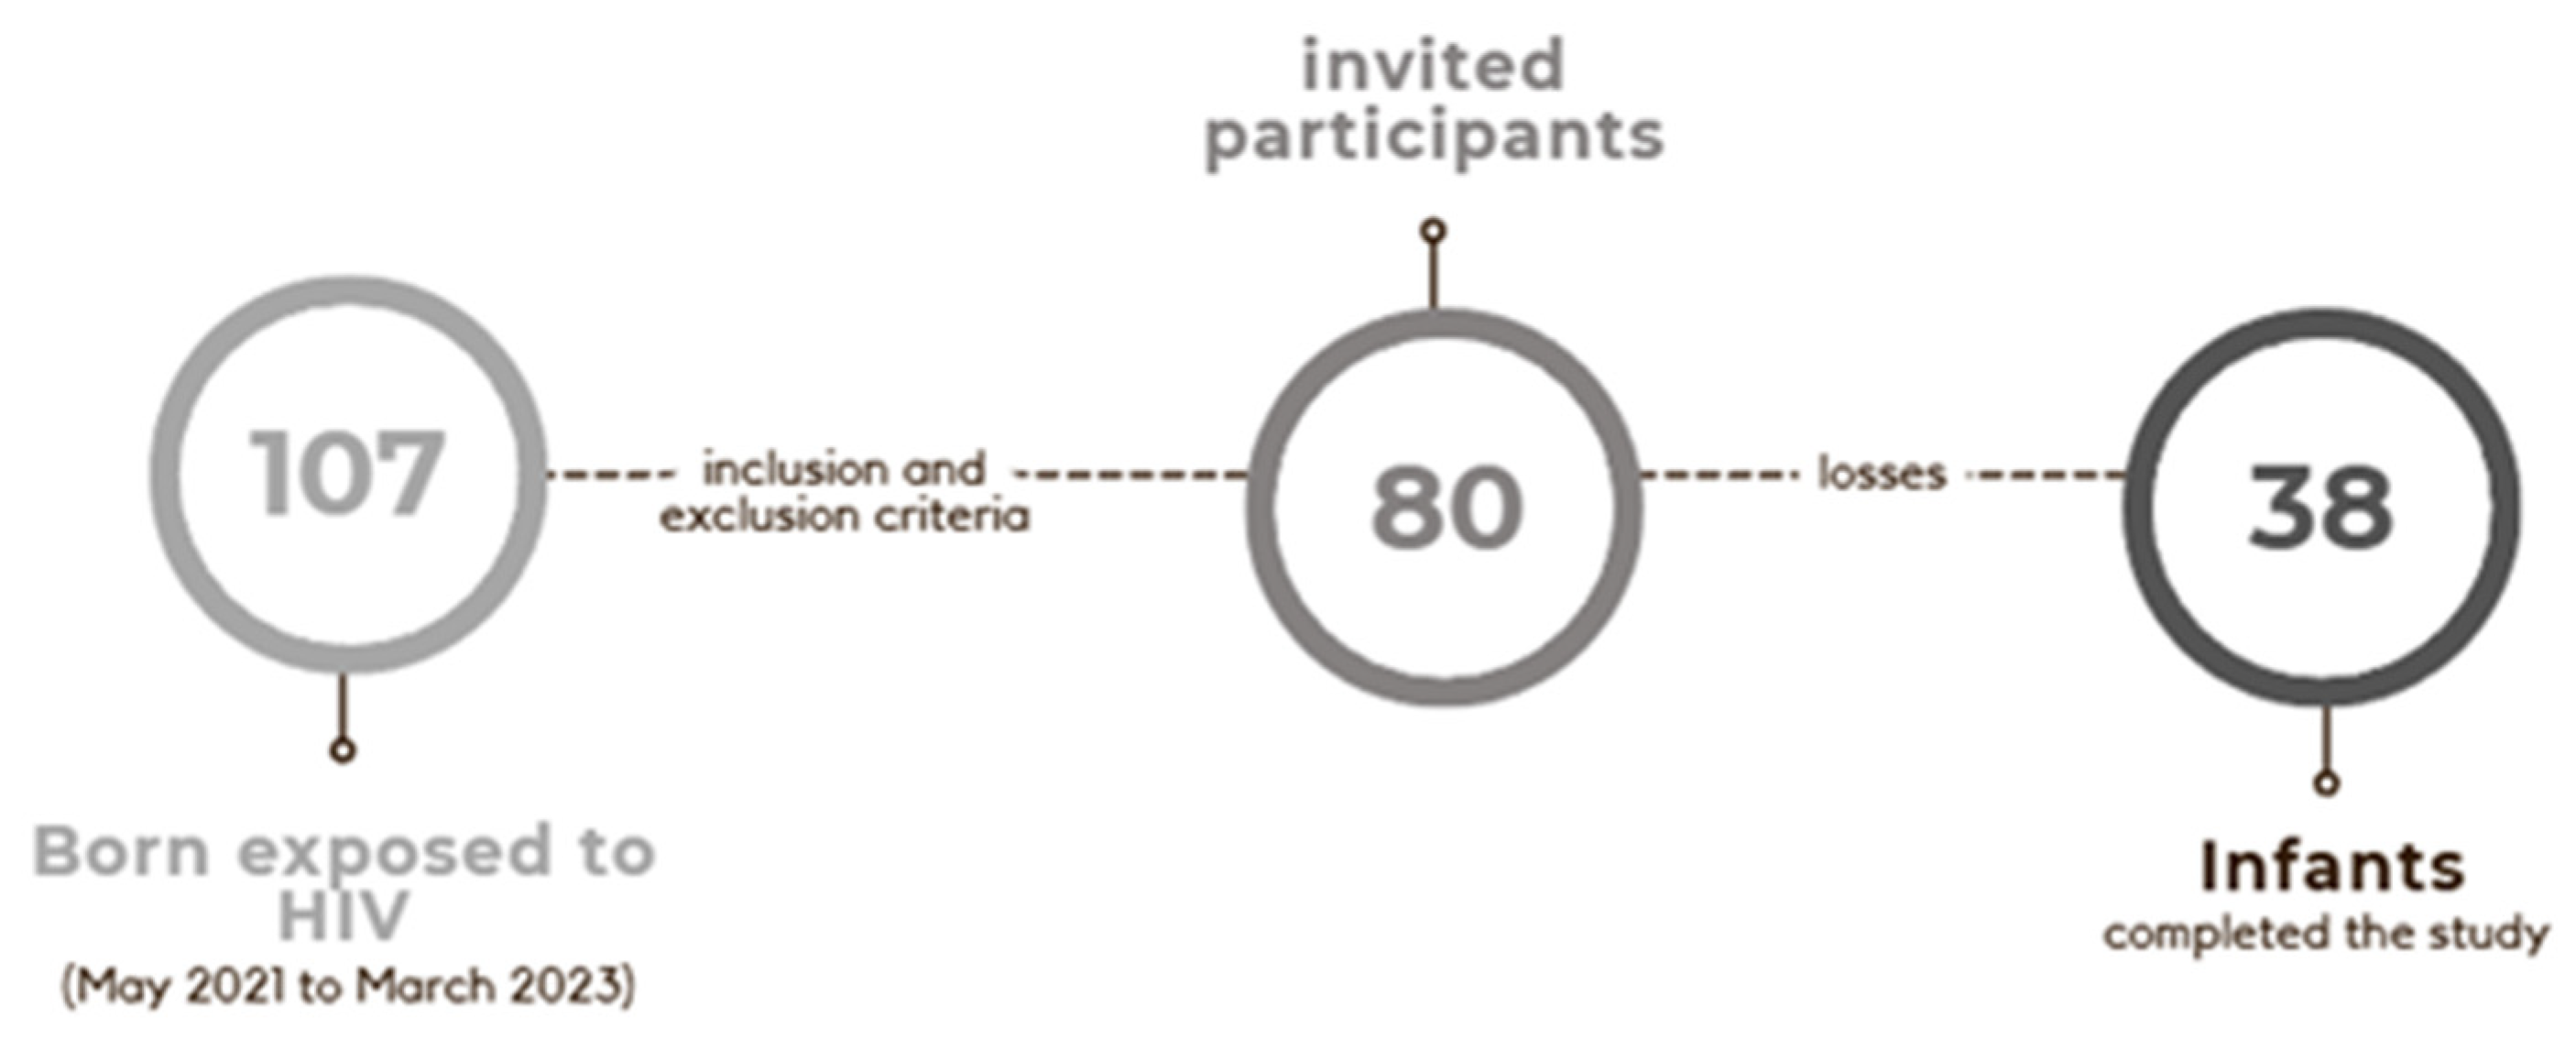
Between 1 May 2021 and 31 March 2023, a total of 5931 LBs occurred at the study hospital. Of these, 107 births were HIV-exposed, resulting in an incidence of HIV-exposed NBs of 1.8 per 1000 LBs. Among the 107 HIV-exposed NBs, 27 met the exclusion criteria, and 80 were eligible for the study and invited to participate. Of these 80 patients, 38 (47.5%) completed all planned stages of the study. All NBs initiated ART prophylaxis within the first hours of life and were not breastfed. Figure 1 presents a flowchart demonstrating the sample of the study. The complete characterization of the sample is presented in Table 1.
Figure 1.
Flowchart demonstrating the sample of the study.
Table 1.
Maternal and neonatal data of the sample (n = 38).
3.2. Neonatal Hearing Screening
All patients underwent Neonatal Hearing Screening (NHS) before hospital discharge. Of the 38 patients, 31 passed the initial screening with TEOAE and 7 were referred for retesting; 4 passed the retesting and 3 failed and were referred for automated auditory brainstem response (AABR). All 3 patients failed the AABR and were subsequently referred for comprehensive audiological evaluation in the outpatient otorhinolaryngology clinic in the same hospital.
3.3. Hearing Testing
Infants underwent the second phase of the study at a mean age of 7 ± 3.3 months. Tympanometric findings and ABR results were analyzed and categorized into evaluation of integrity (absolute and interpeak latencies) and electrophysiological thresholds. Table 2 presents the values of absolute latencies and interpeak latencies along with the tympanometric findings.
Table 2.
Findings of tympanometric curves and values of absolute latencies of waves I, III, and V and interpeak latencies I–III, I–V, and III–V (n = 38).
The absolute values of waves I, III, and V and interpeak intervals were analyzed according to age-specific normative values defined by the equipment and classified as “normal” or “delayed latency”. In 23 infants (60.5%), the values were considered normal. Block delay was observed in 13 infants (34.2%), and the delay of waves III and V and/or interpeak latencies I–III and I–V was noted in 2 infants (5.3%). Electrophysiological thresholds were within normal limits at all frequencies assessed in 24 infants (63.1%). In 14 infants (36.8%), there was an abnormality in the electrophysiological threshold at least at one frequency, with 13 having deviant air conduction (AC) and normal bone conduction (BC), and 1 patient having deviant values for both AC and BC.
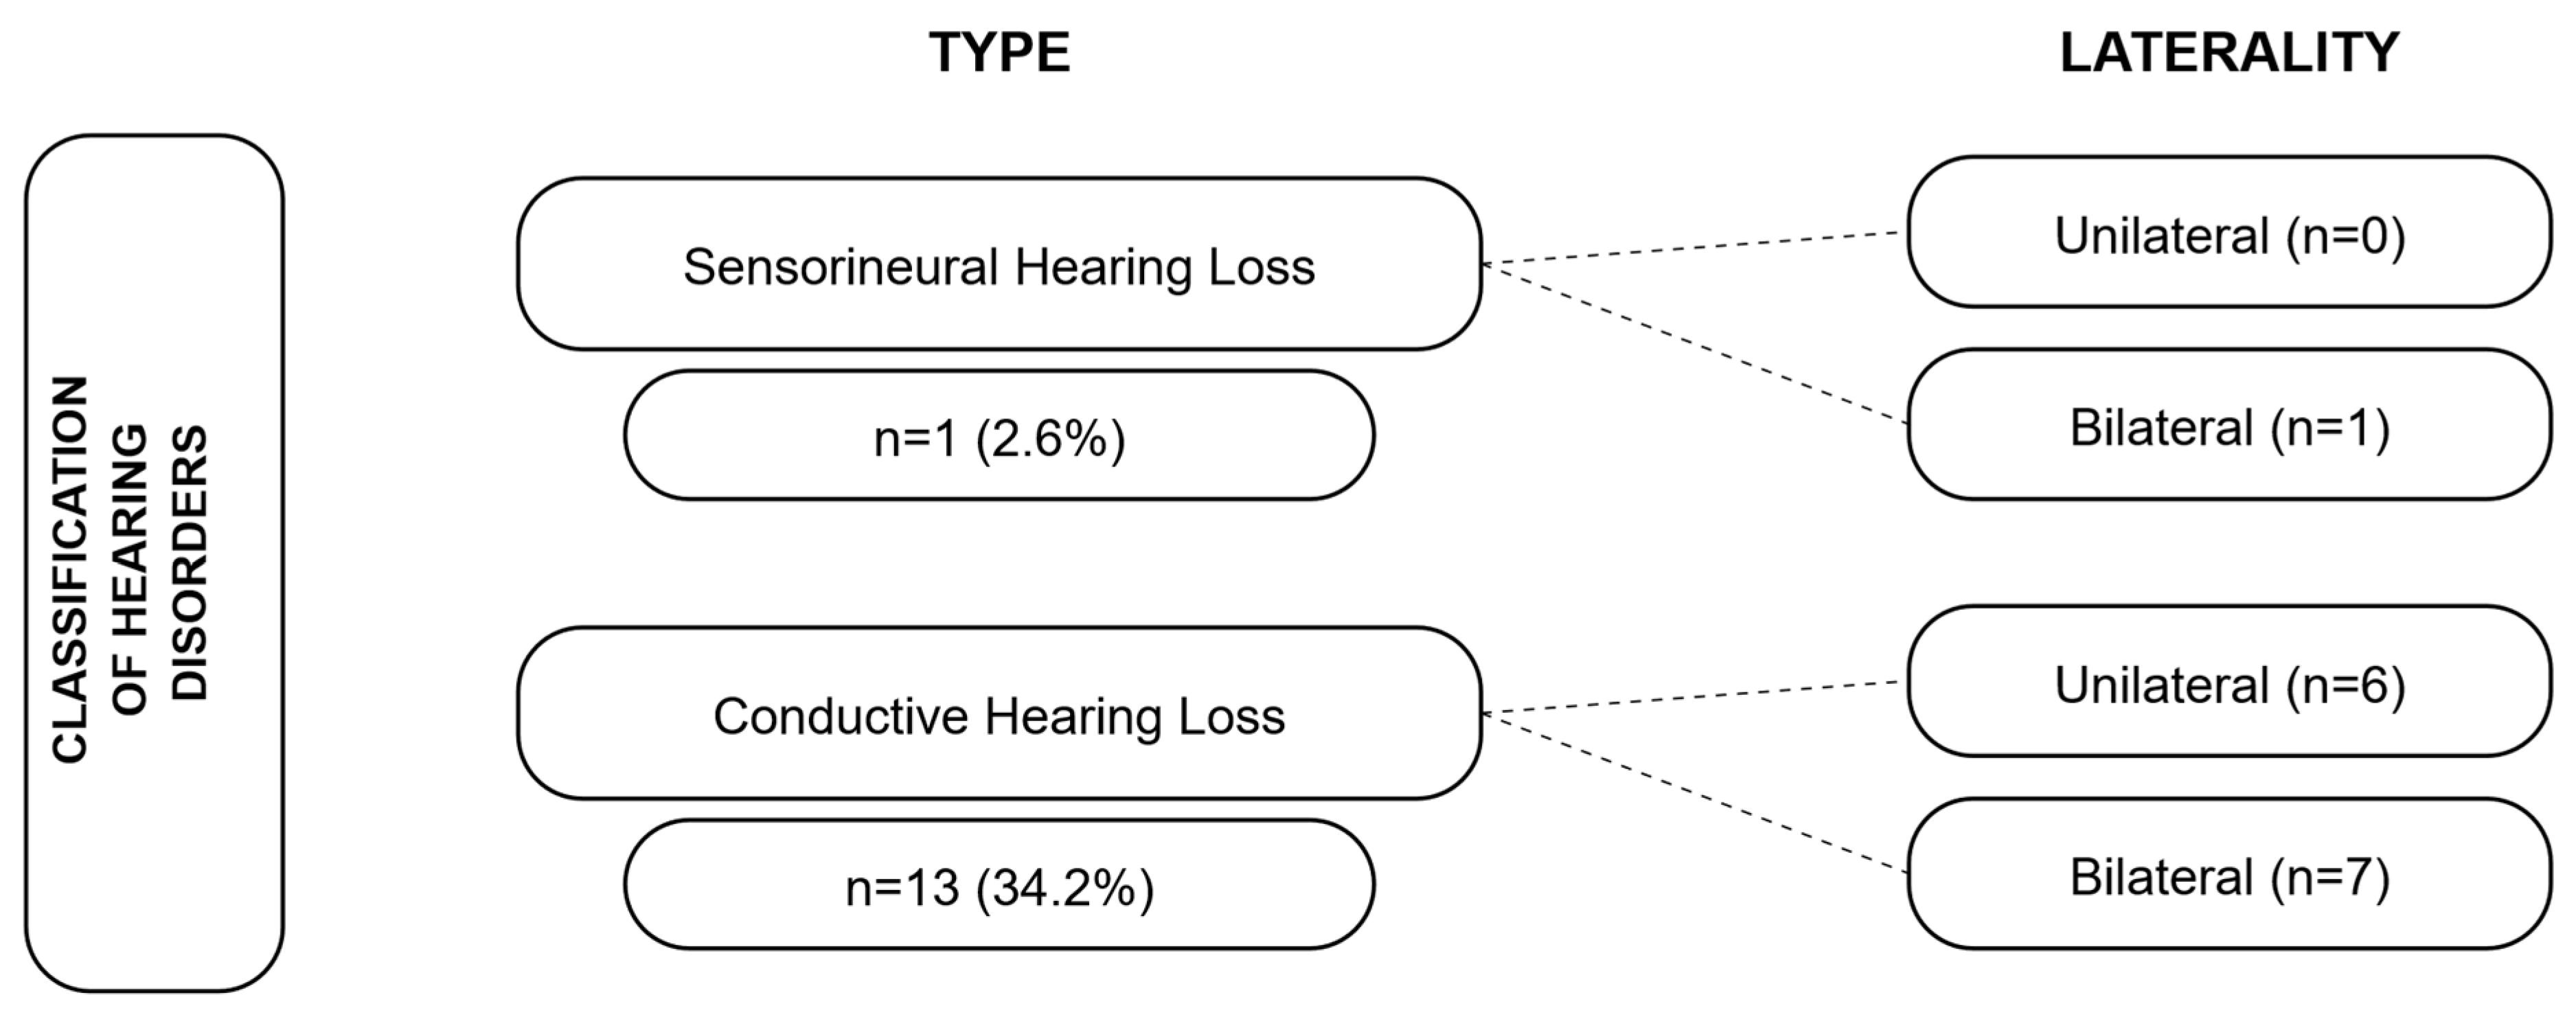
Among the 24 infants with normal electrophysiological thresholds, 2 (5.3%) showed delayed latencies of waves III and V and/or inter-peak latencies I–III and I–V. For the 14 infants with abnormal thresholds, the findings were classified according to the type of alteration as follows: “conductive HL” (when tympanometry and AC were abnormal, with normal BC) and “sensorineural HL” (when tympanometry was normal, but both AC and BC were abnormal). These results are shown in Figure 2.
Figure 2.
Classification of alterations according to auditory evaluation.
All patients who attended the follow-up were evaluated by an otolaryngologist. All infants with normal audiological examinations, as well as the only infant with sensorineural HL, had normal otoscopy findings. Infants with conductive HL presented with otoscopic abnormalities of the middle ear, such as otitis media with effusion. There were no discordant test results regarding tympanometry and ABR.
3.4. Association Between Hearing Loss and Maternal Variables
Table 3 presents the analysis of the association between HL and maternal factors (timing of maternal HIV diagnosis), gestational variables (regular ART use, VL quantification, CD4 count, and mode of delivery), and neonatal factors (weight adequacy for GA and VT risk). For analysis purposes, the only infant who presented with sensorineural HL was excluded, as it was not possible to test for CMV infection in this patient, making it impossible to determine whether HL was caused by HIV exposure or CMV infection. One pregnant woman was unaware of her HIV diagnosis. Therefore, the association analyses included 37 infants, of whom 24 had normal examinations and 13 had conductive HL, except for the “HIV diagnosis” variable, which included 36 infants.
Table 3.
Association between hearing loss (HL) and maternal, gestational, and neonatal variables.
A significant association was found between HL and maternal CD4 cell count, with higher maternal CD4 cell counts being associated with an increased risk of conductive HL. No other associations were statistically significant. However, maternal viral load and ART use during pregnancy had borderline significance.
3.5. Status of HIV Infection
All evaluated infants were confirmed as HIV-uninfected through three undetectable VL tests during the first year of life, as well as a negative anti-HIV serological test performed after 12 months of age, in accordance with MoH guidelines for excluding infection in HIV-exposed infants.
3.6. CMV Data
Of the 38 infants who completed the study, 13 (34.2%) provided a urine sample for CMV PCR testing. All the results were negative for CMV. The other 25 infants who did not undergo CMV testing were discharged early from the hospital, without sufficient time to collect the urine sample.
3.7. Post Hoc Analysis
A post hoc analysis was conducted to determine the power of the study after the losses to follow-up. Considering our 25 patients with maternal CD4 above 500 copies/mL and 8 patients with maternal CD4 below 500 copies/mL, this study has a calculated power of 84.1% to detect a difference of 52% in the prevalence of hearing loss, with α = 0.05.
4. Discussion
This study found conductive HL in 34.2% of HIV HEU infants, as well as 1 infant (2.6%) with bilateral sensorineural HL, despite the favorable prognostic characteristics of the sample (full-term births, appropriate weight for GA, high Apgar scores). Most pregnant women were diagnosed with HIV before pregnancy, received regular antenatal care, used ART regularly, had an undetectable VL in the third trimester, and had adequate CD4 cell counts.
Studies in the literature describe middle ear pathologies in children infected with HIV, primarily conductive abnormalities, in up to 18–25% of patients [7,14,15,18]. However, regarding HEU NBs and infants, the literature remains scarce and limited to the first few months of life, making it difficult to draw conclusions about auditory development [26]. To date, there is no consensus regarding the association between HEU infants and HL.
Some authors have reported normal NHS in this population, suggesting normal cochlear function at birth. However, the absence of cochlear alterations observed in NHS does not exclude the possibility of later auditory impairment [27]. This study found altered NHS in 3 NBs (7.9%), considering both test and retest. Of these, 2 (5.3%) subsequently showed normal diagnostic hearing tests (tympanometry and ABR) and 1 (2.6%) was diagnosed with moderate bilateral sensorineural HL and was referred for auditory rehabilitation. This patient was subsequently excluded from the association analyses, as no CMV detection test was performed, making it impossible to determine whether the cause of HL was associated with HIV exposure.
A previous study evaluating auditory responses in HEU using ABR did not find a significant difference in the prevalence of HL between HEU and non-exposed NBs [26]. The same authors reported higher mean auditory thresholds at 1, 3, 6, and 9 months of age in HEU infants compared to non-exposed ones, using click stimuli in ABR [28].
Our study is among the first to evaluate HL in HEU infants during the first months of life using FS-ABR. We found a 36.8% prevalence of hearing impairment, predominantly conductive HL (13 of 14 cases—92.8%). All the affected infants had abnormal otoscopy, mainly with middle ear effusion, even without acute otitis media. These findings suggest that, even in the absence of HIV infection, exposure to the virus may interfere in some way with hearing function. It can be hypothesized that HIV exposure can affect the immune system of these children, making them more susceptible to middle ear infections in the first months of life compared to the non-exposed population. The causes of this potential immunological alteration are not yet fully understood. One hypothesis is placental inflammation, which could result in reduced transplacental antibody transfer to the fetus, thereby impairing immune function. Some studies have reported differences in CD4 maturation, reduced thymus size, and frequent neutropenia in these patients [7]. This altered immune response also appears to have a direct association with maternal VL at the time of delivery, with children born to mothers with a VL greater than 1000 copies/mL being exposed to a higher risk of immunosuppression due to compromised development of their immune system [7]. Additionally, the absence of breastfeeding in these patients could be an additional cause of immune deficiency, although the exact impact of this situation has not yet been fully clarified [7].
Maternal, gestational, and neonatal factors were analyzed to identify potential associations with the HL detected in the study. No association was found between HL and the timing of HIV diagnosis or the mode of delivery. There was also no association between HL and ART use, which is consistent with previous studies [29,30]. Little is still known about the effects of ART on the auditory health of children and adolescents. However, the association of maternal VL and ART use with hearing loss had borderline significance in the statistical analysis, possibly due to the small sample size.
The present study found no significant association between maternal VL quantification and auditory alterations. It is worth noting that most pregnant women included in the study had an undetectable VL (71.1% of cases), and 68.4% of them had a CD4 count above 500 cells/mm3. These data are consistent with appropriate prenatal care, in accordance with the guidelines of the Brazilian MoH [7]. A positive association was found between conductive HL and a higher maternal CD4 count, a finding not reported in the reviewed literature. For example, studies by Fasunla et al. [26,28], which assessed HEU NBs, found no significant relationship between HL and maternal CD4 count.
The main limitation of this study was the number of patients who were able to complete the second phase of the research. The number of losses reflects the difficulty in following this population, whether due to socioeconomic and mobility challenges, parents’ lack of understanding that HEU infants may still have clinical and laboratory abnormalities resulting from an unfavorable immunological condition, or even due to the stigma that HIV exposure causes in families. Additionally, this study was conducted during the COVID-19 pandemic, which further hindered patients’ access to the healthcare system.
Another limitation of the study was the absence of a control group of non-HIV-exposed infants, which would have allowed comparison with the HEU group, as middle ear alterations occur in the general pediatric population during the first years of life [9,31]. To reduce the occurrence of confounding biases, the sample in the present study consisted of infants with no other risk factors for HL besides intrauterine HIV exposure. We excluded preterm infants, significant congenital anomalies and infants with coinfections like congenital syphilis, CMV and neonatal herpes infection. It is important to note that most HIV-exposed infants born in our institution are born at term and healthy.
Additionally, it was not possible to perform PCR tests for CMV in all recruited patients, preventing the reliable exclusion of HL due to this infection. However, although only 34.2% of the sample was tested, all of these patients had negative results. The HL detected in the present study was conductive HL, which is not consistent with sensorineural HL caused by congenital CMV infection. The only infant with sensorineural HL was excluded from the subsequent analyses. This difficulty in collecting urine samples for CMV PCR testing was primarily due to the early discharge of most of the NBs in the study, who were clinically stable and remained only in the Rooming-In Unit, often being discharged before the research team could request and collect the test. Knowing that the global prevalence of congenital CMV is around 1% and is even higher in HIV-exposed newborns, and since we collected the PCR exam in 34% of our sample with no detected CMV, our hypothesis of hearing abnormalities due to HIV exposure is reliable. Not having detected CMV coinfection in most of the infants with abnormal hearing tests makes it easier to infer that these hearing abnormalities were probably due to HIV exposure.
5. Conclusions
This study demonstrated a high prevalence of conductive HL in HEU infants with no other IRHL. Larger and controlled studies are important to confirm these findings, and the importance of auditory monitoring for these children during the first years of life is evident.
Author Contributions
All authors contributed to the development of the project, and subsequently to its execution by data collection, analysis, and interpretation. Conceptualization of the study: A.Z.B., A.L.C., L.P.S.R., and L.F. Methodology: A.Z.B., A.L.C., P.P., L.P.S.R., R.R.d.A., L.d.P.e.S., M.L.d.S., and L.F. Software/creation of the database of the study: A.Z.B., A.L.C., P.P., L.P.S.R., R.R.d.A., L.d.P.e.S., M.L.d.S., and L.F. Validation of the tested methods: A.Z.B., P.P., and L.P.S.R. Formal statistical analysis of the results: A.Z.B., A.L.C., L.P.S.R., and L.F. Data curation/tables: A.Z.B., A.L.C., and L.F. Writing of the original paper, draft preparation, reviewing, editing: A.Z.B., A.L.C., L.P.S.R., S.S.d.C., and L.F. Translation/paper submission: L.F. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki and approved by the Ethics Committee of Hospital de Clínicas de Porto Alegre (protocol number 2021-0230, approved in 19 August 2021.
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The authors declare that all data generated or analyzed during this study are included in this published article. Some personal patients’ data are not publicly available but are available from the corresponding author on reasonable request.
Acknowledgments
The funders had no role in the study design, data collection and analysis, decision to publish, or preparation of the manuscript. The authors declare that they have no affiliations with or involvement in any organization or entity with any financial interest in the subject matter or materials discussed in this manuscript.
Conflicts of Interest
No financial or non-financial benefits have been received or will be received from any party related directly or indirectly to the subject of this article. The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| AABR | Automatic Auditory Brainstem Response |
| ABR | Auditory Brainstem Response |
| AC | Air conduction |
| AGA | Adequate for Gestational Age |
| ART | Antiretroviral Therapy |
| BC | Bone Conduction |
| CMV | Cytomegalovirus |
| COMUSA | Multiprofessional Committee on Auditory Health (Portuguese) |
| FS-ABR | Frequence-Specific Automatic Brainstem Response |
| GA | Gestational Age |
| HEU | HIV-Exposed Uninfected |
| HIV | Human Immunodeficiency Virus |
| HL | Hearing Loss |
| Hz | Hertz |
| IRAD | Indicator of Risk for Auditory Deficiency |
| JCIH | Joint Committee on Infant Hearing |
| LB | Live Birth |
| LGA | Large for Gestational Age |
| MoH | Ministry of Health |
| NB | Newborn |
| NHS | Neonatal Hearing Screening |
| PCR | Polymerase Chain Reaction |
| SGA | Small for Gestational Age |
| SPSS | Statistical Package for Social Sciences |
| TEOAE | Transient Evoked Otoacustic Emissions |
| UNAIDS | United Nations Programme on HIV/AIDS |
| VL | Viral Load |
| VT | Vertical Transmission |
References
- Friedrich, L.; Menegotto, M.; Magdaleno, A.M.; da Silva, C.L.O. Transmissão vertical do HIV: Uma revisão sobre o tema. Bol. Cient. Pediatr. 2016, 5, 81–86. [Google Scholar]
- Vasconcelos, M.S.B.; de Silva, D.S.B.; Peixoto, I.B. Coinfecção entre HIV e Sífilis: Principais complicações clínicas e interferências no diagnóstico laboratorial. Rev. Bras. Análises Clínicas 2021, 53, 15–20. [Google Scholar] [CrossRef] [Scilit]
- Miranda, A.E.; Santos, P.C.; Coelho, R.A.; Pascom, A.R.P.; de Lannoy, L.H.; Ferreira, A.C.G.; Gaspar, P.C.; Maciel, E.L.; Barreira, D.; Pereira, G.F.M. Perspectives and challenges for mother-to-child transmission of HIV, hepatitis B, and syphilis in Brazil. Front. Public Health 2023, 11, 1182386. [Google Scholar] [CrossRef] [Scilit]
- Slogrove, A.L.; Powis, K.M.; Johnson, L.F.; Stover, J.; Mahy, M. Estimates of the global population of children who are HIV-exposed and uninfected, 2000–2018: A modelling study. Lancet Glob. Health 2020, 8, e67–e75. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brasil. Ministério da Saúde. Boletim Epidemiológico—HIV e Aids 2023 [Internet]. 2023. Available online: https://www.gov.br/aids/pt-br/central-de-conteudo/boletins-epidemiologicos/2023/hiv-aids/boletim-epidemiologico-hiv-e-aids-2023.pdf/view (accessed on 20 December 2025).
- UNAIDS. UNAIDS Data 2023 [Internet]. 2023. Available online: https://www.unaids.org/sites/default/files/media_asset/data-book-2023_en.pdf (accessed on 20 December 2025).
- Brasil. Ministério da Saúde. Protocolo Clínico e Diretrizes Terapêuticas Manejo da Infecção pelo HIV em Crianças e Adolescentes. Módulo 1—Diagnóstico, Manejo e Acompanhamento de Crianças Expostas ao HIV [Internet]. 2023; p. 56. Available online: https://www.gov.br/conitec/pt-br/midias/relatorios/2023/RR_PCDTHIVCrianasmdulo1_Final.pdf (accessed on 20 December 2025).
- Benki-Nugent, S.F.; Yunusa, R.; Mueni, A.B.; Laboso, T.B.; Tamasha, N.B.; Njuguna, I.M.; Gómez, L.B.; Wamalwa, D.C.M.; Tapia, K.; Maleche-Obimbo, E.M.; et al. Lower neurocognitive functioning in HIV-exposed uninfected children compared with that in HIV-unexposed children. J. Acquir. Immune Defic. Syndr. (1988) 2022, 89, 441–447. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dawood, G.; Klop, D.; Olivier, E.; Elliott, H.; Pillay, M.; Grimmer, K. Nature and extent of hearing loss in HIV-infected children: A scoping review. Int. J. Pediatr. Otorhinolaryngol. 2020, 134, 110036. [Google Scholar] [CrossRef] [Scilit]
- Brennan, A.T.; Bonawitz, R.; Gill, C.J.; Thea, D.M.; Kleinman, M.; Useem, J.; Garrison, L.; Ceccarelli, R.; Udokwu, C.; Long, L.; et al. A meta-analysis assessing all-cause mortality in HIV-exposed uninfected compared with HIV-unexposed uninfected infants and children. AIDS 2016, 30, 2351–2360. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Anderson, K.; Kalk, E.; Madlala, H.P.; Nyemba, D.C.; Jacob, N.; Slogrove, A.; Smith, M.; Kroon, M.; Harrison, M.C.; Eley, B.S.; et al. Preterm birth and severe morbidity in hospitalized neonates who are HIV exposed and uninfected compared with HIV unexposed. AIDS 2021, 35, 921–931. [Google Scholar] [CrossRef] [Scilit]
- Wedderburn, C.J.; Evans, C.; Yeung, S.; Gibb, D.M.; Donald, K.A.; Prendergast, A.J. Growth and neurodevelopment of HIV-exposed uninfected children: A conceptual framework. Curr. HIV/AIDS Rep. 2019, 16, 501–513. [Google Scholar] [CrossRef] [Scilit]
- Fowler, M.G.; Aizire, J.; Sikorskii, A.; Atuhaire, P.; Ogwang, L.W.; Mutebe, A.; Katumbi, C.; Maliwichi, L.; Familiar, I.; Taha, T.; et al. Growth deficits in antiretroviral and HIV-exposed uninfected versus unexposed children in Malawi and Uganda persist through 60 months of age. AIDS 2022, 36, 573–582. [Google Scholar] [CrossRef] [Scilit]
- Ensink, R.J.H.; Kuper, H. Is hearing impairment associated with HIV? A systematic review of data from low- and middle-income countries. Trop. Med. Int. Health 2017, 22, 1493–1504. Available online: https://pubmed.ncbi.nlm.nih.gov/29078020/ (accessed on 20 December 2025). [CrossRef] [Scilit]
- Khoza-Shangase, K.; Anastasiou, J. An exploration of recorded ontological manifestations in South African children with HIV/AIDS: A pilot study. Int. J. Pediatr. Otorhinolaryngol. 2020, 133, 109960. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coleman, M. Exposure to HIV increases risk of hearing loss in children. Hear J. 2012, 65, 1. [Google Scholar] [CrossRef] [Scilit]
- Torre, P.; Zhang, Z.J.; Hoffman, H.J.; Frederick, T.; Purswani, M.; Williams, P.L.; Yao, T.-J. Auditory function in the pediatric HIV/AIDS cohort study adolescent master protocol up young adults: A pilot study. J. Acquir. Immune Defic. Syndr. 2023, 92, 340–347. Available online: https://pubmed.ncbi.nlm.nih.gov/36729663/ (accessed on 20 December 2025). [CrossRef] [Scilit]
- Sebothoma, B.; Maluleke, M. Middle ear pathologies in children living with HIV: A scoping review. S. Afr. J. Commun. Disord. 2022, 69, e1–e7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lieu, J.E.C.; Kenna, M.; Anne, S.; Davidson, L. Hearing loss in children: A review. JAMA 2020, 324, 2195–2205. [Google Scholar] [CrossRef] [Scilit]
- Joint Committee on Infant Hearing. Year 2019 position statement: Principles and guidelines for early hearing detection and intervention programs. J. Early Hear Detect. Interv. 2019, 4, 1–44. [Google Scholar]
- Lewis, D.R.; Marone, S.A.M.; Mendes, B.C.A.; Cruz, O.L.M.; de Nóbrega, M. Multiprofessional committee on auditory health: COMUSA. Braz. J. Otorhinolaryngol. 2010, 76, 121–128. [Google Scholar] [CrossRef] [Scilit]
- Brasil. Ministério da Saúde. Nota Informativa n o 12/2023-CGAHV/.DATHI/SVSA/MS [Internet]. 2023. Available online: https://www.gov.br/aids/pt-br/central-de-conteudo/notas-informativas/2023/sei_ms-0038033904-nota-informativa-12_2023_ral-granulado_revoga-nota-n-11.pdf/view (accessed on 20 December 2025).
- Villar, J.; Giuliani, F.; Fenton, T.R.; Ohuma, E.O.; Ismail, L.C.; Kennedy, S.H. INTERGROWTH-21st very preterm size at birth reference charts. Lancet 2016, 387, 844–845. [Google Scholar] [CrossRef] [Scilit]
- British Society of Audiology. Tympanometry—Recommended Procedures [Internet]. 2013, p. 25. Available online: https://www.thebsa.org.uk/resource-type/recommended-procedures/ (accessed on 20 December 2025).
- Jerger, J. Clinical experience with impedance audiometry. Arch. Otolaryngol. Head Neck Surg. 1970, 92, 311–324. [Google Scholar] [CrossRef] [Scilit]
- Fasunla, A.J.; Ogunbosi, B.O.; Odaibo, G.N.; Nwaorgu, O.G.B.; Taiwo, B.; Olaleye, D.O.; Osinusi, K.; Murphy, R.L.; Adewole, I.F.; Akinyinka, O.O. Comparison of auditory brainstem response in HIV-1 exposed and unexposed newborns and correlation with the maternal viral load and CD4+ cell counts. AIDS 2014, 28, 2223–2230. [Google Scholar] [CrossRef] [Scilit]
- Padilha, M.A.D.; Maruta, E.C.S.; de Azevedo, M.F. Ocorrência de alterações auditivas em lactentes expostos à transmissão vertical do HIV. Audiol. Commun. Res. 2018, 23, e1965. [Google Scholar] [CrossRef] [Scilit]
- Fasunla, A.; Omisore, A.G.; Nwaorgu, O.G.; Akinyinka, O.O. Long-term effects of maternal HIV infection and anti-retroviral medications on the hearing of HIV-exposed infants. West Afr. J. Med. 2018, 35, 90–96. [Google Scholar] [PubMed]
- Chao, C.K.; Czechowicz, J.A.; Messner, A.H.; Alarcón, J.; Roca, L.K.; Rodriguez, M.M.L.; Villafuerte, C.G.; Montano, S.M.; Zunt, J.R. High prevalence of hearing impairment in HIV-infected Peruvian children. Otolaryngol. Head Neck Surg. 2012, 146, 259–265. [Google Scholar] [CrossRef] [Scilit]
- Torre, P.; Zeldow, B.; Yao, T.; Hoffman, H.; Siberry, G.; Purswani, M.; Frederick, T.; Spector, S.; Williams, P. Newborn hearing screenings in human immunodeficiency virus-exposed uninfected infants. J. AIDS Immune Res. 2016, 1, 102. [Google Scholar]
- Buriti, A.K.L.; Oliveira, S.H.S.; Muniz, L.F.; Soares, M.J.G.O. Evaluation of hearing health in children with HIV/AIDS. Audiol. Commun. Res. 2014, 19, 105–111. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.