


Abstract
Introduction: Paramedics are at high risk of musculoskeletal injuries associated with the physical demands of the role. Paramedic physical fitness is an important requirement to complete the essential daily tasks of the role and potentially reduce injury risk. It is unclear what the specific fitness requirements should be across many ambulance services and how to assess or prepare for them. Objective: This scoping review explored the existing evidence in relation to paramedic physical fitness, testing and standards required by ambulance services in Australia, New Zealand, South Africa, the United Kingdom, Ireland and Canada. Methods: A scoping review was conducted and reported following PRISMA-ScR guidelines. Electronic databases (MEDLINE, CINAHL, Scopus, ERIC, Emcare, and Informit) and grey literature sources (organisational documents) were searched, with searches completed in October 2025. Results: Paramedics are reported to have poorer general health when compared to the average population despite a physically demanding role. Most ambulance services require candidates to complete some form of pre-employment physical fitness test. No ambulance service identified required regular, ongoing physical fitness testing for all its paramedics. Each pre-employment physical fitness test identified was unique in its format. Conclusions: By prioritising, supporting and accurately assessing the physical health and fitness of paramedics, organisations can enhance job performance readiness and potentially reduce injury rates or injury risk.
1. Introduction
The work of paramedics involves periods of high physical demand [1,2], with perceived demand increasing with patient acuity [3]. Intermittent periods of high physical demand can increase the risk of workplace injury [4]. Musculoskeletal injuries are the most frequently reported type of injury [4,5,6], prevalent due to muscular stress caused by the manual handling requirements, awkward and sustained postures, and high physical demands of the paramedic role [5,7,8]. Injury risk is further exacerbated by significant psychological stress and injury also associated with the role [7,9], and poor physical health is indicated by the prevalence of poor health [10,11,12,13], cardiovascular disease [11,14,15] and obesity in paramedics [12,16]. Existing evidence suggests that emergency services and military personnel with greater levels of job-relevant fitness have a lower likelihood of sustaining injuries [17,18,19]. Broader healthcare literature suggests that poor clinician health is also linked to adverse patient care outcomes [20,21]. Given these demands and associated risks, it is important to consider how ambulance services and paramedic roles are structured, regulated, and supported in relation to these issues.
1.1. Ambulance Services (AS)
Broadly, two models of ambulance systems exist internationally: the Anglo-American model, in which paramedics respond to emergencies, provide treatment, and transport patients to hospital emergency departments; and the Franco-German model, which involves physician-led pre-hospital care or transport only [22]. All countries discussed and included in this review align with the Anglo-American model of emergency medical response. The definition and role description of a paramedic vary across ambulance services, internationally, and the literature shows a lack of consensus [23]. The title ‘paramedic’ is a protected professional title under national law in countries where paramedics are required to register with national health practitioner regulatory bodies, such as the Paramedicine Board of Australia through the Australian Health Practitioner Regulation Agency (Ahpra) [24]. This legislation requires individuals to be registered before using the title ‘paramedic’, and to meet and maintain defined professional capabilities and standards of practice, including physical fitness to practise [25].
Across Australia, each state or territory ambulance service operates under a slightly different structure and funding and regulatory framework, overseen by the respective state or territory government [26]. Paramedics in Australia are required to comply with professional registration requirements and demonstrate capabilities mandated by the Paramedicine Board and the Ahpra [24]. These professional capabilities include paramedics managing their own physical health and so ensuring their fitness to practise [25]. In New Zealand, paramedics must register with the Te Kaunihera Manapou Paramedic Council (Te Kaunihera) and must adhere to established standards and scopes of practice, including management of personal physical health [27,28].
Similarly, paramedics in South Africa and the United Kingdom are required to meet national professional registration standards and capabilities [29,30], also including physical health maintenance. The public ambulance services in the United Kingdom consist of ten individual National Health Service Ambulance Trusts in England, as well as the Eastern Health and Social Services Board in Northern Ireland, the Welsh Ambulance Services University NHS Trust, which covers the whole of Wales, and the Scottish Ambulance Service, which covers the whole of Scotland [31]. While there is a national standard of care that each Trust is expected to meet, the management of services is conducted independently by each Trust [32].
In South Africa and Canada, ambulance services are regulated at the provincial or territorial level, comprising a mix of public, private, and volunteer services [33,34]. While the federal government in Canada sets certain standards, the organisation and delivery of emergency medical services in that country are primarily the responsibility of each province or territory. Regulatory requirements for paramedics vary between Canadian provinces. Some provinces require registration with a provincial regulatory body (e.g., the Alberta College of Paramedics) to practise, whereas others (e.g., Ontario) require certification through a provincial examination and clinical practice under the medical oversight of one of ten designated Base Hospitals [35].
Information regarding the numbers of public emergency medical services in Canada and South Africa is challenging to obtain due to the multitude of organisations involved. In South Africa, nine provinces operate public ambulance services, which, like in Australia, are managed by the provincial departments of health [36,37]. Canada also has provincial and territorial public services, but the delivery of paramedic services varies significantly, with over 250 emergency medical services operating in the country. For the purposes of this review, public state/territory/provincial/trust emergency medical/ambulance services in all these countries will simply be referred to as Ambulance Services (AS).
The AS, or public health National Ambulance Service in Ireland, also requires paramedics to maintain professional regulatory requirements set by a statutory body, the Pre-Hospital Emergency Care Council [38], to be able to practise.
1.2. Physical Fitness Requirements
AS in all these countries (Australia, New Zealand, the UK, Ireland, Canada and South Africa) typically requires that prospective paramedic applicants or candidates pass some form of occupational health assessment, pre-employment physical fitness testing, or physical capacity assessment [39]. However, it is evident that entry-level paramedic education has typically not prepared student paramedics adequately for these pre-employment assessments, and information regarding the specific tasks or criteria involved in most of these tests can be difficult to find [39]. Furthermore, registration requirements for paramedics lack clarity regarding expectations for maintaining physical health and fitness. To date, no comprehensive overview of physical fitness requirements, preparation, and expectations across these jurisdictions has been published.
Importantly, any guidance regarding physical fitness requirements should be informed by rigorous Physical Employment Standards (PES). PES constitute validated benchmarks against which to evaluate a candidate’s ability to complete tasks safely and effectively in public safety occupations such as emergency services [40]. PES development is a systematic process, beginning with a physical demands analysis or physical demands description to identify the most critical and frequently occurring physically demanding tasks associated with an occupational role [2,41]. This is followed by investigation of how to validly and efficiently test the ability of personnel to safely and effectively perform those tasks. This process ensures an employee’s physical capacity meets the physical demands of the job [40,42]. In this way, if they meet the PES in this way, PES in this way, and PES are designed to be criterion-based and to correlate with the physically demanding tasks of the occupation [42]. If this were not the case, there could be legal ramifications for the organisation under human rights and employment law [43]. Additionally, although paramedics in the countries considered here are required to obtain an undergraduate degree in paramedicine or are transitioning toward this requirement, undergraduate education has historically not prepared students for the physical demands assessed in existing physical employment tests (PETs) [39].
On this basis, the aim of this scoping review was to answer the following research questions:
- What are the existing physical fitness or capacity test requirements for paramedics, and what evidence exists for their validity in assessing the capacity of graduate candidates and qualified paramedics to perform the paramedic role effectively and safely?
- To what extent do the physical activity and fitness levels of graduate paramedic candidates and qualified paramedics meet the physical demands and fitness requirements of the paramedic role, represented by ‘pass’ levels of job-specific physical fitness tests and the known physiological demands of paramedic tasks?
The review focused on the following jurisdictions, which follow the Anglo-American model of ambulance services: Australia, New Zealand, the UK, Ireland, Canada, and South Africa.
2. Methods
This article reports findings relating to qualified paramedics from an overarching scoping review that also included findings related to paramedicine students, which have been reported separately [39]. A decision was made to report the findings for qualified paramedics and for paramedicine students separately, due to the unexpectedly large volume of evidence identified across the two closely related populations. The overarching scoping review was conducted in accordance with the JBI methodology for scoping reviews and reported following PRISMA-ScR guidelines [44]. The protocol for the overarching review was registered on the Open Science Framework (OSF; Center for Open Science, Washington, DC, USA; [https://doi.org/10.17605/OSF.IO/6GQBV]) prior to literature identified in the associated searches being assessed for eligibility for inclusion. Elements of the overarching scoping review’s methods that contributed to the findings reported in this article are reported below.
2.1. Inclusion Criteria
Consistent with the framework of PCC (populations, concepts, and context) [45] employed in developing the search strategy for the review, the following inclusion criteria were used.
Populations: This scoping review used the term ‘paramedic’ to include various related roles such as ‘ambulance officer,’ ‘first responder,’ and ‘emergency medical technician (EMT)’. This review included studies and other eligible documents (see below) that considered paramedics or individuals associated with other terms or labels for this role, provided the documents met other eligibility criteria. The alternate terms include ‘Paramedic’, ‘EMT’, ‘emt’, and ‘Emergency Medical Technician’. Subsequent searches following feedback included the alternate terms ‘EMR’, and ‘Emergency Medical Responder’.
Concepts: The scoping review employed the definitions for the concept terms physical activity [46], exercise [47], physical fitness [47], and physical health [48] listed in Appendix A. It is important to clarify the definitions to be used, as these terms are often confused or used interchangeably [47]. Studies and other eligible documents (see below) that considered these concepts in relation to the populations mentioned above were included in the review provided they met other eligibility criteria.
Contexts: The contexts of interest in this review included geographical locations in which AS are considered broadly comparable, particularly in their Anglo-influenced structures and clinical governance models, sharing common English-based legal and health systems. These contexts were Australia, New Zealand, Canada, the United Kingdom, Ireland, and South Africa. Otherwise-eligible documents focused on these contexts were included in the review.
Types of sources: Where they met other eligibility criteria, the review included studies that employed qualitative or quantitative research designs, including secondary research conducted in a systematic manner. Authoritative documents describing AS fitness and testing requirements and standards and fitness requirements and standards of governing organisations responsible for registration or accreditation of paramedics, as well as policies, position statements and procedures relating to any of these, were included as key additional sources of evidence for the review.
2.2. Exclusion Criteria
The following were excluded: opinion pieces, study protocols, non-systematic secondary research (e.g., non-systematic narrative literature reviews), and research reports without detailed methodological detail to confirm they constituted primary or well-designed secondary research. Research conducted in, and information from, the United States of America was excluded due to significant differences perceived in operational systems design, including diverse service delivery models (e.g., fire-based, private, and hospital-based emergency medical services) and differing regulatory frameworks. These factors limit comparability with the more standardised, degree-qualified, and regulated paramedic systems in Australia, New Zealand, the UK, Ireland, Canada, and South Africa. Databases were searched without any date restrictions; the grey literature manual searches were limited to the period 2020–2025.
2.3. Search Strategy
A diverse list of relevant databases and search platforms was accessed and searched to identify eligible peer-reviewed studies and grey literature relevant to the review aims. The electronic databases searched include MEDLINE (via Ovid), Emcare (via Ovid), Informit Health Collection, Scopus, ERIC (via EBSCOhost), and CINAHL (via EBSCOhost). Additional searches were conducted using Google and Google Scholar, including advanced manual searches of grey literature. Reference lists of included studies and citation tracking via Scopus were used to identify additional sources.
An initial exploratory search was conducted to identify a range of relevant documents. Titles and abstracts were screened to extract keywords consistent with the Population, Concept, and Context (PCC) framework guiding this review. These keywords and equivalent thesaurus terms were then used to develop a comprehensive search strategy (Appendix B), optimising both sensitivity and specificity through Boolean operators (AND, OR, NOT) and relevant controlled vocabulary (e.g., MeSH terms). This iterative development of the search, screening, and selection strategies ensured alignment with the research questions and literature mapping [49] (Table 1). The search strategy was peer-reviewed by a librarian with expertise in conducting systematic literature searches, using the PRESS (Peer Review of Electronic Search Strategies) checklist [50] to ensure the search strategy was comprehensive and the risk of bias in the search was minimised.
Table 1.
PCC framework showing search terms and concepts for the scoping review.
Advanced manual grey literature searches were conducted via Google using domain-specific limits (e.g., *.gov.au), as outlined in Appendix B. These manual searches targeted relevant paramedicine-related government and non-government organisational documentation from 2020 to 2025, in all six countries, and involved screening the first five pages of search results.
Additional search strategies were employed for some countries of interest, based on feasibility. Relevant standards, protocols and policy documents were identified and accessed directly via manual searches of websites of Ambulance Services and other paramedicine-related organisations from Australia, New Zealand, the United Kingdom, and Ireland, where such documents were available online. Similar searches of individual websites of ambulance services in Canada and South Africa were not conducted due to the very large numbers of services and complex jurisdictional arrangements in those countries. Ambulance services in Australia and New Zealand were also contacted by email to request copies of these sorts of documents, where available. The study commenced in January 2024, with searches completed in October 2025, and the data extraction, synthesis and report development concluded in June 2026.
2.4. Screening and Selection of Studies and Other Sources of Evidence
Following the search, citations of all identified documents were collated and uploaded to Covidence (Veritas Health Innovation, Melbourne, VIC, Australia; available at www.covidence.org), and duplicates were removed. A pilot test of the planned screening and selection processes was conducted. Titles and abstracts were screened by three independent reviewers (S.S., L.R., and H.S.) against the eligibility criteria. To ensure a consistent approach to screening and selection, three meetings were conducted between reviewers: one to commence the pilot test to clarify the process, one on the conclusion of the pilot to inform the screening and selection process, and a final meeting during the screening process to address any emergent issues or questions.
Clearly ineligible documents were excluded during the screening process, and the remaining, potentially relevant sources were retrieved in full and imported to Covidence for further assessment of eligibility. The full text of each of these potentially relevant documents, except for those identified through the additional manual searching of ambulance service websites or direct email requests to Australian ambulance services, was assessed in detail against the eligibility criteria by three independent reviewers (S.S., S.F., and H.S.). Those identified through the additional manual searching of ambulance service websites or direct email requests were assessed in detail against the eligibility criteria by two independent reviewers (S.S. and L.R.). Differences between the reviewers in eligibility decisions were resolved through discussion and consensus. The results of the search, screening and selection processes were recorded in a flow diagram, using a template provided in the Preferred Reporting Items for Systematic Reviews and Meta-Analyses extension for Scoping Reviews (PRISMA-ScR) [44,51]. Reasons for exclusion of documents reviewed in full text were recorded as part of this process.
2.5. Data Extraction
Data were extracted from the included documents by two independent reviewers (S.S. and L.R.) using an adapted data extraction tool (Appendix C) in Covidence (Veritas Health Innovation, Melbourne, Australia; available at www.covidence.org). The data extracted from each document included, where relevant, specific details about the authors, publication year, participants, concepts, contexts, study methods, and key findings relevant to the review questions, including findings regarding:
- -
- Existing paramedic physical fitness and capacity testing;
- -
- Physiological demands of paramedic tasks and/or the role;
- -
- Existing physical activity and fitness levels of paramedics.
Any disagreements between the reviewers in data extraction decisions were resolved through discussion and consensus.
2.6. Data Synthesis
The research questions that were the focus of the scoping review were answered descriptively, with relevant evidence from the included documents categorised and mapped by topic area: existing physical fitness and capacity testing, physiological demands of paramedic tasks and/or the role, and existing physical activity and fitness levels of paramedics.
A deductive basic qualitative analysis approach was undertaken to describe and summarise evidence in each category, guided by JBI scoping review recommendations [49]. We used a three-step approach, as developed by Elo and Kyngas [52]: preparation, organisation, and reporting [49,52]. Reporting of the scoping review was conducted as per the PRISMA-ScR checklist and explanations [44].
2.7. Ethics
This scoping review used available secondary, non-identifiable data; therefore, ethics approval was not required.
3. Results
The database searches identified 3021 records. The manual Google domain searches, direct manual searches of AS internet sites, and electronic requests added 165 records. After the removal of 1470 duplicates, 1716 records were eligible for initial screening, from which 102 records met the inclusion criteria for this review (Figure 1).
Figure 1.
PRISMA flow chart, depicting results of the search, screening and selection processes, based on the Preferred Reporting Items for Systematic Reviews and Meta-Analyses extension for Scoping Reviews (PRISMA-ScR) [44].
3.1. Document Characteristics
Thirty-six of the 102 included documents were reports of studies sourced via database searches, and data from those are presented in Appendix D (study characteristics). The remaining 66 documents were organisational documents and web sources found via the grey literature Advanced Google domain searches and through direct manual searching of websites of known paramedicine organisations in Australia, New Zealand, the UK, and Ireland, or by direct communication via email with ten AS in Australia and New Zealand.
Of the 36 included study reports, 27 employed quantitative designs, one used a qualitative design, five adopted mixed-methods approaches, and three were literature reviews included in accordance with the protocol registered on the OSF. The studies were published between 1991 and 2025, with a median publication year of 2019. Most studies were conducted in Australia, followed by Canada, while two were international scoping reviews and two were conducted across multiple countries (Figure 2). Some studies reported findings relating to more than one area of interest for this review. Key areas highlighted based on the research questions of this review are shown in Figure 3, with ‘physical health’ of paramedics being the most frequently studied across the 36 included studies, followed by ‘physical fitness’ and ‘physical capacity’ of paramedics. The least researched areas in the included studies were the ‘physical preparation’ and ‘physical fitness training’ of paramedics.
Figure 2.
Distribution of included studies by country or countries.
Figure 3.
Key areas of interest and concepts considered within the 36 included studies. Note: Counts reflect the number of study reports addressing each concept area. Categories are not mutually exclusive, as individual study reports could address more than one concept.
3.2. Physical Demands of the Paramedic Role
Included studies found that the nature of the paramedic role, including aspects such as shift work, on-call duty, irregular shifts, impaired sleep, and psychological trauma, contributes to impaired paramedic health [6,10,53,54,55,56,57,58,59,60,61,62,63]. It was also reported that the role is physically demanding, though with periods of sedentary behaviour [1,3,57,64,65,66]; however, there are inconsistencies within the literature regarding how demanding [55,57,65,66] (Table 2).
Chapman [55] reported a descriptive physical profile study that measured the physical characteristics of two groups of male paramedics in Western Australia. Across this sample, paramedic physical demands appear to be met, especially in aerobic fitness, flexibility, and muscular strength/endurance. The study reported that conventional officers had BMI values significantly greater than age-matched population normative values (24.9 kg/m2), which suggests increased strain when completing low-intensity activities [55]. In contrast, an earlier study by Gamble et al. [57] reported that emergency work involved long periods of inactivity interspersed with shorter periods of intense activity, often above the anaerobic threshold. When job type was looked at by Rodgers [67], it was observed that the highest proportion of retirements because of musculoskeletal disorders/injuries occurred in ‘manual’ ambulance and nursing staff (42%), and the highest proportion of retirements because of circulatory disorders occurred in ambulance staff (31%). MacQuarrie [54] found that significant changes in heart rates and respiratory rates of paramedics in New South Wales, Australia, were associated with changes in Priority Code (i.e., the urgency of the call-out), transport times, BMI, area of work, and type of shift.
A scoping review conducted by Marsh et al. [6] identified the most physically demanding tasks for paramedics, as reported in the literature, as including handling stretchers and equipment [1,66], patient extraction (e.g., from confined spaces, down stairwells) [68], and tasks that involved awkward body positions [68], prolonged postures, and lifting in uncontrolled environments [68,69]—all of which increase injury risk [6].
Coffey et al. [1,2] conducted a physical demands description of paramedics in Ottawa, Canada, and observed call-outs. Despite high physical demands, paramedics were sedentary for more than half of the average 12 h shift due to driving, time on standby, or cleaning and restocking. The frequency of tasks performed varied significantly between services within the study. Commonly handled equipment included cardiac monitors, airway bags, and medication bags, but the weights of these items varied between services; the perceived demand associated with a task depended on the task (e.g., transferring, loading, and raising, etc.), the status of the patient (e.g., non-ambulatory, obese, and vital signs absent), and the location (e.g., on scene and at the hospital) [66].
Waack et al. [65] conducted a prospective cross-sectional study of 18 Advanced Life Support (ALS) paramedics employed at a State and Territory Ambulance Service (AS) in Australia who completed physical task checklists (PTCs) over 12–16 shifts. The study compared the results with data from the study by Fischer et al. [66], who had previously identified 183 physically demanding tasks [1,66]. The study found significant differences in the ratings of perceived exertion during tasks between the Australian AS and the Ottawa Paramedic Service (OPS). The Australian AS paramedics reported lower ratings of perceived exertion (RPE) for all tasks when compared to the OPS paramedics. For example, transferring non-ambulatory combative patients onto stretchers was associated with an average RPE of 5.67 for the Australian AS paramedics, while the OPS paramedics rated this task as RPE ≥ 7. Similarly, performing CPR had an average RPE of 5.67 for the Australian AS paramedics, compared to RPE ≥ 7 for the OPS paramedics. Differences reported regarding the ratings of perceived exertion associated with stretcher handling tasks (raising and lowering, for example) were attributed to the use of hydraulic stretchers (Stryker Power Pro) by the Australian AS, which likely reduced the physical strain when compared to the manual stretchers (Ferno Pro-Flex) used by OPS paramedics [65].
Table 2.
Findings from included studies—physical demands of the paramedic role.
3.3. Physical Fitness and Capacity Testing
Sixty-six organisational documents were reviewed as part of this scoping review, from twenty-four AS across Australia (n = 8), New Zealand (n = 2), the UK (n = 13), and Ireland (n = 1) (Table 3). Eight test protocol documents were identified and reviewed across six AS, with two protocols including two documents. In Australia, all AS required candidates to complete a pre-employment physical fitness test; however, only three testing protocol documents could be sourced, and from these it was not clear what levels of fitness a candidate must achieve to pass the test in its entirety. Not one AS in Australia required regular, ongoing physical fitness testing. In New Zealand, one AS provided the pre-employment physical fitness testing protocol and clear pass standards or criteria for the test it used. In the UK and Ireland, eight AS reviewed appeared to conduct a pre-employment physical fitness assessment; however, only two test protocol documents were sourced through the searches conducted for this review, only one of which demonstrated clear ‘pass’ standards. One AS in the UK mentioned a regular fitness testing requirement for 1% of employees. Each pre-employment physical fitness test identified in the review was unique in its format, with five of the eight sourced test protocol documents including a musculoskeletal assessment, six including a strength assessment, and five including a cardiovascular fitness assessment. What was clear was that each test differed from the others identified.
Table 3.
Data extracted from included documents from AS across Australia, New Zealand, the UK, and Ireland (n = 24) regarding organisational physical fitness and capacity testing.
The findings from included studies support the inconsistent findings when comparing organisational physical fitness and capacity testing (Table 4). Jenkins et al. [5], in one Australian AS, concluded that the existing pre-employment physical capacity test at the time of the study may not be a reliable predictor of workplace musculoskeletal injuries [5].
Table 4.
Findings of included studies—physical fitness and capacity testing.
Coffey et al. [1,2] identified critical physical demands of paramedic work, contributing to the development of physical employment standards in Canada. Five studies included in this review explored the existing Ottawa Paramedic Physical Ability Test (OPPAT™), evaluating movement competency [70], the effectiveness of a strength and conditioning programme [71], test–retest reliability [72], and factors influencing the likelihood of females passing the OPPAT™ [73,74]. Studies by Armstrong et al. [70,71,72] explored: movement competency as a crucial factor in the implementation of physical employment standards (PES) [70]; the effectiveness of a four-week strength and conditioning program for improving OPPAT™ performance and related fitness measures in paramedic candidates [71]; the test–retest reliability of the OPPAT™; and analysis of sex-based performance differences in the OPPAT™ [72]. The authors concluded that incorporating movement competency into physical employment standards may improve alignment between job demands and individual capability, thereby supporting more effective workforce management and musculoskeletal injury prevention [70]. Incorporation of familiarisation opportunities and specific training interventions showed an improvement in the completion of a physical capacity test [71,72].
3.4. Existing Physical Activity, Health and Fitness Levels of Paramedics
Reviews of the literature conducted previously (Table 5) report that paramedics generally have poorer health and fitness than the general population, despite the physically demanding nature of their job [6,11,81]. More than 50% of reported injuries among paramedics were linked to handling heavy patients and equipment. Additionally, paramedics report 14% less physical activity and higher levels of fatigue and stress compared to the general public [11,62]. The physical tasks and demands of the role, such as handling heavy patients and equipment, and awkward postures due to unpredictable environments, are associated with injury risk [5,6,7,11]. Paramedics were reported to be overweight or obese [15,53,63,81,82,83] and to be at substantially higher risk of injury claims than people in other health occupations [9,84] (141.4–163.7 injury claims per 1000 full-time equivalent paramedics across three separate 3-year periods [85]). Overall, the health of paramedics was found to be considerably worse than that of similarly aged people in the general population and similar occupations [6,11,81].
Table 5.
Findings from included studies—existing physical activity, health and fitness levels of paramedics.
A study of NSW Ambulance paramedics [82] reported sex differences and age differences in specific physiological parameters and physical fitness capacity or tests. The findings suggest that older paramedics and female paramedics may be at greater risk of sustaining occupational injuries due to lower physical capacity [82]. The study by Chapman et al. [55] reported that while paramedics generally possessed above-normal levels of aerobic capacity, muscular endurance, and strength, there is a need for targeted conditioning programmes to enhance anaerobic capacity and overall functional performance [55]. There is also a suggested need or preference for annual physical fitness testing and training support [79], which will support general health and a positive correlation with resilience and mental wellbeing [86].
3.5. Physical Preparation and Fitness Training Approaches for Paramedics
As mentioned, the study by Chapman et al. [55] concluded that there is a need for targeted conditioning programmes to enhance anaerobic capacity and overall functional performance of paramedics [55]. Consistent with these conclusions, Mthombeni et al. [76,77] reported on the correlations between performance on a rescue simulation (RS) and fitness training and tests among paramedics (n = 20). Specifically, scores on the 250-metre shuttle run showed a strong positive correlation with RS completion times (r = 0.83, p < 0.01), indicating that better anaerobic capacity was associated with shorter RS completion times [76,77]. Other fitness tests, such as the one-minute sit-up test, isometric leg lift, and grip strength test, showed weaker or non-significant correlations with RS performance. These results again highlight the importance to paramedics of specific fitness components, particularly anaerobic capacity, muscular strength, and endurance, for performing job-related tasks efficiently. The mean ± SD RS completion time was 8.42 ± 0.4 min, and the study emphasised the potential of using the RS as a tool for assessing the physical preparedness of paramedics [76,77].
A report conducted by Baum et al. [87] to support the health of emergency workers in Victoria, Australia, identified that current programmes addressing injury and health issues across six emergency response organisations included injury prevention and management initiatives. Fitness assessments and training were conducted for new recruits across these organisations. The report recommended implementing proactive and tailored injury prevention programmes, emphasising regular heart health checks, offering incentives for fitness and health assessments, and increasing collaboration between organisations to share best practices and improve program effectiveness. However, supervisors expressed concerns around the challenges of doing this without affecting employment security [87].
The study by Phung et al. [61] aimed to understand how English ambulance service trusts manage staff health and wellbeing, and how staff perceive and utilise these services. Using a multi-method qualitative approach, the researchers conducted semi-structured telephone interviews and analysed 57 wellbeing policy documents from various trusts. The results revealed significant variations in wellbeing support, with 57% of wellbeing leads acknowledging tensions between individual and organisational responsibilities. Notably, 68% of staff reported improvements in physical health due to diet and exercise initiatives. The study also highlighted that 75% of staff believed that organisational culture and service delivery challenges impacted their wellbeing.
4. Discussion
This review has identified and summarised findings from literature pertaining to a range of contexts outlined above, involving the Anglo-American model of ambulance services, to answer the research questions underpinning the review. In particular, the review has considered available evidence regarding the existing physical fitness and capacity test requirements for paramedics, their validity for predicting job performance, and the extent to which the physical activity and fitness levels of qualified paramedics meet the requirements of the role. In the discussion that follows, these findings will be situated within the broader literature in this area to highlight implications for training, monitoring and pre-employment practices.
The role of a paramedic is consistently reported as physically demanding [1,2,3,4,57,65,66], requiring an adequate level of physical fitness to safely and effectively complete manual tasks in an uncontrolled environment. Paramedics are consistently reported as being required to perform a range of tasks that involve handling stretchers and equipment, patient extraction from confined spaces, and lifting in uncontrolled environments, all of which increase the risk of musculoskeletal injury [5,7,8]. However, the perceived physical intensity of these tasks varied throughout the literature considered in this review, with some studies indicating that essential paramedic tasks are completed at levels below maximal aerobic capacity [55], while others suggest that the paramedic role is physically demanding [1,65,66] and involves periods of intense activity above the anaerobic threshold [57]. These conflicting findings concerning the extent of the physical demand associated with the paramedic role may be attributed to differences in study methodologies, populations, differences in State and Territory Ambulance Services (AS) equipment, and geographical locations [1,65]. This recognition reinforces the importance of physical employment standards (PES) based on a physical demand description completed for each AS to develop validated benchmarks and occupation-specific testing [40,42]. With greater levels of job-relevant fitness in other emergency services having been associated with a lower likelihood of sustaining injuries [6,17,18,19], further paramedic-specific research is needed to determine if regular fitness assessment or targeted training reduces injury rates in the paramedic workforce. The findings from Chapman et al. [55], Coffey et al. [1,2], and Waack et al. [65] underscore the complexity of the reported physical demands placed on paramedics and differences in perceptions. While many essential tasks are performed below maximal aerobic levels, the higher average BMI observed among the paramedic population may necessitate greater relative exertion during physical tasks. This is particularly concerning given that a significant proportion of paramedics were reported to be overweight or obese [15,53,63,82]. The implications of these findings are critical, as they suggest that current physical fitness levels among paramedics may not meet the demands of their roles, potentially compromising their ability to perform those roles effectively and safely.
The literature reviewed in this paper highlighted the variability in physical fitness testing protocols across different AS internationally. While most services conduct pre-employment physical fitness tests, the specific requirements and pass standards vary widely. This may not be of concern due to the highlighted importance of occupation-specific physical fitness testing [6,17,18,19,65,66,70,71,72,75,77]. What may be of more concern when we are aware of the links between the physical demands of the role [1,2,3,4,57,65,66], injury risk [5,6,7,8,79], and poor physical health [10,12,14,15,16,60] and between poor clinician health and patient care outcomes [20,21] is that no AS identified in this review clearly implemented regular, ongoing fitness testing for all paramedics. This lack of frequency in regular fitness testing raises concerns about paramedics’ maintenance of physical fitness for the paramedic role in a physically demanding and stressful occupation [7,8,9]. The literature reports that occupation-specific training, support, and testing improve physical fitness and job-related performance [53,70,71,72,77,78,79,87].
Although AS typically requires pre-employment physical fitness testing and implies that these tests are based on the demands of the paramedic role, there is insufficient clarity on how these tests have been validated for each service. The exception is when reviewing requirements for additional or extended roles, such as the special operation paramedic roles. This scoping review therefore focussed in part on this gap in the literature for the paramedic role. The extent to which the existing physical fitness tests are predictive of risk of injury was called into question [14,65]. For instance, Jenkins and Smith [5] found no significant differences in existing AS pre-employment physical fitness test scores between injured and non-injured paramedics, suggesting that the test used in that instance may not effectively differentiate between candidates’ differing levels of risk for musculoskeletal injuries. This raises concerns about the predictive validity of such tests in relation to actual job performance and injury prevention. In addition, while some organisations have implemented physical fitness assessments, many lack clear criteria for passing or do not require regular testing. These inconsistencies raise questions about the effectiveness of these assessments in preparing and supporting paramedics for the physical demands of their roles. Evaluation of the OPPAT™, a validated physical employment test informed by a physical demands description, demonstrates good test–retest reliability [72]. Including structured familiarisation opportunities prior to formal testing is an important mechanism to optimise performance [72] and ensure candidates are adequately prepared to meet the operational demands represented by the test.
Specific physical training programmes evaluated in the studies considered in this review were reported to result in significant improvements in subsequent physical capacity test performance, highlighting the importance of targeted training interventions [71,79]. The literature emphasises the importance of structured physical training programmes tailored to the specific demands of the paramedic role [40,71,73]. Implementing targeted conditioning programmes can enhance paramedics’ overall functional performance, particularly in areas such as anaerobic capacity, muscular strength, and endurance. These findings reinforce the need for AS to adopt a proactive approach to fitness training, integrating regular assessments and training interventions into the recruitment and ongoing professional development of paramedics.
4.1. Implications and Recommendations
The preceding discussion underscores the clear need for a re-evaluation of physical fitness testing and physical fitness training practices within the paramedic profession. AS should prioritise implementation of a standardised, evidence-based process to develop PES based on a physical demands description that can inform development of validated, occupation-specific benchmarks and physical fitness assessments that are published, accurately reflect the demands of the role and provide clear pass criteria. Ergonomic and environmental factors are important considerations when defining the physical demands of paramedic work and should be considered in the development and validation of future occupation-specific physical employment standards. Regulatory bodies may consider further evaluating the paramedic role and the associated professional capability requirements for health and fitness maintenance, providing more clarification on what these requirements may be for paramedics. Regular fitness testing should be implemented to ensure that paramedics maintain the necessary physical capabilities throughout their careers; however, we must be cautious not to implement such testing punitively but rather with post-testing support and training. Training programmes should address the specific physical demands of paramedic work, with a focus on enhancing aerobic and anaerobic capacity, muscular strength, and endurance relevant to the physical demands of the AS.
4.2. Strengths and Limitations
This review contributes to the limited literature on job readiness and physical fitness requirements and testing relevant to the paramedic role. The limited inclusion of clear evidence based-physical and pre-employment testing raises broader questions about whether organisations should play a more active role in preparing paramedic candidates physically and supporting paramedics’ continued physical fitness.
Some limitations must be acknowledged. Due to the nature of grey literature searches and organisational documentation, some documents may have been inaccessible. Also, while some data were gathered via direct correspondence with organisations, a lack of response from some may have affected the comprehensiveness of the organisational documentation mapping. Lastly, due to the reduced relevance of results past the five pages, a limitation was applied to the Google domain-specific search (searches reduced to the first five pages of results).
5. Conclusions
In conclusion, the physical fitness demands of the paramedic role are well reported but multifaceted, necessitating a comprehensive and standardised approach by AS to develop rigorous Physical Employment Standards (PES) representing validated benchmarks against which to evaluate candidates and support paramedic physical fitness in an ongoing fashion. Clear guidance and information need to be more readily available to candidates to help them prepare for occupation-specific fitness assessments. By prioritising the physical health and fitness of paramedics, organisations can enhance job performance readiness and potentially reduce injury rates or injury risk, while also potentially improving patient outcomes. The integration of evidence-based practices in physical fitness testing and training will be crucial in shaping the future of the paramedic profession.
Author Contributions
The authors confirm contribution to the paper as follows: S.S. wrote the protocol document; R.P. and L.R. contributed to protocol design, piloting, and writing of the protocol; S.S., L.R., S.F., and H.S. conducted data collection and extraction; S.S. conducted data analysis; R.P., A.M., R.R., H.S., S.F., and R.S.M. contributed to the writing of this scoping review. All authors have read and agreed to the published version of the manuscript.
Funding
This scoping review is funded as part of a doctoral research degree programme by Charles Sturt University (CSU). We acknowledge the financial support from Charles Sturt University (CSU) through its Academic Staff Higher Degree by Research Workload Support Scheme.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The search strategy is publicly available through the Open Science Framework (OSF) at https://doi.org/10.17605/OSF.IO/6GQBV. The data supporting the findings of this scoping review are presented within the article, with all included sources cited in the reference list. Additional data extraction sheets are available from the corresponding author upon reasonable request.
Acknowledgments
This scoping review is to contribute towards a doctoral degree award for S. Sheridan (SS). The data were visualised using Python 3.8 within Jupyter notebooks, hosted on Google Colab (Google LLC, Mountain View, CA, USA; accessed in 2025). The analysis used standard data science Python libraries such as Pandas, with Visualisations created using Matplotlib (v3.11).
Conflicts of Interest
The authors declare no conflicts of interest.
Appendix A. Key Definitions
The World Health Organisation (WHO) refers to physical activity as any movement requiring energy, produced by skeletal muscles during daily activities and leisure time [46].
Exercise [47] is physical activity that is planned, structured and, often, completed to improve efficiency, reduce energy levels required to complete daily activities and improve health. This form of physical activity is likely to be utilised by organisations to benefit the health and work performance of employees, as it can be planned, structured, resourced and coordinated by the organisation.
Physical fitness [47] is defined as a set of attributes that a person has or achieves relating to their ability to perform physical activity. It is the ability to carry out daily tasks with vigour and alertness, without undue fatigue, and with energy remaining to enjoy other activities or manage emergencies.
Physical Health is defined as overall well-being inclusive of physical, mental, and social well-being, and not just the absence of disease or illness [48].
Appendix B. Search Strategy
| Concepts/Keywords | |
| 1. | Paramedic * OR ambulance OR EMT OR “emergency medical technician*” OR prehospital OR pre-hospital OR “out of hospital” OR EMR OR “emergency medical responder” |
| 2. | AND |
| 3. | Fitness OR “physical activity” OR “fitness test” OR ((fitness OR physical) AND standard*) |
| * = broadens the search to include various word endings and spellings. “ ” = key phrase. | |
Appendix B.1. Database: Scopus
Search 1
TITLE-ABS-KEY (paramedic* OR ambulance* OR emt OR “emergency medical technician*” OR prehospital OR emr OR “emergency medical responder*”) AND TITLE-ABS-KEY (fitness OR “physical activit*” OR exercis* OR (physical W/3 performance) OR “physical capacity*”) AND TITLE-ABS-KEY (standard*)
Search 2
TITLE-ABS-KEY (paramedic* OR ambulance* OR emt OR “emergency medical technician*” OR prehospital OR emr OR “emergency medical responder*”) AND TITLE-ABS-KEY (fitness OR “physical activit*” OR exercis* OR (physical W/3 performance) OR “physical capacity*”) AND TITLE-ABS-KEY (student*)
Appendix B.2. Database: Ovid Emcare
Search 1
| Query | |
| 1 | paramedical personnel/or paramedical profession/or paramedical student/ |
| 2 | (paramedic* or ambulance* or EMT or emergency medical technician* or prehospital or pre-hospital or out of hospital or emr or emergency medical responder*).mp. |
| 3 | 1 or 2 |
| 4 | exp cardiorespiratory fitness/or exp fitness/ |
| 5 | exp physical performance/ |
| 6 | (fitness or physical activity or exercis*).mp. [mp = title, abstract, heading word, drug trade name, original title, device manufacturer, drug manufacturer, device trade name, keyword heading word] |
| 7 | 4 or 5 or 6 |
| 8 | exp professional standard/or exp standard/ |
| 9 | Standard*.ti,ab. |
| 10 | 8 or 9 |
| 11 | 3 and 7 and 10 |
| * = broadens the search to include various word endings and spellings. | |
Search 2
| Query | |
| 1. | paramedical personnel/or paramedical profession/or paramedical student/or (paramedic* or ambulance* or EMR or EMT or emergency medical technician* or prehospital or pre-hospital or out of hospital OR emr or emergency medical responder*).mp. |
| 2. | “physical activity, capacity and performance”/or exp exercise/or physical activity/or exp physical capacity/or exp physical performance/or fitness/or cardiorespiratory fitness/or (fitness or physical activit* or exercis* or (physical adj3 adjustment*) or physical capacit*).mp. |
| 3. | “student*”.ab,ti. |
| 4. | 1 and 3 |
| 5. | 2 and 4 |
| * = broadens the search to include various word endings and spellings. “ ” = key phrase. | |
Appendix B.3. Database: CINAHL
Search 1
| Query | |
| 1. | (MH “Emergency Medical Technicians”) OR paramedic* OR ambulance OR EMT OR “emergency medical technician*” OR prehospital OR pre-hospital OR “out of hospital” OR emr OR “emergency medical responder*” |
| 2. | AND |
| 3. | MH (“Physical fitness+” OR “Exercise Test+”) OR fitness OR “physical activity” AND standard* |
| MH = a subject heading has been searched. “ ” = key phrase. * = broadens the search to include various word endings and spellings. + = exploded. | |
Search 2
| Query | |
| 1. | (MH “Paramedics”) OR (MH “Emergency Medical Technicians”) OR (MH “Prehospital Care”) OR (paramedic* OR ambulance* OR EMT OR “emergency medical technician*” OR prehospital OR pre-hospital OR “out of hospital” OR emr OR “emergency medical responder*”) |
| 2. | AND |
| 3. | (MH (“Physical fitness+” OR “Exercise Test+” OR “Exercise”) OR fitness OR “physical activit*” OR exercis* OR (physical N3 performance*) OR physical capacit*) |
| 4. | AND |
| 5. | XB student* |
| MH = a subject heading has been searched. “ ” = key phrase. * = broadens the search to include various word endings and spellings. + = exploded. | |
Appendix B.4. Database: Ovid MEDLINE®
Search 1
| Query | |
| 1 | exp Paramedics/ |
| 2 | exp Emergency Medical Technicians/ |
| 3 | (paramedic* or ambulance* or EMT or emergency medical technician* or prehospital or pre-hospital or out of hospital).mp. |
| 4 | 1 or 2 or 3 |
| 5 | Physical Fitness/or Cardiorespiratory Fitness/or Exercise Test.mp. or Physical Functional Performance/or (fitness or physical activity or exercis*).mp. [mp = title, book title, abstract, original title, name of substance word, subject heading word, floating sub-heading word, keyword heading word, organism supplementary concept word, protocol supplementary concept word, rare disease supplementary concept word, unique identifier, synonyms, population supplementary concept word, anatomy supplementary concept word] |
| 6 | Standard*.mp. [mp = title, book title, abstract, original title, name of substance word, subject heading word, floating sub-heading word, keyword heading word, organism supplementary concept word, protocol supplementary concept word, rare disease supplementary concept word, unique identifier, synonyms, population supplementary concept word, anatomy supplementary concept word] |
| 7 | 4 and 5 and 6 |
| * = broadens the search to include various word endings and spellings. | |
Search 2
| Query | |
| 1 | paramedical personnel/or paramedical profession/or paramedical student/or (paramedic* or ambulance* or EMR or EMT or emergency medical technician* or prehospital or pre-hospital or out of hospital).mp. |
| 2 | “physical activity, capacity and performance”/or exp exercise/or physical activity/or exp physical capacity/or exp physical performance/or fitness/or cardiorespiratory fitness/or (fitness or physical activit* or exercis* or (physical adj3 adjustment*) or physical capacit*).mp. |
| 3 | 1 AND 2 |
| 4 | “student*”.ab,ti. |
| 5 | 3 AND 4 |
| “ ” = key phrase. * = broadens the search to include various word endings and spellings. | |
Appendix B.5. Database: ERIC
Search 1
(DE “Emergency Medical Technicians” OR (paramedic* OR ambulance* OR EMT OR “emergency medical technician*” OR prehospital OR pre-hospital OR “out of hospital” OR emr OR “emergency medical responder*”)) AND ((DE “Physical Fitness”) OR (DE “Exercise”) OR (fitness OR “physical activit*” OR exercis* OR (physical N3 performance*) OR physical capacit*))) AND ((DE “Standards”) OR standard*)
“ ” = key phrase
* = broadens the search to include various word endings and spellings
Search 2
(MH “Paramedics”) OR (MH “Emergency Medical Technicians”) OR (MH “Prehospital Care”) OR (paramedic* OR ambulance* OR EMT OR “emergency medical technician*” OR prehospital OR pre-hospital OR “out of hospital” OR emr OR “emergency medical responder*”)) AND XB (MH (“Physical fitness+” OR “Exercise Test+” OR “Exercise”) OR fitness OR “physical activit*” OR exercis* OR (physical N3 performance*) OR physical capacit*) AND XB student*
“ ” = key phrase
* = broadens the search to include various word endings and spellings
Appendix B.6. Database: Informit
Search 1
[(paramedic* OR ambulance* OR EMT OR “emergency medical technician*” OR prehospital OR “pre-hospital” OR “out of hospital” OR emr OR “emergency medical responder*”)] AND [(fitness OR “physical activit*” OR exercis* OR “physical capacit*”) OR (“physical adjustment*”~3)] AND standard*
“ ” = key phrase
* = broadens the search to include various word endings and spellings
Search 2
[(paramedic* OR ambulance* OR EMT OR “emergency medical technician*” OR prehospital OR “pre-hospital” OR “out of hospital” OR emr OR “emergency medical responder*”)] AND [(fitness OR “physical activit*” OR exercis* OR “physical capacit*”) OR (“physical adjustment*”~3)] AND student*
“ ” = key phrase
* = broadens the search to include various word endings and spellings
Appendix B.7. Grey Literature Advanced Google Search
| Search Terms | Paramedic OR “Emergency Medical Technician” OR “Emergency Medical Responder” OR Student Paramedic AND “Health and Fitness”, “Pre-Employment Fitness Testing”, “Physical Employment Standards”, “Fitness Testing”. | |
| Hand search—curriculum and organisation documentation Including—Paramedic organisations, Ambulance Service Policy, Ambulance Service pre-employment fitness requirements and testing, and University websites. (First 5 pages) | Australia; | paramedic fitness site:edu.au paramedic physical health site:edu.au paramedic fitness site:gov.au paramedic physical health site:gov.au |
| New Zealand; | paramedic fitness site:ac.nz paramedic physical health site:ac.nz paramedic fitness site:govt.nz paramedic physical health site:govt.nz paramedic fitness site:org.nz paramedic physical health site:org.nz | |
| United Kingdom; | paramedic fitness site:ac.uk paramedic physical health site:ac.uk paramedic fitness site:uk paramedic physical health site:uk | |
| Ireland; | paramedic fitness site:ie paramedic physical health site:ie | |
| Canada; | paramedic fitness site:ca paramedic physical health site:ca | |
| South Africa; | paramedic fitness site:ac.za paramedic physical health site:ac.za paramedic fitness site:za paramedic physical health site:za | |
Appendix C. Data Extraction Template
| Evidence Source Details and Characteristics |
| Author |
| Date (year) |
| Journal |
| Title |
| Organisation |
| Objective/s |
| Research question/s |
| Article type |
| Citation details (e.g., author/s, date, title, journal, volume, issue, pages) |
| Population |
| Area of Interest/Concept |
| Country |
| Context—specific area or service |
| Rationale |
| Interventions |
| Relevant factors |
| Methods |
| Study Design |
| No. of participants |
| Details/Results Extracted from Source of Evidence |
| Limitations |
| Key findings |
| Existing physical fitness and capacity testing |
| Existing safety requirements |
| Physical fitness training approaches for paramedics |
| Physiological demands of paramedic tasks and/or the role |
| Existing physical activity and fitness levels of paramedic |
Appendix D. Study Characteristics
| Author(s) | Article Type | Methodology | Study Design | Population | Area of Interest/Concept |
| Armstrong et al. [70] | Original research | Quantitative | Other | Paramedic | Physical employment standards; Physical capacity |
| Armstrong et al. [71] | Original research | Quantitative | Cross sectional study | Paramedic | Pre-employment fitness testing; Physical employment standards; Physical preparation |
| Armstrong et al. [72] | Original research | Quantitative | Non-randomised experimental study; Cohort study | Paramedic; Student paramedic | Pre-employment fitness testing; Physical employment standards; Physical preparation |
| Armstrong et al. [75] | Original research | Quantitative | Cross sectional study | Paramedic | Physical capacity |
| Baum et al. [87] | Original research | Mixed-method | Qualitative—interviews; Qualitative—focus groups; Other | Paramedic | Pre-employment fitness testing; Physical fitness training; Physical capacity; Physical activity; Physical health |
| Chapman et al. [55] | Original research | Quantitative | Cross sectional study | Paramedic | Physical fitness; Physical capacity; Physical health |
| Coffey et al. [2] | Original research; Other | Quantitative | Non-randomised experimental study | Paramedic | Physical employment standards |
| Coffey et al. [1] | Original research | Quantitative | Cross sectional study | Paramedic | Pre-employment fitness testing; Physical employment standards; Physical capacity |
| Courtney et al. [10] | Original research | Quantitative | Cross sectional study | Paramedic | Physical activity; Physical health |
| Courtney et al. [13] | Original research | Quantitative | Cross sectional study | Paramedic | Physical health |
| Edwards et al. [78] | Original research | Mixed-method | Observational study | Paramedic | Physical fitness; Physical health |
| Edwards et al. [79] | Original research | Quantitative | Cross sectional study | Paramedic | Physical fitness; Physical capacity; Physical activity; Physical health |
| Fischer et al. [66] | Original research | Quantitative | Cross sectional study | Paramedic | Pre-employment fitness testing; Physical employment standards |
| Gamble et al. [57] | Original research | Quantitative | Cross sectional study | Paramedic | Physical fitness; Physical employment standards; Physical capacity |
| Gayton & Lovell [86] | Original research | Quantitative | Cross sectional study | Paramedic; Student paramedic | Physical health |
| Hunter et al. [58] | Original research | Quantitative | Cross sectional study | Paramedic | Physical fitness; Physical health |
| Hunter et al. [59] | Original research | Quantitative | Cross sectional study | Paramedic | Physical fitness; Physical health |
| Hunter et al. [60] | Original research | Quantitative | Cross sectional study | Paramedic | Physical fitness; Physical capacity |
| Hunter et al. [82] | Original research | Quantitative | Cross sectional study | Paramedic | Physical fitness; Physical health |
| Jenkins et al. [5] | Original research | Quantitative | Other | Paramedic | Pre-employment fitness testing; Physical capacity |
| Khan et al. [63] | Original research | Quantitative | Cross sectional study | Paramedic | Physical activity; Physical health |
| MacQuarrie et al. [15] | Original research | Mixed-method | Cross sectional study | Paramedic | Physical fitness; Physical activity; Physical health |
| MacQuarrie A. [54] | Original research | Quantitative | Other | Paramedic | Physical fitness; Physical activity; Physical health |
| Malone et al. [73] | Original research | Quantitative | Cross sectional study | Paramedic; Student paramedic | Pre-employment fitness testing; Physical employment standards; Physical capacity |
| Malone, A. [74] | Original research | Quantitative | Cross sectional study | Paramedic | Pre-employment fitness testing; Physical capacity |
| Marsh et al. [6] | Original research | Quantitative | Scoping Review | Paramedic | Physical fitness; Physical capacity; Physical health |
| Meadley, B. [83] | Original research | Quantitative | Cross sectional study | Paramedic | Physical fitness; Physical capacity; Physical activity; Physical health |
| Mthombeni et al. [53] | Original research | Quantitative | Cross sectional study | Paramedic | Physical fitness; Pre-employment fitness testing; Physical fitness training; Physical capacity |
| Mthombeni, S. K. [76] | Original research | Mixed-method | Cross sectional study | Paramedic | Physical fitness; Pre-employment fitness testing; Physical capacity; Physical preparation |
| Mthombeni et al. [77] | Original research | Quantitative | Cross sectional study | Paramedic | Physical health |
| Phung et al. [61] | Original research | Qualitative | Qualitative—interviews; Other | Paramedic | Physical health |
| Rice et al. [62] | Original research | Mixed-method | Cross sectional study; Qualitative—interviews | Paramedic | Physical health |
| Rodgers [67] | Original research | Quantitative | Cohort study | Paramedic | Physical fitness; Physical health |
| Sawyer et al. [81] | Review article | Mixed-method | Systematic literature review | Paramedic | Physical health |
| Sheridan [11] | Review article | Mixed-method | Systematic literature review | Paramedic | Physical fitness; Pre-employment fitness testing; Physical employment standards; Physical capacity; Physical health |
| Waack et al. [65] | Original research | Quantitative | Cross sectional study | Paramedic | Pre-employment fitness testing; Physical employment standards; Physical capacity |
References
- Coffey, B.; MacPhee, R.; Socha, D.; Fischer, S.L. A physical demands description of paramedic work in Canada. Int. J. Ind. Ergon. 2016, 53, 355–362. [Google Scholar] [CrossRef] [Scilit]
- Coffey, B.F.; MacPhee, R.S.; Fischer, S. Paramedic Physical Demands Analysis; Paramedic Association of Canada: Ottawa, Canada, 2014. [Google Scholar]
- Morales, L.; McEachern, B.M.; MacPhee, R.S.; Fischer, S.L. Patient acuity as a determinant of paramedics’ frequency of being exposed to physically demanding work activities. Appl. Ergon. 2016, 56, 187–193. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kearney, J.; Muir, C.; Smith, K. Occupational injury among paramedics: A systematic review. Inj. Prev. 2022, 28, 175–184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jenkins, N.; Smith, G.; Stewart, S.; Kamphuis, C. Pre-Employment physical capacity testing as a predictor of musculoskeletal injury in Victorian paramedics. Work 2021, 70, 263–270. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marsh, E.; Orr, R.; Canetti, E.F.D.; Schram, B. Profiling paramedic job tasks, injuries, and physical fitness: A scoping review. Appl. Ergon. 2025, 125, 104459. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maguire, B.J.; O’Meara, P.F.; Brightwell, R.F.; O’Neill, B.J.; Fitzgerald, G.J. Occupational injury risk among Australian paramedics: An analysis of national data. Med. J. Aust. 2014, 200, 477–480. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reichard, A.A.; Jackson, L.L. Occupational injuries among emergency responders. Am. J. Ind. Med. 2010, 53, 1–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roberts, M.H.; Sim, M.R.; Black, O.; Smith, P. Occupational injury risk among ambulance officers and paramedics compared with other healthcare workers in Victoria, Australia: Analysis of workers’ compensation claims from 2003 to 2012. Occup. Environ. Med. 2015, 72, 489–495. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Courtney, J.A.; Francis, A.J.P.; Paxton, S.J. Caring for the carers: Fatigue, sleep, and mental health in Australian paramedic shiftworkers. Aust. N. Z. J. Organ. Psychol. 2012, 3, 32–41. [Google Scholar]
- Sheridan, S. Paramedic health status, fitness and physical tasks: A review of the literature. Australas. J. Paramed. 2019, 16, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Hegg-Deloye, S.; Brassard, P.; Jauvin, N.; Prairie, J.; Larouche, D.; Poirier, P.; Tremblay, A.; Corbeil, P. Current state of knowledge of post-traumatic stress, sleeping problems, obesity and cardiovascular disease in paramedics. Emerg. Med. J. 2014, 31, 242–247. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Courtney, J.A.; Francis, A.J.; Paxton, S.J. Caring for the country: Fatigue, sleep and mental health in Australian rural paramedic shiftworkers. J. Community Health 2013, 38, 178–186. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thornton, K.E.; Sayers, M.G. Unfit for duty? Evaluation of 4 years of paramedic pre-employment fitness screening test results. Prehosp. Emerg. Care 2014, 18, 201–206. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- MacQuarrie, A.J.; Robertson, C.; Micalos, P.; Crane, J.; High, R.; Drinkwater, E.; Wickham, J. Fit for duty: The health status of New South Wales Paramedics. Ir. J. Paramed. 2018, 3, 1–10. [Google Scholar] [CrossRef] [Scilit]
- Tsismenakis, A.J.; Christophi, C.A.; Burress, J.W.; Kinney, A.M.; Kim, M.; Kales, S.N. The obesity epidemic and future emergency responders. Obesity 2009, 17, 1648–1650. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ras, J.; Soteriades, E.S.; Smith, D.L.; Kengne, A.P.; Leach, L. Association between physical fitness and musculoskeletal health in firefighters. Front. Physiol. 2023, 14, 1210107. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Orr, R.M.; Cohen, B.S.; Allison, S.C.; Bulathsinhala, L.; Zambraski, E.J.; Jaffrey, M. Models to predict injury, physical fitness failure and attrition in recruit training: A retrospective cohort study. Mil. Med. Res. 2020, 7, 26. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pope, R.P.; Herbert, R.; Kirwan, J.D.; Graham, B.J. Predicting attrition in basic military training. Mil. Med. 1999, 164, 710–714. [Google Scholar] [CrossRef] [Scilit]
- Holtzclaw, L.; Arlinghaus, K.R.; Johnston, C.A. The Health of Health Care Professionals. Am. J. Lifestyle Med. 2021, 15, 130–132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Melnyk, B.M.; Tan, A.; Hsieh, A.P.; Gawlik, K.; Arslanian-Engoren, C.; Braun, L.T.; Dunbar, S.; Dunbar-Jacob, J.; Lewis, L.M.; Millan, A.; et al. Critical Care Nurses’ Physical and Mental Health, Worksite Wellness Support, and Medical Errors. Am. J. Crit. Care 2021, 30, 176–184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Timmermann, A.; Russo, S.G.; Hollmann, M.W. Paramedic versus emergency physician emergency medical service: Role of the anaesthesiologist and the European versus the Anglo-American concept. Curr. Opin. Anaesthesiol. 2008, 21, 222–227. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Williams, B.; Beovich, B.; Olaussen, A. The Definition of Paramedicine: An International Delphi Study. J. Multidiscip. Healthc. 2021, 14, 3561–3570. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ahpra & National Boards. About Registration. 2025. Available online: https://www.ahpra.gov.au/Registration.aspx (accessed on 3 October 2026).
- Paramedicine Board of Australia. Professional capabilities for registered paramedics. In Professional Capabilities for Registered Paramedics; Paramedicine Board of Australia: Melbourne, Australia, 2021. [Google Scholar]
- O’Meara, P.; Duthie, S. Paramedicine in Australia and New Zealand: A comparative overview. Aust. J. Rural Health 2018, 26, 363–368. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Te Kaunihera Manapou|Paramedic Council. Standards of Cultural Safety and Clinical Competence for Paramedics; Paramedic Council: Wellington, New Zealand, 2020. Available online: https://www.paramediccouncil.org.nz/common/Uploaded%20files/Continuing%20Competence/Paramedic%20Council%20Standards%20of%20Cultural%20Safety%20and%20Clinical%20Competence.pdf (accessed on 3 October 2025).
- Te Kaunihera Manapou Paramedic Council. Ngā Paerewa Standards; Paramedic Council of New Zealand: Wellington, New Zealand, 2025. Available online: https://www.paramediccouncil.org.nz/PCNZ/PCNZ/0.Te-Tiriti/Standards-.aspx?hkey=b0703e01-2e36-4307-adf7-3a2f1e8bc301 (accessed on 3 October 2025).
- Health & Care Professions Council. Standards: HCPC. 2025. Available online: https://www.hcpc-uk.org/standards/ (accessed on 3 October 2025).
- Health Professions Council of South Africa. Registration Requirements. 2025. Available online: https://www.hpcsa.co.za/page/registration-requirements (accessed on 3 October 2025).
- Association of Ambulance Chief Executives. Structure of the UK Ambulance Services. 2025. Available online: https://aace.org.uk/uk-ambulance-service/ (accessed on 3 October 2025).
- National Audit Office. NHS Ambulance Services; The Stationery Office: Norwich, UK, 2017.
- Government of Canada. About Canada’s Health Care System. 2025. Available online: https://www.canada.ca/en/health-canada/services/canada-health-care-system.html (accessed on 3 October 2025).
- Tucker, J.-M.; Chalkidou, K.; Pillay, Y. Establishing the NHI Service Benefits Framework: Lessons Learnt and Stakeholder Engagement. 2019. Available online: https://journals.co.za/doi/pdf/10.10520/EJC-1d2aad4a4c (accessed on 3 October 2025).
- Canadian Organisation of Paramedic Regulators. Provincial EMR and Paramedic Regulators. 2025. Available online: https://copr.ca/about-canadian-organization-of-paramedic-regulators/jurisdiction/ (accessed on 3 October 2025).
- South African Government. Provinces: Republic of South Africa. 2025. Available online: https://www.gov.za/provinces (accessed on 3 October 2025).
- Eastern Cape Department of Health. Eastern Cape Department of Health; Province of the Eastern Cape Health: Bhisho, South Africa, 2025. Available online: https://provincialgovernment.co.za/units/view/3/eastern-cape/health (accessed on 3 October 2025).
- Pre-Hospital Emergency Care Council. Register. 2017. Available online: https://www.phecit.ie/PHECC/The_register/PHECC/The_Register/Register.aspx (accessed on 3 October 2025).
- Sheridan, S.; Pope, R.; MacQuarrie, A.J.; MacPhee, R.S.; Rayner, R.; Stack, H.; Rose, L.; Fischer, S. The physical preparation of paramedicine students for the paramedic role: A scoping review. Paramedicine 2026, 23, 121–133. [Google Scholar] [CrossRef] [Scilit]
- Drain, J.R.; Reilly, T.J. Physical employment standards, physical training and musculoskeletal injury in physically demanding occupations. Work 2019, 63, 495–508. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jamnik, V.; Gumienak, R.; Gledhill, N. Developing legally defensible physiological employment standards for prominent physically demanding public safety occupations: A Canadian perspective. Eur. J. Appl. Physiol. 2013, 113, 2447–2457. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beck, B.; Billing, D.C.; Carr, A.J. Developing physical and physiological employment standards: Translation of job analysis findings to assessments and performance standards–A systematic review. Int. J. Ind. Ergon. 2016, 56, 9–16. [Google Scholar] [CrossRef] [Scilit]
- Adams, E.M. Human rights at work: Physical standards for employment and human rights law. Appl. Physiol. Nutr. Metab. 2016, 41, S63–S73. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.J.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMA-ScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aromataris, E.; Munn, Z. JBI Manual for Evidence Synthesis; JBI: Adelaide, Australia, 2024. [Google Scholar]
- World Health Organization. Physical Activity. 2025. Available online: https://www.who.int/news-room/fact-sheets/detail/physical-activity (accessed on 10 June 2025).
- Caspersen, C.J.; Powell, K.E.; Christenson, G.M. Physical activity, exercise, and physical fitness: Definitions and distinctions for health-related research. Public Health Rep. 1985, 100, 126–131. [Google Scholar] [PubMed]
- World Health Organization (Ed.) Ottawa charter for health promotion. In Proceedings of the First International Health Promotion Conference, Ottawa, ON, Canada, 21 November 1986. [Google Scholar]
- Pollock, D.; Peters, M.D.J.; Khalil, H.; McInerney, P.; Alexander, L.; Tricco, A.C.; Evans, C.; de Moraes, É.B.; Godfrey, C.M.; Pieper, D.; et al. Recommendations for the extraction, analysis, and presentation of results in scoping reviews. JBI Evid. Synth. 2023, 21, 520–532. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McGowan, J.; Sampson, M.; Salzwedel, D.M.; Cogo, E.; Foerster, V.; Lefebvre, C. PRESS Peer Review of Electronic Search Strategies: 2015 Guideline Statement. J. Clin. Epidemiol. 2016, 75, 40–46. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Elo, S.; Kyngas, H. The qualitative content analysis process. J. Adv. Nurs. 2008, 62, 107–115. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mthombeni, S.; Coopoo, Y.; Noorbhai, H. Physical health status of emergency care providers in South Africa. Asian J. Sports Med. 2020, 11, e100261. [Google Scholar] [CrossRef] [Scilit]
- MacQuarrie, A. Fit for Duty: Context and Correlates of Paramedic Health Status and Job Performance. Ph.D. Thesis, Charles Sturt University, Bathurst, Australia, 2018. [Google Scholar]
- Chapman, D.; Peiffer, J.; Abbiss, C.; Laursen, P. A descriptive physical profile of Western Australian male paramedics. Australas. J. Paramed. 2007, 5, 1–11. [Google Scholar] [CrossRef] [Scilit]
- Courtney, J.A. Fatigue and Mental Health in Ambulance Paramedic Shiftworkers. Ph.D. Thesis, La Trobe University, Melbourne, Australia, 2010. [Google Scholar]
- Gamble, R.P.; Stevens, A.B.; McBrien, H.; Black, A.; Cran, G.W.; Boreham, C.A. Physical fitness and occupational demands of the Belfast ambulance service. Br. J. Ind. Med. 1991, 48, 592–596. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hunter, J.; Sheridan, S.; MacQuarrie, A.; High, R.; Waite, C.; Smith, K.; Thomas, J.; Wheat, J. (Eds.) The health and fitness of paramedics in regional New South Wales: A need for intervention? In Proceedings of the Western NSW Health Research Network (WHRN) Conference, Orange, Australia, 16–17 August 2018. [Google Scholar]
- Hunter, J.; MacQuarrie, A.; Sheridan, S.; High, R.; Waite, C.; Smith, K.; Thomas, J.; Wheat, J. (Eds.) Responding for life: Current health and fitness status of Australian paramedics. In Proceedings of the Exercise and Sports Science Australia, Research to Practice, Brisbane, Australia, 27–29 March 2018. [Google Scholar]
- Hunter, J.; MacQuarrie, A.; Sheridan, S.; High, R.; Waite, C.; Smith, K.; Thomas, J.; Wheat, J. (Eds.) Health and fitness status of Australian paramedics: A Cause for Concern. In Proceedings of the Health, Wellness & Society Conference, London, UK, 20–21 September 2018. [Google Scholar]
- Phung, V.H.; Sanderson, K.; Pritchard, G.; Bell, F.; Hird, K.; Wankhade, P.; Asghar, Z.; Siriwardena, N. The experiences and perceptions of wellbeing provision among English ambulance services staff: A multi-method qualitative study. BMC Health Serv. Res. 2022, 22, 1352. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rice, V.; Glass, N.; Ogle, K.; Parsian, N. Exploring physical health perceptions, fatigue and stress among health care professionals. J. Multidiscip. Healthc. 2014, 7, 155–161. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khan, W.A.A.; Jackson, M.L.; Kennedy, G.A.; Conduit, R. A field investigation of the relationship between rotating shifts, sleep, mental health and physical activity of Australian paramedics. Sci. Rep. 2021, 11, 866. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coffey, B.; Fischer, S.; MacPhee, R. Canadian Safety and Security Program—Physical Demands Analysis; Queen’s University: Kingston, ON, Canada, 2014. [Google Scholar]
- Waack, J.; Meadley, B.; Gosling, C. Comparison of physical demanding paramedic work tasks between an Australian and Canadian ambulance service. Appl. Ergon. 2023, 106, 103905. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fischer, S.L.; Sinden, K.E.; MacPhee, R.S.; Ottawa Paramedic Service Research, T. Identifying the critical physical demanding tasks of paramedic work: Towards the development of a physical employment standard. Appl. Ergon. 2017, 65, 233–239. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rodgers, L.M. A five-year study comparing early retirements on medical grounds in ambulance personnel with those in other groups of health service staff. Occup. Med. 1998, 48, 7–16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reuter, E.; Camba, J.D. Understanding emergency workers’ behavior and perspectives on design and safety in the workplace. Appl. Ergon. 2017, 59, 73–83. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jenkins, N.; Smith, G.; Stewart, S.; Kamphuis, C. Pre-employment physical capacity testing as a predictor for musculoskeletal injury in paramedics: A review of the literature. Work 2016, 55, 565–575. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Armstrong, D.P.; Ross, G.B.; Graham, R.B.; Fischer, S.L. Considering movement competency within physical employment standards. Work 2019, 63, 603–613. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Armstrong, D.P.; Sinden, K.E.; Sendsen, J.; MacPhee, R.S.; Fischer, S.L. Evaluating the effect of a strength and conditioning program to improve paramedic candidates’ physical readiness for duty. Work 2019, 63, 623–633. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Armstrong, D.P.; Sinden, K.E.; Sendsen, J.; MacPhee, R.S.; Fischer, S.L. The Ottawa Paramedic Physical Ability Test: Test-retest reliability and analysis of sex-based performance differences. Ergonomics 2019, 62, 1033–1042. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Malone, A.L.; Armstrong, D.P.; MacPhee, R.S.; Fischer, S.L. Factors influencing the likelihood of females passing the Ottawa paramedic physical ability test. Appl. Ergon. 2024, 116, 104187. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Malone, A.L. Identifying Determinants of Performance for Females Completing a Paramedic Physical Employment Test. Master’s Thesis, University of Waterloo, Waterloo, ON, Canada, 2023. [Google Scholar]
- Armstrong, D.P.; Beach, T.A.C.; Fischer, S.L. The Influence of Contextual and Theoretical Expertise on Generic and Occupation-Specific Lifting Strategy. Hum. Factors 2024, 66, 2590–2605. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mthombeni, S.K. Correlation Between a Fitness Test Battery and an Occupation-Specific Rescue Simulation for Emergency Care Providers. Master’s Thesis, University of Johannesburg, Johannesburg, South Africa, 2018. [Google Scholar]
- Mthombeni, S.; Coopoo, Y.; Noorbhai, H. Correlation between fitness parameters and an occupational rescue simulation among emergency care providers in North West province, South Africa: A pilot study. Australas. J. Paramed. 2021, 18, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Edwards, C.M.; Puranda, J.L.; Miller, É.; MacDonald, M.L.; Aboudlal, M.; Adamo, K.B. Low physical fitness indicates future injury, mental health, menstrual cycle disruptions, and burnout in female emergency service personnel and healthcare providers. Appl. Physiol. Nutr. Metab. 2025, 50, 1–7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Edwards, C.M.; Puranda, J.L.; Miller, É.; Aboudlal, M.; O’Rourke, N.; MacDonald, M.L.; Adamo, K.B. Musculoskeletal Injuries, Exercise Behaviors, and Reproductive Health Are Related to Physical Fitness of Female First-Responders and Health Care Providers. Women’s Health Rep. 2024, 5, 393–403. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reed, A. Cycle response unit paramedics. J. Paramed. Pract. 2012, 4, 608–610. [Google Scholar] [CrossRef] [Scilit]
- Sawyer, S.; Cowlishaw, S.; Kendrick, K.; Boyle, M.; Dicker, B.; Lord, B. Systematic Review of Incidence, Prevalence, and Trends in Health Outcomes for Australian and New Zealand Paramedics. Prehosp. Emerg. Care 2023, 27, 398–412. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hunter, J.R.; Macquarrie, A.J.; Sheridan, S.C. Physical capacity of New South Wales ambulance paramedics. Occup. Med. 2019, 69, 534–540. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meadley, B.; Wolkow, A.P.; Smith, K.; Perraton, L.; Bowles, K.A.; Bonham, M.P. Cardiometabolic, Dietary and Physical Health in Graduate Paramedics during the First 12-Months of Practice—A Longitudinal Study. Prehosp. Emerg. Care 2022, 26, 524–536. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xia, T.; Collie, A. Work-related injury and illness in the Victorian healthcare sector: A retrospective analysis of workers’ compensation claim records. Aust. Health Rev. 2020, 44, 24–30. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gray, S.; Collie, A. The nature and burden of occupational injury among first responder occupations: A retrospective cohort study in Australian workers. Injury 2017, 48, 2470–2477. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gayton, S.D.; Lovell, G.P. Resilience in ambulance service paramedics and its relationships with well-being and general health. Traumatology 2012, 18, 58–64. [Google Scholar] [CrossRef] [Scilit]
- Baum, J.; Hendricks, S.-M.; Lanier, D. A Holistic Review of the Health and Wellness Programs of Victorian Emergency Services. Bachelor’s Thesis, Worcester Polytechnic Institute, Worcester, MA, USA, 2011. [Google Scholar]
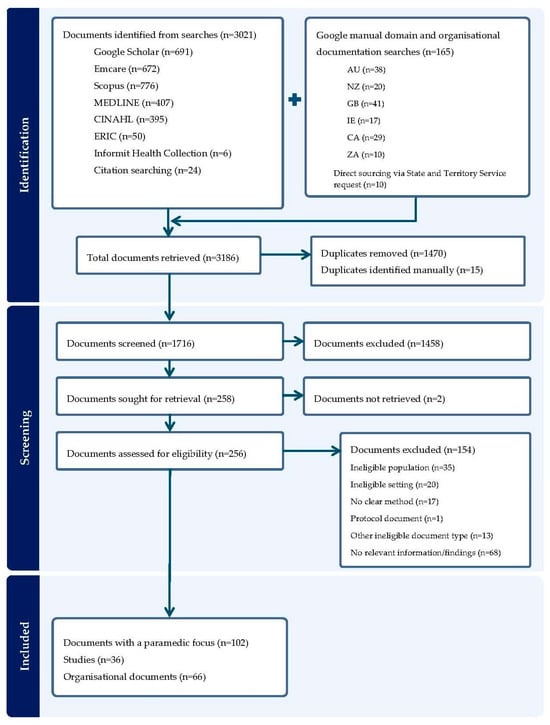
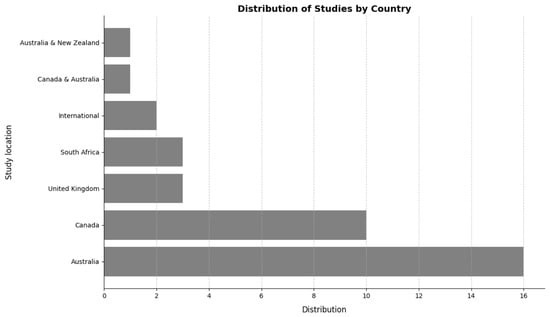
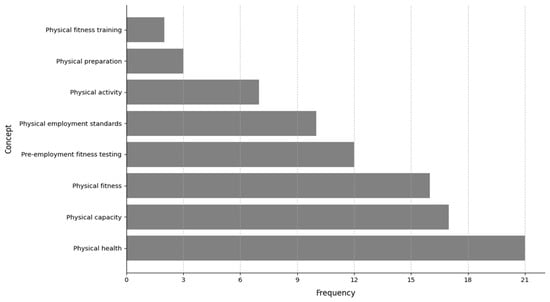

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.