


Abstract
Background: Stackable metallic or magnetic multi-template systems translate a prosthetically (facially) driven plan into each surgical phase of full-arch rehabilitation. Our objective was to map and critically describe the clinical applications, accuracy, and short-term outcomes of stackable/sequential guides and to illustrate the operational steps with a standardized magnet-retained case. Methods: Following a prospectively registered protocol (OSF, June 2025), we performed a scoping review in accordance with and PRISMA guidance. PubMed, Scopus and Embase were searched to 26 June 2025 for primary human studies using stackable or sequential static guides to place ≥4 implants per arch with immediate (≤72 h) loading. Duplicate-independent screening and data-charting captured guide design, planning platform, surgical accuracy, implant survival, prosthetic outcomes and patient-reported measures. A single non-analytic clinical vignette was included solely to illustrate the facially driven stackable workflow. Results: Eight studies (five countries, 2021–2025) encompassing 351 implants and one additional clinical case met the inclusion criteria. Mechanical indexing predominated (7/9 protocols); only two papers, including our case, used magnetic retention. Mean coronal and angular deviations, reported in two cohorts, were 0.95 mm/2.8° and 0.87 mm/2.67°, respectively—well within accepted thresholds for full-arch guided surgery. Immediate loading was achieved in 100% of arches; cumulative implant survival was 97.1% after 3–12 months. Patient-reported satisfaction exceeded 90 mm on VAS scales when measured. Our case demonstrated 0.90 mm/2.95° accuracy, 100% implant stability ≥ 35 N cm and uneventful provisionalisation at 12 weeks. Conclusions: Early clinical reports show clinically acceptable accuracy and high short-term survival with streamlined workflow. However, evidence remains heterogeneous and short-term; prospective multi-centre studies with standardized accuracy metrics, ≥3-year follow-up, validated PROMs, and cost-effectiveness analyses are still needed.
1. Introduction
Early systematic reviews of fixed full-arch therapy demonstrated that immediate loading could achieve implant survival rates above 99%, provided that insertion torque exceeds 30 N cm and splinted cross-arch support is used [1]. Subsequent accuracy studies of static computer-guided surgery reported mean 3D entry deviations of ~1 mm and angular discrepancies of ~5° in fully edentulous jaws [2,3], values generally considered clinically innocuous when a ≥2 mm safety margin to vital anatomy is respected and cross-arch splinting/prosthetic compensation is used [4]. More recently, additive manufacturing and selective laser melting (SLM) have enabled single-visit workflows in which the virtual prosthesis dictates bone reduction and implant positioning before the scalpel touches tissue [5]. These developments underpin a restorative-driven “facial design” philosophy whereby esthetics and phonetics are reverse-engineered first, then translated surgically with rigid reference frames that stay stable from incision to immediate provisionalisation.
Model-free sequential templates improve cumulative accuracy by keeping every surgical act referenced to the same fiducials. Baruffaldi’s model-free protocol showed 100% implant and prosthesis survival at one year across 11 edentulous patients when a single-reference jig guided both osteotomies and prosthetic pickup [6]. In this context, ‘model-free’ indicates that no printed/stone casts are used; instead, a screw-retained reference jig is fixed intraoperatively to stable bone and serves as a single fiducial throughout bone reduction, osteotomy drilling, and prosthetic pickup, thereby limiting cumulative error without intermediate models [6]. Debortoli et al. refined this concept with milled aluminum chassis that bolt together intra-operatively, reducing flexure under drill pressures [5]. Abdelaziz and Tella then demonstrated a fully printed stack with keyed male–female flanges that clip into place, permitting chairside interchange in <30 s [6]. Magnetically indexed connectors further shorten turnover times and provide audible seating verification; a 2024 case report using neodymium inserts achieved mean entry deviations of 0.90 mm and angular error of 2.95° while delivering a same-day prosthesis [7].
Despite enthusiastic adoption, the published body remains sparse. Lan and co-workers’ 2024 scoping review identified only 27 primary papers on stackable guides, with 63% limited to single-case reports and <10% offering ≥1-year biological outcomes [8]. Technical innovation is outpacing clinical validation: Bai et al. have already introduced cone-wedge metal anchors that cut coronal deviation below 1 mm even in dual-arch cases [9], while Ureel’s modular “jaw-in-a-day” system integrates oncologic resection, free-flap fixation and implant restoration in one theatre session [10]. Yet, prospective data on patient-reported outcome measures (PROMs) remain virtually absent. Alruhailie et al. quantified none beyond narrative satisfaction in their dual-arch immediate loading protocol [11].
Digital workflows promise reduced chair-time and higher esthetic certainty, but clinicians must weigh added laboratory costs against tangible benefits. A U.S. Navy review of digital full-arch rehabilitation estimated that stackable protocols shave 43 min from operative time compared with single-stent approaches, yet materials and printing raise per-case expenditure by ~USD 600 [12]. In a 43-arch cohort, Levy-Bohbot et al. reported 96.5% implant survival at four months and 100% prosthesis success at one year but acknowledged the absence of cost-effectiveness metrics [13]. Among geriatric maxillae, Monsalve-Guil’s guided-surgery audit achieved 100% survival over 53 months, albeit without stackable referencing, underscoring the need to isolate the incremental value of coupling templates [14,15,16,17].
Accordingly, this scoping review aims to (i) catalogue every clinical report employing stackable or sequential full-arch guides with immediate/early loading, (ii) detail guide construction (magnetic vs. mechanical), digital planning platforms and prosthetic protocols, (iii) chart surgical accuracy, survival and patient-centred outcomes, and (iv) highlight methodological limitations to inform robust future trials.
2. Materials and Methods
2.1. Scoping Review Framework
This scoping review was designed and reported in line with the Joanna Briggs Institute (JBI) Manual for Evidence Synthesis and the PRISMA-ScR checklist. A detailed protocol, including the a priori search strategy, eligibility criteria, and charting domains, was prospectively deposited in the Open Science Framework (OSF; registration code osf.io/wb5rk) on 18 June 2025, before any records were screened. The review followed the five-stage JBI process: (i) defining the research question; (ii) identifying relevant studies; (iii) selecting studies; (iv) charting data; and (v) collating, summarizing, and reporting the results. No amendments to the protocol were required. Because all data were drawn from the published literature, institutional ethics review was not sought.
2.2. Eligibility Criteria
Studies were eligible when they reported full-arch rehabilitation of completely edentulous or terminal-dentition jaws using stackable, modular, sequential or mechanically or magnetically indexed static guides fabricated by additive or subtractive manufacturing, when planning was prosthetically or facially driven, and when an immediate or very-early provisional restoration was delivered within seventy-two hours. Acceptable designs comprised randomized trials, prospective or retrospective cohorts, case series with at least two patients, single-case clinical reports and technical notes that included clinical execution. Exclusions encompassed in vitro or animal experiments, narrative reviews, opinion articles, workflows based solely on dynamic navigation, partial-arch treatments and protocols lacking immediate or very-early loading. Primary outcomes of interest were three-dimensional positional accuracy, implant survival, prosthetic success, patient-reported outcome measures, biologic complications and adverse events; secondary descriptors concerned guide-indexing mechanisms, planning software, laboratory workflow, insertion torque and follow-up duration.
2.3. Information Sources and Search Strategy
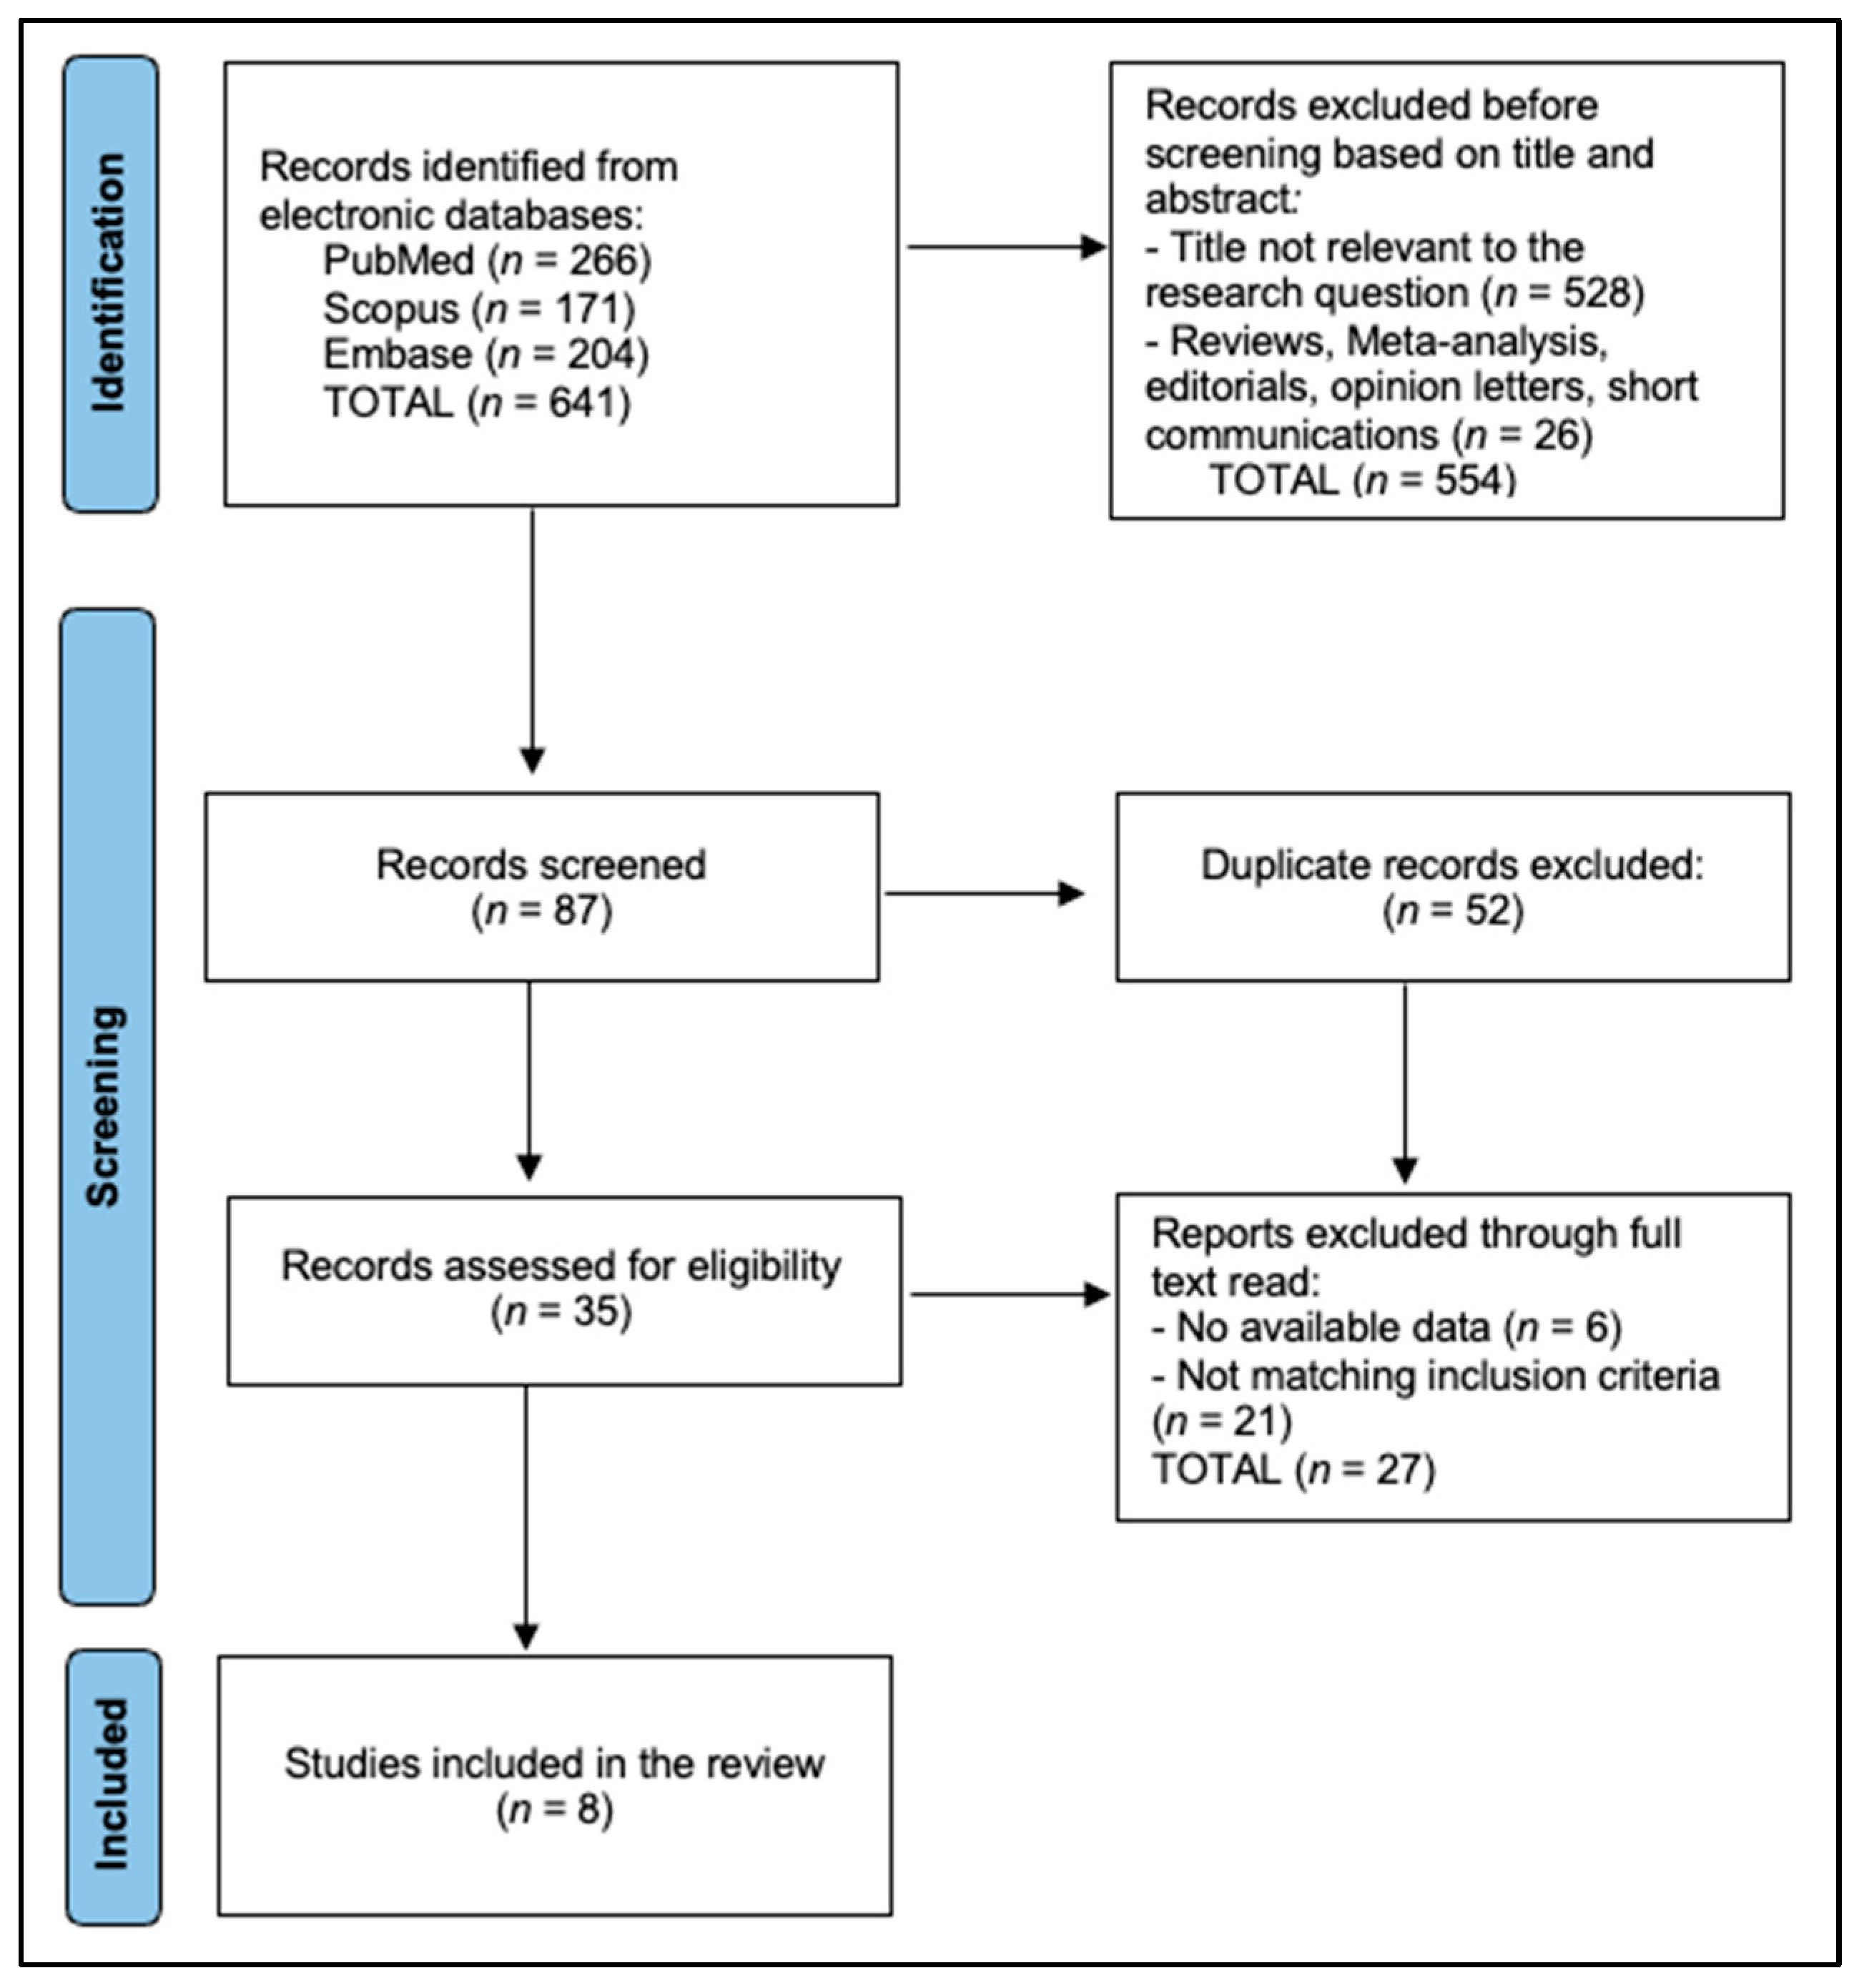
The PubMed strategy, combining MeSH and free-text terms (“stackable” OR “sequential template” OR “magnetic guide”) AND (“full arch” OR “edentulous”) AND (“implant”). The final search (26 June 2025) retrieved eight studies eligible for inclusion, as presented in Figure 1.
Figure 1.
PRISMA flowchart.
2.4. Study Selection and Data Extraction
Titles and abstracts were screened in Rayyan. Full texts were evaluated independently by two reviewers. A piloted Excel form captured: bibliometrics, patient/arch numbers, guide indexing method, planning software, implant count, deviations, loading protocol, follow-up, biological/prosthetic outcomes and patient-reported outcomes. Missing numerical data were coded “NR”.
2.5. Data Synthesis
Extracted variables were charted into three non-overlapping tables (study characteristics, surgical outcomes, prosthetic and patient-centred results). Descriptive statistics (ranges, medians) were calculated; no pooled effect measures were attempted. Narrative analysis explored (i) technology trends over time, (ii) relationship between guide type and accuracy, and (iii) reporting gaps. One clinical vignette was provided for didactic purposes and was prospectively excluded from eligibility screening, data extraction, and all analyses.
2.6. Protocols
VDO increase was determined pre-operatively by integrating digital smile design (incisal edge position and lip dynamics), phonetic testing (/s/ and /f/ sounds to maintain a 1–2 mm speaking space), and esthetic mid-face references. The proposed OVD was verified with a printed mock-up and intraoral try-in to confirm freeway space and patient comfort, then transferred to the stackable prosthetic verification guide for reproducible intraoperative mounting. Residual anterior roots were extracted atraumatically; sockets were debrided and conditioned.
3. Results
3.1. Clinical Vignette
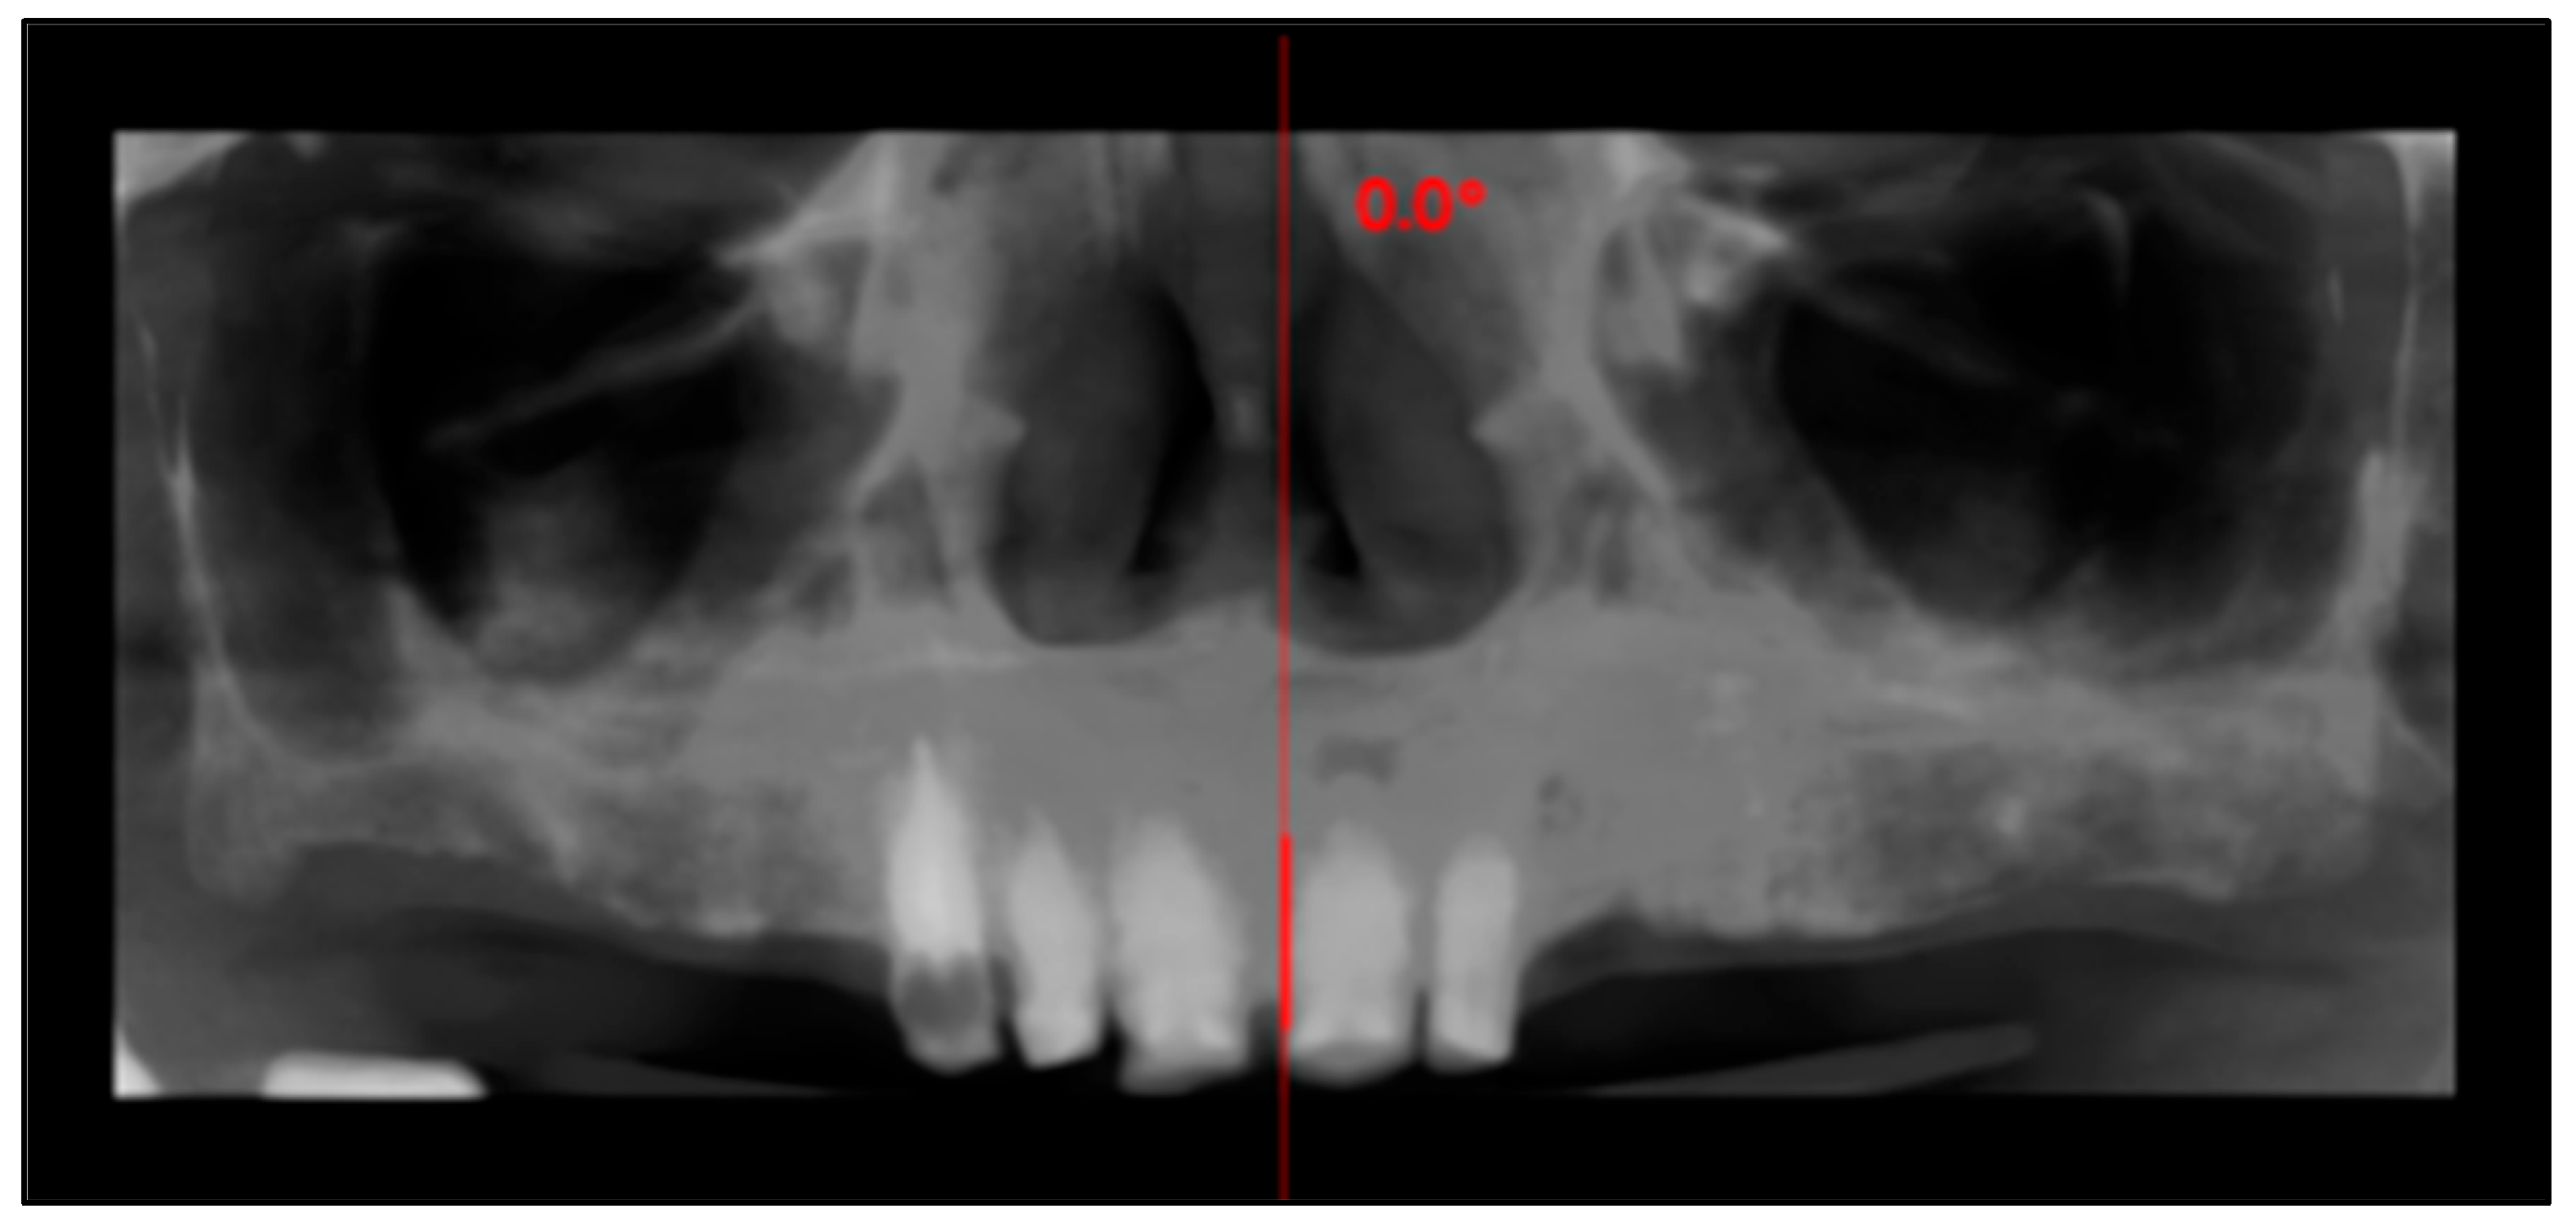
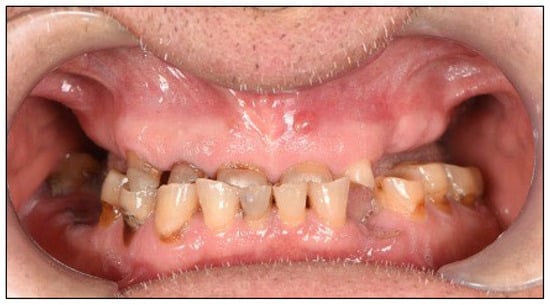
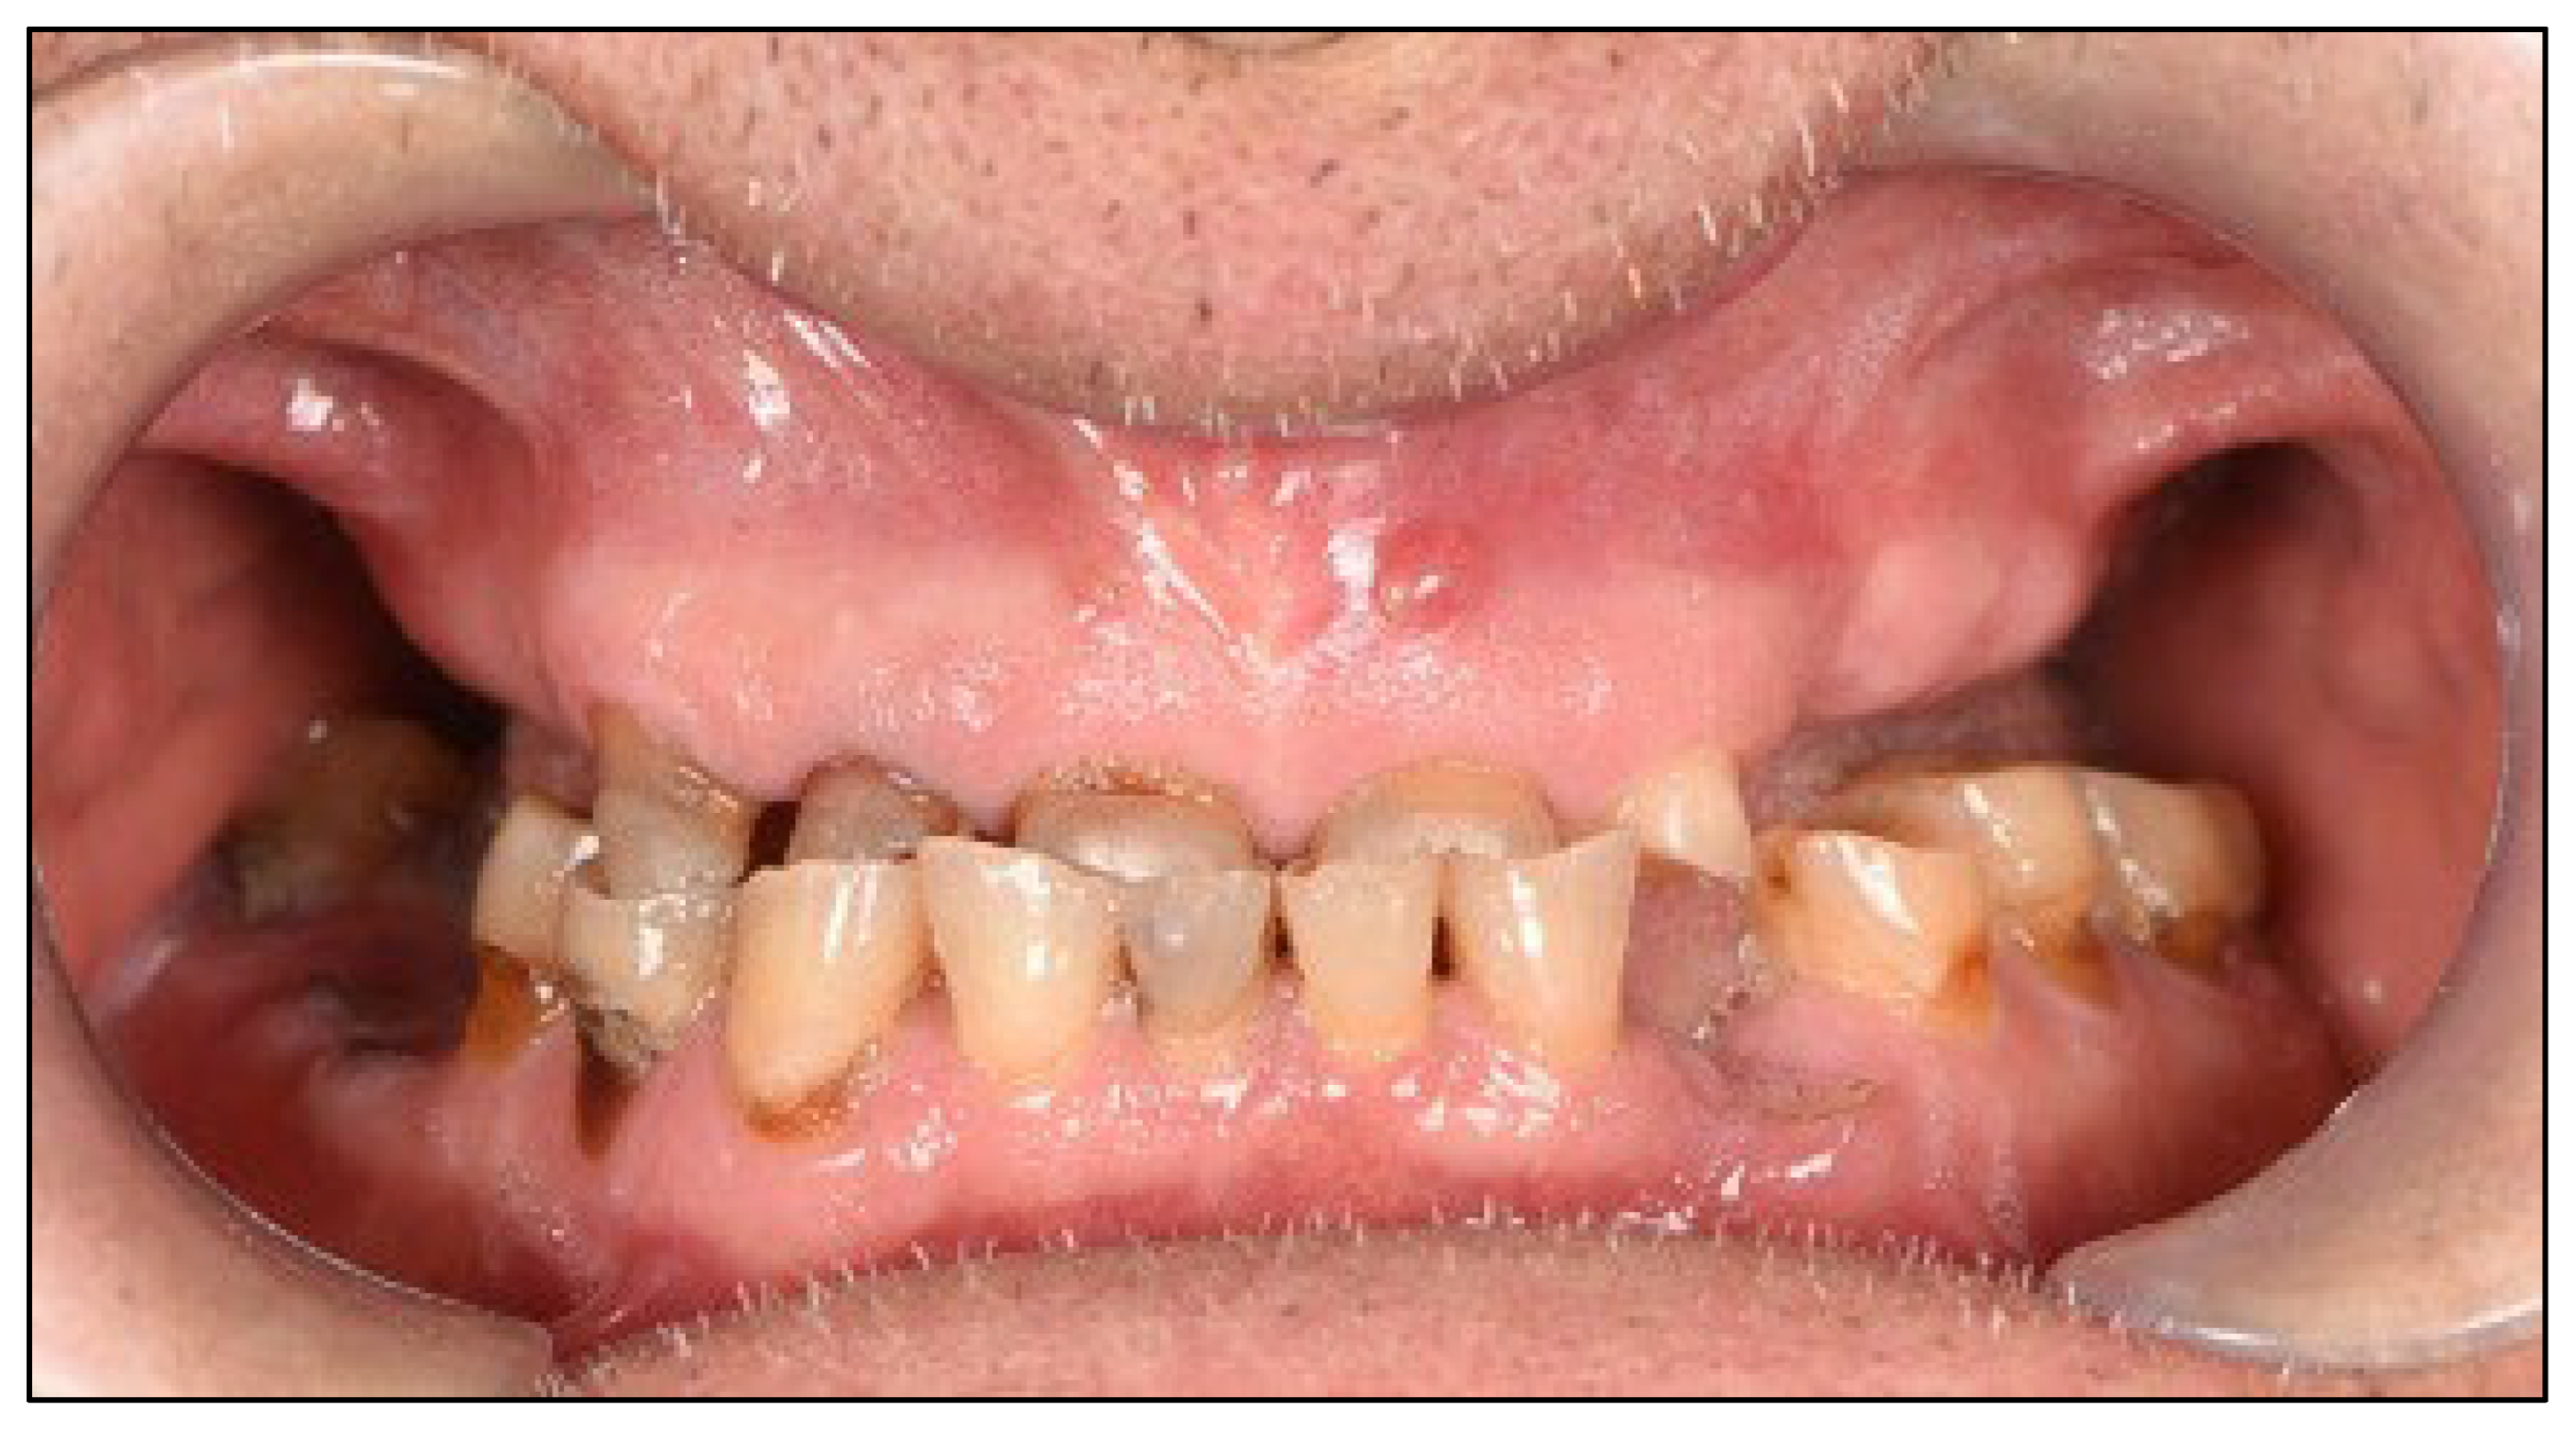
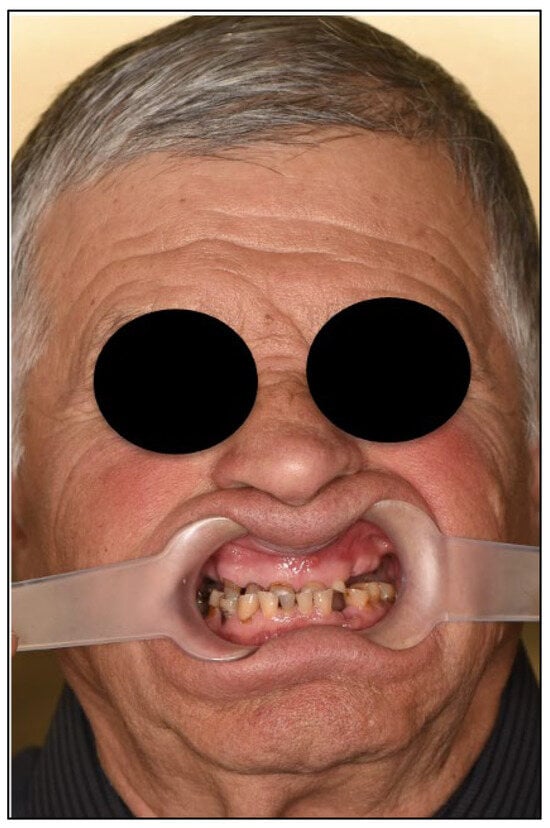
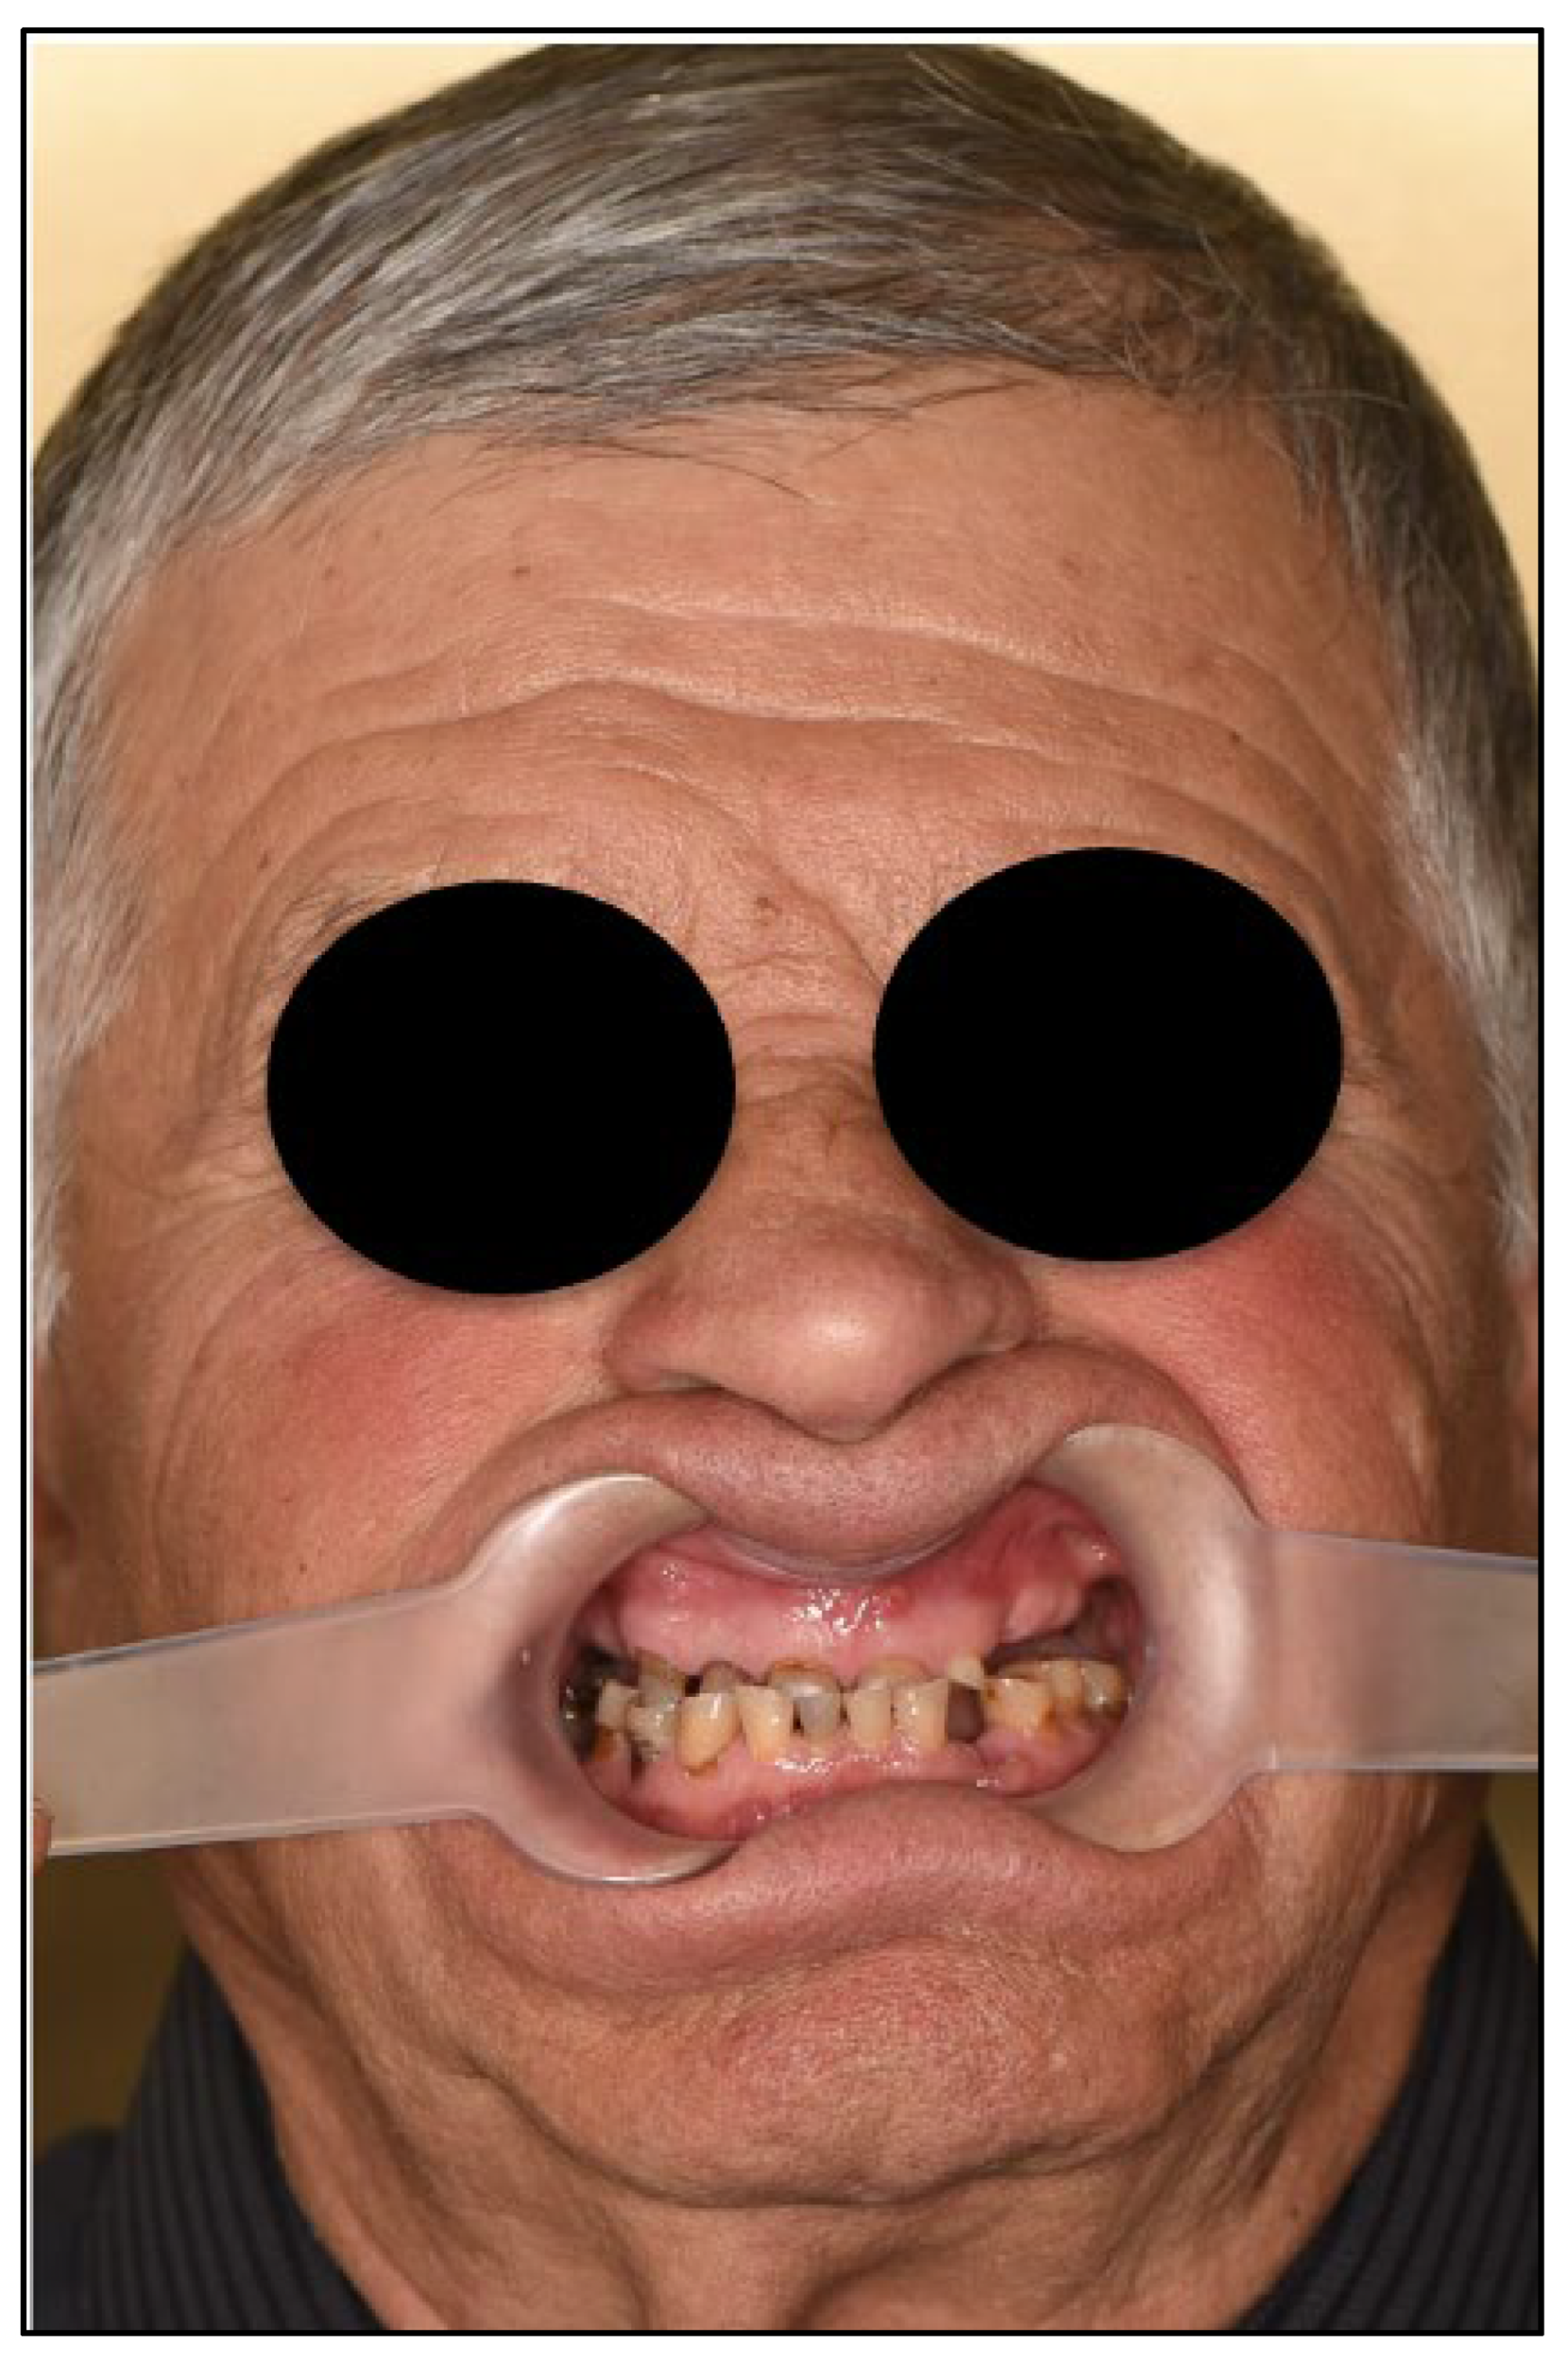
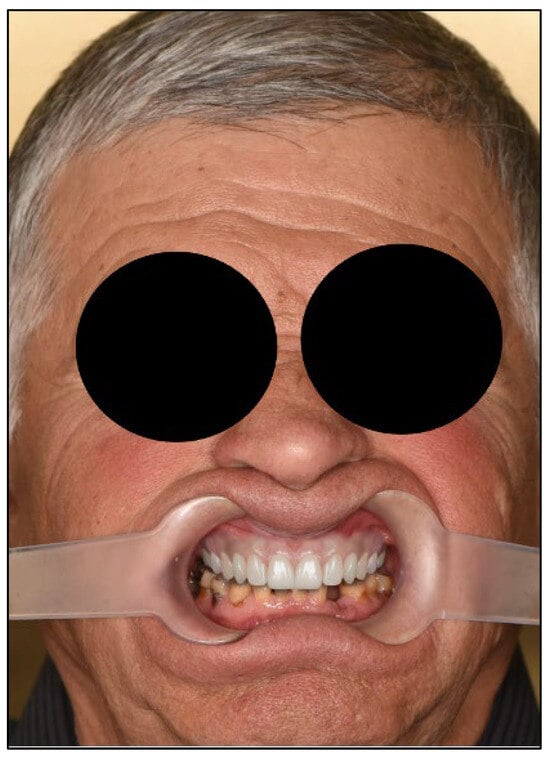
An 81-year-old male presented with complete loss of all lateral maxillary teeth and severe attrition of the remaining frontal teeth, worn to the root (Figure 2). The patient’s chief complaint was impaired function and dissatisfaction with the smile (Figure 3 and Figure 4).
Figure 2.
Panoramic reconstruction derived from the CBCT volume showing the initial situation.
Figure 3.
Frontal close-up photography. Upper remaining teeth present with severe tooth loss, lateral teeth absence impairs bite and function.
Figure 4.
Facial analysis. Extraoral photography with lip retractors to enhance view of the teeth.
The diagnosis was terminal-dentition maxilla with generalized severe attrition (probable parafunctional etiology), reduced occlusal vertical dimension (OVD), and impaired esthetics and function. Treatment plan consisted of atraumatic extraction of non-restorable anterior teeth, alveoloplasty to regularize the crest, placement of six implants using a magnet-retained stackable guide sequence, installation of multi-unit abutments, and immediate screw-retained PMMA provisionalisation. Where primary stability permitted, implants were placed immediately into fresh extraction sockets; in healed sites, implant positions followed the facially driven wax-up to optimize screw-access emergence
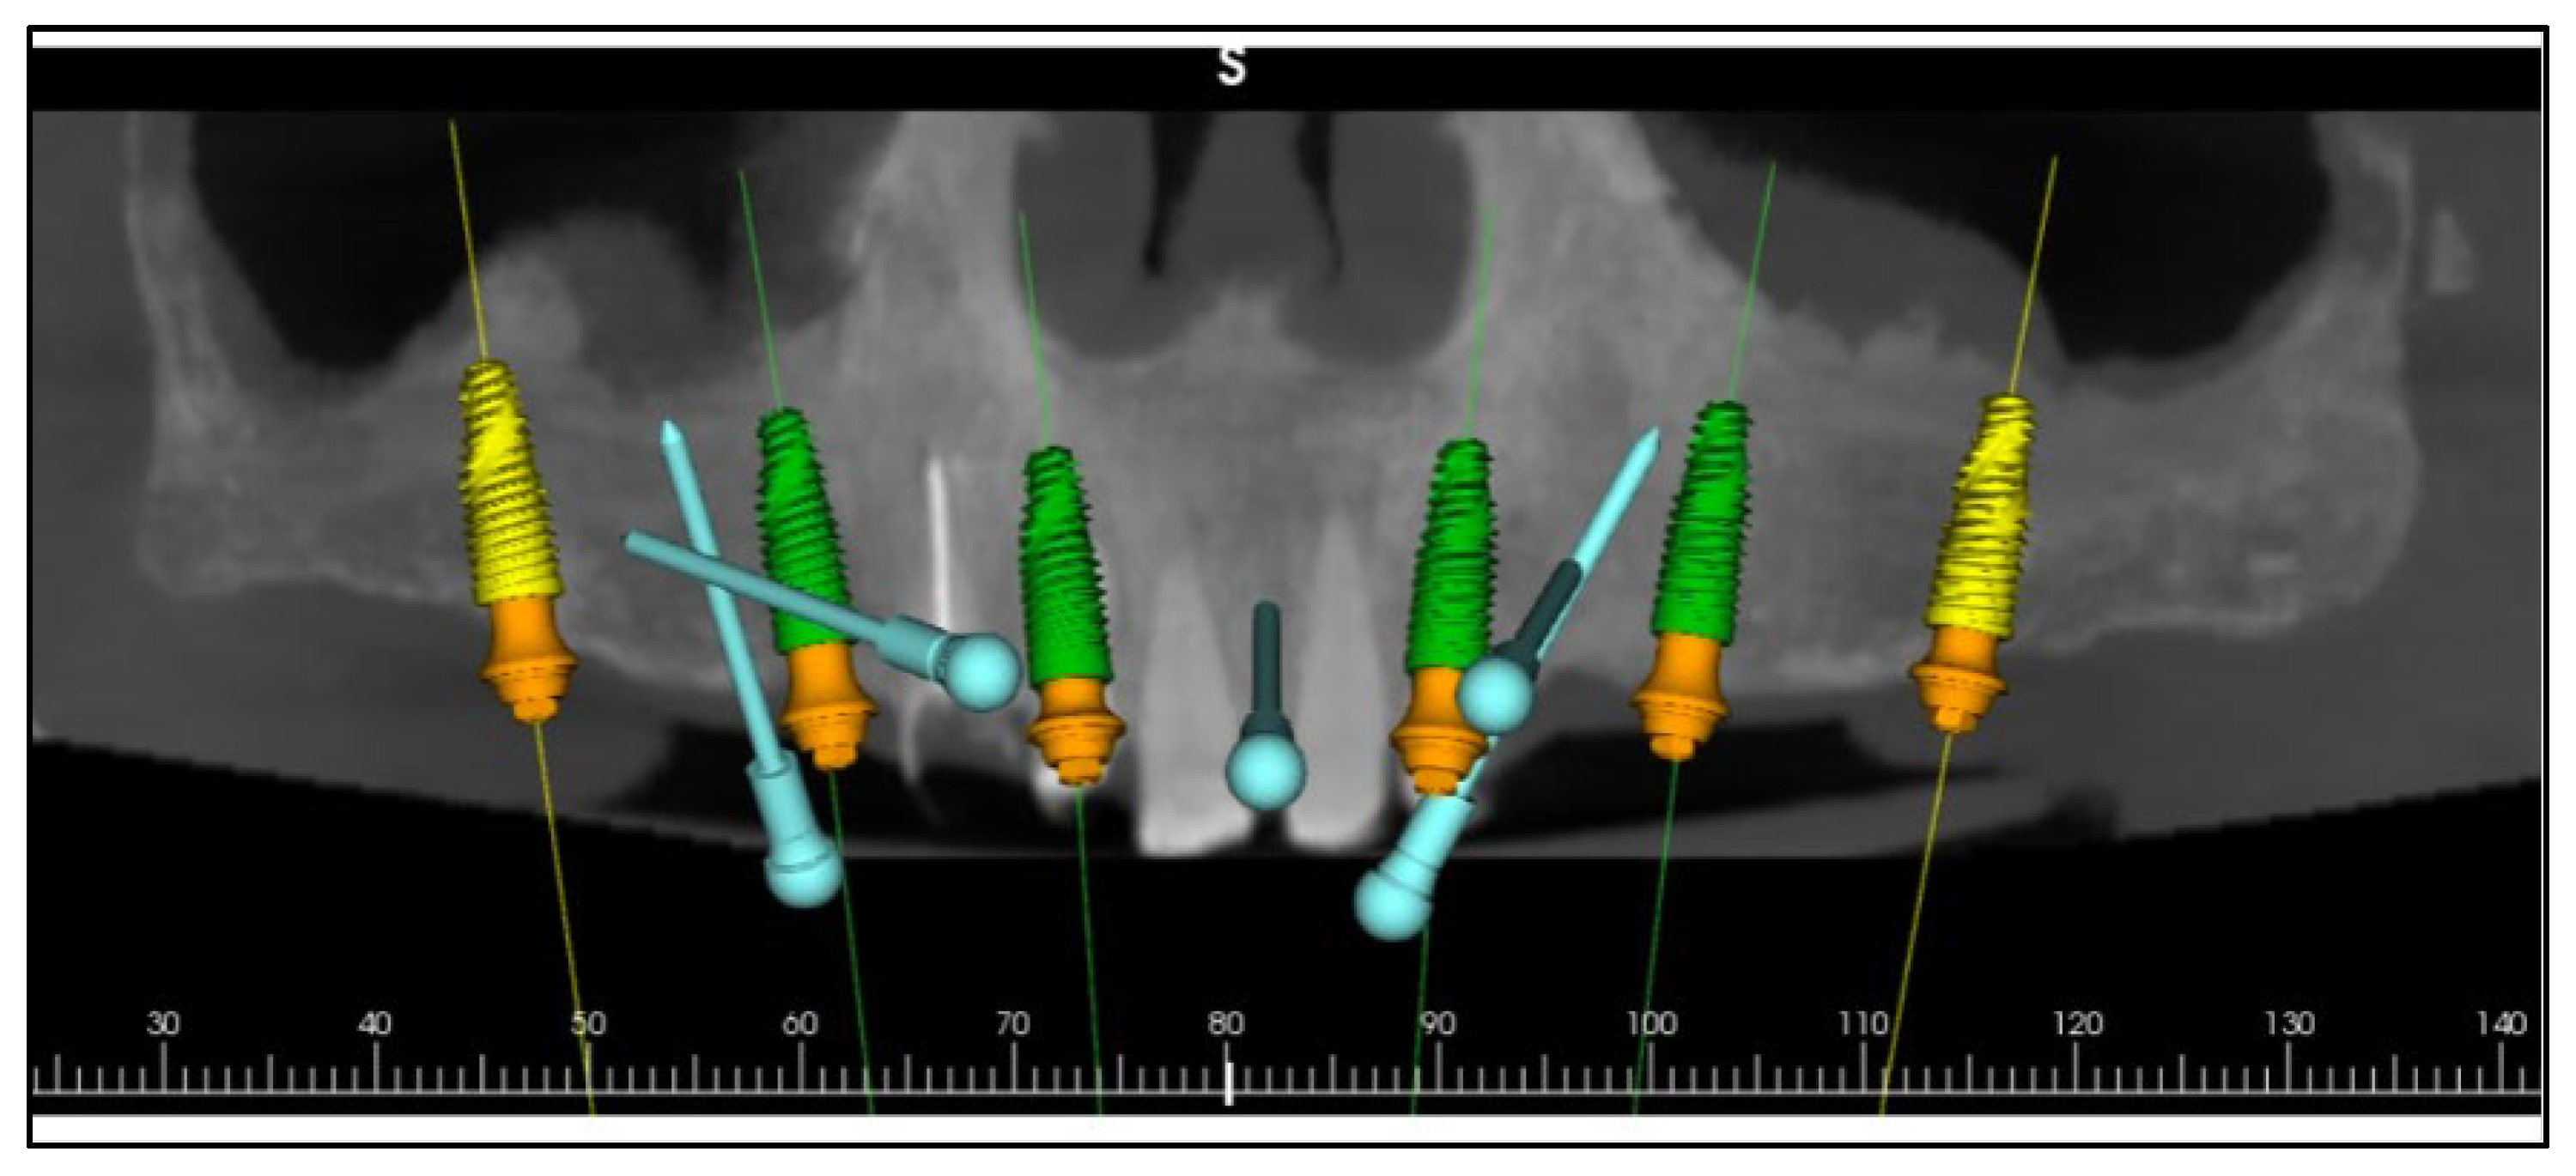
Comprehensive digital records were acquired, including intraoral scans, photographic series, and cone-beam computed tomography (CBCT). These were integrated into the RealGUIDE Universal Open System to create a virtual patient, enabling prosthetically driven planning based on facial analysis [16,17]. A digital smile design was constructed in Smilecloud to define the ideal tooth arrangement, vertical dimension, and smile curve [7,10,18,19,20] (Figure 5, Figure 6 and Figure 7).
Figure 5.
Digital smile design using Smilecloud. Based on facial references and functional and esthetic considerations, the upper teeth were imagined and repositioned to restore all lost functions.
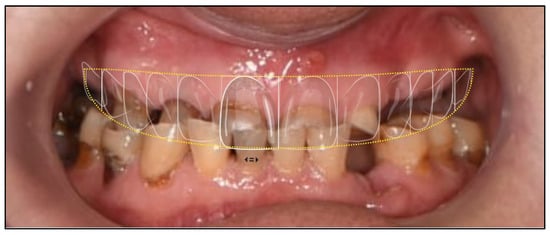
Figure 6.
Upper teeth outline design overimposed on the close-up photography to assess functional and esthetic landmarks in order to create the digital wax-up that will be used to plan the position of the implants.
Figure 7.
Digital planning of the implants.
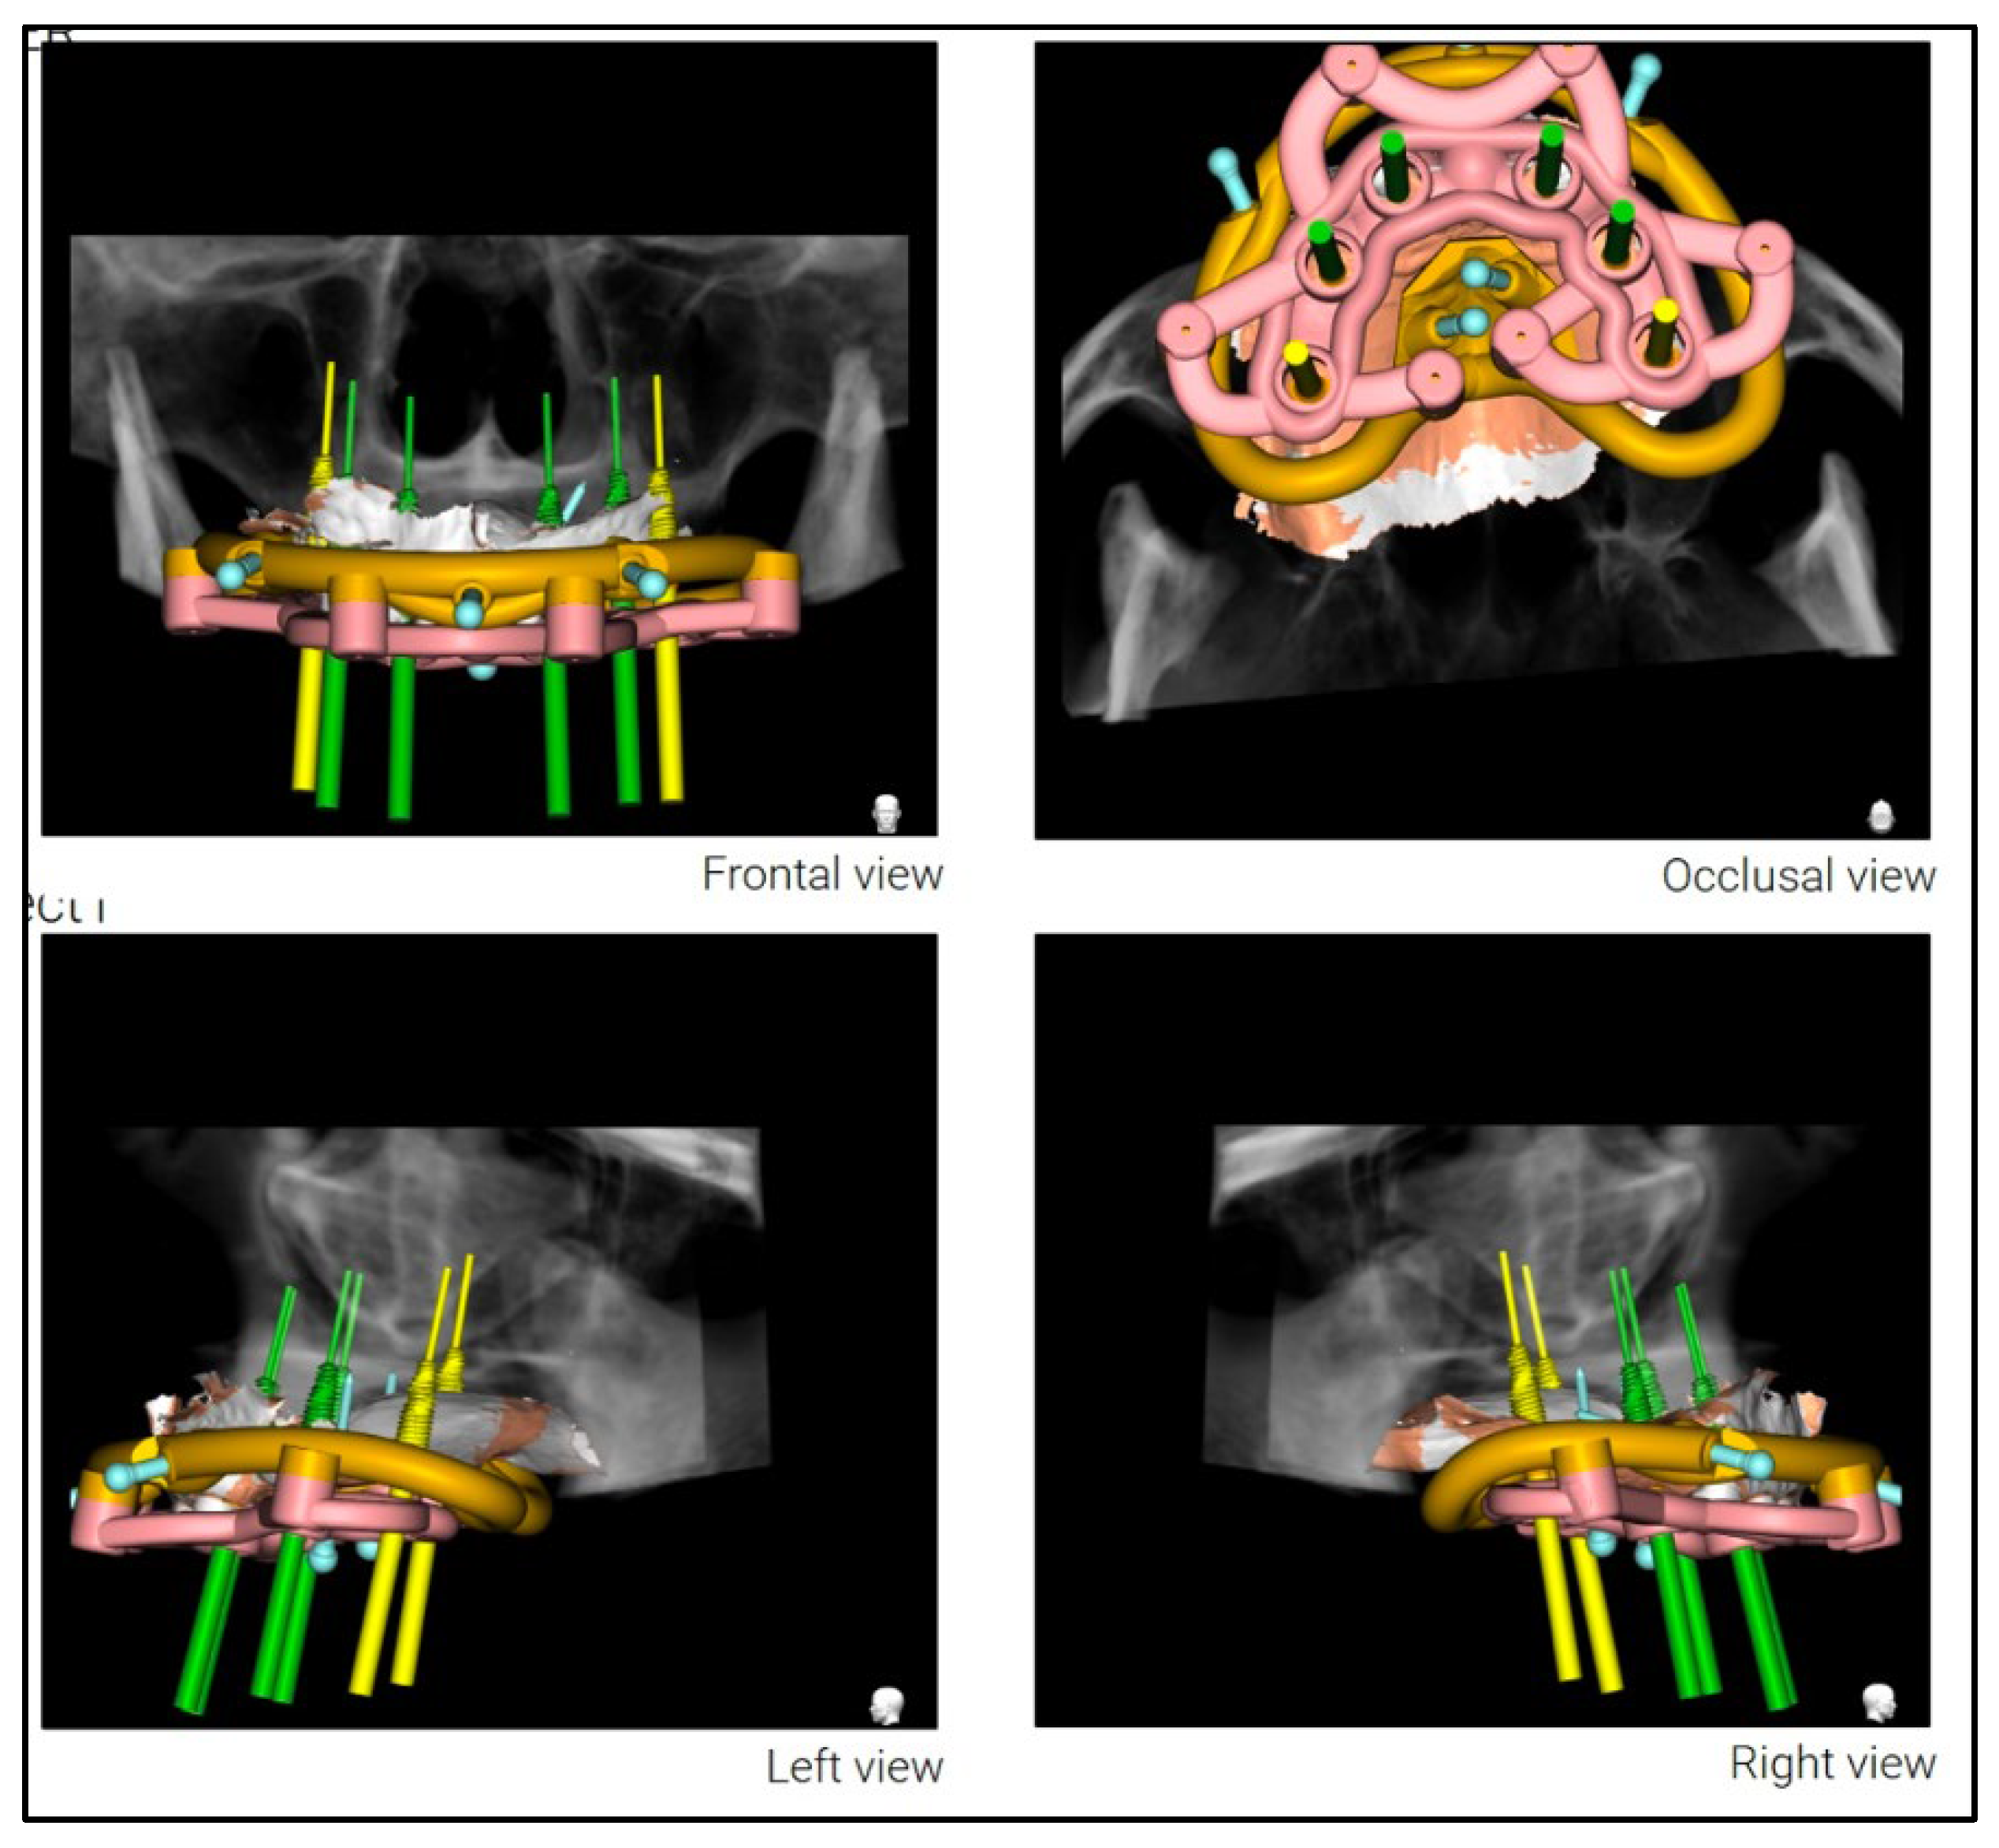
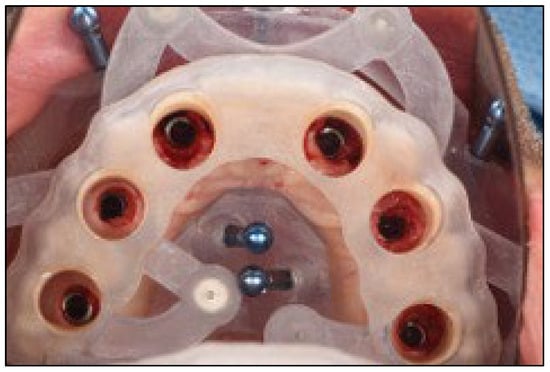
A stackable surgical guide system with magnetic retention was planned and fabricated. The guide set included a mucosa-supported base guide, an implant guide, and a multifunctional prosthetic verification guide. A flapless surgical approach was used. After base guide stabilization, the magnetic implant guide was sequentially positioned for each osteotomy. All six implants were placed according to the digital plan, achieving primary stability. Multi-unit abutments were installed to support immediate loading (Figure 8 and Figure 9).
Figure 8.
Planning of the surgical guide with magnetic retention using Real GUIDE Universal Open Systems.
Figure 9.
Multifunctional prosthetic verification guide—occlusal view—ensuring correct placement of the dental implants in relationship with the provisional restoration.
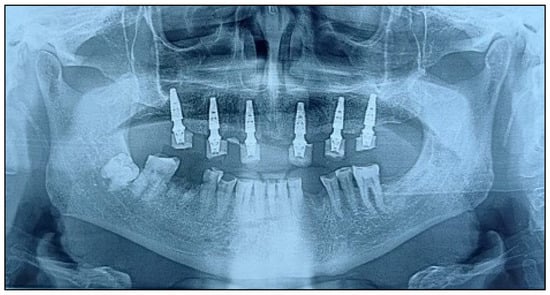
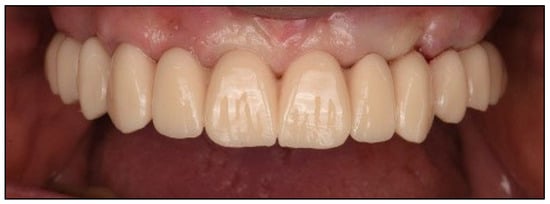
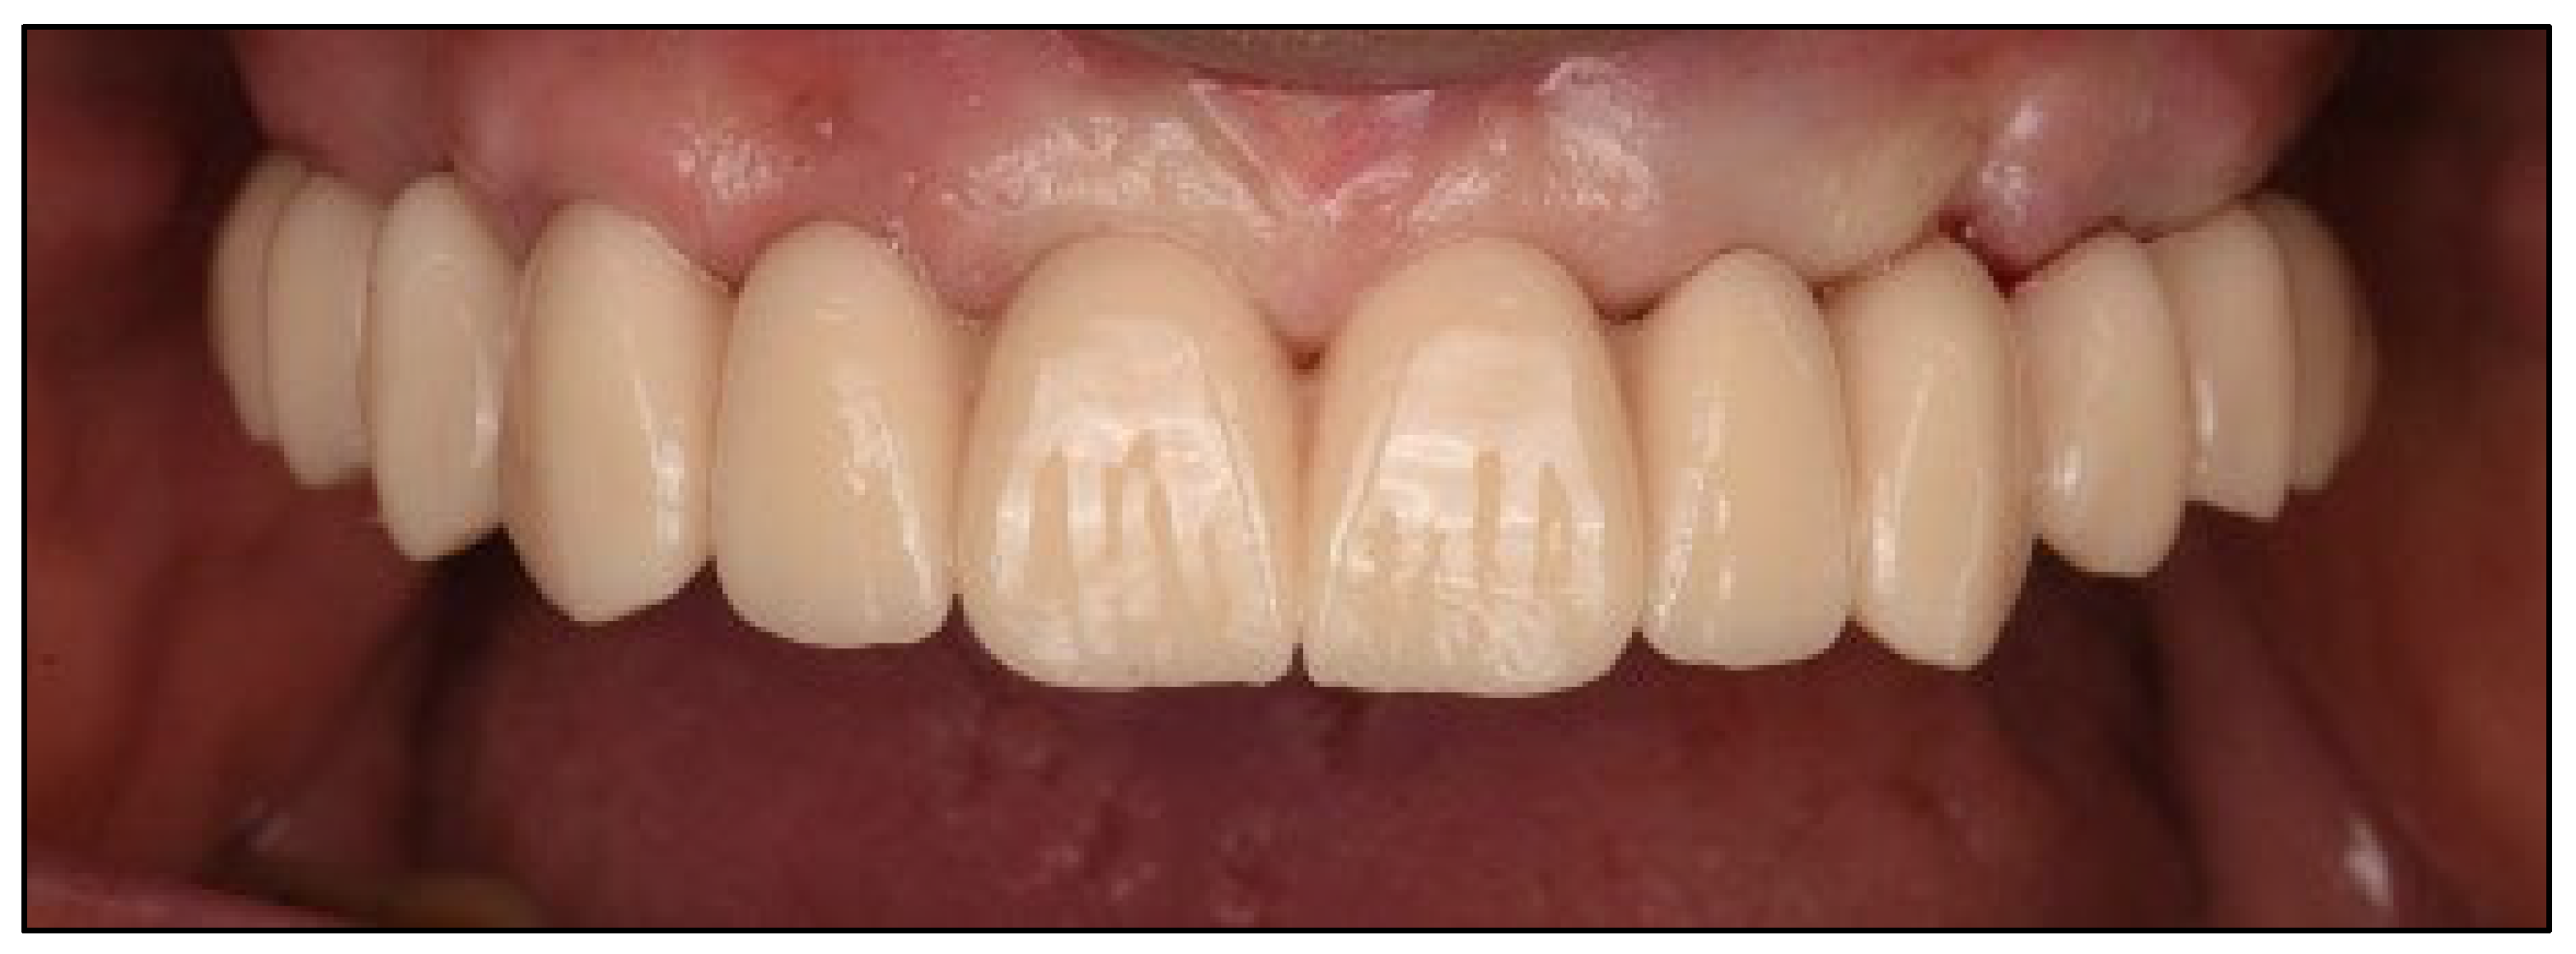
A CAD-CAM provisional prosthesis, designed from the digital wax-up, was prepared prior to surgery. Following implant placement, the provisional was secured using titanium cylinders and acrylic resin, adjusted intraorally to ensure passive fit and occlusal harmony. This prosthesis served as both a functional interim and a blueprint for the definitive restoration (Figure 10 and Figure 11).
Figure 10.
Postoperative orthopantomography with the implants in position and the provisional restoration in place.
Figure 11.
Intraoral frontal view of the upper arch, 12 weeks after new provisional restoration.
3.2. Review of Literature
The eight included reports span five countries across three continents and were published between 2021 and 2025 [13,21,22,23,24,25,26,27]. Seven of the protocols relied on purely mechanical stack indexing and only one used a magnetic stack [23]. Digital planning was heterogeneous: 3Shape® software underpinned three workflows [13,23,25], while R2Gate™ [21], Planmeca Romexis® [26], coDiagnostiX™ [28], ExoCAD + CBCT integration [22] and the FreeForm®/Mimics pairing [24] each featured one. Immediate loading was achieved in 100% of arches, validating the capacity of sequential templates to support same-day prostheses irrespective of the native platform. Follow-up ranged from 3 to 12 months (median ≈ 9 months), with the largest retrospective cohort by Levy Bohbot reporting clinical review at 4 months but prosthetic assessment at 12 months [13], as presented in Table 1.
Table 1.
Study characteristics.
Only two studies quantified positional deviations, recording mean coronal discrepancies of 0.95 mm and 0.87 mm, and angular errors of 2.8° and 2.67°, respectively—values well within the ≤1 mm/≤3° accuracy thresholds generally cited for full-arch guided surgery [21,22]. Across 351 implants, the global primary-stability targets clustered between 35 and 45 N cm, enabling immediate splinting in every case. The retrospective STAGE cohort experienced 10 early failures, yielding 96.5% survival at four surgical months [21], while the remaining 67 implants placed in smaller series or single-case reports all survived, producing an overall cumulative survival of 97.1% at last follow-up [21,22,23,24,25,26,27], as described in Table 2.
Table 2.
Surgical accuracy and implant outcomes.
Provisional restorations were predominantly monolithic or CAD-CAM milled PMMA bridges; one protocol used a prefabricated interim prosthesis delivered within six weeks [26], and another explored a zirconia prototype to test definitive strength pre-delivery [27]. The interval from surgery to final reconstruction averaged ≈22 weeks (range 6–52 weeks), with the longest timeline deliberately extending provisionalisation to shape peri-implant mucosa for a full-arch zirconia bridge [21]. Purposeful soft-tissue sculpting was documented in five of eight studies [13,21,23,24,27]. Patient-reported satisfaction was uniformly high, typically exceeding 90 mm on visual-analogue scales where measured [10,21,22,23], and only a single minor prosthetic event—one screw loosening—was reported across all arches [27], as seen in Table 3.
Table 3.
Performance of predictive models that incorporate wearable data.
4. Discussion
4.1. Summary of Evidence
Terminal dentition, the absence of reliable anatomical landmarks significantly challenges traditional prosthetic planning. The integration of a digitally driven, facially guided workflow represents a paradigm shift, enabling clinicians to merge esthetic vision with functional biomechanics from the earliest stages of treatment. In this case, the use of Smilecloud for esthetic planning and the RealGUIDE Universal Open System for implant planning facilitated a patient-specific design that guided both surgical and prosthetic phases with precision [16,17,18].
By integrating CBCT imaging with high-resolution surface scans, the digital workflow enabled precise visualization of the bone, soft tissues, and proposed restorations [19,20]. This multidimensional diagnostic environment supported a prosthetically guided surgical plan that was fully transferable to the clinical setting through the use of a stackable guide system. Beyond calibrated 2D photographs, contemporary platforms allow import of 3D facial scans, enabling a fully digital ‘virtual patient’ in which CBCT, intraoral scans, and facial soft-tissue geometry are co-registered. Such volumetric datasets improve control of midline, smile arc, and incisal display across expressions and can further reduce intraoperative adjustments by anchoring the stackable sequence to a more robust esthetic reference.
Stackable surgical guides, composed of modular components for adaptation, bone reduction, implant osteotomy, and prosthetic loading, minimize cumulative deviation in full-arch rehabilitation. As shown in this case and corroborated by the recent literature [27,28,29,30], these systems offer a highly accurate, efficient, and reproducible pathway for immediate loading. The magnet-based modular guide used here allowed for stable and flexible transitions between surgical stages, reducing chair time and increasing surgical confidence [31,32,33,34,35].
Each component of the guide system was digitally fabricated using a comprehensive CAD/CAM protocol. The initial design workflow was performed in Real GUIDE Universal Open, with STL exports refined in Meshmixer (Autodesk, San Francisco, CA, USA). Retentive and anti-rotational features—including cylindrical guide housings and embedded neodymium magnets (5 × 1 mm)—were digitally incorporated to ensure precise repositioning and secure coupling of components.
The guides were oriented in PreForm (Formlabs, Somerville, MA, USA) and printed using a Formlabs 3B+ Dental SLA printer with biocompatible Surgical Guide Resin V1. Post-processing adhered strictly to manufacturer recommendations, including dual-stage isopropyl alcohol washes, air drying, and final light curing (30 min at 60 °C and 405 nm). Manual finishing was completed using rotary instruments, and magnet housings were cemented using dual-cure self-adhesive resin cement (Calibra Universal, Dentsply Sirona). Metal sleeves compatible with the implant system were press-fitted into the osteotomy channels to guide drilling and implant placement with maximum precision [31,32,33,34,35].
The completed guides were sterilized via autoclave at 121 °C for 30 min, ensuring both biocompatibility and dimensional integrity. These stackable guides were designed for single use to maximize surgical precision and avoid cross-contamination.
This protocol enabled immediate prosthetic loading using a preoperatively fabricated PMMA provisional restoration. The digital congruence between the surgical plan and prosthetic design minimized intraoperative adjustments and enabled accurate pick-up of temporary cylinders. This clinical outcome underscores the power of merging digital prosthodontics with stackable guided surgery to restore function, esthetics, and confidence in a single procedure. Therefore, the facially driven digital workflow combined with magnet-retained stackable guides offers a highly accurate, modular, and efficient method for full-arch rehabilitation. This case demonstrates how emerging technologies can reshape implantology by merging design, precision, and patient-centred care.
The coronal (≤1 mm) and angular (≈2.7–2.9°) deviations observed in the included stackable-guide studies are markedly lower than those reported for earlier tooth-supported stereolithographic templates, where Derksen et al. found mean entry and angular errors of 1.06 mm and 4.8°, respectively [30]. When the so-called “double-factor” workflow combined static guides with real-time navigation, Pomares-Puig et al. achieved 0.98 mm/3.7° accuracy but added hardware cost and setup time [31]. By contrast, Martins et al. used a fully digital, stackable All-on-4 protocol and reported no positional outliers or biological failures across 16 arches, indicating that rigid sequential templates alone can narrow the accuracy gap between static and dynamic systems without extra instrumentation [29].
Only two of the eight studies captured patient-reported outcome measures with validated tools. In a Portuguese practice-based cohort, Mendonça et al. recorded a mean 33-point reduction in OHIP-14 after the delivery of CAD-CAM PMMA provisionals (effect size > 3.5) [32]. Similarly, a randomized maxillary trial by Marković et al. showed that immediate loading lowered OHIP-14 scores and maintained high satisfaction at 24 months compared with early loading despite equivalent implant stability and marginal bone loss [33]. Conversely, the hybrid static–dynamic series of Pomares-Puig captured only visual-analogue improvements without psychometric calibration [31], underscoring the current paucity of robust PROM data in stackable-guide research. Future trials should integrate standardized quality-of-life instruments to test whether the operative efficiencies translate into meaningful patient benefit.
Efficiency metrics also remain scarce. Martins et al. completed bone reduction, six implant placements and delivery of a prefabricated interim in 2 h 30 min, attributing the streamlined turnover to the modular stack [29]. Pomares-Puig et al. reported a comparable operative window but required additional staff and navigation equipment [31]. None of the retrieved studies performed a formal cost analysis; however, Mendonça et al. noted a 24% provisional-fracture rate that could negate savings if remakes are frequent [32]. Economic evaluations that balance laboratory fees, surgical duration and complication-related revisions are therefore essential before stackable templates can be recommended as cost-effective standard care [33,34,35].
Although posterior fixed partial dentures with cantilevered units have shown comparable prognoses under immediate loading in selected indications [34,35], we selected a full-arch framework on six implants to (i) distribute forces in a patient with probable parafunction, (ii) minimize cantilever length while optimizing screw-access emergence based on the facially driven plan, and (iii) allow cross-arch splinting to accommodate the small positional tolerances inherent to guided surgery. This choice prioritized biomechanical risk mitigation and prosthetic maintenance in the context of terminal dentition.
Clinical case considerations relative to published protocols. Our sequence parallels model-free stacks that preserve a single fiducial from incision to pickup but uses magnetic indexing to accelerate interchange and provide tactile/audible confirmation of seating. Consistent with cohort data, immediate loading criteria were respected by targeting ≥35–40 N·cm primary stability and cross-arch splinting. Compared with purely mechanical stacks, magnets reduced chairside turnover for guide swaps while maintaining repositioning repeatability; in our case, this facilitated atraumatic extractions, osteotomy execution, and rapid prosthetic pickup without deviating from the facially driven plan. These steps mirror the rationale reported in recent cohorts and technique notes while highlighting the operational flexibility of magnetic couplings within a stackable framework.
4.2. Limitations
The present synthesis is constrained by the scarcity and heterogeneity of available reports: over half are single-case descriptions, follow-up rarely exceeds one year, and only two studies quantify positional deviations with uniform measurement tools. Variability in planning software, guide manufacturing methods, loading protocols and outcome definitions precluded pooled analysis and limits direct comparability. Grey literature, non-English papers and unpublished data were not searched, introducing potential selection and language biases. Finally, our own single-patient experience, while illustrative, cannot compensate for the absence of prospective controlled cohorts and may over-represent best-case performance.
5. Conclusions
Stackable surgical guides—particularly when embedded in a comprehensive facially driven digital workflow—offer a viable, accurate path to same-day full-arch rehabilitation. Early clinical data are encouraging, but too immature to endorse the technique as superior to existing static guides. Rigorous, multi-centre trials with standardized accuracy metrics, long-term biologic follow-up and validated patient-reported outcomes are imperative to substantiate routine adoption.
Author Contributions
Conceptualization, I.S. and B.A.B.; methodology, I.S. and B.A.B.; software, A.R. and A.C.; validation, A.R. and A.C.; formal analysis, A.R. and A.C.; investigation, S.T. and T.H.; resources, S.T. and T.H.; data curation, S.T., A.T., V.D.S. and T.H.; writing—original draft preparation, I.S. and B.A.B.; writing—review and editing, R.A., A.T., V.D.S., G.T. and V.N.; visualization, R.A., A.T., V.D.S., G.T. and V.N.; supervision, R.A., G.T. and V.N.; project administration, R.A., G.T. and V.N. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Data Availability Statement
Not applicable.
Acknowledgments
The authors used ChatGPT v4.0, an AI language model developed by OpenAI (San Francisco, CA, USA), to exclusively improve the manuscript’s language and readability. All the scientific content, interpretations, and conclusions are the original work of the authors.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Papaspyridakos, P.; Chen, C.J.; Chuang, S.K.; Weber, H.P. Implant loading protocols for edentulous patients with fixed prostheses: A systematic review and meta-analysis. Int. J. Oral Maxillofac. Implants 2014, 29, 256–270. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schnutenhaus, S.; Edelmann, C.; Rudolph, H.; Dreyhaupt, J.; Luthardt, R.G. 3D accuracy of implant positions in template-guided implant placement as a function of the remaining teeth and the surgical procedure: A retrospective study. Clin. Oral Investig. 2018, 22, 2363–2372. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tahmaseb, A.; Wu, V.; Wismeijer, D.; Coucke, W.; Derksen, W. Accuracy of static computer-aided implant surgery: A systematic review and meta-analysis. Clin. Oral Implants Res. 2018, 29 (Suppl. S16), 416–435. [Google Scholar] [CrossRef] [Scilit]
- Schneider, D.; Marquardt, P.; Zwahlen, M.; Jung, R.E. A systematic review on the accuracy and safety of guided implant surgery. Clin. Oral Implants Res. 2009, 20 (Suppl. S4), 73–86. [Google Scholar] [CrossRef] [Scilit]
- Manfredini, M.; Poli, P.P.; Maiorana, C.; Salina, F.E.; Tandurella, M.; Beretta, M. Computer Aided Full Arch Restoration by Means of One-Piece Implants and Stackable Guide: A Technical Note. Dent. J. 2023, 11, 256. [Google Scholar] [CrossRef] [Scilit]
- Baruffaldi, A.; Baruffaldi, A.; Baruffaldi, M.; Maiorana, C.; Poli, P.P. A suggested protocol to increase the accuracy of prosthetic phases in case of full-arch model-free fully guided computer-aided implant placement and immediate loading. Oral Maxillofac. Surg. 2020, 24, 343–351. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Debortoli, C.; Afota, F.; Latreche, S.; Zammillo, F.; Boujenah, O.; Savoldelli, C. Stackable guide in implantology: A technical note. J. Stomatol. Oral Maxillofac. Surg. 2023, 124, 101459. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pelekanos, S.; Milioni, E.; Gkika, S.; Zachopoulou, A.; Stankov, V.; Schoenbaum, T.; Ntovas, P. A Digital Workflow for Stackable Surgical Templates in Combination With Tripod Provisional Restoration for the Management of Terminal Dentition: A Case Report. J. Esthet. Restor. Dent. 2025; epub ahead of print. [CrossRef] [Scilit] [PubMed]
- Jreige, C.S.; Gama, R.; Parize, H.; Ates, G.; Sesma, N. 3D virtual patient-Magnetically retained printed stackable system for implant guided placement: Case report. J. Esthet. Restor. Dent. 2024, 36, 1604–1613. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lan, R.; Marteau, C.; Mense, C.; Silvestri, F. Current knowledge about stackable guides: A scoping review. Int. J. Implant Dent. 2024, 10, 28. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Bai, X.; Wu, T.; Zhu, Y.; Yang, C.; Cheng, T.; Liu, Y.; Zhou, Y. Cone-wedge anchored surgical templates for stackable metal guide: A novel technique. Int. J. Implant Dent. 2024, 10, 27. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Ureel, M.; Boderé, P.J.; Denoiseux, B.; Corthouts, P.; Coopman, R. Mandibular Reconstruction with Osseous Free Flap and Immediate Prosthetic Rehabilitation (Jaw-in-a-Day): In-House Manufactured Innovative Modular Stackable Guide System. Bioengineering 2024, 11, 1254. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Levy-Bohbot, A.; Bertolus, C.; Durin-Touati-Sandler, A.; Gellée, T. Stackable Guides and Immediate Full-Arch Loading: A Retrospective Cohort Study of 43 Edentulous Arches—The STAGE Study. Int. J. Oral Maxillofac. Implants 2025, 40, 241–249. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stanley, R.J. When Guided Surgery Fails: A Routine to Recover the Implant Original Treatment Plan. Compend. Contin. Educ. Dent. 2022, 43, e10–e14. [Google Scholar] [PubMed]
- Odette, J.; Andersen, M.; Hammer, D.; Andersen, M.R. Stackable Guides: Digital Workflows for Full Arch Dental Implant Rehabilitation. Oral Maxillofac. Surg. Clin. N. Am. 2025, 37, 261–271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ma, A.; Chan, B.; Yip, I.; Hung, C.K.; Kurtzman, G.M.; Tarnow, D.P. A Novel Method to Pick-up Prefabricated CAD/CAM-Designed Screw-Retained Provisional Prostheses for Immediate Full-Arch Rehabilitations: Liquid Pin Technique. Compend. Contin. Educ. Dent. 2025, 46, 77–83. [Google Scholar] [PubMed]
- Monsalve-Guil, L.; Velasco-Ortega, E.; Ortiz-Garcia, I.; Matos-Garrido, N.; Moreno-Muñoz, J.; Núñez-Márquez, E.; Rondón-Romero, J.L.; López-López, J.; Jiménez-Guerra, Á. Retrospective clinical follow-up of implants placed in edentulous jaws after computer-guided surgery and immediate loading, in geriatric patients. Med. Oral Patol. Oral. Cir. Bucal. 2025, 30, e76–e85. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Herklotz, I.; Kunz, A.; Stimmelmayr, M.; Beuer, F. Immediate loading of a fixed full-arch prosthesis on four template-guided implants. Int. J. Comput. Dent. 2022, 25, 221–231. [Google Scholar] [PubMed]
- Cristache, C.M.; Butnarasu, C.; Boiangiu, R.; Burlacu-Vatamanu, O.-E. Full Digital Workflow for Immediate Fixed Rehabilitation Using Stackable Guides. J. Dent. 2024, 147, 105203. [Google Scholar] [CrossRef] [Scilit]
- Kachlan, M.; Mostoufi, B.; Majeed-Saidan, A.; Kanikicharla, S.; Masri, R. Clinical case report: Immediate full-arch implant placement and loading technique using a fiducial-free dynamic navigation workflow. J. Prosthodont. 2025; epub ahead of print. [CrossRef] [Scilit] [PubMed]
- Cristache, C.M.; Burlacu Vatamanu, O.E.; Butnarasu, C.C.; Mihut, T.; Sgiea, E.D. Predictable Full Digital Workflow Using Stackable Surgical Templates for Complete Dental Arch Rehabilitation with Implant-Supported Fixed Restorations-Case Series and Proof of Concept. Dent. J. 2024, 12, 347. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Alruhailie, L.; Zaidan, A.; Alasmari, A.; Raffa, O. A Fully Guided Sequential Template Immediate Loading Protocol for Dual-Arch Implant Surgery. Clin. Cosmet. Investig. Dent. 2024, 16, 167–177. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- García-Sala Bonmati, F.; Pérez-Barquero, J.A.; Ilzarbe Ripoll, L.M.; Labaig Rueda, C.; Fernandez-Estevan, L.; Revilla-León, M. An additively manufactured, magnetically retained, and stackable implant surgical guide: A dental technique. J. Prosthet. Dent. 2023, 130, 444–452. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abdelaziz, M.S.; El Sattar Abd El Megid Tella, E.A. Digital design and manufacture of a stackable implant surgical guide for immediate loading in completely edentulous full-arch cases: A dental technique. Quintessence Int. 2023, 54, 750–755. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, J.W.; Liu, Q.; Yue, Z.G.; Hou, J.X.; Afrashtehfar, K.I. Digital Workflow for Full-Arch Immediate Implant Placement Using a Stackable Surgical Guide Fabricated Using SLM Technology. J. Prosthodont. 2021, 30, 645–650. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Papaspyridakos, P.; De Souza, A.; Bathija, A.; Kang, K.; Chochlidakis, K. Complete Digital Workflow for Mandibular Full-Arch Implant Rehabilitation in 3 Appointments. J. Prosthodont. 2021, 30, 548–552. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fu, X.; Yang, J.; Luo, J.; Zhang, Y. Three-dimensional facial esthetics-driven computer-assisted osteotomy and implant placement for immediate restoration of a failing dentition with a protruded maxilla. J. Prosthet. Dent. 2022, 127, 392–397. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Creagh, J.; Bohner, L.; Sesma, N.; Coachman, C. Integrating a Facially Driven Treatment Planning to the Digital Workflow for Rehabilitation of Edentulous Arches: A Case Report. J. Contemp. Dent. Pract. 2020, 21, 1393–1397. [Google Scholar] [CrossRef] [Scilit]
- Martins, J.; Rangel, J.; de Araújo Nobre, M.; Ferro, A.; Nunes, M.; Almeida, R.; Moura Guedes, C. A New Full Digital Workflow for Fixed Prosthetic Rehabilitation of Full-Arch Edentulism Using the All-on-4 Concept. Medicina 2024, 60, 720. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Derksen, W.; Wismeijer, D.; Flügge, T.; Hassan, B.; Tahmaseb, A. The accuracy of computer-guided implant surgery with tooth-supported, digitally designed drill guides based on CBCT and intraoral scanning. A prospective cohort study. Clin. Oral Implants Res. 2019, 30, 1005–1015. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pomares-Puig, C.; Sánchez-Garcés, M.A.; Jorba-García, A. Dynamic and static computer-assisted implant surgery for completely edentulous patients. A proof of a concept. J. Dent. 2023, 130, 104443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mendonça, C.; de Macedo, D.; Nicolai, C.; Madeira, H.; Van Dooren, E.; Norré, D.; Mata, A. Digital Full-Arch Implant-Supported Polymethyl Methacrylate Interim Prosthesis: A Practice-Based Cohort Study on Survival and Quality of Life. Int. J. Prosthodont. 2024, 37, 394–403. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marković, A.; Mišić, T.; Janjić, B.; Šćepanović, M.; Trifković, B.; Ilić, B.; Todorović, A.M.; Marković, J.; Dard, M.M. Immediate vs. Early Loading of Bone Level Tapered Dental Implants with Hydrophilic Surface in Rehabilitation of Fully Edentulous Maxilla: Clinical and Patient Centered Outcomes. J. Oral Implantol. 2022, 48, 358–369. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- D’Albis, G.; Forte, M.; Alrashadah, A.O.; Marini, L.; Corsalini, M.; Pilloni, A.; Capodiferro, S. Immediate Loading of Implants-Supported Fixed Partial Prostheses in Posterior Regions: A Systematic Review. Dent. J. 2025, 13, 213. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- D’Albis, G.; D’Albis, V.; Susca, B.; Palma, M.; Al Krenawi, N. Implant-supported zirconia fixed partial dentures cantilevered in the lateral-posterior area: 4-year clinical results. J. Dent. Res. Dent. Clin. Dent. Prospect. 2022, 16, 258–263. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).