


Abstract
Introduction and Aim: Propranolol is an effective treatment option for infantile hemangiomas, but there is still insufficient information about neurodevelopmental side effects of propranolol. In our study, the neurodevelopmental levels of infantile hemangioma patients receiving propranolol treatment were examined using the Bayley-III test. Method: In our single-center, cross-sectional study, patients were recruited between 1 January 2020 and 31 December 2023. In total, 40 children (n1) diagnosed with hemangioma who received propranolol treatment and 31 children (n2) who were only under observation were included. A control group of 31 healthy children (n3) matched for age and gender was also included. The demographic, clinical, perinatal, and postnatal characteristics of the total 102 children were recorded from their medical records. Neurodevelopmental levels were assessed with the Bayley-III test. The significance level was set at (p < 0.05). Results: The Bayley-III test composite and percentile scores were used to evaluate the neurodevelopmental levels. Significant differences in motor functions were found between the treated and untreated groups compared to the healthy control group (p = 0.006 and p = 0.006). However, no significant differences were found in cognitive, language, and social-emotional skills. Cognitive, language, and motor functions were associated with maternal education level, and additionally, cognitive functions were also associated with paternal education level. Conclusions: Propranolol has a relatively safer side effect profile, and therefore, it has been described as a safe agent. In our study, no significant effect of propranolol on neurodevelopment was observed. The difference in motor skills shown was mainly between the healthy control group (n3) and the treated and untreated group (n1 and n2), which led to the conclusion that the relevant difference could be due to factors other than propranolol itself.
1. Background/Rationale
Infantile hemangiomas (IHs) are the most common benign tumors of vascular origin [1,2]. Previous studies suggest that their prevalence ranges from 2% to 10%, and with advancements in medical care, the incidence of IHs is on the rise [3].
Until 2008, corticosteroids and chemotherapeutic agents were used as first-line therapy for the treatment of IHs. In 2008, Leaute-Lebreze et al. demonstrated that propranolol could also induce the involution of IHs; however, the therapeutic mechanism is still not fully understood [4]. Nonetheless, by 2012, propranolol had become the gold standard therapy for IH and is now used as a first-line therapeutic agent worldwide.
Propranolol is a non-selective, lipophilic beta-blocker used in the treatment of IHs. Because of its lipophilic nature, it can easily cross the blood–brain barrier and may cause adverse effects in the CNS. Previous animal studies have demonstrated that propranolol might cause motor dysfunctions in zebrafish larvae [5]. In adult mice, propranolol inhibits long-term potentiation and recollection of traumatic experiences via central B2 blockade, potentially prolonging the learning process [6]. An adult study conducted by Mallet et al. showed that propranolol inhibits the recollection of traumatic experiences and might reduce the severity of anxiety and depression in patients with post-traumatic stress disorder [7].
A limited number of studies have attempted to elucidate the effects of propranolol on the developing and organizing CNS. Furthermore, the use of propranolol for IH treatment has been described as the gold standard only in the last decade [8]. The primary hypothesis and objective of our study is to evaluate the potential neurodevelopmental effects of propranolol treatment in IH patients using the Bayley Scales for Infant and Toddler Development III (BSID-III) test. Our secondary objectives include assessing the factors that might influence neurodevelopment.
2. Methods
Our cross-sectional study was conducted in Istanbul University Istanbul Faculty of Medicine Department of Pediatrics Division of Pediatric Hematology and Oncology Clinic (PCOC) and Division of Social Pediatrics Well Child Outpatient Clinic (SP-WCOC).
In the PCOC, children with hemangioma were examined in detail for the size and number, characteristics, location and distribution of the hemangiomas. Since IHs can be seen as a part of clinical syndrome (e.g., PHACE syndrome, LUMBAR syndrome, etc.), thorough systemic physical examination is performed in order to determine the presence of accompanying findings. All children are evaluated with cranial and abdominal ultrasonography for visceral and/or intracranial hemangiomas. Complete blood count, coagulation parameters, and thyroid functions of all children are evaluated. Also, all children undergo routine electrocardiography and echocardiography for evaluation of the cardiac functions. The initiation of therapy with beta blockers, either systemically or topically, or observation-only management was determined based on treatment indications for IH, which are guided by the combined contributions of the Hemangioma Severity Score and the parents’ wishes.
In the SP-WCOC, healthy children visits are performed at fixed intervals. During each visit, children between the ages of 0 and 10 are examined and immunization profiles are assessed and screened neurodevelopmentally. Through these multidisciplinary and rigorous screening methods, children are evaluated holistically on each aspect of their wellbeing.
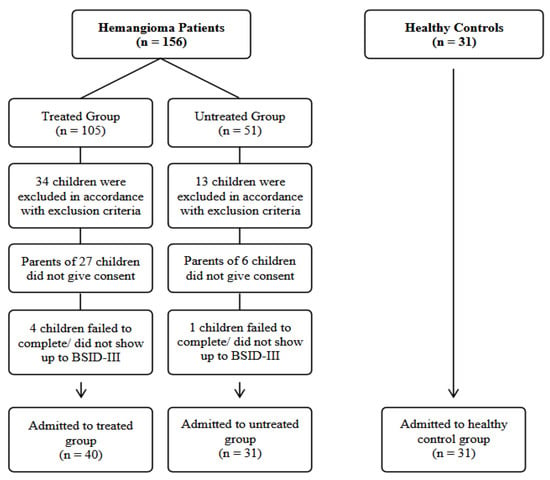
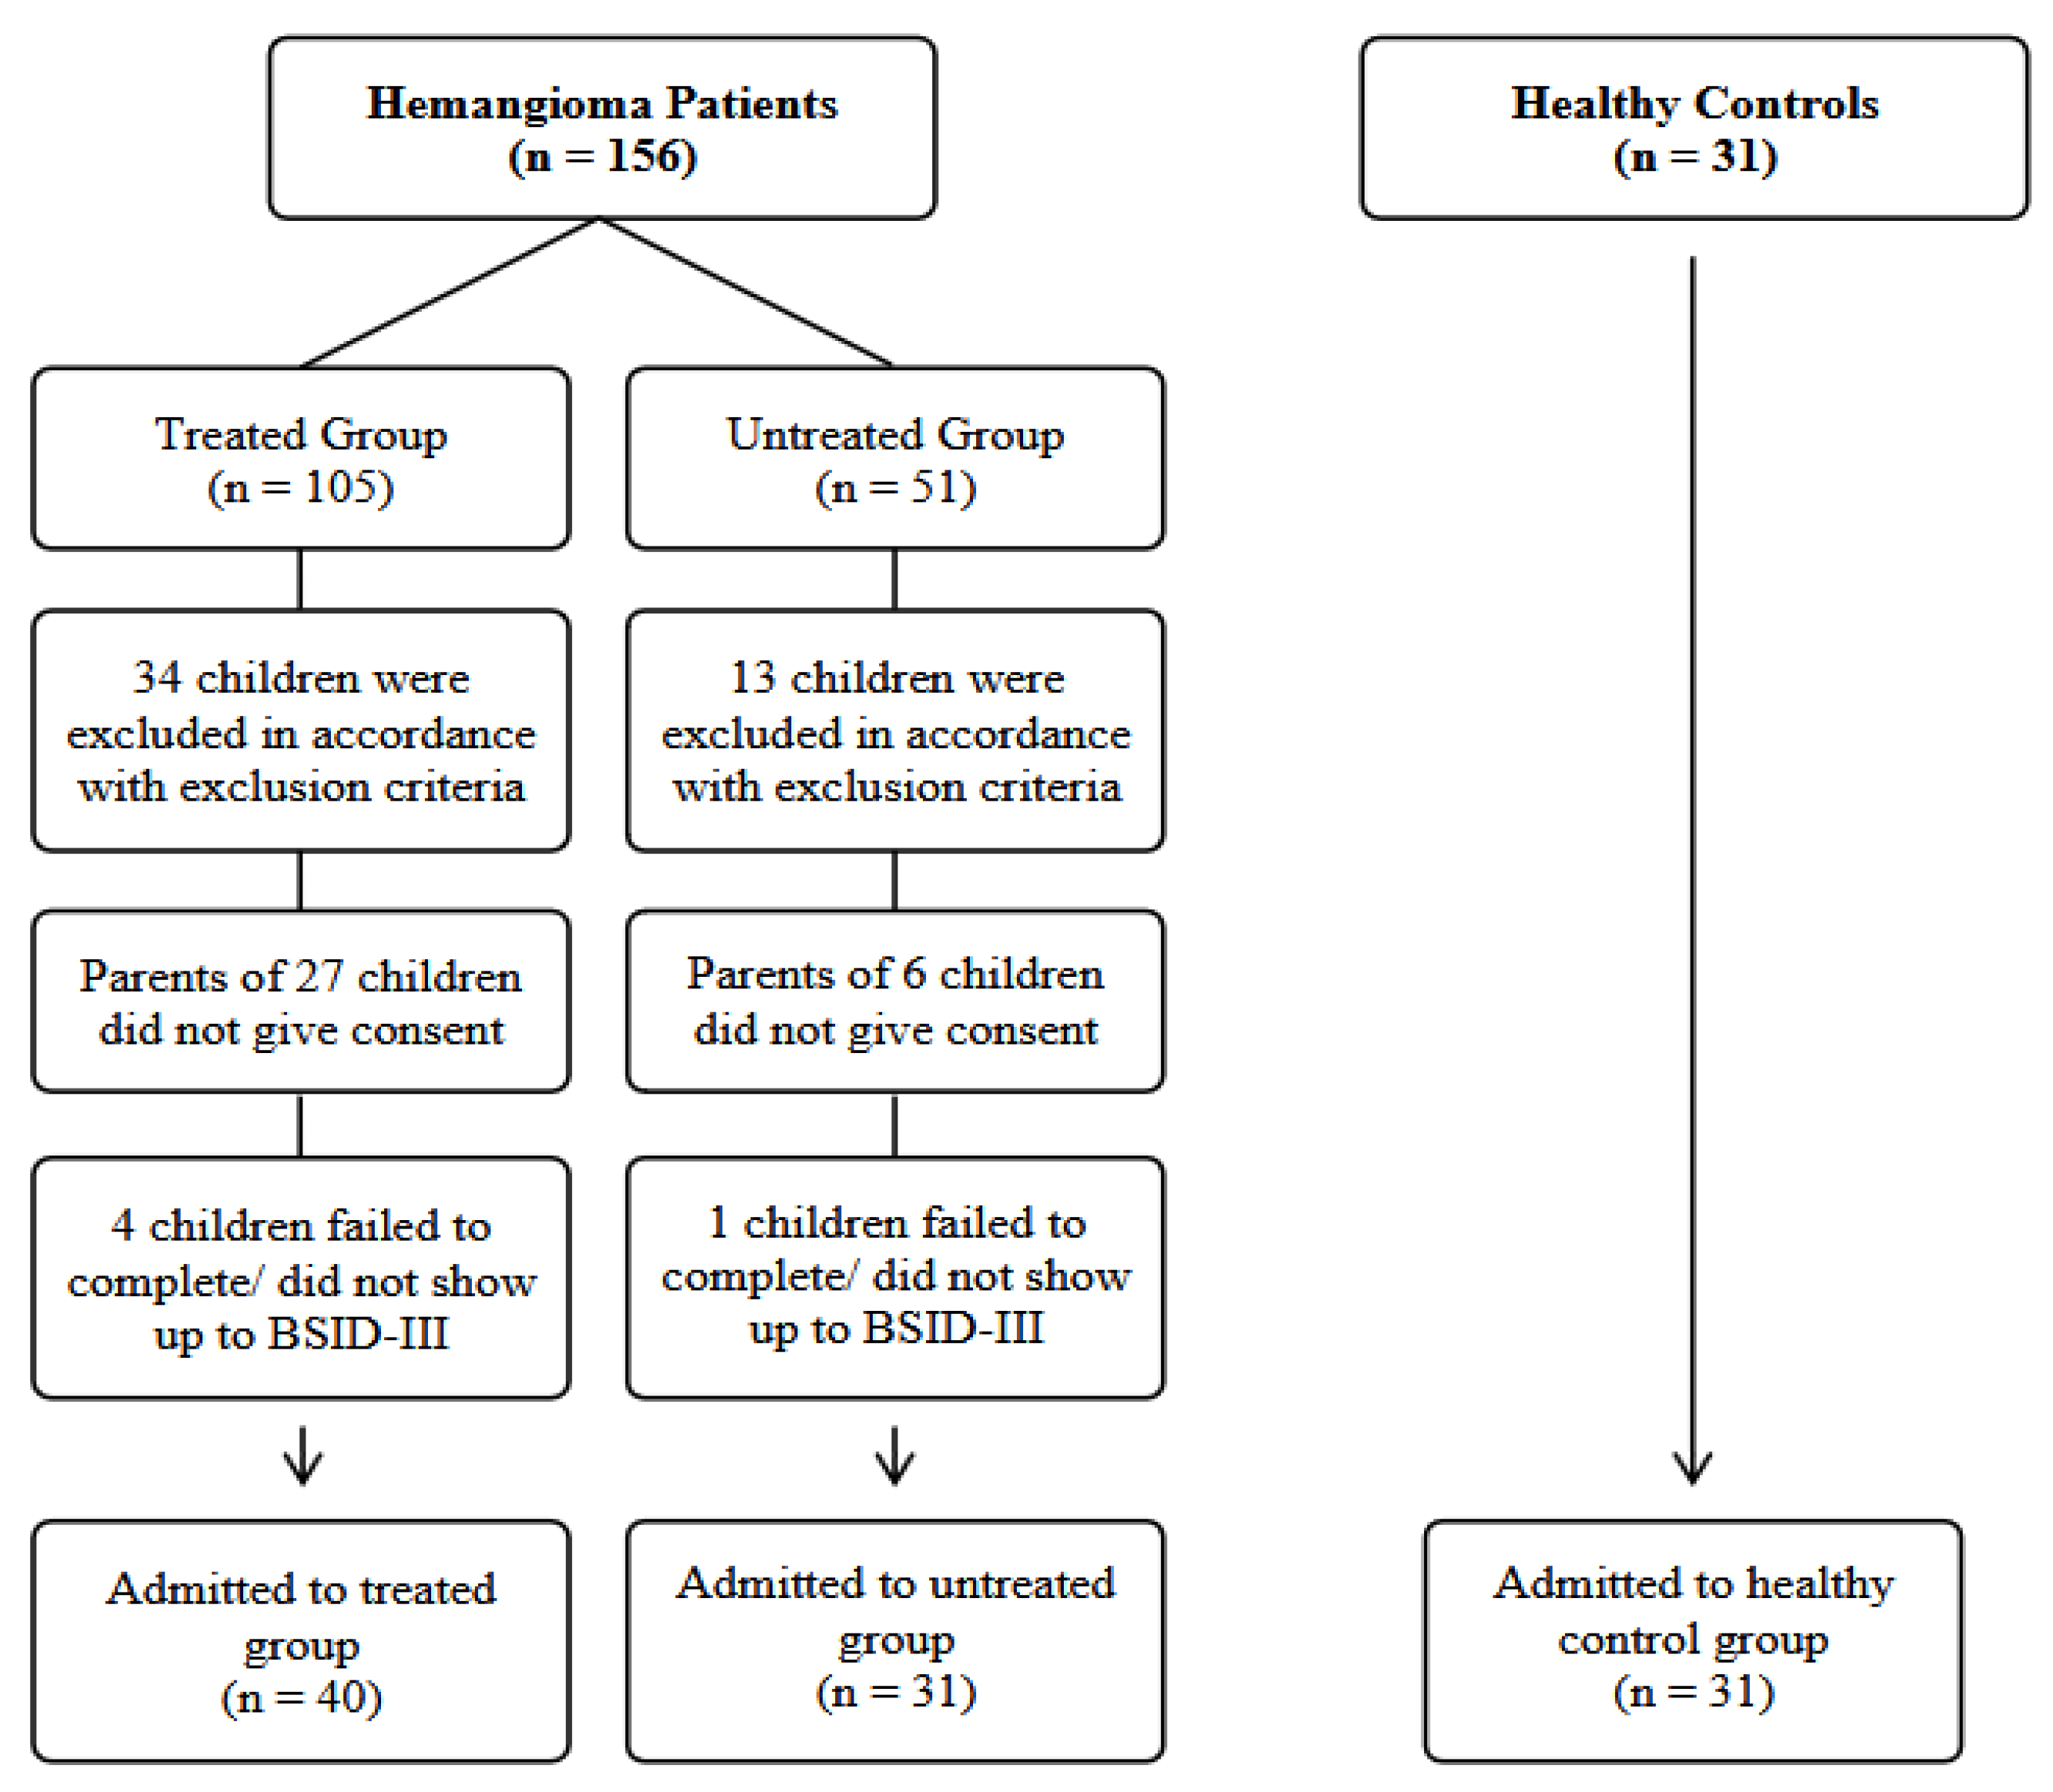
A total of 102 children were recruited between 1 January 2020 and 31 December 2023. Children were assigned to the treated hemangioma group (n1 = 40), untreated hemangioma group (n2 = 31), or the healthy control group (n3 = 31). A total of 71 hemangioma patients were recruited from the Pediatric Hematology and Oncology Department, and 31 healthy controls were recruited from the Child Health Department. The inclusion and exclusion criteria are presented in Table 1. We implemented a matching process, considering the age and gender variables of the patients to minimize selection bias. The final study size was adjusted according to the number of eligible children in both the treated and untreated groups. A flow chart of patient selection is presented in Figure 1.
Table 1.
Inclusion and exclusion criteria for the study.
Figure 1.
Patient recruitment flow chart. BSID-III: Bayley Scales of Infant and Toddler Development-III.
A written consent form was obtained from the parents of all eligible children. Details such as age at the time of the BSID-III test, sex, mode of delivery, gestational age, admission to the Neonatal Intensive Care Unit (NICU) and the reason for admission, breast-feeding duration, and maternal and paternal education levels were noted with a pre-BSID-III test questionnaire. Additionally, information about the duration of treatment and adherence to the treatment were documented. The standard therapeutic dose of propranolol for infantile hemangioma used in our study was 2 mg/kg/day. Propranolol was initially administered at 0.5 to 1 mg/kg/day in two doses, then increased to 2 mg/kg/day in 2-week intervals.
The neurodevelopmental levels of the children who participated in the study were evaluated using the BSID-III test by a certified expert. This expert was blind to the medical records of the patients to minimize evaluation bias. The evaluation comprised four developmental sub-categories: cognitive, language, motor, and social-emotional functions, in accordance with the BSID-III test manual [9]. The BSID-III test was administered to all children in a quiet, distraction-free room under the supervision of an expert certified pedagogist, a pediatrician, and one caregiver.
After evaluation, children who were found to be at risk within any neurodevelopmental sub-categories were referred to the Pediatric Neurology and/or Children and Adolescent Psychiatry departments for further investigation.
All analyses were performed using SPSS 21.0 for Windows (IBM Corp., Armonk, NY, USA). The independent samples t-test was utilized to analyze the continuous variables, while chi-square (χ2) tests were used to compare qualitative variables. ANCOVA tests were conducted to identify co-founding factors influencing BSID-III score. p Values less than 0.05 were considered statistically significant.
3. Results
The results of the descriptive statistical analyses are presented in Table 2. Female-to-male ratios in the groups were 3:1, 1.4:1, and 1.6:1, respectively. However, the gender distribution within the cohort was homogeneous. The distribution of age at the time of BSID-III, maternal education levels, paternal education levels, and duration of breast-feeding were also homogeneous, and their respective p-values are presented in Table 2.
Table 2.
Descriptive data of the cohort.
To test our hypothesis, we compared the neurodevelopmental levels of treated and untreated children with those of healthy children. These findings are summarized in Table 3. Preliminary analyses indicated a significant difference across the motor functions of the cohort, with p-values for motor composite and percentile scores being 0.013 and 0.005, respectively. Post hoc analyses further showed a significant difference between the treated and healthy control groups, as well as between the untreated and healthy control groups. However, post hoc analyses revealed no significant difference between the treated and untreated groups.
Table 3.
Comparison of the BSID-III scores among all groups and post hoc analyses.
To further investigate the effect of propranolol on neurodevelopment, we subdivided the treated group according to the mean treatment duration in our study, which was 16 months. We divided the treated IH patients’ group into two sub-groups (n1a and n1b) based on treatment duration. We compared the BSID-III scores for these two sub-groups with those of the untreated group (n2) to analyze whether an accumulative effect of propranolol occurred. However, we found no statistical significance in any of the four neurodevelopmental categories. The results of this analysis are presented in Table 4.
Table 4.
Comparison of BSID-III scores of treated and untreated groups, after subgrouping according to the mean duration of time (16 months).
The effects of other variables (e.g., maternal and paternal education levels, duration of breast-feeding, and NICU admission) on BSID-III scores were also evaluated. Preliminary analyses revealed that maternal education levels were greatly associated with infant neurodevelopment in cognitive, linguistic, and motor function categories. Post hoc analyses showed significant differences when the infant’s mother had completed at least 12 years of education compared to mothers who completed eight years or less. Paternal education levels were also associated with infant neurodevelopment, specifically in cognitive functions. Likewise, post hoc analyses showed significant differences when the infant’s father had completed at least 12 years of education compared to fathers who completed eight years or less. However, the impact of paternal education on infant neurodevelopment was found to be less substantial than that of maternal education. The results of these analyses are presented in Table 5 and Table 6.
Table 5.
Comparison of BSID-III scores depending on maternal education levels.
Table 6.
Comparison of BSID-III scores depending on paternal education levels.
The effects of NICU admission on BSID-III scores were analyzed. The results of BSID-III scores were compared between infants with a positive history of NICU admission (n = 24) and a negative history of NICU admission (n = 78). Analyses revealed that infants with a positive history of NICU admission had lower scores in motor functions compared to infants with a negative history of NICU admission (p-values for motor composite and percentile scores were p = 0.006 and p = 0.006). No statistical significance was found in cognitive, linguistic, and social-emotional categories. The results of the analyses are presented in Table 7.
Table 7.
BSID-III scores according to history of NICU admission.
The effects of confounding factors such as treatment duration, age at the start of treatment, duration of breast-feeding, and NICU admission were analyzed using m-ANCOVA tests. For the treated group, the confounding factors were exclusively the duration of treatment and the age at the beginning of treatment. On the other hand, NICU admission and the length of breast-feeding affected the entire cohort. However, no significant effect was found for any of these confounding variables. The results are presented in Table 8.
Table 8.
Analyses of effects of co-founding variables on BSID-III scores.
4. Discussion
In our study, in which we aimed to explore the potential adverse effects of propranolol, a lipophilic non-selective beta blocker drug, on the developing brain via the BSID-III test, revealed no significant neurodevelopmental effects.
In 2008, Leaute-Lebreze et al. discovered that the use of propranolol for the treatment of IHs was quite beneficial [4]. Involution of IHs with propranolol therapy was reinforced in subsequent works [10], and hence, propranolol treatment for IHs had been named as the gold standard method for the last decade and half. Considering that the first children are in the second decade of their lives as of today, it is crucial to elucidate whether the use of propranolol, especially in the first 2 years of age, has any negative effect on neurodevelopment.
Previous studies have shown that propranolol may have a negative effect on neurodevelopment and active learning, recalling traumatic experiences and long-term potentiation in animal models. Furthermore, several studies were performed to evaluate the side effects of propranolol CNS in adults, implicating conflicting results. Previous works on the effect of propranolol therapy in infantile hemangioma patients, however, were not only scarce in numbers, but also yielding inconsistent findings.
The results indicated that oral propranolol therapy at a dose of 2 mg/kg/day was not associated with significant difference in cognitive, linguistic, and social-emotional sub-categories of neurodevelopment. However, there was a significant difference in the motor functions of the children within our cohort. Post hoc analyses showed that the detected difference in motor skills was predominantly between the healthy control group (n3) and both the treated and untreated groups (n1 and n2). This led to the conclusion that the observed difference could be attributed to factors other than propranolol itself, such as parental education levels and socioeconomic status.
Furthermore, the cumulative effect of propranolol was investigated by comparing BSID-III scores of untreated children (n2) with those of infants who received propranolol for less than 16 months (n1a) and for 16 months or more (n1b). However, no statistical significance was found. Wang et al. also demonstrated that the use of propranolol for an average of 9.4 months did not cause any significant difference in IH patients compared to healthy controls [11]. We believe that the ongoing, active neuroplasticity, combined with multivariate and continuous stimuli for infants from the outside world, might have led to our inability to show any difference among groups.
A comprehensive literature review was conducted on the adverse effects of propranolol on the developing brain, yielding controversial results, particularly with regard to motor functions. In a study conducted by Wang et al., it was shown that propranolol, prescribed for complicated infantile hemangiomas (IHs), did not cause any significant neurodevelopmental delay or regression compared to healthy infants [11]. Similarly, Moyakine et al. demonstrated that the use of propranolol for the treatment of IH is not associated with gross and fine motor or psychomotor developmental defects [12,13,14]. However, Philipps et al. reported that, in their study, 146 of 188 children experienced delayed walking at 16 months of age, and significant changes in gross motor development occurred in infants with IH when propranolol treatment was stopped. This led them to raise concerns about the potential adverse effects of propranolol on the central nervous system (CNS) [15].
In our study, the level of maternal education appears to be the most significant factor impacting infant neurodevelopment in cognitive, linguistic, and motor domains. Conversely, paternal education correlated only with an infant’s cognitive functions. This difference between the effects of parental education on infant neurodevelopment might be due to unbalanced childcare responsibilities among Turkish parents. Earlier works by Ronfani et al. have demonstrated that socioeconomic status and, in particular, maternal education levels are closely and positively correlated with the cognitive and linguistic functions of infants [16]. In that same study, they found infants’ motor functions to be directly affected by maternal IQ [16]. Premkumar et al. also highlighted that parents’ educational attainment, specifically those levels equal to or greater than a high school degree, had a proportional effect on an infant’s cognitive and linguistic skills, as assessed by the BSID-III test at 18 months of age [17].
The main strength of our study lies in the incorporation of three groups: propranolol treated IHs, untreated IHs, and healthy control groups. We believe that by recruiting children into these three groups, we can better illuminate the potential adverse effects of propranolol on neurodevelopment. The BSID-III demonstrates robust and reliable validity in neurodevelopmental screening, and it also shows excellent inter-rater reliability. As far as we are aware, this study is the first to include three groups and utilize the BSID-III test concurrently.
One of the most significant limiting factors of our study is its cross-sectional design. We believe that neurodevelopment, a unique and magnificent process, occurs throughout life, suggesting that assessments of neurodevelopmental status should not be performed cross-sectionally but prospectively. Future studies should consider a broader range of variables, including demographic and socioeconomic data, to provide a more comprehensive understanding of the factors influencing neurodevelopment in this population.
5. Conclusions
In conclusion, our study did not demonstrate any significant developmental delays in IH patients receiving propranolol compared to untreated IH patients and healthy children. Nevertheless, we advocate for further research using a prospective design and larger samples.
Author Contributions
The study named “Neurodevelopmental Effects of Propranolol Treatments During Infancy in Infantile Hemangioma Patients” was prepared with shared efforts of the listed authors. C.B., G.K., Ö.Ö.A. and H.G.T. designed the study. M.M.Ç. and M.A. performed the BSID-III Test. A.B.K. performed the statistical analyses and reviewed the tables and figures. C.B. and H.G.T. wrote the draft manuscript. Z.K., A.Ü., S.K., D.T., G.K., E.G.G. and Ö.Ö.A. reviewed and commented on the draft manuscript. M.A., H.G.T. and C.B. revised the manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
This study received approval from the Ethics Committee of the Istanbul Medical Faculty, Istanbul University on 25 September 2020 (File Number: E-29624016-050.99-2135793/25.09.2020-2135793). All procedures adhered to the approved study protocols by the same Ethics Committee and were in alignment with the Declaration of Helsinki. A written consent form was taken from the parents of all eligible children prior to participation in the study.
Informed Consent Statement
Not applicable.
Data Availability Statement
All the data in relation to this study were stored in İstanbul University, İstanbul Medical Faculty Hospital, and can be presented upon reasonable request to the corresponding author of the published work.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Rodríguez Bandera, A.I.; Sebaratnam, D.F.; Wargon, O.; Wong, L.F. Infantile hemangioma. Part 1: Epidemiology, pathogenesis, clinical presentation and assessment. J. Am. Acad. Dermatol. 2021, 85, 1379–1392. [Google Scholar] [CrossRef] [Scilit]
- Leung, A.K.C.; Lam, J.M.; Leong, K.F.; Hon, K.L. Infantile Hemangioma: An Updated Review. Curr. Pediatr. Rev. 2021, 17, 55–69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Anderson, K.R.; Schoch, J.J.; Lohse, C.M.; Hand, J.L.; Davis, D.M.; Tollefson, M.M. Increasing incidence of infantile hemangiomas (IH) over the past 35 years: Correlation with decreasing gestational age at birth and birth weight. J. Am. Acad. Dermatol. 2016, 74, 120–126. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Léauté-Labrèze, C.; Dumas de la Roque, E.; Hubiche, T.; Boralevi, F.; Thambo, J.B.; Taïeb, A. Propranolol for severe hemangiomas of infancy. N. Engl. J. Med. 2008, 358, 2649–2651. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, X.; Liao, X.; Chen, C.; Zhang, L.; Sun, S.; Wan, M.; Liu, J.; Huang, L.; Yang, D.; Hu, H.; et al. Propranolol hydrochloride induces neurodevelopmental toxicity and locomotor disorders in zebrafish larvae. Neurotoxicology 2022, 93, 337–347. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, Y.; Barsegyan, A.; Nadif Kasri, N.; Roozendaal, B. Basolateral amygdala noradrenergic activity is required for enhancement of object recognition memory by histone deacetylase inhibition in the anterior insular cortex. Neuropharmacology 2018, 141, 32–41. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mallet, C.; Chick, C.F.; Maatoug, R.; Fossati, P.; Brunet, A.; Millet, B. Memory reconsolidation impairment using the β-adrenergic receptor blocker propranolol reduces nightmare severity in patients with posttraumatic stress disorder: A preliminary study. J. Clin. Sleep. Med. 2022, 18, 1847–1855. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sebaratnam, D.F.; Rodríguez Bandera, A.L.; Wong, L.F.; Wargon, O. Infantile hemangioma. Part 2: Management. J. Am. Acad. Dermatol. 2021, 85, 1395–1404. [Google Scholar] [CrossRef] [Scilit]
- Balasundaram, P.; Avulakunta, I.D. Bayley Scales of Infant and Toddler Development. In StatPearls; StatPearls Publishing LLC.: Treasure Island, FL, USA, 2023. [Google Scholar]
- Léauté-Labrèze, C.; Hoeger, P.; Mazereeuw-Hautier, J.; Guibaud, L.; Baselga, E.; Posiunas, G.; Phillips, R.J.; Caceres, H.; Gutierrez, J.C.L.; Ballona, R.; et al. A randomized, controlled trial of oral propranolol in infantile hemangioma. N. Engl. J. Med. 2015, 372, 735–746. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, C.; Wang, Q.; Xiang, B.; Chen, S.; Xiong, F.; Ji, Y. Effects of Propranolol on Neurodevelopmental Outcomes in Patients with Infantile Hemangioma: A Case-Control Study. BioMed Res. Int. 2018, 2018, 5821369. [Google Scholar] [CrossRef] [Scilit]
- Moyakine, A.V.; Hermans, D.J.; Fuijkschot, J.; van der Vleuten, C.J. Propranolol treatment of infantile hemangiomas does not negatively affect psychomotor development. J. Am. Acad. Dermatol. 2015, 73, 341–342. [Google Scholar] [CrossRef] [Scilit]
- Moyakine, A.V.; Kerstjens, J.M.; Spillekom-van Koulil, S.; van der Vleuten, C.J. Propranolol treatment of infantile hemangioma (IH) is not associated with developmental risk or growth impairment at age 4 years. J. Am. Acad. Dermatol. 2016, 75, 59–63.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moyakine, A.V.; Spillekom-van Koulil, S.; van der Vleuten, C.J.M. Propranolol treatment of infantile hemangioma is not associated with psychological problems at 7 years of age. J. Am. Acad. Dermatol. 2017, 77, 105–108. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Phillips, R.J.; Penington, A.J.; Bekhor, P.S.; Crock, C.M. Use of propranolol for treatment of infantile haemangiomas in an outpatient setting. J. Paediatr. Child. Health 2012, 48, 902–906. [Google Scholar] [CrossRef] [Scilit]
- Ronfani, L.; Brumatti, L.V.; Mariuz, M.; Tognin, V.; Bin, M.; Ferluga, V.; Knowles, A.; Montico, M.; Barbone, F. The Complex Interaction between Home Environment, Socioeconomic Status, Maternal IQ and Early Child Neurocognitive Development: A Multivariate Analysis of Data Collected in a Newborn Cohort Study. PLoS ONE 2015, 10, e0127052. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Premkumar, A.; Mele, L.S.; Casey, B.M.; Varner, M.W.; Sorokin, Y.; Wapner, R.J.; Thorp, J.M.J.; Saade, G.R.; Tita, A.T.; Rouse, D.J.; et al. Relationship Between Maternal Economic Vulnerability and Childhood Neurodevelopment at 2 and 5 Years of Life. Obstet. Gynecol. 2021, 138, 379–388. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).