


Abstract
β-blockers (BBs) remain a cornerstone therapy for cardiovascular disorders, reducing heart rate, blood pressure, and arrhythmia risk. Yet, their influence extends well beyond the heart, impacting renal function, inflammatory responses, metabolism, and endocrine balance. Although cardio-selective BBs are designed to minimize off-target effects, they still modulate immune signaling and hormonal pathways, producing paradoxical outcomes. Suppression of sympathetic tone and RAAS activity underpins therapeutic benefit but may also contribute to renal hypoperfusion, electrolyte imbalance, and pro-inflammatory changes, especially in patients receiving combination therapy with RAAS inhibitors or diuretics. Genetic polymorphisms (e.g., ADRB1, GRK5, eNOS, CYP2D6) and comorbidities further shape individual responses. This review integrates cardiovascular, renal, and immune perspectives to map the pathways by which BBs influence systemic homeostasis, highlighting cytokine interactions and disease-specific remodeling. We emphasize the need for personalized, biomarker-guided strategies, leveraging pharmacogenomics, multi-omics, and machine learning tools to optimize BB selection and dosing. By reframing BBs as dynamic modulators of the cardio-renal-immune axis, this review advances their role in precision cardiovascular medicine.
1. Introduction
Cardiovascular (CV) disease remains the leading cause of morbidity and mortality worldwide. β-blockers (BBs), particularly cardio-selective agents, improve outcomes in congestive heart failure (CHF), coronary artery disease (CAD), post-myocardial infarction (MI), and arrhythmias by antagonizing β1-adrenergic receptors in the heart and kidneys. This blockade reduces cyclic AMP production, decreases Ca2+ influx, slows pacemaker depolarization, and suppresses renin release [1,2]. In a retrospective cohort study, BBs were associated with a lower risk of heart failure (HF) and sudden cardiac death (SCD), especially among patients without prior HF [3]. A meta-analysis further confirmed their benefit in HF, including in subgroups with renal impairment, though efficacy declined with worsening renal dysfunction [4].
BBs are now standard therapies in CV disease due to their ability to counter sympathetic drive, lowering heart rate (HR), blood pressure (BP), and myocardial oxygen demand (MOD). However, patient tolerance is strongly shaped by comorbidities such as chronic kidney disease (CKD), necessitating close clinical monitoring [4,5]. Beyond their cardiac actions, BBs reduce renal blood flow (RBF) and glomerular filtration rate (GFR) via β1-mediated inhibition of renin release [6,7]. In patients with impaired kidney function, these hemodynamic changes can exacerbate renal hypoperfusion and filtration decline, particularly when autoregulation is already compromised [7].
BB effects also extend to immune remodeling and vascular stability through indirect modulation of angiotensin II (ANG II), nitric oxide (NO), and oxidative stress, largely via suppression of the renin–angiotensin–aldosterone system (RAAS) [7,8]. While β1 receptor blockade may influence oxidative stress indirectly through neurohormonal pathways, this relationship remains not fully understood [6]. To maintain systemic homeostasis, compensatory mechanisms engage: the CV system adjusts baroreceptor sensitivity and autonomic tone, while the renal system activates RAAS and alters sodium and fluid handling to preserve blood pressure and intravascular volume [7,8].
This narrative review bridges classical hemodynamic mechanisms with emerging insights into neurohormonal, endocrine, and cytokine signaling, highlighting how these pathways collectively shape BB efficacy and risk. It emphasizes the clinical relevance of genetic polymorphisms, disease heterogeneity, and multi-system interactions in modulating the cardio-renal response to BB therapy. Finally, we propose biomarker-guided, personalized strategies to optimize BB use across overlapping CV and renal comorbidities.
2. Methods
This narrative review synthesizes peer-reviewed literature in cardiovascular pharmacology, immunologic signaling, renal physiology, and clinical medicine within a thematic framework suitable for narrative synthesis. Literature was identified through PubMed/MEDLINE and Google Scholar searches covering January 2010 to July 2025, using search terms including “β-blocker,” “cytokines,” “renin,” “aldosterone,” “atherosclerosis and vascular remodeling,” “chronic kidney disease,” “cardiovascular-renal homeostasis,” “hemodynamics,” “hormonal-immune modulation,” “genetic polymorphisms,” “precision medicine” and “hypertension.” Inclusion criteria comprised English full-text reports that provided mechanistic insights or clinically significant information on the physiologic and immunologic effects of BBs. Eligible sources included clinical trials, preclinical research, experimental models, and systematic reviews. Exclusion criteria omitted non-peer-reviewed literature, conference abstracts, case reports, and studies with limited methodological rigor or mechanistic relevance. To provide context for fundamental mechanisms, such as β-receptor selectivity, neurohormonal regulation, and inflammatory signaling, seminal publications predating the primary search window as well as standard pharmacology and cardiovascular training texts were also consulted.
3. Synthesis of Literature
This review incorporated 153 references spanning clinical trials, mechanistic studies, pharmacogenetic analyses, and translational reviews addressing the CV and renal effects of BBs. The included literature covered diverse topics such as hemodynamic regulation, cytokine and immune modulation, hormonal signaling, and receptor–genetic interactions, with an emphasis on HF, MI, CKD, and thyrotoxicosis. Because this review followed a narrative rather than a systematic methodology, a PRISMA flowchart was not applied. Instead, Table 1 and Table 2 summarize the key mechanistic and clinical studies, respectively, providing clarity and contextual relevance.
Table 1.
Mechanistic Domains of BBs: Selected Studies Linking Molecular Targets to Physiologic Effects. This table summarizes key mechanistic pathways influenced by β-blockers, linking specific molecular targets (e.g., β1/β2 receptors, RAAS components, NO signaling, inflammatory cytokines) to the physiologic outcomes observed with different β-blocker classes.
Table 2.
BBs in Clinical Practice: Linking Therapeutic Applications to Disease-Specific Mechanisms. This table outlines major clinical conditions treated with β-blockers and links each disease state to the primary underlying mechanism, the appropriate β-blocker class, and the resulting therapeutic benefits.
4. Disease-Specific Effects of β-Blockers
This review organizes the physiologic and molecular effects of BBs into four mechanistic domains: hemodynamics, inflammatory cytokines, hormonal signaling, and genetic mechanisms (Figure 1). This framework offers a versatile lens for understanding how BBs modulate CV and renal homeostasis across diverse clinical settings. Rather than focusing on individual disease states in isolation, this structure emphasizes mechanisms that span multiple pathologies, with disease-specific examples mapped onto these broader domains. For instance, hemodynamic modulation is pivotal in HF and post-MI care, endocrine signaling intersects with thyrotoxicosis and CKD, and genetic polymorphisms influence therapeutic response across conditions. This thematic approach allows clinicians and researchers to identify both shared pathways and disease-specific nuances through which BBs shape disease progression, therapeutic outcomes, and long-term consequences.
Figure 1.
Mechanistic Framework of BBs’ Effects on CV and Renal Homeostasis. The model integrates four key domains: (1) hemodynamic regulation, (2) inflammatory and immune signaling, (3) endocrine regulation, and (4) genetic and receptor-level mechanisms, highlighting representative markers such as IL-1β, IL-6, TNF-α, CRP, renin, aldosterone, BNP, ANP, T3/T4, and gene polymorphisms (e.g., ADRB1, CYP2D6).
4.1. β-Blockers in Cardiovascular Disease
4.1.1. Heart Failure (HF)
BBs reduce long-term mortality in chronic HF primarily by mitigating sustained adrenergic overdrive. In acute heart failure (AHF), especially in patients with hemodynamic instability or cardiogenic shock, continuing BB therapy can be unsafe and may trigger severe complications, necessitating an individualized risk–benefit assessment [39]. Registry data support this cautious approach: in the Kyoto Congestive Heart Failure (KCHF) study of 3817 patients with acute decompensated HF (ADHF), BB use at admission was independently associated with lower in-hospital mortality, particularly among patients with prior HF hospitalizations [27].
In HF with reduced ejection fraction (HFrEF), BBs consistently improve survival through suppression of sympathetic hyperactivity, reduction in MOD, and enhancement of left ventricular ejection fraction (LVEF) [40]. In contrast, in HF with preserved ejection fraction (HFpEF), characterized by diastolic dysfunction and lower neurohormonal activation, randomized trials have not demonstrated prognostic benefit from BB therapy [28]. Patients with HF with mildly reduced ejection fraction (HFmrEF, 41–49%) may exhibit enhanced RAAS and SNS activation and thus appear more responsive to neurohormonal therapies, including BBs, although robust, randomized evidence is lacking [41].
Pharmacogenomics strongly influences the BB response in HF. The ADRB1 Arg389Gly variant alters receptor sensitivity; Arg389 homozygotes demonstrate greater BB responsiveness, improved LVEF, and enhanced survival in HFrEF, though not consistently in acute coronary syndrome (ACS) populations [9,10,11,12]. The GRK5 Leu41 allele, more common in African American patients, produces a “genetic β-blockade” via enhanced receptor desensitization and is associated with improved outcomes [12]. Beyond desensitization, GRK5 phosphorylates histone deacetylase 5 (HDAC5), reversing maladaptive Gαq-mediated transcription and promoting adaptive myocardial remodeling [10]. Other polymorphisms, including ADRA2C, GRK4, and ADRB2 variants (Gly16Arg, Glu27Gln), are also under investigation as biomarkers of BB efficacy and tolerability, underscoring the potential for genotype-guided therapy [9,10,11,12]. Beyond genetic determinants, immunomodulation represents an emerging therapeutic axis. BBs such as carvedilol and bisoprolol inhibit pro-inflammatory cytokines, including tumor necrosis factor-α (TNF-α) and interleukin-6 (IL-6), disrupt the cytokine–reactive oxygen species (ROS) amplification cycle, and restore endothelial nitric oxide synthase (eNOS) homeostasis. These findings position BBs not only as hemodynamic modulators but also as potential regulators of inflammatory remodeling in HF [42].
4.1.2. Post-Myocardial Infarction (MI)
Post-MI therapy with BBs attenuates SNS hyperactivity and stabilizes cardiac electrical conduction via β-adrenergic receptor blockade, resulting in significant reductions in mortality, reinfarction, and ventricular arrhythmias [32,33,34,43]. Through selective inhibition of myocardial β1-receptors, BBs reduce HR, myocardial contractility, and BP, thereby lowering MOD and limiting infarct expansion [44,45]. Recent findings suggest that BBs can modulate immune-inflammatory responses following MI by suppressing pro-inflammatory cytokines such as TNF-α and IL-6, decreasing leukocyte recruitment, limiting infarct-related remodeling, and maintaining myocardial tissue [46]. However, chronic β-receptor blockade can impair hepatic glycogenolysis and gluconeogenesis, increasing the risk of hypoglycemia, particularly in diabetic patients [33,44,46]. Thus, clinicians must balance the survival benefits of BB therapy against potential metabolic hazards, with vigilant glucose monitoring recommended to optimize outcomes [34,45]. Genetic polymorphisms, including PAI-1 (4G/5G), MMP-3 (5A/6A), IL-18, LDLR, APOA5, LTA, LGALS2, AT2 (−1332 G/A), ALDH2 (RS671), CX37, AKAP12, and GLRA2, have been associated with MI risk through pathways involving fibrinolysis, lipid metabolism, vascular inflammation, endothelial function, and contractility [47]. While the clinical application of pharmacogenetics to BB therapy remains investigational, β1-selective agents such as metoprolol and bisoprolol show promise by reducing sympathetic activation, suppressing inflammatory cytokine activity, and inhibiting renin release in genetically susceptible populations [46,47].
4.1.3. Acute and Chronic Coronary Diseases
In ACS, BBs are primarily used for symptom relief and reduction in arrhythmias and ischemia [48]. Current guidelines recommend early oral administration within 24 h of presentation when no contraindications exist, whereas routine early intravenous use is discouraged in patients at risk of cardiogenic shock [48]. In chronic CAD, BBs reduce HR, myocardial contractility, and arterial pressure, thereby lowering MOD and improving anginal symptoms [49]. However, routine long-term use for outcome improvement is not generally supported unless another indication exists, such as recent MI, LVEF ≤ 50%, or arrhythmia; thus, therapy should be individualized [49]. Potential adverse effects of prolonged treatment include fatigue and sexual dysfunction, particularly in younger patients, possibly related to endothelial dysfunction and diminished NO bioavailability [50].
Across both ACS and stable CAD, BBs restore supply-demand balance and can improve outcomes, though long-term use may be associated with adverse CNS or metabolic effects [48,49,50]. Pro-inflammatory cytokines, including IL-12p70 and IL-17, are independently associated with CAD severity [51], suggesting a potential immunomodulatory role of BBs beyond hemodynamic effects. Given that CAD itself may produce ECG abnormalities such as poor R-wave progression [52], and BBs can cause bradycardia or atrioventricular block, careful ECG and HR monitoring during initiation and titration is essential [53].
Supporting selective use, a large new-user cohort study of 28,039 patients ≥ 66 years old with angiographically confirmed obstructive CAD (without recent MI or HF) demonstrated that BB initiation within 90 days of angiography was associated with a modest but significant reduction in the 5-year composite outcome of all-cause death, MI, or HF hospitalization (HR 0.92; 95% CI 0.86–0.98; p = 0.006), driven primarily by a reduction in MI hospitalizations (HR 0.87; 95% CI 0.77–0.99), with no effect on overall mortality or HF outcomes [29]. Finally, genetic factors may influence CAD pathogenesis and BB responsiveness. TGFβ1 and its receptor polymorphisms have been linked to vascular inflammation and extracellular matrix (ECM) remodeling [54]. In addition, ADRB1 (Arg389Gly) and ADRB2 (Gly16Arg, Glu27Gln) variants have been associated with altered β-adrenergic signaling and treatment efficacy, reinforcing the potential role of pharmacogenetics in tailoring BB therapy [9,10,11,12].
4.1.4. Arrhythmias
In hereditary arrhythmogenic disorders, such as catecholaminergic polymorphic ventricular tachycardia (CPVT), BBs, particularly propranolol, are a cornerstone therapy for preventing sudden cardiac death (SCD) by reducing catecholamine-induced excitability and suppressing ventricular arrhythmias (Figure 2) [55]. According to the Vaughan Williams classification, antiarrhythmic drugs are categorized into four main classes based on their mechanisms of action: Class I (fast sodium channel blockers), Class II (β-blockers), Class III (potassium channel blockers), and Class IV (calcium channel blockers). As Class II agents, BBs act primarily by reducing the slope of phase 4 depolarization in pacemaker cells, slowing conduction through the atrioventricular node, and prolonging the effective refractory period, thereby reducing HR and suppressing arrhythmias [56]. In other contexts, such as during electroconvulsive therapy (ECT), BBs stabilize hemodynamics by blunting HR peaks with minimal additional adverse effects [57]. Beyond their electrophysiologic actions, certain BBs may exert pleiotropic effects on vascular and inflammatory processes, though the clinical relevance of these effects for arrhythmia prevention remains under investigation [1]. BB pharmacokinetics are influenced by genetic polymorphisms. For example, CYP2D6 variation alters metoprolol exposure: poor metabolizers (PMs) exhibit elevated plasma concentrations and increased risk of bradycardia, whereas ultra-rapid metabolizers (UMs) may require alternative dosing strategies due to reduced efficacy [58]. These findings support a personalized approach to BB therapy, including careful dose titration and, when feasible, genotype-guided selection to maximize efficacy and safety in CV management, particularly in genetically vulnerable populations.
Figure 2.
Electrophysiological Effects of Class II BBs on Pacemaker Action Potential. The drugs reduce the slope of phase 4 depolarization in pacemaker cells, slowing conduction through the atrioventricular node, and prolonging the effective refractory period, which collectively reduces heart rate and suppresses arrhythmias [56].
4.2. β-Blockers and Renal System Dysfunction
4.2.1. Chronic Kidney Disease (CKD)
In patients with CKD, BBs help reduce cardiac load and may lower the markedly elevated risk of SCD, which can be up to 50 times higher in end-stage renal disease compared with that in the general population [31]. BBs suppress sympathetic overactivity, reduce afterload, and normalize BP, improving cortical and medullary oxygenation and potentially offering renal protection, though long-term benefits remain uncertain [59]. CKD is characterized by chronic inflammation, oxidative stress, and RAAS hyperactivation. While direct evidence for cytokine modulation is limited, BBs may exert anti-inflammatory effects through sympathetic-immune regulation [31]. By inhibiting renin secretion, BBs can counteract RAAS hyperactivation. When combined with RAAS inhibitors, BBs may provide better BP control with reduced volume-mediated nephrotoxicity [31]. Evidence from meta-analyses indicates that BB therapy in CKD patients with systolic HF is associated with a 28% relative reduction in all-cause mortality (RR 0.72) and a 34% relative reduction in cardiovascular mortality (RR 0.66). However, the therapy increases the risk of bradycardia and hypotension, especially in patients on dialysis [35]. While BBs are not considered first-line therapy in CKD patients without HF, vasodilating BBs such as carvedilol, an agent that block α1, β1, and β2 adrenergic receptors, offer renal-protective and metabolic benefits, making them reasonable second- or third-line therapeutic options [31,36]. Pharmacogenomic variability may influence BB efficacy and safety in CKD. Polymorphisms in ADRB1 (Arg389Gly), ADRB2 (Gly16Arg, Glu27Gln), CYP2D6 metabolism, and eNOS (NOS3) variants (Glu298Asp, –786T>C) may alter therapeutic response, vascular protection, and risk of adverse effects, particularly in patients with CV comorbidities or those undergoing dialysis [9,10,11,12,60,61].
4.2.2. Diabetic Nephropathy (DN)
Response to BBs in DN may be influenced by patient-specific genetic factors that intersect with hemodynamic, inflammatory, and oxidative stress pathways. Polymorphisms in genes such as ACE, IL-6, TNF-α, COL4A1, eNOS, SOD2, APOE, and GLUT1 have been implicated in DN progression, highlighting the role of genetic determinants in disease pathophysiology [62]. For example, ACE I/D variants modulate RAAS activity, a pathway indirectly inhibited by BBs through sympathetic suppression [62]. BBs may also modulate chronic low-grade inflammation by intersecting with TNF-α and IL-6 signaling, while polymorphisms in eNOS and SOD2 influence NO bioavailability and oxidative stress. Antioxidant BBs, such as carvedilol and nebivolol, may confer renal protection under these conditions [62,63]. Metabolic regulation is also relevant: impaired GLUT1/GLUT4 expression, as observed in diabetic cardiomyopathy (DCM), affects glucose transport and cellular energy handling. BBs may indirectly improve this axis by lowering myocardial and renal metabolic demands and enhancing insulin sensitivity [63]. Furthermore, dysregulation of matrix metalloproteinase-2 (MMP-2), a key mediator of extracellular matrix remodeling in both DCM and DN, may be modulated by BB therapy, as evidenced by alterations in circulating MMP-2/TIMP-2 levels in CKD patients [61,63]. Collectively, these findings support a precision medicine approach in DN, wherein BB therapy could be tailored based on receptor profiling and genetic testing to optimize renal and cardiovascular outcomes.
4.3. Hormonal and Metabolic Effects of β-Blockers
Long-term BB therapy modulates the SNS and hypothalamic–pituitary–adrenal (HPA) axis, influencing adaptation to stress, hormonal homeostasis, and metabolic control over time [30,64]. Clinical and exercise studies indicate that both nonselective and β1-selective BBs significantly alter neurohormonal responses, namely cortisol, E, and prolactin during physical stress, but not baseline levels of hormones [65]. These alterations may blunt appropriate stress-induced hormonal peaks, potentially impairing physiological adaptation in the context of acute or chronic stress [30,64]. For example, in hypertensive men, propranolol or metoprolol infusion during exercise increased lactate levels and decreased free fatty acid mobilization, demonstrating BBs’ impact on energy substrate regulation under adrenergic stimulation [30]. BBs reduce cortisol release by inhibiting β-adrenergic stimulation of adrenal responsiveness to CRH and ACTH [66,67]. This mechanism has been reported to be anecdotally effective in subclinical cases of ACTH-independent macronodular adrenal hyperplasia (AIMAH) associated with Cushing’s syndrome, as demonstrated by a case in which propranolol normalized serum and urinary cortisol levels by blocking ectopically expressed β-adrenergic receptors in the adrenal cortex [68]. However, in the general population, chronic cortisol suppression has been suggested to compromise stress resilience, particularly among psychiatric or surgical patients [66,67]. BBs also influence thyroid hormone metabolism. Nonselective BBs such as propranolol inhibit 5′-deiodinase and hence decrease peripheral conversion of T4 to T3 and thereby decrease active thyroid hormone levels and alleviate the symptoms of hyperthyroidism, including tachycardia, tremor, and widened pulse pressure [37,38]. Propranolol is therefore useful in acute management of thyrotoxicosis. Conversely, in euthyroid or hypothyroid patients, propranolol may exacerbate fatigue, cold intolerance, or depression by further lowering T3 availability, underscoring the importance of monitoring thyroid function in long-term BB therapy [38].
Metabolically, BBs can impair glucose tolerance and increase insulin resistance. Vasodilatory BBs such as carvedilol appear to preserve insulin-mediated endothelial function and may be a better alternative in diabetic patients [69,70]. For example, metoprolol attenuates insulin-stimulated vasodilation, whereas carvedilol preserves endothelial responsiveness, demonstrating subclass-specific effects on metabolism [70]. BBs also suppress plasma renin activity, contributing to their antihypertensive efficacy. When combined with drugs that act on the RAAS, e.g., ACE inhibitors or diuretics; however, this suppression may increase the risk of hyperkalemia (especially in CKD), whereas hyponatremia is primarily associated with thiazide diuretics [71]. In conditions of mineralocorticoid excess or sodium retention, BBs can also alter renal hemodynamics and fluid balance. Therefore, individualized therapy is needed, particularly in comorbid patients [72]. Table 3 summarizes the key hormonal and metabolic effects associated with long-term BB therapy and provides a practical framework for clinical application.
Table 3.
Hormonal and Metabolic Effects of Long-term BB Therapy. This table summarizes the key hormonal and metabolic alterations associated with chronic BB use and offers a practical framework for clinical application.
5. Biochemical Pathways and Cytokine Interactions in BBs Therapy
All three β-adrenergic receptor subtypes (β1, β2, β3) primarily couple to Gs proteins, leading to adenylyl cyclase activation, increased cAMP, and downstream PKA-mediated effects, with tissue-specific expression and target proteins contributing to functional variation [73].
5.1. β-Adrenergic Receptor Interactions
5.1.1. β1 Receptor (Cardiac & Renal)
BBs reduce BP and improve vascular function primarily through negative chronotropic and inotropic effects, as well as the inhibition of renin release [73]. In ANGII-infused rabbit models, β1-adrenergic receptor stimulation is protective against NE-induced vasoconstriction and oxidative stress in renal afferent arterioles via cAMP-mediated signaling, which can be reversed by the β1-selective antagonist CGP-20,712A [7]. Certain BBs with intrinsic sympathomimetic activity (ISA), such as carteolol and alprenolol, possess partial agonist activity at β2-adrenergic receptors. Although experimental models show carteolol increases systolic BP, HR, and cAMP signaling in a dose-dependent manner independent of β1 blockade [13,14,45], in clinical practice ISA agents primarily attenuate bradycardia and preserve exercise HR without causing sustained BP elevation. They provide reduced survival benefit in HF due to reduced β-blockade but can be therapeutically useful in active hypertensives by maintaining vascular tone and CO while avoiding marked bradycardia.
Subclasses differ as carvedilol and labetalol provide additional vasodilation through α1-adrenergic receptor blockade, while nebivolol enhances endothelial NO bioavailability [74]. BBs also decrease HR and MOD, enhancing diastolic filling time and thereby improving coronary perfusion. These anti-ischemic effects make BBs particularly useful in stable angina and ischemic heart disease (IHD), where they counter excessive β-adrenergic stimulation by NE and E [74]. These mechanisms, along with subtype-specific actions, underscore their efficacy in HTN, ischemic disease, and HF [74,75]. By suppressing chronic sympathetic overactivity, BBs also facilitate reverse cardiac remodeling, improve systolic and diastolic left ventricular function, reduce preload and afterload, and suppress malignant arrhythmias. These synergistic actions alleviate anginal symptoms, lower MI risk, and improve long-term survival in patients with HF and IHD [75]. Furthermore, BBs stabilize cardiac electrophysiology through their negative chronotropic, dromotropic, and inotropic effects, making them first-line agents for ventricular rate control in atrial fibrillation and for preventing life-threatening arrhythmias. In congenital syndromes such as long QT syndrome and CPVT, BBs such as nadolol reduce syncope and SCD by inhibiting adrenergic-induced, calcium-dependent arrhythmogenic triggers [1,26,76].
In renal physiology, β1-adrenergic receptors on juxtaglomerular (JG) cells regulate renin release via SNS input-activated cAMP-dependent pathways. BBs inhibit this β1-mediated pathway and thereby inhibit renin release, dampen catecholamine effects, and downregulate the RAAS [15,16,77]. β2-receptor blockade in renal tubules has also been proposed to reduce sodium reabsorption, although the primary renal action of BBs remains β1-mediated inhibition of renin release. These actions necessitate close monitoring of renal function, especially with metabolic diseases such as diabetes, where RAAS dysregulation and renal injury are common [78,79]. Despite potential reductions in renal perfusion, BBs reduce oxygen demand in renal tissue, thereby supporting hemodynamic stability and mitigating ischemic stress in hypertension (HTN) and renovascular disease [59,80]. Table 4 illustrates the mechanisms by which β1-selective BBs influence cardiac and renal physiology.
Table 4.
Mechanisms of β1-Selective BBs in Cardiac and Renal Physiology. This table summarizes how β1-selective BBs regulate key cardiac and renal functions.
5.1.2. β2 Receptor (Vascular, Pulmonary, Metabolic)
β2-adrenergic receptors are expressed predominantly on bronchial smooth muscle, vascular endothelium, liver, pancreas, and skeletal muscle. Activation of β2-receptors normally induces bronchodilation, vasodilation, and metabolic regulation via Gs protein–coupled cAMP/PKA signaling [81]. Nonselective BBs, such as propranolol, inhibit both β1 and β2 receptors, producing clinically relevant effects by reducing bronchodilation, increasing vascular tone, and disrupting glucose homeostasis.
Loss of β2-mediated bronchodilation can cause bronchoconstriction and a reduction in FEV1, posing a particular risk in patients with asthma or COPD due to heightened airway responsiveness [82]. Additionally, β2-receptor blockade in the liver and skeletal muscle may reduce glycogenolysis and insulin-mediated glucose uptake, increasing the risk of hypoglycemia or impaired exercise tolerance, especially in diabetic or insulin-resistant patients [81,82].
Metabolically, β2-antagonism reduces hepatic glucose production by inhibiting glycogenolysis and gluconeogenesis, suppresses insulin release from pancreatic β-cells, increases circulating glucose levels, and masks adrenergic warning symptoms, such as tachycardia. These effects heighten the risk of hypoglycemia unawareness in insulin-treated patients and may worsen insulin resistance in individuals with visceral obesity or metabolic syndrome [83,84]. Cardioselective BBs (e.g., metoprolol, bisoprolol) largely spare β2 receptors and are therefore preferred in patients at risk of bronchospasm or metabolic complications. Vasodilating BBs, such as carvedilol, despite some β2 antagonism, functionally act as β2-sparing agents due to their α1-blockade and NO-mediated endothelial vasodilation. These agents enhance insulin sensitivity and provide metabolic benefits [70]. Propranolol also inhibits type I 5′-deiodinase, decreasing peripheral conversion of thyroxine (T4) to triiodothyronine (T3) [85]. This is beneficial in thyrotoxicosis by alleviating symptoms such as tachycardia and tremors but may exacerbate hypothyroid states with prolonged or excessive use. Figure 3 summarizes the systemic effects associated with nonselective β2-adrenergic receptor blockade, integrating pulmonary, vascular, metabolic, and endocrine consequences.
Figure 3.
The Systemic Effects Associated with Nonselective β2-adrenergic Receptor Blockade. This figure illustrates the pulmonary, vascular, metabolic, and endocrine effects resulting from nonselective β2-receptor blockade.5.1.3. β3 Receptor (Adipose Tissue, Metabolism).
β3-adrenergic receptors, although less commonly discussed, play important roles in adipose tissue, brown adipose tissue, and the urinary bladder, mediating lipolysis, thermogenesis, and detrusor muscle relaxation. Third-generation BBs, such as carvedilol and nebivolol, do not directly target β3 receptors but indirectly modulate β3-associated NO signaling pathways, enhancing endothelial function and promoting vasodilation, which contributes to improved CV [86]. These agents also modulate adipokine profiles by upregulating adiponectin and decreasing leptin, a shift that may improve insulin sensitivity, regulate appetite, and reduce long-term cardiometabolic risk. This is particularly relevant in patients with type 2 diabetes or obesity, where leptin dysfunction contributes to endothelial impairment and increased CV risk [87].
Thus, third-generation BBs exert an indirect effect on β3-adrenergic signaling, underscoring their broader metabolic and vascular impact. This is particularly relevant in patients with obesity, type 2 diabetes, or metabolic syndrome, where dysregulated leptin pathways and impaired β3 signaling may influence clinical outcomes. Figure 4 illustrates the physiological, metabolic, and clinical effects of β3 modulation by third-generation BBs in CV and metabolic contexts [86,87].
Figure 4.
β3-adrenergic Receptor Modulation Across Physiological, Metabolic, and Clinical Contexts. This figure depicts the key physiological, metabolic, and clinical effects of β3-receptor modulation by third-generation β-blockers.
6. Discussion
As discussed above, BBs remain a cornerstone in the treatment of CV conditions. However, their systemic influence extends far beyond the CV system, engaging a complex network of homeostatic, neurohormonal, immunologic, and renal pathways. This discussion integrates the interconnected physiological domains, particularly the RAAS, cytokine networks, NO signaling, and macrophage polarization to illustrate both the therapeutic benefits and potential drawbacks of long-term BB use, with renal involvement serving as a hallmark of chronic hemodynamic remodeling.
6.1. RAAS and Immune Modulation
BBs inhibit renin release by blocking β1-adrenergic stimulation of JG cells, thereby suppressing RAAS activation and downstream ANG II production [15,16]. RAAS inhibition provides CV and renal protection through BP lowering and antifibrotic effects, especially in HF and CKD [31,36]. ANG II promotes pro-inflammatory signaling via AT1 receptor (AT1R)-mediated activation of protein kinase C (PKC), STAT1, and NF-κB, which increases IL-6 secretion and cyclooxygenase-2 (COX-2) expression [17,88,89]. These cascades drive vascular remodeling, renal injury, and chronic inflammation. By contrast, AT2 receptor (AT2R) activation exerts anti-inflammatory effects through upregulation of PPARγ and suppression of NF-κB activity, thereby reducing IL-6 signaling [90]. COX-2 amplifies inflammation by generating prostaglandin E2 (PGE2). While PGE2 induces vasodilation via EP2/EP4 receptors, it paradoxically suppresses inducible NO synthase (iNOS) expression, lowering NO availability in immune cells. This dual role diminishes NO-mediated immune regulation in chronic inflammatory states [91,92,93]. In DN, hyperglycemia-induced COX-2 overexpression in podocytes contributes to proteinuria, mesangial expansion, and podocyte foot process effacement, changes that are attenuated by RAAS inhibition or COX-2 blockade [91,92,93]. By limiting ANG II generation, BBs indirectly modulate this axis by suppressing AT1R-driven COX-2 expression, PGE2 release, and downstream pro-inflammatory signaling. This restores immune balance via the COX-2–PGE2–iNOS pathway, reduces chronic inflammation, and preserves renal function, particularly in patients with metabolic or inflammatory comorbidities [31,36,91,92,93].
Aldosterone and antidiuretic hormone (ADH), both downstream of RAAS, also contribute to fluid and electrolyte homeostasis. Their activity is indirectly regulated by BB-mediated RAAS suppression [94]. While COX-2 does not directly control renin release, it mediates many ANG II-dependent vascular and immune responses [16,95]. Thus, by inhibiting β1-mediated renin release, BBs curb ANG II formation, blunt AT1R-driven inflammatory cascades, and mitigate COX-2/PGE2 dysregulation (Table 5). This integrated mechanism underpins their cardio-renal protective and immunomodulatory benefits [17,96].
Table 5.
Downstream Molecular Pathways Modulated by β-Blockers. This table illustrates how BBs modulate key downstream pathways, including inhibition of the RAAS pathway, regulation of COX-2 expression, modulation of PGE2–iNOS–NO signaling, and suppression of aldosterone activity. Notably, PGE2 can paradoxically inhibit iNOS and NO production in immune cells, which may contribute to altered immune responses during chronic inflammation.
However, ANG II adds complexity to IL-6 modulation through its interaction with AT1R and AT2R. AT1R promotes PKCδ, STAT1, and other pro-inflammatory pathways and induces IL-6 production, leading to tissue damage and chronic inflammation [97,98]. Alternately, AT2R signaling elicits anti-inflammatory responses through the enhancement of peroxisome PPARγ activation or inhibition of NF-κB activity, which decreases IL-6 expression and reduces inflammation [90,99]. This balance demonstrates the context-dependent nature of ANG II effects on inflammatory responses via AT1R or AT2R signaling, as shown in Figure 5.
Figure 5.
ANGII Modulation of IL-6 via AT1R and AT2R Pathways, adapted from prior studies. AT1R-driven signaling via PKC, STAT1, and NF-κB promotes IL-6 and COX-2 expression, whereas AT2R-mediated PPARγ activation and NF-κB suppression counteract inflammation. Although current evidence highlights these opposing mechanisms, further mechanistic mapping and disease-specific studies are needed to fully delineate these pathways [17,88,90,91,92,95,96,98,99].
In addition to the AT1R- and AT2R-mediated cytokine signaling outlined above, systemic vascular tone also depends upon a balance between vasoconstrictors and vasodilators. ANG II, ACTING through AT1R, remains one of the most potent vasoconstrictors, both raising vascular resistance and inducing COX-2 expression with downstream generation of prostaglandins such as PGE2 [17,88,89,95]. This convergence of mechanical stress and inflammatory signaling synergistically enhances fibrosis and endothelial dysfunction. Counter-regulatory mediators such as NO, prostacyclin (PGI2), and bradykinin oppose these effects by inducing vasodilation and, in some cases, attenuating COX-2-mediated pathways [91,92,93]. BBs suppress renin secretion and thereby diminish ANG II-mediated vasoconstrictive and COX-2-inducing impacts [15,16,80,96,100], while RAAS inhibitors act more directly at the receptor or enzymatic level [31,36]. Together, these mechanisms of therapy shift the hemodynamic and immunologic balance away from ANG II-induced vasoconstriction and inflammation to vasodilation, vascular protection, and preservation of organ function in the long term [80,90,96,100].
6.2. Nitric Oxide and Vascular Homeostasis
BB-mediated inhibition of RAAS signaling indirectly suppresses downstream effectors such as COX-2 and PGE2, thereby modulating NO bioavailability, a central determinant of vascular tone, renal perfusion, fluid-electrolyte balance, and immune homeostasis. NO is generated by three NOS isoforms: endothelial NOS (eNOS), neuronal NOS (nNOS), and inducible NOS (iNOS), each activated under distinct physiological or pathological conditions [18].
BBs-mediated inhibition of RAAS signaling indirectly suppresses downstream effectors such as COX-2 and PGE2, thereby modulating NO bioavailability, a critical regulator of vascular tone, renal perfusion, fluid-electrolyte balance, and immune homeostasis. NO is produced by three NOS isoforms: eNOS, neuronal NO synthase (nNOS), and inducible iNOS, each regulated under distinct physiological or pathological conditions [18]. In inflammatory and immunological settings, PGE2 modulates iNOS expression via interferon regulatory factor 1 (IRF1), and prolonged suppression of COX-2/PGE2 during BB therapy may reduce iNOS-derived NO [101,102,103]. This can lead to NO deficiency, promoting vascular dysfunction, platelet activation, and cytokine imbalance, particularly in patients with diabetes or CKD [104]. Beyond immunity, nNOS-derived NO contributes to neurohormonal regulation by influencing vasopressin, oxytocin, and atrial natriuretic peptide (ANP) release through COX-2 and adenosine pathways [105,106,107,108,109,110]. BB-induced suppression of ANG II and RAAS activity may blunt this signaling, predisposing patients to hyponatremia, fluid overload, or impaired hormonal feedback, especially when combined with diuretics or ACE inhibitors [107,110,111]. In the kidney, NO maintains afferent arteriolar vasodilation, GFR, and tubuloglomerular balance. Excessive RAAS blockade or reduced iNOS activity may impair these mechanisms, causing renal hypoperfusion, vasoconstriction, and ischemic tubular injury. The risk is heightened with the NSAID use, dehydration, or polypharmacy involving RAAS inhibitors and diuretics [112]. Furthermore, reduced GFR has been linked with an expansion of terminally differentiated T cells (e.g., CD11a++CD28−CD57+), which impair immune resolution and tissue repair [113,114,115]. Conversely, third-generation BBs such as Nebivolol exert favorable NO-related effects. By stimulating eNOS, activating AMP-activated protein kinase (AMPK), and promoting GLUT4 translocation, Nebivolol enhances endothelial function, induces vasodilation, and improves insulin sensitivity in patients with diabetes or metabolic syndrome [79,116,117,118]. Nebivolol also downregulates pathological iNOS activity, preserving protective NO signaling without exacerbating oxidative stress [19].
Together, these findings highlight the therapeutic duality of BB-induced NO modulation: depending on the agent, dose, and comorbid context, effects can either impair vascular-renal balance or enhance cardiometabolic outcomes. Figure 6 illustrates these interactions across RAAS suppression, COX-2/PGE2 pathways, NOS isoforms, and their vascular, renal, and immune consequences.
Figure 6.
Angiotensin II–mediated signaling pathways regulating COX-2 expression. Binding of ANG II to AT1R activates the mitogen-activated protein kinase (MAPK) and NF-κB pathways, as well as phospholipase A2 (PLA2). Crosstalk between PKC and MAPK enables PKC to activate Raf-1 and downstream ERK, leading to ERK-mediated transcriptional regulation of the COX-2 gene [79,116]. In parallel, PKC activates IκB kinase (IKK) within the NF-κB pathway, further promoting COX-2 expression [117].
6.3. Immune Remodeling and Macrophage Polarization
Persistent ANG II signaling remodels the vasculature through both structural and immunologic mechanisms. Structurally, AT1R activation induces smooth muscle hypertrophy and extracellular matrix (ECM) accumulation via profibrotic pathways, including TGF-β, MAPK, and MMP cascades, leading to arterial fibrosis and stiffening [17,88,95,119,120]. Immunologically, ANG II skews macrophage polarization toward the pro-inflammatory M1 phenotype. These M1 macrophages release cytokines such as TNF-α, IL-6, and IL-1β, thereby amplifying vascular inflammation and renal injury [120,121]. In contrast, AT2R activation promotes M2 macrophage differentiation, which supports tissue repair and fibrosis resolution through PPARγ activation and NF-κB modulation [90,99]. Clinically, these signaling programs translate into distinct cardiac outcomes. Pressure overload drives concentric hypertrophy and fibrosis, volume overload induces eccentric dilation, and post-MI recovery hinges on a timely transition from M1 to M2 macrophages to stabilize scar formation. BBs, particularly when combined with ACE inhibitors, facilitate this reparative shift by lowering wall stress, suppressing inflammation, and preserving structural integrity [122,123,124,125]. Atherosclerosis further illustrates maladaptive immune remodeling. ANG II enhances monocyte adhesion to activated endothelium, promotes macrophage differentiation, and increases ROS production [126,127]. These processes drive endothelial dysfunction, smooth muscle migration, and ECM deposition, forming fibrous caps that can be destabilized by MMP overactivity, precipitating rupture and acute coronary syndromes [128,129]. Ultimately, the balance between M1 and M2 macrophages dictates whether vascular remodeling culminates in progressive damage or reparative healing [130,131].
6.3.1. M1 Pro-Inflammatory Signaling
BBs modulate immune dynamics indirectly through neurohormonal and renal mechanisms. By suppressing renin release, they attenuate RAAS-mediated sodium retention and vasoconstriction, thereby contributing to blood pressure control and renal protection [132,133,134,135]. These renal effects extend into immunomodulation, particularly in shaping macrophage polarization. In CKD and related disease states, macrophages are preferentially skewed toward the pro-inflammatory M1 phenotype. Clinical and translational studies support this association, showing that systemic inflammation, characterized by elevated TNF-α, IL-6, and IL-10, along with altered immune checkpoints such as PD-1, is highly prevalent in HF and atrial fibrillation, reinforcing the role of immune dysregulation in cardio-renal syndromes [24,136]. At the molecular level, pathogenic processes are amplified by intracellular signaling cascades including Notch, NF-κB, JAK-STAT, and PI3K-AKT, which sustain inflammatory activation and propagate tissue injury [137,138,139,140]. Collectively, these cytokines and signaling pathways constitute central therapeutic targets for limiting immune-mediated kidney injury and the broader spectrum of cardio-renal syndromes.
6.3.2. M2 Reparative and Fibrotic Roles
In contrast to M1-mediated inflammation, immune resolution and tissue repair are associated with M2 macrophage activities. Polarized by IL-4, IL-10, or IL-13, M2 macrophages orchestrate anti-inflammatory responses and fibrotic signaling through TGF-β1/Smad3, with NLRP3 inflammasome activation in certain contexts [25]. While protective in acute tissue injury, chronic M2 activation may contribute to maladaptive fibrotic remodeling. Thus, the M2 macrophage repair-fibrosis function is highly context-dependent and relies on temporal and spatial cues from the surrounding microenvironment [25].
6.3.3. CD206+ Macrophages and Macrophage-to-Myofibroblast Transition (MMT)
In CKD, CD206+ macrophages accumulate at sites of tubular injury, and a subset can undergo MMT, a phenotypic shift directly engaged in interstitial fibrosis through acquiring α-smooth muscle actin (α-SMA) expression and a profibrotic phenotype [137,138,139]. MMT is regulated by a complex web of signaling involving TGF-β1, Smad3, Notch, JAK-STAT, PI3K/AKT, Wnt, Hedgehog, RHO/ROCK, and TNF-α pathways [23,25,141]. This switch not only highlights fibrotic remodeling but also provides a critical checkpoint in the transition from inflammation to chronic structural injury in the kidney. Significantly, Smad3 knockout models reduced CD206+ MMT cells and renal fibrosis and suggested that selective targeting of this pathway may have therapeutic value [23]. Targeting surface antigens such as CD206 or Smad3 and TGF-β1 pathways would enable precision-guided immunotherapy to suppress chronic fibrosis without impairing essential repair function.
7. Future Directions
Beyond their established cardiac roles, BBs act as systemic regulators by suppressing renin release and modulating downstream RAAS activity, thereby influencing vascular tone, fluid-electrolyte balance, immune signaling, and endothelial function [9,10,11,12]. These multidimensional effects highlight the need for integrative research that combines endocrine, immune, and hemodynamic readouts, supported by systems biology and omics-based approaches [142,143,144]. Clinical gaps remain. In CHF, BBs improve LVEF and survival, yet their efficacy in HFpEF and acute decompensation is variable and strongly influenced by genetic polymorphisms such as ADRB1 Arg389 and GRK5 Leu41 [15,16,89,91,92,93,94]. In CAD, BBs may modulate cytokines (e.g., IL-12p70, IL-17), but direct immunologic effects remain incompletely characterized [31]. In DN and metabolic disease, genotype-dependent responses linked to ACE I/D, eNOS, and SOD2 polymorphisms complicate drug selection, while non-vasodilating BBs can exacerbate insulin resistance and dyslipidemia. By contrast, third-generation agents (e.g., carvedilol, nebivolol) provide vasodilatory and metabolic advantages, supporting comparative studies tailored to genetic, metabolic, and inflammatory profiles [18,36,38,63,70,79,91,92,93,104,117,145]. Therapeutic innovation remains essential. Combination strategies with nonprotective agents, such as ACE inhibitors, COX-2 modulators, or IL-1β blockers, may mitigate immune and renal side effects [95,96,100,145]. Optimization of drug timing, sequencing, and duration also requires further investigation, particularly with respect to circadian RAAS activity and cytokine oscillations. Precision medicine offers the greatest potential. Pharmacogenomic markers (ADRB1, GRK5, CYP2D6, eNOS) and multi-omics data (transcriptomics, metabolomics, proteomics) integrated with machine learning (ML) can stratify patients by BB responsiveness, adverse event risk, and inflammatory phenotype [142,143,144]. Such tools may evolve into adaptive prescribing platforms that dynamically guide BB initiation, titration, and discontinuation, like current protocols for insulin or anticoagulation therapy. Finally, policy and classification frameworks must evolve. Current BB categories based on cardioselectivity or generation may be inadequate. Future classification should incorporate molecular target profiles, pharmacogenomic concordance, and disease-specific indications [146,147,148]. Vasodilating BBs may be preferred in metabolic syndrome, while ultra-selective BBs could offer safer options in patients with airway disease or cognitive impairment.
Ultimately, the transition from fixed, conventional prescribing protocols to dynamic, biomarker-guided strategies has the potential to redefine BBs as precision medicines capable of safely modulating the interconnected CV, renal, and immune systems [149,150,151,152].
8. Conclusions
BBs remain foundational therapies for CV diseases, including HF, MI, arrhythmias, and HTN. Their benefits arise primarily from sympathetic inhibition and renin suppression, which improve hemodynamics and reduce maladaptive remodeling. However, these same mechanisms can paradoxically produce adverse effects, such as renal hypoperfusion, pro-inflammatory immune activation, and ECG abnormalities. This risk is particularly pronounced in patients receiving “triple therapy” with BBs, RAAS inhibitors, and diuretics, where AKI incidence is elevated, underscoring the need for vigilant monitoring. The pleiotropic effects of BBs are strongly influenced by patient-specific factors, including baseline renal function, cytokine profiles, and genetic polymorphisms (e.g., ADRB1, GRK5, eNOS, CYP2D6). Future strategies should emphasize synergistic use of RAAS modulators, COX-2-targeted approaches, and selective immunotherapies (e.g., IL-1β blockade) to preserve renal function while optimizing CV remodeling.
Emerging biomarker-guided and ML platforms offer the potential to integrate pharmacogenomic and inflammatory data into individualized treatment plans. Such precision-guided approaches can help clinicians select the optimal BB type, dose, and combination for each patient, maximizing therapeutic benefit while minimizing risk.
Ultimately, BBs are not solely cardiac agents but systemic modulators of the cardio-renal-immune-endocrine axis, requiring individualized, precision-guided applications that integrate systems physiology with pharmacogenomic markers and inflammatory profiles. This approach promises to refine drug selection and dosing, advancing BBs from broad, generalized therapies to precision therapeutics.
Author Contributions
Figures and Visualization, J.P. and I.P. created using Canva, Microsoft PowerPoints, and Adobe Photoshop; Conceptualization, H.G.A. and A.H.; Supervision, H.G.A., writing—original draft preparation, J.P. and H.G.A.; writing, review, and editing, All authors. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing does not apply to this article.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| Abbreviation | Full Term |
| ACE | Angiotensin-Converting Enzyme |
| ACS | Acute Coronary Syndrome |
| ACTH | Adrenocorticotropic Hormone |
| ADHF | Acute Decompensated Heart Failure |
| ADRB1 | Beta-1 Adrenergic Receptor |
| ADRB2 | Beta-2 Adrenergic Receptor |
| AIMAH | ACTH-Independent Macronodular Adrenal Hyperplasia |
| AKI | Acute Kidney Injury |
| AMPK | AMP-Activated Protein Kinase |
| ANP | Atrial Natriuretic Peptide |
| ANG II | Angiotensin II |
| APOE | Apolipoprotein E |
| AT1R | Angiotensin II Type 1 Receptor |
| AT2R | Angiotensin II Type 2 Receptor |
| BBs | Beta-Blockers |
| BNP | B-Type Natriuretic Peptide |
| BP | Blood Pressure |
| CAD | Coronary Artery Disease |
| CD206 | Mannose Receptor (Marker of M2 Macrophages) |
| CHF | Congestive Heart Failure |
| CKD | Chronic Kidney Disease |
| COL4A1 | Collagen Type IV Alpha 1 Chain |
| CO | Cardiac Output |
| COPD | Chronic Obstructive Pulmonary Disease |
| COX-2 | Cyclooxygenase-2 |
| CPVT | Catecholaminergic Polymorphic Ventricular Tachycardia |
| CRH | Corticotropin-Releasing Hormone |
| CRP | C-Reactive Protein |
| CNS | Central Nervous System |
| CV | Cardiovascular |
| CYP2D6 | Cytochrome P450 2D6 |
| DCM | Diabetic Cardiomyopathy |
| DN | Diabetic Nephropathy |
| ECG | Electrocardiogram |
| ECM | Extracellular Matrix |
| eNOS | Endothelial Nitric Oxide Synthase |
| FEV1 | Forced Expiratory Volume in 1 s |
| FFA | Free Fatty Acids |
| FVC | Forced Vital Capacity |
| GAL3 | Galectin-3 |
| GFR | Glomerular Filtration Rate |
| GLUT1/4 | Glucose Transporter 1/4 |
| GRK5 | G Protein-Coupled Receptor Kinase 5 |
| HDL | High-Density Lipoprotein |
| HF | Heart Failure |
| HFmrEF | Heart Failure with Mildly Reduced Ejection Fraction |
| HFpEF | Heart Failure with Preserved Ejection Fraction |
| HFrEF | Heart Failure with Reduced Ejection Fraction |
| HR | Heart Rate |
| HPA axis | Hypothalamic–Pituitary–Adrenal Axis |
| IL-1β | Interleukin-1 Beta |
| IL-4 | Interleukin-4 |
| IL-6 | Interleukin-6 |
| IL-10 | Interleukin-10 |
| IL-12p70 | Interleukin-12 subunit p70 |
| IL-13 | Interleukin-13 |
| IL-17 | Interleukin-17 |
| iNOS | Inducible Nitric Oxide Synthase |
| IRF1 | Interferon Regulatory Factor 1 |
| ISA | Intrinsic Sympathomimetic Activity |
| JAK | Janus Kinase |
| LDL | Low-Density Lipoprotein |
| LQTS | Long QT Syndrome |
| LVEF | Left Ventricular Ejection Fraction |
| MCP-1 | Monocyte Chemoattractant Protein-1 |
| MI | Myocardial Infarction |
| ML | Machine Learning |
| MIP-1β | Macrophage Inflammatory Protein-1 Beta |
| M1 | Classically Activated (Pro-inflammatory) Macrophages |
| M2 | Alternatively Activated (Anti-inflammatory/Reparative) Macrophages |
| MMP-2 | Matrix Metalloproteinase-2 |
| MMT | Macrophage-to-Myofibroblast Transition |
| MOD | Myocardial Oxygen Demand |
| NF-κB | Nuclear Factor kappa-light-chain-enhancer of activated B cells |
| NLRP3 | NOD-, LRR- and pyrin domain-containing protein 3 |
| NO | Nitric Oxide |
| NOS | Nitric Oxide Synthase |
| nNOS | Neuronal Nitric Oxide Synthase |
| PGE2 | Prostaglandin E2 |
| PI3K | Phosphoinositide 3-Kinase |
| PKC | Protein Kinase C |
| PLA2 | Phospholipase A2 |
| PM | Poor Metabolizers |
| PPARγ | Peroxisome Proliferator-Activated Receptor Gamma |
| PVR | Peripheral Vascular Resistance |
| RAAS | Renin–Angiotensin–Aldosterone System |
| RBF | Renal Blood Flow |
| RCT | Randomized Controlled Trial |
| ROS | Reactive Oxygen Species |
| SCD | Sudden Cardiac Death |
| Smad3 | Mothers Against Decapentaplegic Homolog 3 |
| SOD2 | Superoxide Dismutase 2 |
| SNS | Sympathetic Nervous System |
| STAT1 | Signal Transducer and Activator of Transcription 1 |
| T3 | Triiodothyronine |
| T4 | Thyroxine |
| TGF-β1 | Transforming Growth Factor Beta 1 |
| TIMP-2 | Tissue Inhibitor of Metalloproteinases-2 |
| TNF-α | Tumor Necrosis Factor Alpha |
| UM | Ultra-rapid Metabolizers |
| α-SMA | Alpha-Smooth Muscle Actin |
References
- Wołowiec, Ł.; Grześk, G.; Osiak, J.; Wijata, A.; Mędlewska, M.; Gaborek, P.; Banach, J.; Wołowiec, A.; Głowacka, M. Beta-Blockers in Cardiac Arrhythmias–Clinical Pharmacologist’s Point of View. Front. Pharmacol. 2023, 13, 1043714. [Google Scholar] [CrossRef] [Scilit]
- Taddei, S.; Tsabedze, N.; Tan, R.-S. β-Blockers Are Not All the Same: Pharmacologic Similarities and Differences, Potential Combinations and Clinical Implications. Curr. Med. Res. Opin. 2024, 40, 15–23. [Google Scholar] [CrossRef] [Scilit]
- Ibanez, B.; Latini, R.; Rossello, X.; Dominguez-Rodriguez, A.; Fernández-Vazquez, F.; Pelizzoni, V.; Sánchez, P.L.; Anguita, M.; Barrabés, J.A.; Raposeiras-Roubín, S.; et al. Beta-Blockers after Myocardial Infarction without Reduced Ejection Fraction. N. Engl. J. Med. 2025, 393, 1889–1900. [Google Scholar] [CrossRef] [Scilit]
- Kotecha, D.; Gill, S.K.; Flather, M.D.; Holmes, J.; Packer, M.; Rosano, G.; Böhm, M.; McMurray, J.J.V.; Wikstrand, J.; Anker, S.D.; et al. Impact of Renal Impairment on Beta-Blocker Efficacy in Patients with Heart Failure. J. Am. Coll. Cardiol. 2019, 74, 2893–2904. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abbott, K.C.; Trespalacios, F.C.; Agodoa, L.Y.; Taylor, A.J.; Bakris, G.L. β-Blocker Use in Long-Term Dialysis Patients. Arch. Intern. Med. 2004, 164, 2465. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schwäble Santamaria, A.; Grassi, M.; Meeusen, J.W.; Lieske, J.C.; Scott, R.; Robertson, A.; Schiffer, E. Performance of Nuclear Magnetic Resonance-Based Estimated Glomerular Filtration Rate in a Real-World Setting. Bioengineering 2023, 10, 717. [Google Scholar] [CrossRef] [Scilit]
- Wang, D.; Jose, P.; Wilcox, C.S. Β1 Receptors Protect the Renal Afferent Arteriole of Angiotensin-Infused Rabbits from Norepinephrine-Induced Oxidative Stress. J. Am. Soc. Nephrol. 2006, 17, 3347–3354. [Google Scholar] [CrossRef] [Scilit]
- Suarez-Roca, H.; Mamoun, N.; Sigurdson, M.I.; Maixner, W. Baroreceptor Modulation of the Cardiovascular System, Pain, Consciousness, and Cognition. In Comprehensive Physiology; Wiley: Hoboken, NJ, USA, 2021; pp. 1373–1423. [Google Scholar]
- Castaño-Amores, C.; Antúnez-Rodríguez, A.; Pozo-Agundo, A.; García-Rodríguez, S.; Martínez-González, L.J.; Dávila-Fajardo, C.L. Genetic Polymorphisms in ADRB1, ADRB2 and CYP2D6 Genes and Response to Beta-Blockers in Patients with Acute Coronary Syndrome. Biomed. Pharmacother. 2023, 169, 115869. [Google Scholar] [CrossRef] [Scilit]
- Zhang, Y.; Matkovich, S.J.; Duan, X.; Gold, J.I.; Koch, W.J.; Dorn, G.W. Nuclear Effects of G-Protein Receptor Kinase 5 on Histone Deacetylase 5–Regulated Gene Transcription in Heart Failure. Circ. Heart Fail. 2011, 4, 659–668. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liggett, S.B.; Cresci, S.; Kelly, R.J.; Syed, F.M.; Matkovich, S.J.; Hahn, H.S.; Diwan, A.; Martini, J.S.; Sparks, L.; Parekh, R.R.; et al. A GRK5 Polymorphism That Inhibits β-Adrenergic Receptor Signaling Is Protective in Heart Failure. Nat. Med. 2008, 14, 510–517. [Google Scholar] [CrossRef] [Scilit]
- Luzum, J.A.; Peterson, E.; Li, J.; She, R.; Gui, H.; Liu, B.; Spertus, J.A.; Pinto, Y.M.; Williams, L.K.; Sabbah, H.N.; et al. Race and Beta-Blocker Survival Benefit in Patients with Heart Failure: An Investigation of Self-Reported Race and Proportion of African Genetic Ancestry. J. Am. Heart Assoc. 2018, 7, e007956. [Google Scholar] [CrossRef] [Scilit]
- Bruck, H.; Poller, U.; Lüssenhop, H.; Pönicke, K.; Temme, T.; Heusch, G.; Philipp, T.; Brodde, O.-E. B2-Adrenoceptor-Mediated Intrinsic Sympathomimetic Activity of Carteolol: An in Vivo Study. Naunyn-Schmiedeberg’s Arch. Pharmacol. 2004, 370, 361–368. [Google Scholar] [CrossRef] [Scilit]
- Nyberg, G.; Wilhelmsson, C.; Vedin, A. Intrinsic Sympathomimetic Activity of Penbutolol. Eur. J. Clin. Pharmacol. 1979, 16, 381–386. [Google Scholar] [CrossRef] [Scilit]
- Schweda, F.; Friis, U.; Wagner, C.; Skott, O.; Kurtz, A. Renin Release. Physiology 2007, 22, 310–319. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kurtz, A. Renin Release: Sites, Mechanisms, and Control. Annu. Rev. Physiol. 2011, 73, 377–399. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Luft, F.C. Angiotensin, Inflammation, Hypertension, and Cardiovascular Disease. Curr. Hypertens. Rep. 2001, 3, 61–67. [Google Scholar] [CrossRef] [Scilit]
- Dong, J.; Li, D.; Kang, L.; Luo, C.; Wang, J. Insights into Human ENOS, NNOS and INOS Structures and Medicinal Indications from Statistical Analyses of Their Interactions with Bound Compounds. Biophys. Rep. 2023, 9, 159–175. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gul, R.; Alsalman, N.; Alfadda, A.A. Inhibition of ENOS Partially Blunts the Beneficial Effects of Nebivolol on Angiotensin II-Induced Signaling in H9c2 Cardiomyoblasts. Curr. Issues Mol. Biol. 2022, 44, 2139–2152. [Google Scholar] [CrossRef] [Scilit]
- Gul, R.; Alsalman, N.; Bazighifan, A.; Alfadda, A.A. Comparative Beneficial Effects of Nebivolol and Nebivolol/Valsartan Combination against Mitochondrial Dysfunction in Angiotensin II-Induced Pathology in H9c2 Cardiomyoblasts. J. Pharm. Pharmacol. 2021, 73, 1520–1529. [Google Scholar] [CrossRef] [Scilit]
- Esplugues, J.V. NO as a Signalling Molecule in the Nervous System. Br. J. Pharmacol. 2002, 135, 1079–1095. [Google Scholar] [CrossRef] [Scilit]
- Toma, T.; Miyakawa, N.; Arakaki, Y.; Watanabe, T.; Nakahara, R.; Ali, T.F.S.; Biswas, T.; Todaka, M.; Kondo, T.; Fujita, M.; et al. An Antifibrotic Compound That Ameliorates Hyperglycaemia and Fat Accumulation in Cell and HFD Mouse Models. Diabetologia 2024, 67, 2568–2584. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.-Y.; Jiang, H.; Pan, J.; Huang, X.-R.; Wang, Y.-C.; Huang, H.-F.; To, K.-F.; Nikolic-Paterson, D.J.; Lan, H.-Y.; Chen, J.-H. Macrophage-to-Myofibroblast Transition Contributes to Interstitial Fibrosis in Chronic Renal Allograft Injury. J. Am. Soc. Nephrol. 2017, 28, 2053–2067. [Google Scholar] [CrossRef] [Scilit]
- Bai, W.; Liu, Z.-Q.; He, P.-Y.; Muhuyati. The Role of IL-6, IL-10, TNF-α and PD-1 Expression on CD4 T Cells in Atrial Fibrillation. Heliyon 2023, 9, e18818. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhu, M.; Zhou, H.; Zhou, L.; Yang, Y.; Chen, R. Research Progress on Macrophages in Cardiovascular Diseases. J. Cardiothorac. Surg. 2025, 20, 307. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baltogiannis, G.G.; Lysitsas, D.N.; di Giovanni, G.; Ciconte, G.; Sieira, J.; Conte, G.; Kolettis, T.M.; Chierchia, G.-B.; de Asmundis, C.; Brugada, P. CPVT: Arrhythmogenesis, Therapeutic Management, and Future Perspectives. A Brief Review of the Literature. Front. Cardiovasc. Med. 2019, 6, 92. [Google Scholar] [CrossRef] [Scilit]
- Tamaki, Y.; Yaku, H.; Morimoto, T.; Inuzuka, Y.; Ozasa, N.; Yamamoto, E.; Yoshikawa, Y.; Miyake, M.; Kondo, H.; Tamura, T.; et al. Lower In-Hospital Mortality with Beta-Blocker Use at Admission in Patients with Acute Decompensated Heart Failure. J. Am. Heart Assoc. 2021, 10, e020012. [Google Scholar] [CrossRef] [Scilit]
- Fragasso, G. The Concept of “Heart Failure with Preserved Ejection Fraction”: Time for a Critical Reappraisal. Rev. Cardiovasc. Med. 2023, 24, 202. [Google Scholar] [CrossRef] [Scilit]
- Godoy, L.C.; Farkouh, M.E.; Austin, P.C.; Shah, B.R.; Qiu, F.; Jackevicius, C.A.; Wijeysundera, H.C.; Krumholz, H.M.; Ko, D.T. Association of Beta-Blocker Therapy with Cardiovascular Outcomes in Patients with Stable Ischemic Heart Disease. J. Am. Coll. Cardiol. 2023, 81, 2299–2311. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Macdonald, I.A.; Bennett, T.; Brown, A.M.; Wilcox, R.G.; Skene, A.M. The Effects of Acute or Chronic Ingestion of Propranolol or Metoprolol on the Metabolic and Hormonal Responses to Prolonged, Submaximal Exercise in Hypertensive Men. Br. J. Clin. Pharmacol. 1984, 17, 283–293. [Google Scholar] [CrossRef] [Scilit]
- Tomiyama, H.; Yamashina, A. Beta-Blockers in the Management of Hypertension and/or Chronic Kidney Disease. Int. J. Hypertens. 2014, 2014, 919256. [Google Scholar] [CrossRef] [Scilit]
- Abbott, J.D.; Goldberger, J.J. Β-Blocker Therapy After Myocardial Infarction: A Little Goes a Long Way. J. Am. Heart Assoc. 2023, 12, e030867. [Google Scholar] [CrossRef] [Scilit]
- Safi, S.; Sethi, N.J.; Korang, S.K.; Nielsen, E.E.; Feinberg, J.; Gluud, C.; Jakobsen, J.C. Beta-Blockers in Patients without Heart Failure after Myocardial Infarction. Cochrane Database Syst. Rev. 2021, 2021, CD012565. [Google Scholar] [CrossRef] [Scilit]
- Silvain, J.; Cayla, G.; Ferrari, E.; Range, G.; Puymirat, E.; Delarche, N.; Guedeney, P.; Cuisset, T.; Ivanes, F.; Lhermusier, T.; et al. Beta-Blocker Interruption or Continuation after Myocardial Infarction. N. Engl. J. Med. 2024, 391, 1277–1286. [Google Scholar] [CrossRef] [Scilit]
- Badve, S.V.; Roberts, M.A.; Hawley, C.M.; Cass, A.; Garg, A.X.; Krum, H.; Tonkin, A.; Perkovic, V. Effects of Beta-Adrenergic Antagonists in Patients with Chronic Kidney Disease. J. Am. Coll. Cardiol. 2011, 58, 1152–1161. [Google Scholar] [CrossRef] [Scilit]
- Parada Barcia, J.A.; Raposeiras Roubin, S.; Fernández, D.G.; García, A.G.; Otero, C.I.; González Bermúdez, I.; Íñiguez Romo, A.; Abu-Assi, E. Comparison between Beta-blockers and Calcium Channel Blockers in Patients with Atrial Fibrillation According to Renal Function. Clin. Cardiol. 2024, 47, e24257. [Google Scholar] [CrossRef] [Scilit]
- Wiersinga, W.M. Propranolol and Thyroid Hormone Metabolism. Thyroid 1991, 1, 273–277. [Google Scholar] [CrossRef] [Scilit]
- Geffner, D.L.; Hershman, J.M. β-Adrenergic Blockade for the Treatment of Hyperthyroidism. Am. J. Med. 1992, 93, 61–68. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schurtz, G.; Mewton, N.; Lemesle, G.; Delmas, C.; Levy, B.; Puymirat, E.; Aissaoui, N.; Bauer, F.; Gerbaud, E.; Henry, P.; et al. Beta-Blocker Management in Patients Admitted for Acute Heart Failure and Reduced Ejection Fraction: A Review and Expert Consensus Opinion. Front. Cardiovasc. Med. 2023, 10, 1263482. [Google Scholar] [CrossRef] [Scilit]
- Joo, S.-J. Beta-Blocker Therapy in Patients with Acute Myocardial Infarction: Not All Patients Need It. Acute Crit. Care 2023, 38, 251–260. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Castiglione, V.; Gentile, F.; Ghionzoli, N.; Chiriacò, M.; Panichella, G.; Aimo, A.; Vergaro, G.; Giannoni, A.; Passino, C.; Emdin, M. Pathophysiological Rationale and Clinical Evidence for Neurohormonal Modulation in Heart Failure with Preserved Ejection Fraction. Card. Fail. Rev. 2023, 9, e09. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- D’Amato, A.; Cestiè, C.; Ferranti, F.; Segato, C.; Prosperi, S.; Germanò, R.; Myftari, V.; Bartimoccia, S.; Castellani, V.; Badagliacca, R.; et al. Implications of Oxidative Stress in the Pathophysiological Pathways of Heart Failure. Int. J. Mol. Sci. 2025, 26, 5165. [Google Scholar] [CrossRef] [Scilit]
- Yndigegn, T.; Lindahl, B.; Alfredsson, J.; Benatar, J.; Brandin, L.; Erlinge, D.; Haaga, U.; Held, C.; Johansson, P.; Karlström, P.; et al. Design and Rationale of Randomized Evaluation of Decreased Usage of Beta-Blockers after Acute Myocardial Infarction (REDUCE-AMI). Eur. Heart J. Cardiovasc. Pharmacother. 2023, 9, 192–197. [Google Scholar] [CrossRef] [Scilit]
- Yndigegn, T.; Lindahl, B.; Mars, K.; Alfredsson, J.; Benatar, J.; Brandin, L.; Erlinge, D.; Hallen, O.; Held, C.; Hjalmarsson, P.; et al. Beta-Blockers after Myocardial Infarction and Preserved Ejection Fraction. N. Engl. J. Med. 2024, 390, 1372–1381. [Google Scholar] [CrossRef] [Scilit]
- Cruickshank, J.M. Beta-Blockers and Heart Failure. Indian Heart J. 2010, 62, 101–110. [Google Scholar] [PubMed]
- Anzai, A.; Ko, S.; Fukuda, K. Immune and Inflammatory Networks in Myocardial Infarction: Current Research and Its Potential Implications for the Clinic. Int. J. Mol. Sci. 2022, 23, 5214. [Google Scholar] [CrossRef] [Scilit]
- Tirdea, C.; Hostiuc, S.; Moldovan, H.; Scafa-Udriste, A. Identification of Risk Genes Associated with Myocardial Infarction—Big Data Analysis and Literature Review. Int. J. Mol. Sci. 2022, 23, 15008. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nohria, R.; Viera, A.J. Acute Coronary Syndrome: Diagnosis and Initial Management. Am. Fam. Physician 2024, 109, 34–42. [Google Scholar] [PubMed]
- Chi, K.-Y.; Nanna, M.G. Stabilizing Stable Coronary Artery Disease. JACC Adv. 2025, 4, 101569. [Google Scholar] [CrossRef] [Scilit]
- Dai, Y.; Mei, Z.; Zhang, S.; Shali, S.; Ren, D.; Xu, L.; Gao, W.; Chang, S.; Zheng, Y.; Qian, J.; et al. Sexual Dysfunction and the Impact of Beta-Blockers in Young Males with Coronary Artery Disease. Front. Cardiovasc. Med. 2021, 8, 708200. [Google Scholar] [CrossRef] [Scilit]
- Liu, S.; Wang, C.; Guo, J.; Yang, Y.; Huang, M.; Li, L.; Wang, Y.; Qin, Y.; Zhang, M. Serum Cytokines Predict the Severity of Coronary Artery Disease Without Acute Myocardial Infarction. Front. Cardiovasc. Med. 2022, 9, 896810. [Google Scholar] [CrossRef] [Scilit]
- Schröder, L.C.; Holkeri, A.; Eranti, A.; Haukilahti, M.A.E.; Kerola, T.; Kenttä, T.V.; Noponen, K.; Seppänen, T.; Rissanen, H.; Heliövaara, M.; et al. Poor R-Wave Progression as a Predictor of Sudden Cardiac Death in the General Population and Subjects with Coronary Artery Disease. Heart Rhythm. 2022, 19, 952–959. [Google Scholar] [CrossRef] [Scilit]
- Oba, Y.; Kabutoya, T.; Kohro, T.; Imai, Y.; Kario, K.; Sato, H.; Nochioka, K.; Nakayama, M.; Fujita, H.; Mizuno, Y.; et al. Relationships Among Heart Rate, β-Blocker Dosage, and Prognosis in Patients with Coronary Artery Disease in a Real-World Database Using a Multimodal Data Acquisition System. Circ. J. 2023, 87, CJ-22-0314. [Google Scholar] [CrossRef] [Scilit]
- Malinowski, D.; Bochniak, O.; Luterek-Puszyńska, K.; Puszyński, M.; Pawlik, A. Genetic Risk Factors Related to Coronary Artery Disease and Role of Transforming Growth Factor Beta 1 Polymorphisms. Genes 2023, 14, 1425. [Google Scholar] [CrossRef] [Scilit]
- Sharma, V.; Maheshwari, V.; Thayumanavan, T.; Sahai, A.; Singh, S.; Kar, B. Heart on Fire: Unmasking RyR2 Mutation in Stress-Induced Ventricular Arrhythmias. Methodist. Debakey Cardiovasc. J. 2025, 21, 25–29. [Google Scholar] [CrossRef] [Scilit]
- Nattel, S. Comparative Mechanisms of Action of Antiarrhythmic Drugs. Am. J. Cardiol. 1993, 72, F13–F17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shimizu, T.; Takekita, Y.; Aoki, N.; Suwa, T.; Yasuda, K.; Uchinuma, N.; Tominaga, H.; Kojima, Y.; Kawashima, H.; Kato, M.; et al. Beta-Blockers for Electroconvulsive Therapy: A Systematic Review and Meta-Analysis. J. Psychiatr. Res. 2025, 183, 269–281. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lymperopoulos, A.; McCrink, K.A.; Brill, A. Impact of CYP2D6 Genetic Variation on the Response of the Cardiovascular Patient to Carvedilol and Metoprolol. Curr. Drug Metab. 2015, 17, 30–36. [Google Scholar] [CrossRef] [Scilit]
- Hall, M.E.; Rocco, M.V.; Morgan, T.M.; Hamilton, C.A.; Jordan, J.H.; Edwards, M.S.; Hall, J.E.; Hundley, W.G. Beta-Blocker Use Is Associated with Higher Renal Tissue Oxygenation in Hypertensive Patients Suspected of Renal Artery Stenosis. Cardiorenal Med. 2016, 6, 261–268. [Google Scholar] [CrossRef] [Scilit]
- Dean, L.; Kane, M. Metoprolol Therapy and CYP2D6 Genotype. In Medical Genetics Summaries; National Center for Biotechnology Information (US): Bethesda, MD, USA, 2012. [Google Scholar]
- Kopańko, M.; Zabłudowska, M.; Pawlak, D.; Sieklucka, B.; Krupa, A.; Sokołowska, K.; Ziemińska, M.; Pawlak, K. The Possible Effect of β-Blocker Use on the Circulating MMP-2/TIMP-2 System in Patients with Chronic Kidney Disease on Conservative Treatment. J. Clin. Med. 2024, 13, 1847. [Google Scholar] [CrossRef] [Scilit]
- Rizvi, S. Association of Genetic Variants with Diabetic Nephropathy. World J. Diabetes 2014, 5, 809. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Galis, P.; Bartosova, L.; Farkasova, V.; Bartekova, M.; Ferenczyova, K.; Rajtik, T. Update on Clinical and Experimental Management of Diabetic Cardiomyopathy: Addressing Current and Future Therapy. Front. Endocrinol. 2024, 15, 1451100. [Google Scholar] [CrossRef] [Scilit]
- DeMorrow, S. Role of the Hypothalamic–Pituitary–Adrenal Axis in Health and Disease. Int. J. Mol. Sci. 2018, 19, 986. [Google Scholar] [CrossRef] [Scilit]
- Gullestad, L.; Dolva, L.O.; Kjeldsen, S.E.; Eide, I.; Kjekshus, J. Effect of Beta-Adrenergic Blockade on Hormonal Responses during Continuous and Intermittent Exercise. Cardiovasc. Drugs Ther. 1989, 3, 63–71. [Google Scholar] [CrossRef] [Scilit]
- Burford, N.; Webster, N.; Cruz-Topete, D. Hypothalamic-Pituitary-Adrenal Axis Modulation of Glucocorticoids in the Cardiovascular System. Int. J. Mol. Sci. 2017, 18, 2150. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bugajski, J.; Gadek-Michalska, A.; Ołowska, A.; Borycz, J.; Głód, R.; Bugajski, A.J. Adrenergic Regulation of the Hypothalamic-Pituitary-Adrenal Axis under Basal and Social Stress Conditions. J. Physiol. Pharmacol. 1995, 46, 297–312. [Google Scholar] [PubMed]
- Oki, K.; Yamane, K.; Nakanishi, S.; Nakashima, R.; Jitsuiki, K.; Kohno, N. Improvement of Hypercortisolism by β-Blocker Therapy in Subclinical Cushing’s Syndrome Associated with ACTH-Independent Macronodular Adrenocortical Hyperplasia. Endocrine 2009, 36, 372–376. [Google Scholar] [CrossRef] [Scilit]
- McGill, J.B. Reexamining Misconceptions About β-Blockers in Patients with Diabetes. Clin. Diabetes 2009, 27, 36–46. [Google Scholar] [CrossRef] [Scilit]
- Kveiborg, B.; Hermann, T.S.; Major-Pedersen, A.; Christiansen, B.; Rask-Madsen, C.; Raunsø, J.; Køber, L.; Torp-Pedersen, C.; Dominguez, H. Metoprolol Compared to Carvedilol Deteriorates Insulin-Stimulated Endothelial Function in Patients with Type 2 Diabetes—A Randomized Study. Cardiovasc. Diabetol. 2010, 9, 21. [Google Scholar] [CrossRef] [Scilit]
- Zanchetti, A.; Leonetti, G.; Terzoli, L.; Sala, C. β-Blockers and Renin. Drugs 1983, 25, 58–63. [Google Scholar] [CrossRef] [Scilit]
- Knox, F.G.; Burnett, J.C.; Kohan, D.E.; Spielman, W.S.; Strand, J.C. Escape from the Sodium-Retaining Effects of Mineralocorticoids. Kidney Int. 1980, 17, 263–276. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Parichatikanond, W.; Duangrat, R.; Kurose, H.; Mangmool, S. Regulation of β-Adrenergic Receptors in the Heart: A Review on Emerging Therapeutic Strategies for Heart Failure. Cells 2024, 13, 1674. [Google Scholar] [CrossRef] [Scilit]
- Khan, O.; Patel, M.; Tomdio, A.N.; Beall, J.; Jovin, I.S. Beta-Blockers in the Prevention and Treatment of Ischemic Heart Disease. Heart Views 2023, 24, 41–49. [Google Scholar] [CrossRef] [Scilit]
- Prijic, S.; Buchhorn, R. Mechanisms of Beta-Blockers Action in Patients with Heart Failure. Rev. Recent Clin. Trials 2014, 9, 58–60. [Google Scholar] [CrossRef] [Scilit]
- Han, L.; Liu, F.; Li, Q.; Qing, T.; Zhai, Z.; Xia, Z.; Li, J. The Efficacy of Beta-Blockers in Patients with Long QT Syndrome 1–3 According to Individuals’ Gender, Age, and QTc Intervals: A Network Meta-Analysis. Front. Pharmacol. 2020, 11, 579525. [Google Scholar] [CrossRef] [Scilit]
- Kurtz, A. Control of Renin Synthesis and Secretion. Am. J. Hypertens. 2012, 25, 839–847. [Google Scholar] [CrossRef] [Scilit]
- Manis, A.D.; Palygin, O.; Khedr, S.; Levchenko, V.; Hodges, M.R.; Staruschenko, A. Relationship between the Renin–Angiotensin–Aldosterone System and Renal Kir5.1 Channels. Clin. Sci. 2019, 133, 2449–2461. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumar, M.; Dev, S.; Khalid, M.U.; Siddenthi, S.M.; Noman, M.; John, C.; Akubuiro, C.; Haider, A.; Rani, R.; Kashif, M.; et al. The Bidirectional Link Between Diabetes and Kidney Disease: Mechanisms and Management. Cureus 2023, 15, e45615. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Strauss, M.H.; Hall, A.S.; Narkiewicz, K. The Combination of Beta-Blockers and ACE Inhibitors Across the Spectrum of Cardiovascular Diseases. Cardiovasc. Drugs Ther. 2023, 37, 757–770. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abosamak, N.R.; Shahin, M.H. Beta2 Receptor Agonists and Antagonists. In StatPearls [Internet]; StatPearls: Treasure Island, FL, USA, 2025. [Google Scholar]
- Loth, D.W.; Brusselle, G.G.; Lahousse, L.; Hofman, A.; Leufkens, H.G.M.; Stricker, B.H. Β-adrenoceptor Blockers and Pulmonary Function in the General Population: The Rotterdam Study. Br. J. Clin. Pharmacol. 2014, 77, 190–200. [Google Scholar] [CrossRef] [Scilit]
- Mangmool, S.; Denkaew, T.; Parichatikanond, W.; Kurose, H. β-Adrenergic Receptor and Insulin Resistance in the Heart. Biomol. Ther. 2017, 25, 44–56. [Google Scholar] [CrossRef] [Scilit]
- Marketou, M.; Gupta, Y.; Jain, S.; Vardas, P. Differential Metabolic Effects of Beta-Blockers: An Updated Systematic Review of Nebivolol. Curr. Hypertens. Rep. 2017, 19, 22. [Google Scholar] [CrossRef] [Scilit]
- Senn, J.R.; Löliger, R.C.; Fischer, J.G.W.; Bur, F.; Maushart, C.I.; Betz, M.J. Acute Effect of Propranolol on Resting Energy Expenditure in Hyperthyroid Patients. Front. Endocrinol. 2023, 13, 1026998. [Google Scholar] [CrossRef] [Scilit]
- Samanta, S.; Bagchi, D.; Bagchi, M. Physiological and Metabolic Functions of the Β3-Adrenergic Receptor and an Approach to Therapeutic Achievements. J. Physiol. Biochem. 2024, 80, 757–774. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morioka, T.; Emoto, M.; Yamazaki, Y.; Kawano, N.; Imamura, S.; Numaguchi, R.; Urata, H.; Motoyama, K.; Mori, K.; Fukumoto, S.; et al. Leptin Is Associated with Vascular Endothelial Function in Overweight Patients with Type 2 Diabetes. Cardiovasc. Diabetol. 2014, 13, 10. [Google Scholar] [CrossRef] [Scilit]
- Cardoso, V.G.; Gonçalves, G.L.; Costa-Pessoa, J.M.; Thieme, K.; Lins, B.B.; Casare, F.A.M.; de Ponte, M.C.; Camara, N.O.S.; Oliveira-Souza, M. Angiotensin II-Induced Podocyte Apoptosis Is Mediated by Endoplasmic Reticulum Stress/PKC-δ/P38 MAPK Pathway Activation and Trough Increased Na+/H+ Exchanger Isoform 1 Activity. BMC Nephrol. 2018, 19, 179. [Google Scholar] [CrossRef] [Scilit]
- Shanmugam, N.; Gaw Gonzalo, I.T.; Natarajan, R. Molecular Mechanisms of High Glucose-Induced Cyclooxygenase-2 Expression in Monocytes. Diabetes 2004, 53, 795–802. [Google Scholar] [CrossRef] [Scilit]
- Fatima, N.; Patel, S.N.; Hussain, T. Angiotensin II Type 2 Receptor: A Target for Protection Against Hypertension, Metabolic Dysfunction, and Organ Remodeling. Hypertension 2021, 77, 1845–1856. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zamora, R.; Vodovotz, Y.; Billiar, T.R. Inducible Nitric Oxide Synthase and Inflammatory Diseases. Mol. Med. 2000, 6, 347–373. [Google Scholar] [CrossRef] [Scilit]
- Leppänen, T.; Korhonen, R.; Laavola, M.; Nieminen, R.; Tuominen, R.K.; Moilanen, E. Down-Regulation of Protein Kinase Cδ Inhibits Inducible Nitric Oxide Synthase Expression through IRF1. PLoS ONE 2013, 8, e52741. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kulesza, A.; Paczek, L.; Burdzinska, A. The Role of COX-2 and PGE2 in the Regulation of Immunomodulation and Other Functions of Mesenchymal Stromal Cells. Biomedicines 2023, 11, 445. [Google Scholar] [CrossRef] [Scilit]
- Louden, J.D. Regulation of Fluid and Electrolyte Balance. Anaesth. Intensive Care Med. 2015, 16, 278–285. [Google Scholar] [CrossRef] [Scilit]
- Siragy, H.M. Interaction of the Renin Angiotensin and Cox Systems in the Kidney. Front. Biosci. 2016, 8, 459. [Google Scholar] [CrossRef] [Scilit]
- Hyman, D.A.; Siebert, V.R.; Birnbaum, G.D.; Alam, M.; Birnbaum, Y. A Modern History RAAS Inhibition and Beta Blockade for Heart Failure to Underscore the Non-Equivalency of ACEIs and ARBs. Cardiovasc. Drugs Ther. 2020, 34, 215–221. [Google Scholar] [CrossRef] [Scilit]
- Frank, G.D.; Saito, S.; Motley, E.D.; Sasaki, T.; Ohba, M.; Kuroki, T.; Inagami, T.; Eguchi, S. Requirement of Ca2+ and PKCδ for Janus Kinase 2 Activation by Angiotensin II: Involvement of PYK2. Mol. Endocrinol. 2002, 16, 367–377. [Google Scholar] [CrossRef] [Scilit]
- McWhinney, C.D.; Hunt, R.A.; Conrad, K.M.; Dostal, D.E.; Baker, K.M. The Type I Angiotensin II Receptor Couples to Stat1 and Stat3 Activation Through Jak2 Kinase in Neonatal Rat Cardiac Myocytes. J. Mol. Cell Cardiol. 1997, 29, 2513–2524. [Google Scholar] [CrossRef] [Scilit]
- Patel, S.N.; Fatima, N.; Ali, R.; Hussain, T. Emerging Role of Angiotensin AT2 Receptor in Anti-Inflammation: An Update. Curr. Pharm. Des. 2020, 26, 492–500. [Google Scholar] [CrossRef] [Scilit]
- Barki-Harrington, L.; Luttrell, L.M.; Rockman, H.A. Dual Inhibition of β-Adrenergic and Angiotensin II Receptors by a Single Antagonist. Circulation 2003, 108, 1611–1618. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zenke, K.; Muroi, M.; Tanamoto, K. IRF1 Supports DNA Binding of STAT1 by Promoting Its Phosphorylation. Immunol. Cell Biol. 2018, 96, 1095–1103. [Google Scholar] [CrossRef] [Scilit]
- Uddin, S.; Sassano, A.; Deb, D.K.; Verma, A.; Majchrzak, B.; Rahman, A.; Malik, A.B.; Fish, E.N.; Platanias, L.C. Protein Kinase C-δ (PKC-δ) Is Activated by Type I Interferons and Mediates Phosphorylation of Stat1 on Serine 727. J. Biol. Chem. 2002, 277, 14408–14416. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jiang, D.-S.; Li, L.; Huang, L.; Gong, J.; Xia, H.; Liu, X.; Wan, N.; Wei, X.; Zhu, X.; Chen, Y.; et al. Interferon Regulatory Factor 1 Is Required for Cardiac Remodeling in Response to Pressure Overload. Hypertension 2014, 64, 77–86. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, H.; Dhalla, N.S. The Role of Pro-Inflammatory Cytokines in the Pathogenesis of Cardiovascular Disease. Int. J. Mol. Sci. 2024, 25, 1082. [Google Scholar] [CrossRef] [Scilit]
- Ollerstam, A.; Persson, A. Macula Densa Neuronal Nitric Oxide Synthase. Cardiovasc. Res. 2002, 56, 189–196. [Google Scholar] [CrossRef] [Scilit]
- Yamaguchi, H.; Gomez, R.A.; Sequeira-Lopez, M.L.S. Renin Cells, From Vascular Development to Blood Pressure Sensing. Hypertension 2023, 80, 1580–1589. [Google Scholar] [CrossRef] [Scilit]
- Reid, I.A. Role of Nitric Oxide in the Regulation of Renin and Vasopressin Secretion. Front. Neuroendocrinol. 1994, 15, 351–383. [Google Scholar] [CrossRef] [Scilit]
- Riedel, W. Role of Nitric Oxide in the Control of the Hypothalamic-Pituitary-Adrenocortical Axis. Z. Rheumatol. 2000, 59, II36–II42. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Konturek, S.J.; Szlachcic, A.; Dembinski, A.; Warzecha, Z.; Jaworek, J.; Stachura, J. Nitric Oxide in Pancreatic Secretion and Hormone-Induced Pancreatitis in Rats. Int. J. Pancreatol. 1994, 15, 19–28. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coleman, J.W. Nitric Oxide in Immunity and Inflammation. Int. Immunopharmacol. 2001, 1, 1397–1406. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Naseem, K. The Role of Nitric Oxide in Cardiovascular Diseases. Mol. Asp. Med. 2005, 26, 33–65. [Google Scholar] [CrossRef] [Scilit]
- Blazquez-Navarro, A.; Mittmann, L.; Thieme, C.J.; Anft, M.; Paniskaki, K.; Doevelaar, A.; Seibert, F.S.; Hoelzer, B.; Konik, M.J.; Berger, M.M.; et al. Impact of Low EGFR on the Immune Response against COVID-19. J. Nephrol. 2022, 36, 199–202. [Google Scholar] [CrossRef] [Scilit]
- Jufar, A.H.; Lankadeva, Y.R.; May, C.N.; Cochrane, A.D.; Bellomo, R.; Evans, R.G. Renal Functional Reserve: From Physiological Phenomenon to Clinical Biomarker and Beyond. Am. J. Physiol. Regul. Integr. Comp. Physiol. 2020, 319, R690–R702. [Google Scholar] [CrossRef] [Scilit]
- Arif, E.; Nihalani, D. Beta2-adrenergic Receptor in Kidney Biology: A Current Prospective. Nephrology 2019, 24, 497–503. [Google Scholar] [CrossRef] [Scilit]
- Maroz, N.; Simman, R. Wound Healing in Patients with Impaired Kidney Function. J. Am. Coll. Clin. Wound Spec. 2013, 5, 2–7. [Google Scholar] [CrossRef] [Scilit]
- Gorin, Y.; Ricono, J.M.; Wagner, B.; Kim, N.-H.; Bhandari, B.; Choudhury, G.G.; Abboud, H.E. Angiotensin II-Induced ERK1/ERK2 Activation and Protein Synthesis Are Redox-Dependent in Glomerular Mesangial Cells. Biochem. J. 2004, 381, 231–239. [Google Scholar] [CrossRef] [Scilit]
- Lira, V.A.; Soltow, Q.A.; Long, J.H.D.; Betters, J.L.; Sellman, J.E.; Criswell, D.S. Nitric Oxide Increases GLUT4 Expression and Regulates AMPK Signaling in Skeletal Muscle. Am. J. Physiol. Endocrinol. Metab. 2007, 293, E1062–E1068. [Google Scholar] [CrossRef] [Scilit]
- Peifer-Weiß, L.; Al-Hasani, H.; Chadt, A. AMPK and Beyond: The Signaling Network Controlling RabGAPs and Contraction-Mediated Glucose Uptake in Skeletal Muscle. Int. J. Mol. Sci. 2024, 25, 1910. [Google Scholar] [CrossRef] [Scilit]
- Griendling, K.K.; Berk, B.C.; Socorro, L.; Tsuda, T.; Delafontaine, P.; Alexander, R.W. Secondary Signaling Mechanisms in Angiotensin II-Stimulated Vascular Smooth Muscle Cells. Clin. Exp. Pharmacol. Physiol. 1988, 15, 105–112. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Suzuki, Y.; Ruiz-Ortega, M.; Lorenzo, O.; Ruperez, M.; Esteban, V.; Egido, J. Inflammation and Angiotensin II. Int. J. Biochem. Cell Biol. 2003, 35, 881–900. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Murray, P.J.; Wynn, T.A. Protective and Pathogenic Functions of Macrophage Subsets. Nat. Rev. Immunol. 2011, 11, 723–737. [Google Scholar] [CrossRef] [Scilit]
- DiNicolantonio, J.J.; Fares, H.; Niazi, A.K.; Chatterjee, S.; D’Ascenzo, F.; Cerrato, E.; Biondi-Zoccai, G.; Lavie, C.J.; Bell, D.S.; O’Keefe, J.H. β-Blockers in Hypertension, Diabetes, Heart Failure and Acute Myocardial Infarction: A Review of the Literature. Open Heart 2015, 2, e000230. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kehat, I.; Molkentin, J.D. Molecular Pathways Underlying Cardiac Remodeling During Pathophysiological Stimulation. Circulation 2010, 122, 2727–2735. [Google Scholar] [CrossRef] [Scilit]
- Prabhu, S.D.; Frangogiannis, N.G. The Biological Basis for Cardiac Repair After Myocardial Infarction. Circ. Res. 2016, 119, 91–112. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arós, F.; Loma-Osorio, Á.; Vila, J.; López-Bescós, L.; Cuñat, J.; Rodríguez, E.; San José, J.M.; Heras, M.; Marrugat, J.; Investigadores del PRIAMHO II. Effect of Combined Beta-Blocker and Angiotensin-Converting Enzyme Inhibitor Treatment on 1-Year Survival After Acute Myocardial Infarction: Findings of the PRIAMHO-II Registry. Rev. Esp. Cardiol. 2006, 59, 313–320. [Google Scholar] [CrossRef] [Scilit]
- Kim, J.A.; Berliner, J.A.; Nadler, J.L. Angiotensin II Increases Monocyte Binding to Endothelial Cells. Biochem. Biophys. Res. Commun. 1996, 226, 862–868. [Google Scholar] [CrossRef] [Scilit]
- Pueyo, M.E.; Gonzalez, W.; Nicoletti, A.; Savoie, F.; Arnal, J.-F.; Michel, J.-B. Angiotensin II Stimulates Endothelial Vascular Cell Adhesion Molecule-1 via Nuclear Factor-ΚB Activation Induced by Intracellular Oxidative Stress. Arterioscler. Thromb. Vasc. Biol. 2000, 20, 645–651. [Google Scholar] [CrossRef] [Scilit]
- Libby, P.; Buring, J.E.; Badimon, L.; Hansson, G.K.; Deanfield, J.; Bittencourt, M.S.; Tokgözoğlu, L.; Lewis, E.F. Atherosclerosis. Nat. Rev. Dis. Primers 2019, 5, 56. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Newby, A.C. Matrix Metalloproteinase Inhibition Therapy for Vascular Diseases. Vasc. Pharmacol. 2012, 56, 232–244. [Google Scholar] [CrossRef] [Scilit]
- Shapouri-Moghaddam, A.; Mohammadian, S.; Vazini, H.; Taghadosi, M.; Esmaeili, S.; Mardani, F.; Seifi, B.; Mohammadi, A.; Afshari, J.T.; Sahebkar, A. Macrophage Plasticity, Polarization, and Function in Health and Disease. J. Cell Physiol. 2018, 233, 6425–6440. [Google Scholar] [CrossRef] [Scilit]
- Marchesi, C.; Paradis, P.; Schiffrin, E.L. Role of the Renin–Angiotensin System in Vascular Inflammation. Trends Pharmacol. Sci. 2008, 29, 367–374. [Google Scholar] [CrossRef] [Scilit]
- Beltrami, M.; Milli, M.; Dei, L.L.; Palazzuoli, A. The Treatment of Heart Failure in Patients with Chronic Kidney Disease: Doubts and New Developments from the Last ESC Guidelines. J. Clin. Med. 2022, 11, 2243. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- De Angelis, E.; Pecoraro, M.; Rusciano, M.R.; Ciccarelli, M.; Popolo, A. Cross-Talk between Neurohormonal Pathways and the Immune System in Heart Failure: A Review of the Literature. Int. J. Mol. Sci. 2019, 20, 1698. [Google Scholar] [CrossRef] [Scilit]
- Fung, J.W.H.; Yu, C.M.; Yip, G.; Chan, S.; Yandle, T.G.; Richards, A.M.; Nicholls, M.G.; Sanderson, J.E. Effect of Beta Blockade (Carvedilol or Metoprolol) on Activation of the Renin-Angiotensin-Aldosterone System and Natriuretic Peptides in Chronic Heart Failure. Am. J. Cardiol. 2003, 92, 406–410. [Google Scholar] [CrossRef] [Scilit]
- van der Horst, I.C.C.; Voors, A.A.; van Veldhuisen, D.J. Treatment of Heart Failure with ACE Inhibitors and Beta-Blockers. Clin. Res. Cardiol. 2007, 96, 193. [Google Scholar] [CrossRef] [Scilit]
- Camafort, M.; Park, S.-M.; Kang, S.-M. Lifestyle Modification in Heart Failure Management: Are We Using Evidence-Based Recommendations in Real World Practice? Int. J. Heart Fail. 2023, 5, 21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lawrence, T. The Nuclear Factor NF- B Pathway in Inflammation. Cold Spring Harb. Perspect. Biol. 2009, 1, a001651. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Shea, J.J.; Murray, P.J. Cytokine Signaling Modules in Inflammatory Responses. Immunity 2008, 28, 477–487. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vieceli Dalla Sega, F.; Fortini, F.; Aquila, G.; Campo, G.; Vaccarezza, M.; Rizzo, P. Notch Signaling Regulates Immune Responses in Atherosclerosis. Front. Immunol. 2019, 10, 1130. [Google Scholar] [CrossRef] [Scilit]
- Chen, X.; Tang, J.; Shuai, W.; Meng, J.; Feng, J.; Han, Z. Macrophage Polarization and Its Role in the Pathogenesis of Acute Lung Injury/Acute Respiratory Distress Syndrome. Inflamm. Res. 2020, 69, 883–895. [Google Scholar] [CrossRef] [Scilit]
- Ban, J.-Q.; Ao, L.-H.; He, X.; Zhao, H.; Li, J. Advances in Macrophage-Myofibroblast Transformation in Fibrotic Diseases. Front. Immunol. 2024, 15, 1461919. [Google Scholar] [CrossRef] [Scilit]
- Ahmadi, M.; Bekeschus, S.; Weltmann, K.-D.; von Woedtke, T.; Wende, K. Non-Steroidal Anti-Inflammatory Drugs: Recent Advances in the Use of Synthetic COX-2 Inhibitors. RSC Med. Chem. 2022, 13, 471–496. [Google Scholar] [CrossRef] [Scilit]
- Tison, G.H. Using Machine Learning to Uncover Heterogeneity of Beta Blocker Response in Heart Failure. Cell Rep. Med. 2022, 3, 100504. [Google Scholar] [CrossRef] [Scilit]
- DeGroat, W.; Mendhe, D.; Bhusari, A.; Abdelhalim, H.; Zeeshan, S.; Ahmed, Z. IntelliGenes: A Novel Machine Learning Pipeline for Biomarker Discovery and Predictive Analysis Using Multi-Genomic Profiles. Bioinformatics 2023, 39, btad755. [Google Scholar] [CrossRef] [Scilit]
- Drygała, S.; Radzikowski, M.; Maciejczyk, M. β-Blockers and Metabolic Modulation: Unraveling the Complex Interplay with Glucose Metabolism, Inflammation and Oxidative Stress. Front. Pharmacol. 2024, 15, 1489657. [Google Scholar] [CrossRef] [Scilit]
- Schenone, M.; Dančík, V.; Wagner, B.K.; Clemons, P.A. Target Identification and Mechanism of Action in Chemical Biology and Drug Discovery. Nat. Chem. Biol. 2013, 9, 232–240. [Google Scholar] [CrossRef] [Scilit]
- Duncavage, E.J.; Bagg, A.; Hasserjian, R.P.; DiNardo, C.D.; Godley, L.A.; Iacobucci, I.; Jaiswal, S.; Malcovati, L.; Vannucchi, A.M.; Patel, K.P.; et al. Genomic Profiling for Clinical Decision Making in Myeloid Neoplasms and Acute Leukemia. Blood 2022, 140, 2228–2247. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Devereux, G.; Cotton, S.; Nath, M.; McMeekin, N.; Campbell, K.; Chaudhuri, R.; Choudhury, G.; De Soyza, A.; Fielding, S.; Gompertz, S.; et al. Bisoprolol in Patients with Chronic Obstructive Pulmonary Disease at High Risk of Exacerbation. JAMA 2024, 332, 462. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wirtz, H.S.; Sheer, R.; Honarpour, N.; Casebeer, A.W.; Simmons, J.D.; Kurtz, C.E.; Pasquale, M.K.; Globe, G. Real-World Analysis of Guideline-Based Therapy After Hospitalization for Heart Failure. J. Am. Heart Assoc. 2020, 9, 16. [Google Scholar] [CrossRef] [Scilit]
- Fuchs, B.; Heesen, P. From Data Integration to Precision Medicine: A Value-Based Healthcare Approach for Sarcoma Care. J. Clin. Med. 2024, 13, 6500. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ingelman-Sundberg, M.; Nebert, D.W.; Lauschke, V.M. Emerging Trends in Pharmacogenomics: From Common Variant Associations toward Comprehensive Genomic Profiling. Hum. Genom. 2023, 17, 105. [Google Scholar] [CrossRef] [Scilit]
- Subramanian, M.; Wojtusciszyn, A.; Favre, L.; Boughorbel, S.; Shan, J.; Letaief, K.B.; Pitteloud, N.; Chouchane, L. Precision Medicine in the Era of Artificial Intelligence: Implications in Chronic Disease Management. J. Transl. Med. 2020, 18, 472. [Google Scholar] [CrossRef] [Scilit]
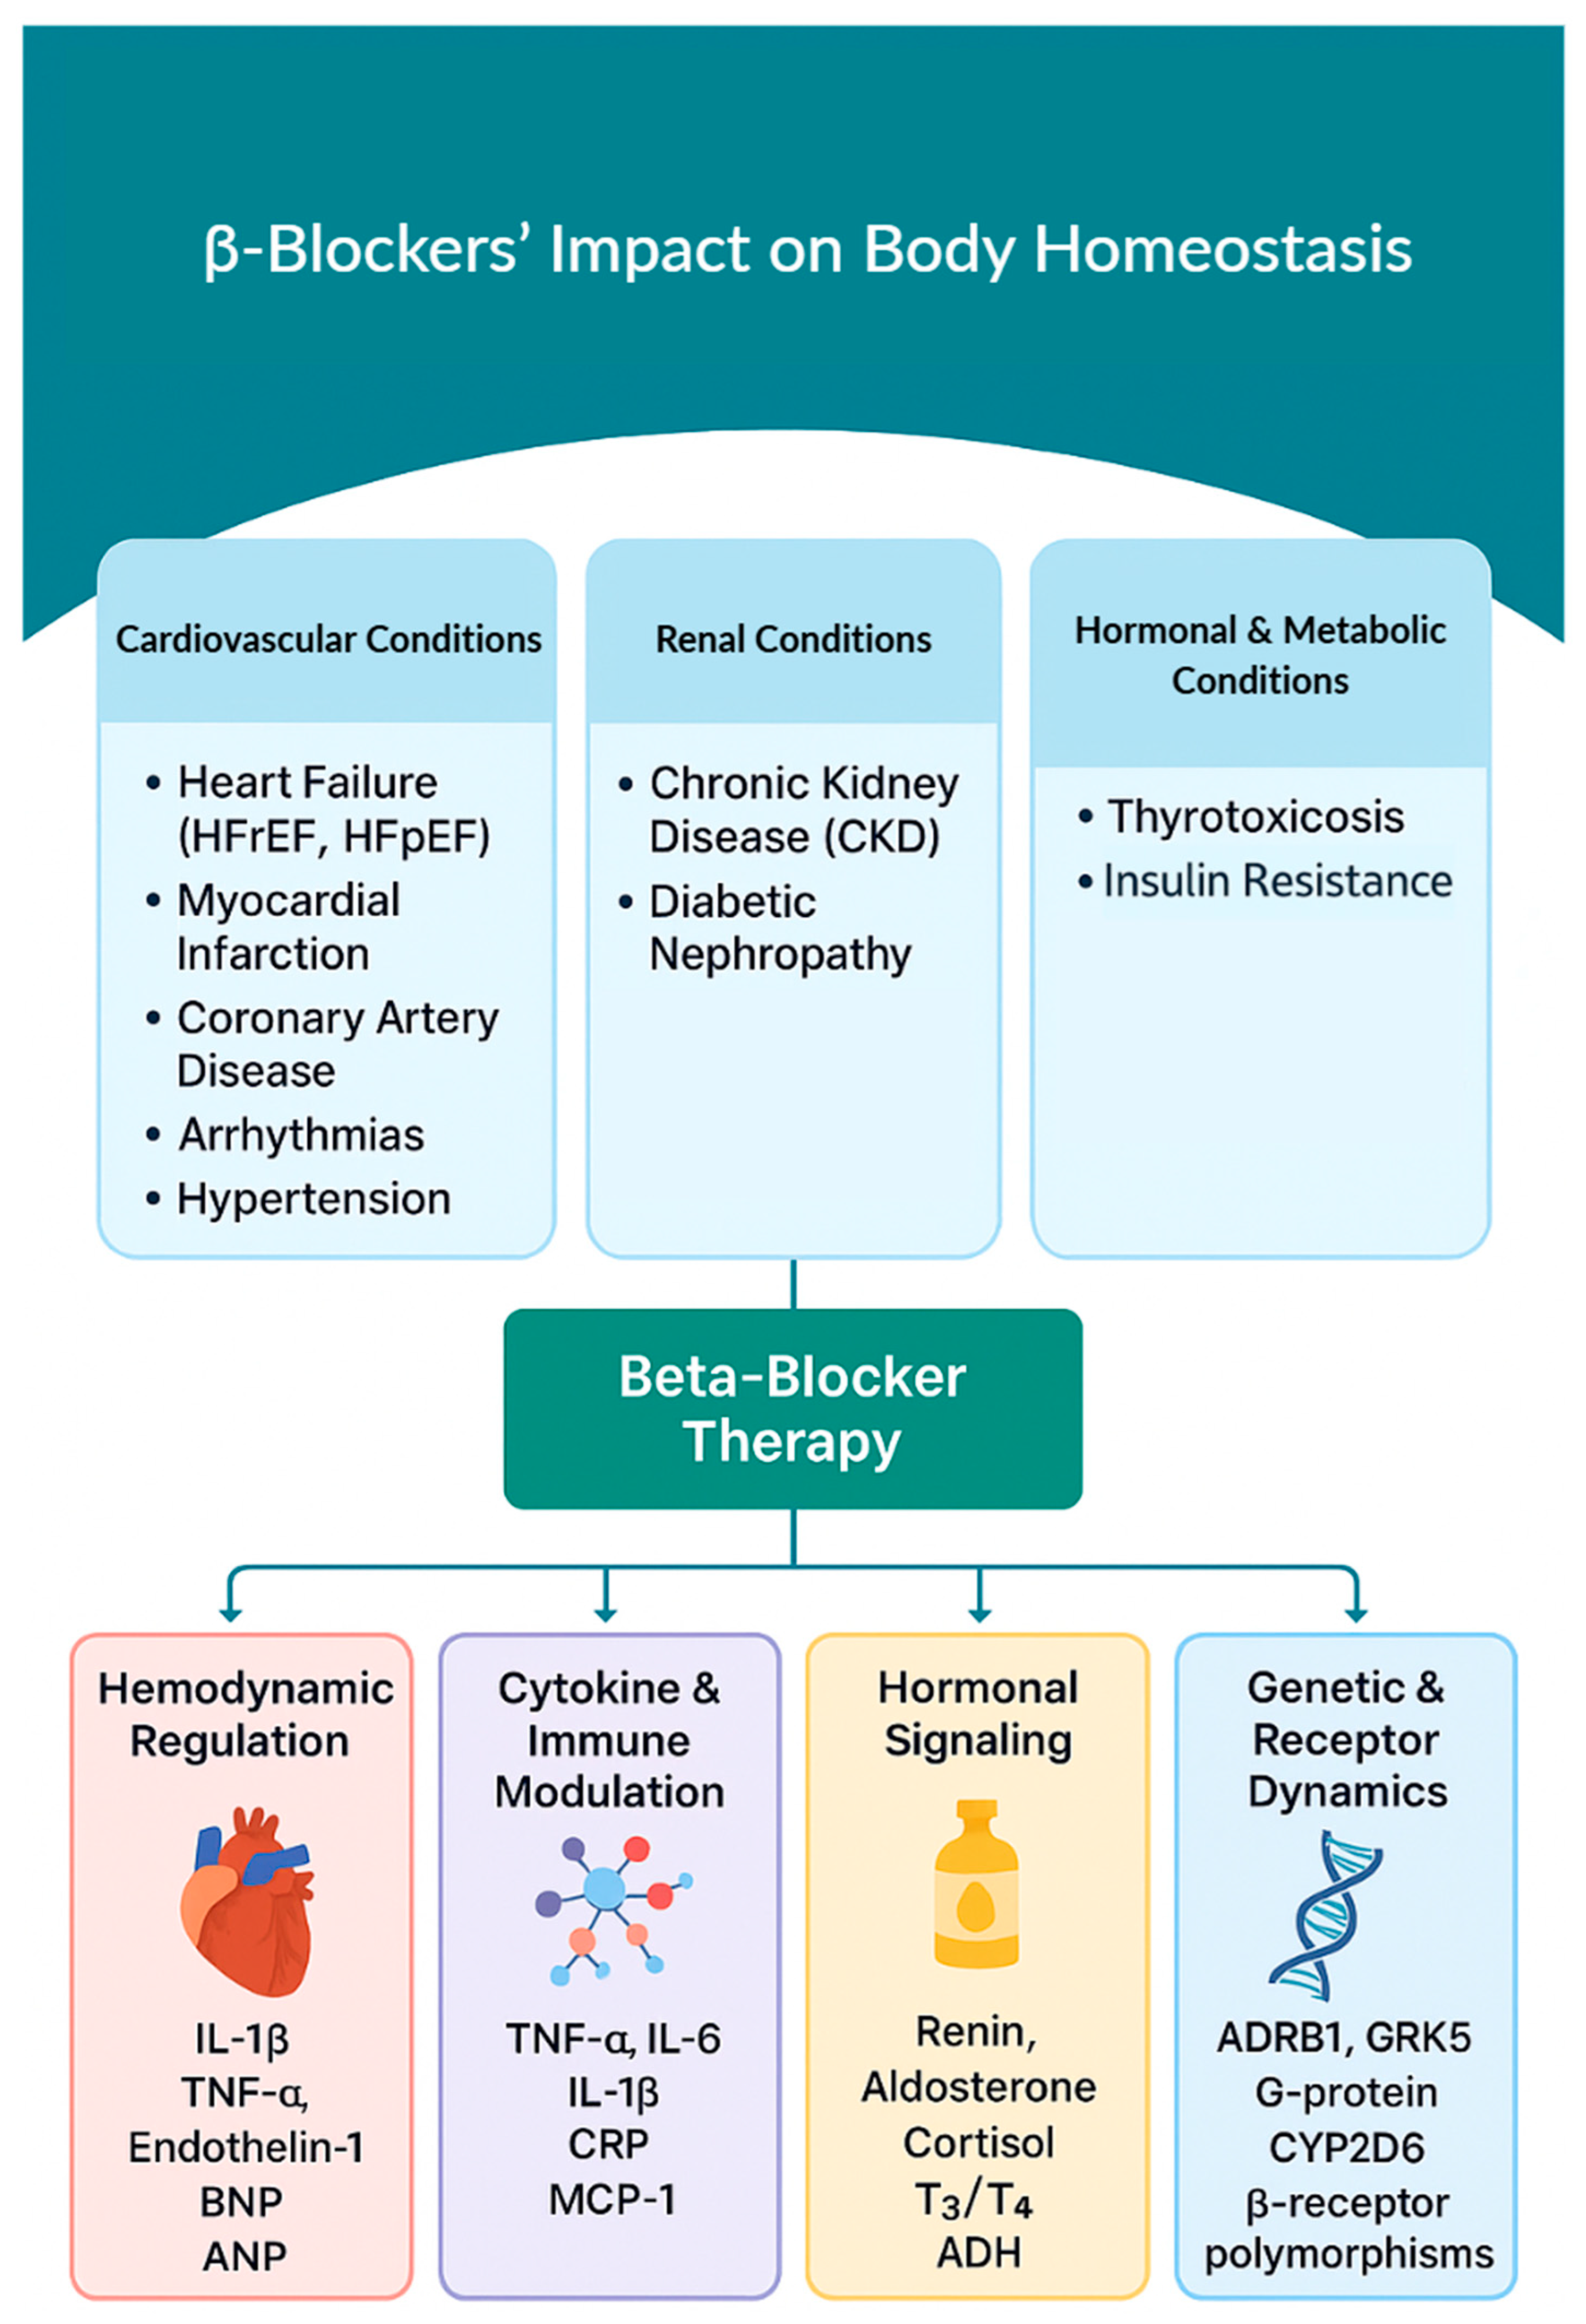
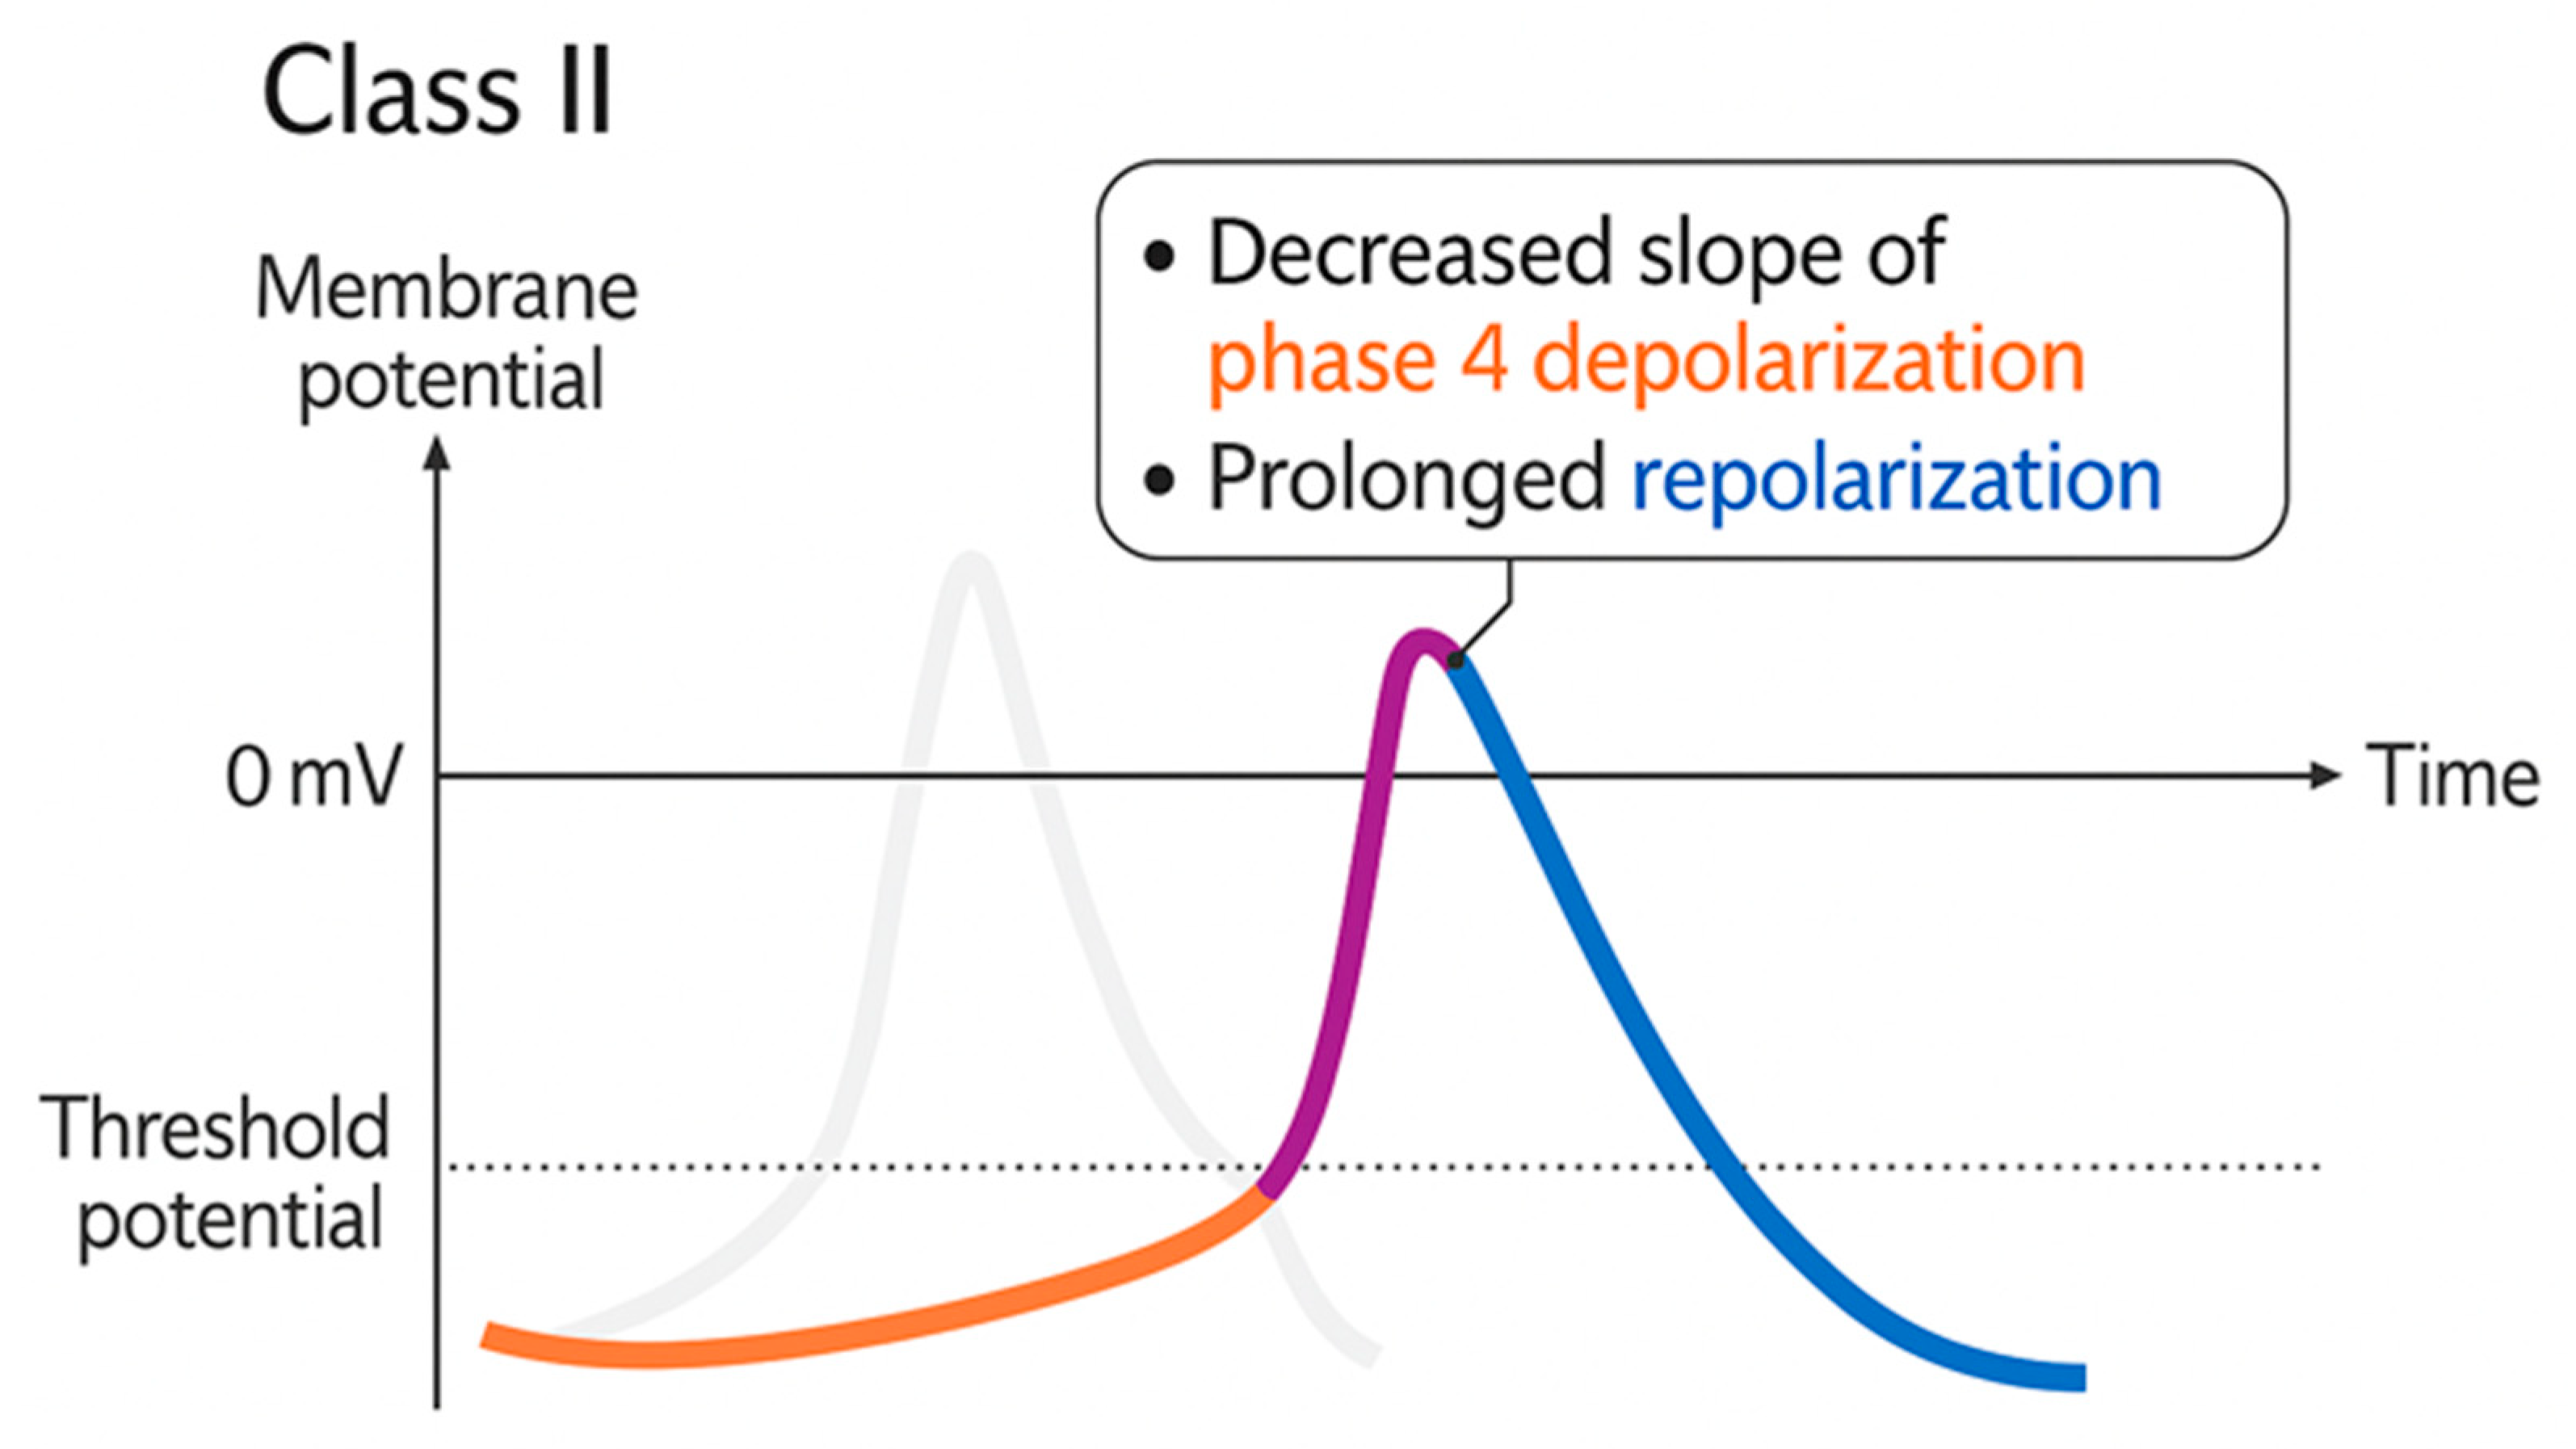
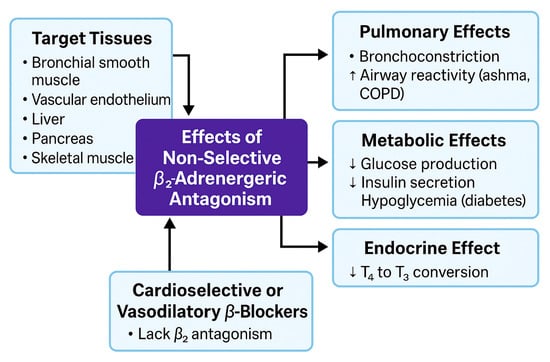
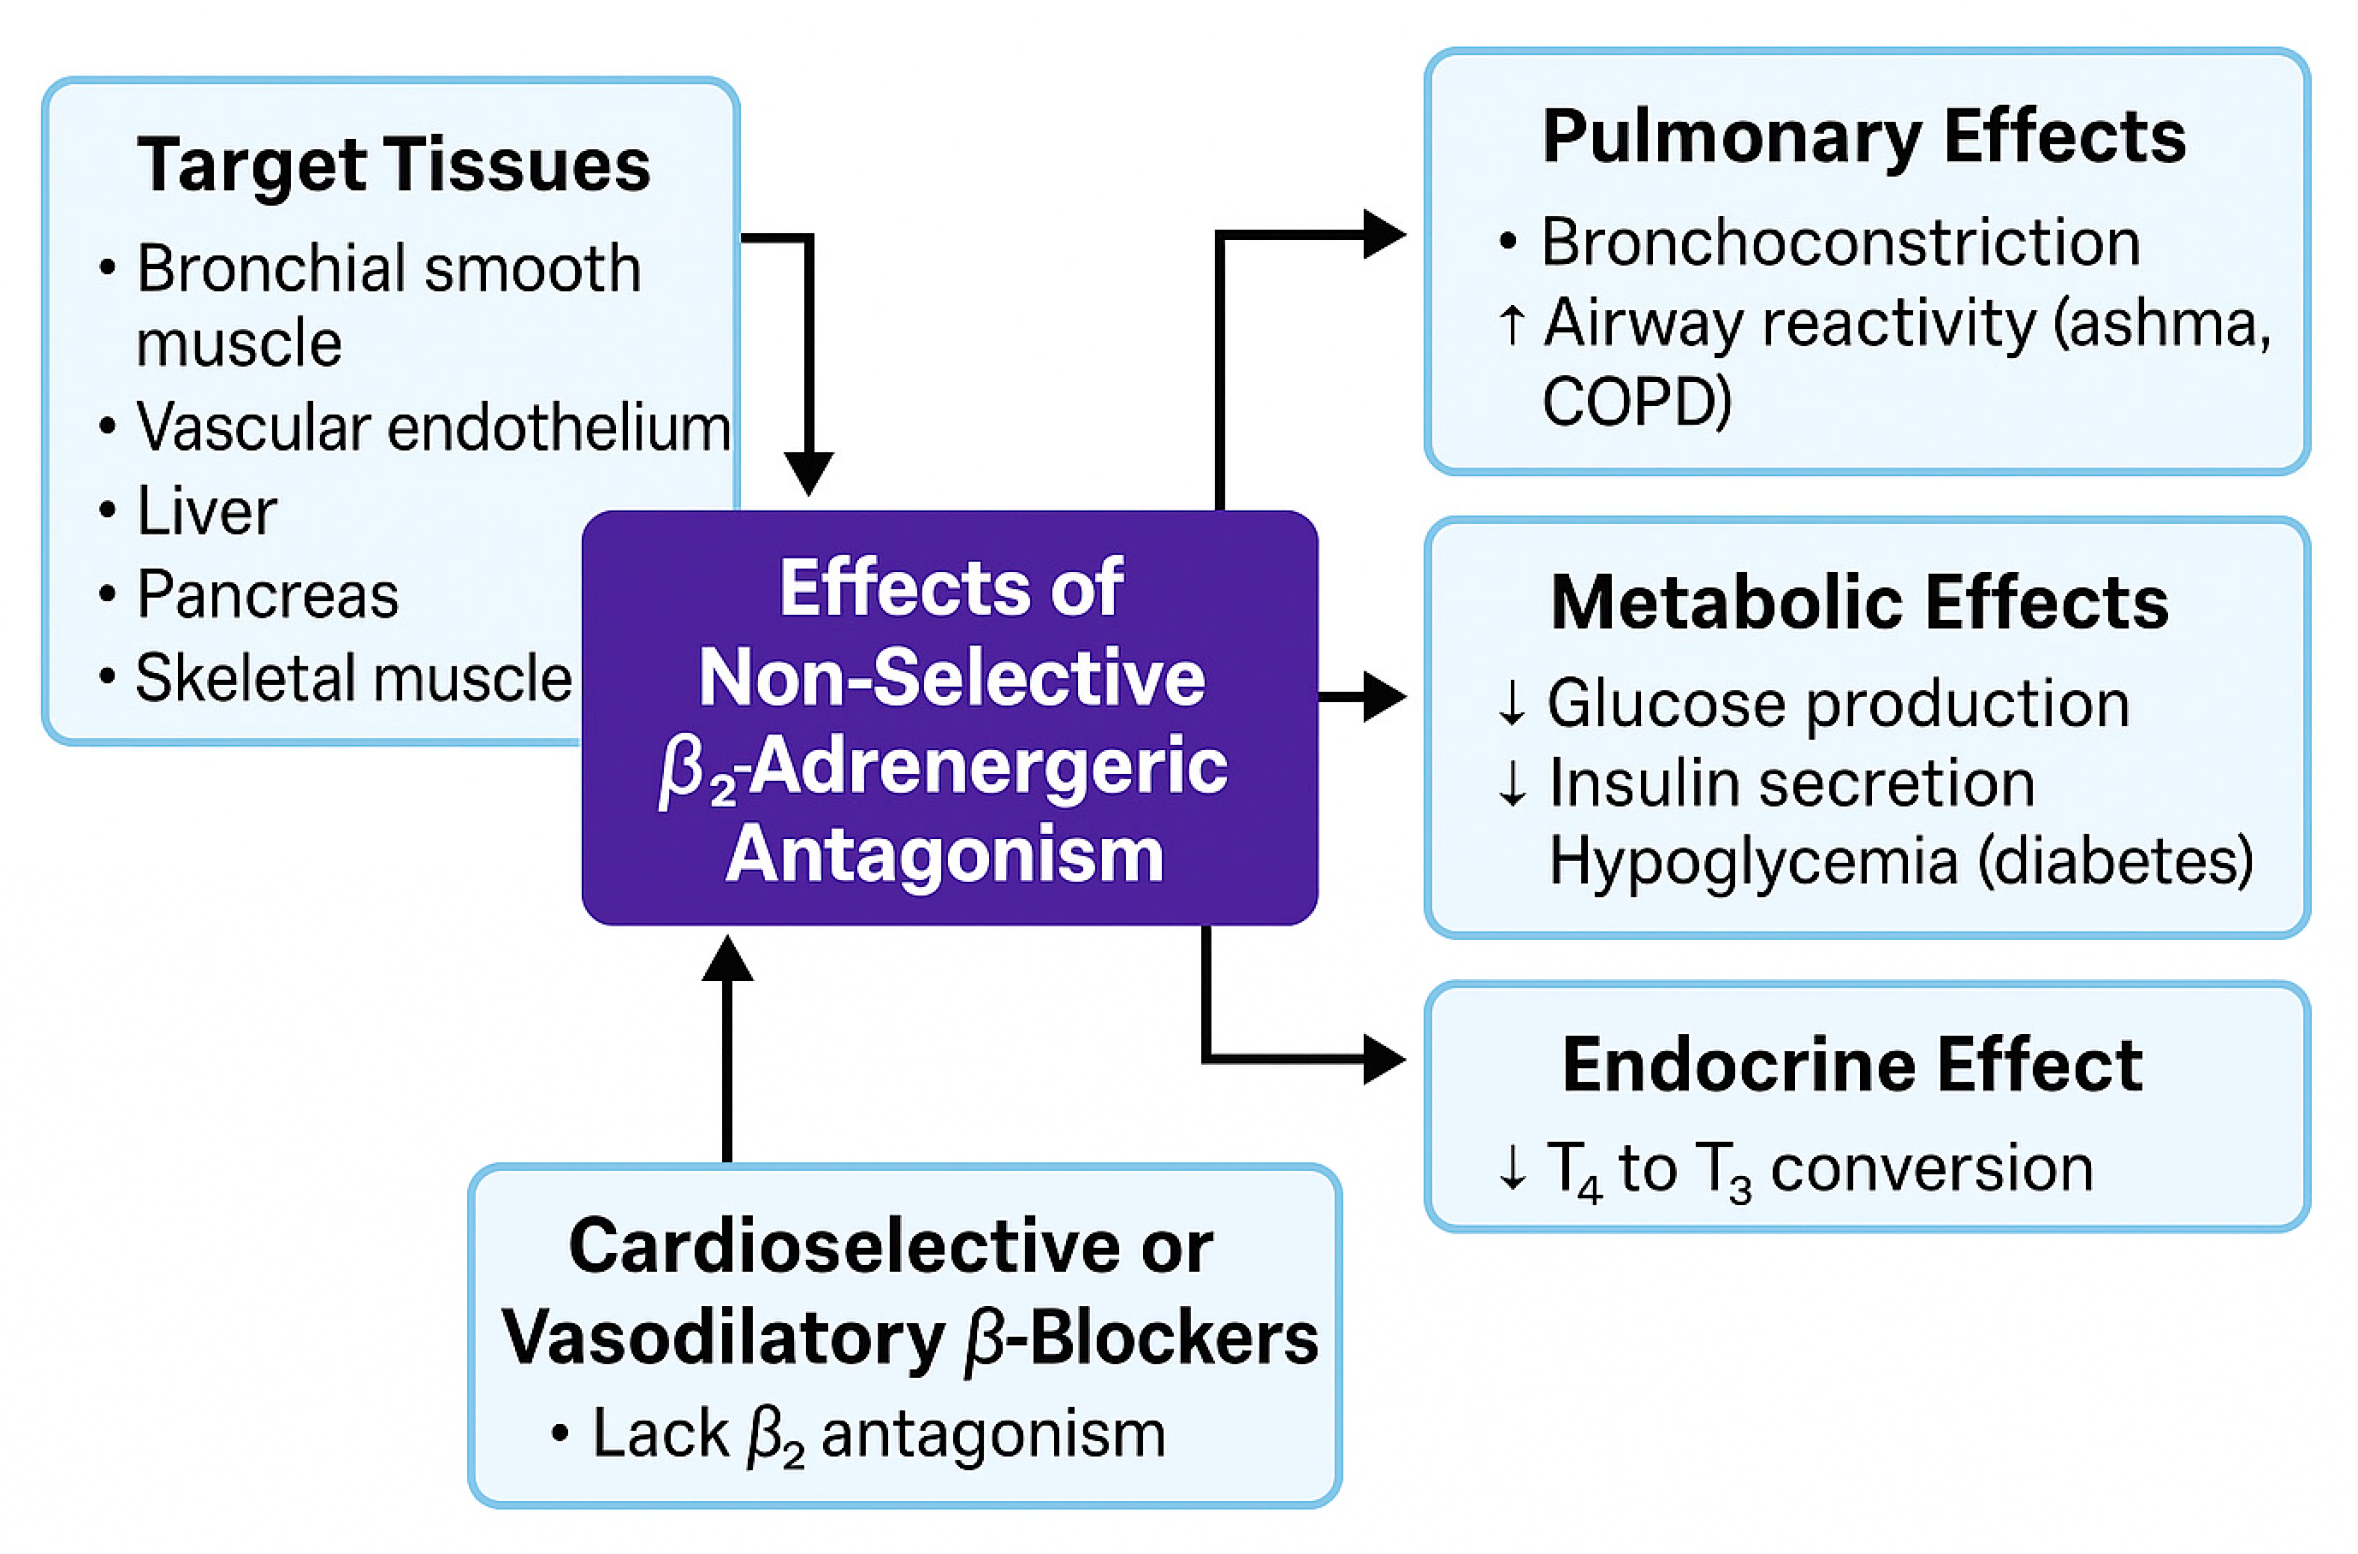
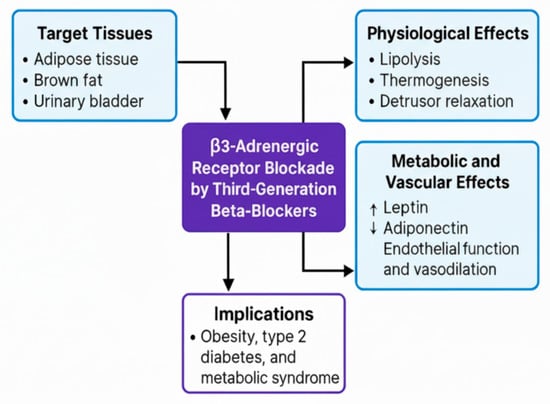
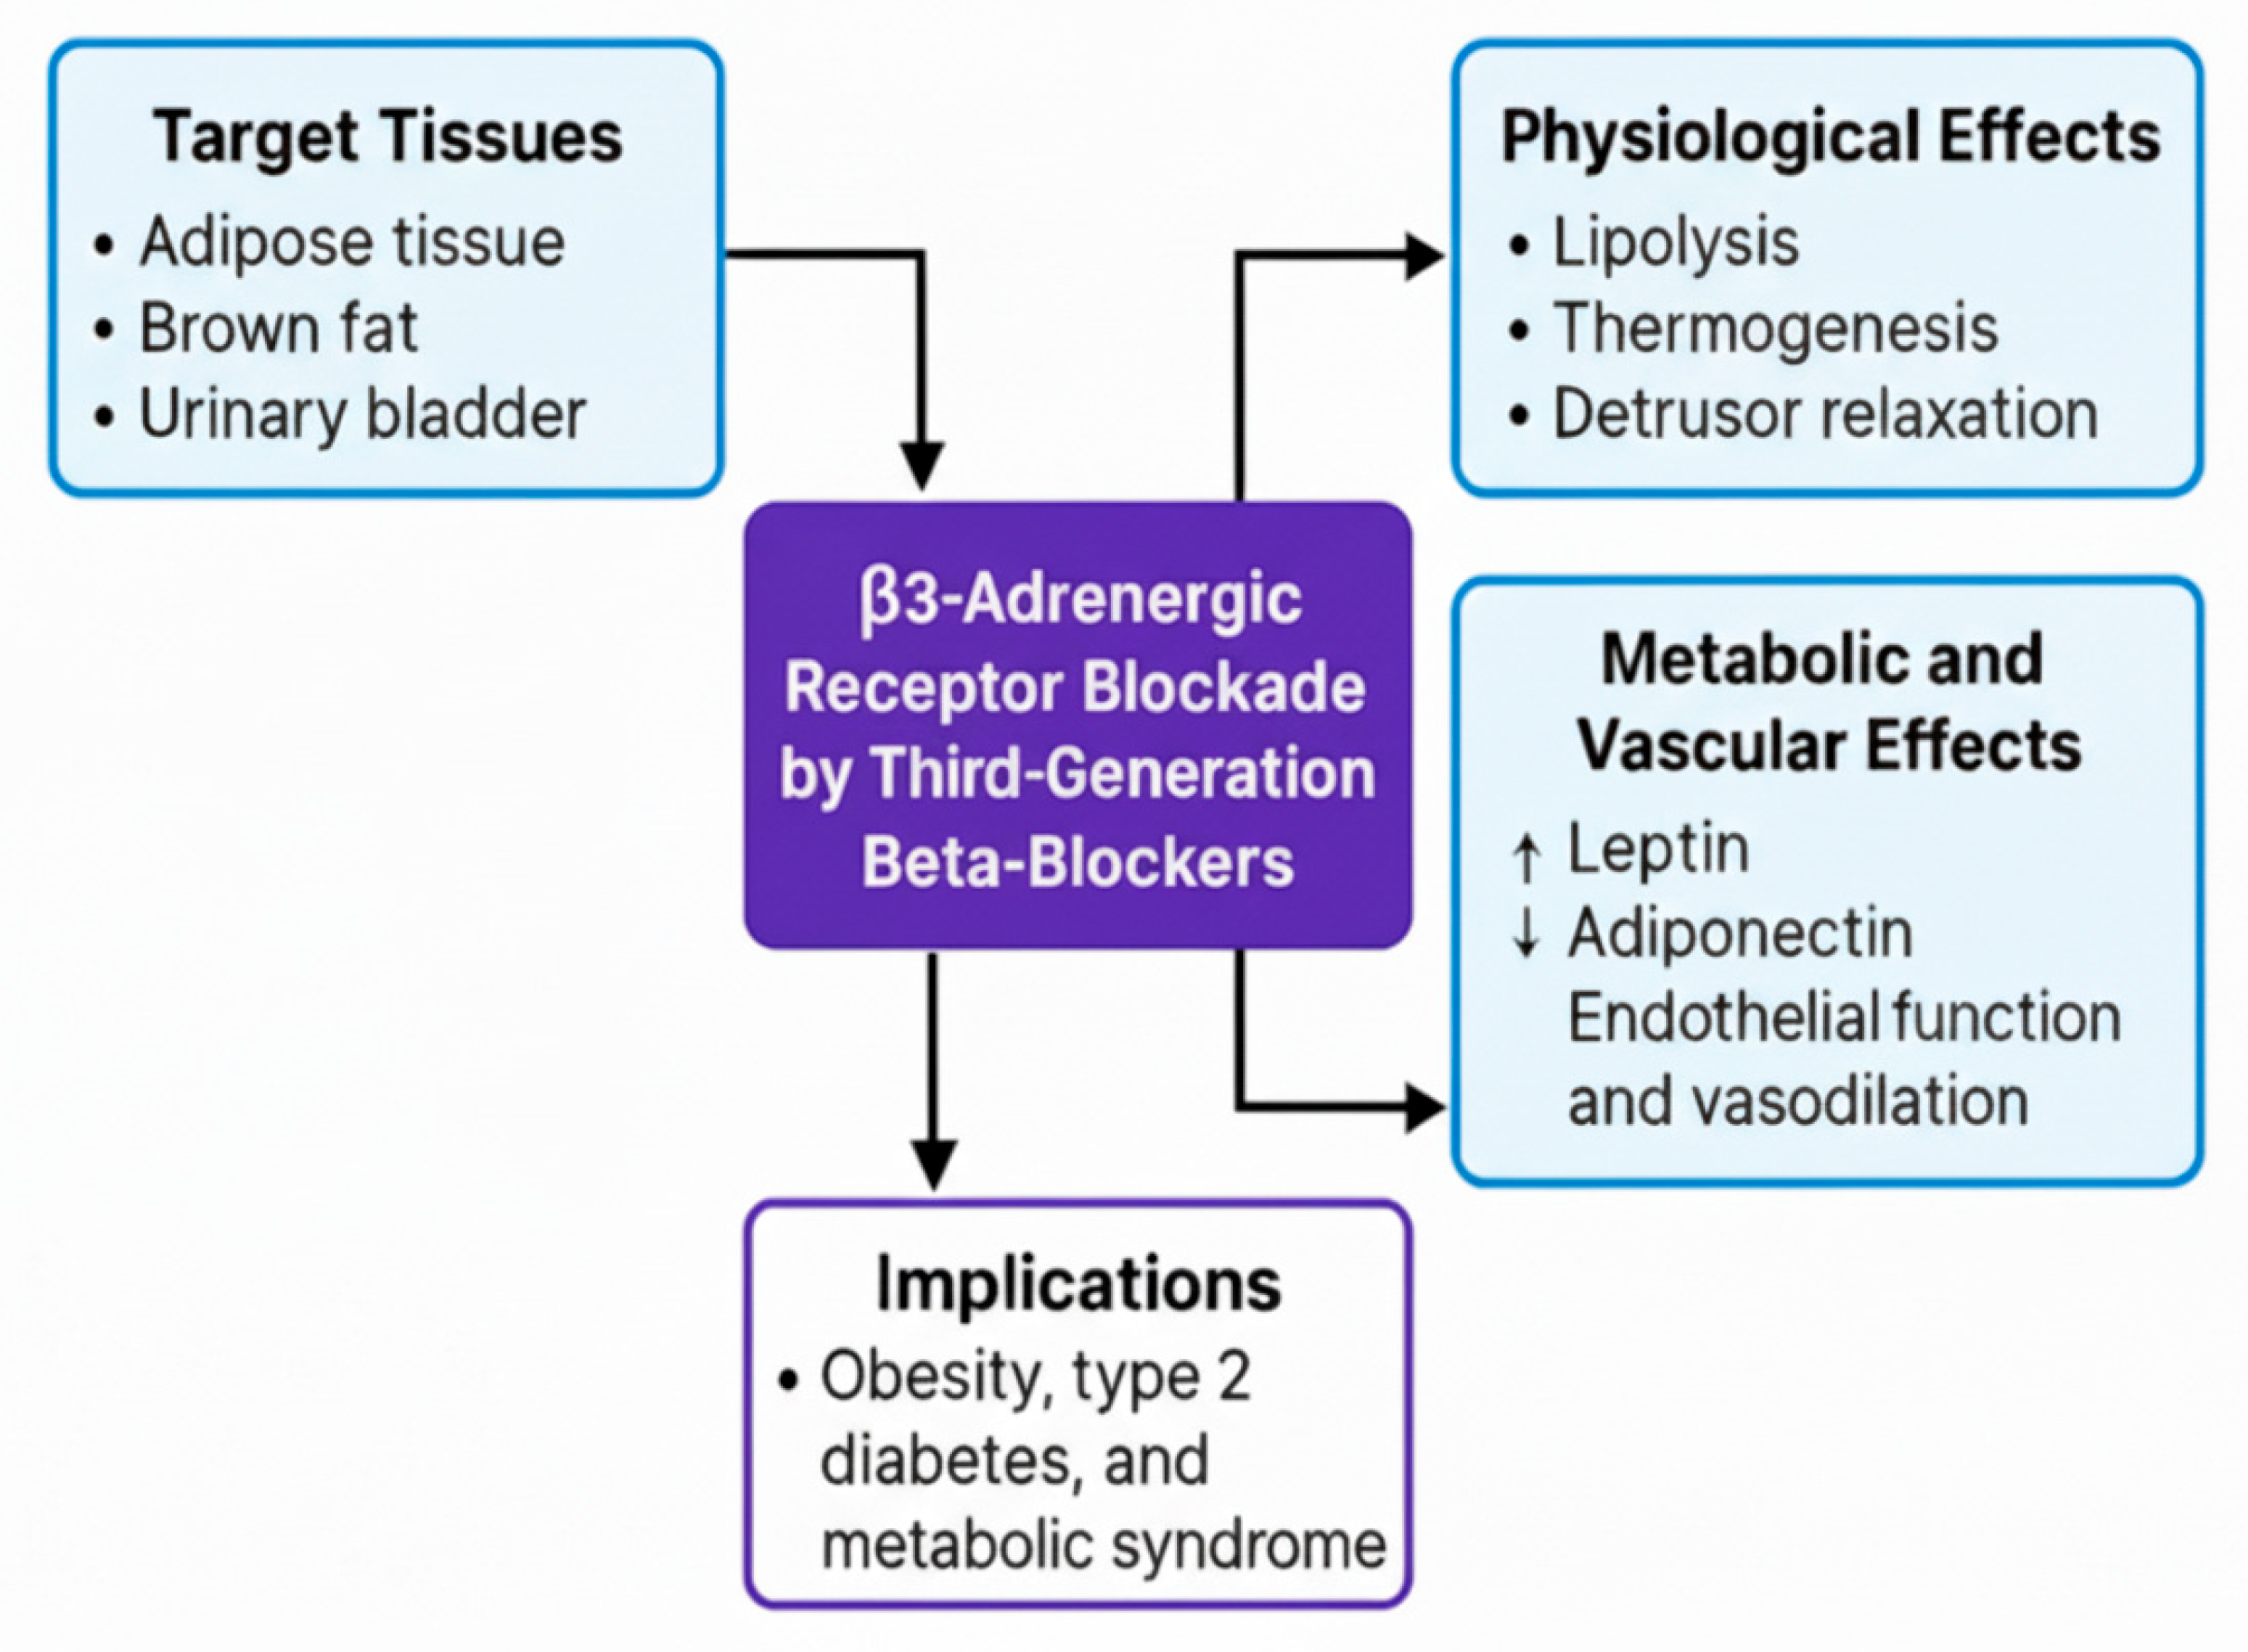
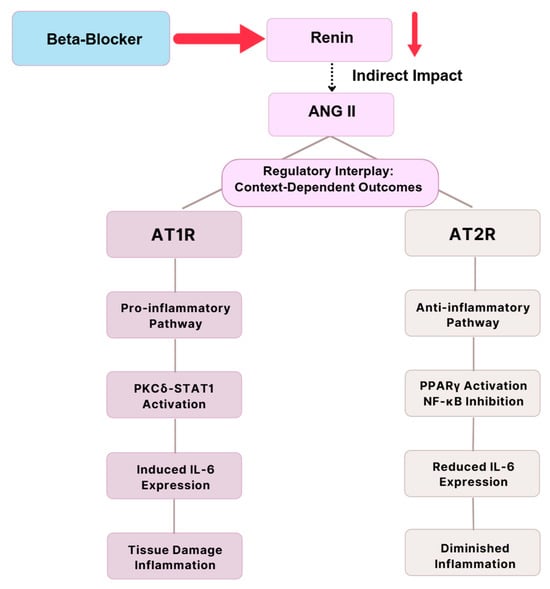
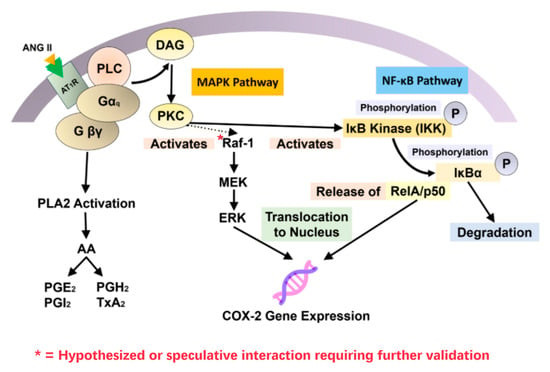

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).