


Abstract
Fingerprint dermatoglyphics serve as a heritable marker of physical ability for talent identification, yet fingerprint loci are linked to limb development, so associations may reflect body morphology. Following a registered protocol (PROSPERO CRD420261469333), we searched five databases and pooled Fisher-transformed correlations between fingerprint indices and objectively measured physical ability with a correlated-and-hierarchical-effects model. Of 20 eligible studies, nine cross-sectional studies contributed 122 correlations from 337 participants, all at high risk of bias. The pooled correlation was r = 0.047 (95% CI −0.036 to 0.130); other models fitted to all nine studies gave 0.02 to 0.07, no interval for the overall effect excluded zero, and none approached the prespecified r = 0.30 benchmark. Only the total ridge count interval excluded zero (r = 0.08). In a sensitivity analysis, adding one borderline report with an ineligible outcome raised the estimate to 0.23 (95% CI −0.11 to 0.53). No study adjusted for anthropometry, maturation, or training. Where measured, anthropometry correlated more strongly with performance than fingerprints did (mean |r| 0.45 vs. 0.17), and adjustment for anthropometry decreased 20 and increased 17 of 37 fingerprint correlations. Certainty was very low. The current evidence does not support using fingerprints to orient or select young athletes.
1. Introduction
Dermatoglyphics, the study of the epidermal ridge patterns of the fingers and palms, occupies an unusual place in sports science. It is marginal in the international literature yet central to practice in large parts of the world. Across Ibero-America and the countries of the former Soviet sphere, fingerprint analysis is used to orient children toward sports, to build athlete profiles, and, in some settings, to inform selection decisions [1,2]. Ridge patterns are established before the 24th week of gestation and do not change thereafter [3]; they are under demonstrable genetic control, to the point that a mutation in a skin-specific isoform of SMARCAD1 produces autosomal-dominant adermatoglyphia [4]; and they can be captured in seconds with ink and paper or an inexpensive optical reader. A stable, heritable, and cheaply measured trait has evident appeal for a talent-identification program in a resource-constrained setting.
Three properties are conflated in that appeal and must be kept apart. Heritability is a population-level quantity: the proportion of the variance of a trait that is attributable to genetic differences among individuals. Association is covariation between the trait and an outcome within a sample, expressed here as a correlation coefficient. Predictive ability is the accuracy with which the trait ranks or classifies new individuals on the outcome, and in a selection context, it also requires that the trait add information beyond measurements that are already available, such as anthropometry [5]. A trait can be highly heritable and unassociated with the outcome; it can be associated with the outcome without ranking individuals usefully; and a cross-sectional association, however large, does not establish prediction in a new sample. The inferential chain that supports practice has three links: fingerprints are fixed in utero; fingerprints are heritable; therefore, fingerprints are genetic markers of physical ability and of the energy systems that underpin it. The first two links concern heritability and are supported by evidence. The third is a claim about association and prediction, and no one has ever tested it. It is assumed in a specific form: a fixed table of equivalences, inherited from Soviet-era sports anthropology, in which arches indicate strength, loops indicate speed, whorls indicate coordination, and the delta index indicates endurance. That table is applied in the primary literature without independent validation [1,6].
Two developments now make the third link testable. The first is genomic. A trans-ethnic genome-wide association meta-analysis identified 43 loci associated with fingerprint patterns; neighboring genes were strongly enriched for limb-development pathways rather than for muscle, metabolic, or neural pathways; a regulatory variant near EVI1 was implicated in limb and digit development on the basis of human developmental expression data, with functional evidence for Evi1 in dermatoglyph patterning obtained in mice; and fingerprint patterns were genetically correlated with hand proportions in human cohorts [7]. This finding does not support the assumed mechanism and suggests an alternative. If fingerprints and limb morphology share developmental genes, and body morphology partly determines physical performance, then an observed fingerprint–performance association may reflect morphology rather than a direct genetic signal. The confounding path (fingerprint ← limb-development genes → hand and limb proportions → performance) is a hypothesis that this review can examine only indirectly and descriptively, not an established pathway.
The second development concerns the exposure itself. Twin data do not support treating the dermatoglyphic indices as interchangeable genetic markers: heritability ranged from 0.11 to 0.96 across characteristics and digits in one female twin series [8], and the additive genetic component ranged from 49% to 81% for digital ridge counts and from 0% to 50% for palmar counts in another [9]. For this review, the consequence is methodological: each index is treated as a distinct exposure, and index-specific estimates are reported alongside the overall summary.
Two systematic reviews of sports dermatoglyphics exist, and the present review addresses a distinct gap relative to each. Fernández-Aljoe et al. [1] mapped the literature of the Americas between 2010 and 2019 and descriptively synthesized thirteen studies by country, sport, and dermatoglyphic profile; the review did not extract effect sizes, assess risk of bias with an instrument for observational designs, or address confounding. Herrera Romero and Castro Jiménez [6] restricted the outcome to strength, narratively synthesized six studies, and appraised them using the Jadad scale, which was designed for randomized trials. Neither review pooled estimates, assessed reporting bias or certainty of evidence, nor examined whether the associations survive adjustment for morphology. The present review covers all objectively measured physical abilities without geographic or date restriction, pools the published correlations with models that account for the dependence among estimates from the same participants and the same research groups, appraises the risk of bias and certainty with tools designed for prognostic-factor questions, and examines the morphological-confounding hypothesis indirectly and descriptively, with the data the primary studies make available. Meta-analyses of dermatoglyphics in pediatric oral disease [10,11] informed only our prior expectation of heterogeneity (I2 of roughly 78% to 98% in [11]).
We therefore conducted a systematic review and meta-analysis with two aims: to quantify the magnitude and direction of the association between quantitative fingerprint dermatoglyphic indices and objectively measured physical abilities and to determine the extent to which that association is attenuated by adjustment for anthropometry, body composition, biological maturation, and training exposure, that is, to test the morphological-confounding hypothesis; because no primary study reported an adjusted estimate, this second aim could be addressed only indirectly (Section 3.9). The hypothesis under test is the one the applied literature makes: that each index predicts the capacity assigned to it in the equivalence table with an association large enough to guide orientation. The benchmark of practical relevance against which the estimates are read, r = 0.30, is defined and justified in Section 2.6. Because the equivalence table predicts different signs for different index-by-capacity combinations, the overall pooled estimate serves as an omnibus summary of the literature, while the index-specific predictions are examined in the subgroup analyses and the evidence map.
2. Materials and Methods
2.1. Protocol, Registration, and Reporting
The protocol was registered prospectively in PROSPERO (CRD420261469333) before screening began, and the full protocol document was uploaded to the register. Reporting follows PRISMA 2020 [12]; the completed checklist is provided in Supplementary Materials (Table S1). Where quantitative pooling was not appropriate, synthesis and its reporting follow the Synthesis Without Meta-analysis (SWiM) guideline [13]. No amendments were made to the registered protocol after screening began; the four deviations that arose during analysis are declared in Section 2.9.
2.2. Eligibility Criteria
The review question was framed as PECO (population, exposure, comparator, outcome). Population included humans of any age, sex, and competitive level, athletes and non-athletes alike. Exposure included normal anatomical variation in fingerprint or palmar dermatoglyphic patterns, characterized by quantitative indices: delta index (D10), total ridge count (SQTL), frequency of arches, loops, and whorls, the atd angle, a–b ridge count, or digital formula (Figure 1). Comparator included individuals with a contrasting dermatoglyphic profile; athletes versus non-athletes; or sports of predominantly aerobic versus predominantly anaerobic demand. Correlational designs without an explicit comparison group were admitted and analyzed separately. Outcome included objectively measured physical ability, comprising maximal and isometric strength, handgrip strength, muscular power and explosive strength, sprint speed, agility, aerobic and anaerobic endurance, flexibility, and motor coordination. The registered outcome list does not include sport-specific technical skills. For eligibility, motor coordination was defined as a general capacity measured with standardized tests that do not depend on practice in a particular sport, such as balance, lateral jumping, or hand–eye coordination tasks scored by time, errors, or count. We did not treat scores of sport-specific technical performance, such as passing, shooting, or dribbling accuracy, as measures of motor coordination: they also reflect training history, tactical knowledge, and experience with the ball and the task, so we cannot attribute differences between players to physical capacity. This distinction decided the eligibility of one report (Section 3.1).
Figure 1.
The quantitative dermatoglyphic indices that constitute the exposure. (a) The three distal-phalanx patterns of the simplified classification used throughout the included corpus, defined by their number of triradii (deltas): an arch (A) has none, a loop (L) has one, and a whorl (W) has two. Finer subtypes (ulnar and radial loops, composite and double-loop whorls) exist in the Cummins and Midlo system but are collapsed into these three classes by every included study. (b) Per-digit ridge count and its total across the ten digits (SQTL). (c) The delta index (D10) is the sum, over the ten digits, of the number of triradii each digit contributes: 0 for an arch, 1 for a loop, and 2 for a whorl. In the panel, “W = 2” therefore means that one digit bearing a whorl contributes two deltas to the sum, not that a digit carries two whorls; each digit carries a single pattern. D10 ranges from 0 (ten arches) to 20 (ten whorls); in the worked example, six loops and two whorls give D10 = 6 + 2 × 2 = 10. (d) Palmar triradii, the atd angle, and the a–b ridge count. (e) Digital formulas. Original schematic; the definitions depicted are transcribed from the full texts of the included corpus, which attribute them to the Cummins and Midlo protocol [14]. No panel reproduces a real fingerprint.
The protocol excluded musculoskeletal injury and musculoskeletal disease as outcomes to distinguish this review from the registered record CRD420261326579, which covers that domain. Eligible designs were cross-sectional studies, case–control studies, cohort studies, and trials in which dermatoglyphics were measured at baseline. Case reports, case series without a comparison group, editorials, conference abstracts without full text, narrative reviews, and other reviews without primary data were excluded. Preprints and articles awaiting peer review, retrieved from the preprint servers listed in Section 2.3, were screened using the same criteria; none contributed to the quantitative synthesis. No language or date restrictions were applied at the search stage.
2.3. Information Sources and Search Strategy
The Web of Science Core Collection was searched via an institutional proxy, along with four Ibero-American databases treated as mandatory rather than supplementary (SciELO, LILACS/BVS, Redalyc, and Dialnet), because the bulk of this literature is Ibero-American and not indexed in the major English-language databases. PubMed, Europe PMC, Crossref, Semantic Scholar, DOAJ, OpenAlex, Cochrane Library, and the medRxiv and bioRxiv preprint servers were also consulted. Searches were run on 3–4 August 2026. The full search syntax for each source is provided in Supplementary File S2 and has been uploaded to PROSPERO.
One feature of the strategy warrants emphasis because it materially affects yield. The term “fingerprint” is used in at least six unrelated senses in the indexed literature: spectral, molecular, epigenetic, connectomic, facial, and radio-frequency. Without an explicit NOT block or restriction of the term to the title field, retrieval is heavily contaminated; the field in which the term was searched in each source is stated in the search syntax (Supplementary File S2). We verified this empirically: eight records reaching full-text assessment in this review were “fingerprint” papers in one of those other senses, including surface-enhanced Raman spectroscopy of β2-agonists, received-signal-strength-indicator fingerprinting for robot localization, and a connectomic study of motor skill.
2.4. Study Selection and Data Collection
Titles and abstracts of the 121 deduplicated records were screened against the eligibility criteria by one reviewer (A.R.-J.). At this stage, a record was excluded only when the title and abstract showed that it did not concern finger or palmar dermatoglyphics (the other senses of “fingerprint”), that no physical ability was measured (clinical, genotypic, or purely descriptive outcomes), or that the design was ineligible (reviews without primary data, reflection articles, case reports); any record for which eligibility could not be settled from the abstract was carried forward to full-text assessment. The full texts of the 77 unique reports available for assessment were read in full by the same reviewer; decisions were recorded per record with the exclusion code applied (Supplementary File S3). The four records co-authored by G.G.-C. were decided jointly by A.R.-J. and J.G.-A. under the recusal rule, and the single borderline report (Section 3.1) was adjudicated by the guarantor. Dual independent screening was therefore not performed for the corpus, and no inter-reviewer agreement statistic is available; this is a limitation that increases the risk of selection error (Section 4.8). A keyword-based pre-classification flag was generated for each record solely as an orienting signal and was not used for decision-making; no automated screening tool was used.
Data were extracted by one reviewer (A.R.-J.) into a structured workbook that recorded, for each effect estimate, the study, sample size, dermatoglyphic index, capacity domain, specific test, the coefficient exactly as published, the published p-value where available, the table or figure from which the value was taken, and whether the sign had been reversed. Because a single extractor was used, no extraction discrepancies arose to resolve; instead, the safeguards applied were arithmetic rather than procedural. Four correlation matrices were published as images without extractable text; these were read by rendering the source page at 140 and 400 dots per inch and are identified as figure-derived in the extraction file. Every transcribed coefficient was checked for arithmetic consistency with its published p-value at the stated sample size, which is how two internally inconsistent rows were detected and excluded (Section 3.10). The complete extraction file, with the provenance of every coefficient, is published so that any reader can audit each value.
One member of the review team (G.G.-C.) has co-authored primary studies in this field and co-authored one of the two previous systematic reviews. A recusal rule was registered and applied: he did not participate in eligibility, extraction, or risk-of-bias assessment for any record he co-authored, which the other two reviewers handled; he is not the guarantor; and the author-group sensitivity analysis was applied to his group on identical terms.
2.5. Risk of Bias and Certainty
Risk of bias was assessed with the Quality in Prognosis Studies (QUIPS) tool [15], applied domain-by-domain by the two reviewers named in Section 2.4. QUIPS was developed for studies of prognostic factors, and its use here requires justification because the included designs are cross-sectional. The review question is nonetheless a prognostic-factor question in the sense of the PROGRESS framework [5]: it asks whether a baseline characteristic of the individual (a fingerprint index, fixed before birth) is associated with an outcome (measured physical ability), irrespective of whether the two were recorded on the same day. QUIPS is the tool recommended for systematic reviews of such questions [16], and its six domains map directly onto the threats to validity that matter here: selection into the sample (study participation), measurement of the factor (ridge counting and pattern classification by a human assessor), measurement of the outcome, confounding (morphology, maturation, and training), and statistical analysis and reporting; the sixth domain, attrition, is not applicable to a single-occasion design and was recorded as such. Inter-rater agreement with QUIPS is only moderate, even among experienced raters, and a documented justification for each domain judgment is the recommended safeguard [17]. The Risk Of Bias In Non-randomized Studies—of Exposure (ROBINS-E) tool [18] was considered but not applied because it is built around exposure effects estimated in follow-up studies, and generic checklists for observational studies lack a domain for the measurement of the factor itself. Per-study, per-domain judgments with their justifications are provided in Supplementary File S3 (Table S2). Measurement validity of the exposure was also assessed, covering the capture method, assessor training, blinding to the outcome, and reported intra- and inter-rater reliability. The Jadad scale was not used; it was designed for randomized trials and applying it to cross-sectional and case–control studies in a previous review in this field (Section 4.5) mismatches the instrument with the study design. Certainty was rated using the Grading of Recommendations Assessment, Development and Evaluation (GRADE) approach, adapted for prognostic-factor questions [19].
2.6. Effect Measures and Synthesis
Only published correlation coefficients were pooled. Studies reporting associations as group-difference statistics on categorized exposures or outcomes (for example, chi-square or Kruskal–Wallis tests across handgrip categories [20]) were retained in the review and the evidence map but were not converted to r, because such conversions require assumptions about the underlying distributions that the reports do not permit us to verify; the consequence of this rule is stated in Section 4.8. Effects reported only as p-values or as non-significant without a coefficient could not be extracted; the study was retained in the evidence map. Correlations were transformed to Fisher z with sampling variance 1/(n − 3). Where a test was scored in time so that a lower value denotes better performance (2000 m rowing ergometer time and the Illinois agility test), the sign was reversed so that a positive value indicates that a higher value of the dermatoglyphic index is associated with better performance; sprint tests expressed by the source as mean velocity in m/s [21] were not reversed. Sign reversal was applied only to time-scored tests; no reversal was applied on the basis of the index. For arch frequency, which lies at the opposite pole of pattern complexity from whorl frequency, delta index, and ridge count, a positive coefficient indicates that higher arch frequency is associated with better performance. The overall pooled estimate consequently averages indices of opposite polarity and opposite predicted sign under the equivalence table and is an omnibus summary rather than a test of the index-specific predictions (Section 3.6 and Section 4.8). The convention is recorded per effect in the extraction file.
Benchmark of practical relevance: We prespecified r = 0.30 as the minimum magnitude at which use of a dermatoglyphic index to orient or select athletes would begin to be defensible, and |r| < 0.10 as a practical null. The value 0.30 is the conventional threshold for a medium correlation [22], the lower bound of a “moderate” correlation in the scale most used in sports medicine [23], and a value that empirical surveys of psychological research classify as large for a single predictor [24]. Its practical meaning is modest: an index correlating 0.30 with performance explains 9% of its variance and, under bivariate normality, correctly orders a randomly chosen pair of athletes based on performance with probability 0.60 rather than 0.50 [25]. Estimates below this benchmark therefore cannot rank individuals with accuracy useful for selection, whatever their statistical significance; a benchmark of this kind is a reading aid for the estimates, not a validated decision threshold, and no equivalence test was performed.
Models: Effects from the same study are computed on the same participants and have correlated sampling errors, and several studies come from the same research groups. Three models address this dependence and are reported together (Section 3.5). The primary inferential analysis is a correlated-and-hierarchical-effects (CHE) working model [26] in which effects are nested within studies, sampling errors within a study are assumed correlated at ρ = 0.6 (with sensitivity analyses at ρ = 0.3 and 0.9), and a between-study (τ2) and a within-study (ω2) variance component are estimated by restricted maximum likelihood (REML); the standard error of the pooled mean was obtained by cluster-robust variance estimation at the study level with the bias-reduced linearization small-sample adjustment (CR2) and Satterthwaite degrees of freedom [27,28], which remain valid with as few as nine clusters at the cost of wide intervals. The CHE model was adopted after an earlier round of peer review in place of the registered model, for the reasons that follow, and the change is declared in Section 2.9. The registered model was a three-level random-effects model with effects nested within studies and studies within author groups [29], estimated by restricted maximum likelihood with a Hartung–Knapp adjustment to the confidence interval [30] using k − 1 = 121 degrees of freedom, and a 95% prediction interval [31]. It was chosen at registration because it is the established approach to dependent effect sizes when the within-study sampling covariances are not reported [29,32], and author group was modeled as a level because preliminary searches showed that a few groups account for most of the corpus. Its limitation is that it treats the sampling errors of effects from one study as conditionally independent and does not estimate a within-study variance component; when both between-level variances are estimated at or near zero, as happened here, it reduces to a fixed-effect analysis of 122 pseudo-independent effects and its intervals are anti-conservative. It is therefore retained as a sensitivity analysis and is the model behind the subgroup estimates in Section 3.6, where the number of studies per subgroup is too small for robust inference. The third approach, cluster-robust variance estimation with the approximate correlated-effects weights of Hedges et al. [33] (one weight per study, τ2 = 0, CR1 small-sample factor, i.e., the conventional sandwich estimator multiplied by clusters/(clusters − 1), t distribution with clusters − 1 degrees of freedom) at the study and the author-group level, was added as a further sensitivity analysis. For the three-level model, the multilevel I2 decomposition of Cheung [29] is reported; for the CHE model, the proportion of total variance attributable to each component is computed with the same typical sampling variance.
Bayesian sensitivity analysis: A Bayesian counterpart to the three-level structure was fitted with weakly informative priors: a standard normal prior on the pooled mean in Fisher z units and half-Cauchy(0, 0.5) priors on the between-study and between-group standard deviations [34]. The random effects were integrated out analytically, and the three remaining parameters were sampled by adaptive random-walk Metropolis in four independent chains of 80,000 iterations each (30,000 discarded as burn-in, thinning 10, 20,000 retained draws). Convergence was assessed with the rank-normalized split R-hat and the bulk and tail effective sample sizes of Vehtari et al. [35]; chains were accepted when R-hat < 1.01 for every parameter. Sensitivity to the priors was examined by refitting with five alternative specifications (half-normal(0, 0.5), half-Cauchy(0, 1), half-Cauchy(0, 0.25), and half-normal(0, 0.2) on the standard deviations, and Normal(0, 0.5) on the mean) and, to mirror the primary model, with sampling errors within a study correlated at ρ = 0.6 and a within-study component in place of the author-group level. The Bayesian 95% prediction interval is the central 95% interval of the posterior predictive distribution of the true correlation in a new study from a new author group. Posterior probabilities were computed for |r| < 0.10, |r| < 0.20, and r > 0.30. The analysis is presented as a sensitivity analysis of the frequentist conclusions, not as independent confirmation of them, because it uses the same data and a closely related model.
Subgroup, moderator, and sensitivity analyses: Prespecified subgroup analyses were by dermatoglyphic index and by type of physical ability, and are reported under the three-level model, with CHE estimates added where at least three studies contributed. Subgroup p-values are exploratory: ten subgroups were examined, no multiplicity correction was applied, and no subgroup hierarchy was prespecified. Whether the pooled correlation differed across physical-ability domains and across indices was tested with a Wald-type Q statistic from a three-level mixed-effects model with the subgroup as a categorical moderator; because that model assumes conditional independence within studies, the test is exploratory. Prespecified sensitivity analyses were a two-level model, retention of a single effect per study (the median oriented correlation of the study, with variance 1/(n − 3)), retention of a single effect per author group (the median oriented correlation across the group, with variance based on the group total n), and a leave-one-study-out influence analysis. Two post hoc analyses added after the earlier round of peer review are labeled as such where reported: an analysis restricted to hypothesis-concordant effects, in which each effect is signed according to the prediction of the equivalence table for its index-by-capacity combination (the cells with data are arches × strength, loops × speed, and total ridge count or delta index × aerobic endurance, all predicting a positive oriented correlation), and first-order partial correlations, rxγ·ᴢ = (rxγ − rxᴢ rγᴢ)/√[(1 − rxᴢ2)(1 − rγᴢ2)], computed from the published matrices in the studies that report the three coefficients required, adjusting for one anthropometric covariate at a time.
2.7. Software
All analyses were performed in Python 3.13 with NumPy 2.5 and SciPy 1.18; R-hat and effective sample sizes were computed with ArviZ 1.3. The three-level and CHE restricted maximum-likelihood estimators were implemented directly, maximizing the restricted log-likelihood over the variance components with the Nelder–Mead algorithm from scipy.optimize from multiple starting values to guard against local optima; the Hartung–Knapp adjustment, the multilevel I2 decomposition, the prediction intervals, the CR2 adjustment matrices and Satterthwaite degrees of freedom [28], and the Hedges et al. robust estimator were likewise implemented directly. The CR2 implementation was verified by simulation under the fitted working model: across 4000 replicates the mean CR2 variance was within 2% of the empirical sampling variance of the pooled estimate, and the Satterthwaite t-test rejected at 3.5% under the null. The Bayesian sampler was written for this analysis using the PCG64 generator of numpy.random with fixed seeds, one per chain. Figures were produced with Matplotlib (https://matplotlib.org), and the extraction workbooks with openpyxl (https://openpyxl.readthedocs.io). For data capture, text and tables were extracted from the retrieved PDFs with Poppler 24.02.0 (pdftotext, including layout-preserving mode); pages containing image-only tables were rendered with pdftoppm at 140 and 400 dots per inch; and two image-only reports were read with Tesseract 5.3.4. No commercial statistical package was used, and every estimator reported here can be reproduced from the deposited code and extraction file.
2.8. Reporting Bias
The protocol conditioned the interpretation of funnel plots and the use of Egger regression on the availability of at least ten studies. Nine studies contributed extractable effects, so Egger regression was not performed, and the funnel plot is presented for descriptive purposes only. A funnel plot of dependent effects is not a valid display of small-study effects across studies because each study’s effects share a single standard error and are stacked horizontally at that value; methods designed for dependent effects exist [36] but require more studies than are available here. The vertical position of a point in the funnel is its standard error, a measure of precision, not a p-value; a point lies outside the pseudo-95% funnel when its Fisher z differs from the pooled value by more than 1.96 standard errors, which is a statement about dispersion around the pooled estimate, not a test of the null hypothesis of zero association for that effect. We report these decisions explicitly because an underpowered, non-significant test would be misread as evidence of no bias.
2.9. Deviations from the Registered Protocol
Four deviations are declared here. First, the protocol anticipated pooling only when at least three studies shared a comparable outcome and metric. Several index-by-capacity cells contain three or four studies (Section 3.10), but no cell contains three studies measuring the outcome with a comparable metric, which is defined as the same measured quantity obtained with the same class of instrument (for example, maximal oxygen uptake (VO2max) measured by gas analysis rather than estimated from a field test, or jump height from a force platform or photoelectric system rather than from a tape measure). Cell-level estimates are therefore presented descriptively as an evidence map, and pooled estimates are reported at the index, capacity domain, and overall levels. Second, cluster-robust variance estimation was not prespecified; it was added because the extracted data contained many effects per study, and after an earlier round of peer review the correlated-and-hierarchical-effects model with CR2 adjustment replaced the registered three-level model as the basis of inference, for the reasons given in Section 2.6; the registered model is retained as a sensitivity analysis. Third, two post hoc analyses were added after that round and are labeled as such where reported: the pooling of hypothesis-concordant effects (Section 3.6) and the single-covariate partial correlations in studies with complete matrices (Section 3.9). Fourth, we introduced an eligibility category, retained in the review and in the evidence map but contributing no poolable effect, for studies that measured both exposure and outcome in the same sample but did not publish any statistic linking them. The registered protocol treats the absence of standard deviations as a sensitivity analysis rather than an eligibility criterion, and excluding these studies would have contradicted the registration and erased precisely the empty cells the review set out to document.
3. Results
3.1. Study Selection
The searches returned 132 records, 68 from the Web of Science Core Collection and 64 from the Ibero-American databases and the supplementary sources listed in Section 2.3 (Google Scholar, Scopus, and the Russian-language index eLibrary/RSCI were not searched, a limitation stated in Section 4.8). After removing 11 duplicates, the 121 unique records were distributed by source of retrieval as follows: Web of Science 68, Dialnet 33, SciELO and LILACS/BVS 15 (two of these also indexed in PubMed), Semantic Scholar/Consensus 3, and Crossref 2; the record-level source is given in Supplementary File S3. The 121 records were screened by title and abstract, and 36 were excluded under the criteria stated in Section 2.4 (not finger or palmar dermatoglyphics, no physical ability measured, or ineligible design); the code applied to each excluded record is given in the screening log (Supplementary File S3). Full texts were sought for 85 reports, and 12 could not be retrieved; these are listed, along with the retrieval attempts made, in Supplementary File S3. Four additional records that no search had returned were identified in the retrieved full texts, so eligibility was assessed for 77 unique studies. Fifty-seven were excluded with documented reasons (Table 1; the reason for each report is listed in Supplementary File S3), and 20 were included (Figure 2).
Table 1.
Reasons for exclusion at full-text assessment (n = 57).
Figure 2.
PRISMA 2020 flow diagram of study selection. The 36 records excluded at the title-and-abstract stage did not concern finger or palmar dermatoglyphics, measured no physical ability, or had an ineligible design (Section 2.4); records of uncertain eligibility were carried forward. Exclusion codes E1–E9 applied at full-text assessment are defined in Table 1. Reports assessed for eligibility comprise the 73 retrieved database records and four further reports identified within the retrieved full texts.
Of the 20 included studies, 12 report an estimate of the association between a dermatoglyphic index and a measured physical ability. Nine of these report correlation coefficients and constitute the quantitative synthesis; three, including [20], report only group-difference statistics for categorized variables, which were not converted to r per the rule in Section 2.6 and thus contribute solely to the evidence map. Seven studies measure both constructs within the same sample but do not publish any statistic linking them. One study [37] was classified as borderline; it was retained in the review and the evidence map but excluded from the quantitative synthesis on the basis of outcome considerations (its outcomes are passing, shooting, and dribbling scores in basketball players, which measure sport-specific technical performance rather than motor coordination as defined in Section 2.2), a decision made before assessing its impact on the pooled estimate (Section 3.8).
Table 1 tabulates the reasons for exclusion at full text. The largest category, with 18 studies, measured a dermatoglyphic profile without assessing any physical ability. The second, with 10, comprises excluded designs. A third category, coded separately (E7), contains seven studies that measured no physical ability; they inferred it from the fingerprint itself using the inherited table of equivalences, and presented that inference as a result about their athletes’ capacities; the implications of this design are taken up in Section 4.4.
One duplicate publication was confirmed. The same sample of the Brazilian men’s national volleyball squad (12 senior, 12 junior, and 14 youth players) appears in a 2007 Brazilian journal [38] and again in 2010 in a French journal [39], with no cross-declaration. The second report was an image-only PDF and was identified via optical character recognition. Two further duplication suspicions could not be resolved and are reported in Section 4.8.
3.2. Characteristics of the Included Studies
The nine studies contributing correlations are all cross-sectional and comprise 337 participants and 122 correlations (Table 2). Seven were conducted in Colombia, one in Chile, and one in Brazil; all were published between 2010 and 2025, and five of the nine (contributing 79 of the 122 effects) appeared in 2021 or later. Sample sizes range from six to 130 with a median of 20; only two studies exceed 50 participants, and together they contribute 42 of the 122 effects. Every sample is a convenience sample from a single squad, team, or delegation: footballers (three studies, under-16 to professional), a national rowing squad, a youth volleyball club, a university basketball team, a youth artistic gymnastics team, a six-athlete national military pentathlon squad, and a multi-sport delegation of high-performance athletes. Five samples were male, one female, two mixed, and one did not state sex. Fingerprints were captured with ink following the Cummins and Midlo protocol in five studies and with a digital reader in three; one study did not specify the capture method. Outcomes were measured with linear encoders or force platforms (power and strength), gas-analysis or field-test estimates of VO2max (aerobic endurance), timed sprints and the Illinois test (speed and agility), handgrip dynamometry or one-repetition maximum (strength), and a sit-and-reach test (flexibility); power contributes 59 of the 122 effects, aerobic endurance 25, strength 16, speed 16, agility contributes five, and flexibility contributes one. None of the studies were prospective, none randomized, and none followed participants over time. Full characteristics are provided in Table 2 and the extraction file (Supplementary File S3).
Table 2.
Characteristics of the nine studies contributing extractable effect estimates. The eleven additional studies [20,37,40,41,42,43,44,45,46,47,48] include three that report a non-correlational association statistic not convertible under Section 2.6, seven that measured both constructs but published no linking statistic, and one borderline report [37]; they are described in the extraction file (Supplementary File S3). No study in either group reported an anthropometry-adjusted estimate or the reliability of its dermatoglyphic measurement. The n given for [49] is the sample size used to compute the published correlation matrix; the article reports a total sample of 149 athletes. Age range, sex, the indices reported, and the completeness of the published correlation matrix for each study are given in the extraction file (Supplementary File S3); the studies with complete fingerprint–anthropometry–performance matrices are marked † (the fourth, Gálvez Pardo et al. 2021 [41], contributed anthropometry correlations only and is listed among the studies without a poolable effect) and they are identified in Section 3.9.
Five author groups account for all nine studies. A Bogotá cluster spanning three institutions with recurring shared authorship contributes four studies and 41 of the 122 effects; a Tolima group contributes two studies and 48 effects, close to 40% of the total. This concentration is the reason the author group was modeled as a level in the registered model rather than treated as a covariate.
None of the 20 included studies estimated the dermatoglyph–performance association while adjusting for anthropometry, body composition, biological maturation, or training exposure. Four studies measured anthropometry and dermatoglyphics in the same participants and correlated the two, but none included anthropometry as a covariate in any model with physical ability as the outcome. The registered secondary objective, to quantify attenuation after adjustment, therefore has no adjusted estimate to act on; the indirect approach that the published matrices permit is described in Section 3.9.
3.3. Risk of Bias
All nine studies were judged to be at high overall risk of bias (Figure 3; per-study, per-domain judgments with their justifications in Table S2, Supplementary File S3). Because every study was judged to be high-risk in at least one domain, the overall judgment is high for all nine regardless of the aggregation rule. Two domains drive this judgment. Confounding was rated high in nine of nine studies because no study adjusted its fingerprint–performance estimate for anthropometry, body composition, maturation, or training, although several measured these variables. Measurement of the prognostic factor was rated high in six of nine and moderate in the remaining three because no study reported intra- or inter-rater reliability for its dermatoglyphic measurements or blinding of the person classifying the fingerprints to the participants’ performance results; the three moderate ratings were given where capture and classification were software-assisted, a method for which a concordance study with the traditional reading exists [56]. Outcome measurement was the strongest domain, rated low in seven of nine studies that used linear encoders, force platforms, photoelectric jump sensors, calibrated dynamometers, or laboratory ergospirometry; the two moderate ratings reflect VO2max estimated from a regression equation rather than measured. Attrition was not applicable in any study given the cross-sectional design. Statistical analysis and reporting were rated high in six of nine studies, on grounds documented per study in Table S2 (selective presentation of coefficients from larger matrices, discrepancies between text and tables, or internally inconsistent statistics); three documented cases are described in Section 3.10.
Figure 3.
Risk of bias by QUIPS domain across the nine studies in the quantitative synthesis. Bars give the number of studies judged at low, moderate, or high risk in each domain. The judgment in each domain is a categorical appraisal of the study design and reporting against the QUIPS signaling questions (Section 2.5), not a measured quantity: confounding is high wherever no adjustment for morphology, maturation, or training was made; factor measurement is high wherever the reliability of ridge counting and pattern classification and the blinding of the assessor were not reported; outcome measurement is low wherever an instrumented test was used. Attrition is not applicable to cross-sectional designs. Per-study judgments and their justifications are given in Table S2 (Supplementary File S3).
3.4. Results of Individual Studies
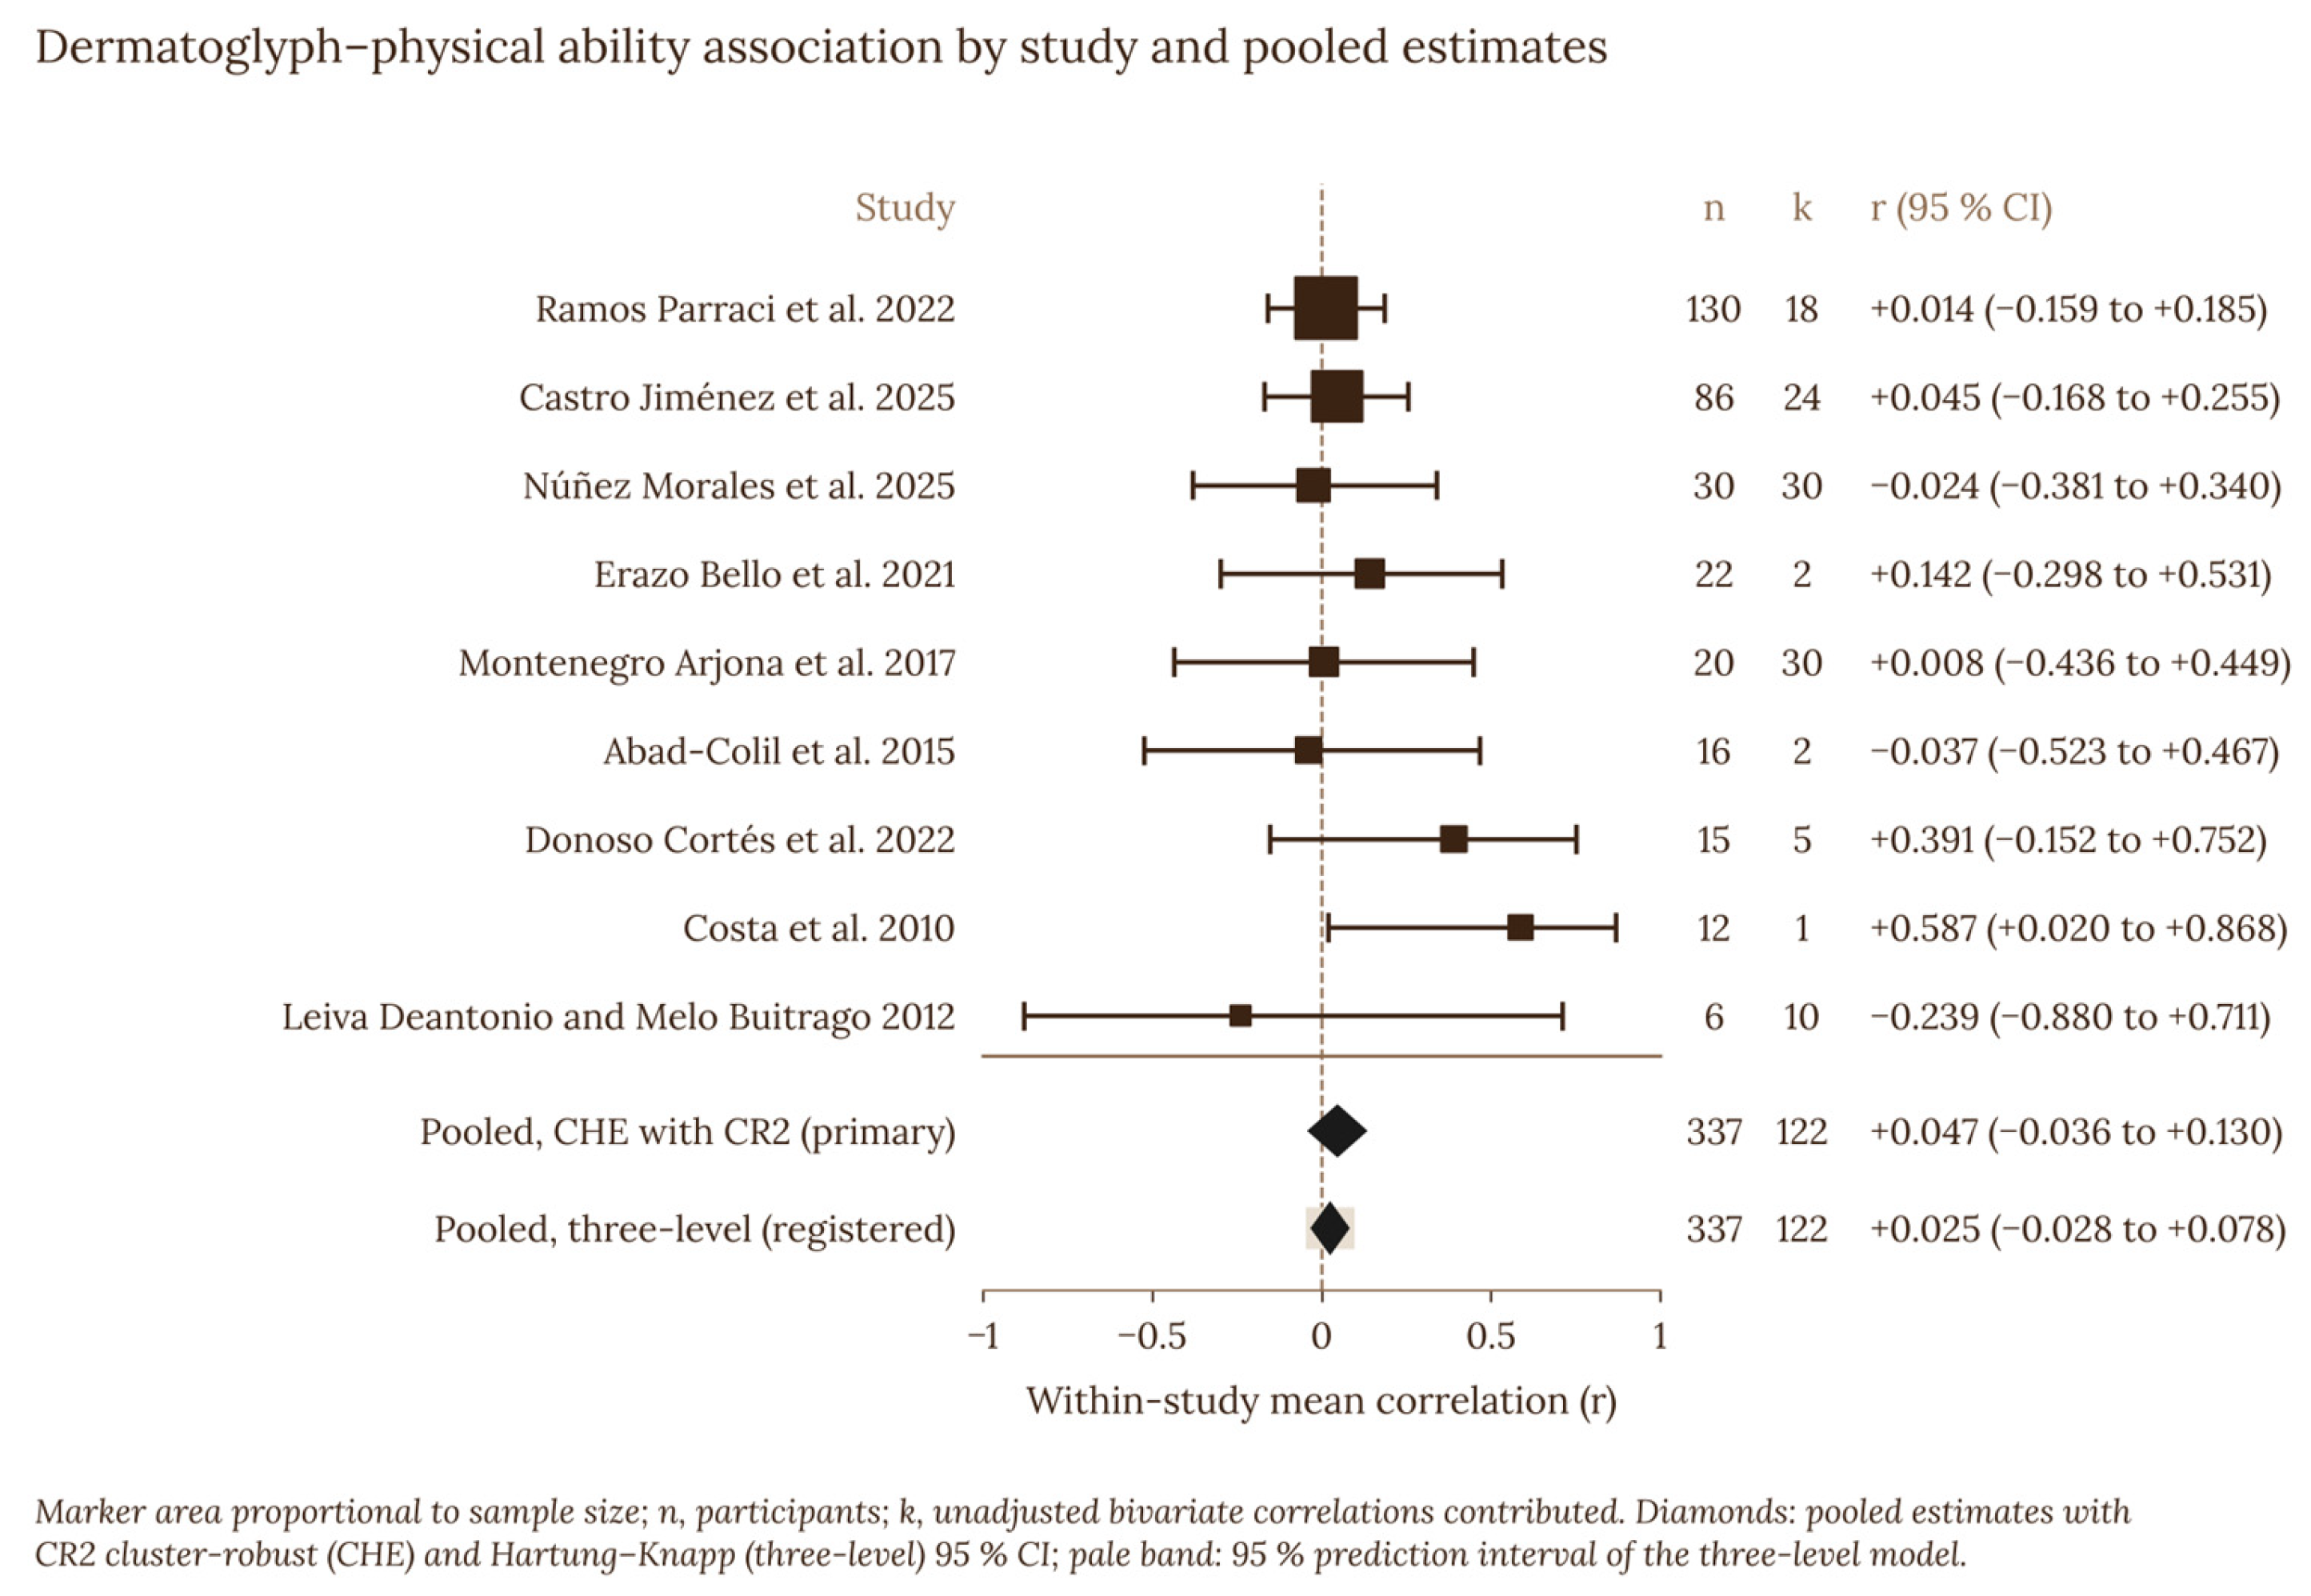
Figure 4 displays the within-study mean of the 122 unadjusted correlations for each study, with the pooled estimates. All coefficients are bivariate correlations between one dermatoglyphic index and one performance test; none derives from a multivariable model, and no predictor other than the index enters any of them. The two studies with more than 80 participants have within-study means of 0.014 and 0.045; the largest coefficients come exclusively from the smallest samples. The military pentathlon study, with six participants, reports correlations of 0.925 and −0.890; with six observations the standard error of the Fisher z is 0.577, so that study carries less than 1% of the weight in the pooled estimate. Across the corpus, the magnitude a study reports and the information it contributes are inversely related. Under the null hypothesis, the expected absolute value of a sample correlation is √(2/(π(n − 1))), about 0.18 at the corpus median n of 20 and 0.36 at n = 6; the observed median |r| across all 122 effects is 0.164.
Figure 4.
Within-study mean association between dermatoglyphic indices and physical ability, and pooled estimates. Each study is labeled on the left as in the reference list, with its numeric estimate on the right; n is the number of participants and k the number of correlations contributed. Within-study intervals were computed from the mean Fisher z using a variance of 1/(n − 3) and describe each study’s precision; marker area is proportional to sample size. The bottom rows show the pooled estimate from the primary correlated-and-hierarchical-effects model with its CR2 cluster-robust 95% confidence interval and from the registered three-level model with its Hartung–Knapp interval (Table 3). The pale band is the 95% prediction interval of the three-level model. Every coefficient is a bivariate, unadjusted correlation; the spread among studies reflects, in the first place, sampling variation in samples of 6 to 130 participants (Section 4.2). Studies, from top to bottom: Ramos Parraci et al. 2022 [49], Castro Jiménez et al. 2025 [50], Núñez Morales et al. 2025 [51], Erazo Bello et al. 2021 [52], Montenegro Arjona et al. 2017 [21], Abad-Colil et al. 2015 [53], Donoso Cortés et al. 2022 [54], Costa et al. 2010 [55], and Leiva Deantonio and Melo Buitrago 2012 [2].
Table 3.
Pooled correlation between quantitative dermatoglyphic indices and objectively measured physical ability under each model (k = 122 effects, 9 studies, 5 author groups, 337 participants). CI, confidence interval (credible interval for the Bayesian model); CHE, correlated-and-hierarchical-effects model; CR2, bias-reduced cluster-robust variance estimator with Satterthwaite degrees of freedom (df); HK, Hartung–Knapp; REML, restricted maximum likelihood; RVE, robust variance estimation with the approximate correlated-effects weights of Hedges et al. [33]. The prediction interval is for the true correlation in a new study (three-level, two-level, and Bayesian models: new study in a new author group; CHE model: new index–test correlation in a new study, which includes the within-study component). The Bayesian row reports the posterior median and the posterior probability that r exceeds zero in place of a p-value.
3.5. Pooled Estimates
Table 3 reports the pooled correlation under every model fitted to the 122 effects. Under the primary correlated-and-hierarchical-effects model with CR2 cluster-robust inference, the pooled correlation was r = 0.047 (95% CI −0.036 to 0.130; Satterthwaite degrees of freedom = 3.2; p = 0.17). The between-study variance was estimated at zero and the within-study variance at ω2 = 0.055 in Fisher z units; the 95% prediction interval for the true correlation of a new index–test pair in a new study was −0.590 to 0.648. The point estimate was insensitive to the assumed within-study sampling correlation (r = 0.041 at ρ = 0.3 and 0.050 at ρ = 0.9, with intervals of similar width). The Satterthwaite degrees of freedom are close to three because the two studies with more than 80 participants carry 66% of the weight.
The registered three-level model gave r = 0.025 (95% CI −0.028 to 0.078; p = 0.347) with a prediction interval of −0.043 to 0.093; both between-level variance components were estimated at or near zero (between-study 0, between-author-group 0.0005 in Fisher z units), so that its standard error of about 0.027 in r units corresponds to the information content of roughly 1400 independent participants, about four times the 337 studied. The two-level model gave r = 0.023 (95% CI −0.018 to 0.065). Cluster-robust estimation with the approximate correlated-effects weights gave r = 0.056 (95% CI −0.018 to 0.131; 8 degrees of freedom; p = 0.12) when clustering by study and r = 0.064 (95% CI −0.162 to 0.283; 4 degrees of freedom; p = 0.48) when clustering by author group. The four-chain Bayesian model (Section 3.7) gave a posterior median of 0.043 (95% credible interval −0.121 to 0.269). No specification produced an interval excluding zero, and no point estimate exceeded 0.07.
3.6. Subgroup and Moderator Analyses
No subgroup provides evidence of an association of useful magnitude (Figure 5; Table 4). The total ridge count yields r = 0.081 under the three-level model (95% CI 0.048 to 0.114) and r = 0.079 under the CHE/CR2 model (95% CI 0.044 to 0.113; 2.1 degrees of freedom; p = 0.009), the only subgroup whose interval excludes zero under either model; its CHE prediction interval (−0.020 to 0.176) includes zero, the estimate is one of ten exploratory subgroup tests, and the coefficient, taken at face value, explains 0.6% of the variance in performance. The three pattern-frequency subgroups have opposite signs (arches 0.133, loops 0.171, whorls −0.221 under the three-level model) with intervals that include zero and prediction intervals that span most of the admissible range; the exploratory moderator test for the index was significant (Q = 25.3 on 4 degrees of freedom, p < 0.001), which reflects the opposite polarity of whorl frequency relative to the ridge-count indices rather than a useful association for any index: under the common-variance moderator model, every index-specific mean lies between −0.079 and 0.083. The pooled correlations of the five physical-ability domains did not differ (Q = 2.26, p = 0.69); the estimates range from 0.019 for aerobic endurance to 0.145 for strength, and the domains that appear to show some association in Figure 5 (strength and agility with a single study) have the widest intervals, all of which include zero. Speed rests on two studies and agility on one, so no robust estimate is available for them.
Figure 5.
Pooled estimate overall and by prespecified subgroup under the registered three-level model. Each subgroup is named on the left and its numeric estimate is given on the right; k is the number of effects and St. the number of studies contributing. Squares are pooled r with Hartung–Knapp 95% confidence intervals; the pale band is the 95% prediction interval. Every confidence interval includes zero except that of the total ridge count; the exploratory test of differences among the five physical-ability domains was not significant (Q = 2.26 on 4 degrees of freedom, p = 0.69), so the visual differences among domains do not indicate that the association differs by domain. The intervals assume conditional independence of effects within studies and are anti-conservative (Section 2.6); robust estimates for the subgroups with at least three studies are given in Table 4. Agility rests on a single study and is shown with its full interval from −1 to 1.
Table 4.
Pooled correlation by prespecified subgroup under the registered three-level model (Hartung–Knapp intervals, HK) and, where at least three studies contribute, under the correlated-and-hierarchical-effects model with CR2 cluster-robust inference (CHE/CR2). Three-level intervals assume conditional independence of effects within studies and are anti-conservative (Section 2.6); when I2 = 0.0%, the prediction interval coincides with the CI because the between-level variances are estimated at zero. All p-values are exploratory: ten subgroups were examined without multiplicity correction. The subgroups by physical ability sum to 121 effects; the single flexibility effect is not assigned to any subgroup. Exploratory moderator tests from the three-level mixed model: physical-ability domain, Q = 2.26 on 4 degrees of freedom, p = 0.69; dermatoglyphic index, Q = 25.3 on 4 degrees of freedom, p < 0.001 (see text).
Post hoc analysis of hypothesis-concordant effects (not registered; Section 2.6). Twenty-one effects from five studies fall in the cells for which the equivalence table predicts a positive oriented correlation: arches × strength (7 effects), loops × speed (3), total ridge count × aerobic endurance (6), and delta index × aerobic endurance (5). Pooled with the CHE/CR2 model, these effects gave r = 0.056 (95% CI −0.211 to 0.315; Satterthwaite degrees of freedom = 2.5; p = 0.53). The point estimate is as close to zero as the omnibus estimate.
3.7. Heterogeneity and Bayesian Sensitivity Analysis
Under the three-level model, overall heterogeneity was low: I2 = 2.1%, with between-study variance estimated at zero and between-author-group variance at 0.0005 in Fisher z units. This contradicts the protocol’s expectation of very high heterogeneity, based on a meta-analysis of dermatoglyphics in pediatric oral disease [11]. Two qualifications apply. Restricted maximum likelihood readily returns boundary estimates of zero with nine clusters, and the three-level model does not estimate a within-study variance component, so dispersion among effects within a study (from −0.89 to 0.93 within the pentathlon study) is attributed entirely to sampling error. The CHE model does estimate that component: ω2 = 0.055 in Fisher z units against a between-study variance of zero, so that 72% of the total variance is attributable to dispersion among the indices and tests within studies and none to differences between studies. Heterogeneity above 90% in the loop and whorl subgroups is produced by the same two studies with six and twelve participants.
The four-chain Bayesian three-level model converged: R-hat was 1.001 or lower, and bulk effective sample sizes exceeded 4900 for every parameter in the six prior specifications of the three-level structure; in the correlated-sampling-error variant, R-hat was 1.002 or lower, and bulk effective sample sizes exceeded 1400 (Table S3). Under the registered priors, the posterior median was r = 0.043 (95% credible interval −0.121 to 0.269; Monte Carlo standard error 0.001), with a 95% prediction interval of −0.386 to 0.515; the posterior medians of the between-study and between-group standard deviations were 0.082 and 0.071 in Fisher z units. The prediction interval is wider than its frequentist counterpart because the half-Cauchy priors keep the between-level standard deviations away from zero, whereas restricted maximum likelihood estimates them at zero; with nine studies in five groups, the data cannot overrule those priors. The posterior probabilities that the true correlation is smaller than 0.10 in absolute value, smaller than 0.20, and larger than 0.30 were 0.74, 0.93, and 0.018. Across the five alternative prior specifications, the posterior median ranged from 0.040 to 0.046, the lower and upper bounds of the credible interval from −0.136 to −0.082 and from 0.220 to 0.294, and the posterior probability that r exceeds 0.30 from 0.006 to 0.023 (Table S3); with sampling errors within a study correlated at ρ = 0.6 and a within-study component, the posterior median was 0.055 (−0.076 to 0.199). The Bayesian results are therefore not sensitive to the priors within the range examined and agree with the frequentist models (Figure 6c).
Figure 6.
Distribution of the 122 effect estimates and the Bayesian pooled estimate. (a) Funnel plot of the 122 effects, shown for description only: the vertical axis is the standard error of each Fisher z, so effects from one study share a single standard error and align horizontally, and the plot cannot display small-study effects across studies [36]. The dashed line is the pooled Fisher z of the three-level model, and the shaded funnel shows its pseudo-95% limits (±1.96 standard errors); a point outside the funnel differs from the pooled value by more than two standard errors, indicating dispersion rather than a test of significance for that effect. (b) Distribution of the 122 observed correlations, with the median marked. (c) Posterior median of the pooled correlation from the four-chain Bayesian three-level model with its 95% credible interval (thick line) and 95% prediction interval (thin line); the shaded band marks the practical null, |r| < 0.10; posterior median 0.043, p(|r| < 0.10) = 0.74.
3.8. Sensitivity Analyses
The pooled point estimate remained stable across all analytical decisions tested (Table 5). Leave-one-study-out analysis moved the CHE/CR2 estimate between 0.031 and 0.064 and the three-level estimate between 0.012 and 0.060. Retaining one effect per study gave r = 0.072 (95% CI −0.059 to 0.201), and one effect per author group gave r = 0.060 (95% CI −0.103 to 0.220); these two analyses make no assumptions about within-study dependence but discard 113 and 117 of the 122 effects, and their intervals are correspondingly the widest. No specification of the overall effect produced an interval excluding zero, and none other than the addition of the borderline report produced a point estimate reaching 0.10. Adding that report, whose three coefficients (0.81 to 0.92) exceed every other coefficient in the corpus, moved the three-level estimate to 0.321 (95% CI −0.299 to 0.750) and raised its I2 from 2.1% to 93.4%, and moved the CHE/CR2 estimate to 0.234 (95% CI −0.112 to 0.529); neither interval excludes zero. The implications of this sensitivity are discussed in Section 4.1. The values 0.234 and 0.321 therefore belong to this specific sensitivity analysis; the range of 0.02 to 0.07 given elsewhere refers to the models fitted to the full registered corpus.
Table 5.
Sensitivity analyses. Each row gives the pooled correlation under the primary correlated-and-hierarchical-effects model with CR2 inference (CHE/CR2) and under the registered three-level model (3L). The one-effect-per-cluster analyses are random-effects models (restricted maximum likelihood, REML; Hartung–Knapp) of independent effects and are shown in the 3L columns; the borderline report [37] contributes three correlations (0.81, 0.86, 0.92; n = 60) between thumb ridge count and basketball technical skills.
3.9. The Morphological-Confounding Triangle
Because no study reported an adjusted estimate, the registered secondary objective could not be addressed as planned. It could be approached indirectly through the complete correlation matrices of the four studies that measured fingerprints, body morphology, and performance in the same participants (Figure 7; Table 6).
Figure 7.
Magnitude of the correlations at the three vertices of the morphological-confounding triangle in the studies that report all three relationships. (a) Mean absolute correlation at each vertex and (b) its distribution, computed within the four studies listed in Table 6 (median, interquartile box, whiskers to 1.5 × the interquartile range, and every coefficient as a point). The panels are descriptive. No inferential test of the difference between vertices is reported because the coefficients at each vertex are dependent (several come from the same participants), the vertices rest on two to four studies, and the anthropometry × physical ability vertex contains no coefficient below about |r| = 0.27 because the source articles published only selected coefficients at that vertex (Section 3.9); a test treating the points as independent observations would be invalid.
Table 6.
Magnitudes of the absolute correlation at the three vertices of the confounding triangle, within the four studies reporting all three relationships: Castro Jiménez et al. 2025 [50], Núñez Morales et al. 2025 [51], Erazo Bello et al. 2021 [52], and Gálvez Pardo et al. 2021 [41]; these studies are marked in Table 2. k is the number of correlations; the number of coefficients per vertex is unequal because the published matrices do not report every pairwise coefficient, and each vertex lists the studies that contribute to it. The precision-weighted mean is the inverse-variance (n − 3)-weighted mean of the Fisher z of |r|, back-transformed. No interval is given: the coefficients are dependent within studies, and each vertex rests on two to four studies, too few for a cluster bootstrap.
The mean absolute correlation of anthropometry with physical ability (0.447; precision-weighted 0.447) is about 2.6 times that of dermatoglyphics with physical ability (0.172; precision-weighted 0.150), and fingerprints correlate more closely with anthropometry (0.233; precision-weighted 0.221) than with performance. Precision weighting does not change the ordering. Three cautions apply. The means are means of absolute correlations, which are inflated in small samples, and are reported without intervals because each vertex rests on two to four dependent clusters. The vertices are not represented equally: 56, 33, and 11 coefficients from three, three, and two studies, respectively. And the anthropometry × ability vertex contains no coefficient below about |r| = 0.27 (Figure 7b) because the two contributing articles [51,52] published only the anthropometry × performance coefficients they selected, so the contrast between vertices is probably inflated by the coefficients available for extraction. The comparison is descriptive: it shows how strongly each pair of constructs covaries in these samples, not whether the fingerprint–performance correlations arise from morphology.
Two studies illustrate the configuration. Among under-20 footballers in Bogotá [52], the delta index and total ridge count correlate with endomorphy (−0.43 and −0.48), and VO2max correlates with body mass index (−0.57), body mass (−0.51), fat mass (−0.50), and ectomorphy (0.52); the correlations between the dermatoglyphic indices and VO2max are 0.16 and 0.12. Among artistic gymnasts in Tolima [51], height and body mass correlate with countermovement jump height (0.386 and 0.359) and with squat jump height (0.405 and 0.507), whereas the ridge-count indices correlate with the same jump variables at −0.22 to 0.09, in the same table and among the same thirty participants. A third observation comes from the only study in the corpus with objective biological maturation: in 136 boys aged 10 to 14 assessed by wrist and hand radiography, basic physical qualities increased with advancing pubertal stage, while no differences in dermatoglyphics or somatotype were found between maturation stages [40].
First-order partial correlations (post hoc; Section 2.6) were computable for the 37 index–test–covariate triplets in the two studies whose matrices contain all three coefficients [51,52]. After adjustment for one anthropometric variable at a time, the mean absolute fingerprint–performance correlation changed from 0.190 to 0.173 and the median from 0.160 to 0.114. These summary changes do not reflect uniform attenuation: the absolute coefficient decreased in 20 triplets and increased in 17, and no coefficient changed by more than 0.11, less than half a standard error for samples of 22 and 30 participants. In the Bogotá footballers [52], the delta index–VO2max correlation changed from 0.16 to −0.04 to 0.13 depending on the covariate, and the ridge count–VO2max correlation changed from 0.12 to −0.13 to 0.06. In the gymnasts [51], the loop and whorl frequencies, whose correlations with jump height are about ±0.4, were unchanged by adjustment for height or body mass, which those two variables do not predict in that sample. Two limits apply to this evidence. A confounded association is still an association: the product of the two indirect arms of the triangle (0.233 × 0.447 ≈ 0.10) is the fingerprint–performance correlation that a pure confounding path would generate, and it lies within every interval reported in Section 3.5 and Section 3.8. And the partial correlations are single-covariate adjustments in two samples; they are the closest approximation to the registered secondary objective that the published data permit, not a substitute for an adjusted analysis. Like the triangle, they describe the published coefficients and cannot show that the fingerprint–performance associations are due to morphology.
3.10. Evidence Map and Reporting Bias
The evidence map (Figure 8) shows how the field has distributed its effort. Occupied cells are based on one to four studies, and four of the thirty cells shown are empty. Motor coordination and anaerobic endurance, two of the capacities the equivalence table claims to predict, have no published coefficients and are omitted from the map. Flexibility contributes a single coefficient. Power accounts for 59 of the 122 effects, nearly half, and comes from four studies, two of which share an author group. Because no cell contained three studies with a comparable metric, as defined in Section 2.9, cell-level estimates are presented as descriptions of the map, following SWiM guidance [13], rather than as synthesis estimates.
Figure 8.
Evidence map: precision-weighted correlation per cell of dermatoglyphic index by capacity domain. The number printed in each cell is a correlation coefficient (the inverse-variance, (n − 3)-weighted mean of the Fisher z values in the cell, back-transformed to r), not a p-value; values such as 0.05 to 0.08 are correlations close to zero, and no cell-level significance test was performed because no cell contains three studies with a comparable metric (Section 2.9). k is the number of effects and e the number of studies in the cell; hatched cells contain no data. Motor coordination and anaerobic endurance have no column because no study published a coefficient for either; flexibility rests on a single coefficient from one study of twelve participants.
Egger regression was not performed for the reason given in Section 2.8. In the funnel plot (Figure 6a), precise effects cluster around zero, and dispersion increases as precision declines; because effects from one study share a single standard error, the plot cannot display small-study effects across studies [36] and no inference regarding publication bias is drawn from it. The plot could be drawn at all only because four studies published complete correlation matrices; studies that publish a single chosen coefficient appear in the funnel with the effect they chose to show.
Within-study reporting discrepancies were documented in three studies. In the gymnastics study, the coefficient that the abstract presents as the principal finding, r = 0.485 with p = 0.007, is a correlation between two dermatoglyphic indices, total ridge count and whorls, not between a dermatoglyphic index and power; the same article states in its text that two of the jump variables show no correlation with dermatoglyphic characteristics [51]. In the futsal study, the results text reports significant correlations between anthropometry and dermatoglyphics, the table shows none, and the discussion states that no statistically significant relationship existed [41]. In the neuromuscular profile study, two rows of the published correlation table showed coefficients that were arithmetically inconsistent with their accompanying p-values for the stated sample size; those two rows were excluded from extraction, and the three internally consistent rows were retained [49]. In each case, the discrepancy is between the abstract or text and the tabulated results. Of the 93 effect estimates with a published p-value, 30 (32.3%) reached p < 0.05; the median absolute correlation across all 122 effects was 0.164.
3.11. Certainty of the Evidence
Certainty was rated using GRADE, adapted for prognostic-factor questions [19]. The body of observational evidence begins at high certainty and was rated down by two levels for risk of bias, since all nine studies were at high risk in the confounding domain and six of nine in exposure measurement; by one level for indirectness, since the exposure is measured without any published reliability and the outcome set is a heterogeneous collection of surrogates in convenience samples of single squads; by one level for imprecision, since the dependency-aware intervals (Section 3.5 and Section 3.8) include zero and the one-effect-per-cluster intervals extend to 0.20 and beyond; and by one level for suspected publication and reporting bias, given documented selective within-study reporting and too few studies to test formally. Inconsistency was rated as not serious for the overall estimate, because between-study variance was estimated at zero under both the three-level and the correlated-and-hierarchical-effects models and the dispersion is within studies, and as serious for strength (I2 = 52%). Certainty is very low for every outcome (Table 7).
Table 7.
GRADE certainty ratings, adapted to prognostic-factor questions. Bodies of observational evidence begin at high certainty. Pooled estimates are from the three-level model for comparability across outcomes; imprecision is rated on the dependency-aware intervals (Section 3.5 and Section 3.8), not on the three-level interval shown.
4. Discussion
4.1. Principal Findings
This is, to our knowledge, the first meta-analysis of the association between fingerprint dermatoglyphics and objectively measured physical ability. Across 122 effect estimates from nine studies and 337 participants, the pooled correlation was close to zero under every model fitted to the full registered corpus (point estimates from 0.02 to 0.07), no interval for the overall effect excluded zero, and no analysis of that corpus approached the benchmark of practical relevance. The finding is an absence of evidence for an association of practical magnitude in a body of evidence that, because of its size and risk of bias, cannot exclude small associations: the primary interval reaches 0.13, the one-effect-per-cluster intervals reach 0.20 and 0.22, and the Bayesian prediction interval for a new study reaches 0.5. The only subgroup whose interval excludes zero, the total ridge count, has a pooled correlation of 0.08, which would explain less than 1% of the variance in performance.
One sensitivity analysis deserves comment. A single borderline report [37], with three coefficients between 0.81 and 0.92 for the correlation of thumb ridge count with basketball passing, shooting, and dribbling in sixty players, moves the CHE/CR2 estimate to 0.23 (95% CI −0.11 to 0.53) and the three-level estimate to 0.32 (95% CI −0.30 to 0.75), and raises the three-level heterogeneity to 93%; both intervals still include zero, and these two values describe this sensitivity analysis only. We excluded it on the registered outcome criterion. Passing, shooting, and dribbling scores measure technical performance specific to basketball; they depend on practice history, tactical knowledge, and familiarity with the ball and are therefore not measures of motor coordination as defined in Section 2.2, which refers to a general capacity assessed with tests that do not require the practice of a particular sport. The decision was made before its effect on the pooled estimate was computed, and we report the counterfactual so that readers can weigh it; coefficients of that size, far above those of every other study and from a venue whose peer-review procedure we could not confirm (Section 4.8), would in any case require independent replication before changing the conclusion.
Alongside the quantitative result sits a structural one. None of the 20 included studies has tested the field’s central claim against its most obvious rival explanation. The registered secondary objective was to quantify the extent to which the dermatoglyph–performance association is attenuated after adjustment for morphology, maturation, and training. No study has made such an adjustment; the objective could be approached only indirectly, through the confounding triangle and through single-covariate partial correlations in the two studies with complete matrices, and that indirect, descriptive evidence neither revealed an association masked by morphology nor showed that the observed associations are due to morphology (Section 3.9).
4.2. Why a Field Can See an Effect That a Meta-Analysis Cannot
The individual studies in this literature routinely report correlations of 0.5, 0.7, and higher, and the studies reporting the largest coefficients are systematically the smallest. Several mechanisms can produce that pattern, and the data of this review do not allow us to establish which of them operates. Sampling variability is the most parsimonious: with n = 6 the expected absolute correlation under the null is about 0.36, and coefficients beyond 0.8 arise readily when the true correlation is zero, and at the corpus median n of 20 the null expectation of about 0.18 matches the observed median |r| of 0.164. Low statistical power also inflates the magnitude of effects that reach significance and lowers the probability that a significant result reflects a true effect [57], and correlation estimates do not stabilize until sample sizes reach roughly 150 to 250 [58]. Selective reporting of coefficients from larger matrices, which we documented in three studies (Section 3.10), and differences in population, measurement, and index definition between small and large studies are alternative or additional explanations that the corpus cannot distinguish from sampling variability. Whatever the mechanism, the consequence is the literature that is internally consistent in a misleading way: each study finds “significant” associations and cites its predecessors as corroboration, and the accumulated citations create the appearance of a replicated finding. Precision weighting dissolves this appearance: once the imprecise studies carry the weight their information warrants, the studies do not disagree, and the dispersion that remains is within studies rather than between them.
4.3. What the Genetics Now Says
The mechanistic case for sports dermatoglyphics has always been inferential rather than molecular: fingerprints are heritable, physical ability is heritable; therefore, fingerprints mark physical ability. Two heritable traits imply nothing about their shared genetic architecture, and the genomic evidence now available points elsewhere: the 43 fingerprint-associated loci lie near genes enriched for limb-development pathways, not for muscle contraction, energy metabolism, or neural drive, and fingerprint patterns are genetically correlated with hand proportions [7]. This genomic reframing is an argument we make from [7], not a finding of the review.
Our descriptive findings are consistent with that argument but do not test it. Across the four studies that measured all three constructs, fingerprints correlated more strongly with body morphology (mean |r| = 0.23) than with performance (0.17), while morphology correlated more strongly with performance than either (0.45), with the cautions regarding extraction and weighting stated in Section 3.9, and single-covariate adjustment changed the mean absolute fingerprint–performance correlation only from 0.190 to 0.173, lowering 20 of the 37 absolute coefficients and raising 17. One hypothesis consistent with this configuration is that any information a fingerprint index carries about performance is information about limb and body proportions that anthropometry measures directly; under that hypothesis, anthropometry is the more informative measurement. The review did not test this hypothesis, which would require an adjusted analysis in a study that measures all three constructs with adequate power, and the data are equally compatible with the simpler account that fingerprints carry no information about performance at all. The heritability premise warrants the same scrutiny: twin data do not support uniform heritability across indices [8,9], so even if fingerprints were predictive of performance, the indices would not be interchangeable, yet the applied literature treats them as if they were.
4.4. Circularity and the Reliability Vacuum
Seven of the 57 studies excluded at the full-text stage did not measure any physical ability. They inferred it from the fingerprint using the equivalence table and reported the inference as a finding about their participants. The design creates a closed loop that renders the hypothesis unfalsifiable: a study that assigns “coordination” to an athlete because she has whorls and then concludes that whorls indicate coordination has generated no evidence. These studies appear in indexed journals.
Related to this is the reliability vacuum. Not one study in the corpus reported intra- or inter-rater agreement for its dermatoglyphic classification, and not one blinded the classifier to performance. Ridge counting and pattern classification are human judgments made on images of variable quality, and the field has an instrument-comparison study available to it [56] that it has not used to characterize measurement error. An exposure with unknown reliability attenuates observed associations toward the null, so the true association could be somewhat larger than estimated here; it also means that no study in this literature can currently distinguish a null association from a well-measured small one.
4.5. Relation to Previous Reviews
The two prior systematic reviews reached broadly favorable conclusions about the utility of dermatoglyphics [1,6]. Several differences account for the divergence from the present conclusions. The first is method: neither review pooled effect sizes, assessed reporting bias, evaluated certainty, or examined confounding, and counting studies that report significant associations yields a different answer than weighting effect estimates by precision, particularly in the literature where the smallest samples yield the significant coefficients. The second is scope and period: the Americas review covered 2010 to 2019 and described profiles rather than associations, and the strength review covered six studies; five of the nine studies pooled here, contributing 79 of the 122 effects and including the two largest samples, were published in 2021 or later and were unavailable to either review. The third is appraisal: the strength review applied the Jadad scale, designed for randomized trials, which cannot register the confounding and measurement problems that drive the risk-of-bias judgments here. The divergence is therefore not a disagreement about individual studies but a difference in which studies were available and in how their evidence was weighed. Meta-analyses of dermatoglyphics in adjacent domains are consistent with the present picture: one found no overall difference in pattern distribution by caries status [10], and another reported heterogeneity of 78–98% across small studies [11].
4.6. Implications for Practice
The current evidence does not support the use of fingerprint dermatoglyphics to orient children toward particular sports, to construct athlete profiles that inform training prescriptions, or to inform selection or de-selection decisions. The overall pooled association is not distinguishable from zero in any specification, including the sensitivity analysis that adds the borderline report; no analysis of the registered corpus estimates an association of the magnitude at which use for orientation would begin to be defensible, and the Bayesian analysis assigns a posterior probability of about 0.02 to that magnitude. Because the evidence is so uncertain, this is a statement about the absence of support rather than a demonstration that no association exists, and it could change if adequately powered studies with reliable measurement and adjustment for morphology find otherwise. Until then, the burden of evidence lies with the practice. Talent identification is a selection decision, and selection decisions based on unvalidated predictors misallocate opportunity in ways that are opaque to the child and the family [59]; where fingerprints, anthropometry, and performance were measured together, anthropometry correlated more strongly with performance than fingerprints did (Section 3.9; descriptive comparison, very low certainty).
4.7. Implications for Research
If the field wishes to test its hypothesis rather than assume it, three requirements follow. First, any future study must report the reliability of its dermatoglyphic measurements and blind the classifier to the outcome; without this, the literature cannot distinguish between the absence of association and measurement failure. Second, the association must be estimated with adjustment for anthropometry, body composition, and biological maturation, which, in pediatric samples, requires an objective maturity indicator rather than chronological age; the one study in this corpus with radiographic bone age found that physical qualities advanced with puberty, whereas dermatoglyphics did not differ between maturation stages [40]. Third, sample sizes must be commensurate with the effects being sought: detecting r = 0.20 with 80% power at a two-sided α of 0.05 requires about 194 participants, which exceeds the sample of every study in this meta-analysis and is more than half of their combined sample. A sensitivity analysis including effects converted from group-difference statistics would accommodate the largest samples in the literature (for example, [20], n = 367, and [60], n = 1002) but requires the categorical cross-tabulations that the reports do not publish in full. A more productive reframing may also be available: if fingerprints and limb morphology share developmental genes [7], fingerprint patterns may be informative about limb and hand proportions, and whether they index aspects of morphology relevant to performance in specific sports is a different, weaker, and testable claim. It does not license current practice.
4.8. Strengths and Limitations
The review has four strengths. The protocol was prospectively registered, the full document was deposited, and the four deviations were disclosed. The search treated Ibero-American databases as mandatory rather than supplementary, recovering most of the eligible literature; a review restricted to major English-language indexes would have missed most of this field. The dependence among effects was addressed with a correlated-and-hierarchical-effects model and small-sample-corrected cluster-robust estimation, cross-checked with the registered three-level model, one-effect-per-cluster analyses, and a Bayesian model whose convergence was verified across chains and whose conclusions were insensitive to the priors; in the registered corpus, the point estimate did not move outside 0.02 to 0.07 under any of them, and only the sensitivity analysis that added the borderline report [37] moved it beyond that range (Section 3.8). And the extraction is traceable: every one of the 122 coefficients is recorded with the table or figure it came from, and the internal arithmetic consistency of each published coefficient and its p-value was checked against the stated sample size.
The limitations are substantial. Screening and extraction were performed by a single reviewer, with a second reviewer involved only in the four recused records and the borderline decision (Section 2.4), so no agreement statistic is available, and single-reviewer error in selection or transcription cannot be excluded; the screening and extraction files are published in full so that any reader can audit every decision, but this does not substitute for independent duplicate assessment, and with only 20 eligible studies the omission of even one would matter. The evidence base is small: nine studies, 337 participants, and a median sample of 20. The primary model rests on nine clusters, two of which carry most of the weight, and robust estimation could not be applied informatively to subgroups with fewer than three studies. The overall estimate averages indices with opposite polarity, so it is an omnibus summary rather than a test of the index-specific hypothesis, and the post hoc hypothesis-concordant analysis rests on 21 effects from five studies. The search did not include Google Scholar, Scopus, or the Russian-language index eLibrary/RSCI, although the practice under review is also established in Eastern Europe. One record brought to our attention during the earlier round of peer review does not appear among the included studies: a cross-sectional study of dermatoglyphics and abdominal endurance in 1002 girls aged 10 to 16 [60], published on a platform with post-publication peer review and, at the time of writing, not approved by its reviewers. It was returned by none of the searches listed in Section 2.3 and was first noted as a citation inside an unidentifiable document that was itself excluded after the search had closed; it reports chi-square associations by digit and no correlation coefficient, so under Section 2.6 it would have entered the evidence map without contributing a poolable effect, and it shares an author (G.G.-C.) with the review team, so the recusal rule would have applied. Three studies with a non-correlational association statistic, including [20] with 367 participants, were not converted to r, which discarded the largest available samples. Twelve reports sought could not be retrieved, and four of these (three twin studies of the heritability of physical fitness and one report on skeletal maturation [61], apparently from the cohort of [40]) are precisely those most informative for the confounding question. Egger regression was not performed because the protocol conditioned it on ten studies, and the funnel plot of dependent effects is descriptive only. The confounding triangle is constructed from correlations reported within studies, not from adjusted models, and the post hoc partial correlations adjust for one covariate at a time in two samples of 22 and 30 participants; both analyses are indirect and descriptive: they are compatible with the confounding hypothesis, but they do not test it and cannot show that any fingerprint–performance association is due to morphology. The borderline report [37] appeared in a library-science venue whose peer-review procedure could not be confirmed; it was excluded from the synthesis on outcome grounds independently of that question. Two further suspicions of duplicate publication (Section 3.1) could not be resolved from the published reports: two descriptions of the same Colombian track-cycling squad, both excluded at full text, and the Linhares 2009 [40] and Vidal-Linhares et al. 2010 [61] reports on what appears to be the same cohort, the second of which was not retrieved; none of the four contributed an effect. Certainty is very low for every outcome.
5. Conclusions
Quantitative fingerprint dermatoglyphic indices show no evidence of an association of practical magnitude with objectively measured physical ability. The pooled correlation is 0.047 (95% CI −0.036 to 0.130) under the correlated-and-hierarchical-effects model that is the basis of inference, between 0.02 and 0.07 under every other model fitted to the full registered corpus, and no interval for the overall effect excludes zero; a sensitivity analysis that added one borderline report with an ineligible outcome raised the estimate to 0.23 (0.32 under the three-level model), with intervals that still included zero. The Bayesian posterior places about 2% of its mass above the benchmark at which the marker would begin to be defensible for orientation, and the evidence cannot exclude small associations. No study in this literature has estimated the association with adjustment for body morphology, maturation, or training exposure; in the four studies that measured all three constructs in the same participants, anthropometry showed, descriptively, about 2.6 times the mean absolute correlation with performance that fingerprints showed, and single-covariate adjustment for anthropometry changed the mean absolute fingerprint–performance correlation only from 0.19 to 0.17, with coefficients decreasing in 20 and increasing in 17 of 37 comparisons. This indirect and descriptive evidence is compatible with the published associations being a noisy reflection of body morphology rather than a genetic signal of physical capacity, but it does not show that the associations are due to morphology. The current use of dermatoglyphics to orient or select young athletes is not supported by the literature; in the samples that measured both, direct body measurements correlated more strongly with performance.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/sports14110486/s1.
Author Contributions
Conceptualization, A.R.-J.; methodology, A.R.-J.; formal analysis, A.R.-J.; investigation (screening, data extraction and risk-of-bias assessment), A.R.-J. and J.G.-A.; resources (domain expertise on the Ibero-American corpus, subject to the recusal rule in Section 2.4), E.I.A.-M. and G.G.-C.; data curation, A.R.-J. and J.G.-A.; writing—original draft preparation, O.A.S.-T. and A.R.-J.; writing—review and editing, A.R.-J., G.G.-C., J.G.-A., E.I.A.-M., E.M.A.-M. and O.A.S.-T.; supervision and project administration, A.R.-J. (guarantor). All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable; this review used only published aggregate data.
Informed Consent Statement
Not applicable.
Data Availability Statement
The screening workbooks (title-and-abstract screening of the 121 records with source, recusal flag, and decision code; full-text assessment of the 77 reports with inclusion category, exclusion code, and non-retrieved and duplicate lists), the extraction tables (Supplementary File S3: included studies, all 122 effect estimates with their table or figure of origin and sign convention, subgroup and sensitivity results, the confounding-triangle coefficients, and the Bayesian output), the risk-of-bias judgments with their justifications (Table S2), the analysis scripts, and the raw numerical output are provided as Supplementary Materials and will be deposited in Zenodo, with the DOI inserted at proof stage. The analysis code implements every estimator reported here directly in Python 3 (NumPy, SciPy, ArviZ) and is provided in full.
Conflicts of Interest
G.G.-C. co-authored primary studies eligible for this review, co-authored one of the two previous systematic reviews in this field, and belongs to one of the author groups whose non-independence the review models. This was declared in the registered protocol together with the safeguards applied: he took no part in eligibility assessment, data extraction, or risk-of-bias assessment for any record he co-authored; he is not the guarantor; the author-group sensitivity analysis was applied to his group on identical terms; and the assessment of how this review differs from the previous one he co-authored was made by the guarantor. The other authors declare no competing interests.
References
- Fernández-Aljoe, R.; García-Fernández, D.A.; Gastélum-Cuadras, G. La dermatoglifia deportiva en América en la última década: Una revisión sistemática. Retos 2020, 38, 831–837. [Google Scholar] [CrossRef] [Scilit]
- Leiva Deantonio, J.H.; Melo Buitrago, P.J. Dermatoglifia dactilar, somatotipo y consumo de oxígeno en atletas de pentatlón militar de la Escuela Militar de Cadetes “General José María Córdova”. Rev. Cient. Gen. José María Córdova 2012, 10, 305–318. [Google Scholar] [CrossRef] [Scilit]
- Kyselicová, K.; Dukonyová, D.; Belica, I.; Ballová, D.S.; Jankovičová, V.; Ostatníková, D. Fingerprint patterns in relation to an altered neurodevelopment in patients with autism spectrum disorder. Dev. Psychobiol. 2023, 65, e22432. [Google Scholar] [CrossRef] [Scilit]
- Nousbeck, J.; Burger, B.; Fuchs-Telem, D.; Pavlovsky, M.; Fenig, S.; Sarig, O.; Itin, P.; Sprecher, E. A mutation in a skin-specific isoform of SMARCAD1 causes autosomal-dominant adermatoglyphia. Am. J. Hum. Genet. 2011, 89, 302–307. [Google Scholar] [CrossRef] [Scilit]
- Riley, R.D.; Hayden, J.A.; Steyerberg, E.W.; Moons, K.G.M.; Abrams, K.; Kyzas, P.A.; Malats, N.; Briggs, A.; Schroter, S.; Altman, D.G.; et al. Prognosis Research Strategy (PROGRESS) 2: Prognostic factor research. PLoS Med. 2013, 10, e1001380. [Google Scholar] [CrossRef] [Scilit]
- Herrera Romero, R.L.; Castro Jiménez, L.E. Revisión sistemática entre dermatoglifia dactilar y fuerza en el deporte a nivel mundial. Rev. Cienc. Act. Fís. 2022, 23, 1–12. [Google Scholar] [CrossRef] [Scilit]
- Li, J.; Glover, J.D.; Zhang, H.; Peng, M.; Tan, J.; Mallick, C.B.; Hou, D.; Yang, Y.; Wu, S.; Liu, Y.; et al. Limb development genes underlie variation in human fingerprint patterns. Cell 2022, 185, 95–112.e18. [Google Scholar] [CrossRef] [Scilit]
- Machado, J.F.; Fernandes, P.R.; Roquetti, R.W.; Fernandes Filho, J. Digital dermatoglyphic heritability differences as evidenced by a female twin study. Twin Res. Hum. Genet. 2010, 13, 482–489. [Google Scholar] [CrossRef] [Scilit]
- Temaj, G.; Škarić-Jurić, T.; Butković, A.; Behluli, E.; Zajc Petranović, M.; Moder, A. Three patterns of inheritance of quantitative dermatoglyphic traits: Kosovo Albanian twin study. Twin Res. Hum. Genet. 2021, 24, 371–376. [Google Scholar] [CrossRef] [Scilit]
- Wang, H.; Yan, J.; Ouyang, W.; Xu, X.; Lan, C.; Ouyang, S.; Sun, D. The correlation between dental caries and dermatoglyphics: A systematic review and meta-analysis. J. Clin. Pediatr. Dent. 2024, 48, 45–58. [Google Scholar] [CrossRef] [Scilit]
- Jain, C.; Uddin, A.; Sharma, N.; Verma, S.; Pandey, A.; Mandava, P.; Singaraju, G.S. Associations between dermatoglyphic patterns and oral diseases in children: A systematic review and meta-analysis. Cureus 2025, 17, e95455. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Campbell, M.; McKenzie, J.E.; Sowden, A.; Katikireddi, S.V.; Brennan, S.E.; Ellis, S.; Hartmann-Boyce, J.; Ryan, R.; Shepperd, S.; Thomas, J.; et al. Synthesis without meta-analysis (SWiM) in systematic reviews: Reporting guideline. BMJ 2020, 368, l6890. [Google Scholar] [CrossRef] [Scilit]
- Cummins, H.; Midlo, C. Finger Prints, Palms and Soles: An Introduction to Dermatoglyphics; Blakiston: Philadelphia, PA, USA, 1943. [Google Scholar]
- Hayden, J.A.; van der Windt, D.A.; Cartwright, J.L.; Côté, P.; Bombardier, C. Assessing bias in studies of prognostic factors. Ann. Intern. Med. 2013, 158, 280–286. [Google Scholar] [CrossRef] [Scilit]
- Riley, R.D.; Moons, K.G.M.; Snell, K.I.E.; Ensor, J.; Hooft, L.; Altman, D.G.; Hayden, J.; Collins, G.S.; Debray, T.P.A. A guide to systematic review and meta-analysis of prognostic factor studies. BMJ 2019, 364, k4597. [Google Scholar] [CrossRef] [Scilit]
- Grooten, W.J.A.; Tseli, E.; Äng, B.O.; Boersma, K.; Stålnacke, B.-M.; Gerdle, B.; Enthoven, P. Elaborating on the assessment of the risk of bias in prognostic studies in pain rehabilitation using QUIPS—Aspects of interrater agreement. Diagn. Progn. Res. 2019, 3, 5. [Google Scholar] [CrossRef] [Scilit]
- Higgins, J.P.T.; Morgan, R.L.; Rooney, A.A.; Taylor, K.W.; Thayer, K.A.; Silva, R.A.; Lemeris, C.; Akl, E.A.; Bateson, T.F.; Berkman, N.D.; et al. A tool to assess risk of bias in non-randomized follow-up studies of exposure effects (ROBINS-E). Environ. Int. 2024, 186, 108602. [Google Scholar] [CrossRef] [Scilit]
- Foroutan, F.; Guyatt, G.; Zuk, V.; Vandvik, P.O.; Alba, A.C.; Mustafa, R.; Vernooij, R.; Arevalo-Rodriguez, I.; Munn, Z.; Roshanov, P.; et al. GRADE Guidelines 28: Use of GRADE for the assessment of evidence about prognostic factors: Rating certainty in identification of groups of patients with different absolute risks. J. Clin. Epidemiol. 2020, 121, 62–70. [Google Scholar] [CrossRef] [Scilit]
- Cruz, I.E.S.; Bim, M.A.; Rigo, V.; Cardoso, A.; Pedrozo, S.C.; Grigollo, L.R.; Zavorski, E.B.; Jesus, J.A.; Nodari Júnior, R.J. Relaciones entre características dermatoglíficas y fuerza manual en hombres. Lect. Educ. Fís. Deport. 2023, 28, 123–138. [Google Scholar] [CrossRef] [Scilit]
- Montenegro Arjona, O.A.; Rodríguez Arrieta, A.N.; Petro Soto, J.L. Perfil dermatoglífico y condición física de jugadores adolescentes de futbol. Educ. Fís. Cienc. 2017, 19, e038. [Google Scholar] [CrossRef] [Scilit][Green Version]
- Cohen, J. A power primer. Psychol. Bull. 1992, 112, 155–159. [Google Scholar] [CrossRef]
- Hopkins, W.G.; Marshall, S.W.; Batterham, A.M.; Hanin, J. Progressive statistics for studies in sports medicine and exercise science. Med. Sci. Sports Exerc. 2009, 41, 3–13. [Google Scholar] [CrossRef] [Scilit]
- Funder, D.C.; Ozer, D.J. Evaluating effect size in psychological research: Sense and nonsense. Adv. Methods Pract. Psychol. Sci. 2019, 2, 156–168, Correction in Adv. Methods Pract. Psychol. Sci. 2020, 3, 509. [Google Scholar] [CrossRef] [Scilit]
- Dunlap, W.P. Generalizing the common language effect size indicator to bivariate normal correlations. Psychol. Bull. 1994, 116, 509–511. [Google Scholar] [CrossRef]
- Pustejovsky, J.E.; Tipton, E. Meta-analysis with robust variance estimation: Expanding the range of working models. Prev. Sci. 2022, 23, 425–438. [Google Scholar] [CrossRef] [Scilit]
- Tipton, E. Small sample adjustments for robust variance estimation with meta-regression. Psychol. Methods 2015, 20, 375–393. [Google Scholar] [CrossRef] [Scilit]
- Pustejovsky, J.E.; Tipton, E. Small-sample methods for cluster-robust variance estimation and hypothesis testing in fixed effects models. J. Bus. Econ. Stat. 2018, 36, 672–683, Correction in J. Bus. Econ. Stat. 2023, 41, 650–652. [Google Scholar] [CrossRef] [Scilit]
- Cheung, M.W.-L. Modeling dependent effect sizes with three-level meta-analyses: A structural equation modeling approach. Psychol. Methods 2014, 19, 211–229. [Google Scholar] [CrossRef] [Scilit]
- IntHout, J.; Ioannidis, J.P.A.; Borm, G.F. The Hartung-Knapp-Sidik-Jonkman method for random effects meta-analysis is straightforward and considerably outperforms the standard DerSimonian-Laird method. BMC Med. Res. Methodol. 2014, 14, 25. [Google Scholar] [CrossRef] [Scilit]
- IntHout, J.; Ioannidis, J.P.A.; Rovers, M.M.; Goeman, J.J. Plea for routinely presenting prediction intervals in meta-analysis. BMJ Open 2016, 6, e010247. [Google Scholar] [CrossRef] [Scilit]
- Van den Noortgate, W.; López-López, J.A.; Marín-Martínez, F.; Sánchez-Meca, J. Three-level meta-analysis of dependent effect sizes. Behav. Res. Methods 2013, 45, 576–594. [Google Scholar] [CrossRef] [Scilit]
- Hedges, L.V.; Tipton, E.; Johnson, M.C. Robust variance estimation in meta-regression with dependent effect size estimates. Res. Synth. Methods 2010, 1, 39–65, Erratum in Res. Synth. Methods 2010, 1, 164–165. [Google Scholar] [CrossRef] [Scilit]
- Gelman, A. Prior distributions for variance parameters in hierarchical models. Bayesian Anal. 2006, 1, 515–534. [Google Scholar] [CrossRef] [Scilit]
- Vehtari, A.; Gelman, A.; Simpson, D.; Carpenter, B.; Bürkner, P.-C. Rank-normalization, folding, and localization: An improved for assessing convergence of MCMC. Bayesian Anal. 2021, 16, 667–718. [Google Scholar] [CrossRef] [Scilit]
- Rodgers, M.A.; Pustejovsky, J.E. Evaluating meta-analytic methods to detect selective reporting in the presence of dependent effect sizes. Psychol. Methods 2021, 26, 141–160. [Google Scholar] [CrossRef] [Scilit]
- Joseph, R.; Swathy, K.K.; Philip, N.; Varghese, B.G. Dermatoglyphics and athletic talent: Analyzing thumb fingerprint ridge counts in junior basketball players. Libr. Prog. Int. 2024, 44, 16780–16788. [Google Scholar]
- Zary, J.C.F.; Fernandes Filho, J. Identificação do perfil dermatoglífico e somatotípico dos atletas de voleibol masculino adulto, juvenil e infanto-juvenil, de alto rendimento no Brasil. Rev. Bras. Ciênc. Mov. 2007, 15, 53–60. [Google Scholar]
- Zary, J.C.; Reis, V.M.; Rouboa, A.; Silva, A.J.; Fernandes, P.R.; Fernandes Filho, J. The somatotype and dermatoglyphic profiles of adult, junior and juvenile male Brazilian top-level volleyball players. Sci. Sports 2010, 25, 146–152. [Google Scholar] [CrossRef] [Scilit]
- Linhares, R.V.; Matta, M.O.; Lima, J.R.P.; Dantas, P.M.S.; Costa, M.B.; Fernandes Filho, J. Efeitos da maturação sexual na composição corporal, nos dermatóglifos, no somatótipo e nas qualidades físicas básicas de adolescentes. Arq. Bras. Endocrinol. Metabol. 2009, 53, 47–54. [Google Scholar] [CrossRef] [Scilit]
- Gálvez Pardo, A.Y.; Cortés García, A.D.; González Reina, D.F.; Castro Jiménez, L.E.; Arguello Gutiérrez, Y.P.; Melo Buitrago, P.J. Dermatoglifía y su relación con el perfil morfo-funcional en un club de fútbol sala masculino profesional de Bogotá. Sport TK 2021, 10, 76–90. [Google Scholar] [CrossRef] [Scilit]
- De Sousa Luna, A.L.; Linhares, R.V.; Costa e Silva, G.V.; Fernandes Filho, J. Antropometría, coordinación motora, dermatoglifia y el proceso de alfabetización de los niños. Rev. Investig. Cuerpo Cult. Mov. 2021, 11, 149–168. [Google Scholar]
- Montoya Monroy, J.S.; Castro Jiménez, L.E.; Melo Buitrago, P.J.; Argüello Gutiérrez, Y.P. Dermatoglifia dactilar y su relación con el consumo máximo de oxígeno en integrantes del equipo de voleibol femenino de la Universidad Santo Tomás. Mov. Cient. 2019, 13, 23–30. [Google Scholar] [CrossRef] [Scilit]
- Fonseca, C.L.T.; Dantas, P.M.S.; Fernandes, P.R.; Fernandes Filho, J. Perfil dermatoglífico, somatotípico e da força explosiva de atletas da seleção brasileira de voleibol feminino. Fit. Perf. J. 2008, 7, 35–40. [Google Scholar] [CrossRef] [Scilit]
- Hernández Chaparro, C.A.; Naranjo Orjuela, R.A. Determinación del perfil genotípico y fenotípico en jugadoras bogotanas del Club Gol Star. Rev. Digit. Act. Fís. Deporte 2016, 2, 22–36. [Google Scholar] [CrossRef] [Scilit]
- Sánchez Rodríguez, D.A.; Rodríguez Buitrago, A. Perfil de las características dermatoglifias dactilares, de composición corporal y del nivel de fuerza explosiva de atletas de semifondo. Rev. Digit. Act. Fís. Deporte 2017, 3, 5–15. [Google Scholar] [CrossRef] [Scilit]
- Restrepo Pardo, C.A.; Avella, R.E. Caracterización de la composición corporal, el perfil dermatoglífico, el consumo máximo de oxígeno (VO2 máx.) y la fuerza prensil en la selección Bogotá de triatlón. Rev. Digit. Act. Fís. Deporte 2016, 2, 5. [Google Scholar] [CrossRef] [Scilit]
- Santos, L.C.; Dantas, P.M.S.; Fernandes Filho, J. Características genotípicas e fenotípicas em atletas velocistas. Motricidade 2008, 4, 49–56. [Google Scholar] [CrossRef] [Scilit]
- Ramos Parraci, C.A.; Patiño-Palma, B.E.; Wheeler-Botero, C.A. Marcadores dermatoglíficos y su relación con el perfil neuromuscular en deportistas colombianos de alto rendimiento. Retos 2022, 46, 597–603. [Google Scholar] [CrossRef] [Scilit]
- Castro Jiménez, L.E.; Argüello Gutiérrez, Y.P.; Melo Buitrago, P.J.; Sánchez Rojas, I.A. Perfil dermatoglífico y funcional en futbolistas profesionales y en formación de la ciudad de Bogotá, Colombia. Rev. Iberoam. Cienc. Act. Fís. Deporte 2025, 14, 325–336. [Google Scholar] [CrossRef] [Scilit]
- Núñez Morales, V.E.; Sandoval Cifuentes, A.A.; Villarreal Ángeles, M.A. Análisis correlacional del perfil dermatoglífico y la potencia del equipo gimnasia artística femenino departamento del Tolima en Colombia. Retos 2025, 70, 870–881. [Google Scholar] [CrossRef] [Scilit]
- Erazo Bello, J.S.; Gálvez Pardo, A.Y.; Castro Jiménez, L.E.; Arguello Gutiérrez, Y.P.; Melo Buitrago, P.J. Composición corporal, dermatoglifia y resistencia aeróbica en futbolistas bogotanos categoría sub 20. MHSalud 2021, 19, 1–12. [Google Scholar] [CrossRef] [Scilit]
- Abad-Colil, A.; Hernández-Mosqueira, C.; Fernandes-Filho, J. Dermatoglifia, fuerza máxima y rendimiento ergométrico en seleccionados chilenos de remo. Rev. Horiz. Cienc. Act. Fís. 2015, 6, 7–13. [Google Scholar]
- Donoso Cortés, W.; Castro Jiménez, L.; Argüello Gutiérrez, Y.; Gálvez Pardo, A.; Melo Buitrago, P. Dermatoglifia y fuerza muscular en deportistas de baloncesto universitario. Rev. Cienc. Act. Fís. UCM 2022, 23, 1–9. [Google Scholar] [CrossRef] [Scilit]
- Costa, C.L.A.; Silva, H.G.; Silva, H.M.; Capistrano, R.D.S. Perfil dermatoglífico e qualidades físicas básicas de jovens atletas de voleibol. Conexões 2010, 8, 1–15. [Google Scholar] [CrossRef] [Scilit][Green Version]
- Nodari-Júnior, R.J.; Heberle, A.; Ferreira-Emygdio, R.; Knackfuss, M.I. Dermatoglyphics: Correlation between software and traditional method in kineanthropometric application. Rev. Andal. Med. Deporte 2014, 7, 60–65. [Google Scholar] [CrossRef] [Scilit]
- Button, K.S.; Ioannidis, J.P.A.; Mokrysz, C.; Nosek, B.A.; Flint, J.; Robinson, E.S.J.; Munafò, M.R. Power failure: Why small sample size undermines the reliability of neuroscience. Nat. Rev. Neurosci. 2013, 14, 365–376, Erratum in Nat. Rev. Neurosci. 2013, 14, 451. [Google Scholar] [CrossRef] [Scilit]
- Schönbrodt, F.D.; Perugini, M. At what sample size do correlations stabilize? J. Res. Pers. 2013, 47, 609–612, Correction in J. Res. Pers. 2018, 74, 194. [Google Scholar] [CrossRef] [Scilit]
- Bergkamp, T.L.G.; Niessen, A.S.M.; den Hartigh, R.J.R.; Frencken, W.G.P.; Meijer, R.R. Methodological issues in soccer talent identification research. Sports Med. 2019, 49, 1317–1335. [Google Scholar] [CrossRef] [Scilit]
- Souza, R.; Alberti, A.; Cuadras, G.G.; de Souza Vale, R.G.; Zanoni, E.M.; Zavorski, E.B.; De Jesus, J.A.; Soares, B.H.; Pertille, F.; Fin, G.; et al. Dermatoglyphics and abdominal resistance in female children and adolescents: A cross-sectional study [version 1; peer review: 1 approved with reservations, 1 not approved]. F1000Research 2021, 10, 945. [Google Scholar] [CrossRef] [Scilit]
- Vidal-Linhares, R.; De Oliveira-Matta, M.; Perrout-Lima, J.; Barros-Costa, M.; Fernandes-Filho, J. A relação entre as características dermatoglíficas e a maturação óssea de adolescentes. Rev. Salud Pública 2010, 12, 929–937. [Google Scholar] [CrossRef] [Scilit][Green Version]
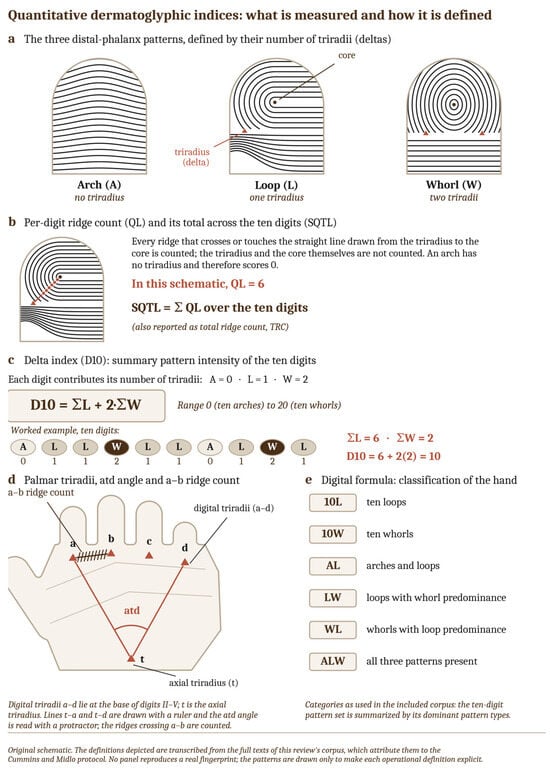

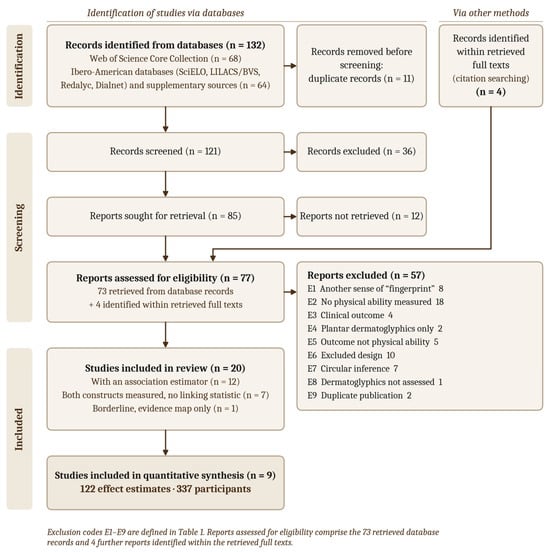
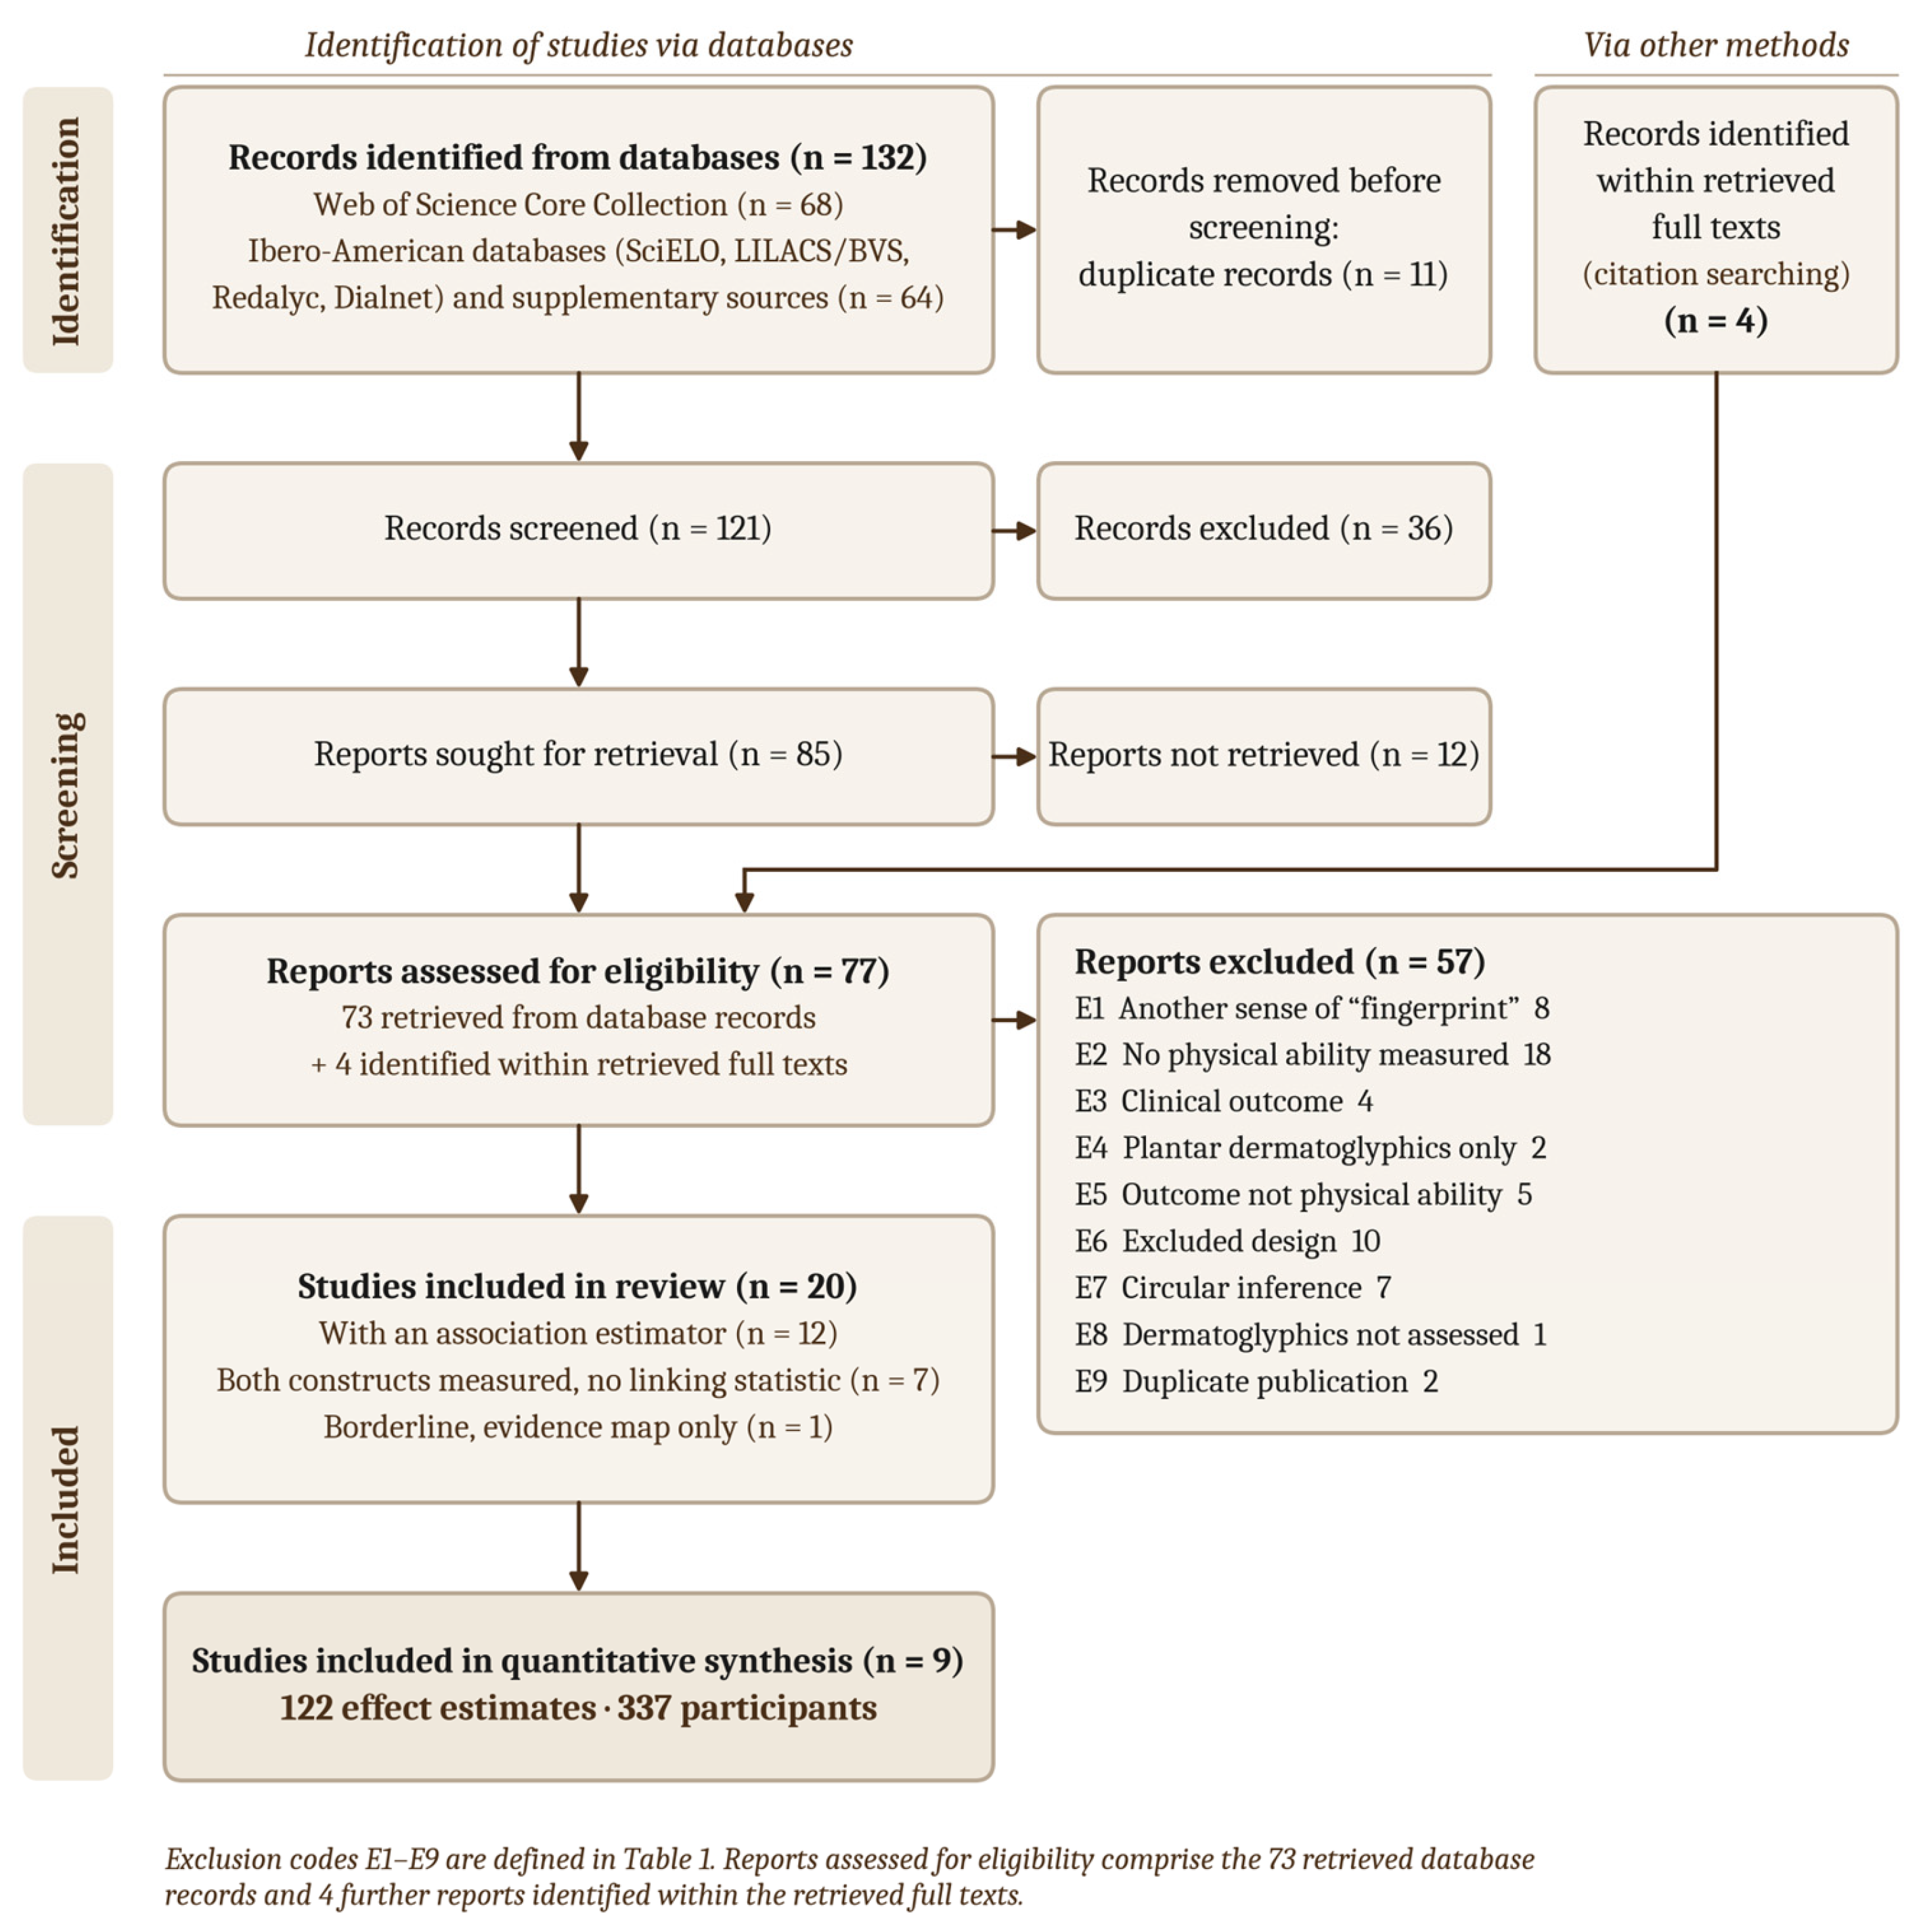
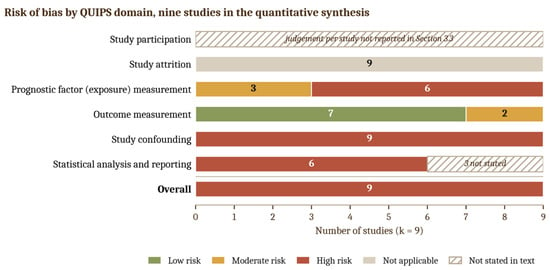
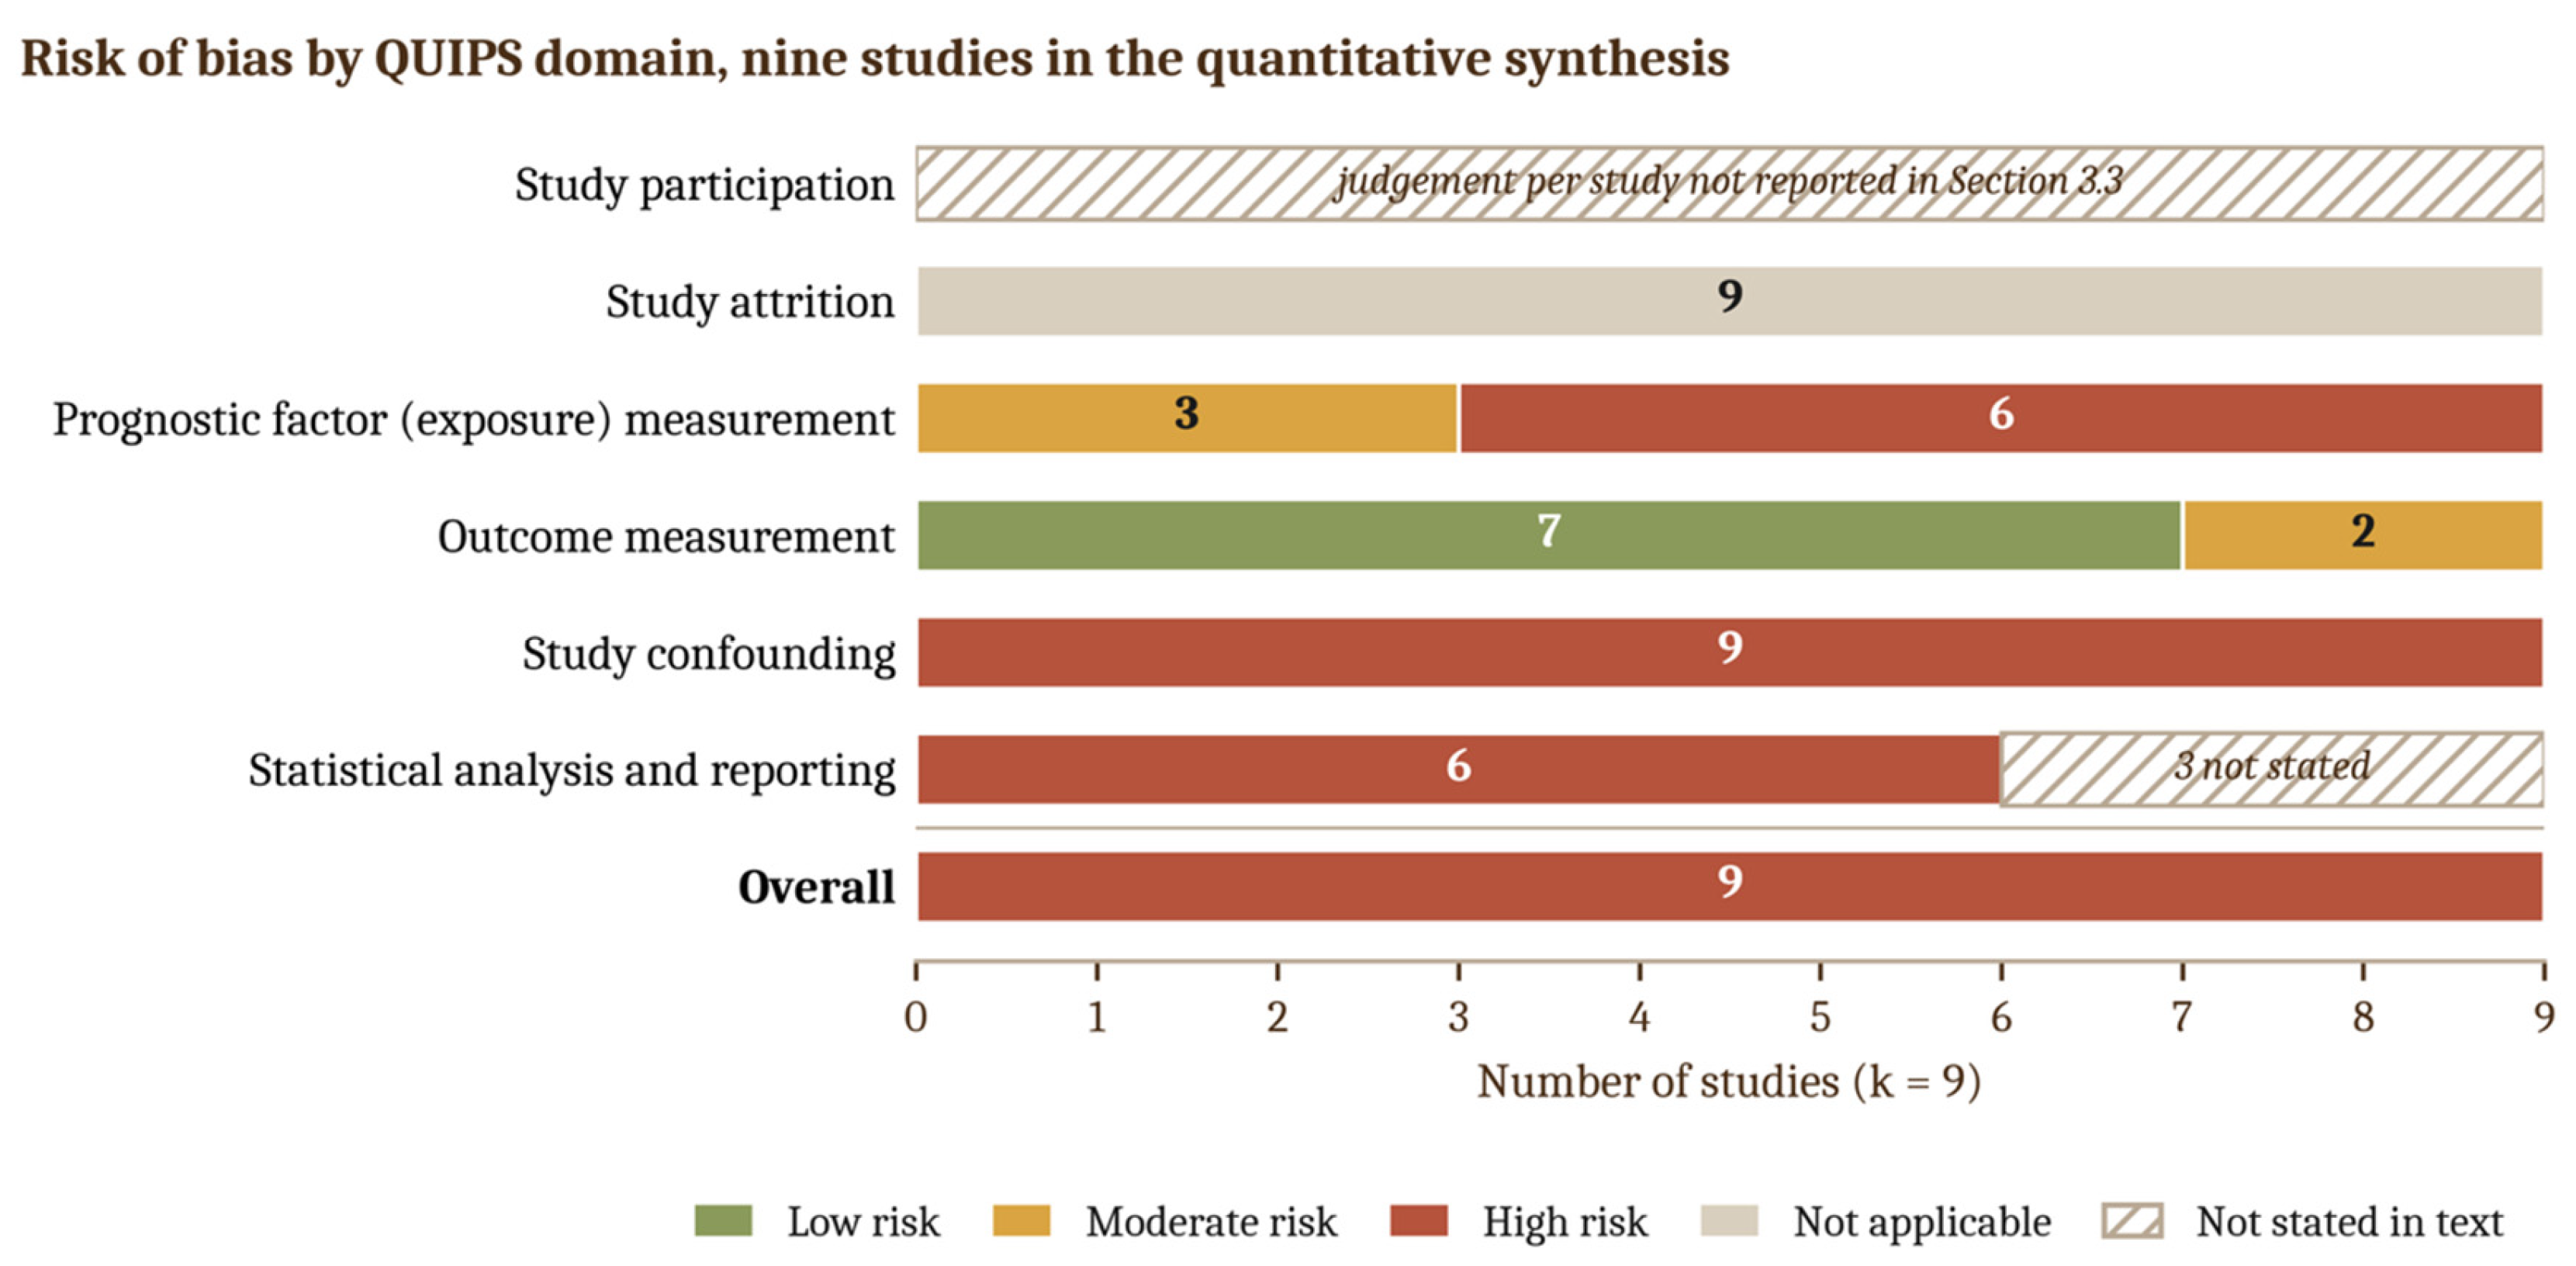
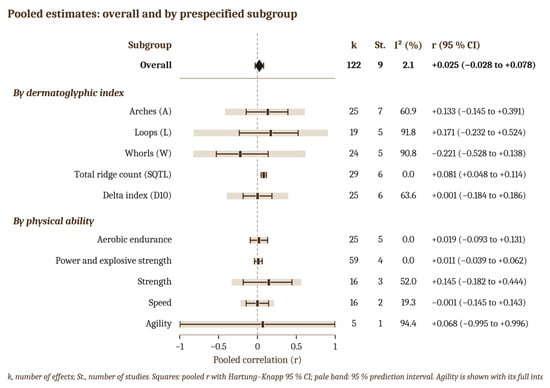
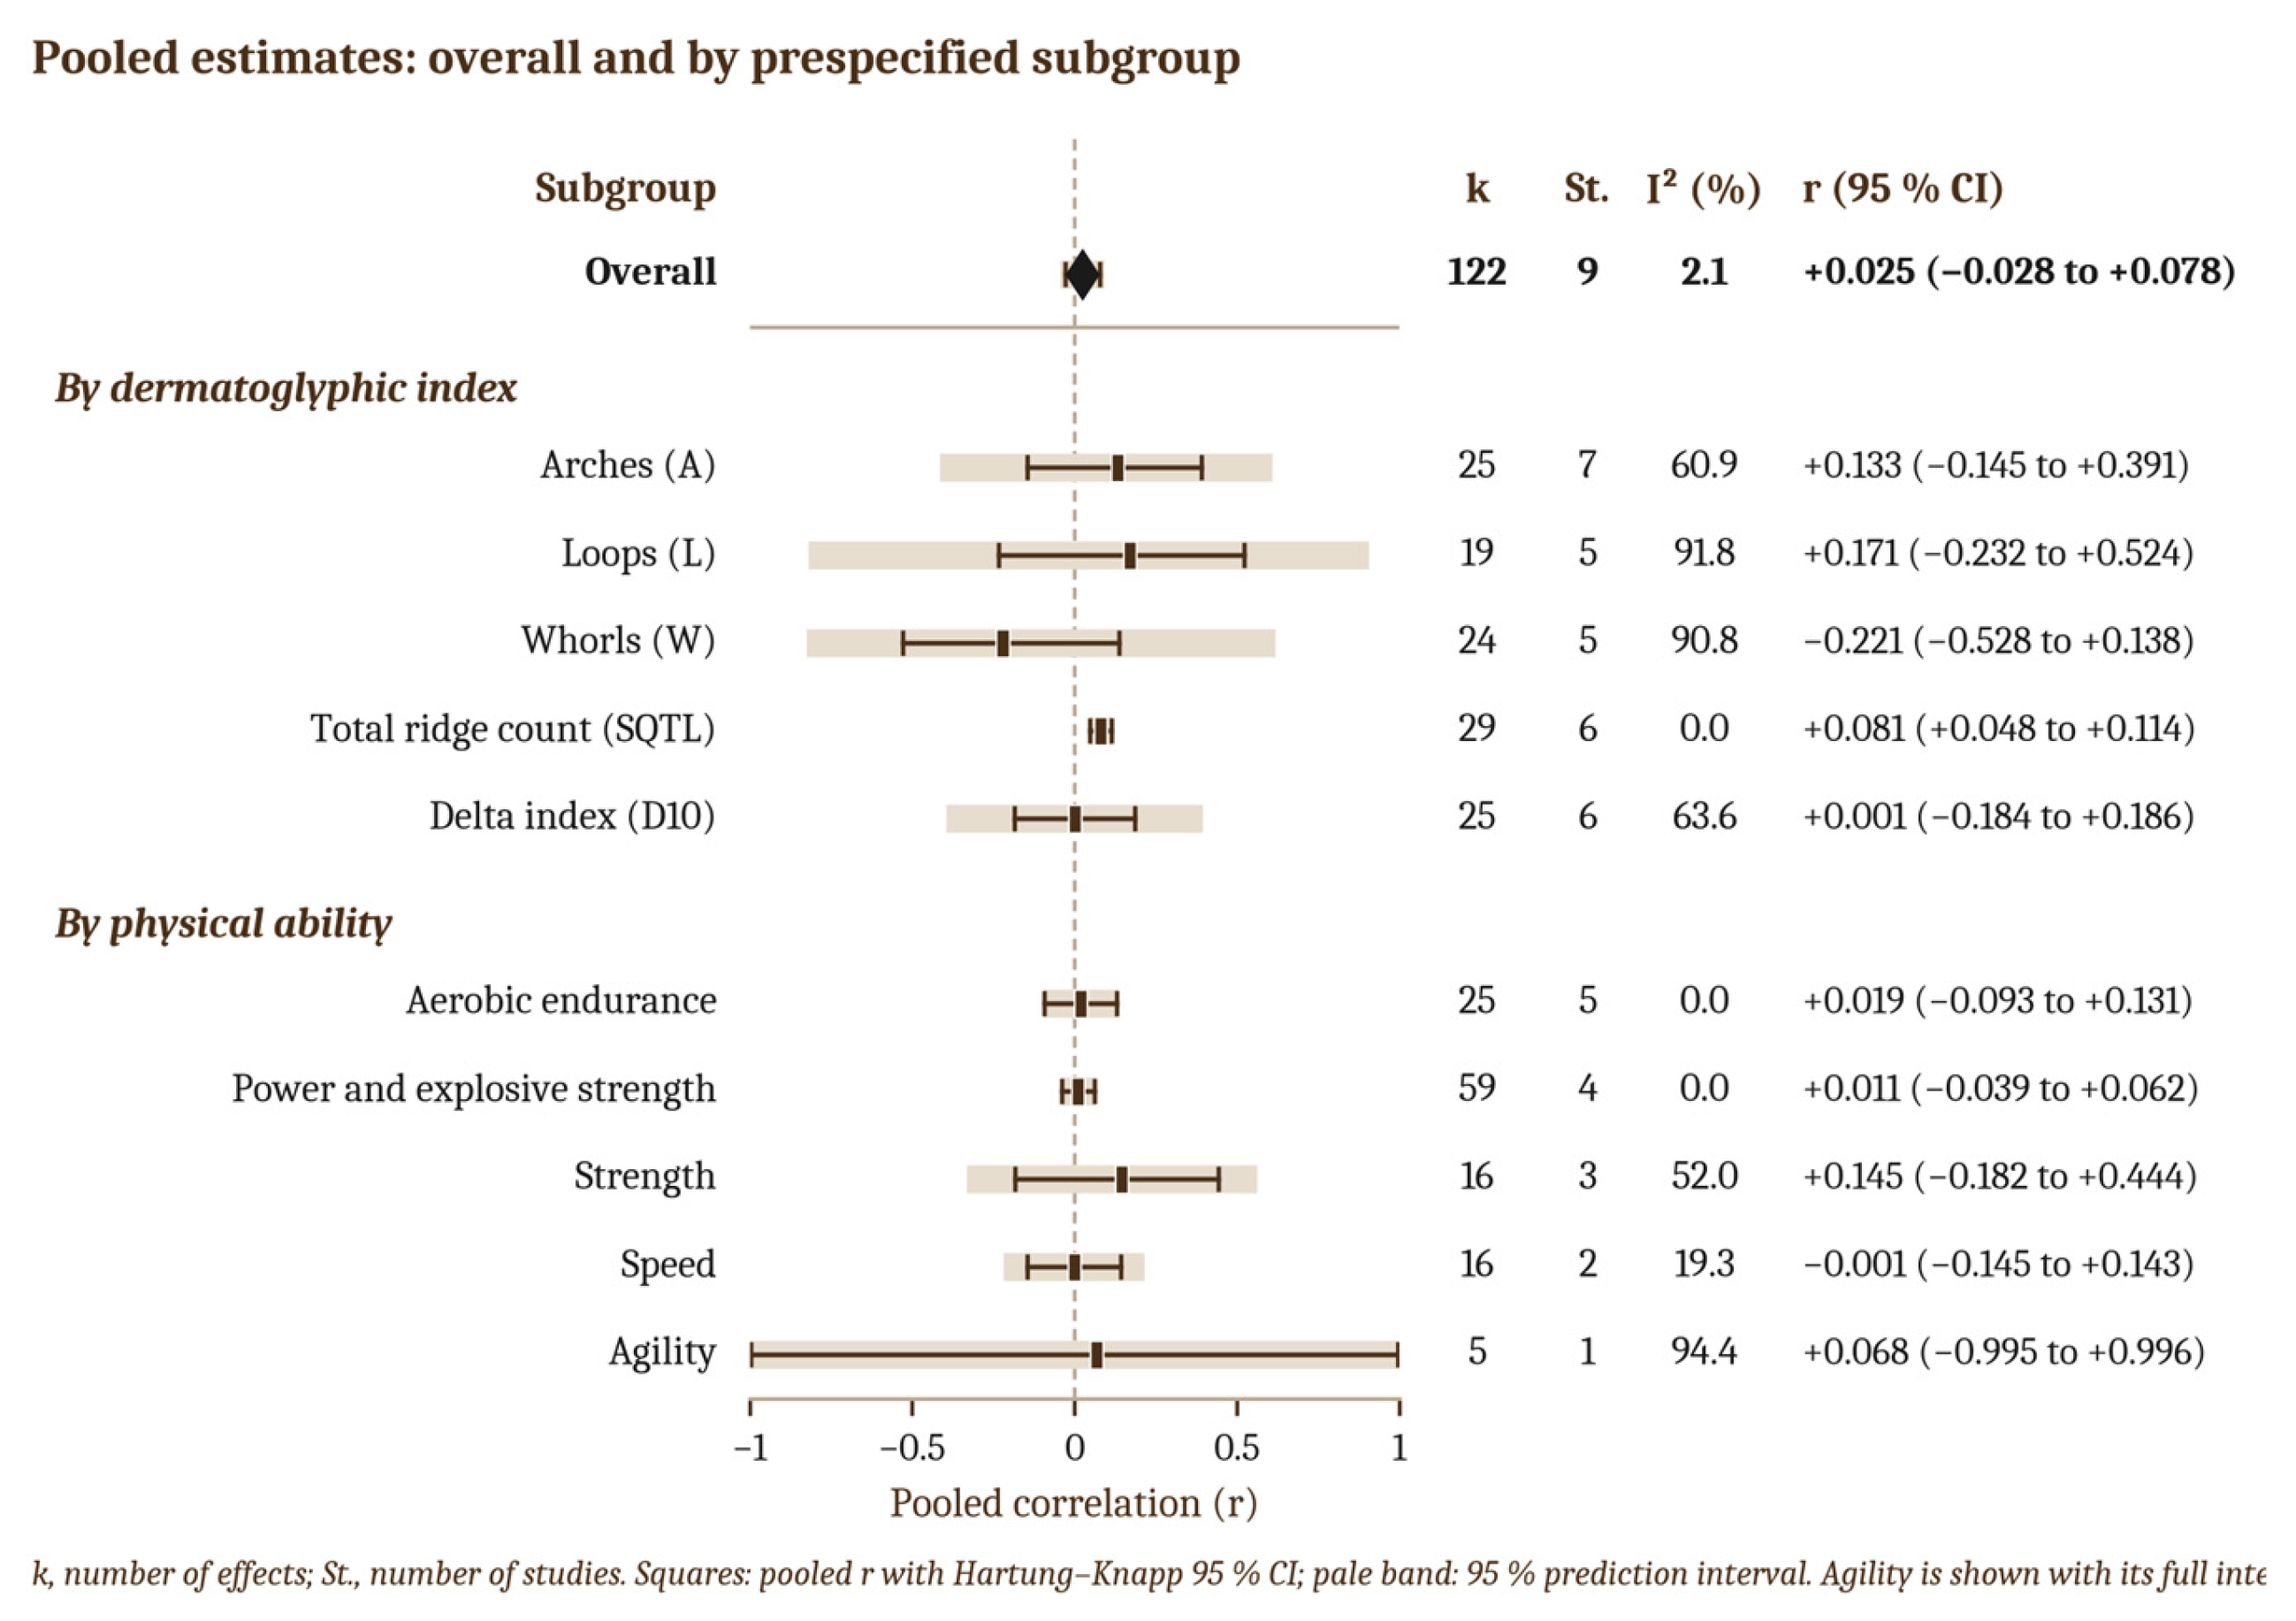
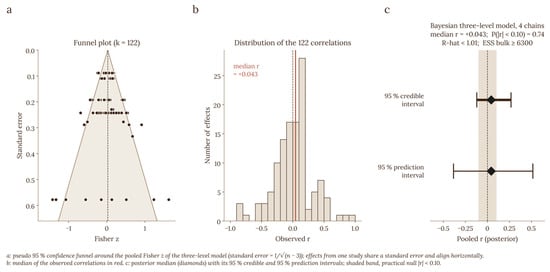
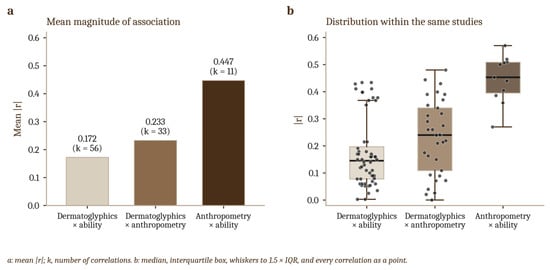
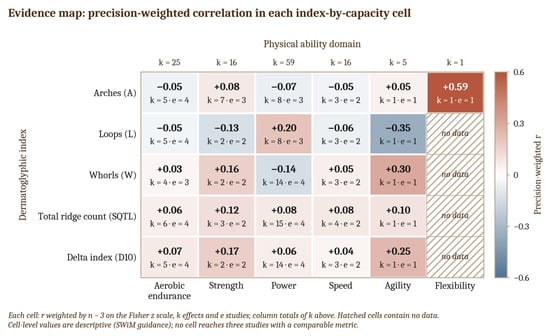
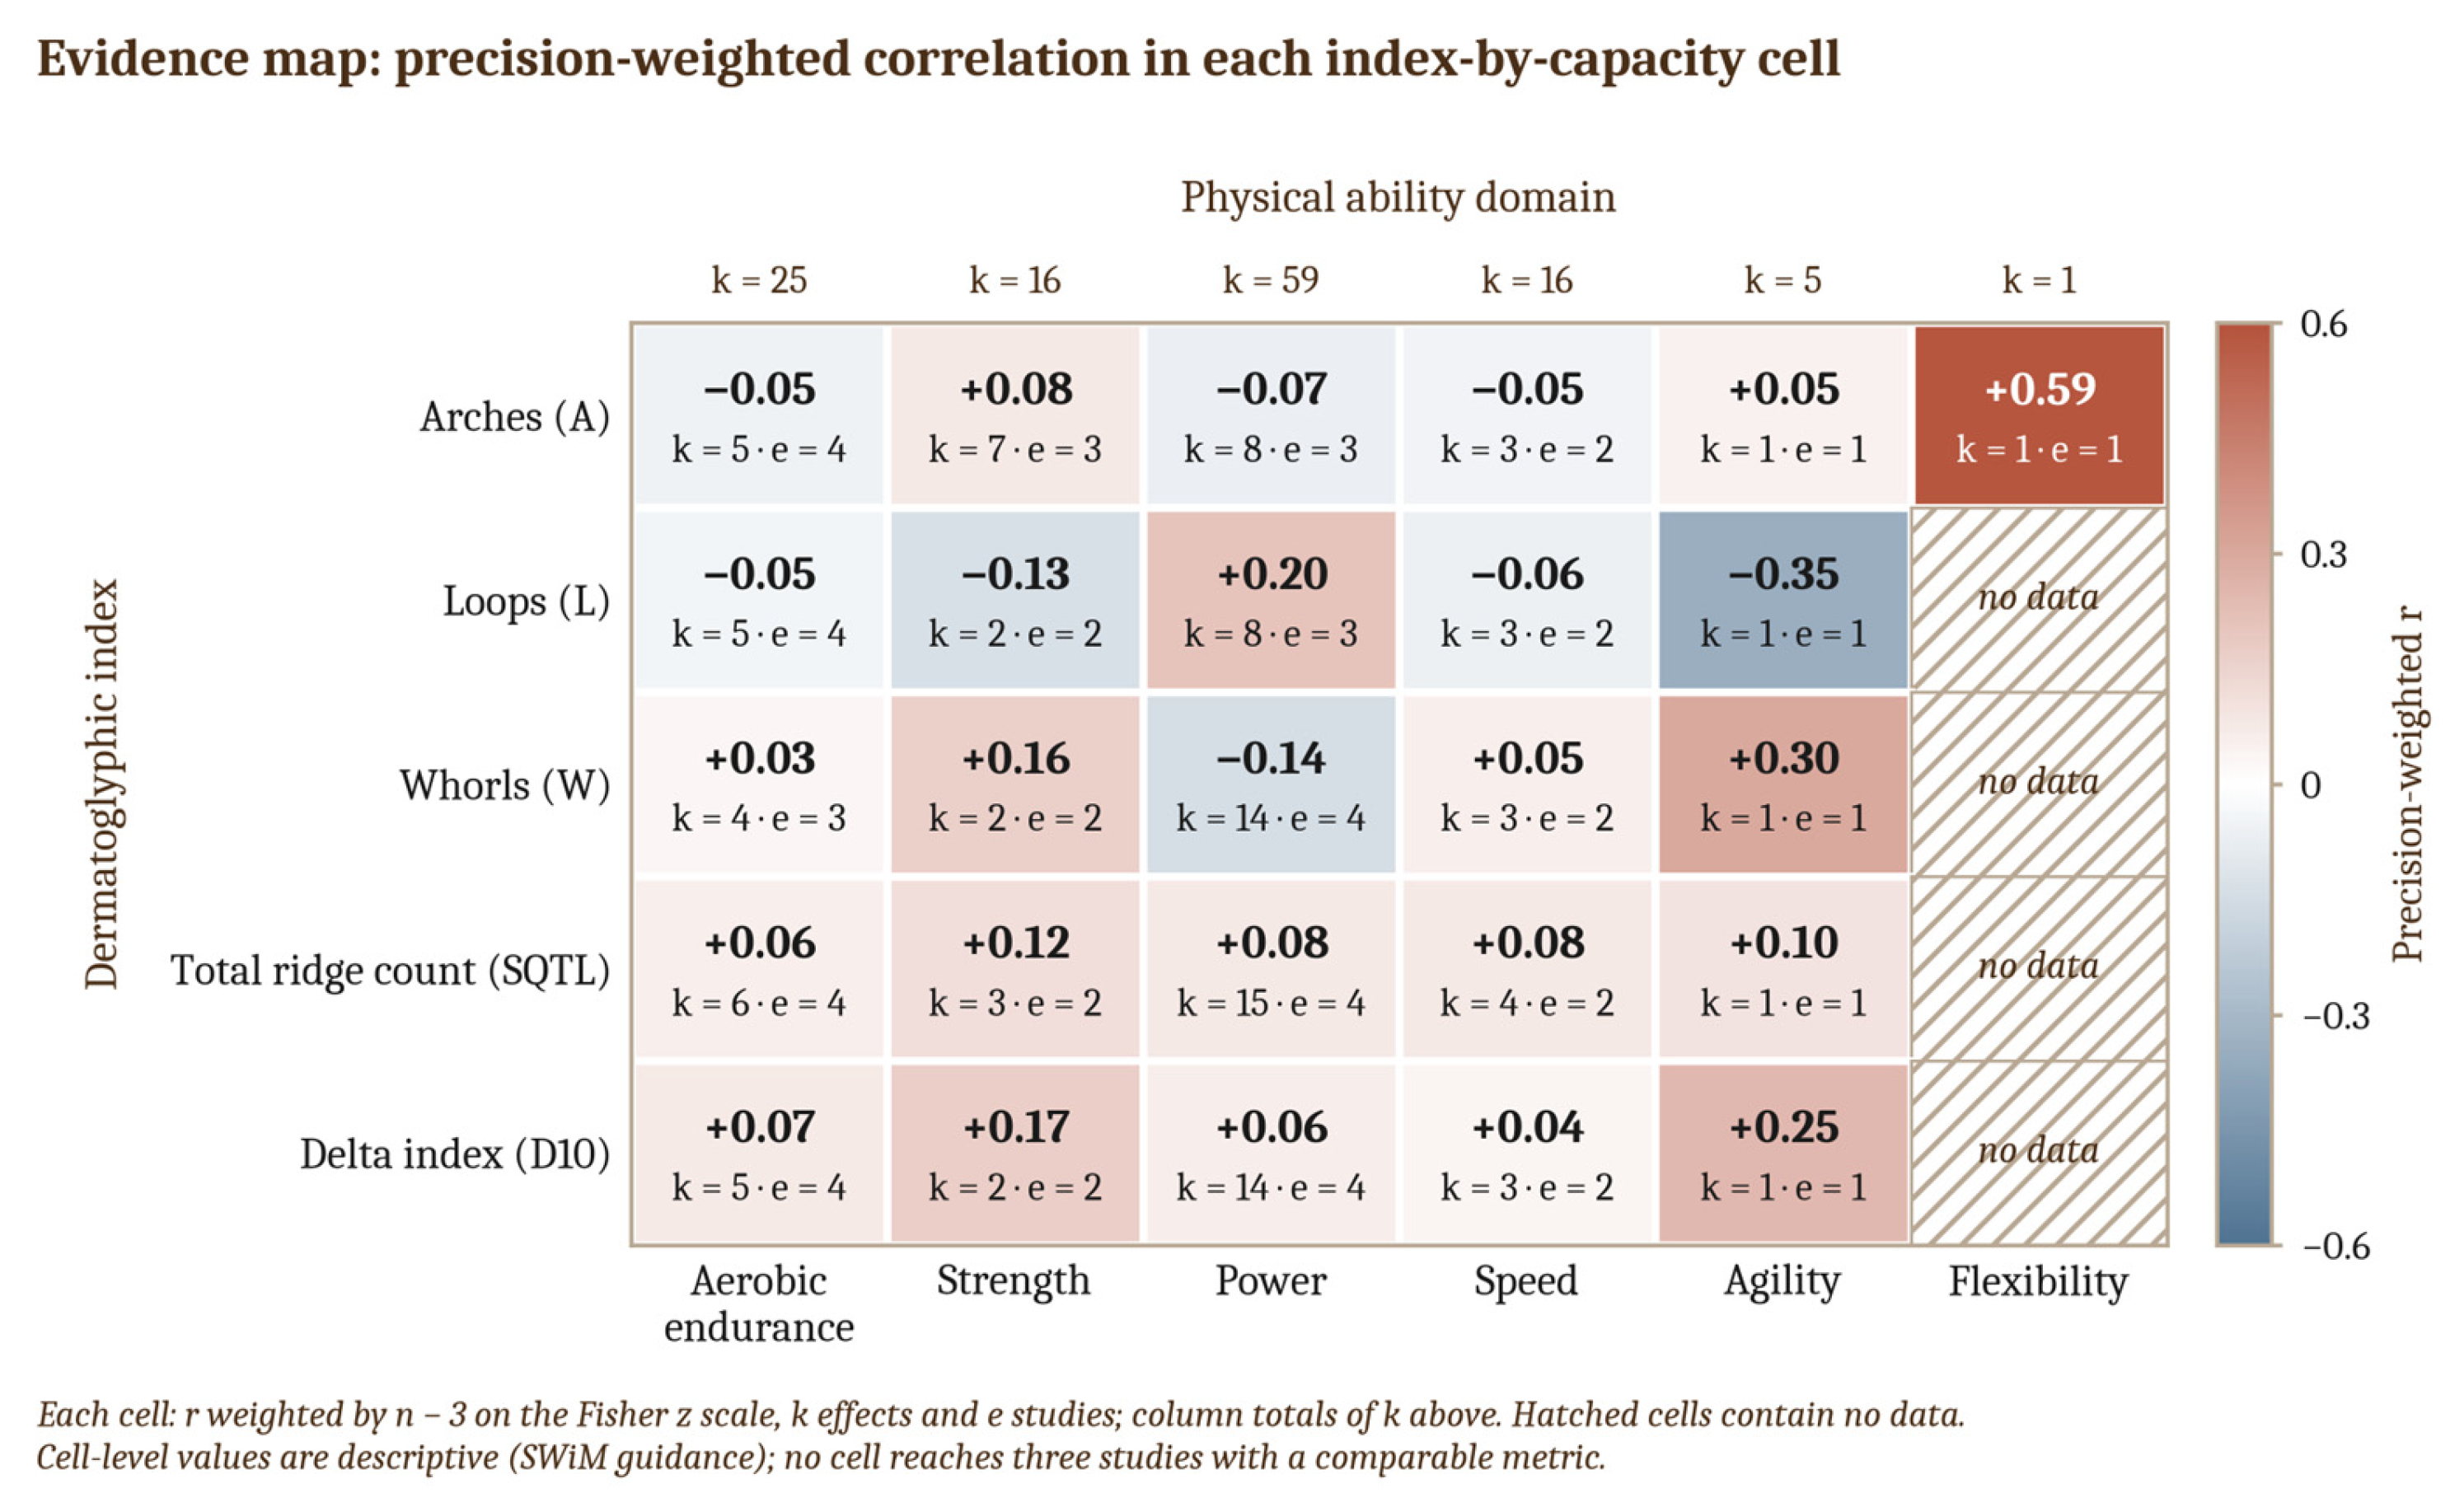

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.