


Simple Summary
Neuroendocrine neoplasms and their main subtype neuroendocrine tumors have an increasing incidence worldwide, associated with a high survival and prevalence rate. Both the tumor itself and systemic therapy can have an impact on patients’ nutrition. Conversely, preliminary data suggest that malnutrition has a negative impact on the development and prognosis of neuroendocrine tumors, as does obesity. The aim of this review is to condense the latest evidence on the role of the most widely used dietary patterns, the Mediterranean diet, the ketogenic diet and intermittent fasting, in the context of neuroendocrine tumors. Nutritional plans are an integral part of the multidisciplinary treatment team of patients with neuroendocrine tumors because they improve the patient’s quality of life. The nutritional approach must be tailored, based on nutritional needs and nutritionally manageable signs and/or symptoms related to drug treatment.
Abstract
Neuroendocrine neoplasms are a heterogeneous group of neoplasms with increasing incidence, high prevalence, and survival worldwide. About 90% of cases are well differentiated forms, the so-called neuroendocrine tumors (NETs), with slow proliferation rates and prolonged survival but frequent development of liver metastases and endocrine syndromes. Both the tumor itself and systemic therapy may have an impact on patient nutrition. Malnutrition has a negative impact on outcome in patients with NETs, as well as obesity. In addition, obesity and metabolic syndrome have been shown to be risk factors for both the development and prognosis of NET. Therefore, dietary assessment based on body composition and lifestyle modifications should be an integral part of the treatment of NET patients. Nutrition plans, properly formulated by a dietician, are an integral part of the multidisciplinary treatment team for patients with NETs because they allow an improvement in quality of life, providing a tailored approach based on nutritional needs and nutritional manageable signs and/or symptoms related to pharmacological treatment. The aim of this review is to condense the latest evidence on the role of the most used dietary models, the Mediterranean diet, the ketogenic diet, and intermittent fasting, in the context of NETs, while considering the clinical and molecular mechanisms by which these dietary models act.
1. Introduction
Neuroendocrine neoplasms represent a group of tumors characterized by wide biological variability and clinical heterogeneity [1,2]. They arise from cells of the neuroendocrine system and can occur in all tissues and organs. However, the gastroenteropancreatic (GEP) and respiratory tracts are the most affected. Neuroendocrine tumors (NETs), which represent the most frequent type (about 90% of cases), are slowly growing and highly surviving tumors, but development of liver metastases, as well as endocrine syndromes is common [1,2]. In the last twenty years, a progressive increase in the incidence of neuroendocrine neoplasms has been reported, with it now being more than 6 cases per 100,000 per year [3,4]. This dramatic incidence increase can mostly be most explained by an improvement in the diagnostic ability, but specific risk factors cannot be excluded.
A few neuroendocrine neoplasms can create biogenic amines and peptide hormones, which may be related with clinical disorders, e.g., the carcinoid disorder (CS) caused by unmetabolized overproduced serotonin, hypoglycemic disorder in case of insulinoma, or Zollinger–Ellison disorder along with gastrinoma [1,2]. The treatment choices for neuroendocrine neoplasms incorporate surgery, somatostatin analogue therapy, radionuclide therapy, chemotherapy, molecular targeted therapies, alpha-interferon therapy, and inhibitors of serotonin production. In the case of hypersensitivity to biogenic amines, a diet that limits most the sources of amines ought to be utilized. The symptoms are ordinarily associated with histamine, tyramine, and putrescine [1,2]. As a result of the sickness, the utilization of a few nutrients can be diminished, driving to nutritional deficiencies, and resulting in malnutrition [5]. Furthermore, changes in digestion system may lead to cachexia in a few of these patients [6]. The crucial role of diet in the development, progression, and outcome of cancer is well known, and the consumption of healthy foods and nutrients is considered an effective strategy for primary cancer prevention, especially in gastrointestinal neoplasms, while tailoring the diet in the disease phase is the key to coping with the symptoms that cancer brings [7]. Based on this potential, several dietary patterns for patients with cancer are currently being studied.
Actually, the largest body of scientific work concerns the Mediterranean Diet (MD). MD’s beneficial effects on cancer are due to the high content of antioxidants and anti-inflammatory nutrients of Mediterranean food (wholegrains, vegetables, nuts, fresh fruit, fish, and extra virgin olive oil), which have a protective effect in counteracting cell degeneration and cancer cell proliferation [8,9,10]. In fact, there is evidence that low adherence to MD may influence the aggressiveness of various tumor types, such as prostate, bladder, and breast cancers [11,12], and, moreover, represent a dietary pattern suitable for both prevention and reduction in mortality from various cancers [10]. Following these observations, a cross-sectional case-control observational study investigated nutritional status, including adherence to MD, in 83 GEP-NET patients, compared to 83 healthy subjects, matched for age, gender, and body mass index (BMI) [13]. The results showed that, compared to healthy subjects, patients with GEP-NETs consumed Mediterranean food less frequently and Western foods (red/processed meats, butter, and sugar drinks) more frequently. Furthermore, NETs patients with more aggressive disease (G2 status) presented lower adherence to MD than patients with less aggressive disease (G1 status). These results highlighted in patients with NETs the association between nutritional status and tumor aggressiveness and the key role of an experienced dietitian in the multidisciplinary management of patients with NETs [13]. In fact, lower adherence to MD could also result from increased symptomatology that limits proper nutrition, representing an important aspect to take into account when applying dietary treatment.
Ketogenic diet (KD), a high-fat, low-carbohydrate diet with an adequate amount of protein, is now also considered a promising approach for the treatment of various cancers, particularly gynecological and neurological cancers [14]. It appears to sensitize most tumors to standard treatment by exploiting the reprogrammed metabolism of cancer cells, making it a promising candidate for adjuvant cancer therapy. Indeed, KD probably creates an unfavorable metabolic environment for cancer cells by inhibiting several signaling pathways involved in cancer cell survival [14]. Moreover, this dietary pattern has been shown to be safe and well tolerated [15,16] and to increase quality of life [17], but there is still a need for studies to confirm these results in NETs.
Finally, caloric restriction (CR) without malnutrition remains the most robust cancer prevention intervention to date in animal models [18,19], and in humans it promotes anticarcinogenic adaptations, such as reduced production of growth factors, inflammatory cytokines, and anabolic hormones, as well as reduced oxidative stress and free radical-induced DNA damage [18,19,20,21]. Despite a wealth of literature on the mechanisms and effects of CR, its clinical applicability remains limited because of challenges with long-term sustainability. Thus, newly designed dietary compositions aimed at inducing fasting-like effects that enable nutrition are beginning to emerge as potential therapies for delaying age-related diseases, such as cancer [22]. These fasting-like diets, such as intermittent fasting (IF), also promote the regeneration and rejuvenation of multiple systems by promoting stem cell self-renewal and white blood cell formation [22]. Therefore, novel, and periodic forms of fasting-like diets, as well as targeted reductions of specific macronutrients and a combination of both are likely to replace the original balanced and chronic restriction of all caloric sources.
Based on this background, we aimed to condense the latest evidence on the role of the most used dietary models (MD, KD, and IF) in the context of NETs while considering the clinical and molecular mechanisms by which these dietary models act.
2. Management of Tumors though Nutritional Approaches
2.1. Clinical Studies
In order to improve the quality life of cancer patient during his journey, several nutritional approaches have been evaluated before, during, and after treatments. The main goals of nutritional therapy for cancer patients are to prevent malnutrition and maintain a healthy weight, assist in symptom management, and reduce risk of treatment intolerance [23]. Indeed, international nutrition societies, such as the American Society of Clinical Oncology (ASCP), the American Society of Parenteral and Enteral Nutrition (ASPEN), the European Society for Clinical Nutrition and Metabolism (ESPEN), and others, have published clinical practice guidelines with recommendations concerning cancers’ patient nutrition care [24]. In general, these recommendations suggest dietary patterns adding value to fresh fruits, vegetables, proteins, and wholegrain cereals while proposing a restricted intake of fat, salt, sugar, and processed food [24]. Moreover, it has been demonstrated that dietary models based on a regular caloric intake of fruits, vegetables (especially cruciferous and garlic), and aliments rich in nutrients, such as vitamins (B-12 or D), folic acid, antioxidants, and selenium can play a protective role in cancer onset [25]. Whereas meat and animal products may increase the incidence of cancer [25]. In the past years, multiple dietary models have been developed following the above-mentioned international guidelines also considering the complex metabolism of cancer. It is estimated that changes in alimentary habits can contribute to avoid cancer onset of 30–50% [26,27]. Indeed, in a case-control study conducted in China on 337 case control pairs within the Shanghai Breast Cancer Study (SBCS), the intake of cruciferous vegetables measured by the urinary secretion of isothiocyanates was inversely related to the risk of breast cancer [28]. In addition, prostate cancer risk was found to be reduced by cruciferous vegetable consumption in a population-based case control study carried out in western Washington State [29]. Three or more servings per week, compared to less than one serving of cruciferous vegetables per week resulted in a statistically significant 41% decrease in prostate cancer risk [29].
Although the above-mentioned studies have reported promising results in cancer prevention, no dietary recommendations can be applied in active cancer patients or during cancer treatments. Indeed, in 2018 the third report of the World Cancer Research Fund/American Institute for Cancer Research (WCRF/AICR) concluded that the evidence of decreased cancer risk associated with greater adherence to dietary models was too scarce, except for cancers of the mouth, pharynx, and larynx [30]. The reason of this conclusion may be also addressed to the wild panel of dietary patterns involved in the studies without a homologous use of descriptive and analytics index [30].
Due to the high prevalence of preclinical evidence and to the strong rationale underlying the association between dietary patterns and cancer incidence, new clinical studies are necessary. Notably, clinical trials and epidemiological studies, together with randomized clinical trials need to be performed with more stringent and specific dietary patterns, in order to acquire consistent and reliable results. In this review, we will emphasize the use of the three major healthy diets models, such as MD, KD, and IF, to better understand their application in cancer prevention, including NET tumors.
2.1.1. Mediterranean Diet
MD embraces a high consumption of fruits, vegetables, nuts, seeds, cereals, and legumes, associated with moderate intake of fish, olive oil, and alcohol beside a low supply of red meat and dairy products [31]. Actually, MD is recognized by United Nations Educational, Scientific and Cultural Organization (UNESCO) as intangible cultural heritage of humanity, and it was defined as a social traditional practice ranging from the landscape to the cuisine of seven Mediterranean countries [32]. The beneficial effects of MD are related to the high content of polyphenol, vitamins, flavonoids, and antioxidants contained in Mediterranean foods [31]. Indeed, their action results in anti-proliferations effects, inhibition of degeneration, DNA damages prevention and anti-inflammatory effects [33]. Due to the large panel of the Mediterranean foods linked to ancient traditions and lifestyles, MD is not a regimen of diet strictly imposed. This peculiarity turns to be an obstacle when applied in clinical research; therefore, in order to overcome discrepancies, different scoring systems and indexes have been developed [34]. In particular, a priori scoring system using the data of each subjects includes the Mediterranean Diet Score (MDS) and the Italian Mediterranean Index [35,36]. The MDS score has nine proper Mediterranean components [36], while the Italian Mediterranean Index includes eleven components: four non-Mediterranean foods, six typical Mediterranean foods, and alcohol [35]. On the other hand, a posteriori scoring is determined after a principal component analysis aimed at defining specific diet model, such as the modified Mediterranean diet (mMED) or alternate Mediterranean diet (aMED) [37,38]. A posteriori scoring system has been used in many observational and prospective studies directed to determine the incidence of each disease and the overall mortality rate [39]. Both, the mMED and aMED consist in a modified MDS, where the ratio of monounsaturated fatty acid (MUFA) + polyunsaturated fatty acid (PUFA) is used as lipid intake. In particular, mMED together with MUFA/PUFA ration measure the saturated fatty acid (SFA) component [37,38]. Notably, employing these methodologies, an inverse and significant correlation between MD and cardiovascular mortality rate was described [40].
Overall, these assumptions together with the well-known relationship between obesity and cancer risk [41,42,43,44], have paved the way to study the association of cancers incidence and mortality with adherence to MD. Although some studies showed that diets rich in fruits and vegetable were not efficient in the reduction in body weight, consistent proof of association between adherence to MD and patient’s body weight have been reported [42,43,44]. PREDIMED and PREDIMED-plus studies are two randomized clinical trials conducted in Spain on high-risk population that provided solid evidence of adherence to MD in weight control [43]. PREDIMED intervention involved subjects with an ad libitum (no dietary intervention) diet, whereas PREDIMED-plus study promoted both physical activity and energy-restricted MD [43]. Nowadays, the most important findings on the association between adherence to MD and cancer risk have been described, especially on breast cancer [45,46], colorectal cancer (CRC) [35,47,48], gastric cancer (GC) [49,50,51], and prostate cancer [52,53,54]. Considering both aMED (excluding alcohol) and MDS score, it emerged that the incidence risk of breast cancer significantly decreased (40%) for post-menopause women [46]. Moreover, it achieved 14–18% when medium or high adherence to MD, together with a moderate alcohol intake, was pursued [45], whereas CRC risk was reduced to about 30% and 45% in both men and women, respectively, with a high adherence to MD [47]. Notably, the predictive capacity of MD in the evaluation of the risk did not change, even when employing different MD scores, such as the Italian Mediterranean Index, mMDS, and center-specific mMDS (CSmMDS), or considering confounding variables [35,48]. Actually, when sex or age variables were considered, it was observing a reduction in mortality rate of 11% and 12%, respectively, for each 1-point increase in mMDS [48]. Concerning GC risk, two case-control studies were conducted in Italy between 1985 and 2007 [49,50]. These two studies were described by Praud and colleagues in an interestingly meta-analysis, in which they were able to assign a proper MDS score to each case control study food frequency questionnaire (FFQ) [51]. Therefore, comparing subjects in the lower category of adherence to MD (0–3) with those in the medium (4–5) and high [6] category, showed a 22% and 43% decreased risk of GC, respectively, hence demonstrating a significant and inverse trend between MD and GC risk [51]. Finally, in prostate cancer patients, it has been shown that a high adherence to MD was not only inversely associated with a low incidence of prostate cancer but also associated with decreased cancer malignancy (44%) and mortality in patients with metastasis (22%) [54]. Overall, a high MD score was associated with a low possibility of prostate cancer [52]. Therefore, prostate cancer risk decreased until 78% in subjects with the highest MD scores, registering in particular a decrease of 14% for each one-point increase in MD score [53].
Interestingly, a novel study of the University of Rochester Medical Center, New York started in 2020 (clinicaltrial.gov NCT04534738). This study will assess the feasibility of delivering an 8-week MD, as well as the efficacy of preliminary interventions on cancer-related fatigue among patients undergoing chemotherapy, compared to usual care (clinicaltrial.gov NCT04534738).
2.1.2. Ketogenic Diets
KD is a high-fat, low-carbohydrate diet with adequate balance of protein and calories [25,55]. Initially, it was developed as therapeutic treatment for pharmacoresistant epilepsy; subsequently, due to its effect in lowering glucose plasma levels, it has been proposed to take advantage of altered metabolism in cancer [25]. Moreover, it has been reported that the low carbohydrate composition (<50 g) is associated with a decreased level of obesity [56,57,58], body weight, and inflammation [59]. These assumptions have grown the clinicians’ interest in the effect of KD application on cancer patients, and, nowadays, emerging results have been reported, as subsequently described. KD dietary pattern requires 65–90% of the daily energy as fat, thus the meals consist of foods enriched of butter, cream mayonnaise, or oils with eggs, meat, and fish—beside cheese—is highly recommended as a protein source [25]. In 1995, the beneficial effects of KD was shown in pediatric patients with advanced-stage malignant astrocytoma [60]. In this case report study, two female pediatric patients with advanced stage malignant astrocytoma tumors displayed an average decrease of 21.8% in glucose uptake after eight weeks of KD at the tumor side [60]. In addition, a clinical trial of 20 patients with recurrent glioblastoma showed a longer progression-free survival under the KD association with standard therapy [61]. Nowadays, clinical studies concerning safety, tolerability, and survival effects reported significant and promising results in several other cancers, including lung cancer [62], endometrial and ovarian cancer [63], breast cancer [16], pancreatic [64], and gastric cancers [65]. The feasibility study preformed on lung cancer demonstrated a high level of response and survival in 44 metastatic non-small cell lung cancer patients undergoing KD [62]. On the other hand, a randomized controlled trial on 73 endometrial and ovarian cancer patients showed a selective loss of fat mass together with a reduced serum insulin level and retention of lean body mass after 12 weeks of KD [63]. Notably, Cohen and colleagues, recording elevated b-hydroxybutyrate in patients’ serum, demonstrated anti-proliferation effects of KD [63]. Overall, these results suggest that KD may be safe tool for endometrial and ovarian cancer. On the other hand, concerning breast cancer, 60 patients treated with chemotherapy associated to KD showed safety, tolerability, and an improved survival, compared to the control group under a standard diet [16]. Whereas in a retrospective observational study with 25 metastatic pancreatic ductal carcinoma patients included, KD compared to the general diet displayed an improved meal compliance, energy intake rate, and meal satisfaction [64]. Finally, survival outcomes were improved in 24 patients with stage III-IV advanced or metastatic gastric adenocarcinoma [65]. Patients received KD combined with chemotherapy, local hyperthermia, and hyperbaric oxygen therapy [65]. These findings suggest that KD is able to promote an improper metabolic environment for tumor cells, assuming a possible role as promising adjuvant for patient-specific multifactorial therapy.
2.1.3. Intermittent Fasting
IF represents one of the strategies to CR and is becoming a popular alternative to daily CR. Indeed, according to the International Food Information Council survey, IF is the most frequently cited diet pattern in 2020 among Americans aged 18 to 80, according to the International Food Information Council (IFIC) [66]. The IF dietary model is characterized by episodic periods of little to no calorie consumption with variation that can range from every-other-day complete 24 h fasting to fasting on 1 or 2 non-consecutive days per week (referred as the 6:1 and 5:2, respectively) [67]. Many fasting programs recommend no or small caloric intake during the fasting period together with an unlimited number of calorie-free beverages, such as water, coffee (without sugar or milk), bone broth, and diet soft drinks [68,69]. The most popular approach is the alternate-day fasting (ADF) in which meals can be either high or low fat if they are less than 500 calories; another variation of IF is named time restricted feeding (TFR) and requires a limited consumption of calories, typically between 4 and 12 h daily [70]. Although initial concern about the fasting exacerbation in cancer patients leading to malnutrition, no significant results were reported in clinical studies [20,67]. The promising effect of both ADF or TRF on glucose, oxidative stress, leptin, and adiponectin implicated in cancer pathogenesis has been reported largely in the literature [71,72,73,74,75]. However, studies of IF adherence in cancer population are limited and are mostly still on trial (recruiting or active phase). Notably, a small nonrandomized study of 23 women at high risk of breast cancer showed that IF adherence of 1 month (2 days per week with 65% of energy restriction) led to a 4.8% reduction in body weight, an 8% reduction in body fat, and an improvement in the homeostatic model assessment (HOMA) for insulin resistance index on both fasting and non-fasting days [76]. Due to this initial result of IF adherence on breast gene expression and breast cancer risk factors, different studies has started analyzing the association between IF, tumor risk factors, and tumor progression. The on-going clinical trials include colon cancer patients (clinicaltrial.gov NCT04345978), gliomas (clinicaltrail.gov NCT04461938), chronic or small lymphocytic (clinicaltrial.gov NCT04626843), childhood cancer (clinicaltrial.gov NCT04626843), and prostate cancer patients (clinicaltrial.gov NCT04288336). Notably, the role of IF in tumor progression is currently studied in patients treated for metastatic breast and prostate cancer with neuroendocrine therapy (clinicaltrail.gov NCT04708860; clinicaltrial.gov NCT02710721).
2.2. Molecular Mechanisms
2.2.1. Mediterranean Diet
MD can favorably contribute to anticancer treatment by several mechanisms [77]. It reduces tumor cell growth by acting on hormones and extra and intracellular pathways, has anti-inflammatory, anti-oxidative and anti-aggregating effects, modulates hormones and growth factors involved in cancer, reduces lipids, and positively affects the production of microbiota bacterial metabolites [77]. The anti-tumoral effects of MD can be played by many food compounds, including fish, fruit, vegetables, cereals, olive oil, and legumes [78]. These elements are full of antioxidants, such as vitamins A, C and E, carotenoids, lycopene, of flavonoids, polyunsaturated fatty acids (PUFAs) and fibers, which are involved in many cellular signaling pathways [78]. Antioxidants scavenge reactive oxygen species (ROS) and reduce their production. ROS are involved in the stimulation of phosphoinositol-3-kinase (PI3K) and mitogen-activated protein kinases (MAPK), which in turn activate the nuclear factor kappa beta (NF-kβ) favoring cancer development [79,80,81,82]. Flavonoids directly reduce the activation of PI3K and MAPK pathways; inhibit the conversion of pro-carcinogens in active carcinogens; increase the expression of phase 2 enzymes, involved in the catabolism of carcinogens; stimulate the AMP-activated protein kinase, which, in turn, is involved in the modulation of NF-kβ activity; moderation of cell cycle; and favor DNA-repairing molecules [83]. Fibers act on gut microbiota, releasing short-chain fatty acids (SCFAs), which can reduce the expression of NF-kβ in enterocytes, reduce the proliferation of cancerous colonocytes and reduce the expression of local neutrophils, lymphocytes, and dendritic cells [84,85]. Further, they reduce the insulin and IGF-1 secretions, which are involved in tumor growth [86,87]. PUFAs contributes to reduce the chronic low-grade inflammation, by down-regulation of NF-kβ and decreased expression of inflammatory cytokines, including IL-6, IL-1β, and TNF-α, and anti-angiogenetic, such as VEGF [88]. Red wine is a source of resveratrol and quercetin able to modulate cell cycle, induce apoptosis in cancer cells, and act as an anti-inflammatory [89]. However, the beneficial effects of red wine are controversial [89].
2.2.2. Ketogenic Diet
KD has been reported as an effective anticancer therapy, enhancing chemotherapy effect, reducing inflammation, and regulating the expression of many factors and proteins, including matrix metalloproteinases, histone deacetylases, AMP-activated protein kinase, pyruvate kinase (AMPK), and p53 [14,90]. The anticancer effects are played both by a decrease in glucose levels and by the production of ketone bodies. KD reduces glucose uptake, essential for tumor cells, which are glucose dependent (Warburg effect) and increases ketone bodies, which cannot be used by cancer cells [91,92]. Interestingly, KD reducing carbohydrate assumption reduces insulin and IGF-1 levels and increases insulin sensitivity. Low IGF-1 levels result in the inhibition of PI3K/Akt/mTOR system and of the synthesis of vascular endothelial growth factor (VEGF), which are involved in angiogenesis, cancer cell proliferation, and survival [93,94,95]. KD reduces the production of pro-inflammatory cytokines, including tumor necrosis factor-α (TNF-α), interleukin-1β (IL-1β), interferon-γ (IFN-γ), and cyclo-oxygenase 2 (COX-2), which are involved in tumor growth, proliferation, angiogenesis, invasion, metastasis, and DNA damage [96,97]. In addition, KD decreases the expression of matrix metallo-proteinases-9 and inhibits the expression of histone deacetylases, resulting in a modulation of the methylation status of oncogenes and, consequently, in a tumor growth slowdown and induction of apoptosis [98]. Further, KD inhibits the expression of pyruvate kinases M2 (PKM2) [87]. PKM2 is involved in the process of glycolysis, catalyzing the conversion of phosphoenolpyruvate to pyruvate with the production of ATP, and it is strongly expressed in cancer cells, mediating their metabolism [99]. Another interesting effect of KD is the silencing of p53 mutant factor. In cancer cells, there are mutations in p53 factor favoring the cancer cell proliferation [88]. KD, reducing glucose levels, results in increased deacetylation and degradation of p53 mutant, reducing its expression in cancer cells [100]. In the end, KD reducing glucose uptake increases the expression of AMPK, resulting in the activation of p53 factor and further inhibition of mTOR expression resulting in the inhibition of tumor growth and proliferation and stimulation of cancer cells apoptosis [101,102] (Figure 1).
Figure 1.
Anticancer effects of ketogenic diets.
Ketogenic diet could be an effective adjuvant anticancer therapy, reducing glucose uptake (Warburg effect) and production of pro-inflammatory cytokines (TNFα, IL-1β, IFN-γ, COX-2) and regulating the expression of many factors and proteins, including matrix metalloproteinases, histone deacetylases, pyruvate kinase, p53, and AMP-activated protein kinase, involved in tumor growth and progression. Abbreviations: MMP9, matrix metallo-proteinases-9; HDAC, histone deacetylases; PKM9, pyruvate kinases M2; AMP-K, pyruvate kinase; TNFα, tumor necrosis factor-α; IL-1β, interleukin-1β; IFN-γ, interferon-γ (IFN-γ); COX-2, cyclo-oxygenase 2; (→), activation; (┬), inhibition.
2.2.3. Intermittent Fasting
The effects of IF in cancer have been demonstrated in preclinical rodent studies [103]. IF was shown to reduce blood glucose, leptin, insulin, and IGF-1 levels, leading to the modulation of the PI3K/AKT/mTOR pathways [104,105]. Notably, IF is associated with an increase in insulin-like growth factor-binding protein (IGFBP-1), reducing IGF-1 bioavailability, and thus reducing cell motility and metastasis [106,107]. In addition, IF was associated with ketone body formation that blocks histone deacetylases and, consequently, tumor growth, and, at the same time, plays an antioxidant function [108,109]. Further, IF could stimulate cellular autophagy, resulting in the elimination of damaged molecules and proteins [110]. Autophagy can act as an anticarcinogenic mechanism against tumor transformation. In addition, autophagy may act to increase the sensitivity to chemotherapy and reduce the toxicity [20]. Finally, IF reduces inflammation by decrease in C-reactive protein, IL-6 and TNF-α [111]. However, all the above-mentioned data are available from animal studies and need to be confirmed in humans.
3. Nutrition and Symptoms Related to Neuroendocrine Neoplasms
Unhealthy diets, along with visceral fat accumulation, could cause cancers, including NETs [112]. In this regard, Barrea et al. found an association between high visceral adiposity index (VAI), which is a gender-specific indicator of adipose dysfunction, high fatty liver index (FLI), a tool for identifying individuals with non-alcoholic fatty liver disease, and metabolic syndrome, with worse clinicopathological characteristics in NET patients [113]. On the other hand, several studies underlined the risk of malnutrition in patients with NET [5,6,114,115]. Specifically, Maasberg et al. highlighted that about 20–25% of patients with NET were at risk of manifest malnutrition, determined by biochemical analysis, anthropometric measurements, and bioelectrical impedance analysis (BIA) [5]; similar results were described by Laing et al. [114] and Borre et al. [6] in their cross-sectional studies, who found 29% and 25% of patients with NET were malnourished, respectively. A lower prevalence of malnutrition was assessed by Qureshi et al., who found this condition in 14% of outpatients with GEP-NET [115]. However, the authors recommended a routine use of malnutrition screening in all patients with GEP-NET.
Furthermore, a worse metabolic profile in NET patients is also associated with higher ki67% index and larger tumor size [116]. For these reasons, nutrition assessment and management should be an integral part of the management of patients with NETs and should be performed by an accredited dietitian [116,117]. Interestingly, Leoncini et al. conducted a meta-analysis and highlighted that body mass index (BMI) was the most relevant risk factor for NETs development, only after family history of cancer [118]. On the other hand, malnutrition could negatively influence the quality of life and survival [5]. Nutritional status in NET patients, mainly gastrointestinal NET, is also affected by the increased production of gastrointestinal hormones, peptides, and amines [116]. In this regard, the clinical manifestations of NETs could be characterized by various hormone hypersecretion syndromes, such as the CS or the hyperinsulinemic hypoglycemia syndrome, in case of insulinomas [116].
Diet should be formulated and individualized by an accredited dietitian, according to the patients’ characteristics, considering age, stage of the disease, pharmacological and/or surgical treatment, and symptoms (i.e., diarrhea or constipation, hypoglycemia, or hyperglycemia) [116,119].
3.1. Diet Protocol and Neuroendocrine Tumors
3.1.1. Mediterranean Diet
MD is considered one of the healthiest dietary patterns, and there is a correlation between low adherence to MD and cancer, and adherence to MD could influence the aggressiveness of different tumor types (i.e., prostate, breast cancer, and melanoma) [12,120]. For all these reasons, MD could be considered a useful model to adopt in NET patients.
Barrea et al. conducted a case-control, cross-sectional study to investigate the nutritional status in a selected group of GEP-NET patients and the adherence to MD, using a validated 14-item questionnaire for the assessment of PREvención con DIeta MEDiterránea (PREDIMED) [13]. The authors found that patients with more aggressive disease showed a lower adherence to MD, compared to G1, localized and free/stable disease status; furthermore, the presence of metastases and progressive disease were higher in patients with scarce adherence to MD. This study highlighted the relationship between nutritional status and tumor aggressiveness, showing how MD could represent an important tool for the prevention of cancer aggressiveness in patients with NET [13]. Obviously, the strength of evidence is related only to one study and further studies are needed to confirm this finding.
Due to the importance of adherence to MD, which appear to be a dietary pattern suitable for the prevention of the disease, some recommendations have been proposed in patients without current disease [121]: (a) to perform a nutritional dietary planning in all NET patient; (b) to limit consumption of red and processed meat, sugar, and sweet beverages; (c) to avoid alcohol, and d) to prefer fruit and vegetables, legumes, and grains.
In patients with CS, small and frequent meals should be suggested [121].
3.1.2. Ketogenic Diet
KD regimen showed promising results as an adjuvant cancer therapy, mainly targeting tumor metabolism, through the modulation of gene expression, as well as tumor microenvironment. To date, there is a lack of randomized controlled trials on the effect of KD on cancer in general [122,123] and, specifically, in NET patients. Moreover, KD, inducing the body to get energy from fat instead of glucose, could antagonize the “Warburg effect”, which refers to the aerobic glycolysis that occurs in cancer cells [124]. This hypothesis leads us to speculate that KD can improve the condition of insulin resistance, even before weight loss. In fact, KD increased the insulin sensitivity in patients suffering with type 2 diabetes mellitus by about 75% [125]. This effect may be particularly useful in some forms of secreting NETs associated with hyperinsulinemia [126]. Interestingly, Fine et al. conducted a pilot study with end-stage cancer and observed that 28 days of KD were related to a significant reduction in insulin levels and a better therapeutic response [127].
On the other hand, it should also be considered that a high-fat diet can worsen or induce symptoms related to fat malabsorption; therefore, caution is needed in KD use.
3.1.3. Intermittent Fasting Diet
In the last decades, a growing interest has been addressed to IF, including different strategies (mainly one or two non-consecutive days per week of 24 h fasting) [67]. Even if preclinical studies showed the promising effects of IF on cancer [128,129], to date, no studies conducted in NET patients are available. However, based on studies in non-cancer patients, we can only speculate that the anti-inflammatory effects and overweight and obesity reduction related to IF could also improve the tumor responses to anticancer treatment in NET patients [130]. Furthermore, it has been supposed that IF could induce an anti-Warburg effect, similar to KD [128]. Obviously, this is an assumption without enough evidence to make recommendations, and further studies are needed.
3.2. Management of Symptoms through Nutritional Approaches
3.2.1. Diarrhea
Diarrhea is a frequent symptom in patients with NET. The main causes are tumor growth and mass effects, as well as over secretion of peptides and hormones by functioning tumors [131]. Furthermore, diarrhea and steatorrhea are common adverse effects of SSAs, due to treatment-induced pancreatic insufficiency [131]. It would be advisable, extending the evidence deriving from non-NET patients, to avoid sources of histamine, such as baker’s yeast, wine, beer, and cheese, as well as highly processed cold meat [132]. In patients with CS, diarrhea, mainly secretory, occurs in 80% of cases. In these cases, frequent small meals and avoiding aged cheeses and fermented foods with high amine content could help to reduce symptoms; furthermore, these indications still require strong scientific evidence. Moreover, replenishing liquids is essential [133].
MD, high in fruit, vegetables, and grains, represents a good dietary pattern; however, patients with symptomatic NETs should reduce insoluble fiber and increase soluble fiber consumption [116]. Moreover, studies conducted on healthy subjects found that adherence to MD dietary pattern could improve fecal microbiota composition [134]; this concept could also be extended to NETs patients. Regarding the effects of KD on diarrhea, a cross-sectional study conducted in 17 patients with diarrhea-predominant irritable bowel syndrome showed an improvement in abdominal pain, stool habits, and quality of life after four weeks of this diet regimen [135]; these results could open a new scenario in the management of patients with NET. Lastly, IF seems to reduce gastrointestinal discomfort related to diarrhea in cancer patients [136], and this could also be helpful in NET patients; however, limited numbers of human studies are available.
3.2.2. Constipation
Chronic constipation can occur in patients with NET less frequently than diarrhea, mainly due to side effects of treatment, ileus, or catecholamines excess; flatulence, pain, and abdominal distension are often related symptoms [137]. In this contest, along with physical exercise, diets should prevent constipation through liquids consumption (i.e., mineral water, juice) and following a high-fiber diet (whole grains, vegetables, and fruit with high fiber content) [116]; for these reasons, MD could represent a valid dietary pattern. KD should be used with caution, based on studies that report an increased risk of constipation in patients using this nutritional pattern, especially those over 70 years of age [138]. Finally, general indications suggested not to skip meals [139]; in this context, IF regimen should be avoided.
3.2.3. Malnutrition and/or Cachexia
Malnutrition, which is a deficiency or imbalances in a person’s intake of energy and/or nutrients, and cachexia, which is characterized by a loss of fat and muscle mass, frequently occur in cancer patients [140]. The main causes are: (1) anorectic effects of the tumor, and (2) a limited food consumption, which is frequently caused by nausea, vomiting, pain, and inflammation of the mucous membrane related to anticancer treatment [140]. The consequences are body mass loss and tiredness [141]. In this contest, a well-balanced diet, i.e., MD, should prevent body mass loss, including an appropriate amount of all nutrients (proteins, fat, carbohydrates, vitamins, and minerals) and consuming meals more frequently. Supplementation with omega-3 fatty acids, as well as arginine may support the nutritional profile. In patients with CS, niacin (vitamin B3) deficiency can occur due to the increased metabolism of tryptophan (which is the precursor of niacin) into serotonin; vitamin B3 supplementation could be helpful [142].
KD used in patients with cancer usually obtain weight loss [90]; however, it has been demonstrated that in cachectic patients, KD induced weight gain [143]. These issues require further studies in order to find effective clinical indications.
3.2.4. Glycemic Imbalance: Hypoglycemia and Hyperglycemia
Hormones hypersecretion could be a cause of imbalanced nutrition and metabolic changes in patients [144]. Patients with insulinoma showed the low level of glucose and the role of diet is to prevent long fasting between meals, as well as the supply of high glycemic index carbohydrates in the case of hypoglycemia. For these reasons, IF diet should be avoided. Glucose metabolism can also be slowed down by a high-protein diet [144]; the high protein content of KD may be supportive, but the absence of carbohydrates should be avoided too. Low glycemic index and complex carbohydrates should be preferred, while rapidly absorbable carbohydrates with a high glycemic index are suited during hypoglycemic episodes [116].
On the other hand, hyperglycemia can occur as an effect of some pharmacological treatment (SSAs), surgery (pancreatectomy with subsequent iatrogenic diabetes), or tumor mass, causing a reduction in insulin secretion [1]. A healthy balanced diet, with reduced carbohydrate intake and high consumption of fiber could be helpful to prevent or delay the onset of diabetes, as well as to improve glycemic control [145]. In this regard, MD represents a healthful eating pattern, which can improve glycemic profile, and delay the need for antidiabetic drug therapy, as also recommended by the American Diabetes Association (ADA) guidelines [146]. On the other hand, KD may represent an alternative, due to insulin-sensitizing effects, reduction in blood glucose, and insulin-like growth factor, which are important drivers of cancer cell proliferation; similarly, IF protocol could ameliorate glucose metabolism, maintain the BMI, and reduce inflammation [147].
3.2.5. NET Treatment-Related Symptoms
NET pharmacological treatment mainly includes SSAs and, in case of unresectable or metastatic NETs or neuroendocrine carcinoma (NEC), targeted therapies (everolimus and sunitinib) and chemotherapy [4]. SSAs, which are the most common pharmacological treatment for advanced well-differentiated NETs, can induce exocrine pancreatic insufficiency, resulting in diarrhea and steatorrhea [148]. Considering target therapy, some foods (i.e., grapefruit, chamomile, garlic, and ginseng) could inhibit cytochrome P450 3A pathway, with a subsequent increasing toxicity of this treatment [112]. With regard to temozolomide, patients should be instructed not to take it with fatty foods, as these can modify the stomach pH, inhibiting cytochrome P450; high-fat meals are also inhibitors of tyrosine kinase [148]. Chemotherapy, including fluoropyrimidine, oxaliplatin, and irinotecan, could induce diarrhea.
MD, which represents a healthy eating model, can be useful in the management of gastrointestinal adverse effects related to NET treatments. Furthermore, it could be speculated that KD can increase the effect of pharmacological treatment, acting on IL-6, VEGF, and PI3K/AKT/mTOR pathways [100]; this strengthens the idea that KD could be considered an “adjuvant cancer therapy”, translatable in the management of NETs. Finally, it could be supposed that the IF diet is capable of decreasing tumor growth, as well as chemotherapy-related toxicity, mainly diarrhea [149]; however, further studies on human are needed to investigate the safety and feasibility of fasting.
4. Conclusions
Neuroendocrine neoplasms and their main subtype NETs have an increasing incidence worldwide, associated with a high survival and prevalence rate. Surgery remains the only curative treatment for early stage disease, while SSAs are the treatment of choice for unresectable/advanced disease, followed by peptide receptor-targeted radiotherapy and various drugs, such as targeted therapy and chemotherapy. Both the tumor itself and systemic therapy may have an impact on patients’ nutrition. Malnutrition has a negative impact on the development and prognosis of NETs, as well as obesity. However, data on nutrition in NETs are scattered and large epidemiological studies, as well as randomized clinical trials are lacking. In addition to the well-known MD, new nutritional approaches seem to have important benefits for patients with NETs, such as KD and IF, and could be used appropriately according to patient characteristics. Therefore, dietary assessment based on body composition and lifestyle modifications should be an integral part of the treatment of NET patients. Nutrition plans are an integral part of the multidisciplinary treatment team for patients with NETs because they allow an improvement in the quality of life, providing a tailored approach based on nutritional needs and nutritional manageable signs and/or symptoms related to pharmacological treatment.
Author Contributions
Conceptualization, G.M. and A.F.; writing—original draft preparation, L.B., M.C.C., V.G., R.M., L.V. and C.V.; writing—review and editing, G.M., L.B. and A.F.; supervision, A.C. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Carra, S.; Gaudenzi, G. New perspectives in neuroendocrine neoplasms research from tumor xenografts in zebrafish embryos. Minerva Endocrinol. 2020, 45, 393–394. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ferolla, P.; Faggiano, A.; Mansueto, G.; Avenia, N.; Cantelmi, M.G.; Giovenali, P.; Milione, F.; Scarpelli, G.; Masone, S.; Lombardi, G.; et al. The biological characterization of neuroendocrine tumors: The role of neuroendocrine markers. J. Endocrinol. Investig. 2008, 31, 277–286. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dasari, A.; Shen, C.; Halperin, D.; Zhao, B.; Zhou, S.; Xu, Y.; Shih, T.; Yao, J.C. Trends in the Incidence, Prevalence, and Survival Outcomes in Patients with Neuroendocrine Tumors in the United States. JAMA Oncol. 2017, 3, 1335–13342. [Google Scholar] [CrossRef] [Scilit]
- Garcia-Carbonero, R.; Sorbye, H.; Baudin, E.; Raymond, E.; Wiedenmann, B.; Niederle, B.; Sedlackova, E.; Toumpanakis, C.; Anlauf, M.; Cwikla, J.M.; et al. ENETS Consensus Guidelines for High-Grade Gastroenteropancreatic Neuroendocrine Tumors and Neuroendocrine Carcinomas. Neuroendocrinology 2016, 103, 186–194. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maasberg, S.; Knappe-Drzikova, B.; Vonderbeck, D.; Jann, H.; Weylandt, K.H.; Grieser, C.; Pascher, A.; Schefold, J.C.; Pavel, M.; Wiedenmann, B.; et al. Malnutrition Predicts Clinical Outcome in Patients with Neuroendocrine Neoplasia. Neuroendocrinology 2017, 104, 11–25. [Google Scholar] [CrossRef] [Scilit]
- Borre, M.; Dam, G.A.; Knudsen, A.W.; Grønbaek, H. Nutritional status and nutritional risk in patients with neuroendocrine tumors. Scand. J. Gastroenterol. 2018, 53, 284–292. [Google Scholar] [CrossRef] [Scilit]
- World Cancer Research Fund; American Institute for Cancer Research. Diet, Nutrition, Physical Activity and Cancer: A Global Perspective; Word Cancer Research Fund International: London, UK, 2018. [Google Scholar]
- Abenavoli, L.; Luzza, F. Mediterranean diet and NAFLD: Where are we now? Minerva Endocrinol. 2021, 46, 371–373. [Google Scholar] [CrossRef] [Scilit]
- Laudisio, D.; Castellucci, B.; Barrea, L.; Pugliese, G.; Savastano, S.; Colao, A.; Muscogiuri, G. Mediterranean diet and breast cancer risk: A narrative review. Minerva Endocrinol. 2021, 46, 441–452. [Google Scholar]
- Morze, J.; Danielewicz, A.; Przybylowicz, K.; Zeng, H.; Hoffmann, G.; Schwingshackl, L. An updated systematic review and meta-analysis on adherence to mediterranean diet and risk of cancer. Eur. J. Nutr. 2021, 60, 1561–1586. [Google Scholar] [CrossRef] [Scilit]
- Buckland, G.; Ros, M.M.; Roswall, N.; Bueno-de-Mesquita, H.B.; Travier, N.; Tjonneland, A.; Kiemeney, L.; Sacerdote, C.; Tumino, R.; Ljungberg, B.; et al. Adherence to the Mediterranean diet and risk of bladder cancer in the EPIC cohort study. Int. J. Cancer 2014, 134, 2504–2511. [Google Scholar] [CrossRef] [Scilit]
- Escrich, E.; Moral, R.; Solanas, M. Olive oil, an essential component of the Mediterranean diet, and breast cancer. Public Health Nutr. 2011, 14, 2323–2332. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barrea, L.; Altieri, B.; Muscogiuri, G.; Laudisio, D.; Annunziata, G.; Colao, A.; Muscogiuri, G.; Faggiano, A.; Savastanp, S. Impact of Nutritional Status on Gastroenteropancreatic Neuroendocrine Tumors (GEP-NET) Aggressiveness. Nutrients 2018, 10, 1854. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Talib, W.H.; Mahmod, A.I.; Kamal, A.; Rashid, H.M.; Alashqar, A.M.D.; Khater, S.; Jamal, D.; Waly, M. Ketogenic Diet in Cancer Prevention and Therapy: Molecular Targets and Therapeutic Opportunities. Curr. Issues Mol. Biol. 2021, 43, 558–589. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barrea, L.; Verde, L.; Vetrani, C.; Marino, F.; Aprano, S.; Savastano, S.; Colao, A.; Muscogiuri, G. VLCKD: A real time safety study in obesity. J. Transl. Med. 2022, 20, 23. [Google Scholar] [CrossRef] [Scilit]
- Khodabakhshi, A.; Akbari, M.E.; Mirzaei, H.R.; Mehrad-Majd, H.; Kalamian, M.; Davoodi, S.H. Feasibility, Safety, and Beneficial Effects of MCT-Based Ketogenic Diet for Breast Cancer Treatment: A Randomized Controlled Trial Study. Nutr. Cancer 2020, 72, 627–634. [Google Scholar] [CrossRef] [Scilit]
- Kämmerer, U.; Klement, R.; Joos, F.; Sütterlin, M.; Reuss-Borst, M. Low Carb and Ketogenic Diets Increase Quality of Life, Physical Performance, Body Composition, and Metabolic Health of Women with Breast Cancer. Nutrients 2021, 13, 1029. [Google Scholar] [CrossRef] [Scilit]
- Colman, R.J.; Anderson, R.M.; Johnson, S.C.; Kastman, E.K.; Kosmatka, K.J.; Beasley, T.M.; Allison, D.B.; Cruzen, C.; Simmons, H.A.; Kemnitz, J.W.; et al. Caloric restriction delays disease onset and mortality in rhesus monkeys. Science 2009, 325, 201–204. [Google Scholar] [CrossRef] [Scilit]
- Mattison, J.A.; Roth, G.S.; Beasley, T.M.; Tilmont, E.M.; Handy, A.M.; Herbert, R.L.; Longo, D.L.; Allison, D.B.; Young, J.E.; Bryant, M.; et al. Impact of caloric restriction on health and survival in rhesus monkeys from the NIA study. Nature 2012, 489, 318–321. [Google Scholar] [CrossRef] [Scilit]
- Pietrocola, F.; Pol, J.; Vacchelli, E.; Baracco, E.E.; Levesque, S.; Castoldi, F.; Maiuri, M.C.; Madeo, F.; Kroemer, G. Autophagy induction for the treatment of cancer. Autophagy 2016, 12, 1962–1964. [Google Scholar] [CrossRef] [Scilit]
- Pietrocola, F.; Pol, J.; Vacchelli, E.; Rao, S.; Enot, D.P.; Baracco, E.E.; Levesuq, S.; Castoldi, F.; Jacquelot, N.; Yamazaki, T.; et al. Caloric Restriction Mimetics Enhance Anticancer Immunosurveillance. Cancer Cell 2016, 30, 147–160. [Google Scholar] [CrossRef] [Scilit]
- Brandhorst, S.; Choi, I.Y.; Wei, M.; Cheng, C.W.; Sedrakyan, S.; Navarrete, G.; Dubeau, L.; Yap, L.P.; Park, R.; Vinciguerra, M.; et al. A Periodic Diet that Mimics Fasting Promotes Multi-System Regeneration, Enhanced Cognitive Performance, and Healthspan. Cell Metab. 2015, 22, 86–99. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muscaritoli, M.; Arends, J.; Bachmann, P.; Baracos, V.; Barthelemy, N.; Bertz, H.; Bozzetti, F.; Hütterer, E.; Isenring, E.; Kaasa, S.; et al. ESPEN practical guideline: Clinical Nutrition in cancer. Clin. Nutr. 2021, 40, 2898–2913. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Prado, C.M.; Laviano, A.; Gillis, C.; Sung, A.D.; Gardner, M.; Yalcin, S.; Dixon, S.; Newman, S.M.; Bastasch, M.D.; Sauer, A.C.; et al. Examining guidelines and new evidence in oncology nutrition: A position paper on gaps and opportunities in multimodal approaches to improve patient care. Support. Care Cancer 2022, 30, 3073–3083. [Google Scholar] [CrossRef] [Scilit]
- Tajan, M.; Vousden, K.H. Dietary Approaches to Cancer Therapy. Cancer Cell 2020, 37, 767–785. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Killeen, I.D.; Moore, N.W. Fertilization and survival of fertilized eggs in the ewe following surgical insemination at various times after the onse of oestrus. Aust. J. Biol. Sci. 1970, 23, 1279–1287. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vineis, P.; Wild, C.P. Global cancer patterns: Causes and prevention. Lancet 2014, 383, 549–557. [Google Scholar] [CrossRef] [Scilit]
- Fowke, J.H.; Chung, F.-L.; Jin, F.; Qi, D.; Cai, Q.; Conaway, C.; Cheng, J.-R.; Shu, X.-O.; Gao, Y.-T.; Zheng, W. Urinary isothiocyanate levels, brassica, and human breast cancer. Cancer Res. 2003, 63, 3980–3986. [Google Scholar]
- Cohen, J.H.; Kristal, A.; Stanford, J.L. Fruit and vegetable intakes and prostate cancer risk. J. Natl. Cancer Inst. 2000, 92, 61–68. [Google Scholar] [CrossRef] [Scilit]
- Steck, S.E.; Murphy, E.A. Dietary patterns and cancer risk. Nat. Rev. Cancer 2020, 20, 125–138. [Google Scholar] [CrossRef] [Scilit]
- Trichopoulou, A.; Critselis, E. Mediterranean diet and longevity. Eur. J. Cancer Prev. 2004, 13, 453–456. [Google Scholar] [CrossRef] [Scilit]
- UNESCO. Representative List of the Intangible Cultural Heritage of Humanity; UNESCO: Paris, France, 2010. [Google Scholar]
- Silva, T.R.; Oppermann, K.; Reis, F.M.; Spritzer, P.M. Nutrition in Menopausal Women: A Narrative Review. Nutrients 2021, 13, 2149. [Google Scholar] [CrossRef] [Scilit]
- Mentella, M.C.; Scaldaferri, F.; Ricci, C.; Gasbarrini, A.; Miggiano, G.A.D. Cancer and Mediterranean Diet: A Review. Nutrients 2019, 11, 2059. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Agnoli, C.; Grioni, S.; Sieri, S.; Palli, D.; Masala, G.; Sacerdote, C.; Vineis, P.; Tumino, R.; Giurdanella, M.C.; Pala, V.; et al. Italian Mediterranean Index and risk of colorectal cancer in the Italian section of the EPIC cohort. Int. J. Cancer 2013, 132, 1404–1411. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Trichopoulou, A.; Costacou, T.; Bamia, C.; Trichopoulos, D. Adherence to a Mediterranean diet and survival in a Greek population. N. Engl. J. Med. 2003, 348, 2599–2608. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fung, T.T.; Hu, F.B.; McCullough, M.L.; Newby, P.K.; Willett, W.C.; Holmes, M.D. Diet quality is associated with the risk of estrogen receptor-negative breast cancer in postmenopausal women. J. Nutr. 2006, 136, 466–472. [Google Scholar] [CrossRef] [Scilit]
- Trichopoulou, A.; Orfanos, P.; Norat, T.; Bueno-De-Mesquita, B.; Ocké, M.C.; Peeters, P.H.; Van Der Schouw, Y.T.; Boeing, H.; Hoffmann, K.; Boffetta, P.; et al. Modified Mediterranean diet and survival: EPIC-elderly prospective cohort study. BMJ 2005, 330, 991. [Google Scholar] [CrossRef] [Scilit]
- Gerber, M.; Hoffman, R. The Mediterranean diet: Health, science and society. Br. J. Nutr. 2015, 113, S4–S10. [Google Scholar] [CrossRef] [Scilit]
- Stefler, D.; Malyutina, S.; Kubinova, R.; Pajak, A.; Peasey, A.; Pikhart, H.; Brunner, E.J.; Bobak, M. Mediterranean diet score and total and cardiovascular mortality in Eastern Europe: The HAPIEE study. Eur. J. Nutr. 2017, 56, 421–429. [Google Scholar] [CrossRef] [Scilit]
- Avgerinos, K.I.; Spyrou, N.; Mantzoros, C.S.; Dalamaga, M. Obesity and cancer risk: Emerging biological mechanisms and perspectives. Metabolism. 2019, 92, 121–135. [Google Scholar] [CrossRef] [Scilit]
- Cox, D.N.; Anderson, A.S.; Reynolds, J.; McKellar, S.; Lean, M.E.J.; Mela, D. Take Five, a nutrition education intervention to increase fruit and vegetable intakes: Impact on consumer choice and nutrient intakes. Br. J. Nutr. 1998, 80, 123–131. [Google Scholar] [CrossRef] [Scilit]
- Estruch, R.; Ros, E. The role of the Mediterranean diet on weight loss and obesity-related diseases. Rev Endocr. Metab. Disord. 2020, 21, 315–327. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kaiser, A.K.; Brown, A.W.; Brown, M.M.B.; Shikany, J.M.; Mattes, R.D.; Allison, D.B. Increased fruit and vegetable intake has no discernible effect on weight loss: A systematic review and meta-analysis. Am. J. Clin. Nutr. 2014, 100, 567–576. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Turati, F.; Carioli, G.; Bravi, F.; Ferraroni, M.; Serraino, D.; Montella, M.; Giacosa, A.; Toffolutti, F.; Negri, E.; Levi, F.; et al. Mediterranean Diet and Breast Cancer Risk. Nutrient 2018, 10, 326. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brandt, P.A.V.D.; Schulpen, M. Mediterranean diet adherence and risk of postmenopausal breast cancer: Results of a cohort study and meta-analysis. Int. J. Cancer 2017, 140, 2220–2231. [Google Scholar] [CrossRef] [Scilit]
- Castelló, A.; Researchers, O.B.O.M.-S.; Amiano, P.; de Larrea, N.F.; Martín, V.; Alonso, M.H.; Castaño-Vinyals, G.; Pérez-Gómez, B.; Olmedo-Requena, R.; Guevara, M.; et al. Low adherence to the western and high adherence to the mediterranean dietary patterns could prevent colorectal cancer. Eur. J. Nutr. 2019, 58, 1495–1505. [Google Scholar] [CrossRef] [Scilit]
- Ratjen, I.; Schafmayer, C.; di Giuseppe, R.; Waniek, S.; Plachta-Danielzik, S.; Koch, M.; Nöthlings, U.; Hampe, J.; Schlesinger, S.; Lieb, W. Postdiagnostic Mediterranean and Healthy Nordic Dietary Patterns Are Inversely Associated with All-Cause Mortality in Long-Term Colorectal Cancer Survivors. J. Nutr. 2017, 147, 636–644. [Google Scholar] [CrossRef] [Scilit]
- Augustin, L.S.A.; Gallus, S.; Negri, E.; La Vecchia, C. Glycemic index, glycemic load and risk of gastric cancer. Ann. Oncol. 2004, 15, 581–584. [Google Scholar] [CrossRef] [Scilit]
- Lucenteforte, E.; Scita, V.; Bosetti, C.; Bertuccio, P.; Negri, E.; La Vecchia, C. Food groups and alcoholic beverages and the risk of stomach cancer: A case-control study in Italy. Nutr. Cancer. 2008, 60, 577–584. [Google Scholar] [CrossRef] [Scilit]
- Praud, D.; Bertuccio, P.; Bosetti, C.; Turati, F.; Ferraroni, M.; La Vecchia, C. Adherence to the Mediterranean diet and gastric cancer risk in Italy. Int. J. Cancer 2014, 134, 2935–2941. [Google Scholar] [CrossRef] [Scilit]
- Kenfield, S.A.; Dupre, N.; Richman, E.L.; Stampfer, M.J.; Chan, J.M.; Giovannucci, E.L. Mediterranean diet and prostate cancer risk and mortality in the Health Professionals Follow-up Study. Eur. Urol. 2014, 65, 887–894. [Google Scholar] [CrossRef] [Scilit]
- Russo, G.I.; Solinas, T.; Urzì, D.; Privitera, S.; Campisi, D.; Cocci, A.; Carini, M.; Madonia, M.; Cimino, S.; Morgia, G. Adherence to Mediterranean diet and prostate cancer risk in Sicily: Population-based case-control study. Int. J. Impot. Res. 2019, 31, 269–275. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schneider, L.; Su, L.J.; Arab, L.; Bensen, J.T.; Farnan, L.; Fontham, E.T.H.; Song, L.; Hussey, J.; Merchant, A.T.; Mohler, J.L.; et al. Dietary patterns based on the Mediterranean diet and DASH diet are inversely associated with high aggressive prostate cancer in PCaP. Ann. Epidemiol. 2019, 29, 16–22.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Castellana, M.; Biacchi, E.; Procino, F.; Casanueva, F.F.; Trimboli, P. Very-low-calorie ketogenic diet for the management of obesity, overweight and related disorders. Minerva Endocrinol. 2021, 46, 161–167. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Celik, O.; Yildiz, B.O. Obesity and physical exercise. Minerva Endocrinol. 2021, 46, 131–144. [Google Scholar] [CrossRef]
- Formenti, A.M. Obesity: Towards a personalized management of a disease with severe clinical implication. Minerva Endocrinol. 2021, 46, 127–130. [Google Scholar] [CrossRef] [Scilit]
- Özyildirim, C.; Uçar, A. An alternative approach to obesity treatment: Intermittent fasting. Minerva Endocrinol. 2021. [Google Scholar] [CrossRef] [Scilit]
- Muscogiuri, G.; Barrea, L.; Laudisio, D.; Pugliese, G.; Salzano, C.; Savastano, S.; Colao, A. The management of very low-calorie ketogenic diet in obesity outpatient clinic: A practical guide. J. Transl. Med. 2019, 17, 356. [Google Scholar] [CrossRef] [Scilit]
- Nebeling, L.C.; Miraldi, F.; Shurin, S.B.; Lerner, E. Effects of a ketogenic diet on tumor metabolism and nutritional status in pediatric oncology patients: Two case reports. J. Am. Coll. Nutr. 1995, 14, 202–208. [Google Scholar] [CrossRef] [Scilit]
- Rieger, J.; Bahr, O.; Maurer, G.D.; Hattingen, E.; Franz, K.; Brucker, D.; Walenta, S.; Kammerer, U.; Coy, J.F.; Weller, M.; et al. ERGO: A pilot study of ketogenic diet in recurrent glioblastoma. Int. J. Oncol. 2014, 44, 1843–1852. [Google Scholar] [CrossRef] [Scilit]
- Iyikesici, M.S. Feasibility study of metabolically supported chemotherapy with weekly carboplatin/paclitaxel combined with ketogenic diet, hyperthermia and hyperbaric oxygen therapy in metastatic non-small cell lung cancer. Int. J. Hyperth. 2019, 36, 446–455. [Google Scholar] [CrossRef] [Scilit]
- Cohen, C.W.; Fontaine, K.R.; Arend, R.C.; Soleymani, T.; Gower, B.A. Favorable Effects of a Ketogenic Diet on Physical Function, Perceived Energy, and Food Cravings in Women with Ovarian or Endometrial Cancer: A Randomized, Controlled Trial. Nutrients 2018, 10, 1187. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iyikesici, M.S. Long-Term Survival Outcomes of Metabolically Supported Chemotherapy with Gemcitabine-Based or FOLFIRINOX Regimen Combined with Ketogenic Diet, Hyperthermia, and Hyperbaric Oxygen Therapy in Metastatic Pancreatic Cancer. Complement Med. Res. 2020, 27, 31–39. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iyikesici, M.S. Survival outcomes of metabolically supported chemotherapy combined with ketogenic diet, hyperthermia, and hyperbaric oxygen therapy in advanced gastric cancer. Niger. J. Clin. Pract. 2020, 23, 734–740. [Google Scholar] [PubMed]
- (IFIC) IFIC. 2020 Food and Health Survey. Available online: https://ific.org/media-information/press-releases/2020-food-and-health-survey/ (accessed on 15 June 2022).
- Clifton, K.K.; Ma, C.X.; Fontana, L.; Peterson, L.L. Intermittent fasting in the prevention and treatment of cancer. CA Cancer J Clin. 2021, 71, 527–546. [Google Scholar] [CrossRef] [Scilit]
- Harvie, M.N.; Pegington, M.; Mattson, M.P.; Frystyk, J.; Dillon, B.; Evans, G.; Cuzick, J.; A Jebb, S.; Martin, B.; Cutler, R.G.; et al. The effects of intermittent or continuous energy restriction on weight loss and metabolic disease risk markers: A randomized trial in young overweight women. Int. J. Obes. 2011, 35, 714–727. [Google Scholar] [CrossRef] [Scilit]
- Tinsley, G.M.; La Bounty, P.M. Effects of intermittent fasting on body composition and clinical health markers in humans. Nutr. Rev. 2015, 73, 661–674. [Google Scholar] [CrossRef] [Scilit]
- Rothschild, J.; Hoddy, K.K.; Jambazian, P.; Varady, K.A. Time-restricted feeding and risk of metabolic disease: A review of human and animal studies. Nutr. Rev. 2014, 72, 308–318. [Google Scholar] [CrossRef] [Scilit]
- Cho, Y.; Hong, N.; Kim, K.-W.; Cho, S.J.; Lee, M.; Lee, Y.-H.; Lee, Y.-H.; Kang, E.S.; Cha, B.-S.; Lee, B.-W. The Effectiveness of Intermittent Fasting to Reduce Body Mass Index and Glucose Metabolism: A Systematic Review and Meta-Analysis. J. Clin. Med. 2019, 8, 1645. [Google Scholar] [CrossRef] [Scilit]
- Grossmann, M.E.; Cleary, M.P. The balance between leptin and adiponectin in the control of carcinogenesis-focus on mammary tumorigenesis. Biochimie 2012, 94, 2164–2171. [Google Scholar] [CrossRef] [Scilit]
- Hutchison, A.T.; Regmi, P.; Manoogian, E.N.; Fleischer, J.G.; Wittert, G.A.; Panda, S.; Heilbronn, L.K. Time-Restricted Feeding Improves Glucose Tolerance in Men at Risk for Type 2 Diabetes: A Randomized Crossover Trial. Obesity 2019, 27, 724–732. [Google Scholar] [CrossRef] [Scilit]
- Jamshed, H.; Beyl, R.A.; della Manna, D.L.; Yang, E.S.; Ravussin, E.; Peterson, C.M. Early Time-Restricted Feeding Improves 24-Hour Glucose Levels and Affects Markers of the Circadian Clock, Aging, and Autophagy in Humans. Nutrients 2019, 11, 1234. [Google Scholar] [CrossRef] [Scilit]
- Sutton, E.F.; Beyl, R.; Early, K.S.; Cefalu, W.T.; Ravussin, E.; Peterson, C.M. Early Time-Restricted Feeding Improves Insulin Sensitivity, Blood Pressure, and Oxidative Stress Even without Weight Loss in Men with Prediabetes. Cell. Metab. 2018, 27, 1212–1221.e3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Harvie, M.N.; Sims, A.H.; Pegington, M.; Spence, K.; Mitchell, A.; Vaughan, A.A.; Allwood, J.W.; Xu, Y.; Rattray, N.J.W.; Goodacre, R.; et al. Intermittent energy restriction induces changes in breast gene expression and systemic metabolism. Breast Cancer Res. 2016, 18, 57. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hernaez, A.; Estruch, R. The Mediterranean Diet and Cancer: What Do Human and Molecular Studies Have to Say about It? Nutrients 2019, 11, 2155. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Corella, D.; Coltell, O.; Macian, F.; Ordovás, J.M. Advances in Understanding the Molecular Basis of the Mediterranean Diet Effect. Annu. Rev. Food Sci. Technol. 2018, 9, 227–249. [Google Scholar] [CrossRef] [Scilit]
- Chen, Y.C.; Hunter, D.J. Molecular epidemiology of cancer. CA Cancer J. Clin. 2005, 55, 45–54. [Google Scholar] [CrossRef] [Scilit]
- Lyons, C.L.; Roche, H.M. Nutritional Modulation of AMPK-Impact upon Metabolic-Inflammation. Int. J. Mol. Sci. 2018, 19, 3092. [Google Scholar] [CrossRef] [Scilit]
- Ma, W.W.; Adjei, A.A. Novel agents on the horizon for cancer therapy. CA Cancer J. Clin. 2009, 59, 111–137. [Google Scholar] [CrossRef] [Scilit]
- Zhang, J.; Wang, X.; Vikash, V.; Ye, Q.; Wu, D.; Liu, Y.; Dong, W. ROS and ROS-Mediated Cellular Signaling. Oxid. Med. Cell. Longev. 2016, 2016, 4350965. [Google Scholar] [CrossRef] [Scilit]
- Miron, A.; Aprotosoaie, A.C.; Trifan, A.; Xiao, J. Flavonoids as modulators of metabolic enzymes and drug transporters. Ann. N.Y. Acad. Sci. 2017, 1398, 152–167. [Google Scholar] [CrossRef] [Scilit]
- Bultman, S.J. Interplay between diet, gut microbiota, epigenetic events, and colorectal cancer. Mol. Nutr. Food Res. 2017, 61, 1500902. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sivaprakasam, S.; Prasad, P.D.; Singh, N. Benefits of short-chain fatty acids and their receptors in inflammation and carcinogenesis. Pharmacol. Ther. 2016, 164, 144–151. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jacobs, D.R., Jr.; Gross, M.D.; Tapsell, L.C. Food synergy: An operational concept for understanding nutrition. Am. J. Clin. Nutr. 2009, 89, 1543S–1548S. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lăcătușu, C.-M.; Grigorescu, E.-D.; Floria, M.; Onofriescu, A.; Mihai, B.-M. The Mediterranean Diet: From an Environment-Driven Food Culture to an Emerging Medical Prescription. Int. J. Environ. Res. Public Health 2019, 16, 942. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tapiero, H.; Ba, G.N.; Couvreur, P.; Tew, K.D. Polyunsaturated fatty acids (PUFA) and eicosanoids in human health and pathologies. Biomed. Pharmacother. 2002, 56, 215–222. [Google Scholar] [CrossRef] [Scilit]
- Amor, S.; Châlons, P.; Aires, V.; Delmas, D. Polyphenol Extracts from Red Wine and Grapevine: Potential Effects on Cancers. Diseases 2018, 6, 106. [Google Scholar] [CrossRef] [Scilit]
- Barrea, L.; Caprio, M.; Tuccinardi, D.; Moriconi, E.; Di Renzo, L.; Muscogiuri, G.; Colao, A.; Savastano, S.; Obesity Programs of nutrition, Education, Research and Assessment (OPERA) group. Could ketogenic diet “starve” cancer? Emerging evidence. Crit. Rev. Food Sci. Nutr. 2022, 62, 1800–1821. [Google Scholar] [CrossRef] [Scilit]
- Frezza, C. Metabolism and cancer: The future is now. Br. J. Cancer. 2020, 122, 133–135. [Google Scholar] [CrossRef] [Scilit]
- Kobliakov, V.A. The Mechanisms of Regulation of Aerobic Glycolysis (Warburg Effect) by Oncoproteins in Carcinogenesis. Biochemistry 2019, 84, 1117–1128. [Google Scholar] [CrossRef] [Scilit]
- Klement, R.J. The emerging role of ketogenic diets in cancer treatment. Curr. Opin. Clin. Nutr. Metab. Care. 2019, 22, 129–134. [Google Scholar] [CrossRef] [Scilit]
- Sengupta, S.; Peterson, T.R.; Laplante, M.; Oh, S.; Sabatini, D.M. mTORC1 controls fasting-induced ketogenesis and its modulation by ageing. Nature 2010, 468, 1100–1104. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tran, Q.; Lee, H.; Kim, C.; Kong, G.; Gong, N.; Kwon, S.H.; Park, J.; Kim, S.-H.; Park, J. Revisiting the Warburg Effect: Diet-Based Strategies for Cancer Prevention. Biomed. Res. Int. 2020, 2020, 8105735. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lu, Y.; Yang, Y.Y.; Zhou, M.W.; Liu, N.; Xing, H.Y.; Liu, X.X.; Li, F. Ketogenic diet attenuates oxidative stress and inflammation after spinal cord injury by activating Nrf2 and suppressing the NF-kappaB signaling pathways. Neurosci. Lett. 2018, 683, 13–18. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Woolf, E.C.; Curley, K.L.; Liu, Q.; Turner, G.H.; Charlton, J.A.; Preul, M.C.; Scheck, A.C. The Ketogenic Diet Alters the Hypoxic Response and Affects Expression of Proteins Associated with Angiogenesis, Invasive Potential and Vascular Permeability in a Mouse Glioma Model. PLoS ONE 2015, 10, e0130357. [Google Scholar]
- Zhang, N.; Liu, C.; Jin, L.; Zhang, R.; Wang, T.; Wang, Q.; Chen, J.; Yang, F.; Siebert, H.C.; Zheng, X. Ketogenic Diet Elicits Antitumor Properties through Inducing Oxidative Stress, Inhibiting MMP-9 Expression, and Rebalancing M1/M2 Tumor-Associated Macrophage Phenotype in a Mouse Model of Colon Cancer. J. Agric. Food Chem. 2020, 68, 11182–11196. [Google Scholar] [CrossRef] [Scilit]
- Zahra, K.; Dey, T.; Ashish; Mishra, S.P.; Pandey, U. Pyruvate Kinase M2 and Cancer: The Role of PKM2 in Promoting Tumorigenesis. Front Oncol. 2020, 10, 159. [Google Scholar] [CrossRef] [Scilit]
- Weber, D.D.; Aminzadeh-Gohari, S.; Tulipan, J.; Catalano, L.; Feichtinger, R.G.; Kofler, B. Ketogenic diet in the treatment of cancer-Where do we stand? Mol. Metab. 2020, 33, 102–121. [Google Scholar] [CrossRef] [Scilit]
- Lee, Y.-K.; Park, S.Y.; Kim, Y.-M.; Lee, W.S.; Park, O.J. AMP kinase/cyclooxygenase-2 pathway regulates proliferation and apoptosis of cancer cells treated with quercetin. Exp. Mol. Med. 2009, 41, 201–207. [Google Scholar] [CrossRef] [Scilit]
- Li, W.; Saud, S.M.; Young, M.R.; Chen, G.; Hua, B. Targeting AMPK for cancer prevention and treatment. Oncotarget 2015, 6, 7365–7378. [Google Scholar] [CrossRef] [Scilit]
- Longo, V.D.; Fontana, L. Calorie restriction and cancer prevention: Metabolic and molecular mechanisms. Trends Pharmacol. Sci. 2010, 31, 89–98. [Google Scholar] [CrossRef] [Scilit]
- Di Biase, S.; Shim, H.S.; Kim, K.H.; Vinciguerra, M.; Rappa, F.; Wei, M.; Brandhorst, S.; Cappello, F.; Mirzaei, H.; Lee, C.; et al. Fasting regulates EGR1 and protects from glucose- and dexamethasone-dependent sensitization to chemotherapy. PLoS Biol. 2017, 15, e2001951. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salvadori, G.; Mirisola, M.G.; Longo, V.D. Intermittent and Periodic Fasting, Hormones, and Cancer Prevention. Cancers 2021, 13, 4587. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cheng, C.W.; Adams, G.B.; Perin, L.; Wei, M.; Zhou, X.; Lam, B.S.; Da Sacco, S.; Mirisola, M.; Quinn, D.I.; Dorff, T.B. Prolonged fasting reduces IGF-1/PKA to promote hematopoietic-stem-cell-based regeneration and reverse immunosuppression. Cell Stem Cell 2014, 14, 810–823. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, C.; Safdie, F.M.; Raffaghello, L.; Wei, M.; Madia, F.; Parrella, E.; Hwang, D.; Cohen, P.; Bianchi, G.; Longo, V.D. Reduced levels of IGF-I mediate differential protection of normal and cancer cells in response to fasting and improve chemotherapeutic index. Cancer Res. 2010, 70, 1564–1572. [Google Scholar] [CrossRef] [Scilit]
- de Groot, S.; Pijl, H.; van der Hoeven, J.J.M.; Kroep, J.R. Effects of short-term fasting on cancer treatment. J. Exp. Clin. Cancer Res. 2019, 38, 209. [Google Scholar] [CrossRef] [Scilit]
- Kimura, I.; Inoue, D.; Maeda, T.; Hara, T.; Ichimura, A.; Miyauchi, S.; Kobayashi, M.; Hirasawa, A.; Tsujimoto, G. Short-chain fatty acids and ketones directly regulate sympathetic nervous system via G protein-coupled receptor 41 (GPR41). Proc. Natl. Acad. Sci. USA 2011, 108, 8030–8035. [Google Scholar] [CrossRef] [Scilit]
- Antunes, F.; Erustes, A.G.; Costa, A.J.; Nascimento, A.C.; Bincoletto, C.; Ureshino, R.P.; Pereira, G.J.S.; Smaili, S.S. Autophagy and intermittent fasting: The connection for cancer therapy? Clinics 2018, 73, e814s. [Google Scholar] [CrossRef] [Scilit]
- Aly, S.M. Role of intermittent fasting on improving health and reducing diseases. Int. J. Health Sci. 2014, 8, 5–6. [Google Scholar] [CrossRef] [Scilit]
- Pobłocki, J.; Jasińska, A.; Syrenicz, A.; Andrysiak-Mamos, E.; Szczuko, M. The Neuroendocrine Neoplasms of the Digestive Tract: Diagnosis, Treatment and Nutrition. Nutrients 2020, 12, 1437. [Google Scholar] [CrossRef] [Scilit]
- Barrea, L.; Muscogiuri, G.; Modica, R.; Altieri, B.; Pugliese, G.; Minotta, R.; Faggiano, A.; Colao, A.; Savastano, S. Cardio-Metabolic Indices and Metabolic Syndrome as Predictors of Clinical Severity of Gastroenteropancreatic Neuroendocrine Tumors. Front. Endocrinol. 2021, 12, 649496. [Google Scholar] [CrossRef] [Scilit]
- Laing, E.; Gough, K.; Krishnasamy, M.; Michael, M.; Kiss, N. Prevalence of malnutrition and nutrition-related complications in patients with gastroenteropancreatic neuroendocrine tumours. J. Neuroendocrinol. 2022, 34, e13116. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- A Qureshi, S.; Burch, N.; Druce, M.; Hattersley, A.; Khan, S.; Gopalakrishnan, K.; Darby, C.; Wong, J.L.H.; Davies, L.; Fletcher, S.; et al. Screening for malnutrition in patients with gastro-entero-pancreatic neuroendocrine tumours: A cross-sectional study. BMJ Open 2016, 6, e010765. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gallo, M.; Muscogiuri, G.; Pizza, G.; Ruggeri, R.M.; Barrea, L.; Faggiano, A.; Colao, A. The management of neuroendocrine tumours: A nutritional viewpoint. Crit. Rev. Food Sci. Nutr. 2019, 59, 1046–1057. [Google Scholar] [CrossRef] [Scilit]
- Altieri, B.; Barrea, L.; Modica, R.; Muscogiuri, G.; Savastano, S.; Colao, A.; Faggiano, A. Nutrition and neuroendocrine tumors: An update of the literature. Rev. Endocr. Metab. Disord. 2018, 19, 159–167. [Google Scholar] [CrossRef] [Scilit]
- Leoncini, E.; Carioli, G.; La Vecchia, C.; Boccia, S.; Rindi, G. Risk factors for neuroendocrine neoplasms: A systematic review and meta-analysis. Ann. Oncol. 2016, 27, 68–81. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fan, P.; Song, P.; Li, L.; Huang, C.; Chen, J.; Yang, W.; Qiao, S.; Wu, G.; Zhang, G.; Ma, X. Roles of Biogenic Amines in Intestinal Signaling. Curr. Protein Pept. Sci. 2017, 18, 532–540. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fortes, C.; Mastroeni, S.; Melchi, F.; A Pilla, M.; Antonelli, G.; Camaioni, D.; Alotto, M.; Pasquini, P. A protective effect of the Mediterranean diet for cutaneous melanoma. Int. J. Epidemiol. 2008, 37, 1018–1029. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Artale, S.; Barzaghi, S.; Grillo, N.; Maggi, C.; Lepori, S.; Butti, C.; Bovio, A.; Barbarini, L.; Colombo, A.; Zanlorenzi, L.; et al. Role of Diet in the Management of Carcinoid Syndrome: Clinical Recommendations for Nutrition in Patients with Neuroendocrine Tumors. Nutr. Cancer 2022, 74, 2–11. [Google Scholar] [CrossRef] [Scilit]
- Cohen, C.W.; Fontaine, K.R.; Arend, R.C.; Gower, B.A. A Ketogenic Diet Is Acceptable in Women with Ovarian and Endometrial Cancer and Has No Adverse Effects on Blood Lipids: A Randomized, Controlled Trial. Nutr. Cancer 2020, 72, 584–594. [Google Scholar] [CrossRef] [Scilit]
- Klement, R.J.; Bandyopadhyay, P.S.; Champ, C.E.; Walach, H. Application of Bayesian evidence synthesis to modelling the effect of ketogenic therapy on survival of high grade glioma patients. Theor. Biol. Med. Model. 2018, 15, 12. [Google Scholar] [CrossRef] [Scilit]
- Racker, E. Bioenergetics and the problem of tumor growth. Am. Sci. 1972, 60, 56–63. [Google Scholar] [PubMed]
- Boden, G.; Sargrad, K.; Homko, C.; Mozzoli, M.; Stein, T.P. Effect of a low-carbohydrate diet on appetite, blood glucose levels, and insulin resistance in obese patients with type 2 diabetes. Ann. Intern. Med. 2005, 142, 403–411. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Adeva-Andany, M.M.; Funcasta-Calderón, R.; Fernández-Fernández, C.; Castro-Quintela, E.; Carneiro-Freire, N. Metabolic effects of glucagon in humans. J. Clin. Transl. Endocrinol. 2019, 15, 45–53. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fine, E.J.; Segal-Isaacson, C.J.; Feinman, R.D.; Herszkopf, S.; Romano, M.C.; Tomuta, N.; Bontempo, A.F.; Negassa, A.; Sparano, J.A. Targeting insulin inhibition as a metabolic therapy in advanced cancer: A pilot safety and feasibility dietary trial in 10 patients. Nutrition 2012, 28, 1028–1035. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bianchi, G.; Martella, R.; Ravera, S.; Marini, C.; Capitanio, S.; Orengo, A.; Emionite, L.; Lavarello, C.; Amaro, A.; Petretto, A.; et al. Fasting induces anti-Warburg effect that increases respiration but reduces ATP-synthesis to promote apoptosis in colon cancer models. Oncotarget 2015, 6, 11806–11819. [Google Scholar] [CrossRef] [Scilit]
- Chen, X.; Lin, X.; Li, M. Comprehensive modulation of tumor progression and regression with periodic fasting and refeeding circles via boosting IGFBP-3 loops and NK responses. Endocrinology 2012, 153, 4622–4632. [Google Scholar] [CrossRef] [Scilit]
- Lauby-Secretan, B.; Scoccianti, C.; Loomis, D.; Grosse, Y.; Bianchini, F.; Straif, K. Body Fatness and Cancer--Viewpoint of the IARC Working Group. N. Engl. J. Med. 2016, 375, 794–798. [Google Scholar] [CrossRef] [Scilit]
- Sagar, V.M.; Cooper, S.C.; Johnson, J.; Shetty, S.; Shah, T. Gastrointestinal manifestations of neuroendocrine tumours: Their investigation and management. Postgrad. Med. J. 2017, 93, 494–497. [Google Scholar] [CrossRef] [Scilit]
- San Mauro Martin, I.; Brachero, S.; Garicano Vilar, E. Histamine intolerance and dietary management: A complete review. Allergol. Immunopathol 2016, 44, 475–483. [Google Scholar] [CrossRef] [Scilit]
- Naraev, B.G.; Halland, M.; Halperin, D.M.; Purvis, A.J.; O’Dorisio, T.M.; Halfdanarson, T. Management of Diarrhea in Patients With Carcinoid Syndrome. Pancreas 2019, 48, 961–972. [Google Scholar] [CrossRef] [Scilit]
- Gutiérrez-Díaz, I.; Fernández-Navarro, T.; Sánchez, B.; Margolles, A.; González, S. Mediterranean diet and faecal microbiota: A transversal study. Food Funct. 2016, 7, 2347–2356. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Austin, G.L.; Dalton, C.B.; Hu, Y.; Morris, C.B.; Hankins, J.; Weinland, S.R.; Westman, E.C.; Yancy, W.S.; Drossman, D.A. A very low-carbohydrate diet improves symptoms and quality of life in diarrhea-predominant irritable bowel syndrome. Clin. Gastroenterol Hepatol. 2009, 7, 706–708.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gabel, K.; Cares, K.; Varady, K.; Gadi, V.; Tussing-Humphreys, L. Tussing-Humphreys, L. Current Evidence and Directions for Intermittent Fasting During Cancer Chemotherapy. Adv. Nutr. 2021, 12, 667–680. [Google Scholar]
- Gibson, R.J.; Keefe, D.M.K. Cancer chemotherapy-induced diarrhoea and constipation: Mechanisms of damage and prevention strategies. Support. Care Cancer 2006, 14, 890–900. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Almodallal, Y.; Cook, K.; Lammert, L.M.; Lee, M.; Le-Rademacher, J.G.; Jatoi, A. Can older patients adopt and maintain a ketogenic diet? An observational study in support of clinical trials in older patients. Medicine 2021, 100, e28033. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bellini, M.; Tonarelli, S.; Barracca, F.; Rettura, F.; Pancetti, A.; Ceccarelli, L.; Ricchiuti, A.; Costa, F.; Bortoli, N.; Marchi, S.; et al. Chronic Constipation: Is a Nutritional Approach Reasonable? Nutrients 2021, 13, 3386. [Google Scholar] [CrossRef] [Scilit]
- Hébuterne, X.; Lemarié, E.; Michallet, M.; De Montreuil, C.B.; Schneider, S.; Goldwasser, F. Prevalence of malnutrition and current use of nutrition support in patients with cancer. J. Parenter. Enteral. Nutr. 2014, 38, 196–204. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bossi, P.; Delrio, P.; Mascheroni, A.; Zanetti, M. The Spectrum of Malnutrition/Cachexia/Sarcopenia in Oncology According to Different Cancer Types and Settings: A Narrative Review. Nutrients 2021, 13, 1980. [Google Scholar] [CrossRef] [Scilit]
- Bouma, G.; Van Faassen, M.; Kats-Ugurlu, G.; de Vries, E.G.; Kema, I.P.; Walenkamp, A.M.E. Niacin (Vitamin B3) Supplementation in Patients with Serotonin-Producing Neuroendocrine Tumor. Neuroendocrinology 2016, 103, 489–494. [Google Scholar] [CrossRef] [Scilit]
- Fearon, K.C.; Borland, W.; Preston, T.; Tisdale, M.J.; Shenkin, A.; Calman, K.C. Cancer cachexia: Influence of systemic ketosis on substrate levels and nitrogen metabolism. Am. J. Clin. Nutr. 1988, 47, 42–48. [Google Scholar] [CrossRef] [Scilit]
- Falconi, M.; Eriksson, B.; Kaltsas, G.; Bartsch, D.K.; Capdevila, J.; Caplin, M.; Kos-Kudla, B.; Kwekkeboom, D.; Rindi, G.; Klöppel, G.; et al. ENETS Consensus Guidelines Update for the Management of Patients with Functional Pancreatic Neuroendocrine Tumors and Non-Functional Pancreatic Neuroendocrine Tumors. Neuroendocrinology 2016, 103, 153–171. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jones, L.W.; Demark-Wahnefried, W. Diet, exercise, and complementary therapies after primary treatment for cancer. Lancet. Oncol. 2006, 7, 1017–1026. [Google Scholar] [CrossRef] [Scilit]
- American Diabetes, A. 9. Pharmacologic Approaches to Glycemic Treatment: Standards of Medical Care in Diabetes-2021. Diabetes Care. 2021, 44 (Suppl. 1), S111–S124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tagde, P.; Tagde, S.; Bhattacharya, T.; Tagde, P.; Akter, R.; Rahman, M.H. Multifaceted Effects of Intermittent Fasting on the Treatment and Prevention of Diabetes, Cancer, Obesity or Other Chronic Diseases. Curr. Diabetes Rev. 2022, 18, e131221198789. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lamarca, A.; McCallum, L.; Nuttall, C.; Barriuso, J.; Backen, A.; Frizziero, M.; Leon, R.; Mansoor, W.; McNamara, M.G.; Hubner, R.A.; et al. Somatostatin analogue-induced pancreatic exocrine insufficiency in patients with neuroendocrine tumors: Results of a prospective observational study. Expert Rev. Gastroenterol. Hepatol. 2018, 12, 723–731. [Google Scholar] [CrossRef] [Scilit]
- Plotti, F.; Terranova, C.; Luvero, D.; Bartolone, M.; Messina, G.; Feole, L.; Cianci, S.; Scaletta, G.; Marchetti, C.; Di Donato, V.; et al. Diet and Chemotherapy: The Effects of Fasting and Ketogenic Diet on Cancer Treatment. Chemotherapy 2020, 65, 77–84. [Google Scholar] [CrossRef] [Scilit]
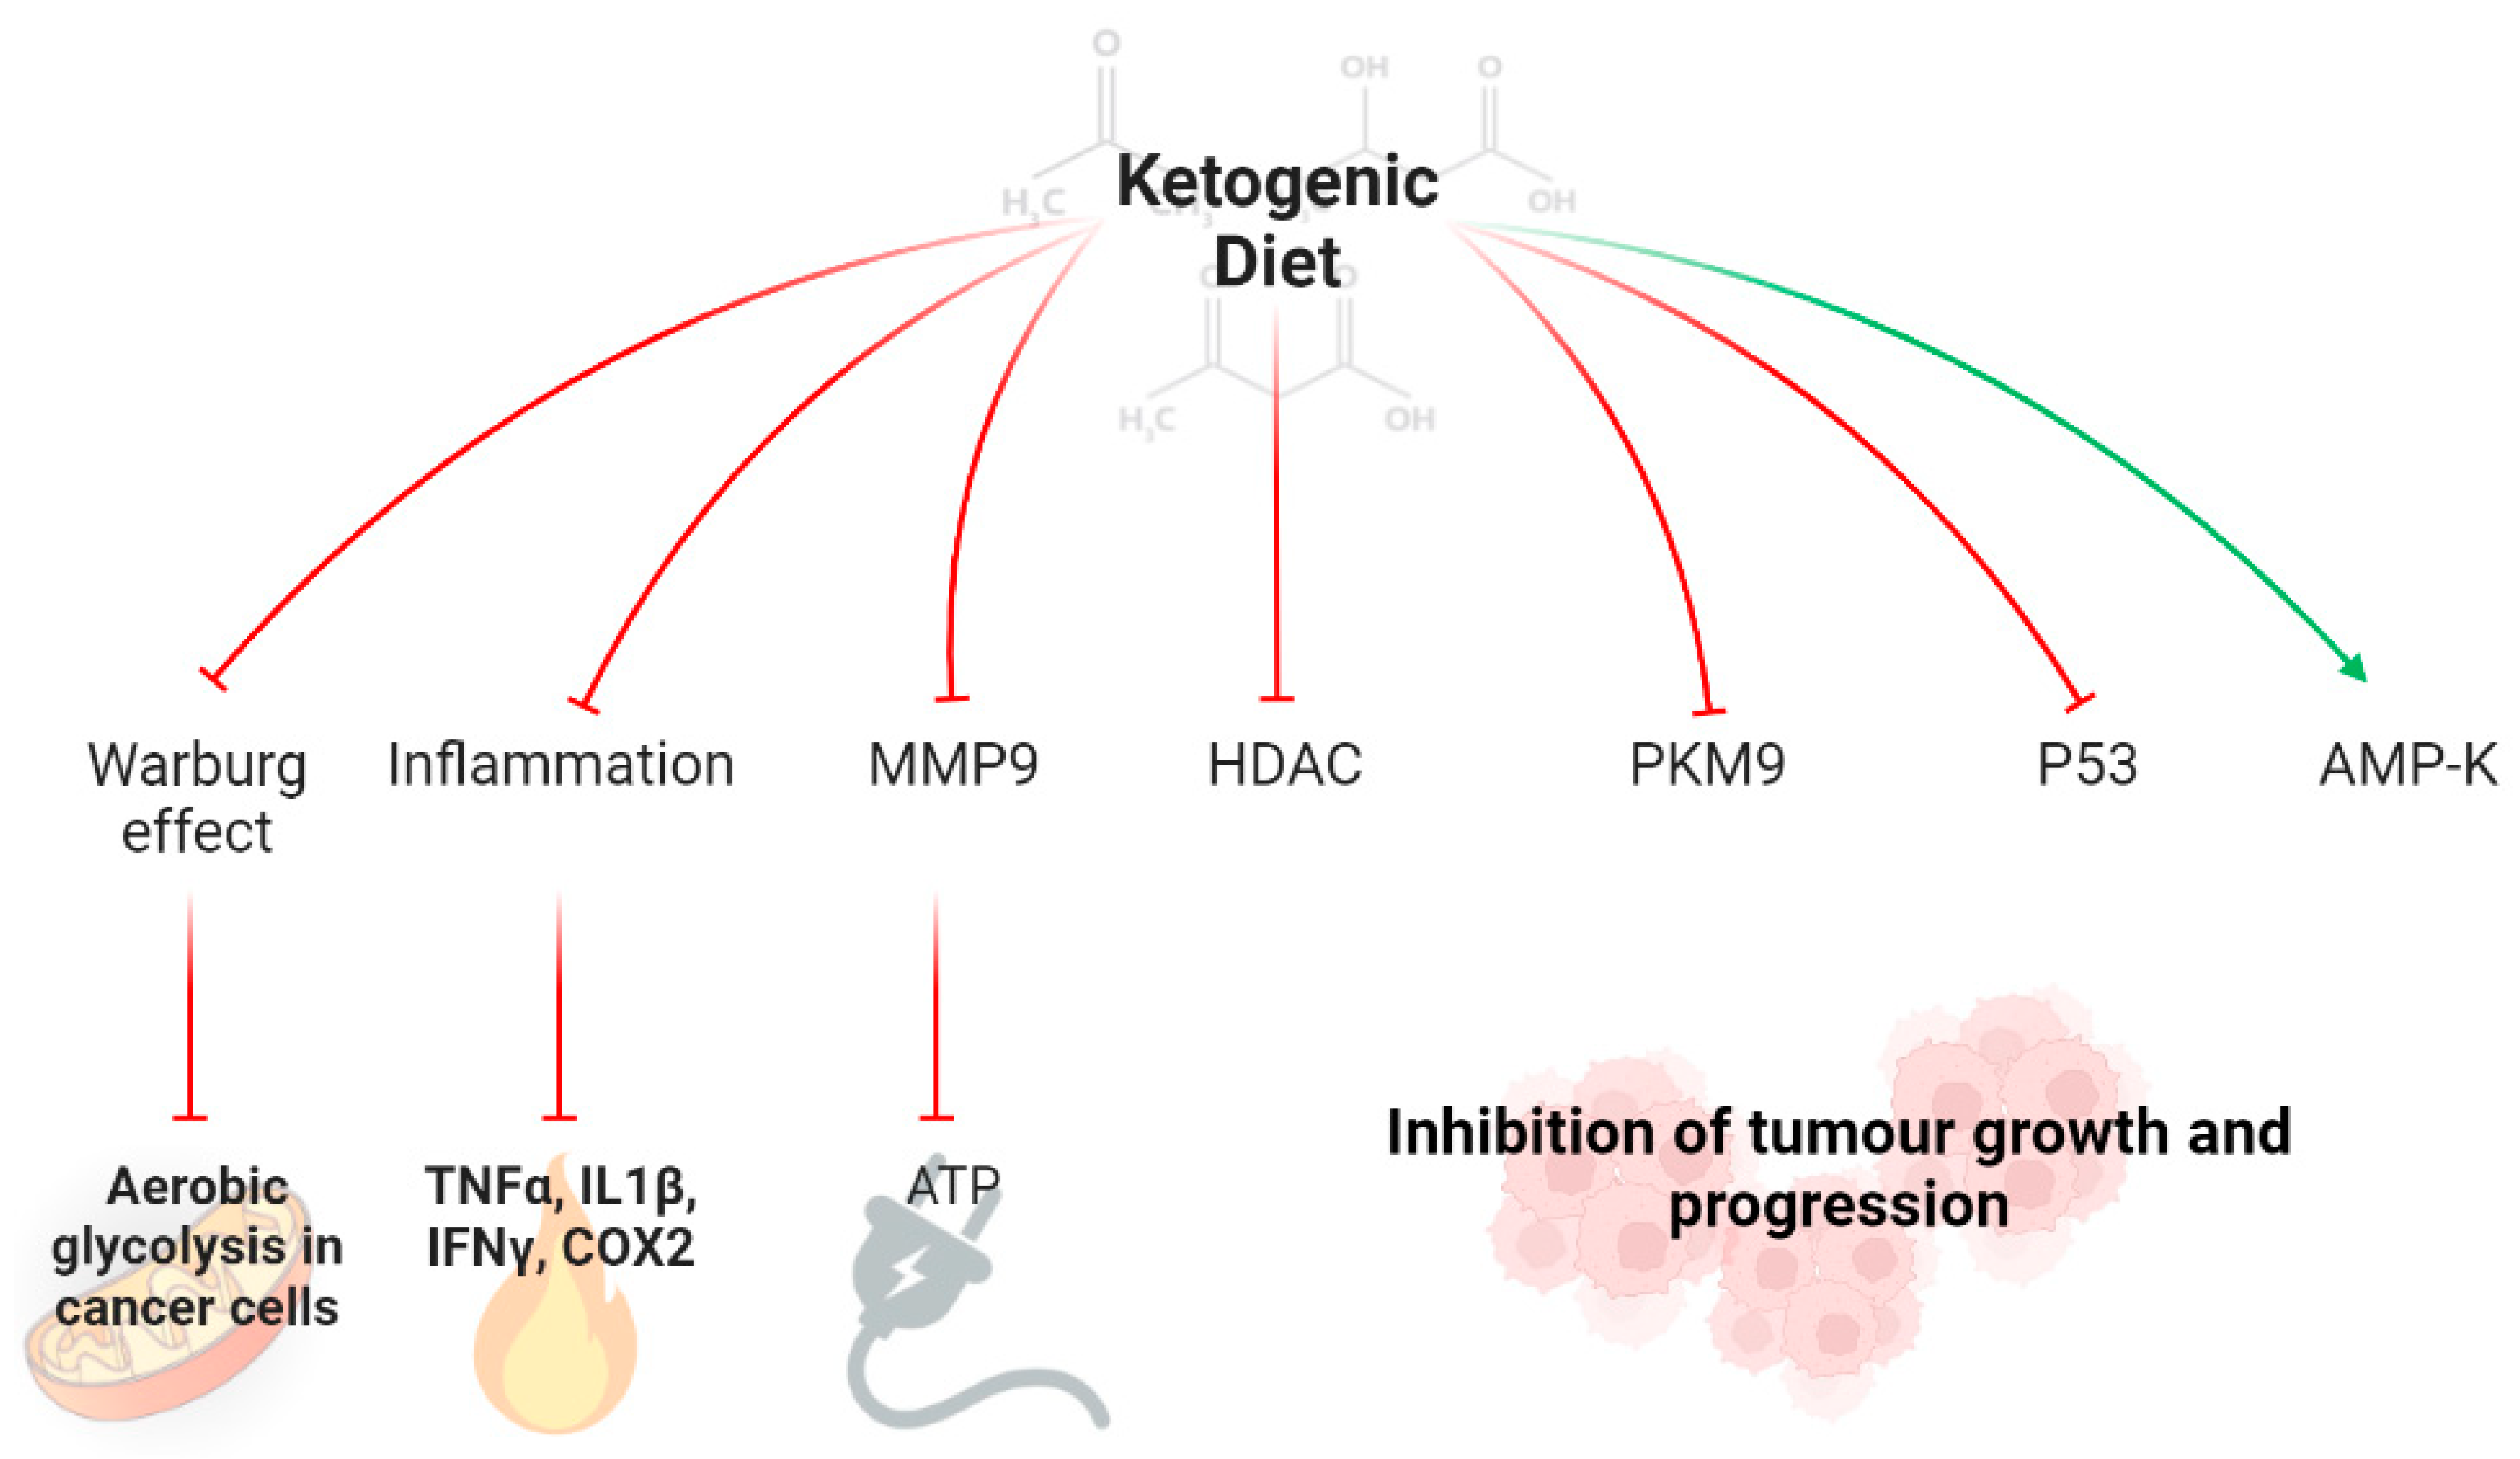
Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).