


Simple Summary
Clinical practice guidelines for cancer treatment during pregnancy have been available for the past 20 years; however, whether they contain bioethical guidance is currently unknown. A systematic medical literature review was performed to identify the presence of biomedical ethics principles present in guidelines published until 2021. Most of the included guidelines (25 out of 32) refer to biomedical ethics principles such as respect for patient’s autonomy, beneficence and justice. Earlier guidelines stress the importance of patient wishes and choices in light of limited evidence and vast unknowns while balancing maternal and fetal wellbeing. More recent guidelines tend to focus on evidence-based data to balance favorable outcomes for pregnant patients and their fetuses with counselling support to help the patients and their support network understand the rationale behind available treatment options. However, ethics-related content in such guidelines is not presented in a structured manner, indicating the need for methodological upgrades. Therefore, a more structured approach is needed when addressing existing and potential ethical issues in clinical practice guidelines for cancer treatment during pregnancy.
Abstract
(1) Background: Current scientific evidence suggests that most cancers, including breast cancer, can be treated during pregnancy without compromising maternal and fetal outcomes. This, however, raises questions regarding the ethical implications of clinical care. (2) Methods: Using a systematic literature search, 32 clinical practice guidelines for cancer treatment during pregnancy published between 2002 and 2021 were selected for analysis and 25 of them mentioned or made references to medical ethics when offering clinical management guidance for clinicians. (3) Results: Four bioethical themes were identified: respect for patient’s autonomy, balanced approach to maternal and fetal beneficence, protection of the vulnerable and justice in resource allocation. Most guidelines recommended informing the pregnant patient about available evidence-based treatment options, offering counselling and support in the process of decision making. The relational aspect of a pregnant patient’s autonomy was also recognized and endorsed in a significant number of available guidelines. (4) Conclusions: Recognition and support of a patient’s autonomy and its relational aspects should remain an integral part of future clinical practice guidelines. Nevertheless, a more structured approach is needed when addressing existing and potential ethical issues in clinical practice guidelines for cancer treatment during pregnancy.
1. Introduction
Pregnancy-related cancer is a relatively rare entity, affecting approximately 1 in 1000 pregnancies [1,2,3]. Nevertheless, as there is a consistent postponement of pregnancy in almost all middle- and high-income countries [4], incidence may increase. Breast cancer is the main oncological disease affecting reproductive age women worldwide and the most common type during pregnancy [5], followed by lymphoma, cervical cancer and thyroid cancer [3,6]. The clinical approach to these complex patients depends not only on the type and stage of the tumor, but also on the pregnancy trimester, and involves a personalized diagnostic and therapeutic approach [7], because cancer diagnosis and treatment during pregnancy pose unique challenges [6]. There is a vast amount of literature regarding cancer treatment during pregnancy that demonstrates that different cancer treatments can safely be conducted during pregnancy without compromising the fetal outcomes [8], namely, different chemotherapy agents, surgery and radiotherapy [9]. This, however, depends on the gestational age of the fetus at the time of treatment, tumor type and disease stage, as treatments may induce developmental teratogenicity [10,11,12]. There are a number of ethical questions involved, especially when oncological prognosis is dire and a patient’s desire for parenthood is strong; practical questions such as breastfeeding after breast cancer are also frequently triggered in this setting [13,14]. Nevertheless, knowledge regarding bioethical aspects arising during this unusual co-occurrence is scarce [15].
Clinical practice guidelines for cancer management in the course of pregnancy provide advice for healthcare professionals to assist their decision-making process throughout the course of their patients’ illness management [16]. However, whether the available guidelines offer guidance regarding the ethical aspects of cancer care during pregnancy and which type of bioethical content is present remains to be compiled. Therefore, the aim of this paper is to review and consolidate the medical ethics guidance provided in clinical practice guidelines for cancer treatment during pregnancy by identifying the core ethical concepts referenced in these documents, analyzing time-trends and demonstrating the implications of this guidance on clinical breast cancer and other cancers management during pregnancy.
This work builds on the foundations created by an earlier research project carried out at the European Institute of Oncology (Milan, Italy) looking at biomedical ethics concepts/principles present in clinical practice guidelines, which sought to understand the standpoints and approaches to ethical issues surrounding cancer care during pregnancy through clinical practice guidelines [16]. Whether the approaches and standpoints expressed in the clinical practice guidelines are ethical in themselves is beyond the scope of this work. Furthermore, the authors did not seek to evaluate the quality of the scientific evidence for cancer treatment during pregnancy presented in the analyzed guidelines.
2. Materials and Methods
A systematic review was conducted to identify clinical practice guidelines offering general or cancer-type specific management of oncological conditions in pregnant patients, adhering to standards laid out in the PRISMA (Preferred Reporting Items for Systematic Reviews and Meta-Analysis) statement [17]. The systematic review has been registered at Research Registry reviewregistry1442. Due to the nature of this research, it did not require Institutional Review Board (IRB) approval. The data search was conducted in two steps, consisting of an initial search of clinical practice guidelines up to 2015 [16], which was further updated in 2021. The search was performed using an electronic database (PubMed) and included articles published in the English language until 14 July 2021, with no retrospective time limit. Other databases were not searched based on previous experience, where Web of Science and Science Direct databases did not yield any additional results, nor did the snowballing approach, to those already identified through the PubMed search. Grey literature, citation track and hand-search were not conducted due to resource constraints and the low likelihood of identifying additional publications.
The following string of search terms was used (pregnancy AND cancer AND guideline) to identify the publications that oncologists and other healthcare professionals would possibly refer to when looking for practical guidance for pregnancy-related cancer care. Two eligibility criteria were established for including the clinical practice guidelines in this review: (1) guidelines should be published as articles and expert meeting reports aiming to provide recommendations for cancer treatment and management during pregnancy; (2) guidelines should be released, reviewed and/or endorsed by a professional society representing clinicians practicing in a clinical field related to oncology. Review articles where the primary goal was to provide guidelines for the management of tumors diagnosed during pregnancy but not related to any professional organization were excluded due to a potential opinion bias, based on the assumption that professional clinical organizations would present a consensual expert view.
The content of the guidelines was analyzed by looking for references to four biomedical ethics principles as defined by Beauchamp and Childress: respect for autonomy, nonmaleficence, beneficence and justice [18], and the European specification of basic ethical principles in bioethics and biolaw: autonomy, dignity, integrity and vulnerability [19]. The content analysis was conducted by the first author in consultation with the supervising authors, with whom difficult cases were discussed.
The selected guidelines were analyzed using the critical interpretative approach [20] by ascribing the wording in clinical practice guidelines to definitions used in medical ethics, since biomedical ethics principles are not referred to directly in the analyzed clinical practice guidelines. Table 1 shows what biomedical ethics principles were identified in the analyzed guidelines and Table 2 illustrates how original wording from the guidelines corresponded to medical ethics concepts. For example, “attention to patient’s personal wishes” [21], “abortion is a personal decision” [22] were interpreted as respect for patient’s autonomy, while “considerations should be given to the health of both mother and foetus” [23] was regarded as balancing maternal and fetal beneficence but “maximizing maternal outcome” [24] was assumed as a preference to maternal beneficence. “Pregnancy should never be interrupted” was regarded as protection of the vulnerable [25] and “reasonable course of action based on current knowledge, available resources and the needs of the patient” [26] was considered as a reference to the biomedical ethics principle of justice.
3. Results
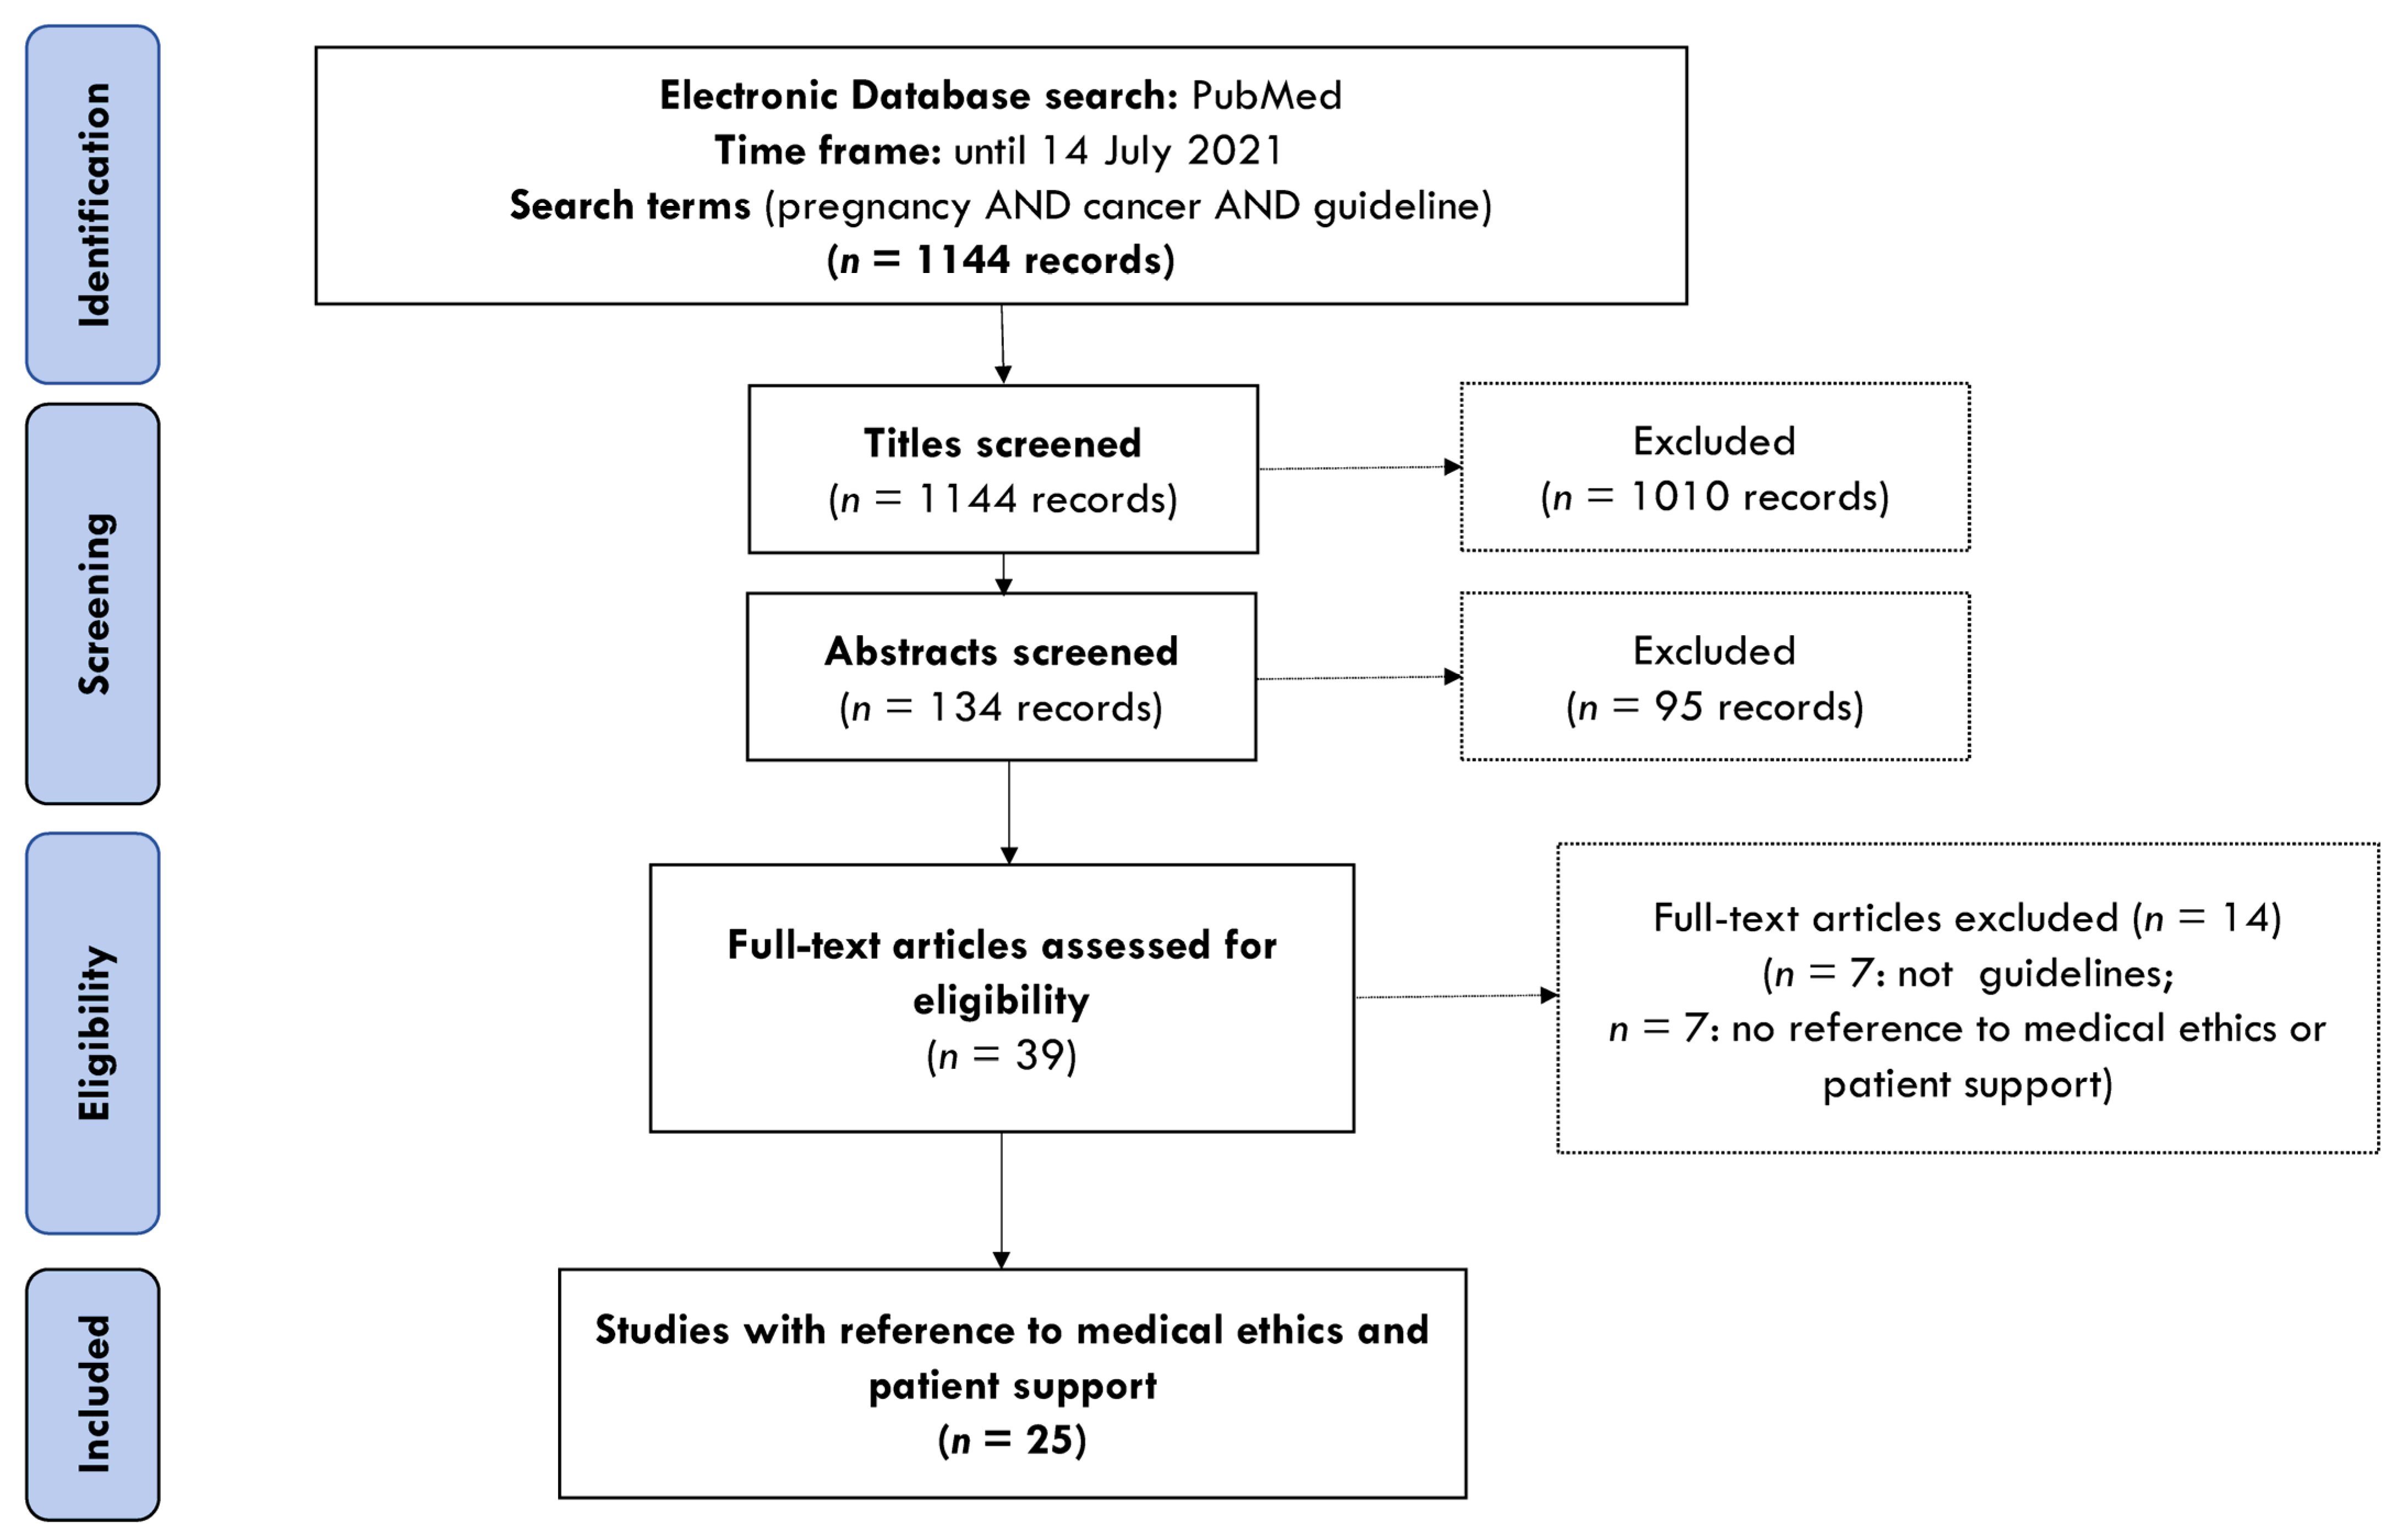
A total of 32 guidelines were included for full-text analysis. From these, 7 were excluded due to the lack of references to patient care outside the clinical aspects and 25 guidelines were included in this systematic review, as detailed in Figure 1. Most of the guidelines referred to a site-specific cancer type (breast [27,28,29,30,31], cervix [32,33], thyroid [25,34,35], melanoma [26,36], leukemia [23,37] and Hodgkin lymphoma [21]) and the remaining ones to groups of pathologies [24,38,39,40] or women cancers and their treatment in general [22,41,42,43,44,45]. Regarding the quality of the included guidelines, it is important to stress that guidance in some professional guidelines was retrieved from case studies, case study reviews and various registries, whereas in others, guidance was based on expert opinion rather than on systematically collected data [16].
Figure 1.
Study Flowchart.
Four biomedical ethics concepts were identified in the reviewed guidelines, as summarized in Table 1 and Table 2. Autonomy, beneficence and vulnerability were transversal throughout the 20-year period. Consideration of justice in resource allocation only appeared in 2015. Respect for patients’ autonomy was the most ubiquitous and dominant ethical principle, as illustrated by the following statements: “the implications of starting chemotherapy in the third trimester and the risks to the woman of delaying chemotherapy to gain advantage for the baby need to be discussed with the mother” [23], “personal priorities for each patient will clearly influence the decision” [21], “termination of pregnancy is an individual decision affected by many factors” [22].
The beneficence principle was the second ethical concept identified, with guidance mentioning a balanced approach to maternal and fetal beneficence: “Consideration should be given to the health of both mother and baby and the informed wishes of the mother. The woman should be fully informed about the diagnosis, treatment of the disease and possible complications during pregnancy” [23], “The priority must be the health of the mother” [21] and “serious consideration should be given to the option of treating breast cancer whilst continuing with the pregnancy” [29]. Some guidelines also introduced concepts surrounding protection of the vulnerable, as exemplified with this sentence: “State-of-the-art treatment should be provided for this vulnerable population to preserve maternal and fetal prognosis” [24].
A relatively new theme emerging in clinical practice guidelines was reasonable resource allocation, considering a large picture of a healthcare system and available resources. This suggests that resources have to be considered based on current knowledge and the needs of the patient to deliver effective and safe medical care “practitioner will follow a reasonable course of action based on current knowledge, available resources and the needs of the patient to deliver effective and safe medical care” [26].
Overall, experts advocate for a multidisciplinary approach to cancer treatment during pregnancy, evidence-based medicine and counselling services for patients. Reference to concepts that can be framed within the ethical principles has changed during the 20-year period analyzed. Some guidelines published before 2015 recognized the importance of personal relationships (relational autonomy) that pregnant cancer patients might be inclined to consider when making their treatment choices: for example, partner and other children, if present: “possibly involving her partner and family in the decision- making process” [41], “the pregnant woman, her family, and her medical team are required to make complex treatment decisions” [44], “discussion should allow appropriate time for reflection and should possibly involve the partner, if present” [27]. All guidelines referring to breast cancer during pregnancy were published before 2015 [27,28,29,30,31] where more focus was given to a patient’s preferences since little evidence-based data was available at that time.
Later guidelines published after 2015 continue to stress the importance of supporting pregnant cancer patients to take informed decisions about their cancer treatment and pregnancy care. This is achieved by providing accessible information about available medical care options and their implications to a pregnant patient and their developing fetus [26,32,33,35,37,39]. For example, “feeling informed and in control through the provision of information can lead to women feeling engaged and active in their treatment decisions leading to better patient outcomes” [33], “every patient must be counselled by a multidisciplinary team. This team should consist of experts in the fields of gynaecologic oncology, neonatology, obstetrics, anaesthesiology, radiation oncology, medical oncology, psychooncology, and, if requested, theology or ethics” [32]. It also continues to emphasize the importance of respect for patient autonomy and taking a patient’s wishes into account when determining the disease management plan [32,33,35,37,39]. For example, “each woman needs to make the decision that fits her best after an in-depth discussion; clinical care teams should be supportive of her choice, whatever that choice may be” [37]. Some guidelines also recognize the importance of the relational aspect of respect for patient autonomy “counselling should be offered to both the affected woman and her partner” [40], “women and their partners should be counselled that no guidelines exist regarding how best to monitor chronic myeloid leukaemia during pregnancy” [37]. However, guidance appears to have shifted from focusing on patients’ personal wishes in the unknown circumstances to counselling, where treatment options are discussed in light of the available scientific evidence. The latter might not be well reflected in currently available guidelines for breast cancer treatment during pregnancy because these guidelines were released before consolidated scientific evidence became more widely available.
There has been one guideline identified which encourages protecting the fetus while ensuring supporting care for its mother “Pregnancy should never be interrupted. Women with differentiated thyroid carcinoma (DTC) and no evidence of aggressive or advanced disease may be reassured that most DTC are slow growing and that surgery soon after delivery is unlikely to change prognosis” [25]. Subsequent guidelines from the past six years do not refer to the protection of the vulnerable, which was seen in the guidelines published earlier. In the earlier guidelines, protection of the vulnerable was defined broadly, including pregnant women, cancer patients, unborn children/fetuses, neonates and children [24,29].
Table 1.
Main biomedical ethics concepts/principles identified in the guidelines.
Table 2.
Review summary and key findings of clinical practice guidelines addressing cancer management during pregnancy.
4. Discussion
This systematic review has summarized the key ethical concepts—based on the core biomedical ethics principles as defined by Beauchamp and Childress [18] and the European specification of basic ethical principles in bioethics and biolaw [19]—present in clinical practice guidelines of pregnancy-related cancer. We found that most of the guidelines assessed in this study (25 out of 32) contained ethical guidance, namely regarding autonomy, beneficence, vulnerability and justice, which were transversal throughout the 20-year period. The first two themes are found in classical biomedical ethics studies and are known as moral principles in modern biomedical ethics [18], while the third theme is considered a European bioethics principle [19], which is also known as a principle of protection of the vulnerable [53] and a principle of respect for human vulnerability [54]. The fourth theme was mentioned only in one guideline emphasizing the importance of the reasonable use of available resources [26].
Globally, there was a predominance of guidance regarding respect for patients’ autonomy and beneficence (balanced approach for mother and fetus). Due to reassuring evidence that maternal cancer can be treated effectively without compromising the fetal outcomes, there has been a growing number of guidelines supporting the balancing of maternal and fetal beneficence [26,32,33,35,37,40,45], which is especially evident in the guidelines released in the last six years (2015–2021). For example, “the potential risk/benefit balance should be carefully evaluated in terms of maternal health and foetal risk before initiation of treatment during pregnancy” [37], while maternal health outcomes are only prioritized if an optimal balance for a pregnant patient and their fetus is not possible “should be carefully discussed with the gynaecologist considering the risks and benefits” [26] and if aggressive disease is detected in the early stages of the pregnancy [39].
A time-trend was observed in the guidelines published in the last quarter analyzed (2016–2021), which focus on counselling the patients (and often their partners) about informed treatment decisions, which may reflect the growing availability of safety data [1,3]. Nevertheless, as more robust medical findings become available for cancer treatment during pregnancy, there is a risk of shifting clinical practice towards the medical side of evidence-based balanced beneficence while reducing the focus on respect for patients’ wishes and choices, without considering other variables. Recognition and support of a patient’s autonomy and its relational aspects should remain an integral part of future clinical practice guidelines for cancer treatment during pregnancy. This will be an important aspect to consider when updated clinical practice guidelines are being released for breast cancer management during pregnancy, because currently available guidelines for this cancer type that include ethical guidance date back to 2012–2013 [27,41].
It is widely recognized that having pregnant cancer patients as active participants in their care and treatment planning is crucial for good maternal and fetal clinical outcomes [33]. This indicates that pregnant patients are being considered as active participants in clinical decision making about available treatment options which seek the best evidence-based outcomes for them and their developing fetuses. The focus on the patient (also known as patient centricity) is seen across most guidelines which corresponds with mainstream healthcare practice, where patient centric efforts have continuously been made to make healthcare delivery more patient focused through patient empowerment, personalized care and relational/care ethics. Patient centricity can be considered as putting the patient first in an open and sustained engagement with the attending clinical team, who respectfully and compassionately work together with the patient to achieve the best care experience and clinical outcome for that person and their family [55]. Overall, the analyzed clinical practice guidelines can be considered patient-centric because treatment decisions are made together with the patient by providing evidence-based information and allowing time and space to consider the available options. It was evident in the included guidelines that patient counselling and decisional support is widely recognized as a standard of care for pregnant cancer patients [22,24,26,27,28,30,31,32,33,35,36,37,38,40,41,45]. Moreover, the patient is not left alone to make difficult moral choices and the most recent guidelines seem to support the maternalistic approach from the clinical teams by emphasizing the importance of available scientific evidence in patient counselling [14]. The content in clinical practice guidelines appears to support the ideas expressed elsewhere that clinicians cannot determine how the patients should view their disease, but when equipped with empathy and compassion clinicians can support their patients by explaining the logical rationale behind evidence-based clinical advice [13]. It also somewhat allows healthcare professionals to have an active, collaborative role in decision making. Furthermore, the resource allocation theme corresponding to the biomedical ethics principle of justice [18], which takes into consideration equity and utility of the chosen treatment plan, emerged in 2015. It is not consistently mentioned in other guidelines, but its importance has been noted in the literature [13] and it would be reasonable to expect that more future guidelines will include resource allocation and treatment futility in their ethical guidance.
This work has reviewed and consolidated the ethical content presented in pregnancy-related cancer clinical practice guidelines and analyzed time-trends for the first time. Nevertheless, this review has inherent limitations that need to be considered when analyzing the results. Firstly, the search and main analysis was conducted by the first author independently, which might have increased the likelihood of selection, coding and interpretation bias. Nonetheless, selection choices and analysis were discussed with the rest of the research team, attempting to overcome these limitations. Secondly, the search was limited to English language and the grey literature was not searched, which might have excluded guidance from some medical organizations that do not have their guidance indexed in PubMed. However, the authors believe that most of the clinically relevant organizations tend to publish in journals indexed in this database and therefore were included. Thirdly, the quality of scientific evidence presented in the selected guidelines was not evaluated systematically. Indeed, the primary interest was to identify the references to ethics while recognizing that such guidelines do not explicitly aim to provide ethics guidance and, therefore, evaluating the quality of the guidance was not in the scope of this research. Hence, further research and debate on how clinical practice guidelines can and/or should address ethical issues related to this difficult clinical area should continue. The need for actionable ethical guidance in clinical practice guidelines has been shown in other clinical areas as well [56].
5. Conclusions
This systematic review has compiled, for the first time, the ethical guidance present in clinical practice guidelines referring to pregnancy-related cancer. Although the majority of analyzed guidelines mentioned some biomedical ethics principles, it is important to stress that 7 out of 32 screened articles (22%) did not make any mention of ethical aspects relating to cancer during pregnancy care, including some very recent guidelines released between 2019 and 2021. Moreover, among the guidelines that mentioned ethical themes, the approach to ethical issues has not been structured or consistent. These data highlight the need for a structured approach when addressing existing and potential ethical issues in clinical practice guidelines for cancer management during pregnancy, as it would help healthcare professionals to provide high-quality, patient-centered care and be prepared to address ethical issues and concerns in their clinics proactively and professionally. Moreover, this review emphasizes the importance of practical ethics and humanities training for healthcare professionals to equip them with skills for ethically challenging clinical situations and of patient-centric training to ensure that patients are active participants in their care. Clinical guidelines methodology would also benefit from more diverse and inclusive input, such as the inclusion of patient advocates, bioethicists and other humanities scholars. Overall, this work underscores the need for more research regarding ethics in the clinical care of pregnant cancer patients and a more systematic inclusion of ethics themes in clinical practice guidance, which should encourage individual healthcare professionals to be more mindful of ethical issues in their practice and skilled in addressing and resolving ethical concerns in their clinics.
Author Contributions
Conceptualization, A.L., F.A.P. and K.D.; methodology, A.L., F.A.P. and K.D.; formal analysis, A.L., R.C., F.A.P. and K.D.; resources, A.L., R.C., F.A.P. and K.D.; writing—original draft preparation, A.L.; writing—review and editing, A.L., R.C., F.A.P. and K.D.; visualization, A.L. and R.C.; supervision, F.A.P. and K.D. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Acknowledgments
The authors would like to thank Barbara Buonomo for insightful discussions and assistance in acquiring full-text copies of the analyzed articles and the Mentorship Program of ESCO (College of the European School of Oncology) without whom the inclusion of Rita Canário in this project would not have been possible.
Conflicts of Interest
The authors (R.C., F.A.P. and K.D.) declare no conflict of interest. A.L. has a gainful employment relationship with a global contract research organization and owns their market stocks, her employer had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.
References
- Cottreau, C.M.; Dashevsky, I.; Andrade, S.E.; Li, D.K.; Nekhlyudov, L.; Raebel, M.A.; Ritzwoller, D.P.; Partridge, A.H.; Pawloski, P.A.; Toh, S. Pregnancy-associated cancer: A U.S. Population-based study. J. Women’s Health 2019, 28, 250–257. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dalmartello, M.; Negri, E.; La Vecchia, C.; Scarfone, G.; Buonomo, B.; Peccatori, F.A.; Parazzini, F. Frequency of pregnancy-associated cancer: A systematic review of population-based studies. Cancers 2020, 12, 1356. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maggen, C.; Wolters, V.E.R.A.; Cardonick, E.; Fumagalli, M.; Halaska, M.J.; Lok, C.A.R.; de Haan, J.; Van Tornout, K.; Van Calsteren, K.; Amant, F. Pregnancy and Cancer: The INCIP Project. Curr. Oncol. Rep. 2020, 22, 17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- United Nations, Department of Economic and Social Affairs PD. World Population Prospects 2019. 2019. Available online: https://population.un.org/wpp/Download/Standard/Fertility/ (accessed on 15 July 2021).
- International Agency for Research on cancer. Breast. Globocan 2020. Available online: https://gco.iarc.fr/today/data/factsheets/cancers/20-Breast-fact-sheet.pdf (accessed on 15 July 2021).
- Hepner, A.; Negrini, D.; Hase, E.A.; Exman, P.; Testa, L.; Trinconi, A.F.; Filassi, J.R.; Francisco, R.P.V.; Zugaib, M.; O’Connor, T.L.; et al. Cancer during Pregnancy: The Oncologist Overview. World J. Oncol. 2019, 10, 28–34. [Google Scholar] [CrossRef] [Scilit]
- Heimovaara, J.H.; Boere, I.A.; de Haan, J.; van Calsteren, K.; Amant, F.; van Zuylen, L.; Lok, C.A.R.; Lok, C.A.R.; van Zuylen, L.; Boere, I.A.; et al. Ten-year experience of a national multidisciplinary tumour board for cancer and pregnancy in the Netherlands. Eur. J. Cancer 2022, 171, 13–21. [Google Scholar] [CrossRef] [Scilit]
- Wolters, V.; Heimovaara, J.; Maggen, C.; Cardonick, E.; Boere, I.; Lenaerts, L.; Amant, F. Management of pregnancy in women with cancer. Int. J. Gynecol. Cancer 2021, 31, 314–322. [Google Scholar] [CrossRef] [Scilit]
- Silverstein, J.; Post, A.L.; Chien, A.J.; Olin, R.; Tsai, K.K.; Ngo, Z.; Van Loon, K. Multidisciplinary Management of Cancer during Pregnancy. JCO Oncol. Pract. 2020, 16, 545–557. [Google Scholar] [CrossRef] [Scilit]
- Peccatori, F.A.; Lambertini, M.; Scarfone, G.; Del Pup, L.; Codacci-Pisanelli, G. Biology, staging, and treatment of breast cancer during pregnancy: Reassessing the evidences. Cancer Biol. Med. 2018, 15, 6. [Google Scholar] [CrossRef] [Scilit]
- Abalo, K.D.; Rage, E.; Leuraud, K.; Richardson, D.B.; Le Pointe, H.D.; Laurier, D.; Bernier, M.-O. Early life ionizing radiation exposure and cancer risks: Systematic review and meta-analysis. Pediatr. Radiol. 2021, 51, 45–56. [Google Scholar] [CrossRef] [Scilit]
- Benoit, L.; Mir, O.; Vialard, F.; Berveiller, P. Cancer during Pregnancy: A Review of Preclinical and Clinical Transplacental Transfer of Anticancer Agents. Cancers 2021, 13, 1238. [Google Scholar] [CrossRef] [Scilit]
- Linkeviciute, A.; Buonomo, B.; Fazio, N.; Spada, F.; Peccatori, F.A. Discussing motherhood when the oncological prognosis is dire: Ethical considerations for physicians. ESMO Open 2020, 5, e000956. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Linkeviciute, A.; Notarangelo, M.; Buonomo, B.; Bellettini, G.; Peccatori, F.A. Breastfeeding after Breast Cancer: Feasibility, Safety, and Ethical Perspectives. J. Hum. Lact. 2020, 36, 40–43. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alpuim Costa, D.; Nobre, J.G.; de Almeida, S.B.; Ferreira, M.H.; Gonçalves, I.; Braga, S.; Pais, D. Cancer during Pregnancy: How to Handle the Bioethical Dilemmas?—A Scoping Review with Paradigmatic Cases-Based Analysis. Front. Oncol. 2020, 10, 598508. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Linkeviciute, A. Cancer during Pregnancy: A Framework for Ethical Care. 2017. Available online: https://air.unimi.it/handle/2434/449004#.YNNNbFT0ldg (accessed on 15 July 2021).
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beauchamp, T.L.; Childress, J.F. Principles of Biomedical Ethics, 7th ed.; Oxford University Press: New York, NY, USA, 2013. [Google Scholar]
- Rendtorff, J.D. Basic ethical principles in European bioethics and biolaw: Autonomy, dignity, integrity and vulnerability—towards a foundation of bioethics and biolaw. Med. Health Care Philos. 2002, 5, 235–244. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McDougall, R. Systematic reviews in bioethics: Types, challenges, and value. J. Med. Philos. 2014, 39, 89–97. [Google Scholar] [CrossRef] [Scilit]
- Follows, G.A.; Ardeshna, K.M.; Barrington, S.F.; Culligan, D.J.; Hoskin, P.J.; Linch, D.; Sadullah, S.; Williams, M.V.; Wimperis, J.Z. Guidelines for the first line management of classical Hodgkin lymphoma. Br. J. Haematol. 2014, 166, 34–49. [Google Scholar] [CrossRef] [Scilit]
- Dauer, L.T.; Thornton, R.H.; Miller, D.L.; Damilakis, J.; Dixon, R.G.; Marx, M.V.; Schueler, B.A.; Vañó, E.; Venkatesan, A.; Bartal, G.; et al. Radiation Management for Interventions Using Fluoroscopic or Computed Tomographic Guidance during Pregnancy: A Joint Guideline of the Society of Interventional Radiology and the Cardiovascular and Interventional Radiological Society of Europe with Endorse. J. Vasc. Interv. Radiol. 2012, 23, 19–32. [Google Scholar] [CrossRef] [Scilit]
- Ali, S.; Jones, G.L.; Culligan, D.J.; Marsden, P.J.; Russell, N.; Embleton, N.D.; Craddock, C. Guidelines for the diagnosis and management of acute myeloid leukaemia in pregnancy. Br. J. Haematol. 2015, 170, 487–495. [Google Scholar] [CrossRef] [Scilit]
- Amant, F.; Halaska, M.J.; Fumagalli, M.; Dahl Steffensen, K.; Lok, C.; Van Calsteren, K.; Han, S.N.; Mir, O.; Fruscio, R.; Uzan, C.; et al. Gynecologic cancers in pregnancy: Guidelines of a second international consensus meeting. Int. J. Gynecol. Cancer 2014, 24, 394–403. [Google Scholar] [CrossRef] [Scilit]
- Papini, E.; Negro, R.; Pinchera, A.; Guglielmi, R.; Baroli, A.; Beck-Peccoz, P.; Garofalo, P.; Pisoni, M.; Zini, M.; Elisei, R.; et al. Thyroid nodule and differentiated thyroid cancer management in pregnancy. An Italian Association of Clinical Endocrinologists (AME) and Italian Thyroid Association (AIT) Joint Statement for Clinical Practice. J. Endocrinol. Investig. 2010, 33, 579–586. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bluemel, C.; Herrmann, K.; Giammarile, F.; Nieweg, O.E.; Dubreuil, J.; Testori, A.; Audisio, R.A.; Zoras, O.; Lassmann, M.; Chakera, A.H.; et al. EANM practice guidelines for lymphoscintigraphy and sentinel lymph node biopsy in melanoma. Eur. J. Nucl. Med. Mol. Imaging 2015, 42, 1750–1766. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cardoso, F.; Loibl, S.; Pagani, O.; Graziottin, A.; Panizza, P.; Martincich, L.; Gentilini, O.; Peccatori, F.; Fourquet, A.; Delaloge, S.; et al. The European Society of Breast Cancer Specialists recommendations for the management of young women with breast cancer. Eur. J. Cancer 2012, 48, 3355–3377. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Royal College of Obstetricians and Gynaecologists. Pregnancy and Breast Cancer; Royal College of Obstetricians and Gynaecologists: London, UK, 2011. [Google Scholar]
- Amant, F.; Deckers, S.; Van Calsteren, K.; Loibl, S.; Halaska, M.; Brepoels, L.; Beijnen, J.; Cardoso, F.; Gentilini, O.; Lagae, L.; et al. Breast cancer in pregnancy: Recommendations of an international consensus meeting. Eur. J. Cancer 2010, 46, 3158–3168. [Google Scholar] [CrossRef] [Scilit]
- Loibl, S.; Von Minckwitz, G.; Gwyn, K.; Ellis, P.; Blohmer, J.U.; Schlegelberger, B.; Keller, M.; Harder, S.; Theriault, R.L.; Crivellari, D.; et al. Breast carcinoma during pregnancy: International recommendations from an expert meeting. Cancer 2006, 106, 237–246. [Google Scholar] [CrossRef] [Scilit]
- Helewa, M.; Lévesque, P.; Provencher, D.; Lea, R.; Rosolowich, V.; Shapiro, H. Breast cancer, pregnancy, and breastfeeding. J. Obs. Gynaecol. Can. 2002, 24, 164–180. [Google Scholar]
- Cibula, D.; Pötter, R.; Planchamp, F.; Avall-Lundqvist, E.; Fischerova, D.; Haie-Meder, C.; Köhler, C.; Landoni, F.; Lax, S.; Lindegaard, J.C.; et al. The European Society of Gynaecological Oncology/European Society for Radiotherapy and Oncology/European Society of Pathology Guidelines for the Management of Patients with Cervical Cancer. Virchows Arch. 2018, 472, 919–936. [Google Scholar] [CrossRef] [Scilit]
- Reed, N.; Balega, J.; Barwick, T.; Buckley, L.; Burton, K.; Eminowicz, G.; Forrest, J.; Ganesan, R.; Harrand, R.; Holland, C.; et al. British Gynaecological Cancer Society (BGCS) cervical cancer guidelines: Recommendations for practice. Eur. J. Obstet. Gynecol. Reprod. Biol. 2021, 256, 433–465. [Google Scholar] [CrossRef] [Scilit]
- De Groot, L.; Abalovich, M.; Alexander, E.K.; Amino, N.; Barbour, L.; Cobin, R.H.; Eastman, C.J.; Lazarus, J.H.; Luton, D.; Mandel, S.J.; et al. Management of thyroid dysfunction during pregnancy and postpartum: An endocrine society clinical practice guideline. J. Clin. Endocrinol. Metab. 2012, 97, 2543–2565. [Google Scholar] [CrossRef] [Scilit]
- Alexander, E.K.; Pearce, E.N.; Brent, G.A.; Brown, R.S.; Chen, H.; Dosiou, C.; Grobman, W.A.; Laurberg, P.; Lazarus, J.H.; Mandel, S.J.; et al. 2017 Guidelines of the American Thyroid Association for the Diagnosis and Management of Thyroid Disease during Pregnancy and the Postpartum. Thyroid 2017, 27, 315–389. [Google Scholar] [CrossRef] [Scilit]
- Marsden, J.R.; Newton-Bishop, J.A.; Burrows, L.; Cook, M.; Corrie, P.G.; Cox, N.H.; Gore, M.E.; Lorigan, P.; MacKie, R.; Nathan, P.; et al. Revised UK guidelines for the management of cutaneous melanoma 2010. J. Plast. Reconstr. Aesthetic Surg. 2010, 63, 1401–1419. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pallera, A.; Altman, J.K.; Berman, E.; Abboud, C.N.; Bhatnagar, B.; Curtin, P.; DeAngelo, D.J.; Gotlib, J.; Tanner Hagelstrom, R.; Hobbs, G.; et al. NCCN guidelines® insights: Chronic myeloid leukemia, version 1. 2017: Featured updates to the NCCN guidelines. JNCCN J. Natl. Compr. Cancer Netw. 2016, 14, 1505–1512. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amant, F.; Van Calsteren, K.; Halaska, M.J.; Beijnen, J.; Lagae, L.; Hanssens, M.; Heyns, L.; Lannoo, L.; Ottevanger, N.P.; Vanden Bogaert, W.; et al. Gynecologic Cancers in Pregnancy. Int. J. Gynecol. Cancer 2009, 19, S1–S12. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lishner, M.; Avivi, I.; Apperley, J.F.; Dierickx, D.; Evens, A.M.; Fumagalli, M.; Nulman, I.; Oduncu, F.S.; Peccatori, F.A.; Robinson, S.; et al. Hematologic malignancies in pregnancy: Management guidelines from an international consensus meeting. J. Clin. Oncol. 2016, 34, 501–508. [Google Scholar] [CrossRef] [Scilit]
- Amant, F.; Berveiller, P.; Boere, I.A.; Cardonick, E.; Fruscio, R.; Fumagalli, M.; Halaska, M.J.; Hasenburg, A.; Johansson, A.L.V.; Lambertini, M.; et al. Gynecologic cancers in pregnancy: Guidelines based on a third international consensus meeting. Ann. Oncol. 2019, 30, 1601–1612. [Google Scholar] [CrossRef] [Scilit]
- Peccatori, F.A.; Azim, H.A.; Orecchia, R.; Hoekstra, H.J.; Pavlidis, N.; Kesic, V.; Pentheroudakis, G. Cancer, pregnancy and fertility: ESMO Clinical Practice Guidelines for diagnosis, treatment and follow-up. Ann. Oncol. 2013, 24 (Suppl. S6), 160–170. [Google Scholar] [CrossRef] [Scilit]
- Pentheroudakis, G.; Orecchia, R.; Hoekstra, H.J.; Pavlidis, N. Cancer, fertility and pregnancy: ESMO Clinical Practice Guidelines for diagnosis, treatment and follow-up. Ann. Oncol. 2010, 21, 266–273. [Google Scholar] [CrossRef] [Scilit]
- Pentheroudakis, G.; Pavlidis, N.; Castiglione, M. Cancer, fertility and pregnancy: ESMO Clinical Recommendations for diagnosis, treatment and follow-up. Ann. Oncol. 2008, 19, ii108–ii109. [Google Scholar] [CrossRef] [Scilit]
- Koren, G.; Carey, N.; Gagnon, R.; Maxwell, C.; Nulman, I.; Senikas, V. Cancer Chemotherapy and Pregnancy. J. Obstet. Gynaecol. Canada 2013, 35, 263–278. [Google Scholar] [CrossRef] [Scilit]
- Coccia, P.F.; Pappo, A.S.; Beaupin, L.; Borges, V.F.; Borinstein, S.C.; Chugh, R.; Dinner, S.; Folbrecht, J.; Frazier, A.L.; Goldsby, R.; et al. Adolescent and young adult oncology, version 2.2018: Clinical practice guidelines in oncology. JNCCN J. Natl. Compr. Cancer Netw. 2018, 16, 66–97. [Google Scholar] [CrossRef] [Scilit]
- Morice, P.; Narducci, F.; Mathevet, P.; Marret, H.; Darai, E.; Querleu, D. French Recommendations on the Management of Invasive Cervical Cancer During Pregnancy. Int. J. Gynecol. Cancer 2009, 19, 1638–1641. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abalovich, M.; Amino, N.; Barbour, L.A.; Cobin, R.H.; De Groot, L.J.; Glinoer, D.; Mandel, S.J.; Stagnaro-Green, A.; Edwards, H. Clinical practice guideline: Management of thyroid dysfunction during pregnancy and postpartum: An endocrine society clinical practice guideline. J. Clin. Endocrinol. Metab. 2007, 92, S1–S47. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stagnaro-Green, A.; Abalovich, M.; Alexander, E.; Azizi, F.; Mestman, J.; Negro, R.; Nixon, A.; Pearce, E.N.; Soldin, O.P.; Sullivan, S.; et al. Guidelines of the American Thyroid Association for the Diagnosis and Management of Thyroid Disease during Pregnancy and Postpartum. Thyroid 2011, 21, 1081–1125. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Galofré, J.C.; Riesco-Eizaguirre, G.; Álvarez-Escolá, C. Clinical guidelines for management of thyroid nodule and cancer during pregnancy. Endocrinol. Nutr. 2014, 61, 130–138. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cwynarski, K.; Marzolini, M.A.V.; Barrington, S.F.; Follows, G.; Illidge, T.; Stern, S.; Davies, A. The management of primary mediastinal B-cell lymphoma: A British Society for Haematology Good Practice Paper. Br. J. Haematol. 2019, 185, 402–409. [Google Scholar] [CrossRef] [Scilit]
- Bourdel, N.; Huchon, C.; Abdel Wahab, C.; Azaïs, H.; Bendifallah, S.; Bolze, P.A.; Brun, J.L.; Canlorbe, G.; Chauvet, P.; Chereau, E.; et al. Borderline ovarian tumors: French guidelines from the CNGOF. Part 2. Surgical management, follow-up, hormone replacement therapy, fertility management and preservation. J. Gynecol. Obstet. Hum. Reprod. 2021, 50, 101966. [Google Scholar] [CrossRef] [Scilit]
- Gradishar, W.; Moran, M.; Abraham, J.; Aft, R.; Agnese, M.; Allison, K.; Blair, S.; Kumar, R. Breast Cancer, Version 4. 2021 Featured Updates to the NCCN Guidelines. J. Natl. Compr. Cancer Netw. 2021, 19, 484–494. [Google Scholar] [CrossRef] [Scilit]
- Hurst, S.A. Vulnerability in research and health care; Describing the elephant in the room? Bioethics 2008, 22, 191–202. [Google Scholar] [CrossRef] [Scilit]
- Ten Have, H. Respect for Human Vulnerability: The Emergence of a New Principle in Bioethics. J. Bioeth. Inq. 2015, 12, 395–408. [Google Scholar] [CrossRef] [Scilit]
- Yeoman, G.; Furlong, P.; Seres, M.; Binder, H.; Chung, H.; Garzya, V.; Jones, R.R.M. Defining patient centricity with patients for patients and caregivers: A collaborative endeavour. BMJ Innov. 2017, 3, 76–83. [Google Scholar] [CrossRef] [Scilit]
- Cavolo, A.; de Casterlé, B.D.; Naulaers, G.; Gastmans, C. Neonatologists’ decision-making for resuscitation and non-resuscitation of extremely preterm infants: Ethical principles, challenges, and strategies—A qualitative study. BMC Med. Ethics 2021, 22, 129. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).