


Abstract
Background: Dietary calcium and dairy products are hypothesized protective factors against metabolic syndrome (MetS), yet epidemiological evidence remains inconsistent. This systematic review and meta-analysis evaluated the association between total dietary calcium intake or dairy consumption and MetS prevalence in adults. Methods: Following PRISMA 2020 guidelines, PubMed, Cochrane Library, ClinicalTrials.gov, and SCOPUS were searched through to October 2025 for eligible cross-sectional studies assessing dietary calcium or dairy intake and MetS (NCEP ATP III, IDF, or JIS criteria). Longitudinal studies, non-English articles, and pediatric populations were excluded. Quality was assessed via an adapted Newcastle–Ottawa Scale. Random-effects meta-analyses pooled fully adjusted odds ratios (ORs) and 95% confidence intervals (CIs) comparing the highest versus lowest intake categories. Results: Twenty-four studies were included (12 for dietary calcium intake, 12 for dairy products). Higher dietary calcium intake was significantly associated with lower MetS odds (pooled OR: 0.85; 95% CI: 0.80–0.91), despite substantial heterogeneity (I2 = 70.1%). Higher dairy consumption was also inversely associated with MetS (pooled OR: 0.78; 95% CI: 0.72–0.85; I2 = 64.6%). While small-study effects were observed for dairy, trim-and-fill analysis confirmed the robustness of the findings. Higher calcium intake further correlated with favorable profiles in individual MetS components, including blood pressure, HDL cholesterol, waist circumference, triglycerides, and fasting glucose. Conclusions: Higher total dietary calcium intake and dairy product consumption are associated with a lower prevalence of MetS in adults. However, the cross-sectional nature of the included studies precludes any inference of causality between calcium intake and MetS. Therefore, although these findings suggest a protective role of calcium-rich diets, well-designed prospective and interventional studies are warranted to clarify whether this relationship is causal.
1. Introduction
Metabolic syndrome (MetS), first described by Reaven in 1988 as “Syndrome X,” is characterized by the clustering of metabolic risk factors that substantially increase the risk of cardiovascular disease and type 2 diabetes mellitus [1]. Diagnostic criteria included the presence of at least three of the following components: central obesity, arterial hypertension, fasting hyperglycemia, hypertriglyceridemia, and low HDL cholesterol levels [2]. MetS reflects a complex metabolic dysfunction, frequently associated with insulin resistance and chronic low-grade inflammation, and represents a major determinant of cardiovascular morbidity and mortality [3]. The prevalence of MetS is increasing worldwide, particularly in Western countries, the Americas, and the Eastern Mediterranean region, driven by sedentary lifestyles, rising obesity rates, and population aging [4]. In Western populations, MetS affects approximately 20–35% of adults; in the United States, about 34% of adults meet ATP III criteria, while Europe shows comparable prevalence with notable regional variability [4,5]. In Italy, epidemiological studies report prevalence rates between 25% and 30%, with higher rates among older individuals, men, and those with obesity, and a narrowing of sex differences after menopause [6].
Despite extensive research, the pathogenesis of MetS remains only partially understood. Both genetic and environmental factors contribute, with diet playing a central role. Diets rich in simple sugars and saturated or trans fats and poor in fiber and micronutrients promote insulin resistance, inflammation, and endothelial dysfunction [7]. Conversely, healthy dietary patterns such as the Mediterranean and Dietary Approaches to Stop Hypertension (DASH) diets have been shown to improve glucose and lipid metabolism and favorably influence individual MetS components, including waist circumference, triglycerides, HDL cholesterol, and fasting glucose [7,8,9,10].
Growing epidemiological evidence suggests that higher consumption of dairy products—particularly low-fat and fermented types—is associated with a lower risk of MetS and improvements in its individual components [11,12,13]. Although dairy foods contain multiple nutrients that may affect metabolic health, calcium has been proposed as a key contributor. Observational studies have consistently reported inverse associations between dietary calcium intake and MetS prevalence, particularly in women [14,15]. Higher calcium intake has been linked to reduced obesity risk, possibly through effects on lipogenesis and fat oxidation [16], as well as improvements in insulin secretion, blood pressure regulation, and lipid metabolism [17,18]. However, other studies have failed to confirm these associations, yielding inconsistent findings [19,20]. In summary, while evidence suggests a potential link between dietary calcium intake and MetS, current data remain inconclusive.
Therefore, this systematic review and dose–response meta-analysis aims to examine evidence from cross-sectional studies on the association between dietary calcium intake or dairy products and metabolic syndrome, to better clarify the nature of this relationship.
2. Materials and Methods
2.1. Search and Assessment of Studies
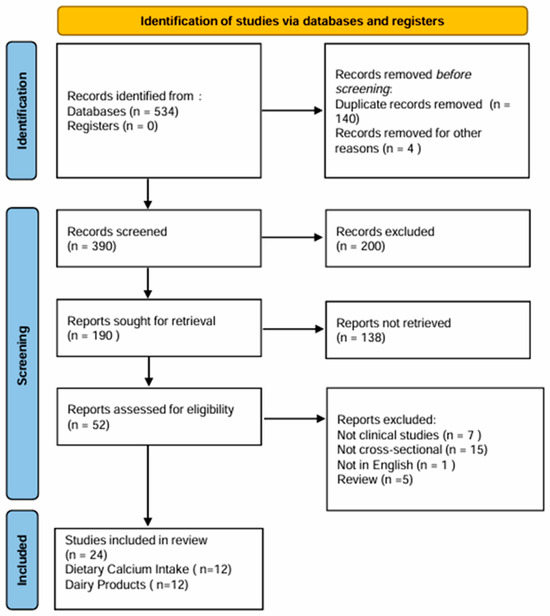
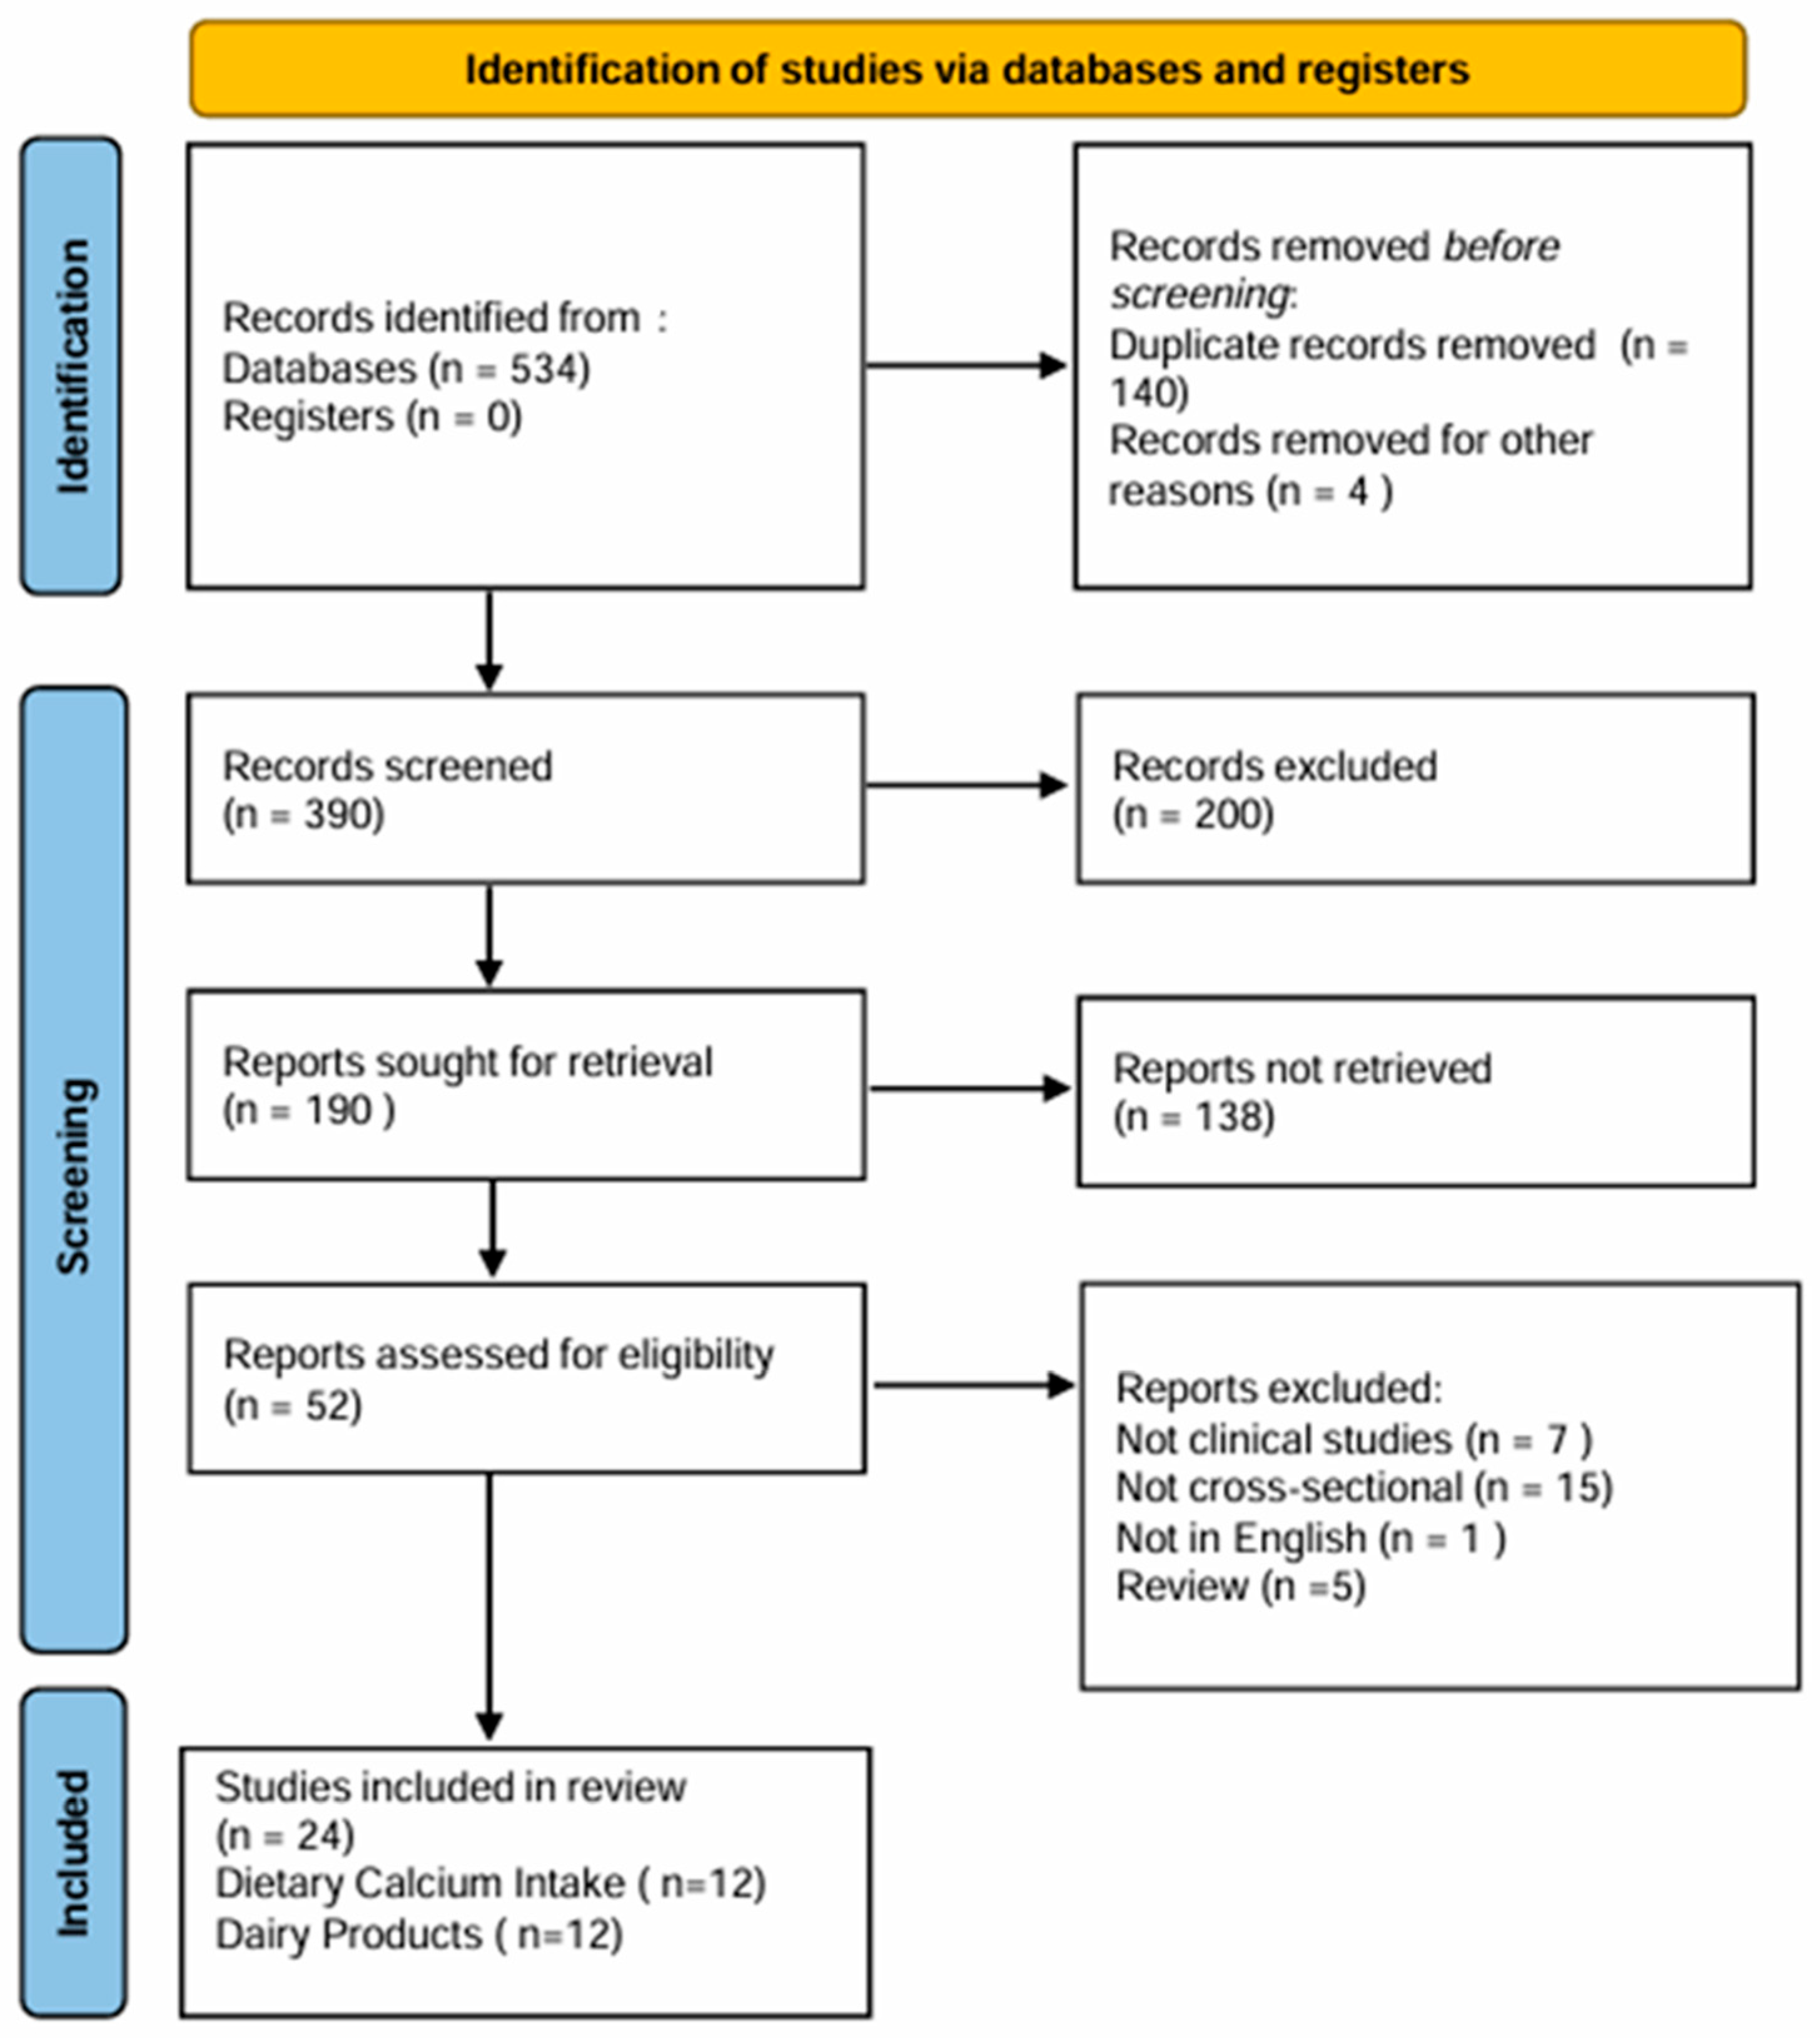
For this review we considered all relevant articles published up to October 2025. The PubMed/Medline, Cochrane Library, ClinicalTrials.gov, and SCOPUS databases were searched using the following search terms: “calcium intake” or “dietary calcium”, “dairy foods/products consumption” and “metabolic syndrome” or “MetS”. The process of selecting the studies for review in adherence to the PRISMA 2020 (Preferred Reporting Items for Systematic reviews and Meta Analyses) [21] is shown in Figure 1. Moreover, the protocol was registered in PROSPERO with code CRD420261328992. After excluding irrelevant articles, duplicates, case–control, cohort, reviews, and meta-analyses, 24 studies were deemed eligible for inclusion in the review. Of these, 12 examined the relationship between total dietary calcium intake and metabolic syndrome, while 12 investigated the association between dairy products consumption and metabolic syndrome, thereby forming two distinct groups that were analyzed separately. All included studies had a cross-sectional design. In all cases, daily dairy food consumption and total dietary calcium intake were assessed using dietary questionnaires. The exclusion criteria were as follows: (i) cohort and longitudinal studies; (ii) studies written in languages other than English; (iii) studies assessing the association between dietary calcium intake or dairy consumption and one or only some components of metabolic syndrome, rather than metabolic syndrome as a whole; and (iv) studies including participants under 18 years of age or with specific pathologies.
Figure 1.
PRISMA flow diagram illustrating the study selection process for inclusion and exclusion in the systematic review and meta-analysis.
2.2. Methodological Quality and Risk of Bias of Studies
Methodological quality and risk of bias of the included cross-sectional studies were assessed using an adapted version of the Newcastle–Ottawa Scale (NOS). This tool evaluates studies across three domains: Selection (maximum 4 stars), Comparability (maximum 2 stars), and Outcome (maximum 3 stars), with a total possible score of 9 stars. Overall study quality was categorized as low (0–4 stars), moderate (5–6 stars), or high (7–9 stars). Two investigators (A.A. and G.S.) independently reviewed all identified studies and performed quality assessment; any disagreements regarding study eligibility were resolved through discussion and consensus (Table S1A,B of the Supplementary Material).
In all the selected studies, metabolic syndrome was defined exclusively according to one of the following criteria: (1) the Third Report of the National Cholesterol Education Program Adult Treatment Panel (NCEP ATP III) [22], (2) the International Diabetes Federation definition (IDF) [23], or (3) the Joint Interim Statement of the International Diabetes Federation (JIS) [24].
To assess the certainty of evidence, we applied the GRADE (Grading of Recommendations, Assessment, Development, and Evaluations) approach, separately evaluating the studies that considered dietary calcium intake and those that assessed dairy product consumption (Table S2A,B of the Supplementary Material) [25].
2.3. Statistical Analysis
Two separate random-effects meta-analyses were conducted to calculate the overall association between the prevalence of metabolic syndrome in studies that evaluated total dietary calcium intake and in those that evaluated dairy product intake, respectively. For each study, the most fully adjusted odds ratio (ORs) and 95% confidence intervals (CIs) comparing the highest versus the lowest categories of intake were extracted and pooled. Random-effects models were applied to account for between-study variability. Statistical heterogeneity was assessed using Cochran’s Q-test and quantified with the I2 statistic, calculated as
where Q represents Cochran’s heterogeneity statistic and df the degrees of freedom. I2 values of <50%, 50–75%, and >75% were considered indicative of low, moderate, and high heterogeneity, respectively. A Q-test p-value < 0.05 was considered statistically significant. The between-study variance (τ2) was estimated within the random-effects framework. Potential publication bias was evaluated by visual inspection of Begg’s funnel plots and statistically assessed using Begg’s rank correlation test and Egger’s regression test. A p-value < 0.05 was considered statistically significant. The Greenland and Longnecker method was used to evaluate the dose response meta-analysis [26].
3. Results
According to our search strategy, twenty-four cross-sectional articles were selected and included in this review. Of these, 12 articles focused on the association between total dietary calcium intake and metabolic syndrome, while the remaining 12 explored the possible association between daily consumption of dairy foods and metabolic syndrome.
3.1. Total Dietary Calcium Intake and Metabolic Syndrome
Table 1 presents the main characteristics of the eligible cross-sectional studies included in the systematic review and meta-analysis examining the association between dietary calcium intake and metabolic syndrome in adults [19,20,27,28,29,30,31,32,33,34,35,36]. Overall, the included studies comprised a total of 73,652 men and 128,058 women. With regard to study location, eight studies were conducted in Asia, two in the United States, one in Brazil, and one in Australia. Dietary calcium intake was assessed using food frequency questionnaires (FFQs) and/or 24–48 h dietary recalls. Study quality was rated as high in eight studies, moderate in three, and low in one [Table S1A in Supplementary Materials].
Table 1.
Main characteristics of the eligible cross-sectional studies included in the systematic review and meta-analysis investigating the association between total dietary calcium intake and metabolic syndrome in adults.
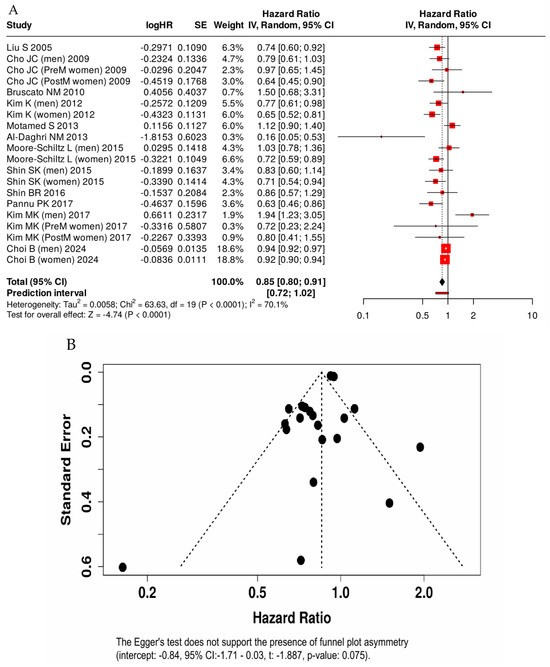
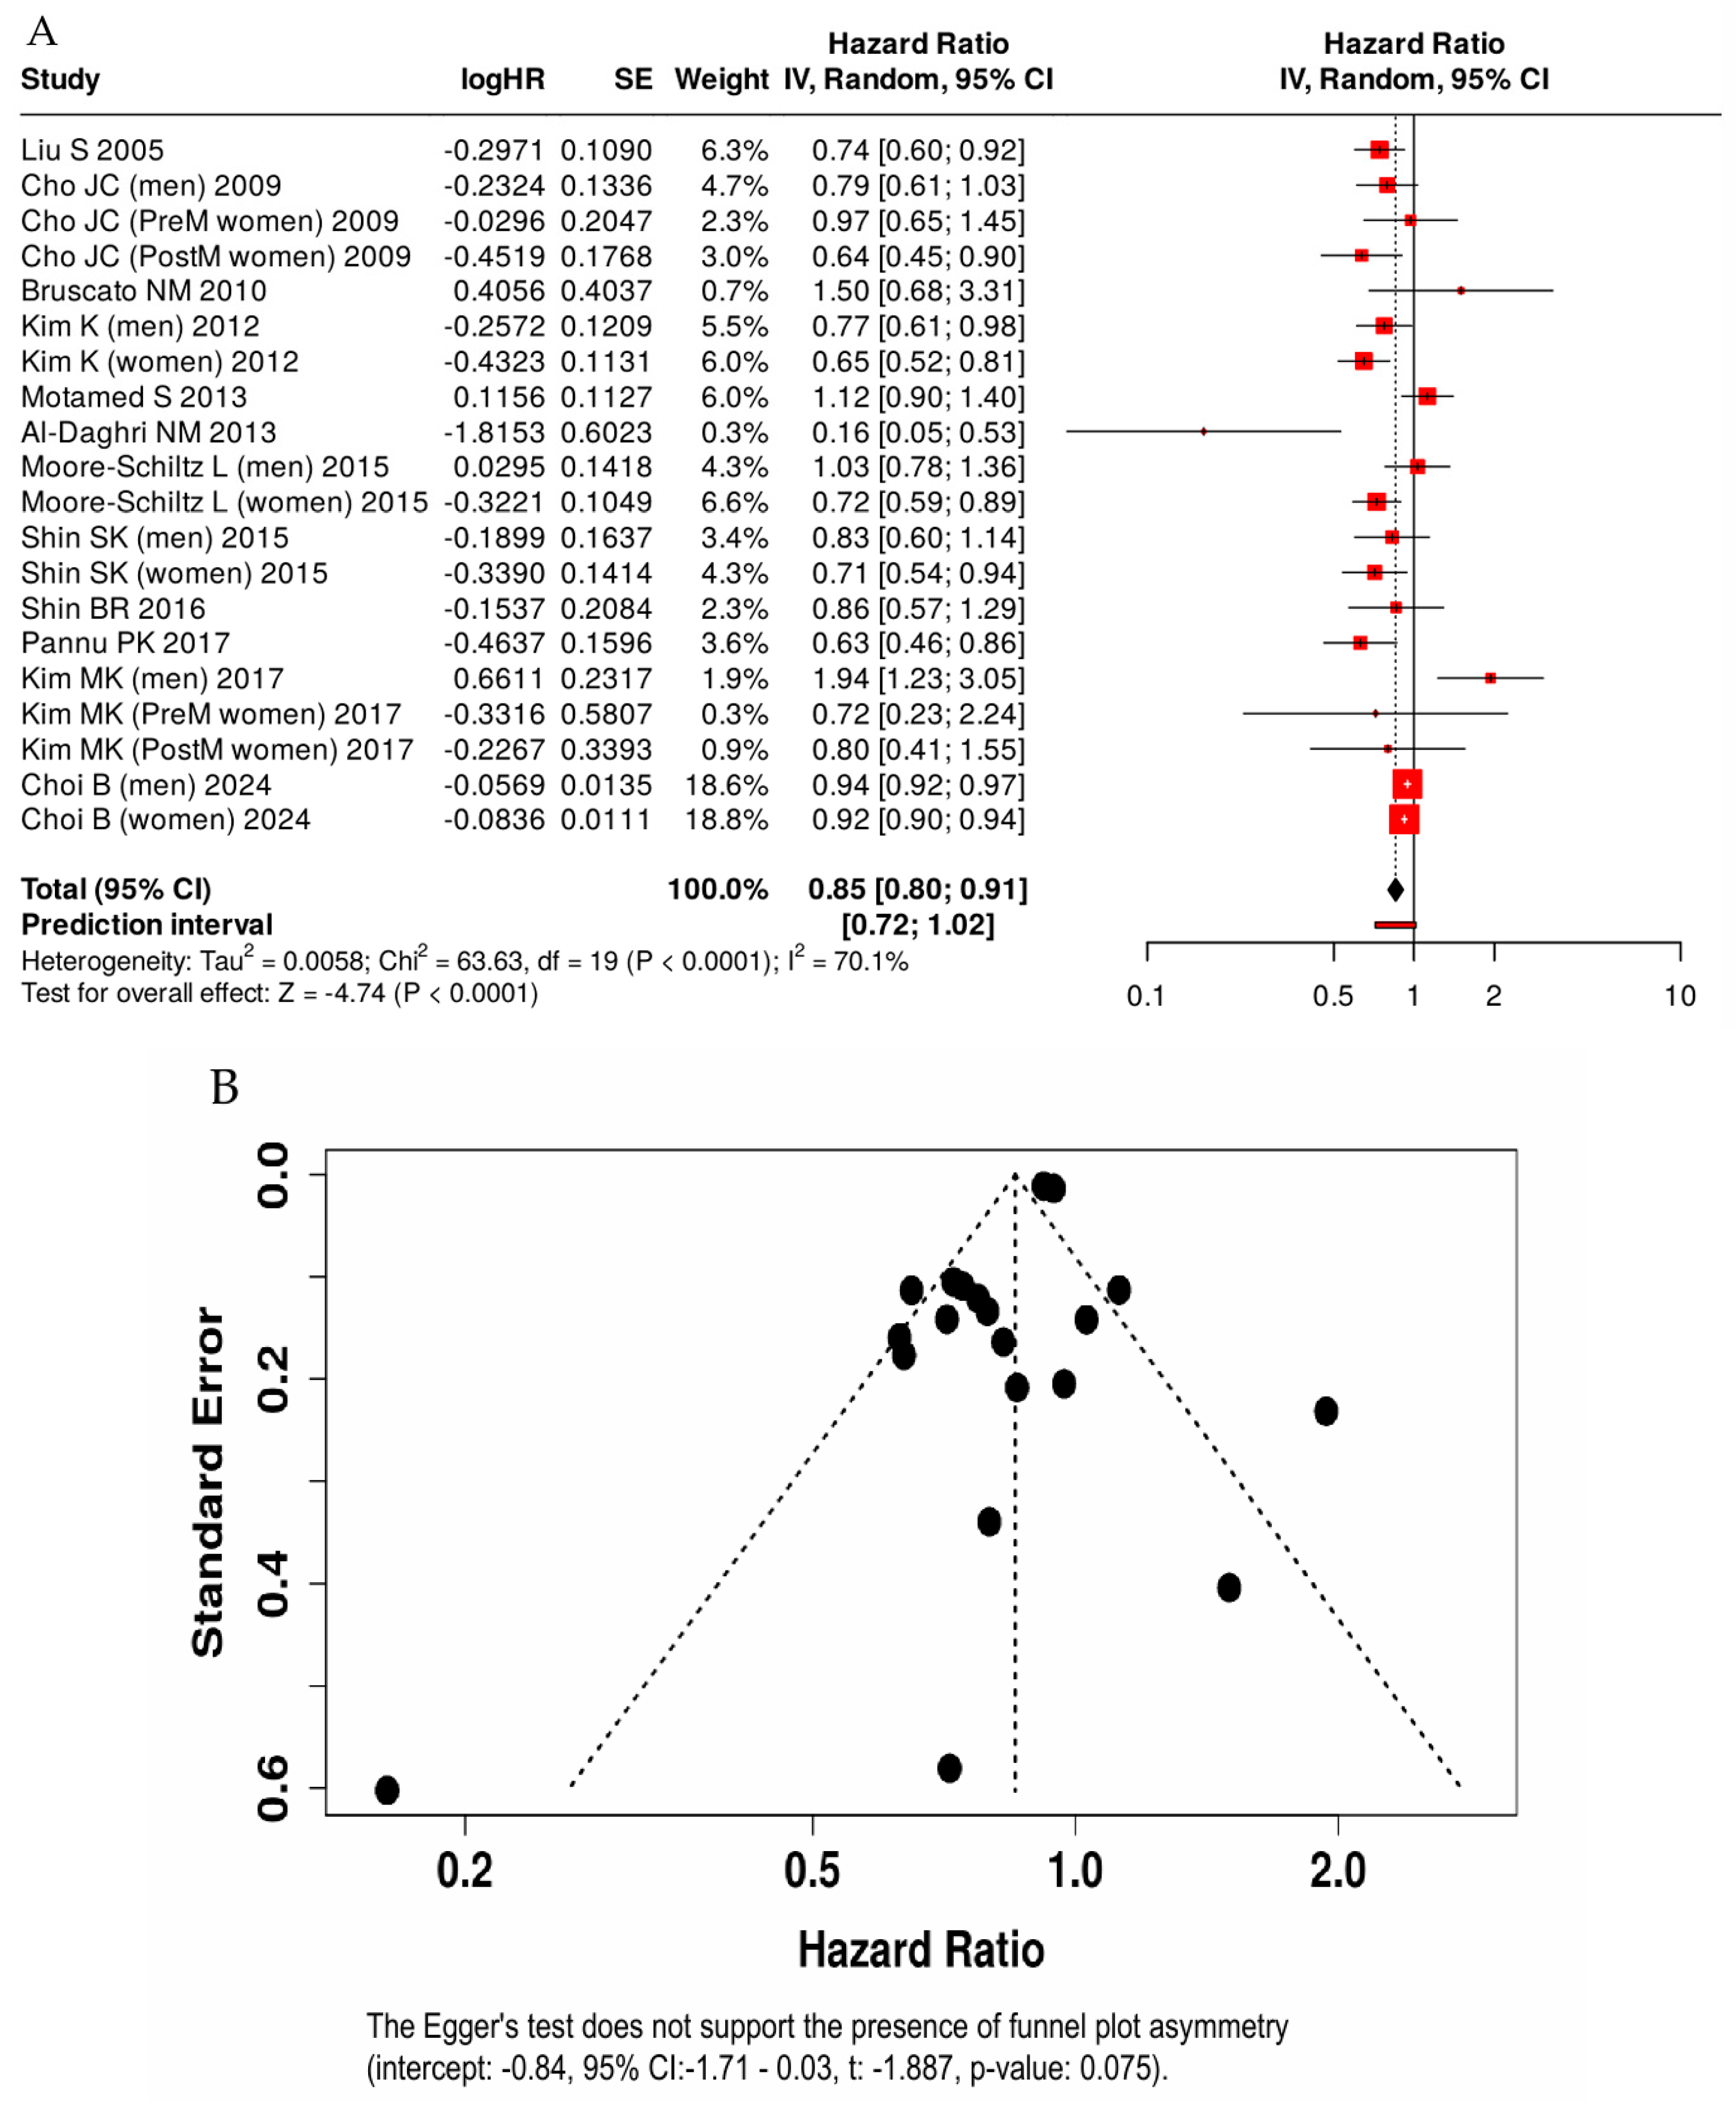
Moreover, all studies were conducted in apparently healthy participants. Across studies, higher dietary calcium intake was associated with lower odds of metabolic syndrome, with a pooled odds ratio of 0.85 (95% CI: 0.80–0.91) [Figure 2]. Thus, the highest level of dietary calcium intake, compared with the lowest, was associated with a statistically significant 15% reduction in the odds of metabolic syndrome. Substantial relative heterogeneity was observed (I2 = 70.1%); however, the estimated between-study variance was small (τ2 = 0.005; τ ≈ 0.07), indicating limited absolute variability in effect sizes on the log-odds scale. Visual inspection of the funnel plot of log (OR) versus standard error did not indicate substantial asymmetry. This observation was supported by Egger’s regression test (p = 0.075) and Begg’s test (Kendall’s τ = −0.02, p = 0.92), suggesting no strong evidence of publication bias among the included studies.
Figure 2.
Forest plot (A) and funnel plot (B) of the association between the highest versus lowest category of dietary calcium intake and metabolic syndrome in adults [19,20,27,28,29,30,31,32,33,34,35,36].
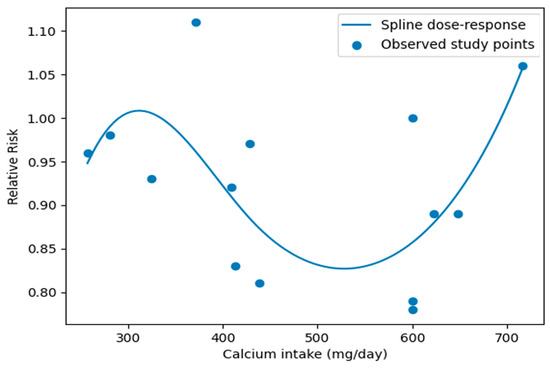
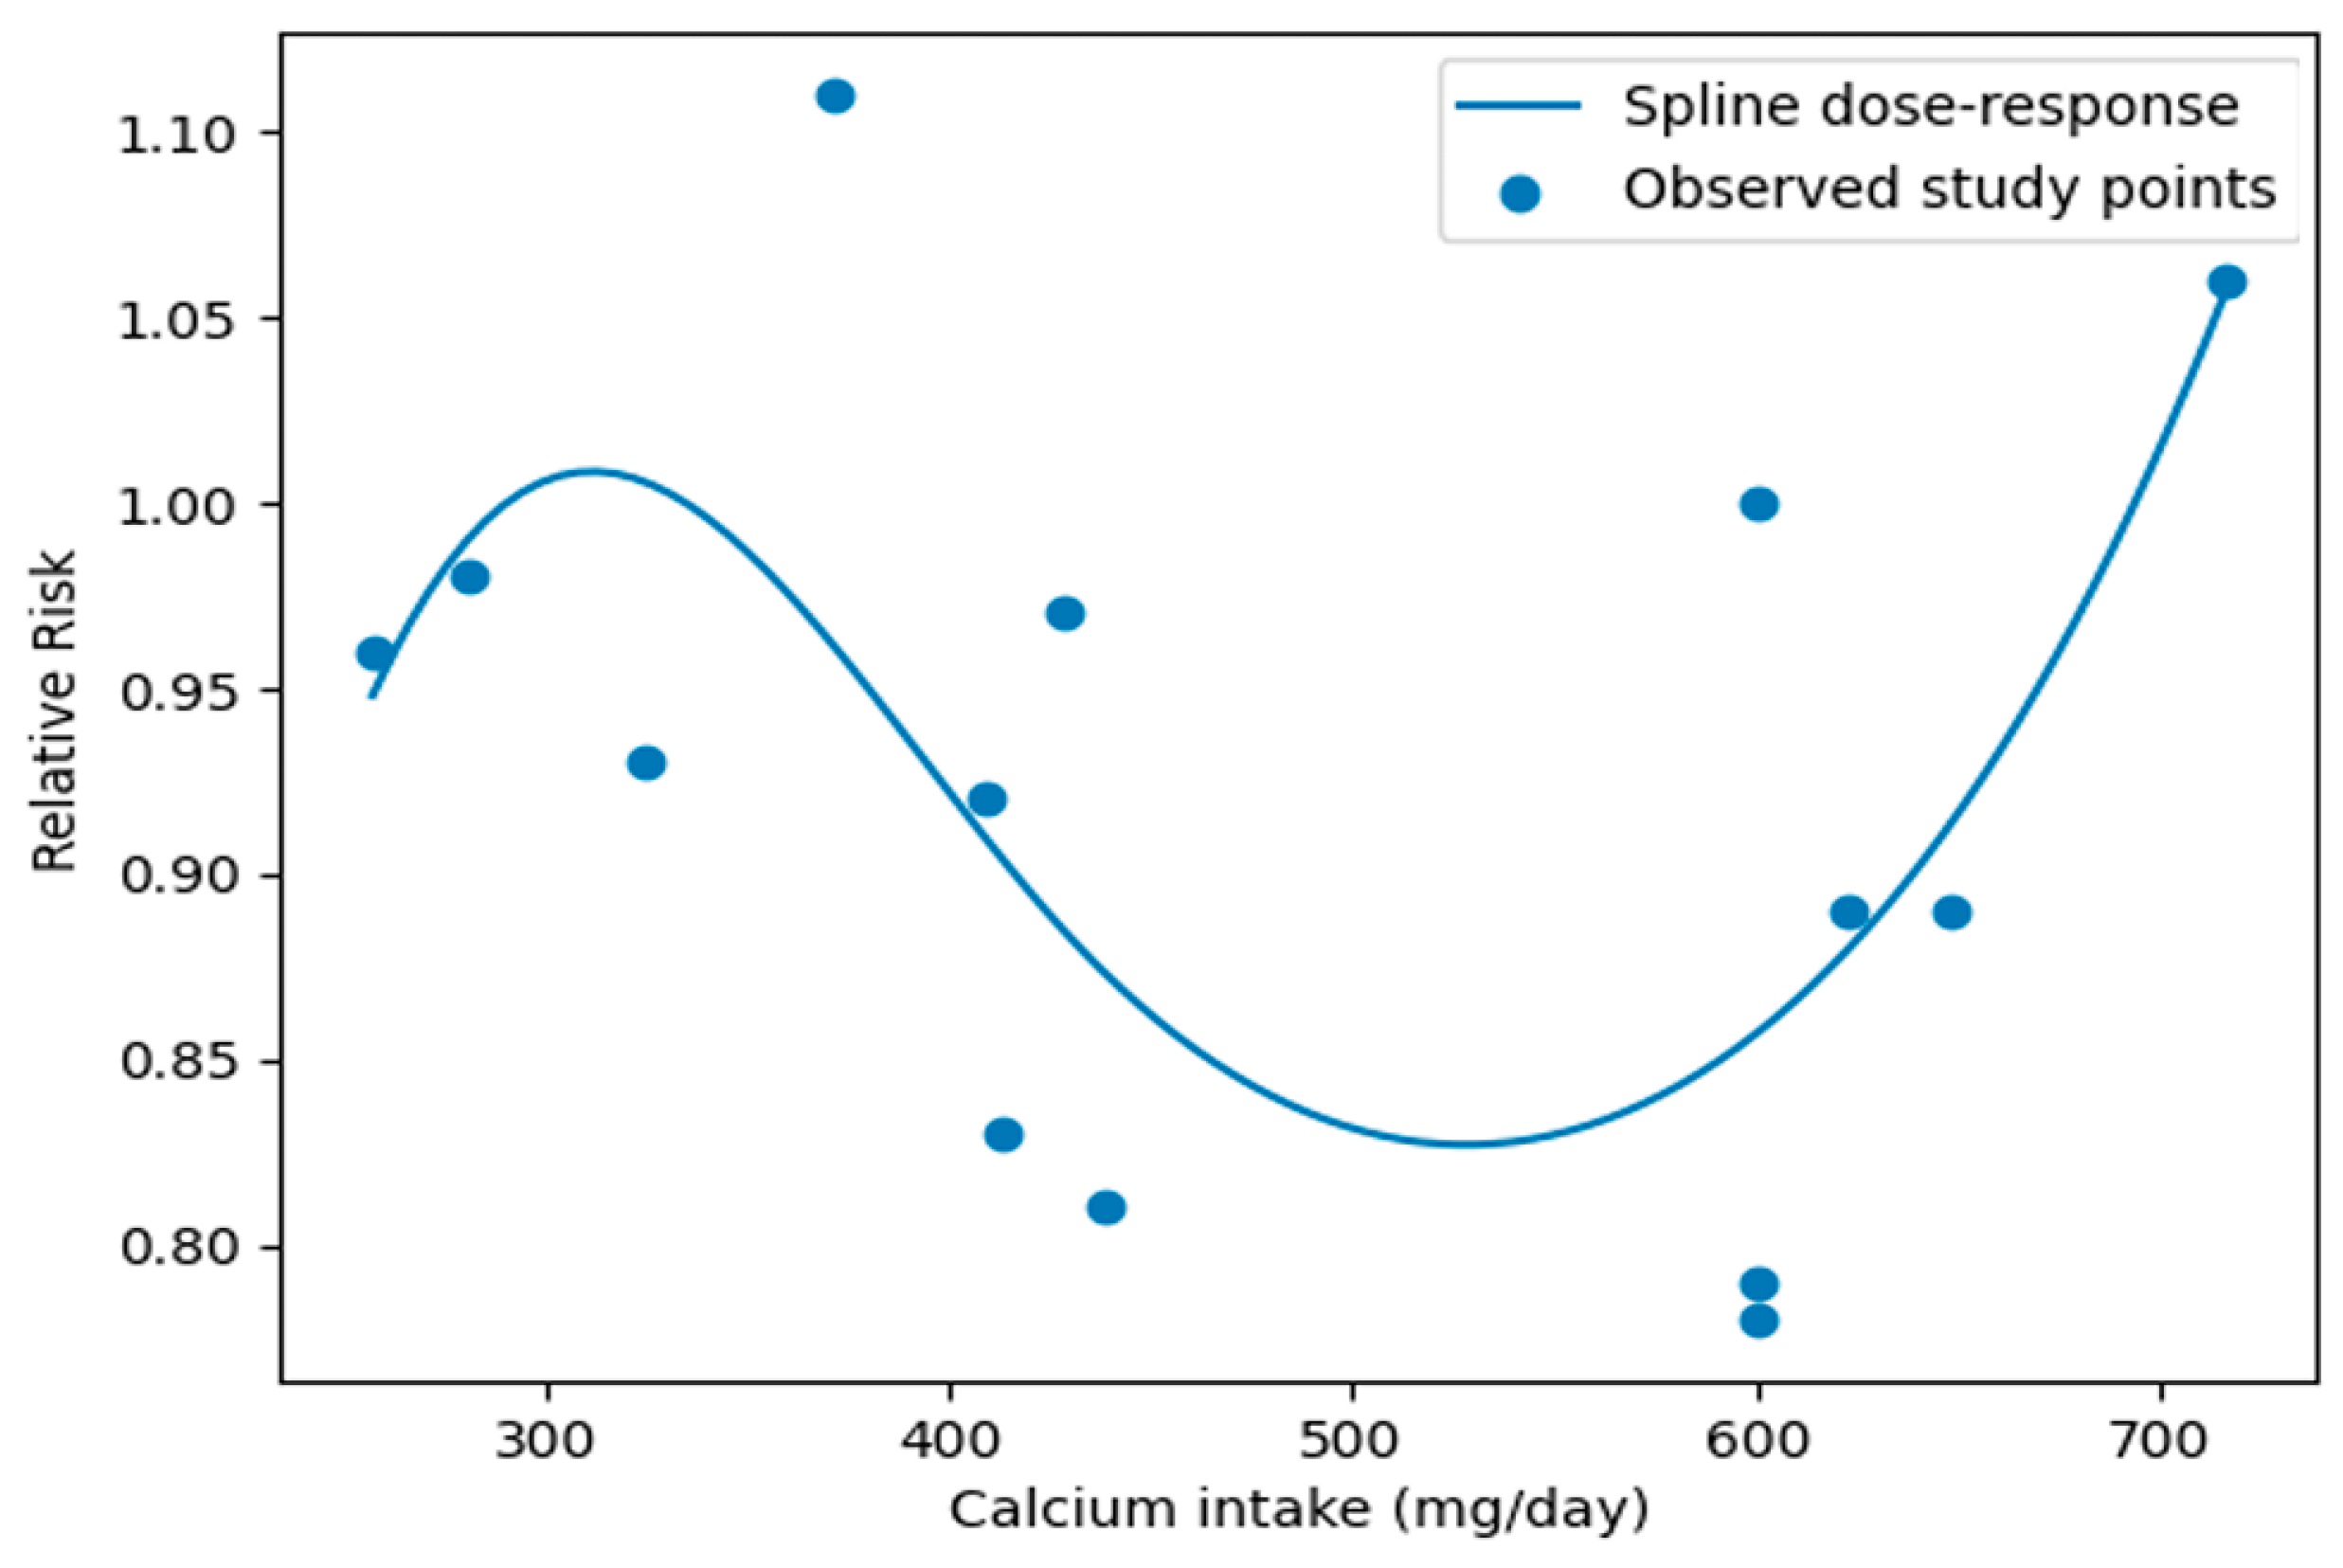
Meta-regression analyses were conducted to explore potential sources of heterogeneity, including geographic region, sex group, and dietary assessment method. The analysis showed that sex significantly moderated the association between dietary calcium intake and metabolic syndrome (β = −0.275, p = 0.038), indicating an inverse association in women compared with men. Geographic region and dietary assessment method were not significantly associated with Mets. Dose–response relationships were examined using a two-stage random-effects dose–response meta-analysis based on the method of Greenland and Longnecker. A linear dose–response analysis including 10 studies showed that each 100 mg/day increment in dietary calcium intake was associated with an approximately 2% lower odds of metabolic syndrome (OR = 0.98). Accordingly, a 300 mg/day increment corresponded to an estimated 6% lower odds of MetS (OR = 0.94) (Table S3A of the Supplementary Material). Potential nonlinear dose–response relationships were evaluated using restricted cubic splines with three knots placed at the 10th, 50th, and 90th percentiles of the exposure distribution. The nonlinear analysis indicated a significant association between dietary calcium intake and MetS, with the greatest reduction in MetS odds observed at approximately 500 mg/day of dietary calcium intake. Beyond this level, further increases in calcium intake were not associated with additional reductions in MetS odds [Figure 3]. This pattern suggests a potential threshold effect, whereby moderate dietary calcium intake may be sufficient to achieve the maximal reduction in MetS odds.
Figure 3.
Nonlinear dose–response spline: dairy calcium intake and metabolic syndrome.
3.2. Total Daily Consumption of Dairy Foods and Metabolic Syndrome
Table 2 presents the main characteristics of the studies that evaluated the association between dairy products consumption and metabolic syndrome in adults [37,38,39,40,41,42,43,44,45,46,47]. Overall, the included studies comprised a total of 70,985 men and 129,952 women. With regard to study location, seven studies were conducted in Asia, two in Europe and in Brasil and one in the USA. Dietary calcium intake was assessed using FFQs and/or 24–48 h dietary recalls. Study quality was rated as high in nine studies, moderate in two, and low in one.
Table 2.
Main characteristics of the eligible cross-sectional studies included in the systematic review and meta-analysis on the association between dairy foods/products consumption and metabolic syndrome in the adult population.
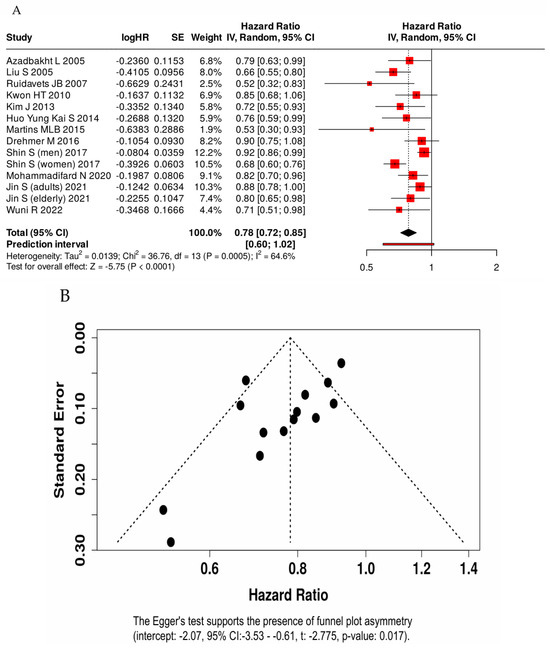
Using a random-effects model, higher total calcium intake was associated with lower odds of metabolic syndrome, with a pooled odds ratio of 0.78 (95% CI: 0.72–0.85) for the highest compared with the lowest intake category. Thus, the highest level of dairy products consumption, compared with the lowest, was associated with a 22% reduced odds of metabolic syndrome [Figure 4]. Moderate-to-substantial heterogeneity was observed across studies (I2 = 64.6%). The estimated between-study variance was modest (τ2 = 0.013; τ ≈ 0.11), indicating limited absolute variability in effect sizes across studies. Egger’s regression test showed significant funnel plot asymmetry (p = 0.016), which was confirmed by Begg rank correlation test (Kendall’s τ = −0.56, p = 0.005). Although both Egger’s and Begg’s tests indicated the presence of small-study effects, the trim-and-fill analysis showed an attenuation of the pooled effect after imputing potentially missing studies, while the association remained statistically significant. This suggests that publication bias may have inflated the magnitude of the effect, but it is unlikely to fully account for the observed association.
Figure 4.
Forest plot (A) and funnel plot (B) of the association between the highest versus lowest category of dairy food/product consumption and metabolic syndrome in adults [27,37,38,39,40,41,42,43,44,45,46,47].
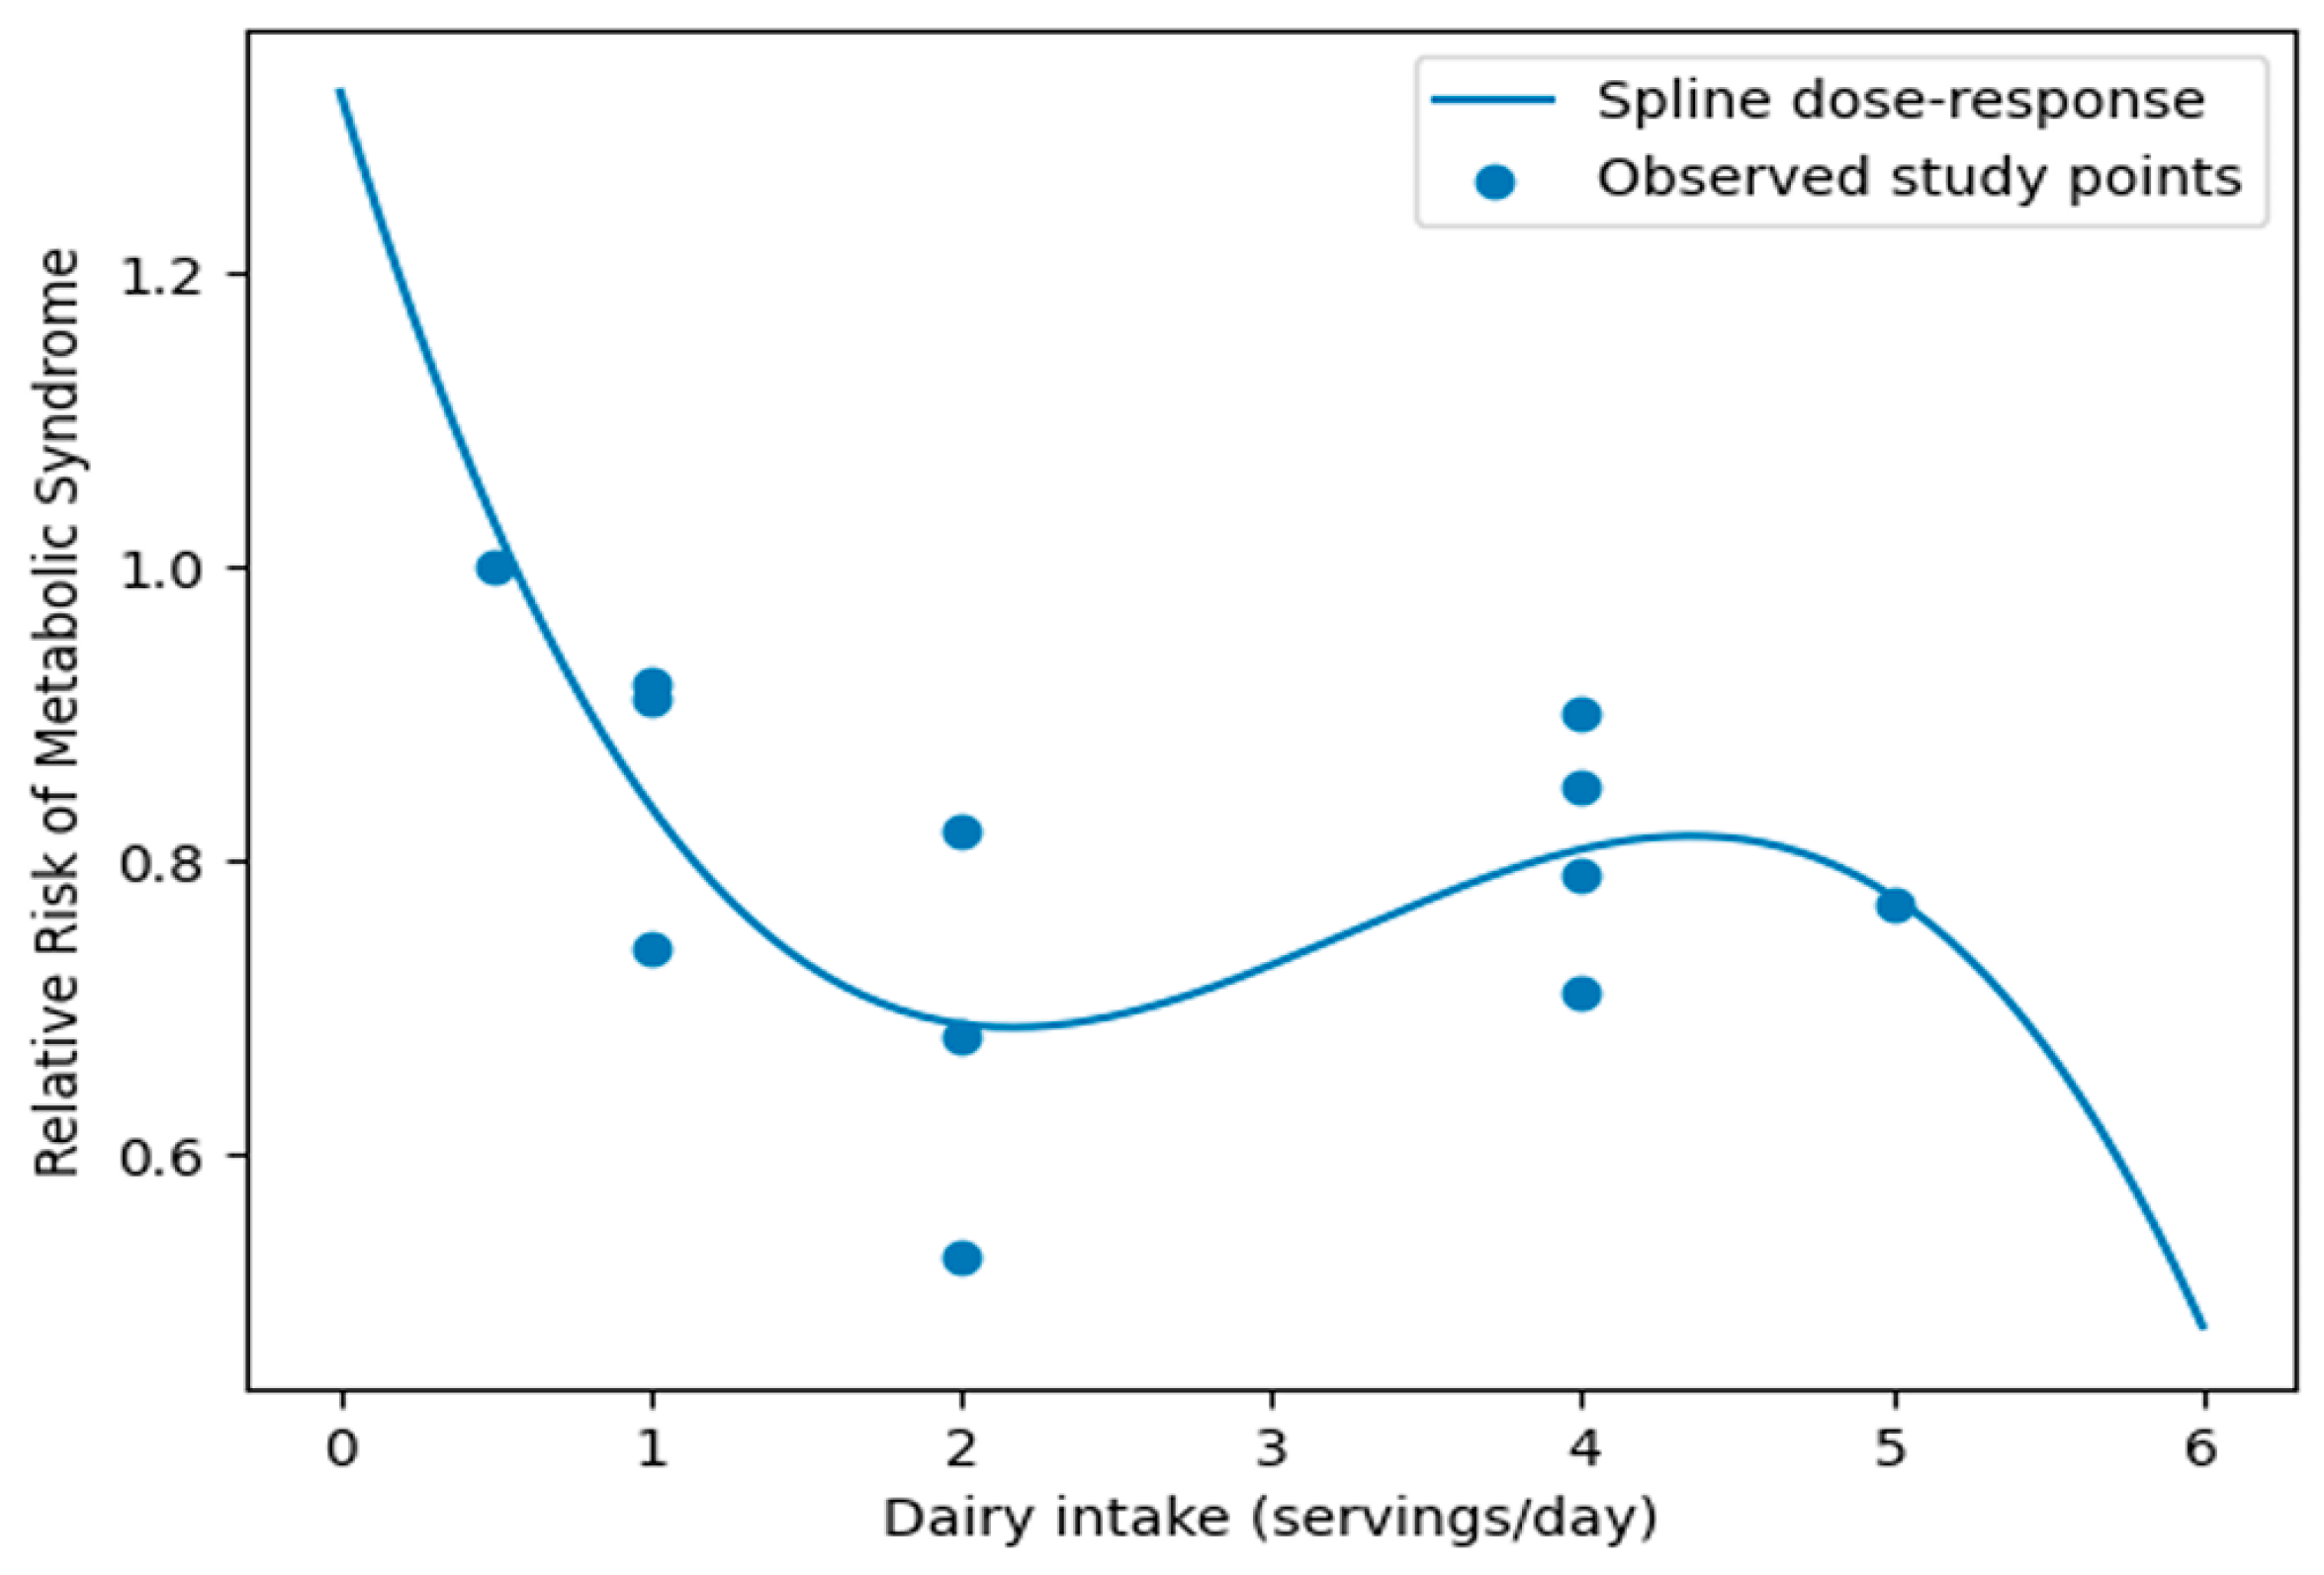
We conducted additional meta-regression analyses to explore potential sources of heterogeneity. The models included geographic region, sex group, and dietary assessment method as study-level moderators. The results indicated that sex significantly moderated the association between dairy products and metabolic syndrome, with a stronger inverse association observed in women compared with men (β = −0.302, p = 0.003). In contrast, geographic region and dietary assessment method were not significantly associated with the effect size. These findings suggest that sex differences may partly explain the between-study heterogeneity observed in the analysis (Table S3B of the Supplementary Material). Dose–response relationships were examined in nine studies where dairy product intake could be evaluated in terms of servings per day, using a two-stage random-effects dose–response meta-analysis based on the Greenland and Longnecker method. A linear dose–response analysis showed that 1-serving/day increment in dairy intake was associated with an 8% lower risk of metabolic syndrome (OR 0.92, 95% CI 0.90–0.95). A restricted cubic spline dose–response meta-analysis showed a nonlinear inverse association between dairy intake and metabolic syndrome. The steepest reduction in risk was observed up to approximately 2 servings/day, after which the association plateaued [Figure 5].
Figure 5.
Nonlinear dose–response spline: dairy products and metabolic syndrome.
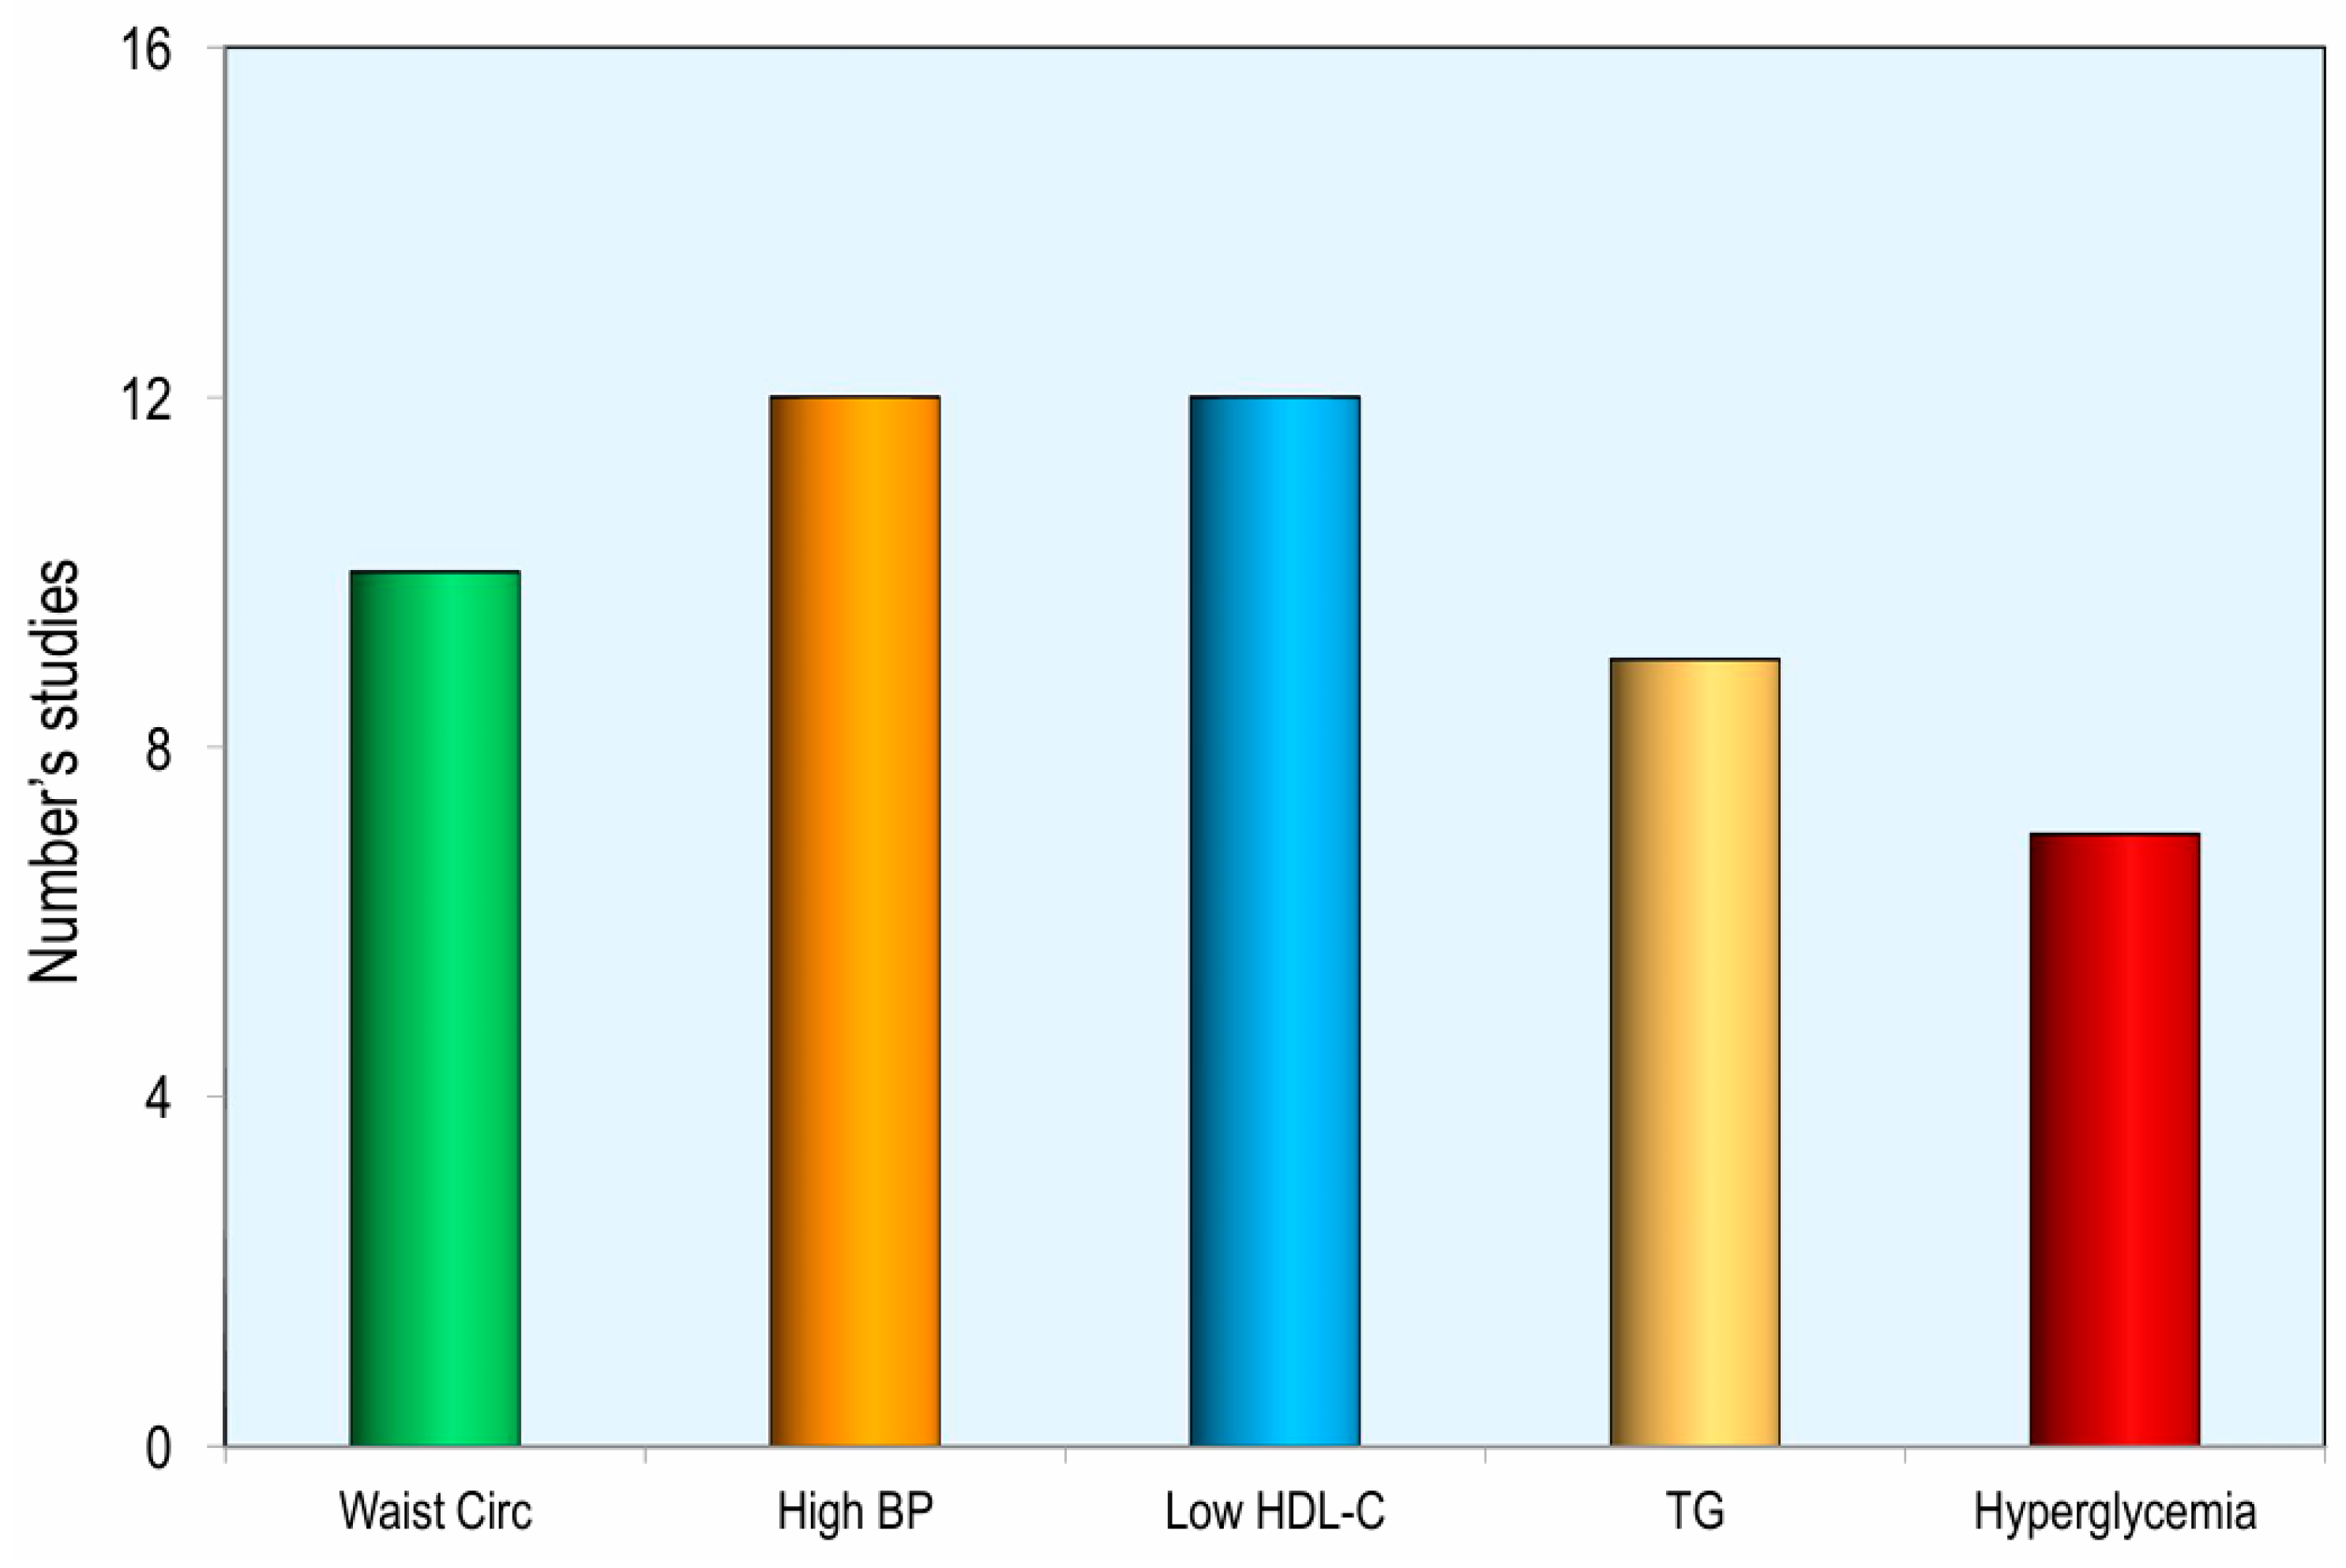
Sixteen studies examined the association between dietary calcium intake and the odds of individual components of metabolic syndrome. Higher calcium intake, from either total dietary sources or dairy products, was associated with significantly lower odds of elevated blood pressure and low HDL cholesterol in 12 studies, increased waist circumference in 10 studies, elevated triglycerides in 9 studies, and fasting hyperglycemia in 7 studies [Figure 6].
Figure 6.
Number of studies reporting a significant difference in the odds of individual metabolic syndrome components between the highest and lowest calcium intake groups (BP = Blood Pressure; C-HDL = High-Density Lipoprotein Cholesterol, TG = Triglycerides).
4. Discussion
The majority of cross-sectional studies included in this meta-analysis indicate that dietary calcium intake is inversely associated with the odds of metabolic syndrome in adults. This association was not observed only in the studies by Bruscato and Motamed [29,31]. In particular, in the study by Bruscato et al., the lack of association may be explained by the characteristics of the study population, which consisted exclusively of postmenopausal women older than 65 years, suggesting that nutritional factors may exert a stronger influence on MetS development at younger ages [29]. Moreover, estrogen deficiency may contribute to these age-related differences, as estrogens enhance calcium absorption and exert beneficial metabolic effects, including improvements in insulin sensitivity, reductions in inflammation, and limitation of abdominal fat accumulation [48,49]. Supporting this evidence, studies that analyzed men and women separately consistently reported a stronger protective effect of calcium intake in women than in men [28,30,32,33,35]. Similarly, in the study by Shin S. et al. [44], higher milk consumption was associated with lower odds of MetS, with a more pronounced inverse association in females. Numerous studies have demonstrated an association between dairy products with MetS [37,50]. However, this association often loses statistical significance after adjustment for calcium intake, highlighting the central role of this mineral [42]. Milk is a rich source of bioactive compounds that may improve metabolic efficiency and target multiple components of MetS; nevertheless, calcium appears to represent a key mediator of these beneficial effects. Importantly, the source of calcium seems to be a critical determinant. In a study by Shin BR et al., a paradoxical finding was reported, whereby obese males with the highest calcium intake who did not consume dairy products showed an increased incidence of MetS [34]. This observation suggests that both the dietary source of calcium and obesity status may significantly modify the association between calcium intake and MetS risk. This factor should therefore be carefully considered when interpreting associations between calcium intake and metabolic outcomes. Whether calcium supplementation can replicate the beneficial effects observed with dietary calcium remains unclear, and the optimal supplemental dose has yet to be established. Moreover, although higher dietary calcium intake has been associated with a reduced risk of metabolic syndrome in several studies, elevated serum calcium concentrations have conversely been linked to an increased likelihood of developing metabolic syndrome [51]. This apparent discrepancy suggests that the metabolic effects of calcium may depend on its dietary source and physiological regulation rather than on total systemic calcium levels alone. Collectively, these findings underscore the importance of promoting an overall healthy dietary pattern rather than reliance on isolated nutrient supplementation. Consistent with the previous literature, the present meta-analysis confirms that higher total dietary calcium intake and dairy consumption are inversely associated with the risk of individual components of metabolic syndrome [13,15]. Furthermore, the protective effect of dietary calcium appears to be more pronounced for blood pressure and lipid profiles. Several studies have reported that dairy foods may exert beneficial effects on blood pressure [17]. The beneficial effects of dairy foods on metabolic syndrome may extend beyond their calcium content and may be attributed to the complex dairy matrix, likely reflecting the combined action of bioactive peptides, whey proteins, specific fatty acids, vitamins, and fermentation-derived compounds that can favorably modulate insulin sensitivity, blood pressure, inflammation, and gut microbiota composition [52]. In particular, adequate calcium intake has been shown to modulate the renin–angiotensin–aldosterone system and improve the sodium–potassium balance, thereby contributing to blood pressure reduction [53]. Blood pressure is tightly regulated by intracellular calcium concentrations in vascular smooth muscle cells, which influence vasoconstriction and vascular tone. Low dietary calcium intake appears to activate multiple hypertensive mechanisms, including increased secretion of the parathyroid hormone, which elevates intracellular calcium directly and via calcitriol activation, and stimulation of the renin–angiotensin–aldosterone system, leading to enhanced sodium and water reabsorption and subsequent expansion of vascular volume [54]. Increased dietary calcium reduces intracellular Ca2+ influx in adipocytes, thereby decreasing fatty acid synthesis and enhancing lipolysis, which results in reduced triglyceride storage. Moreover, calcium, which is abundant in milk and yogurt, can bind fatty acids and bile acids in the intestine, increasing fecal fat excretion and inhibiting lipid reabsorption [16]. Consequently, higher calcium intake may contribute to an improvement in the HDL-cholesterol to LDL-cholesterol ratio [16,18] and a reduction in fat mass, particularly in females [55]. However, despite the aforementioned positive effects of dietary calcium intake on the various components of the metabolic syndrome, studies that have evaluated the relationship between calcium intake and cardiovascular diseases such as stroke and coronary syndromes have reported inconclusive results [56]. Beyond lipid metabolism, calcium may exert additional benefits through its effects on oxidative stress and inflammation. Both oxidative stress and chronic low-grade inflammation are recognized as key contributors to the development and progression of metabolic syndrome [57]. Evidence suggests that adherence to a Mediterranean dietary pattern and higher dietary calcium intake may exert antioxidant effects, providing an additional layer of protection against MetS [58]. From a nutrigenomic perspective, the role of calcium appears particularly relevant. Nutrigenomics, which investigates interactions between nutrients and genetic variants, has shown that dietary patterns, such as high-fat diets, can modulate genetic susceptibility to MetS [59]. In a study conducted in a Korean population, Kim et al. reported that higher calcium intake attenuated the risk of MetS among carriers of the minor alleles of rs6445834 in the ARHGEF3 gene, rs10850335 in the TBX5 gene, and rs180349 in the BUD13 gene [30]. These findings suggest that calcium intake may interact with specific genetic profiles to influence metabolic health outcomes, highlighting its potential role in personalized nutrition strategies.
Several limitations of this study should be acknowledged. First, all included studies were cross-sectional, which precludes causal inference and allows for potential residual confounding and reverse causation. Second, moderate-to-substantial heterogeneity was observed, likely reflecting differences in study populations, dietary assessment methods, and confounder adjustment. Third, calcium intake was primarily assessed using self-reported dietary instruments, which are inherently prone to measurement error. Fourth, evidence of small-study effects was detected in the analysis of dairy consumption, which may have led to an overestimation of effect sizes. Fifth, since the study did not report results based on identical covariate models, standardizing the adjustment across studies was not feasible. Finally, the predominance of studies conducted in Asian and Western populations may limit the generalizability of the findings to other ethnic and geographic groups. This systematic review and meta-analysis also has several notable strengths. First, it is based on a large overall sample size, providing high statistical power and precise effect estimates. The inclusion of studies assessing both total dietary calcium intake and calcium derived from dairy products allowed evaluation of different dietary sources of calcium. Most included studies were of moderate-to-high methodological quality and involved apparently healthy adults, reducing the likelihood of disease-related reverse causation. The consistency of inverse associations across several components of metabolic syndrome, particularly blood pressure and HDL cholesterol, supports the biological plausibility of the findings. Additionally, the use of random-effects models and multiple approaches to assess publication bias enhanced the robustness and generalizability of the results.
5. Conclusions
In conclusion, this systematic review and meta-analysis provides robust evidence of an inverse association between dietary calcium intake and metabolic syndrome in adults, with a more pronounced protective effect in women. Evidence suggests that calcium is a key mediator of the beneficial effects of dairy products on metabolic health, particularly on blood pressure and lipid profiles. Biological plausibility is supported by mechanisms involving lipid metabolism, blood pressure regulation, inflammation, and gene–diet interactions. However, the cross-sectional nature of the included studies precludes any inference of causality between calcium intake and MetS. Well-designed prospective and interventional studies are warranted to clarify whether this relationship is causal and to define optimal dietary recommendations. Overall, these findings support recommendations promoting adequate calcium intake from foods within healthy dietary patterns, given its potential contribution to a lower risk of metabolic syndrome and better cardiometabolic health.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/nu18061006/s1, Supplementary Table S1A: Details of quality assessment of included studies in the systematic review and met-analysis based on Newcastle-Ottawa Scale adapted for cross-sectional studies on dietary calcium intake. Supplementary Table S1B: Details of quality assessment of included studies in the systematic review and met-analysis based on Newcastle-Ottawa Scale adapted for cross-sectional studies on dairy products. Supplementary Table S2A: GRADE evidence Profile of dietary calcium intake and MetS. Supplementary Table S2B: GRADE evidence Profile of dairy products and MetS. Supplementary Table S3A: Meta-regression analysis Dietary Calcium Intake and MetS. Supplementary Table S3B: Meta-regression analysis Dairy Products and MetS. References [19,20,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41,42,43,44,45,46,47] are cited in the supplementary materials.
Author Contributions
Conceptualization, S.G. (Stefano Gonnelli), A.A.R. and C.C.; methodology, S.G. (Sara Gonnelli) and A.A.R.; formal analysis, C.C. and A.C.; data curation, S.G. (Sara Gonnelli), C.M. and G.C.; writing—original draft preparation, S.G. (Stefano Gonnelli); writing—review and editing, C.C.; visualization, S.G. (Stefano Gonnelli) and A.A.R. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Where no new data were created.
Acknowledgments
The authors have reviewed and edited the output and take full responsibility for the content of this publication.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| MetS | Metabolic syndrome |
| ORs | Odds Ratios |
| CIs | Confidence intervals |
| FFQs | Food Frequency Questionnaires |
| LDL | Low-Density Lipoprotein |
| HDL | High-Density Lipoprotein |
| DASH | Dietary Approaches to Stop Hypertension |
| NOS | Newcastle-Ottawa Scale |
| NCEP ATPIII | Third Report of the National Cholesterol Education Program Adult Treatment Panel |
| IDF | International Diabetes Federation |
| JIS | Joint Interim Statement of the International Diabetes Federation |
References
- Reaven, G.M. Banting Lecture 1988. Role of insulin-resistance in human disease. Diabetes 1988, 37, 1595–1607. [Google Scholar] [CrossRef] [Scilit]
- Expert Panel on Detection, Evaluation, and Treatment of High Blood Cholesterol in Adults. Executive summary of the third report of the National Cholesterol Education Program (NCEP) expert panel on detection, evaluation, and treatment of high blood cholesterol in adults (Adult Treatment Panel III). J. Am. Med. Assoc. 2001, 285, 2486–2497. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Obunai, K.; Jani, S.; Dangas, G.D. Cardiovascular morbidity and mortality of the metabolic syndrome. Med. Clin. N. Am. 2007, 91, 1169–1184. [Google Scholar] [CrossRef] [Scilit]
- Noubiap, J.J.; Nansseu, J.R.; Lontchi-Yimagou, E.; Nkeck, J.R.; Nyaga, U.F.; Ngouo, A.T.; Tounouga, D.N.; Tianyi, F.L.; Foka, A.J.; Ndoadoumgue, A.L.; et al. Geographic distribution of metabolic syndrome and its components in the general adult population: A meta-analysis of global data from 28 million individuals. Diabetes Res. Clin. Pract. 2022, 188, 109924. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hirode, G.; Wong, R.J. Trends in the prevalence of metabolic syndrome in the United States, 2011–2016. J. Am. Med. Assoc. 2020, 323, 2526–2528. [Google Scholar] [CrossRef] [Scilit]
- Cicero, A.F.; Dormi, A.; D’Addato, S.; Gaddi, A.V.; Borghi, C. Long-term effect of a dietary education program on postmenopausal cardiovascular risk and metabolic syndrome: The Brisighella Heart Study. J. Womens Health 2010, 19, 133–137. [Google Scholar] [CrossRef] [Scilit]
- Esposito, K.; Marfella, R.; Ciotola, M.; Di Palo, C.; Giugliano, F.; Giugliano, G.; Armiento, P.; Giugliano, D. Effect of a Mediterranean-style diet on endothelial dysfunction and markers of vascular inflammation in the metabolic syndrome: A randomized trial. J. Am. Med. Assoc. 2004, 292, 1440–1446. [Google Scholar] [CrossRef] [Scilit]
- Kastorini, C.M.; Milionis, H.J.; Esposito, K.; Giugliano, D.; Goudevenos, J.A.; Panagiotakos, D.B. The effect of Mediterranean diet on metabolic syndrome and its components: A meta-analysis of 50 studies and 534,906 individuals. J. Am. Coll. Cardiol. 2011, 57, 1299–1313. [Google Scholar] [CrossRef] [Scilit]
- Siervo, M.; Lara, J.; Chowdhury, S.; Ashor, A.; Oggioni, C.; Mathers, J.C. Effects of the DASH diet on cardiovascular risk factors: A systematic review and meta-analysis. Br. J. Nutr. 2015, 113, 1–15. [Google Scholar] [CrossRef] [Scilit]
- Angelico, F.; Baratta, F.; Coronati, M.; Ferro, D.; Del Ben, M. Diet and metabolic syndrome: A narrative review. Intern. Emerg. Med. 2023, 18, 1007–1017. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, M.; Pan, A.; Malik, V.S.; Hu, F.B. Effects of dairy intake on body weight and fat: A meta-analysis of randomized controlled trials. Am. J. Clin. Nutr. 2012, 96, 735–747. [Google Scholar] [CrossRef] [Scilit]
- Crichton, G.E.; Bryan, J.; Buckley, J.; Murphy, K.J. Dairy consumption and metabolic syndrome: A systematic review of findings and methodological issues. Obes. Rev. 2011, 12, e190–e201. [Google Scholar] [CrossRef] [Scilit]
- Lee, M.; Lee, H.; Kim, J. Dairy food consumption is associated with a lower risk of the metabolic syndrome and its components: A systematic review and meta-analysis. Br. J. Nutr. 2018, 120, 373–384. [Google Scholar] [CrossRef] [Scilit]
- Cho, Y.A.; Kim, J.; Cho, E.R. Calcium intake and the risk of metabolic syndrome in Korean adults: The Korean National Health and Nutrition Examination Survey (KNHANES IV). Public Health Nutr. 2011, 15, 330–338. [Google Scholar]
- Cheng, L.; Hu, D.; Jiang, W. Dietary calcium intake and the risk of metabolic syndrome: Evidence from observational studies. Public Health Nutr. 2019, 22, 2055–2062. [Google Scholar] [CrossRef] [Scilit]
- Zemel, M.B.; Shi, H.; Greer, B.; Dirienzo, D.; Zemel, P.C. Regulation of adiposity by dietary calcium. FASEB J. 2000, 14, 1132–1138. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McCarron, D.A.; Morris, C.D.; Cole, C. Dietary calcium and blood pressure control: Lessons learned from controlled clinical trials. Curr. Opin. Lipidol. 2001, 12, 37–39. [Google Scholar]
- Hajhashemy, Z.; Rouhani, P.; Saneei, P. Dietary calcium intake in relation to blood lipids and lipoproteins profiles: A systematic review and meta-analysis of epidemiologic studies. Nutr. Metab. Cardiovasc. Dis. 2022, 32, 1609–1626. [Google Scholar] [CrossRef] [Scilit]
- Al-Daghri, N.M.; Khan, N.; Alkharfy, K.M.; Al-Attas, O.S.; Alokail, M.S.; Alfawaz, H.A.; Al-Othman, A.M.; Vanhoutte, P.M. Selected dietary nutrients and the prevalence of metabolic syndrome in adult males and females in Saudi Arabia: A pilot study. Nutrients 2013, 5, 4587–4604. [Google Scholar] [CrossRef] [Scilit]
- Pannu, P.K.; Zhao, Y.; Soares, M.J.; Piers, L.S.; Ansari, Z. The associations of vitamin D status and dietary calcium with the metabolic syndrome: An analysis of the Victorian health monitor survey. Public Health Nutr. 2017, 20, 1785–1796. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grundy, S.M.; Brewer, H.B., Jr.; Cleeman, J.I.; Smith, S.C., Jr.; Lenfant, C. Definition of Metabolic Syndrome: Report of the National Heart, Lung, and Blood Institute/American Heart Association Conference on Scientific Issues Related to Definition. Circulation 2004, 109, 433–438. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alberti, K.G.; Zimmet, P.; Shaw, J. The metabolic syndrome: A new worldwide definition. Lancet 2005, 366, 1059–1062. [Google Scholar] [CrossRef] [Scilit]
- Alberti, K.G.; Eckel, R.H.; Grundy, S.M.; Zimmet, P.Z.; Cleeman, J.I.; Donato, K.A.; Fruchart, J.C.; James, W.P.; Loria, C.M.; Smith, S.C., Jr. Harmonizing the metabolic syndrome: A joint interim statement of the International Diabetes Federation Task Force on Epidemiology and Prevention; National Heart, Lung, and Blood Institute; American Heart Association; World Heart Federation; International Atherosclerosis Society; and International Association for the Study of Obesity. Circulation 2009, 120, 1640–1645. [Google Scholar]
- Guyatt, G.H.; Oxman, A.D.; Vist, G.E.; Kunz, R.; Falck-Ytter, Y.; Alonso-Coello, P.; Schünemann, H.J. GRADE: An emerging consensus on rating quality of evidence and strength of recommendations. BMJ 2008, 336, 924–926. [Google Scholar] [CrossRef] [Scilit]
- Greenland, S.; Longnecker, M.P. Methods for trend estimation from summarized dose-response data, with applications to meta-analysis. Am. J. Epidemiol. 1992, 135, 1301–1309. [Google Scholar] [CrossRef] [Scilit]
- Liu, S.; Song, Y.; Ford, E.S.; Manson, J.E.; Buring, J.E.; Ridker, P.M. Dietary calcium, vitamin D, and the prevalence of metabolic syndrome in middle aged and older U.S. women. Diabetes Care 2005, 28, 2926–2932. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cho, G.J.; Park, H.T.; Shin, J.H.; Hur, J.Y.; Kim, Y.T.; Moon, H.S.; Kim, S.H. Calcium intake is inversely associated with metabolic syndrome in postmenopausal women: Korea National Health and Nutrition Survey, 2001 and 2005. Menopause 2009, 16, 992–997. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bruscato, N.M.; da Costa Vieira, J.L.; do Nascimento, N.M. Dietary intake is not associated to the metabolic syndrome in elderly women. N. Am. J. Med. Sci. 2010, 2, 182–186. [Google Scholar]
- Kim, K.; Yang, Y.J.; Kim, K.; Kim, M.K. Interactions of single nucleotide polymorphisms with dietary calcium intake on the risk of metabolic syndrome. Am. J. Clin. Nutr. 2012, 95, 231–240. [Google Scholar] [CrossRef] [Scilit]
- Motamed, S.; Ebrahimi, M.; Safarian, M.; Ghayour-Mobarhan, M.; Mouhebati, M.; Azimi-Nezhad, M.; Ferns, G.A. Micronutrient intake and the presence of the metabolic syndrome. N. Am. J. Med. Sci. 2013, 5, 377–385. [Google Scholar]
- Moore-Schiltz, L.; Albert, J.M.; Singer, M.E.; Swain, J.; Nock, N.L. Dietary intake of calcium and magnesium and the metabolic syndrome in the National Health and nutrition examination (NHANES) 2001–2010 data. Br. J. Nutr. 2015, 114, 924–935. [Google Scholar] [CrossRef] [Scilit]
- Shin, S.K.; Kim, M.K.; Lee, Y.H.; Shin, D.H.; Chun, B.Y.; Choi, B.Y. The cross-sectional relationship between dietary calcium intake and metabolic syndrome among men and women aged 40 or older in rural areas of Korea. Nutr. Res. Pract. 2015, 9, 328–335. [Google Scholar] [CrossRef] [Scilit]
- Shin, B.R.; Choi, Y.K.; Kim, H.N.; Song, S.W. High dietary calcium intake and a lack of dairy consumption are associated with metabolic syndrome in obese males: The Korean National Health and Nutrition Examination Survey 2010 to 2012. Nutr. Res. 2016, 36, 518–525. [Google Scholar] [CrossRef] [Scilit]
- Kim, M.; Chon, S.; Noe, E.; Kim, J.; Oh, S.S.; Woo, J.T.; Kim, S.W.; Kim, J.W. Associations of dietary calcium intake with metabolic syndrome and bone mineral density among the Korean population: KNHANES 2008–2011. Osteoporos. Int. 2017, 28, 299–308. [Google Scholar]
- Choi, B.; Kim, J.; Kim, Y.; Shin, J.; Lee, S.A. Calcium- and Sodium-Rich Food Intake among Koreans with and without Metabolic Syndrome: Cross-Sectional Analysis of the Korean Genome and Epidemiology Study. Nutrients 2024, 16, 2439. [Google Scholar]
- Azadbakht, L.; Mirmiran, P.; Esmaillzadeh, A.; Azizi, F. Dairy consumption is inversely associated with the prevalence of the metabolic syndrome in Tehranian adults. Am. J. Clin. Nutr. 2005, 82, 523–530. [Google Scholar] [CrossRef]
- Ruidavets, J.B.; Bongard, V.; Dallongeville, J.; Arveiler, D.; Ducimetiere, P.; Perret, B.; Simon, C.; Amouyel, P.; Ferrieres, J. High consumptions of grain, fish, dairy products and combinations of these are associated with a low prevalence of metabolic syndrome. J. Epidemiol. Community Health 2007, 61, 810–817. [Google Scholar] [CrossRef] [Scilit]
- Kwon, H.T.; Lee, C.M.; Park, J.H.; Ko, B.P.; Wee, H.L.; Kim, C.H.; Kim, S.; Cho, B. Milk intake and its association with metabolic syndrome in Korean: Analysis of the third Korea National Health and Nutrition Examination Survey (KNHANES III). J. Korean Med. Sci. 2010, 25, 1473–1479. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, J. Dairy food consumption is inversely associated with the risk of the metabolic syndrome in Korean adults. J. Hum. Nutr. Diet. 2013, 26, 171–179. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huo Yung Kai, S.; Bongard, V.; Simon, C.; Ruidavets, J.B.; Arveiler, D.; Dallongeville, J.; Ferrieres, J. Low-fat and high-fat dairy products are differently related to blood lipids and cardiovascular risk score. Eur. J. Prev. Cardiol. 2014, 21, 1557–1567. [Google Scholar]
- Martins, M.L.; Kac, G.; Silva, R.A.; Bessa, A.R.; Moreira, A. Dairy consumption is associated with a lower prevalence of metabolic syndrome among young adults from Ribeirao Preto, Brazil. Nutrition 2015, 31, 716–721. [Google Scholar] [CrossRef] [Scilit]
- Drehmer, M.; Pereira, M.A.; Schmidt, M.I.; Alvim, S.; Lotufo, P.A.; Luft, V.C.; Duncan, B.B. Total and Full-Fat, but Not Low-Fat, Dairy Product Intakes are Inversely Associated with Metabolic Syndrome in Adults. J. Nutr. 2016, 146, 81–89. [Google Scholar] [CrossRef] [Scilit]
- Shin, S.; Lee, H.W.; Kim, C.E.; Lim, J.; Lee, J.K.; Kang, D. Association between Milk Consumption and Metabolic Syndrome among Korean Adults: Results from the Health Examinees Study. Nutrients 2017, 9, 1102. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mohammadifard, N.; Akhavan-Tabib, A.; Sajjadi, F.; Alikhasi, H.; Taheri, M.; Khani, A.; Karimi, S. Dairy products and metabolic syndrome among Iranian adult population: Isfahan Healthy Heart Program. Int. Dairy J. 2020, 105, 104667. [Google Scholar] [CrossRef] [Scilit]
- Jin, S.; Je, Y. Dairy Consumption and Risk of Metabolic Syndrome in Korean Adults and Elderly People. Metab. Syndr. Relat. Disord. 2021, 19, 272–280. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wuni, R.; Lakshmipriya, N.; Abirami, K.; Ventura, E.F.; Anjana, R.M.; Sudha, V.; Shobana, S.; Unnikrishnan, R.; Krishnaswamy, K.; Vimaleswaran, K.S.; et al. Higher Intake of Dairy Is Associated with Lower Cardiometabolic Risks and Metabolic Syndrome in Asian Indians. Nutrients 2022, 14, 3699. [Google Scholar] [CrossRef] [Scilit]
- Mauvais-Jarvis, F.; Clegg, D.J.; Hevener, A.L. The role of estrogens in control of energy balance and glucose homeostasis. Endocr. Rev. 2013, 34, 309–338. [Google Scholar] [CrossRef] [Scilit]
- De Paoli, M.; Zakharia, A.; Werstuck, G.H. The role of estrogen in insulin resistance: A review of clinical and preclinical data. Am. J. Pathol. 2021, 191, 1490–1498. [Google Scholar] [CrossRef] [Scilit]
- Elwood, P.C.; Pickering, J.E.; Givens, D.I.; Gallacher, J.E. The consumption of milk and dairy foods and the incidence of vascular disease and diabetes: An overview of the evidence. Lipids 2010, 45, 925–939. [Google Scholar] [CrossRef] [Scilit]
- Alsheikh, R.; Aldulaimi, H.; Hinawi, R.; Al-Sadi, F.; Al-Baker, A.; Alkuwari, A.; Sameer, M.; Al-Abdulla, G.; Shi, Z.; Rathnaiah Babu, G. Association of serum magnesium and calcium with metabolic syndrome: A cross-sectional study from the Qatar-biobank. Nutr. Metab. 2025, 22, 8. [Google Scholar] [CrossRef] [Scilit]
- Astrup, A.; Geiker, N.R.W.; Magkos, F. Dairy and cardiovascular disease: A review of recent observational and randomized controlled trials. Am. J. Clin. Nutr. 2019, 110, 1453S–1463S. [Google Scholar]
- Cormick, G.; Belizán, J.M. Calcium Intake and Health. Nutrients 2019, 11, 1606. [Google Scholar] [CrossRef] [Scilit]
- Villa-Etchegoyen, C.; Lombarte, M.; Matamoros, N.; Belizán, J.M.; Cormick, G. Mechanisms Involved in the Relationship between Low Calcium Intake and High Blood Pressure. Nutrients 2019, 11, 1112. [Google Scholar] [CrossRef] [Scilit]
- Caffarelli, C.; Al Refaie, A.; Mondillo, C.; Cavati, G.; Lora, A.; Gennari, L.; Nuti, R.; Gonnelli, S. Influence of Dietary Calcium Intake on Skeletal Health and Body Composition in an Italian Elderly Population. Nutrients 2025, 17, 2073. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, J.K.; Tran, T.M.C.; Choi, E.; Baek, J.; Kim, H.R.; Kim, H.; Yun, B.H.; Seo, S.K. Association between Daily Dietary Calcium Intake and the Risk of Cardiovascular Disease (CVD) in Postmenopausal Korean Women. Nutrients 2024, 16, 1043. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Masenga, S.K.; Kabwe, L.S.; Chakulya, M.; Kirabo, A. Mechanisms of Oxidative Stress in Metabolic Syndrome. Int. J. Mol. Sci. 2023, 24, 7898. [Google Scholar] [CrossRef] [Scilit]
- Sun, X.; Zemel, M.B. Dietary calcium regulates ROS production in aP2-agouti transgenic mice on high-fat/high-sucrose diets. Int. J. Obes. 2006, 30, 1341–1346. [Google Scholar] [CrossRef] [Scilit]
- Roche, H.M.; Phillips, C.; Gibney, M.J. The metabolic syndrome: The crossroads of diet and genetics. Proc. Nutr. Soc. 2005, 64, 371–377. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.