Article

Food and Nutrition Security Status of Rural Female-Headed Households in Lesotho

1
Department of Consumer Sciences: Food and Nutrition, Faculty of Applied Science, Durban University of Technology, Durban 4000, South Africa
2
School of Mathematics, Statistics & Computer Science, College of Agriculture, Engineering and Science, University of KwaZulu-Natal, Durban 4041, South Africa
*
Authors to whom correspondence should be addressed.
Sustainability 2026, 18(5), 2189; https://doi.org/10.3390/su18052189
Submission received: 13 November 2025 / Revised: 21 December 2025 / Accepted: 30 December 2025 / Published: 25 February 2026

Abstract

This study quantifies household-level socioeconomic drivers of food and nutrition insecurity in two rural Lesotho villages and translates those findings into clear monitorable pathways for sustainable development. Lesotho has a population of just over 2 million, of which 580,000 people live below the poverty line, and 24% (about 139,200) in the subset are experiencing extreme poverty, particularly in rural areas. Food and nutrition insecurity affects 61% of the population in rural areas and 39% in urban areas. The study aimed to determine the socioeconomic conditions and food security status of 126 females residing in Mpharane and Maqoala villages in the district of Mohale’s Hoek in Lesotho. A cross-sectional quantitative design was employed, and the measurement instruments included a socio-demographic questionnaire, the Household Hunger Scale (HHS), the Household Food Insecurity Access Scale (HFIAS), and a food frequency questionnaire. Statistical analyses were conducted using descriptive statistics. The results indicated that all the participants were mothers and caregivers living in overcrowded households, with 61% residing in one-room homes. Unemployment was a universal experience among the participants, resulting in severe food insecurity as 100% of the participants reduced the food intake of their children, as well as other household members, due to limited financial resources. The participants’ diet was predominantly cereal-based, with a mean cereal group intake of 26.70 (±8.53), and wheat was the most frequently consumed cereal (59.5%). By linking food security metrics (HHS, HFIAS, and food frequency) to household structure, unemployment, housing density, and cash access, the research produces evidence that can be used to design, prioritize, and evaluate interventions across the social, economic, environmental, and governance dimensions of sustainability. In conclusion, by defining measurable household-level links between socioeconomic conditions and food insecurity, this study provides baseline indicators and practical intervention targets aimed at achieving sustainable food systems, social equity, and economic resilience in rural Lesotho.

1. Introduction

In the last four years, acute food insecurity has been on a constant rise, and this increase has created significant challenges in achieving zero hunger in 2030 globally [1]. In 2022, global food insecurity increased, causing 258 million people to face high levels of acute food insecurity [2], and, in 2025, more than 48 million people across nine countries of the Southern African Development Community (SADC) continued to experience persistent food insecurity. Lesotho is among the Southern African countries that were facing food crises or worse, acute food insecurity [3,4]. The increase was particularly in lower middle-income countries due to overlapping disasters, such as the COVID-19 pandemic, international conflicts, and war, especially the Russia–Ukraine war, and extreme climate changes [4]. More than half of the population in Lesotho lives below the poverty line, which is less than USD 1 per day, equivalent to LSL 16.63. Moreover, 75% of the population lives in poor rural areas, and the unemployment rate is high, resulting in people being exposed to food insecurity [5,6,7]. According to the Food and Nutrition Coordinating office, there was an estimate that 229,000 people around Lesotho in 2022 were categorized under IPC Phase 3 (Crisis), which stands for acute food security. Fifteen percent of the population living in rural areas were under IPC Phase 3 (Crisis). Out of the ten districts in Lesotho, six were categorized under IPC Phase 2 (Stressed) of acute food security, and four were categorized under IPC Phase 3 (Crisis). The general contributing factors are low agricultural productivity, developmental challenges, chronic poverty, and high rates of malnutrition and Human Immunodeficiency Virus (HIV) prevalence. The population infected with HIV was mostly females, 27.7%, and males, 17.8%, because of gender-based violence. About 80% of individuals infected with HIV also have tuberculosis (TB). The country is also facing a triple burden of malnutrition [4,8,9]. In September 2023, 245,000 (16%) of the population residing in rural areas experienced extreme levels of acute food insecurity [10] due to excessively high food prices in 2021 and 2022 and the EL Niño droughts between 2015, 2017, and 2019, which caused induced drought (irregular climate circumstances composed of unpredictable floods and persistent and frequent droughts). As a result, crop failure led to low income and high food prices, resulting in more than 30% of the populace throughout the ten regions facing excessively high levels of severe food insecurity and 41% of the rural Basotho population spending more than half of their wages on foodstuffs. Roughly 80% of the populace exists in rural regions, and more than 70% of the populace in rural areas is engaged in subsistence farming, which has not performed well for many years due to numerous factors in addition to climate change: rural families lack access to arable land, and, for those individuals who do possess arable land, a lack of resources to maximize production, such as fertilizers and high-yield seeds, is a problem [11].
A study conducted in Lesotho in 2023, between the districts of Mafeteng, Mohale’s Hoek, and Quthing, reported that, out of 300 participants, 95.3% were food insecure. The majority of the participants, 57.7%, were from male-headed households, and 42.3% were from female-headed households. The female-headed households, at 96.1%, were more food insecure than the male-headed households. Young age, low education, and unemployment were the contributing elements [12]. The influence of COVID-19, which reached the nation in May 2020, was projected to have a severe effect on monetary stability and food security [13].
The hypothesis gathered from the literature review above indicates that food insecurity is a global crisis that is progressively increasing because of multiple factors, and Lesotho is confronted with high levels of acute food insecurity. The study’s hypothesis was that rural female-headed households in Mpharane and Maqoala experience a high prevalence of food insecurity, driven in part by low agricultural productivity, the impacts of climate change, unemployment, and rising food prices. The research question for this study was as follows: what is the prevalence of food insecurity among rural female-headed households in Mpharane and Maqoala? Therefore, the purpose of this study was to determine the socioeconomic conditions and food security status of 126 rural female-headed households in Mpharane and Maqoala villages in Mohale’s Hoek District, Lesotho. This article reports on the findings of the food and nutrition insecurity status of rural female-headed households in Mpharane and Maqoala villages based on socioeconomic conditions and food security status. Food and nutrition insecurity remain a challenge in Lesotho. Despite some economic growth, Lesotho must still address rural poverty and promote inclusive social development. Over a quarter of the populace faces elevated rates of acute food insecurity and needs humanitarian intervention to decrease food gaps, safeguard, rebuild livelihoods, and inhibit severe undernourishment.

2. Materials and Methods

2.1. Description of the Study Area

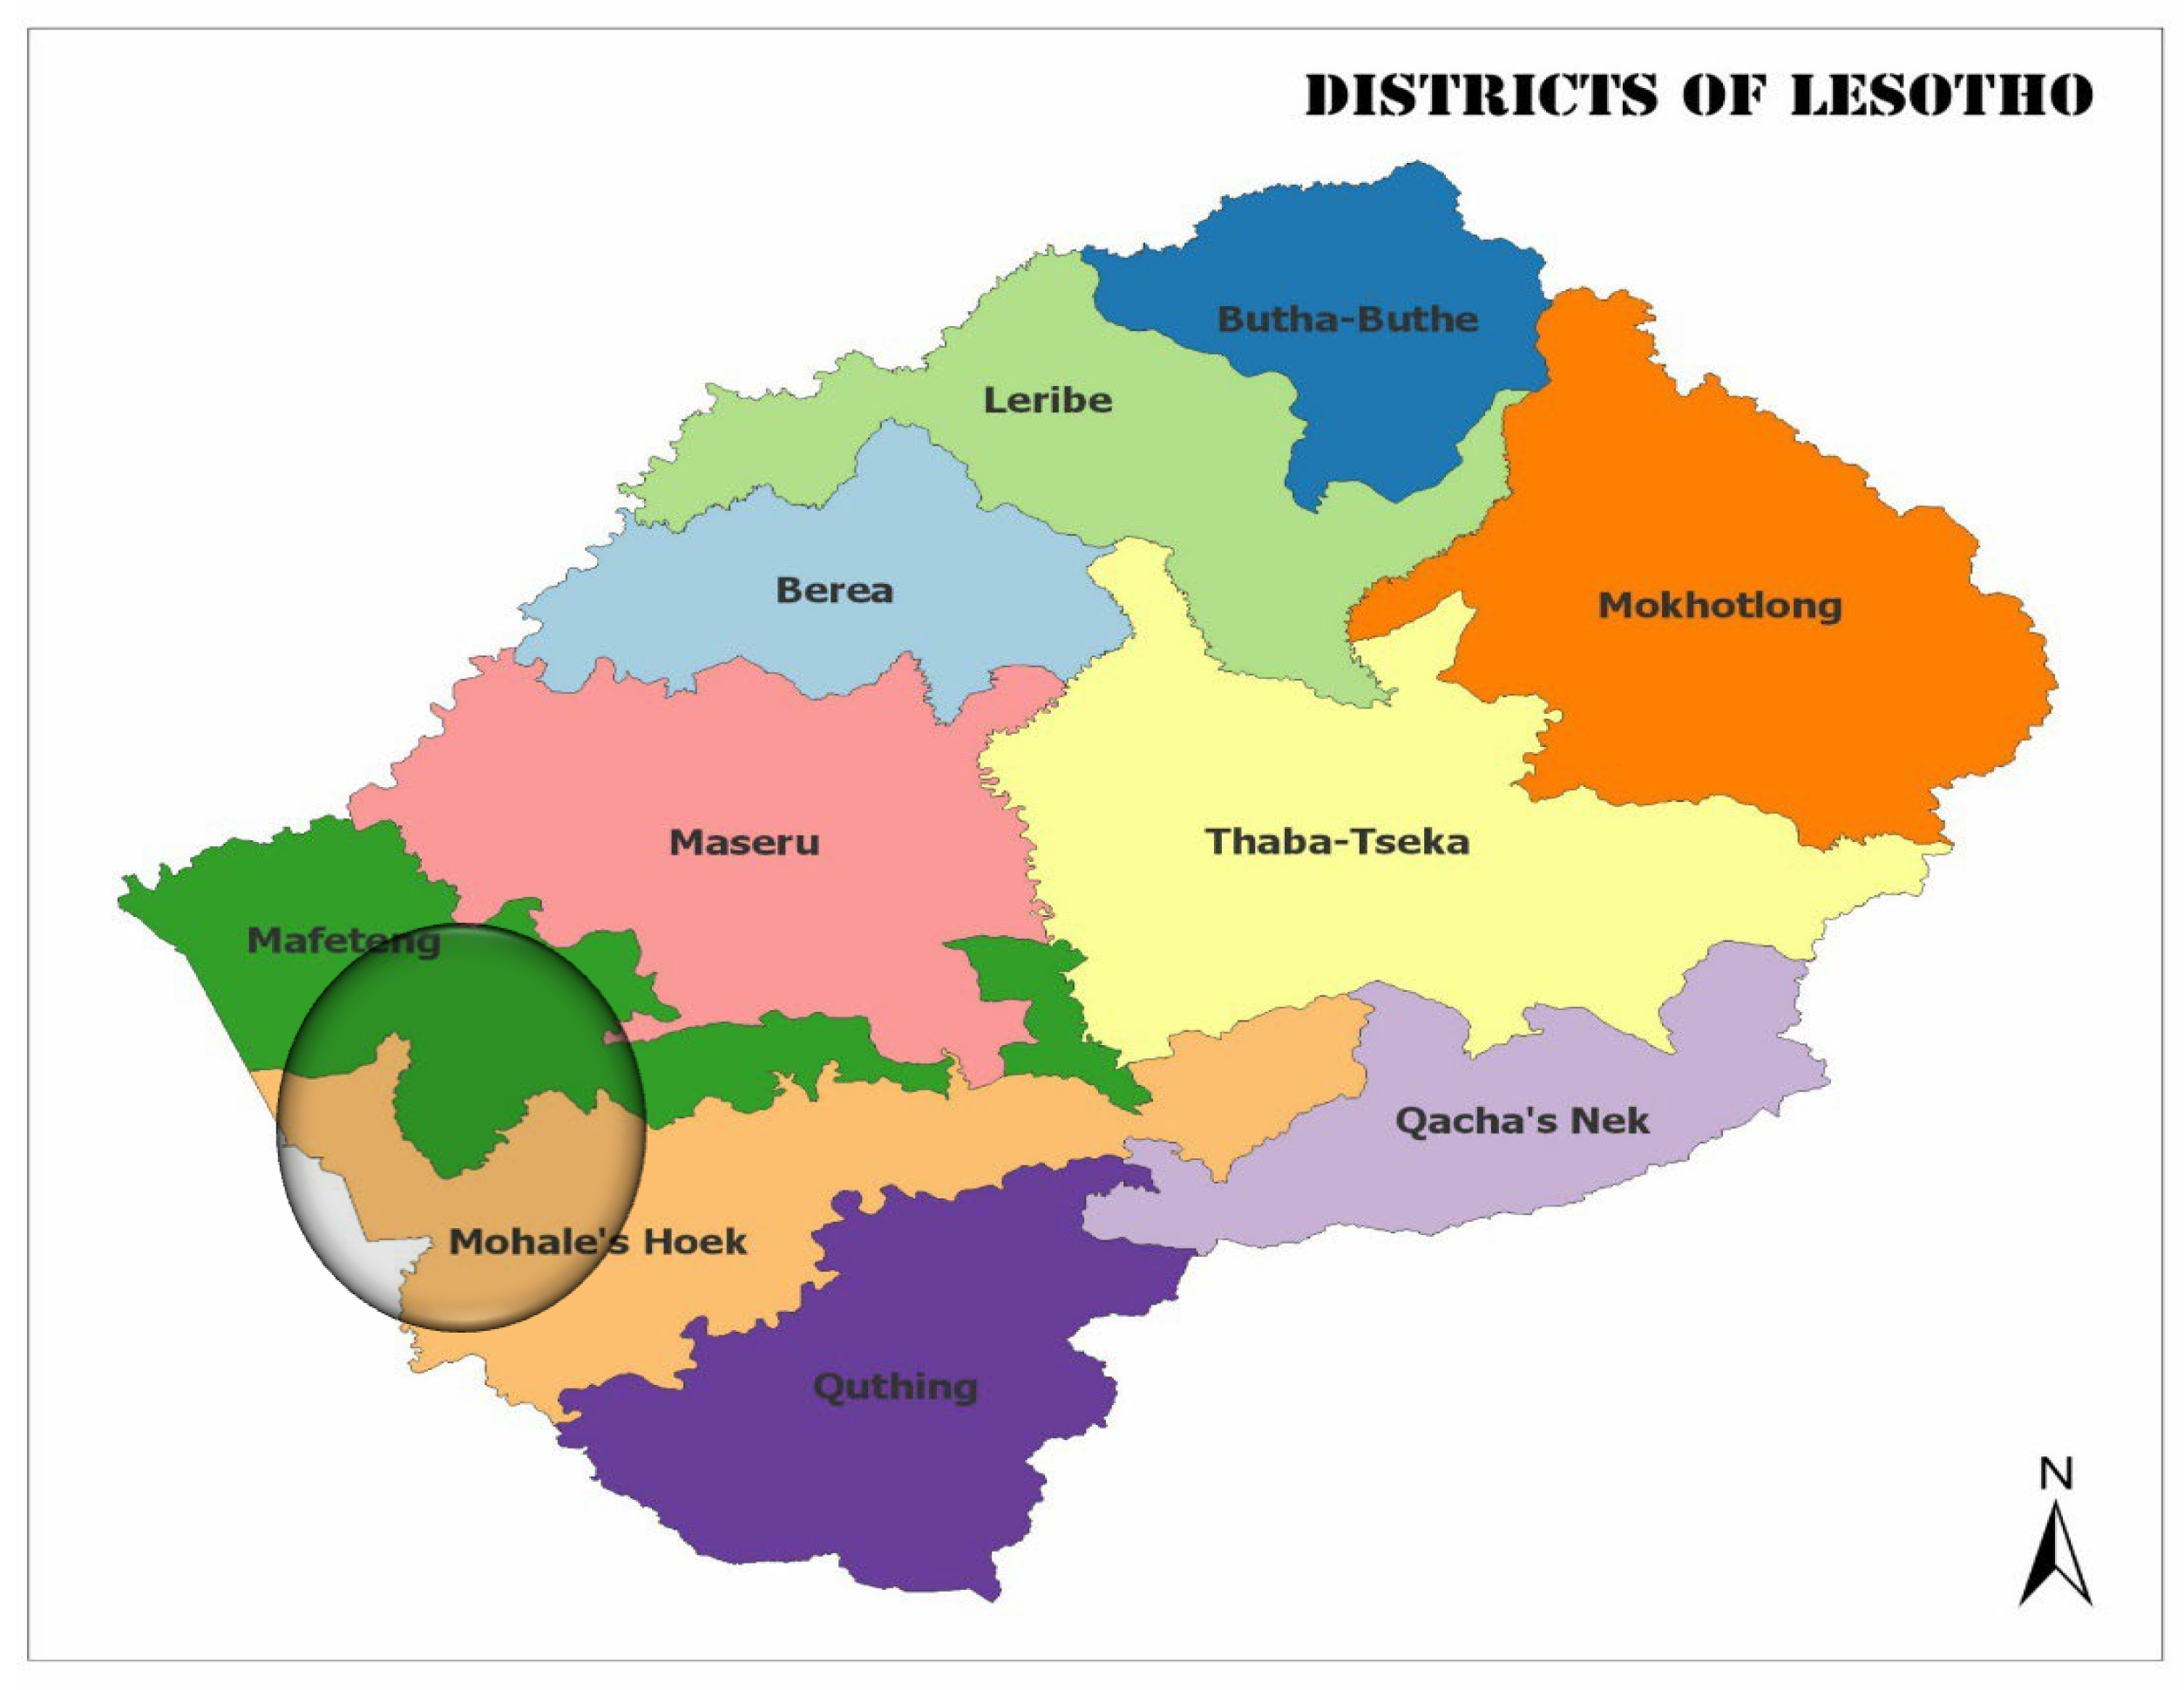
Lesotho has ten districts, and the capital and largest city is Maseru as depicted in Figure 1. Lesotho has a population density of 68 people per square kilometer (162/sq. mi) and is 138th worldwide for this statistic [14]. Population density is lowest in the highlands. This research was conducted in one of the ten districts of Lesotho, called Mohale’s Hoek. Mohale’s Hoek has a population of approximately 165,590, with 81,299 males and 84,291 females. Mohale’s Hoek has an area of 3530 square kilometers with 186 villages. Mpharane and Maqoala villages fall under the Council (cluster) of Thaba-Mokhele, which comprises 136 villages, 4526 households, 9210 males, 9176 females, and a total population of 18,386. In Mpharane village, there are 101 households with 131 males, 151 females, and a total population size of 282. In Maqoala, there are 50 households with 90 males, 91 females, and a total population size of 181 [15]. The two villages were selected based on their geographic location as they are rural communities with low-income households, and they share similar profiles [16]. The Maqoala village is situated approximately 37.6 km away, which is approximately 1 h and 6 min by car, from Mpharane. A fixed research design was employed as the subjects, timescale, and location were predetermined before data collection commenced [17].

2.2. Research Design

The research explored the well-defined problems of food and nutrition insecurity by explaining the causes and consequences in both Mpharane and Maqoala villages. The type of research data is primary data because the researcher collected data directly through interviews of adapted questionnaires [18]. A cross-sectional quantitative design was used [16,19]. A pilot study was conducted with ten female members from each village to assist in validating and assessing the reliability of the adapted questionnaires. All fieldworkers were trained using an adapted training manual from the Department of Consumer Science, Food and Nutrition, to assist participants in completing questionnaires during interviews. Fieldworkers were fluent in both Sesotho and English. The fieldworkers had to be trained in administering questionnaires to participants and assisting the researcher with data collection. The training session for the fieldworkers was conducted in both English and Sesotho. The study aimed to identify the food and nutrition security status of rural female-headed households. The research’s purpose was to develop techniques, products, and procedures by expanding scientific understanding and solving the practical problems of food and nutrition insecurity that rural female-headed households face.

2.3. Target Population and Sampling Procedures

Probability sampling, in the form of simple random sampling, ensures that every member of the population group has an equal chance of being selected for the sample. The total population size of females in Mohale’s Hoek was 84,291, and the total population size of females in Cluster Thaba-Mokhele was 9176. From that cluster, it was determined that there were 151 female-headed households in Mpharane and 91 households in Maqoala. The total number of eligible female participants from Mpharane and Maqoala was 242. The sample size was calculated using Qualtrics’ calculation with a 95% confidence level (Z Score = 1.645) and a 6% margin of error (MoE); the ideal sample size was determined to be 127 participants. For this study, 6% was chosen because it provided reasonable precision for prevalence estimates (e.g., food insecurity rates or dietary diversity scores) while keeping the required sample size within what is operationally achievable for surveying 126–127 households across two villages. The sample size of 126 was evenly divided between the two villages, with 63 participants from Mpharane and 63 from Maqoala village. The sample size included young female adults aged 20 years and older, as well as female adults aged up to 60 years. The adapted CONSORT flow diagram of a Randomized Controlled Trial (RCT) was used for participant enrollment, and all participants were screened for eligibility. All selected participants met the inclusion criteria.

2.4. Data Collection

Initially, prior to data collection, ethical approval was obtained from the Durban University of Technology (DUT) under the Faculty Research Committee (FRC) and ethical clearance from the Institutional Research Ethics Committee (IREC) (No. 029/19). The second ethical approval was obtained from Lesotho through the Lesotho Research Coordinating Unit (ethics committee), the Ministry of Agriculture and Food Security, and the Ministry of Health and Social Welfare. A meeting with the councillor of the district of Mohale’s Hoek was arranged to obtain written permission to conduct the research in the two villages of the district. Once consent was obtained from the district councillor, a meeting was arranged with the chiefs from the two villages. Information letters regarding the research were given to the chiefs from Mpharane village and Maqoala village. A meeting was held to discuss the research project and to obtain written permission to conduct the study in the villages. When permission was granted in a written form by the chiefs of the Mpharane and Maqoala villages, the chiefs assisted in creating a community forum composed of five local women from each village to explain and inform all parties about the study to be conducted in their villages. The ten women assisted the researcher in understanding the dynamics and interests of the women residing in the two villages. The community forums also helped to adapt the research questionnaires to the community’s needs.
Data was collected using valid and reliable questionnaires. The socio-demographic questionnaire developed by [20,21] was adapted for this specific community by the researcher and the focus group through a pilot study. A socio-demographics questionnaire assists the researcher to understand the target audience so as to create products and services that the participants need to solve their problem. The socio-demographic questionnaire was designed to determine the socio-demographic profile of households based on social and demographic data from population, housing censuses, and administrative records [22]. Moreover, the socio-demographics questionnaire was administered to understand the participants’ background, including their accommodation status, family composition, employment, and economic status. The Household Hunger Scale (HHS) and Household Food Insecurity Access Scale (HFIAS) were used to evaluate the food security status in each of the women farmers’ households [23,24]. For HFIAS and HHS, participants were asked to recall their day-to-day challenges related to food insecurity. Furthermore, the participants were required to report on their experiences with household food insecurity, food affordability, food adequacy, meal reduction, hunger among family members, and coping strategies over a 12-month period. Response options, scoring rules, and standard cut-offs were used. Moreover, nutritional assessments were conducted using a food frequency questionnaire (FFQ), which assessed nine different food groups. The FFQ list included cereal grains (maize, sorghum, and bread), roots and tubers (potato), legumes (beans and peas), vegetables (green leafy vegetables, e.g., spinach, tomatoes, and onions), fruits (bananas, oranges, and apples), dairy (fresh milk and maas), meat, poultry, fish (beef, chicken, and tinned fish), eggs (chicken egg (whole)) and fats, and oils and sugar (cooking oil and sugar). Household measurements were used to report on the portion control, and the number of times a food item was consumed was reported under frequency (%) to calculate the score [21,25]. The variables measured included gender, age, education level, levels of food and nutrition insecurity, and consumed food variety to meet the research objectives.

2.5. Data Analysis

The research study employed a quantitative method to collect data using questionnaires to assess the food and nutrition insecurity status of female-headed households. The data was sorted and checked for completeness and accuracy and captured on a Microsoft Excel® Spreadsheet by the researcher. Statistical Package for the Social Sciences (SPSS) version 29 was used to analyze the data. The statistical analysis, which included descriptive statistics, such as means and standard deviations (where applicable), as well as frequencies, was represented in tables or graphs. The paired sample t-test was used to compare the means between the two villages for the food frequency data.

3. Results

The quantitative data determined the interaction between the socioeconomic conditions, dietary diversity, food consumption patterns, and food security status in relation to food insecurity in rural female-headed households.

3.1. Socio-Demographic Characteristics

Table 1 presents a summary of the socio-demographic characteristics of the sampled population. All the participants (n = 126) were mothers from both villages who were unemployed, with a mean age of 40.4 years and a SD± of 12.6, with full ownership of the house unit and residing with other people. A large number (61.9%) of the houses had one room: the majority (32.6%) resided with five or more people, 21.4% resided with two people, and 49.2% did not have other houses or shacks within the yard. All the participants and their children consumed most of their meals at home; at times, children also consumed some of their meals at their friends’ homes, schools, and in other locations (relatives).

3.2. Household Hunger Scale (HHS) and Household Food Insecurity Access Scale (HFIAS)

HHS and HFIAS are indicators used to illustrate households experiencing food insecurity and hunger due to food affordability, adequacy, accessibility, and the participants’ coping strategies regarding food insecurity. The findings in Table 2 indicate that all the participants experienced anxiety about running out of food before having the money to buy more. Ninety-seven-point-seven percent reported that they bought food that did not last, and all the participants occasionally could not afford to eat balanced meals. Eleven-point-one percent of the participants spent between ZAR 0 and ZAR 200.00, 25.4% of the participants spent between ZAR 201.00 and ZAR 300.00, and 36.5% of the participants spent between ZAR 301.00 and ZAR 400.00 on food each month. Furthermore, not all the participants had enough money to buy food. All the participants indicated skipping meals and reducing the size of the meals before because of inadequate access to funds to buy food. Ninety-five percent of the participants reduced the size of their meals or skipped meals in some months, while 9.5% did this in one or two months. Additionally, all the participants reported that sometimes they were unable to provide a balanced meal for their children, and they reduced the size of their children’s meals because there was not enough money to buy food. Five-point-six percent of the participants reported that they had a situation where their children went an entire day without eating because they did not have money to buy food. All of the participants relied on low-cost food to feed their children because they ran out of money to buy food. All the participants indicated that they experienced hunger because they ate less food since they could not afford to buy food. More than half, 54.0%, reported that they were always hungry because of insufficient food, and 22.2% reported that they had gone without food for an entire day due to financial difficulties. In addition, the household coping strategies were 20.6% of the participants borrowed food from their friends, neighbors, relatives, and others. Among the participants, only 18.3% reported that they stuck to simple foods that were cost-effective. Fourteen-point-three percent reported selling assets they owned to have money to buy food for their households.

3.3. Dietary Results Based on Food Variety Score and Dietary Diversity Score

The dietary assessment was conducted using a food frequency questionnaire, indicating food variety, food group diversity over a seven-day period, and the top 20 foods consumed.
The results in Table 3 are the summary of the food group variety for Mpharane and Maqoala. Mean ± SD was observed for all the food consumed from all the food groups over a period of seven days for all the participants. The mean ± SD for group 1 was 11.20 (±7.09). Group 2 was 40.48 (±49.28). Group 3 was 10.58 (±16.68). Group 4 was 26.70 (±8.53). Group 5 was 20.00 (±12.13). Groups 5 and 6 were 19.18 (±8.62). Lastly, group 7 was 22.22 (±9.60).
The Mpharane and Maqoala participants consumed different food items under the seven food groups. The participants consumed chicken (38.9%), eggs (40.5%), milk (52.3%), wheat (59.5%), and dried peas (20.6%). Under group 6, the majority of the participants consumed wild leafy vegetables (84.9%) and sunflower oil (75.4%) in group 7. The participants indicated that, out of n = 126, n = 49 did not consume any meat group foods, participants n = 10 consumed one type of the meat group, and participants n = 25 consumed five different types of the meat group. In the egg group, participants n = 51 did not consume eggs. Participants n = 93 consumed one type of dairy. Out of five different types of cereal in the cereal group, participants n = 124 consumed one type of cereal, participants n = 119 consumed two types of cereal, and participants n = 55 consumed five different types of cereal. A large number of participants, n = 85, did not consume any of the three different legumes, while only 26 participants consumed one type of legume. The fruit group had three different types of fruits, and participants (n = 23) did not consume any fruits, participants (n = 28) consumed two types of fruits, and participants (n = 34) consumed three different types of fruits. Under the vegetable group with five different types, participants n = 14 did not consume any vegetables, participants n = 9 consumed one type of vegetable, n = 107 of the participants consumed two types of vegetables, and participants n = 82 consumed five different types of vegetables. The majority of the participants, n = 95, did not consume the two types of oils or fats.

4. Discussion

The results of the study clearly indicate that there were high levels of food and nutrition insecurity among rural female-headed households in Mpharane and Maqoala villages in Lesotho. Rural female-headed households in Lesotho face severe food and nutrition insecurity, shaped by a complex interplay of socioeconomic, environmental, and gendered factors. Lesotho faces a high prevalence of food insecurity, and over 95% of rural households in southern Lesotho experience food insecurity, with female-headed households disproportionately affected. A similar cross-sectional study conducted in 2023 by Sello and colleagues in Mafeteng, Mohale’s Hoek, and Quthing districts reported that 95.3% of the participants were food insecure and only 4.7% were food secure. Furthermore, 42.3% of the participants were households headed by females, and the analysis revealed that the number of children in a household had a significantly positive contribution to household food insecurity. Food insecurity affects both developed and developing countries, and Lesotho is no exception. In 2023, the degree of acute food insecurity globally continued to increase due to food emergencies and different challenges. In 48 nations, 238 million people were experiencing extreme rates of acute food insecurity, which was 10% higher than in 2022 [12,14,26]. The Food Security Information Network indicated that, in 2023, Lesotho was grappling with food insecurity, and, out of a population of over 2 million, 58,000 people were food insecure, and 24% lived in extreme poverty [1]. Lesotho’s rural female-headed households face a compound vulnerability: insecure land access, labor shortages from male outmigration, and acute climate shocks that reduce both food availability and dietary diversity; qualitative and quantitative Lesotho studies document these dynamics and link them to poorer household food and nutrition outcomes [27]. Policy gaps notably limit the reach of social protection, and weak enforcement of women’s land rights amplifies risk and constrains recovery after droughts [28]. From July to September 2022, 229,000 people (15%) of the population in Lesotho residing in rural areas fell under IPC Phase 3, indicating a food security crisis. The results of the study concurred with the above statement by indicating that the participants were facing high food insecurity since 54% of the participants reported that there were times when they would be hungry but could not eat, and, in extreme cases, 22.2% of the participants reported that other adults in the household would go the whole day without eating.
Furthermore, [29] highlighted that Basotho people in Lesotho experience food insecurity at different levels, and there was a steady increase in the frequency of moderate to severe food insecurity in Lesotho in the last four years of the total population (percent) of Lesotho over a 3-year average from 2020 to 2022. From 2017 to 2019, the prevalence was 49.7%; from 2018 to 2020, the prevalence increased to 52.0%; from 2019 to 2021, the prevalence increased to 54.4%; and, from 2020 to 2021, it increased to 56.7%. Furthermore, the FSIN supported the study’s reports regarding the increasing food insecurity in Mohale’s Hoek by indicating that, in Mohale’s Hoek, 80,065 (50%) of people were in Phase 1, falling under minimal food insecurity; 48,039 (30%) were in Phase 2, falling under stressed food insecurity; and 32,026 (20%) were in Phase 3, falling under crisis food insecurity [1]. None of the people experienced Phase 4, which was characterized by emergency food insecurity, or Phase 5, which was marked by famine food insecurity. However, Phase 3 or above meant people faced high food insecurity and needed urgent action. The food insecurity in the study is more alarming because the results indicated that the children in the participants’ households were experiencing food insecurity, with 89.7% of the children skipping meals. In the most extreme cases, 5.6% of the participants reported that children went a whole day without eating.
In agreement with the above results, six out of the ten districts in Lesotho were categorized as IPC Phase 2 (Stressed), and four districts were classified as IPC Phase 3 (Crisis). The population in Lesotho residing in rural areas under IPC Phase 3 (Crisis) increased to 320,000 (22%) from October 2022 to March 2023. This means eight out of ten districts were classified as IPC Phase 3 (Crisis). The first reason for the increase from 15% to 22% in IPC Phase 3 (Crisis) in Lesotho from 2022 to 2023 was attributed to climate change [1]. At the national level, seasonal rain occurred with no delay. Nonetheless, most of the regions experienced extreme volumes of rainfall, which damaged several producers and initiated waterlogging in some parts of the nation. As a result, Lesotho reported decreased crop productivity compared to the previous year, 2021, and the five-year average. The second reason was escalated prices; the prices stayed higher than the 5-year average and higher than the previous year. The third reason was economic decline, which resulted in increased inflation combined with decreased salary prospects from primary sources, and this has reduced purchasing power. The research study reflected the same sentiments that the high levels of food insecurity were caused by unemployment, affordability, and accessibility, which contributed to poverty and hunger. The participants reported that the decreased access to and availability of food in their households was due to a lack of money to buy food. The above financial constraint on acquiring food is highlighted in Table 2, which indicated that 36.5% of the participants spent under ZAR 500.00 on food each month. As a result, all the participants from both villages indicated that, in the last 12 months, there has been a change in their food intake because, sometimes in the household, some members would eat less food, cut the size of meals, or skip meals.
The FAO confirmed these findings, which stated that poverty remains relatively high in lower-middle-income countries such as Lesotho [4]. Thirty-three-point-nine percent of the people were projected to live below USD 2.15/day, the global poverty line in 2023, whilst 56.2% of the populace was under the lower-middle-income country poverty line of USD 3.65/day. The UN in 2023 explained that poverty was linked to inadequate national monetary performance, inadequate revenue delivery, and poor governmental structures that render poor individuals powerless in either a democratic system or dictatorship [25,26]. Restrictive economic systems increase food volatility and prices, making the cost of food a constant concern for poor people in developing nations because most people spend over 50% of their income on food. Furthermore, poverty is a global problem. In 2020, the global poverty rate was 9.2%, meaning 689 million individuals lived in poverty on USD 1.90 or less per day. In the United States, 11.8% of the populace, meaning 38.1 million people, lived in poverty, with a salary of USD 33.26 per day or less. In 2018, four out of five people globally lived below the poverty line in rural regions. Almost one-third of the population in emerging nations was poor, with 70% to 80% from Sub-Saharan Africa. Nearly half of the underprivileged individuals in Sub-Saharan Africa were found in the following five countries: the Democratic Republic of Congo, Madagascar, Tanzania, Ethiopia, and Nigeria.
Lesotho is landlocked and surrounded by South Africa. The two countries share similar food insecurity challenges and socio-demographic problems [30]. According to the global gender gap report of 2022 and [31], approximately 43% of South African homes were female-headed households. The reasons for this include decades of colonization and apartheid, which resulted in men working far from their households, and a higher proportion of female birth as compared to men. The Department of Statistics South Africa [22,32] revealed that many female-headed households in South Africa experienced inadequate access to food. As a result, 16.5% experienced moderately inadequate food access, and 7.7% experienced severely insufficient access to food, which was higher than the national average in both these categories of food access. The above findings were supported by the findings of [33], which estimated poverty at 62.6% in 2022 in South Africa based on the upper-middle-income country poverty line. South Africa does not have as high an occurrence of food insecurity as Lesotho. In South Africa, between 2017 and 2019, the prevalence was 17.4%; between 2018 and 2020, the prevalence was 18.2%; between 2019 and 2021, the prevalence was 19.0%; and, between 2020 and 2021, the prevalence was 20% [4].
Evidence from the current study has highlighted that female-headed households in Lesotho, like in South Africa, have trouble accessing food. The participants expressed anxiety over running out of food, with 50.8% of the participants running out of food and not having money to buy more food. This contributed to 63.5% of the participants being unable to eat a balanced meal in the past 12 months. Because money has been the primary reason for inadequate access to food, some coping strategies have been employed. The results indicated that 20.6% of the participants borrowed food from their friends, neighbors, relatives, and others. Among the participants, only 18.3% reported that they were stuck to cost-effective simple foods. Fourteen-point-three percent reported selling assets they owned to have money to buy food for their households.
The current study showed that, in terms of the frequency of experiencing hunger, all the participants had previously eaten less than they thought they should have because they could not afford to buy food. Among the participants, 22.2% reported having gone without food for an entire day due to financial difficulties. Kent, 2019 specifically indicated that Lesotho has a hunger score of 34.5, which falls under the category of alarming (the scoring ranges between ≤9.9 low, 10.0 to 19.9 moderate, 20.0 to 34.9 serious, 35.0 to 49.9 alarming, and ≥50.0 extremely alarming) [30]. Lesotho ranks 121 out of 125 countries evaluated, experiencing hunger under the Global Hunger Index. The disparity in income levels is one of the causes of the accumulating high levels of starvation globally, particularly in Africa [26,31].
The FAO reported that, from 2019 to 2022, millions of people experienced hunger. Some contributing factors are the COVID-19 pandemic, climate change, global conflict, and political instability [4]. Oyekanmi explained that, in 2022, 2.4 billion individuals, primarily women residing in rural areas, experienced hunger and did not have consistent access to nutritious, safe, and sufficient food. In 2021, 22.3% (148.1 million) of children were stunted, 6.8% (45 million) were wasted, and 5.6% (37 million) were overweight [13]. These figures indicate that child malnutrition is still high in the world. The study’s results highlight several reasons for the increased malnutrition in children. All the participants explained that children were sometimes not eating enough because the participants could not afford to buy enough food. Also, the participants could not provide a balanced meal for their children due to financial constraints. More than half, 63.5% of the participants, outlined that they frequently relied on a few kinds of low-cost food to feed their children because they were running out of money to buy food. The participants also experienced situations where their children were hungry and could not afford more food, and 5.6% of the participants reported that their children ran out of food the entire day because of insufficient money. The FAO indicated that Lesotho struggles with malnutrition in children, which contributes to child mortality [29]. Thirty-six percent of the children were reported to suffer from stunting, and only 15% of the children received a minimum acceptable diet. The prevalence of micronutrient deficiencies is promoted by inadequate infant and children’s feeding practices, especially in rural communities. There were similarities between the research study and the UNICEF report regarding contributing factors, such as decreased accessibility to nutritious food and inadequate feeding practices.
Since the participants have reported experiencing inadequate access to food over a period, this experience could have negatively affected their food variety and dietary diversity intake. Erenstein and colleagues agree with the above research statement by indicating that inadequate access to food constrains the number of foods households can procure and consume; it has been consistently linked with reduced dietary diversity and lower food variety scores [34]. In Sub-Saharan Africa, studies have found that food insecurity correlates with a diminished intake of various food groups and an increased risk of micronutrient deficiencies, underscoring how limited access narrows the range of foods people can eat. Empirical analyses further demonstrate that both the quantity and variety of foods consumed complement each other in reducing hunger and improving nutrition outcomes [35]. The study’s mean intake values paired with their standard deviations reveal not only how much was eaten on average but also how wildly consumption fluctuated across individuals. The large SDs indicate uneven access to food, with some participants eating liberally from certain groups, while others had minimal intake, highlighting the impact of erratic food availability on diet patterns. The results highlight not only how much participants ate in each broad category but also the variety of their diets within those categories. For instance, most people relied heavily on staple cereals. Some Mpharane participants consumed sorghum 100.0% and maize 98.4%. Some Maqoala participants consumed maize 98.4% and sorghum 88.9%. According to [36], heavy reliance on staple cereals such as maize and sorghum reflects a common coping strategy among food-insecure populations, where energy needs are met by cheap kilojoule-dense grains. In many African contexts, cereals like maize and sorghum contribute a majority share of daily kilojoules, and the near universal consumption rates (98 to 100%) attest to their role as dietary backbones. Wild leafy vegetables dominate both communities’ diets. In Mpharane, wild leafy vegetables accounted for 85.7%, and, in Maqoala, they accounted for 84.1%. According to [37,38], wild leafy vegetables serve as vital sources of micronutrients and health-promoting phytochemicals. Their resilience to local growing conditions and strong integration in traditional diets make them key components in supporting food security and reducing hidden hunger in rural populations. According to [37], conversely, low uptake of processed meats, certain fruits, fats, legumes, and eggs often stems from higher cost, limited market presence, and shifting cultural preferences under resource constraints. Ultra-processed foods tend to dominate urbanizing food environments, but their prevalence does not translate into improved dietary quality for poorer households, which remain unable to diversify beyond staples and foraged greens. The results clearly agree with the above statement by indicating that processed meats, certain fruits, fats, legumes, and eggs showed low uptake in the study. The pronounced variability in group 2 consumption, in contrast to the tight consistency in groups 1 and 3, reflects heterogeneous access and purchasing power within the study populations. Some households sporadically access a broader array of foods, thereby increasing variability, while others maintain a narrow subsistence-level diet with little day-to-day variation. In addition to money being one of the main factors in accessing food, seasonal availability, nutrition knowledge, and dietary preference play major roles in food consumption.
In East Africa, empirical work finds that resilience often hinges on livelihood diversification, social networks, and targeted cash support; food-secure households combine diversified cropping, off-farm income, and community risk-sharing, strategies that can partially offset the labor and asset deficits female heads face [39]. This suggests actionable transfers for Lesotho: scale cash-plus programs that pair transfers with inputs and labor-saving technologies to compensate for reduced household labor. Similar research from the South Asian literature highlights the gendered care burdens and institutional barriers, women’s time poverty, and weaker legal claims to land and entitlements, which undermine both production and intra-household nutrition, even when aggregate food supplies are adequate [40]. For Lesotho, this implies that nutrition outcomes will not improve solely through food availability; interventions must address women’s time, caregiving load, and legal access to assets.
Strengths of the study
The study targeted rural female-headed households, a group with distinct vulnerability pathways, which strengthens the relevance of the findings for gender-sensitive policy and programming. The study employed household food security indicators, including dietary diversity, food consumption scores, coping strategies, and dietary proxies, to enhance the study’s ability to capture both access and utilization dimensions.
Limitations of the study
The cross-sectional design limits causal inference: the sample was limited to two villages, which reduces generalizability. Self-reported dietary data and coping data may be biased due to social desirability; in that case, it does not capture chronic trends. Food security fluctuates with the season; the study may overestimate or underestimate the prevalence and miss coping dynamics. Standard household-level indicators can obscure intra-household differences in access to food and care that particularly affect women and children. The pilot was used for feasibility and comprehension testing. The research study lacks psychometric results. To better inform practice and policy, future research should adopt longitudinal and mixed-methods approaches, recruit larger and more diverse samples, and incorporate objective measures and experimental designs to test causal pathways and intervention effects.

5. Conclusions

The results indicated that Mpharane and Maqoala villages, which are characterized by female-headed households in Lesotho, endure markedly higher levels of food and nutrition insecurity due to poverty, hunger, and poor socioeconomic conditions, and this resulted in many households relying on negative coping mechanisms, such as meal skipping, asset sales, and informal borrowing, which further entrench food insecurity. This statement was supported by the results, which indicated that all the participants were concerned that the food they bought would run out before they had enough money to buy more, and the majority of the participants thought the food would not last a month. Chronic poverty, limited access to productive resources, and entrenched gender norms curtail women’s control over land, inputs, and income, trapping many households in cycles of insufficient food intake and poor dietary diversity. Seasonal hunger peaks exacerbated by recurrent droughts and climate variability compound these vulnerabilities, often forcing women to adopt coping strategies that undermine their long-term well-being and nutritional status. Gendered constraints intersect with environmental stressors and socioeconomic deprivation to produce a landscape of persistent food deficits and micronutrient shortfalls. The recommendations based on the above findings are to provide skills training, microfinance, and market linkages tailored to women, thereby increasing income-generating opportunities.
In addition, local safety nets and community coping mechanisms should be strengthened through the formalization of community food banks, savings groups, and asset-protection schemes, thereby reducing reliance on harmful coping strategies, such as asset sales and the postponement of healthcare and education.

Author Contributions

Conceptualization, L.M. and A.N.; Methodology, K.D.; Resources, A.N. and K.D.; Writing—original draft, L.M. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

Not applicable.

Informed Consent Statement

Not applicable.

Data Availability Statement

The research data can be obtained from DUT Open Scholar: https://openscholar.dut.ac.za/items/3127a2b2-0fe7-456e-b550-1e0759d12e86/full (accessed on 12 November 2025).

Conflicts of Interest

The authors declare no conflict of interest.

References

  1. FSIN and Global Network Against Food Crises. Global Report on Food Crises; Food Security Information Network: Rome, Italy, 2023; Available online: https://www.fsinplatform.org/global-report-food-crises-2023 (accessed on 12 November 2025).
  2. IPC. Analysis Portal—Lesotho Cute Food Insecurity Projection Update January–March 2025. Integrated Food Security Phase Classification. 2024. Available online: https://www.ipcinfo.org/ipc-country-analysis/ (accessed on 12 November 2025).
  3. FSIN and Global Network Against Food Crises. Global Report on Food Crises; Food Security Information Network: Rome, Italy, 2024; Available online: https://www.fsinplatform.org/report/global-report-food-crises-2024/ (accessed on 12 November 2025).
  4. FAO; IFAD; UNICEF; WFP; WHO. The State of Food Security and Nutrition in the World 2023. Urbanization, Agrifood Systems Transformation and Healthy Diets Across the Rural–Urban Continuum; Food and Agriculture Organisation of the United Nations: Rome, Italy, 2023; Available online: https://openknowledge.fao.org/items/445c9d27-b396-4126-96c9-50b335364d01 (accessed on 12 November 2025).
  5. WFP. Country Brief August; World Food Program: Maseru, Lesotho, 2023; Available online: https://www.wfp.org/publications/annual-country-reports-lesotho (accessed on 12 November 2025).
  6. The World Bank Group. Poverty and Inequity Update. 2025. Available online: https://www.worldbank.org/en/topic/poverty (accessed on 12 November 2025).
  7. The World Bank Group. Poverty and Equity Brief: Lesotho. 2025. Available online: https://pip.worldbank.org/country-profiles/LSO (accessed on 12 November 2025).
  8. Food and Nutrition Coordinating Office. Lesotho Food and Nutrition Policy (LFNP) 2016–2025; Food and Nutrition Coordinating Office: Maseru, Lesotho, 2016; Available online: https://faolex.fao.org/docs/pdf/les209966.pdf (accessed on 12 November 2025).
  9. FAO; IFAD; UNICEF; WFP; WHO. The State of Food Security and Nutrition in the World 2020. Transforming Food Systems for Affordable Healthy Diets; FAO: Rome, Italy, 2020; Available online: https://openknowledge.fao.org/handle/20.500.14283/ca9692en (accessed on 12 November 2025).
  10. IPC. Excessive Rains Received from October 2021 to March 2022 Resulted in Low Crop Production Compared to 2021 and Reference Year. Lesotho IPC Acute Food Insecurity Analysis July 2022–March 2023: Lesotho. 2022. Available online: https://www.fsinplatform.org/sites/default/files/resources/files/IPC_Lesotho_Acute_Food_Insecurity_2022July2023Mar_Report.pdf (accessed on 12 November 2025).
  11. FAO; IFAD; UNICEF; WFP; WHO. The State of food Security and Nutrition in the World: Safeguarding against Economic Slowdowns and Downturns; FAO: Rome, Italy, 2019; Available online: https://openknowledge.fao.org/items/f73edb75-4017-497b-8ca3-e66ea2109560 (accessed on 12 November 2025).
  12. Sello, G.; Motanyane, M.F.; Mokhesi, N.A.; Ntsieane, R. Food Insecurity and Its Determinants among Rural Households in the Southern Region of Lesotho. J. Food Secur. 2023, 11, 56–63. [Google Scholar] [CrossRef] [Scilit]
  13. Oyekanmi, A.Q. Hunger: Facts, the Global Hunger Index 2020, and Ways to Solve World Hunger. 2023. Iyops (Blog). Available online: https://www.iyops.org/post/ways-to-solve-world-hunger (accessed on 12 November 2025).
  14. Department of Economic and Social Affairs. World Population Prospects 2024 Summary of Results; United Nations: New York, NY, USA, 2024; Available online: https://population.un.org/wpp/assets/Files/WPP2024_Summary-of-Results.pdf#:~:text=The%20world’s%20population%20is%20expected%20to%20continue,people%20by%20the%20end%20of%20the%20century (accessed on 12 November 2025).
  15. Lesotho National Development Corporation (LNDC). Annual Report. Lesotho. 2022. Available online: https://staging2.digitalterrace.co.za/document/annual-report-2022-23/ (accessed on 12 November 2025).
  16. McCombes, S. Sampling Methods|Types, Techniques and Examples. 2023. Available online: https://www.scribbr.com/methodology/sampling-methods/ (accessed on 9 November 2025).
  17. Bhide, A.; Shah, P.S.; Acharya, G. A Simplified guide to randomized controlled trials. Acta Obstet. Gynecol. Scand. 2018, 97, 380–387. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  18. Gravetter, F.J.; Forzano, L.B. Research Methods for the Behavioural Sciences, 5th ed.; Cengage Learning: Boston, MA, USA, 2015; 658p. [Google Scholar]
  19. Streefkerk, R. Qualitative vs. Quantitative Research|Differences, Examples and Methods. 2023. Available online: https://www.scribbr.com/methodology/qualitative-quantitative-research/ (accessed on 11 November 2025).
  20. Saunders, M.N.K.; Lewis, P.; Thornhill, A. Research Methods for Business Students, 8th ed.; Pearson Education Limited: London, UK, 2019; Available online: https://www.researchgate.net/profile/Mark-Saunders-10/publication/330760964_Research_Methods_for_Business_Students_Chapter_4_Understanding_research_philosophy_and_approaches_to_theory_development/links/5c53056f299bf12be3f0e2cf/Research-Methods-for-Business-Students-Chapter-4-Understanding-research-philosophy-and-approaches-to-theory-development.pdf (accessed on 18 March 2025).
  21. Oldewage-Theron, W.; Salami, L.; Zotor, F.B.; Venter, C. Health status of an elderly population in Sharpeville, South Africa. Health SA Gesondheid 2008, 13, a282. [Google Scholar] [CrossRef] [Scilit]
  22. Banda, J.P. Main Sources of Socio-Demographic Statistics; United Nations Secretariat Statistics Division: New York, NY, USA, 2003; Available online: https://unstats.un.org/unsd/demographic/meetings/egm/sampling_1203/docs/no_1.pdf (accessed on 12 November 2025).
  23. FAO. World Summit on Food Security; Food and Agricultural Organisation: Rome, Italy, 2009; Available online: http://www.fao.org/tempref/docrep/fao/meeting/018/k6628e.pdf (accessed on 23 November 2025).
  24. International Monetary Fund. Making the Global Economy Work for All. Annual Report. 2008. Available online: https://www.imf.org/en/Publications/AREB/Issues/2016/12/31/International-Monetary-Fund-Annual-Report-2008-Making-the-Global-Economy-Work-for-All-22083 (accessed on 12 November 2025).
  25. United Nations. Meeting Coverage and Press Releases. Extreme Poverty in Developing Countries Inextricably Linked to Global Food Insecurity Crisis, Senior Officials Tell Second Committee; United Nations: New York, NY, USA, 2023; Available online: https://press.un.org/en/2023/gaef3590.doc.htm (accessed on 12 November 2025).
  26. IFAD. Wool and Mohair Value Chain Competitiveness Project. Project Design Report: Lesotho. 2022. Available online: https://www.ifad.org/en/w/projects/2000003942 (accessed on 12 November 2025).
  27. Mokati, J.T.W. Assessing the Impact of Gender Roles on Food Insecure Households in Lesotho: A Case Study of ‘Maneo Village in Southern Lowland District. Master of Disaster Management. 2019. Available online: https://ufscms.ufs.ac.za/docs/librariesprovider22/disaster-management-training-and-education-centre-for-africa-%28dimtec%29-documents/thesis/mokati-thesis.pdf?sfvrsn=c46d6220_2 (accessed on 19 December 2025).
  28. Mokati, J.T.W.; Ncube, A.; Bahta, T.Y. Is It Really Feminization of Agriculture? The Issue of Household Food Security in Lesotho’s Southern Lowland District. J. Asian Afr. Stud. 2024, 59, 411–424. [Google Scholar] [CrossRef] [Scilit]
  29. World Bank Group. The World Bank’s Strategy in South Africa Reflects the Country’s Development Priorities and Its Unique Leadership and Anchor Position, at the Sub-Regional Level Through the Southern African Development Community and Southern Africa Customs Union, and at the Continental Level Through the African Union: South Africa. 2025. Available online: https://www.worldbank.org/en/country/southafrica/overview (accessed on 12 November 2025).
  30. Kent, G. GQ8 are we serious about ending hunger? World Nutr. 2019, 10, 3–22. [Google Scholar] [CrossRef] [Scilit]
  31. Gassara, G.; Chen, J. Household Food Insecurity, Dietary Diversity, and Stunting in Sub-Saharan Africa: A Systematic Review. Nutrients 2021, 13, 4401. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  32. UNICEF. Nutrition Recommended Resources. Working to Support Healthier Communities: Lesotho. 2025. Available online: https://www.unicef.org/lesotho/topics/nutrition (accessed on 12 November 2025).
  33. Thornton, A.J.; Leibbrandt, M.; Ardington. Pathways to Food Security in South Africa: Food Quality and Quantity in NIDS Wave 1; SALDRU Working Papers 190; Southern Africa Labour and Development Research Unit, University of Cape Town: Cape Town, South Africa, 2016. [Google Scholar]
  34. Erenstein, O.; Jaleta, M.; Sonder, K.; Mottaleb, K.; Prasanna, B.M. Global maize production, consumption and trade: Trends and R&D implications. Food Secur. 2022, 14, 1295–1319. [Google Scholar] [CrossRef] [Scilit]
  35. Malebo, N.J. Nutritional and Functional Value of African Leafy Vegetables: Advantages and Limitations. In Plant-Based Diet; Hernández-Ledesma, B., Ed.; IntechOpen: London, UK, 2023. [Google Scholar] [CrossRef] [Scilit]
  36. Patra, S.; Shand, H.; Manna, A.; Bose, D.; Some, S.; Mondal, R. Ethnopharmacological and nutritional insights into wild leafy vegetables: Implications for food security, nutraceutical potential, and environmental remediation. Discov. Plants 2024, 1, 56. [Google Scholar] [CrossRef] [Scilit]
  37. Frank, T.; Ng, S.W.; Lowery, C.M.; Thow, A.M.; Swart, E.C. Dietary intake of low-income adults in South Africa: Ultra-processed food consumption a cause for concern. Public Health Nutr. 2024, 27, e41. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  38. Deitchler, M.; Ballard, T.; Swindale, A.; Coates, J. Introducing a Simple Measure of Household Hunger for Cross-Cultural Use; FANTA: Washington, DC, USA, 2011; Available online: https://www.researchgate.net/publication/275650680_Introducing_a_Simple_Measure_of_Household_Hunger_for_Cross-Cultural_Use?enrichId=rgreq-ee57e0f8414ad0b6485bce07708a5199-XXX&enrichSource=Y292ZXJQYWdlOzI3NTY1MDY4MDtBUzoyMjQwMTEwOTYyMDMyNjZAMTQzMDQxOTgxNTE2NQ%3D%3D&el=1_x_2&_esc=publicationCoverPdf (accessed on 12 November 2025).
  39. Silvestri, S.; Douxchamps, S.; Kristjanson, P.; Förch, W.; Radeny, M.; Mutie, L.; Quiros, F.C.; Herrero, M.; Ndungu, A.; Claessens, L.F.G. Households and food security: Lessons from food secure households in East Africa. Agric. Food Secur. 2015, 4, 23. [Google Scholar] [CrossRef] [Scilit]
  40. Adeel, Z.; Böer, B. The Water, Energy, and Food Security Nexus in Asia and the Pacific Central and South Asia; eBook; Springer: Cham, Switzerland, 2024; ISBN 978-3-031-29035-0. [Google Scholar] [CrossRef] [Scilit]
Figure 1. Map of Lesotho, showing its ten districts. Available online: https://www.mappr.co/counties/lesotho/ (accessed on 11 November 2025).
Sustainability 18 02189 g001
Table 1. Socio-demographic characteristics of the participants.
Variable Number (%) (n = 126)
The language spoken in the house
Sesotho 100
The role in the family
Mother 100
Mean age years (SD)
The whole group 40.40 ± 12.6 (126)
Mpharane 41.00 ± 13.1 (63)
Maqoala40.67 ± 12.1 (63)
The living situation at the moment
Own house/flat100 (126)
Do other people live in the house with you
Yes100 (126)
How many people are permanent residents living in the house?
19.5 (12)
221.4 (27)
316.5 (21)
418.3 (23)
5–10+34.2 (43)
The number of rooms per household
1 room 61.9 (78)
2 rooms 16.7 (21)
3 rooms 11.9 (15)
4 rooms 9.5 (12)
Other houses/shacks within the yard
Yes 50.8 (64)
No 49.2 (62)
Where do you eat most of your meals?
Home 100
Friends0
Work 0
Other 0
Where do your children eat most of their meals?
Home 37.4
Friends7.9
school19.8
Other (neighbors, family members)34.9
Table 2. Household food insecurity and coping strategies experienced in 12 months.
Variable Number (%)
In the past 12 months, have you been worried that the food you bought would finish before having money to buy more100
In the past 12 months, the food that you bought did it last for a month
Yes 89.7
No10.3
In the past 12 months, could not afford to eat balanced meals?
Yes 63.5
No 36.5
How much money do you spend on food each month?
ZAR 0–200.0011.1
ZAR 201.00–30025.4
ZAR 301.00–400.0036.5
ZAR 401.00–500.0019.8
ZAR 501.00–700.007.1
How often you do not have enough money to buy food
Yes 100
In the last 12 months, did you or other adults in the household ever cut the size of your meals or skipped meals because there wasn’t enough money for?
Yes 100
How often in the last 12 months did you or other adults in the household ever cut the size of your meals or skipped meals because there wasn’t enough money for?
1 or 2 months 9.1
Yes 90.5
In the last 12 months, the children did not have a balanced meal and was the did the size of the meals get reduced because they just couldn’t afford enough food.
Yes 100
Did any of the children ever not eat for a
whole day because of lack of money to buy food?
Yes 5.6
No 94.4
In the last 12 months, did you ever rely on only a few kinds of low-cost food to feed our children because of money
Yes 100
In the last 12 months, did you ever eat less than you felt you should because there wasn’t enough money for food?
Yes 100
In the last 12 months, were you ever hungry,
but didn’t eat, because there wasn’t enough money for food?
Yes 54.0
No 46.0
In the last 12 months did you or other adults in your household ever not eat for a whole day because there wasn’t enough money for food?
Yes 22.2
No 77.8
Household coping strategies because of food insecurity
Borrowing food from friends, neighbors, relatives, etc.19.0
Stick to simple food 18.3
Reduce expenditure on health19.0
Reducing expenditure on education 14.3
Adults skipping meals once a day 15.9
Selling assets, e.g., motorcycle 13.3
Table 3. A summary of the food variety within the food groups for Mpharane and Maqoala.
Variable Consumed Food Variety Groups n = 126 Mean
(SD)
Food Item
(Frequency (%))
Group 1: Flesh Foods (meat, poultry, and fish) 0 = 49
1 = 10
2 = 3
3 = 7
4 = 5
5 = 25
11.20
(7.09)
Chicken meat
(38.9)
Group 2: Eggs 0 = 51
1 = 75
40.48
(49.28)
Eggs
(40.5)
Group 3: Dairy Products0 = 33
1 = 93
10.58
(16.68)
Milk
(52.3)
Group 4: Cereal0 = 7
1 = 124
2 = 119
3 = 75
4 = 4
5 = 55
26.70
(8.53)
Wheat
(59.5)
Group 4: Legumes0 = 85
1 = 26
2 = 4
3 = 3
20.00
(12.13)
Dried peas
(20.6)
Group 5: Fruits0 = 23
1 = 30
2 = 28
3 = 34
19.18
(8.62)
Apples
(18.2)
Group 6: Vegetables 0 = 14
1 = 9
2 = 107
3 = 20
4 = 42
5 = 82
Wild leafy vegetables
(84.9)
Group 7: Oils and Fats 0 = 95
1 = 21
22.22
(9.60)
Sunflower oil
(75.4)
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.