


Abstract
Blue spaces, like canals, are central to health policies promoting physical activity (PA), enhancing wellbeing, and addressing inequalities. Alongside the health benefits, they can offer an array of societal, environmental, cultural, and other welfare-enhancing benefits, which shape the overall value of blue spaces for population wellbeing. This study investigated the multifaceted value of canals for promoting physical activity and wider community wellbeing from the perspective of local community members in Birmingham (UK). Two consensus workshops were conducted to identify enablers and barriers to engaging in PA alongside canals. Data were generated using the nominal group technique and analysed quantitatively and qualitatively. The community members shared that connecting with nature, enhancing mental health, and socialising were all key facilitators for using canals for PA. Prominent barriers identified were safety concerns, including anti-social behaviour, inadequate lighting, and fear of visiting alone, as well as a lack of accessibility. Overall, the findings highlight the importance of understanding the community perspective when considering the value of blue spaces, and subsequent investment opportunities. By incorporating the community perspective and embedding a notion of ‘ownership’ over these local assets, this will further enhance the sustainability of investment.
1. Introduction
There has been considerable work undertaken in recent years operationalising the value of natural environments, such as green and blue spaces, for health and wellbeing [1]. Several studies have identified the potential health benefits of green and blue spaces ranging from their provision for physical activity (PA) and psychological restoration to opportunities for social interactions, community cohesion, environmental benefits, and alleviation of health inequalities in local populations [2,3,4].
In valuing the contribution of green and blue spaces to population health and wellbeing, researchers and policymakers aim to disentangle the mechanisms by which these benefits accrue. Economic frameworks distinguish between direct use, indirect use, and option values [5]. Direct-use value refers to the direct benefits from participating in recreation or formal activities, whereas indirect-use value involves wider societal benefits such as improved health or absence of illness in the population, psychological effects including restoration and stress relief, social cohesion, and community attachment [5]. Option value reflects the values of non-users. From a policy perspective, conceptualising and measuring the social value of green and blue spaces are becoming increasingly important for evaluating the sustainability, effectiveness, and efficiency of interventions related to these environments. Specifically, exploring the value of green/blue spaces from the local community perspective will inform investment towards sustainable interventions that promote the continuation of health benefits after initial funding ends, as well as capacity building-practices across organisations and communities [6].
Most of the research to date has focused on the physical and mental health benefits of green areas, such as urban parks and woodlands, and inland blue spaces (e.g., rivers, canals) are often classified as a form of green space [7,8]. Green and blue spaces share common characteristics and offer similar qualities in terms of cooling effects, biodiversity, and physical activity. However, health-enhancing effects relating to restoration, mental health, social participation, emotional bonding, and recreational physical activity were found to be particularly prominent for blue spaces [2,9,10]. Furthermore, many of the interventions implemented in blue spaces are explicitly designed to encourage active travel (e.g., by encouraging walking and cycling), which further highlights their role in promoting PA in local populations [11].
Therefore, the aim of this study was to explore the social value that communities place on blue environments, specifically canals, by identifying enablers and barriers to their use for PA. The findings will guide the selection of key factors within a framework for assessing blue spaces for physical activity and health and wellbeing, as well as for prioritising investment in these environments.
2. Materials and Methods
Workshops were conducted with local community groups, including members of the public with varying degrees of interest in using canals for physical activity. Individuals who visited canals less frequently also participated in the workshops to ensure that a wide range of views was captured. The overarching aim of the workshops was to identify community needs and priorities for using local canals for PA, including recreational PA and travel-related activity. As experts of their own circumstances, community members were encouraged to share their perspectives and experiences to conceptualise the value they place on using canals for their PA and, subsequently, their health and wellbeing. To achieve this, participants in the workshops were encouraged to use the nominal group technique (NGT) to define enabling and discouraging factors that influence their use of local canals, and subsequently vote for the most important ones. The total votes were tallied to calculate rating scores, which were then used to rank ‘factors’ by order of importance (i.e., highest to lowest rating score). Group discussions were recorded and data were analysed quantitatively and qualitatively. Ethics approval was granted by the Science, Technology, Engineering and Mathematics Committee at the University of Birmingham (ERN_2022-0291).
2.1. Participants and Recruitment
Two workshops (WS1 and WS2) were organised and held in Birmingham, UK, with different public groups. For the first workshop (WS1), adult community members were invited irrespective of whether they routinely visited canals for their (physical) activities. Participants were recruited by using convenience sampling and targeting local community groups, local park users, and University of Birmingham staff and students. Invites were either (a) electronic invitations distributed via mailing lists for university staff and students or (b) flyers and posters placed in parks and key community locations (e.g., notification boards in community buildings). Interested participants emailed the lead researcher (N.A.), who then provided more information about the study.
For the second workshop (WS2), targeted participants were members of a canal walking group and hence, regular users of local canals. The group meet weekly and engage in walks and other activities by a canal. Initial contact with the group leader, who was a Canal & River Trust volunteer, was established through a member of the Public Advisory Group in the Centre for Economics of Obesity, University of Birmingham. WS2 took place during the walking group’s usual meet-up following the canal walk. Participants were informed about the workshop in advance, to ensure their voluntary participation. Interested participants registered their attendance with the group leader, who then informed the researcher (N.A.) about the total number of attendees in advance. Since participants’ membership with the canal walking group was pre-determined, it was not possible to control for a balanced representation of participants’ characteristics. The structure of the two workshops was not expected to yield comparable findings but rather it reflects a pragmatic approach to identifying participants who might be interested in the study.
A group size of between 6 and 12 participants is recommended for the NGT to ensure a range of opinion [12]. Prior to the workshops, participants received a Participant Information Sheet detailing the study objectives and information about protection of their personal data. Written informed consent was obtained from all individuals participating, and each participant received a GBP 20 high street shopping voucher as compensation for their time.
2.2. Setting
Participation in the workshops was limited to in-person attendance only. A city centre location was selected for WS1, because it was easily accessible by public transport and had disabled access. The room featured a round table, flipchart, and monitor. WS2 was held at a canal-side venue often used by the canal walking group, which was adapted to facilitate the focus group. Adaptations included the addition of a round table and monitor and participant-only access to the room for data protection purposes. Refreshments were provided to all participants. The workshops took place in February 2023 (WS1) and June 2023 (WS2).
2.3. Data Collection
2.3.1. Nominal Group Technique
Both WS1 and WS2 used the NGT to collect data on the enablers and barriers related to using canals for PA. The NGT, first developed by Delbecq and Van deVen (1972) [13], involves a group process for judgemental problem exploration that aims to achieve a group agreement in response to specific question(s) on a chosen topic, and is particularly relevant to health planning situations. The technique allows for direct participant involvement in a non-hierarchical and highly structured way, and is used for idea generation, strategic problem solving, and priority identification [13]. Each participant is given the opportunity to present their ideas and vote independently; thus, the NGT prevents the discussion being dominated by group members who are more vocal or have authority [14]. In this context, the NGT was selected for its ability to promote inclusive participation and plurality in generated views, while mitigating the influence of power dynamics within the group. Additionally, it offers a resource-efficient way of finding solutions to simple problems [15].
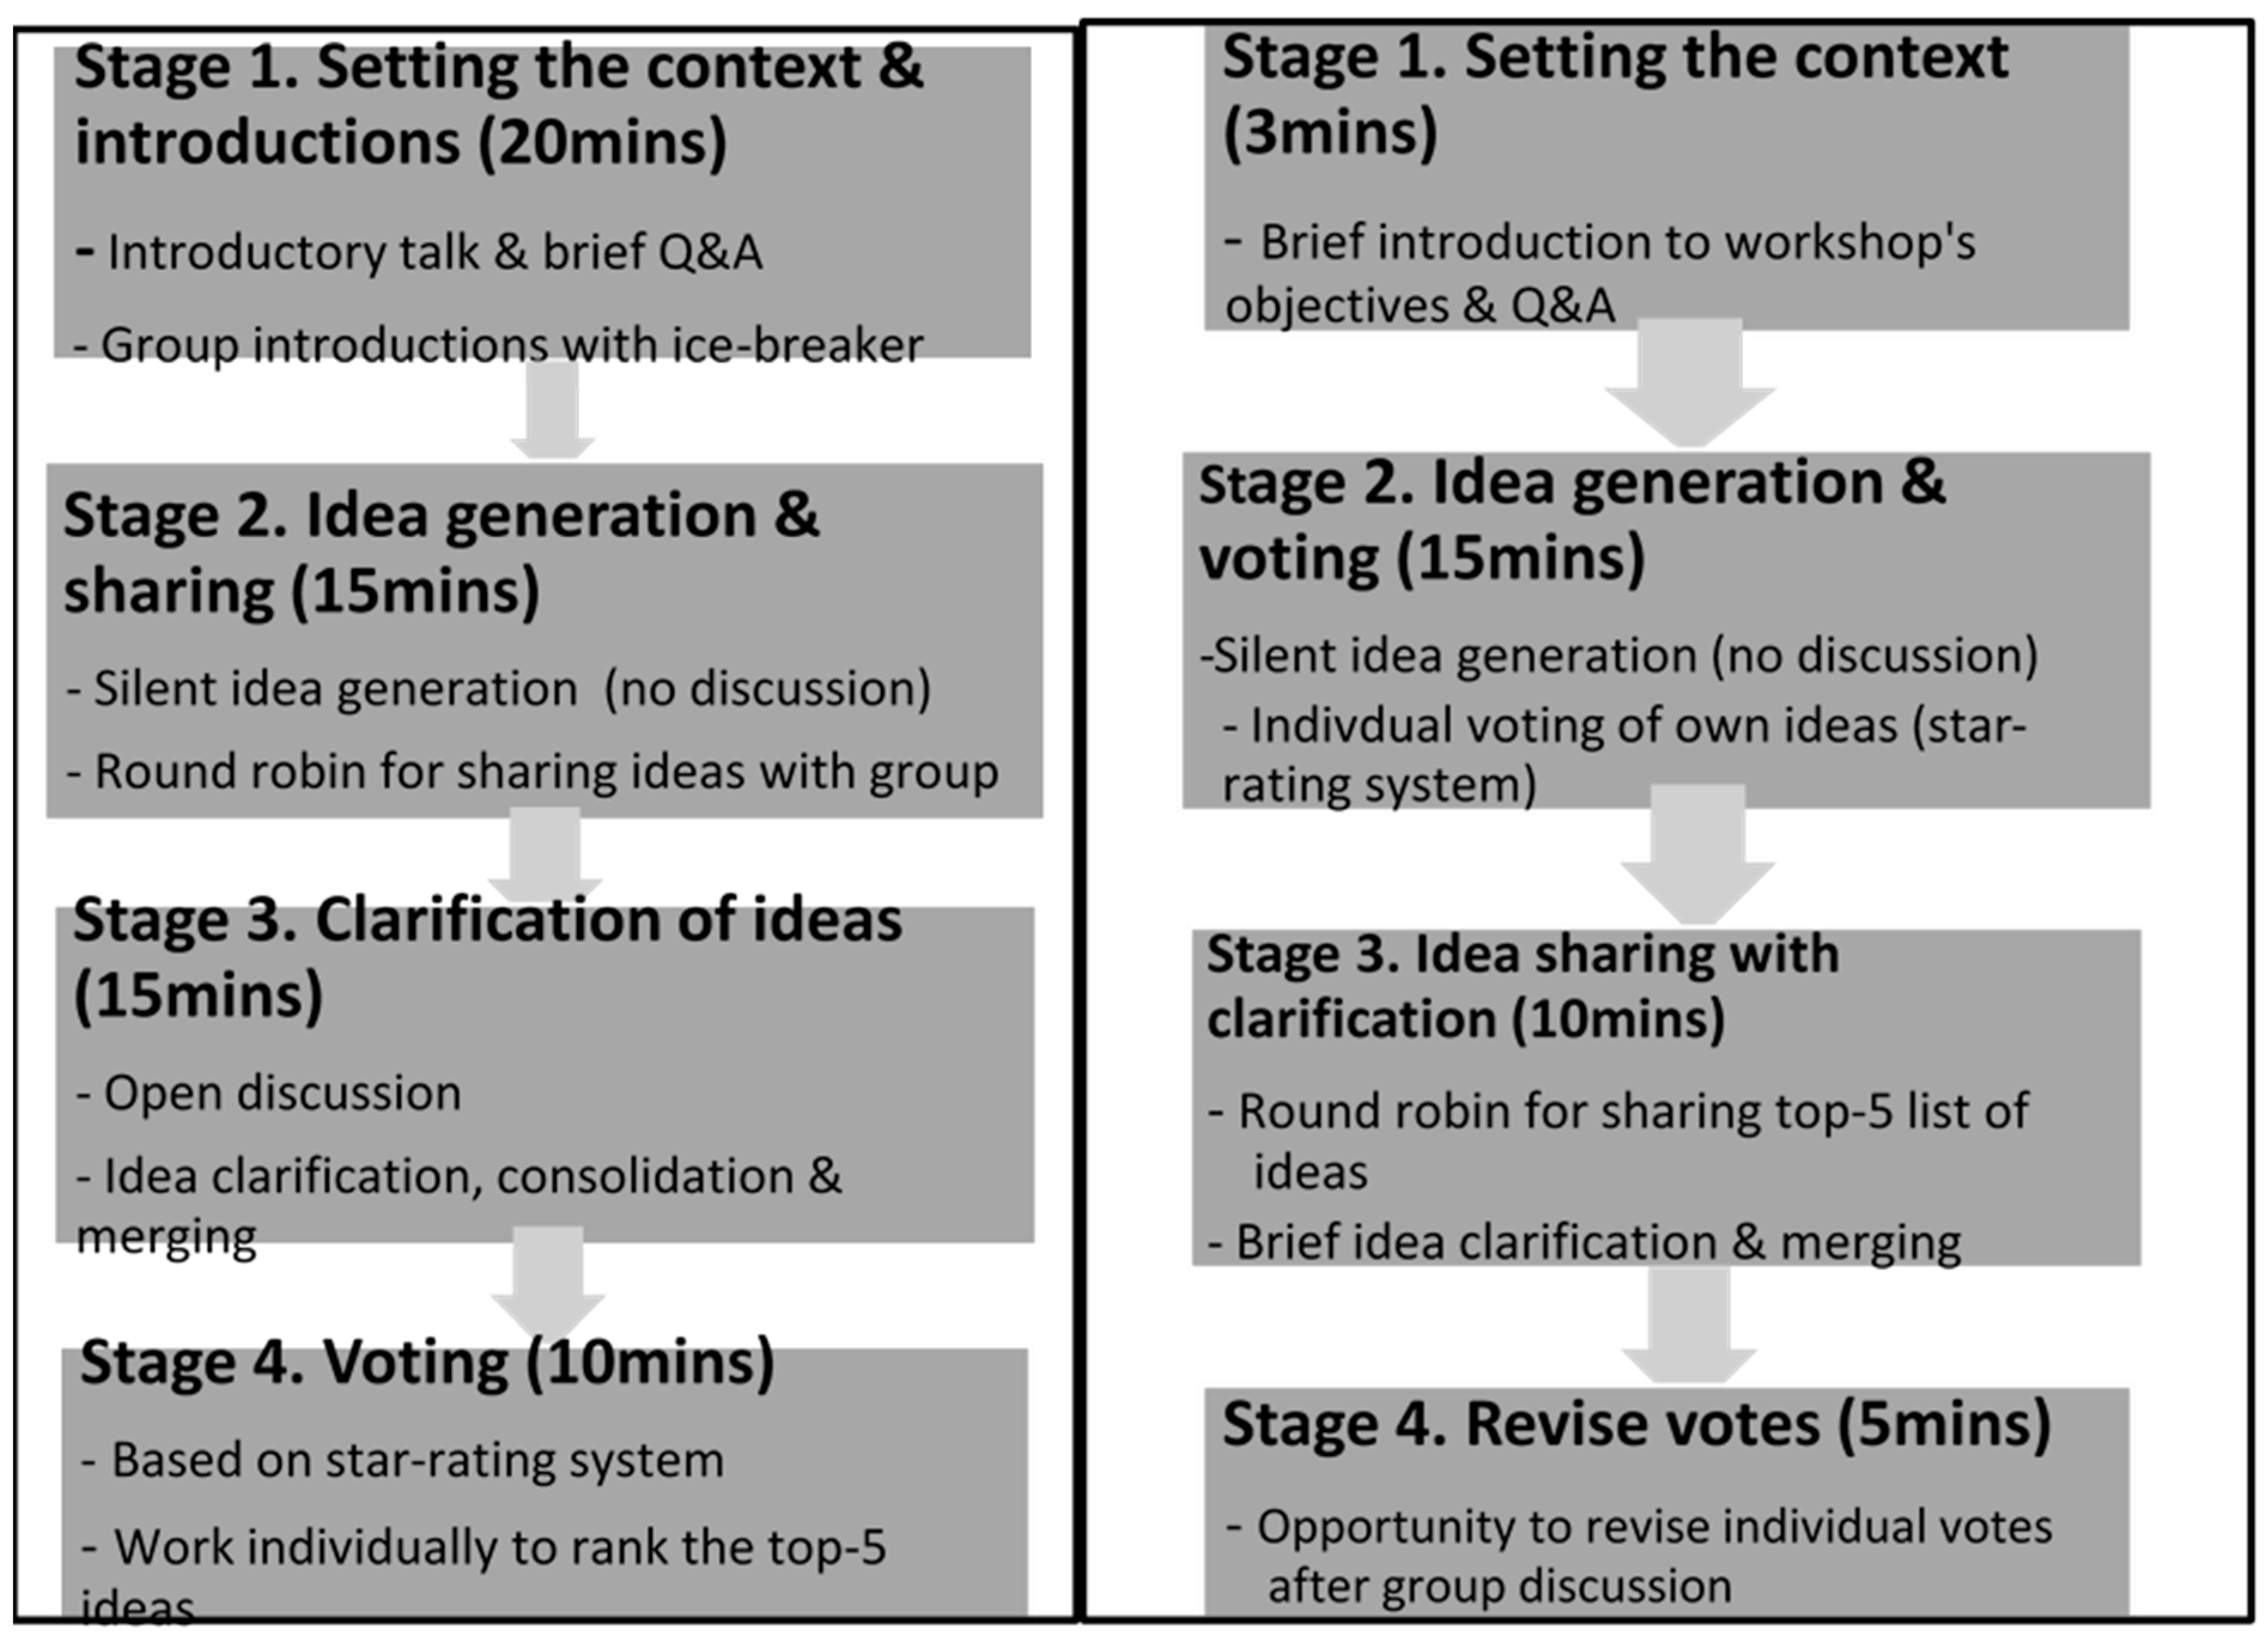
The NGT was applied in four steps: (1) silent idea generation, (2) round robin, (3) clarification of ideas, and (4) individual voting of ideas (Figure 1). Prior to the idea generation step, the facilitator [NA] presented information about blue spaces, determinants of canal use, and relevant health and wellbeing benefits to participants. Participants were given instructions about the NGT tasks, emphasising the importance of working independently during the idea generation and voting stages. All ideas generated by individual group members were eligible for the voting without any exclusions. To ensure clarity of the voting process, a star rating system was applied where more stars were allocated to more important ideas. During the voting, participants were asked to work individually and vote for their top five ideas—in order of importance [14]—with 5 stars/votes given to the most important idea and 1 star/vote to the least important idea. Following the voting stage, group ideas were ranked and participants were given the opportunity to discuss their reflections on the final rankings. The facilitator coordinated the group discussion, recorded the group’s votes on a flipchart, and calculated the final combined votes for each idea. The method was piloted during a public discussion event focused on the value of green/blue spaces for health.
Figure 1.
Nominal group technique process in WS1 (left) and WS2 (right).
In each workshop, the NGT steps were repeated twice to generate and vote on ideas in response to the following questions:
Q1. “In your opinion, what are some encouraging factors that make people want to use canals for exercise?”
Q2. “In your opinion, what are some barriers that discourage people from using canals and can have a negative impact on exercise levels and wider health and wellbeing?”
WS2 took place during the group’s planned meet-up and thus had a shorter duration than WS1.
Therefore, it was necessary to use a slightly adapted version of the NGT. Within the adapted NGT, the idea generation stage was followed by the individual voting of own ideas. Participants then shared their top-5 list of ideas with the group in a brief round robin and clarification session. Finally, participants had the opportunity to revise their individual votes based on the group discussion. The same steps were followed for each of the questions above (i.e., Q1 and Q2). Participants’ ideas were recorded on a flipchart and supplemented with field notes taken by two facilitators: the researcher (N.A.) and a community researcher. An outline of this adapted NGT is available in Figure 1.
2.3.2. Recordings and Field Notes
Group discussions in WS1 were audio recorded and transcribed to collect further explanatory data on participants’ ideas. In WS2, facilitators captured all additional information in field notes, as audio recording was not feasible. The data collected from the recordings and field notes were used alongside the NGT results to provide context and help with categorising the ideas into key criteria for the assessment framework.
2.4. Data Analysis
2.4.1. Ratings and Rankings
Individual votes on the five most important ideas for each question were transferred to a spreadsheet and analysed separately for the WS1 and WS2 groups. The total rating for each idea was calculated by summing the votes for each idea from all participants in the group, according to the equation below:
where vi is the number of votes given to the idea by participant i.
Total rating = Σ(vi)
Based on the total rating, ideas were then ranked from top to bottom. All calculations were performed using Microsoft Excel 2019®.
2.4.2. Categories Used as Factors within the Framework
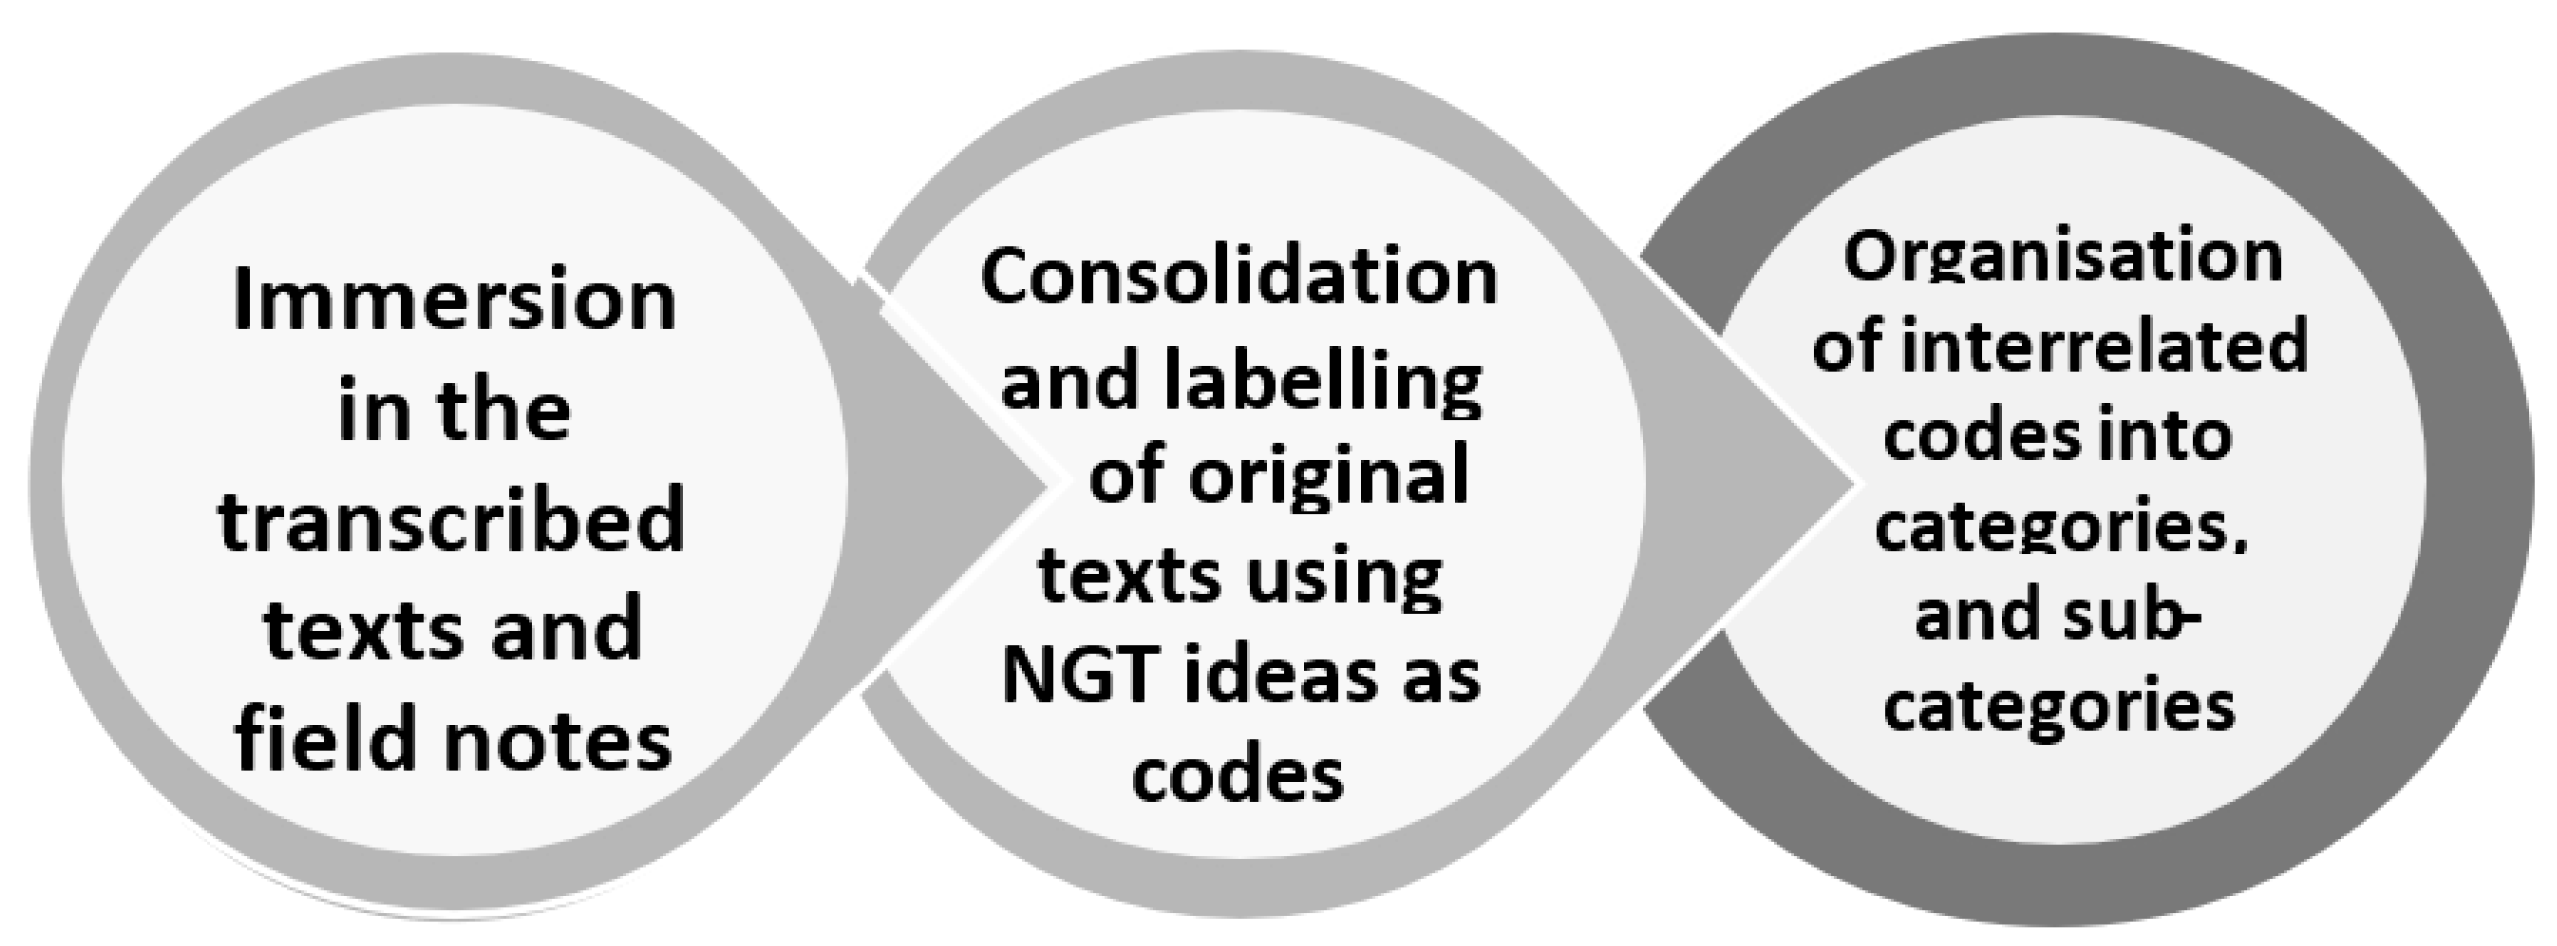
The WS1 transcript and WS2 field notes were analysed qualitatively to (i) provide context on participants’ ideas and (ii) organise the ideas into broader categories corresponding to key criteria within the assessment framework. A deductive thematic analysis (Figure 2) was employed, with pre-defined codes based on participant’s ideas [16,17]. Broader themes emerged by grouping related codes into categories. Firstly, texts were read to understand the concepts and meaning of discussions. Secondly, the texts were condensed and labelled using codes, which corresponded to the ideas recorded through the NGT steps. Codes were compared, looking for similarities and differences, and then organised into categories. Each category included several codes related in either content or context. In cases where codes referred to different aspects of the same category, sub-categories were generated for intermediate grouping. Brief definitions were developed for each category to enhance understanding. The coding and category construction were performed using NVivo12.
Figure 2.
Process of identifying codes and categories using deductive thematic analysis.
3. Results
3.1. Sample Characteristics
A total of 21 participants took part across the two workshops. The WS1 group comprised eight members of the public with differing levels of interest in using local canals for PA, including individuals who visit rarely. The WS2 group consisted of 13 regular canal users who actively participated in a canal walking group. In both the WS1 and WS2 groups, the majority of participants were female, accounting for 63% and 92%, respectively. Within WS1, there was representation from different age groups and different ethnicities, such as British white (50%), other white (25%), Asian/Asian British (13%), and mixed/multiple ethnic groups (13%). Most WS2 participants were aged 55 years and above and British white (73%), with only one participant coming from an Asian/Asian British background. With respect to highest qualification, 63% of the participants in WS1 had a Doctorate/Master’s degree, while 46% of WS2 participants had a high school/college diploma. Additionally, the WS1 group had a higher proportion of participants in full-time employment (25%) or retired (25%) compared to the 54% of unemployed (looking for work) participants in WS2. The majority of participants in both groups were physically active, doing more than 150 min of PA per week. All sample characteristics are presented in Table 1.
Table 1.
Sample characteristics.
3.2. Ratings and Ranking of Enablers and Barriers in WS1
A total of 20 encouraging factors for using canals for PA emerged from WS1 and are presented in Table 2. During the clarification stage, WS1 participants discussed merging the initially separate ideas of “Good routes/transport” and “Pubs/destinations”, as they perceived them as overlapping. “Connectedness with nature” was described in various ways by different participants, including opportunities to participate in relevant activities (e.g., birdwatching) and new learning experiences (e.g., learning about the local flora and fauna).
Table 2.
Ratings and rankings of enablers and barriers in WS1.
Regarding the ratings of ideas, a total score was calculated by summing the votes of all participants. “Connectedness with nature” had the highest rating (rating score: 26) and ranked top in the list of enablers, followed by “good routes/transport to destinations” which had a rating of 20 and was ranked second. In third place was “traffic-free space” with a rating score of 17.
With respect to the barriers, WS1 participants reported 22 factors restricting use of local canals. Most of the barriers were safety-related, such as anti-social behaviour, insufficient lighting, lack of cameras, and unkempt paths along the stretches. Barriers relating to the “maintenance of facilities” were also highlighted and centred around the “lack of resting stations”, “cleanliness” (of both water and paths), and “uneven/badly maintained surfaces”. Inequality concerns were widely discussed within the WS1 group, emphasising the need for fairer resource distribution across stretches and the lack of diversity in demographic characteristics among canal users. No ideas were omitted during the group discussion. The top three barriers with the highest rankings were “anti-social behaviour” (rating score: 22), “lack of lighting and cameras” (rating score: 21), and “social acceptability” (rating score: 13). All ratings and rankings are presented in Table 2, with the top three factors highlighted in bold.
3.3. Rankings of Enablers and Barriers in WS2
The WS2 participants reported 10 factors that facilitated the use of canals for PA and 11 barriers that restricted their use (Table 3). Amongst the enablers, the “opportunity to be sociable/interact with people” was voted by the majority of participants and ranked top with the highest rating (39). The “mental health benefits” referred to the quiet and peaceful water environment with its stress-relieving properties, and the opportunity to talk about mental health and mindfulness with other people. This factor was voted in second place with a rating of 24. Finally, the factor “being outside in the fresh air/nature while exercising—countryside feeling in urban area” was ranked in third place (rating: 23). Key barriers were safety perceptions, physical risks, and lack of well-maintained facilities. The top three enabling and discouraging factors as voted by the WS2 group are highlighted in bold.
Table 3.
Ratings and rankings of enablers and barriers in WS2.
3.4. Categories and Key Framework Criteria Emerging from the Workshops
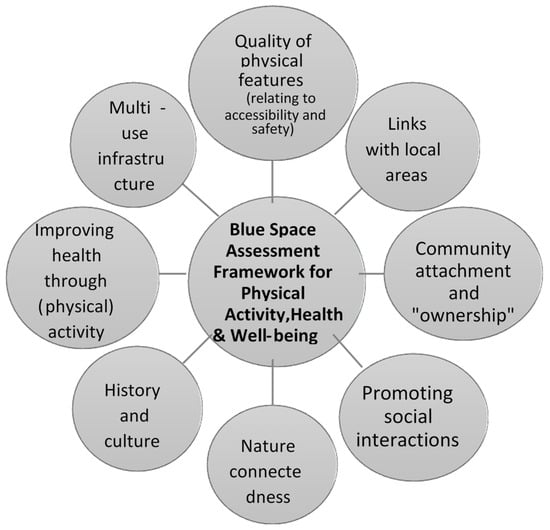
Deductive thematic analysis was used to organise the ideas from both workshops into broader categories. The main categories that emerged were (1) quality of physical features of canals; (2) locality of canals/links with local areas; (3) improving health through (physical) activity; (4) multi-use canal infrastructure; (5) community attachment and “ownership”; (6) promoting social interactions; (7) connectedness with nature; and (8) history and culture. Each of these categories represents a specific criterion in the assessment framework as presented in Figure 3.
Figure 3.
Framework for assessing blue environments for physical activity, health, and wellbeing.
Detailed descriptions of the categories are presented in Appendix A (Table A1). The first category, ‘quality of physical features of canals’, was further divided into two sub-categories of (a) accessibility and (b) safety. Accessibility referred to path conditions and width, entrance points, disabled access, and transport routes. Safety included both physical risks, such as uneven surfaces, lack of signage, or lack of lighting and cameras, as well as feelings/perceptions of fear of walking alone or feeling unsafe when less people are around. Within both workshops, participants agreed that accessibility and safety of canals are different aspects that determine the overall quality of canals.
The ‘locality of canals’ was about canals offering a means to explore or travel around the local area and access other destinations (e.g., pubs, shops, etc.). This category included factors relating to public transport links, active travel routes, and traffic-free access.
The multidimensional benefits to physical and mental health and broader wellbeing provided through using canals for PA were widely discussed by WS1 and WS2 participants. Discussions focused on the opportunities for improving health through various activities, including recreation, day-to-day activities such as dog walking, and participation in formal sports such as paddle boarding. Additionally, participants talked about wider wellbeing benefits from the relaxing and stress-relieving properties of water and opportunities to talk about mental health with peers. The respective category related to ‘improving health through (physical) activity’.
The ‘multi-use canal infrastructure’ category was described as the infrastructure that enables the use of canals for different types of users such as runners and cyclists, and which allow various activities to take place simultaneously.
The next category, ‘community attachment and ownership’, was about enhancing the attachment of local communities with canals through disseminating information and raising awareness about local canals.
Canals were also perceived as a meeting place where people can expand their social network and participate in collective activities which enhance their sense of belonging. Therefore, the category ‘promoting social interactions’ was formed to describe this contribution of canals to individuals’ social relationships.
‘Connectedness with nature’ was reflected in various discussions and ranked amongst the top-three enablers by participants in both workshops. This category was described by the opportunities to be close to, explore, and observe nature while participating in activities near a canal.
Finally, the category ‘history and culture’ included sharing information and awareness about the historical and cultural aspects of canals, since canals are recognised as an important part of a place’s heritage. Despite not being directly linked to PA, this was discussed as a facilitator of long-term engagement and usage of canals.
Further details on the respective codes for each category are presented in Appendix B (Table A2).
4. Discussion
4.1. Main Findings
This study aimed to explore the key enablers and barriers to using local canals for PA within local communities to inform investment towards sustainable and efficient interventions. Across two workshops, data were obtained from community members who expressed differing levels of interest in using local canals for physical activity. The key enablers for exercising at canals included opportunities to be close to nature, enjoy a quiet and stress-free environment, meet with others, and connect to local destinations. The key barriers were safety-related, including anti-social behaviour, lack of lighting and cameras, and fear of visiting alone. In the discussion, females and older individuals raised the most concerns about the safety of canal stretches. Additionally, participants highlighted the importance of belonging to a group and engaging in social interactions alongside doing PA in those spaces. The most important enabling and discouraging factors of canal use were compiled qualitatively and organised into eight categories to inform a framework for assessing blue environments for physical activity, health, and wellbeing. The framework covers a broad range of factors relating to infrastructure, social networks, culture, local areas and nature, and health.
4.2. How the Findings Link to Previous Studies
Previous studies exploring factors influencing the use of green/blue spaces and local neighbourhoods for physical activities have found similar results to this study. For instance, research conducted in an urban area of Beijing, China, identified several significant barriers to green space usage, including inadequate maintenance and sanitation, substandard vegetation quality, limited space size, and poor accessibility (e.g., lengthy access distances and inadequate linkage with local areas) [18]. Additionally, a recent literature review highlighted that physical characteristics such as accessibility (including disabled access), path conditions and maintenance, surrounding road networks, public transport, and active travel routes all play important roles in determining blue space quality for public health [19].
A system dynamics assessment of enablers and barriers to the use of green/blue spaces for health and wellbeing in Ireland identified seven key categories, most of which align with findings from this study. Common categories included multiple uses and transport access; social inequalities; social and community cohesion through opportunities for activities, participation, and shared experiences; perceived and actual risks; participation and engagement in outdoor activities; and biodiversity and natural environment [20].
From a systems thinking perspective, the value of green/blue spaces involves complex, multifactorial relationships between the physical characteristics of spaces and social factors that affect their use. Our study has identified several social factors as enablers of canal use expressed as social interactions, community attachment, and a sense of “ownership” cultivated through participation in collective activities, as well as disseminating information and awareness. These factors promote social cohesion in local communities, which has been shown to alleviate disparities in use and, subsequently, health inequalities [21]. Additionally, such factors help to sustain the effects of interventions beyond the initial funding period so as to achieve more sustainable health and wellbeing outcomes.
4.3. Strengths and Limitations
The use of quantitative and supplementary qualitative data represents an important strength of this study. Factors influencing canal use were ranked based on the total sum of participants’ votes and organised into categories using qualitative data collected through recordings and field notes during the workshops. The mixed-method analysis provided a detailed list of community ideas, which was then translated into key areas for future policy action. The collaborative nature of the NGT approach was another strength as it facilitated the co-production of dimensions of the social value of canals with community members. This was achieved through the direct involvement of participants in a democratic, non-hierarchical manner. Lastly, representation of community members with varying levels of interest in using local canals and from various demographic groups in the study population was an advantage of this study, as it allowed for diversity in views, helping us to understand ‘true’ barriers and enablers for all. Consequently, the use of these findings to inform future canal investments would ensure an evidence-based funding allocation process that prioritises benefits to community health and wellbeing.
Nevertheless, this study had some limitations. Firstly, convenience sampling of a smaller participant group may have hindered the generalisability of the findings. Additional data collection using a larger, representative sample would have strengthened the results. However, within this study, recruitment was restricted due to resource (i.e., time and budget) and methodological constraints. Additionally, the day and timing of the workshops may have limited participation, particularly for working age individuals, possibly skewing towards representation of more ‘research engaged’ and available individuals. Secondly, it is noteworthy that the majority of participants in both workshops were female. This gender imbalance may have had an impact on the applicability of findings to other population groups. Achieving a more balanced representation would enhance the study’s ability to accurately capture diverse and unique experiences. Thirdly, the use of an adapted NGT in WS2 resulted in shorter time for discussion, potentially compromising the richness and depth of the collected data. However, in their feedback, participants were satisfied with the opportunity and time to share their views without raising any concerns. Finally, the total votes for an idea could have been influenced by the size of the group in two ways: first, the total number of ideas generated, and second, the number of votes available to assign to each idea. Nevertheless, the purpose of this study was to present the voting results of the two groups separately, and not in combination, so no weighting was applied.
5. Conclusions
This study contributes to the current literature by advancing the understanding of the value that communities place on blue spaces as local assets, which are key to their health and wider wellbeing. The findings informed the development of a framework for assessing blue environments for physical activity, health, and wellbeing. The framework included a wide range of infrastructural, societal, cultural, and local integration factors. Factors related to accessibility, safety, and user-friendly environments can guide investment towards improving these assets with a focus on public health. Additionally, understanding the impact of sociocultural factors is valuable for broadening the evaluative scope of investment prioritisation towards more sustainable and efficient policies that can bring long-lasting improvements in population health and wellbeing.
The findings from this study will inform future work on prioritising investment aimed at promoting PA in natural environments, alleviating access inequalities, and improving the overall health and wellbeing of local communities.
Author Contributions
Conceptualization, N.A. and E.F.; methodology, N.A.; formal analysis, N.A.; investigation, N.A.; resources, K.H., S.E. and J.S.; data curation, N.A.; writing—original draft preparation, N.A.; writing—review and editing, E.F., L.J., L.F.A., K.H., S.E. and J.S.; supervision, E.F., L.J. and L.F.A.; funding acquisition, E.F. All authors have read and agreed to the published version of the manuscript.
Funding
N.A., E.F. and L.F.A. are funded by the National Institute for Health and Care Research (NIHR) [Research Professorship Award NIHR300773]. The views expressed are those of the author(s) and not necessarily those of the NIHR or the Department of Health and Social Care.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki, and approved by the Institutional Review Board (or Ethics Committee) of the University of Birmingham (protocol code ERN_2022-0291 and 29/07/2022).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
Data are unavailable due to privacy and ethical restrictions.
Acknowledgments
We would like to acknowledge the members of our Public Advisory Group for contributing to the organisation and facilitation of the workshops.
Conflicts of Interest
Authors Stephanie Elliott, Katrina Hull, and Jenny Shepherd were employed by the third sector organisation Canal and River Trust. The remaining authors declare that the research was conducted in the absence of any commercial or financial relationships that could be construed as a potential conflict of interest.
Appendix A
Table A1.
Factor categories and respective descriptions.
Appendix B
Table A2.
Detailed presentation of categories, sub-categories, and codes.
References
- Assessing the Value of Urban Green and Blue Spaces for Health and Well-Being; WHO Regional Office for Europe: Copenhagen, Denmark, 2023.
- White, M.P.; Elliott, L.R.; Gascon, M.; Roberts, B.; Fleming, L.E. Blue space, health and well-being: A narrative overview and synthesis of potential benefits. Environ. Res. 2020, 191, 110169. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- White, M.P.; Elliott, L.R.; Grellier, J.; Economou, T.; Bell, S.; Bratman, G.N.; Cirach, M.; Gascon, M.; Lima, M.L.; Lõhmus, M.; et al. Associations between green/blue spaces and mental health across 18 countries. Sci. Rep. 2021, 11, 8903. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, A.C.; Maheswaran, R. The health benefits of urban green spaces: A review of the evidence. J. Public Health 2011, 33, 212–222. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- UK National Ecosystem Assessment. The UK National Ecosystem Assessment; UNEP-WCMC: Cambridge, UK, 2011. [Google Scholar]
- Walugembe, D.R.; Sibbald, S.; Le Ber, M.J.; Kothari, A. Sustainability of public health interventions: Where are the gaps? Health Res. Policy Syst. 2019, 17, 8. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Twohig-Bennett, C.; Jones, A. The health benefits of the great outdoors: A systematic review and meta-analysis of greenspace exposure and health outcomes. Environ. Res. 2018, 166, 628–637. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bosch, M.v.D.; Sang, O. Urban natural environments as nature-based solutions for improved public health—A systematic review of reviews. Environ. Res. 2017, 158, 373–384. [Google Scholar] [CrossRef] [Scilit]
- Völker, S.; Kistemann, T. Developing the urban blue: Comparative health responses to blue and green urban open spaces in Germany. Health Place 2015, 35, 196–205. [Google Scholar] [CrossRef] [Scilit]
- Pearson, A.L.; Shortridge, A.; Delamater, P.L.; Horton, T.H.; Dahlin, K.; Rzotkiewicz, A.; Marchiori, M.J. Effects of freshwater blue spaces may be beneficial for mental health: A first, ecological study in the North American Great Lakes region. PLoS ONE 2019, 14, e0221977. [Google Scholar] [CrossRef] [Scilit]
- Bell, S.; Yiyan, C.; Zheng, C. Health and well-being aspects of urban blue space: The new urban landscape research field. Landsc. Archit. 2019, 26, 113–119. [Google Scholar]
- Harvey, N.; Holmes, C.A. Nominal group technique: An effective method for obtaining group consensus. Int. J. Nurs. Pract. 2012, 18, 188–194. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van de Ven, A.H.; Delbecq, A.L. The nominal group as a research instrument for exploratory health studies. Am. J. Public Health 1972, 62, 337–342. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Delbecq, A.L. Group Techniques for Program Planning: A Guide to Nominal Group and Delphi Processes; Gustafson, D.H., Van de Ven, A.H., Eds.; Scott Foresman: Glenview, IL, USA, 1975. [Google Scholar]
- Sink, D.S. Using the nominal group technique effectively. Natl. Product. Rev. 1983, 2, 173–184. [Google Scholar] [CrossRef] [Scilit]
- Boyatzis, R.E. Transforming Qualitative Information: Thematic Analysis and Code Development; Sage: Newcastle upon Tyne, UK, 1998. [Google Scholar]
- Braun, V.; Clarke, V. Using thematic analysis in psychology. Qual. Res. Psychol. 2006, 3, 77–101. [Google Scholar] [CrossRef] [Scilit]
- Zhang, W.; Yang, J.; Ma, L.; Huang, C. Factors affecting the use of urban green spaces for physical activities: Views of young urban residents in Beijing. Urban For. Urban Green. 2015, 14, 851–857. [Google Scholar] [CrossRef] [Scilit]
- Mishra, H.S.; Bell, S.; Vassiljev, P.; Kuhlmann, F.; Niin, G.; Grellier, J. The development of a tool for assessing the environmental qualities of urban blue spaces. Urban For. Urban Green. 2020, 49, 126575. [Google Scholar] [CrossRef] [Scilit]
- Kindermann, G.; Domegan, C.; Britton, E.; Carlin, C.; Mashinchi, M.I.; Ojo, A. Understanding the Dynamics of Green and Blue Spaces for Health and Wellbeing Outcomes in Ireland: A Systemic Stakeholder Perspective. Sustainability 2021, 13, 9553. [Google Scholar] [CrossRef] [Scilit]
- Lee, A.C.; Jordan, H.C.; Horsley, J. Value of urban green spaces in promoting healthy living and wellbeing: Prospects for planning. Risk Manag. Healthc. Policy 2015, 8, 131–137. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).