


Abstract
The local communities of Pakistan have vast traditional knowledge about local medicinal plants that is centuries old and transferred from generation to generation, but now, the survival of this precious ethnic knowledge is threatened. This study aimed to document the ethnomedicinal information residing within the communities of the Khadukhel Tehsil, Buner District, Pakistan. To conserve this valuable traditional knowledge, data were collected through a semi-structured questionnaire, one-on-one interviews, and group discussions. From 2018 to 2021, 853 people were interviewed regarding 317 plant species. Most of the ethnomedicinal data were obtained from members of the 60–69 age group. The most dominant plant family was Asteraceae (27 sp.). Leaves (124 sp.) were the most dominant plant part used in medicines, and paste (80 sp.) was the most common herbal formulation method. Most (88) medicinal plants were used to cure digestive system diseases. The collected medicinal plants and related indigenous medicinal knowledge were compared with previously published work on the surrounding areas. We suggest a phytochemical and pharmacological evaluation of the collected medicinal plants for the discovery of new drugs.
1. Introduction
Most (60.78%) of the population of Pakistan lives in rural parts of the country. Poverty, illiteracy, the poor quality of drinking water, the low status of women, and poor sanitation have a profound effect on their health [1]. Furthermore, the main health limitations across Pakistan, although especially in the rural areas, are inadequate awareness about health and illnesses, health service perceptions, and barriers within society. The healthcare system of Pakistan is divided into two main sectors: the public sector and the private sector. The allopathic healthcare system is the main pillar of the public-sector healthcare system, which is well-organized and regulated. However, it is underutilized due to shortcomings such as the poor attention paid to the upgrading of healthcare facilities [1], political interference, below-par human resources, and poor management and policy development [2]. The private sector of the healthcare system comprises a few recognized hospitals and health centers and several unrecognized hospitals, medical practitioners, homeopathists, hakims (physicians using traditional remedies), Unani (Grecoarab) herbalists, and local herbalists and spiritual therapists [3]. The local population consults these institutions and practitioners due to easy availability and access, affordability, family pressure, and the community’s strong opinions [1]. They are the primary choice for the treatment of illnesses such as depression, epilepsy, infertility, and psychosomatic troubles [3].
Medicinal plant research in Pakistan primarily comprises the documentation of their ethnic values. The local communities of Pakistan have vast traditional knowledge about local medicinal plants that is centuries old and transferred from generation to generation, but now, this knowledge is threatened [1] because of a lack of interest among the younger generations. Therefore, it needs proper documentation and conservation. Up till now, several studies have been carried out in different parts of the Buner District [1,4,5,6,7,8,9], but no single ethnomedicinal study has been conducted in the Khadukhel Tehsil. Therefore, the present survey was carried out to assess and conserve the ethnomedicinal knowledge of the Khadukhel Tehsil. This study will help to familiarize the local and surrounding communities with the novel medicinal uses of already known medicinal plants as well as newly reported medicinal plants.
2. Materials and Methods
2.1. Literature Review
Before starting the fieldwork, the online databases Google Scholar, ISI Web of Science, MEDLINE, Science Direct, and Scopus were searched using the terms “alternative medicines”, “therapeutic plants”, “medicinal plants”, “Tehsil Khadukhel”, and “District Buner, Pakistan”. The term “Tehsil Khadukhel and Buner Pakistan” was used to constrain the topographical extent of the search. The criteria for the selection of published articles were climate condition, forest type, closeness to the study area, and cultural similarity. The correctness of the botanical name(s) of various species mentioned in the current study depends upon that of the original sources.
2.2. Study Area
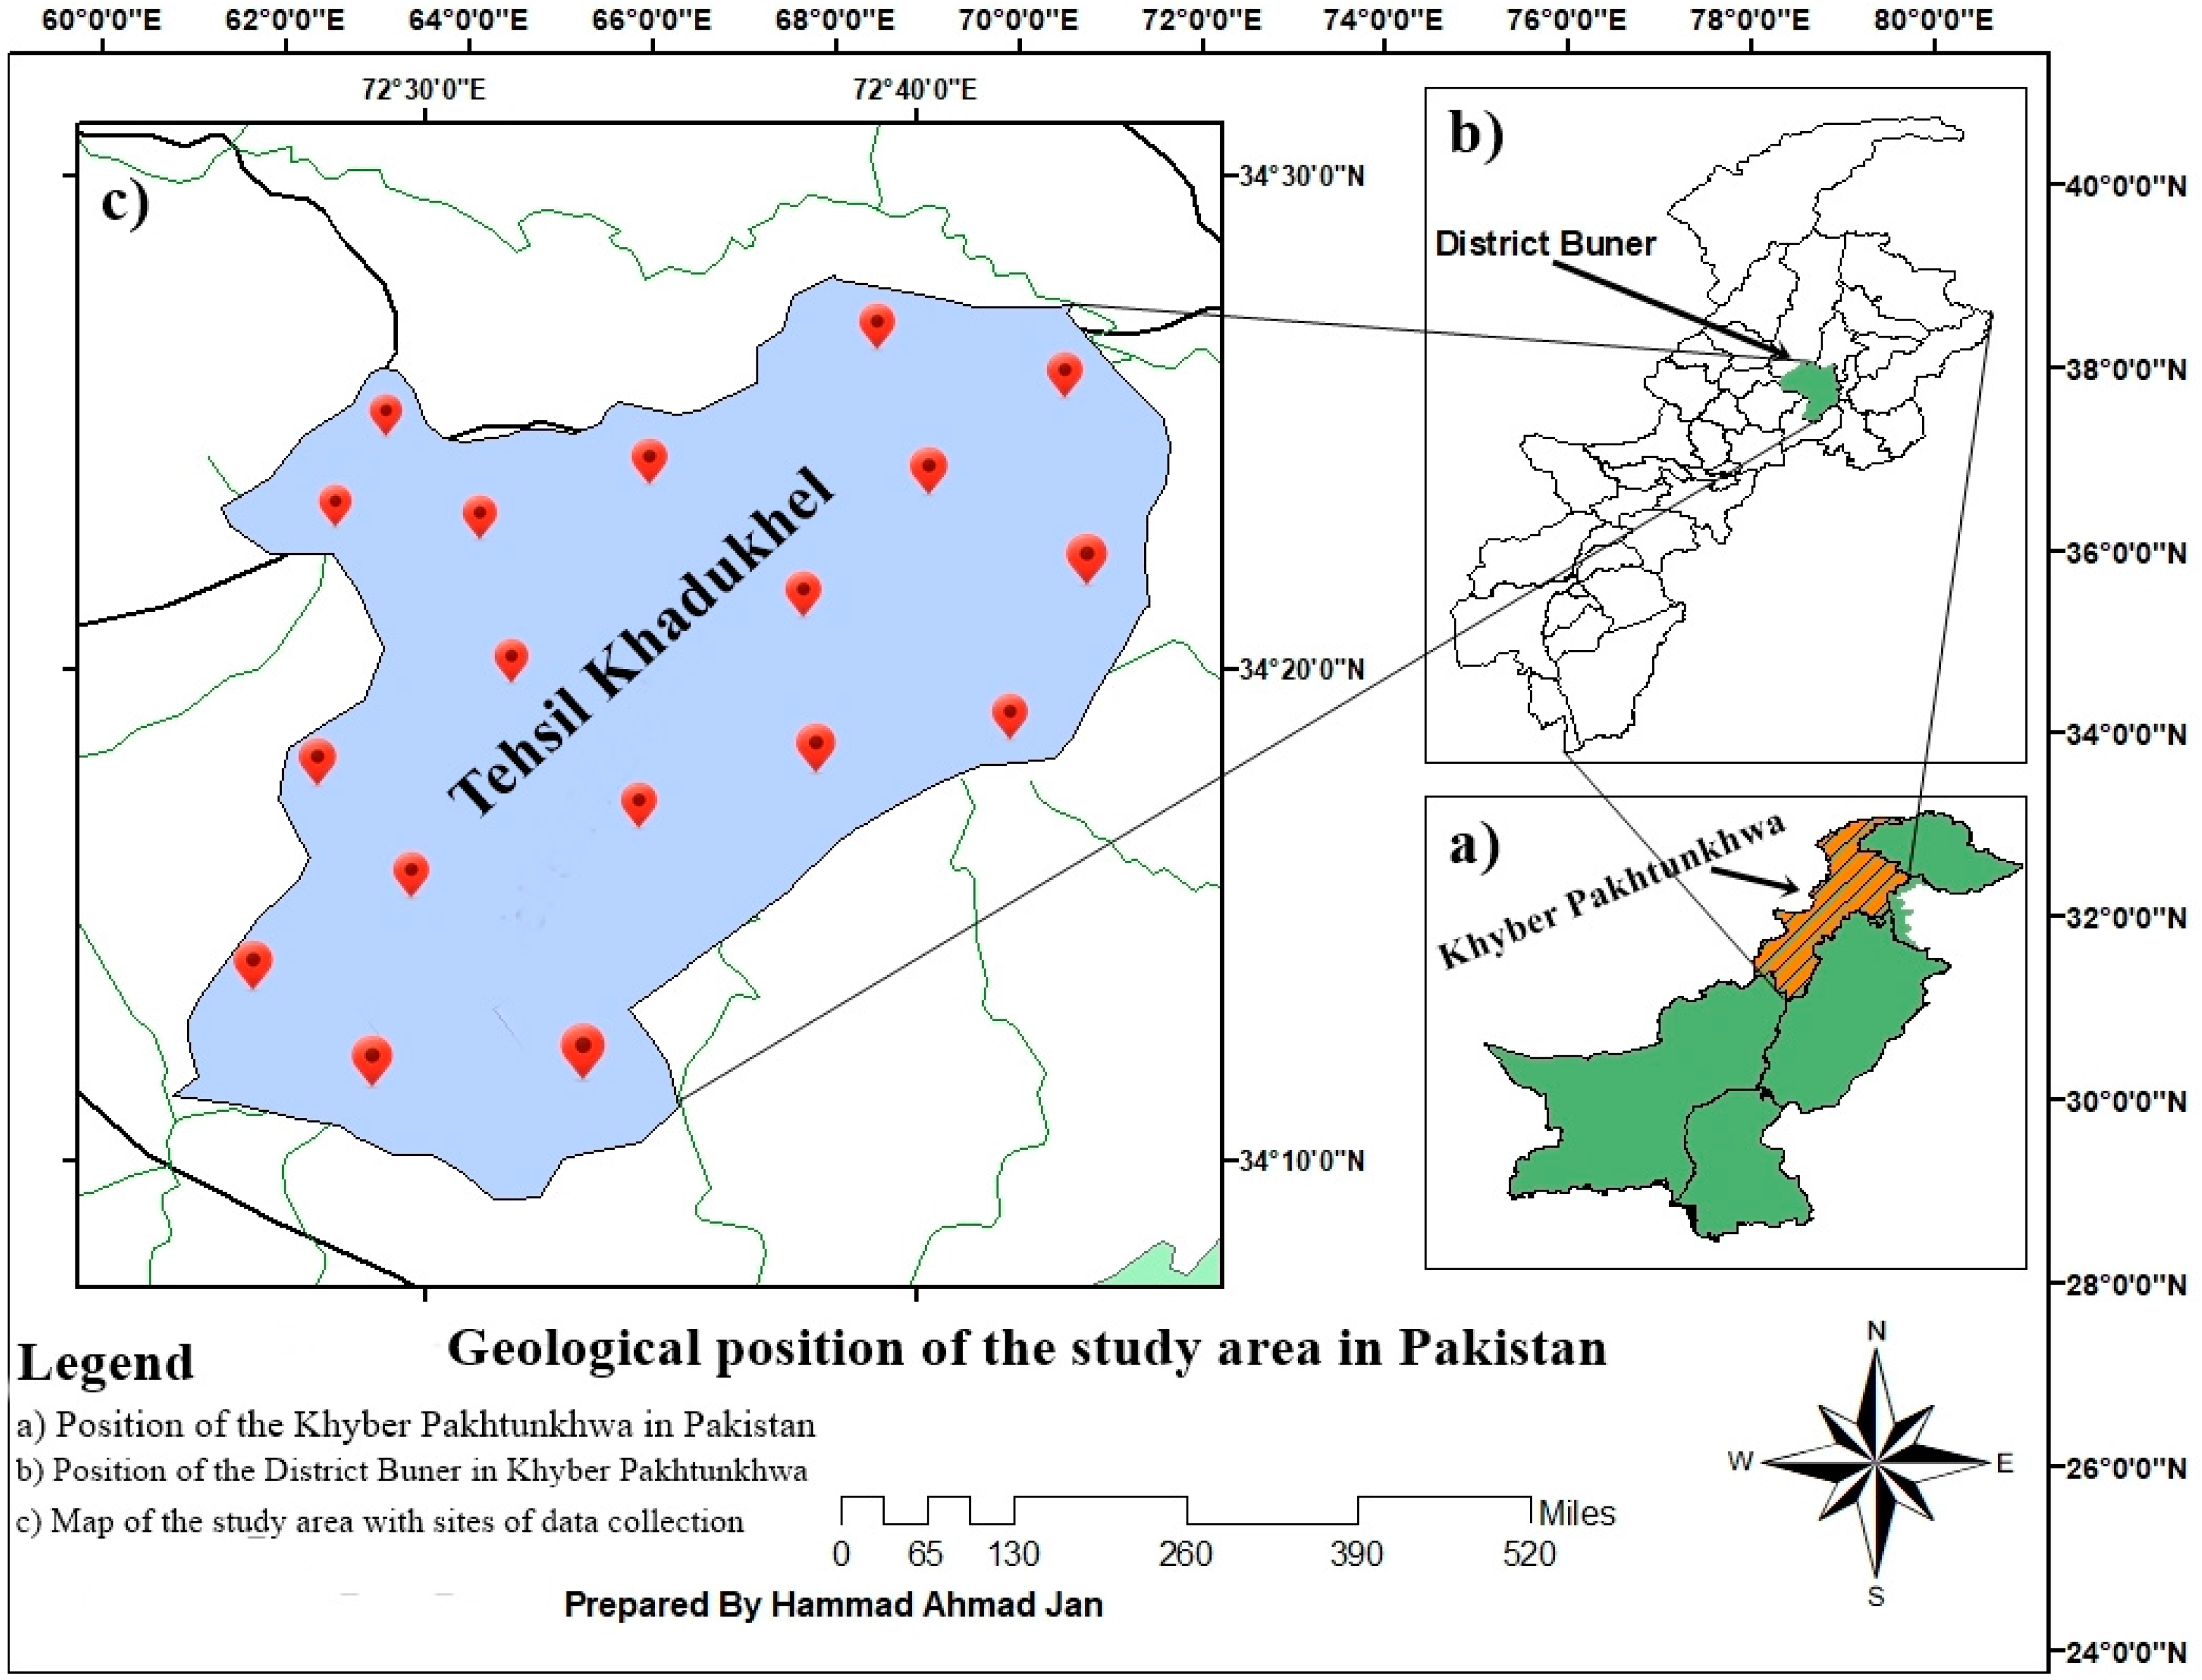
The study area is located in the south part of Buner District [9]. The geographical position of the Khadukhel Tehsil is 34.193301 N and 72.4924707 E (Figure 1). The dominant shrubs and tree species of the local flora are Acacia modesta, Butea monosperma, Dodonea viscosa, Grewia optiva, Gymnosporia royleana, Justicia adhatoda, Mallotus actinoneurus, Myrsine africana, Otostegia limbata, Olea ferruginea, Pinus roxburghii, Ziziphus jujube, Ziziphus nummularia, and Ziziphus oxyphylla [7]. The tehsil contains two hospitals; one is located in Totalai, with MBBS 1 or 2 doctors, and the other is located in Bagh, although it is nonfunctional. The population of the study area is 118,185, according to the 2017 Census. The covered area is 343 km2. Most of the population is Sunni Muslim, but Sikh families also live in this area as the minority population, especially in Ghurghostu and Chinglai [10]. Most of the inhabitants live in rural areas, and their primary source of income is agriculture and farming.
Figure 1.
Map of the study area, (a) Position of Khyber Pakhtunkhwa in Pakistan, (b) Position of District Buner in Khyber Pakhtunkhwa, (c) Map of the study area with sites of data collection.
2.3. Collection of Medicinal Plants
The plant specimens were collected during different seasons of the year. Eighteen different locations were selected randomly to collect medicinal plants and document ethnomedicinal data (Figure 1). Furthermore, randomly, four to five field trips were arranged during each season for the collection of maximum plants. During each field trip, we had a local guide show us essential medicinal plants for collection, and after collecting the plants, we met with local informants to document the medical uses of the collected plants. During the interviews with people, we observed that several species were not endemic to the study region yet were utilised to cure a variety of ailments. These non-native plants were either cultivated by residents or imported from other parts of the country. Their medicinal uses were also documented. The collected plant specimens were preserved according to the technique of Forman and Birdson [11]. During field work photographs of the vegetative parts, fruits and flowers were captured with the help of a Fuji digital camera for identification purposes. Furthermore, self and informants’ photographs were also captured during interviews. The collected specimens were identified by Dr. Zahid Ullah (Assist. Prof. in UoS) and with the help of the available literature and the Flora of Pakistan Tropicos [12]. The botanical names were further confirmed from the databases International Plant Names Index [13], The Plants list [14], and medicinal plants name service [15]. All the collected specimens were acquiesced to the Herbarium of the Department of Botany, Islamia College Peshawar, Pakistan for future reference.
2.4. Ethnomedicinal Data Documentation of Medicinal Plants
The present work was conducted from 2018 to 2021. A semi-structured questionnaire was used as a tool for ethnomedicinal data collection (Appendix A). The informants were interrogated through one-on-one interviews and group discussions. The snowball method was used for selecting the informants [16]. Detailed interviews were mostly followed by free listing. We encouraged the local population to enlarge the free listing. The collected ethnomedicinal data was cross-checked among the informants to confirm the genuineness of the data. Prior verbal consent was always taken from each informant [17]. We interviewed 853 local people, comprising 639 males, including 19 herbalists (Hakims), and 214 females, of which 26 were dayiahs (women famous for treating female-specific diseases). The native language (Pashto) was used during the interview to collect complete and correct data. Male informants were interviewed in the field, Hujra, or Baithaks, while female informants were interviewed at home. Local herbalists (hakims) were also interviewed at their herbal stores to document the current status of traditional knowledge. The questionnaire was mainly comprised of questions about the local name, part used as medicine, use for disease(s), complete method of preparation of recipes/medicine, and amount/dosage of medicine. Unceremonious talks and field walks were undertaken with key informants (185), which included herders, farmers, teachers, housewives, shepherds, and students (from school to university), to improve comprehension of the documented ethnomedicinal data. The ages of the informants varied from 20 to 113. The information they provided us was carefully documented using the technique of Mengistu and Hager [18]. To confirm the validity of the ethnomedicinal data collected about medicinal plants, it was cross-checked in different communities by presenting the plant’s fresh or dried specimen, telling the local name/s of the plant, or showing the plant’s photograph/s to the informants.
2.5. Ethical Considerations
The current work has been permitted by the ethical committee of the Department of Botany, Islamia College Peshawar, and Biodiversity Action Plan (BAP-2010–2020) for Pakistan. Prior consent was obtained from all participants before conducting interviews. This study has been conducted under the provisions of the Nagoya Protocol on Access to Genetic Resources and the Fair and Equitable Sharing of Benefits Arising from their Utilization of the Convention on Biological Diversity.
2.6. Software Used for Documentation and Analysis of Data
MS-Excel-2010 and PAST 4.10 version (Microsoft, Redmond, Washington DC, USA) were used for sorting the collected ethnomedicinal data and basic quantitative analysis and figure making. For the index used, the questionnaire was analyzed in two ways: firstly, responses of the informants were documented, and in the second step, binary values for the questions were considered: the 0 value was allotted to answer “NO” and the value 1 allotted to the answer “YES” [19].
2.7. Informant Consensus Factor (ICF)
This index is used to find out the agreement or similarity among the informants of the study area about the uses of plants for a particular group of diseases. The ICF is determined with the help of the succeeding formula [20]:
In the above formula, Nur is representing the use-reports number for a specific group of diseases and Nt is representing the taxa number used as medicine for that specific group of diseases by all the local respondents.
All the diseases were grouped according to the local people’s preferences in 14 different categories to determine the informant consensus factor (ICF). The ICF identifies the informants’ agreement about each category of disease. The ICF is used to determine the effectiveness of medicinal plants in treating a certain group of diseases. Furthermore, the ICF pointed out the most effective medicinal plants against the common group of diseases. The value of ICF varies between 0 and 1. If the value of ICF is near one, it shows the homogeneity of uses of plants for multiple purposes, well-defined selection criteria are present in the community, and the informants regularly exchanged ethnomedicinal knowledge. A value of ICF closer to zero indicates that the medicinal plants are selected randomly or there is a limited exchange of ethnomedicinal knowledge among informants of the community.
3. Results and Discussion
3.1. The Socio-Demographic Distribution and Characteristics of the Local Informants
To document the ethnic knowledge about the medicinal plants used for the cure of various diseases, a total of 853 indigenous people were interviewed including dayiahs, drivers, farmers, housewives, labors, shepherds, teachers, students (school to university), shopkeepers, hakims, herbalists (person who sells herbal medicines), and pansaries, etc. Of these, 639 were male informants. In terms of male informants, 19 were hakims, herbalists, and pansaries while 26 female informants were Dayiahs. The informants that were interviewed ranged in age from 20 to 113. These respondents were subsequently divided into seven groups of varying ages and seven groups of different literacy levels. Most of the ethnomedicinal data were obtained from the age group 60–69, followed by the 70–79 age group and 50–59. A decline in the ethnic knowledge of medicinal plants was observed in the informant groups with ages under 50. The informants aged 20 to 29 had the least knowledge about herbal remedies (Table 1). This may be due to the modernity of lifestyle, which encourages younger generations to choose allopathic medicines over natural remedies. [21]. Furthermore, according to the literacy classification with a rising literacy rate, there was a decreasing tendency in informants’ ethnomedicinal knowledge observed. This may be because educated individuals prefer the more advanced healthcare system over the conventional healthcare system [7]. Furthermore, other studies observed similar findings [7,22]. Furthermore, it has been noticed that males and females have almost similar ethnomedicinal knowledge. This might be because males harvest medicinal plants while women prepare herbal medications and treat patients at home. As a result, both men and women are more or less aware of the medicinal properties of plants [7,23].
Table 1.
Demographic profile of the study area.
3.2. Diversity of Families and Life Forms
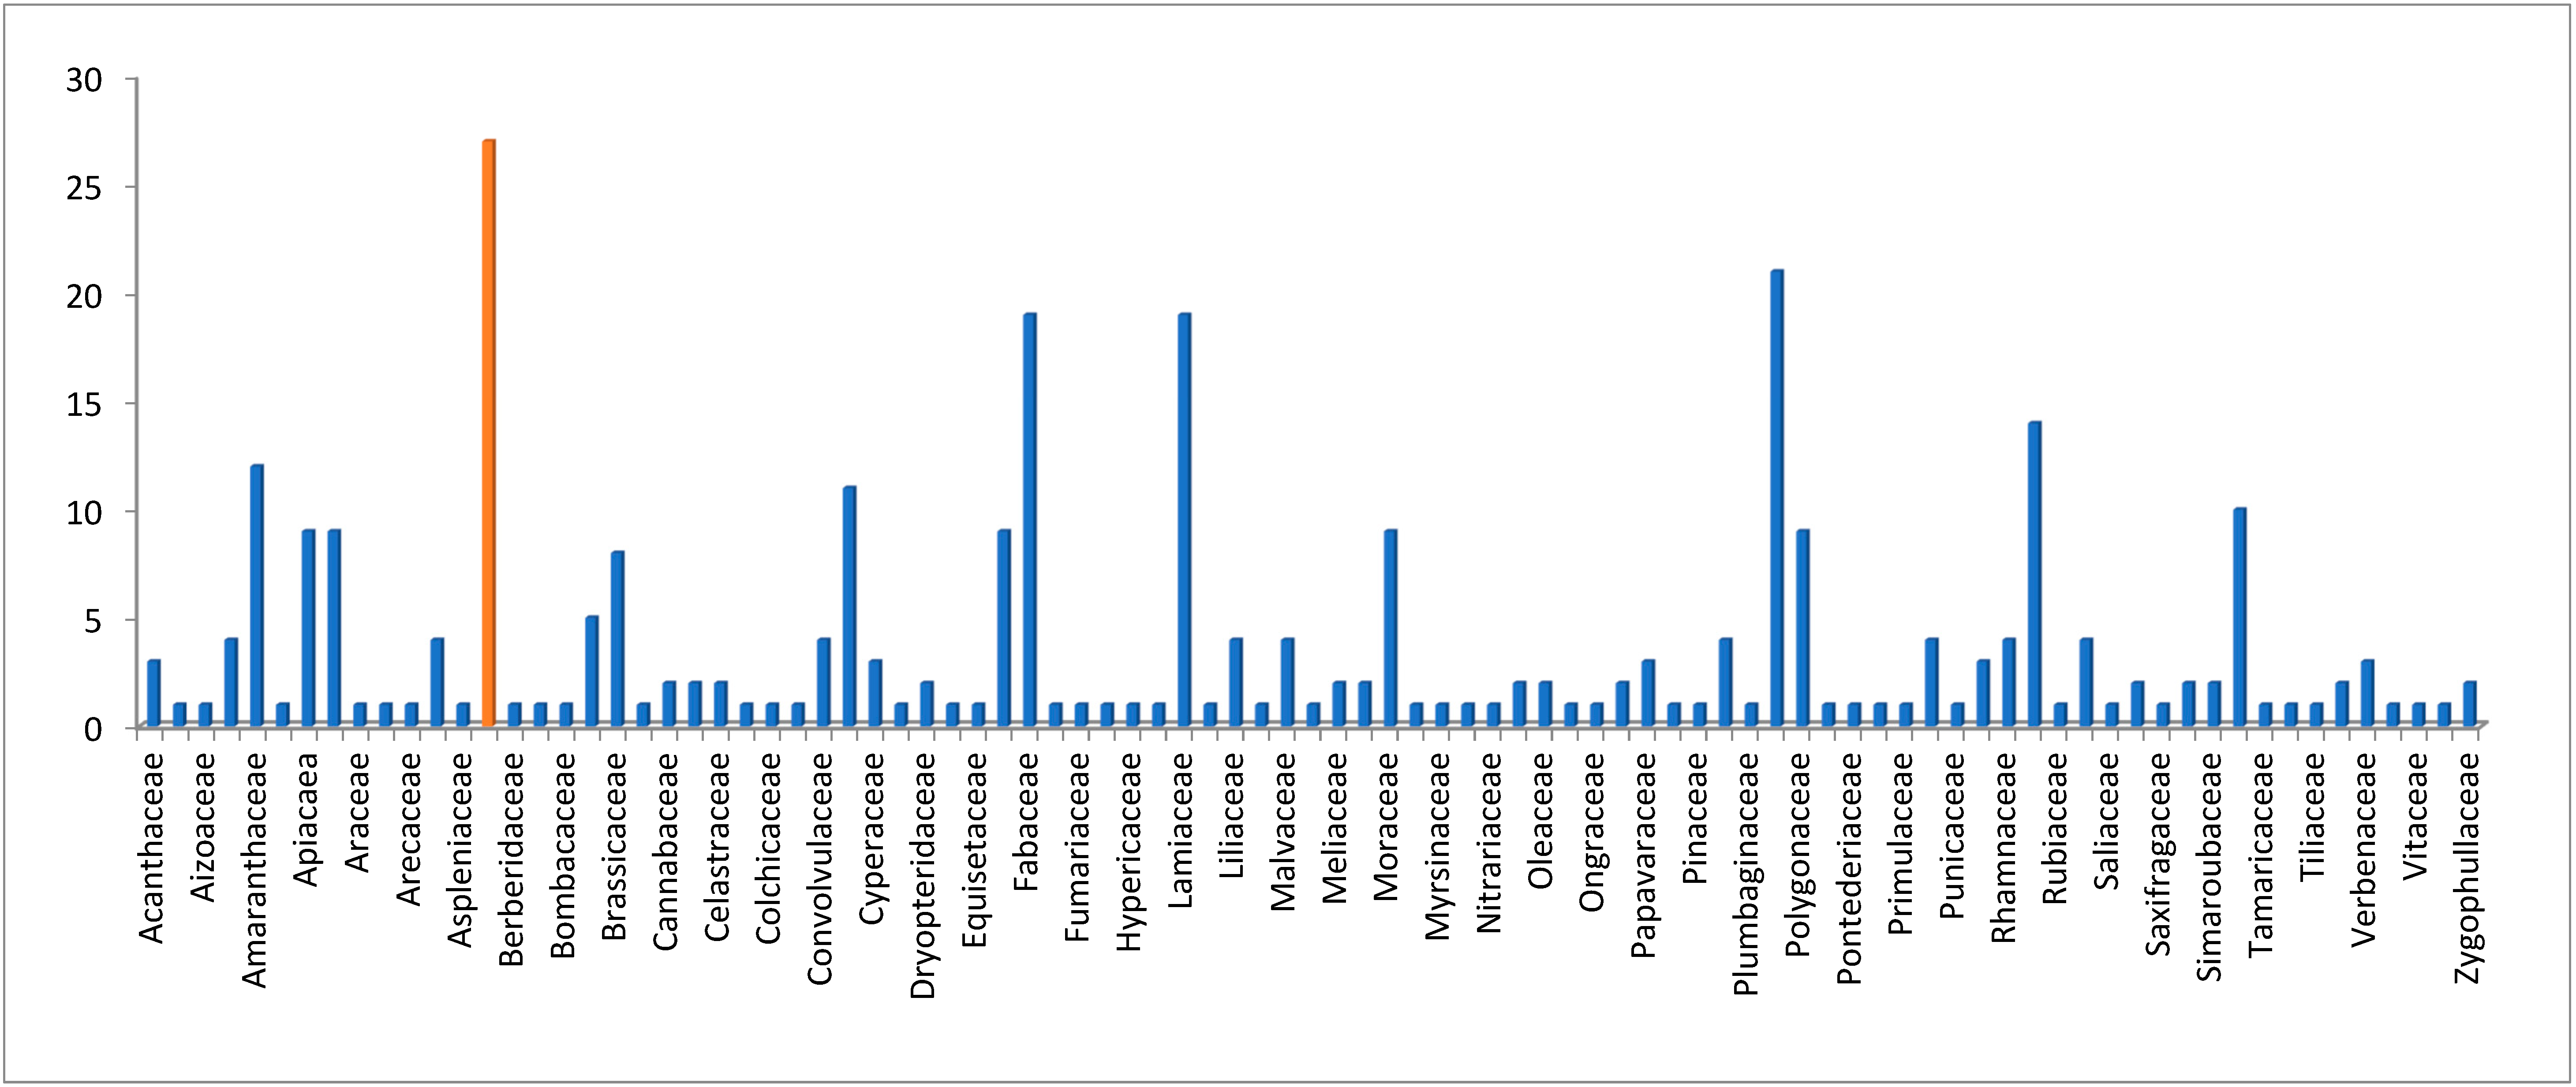
The collected medicinal plants belong to 91 families. The most dominant family in terms of species number was Asteraceae (27 species), followed by Poaceae (21 species), Fabaceae and Lamiaceae (19 species each), and Rosaceae (14 species) (Figure 2). The widespread distribution of these families in the study area may be a contributing factor to their dominance. Asteraceae is also the most prevalent family in Pakistan, according to the Flora of Pakistan. Additionally, the Asteraceae family is abundantly distributed across the study area [24]. In addition, the dominancy of the Asteraceae is reported from the surrounding areas in different studies [24,25,26,27]. Fabaceae as a dominant family was reported by other studies from surrounding areas [28]. The main reason for the therapeutic usage of Lamiaceae members in the study area is their vast distribution and the presence of monoterpenes in the form of volatile oils and other metabolically significant secondary metabolites [29]. The dominancy of the family Lamiaceae is also reported by other studies from the surrounding areas [7,30,31]. The dominance of the Rosaceae family may be attributed to suitable habitats, favorable environmental conditions for the growth of its species, and increased interactions of local communities with them. As a result, the traditional usage of these species is commonly known by the inhabitants [32].
Figure 2.
Families and number of species in each family.
The collected medicinal plants belong to different life forms. The most dominant life form was herbs (230 species), followed by trees (47 species), and shrubs (40 species) (Table 2). Herbs may have better adaptability to the climate and geography of the research area, which may be the cause of their domination. In addition, compared to shrubs or trees, herbs are more potent and grow rapidly [33]. Moreover, the availability of herbs is easy [34]. Additionally, herbs have different types of bioactive compounds which help them to adapt to any climatic condition easily [35]. Also, herbs have a higher concentration of various bioactive compounds than other life forms. Lastly, compared to shrubs and trees, herbs often have more medical efficacy [29]. High-altitude regions have a more herbaceous flora [34]. Furthermore, a similar result was reported in other studies from surrounding areas [7,25,29,32,34,35,36].
Table 2.
Medicinal plants of Tehsil Khadukhel and their local medicinal uses along with quantitative data.
3.3. Diversity of the Plants’ Parts and Formulation Methods
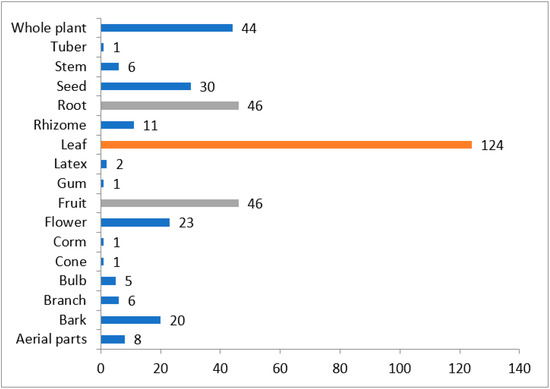
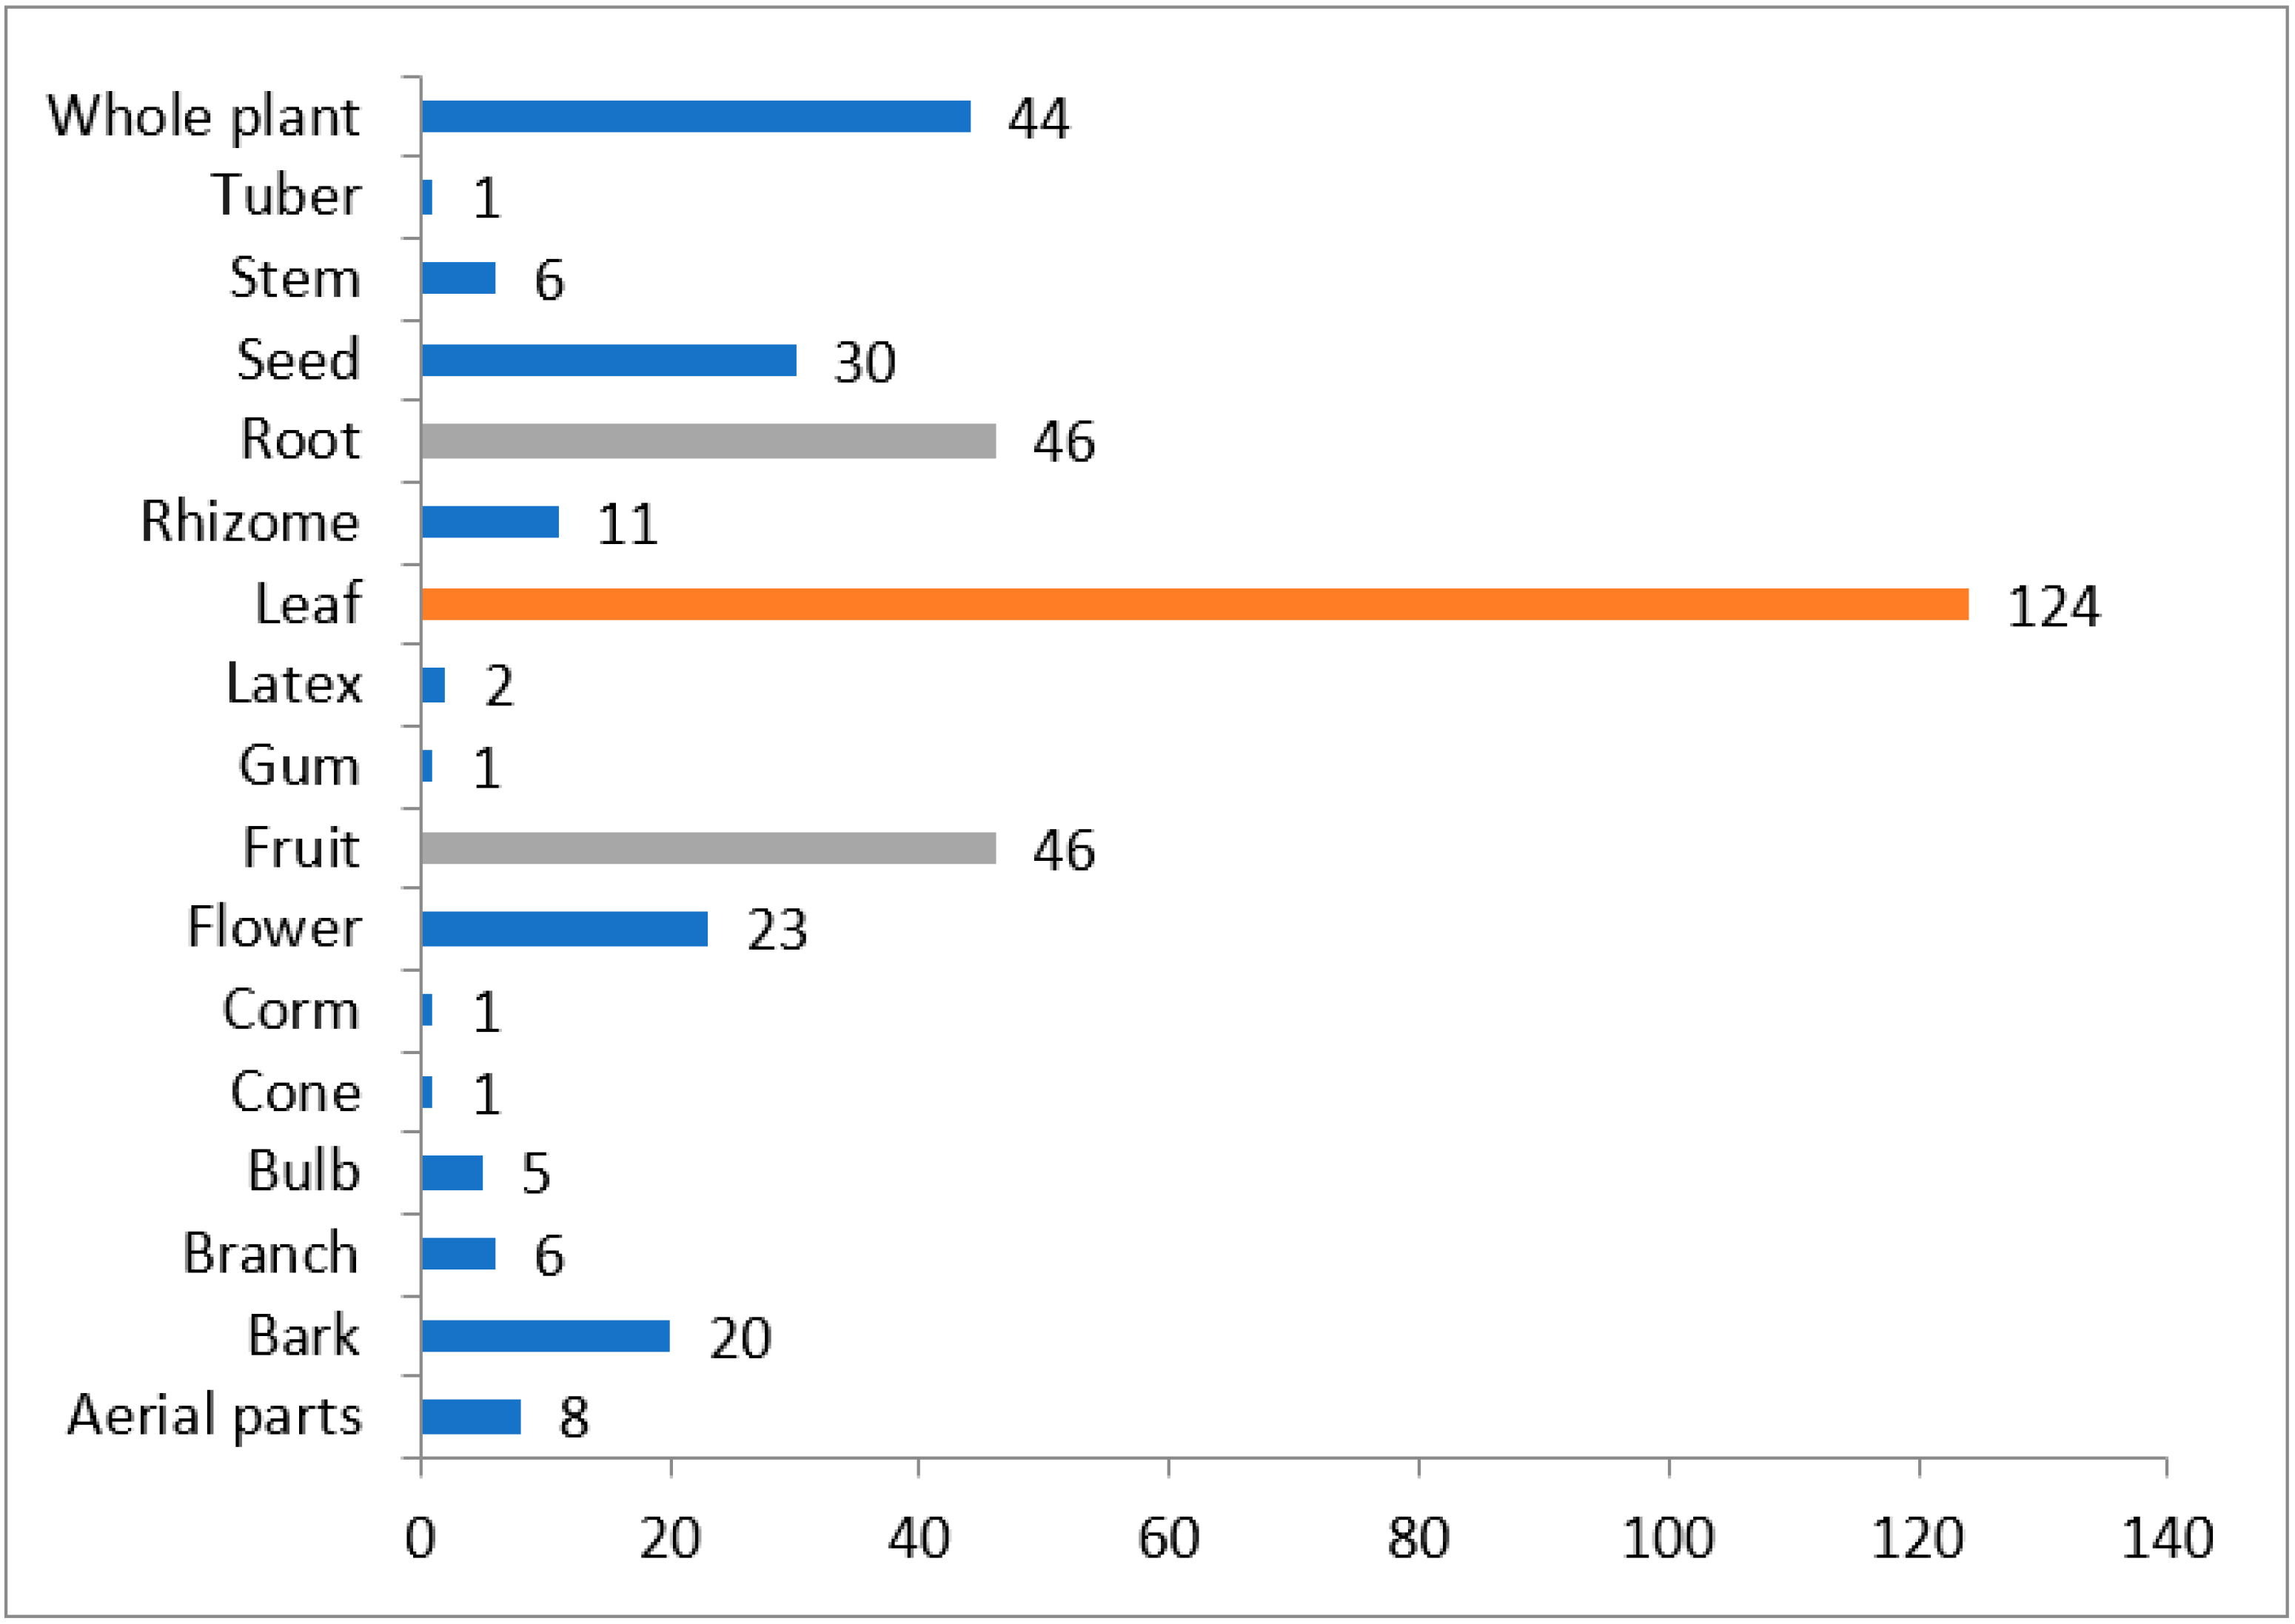
Different plant parts are used in herbal medicines to treat a variety of ailments. In this study, 17 vegetative and reproductive plant parts were documented to be used for therapeutic reasons. The most dominant plant part used was the leaf (124 sp.) followed by fruit and root (46 sp.), and the whole plant (44 sp.) (Figure 3). These results are in agreement with the studies from the surrounding areas [7,25,26,29,36,64,65]. Furthermore, as the plant’s leaves are its primary photosynthetic organ and contain a variety of metabolites in great numbers, they are often used in herbal medicines [7,29]. Moreover, leaves are the only part that is easy to collect and produced in large quantities [23]. Additionally, from a conservation point of view, the use of leaves is sustainable and with limited negative consequences for plants [7]. Root as a frequently used part in herbal recipes is also reported in other studies of the surrounding areas [34,66]. But from the conservation point of view, the use of roots in herbal recipes is not sustainable and safe for plants’ survival [33]. The use of whole plants more common in herbal medicine may be due to the ease of collection, availability, and presence of a large number of different chemical constituents [58]. The same results were also reported elsewhere [58,66]. The frequent use of fruit in herbal recipes is due to the presence of bioactive compounds in high proportion because in most plants, fruit serves as a storage organ [32]. A similar result to this study was also reported by others [67,68].
Figure 3.
Plants’ parts used in herbal medicines.
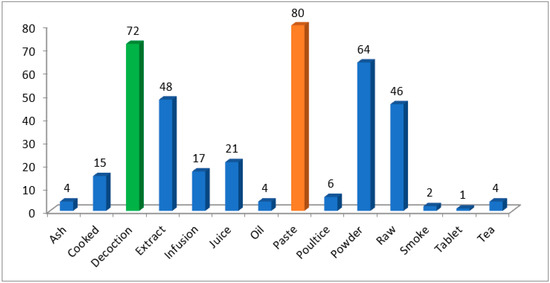
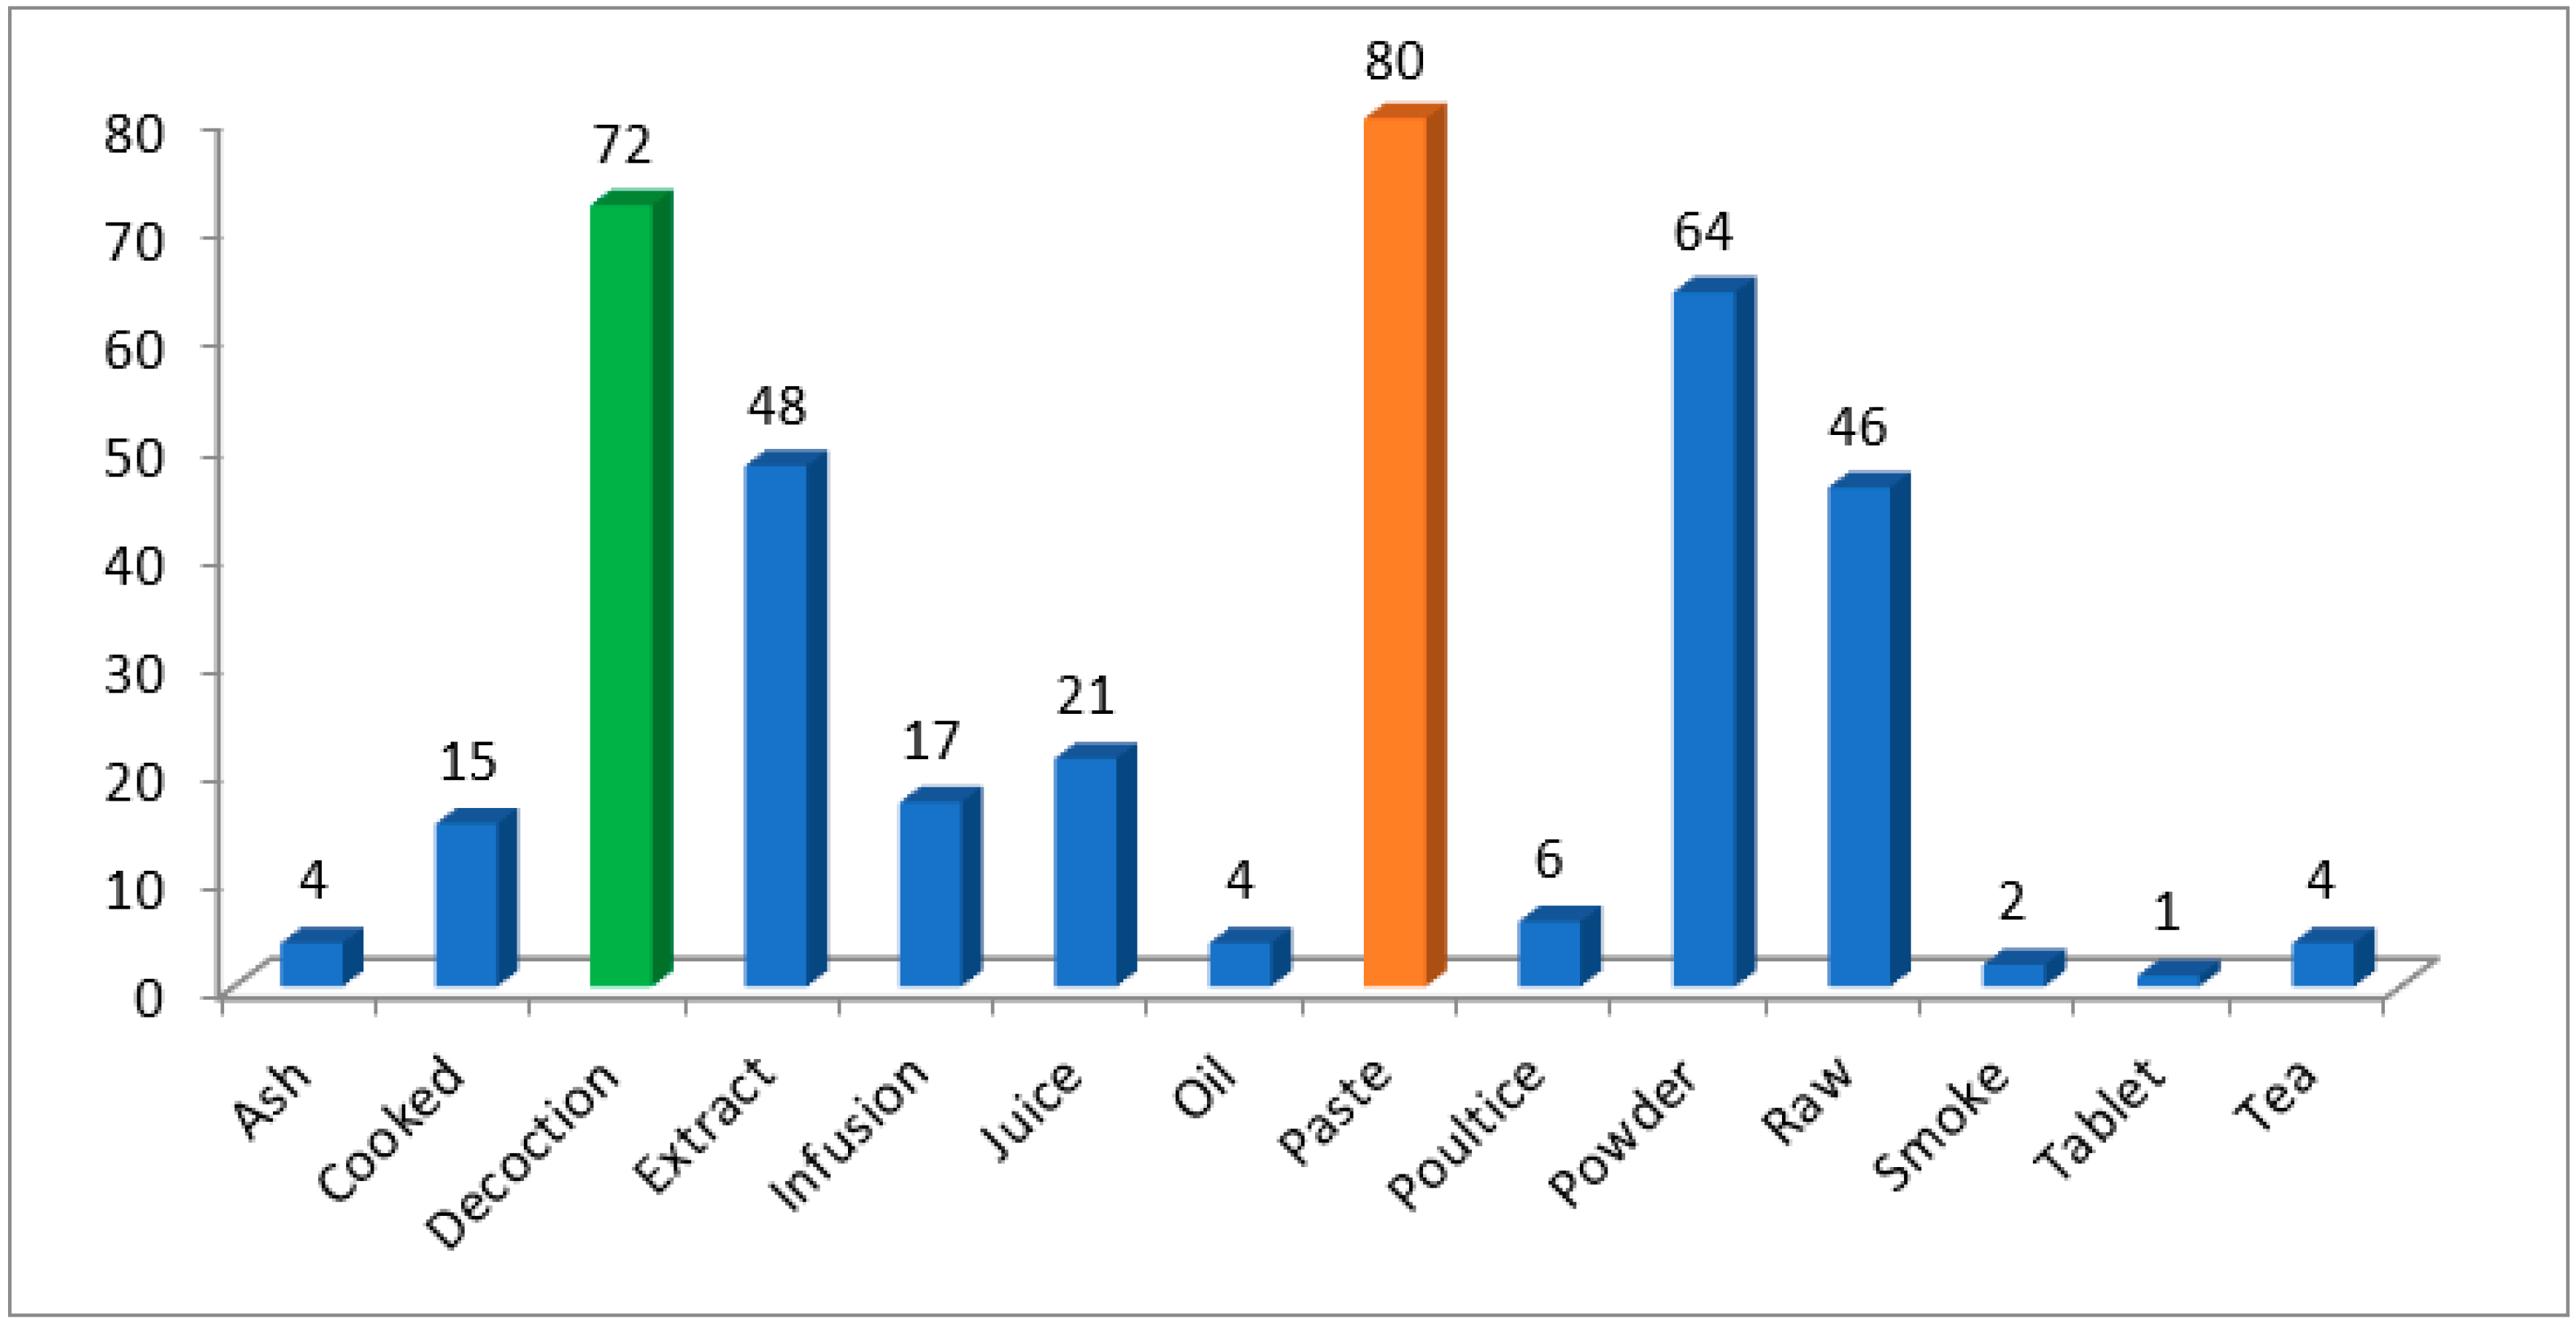
The preparation of medications involves a variety of formulation techniques. The documented formulation methods were classified into 14 groups. The most prominent herbal formulation method was paste (80 sp.) followed by decoction (72 sp.) and powder (64 sp.) (Figure 4). Paste was the dominant mode of administration of herbal medicine; a similar result was documented from the surrounding areas [58,62,68,69,70]. The study area is mountainous, and as a result, the locals experience more external wounds and injuries. Additionally, locals utilise pond water to wash their bodies and clothing since it contains germs that cause skin infections to treat these types of issues. Therefore, herbal paste medications were more popular among the local populace. For physical trauma and skin problems, the application of the paste is thought to be more effective [71]. Furthermore, the frequent use of paste may be due to its easy preparation [72]. The second most common method of administration was a powder; similar results were reported from the surrounding areas [33,73,74]. Decoction was the third most common medication preparation technique. A possible reason may be the simplicity of the preparation process [34]. Another reason is that boiling of the plant(s) in water leads to the extraction and availability of different compounds for the curing of diseases [75]. Also, similar findings were reported by others [7,8,23,38,72,76,77].
Figure 4.
Method of formulation of herbal medicines.
3.4. Informant Consensus Factor (ICF)
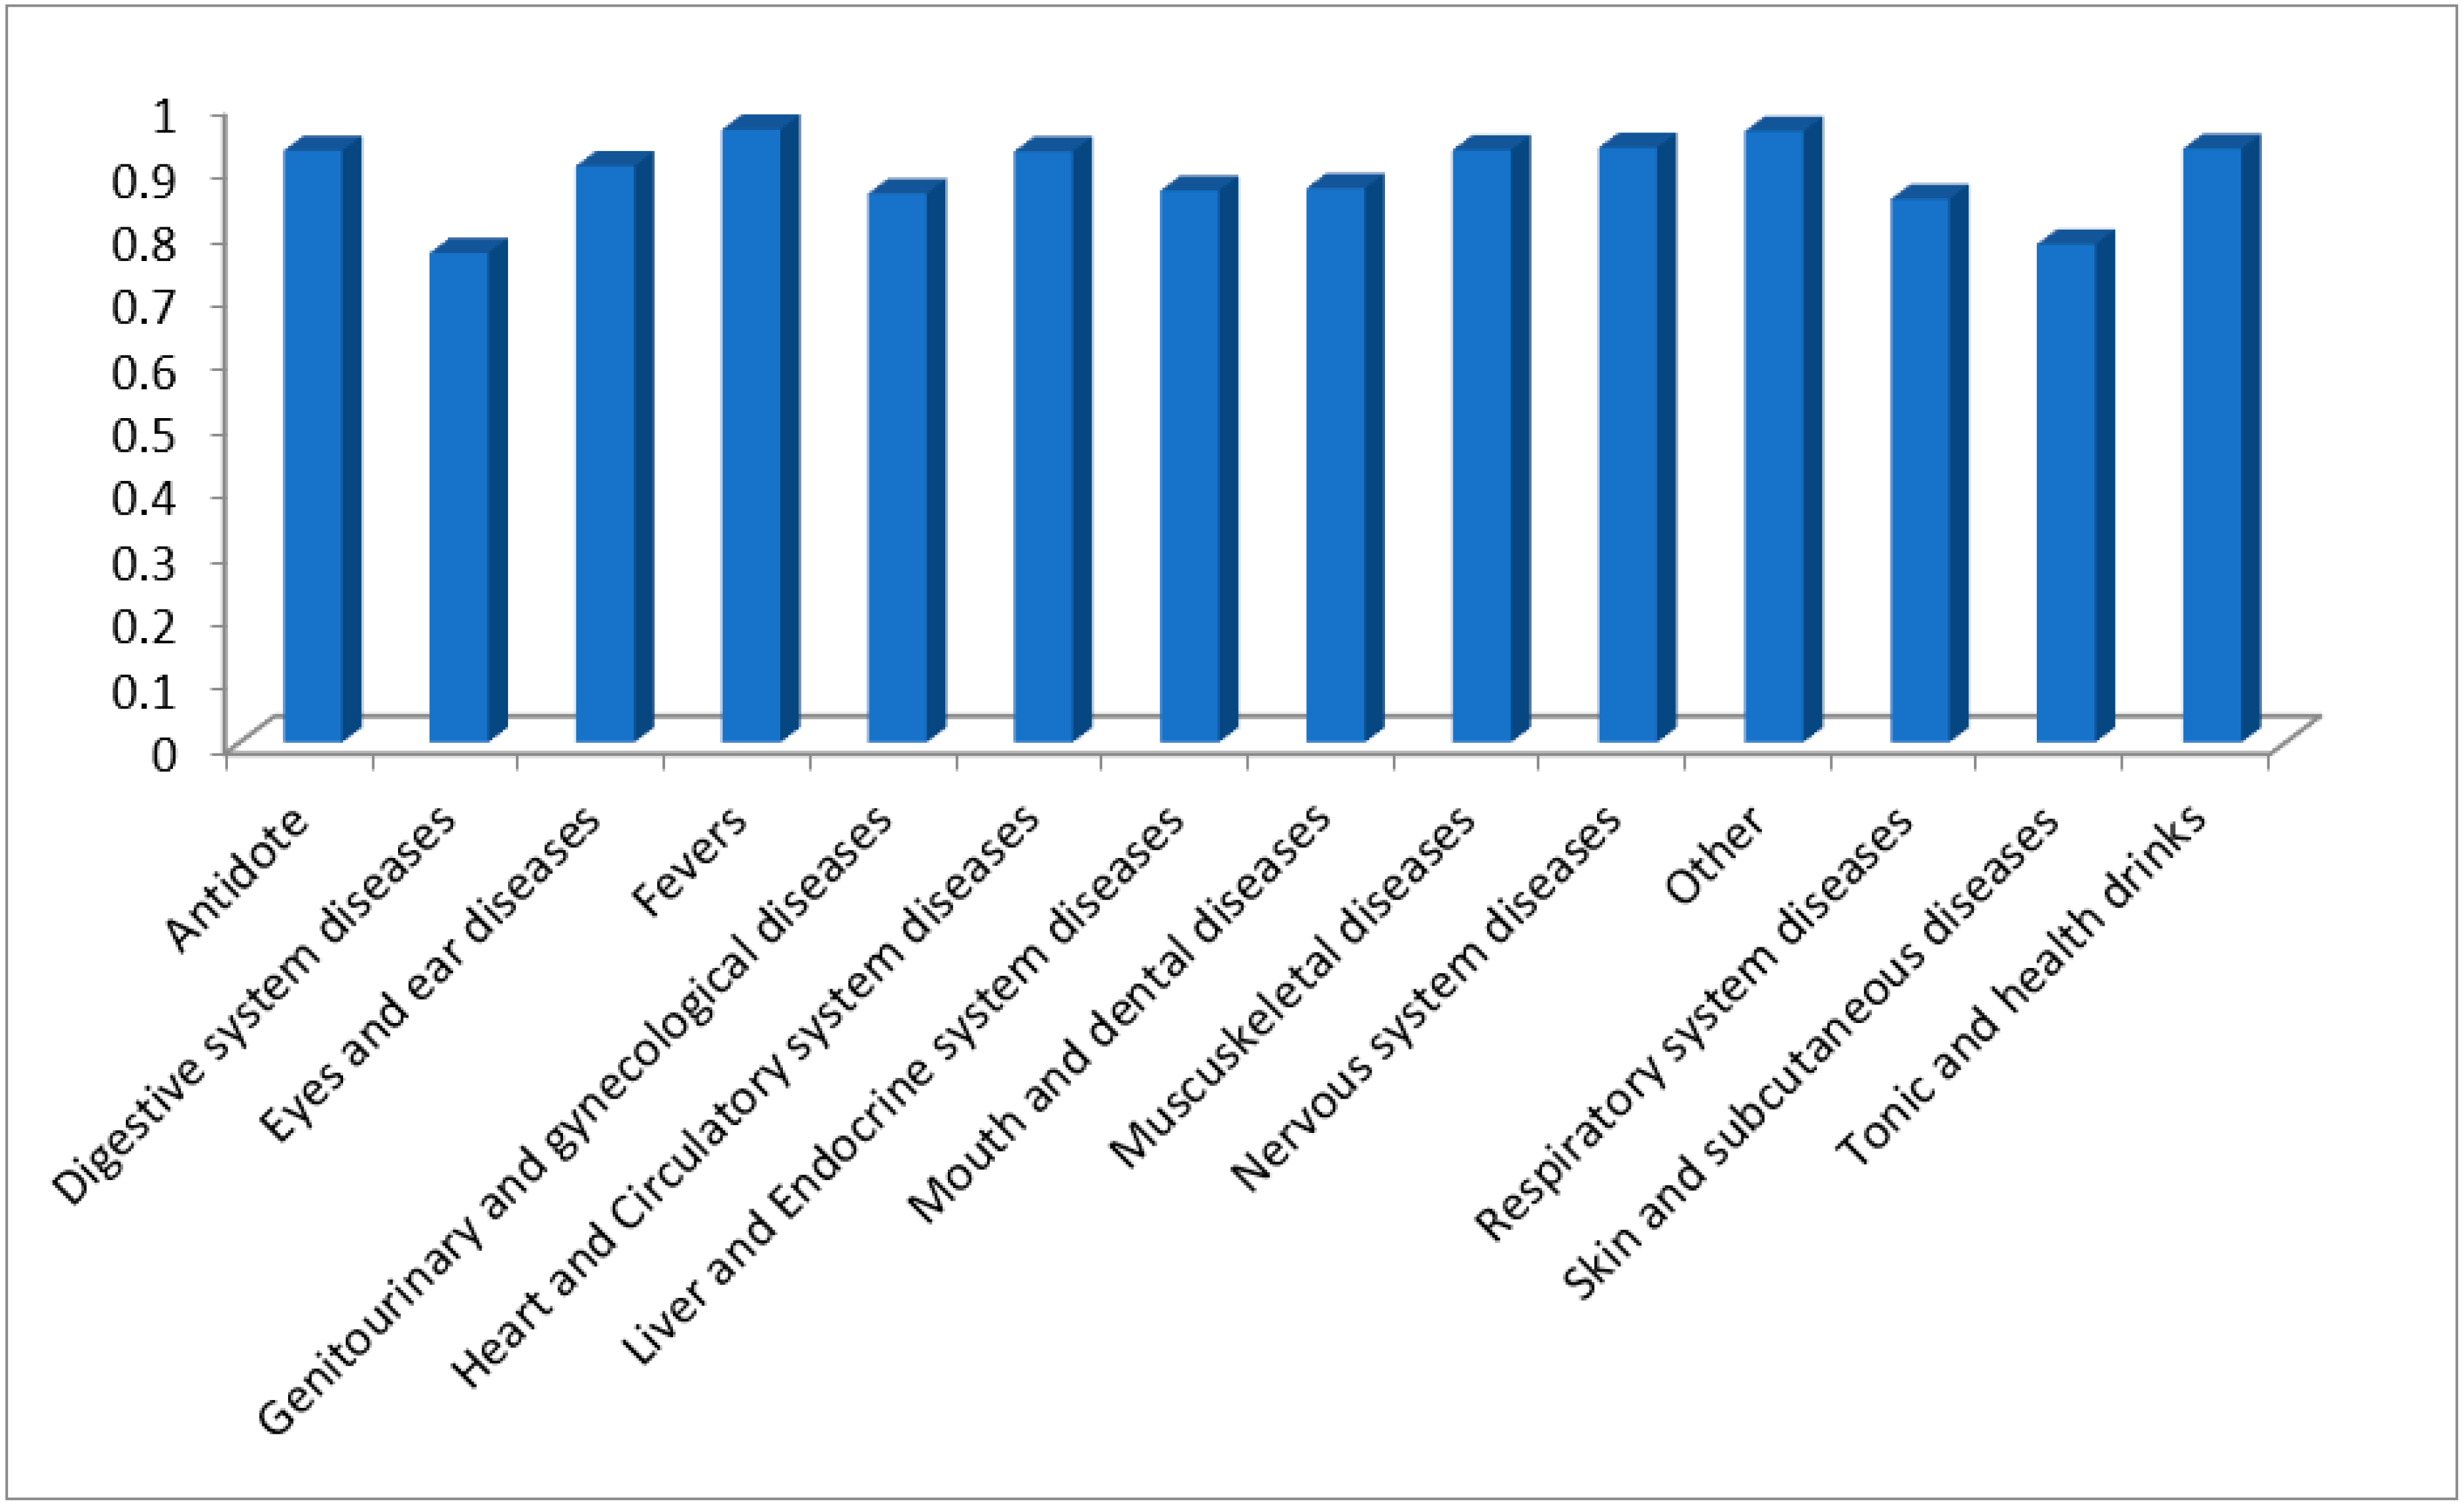
In this study, the highest value of ICF was obtained for fevers (0.96), and the lowest ICF was for digestive system diseases (0.76) (Table 3 and Figure 5). The low ICF value suggested that there is a lower degree of consensus about the usage of a certain medicinal plant to treat a particular illness category. Furthermore, the low value of ICF suggests that numerous plants have almost equally high potential for treating a variety of ailments. The low ICF value also means that alternative allopathic medications are easily accessible to the local populace. These alternative allopathic medicines may reduce the use of traditional medicines for that particular group of diseases [7,36,78]. Furthermore, an almost similar result was reported by others [7,8,20,74,79,80,81].
Table 3.
Disease categories and medicinal plants used for their treatment.
Figure 5.
ICF values of various disease groups.
3.5. Comparison of Medicinal Flora and Their Uses
The collected medicinal plants and their indigenous knowledge were compared with previously published work from the surrounding areas. The highest similarity was documented in the study carried out by Rahman et al. [41] and the lowest was documented in that conducted by Sher et al. [55] as listed in Table 4 and Figure 6. The local communities of the two compared areas share their traditional knowledge because they are close and in a similar geological zone, which means they have similar flora and also have similar socioeconomic and cultural characteristics. Meanwhile, the lowest similarity of the medicinal flora indicates that there is less similarity in the flora because the areas are distant and located in different geological zones, as a result of which, sharing of ethnic knowledge about medicinal plants is also limited. [29].
Table 4.
Floristic comparison of the present work with previously published work.
Figure 6.
Comparison of the present study with previously published work [4,7,8,9,20,23,26,30,37,38,39,40,41,42,43,44,45,46,47,48,49,50,51,52,53,54,55,56,57,58,59,60,61,63].
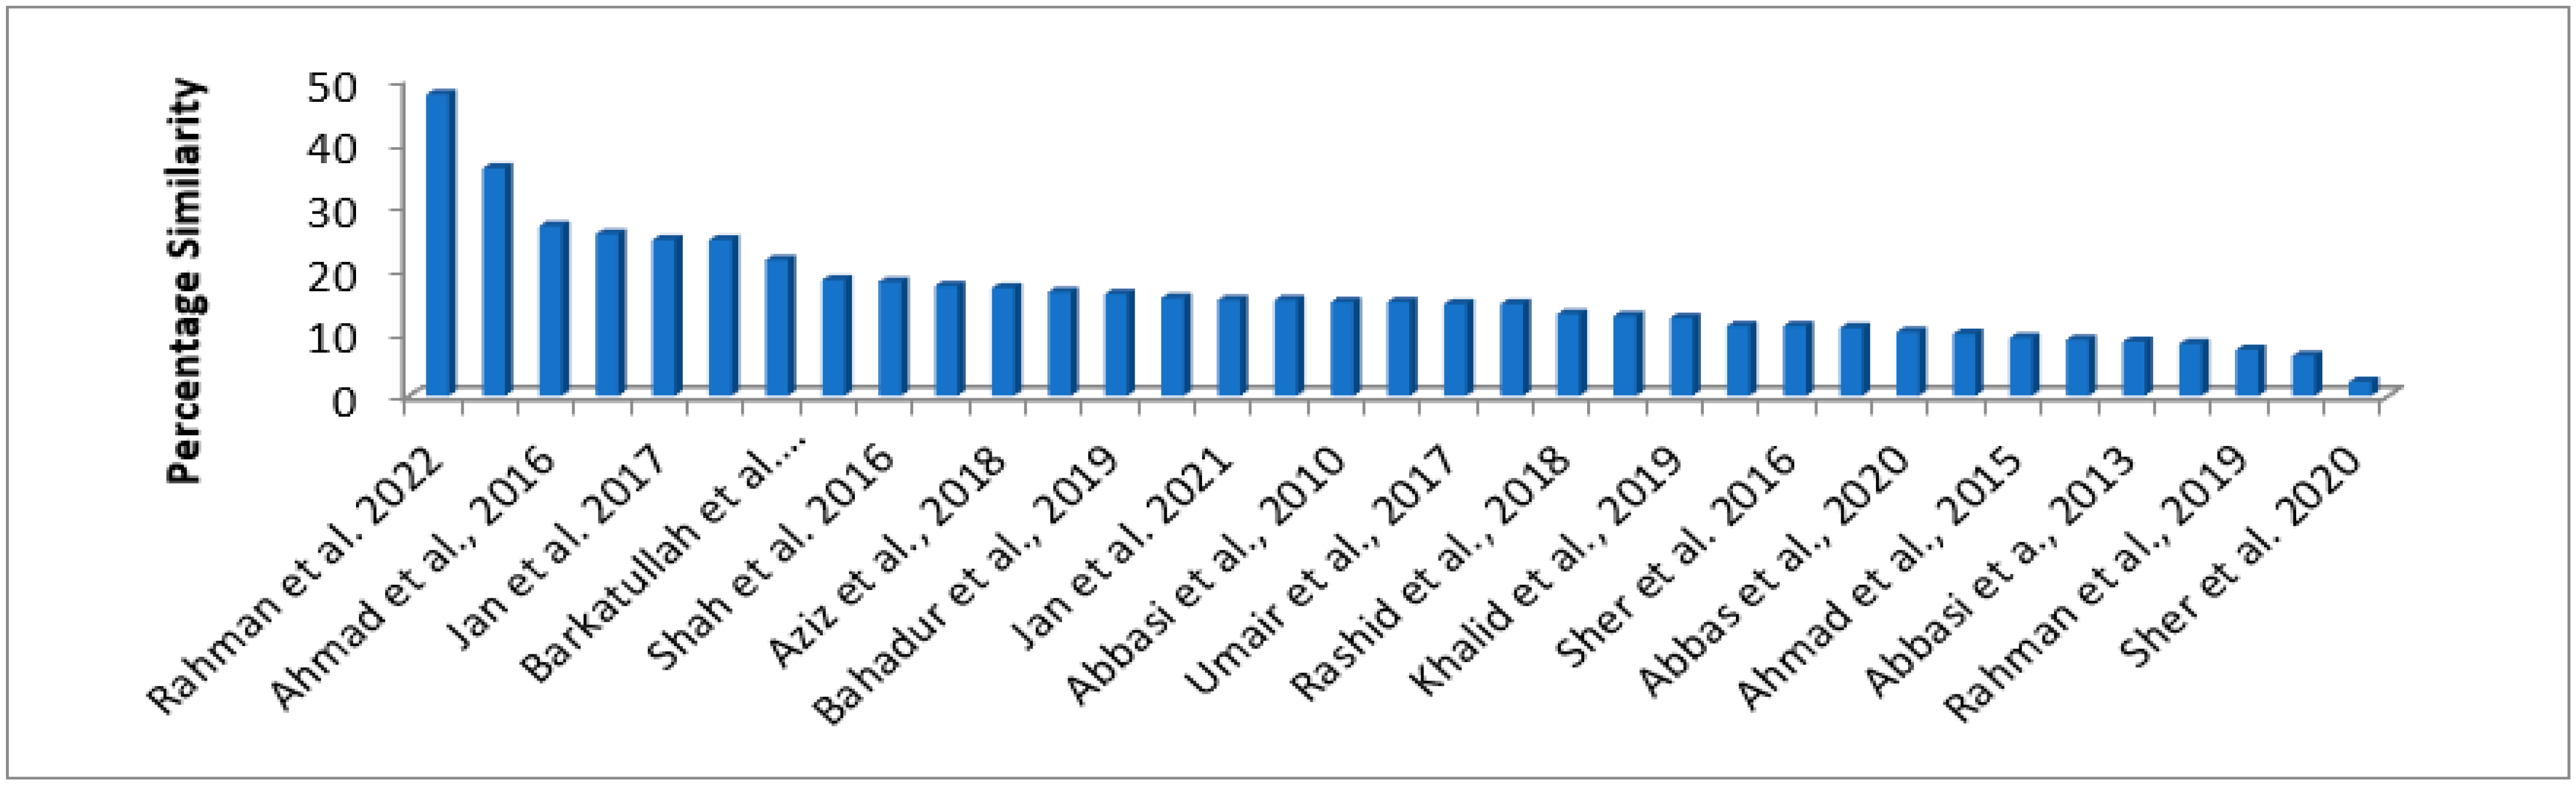
The study by Rahman et al. [41] in the Buner District reported that Justicia adhatoda L. is used locally for wounds, pus release, general body pain, as a cooling agent, fever, and TB treatment, whereas we observed that it is used for rheumatism. The study carried out by Shah et al. [39] in the Torghar District reported that the Basikhel tribe uses Artemisia scoparia Waldst. & Kitam. as a purgative anthelmintic and to treat malaria, but we have reported that it is used to treat vomiting. Jan et al. [7] reported in their study conducted in the Chinglay Valley of the Buner District that Allium jacquemontii Kunth is locally used to treat stomachache and hypertension, while our study reported that the plant is used for the treatment of hypertension and unequal mammary gland size. Furthermore, Sulaiman et al. [9] reported that Berberis lycium Royle is used by the local community for diabetes, wound healing, fractured bones, body pain, and diarrhoea, whereas we documented it is used to increase male potency, treat internal wounds, and cure antidiabetes and eye infection.
Calotropis procera (Aiton) Dryand was utilised locally as an antimalarial medicine [42], and we have reported that the plant is used to treat obesity. The study conducted by Hussain et al. [43] reported that Melia azedarach L. is used for treating scrofula, pimples, and rheumatism, and Ziziphus nummularia (Burm. f.) Wight & Arn. is used for blood purification, digestion, healing wounds, and ulcers, while in our study, we reported that Melia azedarach L. is used for the treatment of fever and Ziziphus nummularia (Burm. f.) Wight & Arn. is used to manage bleeding gums. Similarly, Barkatullah et al. [26] documented that Senegalia modesta (Acacia modesta Wall.) is used as a tonic, aphrodisiac, pain killer for backache, and wound healer, while we documented that it is used as a tonic after delivery. Likewise, Shah et al. [30] reported Achyranthes aspera L. is locally used for treating jaundice, while our study reported that it is used to cure piles, boils, toothache, and gum inflammation; other studies reported that Caralluma tuberculata N.E.Br. is used in antidiabetic, carminative, and analgesic applications, while we reported antidiabetic and carminative medicinal uses for it. Furthermore, Hassan et al. [58] reported Acorus calamus L. and Actaea spicata L. are locally used as antiasthmatics and Anagallis arvensis L. as an antiseptic, while we reported that these plants are used to treat dyspepsia and dysentery, rheumatic pain, and body pain in cattle, respectively.
Moreover, Jan et al. [41] documented that Butea monosperma (Lam.) Taub. is locally used to cure leucorrhea, Equisetum arvense L. is for treating gonorrhea, Ficus racemosa L. for the treatment of menorrhagia, and Momordica charantia L. is used to induce abortion, while we reported that these plants are used locally for the treatment of intestinal worms, stopping bleeding after childbirth, kidney stones, urinogenital problems, and for dysentery and as an antidiabetic, respectively. Furthermore, Bahadur et al. [59] reported that Taraxacum officinale (L.) Weber ex F. H. Wigg is locally used as a diuretic and tonic, Cannabis sativa L. is used to cure respiratory disorders, and Sonchus asper (L.) Hill is used to cure fever and constipation, while we reported that Taraxacum officinale (L.) Weber ex F. H. Wigg is used as a tonic, Cannabis sativa L. is used to stop bed urination at night in children and for wound healing, and Sonchus asper (L.) Hill is used to cure boils.
Aziz et al. [82] reported in their study that Cassia fistula L. is locally used to treat gastric problems and fever, and Celtis austtalis L. is used to cure skin problems, while we reported that Cassia fistula L. is used for snakebites, pneumonia, and fever, and Celtis austtalis L. is used in the study area for the treatment of herpes. Jan et al. [9] reported in their study that Acorus calamus L. is used by the local people for gum ache and toothache and Dalbergia sisso DC. is used to kill worms of the teeth, while we reported that Acorus calamus L. is used to cure dyspepsia and dysentery and Dalbergia sisso DC. is used for treating jaundice. Furthermore, Ijaz et al. [38] documented that Cyperus rotundus L. is used to treat respiratory infections, while in our area, we reported that it is used as a tonic. Similarly, we reported that Ficus sarmentosa Buch.-Ham. ex. Sm. is used as a tonic for blood, the same use that was reported by Ijaz et al. [38] too.
Hamayun et al. [4] reported that Adiantum venustum D. Don is used as an expectorant, emetic, and diuretic, while we reported that it is used to treat sore eyes; furthermore, they reported that Adiantum incisum Forssk. is used to cure skin diseases, fever, cough, and diabetes, and in our study, we reported that it is used to cure wounds. Abbasi et al. [44] reported that Bergenia ciliata (Haw.) Sternb. is used for wound healing and in our study, we reported that it is used for wound healing as well as for toothache; moreover, they reported that Calendula arvensis M.Bieb. is also used for wound healing and we documented in our study that it is used to treat cancer. Farooq et al. [37] reported that Hedera nepalensis K.Koch is used for treating diabetes, indigestion, and ulcer and we documented that it is used for the removal of leeches from the body of cattle. Furthermore, they reported that Ipomoea purpurea (L.) Rath is used as a diuretic, to treat mental disorders, and constipation and we have documented that it is used to treat bronchitis and diarrhea.
Umair et al. [60] reported that Chrozophora tinctoria (L.) A. Juss. is used to cure stomachache, sore throat, emetic, and cataracts and we reported that it is used for treating stomach acidity. Furthermore, they documented that Euphorbia helioscopia L. is used as an anthelmintic and to treat athlete’s foot, sore eyes, asthma, constipation, and cholera, and in our work, we reported that it is used for the treatment of skin problems and constipation. Similarly, they reported that Euphorbia prostrata Ait. is used to treat diarrhea and dysentery; used as a liver tonic; used for the treatment of ringworm, diabetes, and kidney stones; and used as a blood purifier, and we reported in our study that it is used for the treatment of asthma and ringworm.
Ali et al. [37] reported that the fruit of the Elaeagnus umbellate Thunb. is used as a cardiac simulator and we reported that it is used as a cooling agent and to cure cough; furthermore, they reported that Lamium album L. is used to treat liver disorders and we documented that it is used for the treatment of cough. Kayani et al. [45] reported that Actaea spicata L. is used to treat asthma and we reported that it is used for rheumatic pain; similarly, Bistorta amplexicaulis (D. Don) Greene is used for treating sore throat while we reported that it is used for treating wounds. Akhtar et al. [63] reported in their study that the plant is used to treat eczema and for blood purification and we reported that it is used to treat cephalalgia; furthermore, they reported that Peganum harmala L. is used as a diuretic while we reported in our study that it is used as antidiabetic medicine.
3.6. Novelty of the Study
The present study is the first ever of its kind conducted in the study area to conserve the ethnic knowledge of medicinal plants. In this study, a total of 317 medicinal plant species were documented for their medicinal uses. The result clearly shows that 50 plant species are new that were not previously reported from the study area or the surrounding areas. New medicinal uses for 272 medicinal plant species are also reported from the study area (Table 2).
4. Conclusions
The results of the current work clearly show that the study area has rich floristic and cultural diversity, due to which the local population has rich ethnomedicinal knowledge. Furthermore, most of the study area is mountainous and remote and lacks modern health facilities; therefore, local people rely on medicinal plants. The present study mainly highlights the important indigenous ethnomedicinal knowledge associated with the local medicinal flora. It was noted that the valuable indigenous ethnomedicinal knowledge of the study area is at risk of extinction because the younger generation does not take interest in it. Moreover, the local population transfers this valuable treasure of knowledge orally from generation to generation which is a major factor in the loss of this valuable knowledge. During the survey, a total of 317 medicinal plant species belonging to 91 families along with their indigenous ethnomedicinal knowledge were documented. Most of the knowledge was shared by the age group 50–59. Asteraceae was the leading family with 27 species. The conservation of traditional knowledge for future generations, its protection by placing the knowledge in the public domain, and its use as the starting point for further study and conservation initiatives are just a few of the many uses for which it was documented. We recommend that future research projects should be designed to develop awareness in the local community about the conservation of medicinal plants. Furthermore, phytochemical and pharmacological evaluation of these medicinal plants should be carried out for the exploration of new medicines.
Author Contributions
H.A.J. and H.M.A. designed the research work. H.A.J. collected the data. A.K.A., S.Z.U.A. and M.Z.B. contributed to the data analysis. A.K.A., H.A.J. and L.A. contributed to the write-up. Review and editing were done by H.A.J., H.M.A. and M.Z.B. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The original data are presented in the article.
Acknowledgments
All the authors are thankful to the local people for sharing their valuable ethnomedicinal data and facilitation during research work.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A. Data about Informant
Informant’s Name: Age:
Village Name: Education:
Occupation: Date:
Gender: Marital Status:
Data about medicinal plants
Local name: Botanical name/Family:
Part used: Used for disease(s):
Locality:
Complete method of preparation of Recipes/Medicine:
Amount/dosage of medicine:
Number of times per day of taking medicine:
Medicine taken before meal: Medicine taken after meal:
Side/poisonous effects of plant:
The uses of medicinal plants are increasing/deceasing/remains the same?
If deceasing then why?
What are the most recent diseases, your family members, suffered from?
What kind of treatment you get? Allopathic/ Herbal/ Religious/ Homeopathic
Have you got any herbal medicine, why?
What is the availability status of herbal medicine? Easily/Difficult
Affectivity of herbal medicine:
How many medicinal Plants you know?
How you got the knowledge about the use of medicinal plants?
Who collect Men/Women/Children/Herbalist/Others?
References
- Popović, Z.; Matic, R.; Bojović, S.; Stefanović, M.; Vidaković, V. Ethnobotany and herbal medicine in modern complementary and alternative medicine: An overview of publications in the field of I&C medicine 2001–2013. J. Ethnopharmacol. 2016, 181, 182–192. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gwalwanshi, D.R.; Salunkhe, O.; Shukla, A.; Bishwas, A.J.; Vyas, D. Indigenous Knowledge and Documentation of Eth-no-Medicinal Plants of Panna District, Central India: A Case Study. J. Ethnobiol. Trad. Med. Phot. 2014, 122, 868–876. [Google Scholar]
- Jan, H.A.; Jan, S.; Bussmann, R.W.; Wali, S.; Sisto, F.; Ahmad, L. Complementary and alternative medicine research, prospects and limitations in Pakistan: A literature review. Acta Ecol. Sin. 2019, 40, 451–463. [Google Scholar] [CrossRef] [Scilit]
- Khan, A. Policy-making in Pakistan’s population programme. Health Policy Plan. 1996, 11, 30–51. [Google Scholar] [CrossRef] [Scilit]
- Renckens, C. Alternative treatments in reproductive medicine: Much ado about nothing. The fact that millions of people do not master arithmetic does not prove that two times two is anything else than four: W.F. Hermans. Hum. Reprod. 2002, 17, 528–533. [Google Scholar] [CrossRef] [Scilit]
- Hamayun, M.; Khan, A.; Afzal, S.; Khan, M.A. Study on traditional knowledge and utility of medicinal herbs of district Buner, NWFP, Pakistan. IJTK 2006, 5, 407–412. [Google Scholar]
- Alam, N.; Shinwari, Z.K.; Ilyas, M.; Ullah, Z. Indigenous knowledge of medicinal plants of Chagharzai valley, District Buner, Pakistan. Pak. J. Bot. 2011, 43, 773–780. [Google Scholar]
- Sher, Z.; Khan, Z.; Hussain, F. Ethnobotanical studies of some plants of Chagharzai valley, district Buner, Pakistan. Pak. J. Bot. 2011, 43, 1445–1452. [Google Scholar]
- Jan, H.A.; Wali, S.; Ahmad, L.; Jan, S.; Ahmad, N.; Ullah, N. Ethnomedicinal survey of medicinal plants of Chinglai valley, Buner district, Pakistan. Eur. J. Integr. Med. 2017, 13, 64–74. [Google Scholar] [CrossRef] [Scilit]
- Rahman, S.U.; Ullah, Z.; Ali, A.; Aziz, M.A.; Alam, N.; Sher, H.; Ali, I. Traditional knowledge of medicinal flora among tribal communities of Buner Pakistan. Phytomed. Plus 2022, 2, 100277. [Google Scholar] [CrossRef] [Scilit]
- Jan, H.A.; Jan, S.; Bussmann, R.W.; Ahmad, L.; Wali, S.; Ahmad, N. Ethnomedicinal survey of the plants used for gynecological disorders by the indigenous community of district Buner, Pakistan. Ethnobot. Res. Appl. 2020, 19, 1–18. [Google Scholar] [CrossRef] [Scilit]
- Available online: https://kp.gov.pk/ (accessed on 30 July 2022).
- Forman, L.; Birdson, D. The Herbarium Hand Book; Royal Botanical Gardens, Kew: London, UK, 1989. [Google Scholar]
- Available online: www.tropicos.org/Project/Pakistan (accessed on 30 July 2022).
- Available online: http://www.ipni.org (accessed on 30 July 2022).
- Available online: http://www.theplantlist.org/ (accessed on 30 July 2022).
- Available online: http://mpns.kew.org/mpns-portal/ (accessed on 30 July 2022).
- Abidin, S.Z.U.; Khan, R.; Ahmad, M.; Jan, H.A.; Zafar, M.; Shah, A.H. A cross-cultural ethnobotanical knowledge comparison about local plants among Pashto, Punjabi and Saraiki communities living in Southwest Pakistan. Ethnobot. Res. Appl. 2022, 23, 1–16. [Google Scholar] [CrossRef] [Scilit]
- Ghorbani, A.; Langenberger, G.; Feng, L.; Sauerborn, J. Ethnobotanical study of medicinal plants utilised by Hani ethnicity in Naban River Watershed National Nature Reserve, Yunnan, China. J. Ethnopharmacol. 2011, 134, 651–667. [Google Scholar] [CrossRef] [Scilit]
- Heinrich, M.; Ankli, A.; Frei, B.; Weimann, C.; Sticher, O. Medicinal plants in Mexico: Healers’ consensus and cultural im-portance. Soci. Sci. Med. 1998, 47, 1859–1871. [Google Scholar] [CrossRef] [Scilit]
- Andrade-Cetto, A. Ethnobotanical study of the medicinal plants from Tlanchinol, Hidalgo, México. J. Ethnopharmacol. 2009, 122, 163–171. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mangestu, F.; Hager, H. Wild Edible Fruit Species Culture Domain, Informant Species Competence and Preference in Three Districts of Amhara Region, Ethiopia. Ethnobot. Res. Appl. 2008, 6, 487–502. [Google Scholar] [CrossRef] [Scilit]
- Sargin, S.A. Ethnobotanical survey of medicinal plants in Bozyazı district of Mersin, Turkey. J. Ethnopharmacol. 2015, 173, 105–126. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bhatia, H.; Sharma, Y.P.; Manhas, R.; Kumar, K. Ethnomedicinal plants used by the villagers of district Udhampur, J&K, India. J. Ethnopharmacol. 2014, 151, 1005–1018. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ahmad, L.; Semotiuk, A.; Zafar, M.; Ahmad, M.; Sultana, S.; Liu, Q.-R.; Zada, M.P.; Abidin, S.Z.U.; Yaseen, G. Ethnopharmacological documentation of medicinal plants used for hypertension among the local communities of DIR Lower, Pakistan. J. Ethnopharmacol. 2015, 175, 138–146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abbas, Z.; Khan, S.M.; Alam, J.; Khan, S.W.; Abbasi, A.M. Medicinal plants used by inhabitants of the Shigar Valley, Baltistan region of Karakorum range-Pakistan. J. Ethnobiol. Ethnomed. 2017, 13, 53. [Google Scholar] [CrossRef] [Scilit]
- Bano, A.; Ahmad, M.; Ben Hadda, T.; Saboor, A.; Sultana, S.; Zafar, M.; Khan, M.P.Z.; Arshad, M.; Ashraf, M.A. Quantitative ethnomedicinal study of plants used in the skardu valley at high altitude of Karakoram-Himalayan range, Pakistan. J. Ethnobiol. Ethnomed. 2014, 10, 43. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barkatullah; Ibrar, M.; Rauf, A.; Ben Hadda, T.; Mubarak, M.S.; Patel, S. Quantitative ethnobotanical survey of medicinal flora thriving in Malakand Pass Hills, Khyber Pakhtunkhwa, Pakistan. J. Ethnopharmacol. 2015, 169, 335–346. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Haq, S.M.; Hassan, M.; Jan, H.A.; Al-Ghamdi, A.A.; Ahmad, K.; Abbasi, A.M. Traditions for Future Cross-National Food Security—Food and Foraging Practices among Different Native Communities in the Western Himalayas. Biology 2022, 11, 455. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ahmad, M.; Qureshi, R.; Arshad, M.; Khan, M.A.; Zafar, M. Traditional herbal remedies used for the treatment of diabetes from district Attock (Pakistan). Pak. J. Bot. 2009, 41, 2777–2782. [Google Scholar]
- Ullah, N.; Siraj-Ud-Din, S.; Bussmann, R.W.; Jan, H.A.; Wali, S. A step towards the documentation of indigenous knowledge about the medicinal plants in mollagori: A tribal war affected area of Fata, Pakistan. Pak. J. Bot. 2021, 53, 1779–1789. [Google Scholar] [CrossRef] [Scilit]
- Shah, S.A.; Shah, N.A.; Ullah, S.; Alam, M.M.; Badshah, H.; Ullah, S.; Mumtaz, A.S. Documenting the indigenous knowledge on medicinal flora from communities residing near Swat River (Suvastu) and in high mountainous areas in Swat-Pakistan. J. Ethnopharmacol. 2016, 182, 67–79. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Haq, S.M.; Singh, B. Ethnobotany as a Science of Preserving Traditional Knowledge: Traditional Uses of Wild Medicinal Plants from District Reasi, J&K (Northwestern Himalaya), India. In Botanical Leads for Drug Discovery; Springer: Singapore, 2020; pp. 277–293. [Google Scholar] [CrossRef]
- Malik, K.; Ahmad, M.; Zafar, M.; Sultana, S.; Tariq, A.; Rashid, N. Medicinal plants used for treatment of prevalent diseases in Northern Pakistan of Western Himalayas. In Medicinal Plants-Use in Prevention and Treatment of Diseases; IntechOpen: London, UK, 2019. [Google Scholar] [CrossRef] [Scilit]
- Shah, A.; Rahim, S. Ethnomedicinal uses of plants for the treatment of malaria in Soon Valley, Khushab, Pakistan. J. Ethnopharmacol. 2017, 200, 84–106. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zahoor, M.; Yousaf, Z.; Aqsa, T.; Haroon, M.; Saleh, N.; Aftab, A.; Javed, S.; Qadeer, M.; Ramazan, H. An ethnopharmacological evaluation of Navapind and Shahpur Virkanin district Sheikupura, Pakistan for their herbal medicines. J. Ethnobiol. Ethnomed. 2017, 13, 27. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Farooq, A.; Amjad, M.S.; Ahmad, K.; Altaf, M.; Umair, M.; Abbasi, A.M. Ethnomedicinal knowledge of the rural communities of Dhirkot, Azad Jammu and Kashmir, Pakistan. J. Ethnobiol. Ethnomed. 2019, 15, 45. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rashid, S.; Ahmad, M.; Zafar, M.; Sultana, S.; Ayub, M.; Khan, M.A.; Yaseen, G. Ethnobotanical survey of medicinally important shrubs and trees of Himalayan region of Azad Jammu and Kashmir, Pakistan. J. Ethnopharmacol. 2015, 166, 340–351. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Awan, A.A.; Akhtar, T.; Ahmed, M.J.; Murtaza, G. Quantitative ethnobotany of medicinal plants uses in the Jhelum valley, Azad Kashmir, Pakistan. Acta Ecol. Sin. 2020, 41, 88–96. [Google Scholar] [CrossRef] [Scilit]
- Sulaiman; Shah, S.; Khan, S.; Bussmann, R.W.; Ali, M.; Hussain, D.; Hussain, W. Quantitative Ethnobotanical Study of Indigenous Knowledge on Medicinal Plants Used by the Tribal Communities of Gokand Valley, District Buner, Khyber Pakhtunkhwa, Pakistan. Plants 2020, 9, 1001. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jan, H.A.; Ahmad, L.; Bussmann, R.W.; Jan, S.; Wali, S.; Haq, S.M.; Alam, I.; Romman, M. Medicinal plants used for veterinary diseases by the local inhabitants of the Teshil Tangi, District Charsadda, Pakistan. Indian J. Tradit. Knowl. 2021, 20, 990–1001. [Google Scholar] [CrossRef] [Scilit]
- Sher, H.; Inamuddin, I.; Khan, Z.; Bussmann, R.W.; Ur-Rahman, I. Medicinal plant diversity of Hindubaig Mountain, Lalku Valley, District Swat, Pakistan. Ethnobot. Res. Appl. 2020, 20, 1–13. [Google Scholar] [CrossRef] [Scilit]
- Shah, A.H.; Khan, S.M.; Shah, A.H.; Mehmood, A.; Rahman, I.U.; Ahmad, H. Cultural uses of plants among Basikhel tribe of district Tor Ghar, Khyber Pakhtunkhwa, Pakistan. Pak. J. Bot. 2015, 47, 23–41. [Google Scholar]
- Bahadur, S.; Khan, M.S.; Shah, M.; Shuaib, M.; Ahmad, M.; Zafar, M.; Begum, N.; Gul, S.; Ashfaq, S.; Mujahid, I.; et al. Traditional usage of medicinal plants among the local communities of Peshawar valley, Pakistan. Acta Ecol. Sin. 2018, 40, 1–29. [Google Scholar] [CrossRef] [Scilit]
- Umair, M.; Altaf, M.; Abbasi, A.M. An ethnobotanical survey of indigenous medicinal plants in Hafizabad district, Punjab-Pakistan. PLoS ONE 2017, 12, e0177912. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Akhtar, N.; Begum, S. Ethnopharmacological important plants of Jalala, district Mardan, Pakistan. Pak. J. Pl. Sci. 2009, 15, 95–100. [Google Scholar]
- Bibi, F.; Abbas, Z.; Harun, N.; Perveen, B.; Bussmann, R.W. Indigenous knowledge and quantitative ethnobotany of the Tanawal area, Lesser Western Himalayas, Pakistan. PLoS ONE 2022, 17, e0263604. [Google Scholar] [CrossRef] [Scilit]
- Shuaib, M.; Ahmed, S.; Ali, K.; Ilyas, M.; Hussain, F.; Urooj, Z.; Shah, S.S.; Kumar, T.; Shah, M.; Khan, I.; et al. Ethnobotanical and ecological assessment of plant resources at District Dir, Tehsil Timergara, Khyber Pakhtunkhwa, Pakistan. Acta Ecol. Sin. 2018, 39, 109–115. [Google Scholar] [CrossRef] [Scilit]
- Rahman, I.U.; Afzal, A.; Iqbal, Z.; Hart, R.; Abd Allah, E.F.; Hashem, A.; Alsayed, M.F.; Ijaz, F.; Ali, N.; Shah, M.; et al. Herbal Teas and Drinks: Folk Medicine of the Manoor Valley, Lesser Himalaya, Pakistan. Plants 2019, 8, 581. [Google Scholar] [CrossRef] [Scilit]
- Wali, S.; Jan, H.A.; Haq, S.M.; Yaqoob, U.; Bussmann, R.W.; Rahim, F. The Traditional phyto-recipes used to cure various ailments by the local people of Shishi Koh valley, Chitral, Pakistan. ERA 2021, 22. [Google Scholar] [CrossRef]
- Rashid, N.; Gbedomon, R.C.; Ahmad, M.; Salako, V.K.; Zafar, M.; Malik, K. Traditional knowledge on herbal drinks among indigenous communities in Azad Jammu and Kashmir, Pakistan. J. Ethnobiol. Ethnomed. 2018, 14, 16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hussain, M.; Khalid, F.; Noreen, U.; Bano, A.; Alam, S.; Shah, S.; Sabir, M.; Habiba, U. An ethno-botanical study of indigenous medicinal plants and their usage in rural valleys of Swabi and Hazara region of Pakistan. Braz. J. Biol. 2022, 82, e243811. [Google Scholar] [CrossRef] [Scilit]
- Khan, S.M.; Page, S.; Ahmad, H.; Shaheen, H.; Ullah, Z.; Ahmad, M.; Harper, D.M. Medicinal flora and ethnoecological knowledge in the Naran Valley, Western Himalaya, Pakistan. J. Ethnobiol. Ethnomed. 2013, 9, 4. [Google Scholar] [CrossRef] [Scilit]
- Sher, H.; Bussmann, R.W.; Hart, R.; de Boer, H.J. Traditional use of medicinal plants among Kalasha, Ismaeli and Sunni groups in Chitral District, Khyber Pakhtunkhwa province, Pakistan. J. Ethnopharmacol. 2016, 188, 57–69. [Google Scholar] [CrossRef] [Scilit]
- Ullah, S.; Muhammad, N. Evaluation of Informant Consensus Factor of Medicinal Plants Used in Shamozai Valley SWAT, KPK, Pakistan. Int. J. Med. Plants Nat. Prod. 2018, 4, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Kayani, S.; Ahmad, M.; Zafar, M.; Sultana, S.; Khan, M.P.Z.; Ashraf, M.A.; Hussain, J.; Yaseen, G. Ethnobotanical uses of medicinal plants for respiratory disorders among the inhabitants of Gallies—Abbottabad, Northern Pakistan. J. Ethnopharmacol. 2014, 156, 47–60. [Google Scholar] [CrossRef] [Scilit]
- Shinwari, S.; Ahmad, M.; Luo, Y.; Zaman, W. Quantitative analyses of medicinal plants consumption among the inhabitants of shangla-kohistan areas in Northern-Pakistan. Pak. J. Bot. 2017, 49, 725–734. [Google Scholar]
- Adnan, M.; Ullah, I.; Tariq, A.; Murad, W.; Azizullah, A.; Khan, A.L.; Ali, N. Ethnomedicine use in the war affected region of northwest Pakistan. J. Ethnobiol. Ethnomed. 2014, 10, 16. [Google Scholar] [CrossRef] [Scilit]
- Ahmad, M.; Khan, M.P.Z.; Mukhtar, A.; Zafar, M.; Sultana, S.; Jahan, S. Ethnopharmacological survey on medicinal plants used in herbal drinks among the traditional communities of Pakistan. J. Ethnopharmacol. 2016, 184, 154–186. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abbasi, A.M.; Khan, M.; Ahmad, M.; Zafar, M.; Jahan, S.; Sultana, S. Ethnopharmacological application of medicinal plants to cure skin diseases and in folk cosmetics among the tribal communities of North-West Frontier Province, Pakistan. J. Ethnopharmacol. 2010, 128, 322–335. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abbasi, A.M.; Khan, M.A.; Shah, M.H.; Shah, M.M.; Pervez, A.; Ahmad, M. Ethnobotanical appraisal and cultural values of medicinally important wild edible vegetables of Lesser Himalayas-Pakistan. J. Ethnobiol. Ethnomed. 2013, 9, 66. [Google Scholar] [CrossRef] [Scilit]
- Srithi, K.; Balslev, H.; Wangpakapattanawong, P.; Srisanga, P.; Trisonthi, C. Medicinal plant knowledge and its erosion among the Mien (Yao) in northern Thailand. J. Ethnopharmacol. 2009, 123, 335–342. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ali, S.; Perveen, A.; Qaiser, M. Vegetation structure, edaphalogy and ethnobotany of Mahaban and Malka (District Buner) KPK, Pakistan. Pak. J. Bot. 2015, 47, 15–22. [Google Scholar]
- Amjad, M.S.; Qaeem, M.F.; Ahmad, I.; Khan, S.U.; Chaudhari, S.K.; Malik, N.Z.; Shaheen, H.; Khan, A.M. Descriptive study of plant resources in the context of the ethnomedicinal relevance of indigenous flora: A case study from Toli Peer National Park, Azad Jammu and Kashmir, Pakistan. PLoS ONE 2017, 12, e0171896. [Google Scholar] [CrossRef] [Scilit]
- Wali, A.; Jan, H.A.; Bussmann, R.W. Quantitative ethnomedicinal study of indigenous medicinal plants used for digestive disorders of Laspur Valley, Chitral, Northern Pakistan. Ethnobot. Res. Appl. 2019, 18, 1–18. [Google Scholar] [CrossRef] [Scilit]
- Ishtiaq, M.; Mahmood, A.; Maqbool, M. Indigenous knowledge of medicinal plants from Sudhanoti district (AJK), Pakistan. J. Ethnopharmacol. 2015, 168, 201–207. [Google Scholar] [CrossRef] [Scilit]
- Hassan, N.; Din, M.U.; Hassan, F.U.; Abdullah, I.; Zhu, Y.; Jinlong, W.; Nisar, M.; Iqbal, I.; Wadood, S.F.; Iqbal, S.S.; et al. Identification and quantitative analyses of medicinal plants in Shahgram valley, district swat, Pakistan. Acta Ecol. Sin. 2019, 40, 44–51. [Google Scholar] [CrossRef] [Scilit]
- Hamayun, M.; Khan, A.; Khan, M.A. Common medicinal folk recipes of District Buner, NWFP, Pakistan. Ethnobot. Leaf. 2003, 2005, 45. [Google Scholar]
- Shah, A.; Sarvat, R.; Shoaib, S.; Ayodele, A.E.; Nadeem, M.; Qureshi, T.M.; Abbas, A. An ethnobotanical survey of medicinal plants used for the treatment of snakebite and scorpion sting among the people of Namal valley, Mianwali district, Punjab, Pakistan. Appl. Ecol. Environ. Res. 2018, 16, 111–143. [Google Scholar] [CrossRef]
- Ayyanar, M.; Ignacimuthu, S. Ethnobotanical survey of medicinal plants commonly used by Kani tribals in Tirunelveli hills of Western Ghats, India. J. Ethnopharmacol. 2011, 134, 851–864. [Google Scholar] [CrossRef] [Scilit]
- Akhtar, N.; Rashid, A.; Murad, W.; Bergmeier, E. Diversity and use of ethno-medicinal plants in the region of Swat, North Pakistan. J. Ethnobiol. Ethnomed. 2013, 9, 25. [Google Scholar] [CrossRef] [Scilit]
- Butt, M.A.; Ahmad, M.; Fatima, A.; Sultana, S.; Zafar, M.; Yaseen, G.; Ashraf, M.A.; Shinwari, Z.K.; Kayani, S. Ethnomedicinal uses of plants for the treatment of snake and scorpion bite in Northern Pakistan. J. Ethnopharmacol. 2015, 168, 164–181. [Google Scholar] [CrossRef] [Scilit]
- Adhikari, M.; Thapa, R.; Kunwar, R.M.; Devkota, H.P.; Poudel, P. Ethnomedicinal Uses of Plant Resources in the Machhapuchchhre Rural Municipality of Kaski District, Nepal. Medicines 2019, 6, 69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Singh, A.; Nautiyal, M.C.; Kunwar, R.M.; Bussmann, R.W. Ethnomedicinal plants used by local inhabitants of Jakholi block, Rudraprayag district, western Himalaya, India. J. Ethnobiol. Ethnomed. 2017, 13, 49. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bibi, T.; Ahmad, M.; Tareen, N.M.; Jabeen, R.; Sultana, S.; Zafar, M.; Zain-Ul-Abidin, S. The endemic medicinal plants of Northern Balochistan, Pakistan and their uses in traditional medicine. J. Ethnopharmacol. 2015, 173, 1–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zheng, X.-L.; Xing, F.-W. Ethnobotanical study on medicinal plants around Mt.Yinggeling, Hainan Island, China. J. Ethnopharmacol. 2009, 124, 197–210. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ijaz, F.; Iqbal, Z.; Rahman, I.U.; Alam, J.; Khan, S.M.; Shah, G.; Khan, K.; Afzal, A. Investigation of traditional medicinal floral knowledge of Sarban Hills, Abbottabad, KP, Pakistan. J. Ethnopharmacol. 2016, 179, 208–233. [Google Scholar] [CrossRef] [Scilit]
- Ullah, A.; Hassan, N.; Amin, R.; Khan, A.; Shi, L.; Li, M. Quantitative ethnobotanical survey of medicinal plants used as remedy in Mera, District Charsadda, KP, Pakistan. J. Biol. Environ. Sci. 2018, 12, 163–173. [Google Scholar]
- Singh, B.; Singh, B.; Kishor, A.; Singh, S.; Bhat, M.N.; Surmal, O.; Musarella, C.M. Exploring Plant-Based Ethnomedicine and Quantitative Ethnopharmacology: Medicinal Plants Utilized by the Population of Jasrota Hill in Western Himalaya. Sustainability 2020, 12, 7526. [Google Scholar] [CrossRef] [Scilit]
- Ullah, S.; Khan, M.R.; Shah, N.A.; Shah, S.A.; Majid, M.; Farooq, M.A. Ethnomedicinal plant use value in the Lakki Marwat District of Pakistan. J. Ethnopharmacol. 2014, 158, 412–422. [Google Scholar] [CrossRef] [Scilit]
- Kayani, S.; Ahmad, M.; Sultana, S.; Shinwari, Z.K.; Zafar, M.; Yaseen, G.; Hussain, M.; Bibi, T. Ethnobotany of medicinal plants among the communities of Alpine and Sub-alpine regions of Pakistan. J. Ethnopharmacol. 2015, 164, 186–202. [Google Scholar] [CrossRef] [Scilit]
- Aziz, M.A.; Adnan, M.; Khan, A.H.; Sufyan, M.; Khan, S.N. Cross-Cultural Analysis of Medicinal Plants commonly used in Ethnoveterinary Practices at South Waziristan Agency and Bajaur Agency, Federally Administrated Tribal Areas (FATA), Pakistan. J. Ethnopharmacol. 2018, 210, 443–468. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abbas, W.; Hussain, W.; Badshah, L.; Hussain, K.; Pieroni, A. Traditional wild vegetables gathered by four religious groups in Kurram District, Khyber Pakhtunkhwa, North-West Pakistan. Genet. Resour. Crop Evol. 2020, 67, 1521–1536. [Google Scholar] [CrossRef] [Scilit]
- Khan, K.; Rahman, I.U.; Calixto, E.S.; Ali, N.; Ijaz, F. Ethnoveterinary Therapeutic Practices and Conservation Status of the Medicinal Flora of Chamla Valley, Khyber Pakhtunkhwa, Pakistan. Front. Vet. Sci. 2019, 6, 122. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).