


Abstract
A study was conducted to determine whether plantar surface contact area measures calculated from footprints collected during walking can be used to predict the height of the medial longitudinal arch. Thirty healthy women participated in the study. Arch height was determined by the distance from the navicular tuberosity to the floor and by the “bony” arch index. Dynamic plantar surface contact area was recorded using a pressure platform as the subjects walked across a 12-m walkway. The arch index and the total plantar surface contact area were determined from the pressure sensor data. The results indicated that plantar surface contact area could be used to estimate only approximately 27% of the height of the medial longitudinal arch as determined by navicular tuberosity height and the bony arch index. These findings demonstrate the inability of the clinician to predict the vertical height of the medial longitudinal arch on the basis of the amount of foot plantar surface area in contact with the ground during walking.
One of the most widely studied characteristics of foot morphology is the medial longitudinal arch. The mechanical actions that occur in the human foot during dynamic movement can be influenced by foot morphology or structure and are often classified by the height of the medial longitudinal arch. Numerous researchers[1–4] have also reported that medial longitudinal arch height can influence the pattern of overuse injuries during physical activity.
Various techniques have been suggested for determining medial longitudinal arch height. The most direct method is to measure the distance from the most prominent point of the tuberosity of the navicular bone to the supporting surface with the subject standing. Although this method is commonly used in the clinic, identification of the tuberosity of the navicular bone depends on palpation, which can be subjective and experience-dependent. Another issue that arises when measuring navicular bone height as an isolated measure of arch height is that it does not take into account variations in subject foot length. Two subjects may have the same navicular height measurement, but if one subject has a longer foot than the other subject, the medial longitudinal arch is lower. In light of this problem, Cowan et al[1] proposed using a “bony” arch index, defined as the ratio of the height of the navicular bone to the truncated foot length. The truncated foot length was defined as the distance from the most posterior aspect of the heel to the first metatarsophalangeal joint line. The truncated foot length is often referred to as the ball length. In addition to palpation, other techniques that have been used to assess medial longitudinal arch height include radiographs,[5,6] ultrasound,[7] and footprint parameters. Radiography and ultrasound are relatively expensive and can require special facilities. Radiography also presents the problem of radiation exposure, with its potential health risks.
McKenzie[8] described the use of footprints as a method of classifying foot structure in 1923. Schwartz et al[9] reported one of the first footprint measurements, called the arch angle, which they described as a mathematical measure of foot conditions obtained from a footprint. On the basis of their data, a high medial longitudinal arch would have a greater angle. Rogers[10] used the same footprint angle and reported high reliability coefficients. Rogers also noted that experience and judgment were necessary to determine optimal placement of the lines that formed the arch angle. In an attempt to objectify the footprint angle, Clarke[11] modified the original lines described by Schwartz et al and reported high validity and reliability using the modified procedure. In 1935, Cureton[12] questioned the validity of footprints as a measure of the vertical height of the arch. Cureton used a sand-box to measure the vertical height of the arch and correlated the height to the modified footprint angle proposed by Clarke. Cureton found that the footprint angle could predict vertical arch height only 58% of the time and concluded that footprints alone are not sufficient for accurate classification of arch height.
In 1987, Cavanagh and Rodgers[13] described a more currently used method of assessing footprints termed the arch index. The arch index was calculated from a footprint in which the area of the toes was excluded and the remaining footprint was divided into three equal regions: rearfoot, midfoot, and forefoot. The arch index was the ratio of the midfoot region area to the total area of the foot. The authors provide a distribution of the arch index based on 107 feet and, using quartiles, arch index values for classifying low, normal, and high arches. Because Cavanagh and Rodgers did not measure any structural elements of the arch, they noted that although the arch index is a quantitative method of characterizing footprints, it may not be a valid method of describing the structural characteristics of the feet that made the prints. A further complication of using footprints to quantify bony foot structure is the suggestion by Cobey and Sella[14] that feet with a radiographically similar structure can exhibit different footprints owing to soft-tissue influences. These authors also reported that the most prominent point of the navicular tuberosity is an extremely variable point on radiographs that could be confounded by magnification and parallax errors.
Several investigators have attempted to quantify the ability of foot measurements to predict the vertical height of the medial longitudinal arch. Hawes et al[15] collected right footprints from 115 healthy male subjects using an ink pad system. A caliper was used to measure arch height with the ankle joint in the neutral position and equal body weight placed on both lower extremities. Footprints were digitized so that five different quantitative measurements were calculated, including the arch index. The correlation coefficients between footprint parameters and arch height ranged from −0.39 to 0.39, indicating that only 4% to 15% of the variation in arch height could be explained by the various footprint measurements studied. Of the five footprint measurements evaluated by Hawes et al, the arch index exhibited one of the highest correlation coefficients. They concluded from their results that the five quantitative measurements obtained from the footprints were invalid as a basis for predicting or categorizing arch height.
Chu et al[16] used a specially developed pedobarograph to digitally acquire footprints from 51 healthy subjects (37 males and 14 females). Subjects stood with 50% of their body weight on each foot while the digital images were being recorded. The distance between the bottom of the navicular tuberosity and the floor was measured using a caliper. They also calculated the arch index and a modified arch index that was determined on the basis of foot pressure. The coefficient determined for the arch index was −0.70 and for the modified arch index was −0.71. They concluded that because the arch index could explain 49% of the variance in arch height, a significant correlation exists between the arch index and arch height. Chu et al also reported that no differences existed for the arch index and the modified arch index between the left and right feet, and they noted that in future studies these data could be consolidated.
More recently, Shiang et al[17] used the same digital pedobarograph previously described by Chu et al[16] to obtain footprints from 26 male and 8 female healthy subjects. Eight different quantitative measurements, including the arch index and the modified arch index, were calculated from the digital footprints of the left and right feet. The same method of measuring navicular height described by Chu et al was also used by these researchers. The coefficient determined for the eight footprint measurements ranged from −0.14 to −0.74, with the arch index and the modified arch index exhibiting the largest coefficients. Shiang et al concluded that because 53% and 55% of the variance in arch height could be explained by the arch index and the modified arch index, respectively, either could be used to classify medial longitudinal arch structure. Chu et al and Shiang et al stated that their results were different from the findings reported by Hawes et al[15] because they both found a significant correlation between bony arch height and both the arch index and the modified arch index. However, these two groups of researchers could explain only approximately 50% of the bony height of the medial longitudinal arch on the basis of footprint measurements.
Although the previous studies seem to create considerable controversy regarding whether measurements obtained from footprints can be used to predict arch height, important factors to consider when assessing the results of these studies are the different systems used for the collection of footprints and the fact that footprints in all three studies were obtained during static standing. Urry and Wearing[18] reported that footprints obtained from certain types of matrix pressure platforms are not the same as footprints obtained using an inked mat when the data are collected during static standing. This factor could help explain the variation in results reported in previous studies. More importantly, it would be beneficial to know whether the height of the medial longitudinal arch measured in static standing has a relationship to the plantar surface area of the foot during dynamic activities such as walking. Furthermore, previous studies assessing the relationship between medial longitudinal arch height and plantar surface area have not included a substantial number of female subjects. Thus the purpose of this study was to determine whether the arch index, calculated from footprints collected from women during walking, could be used to predict the height of the medial longitudinal arch represented by the distance from the navicular tuberosity to the supporting surface.
Methods
Subjects
Thirty women volunteered to participate in the study and met all of the following screening criteria: 1) no history of congenital deformity, 2) no history of lower-extremity or foot fractures, and 3) no history of trauma or pain involving either foot, either lower extremity, or the lumbosacral region within the 12 months before the start of the investigation. The mean age of the 30 subjects was 26.3 years (range, 21–38 years). The human ethics review board of Northern Arizona University approved the protocol for data collection, and all of the subjects provided written informed consent before participation.
Instrumentation
A floor-mounted capacitance transducer matrix platform (EMED-SF; Novel USA Inc, Minneapolis, Minnesota) with an active sensor area of 23 × 44 cm was positioned at the midpoint of a 12-m walkway to collect dynamic plantar surface area data during walking. The platform had a matrix of 1,944 force transducers, with a density of two sensors per square centimeter and a sampling rate of 70 Hz. The input pressure-saturation level for the capacitance sensors used in the platform is 1,200 kPa. In the present study, none of the subject trials achieved pressure-saturation levels for the platform system.
Lateral Radiography
After completion of the static measurements, each subject was prepared to have a lateral radiograph obtained of the right foot. A small 2-mm metallic bead was placed over the same felt-tipped mark used for the clinical measurements of navicular height. With the subject standing on the foot template that was placed over the same elevated platform to ensure that foot placement was identical, a lateral radiograph was obtained with the radiographic cassette positioned between the two feet. Before exposure, each subject was instructed to stand with her feet completely relaxed and to maintain 50% of her weight as noted on the scale. The radiography unit was positioned vertical to the supporting surface, and the center of the radiography beam was placed just superior to the fifth metatarsal tuberosity. The distance from the radiography tube to the foot was 40 inches, and the exposure setting used was 100 mA at 62 kV. The same protocol for obtaining the lateral radiographs was used for all 30 subjects. To prevent possible magnification and parallax errors when obtaining measurements from the lateral radiograph, three metal pieces of known length were placed at the top and at both ends of the radiograph to serve as linear calibration references during data analysis.
Dynamic Surface Area Measurements
After completion of the radiograph, each subject was instructed to practice walking barefoot at a self-selected speed along the 12-m walkway for several minutes. To prevent targeting of the EMED-SF platform, subjects were instructed not to look at the ground while walking. Walking speed was monitored using two infrared photocells (Tandy Corp, Fort Worth, Texas) positioned 6.1 m apart and connected to a digital timer (model 54030; Lafayette Instrument Co, Lafayette, Indiana). When between-trial walking speed was consistent (variation of <5% between trials), each subject was asked to walk barefoot across the walkway while data were recorded from the EMED-SF platform for five trials on both the left and right feet.
Data Analysis
For each of the 30 right foot lateral radiographs, the distance from the metallic bead to the supporting surface was measured using the same metal centimeter scale. In addition, the joint line of the first metatarsophalangeal articulation was identified on the radiograph, and the distance from the joint line to the most posterior aspect of the calcaneus (ball length) was measured using the same metal scale. Each of these measurements was repeated three times to assess the reliability of the rater. The mean navicular height and ball length obtained from the static and radiographic measurements were used to calculate the bony arch index using the formula described by Cowan et al,[1] in which the navicular height was divided by the ball length.
The stance phase durations for each of five trials per foot were calculated using a software program (NovelWin EMED-SF; Novel USA Inc) to assess the reliability of each subject’s walking speed across the five trials. A standardized four-region masking model (Automask; Novel USA Inc) was used to divide the plantar surface area into four regions: rearfoot, midfoot, forefoot, and toes. The heel-to-midfoot and midfoot-to-forefoot regions were defined by using 73% and 45%, respectively, of the entire foot length from the toes to the heel. The forefoot-to-toes region was defined by using the pressure gradients around the peak pressures of the toes. The toe region was discarded, and only the rearfoot, midfoot, and forefoot regions were used for further analysis. The Group-mask program (Novel USA Inc) was used to determine the mean plantar surface contact area for the five trials collected on each subject’s feet. The arch index was then calculated using the formula described by Cavanagh and Rodgers[13] in which the midfoot area was divided by the combined areas of the rearfoot, midfoot, and forefoot. In addition, the total foot plantar surface contact area was calculated by summing the rearfoot, midfoot, and forefoot contact areas.
Statistical Analysis
Type (3,1) intraclass correlation coefficients (ICCs)[19] were calculated to determine the reliability of the stance phase durations and the three measures of navicular height and ball length that were obtained statically and from the radiographs. The level of reliability for the ICCs was classified using the characterizations reported by Landis and Koch[20]: slight, 0 to 0.20; fair, 0.21 to 0.40; moderate, 0.41 to 0.60; substantial, 0.61 to 0.80; and almost perfect, 0.81 to 1.00.
T tests were used to determine whether differences existed between measurements of the navicular height and the bony arch index that were obtained from the static measurements and the radiographs. To test the ability of the arch index or the total foot plantar surface contact area to predict the navicular height or the bony arch index, Pearson product moment correlation coefficients were calculated. An α of .05 was established for all tests of significance.
Results
Descriptive statistics for the navicular height, bony arch index, arch index, and total foot plantar surface contact area are listed in Table 1. The mean (SD) stance phase duration for all of the subjects was 0.634 (0.031) sec. The ICC calculated to determine the consistency of the subject’s walking speed among the five data trials recorded for each foot was 0.98. The ICCs calculated for the static and radiographic navicular height measurements were 0.98 and 0.97, respectively. The ICCs calculated for the static and radiographic ball length measurements were 0.99 and 0.98, respectively. On the basis of the classification scheme of Landis and Koch,[20] all of the ICC values obtained would be classified as almost perfect. Thus, for the static and radiographic measurements of navicular height and ball length, the examiner in this investigation demonstrated a high level of intrarater reliability. The result of the t test used to determine whether differences existed between the static and radiographic navicular height measurements was not significant (P > .18). The result of the t test used to determine whether differences existed between the static and radiographic bony arch index also was not significant (P > .06).
Discussion
The purpose of this study was to determine whether the arch index, calculated from footprints collected from women during walking, could be used to predict the height of the medial longitudinal arch, represented by the distance from the navicular tuberosity to the supporting surface or by the bony arch index. We also included two additional variables in this analysis: plantar surface contact area, with the toes excluded, and the bony arch index. As noted previously here, although numerous authors[13,16,17] have inferred that footprints can be used to characterize the bony height of the medial longitudinal arch, controversy exists in the literature concerning the use of footprint parameters to predict medial longitudinal arch height. Footwear manufacturers have used the plantar surface contact area, derived from dynamic footprints, in an attempt to guide consumers to more properly fitting shoes, and orthotic device laboratories have used it to prescribe custom foot orthoses. Thus the issue of whether plantar surface contact area can be used to predict the bony height of the medial longitudinal arch is a critical one not only for the clinician but also for the consumer.
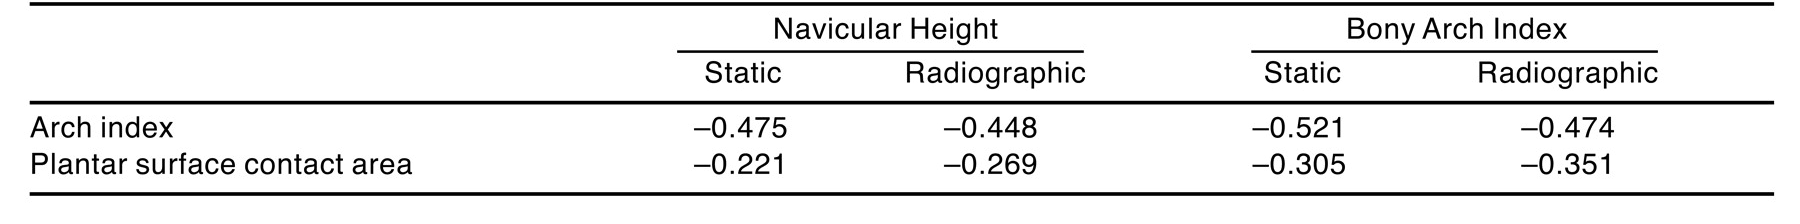
In the present study, the highest correlation coefficients were obtained between the arch index and the vertical height of the navicular tuberosity when measured statically and between the arch index and the bony arch index when calculated from a static measurement. The results indicate that plantar surface contact area, as determined by the arch index and total foot plantar surface contact area, can at best explain only 27% of the vertical height of the medial longitudinal arch using navicular height or the bony arch index. These findings are in agreement with those of Hawes et al,[15] who reported that only 4% to 15% of the variation in bony arch height could be explained by footprint measurements. Findings from the present study and those reported by Hawes et al must be compared cautiously, however, because footprints in the present study were collected dynamically rather than statically.
Previous researchers[14] have reported that the most prominent point of the navicular tuberosity can be an extremely variable point on radiographs and could be confounded by possible magnification and parallax errors. The protocol used in the present study to standardize foot placement and radiographic beam position, in addition to having known distances captured on the radiograph to calibrate linear measurements, seems to have been successful in controlling for radiographic measurement error, because no significant differences were found between navicular height and ball length when measured statically or when using radiographs. A limitation in analyzing the results of the present study, however, is that only within-rater reliability for a single examiner was assessed for the static and radiographic measurements of the navicular height and the bony arch index. The issue of multiple-rater reliability regarding identifying the tuberosity of the navicular was not addressed in this study.
The results of the present study indicate that the use of measurements that directly assess the bony height of the medial longitudinal arch, such as the arch height ratio, is more appropriate than attempting to analyze footprints.[21] The arch height ratio, first described by Williams and McClay,[21] is a measurement that does not require the palpation of a bony landmark, such as the medial prominence of the navicular tuberosity. The arch height ratio is calculated by dividing the height of the dorsum of the foot, measured at 50% of the total foot length, by the ball length. In their study, Williams and McClay assessed the reliability and validity of seven different measurements used to characterize the medial longitudinal arch, including the vertical height of the navicular. They found that one of the most reliable and valid measurements for clinically assessing the height of the medial longitudinal arch was the arch height ratio.
Another limitation of the present study was that only women were tested. The reason for selecting only women to serve as subjects was that the three previous studies that assessed the relationship between plantar surface contact area and medial longitudinal arch height used mostly male subjects. Thus caution should be exercised when applying the findings of this study to male subject populations. Chu et al[16] and Shiang et al,[17] in assessing female and male subjects, reported no differences in the relationship between plantar surface contact area and medial longitudinal arch height.
Conclusion
The results of this study demonstrate that plantar surface contact area, as determined by footprints, can explain only approximately 27% of the medial longitudinal arch height as represented by the vertical height of the medial prominence of the navicular bone. These findings demonstrate that the clinician cannot predict the vertical height of the medial longitudinal arch on the basis of the amount of foot plantar surface area in contact with the ground during walking. It seems that the observation of Cureton,[12] who in 1935 stated that footprints alone are not a sufficient basis for the accurate classification of the vertical height of the arch, is still relevant today.

Table 1.
Descriptive Statistics for Navicular Height, Bony Arch Index, Arch Index, and TPCA.
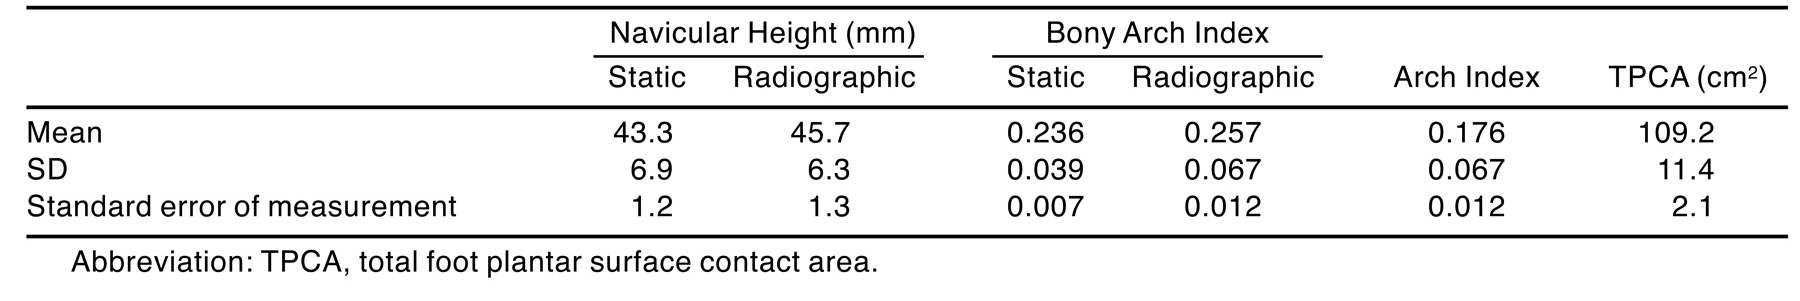
Table 2.
Pearson Product Moment Correlation Coefficients for Arch Height Measurements and Total Foot Plantar Surface Contact Area Variables.
References
- Cowan DN, Jones BH, Robinson JR: Foot morphologic characteristics and risk of exercise-related injury. .Arch Fam Med2::773. ,1993. .
- Giladi M, Milgrom C, Stein M, et al: The low arch, a protective factor in stress fracture: a prospective study of 295 military recruits. .Orthop Rev14::709. ,1985. .
- Kaufman KR, Brodine SK, Shaffer RA, et al: The effect of foot structure and range of motion on musculoskeletal overuse injuries. .Am J Sports Med27::585. ,1999. .
- Williams DS III, Davis IM, Scholz JP, et al: High-arched runners exhibit increased leg stiffness compared to low-arched runners. .Gait Posture19::263. ,2004. .
- Rose GK, Welton EA, Marshall T: The diagnosis of flat foot in the child. .J Bone Joint Surg Br67::71. ,1985. .
- Saltzman CL, Nawoczenski DA, Talbot KD: Measurement of the medial longitudinal arch. .Arch Phys Med Rehabil76::45. ,1995. .
- Hennig EM, Cavanagh PR: “Ultrasound Quantification of the Arch of the weightbearing Foot,” in Biomechanics IX-B, ed by DA Winter, RW Norman, RP Wells, et al, p 211, Human Kinetics, Champaign, IL. ,1985. .
- McKenzie RT: “Flat-Foot and Club-Foot: Their Treatment by Exercise,” in Exercise in Education and Science, p 155, WB Saunders, Philadelphia. ,1923. .
- Schwartz L, Britten RH, Thompson LR: Studies in Physical Development and Posture, p 23, US Public Health Service Bulletin No 179. ,1928. .
- Rogers FR: Fundamentals of Administrative Measures in Physical Education, p 155, Pleiades, Newton, MA. ,1932. .
- Clarke HH: An objective method of measuring the height of the longitudinal arch in foot examinations. .Res Q4::99. ,1933. .
- Cureton TK Jr: The validity of footprints as a measure of the vertical height of the arch and functional efficiency of the foot. .Res Q6::70. ,1935. .
- Cavanagh PR, Rodgers MM: The arch index: a useful measure from footprints. .J Biomech20::547. ,1987. .
- Cobey JC, Sella E: Standardizing methods of measurement of foot shape by including the effects of subtalar rotation. .Foot Ankle2::30. ,1981. .
- Hawes MR, Nachbauer W, Sovak D, et al: Footprint parameters as a measure of arch height. .Foot Ankle13::22. ,1992. .
- Chu WC, Lee SH, Chu W, et al: The use of arch index to characterize arch height: a digital image processing approach. .IEEE Trans Biomed Eng42::1088. ,1995. .
- Shiang TY, Lee SH, Lee SJ, et al: Evaluating different footprint parameters as a predictor of arch height. .IEEE Eng Med Biol Mag17::62. ,1998. .
- Urry SR, Wearing SC: Arch indexes from ink footprints and pressure platforms are different. .The Foot15::68. ,2005. .
- Shrout PE, Fleiss JL: Intraclass correlations: uses in assessing rater reliability. .Psychol Bull86::420. ,1979. .
- Landis JR, Koch GG: The measurement of observer agreement for categorical data. .Biometrics33::159. ,1977. .
- Williams DS, McClay IS: Measurements used to characterize the foot and the medial longitudinal arch: reliability and validity. .Phys Ther80::864. ,2000. .
© 2006 American Podiatric Medical Association