


Abstract
A prospective epidemiologic survey on the prevalence of foot disease in Hong Kong found foot disease in 64% of patients screened. All of the patients were ethnically Chinese. Of the conditions specified in the questionnaire, fungal foot infection, tinea pedis, and toenail onychomycosis were the most frequently encountered conditions, followed by metatarsal corns, eczema, psoriasis, and pes planus. Vascular disease, osteoarticular pathology, diabetes mellitus, obesity, atopy, and participation in sports were the main factors coexisting with the foot conditions. Of the study population, 17% and 21% reported that their quality of life was affected by pain and discomfort, respectively. These percentages are much lower than those obtained in other studies; it may therefore be inferred that foot complaints are being neglected by the ethnic Chinese population in Hong Kong.
Foot health problems are prevalent everywhere. However, they are not regarded as a priority by the major health-care systems of the world. It has been estimated that in Europe, 3% to 5% of the total population has onychomycosis or tinea pedis.[1] In the United States, 10 million people (4% of the population) experience calluses, corns, or some other foot condition at some point during their lifetime.[2] Ingrown toenails, foot infection, and calluses are the three most prevalent foot conditions in this country.[3] According to BrimmComm, a public relations and marketing communications company that carried out a nationwide foot-care survey in the United States, an estimated 50 million visits to podiatrists were made by civilian patients in 1990.[4] These figures may reflect only the tip of the iceberg, as many patients neglect their foot health and never seek medical advice.
To collect data on foot diseases in Hong Kong, a prospective epidemiologic survey on the prevalence of foot disease was conducted. The study, known as the Achilles Foot-Screening Project, is an international collaborative effort to investigate the prevalence and severity of foot problems in Europe and Asia. The goal of the project is to make the general public more aware of foot disease and to collect data on its prevalence, major coexisting factors, and the effect of these diseases on quality of life. The project surveyed patients who visited clinics for somatic complaints other than foot disease. Clinics in Austria, Belgium, Germany, the Netherlands, Luxembourg, Switzerland, Italy, Hungary, the United Kingdom, Poland, Greece, China, South Korea, the Philippines, Singapore, Malaysia, Taiwan, and Hong Kong participated in the project. The investigators in the survey consisted of general practitioners and dermatologists. Some results from the European study have already been published.[5] This article presents and discusses the data from the Achilles Foot-Screening Project in Hong Kong.
Methodology
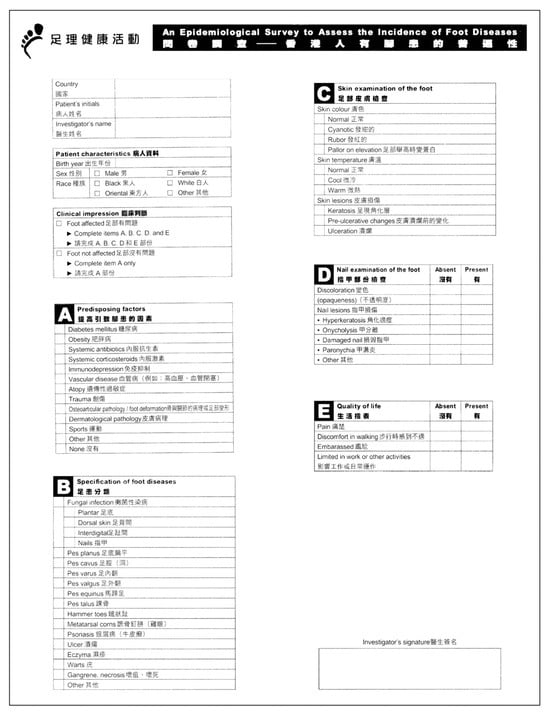
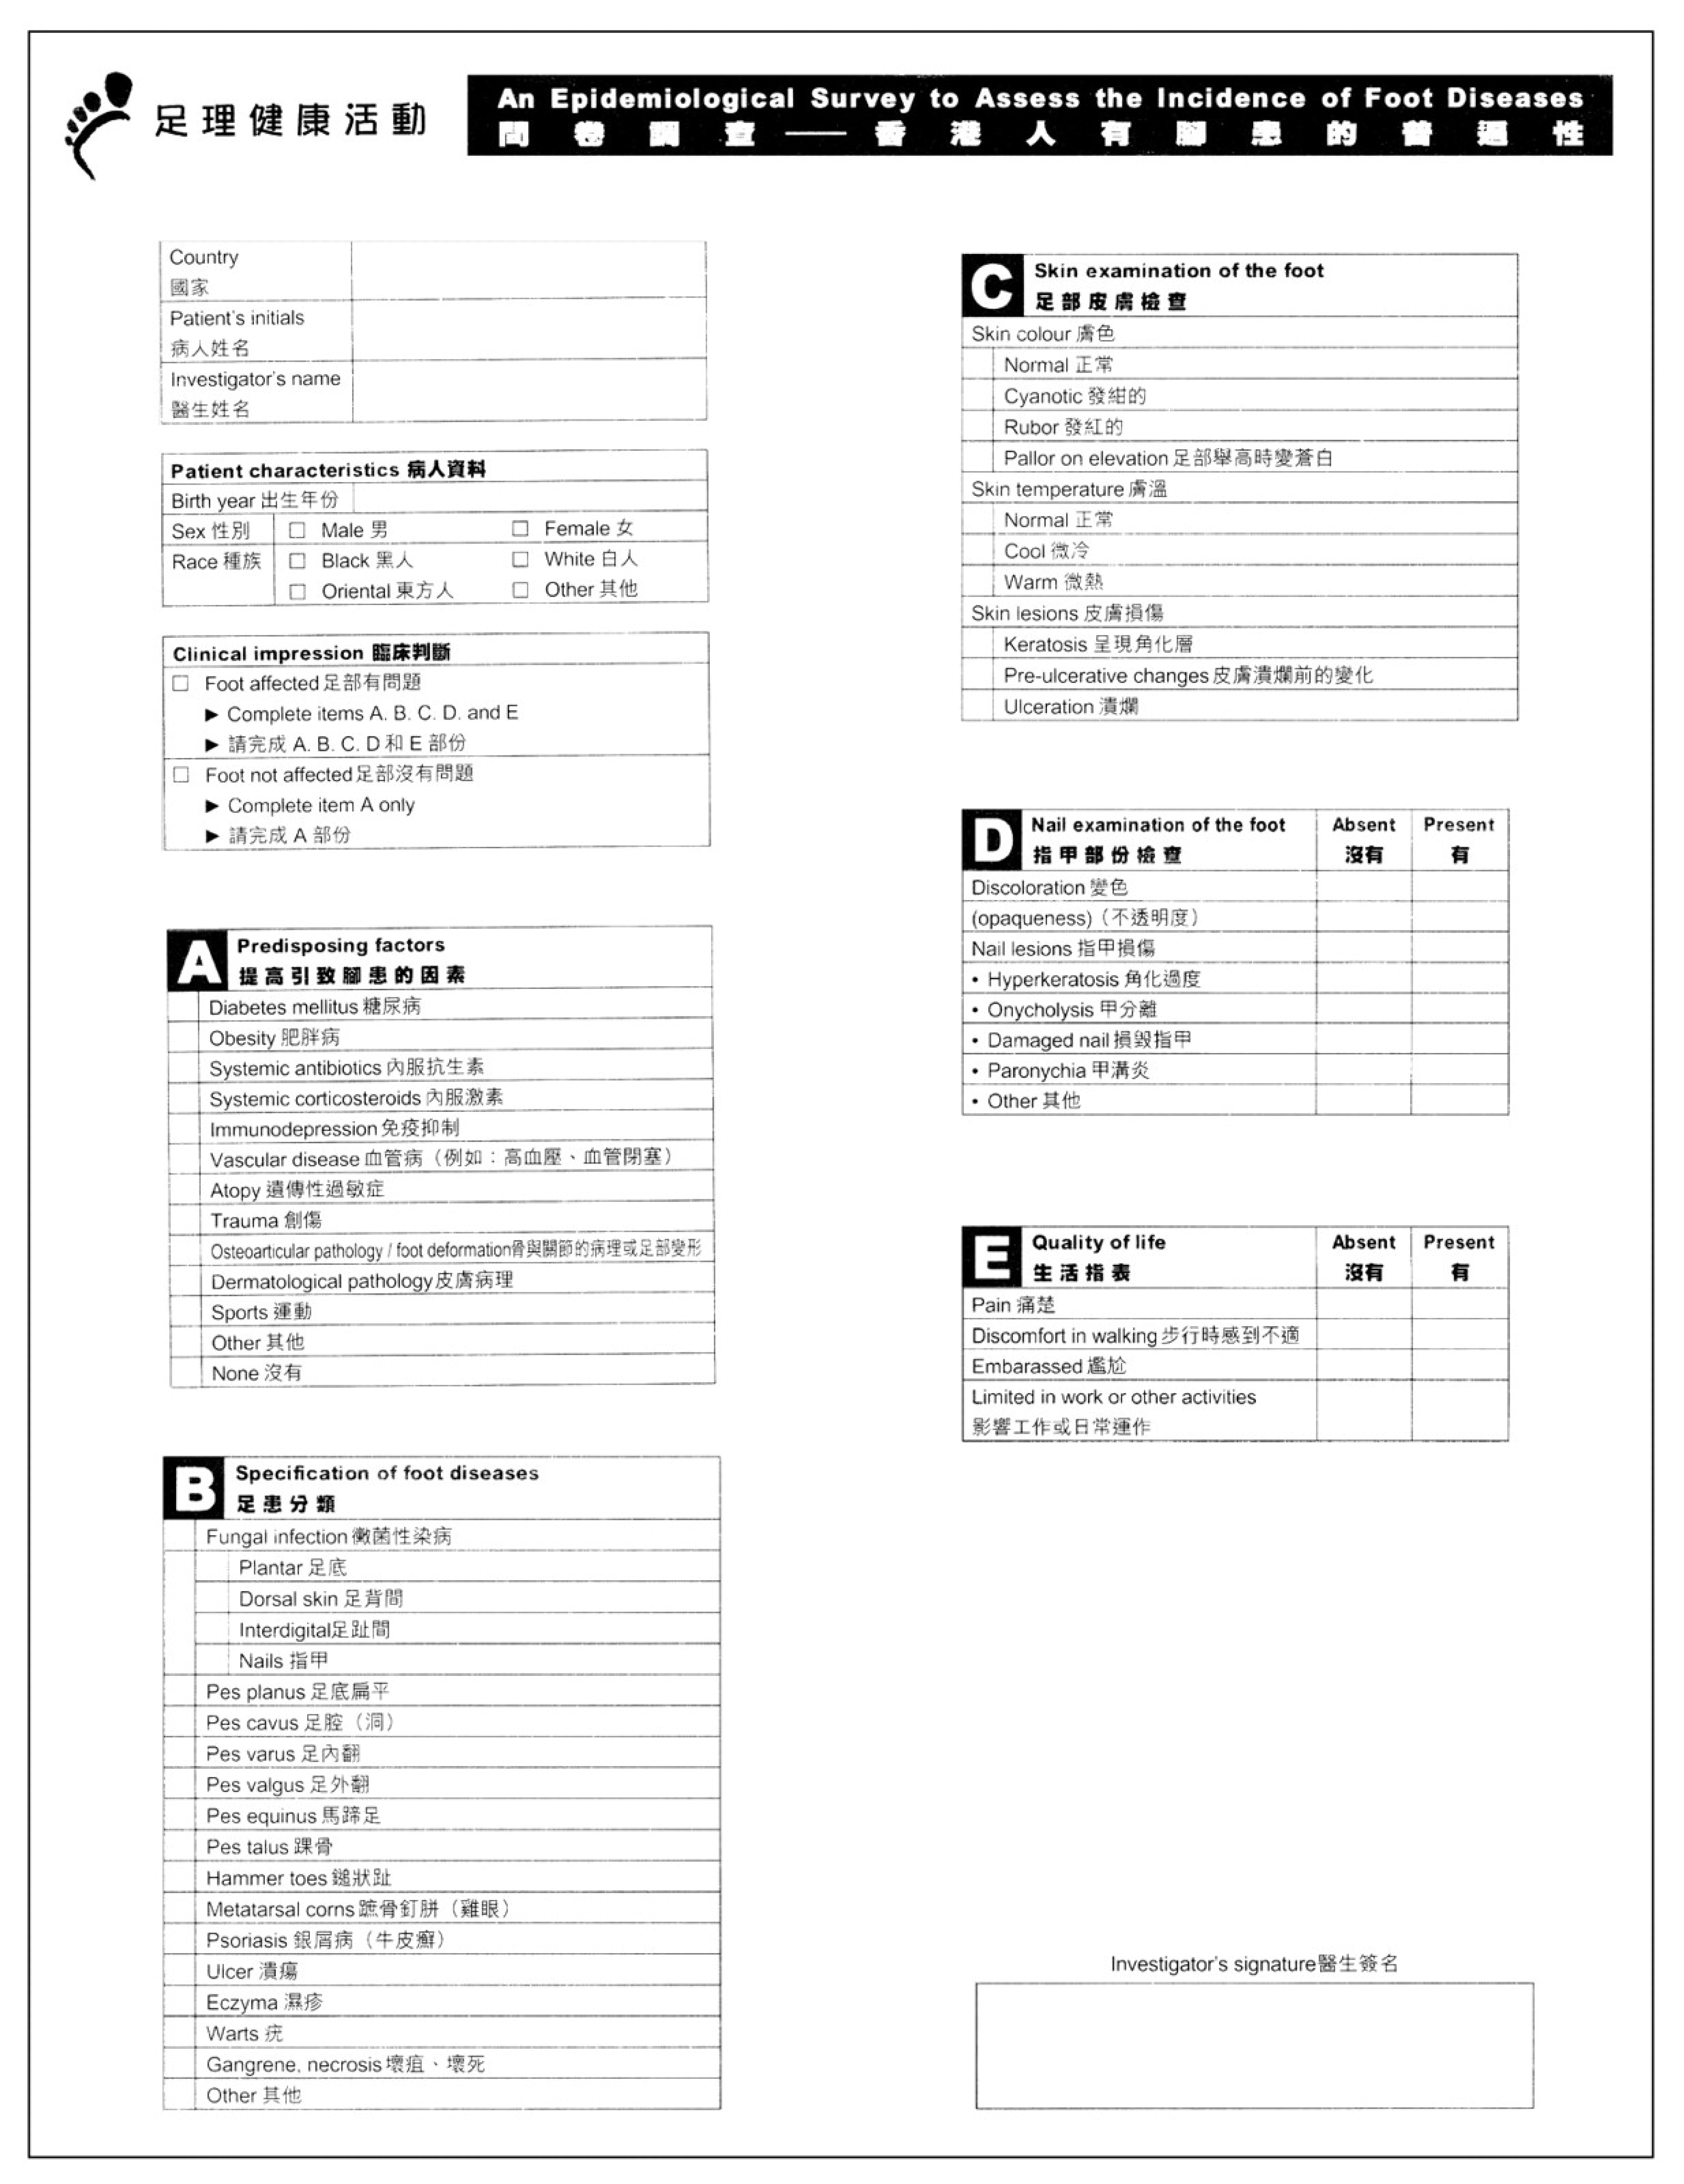
A prospective survey was conducted over a 1-week period from July 26, 1998, to August 2, 1998. A total of 15 dermatologists from public dermatologic clinics and 192 private general practitioners and dermatologists participated in the survey. The investigators completed a questionnaire and examined the feet of patients who visited their clinics for diseases other than foot problems. Patients were randomly selected, with no consideration given to age, sex, or medical complaint. The questionnaire collected basic demographic information, including year of birth, sex, and race. The observer also recorded the following information: clinical impression as to whether the foot was affected, factors coexisting with foot disease, which foot disease or diseases were present, the results of skin and nail examinations of the foot, and the quality of life of the patients in terms of foot health. The investigators then examined the patients’ feet to make a clinical diagnosis of foot disease. For the establishment of coexistent morbidity, such as vascular disease, osteoarticular pathology, and diabetes mellitus, the investigators included additional information from the patients’ medical history and performed necessary physical examinations, such as palpation of the foot pulses to establish evidence of vascular disease. Finally, the investigators assessed the impact of the foot disease on the patients’ quality of life. The detailed questionnaire appears in Figure 1. In contrast to the Achilles Foot-Screening Project in Europe, no mycologic investigation was conducted in the current study owing to limited resources. All results were analyzed statistically with two-sided statistical tests interpreted at the 5% significance level. A z-test was used to calculate the difference in prevalence between two groups.
Figure 1.
The questionnaire used in the study.
Results
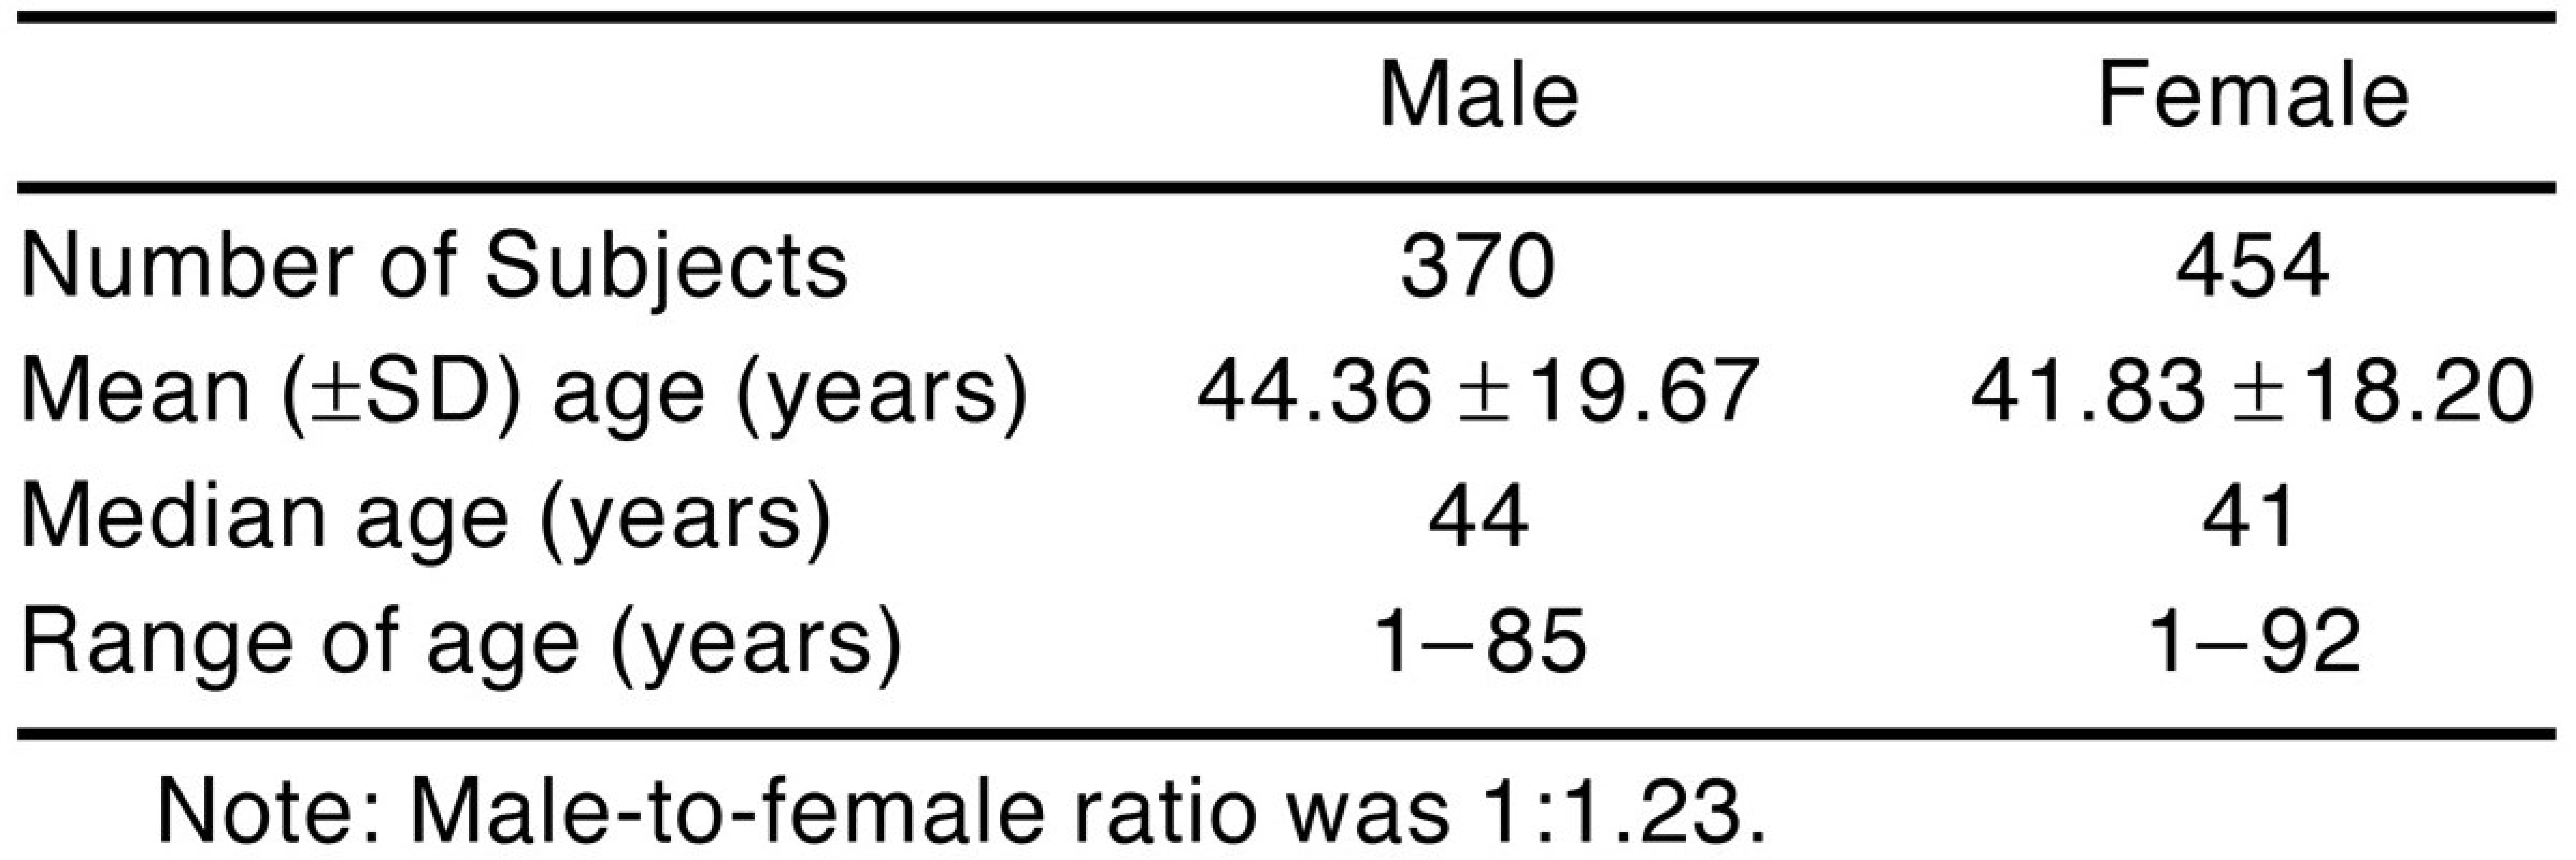
A total of 877 patients participated in the survey. Data were incomplete in 53 cases, which were excluded from the study. The remaining 824 patients consisted of 370 males and 454 females, resulting in a male-to-female ratio of 1:1.23. Basic demographic data appear in Table 1. All subjects were ethnically Chinese.
Table 1.
Basic Demographic Characteristics of the Population Surveyed (N=824).
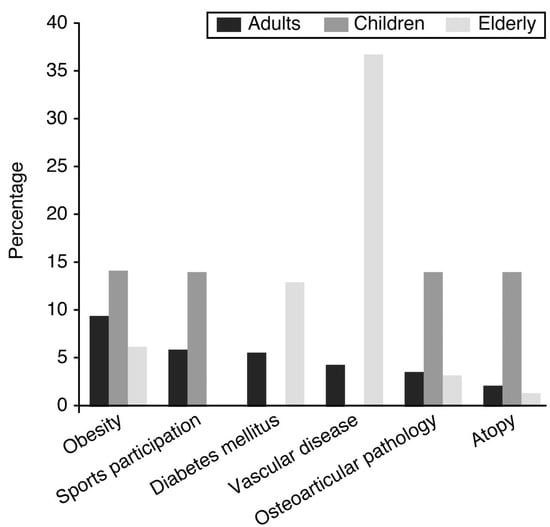
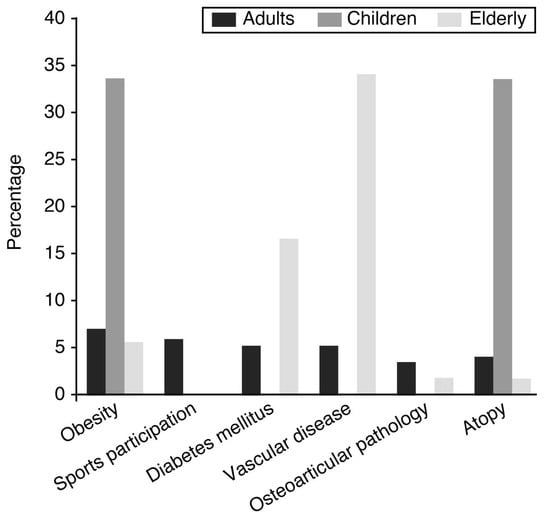
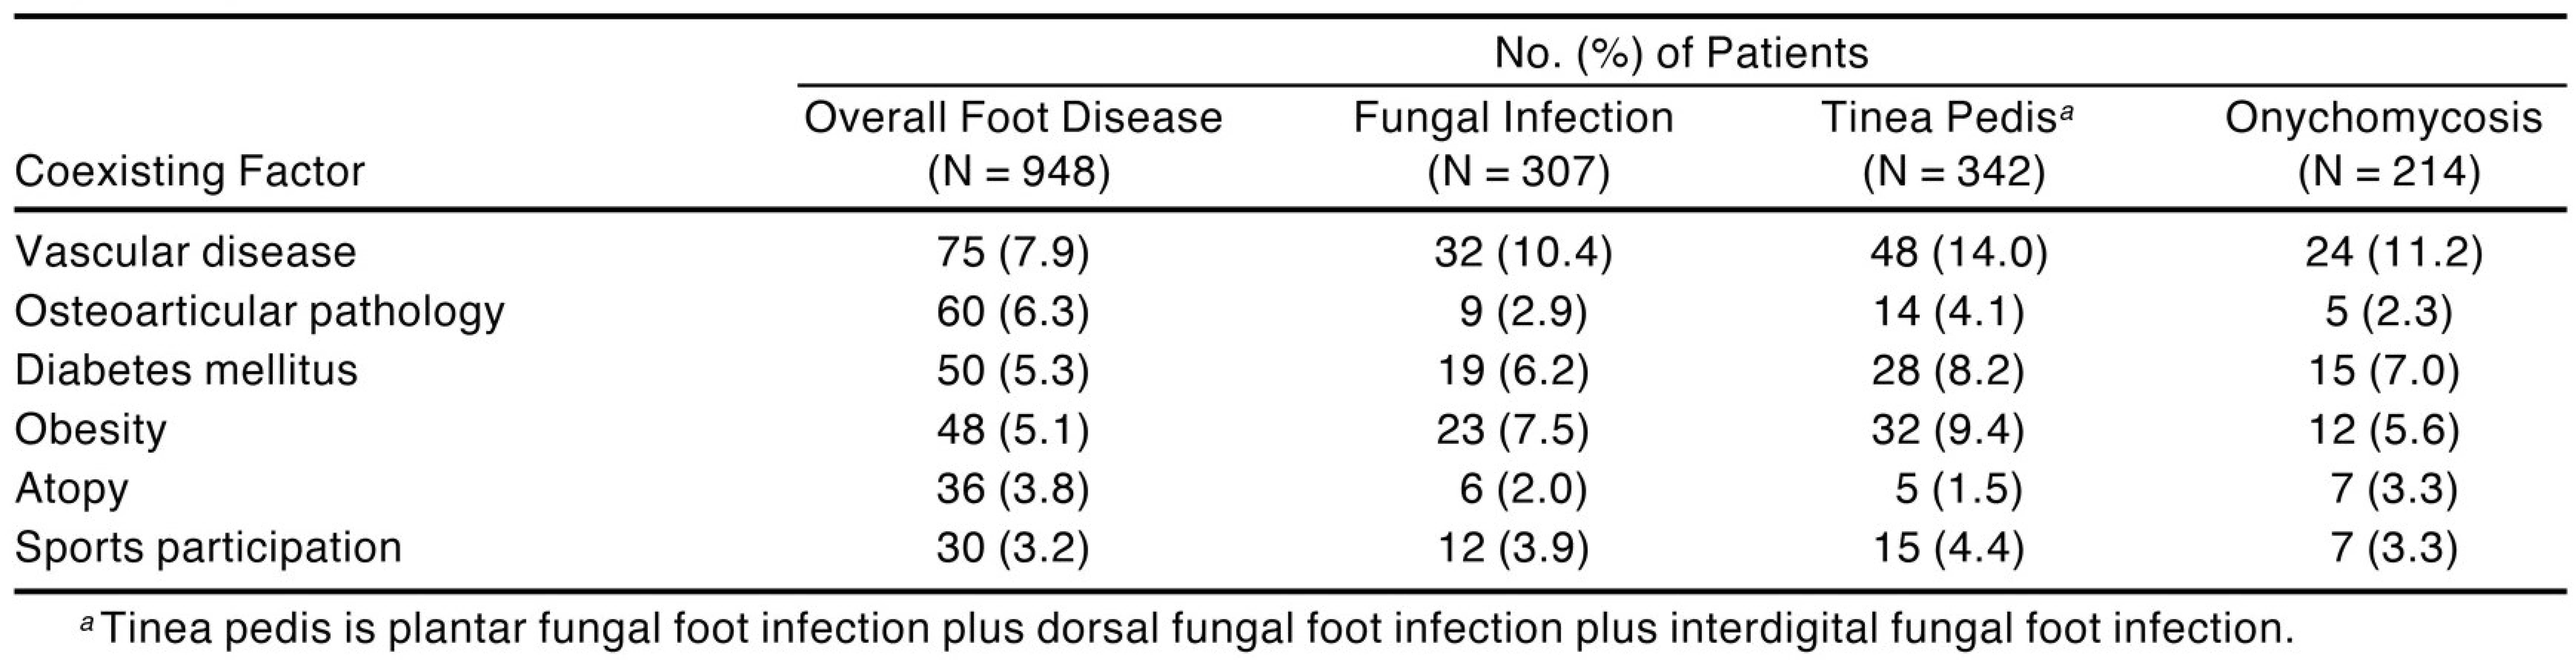
Of the screened population, 64% had some kind of foot disease (Fig. 2). Overall, fungal infection of the foot (31%), tinea pedis (30%), and toenail onychomycosis (21%) were the three most frequently diagnosed foot diseases in the survey. These were followed by metatarsal corns (11%), foot eczema (9%), pes planus (4%), and psoriasis (4%). Most of the foot diseases were most prevalent in the 21- to 60-year-old age group. This pattern of age distribution was evident for fungal foot disease (Table 2). Adults (21 to 60 years of age) had the highest prevalence of fungal foot diseases (39.7%); the elderly (older than 60 years of age) came next (14.1%); and children and adolescents (20 years of age or younger) had the lowest prevalence (1.5%). Factors coexisting with overall foot disease were vascular disease (7.9%), osteoarticular pathology (6.3%), diabetes mellitus (5.3%), obesity (5.1%), atopy (3.8%), and participation in sports (3.2%) (Table 3). Vascular disease and diabetes mellitus coexisted most frequently with such diseases as tinea pedis and onychomycosis. There was no gender difference in the three factors found to coexist most frequently with fungal disease or onychomycosis. There were, however, differences in terms of age group. In children, no particular factors favored more fungal foot infection. In adults, obesity (9.6%) appeared to be the most frequently occurring factor coexisting with fungal foot disease, followed by participation in sports (6%) and diabetes mellitus (5.3%). In the elderly, vascular disease (36.9%), diabetes mellitus (13.6%), and obesity (6.2%) occurred most frequently with fungal foot disease (Fig. 3). The differences among children, adults, and the elderly in factors that most frequently coexisted with fungal foot disease were all statistically significant (P < .001). For toenail onychomycosis, obesity (33%) and atopy (33%) were observed to coexist in children. In adults, the coexisting factors were obesity (6.7%), participation in sports (5.9%), diabetes mellitus (5.0%), and vascular disease (5.0%). In the elderly, these factors were vascular disease (34%), diabetes mellitus (17%), and obesity (5.7%) (Fig. 4). The differences among children, adults, and the elderly in the major factors coexisting with toenail infection were all statistically significant (P < .001).
Figure 2.
Prevalence of foot diseases in the study population.
Table 2.
Prevalence of Overall Fungal Foot Infection, Tinea Pedis, and Onychomycosis in the Screened Population by Age Group (N = 824).
Table 3.
Prevalence of the Major Factors Coexisting with Overall Foot Disease, Fungal Foot Infection, Tinea Pedis, and Onychomycosis in the Screened Population.
Figure 3.
The six leading factors coexisting with fungal diseases by age group.
Figure 4.
The six leading factors coexisting with toenail onychomycosis by age group.
Finally, in the assessment of the impact of foot disease on quality of life, 21% of patients in the study responded that their foot problems caused them discomfort while walking; 17% indicated that their foot disease caused them pain; 8% reported that the foot disease limited their work and other activities; and 6% said they were embarrassed by their foot condition (Table 4).
Table 4.
Quality of Life of Patients in the Survey with Diagnosed Foot Diseases.
Discussion
Few epidemiologic data exist on the prevalence of foot disease worldwide. Most studies on the incidence of fungal foot infections have been based on questionnaires in which patients make a self-diagnosis of disease.[6,7] Owing to recall bias, these studies may underestimate the true prevalence of the disease. Other studies have examined selected populations, such as schoolchildren, people visiting swimming pools,[8-10] coal miners,[11] and soldiers.[6,12] These studies may show selection bias due to the study population, and thus the epidemiologic data in these studies may not be representative. Studies involving mycologic examination are more detailed but require special facilities; because not all clinics can conduct such investigations, their inclusion would limit the number of subjects studied.[12-15] The Achilles Foot-Screening Project collects valuable baseline epidemiologic data on people who are affected by foot disease but have not consulted their medical practitioner.
The results of the current study indicate that foot diseases are prevalent in the general population of Hong Kong. Of all of the patients screened, 64% had some kind of foot pathology. This figure is higher than, but comparable to, the 58% prevalence rate of foot disease reported in the European Achilles study.[5] The results here show that fungal foot infection (31%), tinea pedis (30%), and toenail onychomycosis (21%) were the three most prevalent foot diseases in the population screened. These conditions were followed, in descending order, by metatarsal corns, eczema, pes planus, and psoriasis. Despite the order of prevalence found in this study, it must be emphasized that since not all foot diseases were specified in the questionnaire, these conditions may not in fact be the most common foot diseases in the population. The European study showed fungal foot infection (35%) and onychomycosis (23%) to have prevalence rates similar to those in this study, but showed a lower prevalence rate for tinea pedis (22%).[5] The other Achilles Foot-Screening Project that studied the population of East Asian countries also showed a higher prevalence rate of tinea pedis than its European counterpart. This difference in geographic distribution of tinea pedis may be due to climatic, socioeconomic, or cultural factors.[1]
The results of the present study show that metatarsal corns (11%) and pes planus (4%) were less prevalent than fungal foot infections in the local Chinese population studied. According to data from the 1990 National Health Interview Survey,[3] the five most common foot problems in the United States are ingrown toenails and other toenail problems, foot infections, corns and calluses, foot injury, and pes planus or flatfoot. The survey concluded that corns and calluses were by far the most prevalent foot disease in the US population. Pes planus or flatfoot was also considered a prevalent disease among Americans; it was ranked as the fifth most common foot disease by the National Health Interview Survey. A relatively high prevalence of pes planus and metatarsal corns in the Western population was also seen in the European Achilles Foot-Screening Project, which showed pes planus (18%) to be the second most common foot disease after foot infections, and more common than metatarsal corns (11%).[5] The geographic variation in the distribution of these foot diseases may be due to the genetic and phenotypic differences between the Chinese and Western populations.
In the current survey, the major factors occurring along with overall foot disease were vascular disease, osteoarticular pathology, diabetes mellitus, obesity, atopy, and participation in sports. Vascular disease and osteoarticular pathology coexisted more frequently with fungal disease, tinea pedis, and toenail onychomycosis in all age groups while diabetes mellitus and obesity coexisted most frequently with onychomycosis and tinea pedis, respectively. The apparent coexistence of these factors with foot diseases may suggest a coincidence or association rather than causation. In the European study, vascular disease, participation in sports, obesity, osteoarticular pathology, dermatologic pathology, atopy, and diabetes mellitus, in descending order, were found to be the most prevalent factors coexisting with foot disease in the population.[5] Both surveys showed that vascular disease and obesity were important factors coexisting with fungal infection and tinea pedis. In the current survey, however, the coexistence of participation in sports with fungal infection and tinea pedis is less frequent, and only 4% of the diagnosed cases occurred together with participation in sports. Whether this difference is a result of a general lack of exercise of the local population is unknown. The data in this study also support the results of other studies showing that diabetes mellitus appears to occur more frequently with toenail onychomycosis.
There is only one gender difference in the factors coexisting with fungal disease and onychomycosis: For both diseases, diabetes mellitus was a more frequently coexisting factor in men and obesity was more frequent in women. In the elderly, vascular disease was the most frequent factor coexisting with fungal foot infection and onychomycosis, whereas among adults obesity and diabetes mellitus were the most frequent coexisting factors. The importance of vascular pathology in the foot diseases of the aged population was also evident in the European study.[5]
The results of this study confirm that foot diseases can have a significant impact on a patient’s quality of life. In this survey, 21% of patients whose feet were affected complained of discomfort while walking; 17% felt pain; 8% said that the disease limited their daily activities; and 6% were embarrassed by their foot problems. Considerably lower percentages of patients complained of discomfort and pain in this study than in the European study (51% and 33%, respectively).[5] This higher threshold of perception of symptoms of foot disease by the Chinese may result in the general neglect of these diseases. It may also prevent people from seeking appropriate care and treatment for foot problems.
The impact of foot diseases on the community is considerable. First, the pain and discomfort caused by foot diseases such as onychomycosis and metatarsal corns can cause significant morbidity. Although effective treatment is available, it may not be readily accessible to the general public, especially to the elderly population, in which it is most needed. Inaccessibility may be due to a general lack of adequate services such as podiatric clinics or insufficient publicity about such services. If these foot pathologies are not dealt with early, the condition of the foot may deteriorate and cause premorbid complications, such as cellulitis, foot ulceration, gangrene, and even sepsis. At this later stage, patients may require hospitalization, greatly increasing the medical and insurance costs of these conditions. The ultimate economic burden rests not only on the individual but on society as well. Second, immobility can be a significant end result of foot disease, which may be particularly detrimental to the well-being of the aged population. Metatarsal corns, hammer toes, and foot deformity can significantly reduce the degree of freedom in a geriatric population that already experiences reduced mobility.[16] This can place a tremendous psychological burden on those senior citizens who have already been affected by multisystem diseases.
Podiatric physicians in Hong Kong belong to a multidisciplinary team that provides a comprehensive service to the community with foot disease. Their work includes diagnosing and treating foot diseases and educating the public on prevention. The podiatric service in Hong Kong was started in 1984. Currently, only 25 podiatric physicians serve the entire Hong Kong area. Of these 25 podiatric physicians, 22 work in the public sector, mostly in the geriatric service of the public hospitals, and 3 practice in the private sector. With a local population of 6.5 million, each podiatric physician in Hong Kong has to treat 260,000 patients. When compared with other developed countries, such as the United States, which has one podiatric physician per 30,000 people, this ratio is clearly inadequate. With a normal waiting time of 3 to 4 months for new appointments, many patients in Hong Kong may purchase unproven, over-the-counter remedies that could do more harm than good.
Conclusion
The Achilles Foot-Screening Project has shown a high prevalence of foot disease in Hong Kong. The three most prevalent foot conditions found in this survey were fungal foot diseases, tinea pedis, and toenail onychomycosis. Vascular disease, obesity, and diabetes mellitus were the main morbid factors found to coexist with the foot conditions. Podiatric service in Hong Kong is profoundly inadequate to meet the local demand, indicating that more resources and personnel should be allocated to podiatric medicine.
Acknowledgments
All who participated in the Achilles Project Working Group in Hong Kong. This survey was funded by Janssen Pharmaceuticals.
- Haneke E, Roseeuw D: The scope of onychomycosis: epidemiology and clinical features. Int J Dermatol38 (suppl 2): 7, 1999.
- Cobb J, Cornely PB, Grubb W, et al: An assessment of foot health problems and related health manpower utilization and requirements. JAPMA67: 102, 1977.
- Greenberg L, Davis H: Foot problems in the US: the 1990 National Health Interview Survey. JAPMA83: 475, 1993.
- Greenberg L: Foot care data from two recent nationwide surveys: a comparative analysis. JAPMA84: 365, 1994.
- Roseeuw D: Achilles Foot-Screening Project: preliminary results of patients screened by dermatologists. J Eur Acad Dermatol Venereol12 (suppl 1): S6, 1999.
- Roberts DT: Prevalence of dermatophyte onychomycosis in the United Kingdom: results of an omnibus survey. Br J Dermatol126 (suppl 39): 23, 1992.
- Sais G, Jucgla A, Peyri J: Prevalence of dermatophyte onychomycosis in Spain: a cross-sectional study. Br J Dermatol132: 758, 1995.
- English M, Gibson M: Studies in the epidemiology of tinea pedis. Br Med J1: 1442, 1959.
- Gentle JC, Evans EGV: Foot infection in swimming baths. Br Med J3: 260, 1973.
- Barranco V: New approaches to the diagnosis and management of onychomycosis. Int J Dermatol33: 292, 1994.
- Gotz H, Hewtschke D: Einblicke in die epidemiologie der dermatimykoses im Kohlenbergblan. Hautarzt16: 593, 1965.
- Heikhila H, Stubb S: The prevalence of onychomycosis in Finland. Br J Dermatol133: 677, 1995.
- Elewski BE, Charif MA: Prevalence of onychomycosis in patients attending a dermatology clinic in northeastern Ohio for other conditions. Arch Dermatol133: 1172, 1997.
- Gupta AK, Jain HC, Lynda CW, et al: Prevalence and epidemiology of unsuspected onychomycosis in patients visiting dermatologists’ offices in Ontario, Canada: a multicentre survey of 2001 patients. Int J Dermatol36: 783, 1997.
- Wang DL: Pathogen investigation in onychomycosis: a multicenter study. Chin J Dermatol29: 61, 1996.
- Black JR, Hale WE: Prevalence of foot complaints in the elderly. JAPMA77: 308, 1987.



© 2002 American Podiatric Medical Association