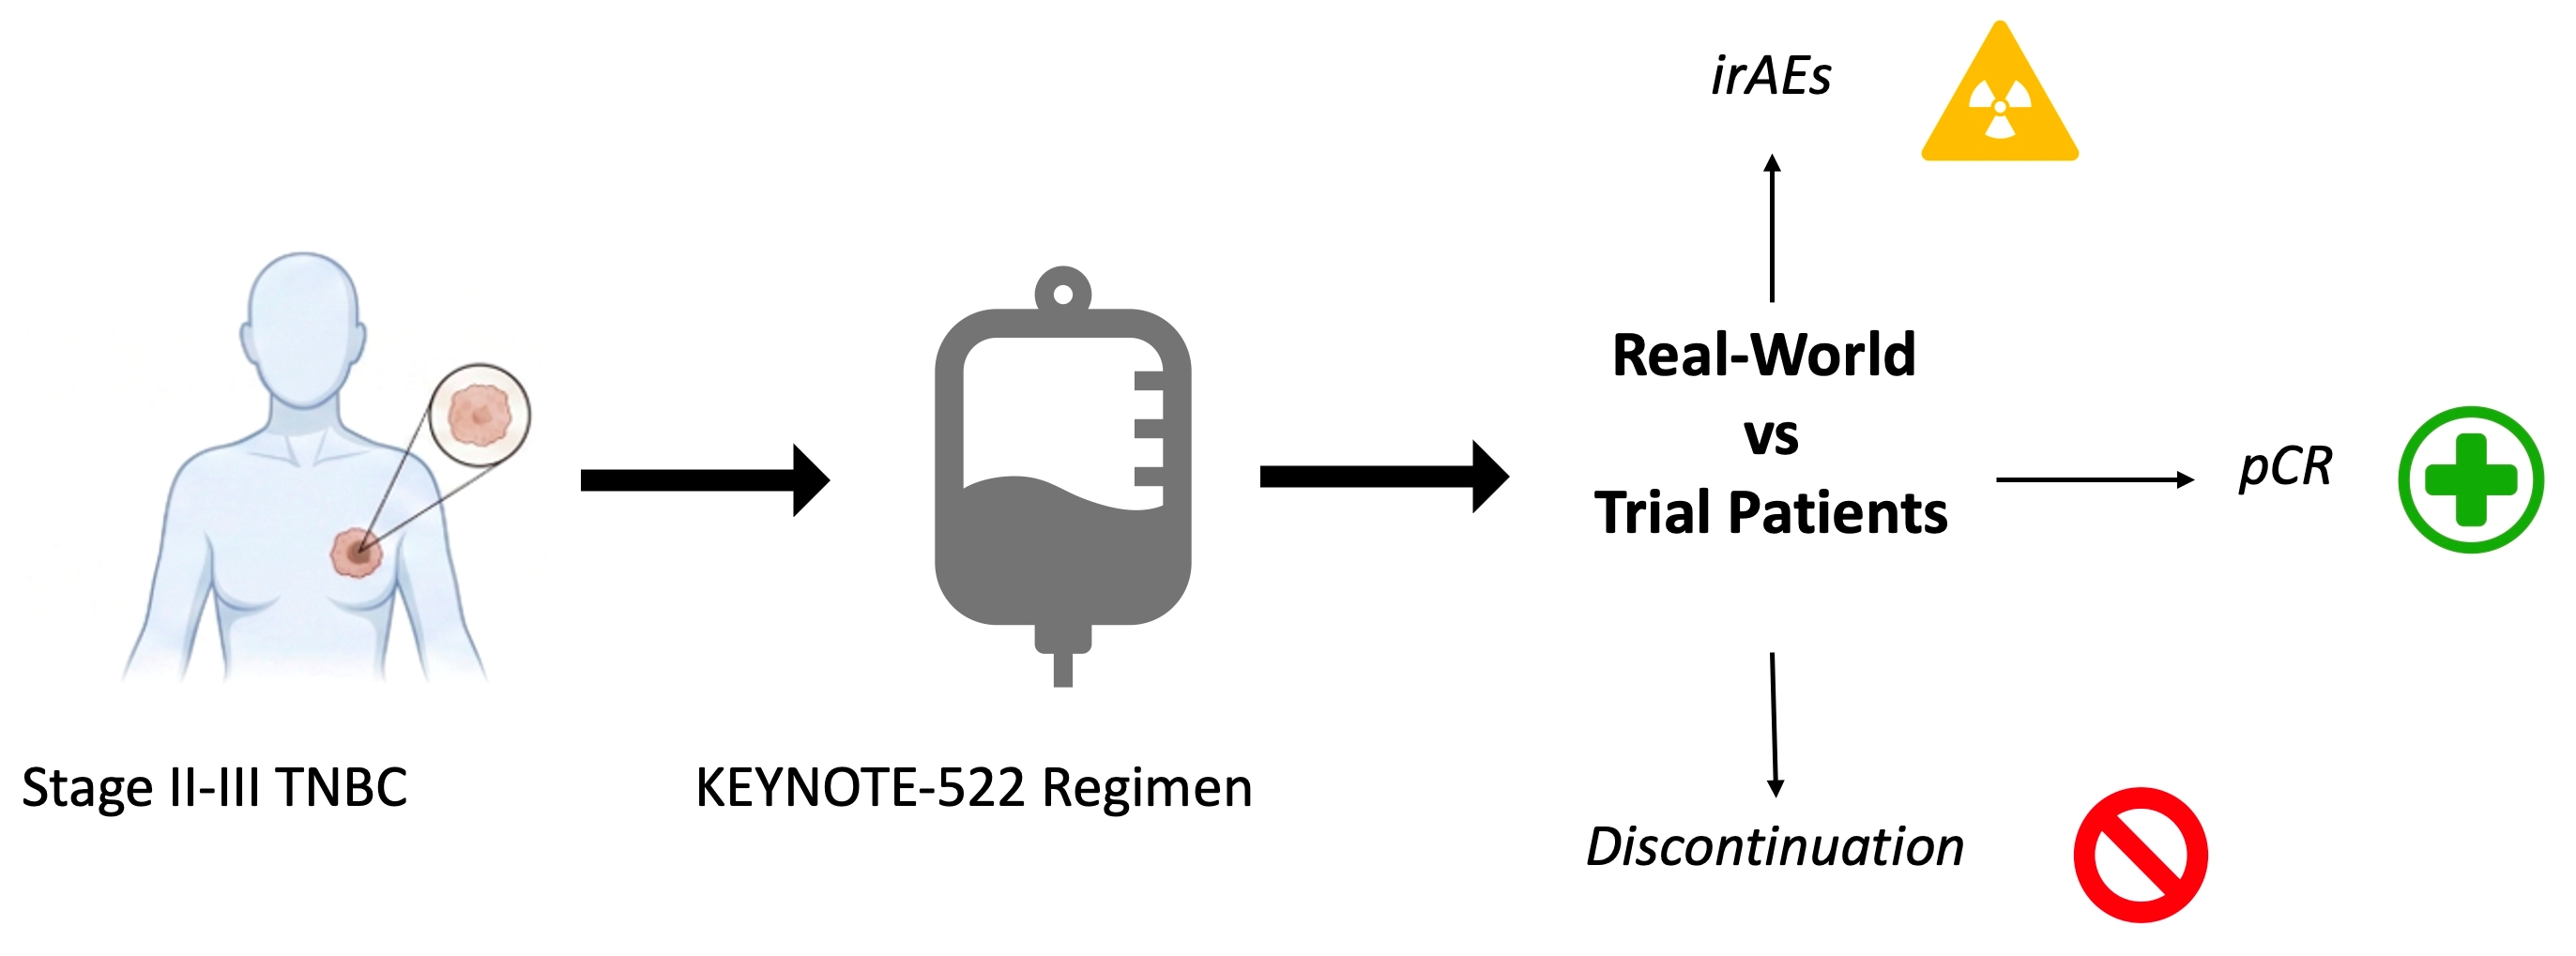
Real-World Toxicities and Outcomes of Pembrolizumab in Early-Stage Triple-Negative Breast Cancer

 , , ,
Simple Summary
Abstract
1. Introduction
2. Materials and Methods
2.1. Study Design and Setting
2.2. Participants
2.3. Data Collection
2.4. Outcomes
2.5. Data Analysis
2.6. Ethics
3. Results
3.1. Participants
3.2. Efficacy
3.3. Immunotherapy-Related Adverse Events
3.4. Neoadjuvant Phase
3.5. Adjuvant Phase
3.6. Treatment Discontinuation
3.7. Hospital Admission
4. Discussion
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Acknowledgments
Conflicts of Interest
Abbreviations
| TNBC | Triple-Negative Breast Cancer |
| KEYNOTE-522 | Name of the Phase III Pembrolizumab Clinical Trial in Early-Stage TNBC |
| irAE/irAEs | Immune-Related Adverse Event(s) |
| pCR | Pathological Complete Response |
| PD-1 | Programmed Cell Death Protein 1 |
| ER | Estrogen Receptor |
| PR | Progesterone Receptor |
| HER2 | Human Epidermal Growth Factor Receptor 2 |
| LHSC | London Health Sciences Centre |
| WRH | Windsor Regional Hospital |
| REDCap | Research Electronic Data Capture |
| AJCC | American Joint Committee on Cancer |
| CTCAE | Common Terminology Criteria for Adverse Events |
| REB | Research Ethics Board |
References
- Foulkes, W.D.; Smith, I.E.; Reis-Filho, J.S. Triple-Negative Breast Cancer. N. Engl. J. Med. 2010, 363, 1938–1948. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumar, P.; Aggarwal, R. An Overview of Triple-Negative Breast Cancer. Arch. Gynecol. Obstet. 2016, 293, 247–269. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Howlader, N.; Cronin, K.A.; Kurian, A.W.; Andridge, R. Differences in Breast Cancer Survival by Molecular Subtypes in the United States. Cancer Epidemiol. Biomark. Prev. 2018, 27, 619–626. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bauer, K.R.; Brown, M.; Cress, R.D.; Parise, C.A.; Caggiano, V. Descriptive Analysis of Estrogen Receptor (ER)-negative, Progesterone Receptor (PR)-negative, and HER2-negative Invasive Breast Cancer, the So-called Triple-negative Phenotype: A Population-based Study from the California Cancer Registry. Cancer 2007, 109, 1721–1728. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schmid, P.; Cortes, J.; Pusztai, L.; McArthur, H.; Kümmel, S.; Bergh, J.; Denkert, C.; Park, Y.H.; Hui, R.; Harbeck, N.; et al. Pembrolizumab for Early Triple-Negative Breast Cancer. N. Engl. J. Med. 2020, 382, 810–821. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schmid, P.; Cortes, J.; Dent, R.; Pusztai, L.; McArthur, H.; Kümmel, S.; Bergh, J.; Denkert, C.; Park, Y.H.; Hui, R.; et al. Event-Free Survival with Pembrolizumab in Early Triple-Negative Breast Cancer. N. Engl. J. Med. 2022, 386, 556–567. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schmid, P.; Cortes, J.; Dent, R.; McArthur, H.; Pusztai, L.; Kümmel, S.; Denkert, C.; Park, Y.H.; Hui, R.; Harbeck, N.; et al. Overall Survival with Pembrolizumab in Early-Stage Triple-Negative Breast Cancer. N. Engl. J. Med. 2024, 391, 1981–1991. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sherman, R.E.; Anderson, S.A.; Dal Pan, G.J.; Gray, G.W.; Gross, T.; Hunter, N.L.; LaVange, L.; Marinac-Dabic, D.; Marks, P.W.; Robb, M.A.; et al. Real-World Evidence—What Is It and What Can It Tell Us? N. Engl. J. Med. 2016, 375, 2293–2297. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, F.; Yang, S.; Palmer, N.; Fox, K.; Kohane, I.S.; Liao, K.P.; Yu, K.-H.; Kou, S.C. Real-World Data Analyses Unveiled the Immune-Related Adverse Effects of Immune Checkpoint Inhibitors across Cancer Types. npj Precis. Oncol. 2021, 5, 82. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jayan, A.; Sukumar, J.S.; Fangman, B.; Patel, T.; Raghavendra, A.S.; Liu, D.; Pasyar, S.; Rauch, R.; Basen-Enguist, K.; Tripathy, D.; et al. Real-World Immune-Related Adverse Events in Patients with Early Triple-Negative Breast Cancer Who Received Pembrolizumab. JCO Oncol. Pract. 2025, 21, 1265–1273. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Harris, P.A.; Taylor, R.; Minor, B.L.; Elliott, V.; Fernandez, M.; O’Neal, L.; McLeod, L.; Delacqua, G.; Delacqua, F.; Kirby, J.; et al. The REDCap Consortium: Building an International Community of Software Platform Partners. J. Biomed. Inform. 2019, 95, 103208. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Connors, C.; Valente, S.A.; ElSherif, A.; Escobar, P.; Chichura, A.; Kopicky, L.; Roesch, E.; Ritner, J.; McIntire, P.; Wu, Y.; et al. Real-World Outcomes with the KEYNOTE-522 Regimen in Early-Stage Triple-Negative Breast Cancer. Ann. Surg. Oncol. 2025, 32, 912–921. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mezzanotte-Sharpe, J.; Hsu, C.-Y.; Choi, D.; Sheffield, H.; Zelinskas, S.; Proskuriakova, E.; Montalvo, M.; Lee, D.S.; Whisenant, J.G.; Gaffney, K.; et al. Adverse Events in Patients Treated with Neoadjuvant Chemo/Immunotherapy for Triple Negative Breast Cancer: Results from Seven Academic Medical Centers. Breast Cancer Res. Treat. 2025, 213, 71–80. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Andrade, M.d.O.; Gutierres, I.G.; Tavares, M.C.; de Sousa, I.M.; Balint, F.C.; Marin Comini, A.C.; Gouveia, M.C.; Bines, J.; Madasi, F.; Ferreira, R.D.P.; et al. Immune-Related Adverse Events among Patients with Early-Stage Triple-Negative Breast Cancer Treated with Pembrolizumab plus Chemotherapy: Real-World Data from the Neo-Real/GBECAM 0123 Study. Breast Edinb. Scotl. 2025, 83, 104473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Luoma, A.M.; Suo, S.; Wang, Y.; Gunasti, L.; Porter, C.B.M.; Nabilsi, N.; Tadros, J.; Ferretti, A.P.; Liao, S.; Gurer, C.; et al. Tissue-Resident Memory and Circulating T Cells Are Early Responders to Pre-Surgical Cancer Immunotherapy. Cell 2022, 185, 2918–2935.e29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sinicrope, F.A.; Turk, M.J. Immune Checkpoint Blockade: Timing Is Everything. J. Immunother. Cancer 2024, 12, e009722. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arora, A.; Seenu, V.; Parshad, R.; Bansal, V.K.; Dhar, A.; Mathur, S.; Tanwar, P.; Mishra, P.; Kataria, K.; Suhani; et al. A Phase II, Randomized, Open-Labeled Study to Evaluate Low-Dose Pembrolizumab in Addition to Neoadjuvant Chemotherapy for Triple-Negative Breast Cancer (TNBC). Trials 2025, 26, 73. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McKeon, J.; Daniels, E.; Halstead, A.; Machado, C.; Potter, S.; Strawson-Smith, T.; Okines, A.; Mcintosh, S.; Tovey, H.; Robinson, T.; et al. UK Real-World Evidence on Pembrolizumab and Neoadjuvant Chemotherapy for Early-Stage Triple-Negative Breast Cancer. ESMO Real World Data Digit. Oncol. 2026, 11, 100664. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rached, L.; Peyre-Pradat, F.; Spotti, M.; Baldini, C.; Laparra, A.; Lambotte, O.; Sakkal, M.; Perret, A.; Viansone, A.; Michiels, S.; et al. Real-World Safety and Effectiveness of Neoadjuvant Chemotherapy Combination with Pembrolizumab in Triple-Negative Breast Cancer. ESMO Real World Data Digit. Oncol. 2024, 5, 100061. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Le, T.K.; Brown, I.; Goldberg, R.; Taylor, M.T.; Deng, J.; Parthasarathy, V.; Bordeaux, Z.A.; Alphonse, M.P.; Kwatra, M.M.; Naranbhai, V.; et al. Cutaneous Toxicities Associated with Immune Checkpoint Inhibitors: An Observational, Pharmacovigilance Study. J. Investig. Dermatol. 2022, 142, 2896–2908.e4. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wongvibulsin, S.; Pahalyants, V.; Kalinich, M.; Murphy, W.; Yu, K.-H.; Wang, F.; Chen, S.T.; Reynolds, K.; Kwatra, S.G.; Semenov, Y.R. Epidemiology and Risk Factors for the Development of Cutaneous Toxicities in Patients Treated with Immune-Checkpoint Inhibitors: A United States Population-Level Analysis. J. Am. Acad. Dermatol. 2022, 86, 563–572. [Google Scholar] [CrossRef] [Scilit]
- Gumusay, O.; Callan, J.; Rugo, H.S. Immunotherapy Toxicity: Identification and Management. Breast Cancer Res. Treat. 2022, 192, 1–17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maunu, M.; Lähteenmaa, J.; Karihtala, P.; Tuohinen, S.; Laaksolilja, J.; Ståhls, A.; Meretoja, T.; Mattson, J. Real-World Outcome of Neoadjuvant Therapy with or without Pembrolizumab for Triple-Negative Breast Cancer. Acta Oncol. 2026, 65, 44896. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marhold, M.; Udovica, S.; Halstead, A.; Hirdler, M.; Ferner, M.; Wimmer, K.; Bago-Horvath, Z.; Exner, R.; Fitzal, F.; Strasser-Weippl, K.; et al. Emergence of Immune-Related Adverse Events Correlates with Pathological Complete Response in Patients Receiving Pembrolizumab for Early Triple-Negative Breast Cancer. Oncoimmunology 2023, 12, 2275846. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bischoff, H.; Somme, L.; Petit, T. Optimizing Post-Neoadjuvant Treatment in Early Triple-Negative Breast Cancer. Cancers 2025, 17, 3288. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Winchester, D.J.; Singh, L.; Edge, S.B.; Allison, K.H.; Barlow, W.E.; Bossuyt, V.; Chavez-MacGregor, M.; Conant, E.F.; Connolly, J.L.; De Los Santos, J.F.; et al. Novel Postneoadjuvant Prognostic Breast Cancer Staging System. J. Clin. Oncol. 2025, 43, 1948–1960. [Google Scholar] [CrossRef] [Scilit] [PubMed]

| Characteristics | Real-World (N = 79) | KEYNOTE-522 (N = 784) |
|---|---|---|
| Age | ||
| Median (range)—yr | 53 (27–79) | 49 (22–80) |
| <65 yr—no. (%) | 62 (78.5) | 701 (89.4) |
| Menopausal status—no. (%) | ||
| Premenopausal | 29 (36.7) | 438 (55.9) |
| Postmenopausal | 50 (63.3) | 345 (44.0) |
| Primary tumor classification—no. (%) | ||
| T1 to T2 | 59 (74.7) | 580 (74.0) |
| T3 to T4 | 20 (25.3) | 204 (26.0) |
| Nodal involvement—no. (%) | ||
| Positive | 46 (58.2) | 405 (51.7) |
| Negative | 33 (41.8) | 379 (48.3) |
| Overall disease stage—no. (%) | ||
| Stage II | 41 (51.9) | 590 (75.3) |
| Stage III | 38 (48.1) | 194 (24.7) |
| HER2 status score—no. (%) | ||
| 0–1 | 60 (75.9) | 595 (75.9) |
| 2+ | 19 (24.1) | 188 (24.0) |
| Event | Real-World (N = 79) | KEYNOTE-522 (N = 781) |
|---|---|---|
| Arthritis | 2 (2.5%) | 0 |
| Neurotoxicity | 1 (1.3%) | 0 |
| Dermatitis | 12 (15.2%) | 34 (4.4%) |
| Hypothyroidism | 5 (6.3%) | 107 (13.7%) |
| Colitis | 4 (5.1%) | 13 (1.7%) |
| Myositis | 2 (2.5%) | 3 (0.4%) |
| Renal/Nephritis | 1 (1.3%) | 7 (0.9%) |
| Adrenal insufficiency | 1 (1.3%) | 18 (2.3%) |
| Hepatitis | 1 (1.3%) | 11 (1.4%) |
| Pneumonitis | 1 (1.3%) | 10 (1.3%) |
| Hyperthyroidism | 0 | 36 (4.6%) |
| Diabetes | 0 | 2 (0.3%) |
| Hypophysitis | 0 | 14 (1.8%) |
| Event | Real-World (N = 79) | KEYNOTE-522 (N = 781) |
|---|---|---|
| Arthritis | 1 (1.3%) | 0 |
| Neurotoxicity | 0 | 0 |
| Dermatitis | 2 (2.5%) | 30 (3.8%) |
| Hypothyroidism | 0 | 3 (0.4%) |
| Colitis | 2 (2.5%) | 7 (0.9%) |
| Myositis | 0 | 0 |
| Renal/Nephritis | 1 (1.3%) | 7 (0.9%) |
| Adrenal insufficiency | 0 | 10 (1.3%) |
| Hepatitis | 0 | 9 (1.2%) |
| Pneumonitis | 0 | 3 (0.4%) |
| Hyperthyroidism | 0 | 2 (0.3%) |
| Diabetes | 0 | 2 (0.3%) |
| Hypophysitis | 0 | 8 (1.0%) |
| Event | Real-World (N = 68) | KEYNOTE-522 (N = 547) |
|---|---|---|
| Arthritis | 1 (1.5%) | 0 |
| Neurotoxicity | 3 (4.4%) | 0 |
| Dermatitis | 5 (7.4%) | 9 (1.6%) |
| Hypothyroidism | 8 (11.8%) | 10 (1.8%) |
| Colitis | 5 (7.4%) | 2 (0.4%) |
| Myositis | 1 (1.5%) | 1 (0.2%) |
| Renal/Nephritis | 0 | 1 (0.2%) |
| Adrenal insufficiency | 2 (2.9%) | 3 (0.5%) |
| Hepatitis | 0 | 0 |
| Pneumonitis | 1 (1.5%) | 5 (0.9%) |
| Hyperthyroidism | 0 | 4 (0.7%) |
| Diabetes | 1 (1.5%) | 1 (0.2%) |
| Hypophysitis | 1 (1.5%) | 0 |
| Event | Real-World (N = 68) | KEYNOTE-522 (N = 547) |
|---|---|---|
| Arthritis | 0 | 0 |
| Neurotoxicity | 1 (1.5%) | 0 |
| Dermatitis | 0 | 4 (0.7%) |
| Hypothyroidism | 1 (1.5%) | 3 (0.4%) |
| Colitis | 1 (1.5%) | 1 (0.2%) |
| Myositis | 0 | 0 |
| Renal/Nephritis | 0 | 0 |
| Adrenal insufficiency | 1 (1.5%) | 0 |
| Hepatitis | 0 | 0 |
| Pneumonitis | 1 (1.5%) | 2 (0.4%) |
| Hyperthyroidism | 0 | 0 |
| Diabetes | 0 | 1 (0.2%) |
| Hypophysitis | 0 | 0 |
| Characteristic | Value |
|---|---|
| Total number of patients with discontinuation | 18 (22.8%) |
| Stage at diagnosis | |
| Stage II | 8 (44.4%) |
| Stage III | 10 (55.6%) |
| Mean % of planned immunotherapy received | 46.2% ± 21.6 |
| Timing of discontinuation | |
| Neoadjuvant phase | 11 (61.1%) |
| Adjuvant phase | 7 (38.9%) |
| irAEs leading to discontinuation | |
| Colitis | 8 (44.4%) |
| Dermatitis | 5 (27.8%) |
| Hypothyroidism | 3 (16.7%) |
| Adrenal insufficiency | 1 (5.6%) |
| Arthritis | 1 (5.6%) |
| Pathological complete response (pCR) | 15 (83.3%) |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Boujeke, E.J.; Catalan, A.; Arayan, L.; Mina, A.P.; James-McDonald, C.E.; Gupta, R.; Kulkarni, S.; Nasser, A.; Chowdhury, D.; Brackstone, M.; et al. Real-World Toxicities and Outcomes of Pembrolizumab in Early-Stage Triple-Negative Breast Cancer. Curr. Oncol. 2026, 33, 513. https://doi.org/10.3390/curroncol33090513
Boujeke EJ, Catalan A, Arayan L, Mina AP, James-McDonald CE, Gupta R, Kulkarni S, Nasser A, Chowdhury D, Brackstone M, et al. Real-World Toxicities and Outcomes of Pembrolizumab in Early-Stage Triple-Negative Breast Cancer. Current Oncology. 2026; 33(9):513. https://doi.org/10.3390/curroncol33090513
Chicago/Turabian StyleBoujeke, Emmanuel Joran, Aaron Catalan, Laurice Arayan, Alfred Patrick Mina, Christian Edward James-McDonald, Rasna Gupta, Swati Kulkarni, Abdullah Nasser, Deepro Chowdhury, Muriel Brackstone, and et al. 2026. "Real-World Toxicities and Outcomes of Pembrolizumab in Early-Stage Triple-Negative Breast Cancer" Current Oncology 33, no. 9: 513. https://doi.org/10.3390/curroncol33090513
APA StyleBoujeke, E. J., Catalan, A., Arayan, L., Mina, A. P., James-McDonald, C. E., Gupta, R., Kulkarni, S., Nasser, A., Chowdhury, D., Brackstone, M., Mathews, J., & Hamm, C. (2026). Real-World Toxicities and Outcomes of Pembrolizumab in Early-Stage Triple-Negative Breast Cancer. Current Oncology, 33(9), 513. https://doi.org/10.3390/curroncol33090513