Article

Tree Canopy and Self-Reported Mental and Physical Health in Urban Alabama: A Census Tract-Level Ecological Study


1
UAB Marnix E. Heersink School of Medicine, Birmingham, AL 35233, USA
2
Department of Health Policy & Organization, School of Public Health, University of Alabama at Birmingham, Birmingham, AL 35294, USA
3
School of Science and Mathematics, Emporia State University, Emporia, KS 66801, USA
4
Department of Occupational Therapy, School of Health Professions, University of Alabama at Birmingham, Birmingham, AL 35233, USA
*
Author to whom correspondence should be addressed.
Int. J. Environ. Res. Public Health 2026, 23(9), 1143; https://doi.org/10.3390/ijerph23091143
Submission received: 22 July 2026 / Revised: 29 August 2026 / Accepted: 31 August 2026 / Published: 2 September 2026

Highlights

Public health relevance—How does this work relate to a public health issue?
  • This article offers a unique perspective to the field of population health by using new ecological data from the Deep South region of the United States, a region that is understudied in context of urban greenspace.
Public health significance—Why is this work of significance to public health?
  • This article contributes to the field by estimating associations between self-reported health and urban tree canopy, an exposure variable of growing interest in greenspace research.
Public health implications—What are the key implications or messages for practitioners, policymakers, and/or researchers in public health?
  • This article demonstrates employing machine learning techniques to leverage large, publicly available datasets for environmental health research—which is essential in an era of limited research funding in the field.
  • This article provides support for additional funding and city planning efforts to ensure more equitable distribution of the tree canopy in urban Alabama.

Abstract

Background: Urban tree canopy, the proportion of a city’s land surface covered by trees, has been linked to physical and mental health benefits. This association is understudied in the U.S. Deep South despite its high burden of poor health and environmental inequity. This study examined associations between census tract-level tree canopy and self-reported mental and physical health in urban Alabama. Methods: We linked tract-level tree canopy estimates for Alabama metropolitan statistical areas with self-reported health and contextual measures from publicly available data, retaining tree canopy as the exposure of interest. A bootstrap-stabilized penalized variable-selection approach identified covariates from socioeconomic, demographic, housing, transportation, environmental, and health-related measures; we then mapped spatial distributions and fit spatial error multivariable models. Results: A higher proportion of land surface covered by trees was associated with a lower age-adjusted prevalence of adults who report 14 or more days during the past 30 days during which their mental health was not good (estimate: −0.0110; p < 0.001). A higher proportion of land surface covered by trees was also associated with a lower age-adjusted prevalence of adults who report 14 or more days during the past 30 days during which their physical health was not good (estimate: −0.0045; p = 0.002). Spatial error parameters persisted in both models, indicating residual spatial patterning not fully explained by canopy or the selected covariates. Conclusions: The findings extend the urban tree canopy literature to an understudied setting and demonstrate how publicly available tract-level data, combined with machine learning-guided covariate selection and spatial modeling, can generate actionable hypotheses for environmental health and equity research.

1. Introduction

Exposure to the natural environment is increasingly recognized as beneficial to human health, and a growing body of research has demonstrated the extensive health benefits of nature-centered interactions, including improved physical and mental well-being [1]. One component of nature which has proved particularly important to human health is the tree. According to a 2022 study by the USDA Forest Service, it is predicted that 87% of urbanized counties in the U.S. will experience a decline in tree canopy by 2060, with a national drop in urban tree cover from 39.4% to 33.6%; the primary threats to the urban tree canopy include urban expansion, pests, extreme weather events, and changes in climate, such as rising ambient temperatures and projected sea level rise [2]. Trees can provide a range of health benefits in urban areas, such as supporting respiratory health by removing air pollutants, reducing exposure to harmful ultraviolet radiation through shade, mitigating heat-related health risks by lowering urban temperatures, and supporting physical activity by making outdoor environments seem more accessible and inviting [1,3,4,5,6]. Several studies have suggested that urban tree canopy may provide greater benefits than other forms of green space [7], particularly for mental health [8,9,10,11]. At the same time, the distribution of urban tree canopy in the United States is often unequal, and historically marginalized communities, particularly those with predominately minority populations, commonly have less tree canopy than more socioeconomically advantaged communities [12].
This study evaluated the relationship between tree canopy and self-reported health in urban Alabama. This is important for two reasons. First, the Deep South region is an understudied region in the context of environmental health. Alabama consistently ranks among the lowest in the United States for several adverse health outcomes [13]. Redlining, or the discriminatory practice of denying mortgages to individuals who lived in neighborhoods deemed unfavorable by the Home Owners Loan Corporation (HOLC), greatly contributed to the health disparities seen in Alabama cities such as Birmingham by excluding racial minorities from the opportunity of economic growth through homeownership. By withholding the means for generational economic growth from redlined communities, those communities began to accumulate more unfavorable living conditions, such as attracting industries that contributed to greater levels of pollution, having less access to healthcare due to lower rates of health insurance, and accumulating less money for city planning, such as planting urban trees [14]. Redlined areas were also much more likely to become urban heat islands, with significantly greater heat exposure than neighborhoods supported by the HOLC [14]. While Alabama itself is one of the more heavily forested in the nation, its urban areas have substantial disparities in tree canopy [15], with sparser tree canopy closely mirroring historical redlining [15]; evidence suggests that this contributes to higher ambient temperatures in disadvantaged neighborhoods compared to more affluent areas [16]. While many factors associated with systemic inequality in Alabama cities contribute to the adverse health outcomes and wide health disparities in the state, tree canopy itself stands out as an important detail that warrants further exploration. Working towards a more equitable distribution of the tree canopy in urban areas may represent one practical and accessible step toward bridging the gap between complex urban health inequalities.
This study also contributes to the field because it demonstrates how large, publicly available datasets, such as the U.S. Climate Vulnerability Index (CVI), can be leveraged for place-based environmental research using machine learning techniques [17]. The U.S. CVI consolidates nationally comparable census-tract measures across social, health, environmental, infrastructure, and climate domains. While most existing studies in the field select auxiliary covariates a priori [18,19,20], we used the least absolute shrinkage and selection operator (LASSO) to screen a broad set of candidate contextual measures while keeping tree canopy in the model as the primary exposure. This approach is exploratory and hypothesis-generating but allows the analysis to take advantage of rich area-level data and to help navigate the challenges posed by a complex, interrelated, and sometimes unwieldy set of potential covariates. This approach has been established as a useful tool for covariate selection, especially when many potential predictor variables are available [21]. Employing LASSO to screen for covariates from publicly available data may reveal new insights into interactions among tree canopy, health, and census-tract characteristics.
To our knowledge, this is among the first statewide urban census-tract analyses to explore associations between tree canopy and self-reported mental and physical health in Alabama. Its findings help address the paucity of information on this topic in the Deep South region of the United States. By applying new census tract-level data on tree canopy from the state of Alabama to analyze the correlation between health and tree canopy through machine learning techniques, this study offers a unique perspective to the well-established literature on urban greening and public health.

2. Methods

2.1. Study Design and Setting

We first described the spatial distribution of the tree canopy across census tracts in Alabama metropolitan statistical area (MSA) counties. The primary outcome was tract-level self-reported poor mental health. The tree canopy was specified as the primary exposure of interest and was forced into all variable-selection models. Candidate covariates included socioeconomic, demographic, housing, transportation, environmental, and community-contextual measures from the U.S. CVI, a comprehensive environmental and screening tool developed by the Environmental Defense Fund, Texas A&M University, and Darkhorse Analytics [17].
To select covariates for multivariable modeling, we used group minimax concave penalty (MCP) penalized linear regression, a LASSO-related penalized variable-selection approach. Penalized regression adds a penalty term to the regression objective function, which shrinks regression coefficients toward zero. Covariates whose coefficients are shrunk to zero are excluded from the selected model. The tree canopy was specified a priori as the primary exposure and was included as an unpenalized variable so that it remained in all candidate models. The remaining candidate covariates were penalized and subject to selection. We used a group penalty so that grouped predictors (categorical variables) could be selected or removed as a group. The tuning parameter controlling the amount of penalization was selected using the extended Bayesian information criterion (EBIC), which favors models that balance model fit and parsimony [22,23]. To enhance stability, we repeated the variable-selection procedure 200 times using bootstrap resampling. Covariates selected in more than 90% of bootstrap samples were retained in the final model [24,25].
After selecting covariates, we further assessed multicollinearity using variance inflation factors (VIFs). We used VIF > 10 to identify severe multicollinearity and to remove highly collinear variables, while recognizing that VIF values between 5 and 10 may indicate moderate collinearity requiring further inspection [26]. Variables with a high VIF (>10) were removed. Spatial contiguity was defined using queen adjacency based on census tract polygons, allowing tracts sharing either a boundary or vertex to be considered neighbors. We examined global spatial autocorrelation using Moran’s I. Rao’s score diagnostics were used to evaluate spatial error and spatial lag dependence [27]. In secondary analysis, we used self-reported physical health as the outcome and repeated our prior methodology. All analyses were performed using R version 4.4.3 (R Foundation for Statistical Computing, Vienna, Austria). Statistical significance was set at a two-sided p < 0.05.

2.2. Tree Canopy Data

Tree canopy data, measured at the census tract level, were obtained from the Social Determinants of Health (SDH) Core Program at the University of Alabama at Birmingham [28]. The tree canopy was calculated using the U.S. National Land Cover Database (NLCD) Tree Canopy Cover produced by the Multi-Resolution Land Characteristics Consortium for the National Land Cover Database. In the NLCD, tree canopy coverage represents the proportion of land surface covered by trees, measured at a 30 m resolution for each pixel, between 2011 and 2021. Pixel-level averages were calculated for each census tract using the zonal statistics as a table tool in ArcGIS Pro 3.5.0; 0% indicated no trees present, while 100% indicated full tree canopy coverage.

2.3. Mental Health and Physical Health Data

Self-reported mental health and physical health data were obtained from the U.S. Climate Vulnerability Index (CVI) [17]. Mental health data were listed as “self-reported mental health,” which was defined as the “age-adjusted prevalence of adults who report 14 or more days during the past 30 days during which their mental health was not good.” Therefore, higher percentages in the dataset indicated poorer mental health. The definition of mental health was subjective and included factors such as stress, depression, and problems with emotions. The detailed probability of adults aged 18 years or older who report poor mental health for 14 or more days during the past 30 days was determined by using data from the Centers for Disease Control and Prevention’s Behavioral Risk Factor Surveillance System (2018, 2019), U.S. Census Bureau data from 2010, and American Community Survey (ACS) estimates from 2015–2019 or 2014–2018 to create a multilevel regression and post-stratification approach.
Physical health data were listed as “self-reported physical health,” which was defined as the “age-adjusted prevalence of adults who report 14 or more days during the past 30 days during which their physical health was not good.” Therefore, higher percentages in the dataset indicated poorer physical health. The definition of physical health was subjective and included both physical illness and injury. The detailed probability was calculated using the same model and datasets as self-reported mental health.

3. Results

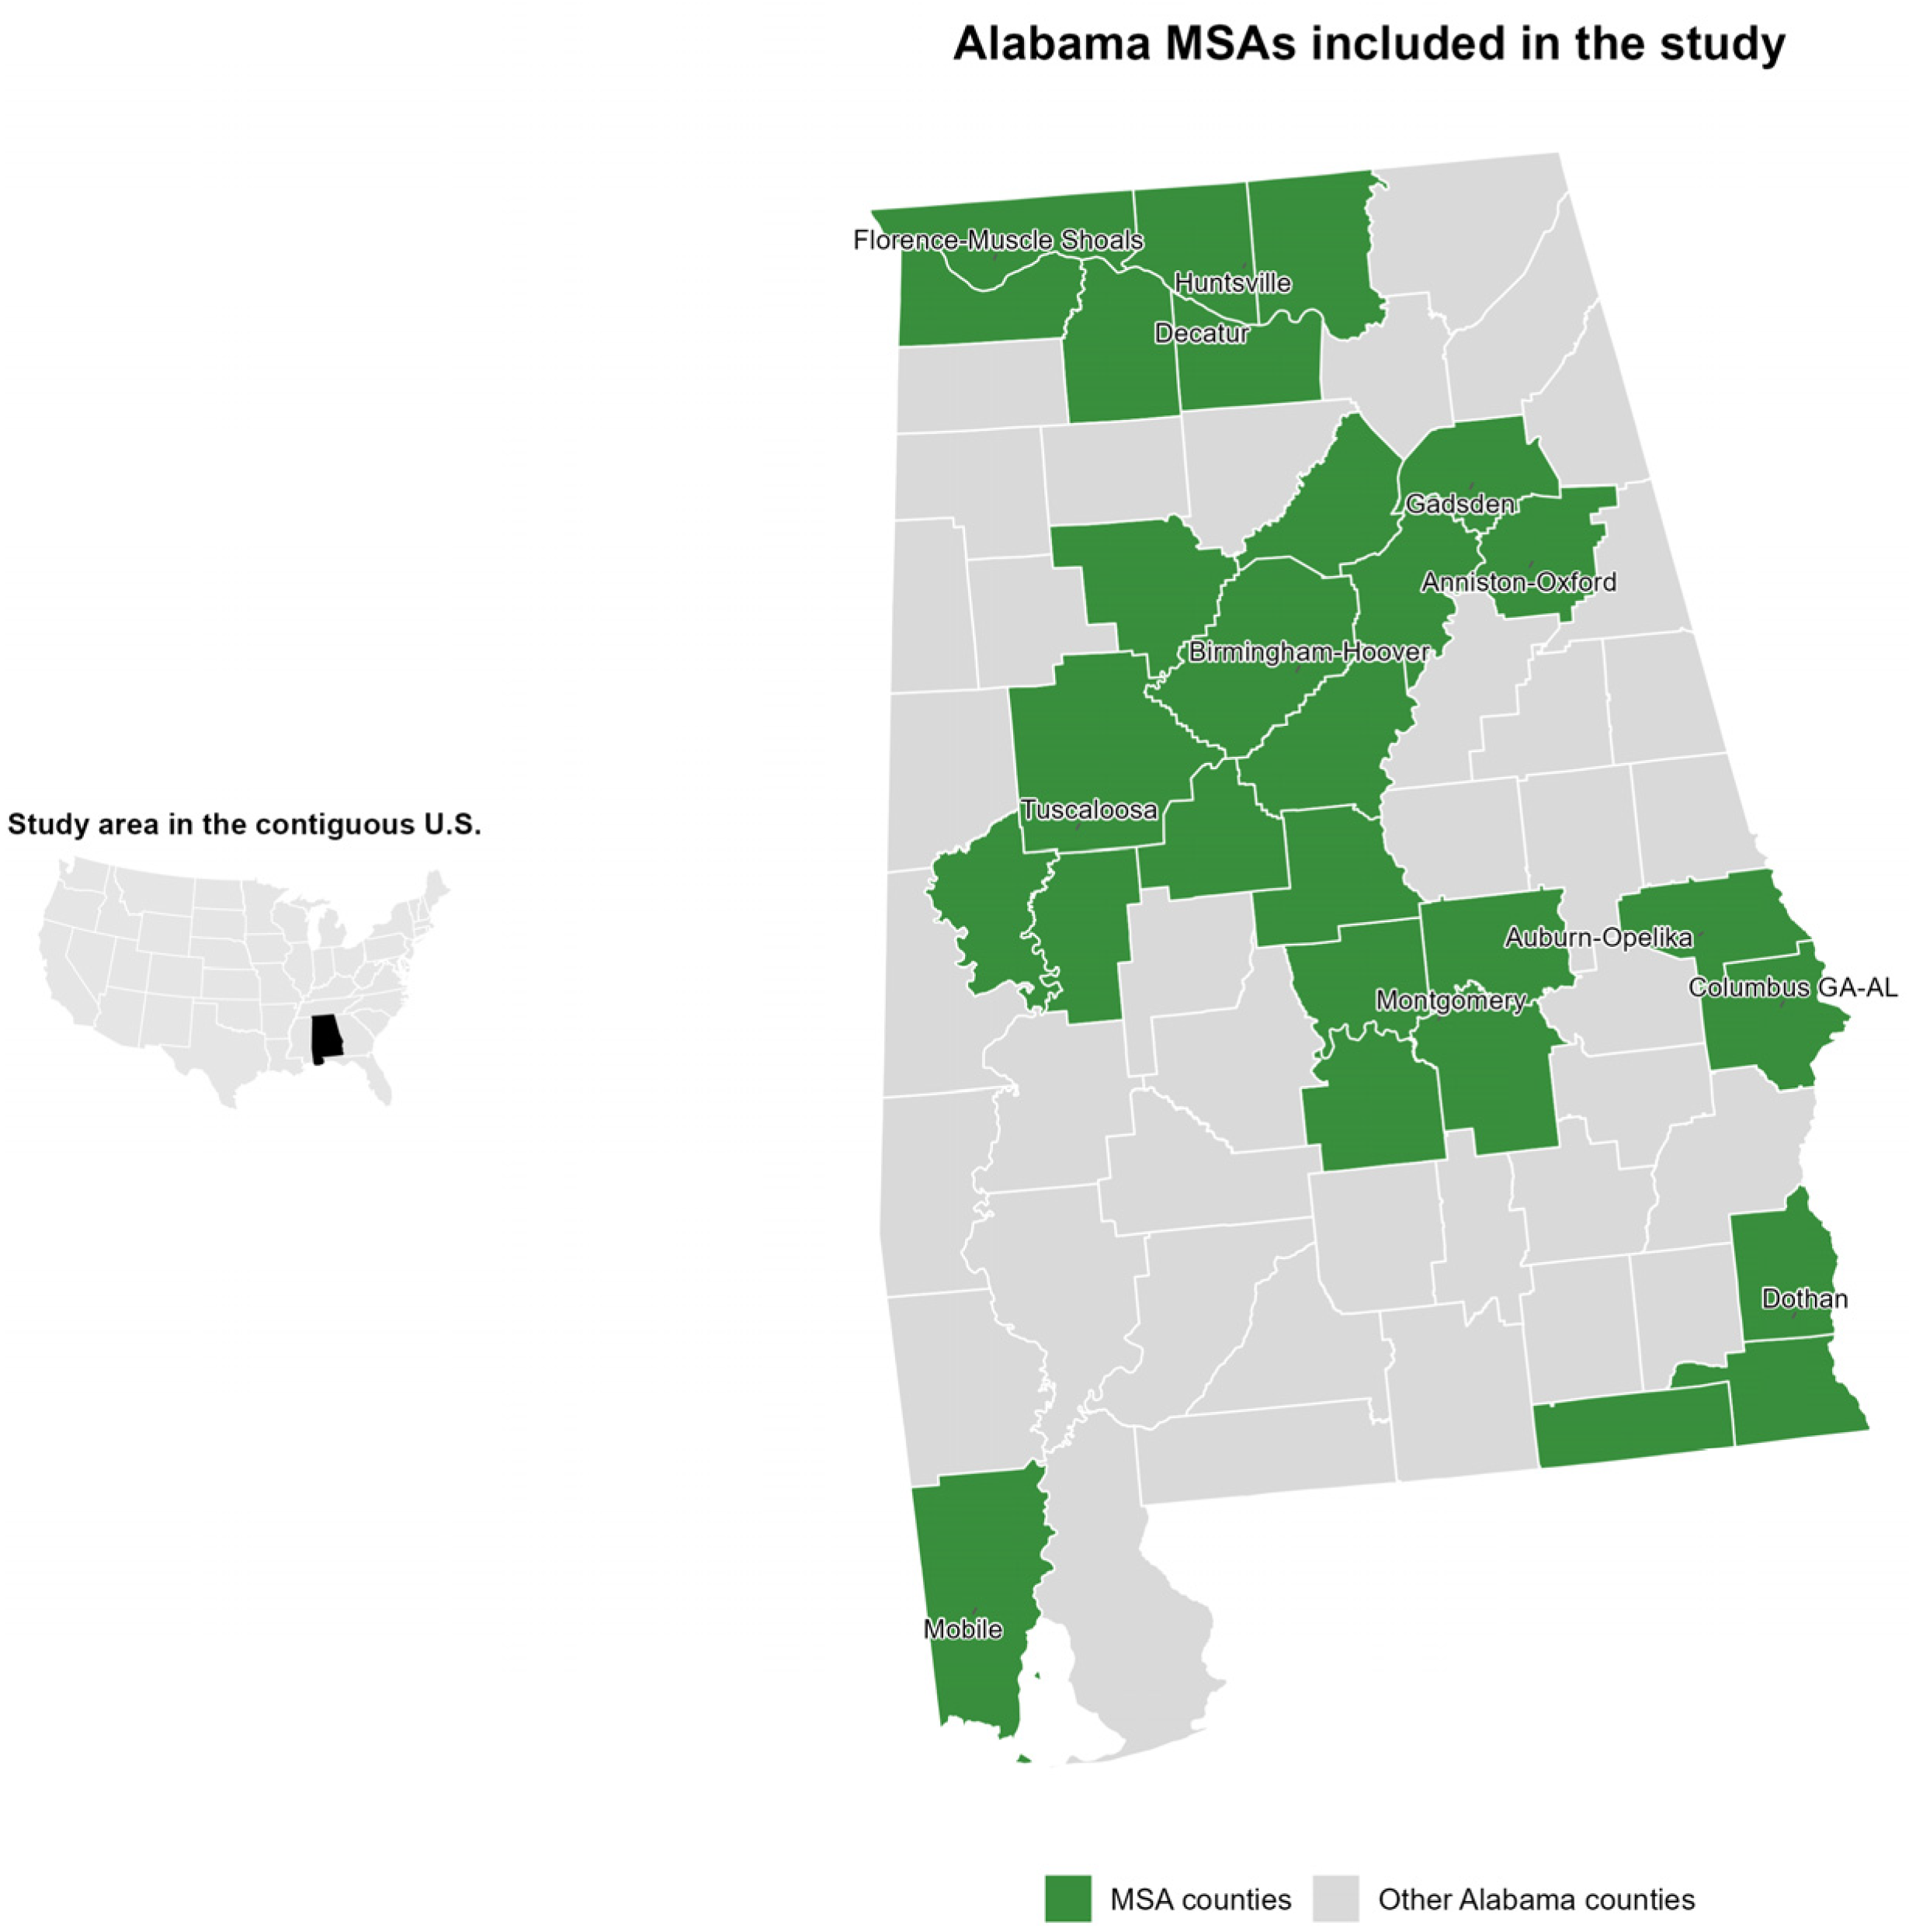
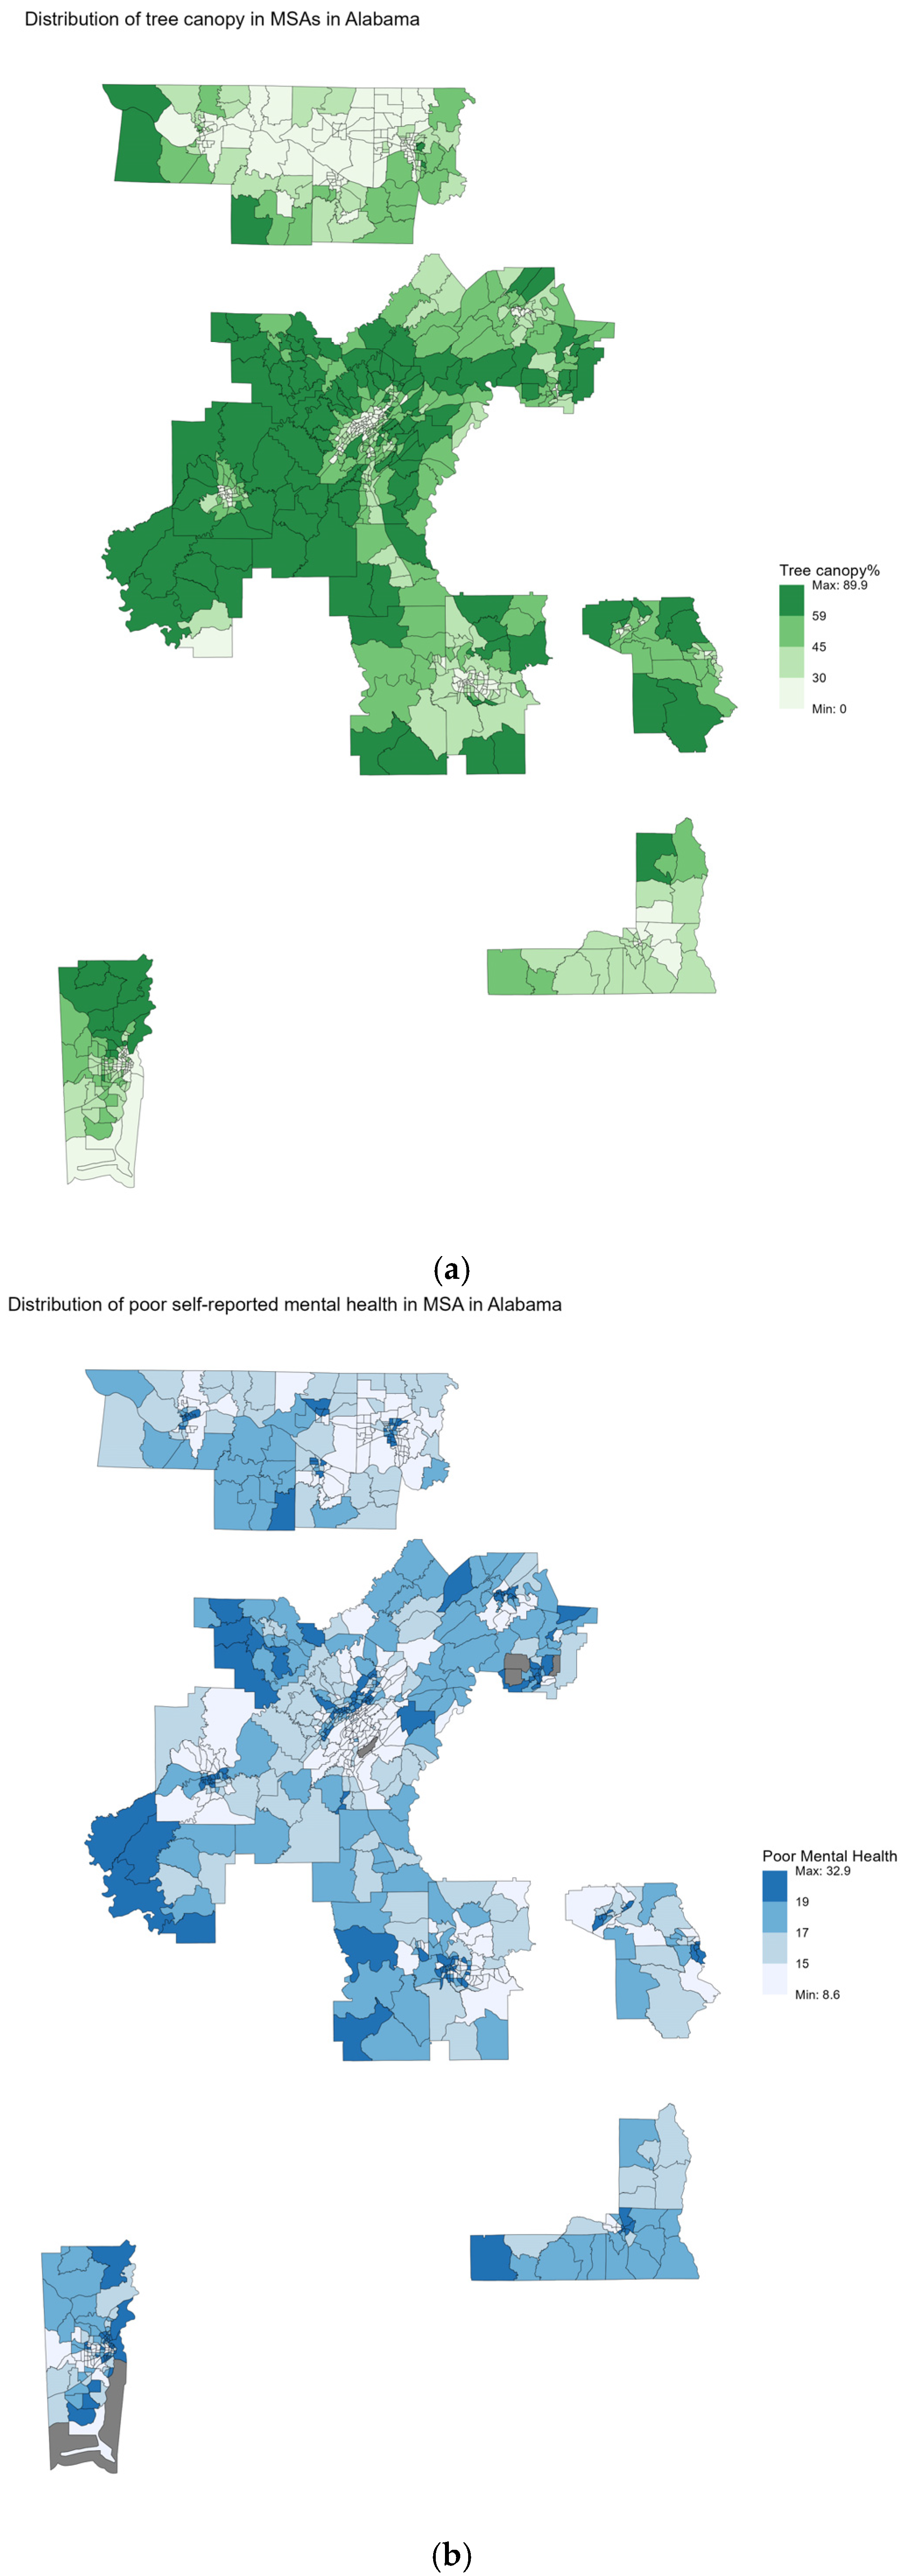
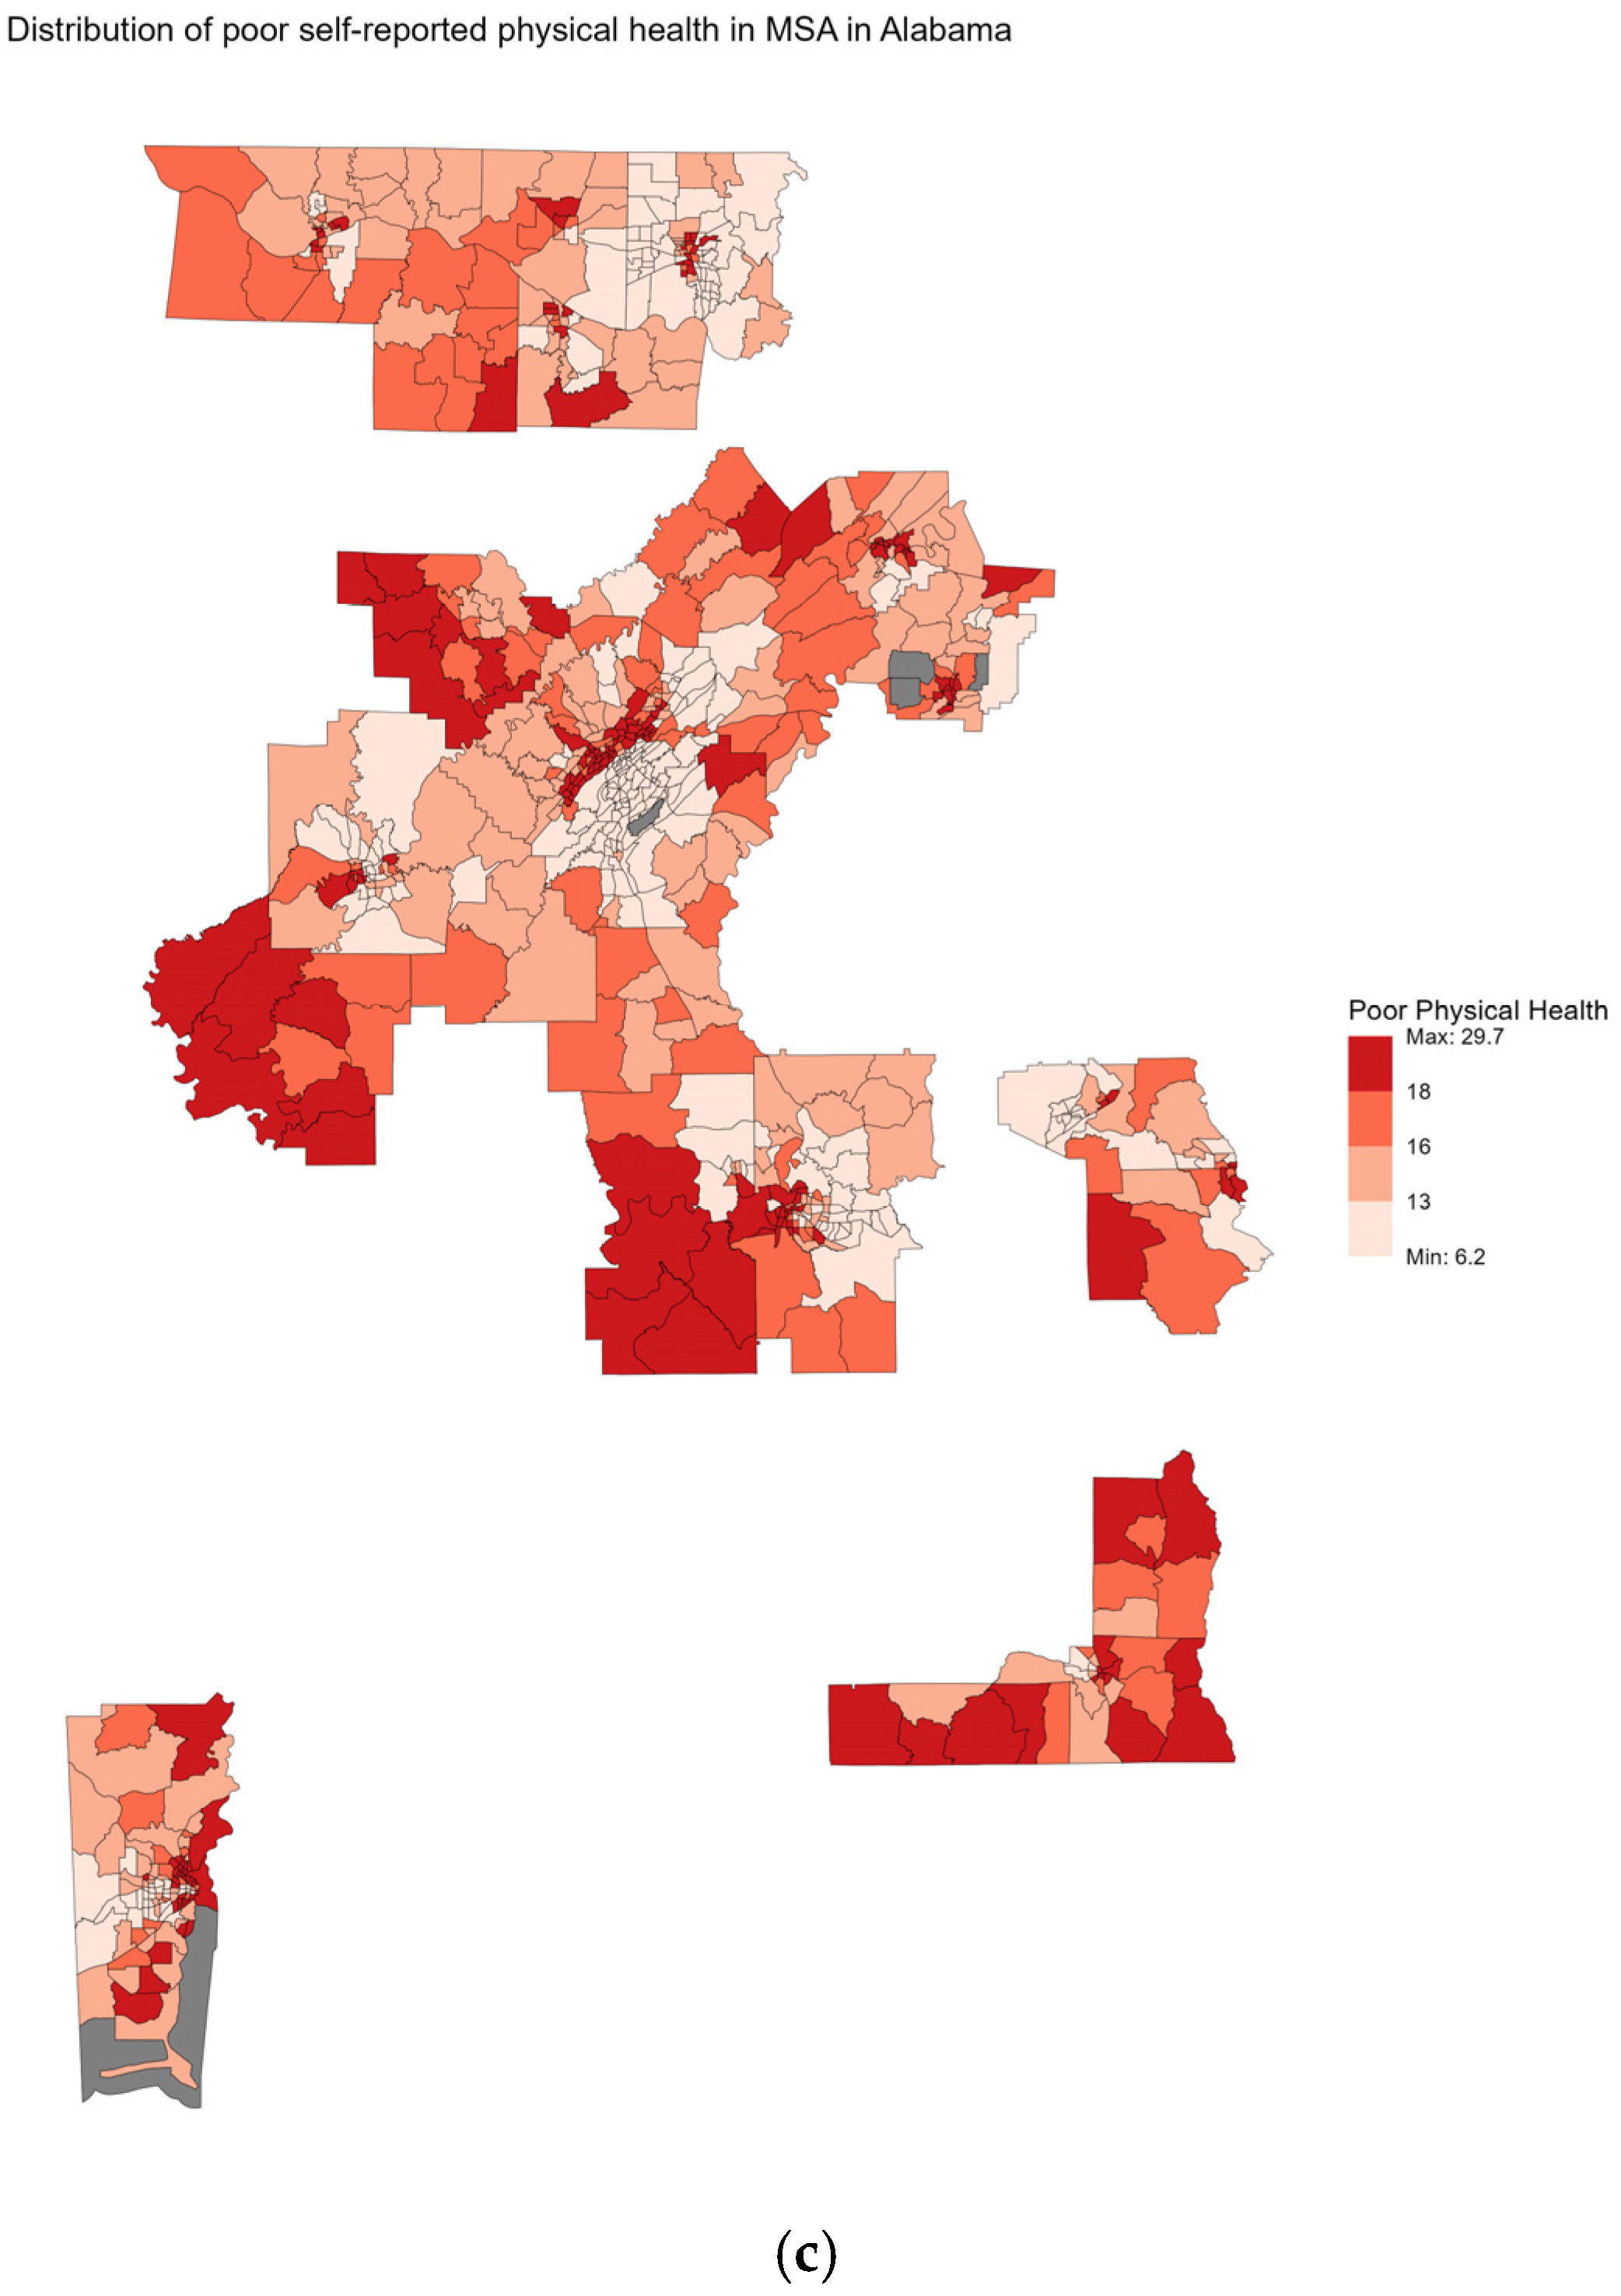
Geographic models were created to demonstrate the census tract-level spatial distribution of the tree canopy in Alabama and self-reported poor mental and physical health across the state (Figure 1a–c). Figure 2 showed the MSAs of Alabama included in this analysis.
After employing LASSO with bootstrap resampling, the following variables were selected for the self-reported mental health outcome, in addition to tree canopy: current adult asthma, low income, minority, annualized drought frequency, no high school diploma, high blood pressure, routine doctor visits, and mammogram screening. High blood pressure was removed after assessing multicollinearity because it had a VIF of >10 (Table 1). A list of the final covariates, as selected through machine learning techniques, is given in Table 2.
Global Moran’s I indicated statistically significant positive global spatial autocorrelation (Moran’s I = 0.249, p < 0.001). Since the magnitude of Moran’s I depends on the spatial weights matrix and should not be interpreted using a universal threshold, spatial model specification was guided primarily by Rao’s score diagnostics for spatial error and spatial lag dependence. Rao’s score diagnostics supported spatial error dependence. The spatial error test was highly significant (RSerr = 143.63, p < 0.001), and the adjusted spatial error test remained highly significant (adjRSerr = 142.66, p < 0.001), supporting the use of a spatial error model (SEM). In contrast, spatial lag dependence was not statistically significant.
In the SEM, tree canopy was inversely associated with self-reported poor mental health, meaning an increase in tree canopy was associated with better self-reported mental health. The relationship between tree canopy and self-reported mental health was statistically significant (Table 3). While the relationship was statistically significant, absolute changes in predicted prevalence were modest. For interpretability, a 10-percentage-point increase in tree canopy was associated with an estimated 0.11-percentage-point decrease in the prevalence of self-reported poor mental health. A quadratic term for tree canopy in the primary mental health model was tested, but it was not supported by the data, as the quadratic term was not significant (p = 0.59), model fit did not improve (AIC 1988.6 vs. 1986.9), and the likelihood-ratio test was not significant (p = 0.60).
The covariates current adult asthma, low income, annualized drought frequency, and mammogram screening were positively associated with self-reported poor mental health, whereas minority and routine doctor visits were inversely associated with the outcome. The covariate “no high school diploma” was not statistically significant. Table 3 outlines the variable associations with self-reported poor mental health. It also demonstrates that the spatial error parameter remained statistically significant, indicating residual spatial autocorrelation after covariate adjustment.
In our secondary analysis of self-reported poor physical health, we applied a similar LASSO and bootstrap approach to select variables and fit an SEM. The final list of covariates for the secondary analysis, as well as their definitions as found in the CVI, can be seen in Table 4.
In the SEM for self-reported physical health, tree canopy was inversely associated with self-reported poor physical health, meaning an increase in tree canopy was associated with better self-reported physical health. The relationship between the tree canopy and self-reported physical health was statistically significant (Table 5). While the relationship was statistically significant, absolute changes in predicted prevalence were modest—similar to the results seen in the primary analysis. The results indicate that a 10-percentage-point increase in tree canopy corresponded to an estimated 0.045-percentage-point decrease in the prevalence of self-reported poor physical health. The interpretable change in prevalence from the secondary analysis was notably more modest than that seen in the primary analysis.
The covariates chronic obstructive pulmonary disease (COPD), minority, routine doctor visits, and low income were positively associated with worse self-reported physical health. Age 65 or older and age 17 or younger were also negatively associated with poor self-reported physical health, while age 17 or younger was not significant. As outlined in Table 5, the spatial error parameter was statistically significant, indicating residual spatial autocorrelation after covariate adjustment. Overall, the findings from the secondary analysis corroborated previous findings from the primary analysis. Both findings showed a statistically significant positive correlation between self-reported health and tree canopy.

4. Discussion

This ecological study explored the relationship between the urban tree canopy and self-reported health across census tracts in urban areas of Alabama. A higher tree canopy was associated with a lower prevalence of self-reported frequent poor mental health and frequent poor physical health after adjustment for machine learning-selected contextual covariates and spatial dependence. The magnitude of the association—as well as the interpretable changes in prevalence—was modest, but the direction was consistent across both outcomes. As this study was ecological and cross-sectional, these findings should be interpreted as tract-level associations rather than evidence of individual-level or causal effects.
Overall, results from Alabama were consistent with a growing body of literature associating a greater urban tree canopy coverage with more favorable mental and physical health. Studies in other regions have linked the urban tree canopy to several health outcomes. A recent analysis in Australia found that a 10% increase in tree canopy among women was associated with lower odds of prevalent and incident social loneliness [8]. A study in Southern California found strong protective effects of the tree canopy against postpartum depression (OR = 0.98, 95% CI: 0.97–0.99) [10], and a study in Kentucky found that reductions in tree canopy cover below 10% in a particular zip code were associated with an increase in suicide rates [11]. Regarding physical health, in the secondary analysis, our findings of a significant association between self-reported physical health and the tree canopy in Alabama also supported previous findings from other regions. A 2024 health assessment found that a 20% urban tree canopy attainment in Denver, CO would avert 200 premature deaths and 4.1 cases of stroke annually; similarly, a 25% urban tree canopy attainment in Phoenix, AZ was predicted to prevent 368 premature deaths and 8.7 cases of stroke [29]. A 2024 analysis across 5723 U.S. municipalities estimated that an ambitious reforestation program across the U.S. involving 1.2 billion trees could reduce heat-related mortality by an additional 464  ±  89 people and annual heat-related morbidity by 80,785  ±  6110 cases [5]. The proposed mechanisms for the tree canopy’s positive effect on health, even when adjusting for confounding, could not be tested directly in the present study but include heat mitigation, air pollution reduction, opportunities for physical activity, restoration from stress, and social connection. The current findings extend this work to urban census tracts in Alabama, a Deep South state where the tree canopy, environmental conditions, and health inequities may intersect in locally important ways.
This study also makes a methodological and practical contribution. The study combined publicly available contextual data from the U.S. CVI with newly developed tree canopy data from the SDH Core at the University of Alabama at Birmingham. This approach illustrates how publicly available data sources can be leveraged for place-based environmental health research, particularly when primary data collection is not feasible, or if funding for such research continues to decline. Machine learning techniques were used to select relevant covariates for analysis from large datasets. Screening covariates with machine learning may improve efficiency, particularly when working with highly correlated and complex datasets; a 2024 analysis found that the machine learning technique ridge regression could be approximately 20,000 times faster than stepwise covariate modeling (SCM), and prescreening with a machine learning algorithm reduced the SCM runtime by 42.86% [30]. Among the machine learning techniques considered, LASSO has been suggested in prior studies to provide strong predictive covariate selection; in a study of patients with metastatic colorectal cancer receiving bevacizumab treatment, prediction models of progression-free survival and overall survival showed that models using the LASSO technique had the lowest predictive error compared to other machine learning techniques, and it also had a higher concordance index, a measure of how well a model predicts the order in which events happen (LASSO increased concordance index from 0.727 to 0.754 for overall survival and from 0.972 to 0.979 for progression-free survival) [31]. While the machine learning approach does not replace theory-driven model building, it can help researchers identify contextual variables from a broad field of complex and interrelated socioeconomic, demographic, health, and environmental measures for subsequent spatial modeling. If using machine learning techniques alongside theory-driven modeling, machine learning techniques may be most useful as a prescreening tool for large datasets with multiple confounding variables, such as the datasets used in this study.
The results for the selected covariates are largely consistent with the literature. The associations of living with asthma, poor mental health [32,33], or conditions such as COPD and poor physical health [34] are well-established. Unsurprisingly, census tracts that ranked higher in percentiles of low income reported a higher frequency of poor physical and mental health, supporting the well-established correlations between low income and poor health [35,36,37]. We conjecture that the low income covariate reflects a range of socio-economic deprivation, stress, and lack of access to healthcare resources that contribute to poor health.
The associations between minority population share and self-reported mental health may appear counterintuitive, but this phenomenon, sometimes termed the “Black–White mental health paradox,” is documented in the previous literature, particularly in the southern United States [38,39]. However, the ecological association between resilience and minority communities—sometimes attributed to greater family, community, and religious support that helps build self-esteem—does not negate the barriers, lack of resources, and chronic disease burdens that affect minority communities in Alabama, which is evidenced by the positive correlation between minority population share and poor physical health. Similarly, two other covariates that are indicative of preventive care—mammogram screening in the case of the mental health model, and routine doctor visits in the physical health model—also appear to yield counterintuitive results. We speculate that this may be a case of “confounding by indication,” which is a frequent challenge in observational studies. Confounding by indication is the observation that higher use of medical care may indicate a higher risk of disease or higher prevalence of patient frailty. This association may result in spurious positive associations between use of preventive care and poorer health [40].
The covariate “annualized drought frequency” was positively associated with poor mental health and may suggest new directions for research in the U.S. context. Globally, exposure to drought is linked to economic strain, worry, hopelessness, and even suicidal ideation [41,42,43]. However, linkages between drought and mental health in a primarily urban population in the United States are an understudied but important area to explore in a time of rapidly changing weather patterns. The percentage of residents aged 65 years or older had a significant negative association with poor physical health, which is counterintuitive if interpreted at the individual level. Tracts with higher older-adult percentile rankings may differ in unmeasured ways, such as insurance coverage, residential stability, access to care, social resources, or neighborhood characteristics. This finding should not be interpreted as evidence that older adults have better physical health, but rather as an ecological pattern that warrants further study. Several selected covariates were not statistically significant after adjustment, suggesting that their associations with self-reported health were attenuated when considered alongside other contextual measures.
While the findings in this study were statistically significant, it is important to address that the interpretable impact of urban tree canopy expansion on self-reported health was modest. A 10-percentage-point increase in tree canopy was only associated with a 0.11-percentage-point decrease in prevalence of poor self-reported mental health and a 0.045-percentage-point decrease in prevalence of poor self-reported physical health. Additionally, it is important to address the significant spatial error parameters in both the mental health (0.6404) and physical health (0.5983) models. The significant spatial error parameters in both the mental and physical health models indicate residual spatial autocorrelation after adjustment for tree canopy and selected census-tract covariates, which may reflect omitted or incompletely measured spatially patterned factors. In the context of Alabama’s history, residual spatial patterning may reflect the lasting influence of redlining, which—through the accumulative economic and social effects of discriminatory housing practices—lead to various unfavorable living conditions coinciding within the same redlined census-tracts. Historically, census-tracts that were subject to redlining by the HOLC were more likely to attract factory work for industrial land use, which contributed to more coverage of land by impervious surfaces, worsened air pollution, and a decreased urban tree canopy [44]. People in redlined census-tracts have also historically had decreased access to other health-promoting resources, such as access to healthy food retailers [45]. The significant spatial error parameter suggests that other spatial factors within census-tracts may represent confounding variables that were not selected by the LASSO machine learning technique but that may represent important factors in theory-driven models such as those based on the effects of historical redlining.
Several limitations of this study should be acknowledged. Since the analysis was conducted at the census-tract level within Alabama MSAs, the findings may be affected by the Modifiable Area Unit Problem, edge effects at study-area boundaries, and neighborhood selection bias due to nonrandom residential sorting. The observational design of the study precludes causal inference, and the reliance on self-reported health measures may introduce reporting bias. Additionally, the cross-sectional nature of the data limits our ability to assess temporal relationships. Changes in tree canopy throughout the life of residents may have had effects on self-reported physical and mental health. Tree canopy data in this study represented an average over several years (2011–2021). Census-tract-level aggregations prevent more nuanced analyses at the individual level and create the possibility of ecological fallacy; therefore, tract-level associations should not be interpreted as individual-level effects. For example, recent research suggests that reductions in ambient temperature and any resultant benefits are most dependent on proximity and the density of tree cover within 10 m [46], and census-tract-level measures cannot capture such variation. The tree canopy was measured via satellite imagery, which does not capture the street-level quality, maintenance status of trees, or species composition.
While total tree canopy data through satellite imagery offers a valuable insight into the urban landscape, future studies should also pay attention to the true accessibility of such tree canopy and residents’ practical ability to interact with urban tree canopy in an effective way. Modest improvements in self-reported mental and physical health in this study may be related to a lack of true accessibility, such as the majority of the tree canopy being located in private parks or residences rather than public areas such as along streets or in public green spaces. Future studies should incorporate more precise, street-level indicators of tree canopy quality, maintenance, accessibility, and perceived safety. Future studies should also examine other local indicators that may influence the relationship between tree canopy and health, such as heat exposure, air quality, health care access, walkability, housing quality, and neighborhood social conditions.
Another limitation that must be addressed is the use of CDC PLACES-derived measures. Both outcomes of self-reported mental health and self-reported physical health were derived from PLACES using multilevel regression and post-stratification applied to ACS and BRFSS data. Several of the covariates, such as current adult asthma and routine doctor visits, also used measures from PLACES, and other covariates, such as income and racial/ethnic composition, were derived from ACS data—data that, as stated previously, was used in the generation of PLACES estimates. This overlap between covariates and outcome data may produce a degree of circularity that may amplify the final results. In addition, it is important to emphasize that PLACES measures are model-derived estimates, not observed prevalences; therefore, currently reported standard errors and confidence intervals may not fully address the total uncertainty surrounding the estimated associations. Finally, because covariates were selected using a machine learning screening approach, the findings should be interpreted as exploratory and contextual rather than as a fully theory-specified causal model. Although bootstrap-stabilized penalized regression was used to improve the stability of covariate selection, the post-selection SEM estimates and confidence intervals do not fully account for uncertainty introduced by the variable-selection step.
Future directions include collaboration with local organizations in Alabama, such as Cool Green Trees [47], which currently works to plant more trees in Alabama’s urban heat islands, potentially providing opportunities for quasi-experimental study designs. Moreover, smaller-scale studies with targeted primary data collection could provide more clarity on the complex relationships between tree canopy, neighborhood perceptions, contextual socioeconomic factors, and health outcomes of neighborhood residents. Longitudinal or quasi-experimental studies that measure tree planting, tree maintenance, resident use, temperature, air quality, and perceived neighborhood conditions would be especially useful for clarifying mechanisms and informing urban greening strategies.

5. Conclusions

This study contributes to a growing understanding of the complex, context-dependent relationship between urban greenness and health by leveraging publicly available data and novel tree canopy estimates from Alabama, a state that has largely been overlooked in this area of research. While the gold standard in research remains randomized controlled trials, such as the Green Heart Project in Louisville, KY [2], replicable methods that leverage large, open-access datasets can help provide critical tools to the research community, especially in an era of limited funding for environmental health and environmental justice research.

Author Contributions

Conceptualization, S.N.S., B.S., and L.A.M.; methodology, B.S., Y.L., and R.D.; software, Y.L. and R.D.; validation, Y.L. and R.D.; formal analysis, Y.L., B.S., and R.D.; investigation, S.N.S., L.A.M., B.S., Y.L., and R.D.; resources, E.H.B., Y.L., and R.D.; data curation, E.H.B., S.N.S., and L.A.M.; writing—original draft preparation, S.N.S.; writing—review and editing, S.N.S., L.A.M., and B.S.; visualization, Y.L. and R.D.; supervision, B.S. and L.A.M.; project administration, B.S. and L.A.M. All authors have read and agreed to the published version of the manuscript.

Funding

This work was partially supported by the Blue Cross Blue Shield Endowed Chair in Health Economics.

Institutional Review Board Statement

Ethical review and approval were waived for this study because it used publicly available, de-identified data and did not meet the criteria for Human Subjects Research, per the UAB Office of Research.

Informed Consent Statement

Not applicable.

Data Availability Statement

The original data presented in this study are openly available at climatevulnerabilityindex.org. The tree canopy data presented in this study are available on request from the corresponding author.

Acknowledgments

We thank Emily Delzell for her editorial review and assistance in the preparation of this manuscript.

Conflicts of Interest

The authors declare no conflicts of interest.

References

  1. Wolf, K.L.; Lam, S.T.; McKeen, J.K.; Richardson, G.R.; Bosch, M.v.D.; Bardekjian, A.C. Urban trees and human health: A scoping review. Int. J. Environ. Res. Public Health 2020, 17, 4371. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  2. Nowak, D.J.; Greenfield, E.J.; Ellis, A. Assessing Urban Forest Threats across the Conterminous United States. J. For. 2022, 120, 676–692. [Google Scholar] [CrossRef] [Scilit]
  3. Yang, W.; Lin, W.; Li, Y.; Shi, Y.; Xiong, Y. Estimating the seasonal and spatial variation of urban vegetation’s PM2.5 removal capacity. Environ. Pollut. 2025, 369, 125800. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Downs, N.J.; Amar, A.; Dearnaley, J.; Butler, H.; Dekeyser, S.; Igoe, D.; Parisi, A.V.; Raj, N.; Deo, R.; Turner, J. The mitigating effect of street trees, urban flora, and the suburban environment on seasonal peak UV indices: A case study from Brisbane, Australia. Photochem. Photobiol. 2025, 101, 251–266. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. McDonald, R.I.; Biswas, T.; Chakraborty, T.C.; Kroeger, T.; Cook-Patton, S.C.; Fargione, J.E. Current inequality and future potential of US urban tree cover for reducing heat-related health impacts. npj Urban Sustain. 2024, 4, 18. [Google Scholar] [CrossRef] [Scilit]
  6. Fry, D.; McIntire, R.K.; Kondo, M.C. Understanding perceived park access and physical activity among older adults: A structural equation modeling approach. Health Place 2024, 88, 103258. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Zhang, L.; Tan, P.Y. Associations between urban green spaces and health are dependent on the analytical scale and how urban green spaces are measured. Int. J. Environ. Res. Public Health 2019, 16, 578. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Astell-Burt, T.; Walsan, R.; Davis, W.; Feng, X. What types of green space disrupt a lonelygenic environment? A cohort study. Chest 2023, 58, 745–755. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. Ryan, S.C.; Sugg, M.M.; Runkle, J.D.; Thapa, B. Advancing understanding on greenspace and mental health in young people. GeoHealth 2024, 8, e2023GH000959. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  10. Sun, Y.; Molitor, J.; Benmarhnia, T.; Avila, C.; Chiu, V.; Slezak, J.; Sacks, D.A.; Chen, J.-C.; Getahun, D.; Wu, J. Association between urban green space and postpartum depression, and the role of physical activity: A retrospective cohort study in Southern California. Lancet Reg. Health Am. 2023, 21, 100462. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. El-Mallakh, T.V.L.; Hedges, S.; Rai, J.; Bhatnagar, A.; Moyer, S.; El-Mallakh, R. Suicide and homicide more common with limited urban tree canopy cover. Cities Environ. 2022, 14, 4. [Google Scholar] [CrossRef] [Scilit]
  12. Schinasi, L.H.; Kanungo, C.; Christman, Z.; Barber, S.; Tabb, L.; Headen, I. Associations between historical redlining and present-day heat vulnerability housing and land cover characteristics in Philadelphia, PA. J. Urban Health 2022, 99, 134–145. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. United Health Foundation. America’s Health Rankings 2026 Senior Report: Alabama State Summary; United Health Foundation: Eden Prairie, MN, USA, 2026; Available online: https://www.americashealthrankings.org/publications/reports/2026-senior-report (accessed on 28 June 2026).
  14. Hannon, L.; Jones, P.; Dulin, A.; Judd, S.; Smith, T. Redlining and contemporary health effects in Birmingham neighborhoods: Paying the price for past policies. Discov. Public Health 2026, 23, 22. [Google Scholar] [CrossRef] [Scilit]
  15. Hedgepeth, L. A tree grows in Birmingham. Inside Climate News, 9 August 2023. Available online: https://insideclimatenews.org/news/09082023/a-tree-grows-in-birmingham-heat-islands-alabama/ (accessed on 6 January 2025).
  16. Sabrin, S.; Karimi, M.; Nazari, R. The cooling potential of various vegetation covers in a heat-stressed underserved community in the deep south: Birmingham, Alabama. Urban Clim. 2023, 51, 101623. [Google Scholar] [CrossRef] [Scilit]
  17. Environmental Defense Fund. The U.S. Climate Vulnerability Index. Available online: https://map.climatevulnerabilityindex.org/map/cvi_overall/usa?mapBoundaries=Tract&mapFilter=0&reportBoundaries=Tract&geoContext=State (accessed on 19 June 2026).
  18. McDonald, R.I.; Biswas, T.; Sachar, C.; Housman, I.; Boucher, T.M.; Balk, D.; Nowak, D.; Spotswood, E.; Stanley, C.K.; Leyk, S. The tree cover and temperature disparity in US urbanized areas: Quantifying the association with income across 5723 communities. PLoS ONE 2021, 16, e0249715. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Lee, S.; Ye, X.; Nam, J.W.; Zhang, K. The association between tree canopy cover over streets and elderly pedestrian falls: A health disparity study in urban areas. Soc. Sci. Med. 2022, 306, 115169. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  20. Feng, X.; Navakatikyan, M.; Eckermann, S.; Astell-Burt, T. Show me the money! Associations between tree canopy and hospital costs in cities for cardiovascular disease events in a longitudinal cohort study of 110,134 participants. Environ. Int. 2024, 185, 108558. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. McConville, K.S.; Breidt, F.J.; Lee, T.C.M.; Moisen, G.G. Model-assisted survey regression estimation with the lasso. J. Surv. Stat. Methodol. 2017, 5, 131–158. [Google Scholar] [CrossRef] [Scilit]
  22. Zhang, C.-H. Nearly unbiased variable selection under minimax concave penalty. Ann. Stat. 2010, 38, 894–942. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Breheny, P.; Huang, J. Group descent algorithms for nonconvex penalized linear and logistic regression models with grouped predictors. Stat. Comput. 2015, 25, 173–187. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Huang, Z.; Klaric, L.; Krasauskaite, J.; Khalid, W.; Strachan, M.W.J.; Wilson, J.F.; Price, J.F. Combining serum metabolomic profiles with traditional risk factors improves 10-year cardiovascular risk prediction in people with type 2 diabetes. Eur. J. Prev. Cardiol. 2023, 30, 1255–1262. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Xie, R.; Herder, C.; Sha, S.; Peng, L.; Brenner, H.; Schöttker, B. Novel type 2 diabetes prediction score based on traditional risk factors and circulating metabolites: Model derivation and validation in two large cohort studies. eClinicalMedicine 2025, 79, 102971. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. O’brien, R.M. A Caution Regarding Rules of Thumb for Variance Inflation Factors. Qual. Quant. 2007, 41, 673–690. [Google Scholar] [CrossRef] [Scilit]
  27. Anselin, L.; Bera, A.K.; Florax, R.; Yoon, M.J. Simple diagnostic tests for spatial dependence. Reg. Sci. Urban Econ. 1996, 26, 77–104. [Google Scholar] [CrossRef] [Scilit]
  28. Housman, I.W.; Schleeweis, K.; Heyer, J.P.; Ruefenacht, B.; Bender, S.; Megown, K.; Goetz, W.; Bogle, S. National Land Cover Database Tree Canopy Cover Methods v2021.4; GTAC-10268-RPT1; Department of Agriculture, Forest Service, Geospatial Technology and Applications Center: Salt Lake City, UT, USA, 2023.
  29. Dean, D.; Garber, M.D.; Anderson, G.B.; Rojas-Rueda, D. Health implications of urban tree canopy policy scenarios in Denver and Phoenix: A quantitative health impact assessment. Environ. Res. 2024, 241, 117610. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  30. Asiimwe, I.G.; Ndzamba, B.S.; Mouksassi, S.; Pillai, G.C.; Lombard, A.; Lang, J. Machine-Learning Assisted Screening of Correlated Covariates: Application to Clinical Data of Desipramine. AAPS J. 2024, 26, 63. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  31. Karatza, E.; Papachristos, A.; Sivolapenko, G.B.; Gonzalez, D. Machine learning-guided covariate selection for time-to-event models developed from a small sample of real-world patients receiving bevacizumab treatment. CPT Pharmacomet. Syst. Pharmacol. 2022, 11, 1328–1340. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  32. Ogbu, C.E.; Ravilla, J.; Okoli, M.L.; Ahaiwe, O.; Ogbu, S.C.; Kim, E.S.; Kirby, R.S. Association of depression, poor mental health status and asthma control patterns in US adults using a data-reductive latent class method. Cureus 2023, 15, e33966. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  33. Stanescu, S.; Kirby, S.E.; Thomas, M.; Yardley, L.; Ainsworth, B. A systematic review of psychological, physical health factors, and quality of life in adult asthma. npj Prim. Care Respir. Med. 2019, 29, 37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  34. Sørensen, H.D.; Egholm, C.L.; Løkke, A.; Barna, E.N.; Hougaard, M.S.; Raunkiær, M.; Farver-Vestergaard, I. Using a patient-reported outcome measure to assess physical, psychosocial, and existential issues in COPD. J. Clin. Med. 2024, 13, 6200. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Jespersen, A.; Madden, R.A.; Whalley, H.C.; Reynolds, R.M.; Lawrie, S.M.; McIntosh, A.M.; Iveson, M.H. Socioeconomic status and depression—A systematic review. Epidemiol. Rev. 2025, 47, mxaf011. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  36. Marbin, D.; Gutwinski, S.; Schreiter, S.; Heinz, A. Perspectives in poverty and mental health. Front. Public Health 2022, 10, 975482. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  37. Rhubart, D.C.; Monnat, S.M. Self-rated physical health among working-aged adults along the rural-urban continuum—United States, 2021. MMWR. Morb. Mortal. Wkly. Rep. 2022, 71, 161–166. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  38. Louie, P.; Upenieks, L.; Erving, C.L.; Tobin, C.S.T. Do racial differences in coping resources explain the Black–White paradox in mental health? A test of multiple mechanisms. J. Health Soc. Behav. 2021, 63, 55–70. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  39. Erving, C.L.; Satcher, L.A.; Montúfar, S.; Thomas Tobin, C.S. Black-White Mental Health Paradox Across U.S. Regions; Population Research Center, University of Texas at Austin: Austin, TX, USA, 2026. [Google Scholar]
  40. Assimon, M.M. Confounding in observational studies evaluating the safety and effectiveness of medical treatments. Kidney360 2021, 2, 1156–1159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  41. Varshney, K.; Makleff, S.; Krishna, R.N.; Romero, L.; Willems, J.; Wickes, R.; Fisher, J. Mental health of vulnerable groups experiencing a drought or bushfire: A systematic review. Glob. Ment. Health 2023, 10, e24. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  42. Vins, H.; Bell, J.; Saha, S.; Hess, J.J. The mental health outcomes of drought: A systematic review and causal process diagram. Int. J. Environ. Res. Public Health 2015, 12, 13251–13275. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  43. Padrón-Monedero, A.; Linares, C.; Díaz, J.; Noguer-Zambrano, I. Impact of drought on mental and behavioral disorders, contributions of research in a climate change context. A narrative review. Int. J. Biometeorol. 2024, 68, 1035–1042. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  44. Nardone, A.; Rudolph, K.E.; Morello-Frosch, R.; Casey, J.A. Redlines and greenspace: The relationship between historical redlining and 2010 greenspace across the United States. Environ. Health Perspect. 2021, 129, 017006. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  45. Li, M.; Yuan, F. Historical redlining and food environments: A study of 102 urban areas in the United States. Health Place 2022, 75, 102775. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  46. Ettinger, A.K.; Bratman, G.N.; Carey, M.; Hebert, R.; Hill, O.; Kett, H.; Levin, P.; Murphy-Williams, M.; Wyse, L. Street trees provide an opportunity to mitigate urban heat and reduce risk of high heat exposure. Sci. Rep. 2024, 14, 3266. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  47. Cool Green Trees. Green Opportunities. 2024. Available online: https://coolgreentrees.org/tree-map/ (accessed on 5 December 2024).
Figure 1. (a) Geographic distribution of tree canopy in metropolitan statistical areas (MSAs) in Alabama. Note: (a) illustrates the distribution of tree canopy in Alabama MSAs. Tree canopy was categorized into quartiles based on its distribution in the state. Darker green indicates census tracts in higher quartiles of tree canopy coverage. Values shown in the legend represent tree canopy percentage cut points for the quartile categories. (b) Geographic distribution of self-reported poor mental health in MSAs in Alabama. Note: (b) illustrates the distribution of self-reported poor mental health in Alabama’s MSAs. Self-reported mental health was categorized into quartiles based on its distribution in the state. Darker blue indicates census tracts in higher quartiles of self-reported poor mental health. Values shown in the legend represent self-reported poor mental health percentage cut points for the quartile categories. Gray indicates no data are available. (c) Geographic distribution of self-reported poor physical health in MSAs in Alabama. Note: (c) illustrates the distribution of poor physical health in Alabama’s MSAs. Self-reported physical health was categorized into quartiles based on its distribution in the state. Darker red indicates census tracts in higher quartiles of self-reported poor physical health. Values shown in the legend represent self-reported poor physical health percentage cut points for the quartile categories. Gray indicates no data are available.
Ijerph 23 01143 g001aIjerph 23 01143 g001b
Figure 2. For this study, 28 counties with 827 census tracts were included in the analysis. The above figure demonstrates where Alabama is located within the U.S. The above figure also demonstrates the 28 MSA counties included in the study. Major cities within Alabama are labeled on the map.
Ijerph 23 01143 g002
Table 1. Assessment of multicollinearity using variance inflation factors (VIFs) for self-reported mental health.
VariableVIF Before Removing Variables with High VIFVIF After Removing Variable with High VIF
Tree canopy1.281.27
Current adult asthma6.866.72
Low income5.024.99
Minority 4.043.97
Annualized drought frequency1.071.06
No high school diploma4.793.34
High blood pressure10.10-
Routine doctor visits8.412.31
Mammogram screening2.782.61
Note: High blood pressure was removed after assessment because it had a VIF greater than 10; “-” indicates the variable was removed and not retained in the final model.
Table 2. Covariates from the U.S. Climate Vulnerability Index used in the self-report mental health model.
CovariateDefinitionSourceYear of Data Collection
Current adult asthmaMulti-level regression and post-stratification approach was applied to BRFSS and ACS data to compute a detailed probability of having current asthma, defined as reporting “yes” to both of the following questions: “Have you ever been told by a doctor, nurse, or other health professional that you have asthma?” and “Do you still have asthma?” over a calendar year. Centers for Disease Control and Prevention; Robert Wood Johnson Foundation; and Center for Disease Control and Prevention Foundation. PLACES: Local Data for Better Health, https://www.cdc.gov/places/about/index.html (accessed on 10 July 2026).2018
Low incomeUsing data from the U.S. Census Bureau’s ACS, percentage of population with an income below 200% of the federal poverty level was calculated.Centers for Disease Control and Prevention—Agency for Toxic Substances and Disease Registry. Social Vulnerability Index, https://www.atsdr.cdc.gov/placeandhealth/svi/faq_svi.html (accessed on 10 July 2026).2018
MinorityUsing data from the U.S. Census Bureau’s ACS, percentage of population that is a racial/ethnic minority (i.e., all persons except white, non-Hispanic) was calculated. Centers for Disease Control and Prevention—Agency for Toxic Substances and Disease Registry. Social Vulnerability Index, https://www.atsdr.cdc.gov/placeandhealth/svi/faq_svi.html (accessed on 10 July 2026).2018
Annualized drought frequencyFrom the 2022 FEMA National Risk Index, the number of recorded drought event-days per year, calculated as the total number of drought event-days (drought event-weeks × 7 days), divided by the 18-year period of record.U.S. Department of Homeland Security: FEMA. The National Risk Index, https://hazards.fema.gov/nri/ (accessed on 10 July 2026).18-year period between 1 January 2000 and 31 December 2017
No high school diplomaUsing data from the U.S. Census Bureau’s ACS, percentage of population without a high school diploma was calculated.Centers for Disease Control and Prevention—Agency for Toxic Substances and Disease Registry. Social Vulnerability Index, https://www.atsdr.cdc.gov/placeandhealth/svi/faq_svi.html (accessed on 10 July 2026).2018
Routine doctor visitsMulti-level regression and post-stratification approach was applied to BRFSS and ACS data to compute detailed probability among adults who report having been to a doctor for a routine check-up (e.g., a general physical exam, not an exam for a specific injury, illness, or condition) in the previous year.Centers for Disease Control and Prevention; Robert Wood Johnson Foundation; and Center for Disease Control and Prevention Foundation. PLACES: Local Data for Better Health, https://www.cdc.gov/places/about/index.html (accessed on 10 July 2026).2018
Mammogram screeningMulti-level regression and post-stratification approach was applied to BRFSS and ACS data to compute a detailed probability among women aged 50–74 who report having had a mammogram within the previous 2 years.Centers for Disease Control and Prevention; Robert Wood Johnson Foundation; and Center for Disease Control and Prevention Foundation. PLACES: Local Data for Better Health, https://www.cdc.gov/places/about/index.html (accessed on 10 July 2026).2018
Note: CVI obtained data posted on CDC website for ATSDR (Agency for Toxic Substances and Disease Registry) in 2018, data posted on CDC website for PLACES (Population Level Analysis and Community Estimates) in 2020, and data posted on website for FEMA National Risk Index (Federal Emergency Management Agency) in 2022. Abbreviations: BRFSS, Behavioral Risk Factor Surveillance System; ACS, American Community Survey. Directionality: Higher values or “current adult asthma” indicate higher prevalence of asthma. Higher values for “low income” indicate greater burden of low income. Higher values for “minority” indicate greater percentage of minority population. Higher values for “annualized drought frequency” indicate more frequent drought. Higher values for “no high school diploma” indicate greater percentage of the population with no high school diploma. Higher values for “routine doctor visit” indicate more regular check-up visits among the adult population. Higher values for “mammogram screening” indicate that a greater number of women have regular mammogram screening.
Table 3. Spatial error model estimates for associations of tree canopy and selected census-tract characteristics with self-reported poor mental health.
VariableEstimateSE95% CIp-Value
Tree canopy−0.01100.0024(−0.0157, −0.0064)<0.001
Current adult asthma2.21760.0448(2.1297, 2.3054)<0.001
Low income2.42750.2332(1.9705, 2.8846)<0.001
Minority−3.08180.1933(−3.4607, −2.7029)<0.001
Annualized drought frequency0.03110.0065(0.0183, 0.0438)<0.001
No high school diploma−0.14440.1831(−0.5033, 0.2146)0.4305
Routine doctor visits−0.19540.0100(−0.2151, −0.1758)<0.001
Mammogram screening0.07090.0079(0.0554, 0.0865)<0.001
Spatial error parameterEstimateSE95% CIp-value
Spatial error autoregressive parameter, φ0.64040.0346(0.5726, 0.7083)<0.001
Note: Tree canopy is measured as percent census-tract tree canopy coverage. Current adult asthma is the age-adjusted percentage of adults reporting current asthma. Routine doctor visits are the age-adjusted percentage of adults reporting a routine check-up in the previous year. Mammogram screening is the age-adjusted percentage of female respondents aged 50–74 years reporting mammogram screening. Annualized drought frequency is measured as the annualized frequency of drought events. Low income, minority, and no high school diploma are census-tract percentile-ranking variables scaled from 0 to 1. Abbreviations: SE, standard error; CI, confidence interval.
Table 4. Covariates for self-reported physical health model.
CovariateDefinitionSourceYear of Data Collection
COPDMulti-level regression and post-stratification approach was applied to BRFSS and ACS data to compute a detailed probability among adults who report having ever been told by a doctor, nurse, or other health professional if they had COPD, emphysema, or chronic bronchitis.Centers for Disease Control and Prevention; Robert Wood Johnson Foundation; and Center for Disease Control and Prevention Foundation. PLACES: Local Data for Better Health, https://www.cdc.gov/places/about/index.html (accessed on 14 July 2026).2018
MinorityUsing data from the U.S. Census Bureau’s ACS, percentage of population that is a racial/ethnic minority (i.e., all persons except white, non-Hispanic) was calculated.Centers for Disease Control and Prevention—Agency for Toxic Substances and Disease Registry. Social Vulnerability Index, https://www.atsdr.cdc.gov/placeandhealth/svi/faq_svi.html (accessed on 14 July 2026).2018
Aged 17 or youngerUsing data from U.S. Census Bureau’s ACS, the percentage of population 17 and younger was calculated.Centers for Disease Control and Prevention—Agency for Toxic Substances and Disease Registry. Social Vulnerability Index, https://www.atsdr.cdc.gov/placeandhealth/svi/faq_svi.html (accessed on 14 July 2026).2018
Routine doctor visitsMulti-level regression and post-stratification approach was applied to BRFSS and ACS data to compute detailed probability among adults who report having been to a doctor for a routine check-up (e.g., a general physical exam, not an exam for a specific injury, illness, or condition) in the previous year.Centers for Disease Control and Prevention; Robert Wood Johnson Foundation; and Center for Disease Control and Prevention Foundation. PLACES: Local Data for Better Health, https://www.cdc.gov/places/about/index.html (accessed on 14 July 2026).2018
Low incomeUsing data from the U.S. Census Bureau’s ACS, percentage of the population with an income below 200% of the federal poverty level was calculated.Centers for Disease Control and Prevention—Agency for Toxic Substances and Disease Registry. Social Vulnerability Index, https://www.atsdr.cdc.gov/placeandhealth/svi/faq_svi.html (accessed on 14 July 2026).2018
Aged 65 or olderUsing data from the U.S. Census Bureau’s ACS, percentage of the population aged 65 or older was calculated.Centers for Disease Control and Prevention—Agency for Toxic Substances and Disease Registry. Social Vulnerability Index, https://www.atsdr.cdc.gov/placeandhealth/svi/faq_svi.html (accessed on 14 July 2026). 2018
Note: CVI obtained data posted on CDC website for ATSDR in 2018 and data posted on CDC website for PLACES in 2020. Abbreviations: COPD, chronic obstructive pulmonary disease. Directionality: Higher values for “COPD” indicate more people with a diagnosis of COPD. Higher values for “minority” indicate greater percentage of the population that is a racial/ethnic minority. Higher values for “aged 17 or younger” indicate greater percentage of the population that is aged 17 and younger. Higher values for “routine doctor visits” indicate more people who report going to a routine check-up. Higher values for “low income” indicate greater percentage of the population with income below 200% of the federal poverty level. Higher values for “aged 65 and older” indicates greater percentage of population aged 65 and older.
Table 5. Spatial error model estimates for associations of tree canopy and selected census-tract characteristics with self-reported poor physical health.
VariableEstimateSE95% CIp-Value
Tree canopy−0.00450.0015(−0.0074, −0.0016)0.002
COPD1.40430.0128(1.3792, 1.4294)<0.001
Minority2.46220.1164(2.2341, 2.6904)<0.001
Aged 17 or younger−0.03090.0770(−0.1818, 0.1200)0.688
Routine doctor visits0.02410.0033(0.0176, 0.0306)<0.001
Low income0.62840.1292(0.3751, 0.8817)<0.001
Aged 65 or older−1.17780.1017(−1.3771, −0.9786)<0.001
Spatial error parameterEstimateSE95% CIp-value
Spatial error autoregressive parameter, φ0.59830.0370(0.5258, 0.6707)<0.001
Note: Tree canopy is measured as percent census-tract tree-canopy coverage. COPD and routine doctor visits are age-adjusted prevalence measures, expressed as percentages. Low income, minority, aged 17 or younger, and aged 65 or older are percentile-ranking variables scaled from 0 to 1.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.