Article

Water Insecurity as Health Crisis: Everyday Embodiment and Gendered Vulnerability Among Girls in Ghana’s Upper West Region


by
Mildred Naamwintome Molle
1,*,
Sulemana Ansumah Saaka
1,
Cornelius K. A. Pienaah
1,
Elijah Bisung
2 and
Isaac Luginaah
1
1
Department of Geography and Environment, Western University, London, ON N6A 5C2, Canada
2
School of Kinesiology and Health Studies, Queen’s University, 28 Division Street, Kingston, ON K7L 3N6, Canada
*
Author to whom correspondence should be addressed.
Int. J. Environ. Res. Public Health 2026, 23(9), 1142; https://doi.org/10.3390/ijerph23091142
Submission received: 29 July 2026 / Revised: 29 August 2026 / Accepted: 31 August 2026 / Published: 2 September 2026
(This article belongs to the Special Issue Health Impacts of Resource Insecurity on Vulnerable Populations)

Highlights

Public health relevance—How does this work relate to a public health issue?
  • Adolescent girls in water-insecure communities in the Upper West Region of Ghana continue to bear the burden of water collection.
  • This responsibility translates into direct physical, psychological, and neurological health consequences for adolescent girls.
Public health significance—Why is this work of significance to public health?
  • Water insecurity intensifies musculoskeletal injury, disrupted sleep and psychosocial health risk for adolescent girls.
  • The study reveals that girls living with pre-existing health vulnerabilities such as epilepsy are at high risk in water-insecure areas.
Public health implications—What are the key implications or messages for practitioners, policymakers and/or researchers in public health?
  • There is a need to incorporate issues of water security into existing social protection frameworks and gender-responsive water policy.
  • Coordinated investment in safe water and regulated pricing are necessary to help increase access to water for adolescent girls residing in water-insecure areas.

Abstract

In semi-arid Ghana, girls bear primary responsibility for household water collection in communities without on-premises access, a burden intensified by climate change associated with rising temperatures and frequent droughts. Yet little is known about how this responsibility shapes their embodied health and well-being. Guided by a political ecology of health framework, this qualitative study examined how water insecurity shapes girls’ physical, psychosocial, and neurological health in two communities, Wechiau and Kandue, in Ghana’s Upper West Region. We conducted in-depth interviews with nineteen purposively selected girls aged 10 to 19 and analyzed the transcripts thematically. Four interconnected themes emerged: structural and political determinants of water access, environmental and ecological conditions, gendered social relations, and embodied health consequences. Financial barriers, governance failures, and infrastructure deficits force girls into long queues and repeated trips, a burden that falls disproportionately on girls under cultural norms exempting boys from water duties. This gendered allocation of labour produces gendered health harm, whereby girls sustain musculoskeletal pain and injury carrying heavy loads over hazardous terrain, while chronic time loss disrupts sleep, schooling, and psychological well-being. Girls with pre-existing conditions such as epilepsy face the most acute risk, as water fetching directly exacerbates their vulnerability to seizures. These findings show that addressing this crisis requires more than infrastructure investment. Coordinated public–private investment in water access must be paired with social protection for vulnerable households, gender-responsive water policy, and rainwater-harvesting strategies that confront the structural and gendered inequities placing this burden on girls.

1. Introduction

Every morning before sunrise, in villages scattered across Ghana’s Upper West Region, girls as young as eight years old shoulder basins, gallons, and pans on a journey that will define much of their day, searching for water. They walk long distances and return home with aching necks and sometimes bruised feet, only to repeat the trip before nightfall. This is not an occasional hardship but a daily, often multiple-times-daily, obligation woven into the fabric of girlhood in water-insecure communities [1,2]. While the global water crisis is frequently narrated through the language of infrastructure deficits and policy targets [3], these girls’ lived experiences are embodied in chronic pain, disrupted sleep, lost school days, and, for some, the triggering of seizures. This paper centers their experiences to ask a question that remains underexplored in the scholarship on water security: what does chronic water insecurity do to the health and well-being of the girls who are tasked with managing it?
Water insecurity remains one of the most pressing threats to human health and well-being globally, disproportionately burdening the world’s most vulnerable populations [4]. Despite two decades of concerted global policy attention, from the Millennium Development Goals (2000–2015) to the Sustainable Development Goals (2015–2030), more than two billion people worldwide still lack safely managed drinking water, including 771 million who lack even basic access. Sub-Saharan Africa carries the heaviest share of this burden, home to roughly half (387 million) of those without basic drinking water services [4]. For much of the region, water insecurity is not an aberration but an entrenched condition of daily life, driven by a convergence of climate change, poverty, and chronically underdeveloped water infrastructure [5,6]. Rising temperatures, recurrent droughts, and erratic rainfall are steadily reducing the availability and quality of the water sources on which rural households depend, while Africa continues to face an annual $22 billion shortfall in the investment needed to close its water infrastructure gap [7]. Where infrastructure does exist, poor governance through inadequate maintenance may lead to high rates of water loss, thereby further undermining its reliability [8]. The result is a landscape in which access to water is neither guaranteed nor evenly distributed, and where the consequences of that scarcity fall hardest on those least equipped to advocate for change.
Ghana illustrates this unevenness starkly. While 44.4% of the national population had access to safely managed water services as of 2022, this figure conceals a profound rural–urban divide: 62.6% of urban residents enjoy safely managed access compared to just 18.8% of rural residents. One in ten Ghanaians spends more than 30 min accessing an improved water source, and many households outside urban centers rely entirely on sources beyond their own premises [9]. In the semi-arid Upper West Region, households spend an average of 26 min per round trip simply to retrieve drinking water [10], a figure that masks substantial variation and does not capture the queuing, terrain, or seasonal disruptions that can extend this burden considerably [11]. Crucially, this burden is not distributed equally within households. It falls overwhelmingly on women and girls. In patriarchal social structures like those of semi-arid Ghana, deeply entrenched gender norms assign water collection as feminine labour, often explicitly excluding boys and men regardless of household need [12]. For girls, this translates into hours spent walking to distant water points, waiting in long queues, and, in many households, sacrificing school attendance to meet domestic water demands. Despite measurable national progress in girls’ education, water-fetching responsibilities continue to pull girls out of classrooms and into the work of sustaining their households, a quiet, unpaid labour that rarely registers in national statistics but shapes the trajectory of girls’ lives in fundamental ways.

1.1. Health Implications of Water Insecurity

Various studies have linked water insecurity to physical health, emotional distress, and diminished psychological well-being [11,13,14], and others have examined the coping strategies households deploy to manage chronic scarcity [15]. Yet this literature, while valuable, has tended to treat water insecurity and health as loosely connected domains rather than tracing the specific, embodied pathways through which the daily work of water collection translates into physical injury and psychosocial distress, and cases involving pre-existing conditions such as epilepsy can result in direct and dangerous exacerbation of neurological vulnerability. Few studies have asked girls themselves, in their own words, to describe how fetching water affects their bodies and minds, and fewer still have examined how these effects compound for girls who are already managing chronic health conditions. This study addresses that gap by drawing on an interpretative study with girls from communities in the semi-arid Upper West Region. We examine how chronic water insecurity is experienced and managed at the household level, and how it shapes girls’ physical, psychosocial, and neurological health. We pay particular attention to the strategic, adaptive decisions girls make in navigating multiple, often unsafe, water sources; the gendered social norms that concentrate this labour on girls’ shoulders even in mixed-sex households; and the geographic, environmental and health hazards that compound the risks of collection. In doing so, this study moves beyond documenting that water insecurity harms girls to specifying and tracing the everyday mechanisms that connect the chore of water fetching to compounding health vulnerability. The findings will have implications well beyond the communities in the UWR. As climate change intensifies water stress across Sub-Saharan Africa, the structural burden currently carried by girls is likely to deepen rather than ease, unless policy responses move beyond infrastructure investment alone to confront the gendered allocation of water labour and its embodied health consequences. By centering girls’ own accounts of their everyday water insecurity, this study provides both an empirical contribution to water security and the basis for water policy reform that explicitly recognizes girls as a population requiring urgent, targeted attention.

1.2. Theoretical Context

This study is situated within a political ecology of health (PEH) framework, which understands health and illness not as isolated biological events but as outcomes shaped by the interaction of political, economic, social, and environmental structures across scales [16,17]. PEH extends classical political ecology concerned with how power relations mediate human–environment interactions, by acknowledging the body as a site where structural inequities become physically inscribed [18]. This conceptualization particularly informs the present study because it goes beyond the notion that water-related illness frequently results in individual behavior or proximate environmental hazards and instead interrogates how broader systems of power, including colonial histories of underinvestment, patriarchal gender norms, weak water governance, and climate change, may converge to produce uneven vulnerability to water insecurity and its health consequences [19].
Within PEH, water provisioning itself becomes a political resource whose distribution, quality, and accessibility reflect existing social hierarchies rather than simple natural scarcity [20]. In semi-arid Ghana, the inadequacy of water infrastructure is not incidental but the product of decades of both colonial and preceding governments’ underinvestment, which is currently compounded by climate stressors that further strain already fragile systems [21]. PEH directs attention to how these macro-level structural failures are absorbed at the household and individual levels, and crucially, how that absorption is gendered. Feminist political ecology, a key strand within this tradition, emphasizes that environmental burdens are rarely distributed evenly within households, but are instead allocated according to gender norms that assign caregiving and subsistence labour, including water collection, disproportionately to women and girls [22,23,24,25]. This study draws on that insight to understand why girls, rather than other household members, bear significant physical and psychological costs of water insecurity.
PEH further conceptualizes the ways that structural and environmental conditions may negatively influence the body through musculoskeletal strain, exposure to pathogens, chronic stress, and the exacerbation of preexisting conditions such as epilepsy [26]. Accordingly, the objective of this study is to trace the specific, embodied pathways through which chronic water insecurity is translated into physical, psychosocial, and neurological harm among adolescent girls in Ghana’s Upper West Region, and to identify the structural, ecological, and gendered forces that produce and sustain this harm. The PEH framework is well suited to this objective precisely because it refuses to treat the body as separate from the political and environmental context. Consequently, in the current study, it focuses analytic attention simultaneously on the governance failures that produce water scarcity, the ecological conditions that intensify it, and the patriarchal norms that allocate its burden to girls, while insisting that these forces converge and become legible in girls’ bodies.

2. Methods

Research Design

The study adopted a case study design to understand the lived experience of adolescent girls in relation to water security in the Upper West Region of Ghana [27]. In line with this design, a qualitative approach was utilized in the data collection and analysis. Adolescent girls, defined by the World Health Organization (WHO) as individuals between the ages of 10 and 19, were the main study participants selected for the study using a purposive sampling technique. Purposive sampling was suited for this study because it allowed for the intentional inclusion of participants given their everyday role in water fetching at the household level and because of their direct experience of water insecurity. Initial contact was made through a community focal person to help identify eligible participants for the study. Participants and the parents or legal guardians who expressed interest were provided with a letter of invitation (LOI) that detailed the purpose of the study and their rights as study participants, and a consent form. Participants were informed that their participation in the study was voluntary, informing them of the study’s objectives and purpose.
In all, we conducted interviews with 19 girls. Two of the girls reported living with epilepsy—a neurological condition characterized by recurrent (at least two) unprovoked seizures. These girls were not specifically recruited for their neurological condition but were recruited as part of a broader study exploring the impact of water insecurity on women and adolescent girls in the Upper West Region of Ghana. Their health conditions emerged during the interviews. Out of the two, the participant living in Kandeu reported that her condition had been diagnosed by a medical doctor, while the participant from Wechiau self-reported her condition based on the symptoms and her experiences of seizure episodes. Her self-reported medical condition was corroborated by her mother, who provided the consent for her participation in the study. Given that the study included minors, consent was obtained from their parents and legal guardians. The parents and legal guardians either signed or provided a thumbprint to provide consent for their children’s participation in the study. All the interviews with the girls were conducted in the presence of the parents and the legal guardians to ensure that the research was conducted as explained to the parents. The interviews were conducted at the homes of the participants for convenience and to minimize interruptions. Participants’ identities in the study are protected by pseudonyms. The Western University Non-Medical Research Ethics Board reviewed and approved the study.
In line with the study objectives, an interview guide was developed based on the literature on water insecurity and health outcomes, and solicited in-depth information from the participants. On average, the interviews lasted between 25 and 30 min. The interviews were conducted in both English and Dagaare (the local language spoken in the communities). All interviews in Dagaare were translated verbatim from the local language to English for analysis and theme generation. A field notebook was used to document any observations, emotions, reflections, and insights that evolved during the process of data collection and analysis. This was a reflective practice to manage any potential bias.
Thematic analysis was applied to analyze the data from the transcripts. We employed Braun & Clarke’s (2006) [28] thematic analysis method, an iterative process consisting of six steps: (1) becoming familiar with the data, (2) generating codes, (3) generating sub-themes, (4) defining and naming themes, and (5) locating exemplars related to the sub-themes. A codebook was developed to guide the coding process based on the study objectives, after familiarizing ourselves with the transcripts. For the coding, a line-by-line coding method was used to code the data into main themes and sub-themes guided by the codebook. The line-by-line coding method made us pay close attention to what the respondents were saying and construct codes that reflected their views about what was being studied [29].
To establish rigour and the trustworthiness of the findings, we drew on Lincoln and Guba’s (1985) criteria: credibility, dependability, confirmability, and transferability [30]. Credibility was strengthened through investigator triangulation, whereby the authors independently reviewed and coded the transcripts before reconciling interpretations and resolving discrepancies in theme identification during team meetings. This was further reinforced by anchoring each theme in verbatim participant quotes selected for their clarity, representativeness, and relevance, allowing the girls’ own language to substantiate the analysis rather than relying solely on researcher interpretation. Dependability was ensured by maintaining a systematic process by using an interview guide grounded in the existing literature, the codebook developed prior to full coding, and reflective field notes during data collection. Confirmability was addressed through this same reflexive practice, which allowed the research team to identify and manage potential bias arising from their positionality as researchers based outside the study communities. Transferability was supported by describing the study context, including participants’ age, schooling status, and household characteristics (Table 1).
The broader themes that emerged after PEH-informed coding and categorization were structural and political determinants of access to water, environmental and ecological conditions, and gendered social and embodied health consequences. In presenting the results, quotes from the participants are provided to support the sub-themes and themes. The quotes were selected based on clarity, representativeness, and relevance. Each quote was identified with a pseudonym to protect the identity of the participant. Table 2 provides the code descriptions, sub-themes, themes, and exemplars.

3. Results

3.1. Background Characteristics of Participants

A total of nineteen (19) girls were included in the study. The majority of the participants were between the ages of 16 and 19, representing 52.63% of the total sample. More than seventy of the girls were actively in school, while 21.05% were out of school. Out of the 19 participants, only two (10.5%) reported living with a health condition—epilepsy—while the remaining 17 (89.5%) were not living with any health condition.

3.2. Structural and Political Determinants of Water Access

The structural conditions that shape water access in the study communities are rooted in financial barriers, related to the cost of water, governance failures, and chronic infrastructure deficits. These macro-level determinants are not incidental, as they are the product of historical underinvestment in rural water systems and the commodification of water under privatised management arrangements. For the girls in this study, the consequences are immediate and embodied as expressed through daily navigations of exclusion, crowding, and depleted time geographies.

3.2.1. Cost of Water

The cost of water also influences the decision to use a particular water source. During the interviews, the girls revealed that the cost of a basin of water ranged between 50 pesewas and 80 pesewas. Therefore, a household could spend between GH¢ 1.50, GH¢ 2, and GH¢ 3 on water daily. One participant mentioned this payment as a challenge that hinders their water access. As one of the participants noted:
“When my mom does not have money for me to go and fetch from the standpipes, I have to go to the borehole which is farther away to fetch water.”
(Milly, 18)
Participants described the challenges of accessing water from private sources due to the cost involved:
“We occasionally go to fetch water from private sources. It is very expensive and costs 80 pesewas. We [family] can even go longer periods without fetching from there because it is very expensive, given our house situation. We don’t have the money and so fetching two basins will cost 1 cedi 50 pesewas. This is too much for us.”
(Alli, 18)

3.2.2. Water Governance Failure

Beyond the direct cost of water, participants described how the management of existing water infrastructure actively excludes households that cannot pay. Standpipes controlled by private caretakers are closed, or access is denied to households with outstanding balances, a governance arrangement that functions not as a safety net but as a mechanism of exclusion. This reveals water insecurity not merely as a supply problem but as a governance failure, one in which the distribution of existing resources reflects and reinforces existing poverty.
“Sometimes the pipe does not flow, or it is closed by the caretakers, so our option is the dam. We use the dam water for bathing and washing our clothes. Although the dam is dirty, it is hard to get clean water around here. At times, we even drink the dam water. It looks green because it is contaminated, but we locally treat it with alum and drink it.”
(Memuna, 16)
Underpinning the experiences girls described throughout the interviews is a fundamental infrastructure deficit, whereby the number of functioning water points in the study communities is grossly inadequate relative to population demand.

3.2.3. Infrastructure Deficit

Several participants talked about the lack of pipe-borne water and an adequate number of boreholes in their communities. In the quote below, a participant talked about how they have to sometimes go to nearby communities to fetch water:
“We have one borehole in this whole village. Ideally if we had about three or four, it serves us better. So, if one breaks down, we can still fetch water from the others. But, you see, it is just one and we all usually crowd there and it breaks down frequently.”
(Alli, 18)
The infrastructure gap is not simply geographic; it is the accumulated result of decades of underinvestment in rural water infrastructure. This inadequacy forces households to compete for limited access to improved water sources.

3.2.4. Crowding of Girls at Water Sources

Crowding at the water sources, especially the borehole, emerged as a key determinant related to the selection of the particular water source girls go to and a household’s water security. Huge crowds of girls cause long wait times and disrupt girls’ household activities. One of the girls explained:
“When the taps are not flowing and we go to the borehole, it is mostly crowded. If you spend too much time, you will not be able to finish the rest of your house chores, which no one will do for you. So that is why we always go to the dam to fetch water. It is faster, especially when we want water for washing.”
(Sung, 16)
To ensure that they have sufficient water at home, most girls tend to draw a lot of water, bringing many water collection containers and basins. This, however, increases wait time for others trying to access water:
“They can be like 15–20 people, with most people fetching more than one basin. A single individual can fetch like 3 or 4 basins when it is their turn. Even if you have one basin, you will have to wait for the person to fetch all, which leads to increasing wait time just to get a basin of water.”
(Fortune, 18)
Another participant described how crowding forces repeated trips to water sources:
“If the borehole is crowded, it looks like the whole community is there. When you are not getting water, you have to go back home, eat, and go back to fetch. You can come back home late without water and are forced to use the alum to treat the dam water for drinking.”
(Juliet, 18)
Yet the inadequacy of the clean water sources drives many to rely on unimproved sources during peak demand periods.
Taken together, these sub-themes reveal a structural pathway showing that the cost of water, exclusionary governance practices, and chronic infrastructure deficits converge to produce crowding at the few functioning water points, forcing girls into longer waits, repeated trips, and reliance on unsafe alternative sources simply to meet their households’ daily water needs in challenging environmental conditions.

3.3. Environmental and Ecological Conditions

Beyond structural barriers, girls navigate a set of environmental and ecological conditions that fundamentally shape the availability, quality, and safety of water across the semi-arid Upper West Region. These conditions are neither fixed nor purely natural; they are intensified by climate change, degraded by poor drainage and sanitation infrastructure, and made more dangerous by seasonal patterns that undermine the reliability of existing sources. Taken together, they constitute an ecological layer of water insecurity reinforced by structural conditions.

3.3.1. Perceptions of Water Quality

The perception of water quality influences the choice of water source. Water from the dams is generally considered suitable for washing and cleaning, but not for drinking purposes. One of the participants explained that:
“We go to the dam to fetch the water to wash our clothes and bathe. The dam water is mostly contaminated and cannot be used for drinking, so we go for that one to wash our clothes and not drink.”
(Asana, 15)
Another participant in the same community corroborated this, explaining how the dam water is utilized and sometimes used as a drinking water source due to limited access to safe drinking water:
“During the dry season all the animals go to the dam to drink, and yet we also go there to fetch this contaminated water for household use. It is not nice, but what can we do?”
(Memuna, 16)
In Kandeu, one of the community’s boreholes has a salty taste, which participants indicated was not safe for drinking; they only use it for domestic chores such as cleaning and washing.
“The borehole by the mosque produces salty water. People only use it to perform ablution, but you cannot use it for drinking or for household chores. If you use it to wash bowls, it will not lather properly.”
(Janice, 14)
This indicates that with infrastructure deficits, water coming from some sources may be suitable for consumption. Yet this changes frequently from the dry to the wet season. The girls also highlighted how seasonal changes impact water availability from open sources such as the dam. One of the girls, Alice, revealed that:
“For the dam, the water gets muddy and dries up in the dry season. So, we fetch from the well during the dry season. We spend so much time in the dry season looking for water, and then go back to using the dam during the rainy season.”
(Alice, 13)
Another participant commented that:
“During the harmattan season, the dam water becomes horrible. It changes colour because of all the dirt that is carried into it. Right now (i.e., rainy season), it is clean, but later in the dry season, when you fetch it, you will have to add alum to it. Some people drink it even though the colour is green and bad. We considered it to be natural water. It is not that contaminated (Laughing).”
(Milly, 18)

3.3.2. Poor Terrain and Associated Risks

During the interviews, participants identified geographical and environmental barriers that limit access to water in the community. The girls described how geographical features, like eroded footpaths, swamps and waterlogged areas, hindered access to water sources in the study communities:
“Where the well is located, the place becomes very busy and slippery during the rainy season. You cannot fetch water from there when it is bushy and slippery, as you can slip and fall there.”
(Jullie, 15)
Similarly, another participant described an incident of how rainfall and a poor drainage system in the communities created an unsafe environment around the water sources:
“It rained, and there is a gutter around where the borehole is located. Between the houses, some have the drainage systems outside, and all the dirty water from their houses flows onto the paths we used to get to the borehole. This makes the paths very slippery because of the green algae. This becomes very risky when you are carrying the water.”
(Milly, 18)
Beyond the slippery nature of the paths to the water sources, other dangers, such as crocodiles in the dams, were reported by the participants. A participant provided a vivid account by saying:
“If you can’t afford the money to fetch from the standpipes, you have no choice but to traverse busy roads and swamps to access water from wells and boreholes. Even in the dams, crocodiles are lurking, so fetching water from there means risking your life. If you get bitten, it can become a serious problem.”
(Saabie, 17)
Describing the dangerous geographical conditions that surround water collection, one of the participants explained that:
“We fetch from the dam too, but this rainy season you can’t fetch from there again. The place is very bushy, slippery, and dangerous. It is a waterlogged area. The place makes our legs very dirty. It is very bushy, so you can’t see what is on the ground, and any dangerous animal can bite you when you set foot in there.”
(Deripog, 13)
Another participant commented that:
“Sometimes, they wake you up at dawn to get water, and this can be dangerous. I know a few girls that got bitten by snakes while they were on their way to the well.”
(Azara, 13)
When put together, seasonally degraded water quality and physically hazardous terrain show that the environment itself compounds girls’ vulnerability each time they set out to collect water, turning a routine chore into a recurring risk of disease exposure and injury. The fact that mostly girls, rather than other household members, especially boys, are the ones exposed to these risks is strongly influenced by gender norms rather than chance.

3.4. Gendered Social Relations and the Feminization of Water Labour

In the study communities, deeply entrenched patriarchal norms ensure that the burden of navigating these conditions falls overwhelmingly and exclusively on girls. Water collection is culturally constructed as feminine labour, and this construction is actively enforced through cultural norms and expectations that exempt boys and men from water-related duties, household expectations and dynamics, and social pressure on girls. The findings as described below reveal not only who bears the water burden, but also how that burden is amplified by household composition and social dynamics of how the duty is performed.

3.4.1. Cultural Norms and the Feminization of Water Collection

In the study communities, girls were solely responsible for fetching water and ensuring that there was water at the household level. Across all the interviews, participants described water collection as a gendered activity characterized by embedded gender norms and cultural expectations. During the interviews, the girls described water fetching as a duty assigned to them. These cultural norms discourage men from collecting water, irrespective of the household’s water needs. One of the girls clearly elaborated this by stating that:
“It is against our cultural norms. You hardly see a man going to fetch water with a pot or gallon in this community, and that is the truth. It is against our culture for a man to fetch water. Wherever you will find water as a girl or woman, you must go and get it.”
(Charity, 18)
These cultural expectations translate into limited participation and involvement of boys in water-related activities. Even in households that have boys, girls are still responsible for water collection.
“We are seven people in the house, but my cousins, who are boys in the house, don’t help with water collection. If you ask them to help, they will just go out of the house to play. Nobody forces them to take a bucket and go fetch water. They see it as normal for boys not to fetch water. It is a common belief in the community that boys are not supposed to fetch water, so they live by it.”
(Charity, 18)
“We are four in the house (two males and two females). But the boys don’t help in water collection because they believe males are not supposed to fetch water. They don’t want to carry the gallons on their heads as they think other boys will ridicule them. Occasionally they will take a bucket that they can carry by hand even when it is full. They never want to put any water on their heads.”
(Alli, 18)
Gender norms not only determine who fetches water but also determine that, regardless of household size, the full volume of water required must be secured by the girl or girls available. In larger households, the volume of water needed for cooking, cleaning, bathing, and drinking is significantly greater, but the relative prohibition on boys’ participation means that the additional demand falls entirely on girls. Participants in larger households described the disproportionate burden they carry in this regard:
“We are seven people in the house, but my cousins, who are boys in the house, don’t help with water collection. If you ask them to help, they will just run out of the house. They see it as normal for boys not to fetch water. It is a common belief in the community that boys are not supposed to fetch water, so they live by it.”
(Charity, 18)
The concentration of water duty on girls is further compounded by the age and physical capacity of other household members. In households where elderly relatives are present, the physical demands of water collection mostly still fall on girls given that older members cannot contribute, further narrowing the pool of those able to share the burden.

3.4.2. Social Pressure on Water Labour Norms

Gender norms not only assign water collection to girls but also actively govern how that collection is performed. Girls who carry smaller containers risk being labelled lazy or immature, creating a social enforcement mechanism that compels heavier and physically riskier loads.
“When we carry the water from the borehole, our neck really hurts—these village pans are very heavy. But you cannot carry a small pan because they will say you are lazy or weak. As a big girl, you are expected to carry big containers. People will insult you and call you lazy. Sometimes it is risky. I slipped and fell one time when it rained, and my rubber basin broke, but it was very big, which is why it broke.”
(Hannah, 18)
This dynamic directly amplifies the embodied health consequences that girls experience in their water collection duties, with the social cost of appearing to underperform feminine duty overriding the imperative of carrying manageable loads. Consequently, the preceding norms function not as passive background conditions but as active amplifiers of girls’ bodily harm.

3.5. Embodied Health Consequences of Water Insecurity

The intersection of the preceding themes related to structural deprivation, environmental hazard, and gendered labour allocation produces a range of embodied health consequences for girls. These consequences span physical domains such as the risk of exposure to waterborne diseases through contaminated waters, psychosocial domains, and neurological domains, and are not uniformly distributed, with girls in larger households, girls who attend school, and girls with pre-existing health conditions each facing compounding vulnerabilities that are frequently not captured in water-insecurity metrics.

3.5.1. Contaminated Waters

Access to water is integral to the health of girls. Water availability reduces the risks of waterborne diseases. However, in the study communities, girls continued to use unimproved water sources due to the limited number of improved sources in the community.
“They always say that the contaminated water causes us to fall sick, but we don’t have any other choice than to drink that water. If they ask you to stop, you can’t go to the district capital (Wechiau) to get water, so you have to drink it like that. When you are sick, you just go, and the doctors will insult you and give you the medications again.”
(Agnes, 19)
This was corroborated by another participant, who indicated that:
“When you drink water containing the germs, you will vomit, or you will have diarrhoea. It is the water, and we know that, but we don’t have any choice but to drink from there. The NGO brought water to the community, but if you don’t have money, you cannot fetch it from there. It is not free. If you don’t have the money, then you have to fetch from the well.”
(Jamila, 18)

3.5.2. Physical Strain and Fatigue

Beyond exposure to waterborne disease, limited access to water resulted in persistent bodily pains due to travelling longer distances and carrying heavy pans. In the comments below, participants described the pains they experience while carrying water over long distances:
“The water is very far from us. If we have a tap here, it will really help us. We have to travel a long distance to get water. By the time one carries the water from the water source to the house, you sometimes feel chest and leg pain.”
(Zienaa, 13)
“Accessing clean water is a difficult challenge. The water is far away, and when I carry a basin for a long distance, my neck tends to really hurt. But I still have to go and fetch it like 2–3 times a day.”
(Jamila, 18)
Pumping and carrying water from the water points to the house contributes to bodily exhaustion for these girls. As narrated by one of the participants:
“You will pump the water, and that makes you more tired. But after that, you will have to carry it back to the house, which will make you more tired.”
(Alli, 18)

3.5.3. Injuries Through Slips and Falls

Reflecting on the poor environmental terrain and how slippery and bushy the paths to the water sources are, one of the girls vividly described the vulnerabilities she has been exposed to due to the poor nature of the roads:
“I slipped during the rainy season when I was carrying water back home. The paths are bad. I had a dislocation in my leg. I was taken to the community herbalist for treatment, but it took a long time for me to recover.”
(Zienaa, 13)
The poor terrain not only causes girls to slip and fall but also often results in water spilling from the large basins they carry. This forces girls to make repeated trips to secure water.
“The terrain is very bad. You will fetch the water and fall because the place was slippery. You will have to go to the water source multiple times because the water spills, and there is no way you will send an empty basin home.”
(Alima, 15)

3.5.4. Time Poverty and Education Disruption

The cumulative effect of the cost issues, infrastructure deficit, and crowding at water sources for collection results in systematic time poverty for girls, whereby the aggregated time lost to water collection each day runs to several hours. This becomes time that is subtracted from schoolwork, rest, and other productive activities.
“Every day, I go fetch water in the morning before going to school. Immediately after school, then I have to go fetch water for the evening chores. Most days I go to the borehole at least 3 times. Most of the girls in this community are doing the same all the time.”
(Azara, 13)
The time demands of water collection generate specific physiological effects on girls. Early dawn water collection routines disrupt girls’ sleep in ways that carry consequences extending well beyond fatigue. Azara (13) further indicated that:
“My mom would wake me up at dawn, sometimes by 5.00 am or 5.30 am to go and fetch water. I get up early to avoid the morning crowds at the water sources. But sometimes you get there, and there are many people, so you still have to wait for a long time for your turn. But what can one do? You just have to live with it.”
(Azara, 13)
Waking up too early results in sleep deprivation that can cause physiological health harm distinct from the exhaustion produced by physical exertion. Yet, to avoid the crowded water points, many girls begin collection before dawn, a routine that directly curtails sleep, frequently leaving these girls to arrive at school physically exhausted with tiredness and inattentiveness, which can lead to struggling to participate fully in learning, as indicated in the comments below:
“Sometimes you go to school, and you will be sleeping from the tiredness of collecting water early in the morning before going to school. We do this because if you don’t fetch before school, then the water point will be crowded, and you will not get sufficient water for domestic household chores.”
(Agnes, 19)
“The water collection is on us, the girls in the household, so we always plan to fetch some in the morning before school, so that there will be water available for those at home to use.”
(Hannah, 18)
This finding connects water insecurity directly to diminished educational opportunity among girls in the study context. Time poverty functions as the key mediating variable linking structural infrastructure failure to the downstream health and educational harms for girls.

3.5.5. Psychosocial and Emotional Distress

Girls’ navigation of the challenges in accessing water in the study communities often results in feelings of emotional stress and frustration. Water collection has associated stress, as elaborated by a participant below:
“Fetching water in this community is a very stressful activity. If I get to the water point and there are a lot of people, I have to go back home. If I don’t get water because of the crowd, then I have to bring the empty basin and go back early in the morning to try again. It is stressful.”
(Alima, 15)
Competition among girls at the standpipe to acquire this limited resource sometimes results in conflicts and confrontations at the water collection points:
“We sometimes fight physically because someone wants to fetch before you, while you came before that person. But this is out of frustration. We spend so much time at the water collection points, especially at the boreholes, so if someone wants to fetch before you, it leads to arguments and eventually physical fights.”
(Alli, 18)

3.5.6. Neurological Vulnerability and Mobility Restrictions

Findings from the analysis reveal that water collection activities present severe challenges to girls living with neurological conditions such as epilepsy. Study participants with epilepsy discussed how water collection duties expose them to heightened risk of seizures and injuries, especially during episodes of unconsciousness. A participant indicated that despite her health conditions, she is still expected to perform water-collecting duties in the house, and this frequently poses a significant health risk:
“I have epilepsy, which makes me worry and, at times, causes me to have seizures. One time at the dam, I was carrying the basin, and I fell and hit my head and was unconscious for a while.”
(Adeku, 15)
To further illustrate this, the second girl describes how she manages water responsibilities while living with epilepsy:
“When I go to fetch the water, and I feel symptoms of the disease or have the feeling that I will collapse, I will pick up the basin and go back to the house without fetching the water. When I am heading back home, and I start to feel a bit better, then I turn back to the borehole or the pipe to fetch. If I am at the water point and I feel dizzy, my friends who are aware of the disease help me to sit under a shade to get some rest. If I get better, then I fetch the water and come home.”
(Naeema, 15)
Naeema (15) further described the precautions taken by her parents to safeguard her health:
“My parents don’t allow me to go closer to the streams because of the disease. The doctor has made us aware that I am not supposed to get closer to the streams, fire, or even climb trees. They don’t even allow me to sit close to open fires to cook.”
(Naeema, 15)
Overall, the findings show that structural and political barriers related to the cost of water, exclusionary governance, and inadequate infrastructure produce crowding at water sources. These structural failures intersect with environmental hazards, including seasonally degraded water quality and dangerous terrain, and with gendered social norms that assign water collection almost exclusively to girls. Together, these forces converge on girls’ bodies, producing embodied health consequences, including musculoskeletal injury, disrupted sleep and schooling, psychosocial distress, and heightened neurological vulnerability for girls with pre-existing conditions such as epilepsy.

4. Discussion

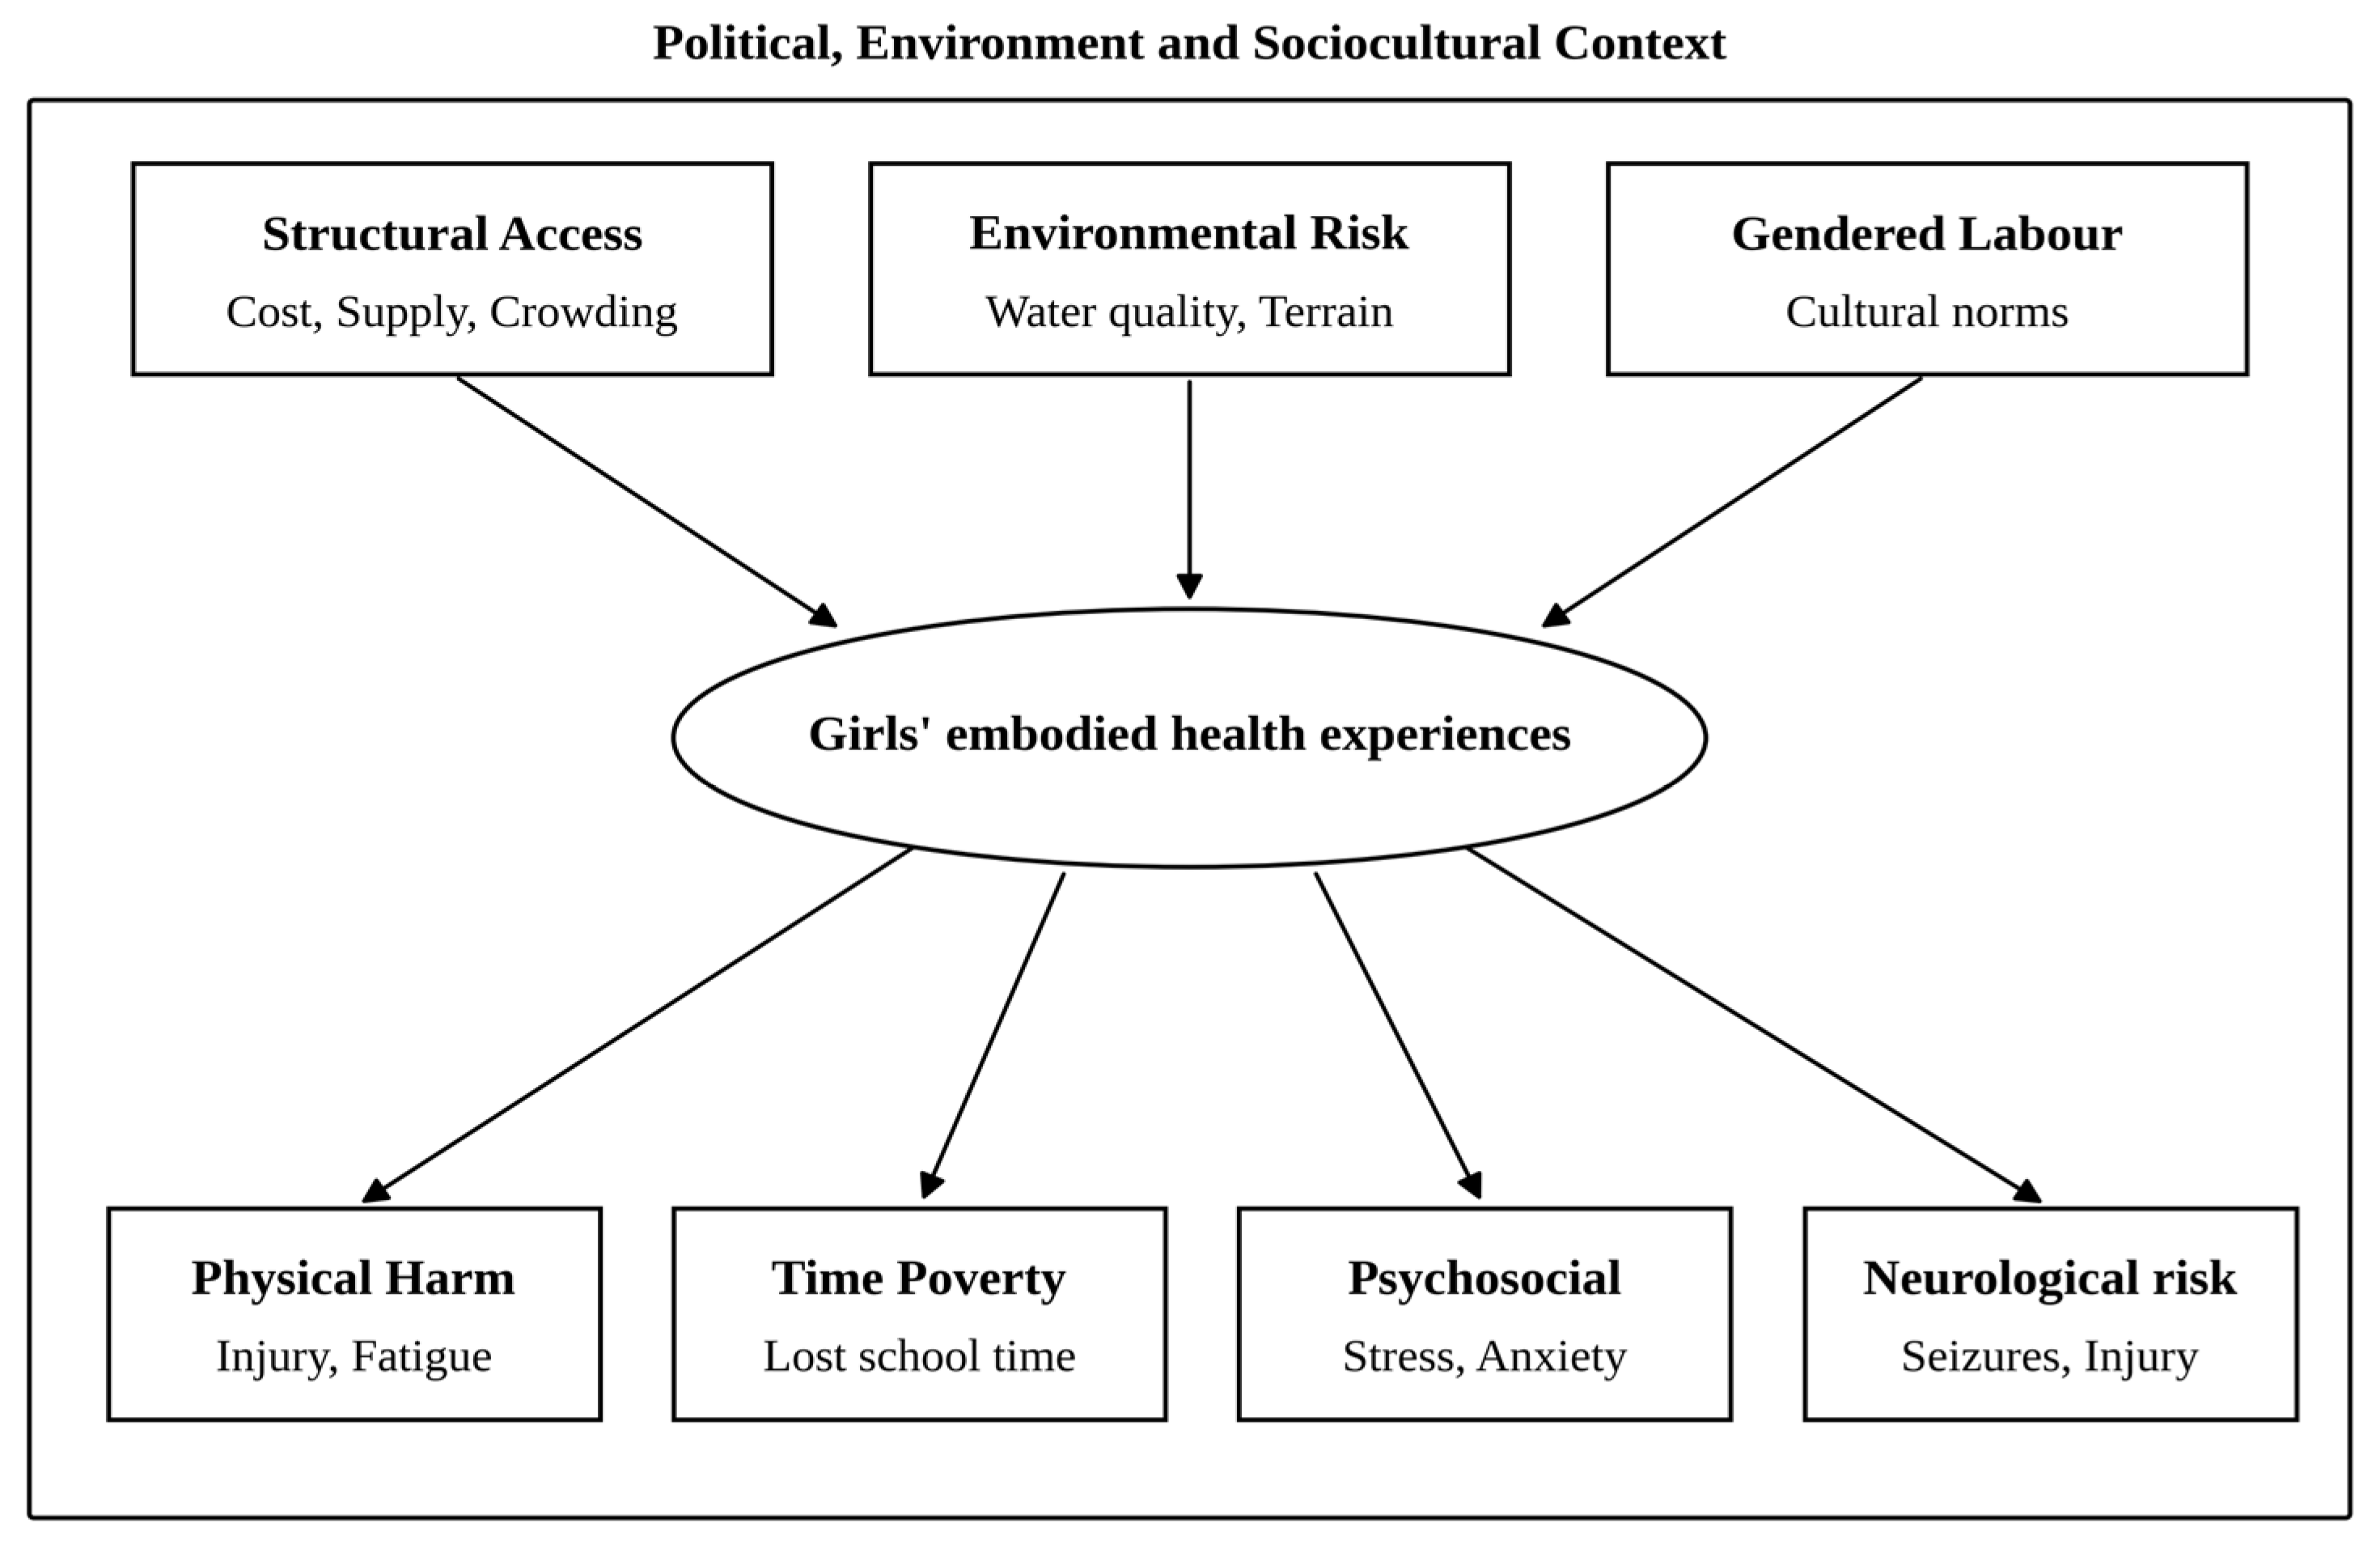
This study aimed to examine how chronic water insecurity shapes the health and well-being of adolescent girls in Ghana’s semi-arid Upper West Region, and to trace the mechanisms through which the daily labour of water collection becomes embodied harm [16,17,18]. A key and novel finding of this study is that water insecurity shapes girls’ health through multiple interacting pathways that converge directly on their bodies, rather than through any single, isolated mechanism (Figure 1). The findings are discussed in line with the four main themes in this paper.
In the Upper West Region (UWR), access to clean water is not simply a natural resource distributed by scarcity, but a political resource whose accessibility is mediated by histories of underinvestment and by both colonial and contemporary governance arrangements that reproduce inequity [19,20]. The cost of water from standpipes, the exclusionary practices of private caretakers, and the chronic inadequacy of borehole infrastructure relative to community demand are not incidental technical failures; they are the outcomes of decades of colonial and post-colonial disinvestment in rural water systems, now overlaid with the commodification of water under privatized management [31,32]. When girls describe being “chased away” from standpipes for lack of payment, or resorting to contaminated water sources because the pipe has been closed by a caretaker, they are narrating the everyday, embodied absorption of macro-level governance failure. That these structural and political–economic conditions become physically inscribed on the body is borne out precisely by this pattern, whereby girls do not merely lack water in their households; they carry the consequences of that lack in aching necks, lost school hours, and heightened health risks [33]. The findings also show that seasonal degradation of dam water during the harmattan, the disappearance of surface water in the dry season, and the challenges of physical terrains represent environmental and ecological conditions that align with the global climate crisis, whose burdens are distributed according to existing social hierarchies [6,34]. Invariably, the girls’ descriptions of treating contaminated dam water with alum because they tend to have “no other choice” illustrates how ecological degradation and structural neglect compound one another (Figure 1).
The structural and ecological burdens of water insecurity fall disproportionately on girls rather than being distributed across household members within the cultural context [22,23]. The findings show that cultural norms constructing water collection as inherently feminine labour operate with deep-seated rigidity, whereby boys in mixed-sex households are mostly exempted from water duties regardless of household need, and this exemption is reinforced through informal social sanction, including the mockery directed at boys who might otherwise help. Girls, meanwhile, face their own disciplining mechanism, the social pressure to carry large, heavy containers so as not to be labelled “lazy” or “weak,” which actively amplifies their physical risk. This dynamic illustrates Kabeer’s (1999) [35] concept of internalized subordination, given that several participants described water fetching not as an imposition but as a natural and inevitable duty, even while describing significant bodily and psychological harm. Within a PEH lens, this normalization is itself a political outcome, one in which patriarchal gender relations function alongside infrastructural and governance failures to determine who absorbs the cost of scarcity. In larger, multigenerational households where elderly members cannot contribute, the pool of eligible water fetchers narrows further, concentrating an already gendered burden on fewer, often younger girls.
The embodied health consequences of water insecurity did not show a reported relationship with the daily water-fetching frequency according to the participants’ accounts. Irrespective of the number of times girls reported fetching water in a day, there was still the experience of persistent bodily pains. This indicates that the water-fetching frequency was not the only operative factor that shaped the embodied experiences of girls in the communities. Rather, the health consequences were a result of the weight of the water load and the distance covered with this load. Girls who reported carrying heavier loads or carrying them over longer distances reported back and neck pains irrespective of how many trips this represented in a day. This finding extends the understanding of water-related health vulnerabilities by suggesting that exposure to water health risk should be conceptualized not simply in terms of the frequency of water collection, but also in terms of its intensity and the conditions surrounding it. Time poverty emerges as a central mediating mechanism within this pathway, whereby girls’ educational trajectories are disrupted specifically because dawn water collection routines are timed to avoid crowding, demonstrating how an infrastructural deficit is converted into downstream harm in both health and human capital terms. Most strikingly, the experiences of girls with disabilities reveal that chronic water insecurity does not simply add to the burden of a pre-existing neurological condition, but qualitatively transforms a manageable condition into a recurring, life-threatening risk, because the gender norm assigning water duty to girls fails to accommodate the needs of girls with health challenges such as epilepsy. The documented health vulnerabilities faced by the girls in the study feed into the broader challenges faced by persons living with disability. In developing countries like Ghana, adolescents living with physical and psychosocial limitations may have difficulties accessing water points, carrying heavy metallic pans and navigating poor terrain, especially during the rainy season. Although our current study was not designed to include disability as a standalone category, environmental challenges and difficulties in accessing water on poor terrain reported by the girls reflects the well-documented impact of water security on persons living with disability, especially in developing countries [36,37,38]. This finding shows that adolescents living with disability form an important population group that should be considered in the design of WASH interventions and extends existing water-security and disability scholarship [39] by revealing that in contexts of extreme water stress, gendered obligation can override rather than accommodate medical vulnerability, a dynamic with direct implications for how disability-inclusive water policy should be conceived in the UWR and across Sub-Saharan Africa. These findings further resonate with the growing body of literature on the climate resilience, gender, and gender inclusion in WASH intervention design. A scoping review by [40] indicates that climatic stressors including extreme heat, drought and flooding act as barriers to water access, creating more disparities, especially for people living with disabilities and neurological conditions, including epilepsy. Re-echoing this finding, in Cambodia [41], it was found that the elderly and persons with disability face significant challenges in accessing WASH services, with gender norms further compounding the challenges rather than accommodating the challenges that these disadvantaged groups constantly face [41].
Prior research has established that water insecurity is associated with emotional distress and diminished psychological well-being [11,13,14,42], and that households deploy a range of coping strategies, from source switching to water rationing, to manage chronic scarcity [15,31]. This study confirms these patterns among girls specifically, but it moves beyond an inventory of coping strategies to specify the causal architecture connecting daily fetching labour to injury, disease exposure, sleep disruption, and neurological risk. In doing so, it responds directly to calls within the water-security literature for research that traces the embodied, physiological pathways of harm rather than treating water insecurity and health as loosely associated domains [9,43,44]. The consistency between this study’s findings on musculoskeletal strain and those reported in South Africa, Ghana, and Vietnam [44] and in Uganda [45] suggests that the mechanisms identified here are not idiosyncratic to the Upper West Region but reflect a more general pattern of embodied harm wherever water collection is feminized and infrastructure remains inadequate. The findings highlight the need for broader research focusing on girls managing pre-existing neurological conditions under conditions of chronic water insecurity. Global health literature on epilepsy in low- and middle-income settings has documented the stigma, mobility restriction, and safety precautions imposed on people living with the condition [39,46] but has rarely examined how these precautions interact with unavoidable subsistence obligations such as water collection.

4.1. Limitations

There are a few limitations worth noting. The use of purposive sampling, while appropriate for reaching girls with direct water-fetching experience, may under-represent those most severely affected by water insecurity, including girls who were unavailable or unwilling to participate. Findings rely on girls’ subjective, retrospective accounts, which may be subject to over- or under-reporting of experiences. The sub-sample of girls living with epilepsy was small, limiting the extent to which the disability–gender relationship identified here can be generalized. However, these accounts nonetheless offer critical insight into an understudied population. Based on these limitations, future research should build on these findings by pairing girls’ retrospective accounts with longitudinal or mixed-methods designs and incorporating objective measures, such as clinical assessments or accelerometry-based indicators of physical strain, to track how water-insecurity-related health harms accumulate and change over time. Future studies should also prioritize larger, purposively stratified samples of girls living with epilepsy and other pre-existing conditions, so that the compounding relationship between gender, disability, and water insecurity can be more robustly quantified and generalized.

4.2. Policy Recommendations

First, coordinated public investment in water infrastructure is needed to close the financing gap in rural water systems, paired with regulatory oversight of privatized water points. For instance, the government should establish enforceable, non-discretionary rules for service suspension to prevent the informal exclusion of the poorest households from accessing safe water. New boreholes and standpipes should be sited closer to residential clusters and away from hazardous terrain, such as swampy or crocodile-inhabited areas, to directly reduce girls’ exposure to injury.
Second, existing social protection programs, such as Ghana’s Livelihood Empowerment Against Poverty (LEAP) scheme, should be extended to subsidize water access for households with school-aged girls and members with chronic conditions such as epilepsy [3], reducing the trade-off between paying for water and relying on contaminated alternatives.
Third, gender-responsive water governance should be institutionalized at the community level, including girls’ inclusion in water management committees, alongside community dialogue that challenges the exclusion of boys and men from water labour rather than treating it as a fixed cultural given. Household investment in rainwater harvesting and storage would also reduce collection frequency, particularly in the wet season, freeing time for schooling and rest.
Fourth, disability-inclusive water policy should be developed within WASH programming, including household-level support for girls with epilepsy or other chronic conditions, community sensitization on collection-related risks, and training for caregivers and peers in recognizing and responding to seizure activity at water points.
Finally, water infrastructure planning in the UWR should be integrated with climate adaptation strategies, including improved borehole technologies and water-quality monitoring for surface sources such as dams that remain in use despite contamination. Only by addressing the political, ecological, and gendered roots of water insecurity together can policy meaningfully reduce the embodied health burden currently carried by girls in semi-arid Ghana.

5. Conclusions

This study has shown that chronic water insecurity in semi-arid Ghana is not merely an infrastructural deficit, but a lived, embodied health crisis disproportionately borne by girls. Viewed through a political ecology of health framework, girls’ aching bodies, disrupted sleep, interrupted schooling, and, for some, heightened seizure risk are not random hardships but are due to the collective contributions of colonial and present-era underinvestment, weak water governance, and entrenched patriarchal norms that are reinforced by climate change. The findings reveal how overlapping structural vulnerabilities can transform a manageable health condition such as epilepsy into a recurring emergency. Coordinated investment in accessible, safe water points; regulated and subsidized pricing; gender-responsive governance that includes girls’ voices; climate-resilient water strategies; and disability-inclusive protections are together necessary to interrupt this cycle. Without such integrated action, the structural burden currently carried by girls in the Upper West Region is likely to deepen as climate stress intensifies across the region. By centering girls’ own accounts of their everyday water insecurity, this study not only contributes to water security and gender scholarship but has also provided useful pointers for water policy reform that recognizes girls as a population requiring urgent, targeted, and sustained attention.

Author Contributions

Conceptualization, M.N.M. and I.L.; Methodology, M.N.M., I.L. and S.A.S.; Formal analysis M.N.M.; Data curation, M.N.M.; Writing—original draft preparation, M.N.M., I.L., S.A.S. and C.K.A.P.; Writing—review and editing, I.L. and S.A.S.; Supervision, I.L. and E.B.; Funding, E.B. All authors have read and agreed to the published version of the manuscript.

Funding

This work received funding from the Government of Canada’s New Frontiers in Research Fund (NFRF), [NFRF-00594].

Institutional Review Board Statement

The study was approved by the Western University Non-Medical Research Ethics Board (NMREB) (REB# 123741, 13 October 2023).

Informed Consent Statement

Informed consent was obtained from all the girls who participated in the study.

Data Availability Statement

Data will be made available on request.

Acknowledgments

The authors are sincerely grateful to all the girls who participated in the study from the two communities: Kandeu and Wechiau.

Conflicts of Interest

The authors declare no conflicts of interest.

References

  1. Apatinga, G.A.; Schuster-Wallace, C.; Dickson-Anderson, S. Exploring the experiences of the overburden of water collection responsibility of rural women in Ghana. J. Water Health 2024, 22, 2015–2039. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  2. Liebenehm, S.; Weyori, A.; Food, W.; Hope, P.L.; Boateng-Gyambiby, D. Water access and school absence among boys and girls: Evidence from rural Ghana. J. Water Econ. 2026, 54, 59–92. [Google Scholar] [CrossRef] [Scilit]
  3. Molle, M.N.; Saaka, S.A.; Bisung, E.; Soliku, O.; Luginaah, I. Cash transfers, beneficiaries’ livelihoods, and co-responsibilities in the context of water and sanitation insecurity in Ghana. J. Water Sanit. Hyg. Dev. 2025, 15, 355–366. [Google Scholar] [CrossRef] [Scilit]
  4. United Nations Children’s Fund. Reimagining WASH Water Security for All. 2021. Available online: https://www.unicef.org/media/95241/file/water-security-for-all.pdf (accessed on 30 August 2026).
  5. Rosińska, W.; Jurasz, J.; Przestrzelska, K.; Wartalska, K.; Kaźmierczak, B. Climate change’s ripple effect on water supply systems and the water-energy nexus—A review. Water Resour. Ind. 2024, 32, 100266. [Google Scholar] [CrossRef] [Scilit]
  6. Brosse, M.; Benateau, S.; Gaudard, A.; Stamm, C.; Altermatt, F. The importance of indirect effects of climate change adaptations on alpine and pre-alpine freshwater systems. Ecol. Solut. Evid. 2022, 3, e12127. [Google Scholar] [CrossRef] [Scilit]
  7. George-Williams, H.E.M.; Hunt, D.V.L.; Rogers, C.D.F. Sustainable Water Infrastructure: Visions and Options for Sub-Saharan Africa. Sustainability 2024, 16, 1592. [Google Scholar] [CrossRef] [Scilit]
  8. International Monetary Fund. Issues in Managing Water Challenges and Policy Instruments: Regional Perspectives and Case Studies. 2015. Available online: https://www.imf.org/-/media/websites/imf/imported-publications/external/pubs/ft/sdn/2015/_sdn1511tn.pdf (accessed on 15 May 2026).
  9. Adams, E.A.; Adams, Y.J.; Koki, C. Water, sanitation, and hygiene (WASH) insecurity will exacerbate the toll of COVID-19 on women and girls in low-income countries. Sustain. Sci. Pract. Policy 2021, 17, 86–90. [Google Scholar] [CrossRef] [Scilit]
  10. Ghana Statistical Service. Ghana 2010 and 2021 Population and Housing Census. Water Report. 2023. Available online: https://census2021.statsghana.gov.gh/ (accessed on 10 June 2026).
  11. Bisung, E.; Elliott, S.J. Psychosocial impacts of the lack of access to water and sanitation in low- and middle-income countries: A scoping review. J. Water Health 2017, 15, 17–30. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Saaka, S.A.; Luginaah, I. Do women’s autonomy lessen the brunt of unequal household responsibilities in the patriarchal context of semi-arid Northern Ghana? PLoS ONE 2025, 20, e0335142. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Kangmennaang, J.; Bisung, E.; Elliott, S.J. ‘We Are Drinking Diseases’: Perception of Water Insecurity and Emotional Distress in Urban Slums in Accra, Ghana. Int. J. Environ. Res. Public Health 2020, 17, 890. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Bisung, E.; Elliott, S.J. It makes us really look inferior to outsiders: Coping with psychosocial experiences associated with the lack of access to safe water and sanitation. Can. J. Public Health 2017, 108, e442–e447. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Baddianaah, I.; Dongzagla, A.; Salifu, S.N. Navigating access to safe water by rural households in sub-Saharan Africa: Insights from north-western Ghana. Sustain. Environ. 2024, 10, 2303803. [Google Scholar] [CrossRef] [Scilit]
  16. King, B. Political ecologies of health. Prog. Hum. Geogr. 2010, 34, 38–55. [Google Scholar] [CrossRef] [Scilit]
  17. Mayer, J.D. The political ecology of disease as one new focus for medical geography. Prog. Hum. Geogr. 1996, 20, 441–456. [Google Scholar] [CrossRef] [Scilit]
  18. Jackson, P.; Neely, A.H. Triangulating health: Toward a practice of a political ecology of health. Prog. Hum. Geogr. 2015, 39, 47–64. [Google Scholar] [CrossRef] [Scilit]
  19. Sultana, F. Suffering for water, suffering from water: Emotional geographies of resource access, control and conflict. Geoforum 2011, 42, 163–172. [Google Scholar] [CrossRef] [Scilit]
  20. Swyngedouw, E. Social Power and the Urbanization of Water: Flows of Power; Oxford University Press: Oxford, UK, 2004. [Google Scholar]
  21. Pienaah, C.K.A.; Amoak, D.; Batung, E.; Dassah, C.; Molle, M.N.; Antabe, R.; Luginaah, I. Water supply sources, management committees, and water insecurity in semi-arid northwest Ghana. Sustain Water Resour. Manag. 2025, 11, 85. [Google Scholar] [CrossRef] [Scilit]
  22. Rocheleau, D.; Thomas-Slayter, B.; Wangari, E. Feminist Political Ecology; Psychology Press: East Sussex, UK, 1996. [Google Scholar]
  23. Sultana, F. Fluid lives: Subjectivities, gender and water in rural Bangladesh. Gend. Place Cult. 2009, 16, 427–444. [Google Scholar] [CrossRef] [Scilit]
  24. Tallman, P.S.; Salmon-Mulanovich, G.; Archdeacon, N.; Kothadia, A.; Lopez Flores, L.; Castañeda, K.; Collins, S.; Rusyidi, B.; Cole, S. “Gender-Based Water Violence”: Cross-Cultural Evidence for Severe Harm Associated With Water Insecurity for Women and Girls. Violence Against Women 2025, 31, 916–932. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Chitukula, C.; Wrigley, K.; Nyanjom, J.; Godden, N.J. Centring girls in water justice research and social movements. Environ. Dev. 2026, 59, 101471. [Google Scholar] [CrossRef] [Scilit]
  26. Szaflarski, M. Social determinants of health in epilepsy. In Epilepsy and Behavior; Academic Press Inc.: London, UK, 2014; pp. 283–289. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Yin, R.K. Case Study Research: Design and Methods; Sage Publication: Thousand Oaks, CA, USA, 2014. [Google Scholar]
  28. Braun, V.; Clarke, V. Using thematic analysis in psychology. Qual. Res. Psychol. 2006, 3, 77–101. [Google Scholar] [CrossRef] [Scilit]
  29. Gibbs, G. Analyzing Qualitative Data, 2nd ed.; Steele, M., Nightingale, J., Eds.; SAGE Publications: Thousand Oaks, CA, USA, 2007. [Google Scholar]
  30. Lincoln, Y.S.; Guba, E.G. Naturalistic Inquiry; Sage Publication: Thousand Oaks, CA, USA, 1985. [Google Scholar]
  31. Pienaah, C.K.A. Community resource management areas and household food security in northern Ghana: Insights from a socio-ecological systems perspective. Policy Econ. 2025, 180, 103628. [Google Scholar] [CrossRef] [Scilit]
  32. Foster, V.; Briceño-Garmendia, C. Africa’s Infrastructure. In Proceedings of the Africa Development Forum, Washington, DC, USA, 10–15 October 2010. [Google Scholar]
  33. Moss, P. Inquiry into environment and body: Women, work, and chronic illness. Environ. Plan. D 1985, 14, 737–775. [Google Scholar] [CrossRef] [Scilit]
  34. Rosińska, W.; Przestrzelska, K.; Wartalska, K.; Grzegorzek, M.; Wdowikowski, M.; Czerska, Z.; Kaźmierczak, B. Rainwater harvesting for watering greenery at Polish university as a climate change adaptation strategy. Bull. Geogr. 2025, 7–22. [Google Scholar] [CrossRef] [Scilit]
  35. Kabeer, N. Resources, Agency, Achievements: Reflections on the Measurement of Women’s Empowerment. Dev. Change 1999, 30, 435–464. [Google Scholar] [CrossRef] [Scilit]
  36. Azupogo, U.W.; Dassah, E.; Bisung, E. Navigating water and sanitation environments in schools: Exploring health risk perceptions of children with physical disabilities using drawing. Wellbeing Space Soc. 2025, 8, 100255. [Google Scholar] [CrossRef] [Scilit]
  37. Nishu, N.A.; Roy, T.; Razu, S.R.; Akter, S. Barriers to Accessing Water, Sanitation, and Hygiene Services for Persons With Disabilities in the Southwestern Region of Bangladesh. SAGE Open 2025, 15, 21582440251380013. [Google Scholar] [CrossRef] [Scilit]
  38. Dosu, B.; Hanrahan, M. Barriers to Drinking Water Security in Rural Ghana: The Vulnerability of People with Disabilities. Water Altern. 2021, 14, 453–468. [Google Scholar]
  39. Boling, W.; Means, M.; Fletcher, A. Quality of life and stigma in epilepsy, perspectives from selected regions of Asia and Sub-Saharan Africa. Brain Sci. 2018, 8, 59. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  40. Wilbur, J.; Kovats, S.; Ruuska, D.; Nawaz, S.; Natukunda, J. Climate change, disability, and water, sanitation and hygiene: A scoping review of evidence and interventions in low and middle-income countries. PLoS Glob. Public Health 2025, 5, e0003676. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  41. Ang, R.; Cumming-Bruce, A.; Grant, M.; Chhaing, M.; So, L.; Kim, H.; Has, R.; Khath, D.; Iv, B.; Kry, V. Strengthening systems for inclusive climate resilient water, sanitation and hygiene services in Cambodia. H2Open J. 2026, 9, 100003. [Google Scholar] [CrossRef] [Scilit]
  42. Mushavi, R.C.; Burns, B.F.O.; Kakuhikire, B.; Owembabazi, M.; Vořechovská, D.; McDonough, A.Q.; Cooper-Vince, C.E.; Baguma, C.; Rasmussen, J.D.; Bangsberg, D.R. “When you have no water, it means you have no peace”: A mixed-methods, whole-population study of water insecurity and depression in rural Uganda. Soc. Sci. Med. 2020, 245, 112561. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  43. Azupogo, U.W.; Achore, M.; Dery, F.A.; Bisung, E. Health implications of coping with water insecurity at the household level. Water Secur. 2023, 19, 100135. [Google Scholar] [CrossRef] [Scilit]
  44. Geere, J.A.; Bartram, J.; Bates, L.; Danquah, L.; Evans, B.; Fisher, M.B.; Groce, N.; Majuru, B.; Mokoena, M.M.; Mukhola, M.S. Carrying water may be a major contributor to disability from musculoskeletal disorders in low income countries: A cross-sectional survey in South Africa, Ghana and Vietnam. J. Glob. Health 2018, 8, 010406. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  45. Asaba, R.B.; Fagan, G.H.; Kabonesa, C.; Mugumya, F. Beyond Distance and Time: Gender and the Burden of Water Collection in Rural Uganda. J. Gend. Water 2013, 2, 31–38. [Google Scholar]
  46. Birbeck, G.L. Epilepsy Care in Developing Countries: Part II of II. Epilepsy Curr. 2010, 10, 105–110. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Figure 1. Framework of girls embodied experiences in the context of water insecurity.
Ijerph 23 01142 g001
Table 1. Background characteristics of participants (N = 19).
VariableFrequencyPercentage (%)
Age
10–12210.53
13–15736.84
16–191052.63
Current Level of Education
Primary736.84
Junior high school526.32
Senior high school315.79
Dropouts421.95
Location
Wechiau1157.89
Kandue842.11
Water-Fetching Frequency per Day
1–3526.32
4–61157.89
7 or more315.79
Average Water-Fetching Time (Per Trip)
Less than 30 min947.37
More than 30 min 1052.63
Household Size
1–5947.37
6–10631.58
11 or more members421.05
Health Conditions
Neurological conditions (epilepsy)210.5
No health conditions 1789.5
Table 2. Codes: code description, sub-themes, major themes, and exemplars that emerged from interviews.
Code Number of Mentions (Number of Participants)Code DescriptionSub-ThemeTheme
(PEH Domain)
Exemplar
Water cost39 (17)Financial cost of accessing water from standpipesCost of waterStructural and political determinants of access to water“The tap is not free; you have to pay for it… It is because of the money, that is why we fetch from the borehole.” (Naah, 12)
Water governance10 (5)Active exclusion of households from infrastructure-supplied water by caretakers; pipe closures by managing individualsWater governance failure“People who don’t have money or owe money for water are chased away by the caretakers. Sometimes the pipe does not flow, or it is closed by the caretakers, so our option is the dam.” (Memuna, 16)
Infrastructure39 (19)Quantitative inadequacy of water infrastructure relative to community demand, forcing reliance on unimproved sourcesInfrastructure deficit“There is a borehole down there opposite the roadside. We also have water connected to our house, but because of the money, it is locked, and we have to move to the well to fetch water. That place too is far.” (Fortune, 18)
Crowding24 (17)Long queues at water points that delay access and force repeated tripsCrowding of girls at water sources“If the borehole is crowded, it looks like the whole community is there. When you are not getting water, you have to go back home, eat, and go back to fetch.” (Juliet, 18)
Water quality25 (8)Perception of cleanliness and suitability of water quality during wet and dry seasons for usePerceptions of water qualityEnvironmental and ecological conditions“The dam water is green in colour, but the well water also looks whitish… But we just drink it like that.” (Alice, 13)
Poor terrain15 (7)Challenging environmental conditions that hinder and endanger water collectionPoor terrain and associated risks“There are even crocodiles. There was a time we went there, and crocodiles were coming out of the water.” (Naah, 12)
Cultural norms35 (15)Social and gender norms that dictate water collection as an exclusively feminine dutyCultural norms and feminization of water collectionGendered social relations“They are big boys so they can’t carry pans or gallon… They always say that men don’t do house chores.” (Charity, 18)
Social pressure12 (9)Social policing of load size through insults directed at girls who carry smaller containers, compelling heavier and riskier loadsSocial pressure on water labour norms“You cannot carry a small pan because they will say you are playing. As a big girl, you are expected to carry big ones; they will insult you and call you lazy.” (Hannah, 18)
Contamination19 (7)Exposure to disease-causing pathogens through unavoidable use of contaminated water sourcesContaminated watersEmbodied health consequences“They always say that the contaminated water causes us to fall sick, but we don’t have any other choice than to drink that water.” (Agnes, 19)
Fatigue and tiredness36 (17)Exhaustion from manually pumping and carrying water over long distances, repeated multiple times dailyPhysical strain and fatigue“Carrying a big basin from the water sources over long distances to the house makes us very tired… and this is an activity that we do repeatedly.” (Alli, 18)
Slips and falls7 (6)Physical injuries resulting from navigating slippery, swampy, and uneven terrain while carrying heavy water containersInjuries through slips and falls“The place is mostly slippery during the rainy season, so I slipped and had a dislocation in my leg.” (Zienaa, 13)
Time poverty44 (19)Systematic depletion of girls’ discretionary time through cumulative water collection demands, limiting rest, education, and productive activityTime poverty and education disruption“We always plan to fetch some in the morning before school, so that there will be water available for those at home to use.” (Agnes, 19)
Stress10 (8)Feelings of stress, anxiety, and frustration arising from chronic water insecurity and collection challengesPsychological and emotional distress“Fetching water in this community is a very stressful activity. If I get to the water point and there are a lot of people, I have to go back home. It is stressful.” (Alima, 15)
Seizures7 (3)Episodes of seizures triggered or worsened by the physical demands of water collection among girls with epilepsyNeurological vulnerability and mobility restrictions“I have epilepsy, which makes me worry and, at times, causes me to collapse. One time at the dam, I was carrying the basin, and I fell and hit my head and was unconscious for a while.” (Adeku, 15)
Total number of mentions (number of participants who discussed the code): n = 19.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.