1. Introduction
Mate wareware has been described as a Māori cultural concept underpinned by mātauranga Māori, reflecting a Māori understanding of changes commonly described as dementia [
1]. The 2020 Dementia Economic Impact Report projected that approximately 167,000 people would be living with dementia in Aotearoa New Zealand by 2050, including about 12,000 Māori [
2]. However, Aotearoa New Zealand has not undertaken a nationwide community-based dementia prevalence study. The projections in the 2020 Dementia Economic Impact Report applied prevalence data derived from international research to New Zealand population projections, while more recent national analyses have used routinely collected health data [
2,
3,
4,
5,
6]. Capture–recapture analysis of three linked national health datasets estimated that 47.8% of dementia cases were not present in any of the datasets, with larger estimated gaps for Māori, Pacific, and Asian peoples than for Europeans [
3]. Analyses of routinely collected national data also indicate higher age- and sex-standardised dementia prevalence among Māori than Europeans [
4,
5]. A nationwide analysis of young-onset dementia similarly found higher age- and sex-standardised prevalence among Māori than Europeans [
6]. In one New Zealand memory service, Māori patients presented on average 8.5 years younger than New Zealand European patients [
7]. Dyall [
8] argued that dementia policy and planning for Māori must account for socioeconomic determinants across the life course, the ongoing effects of colonisation, whānau realities, and Māori rights under Te Tiriti o Waitangi, rather than treating dementia primarily as a consequence of chronological age. These national findings are consistent with a 2024 systematic review of dementia prevalence among Indigenous populations in very-high-HDI countries, which reported higher age-standardised prevalence among Māori than European New Zealanders and more pronounced disparities at younger ages [
9]. Together, this literature points to inequities in dementia burden and recognition, with implications for when and how Māori whānau reach assessment and support.
These inequities extend into aged care more broadly. Among older people with daily care needs, Māori are about half as likely as non-Māori to access community-based aged care, while non-Māori enter aged residential care at almost twice the rate of Māori [
10]. Hikaka et al. [
10] situate these inequities within a health system shaped by colonisation and structural racism. Recent kaupapa Māori research with older Māori and whānau has further identified structural barriers to aged residential care, including difficulties navigating care pathways, obtaining and using information about care options, and accessing appropriate services close to home [
11]. Lapsley et al. [
12] found that Māori received more hours of informal care, meaning unpaid care provided by whānau, friends, or others in existing relationships, with a higher estimated dollar value than non-Māori. Together, these studies show that lower use of formal aged care services coexists with substantial unpaid caregiving, making both access to support and the way services respond to Māori relevant to equity.
Dudley et al. [
1], drawing on kaupapa Māori research with 223 kaumātua and eight whānau, identified Te Oranga Wairua as central to Māori understandings of mate wareware and described its effects as extending across whānau, hapū, and communities rather than being confined to an individual. Their findings emphasised aroha (love and compassion) and manaakitanga (care, hospitality, and generosity) in caregiving and described “mana-enhancing” relationships as informed by aroha, manaakitanga, whakapapa, and whanaungatanga (relationships and connections) [
1]. Te Maringi Mai o Hawaiiki et al. [
13] similarly identified wairuatanga as important to Māori wellbeing in the context of mate wareware, with kaumātua accounts linking it to social connection, tūrangawaewae (places of connection), identity, and mindful practices. Together, this literature positions mate wareware care as relational and culturally situated, extending beyond cognitive change alone.
Research on whānau care of kaumātua also points to challenges within collective care systems. Simpson et al. [
14] found that structural holes within collective whānau care systems can create coordination challenges and leave primary carers’ knowledge, preferences, and self-care needs unseen despite extensive whānau support. How these dynamics operate specifically in mate wareware care remains less clear; Simpson et al. [
14] did not specifically examine care recipients’ health conditions and identified dementia as a relevant direction for future research. These questions sit within a statutory context that continues to prioritise health equity. The Healthy Futures (Pae Ora) Act 2022 [
15], as amended in 2026, retains a statutory purpose of achieving equity in health outcomes, including by addressing disparities particularly affecting Māori, and provides iwi-Māori partnership boards with a role in representing local Māori community perspectives on health outcomes, informed by their needs and aspirations. Taken together, this literature leaves an important gap in understanding how whānau Māori experience support for mate wareware across whānau and community life, including encounters with health and aged care services, what they find helpful, and what they consider necessary.
A kaupapa Māori research approach centres Māori knowledge, perspectives, and priorities and responds to Indigenous critiques of the historical relationship between research, colonialism, and the control of Indigenous knowledge [
16]. Haitana et al. [
17] show how kaupapa Māori research can privilege Māori participants’ expertise while directing attention to clinical, organisational, and structural features of health systems. Drawing on a kaupapa Māori qualitative study involving co-design hui with seven kaumātua and in-depth hui with ten whānau Māori, this study asks: how do whānau Māori describe the experience of supporting a whānau member with mate wareware, including the support they find helpful and what they consider important for mate wareware-friendly communities? By foregrounding whānau accounts, the study seeks to identify implications for dementia health and social care services across wider contexts in which mate wareware care occurs.
3. Results
The analysis developed four interconnected themes: Delayed Recognition; Whānau Caregiving: Collective Strength and Concentrated Responsibility; Sustaining Wairua, Identity, and Belonging; and Care Transitions and Structural Barriers.
3.1. Delayed Recognition
Across many accounts, recognising mate wareware was a slow, retrospective process of reinterpreting behaviour that had previously been explained in other ways. One participant reflected, “there’s a lot of mystery around it... we didn’t really take that as a red flag,” describing signs that in hindsight had been present for at least a decade before formal diagnosis. Another explained that a relative “could be going along for a long time without anyone recognising” the changes, because whānau would “just put it aside” and assume they were simply being hōhā (frustrated, bothered). A further participant recalled repeatedly raising concerns before a diagnosis was made: “no one listened to me for about four years, until they finally diagnosed it... I told the whānau, and even doctors didn’t listen... I was angry.” Another reflected, “no one in our family talked about dementia... it was just like general ageing.”
Underpinning this delay was a recurring knowledge gap: whānau wanted specific, staged, and culturally grounded information about what mate wareware is, how it progresses, and what to expect, but described difficulty accessing it. “We didn’t even really know about what was Alzheimer’s as well as the dementia,” one participant reflected. “It would have been cool if we had seminars or workshops.” Navigating mate wareware without this kind of culturally grounded knowledge was, for some, isolating: one participant described it as “the blind leading the blind, feeling real isolated.” “A lot of Māori people need to be taught what the disease is all about,” another said, describing a wish for visual, staged, Māori-facilitated education delivered alongside cultural activity rather than through clinical pamphlets alone. Participants also described building knowledge as a collective responsibility within Māori communities: “Bring it up. Because our people have got this disease. Teach it to our people. We have to. We’re only helping our own.” Participants wanted this knowledge shared earlier and across generations, “not just single generations… tamariki, rangatahi, pakeke, kaumātua”, while “keeping it empowering, whakamana i te whānau.”
Whakamā (ashamed, shy, embarrassed) and fear of judgement also discouraged open discussion. As one participant explained, “they don’t talk about it, like it’s a spell, a tapu [sacred, restricted].” Participants described relatives who avoided kaumātua groups “in case they make a fool of themselves,” and whānau who “hide it underneath the carpet” out of concern for the family’s name being shamed. For some, concealment was connected to standing within the community. One participant whose whānau member was well-known said, “I don’t like letting other people know what’s wrong with my family.” One participant also distinguished the role of karakia (prayer) from understanding mate wareware, emphasising that blessing alone would not resolve the condition. Reluctance to ask for help was also evident: “you don’t ask, you won’t get any,” as one participant put it.
Across these accounts, recognition was not simply an individual’s ability to notice mate wareware, but a socially and culturally mediated process.
3.2. Whānau Caregiving: Collective Strength and Concentrated Responsibility
Whānau caregiving was described as a collective strength, grounded in relationships, reciprocity, community, and whakapapa. As one participant explained: “The best supports were our relationships with each other. Māori are really good; the community is wrapping around... the kūmara (sweet potato) vines shoot out... people jump into gear or do what has to be done.” Caregiving was also understood as a responsibility grounded in whakapapa: “That’s why Māori services continue … it’s like a whakapapa, so you don’t drop your family member.” Participants described stepping into caregiving because it was reciprocal (“They brought me up, so I’m gonna help”), because it was simply “the way you should,” or because care was expected when a whānau member needed support. One participant described providing personal care for their father as “very whānau, very Māori,” explaining, “It’s my way of giving back and staying linked.” These expectations were not universal; one participant described a father who had explicitly stated that they did not want to be cared for by their own children if they became unwell, and whose wishes were respected.
This collective responsibility was not always shared evenly, with caregiving becoming concentrated in one or two whānau members. Responsibilities including showering, medication, appointments, managing night wandering and incontinence, and responding to crises could fall on the same people over extended periods, with respite arriving late or not at all. One participant described the cumulative toll: “it was really impacting on my whole life and my work. I said, I’m not coping. I need someone to come and give the caregiver a break.” Another described going without any break until residential placement: “I was staying close by them and didn’t have a break from it. The first time they went in, I slept for about two days.” Sustained caregiving also had employment and physical consequences: “my sister retired early... their back started going out on them... they’ve done their work; they can’t do any more, because they’ve stuffed their body.”
Whānau described experiences consistent with anticipatory grief, including an ongoing sense of loss as relationships changed with the progression of mate wareware. “It’s like they’re dead but they’re alive,” one participant said. Whānau also described creating joyful moments through dancing, singing, and humour, and taking photographs and videos “to keep them with us … we’re losing them twice.” Others described the distress of being met with unrecognition or hostility while continuing to provide care: “when they’re terse to me or upset and they don’t recognise me, it’s quite traumatising for myself as well... it’s exhausting on top of everything.”
Concentrated caregiving responsibility could be lonely, even where other whānau members were involved. One participant explained: “I still feel alone because I carry it. I carry it all… I am the coordinator.” Another reflected: “they’re on that journey by themselves. No one’s ever gonna understand that really, that’s half of the problem, is cause they’re lonely.” These accounts distinguished whānau involvement from the experience of carrying day-to-day responsibility, including coordinating others’ involvement. Participants valued opportunities to connect with other whānau navigating similar experiences, share what they had learned, and support one another, but described few opportunities to do so. One participant reflected: “getting all the whānau members together… see how far they’ve got and what they did… you can just feed off each other.” Another described the need for “a system or a network that whānau can link in with… so that we didn’t feel so alone.”
Across these accounts, whānau caregiving was sustained through aroha, whakapapa, reciprocity, and community strength, while concentrated responsibility could come at considerable personal cost.
3.3. Sustaining Wairua, Identity, and Belonging
Changes associated with mate wareware did not diminish who the person was or how they should be regarded and treated. As one participant put it: “You put the disease out there to say that that’s the problem, and not them personally … you still got to treat them the same way you treated them when they didn’t have it.” For another participant, this continuity encompassed their name, whakapapa, and collective mana: “It’s really important that they go with the integrity and the mana of our name.”
One participant described the importance of knowing something about other residents beyond their names: “In Māoridom, knowing about someone is rongoā, is about healing. And so when I go in every night, I only know their first names. I’ve suggested we have a little bit about the people; it links us, and this is a form of pepeha that they can’t often provide, but it allows visitors to know a little, enough to respect, to be a bit more respectful.” Pepeha can express a person’s connections to people, whakapapa, and place.
Whakapapa and identity were sustained through connection to familiar places, including taking a relative to the marae (Māori communal meeting place). One participant emphasised the importance of familiar surroundings: “put them amongst what they had before, don’t let them lose it.” Another explained, “they know spaces and places like where they were raised,” while “people will know of them.”
Community and neighbourhood belonging also sustained connection for people living with mate wareware. Participants described coffee groups, kapa haka (Māori performing arts) and ukulele groups, kaumātua lunches, and neighbours who “know when the bloody jug’s on.” One participant pointed to the role of waiata (song), explaining that “music can do that, especially Māori people as well cause that’s part of our culture,” and described environments built around “having kai, having people, having waiata, having waiata-ā-ringa” (action songs), where “anyone can visit... ‘come on in’... and let them be supported.”
Participants also described wairua as remaining present and responsive even when recognition had changed. “They know of the vibe and wairua of people, but they don’t know where they place,” one participant explained. Another noted that “this person... won’t realise that you’re doing it wrong,” “the thing is, their spirit will. Their wairua will.” Tikanga could similarly remain meaningful as mate wareware progressed. One participant described a relative continuing to follow tikanga around water and personal cleansing, explaining, “that’s a Māori thing, that’s water,” and questioned whether future care environments could accommodate this practice.
Participants described seeking Māori providers, navigators, and other culturally grounded forms of support, including assistance with practical needs, kaumātua activities, and cultural support within residential care. One participant described searching for “somewhere like [a local kaupapa Māori health provider] … you just gotta hunt them out.” Another described choosing a dementia unit because it felt culturally familiar, with Māori and Pacific staff, explaining simply: “this is the place.” A participant with experience of both mainstream and Māori-specific services for the same relative described the difference in terms of continuity: “The services that stayed with them were the Māori services; the services that left them at the door were non-Māori, mainstream.” The same participant noted, “They still to this day have a Whānau Ora navigator…” Other participants described mainstream services asking about cultural needs and adapting accordingly, although this could sometimes feel like “ticking the box.”
Participants also described what dedicated kaupapa Māori residential care for people living with mate wareware could look like. One participant envisaged a unit staffed by Māori and Pacific kaimahi (workers, staff) so that care was “not always reliant on the whānau teaching the staff.” The participant also identified the importance of space for whānau to stay overnight: “A whānau room, or down the hall, where I will see them in the morning.” Another envisaged residential care organised around community and cultural life: “creating like a marae-centred residential unit… a community where everyone knew each other… had people to support them, they had whānau… there could be activities they could be involved in.”
Isolation could arise when community, cultural, and relational connections were disrupted, including through distance from marae and community. One participant described this: “no one, really… it was just us… they were living away from their community… we can’t always go back home to our marae.” Another traced their mother’s loneliness to moving away from a community that had previously “kept an eye out,” reflecting that they had “never thought about that until I just thought about it now.” Participants also described meaningful activities falling away when the relationships and environments that had supported them were no longer present, including a relative no longer engaging in weaving that had previously been central to their life.
3.4. Care Transitions and Structural Barriers
Whānau described gaps in continuity, coordination, and culturally responsive care within formal health and aged care services that they often worked to bridge.
Participants described limited contact hours: “we had community support... just two hours a week.” Others described a lack of communication about what was happening: “they all knew what they were going through but none of them would openly talk about what’s going on enough… the silence was kind of deafening.” Continuity, where it occurred, was valued. One participant described keeping the same support worker for seven years because a new person would “not know them, and it’d be starting again.” Participants also described a lack of coordination across providers: “there needs to be a lot more collaboration with other services… how can we all work more collectively to reduce those barriers so that care can happen?” Navigating services could also be difficult: “a lot of families don’t know how to go about it… they don’t know how to go about it, who to ask.” One participant wanted “someone relatable... who could guide us through the system,” while another described learning about potentially helpful support only after their relative had passed: “things like that... we didn’t know about until after they had passed.”
Participants described instances where residential care practices did not readily accommodate tikanga. One participant described the negotiation involved in sharing kai (food): “can I share this kai? There’s rules around that. Can we get consent from the family? I get those complications, but culturally it’s quite tricky. The importance of cultural food is not just about the giving. It’s actually the whakapapa of the kai, the manaaki, the hospitality of that.” Facility naming was also raised as relevant to whether a service felt culturally connected to the Māori community it served. Another connected their experience of placement in a facility that felt like “the back burner” with an earlier history of institutional schooling that had contributed to the loss of te reo (the Māori language) within their whānau. The same participant questioned whether being Māori had shaped their whānau’s experiences more broadly: “I don’t know if this is a because you’re Māori thing, but in our experiences, that’s what had happened to us before.”
Residential placement emerged as a distinct transition marked by guilt and emotional difficulty for whānau. Some participants related this difficulty to expectations about caring for kaumātua at home. “They never wanted to be in that situation... we tend to die at home,” as one participant put it. Another explained: “we were always brought up… you don’t put your folks in a home; you don’t put your kaumātua in a home. So, I really struggled with it.” One participant described the day of placement: “driving them to the unit, I said, ‘I’m sorry... I have to put you here... it’s not an easy one, because I’d love to still have you.’ They said, ‘It’s okay... it’s okay.’ A little bit after that they said, ‘right, where are we going now? Are we going out?’ Like, oh my God, I’ve just said all this...” Another described the continuing guilt associated with placement: “the guilt I have is massive, massive, over putting [my relative] into a unit... when I go in and see them, I’m immediately relieved of my guilt. It becomes a medicine.”
Continued whānau presence after residential placement was also described as important for the person living with mate wareware: “if you don’t go in to see them because you’re afraid of that place, it’s affecting them,” as one participant explained. Whānau also described trying to preserve familiarity and connection within institutional settings: “we tried to kind of make it feel homely for them, put their photos up... it was real hard leaving them in a foreign place.” Participants also expressed concerns about the care their relative received: “that is not just a Māori family being disconnected to their culture,” one participant reflected, “but also that Māori family... feels like they’re not getting the best treatment for their whānau member.” Residential placement therefore did not end whānau involvement in care.
4. Discussion
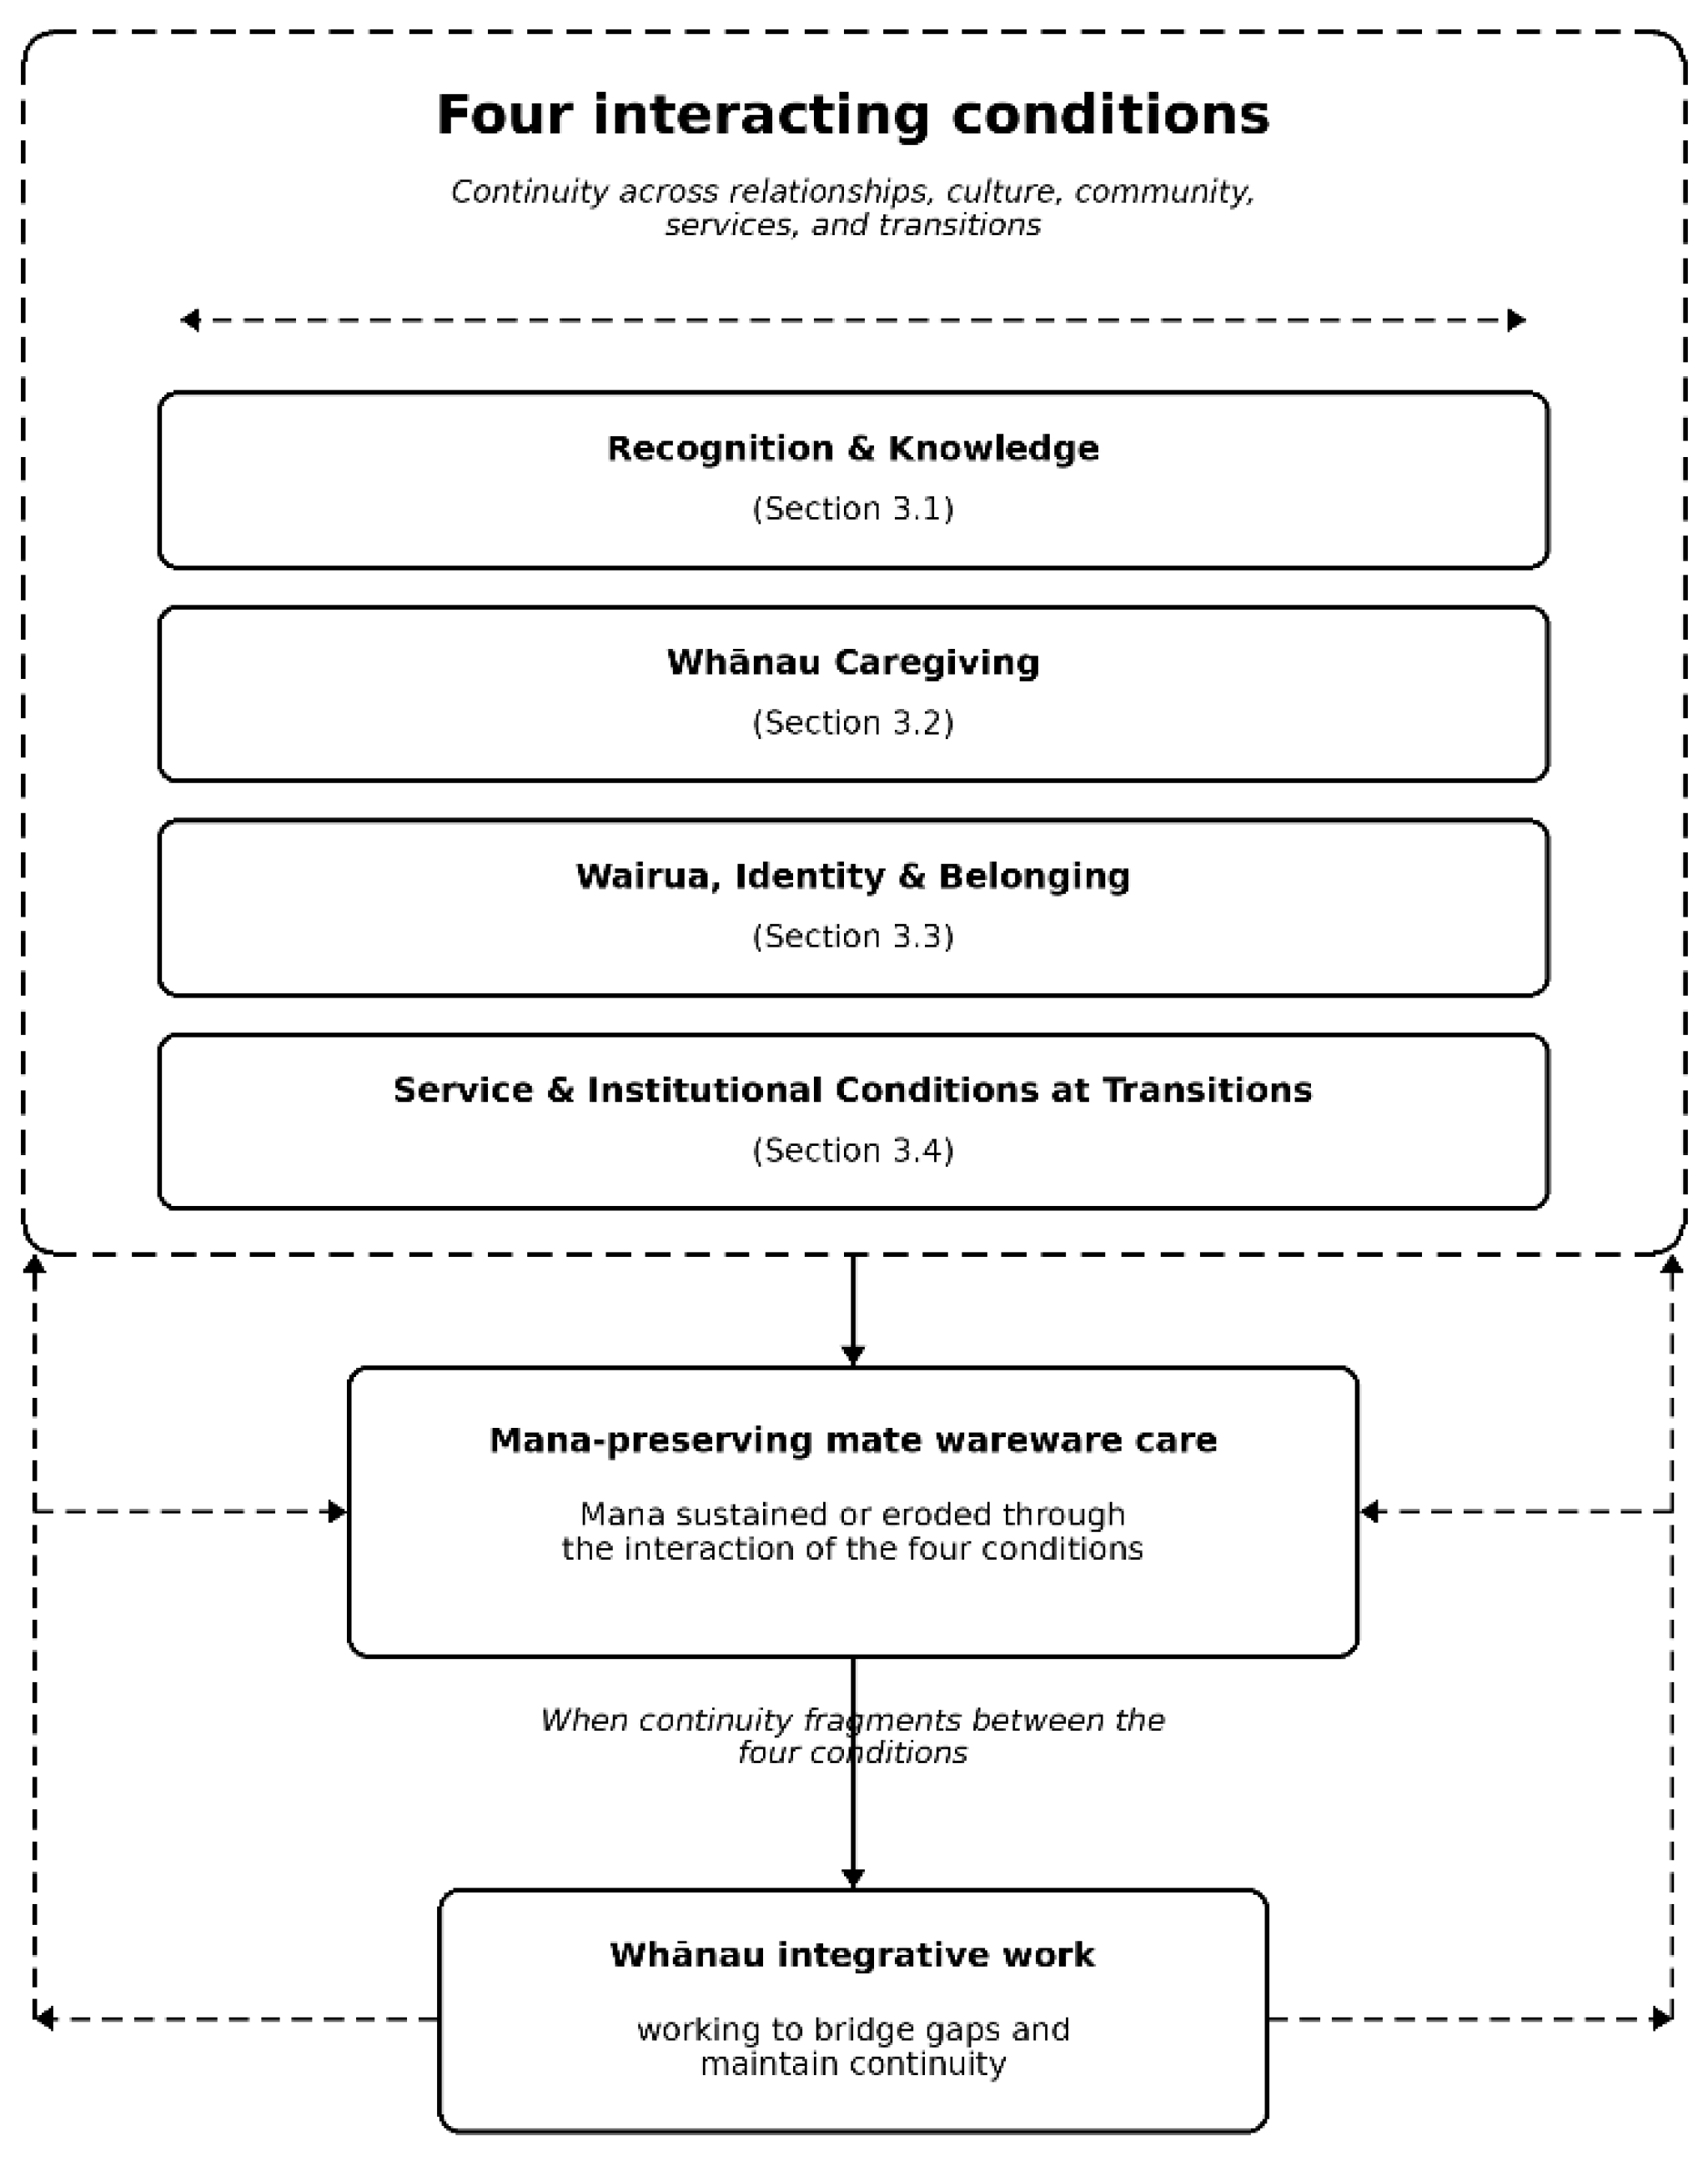
Mana-preserving mate wareware care is not located in a single interaction, service, or point in the care journey. Interpreted together, the four empirical themes informed four interacting conditions through which mana was sustained or eroded: delayed recognition informed recognition and knowledge; collective strength and concentrated caregiving responsibility informed whānau caregiving; sustaining wairua, identity, and belonging informed the corresponding condition; and care transitions and structural barriers informed service and institutional conditions at points of transition. Mana-preserving care is therefore an interpretive synthesis across the four themes rather than a fifth theme. Across these domains, continuity emerged as an important thread, including continuity in relationships, cultural and community connection, whānau presence, and support across services and transitions. No single condition accounted for whether mana was sustained or eroded on its own; their significance lay in how they interacted over time.
Across these conditions, whānau frequently undertook integrative work to maintain continuity, including navigating services, negotiating tikanga, sustaining relational and cultural connections, and remaining involved after residential placement. Where continuity fragmented, whānau often worked to bridge the resulting gaps.
Figure 1 summarises this conceptual relationship.
These findings build on existing Aotearoa scholarship. Dudley et al. [
1] identified Te Oranga Wairua as central to Māori understandings of mate wareware and described whānau as crucial to care, with mana-enhancing relationships informed by aroha, manaakitanga, whakapapa, and whanaungatanga (relationships and connections). Participants in the present study described these relational and cultural foundations of care being sustained, or coming under strain, through caregiving, community connections, service interactions, and transitions in care. This emphasis on interdependence is also consistent with Durie’s Te Whare Tapa Whā model [
25], which conceptualises health through physical, psychological, whānau, and spiritual dimensions. Rochford [
26] situates Te Whare Tapa Whā within a Māori worldview characterised by interconnectedness and interdependence and describes its development as part of Māori efforts to regain greater control over health services. Taken together, these provide a wider context for understanding why sustaining mana is closely bound to the relational, cultural, community, and service conditions surrounding a person with mate wareware. The comparison is one of interdependence rather than direct correspondence: Te Whare Tapa Whā articulates interrelated dimensions of hauora, whereas the four conditions identified here concern mate wareware care across whānau, community, and service contexts. A related analysis from the same wider research programme developed the He Tūhononga Whaiaro framework, linking whānau, place, tūpuna and social relationships with wairua and identity [
27].
Participants’ accounts of continuing to recognise and treat the person as themselves despite changes associated with mate wareware (
Section 3.3) reflected a view of personhood grounded in whakapapa, wairua, and community relationships. Changes in cognitive recognition did not necessarily mean that relational, cultural, or wairua connections were understood to have disappeared; identity could continue to be held through whakapapa, familiar people and places, and the recognition of others. One participant illustrated this through their concern that knowing only residents’ first names was insufficient, proposing that information about who they were and their connections be made available because “knowing about someone is rongoā, is about healing.” There are important parallels with person-centred dementia care. Parker [
28] emphasises retaining a clear sense of the person within dementia care and integrating medical understanding with more holistic and humane approaches, while Spector and Orrell [
29] locate dementia within interacting biological, psychological, social, and environmental influences. In the present accounts, however, personhood was sustained through culturally and relationally situated connections including whakapapa, wairua, whānau identity, place, and community. Mana-preserving care therefore provides an empirically grounded account of what sustaining personhood can involve within a Māori relational context.
Simpson et al. [
14] use the concept of ‘structural holes’ to describe gaps within collective whānau care systems that can create challenges in care coordination and leave primary carers’ knowledge, preferences, and self-care needs unseen despite extensive whānau support. The present findings add an emotional dimension to this account of primary carer invisibility: participants described loneliness associated with carrying concentrated caregiving responsibility even where other whānau were involved. A related but distinct finding was experiences consistent with anticipatory grief as relationships changed through the progression of mate wareware. Anticipatory grief refers to emotional responses to cumulative and ongoing losses while the person remains alive [
30]. Such experiences were evident in several participants’ accounts, yet culturally diverse caregiver experiences remain underrepresented in this literature: a recent scoping review of 30 studies found that samples primarily included caregivers identifying as White or Asian and called for research with more racially and ethnically diverse caregiver populations [
30].
Recent Aotearoa research provides relevant points of comparison with the four-condition account developed here. Two companion analyses of Māori aged residential care (ARC) identified structural barriers concerning navigation and service design and locality [
11], and organisational barriers involving facility acceptability and adequacy, the interface between ARC and whānau care, and the workforce [
31]. The latter also described Māori Health Workers as bridging gaps between hospital and community settings and services. A further analysis from this research programme [
32] identified the value and burden of whānau care, transitions and communication across community-based services, and the importance of trusting relationships and tikanga-informed residential care. Hikaka et al. [
33] independently found that ARC decisions reflected cultural expectations and emotional responsibility, alongside aspirations for home-like, relational settings enabling whānau involvement and cultural connection; where these aspirations were not met, guilt could be heightened. Although these studies concerned older Māori generally rather than mate wareware specifically, they provide relevant comparisons. Te Maringi Mai o Hawaiiki et al. [
13] identified social connection, tūrangawaewae, identity, and mindful practices as themes influencing wairuatanga, closely paralleling Theme 3. Ma’u et al. [
34] found that lower residential care among Māori and Pacific people living with dementia was not matched by an equivalent increase in home-based support, suggesting greater reliance on unpaid family care. Taken together, these findings support individual elements of the account developed here; the present study brings them together across the mate wareware care journey.
These patterns reflect more than coordination or communication problems. Graham and Masters-Awatere’s [
35] systematic review of Māori patients’ and whānau experiences of the Aotearoa New Zealand public health system, drawing on 14 studies spanning 18 years, concluded that the system was experienced by many Māori as “hostile and alienating,” with whānau mitigating these experiences at a cost to their own time, resources, and emotional wellbeing. The review also documented positive interactions with individual health professionals, including experiences of compassion, respect, and relational connection, despite wider systemic barriers. A similar distinction is relevant here: participants described routine institutional rules and procedures that did not readily accommodate tikanga, showing how culturally disruptive care can arise at an institutional level without being reducible to the intentions of individual staff. These experiences can be considered within a wider historical and structural context. Pihama et al. [
36] describe colonisation as disrupting the intergenerational transmission of tikanga, reo, and mātauranga Māori, while Reid, Cormack and Paine [
37] describe coloniality as an ongoing process through which historical power relations continue to shape contemporary conditions. This literature provides a basis for understanding disruptions to tikanga and cultural connection in care as connected to, rather than detached from, the wider history of colonisation and coloniality.
Internationally, the present findings resonate with two bodies of literature while remaining grounded in the specific cultural and relational context of mate wareware in Aotearoa. A recent synthesis of First Nations Australian research emphasises culturally safe, community-led approaches to dementia care and identifies gaps in diagnostic tools and culturally appropriate care pathways [
38]. This parallels the present study’s emphasis on culturally grounded care extending beyond formal clinical services, while the relationships, practices, and forms of belonging through which such care is sustained remain culturally specific. The international dementia-friendly community literature similarly emphasises social participation, supportive physical and social environments, community connection, and engagement across organisations and services [
39,
40]. Both bodies of literature therefore reinforce the importance of conditions beyond formal clinical care, but those conditions cannot be assumed to be culturally interchangeable. In the context of mate wareware, they included wairua, whakapapa, marae-based belonging, and continuing relationships with whānau, place, and community.
4.1. Implications for Practice, Service Design, and Policy
The findings most directly support ensuring that mate wareware information and support reach whānau early, including before formal diagnosis, through Māori-facilitated and community-based approaches rather than relying on clinical information alone. This direction has a concrete precedent in Aotearoa, where kaumātua perspectives informed the development of a digital mate wareware awareness resource [
41]. A recent systematic review found limited evidence for Indigenous dementia communication interventions, while highlighting cultural and linguistic representation, locally appropriate knowledge sharing, and community involvement [
42]. The present findings therefore support further development and evaluation of Māori-led information approaches. The findings also point to the importance of respite provision that recognises that collective whānau involvement does not necessarily mean caregiving responsibility is shared, with participants describing concentrated responsibility, exhaustion, and unmet needs for respite. Peer support opportunities may also help address the loneliness participants described, while providing space for whānau to connect with others navigating similar experiences.
Navigation difficulties, the value placed on continuity where it occurred, participants’ desire for a relatable person to guide whānau through the system, and an example of Māori-led support that remained involved over time (
Section 3.3 and
Section 3.4) suggest value in evaluating dedicated kaupapa Māori continuity roles that remain alongside whānau through changes in services and care settings. Such roles could help sustain access to information, relationships, cultural connection, and whānau involvement across transitions, rather than requiring these connections to be repeatedly re-established. The findings also support embedding tikanga into routine residential and institutional practice, rather than requiring whānau to negotiate tikanga as an exception.
Participants’ aspirations for kaupapa Māori residential care should be understood alongside strong preferences and expectations around supporting kaumātua to remain at home, including where possible at the end of life (
Section 3.4). Theme 3 described aspirations for dedicated kaupapa Māori residential care, including culturally grounded staffing, less reliance on whānau to educate staff, and accommodation that enables whānau to remain overnight, while Theme 2 identified unmet needs for respite. Taken together, these findings suggest value in evaluating culturally grounded residential and respite provision for circumstances in which care at home can no longer be sustained or whānau need relief, rather than as a substitute for supporting care at home. Ways of sustaining the informal neighbourhood and community connections participants identified as important to belonging also warrant exploration and evaluation. These directions represent aspirations and implications arising from participants’ accounts rather than service models evaluated in this study. They are consistent with national dementia mate wareware action plan directions. The 2021 Dementia Mate Wareware Action Plan explicitly aligned its approach with Te Tiriti o Waitangi obligations, including tino rangatiratanga, and stated that “an approach grounded in Te Ao Māori [a Māori way of understanding the world] underpins the design, development and delivery of solutions and programmes that work for Māori whānau” [
43]. The refreshed 2026–2031 Action Plan continues to prioritise Māori and places Te Tiriti and kaupapa Māori frameworks within a wider dementia mate wareware ecosystem that includes whānau-centred support, navigation, respite and residential care, community and home-based services, and system integration [
44].
Taken together, these implications position culturally grounded care as a core feature of service design rather than an optional addition to existing services. These findings suggest value in embedding cultural and relational continuity across the care journey while reducing reliance on whānau to bridge gaps between information, support, and care settings.
4.2. Limitations
The Phase 2 analytic sample comprised ten whānau hui involving 12 individual participants purposively recruited for their lived experience of supporting a whānau member with mate wareware; seven kaumātua had separately contributed to the earlier co-design phase. The whānau hui generated rich, extended accounts, but the findings should not be read as representative of all whānau Māori experiences of mate wareware. Participants had affiliations to diverse iwi across Aotearoa, providing perspectives across several iwi contexts while limiting the study’s ability to represent the specific realities of any particular iwi or hapū (subtribe). This study focused on whānau perspectives and did not include people living with mate wareware as participants. It therefore cannot represent their experiences or how their perspectives might differ from those of participating whānau. Accounts were also retrospective, describing events that in some cases occurred years earlier, which may have shaped how experiences were recalled and narrated. Recruitment through Māori community, kaumātua, and health provider networks may also have shaped whose experiences were represented, including participants’ connections with Māori services and community structures. The research team’s positioning and KR’s prior community-level engagement may also have shaped data generation and interpretation; consistent with the kaupapa Māori and reflexive orientation, these influences were understood as part of knowledge generation.
Finally, this study was conducted in Aotearoa New Zealand with whānau Māori specifically. The applicability of the four-condition account of mana-preserving care beyond this context was not examined and should not be assumed.




 ,