


Highlights
Public health relevance—How does this work relate to a public health issue?
- This study emphasised the influence and importance of knowledge and attitude in promoting and sustaining protective behaviour during pandemics and public health crises.
- The empirical examination of the knowledge, attitude and behaviour model provided a deeper understanding of behavioural determinants of self-care practices, which are cornerstones of efficient public health responses during pandemics.
Public health significance—Why is this work of significance to public health?
- This study showed that knowledge alone is insufficient to trigger and sustain protective behaviours, as emerging evidence indicates that attitude mediates the promotion and encouragement of protective behaviours and practices. These findings highlight the importance of designing public health interventions that go beyond simple dissemination of knowledge and promotional materials.
- The reported difference between gender and academic disciplines underscored the structural and contextual inequities in health literacy and readiness to follow and adopt preventive self-care practices.
Public health implications—What are the key implications or messages for practitioners, policy makers and/or researchers in public health?
- For policy-makers, public health practitioners and health educators, the study’s results propose that efficient pandemic and health crises preparedness requires a comprehensive intervention that addresses aspects related to knowledge (cognitive), attitudes (affective) and contextual (structural) factors.
- For public health researchers, the current study offers analytical and theoretical support for the deployment of mediated behavioural models and theories, such as the KAB model, to understand the complex pathways through which knowledge and attitudes affect behaviour.
Abstract
Background: Regulatory restrictions and mandates typically offer short-term behaviour guidance, whereas interventions to improve knowledge and attitudes could result in more sustainable behavioural changes. Health authorities implemented awareness campaigns to enhance public knowledge and attitudes regarding COVID-19. This study explored the interplay between knowledge, attitudes and behaviours related to COVID-19 among university undergraduate students in Jordan, aiming to inform public health initiatives and educational programmes. Methods: A cross-sectional survey targeting undergraduate students enrolled at Yarmouk University in Jordan was conducted between January and May 2021. Participants consented to complete an anonymised validated self-administered questionnaire to evaluate their understanding of COVID-19 symptoms, treatment and transmission and attitudes and behaviours towards preventive measures. Data were analysed using descriptive and inferential statistics and structural equation modelling to investigate the associations between knowledge, attitudes and behaviours. Results: A total of 1375 undergraduate students participated in the survey. Knowledge of COVID-19 was low among most participants, with only 1.3% demonstrating high knowledge. Conversely, 58.5% exhibited good behaviour, and 31.4% reported full compliance with recommended behaviours. Significant differences were found in knowledge, attitudes and behaviours across different faculty clusters, with health faculties showing superior knowledge and more positive attitudes. Female participants (66.3%) were more likely to engage in positive behaviours than males (p-value = 0.02). Structural equation model (SEM) analysis showed that knowledge significantly influenced attitudes, which affected behaviours, confirming the model’s validity. Conclusions: The study highlights the critical role of knowledge and attitudes in shaping COVID-19-related behaviours among university students. Significant variations in knowledge and attitudes across different academic disciplines highlight the need for tailored educational interventions. The analysis supports the theoretical model linking knowledge, attitudes and behaviours, emphasising the importance of improving knowledge and attitudes to drive behaviour change. The findings suggest that comprehensive health education programmes targeting cognitive and affective aspects are essential for effective public health responses during pandemics.
1. Background
The World Health Organisation (WHO) declared COVID-19 a pandemic in March 2020, advising countries to adopt a slow-and-stop strategy to reduce transmission and flatten the curve [1,2,3,4,5,6]. This strategy encouraged communication, promoted preventive measures, and discouraged mass gatherings and travel. Governments implemented strict social distancing measures, including partial or complete lockdowns [4,7]. The pandemic also significantly affected educational systems, leading to nearly total closures of schools, colleges, and universities. As of April 2020, nearly all educational institutions were shut down [8,9].
In addition to country- and institution-level measures, healthcare authorities were heavily involved in encouraging citizens to comply with authorities’ mandates and to adopt individual-level self-care practices to help limit the spread of severe acute respiratory syndrome coronavirus-2 (SARS-CoV-2), including handwashing and respiratory hygiene practices (RHPs) [10]. The latter encompass a variety of behaviours, such as covering the mouth and nose when coughing or sneezing, wearing face masks, and keeping a physical distance from other people [11,12]. Implementing these procedures was deemed essential to reduce the spread of COVID-19, particularly in public and communal areas [13]. Additionally, RHPs include avoiding direct contact with infected or at-risk individuals, staying at home when infected and enhancing ventilation in indoor places [14].
Evidence showed that public compliance with authoritative mandates and adherence to RHPs are influenced by several factors related to public health communications, cultural beliefs, societal norms and the perceived susceptibility and severity of COVID-19 [15,16,17]. Life in higher-education institutions (HEIs) necessarily involves social gatherings of students, educators, researchers and administrative staff. Accordingly, campuses with little or no social distancing measures could be hot spots for virus transmission. Therefore, the way students and staff behaved and their compliance with risk avoidance strategies, RHPs and social distancing measures played a central role in controlling and preventing the spread of COVID-19 in educational settings and communities.
Regulatory restrictions could guide behaviours, but their influence is often temporary and unsustainable [18,19]. On the other hand, interventions targeting knowledge and attitudes could lead to permanent and sustained behaviours [20,21,22]. Health authorities, while issuing behaviour-related mandates and guidelines, have also been actively involved in awareness campaigns primarily aimed at enhancing knowledge and health literacy among the general population and to cultivate positive attitudes toward RHPs and COVID-19 slow-and-stop procedures [23,24]. The importance of knowledge and attitudes in shaping sustainable behaviours cannot be overstated [23,24].
The current study was broadly guided by the Knowledge–Attitude–Behaviour (KAB) model, a frequently deployed model that investigates the interplay between attitude, knowledge and behaviour in healthcare settings. The model assumes that acquired knowledge would shape individuals’ attitudes and subsequently influence their health behaviour [25]. Despite being criticised for oversimplifying the behaviour-influencing factors, the model remains a valuable framework for hypothesis-driven research in health behaviour and promotion research. Over the past six years, several researchers have employed the KAB model to analyse population behaviours and responses to the COVID-19 pandemic. For instance, Azlan et al. (2020) in Malaysia and Limbu et al. (2020) in Nepal reported that higher COVID-19 knowledge triggered protective attitudes and adherence to preventative behaviours, such as respiratory hygiene practices [26,27]. This evidence highlights the significance of the KAB model in examining how undergraduate students’ knowledge and attitudes might influence their COVID-19-related behaviours and practices.
The current study explored the dynamics between knowledge, attitudes and behaviours toward COVID-19 of university undergraduate students in Jordan who were at a critical stage of social and academic development. By examining the associations between knowledge, attitudes and behaviours, this research sought to inform public health initiatives and educational programmes tailored to enhance the understanding and management of COVID-19, other pandemics and related public health emergencies.
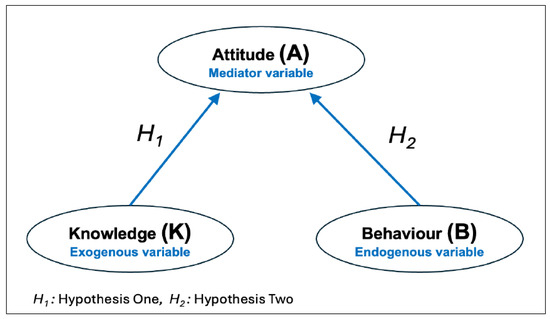
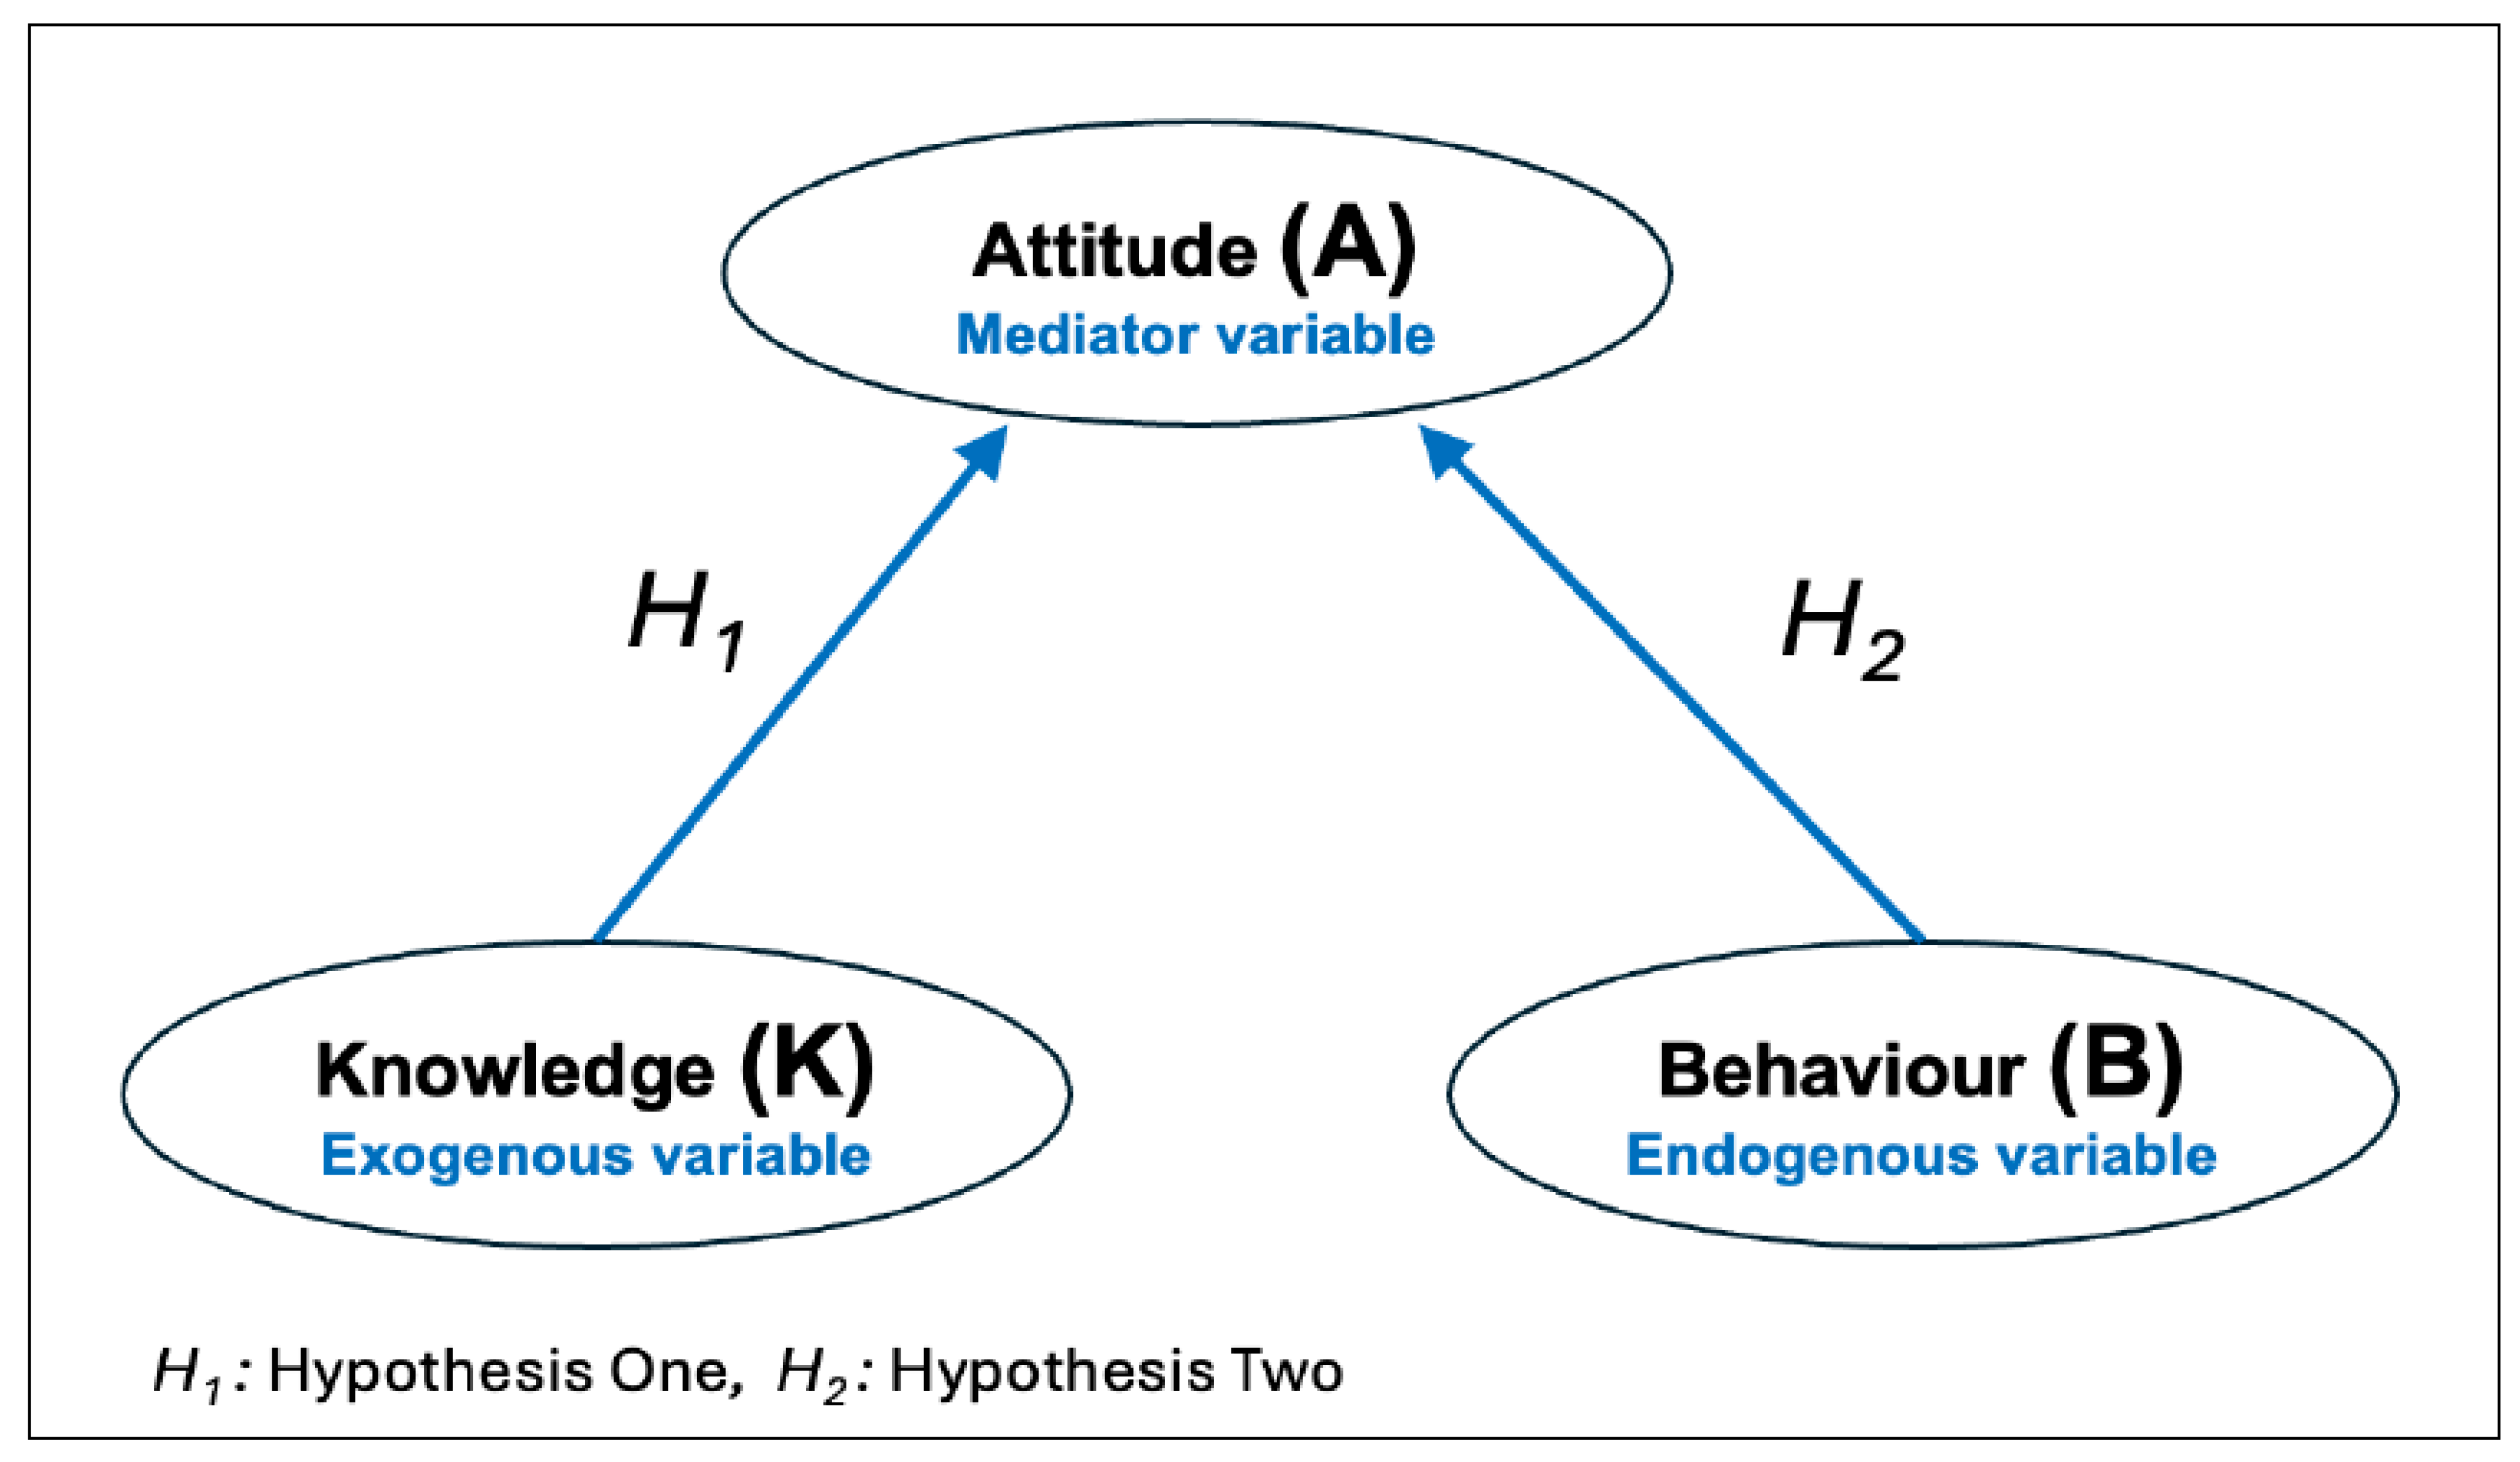
The aim of this study was to evaluate the knowledge, attitudes and behaviours [20] of university undergraduate students regarding COVID-19-related hygiene and precautionary practices. This was achieved by developing and validating a reliable instrument to assess knowledge, attitudes and behaviours (KAB) of HEI students. The tool consisted of three main variables: the endogenous variable (behaviours), the mediator variable (attitudes), and the exogenous variable (knowledge); Figure 1 illustrates the model.
Figure 1.
KAB model structure and proposed hypotheses; H1 (Hypothesis 1): knowledge has a significantly positive association with attitude; H2 (Hypothesis 2): attitude has a significant positive association with behaviour.
2. Methods
2.1. Study Design
A cross-sectional study was conducted among undergraduate students attending Yarmouk University between January and May 2021. The study was carried out in three phases: Phase-1 aimed to develop a validated online tool that investigated undergraduate students’ knowledge, attitudes and behaviours related to COVID-19 RHPs. Phase-2 investigated the associations between knowledge, attitude and behaviour using a structural equation model approach, whereas Phase-3 assessed research participants’ knowledge, attitudes and behaviours regarding COVID-19 RHPs.
2.2. Tool Development and Validation
Items and Domains Development
The tool’s design was based on a thorough review of the available literature, guidelines and WHO statements [10,12], including relevant materials for other pandemics such as severe acute respiratory syndrome [28], avian influenza [29], the H1N1-2009 pandemic (swine flu) [30] and other viral respiratory infections such as influenza [31]. The relevant literature was reviewed to identify constructs and items related to the study variables, namely knowledge, attitudes, and behaviours. Elements identified were later grouped into constructs within three domains: knowledge (K), attitudes (A) and behaviours (B) based on Bish and Michie’s review [32], the WHO KAP Survey Development Guide [33] and the Flu Telephone Survey Template (FluTEST) [34].
2.3. Validation and Reliability Assessment
A panel of nine experts in epidemiology (n = 2), microbiology (n = 1), public health (n = 3) and health behaviour (n = 3) assessed the face and content validity of the first draft. The experts independently and subjectively assessed the drafted instrument’s readability, clarity of use terminology, language, relevance, compatibility between items and construct definition and scope and suitability and adequacy of the proposed scales. The reviewers were provided with a customised assessment form that addressed all assessment criteria.
The initial draft of the questionnaire instrument contained fifteen questions: four questions assessing knowledge, seven assessing attitudes, one assessing behaviour and three related to demographics and characteristics. Across the model-related domains, 134 items were included, while eight items were within the demographics. The tool’s reliability and internal consistency coefficients were determined in a pilot study with 78 participants who met similar eligibility criteria to the intended profile of research participants. The internal consistency of each construct was determined using Cronbach’s coefficient α analysis; Cronbach’s α of (0.60) and above was considered acceptable.
Based on the panel’s recommendations and the pilot study’s results, some items and questions were either merged, dropped, or rephrased for clarity to enhance the questionnaire instrument’s conceptual alignment and coherence.
2.4. Tool Description
The final refined tool consisted of fourteen questions grouped as follows: three questions related to participants’ demographics, three questions related to the knowledge domain (31 items grouped into three constructs), seven questions investigating attitudes (78 items grouped into seven constructs), and one question assessing behaviour (16 items in one construct). Table 1 details the constructs, constructs codes, items and scales used within each domain.
Table 1.
Domain, constructs and scales in the data collection tool.
Data coding was domain- and construct-specific; for the knowledge (K) domain, any correct answer was awarded one point (+1), an incorrect answer was awarded minus one point (−1), and “do not know” answers were awarded zero points (0). For the attitude (A) domain, data coding for all constructs, except the cue to action, used a 1 to 5 scale (Strongly Disagree = 1, Strongly Agree = 5). The cues to action coding were done using a 1 to 3 scale (Yes = 3, Not Sure = 2 and No = 1). Lastly, the behaviour (B) domain was coded using a 1 to 5 scale (Never = 1 and Always = 5). Total knowledge and attitude scores were calculated and categorised as per Bloom’s cut-off point, a commonly used percentage-based threshold in KAB studies [35] that classifies KAB model domains into three categories: high, moderate and low [36], as detailed in Table 2.
Table 2.
Bloom’s cut-off categories of the total knowledge and attitude scores.
2.5. Study Population and Participant Recruitment
A suitable sample size is critical to achieving a stable, representative and accurate statistical model. For structural equation modelling (SEM), it is recommended to have at least ten participants per item (parameter) to achieve a stable model [37,38]. Given that the tool included a total of 125 items (parameters), a minimum sample of 1250 participants was required.
A stratified random sample approach was employed to guarantee adequate representation across various faculties, academic years and disciplines at Yarmouk University, Jordan. The inclusion criteria for this study were as follows: (i) being enrolled as an undergraduate student and (ii) willing to provide informed consent to participate in the study.
The study sample consisted of undergraduate students who were registered at Yarmouk University, Jordan, at the time of the study. Eligible participants were identified and recruited through electronic channels and platforms provided by the University. The recruitment method entailed initiating an email invitation containing a hyperlink to the anonymous questionnaire, supplemented by a minimum of three reminders to enhance the response rate. Additionally, direct recruitment tactics were utilised, involving the approach and invitation of students to engage in various campus activities and events.
2.6. Data Collection Procedures
The finalised tool was electronically distributed using the Qualtrics XM platform. Eligible participants were sent an email invitation containing a hyperlink to access the questionnaire. The survey was anonymous, and no personal data or identifiers were collected. Three reminders were sent to improve the response rate. Data collection spanned four months, commencing on 3 January 2021 and concluding on 31 May 2021.
2.7. Data Analysis
Completed questionnaires were extracted and logged into an Excel® workbook (Microsoft Office MS, 2013). Prior to analysis, the data were cleaned and coded.
Knowledge, attitude and behaviour constructs were coded as per Table 1. Data were initially analysed descriptively using frequencies, percentages, standard deviation and Z-tests when applicable; a p-value < 0.05 was considered statistically significant. A chi-square test of independence was performed to examine the relation between faculty cluster and knowledge, attitude and behaviour scores. To account for potential confounding, participant demographics and characteristics were included in the descriptive and inferential analysis.
The associations between knowledge-related constructs, attitude-related constructs and behaviour-related constructs were examined using the Lavaan package (latent variable analysis), which works under the R environment, to test the model using structural equation modelling (SEM) analysis with latent variables. Analysis of associations between constructs and variables of the proposed model started by assessing the model’s global fit, followed by assessing coefficients and associations. Data was analysed using the Statistical Package for Social Sciences (SPSS) (Version 27, launched in June 2020). SEM reduced potential demographic bias by modelling latent constructs and their measurement error. The stability and suitability of the proposed model were assessed using several fit indices. Following Hu and Bentler (1999) and Kline’s (2016) guidance [38,39], a comparative fit index (CFI) and Tucker–Lewis index (TLI) ≥ 0.90, root mean square error of approximation (RMSEA) ≤ 0.08, and standardised root mean square residual (SRMR) ≤ 0.08 were considered indicative of acceptable and stable model fit.
2.8. Ethical Considerations and Approvals
This study was reviewed and approved by the Institutional Review Board at Jordan University of Science and Technology and King Abdulla University Hospital, Irbid, Jordan (reference number: 119/12/2020), on 2 September 2020. Before participating in this study, participants received an information letter at the end of September and were asked to indicate electronic consent before accessing and proceeding with the questionnaire; participants who did not consent to participate were unable to proceed.
3. Results
3.1. Sample Characteristics
In total, 1375 undergraduate students provided completed surveys. Table 3 summarises the participants’ characteristics and knowledge, attitude and behaviour scores. From the total sample, 911 (66.3%) were females, and more than half (56.4%) were students at humanitarian faculties. Only sixteen participants (1.2%) were involved in an active relationship (married, engaged or in a relationship).
Table 3.
Participants characteristics and knowledge, attitude and behaviour scores.
Analysis of COVID-19-related knowledge, attitudes and behaviour (KAB) scores showed that only eighteen (1.3%) had a good knowledge of COVID-19 symptoms, treatment and transmission. On the other hand, 805 (58.5%) participants exhibited good behaviour, whereas 253 (31.4%) reported full compliance with all recommended precautionary behaviours. The chi-square analysis showed that KAB scores were statistically different between the three faculties’ clusters. Lastly, a comparison between female and male participants showed that female participants were significantly more likely to behave positively toward COVID-19 than male participants (p-value = 0.02).
3.2. Model Global Fit Indices
Global fit indices are statistical tests that assess the stability and adequacy of the retrieved data’s structural equation model (SEM) by assessing how well the model represents the underlying data structure. Among the main global fit indices are the (i) root mean square error of approximation (RMSEA), (ii) comparative fit index (CFI), (iii) standardised root mean square residual (SRMR), (iv) χ2/df ratio and (v) the Tucker–Lewis index (TLI). These indices can help in evaluating the proposed model’s stability, providing guidance for its accuracy or confirming the model’s validity if the indices suggest a satisfactory match [38,40]. As there is no agreement between scholars regarding the cutoff criteria, it is advisable to use several fit indices simultaneously [41]. Moreover, the sample size and the model complexity should be considered when assessing the model fit indices [39,40]. Generally, a model is considered to fit better when the values of CFI and TLI are close to (1) and the values of RMSEA and SRMR are close to (0) [38,40]. In this study’s model, the RMSEA of (0.05) and SRMR value of (0.06) values indicated a good fit for the model.
3.3. Structural Equation Model Analysis Output
3.3.1. The Relationship Between Mediator and Endogenous Variables
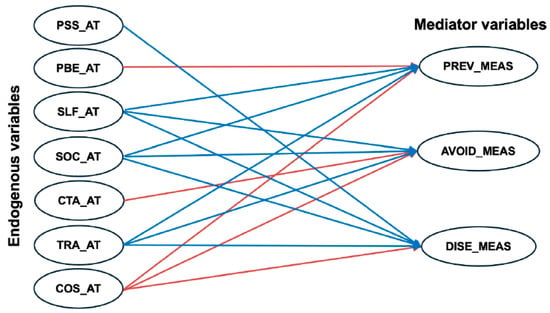
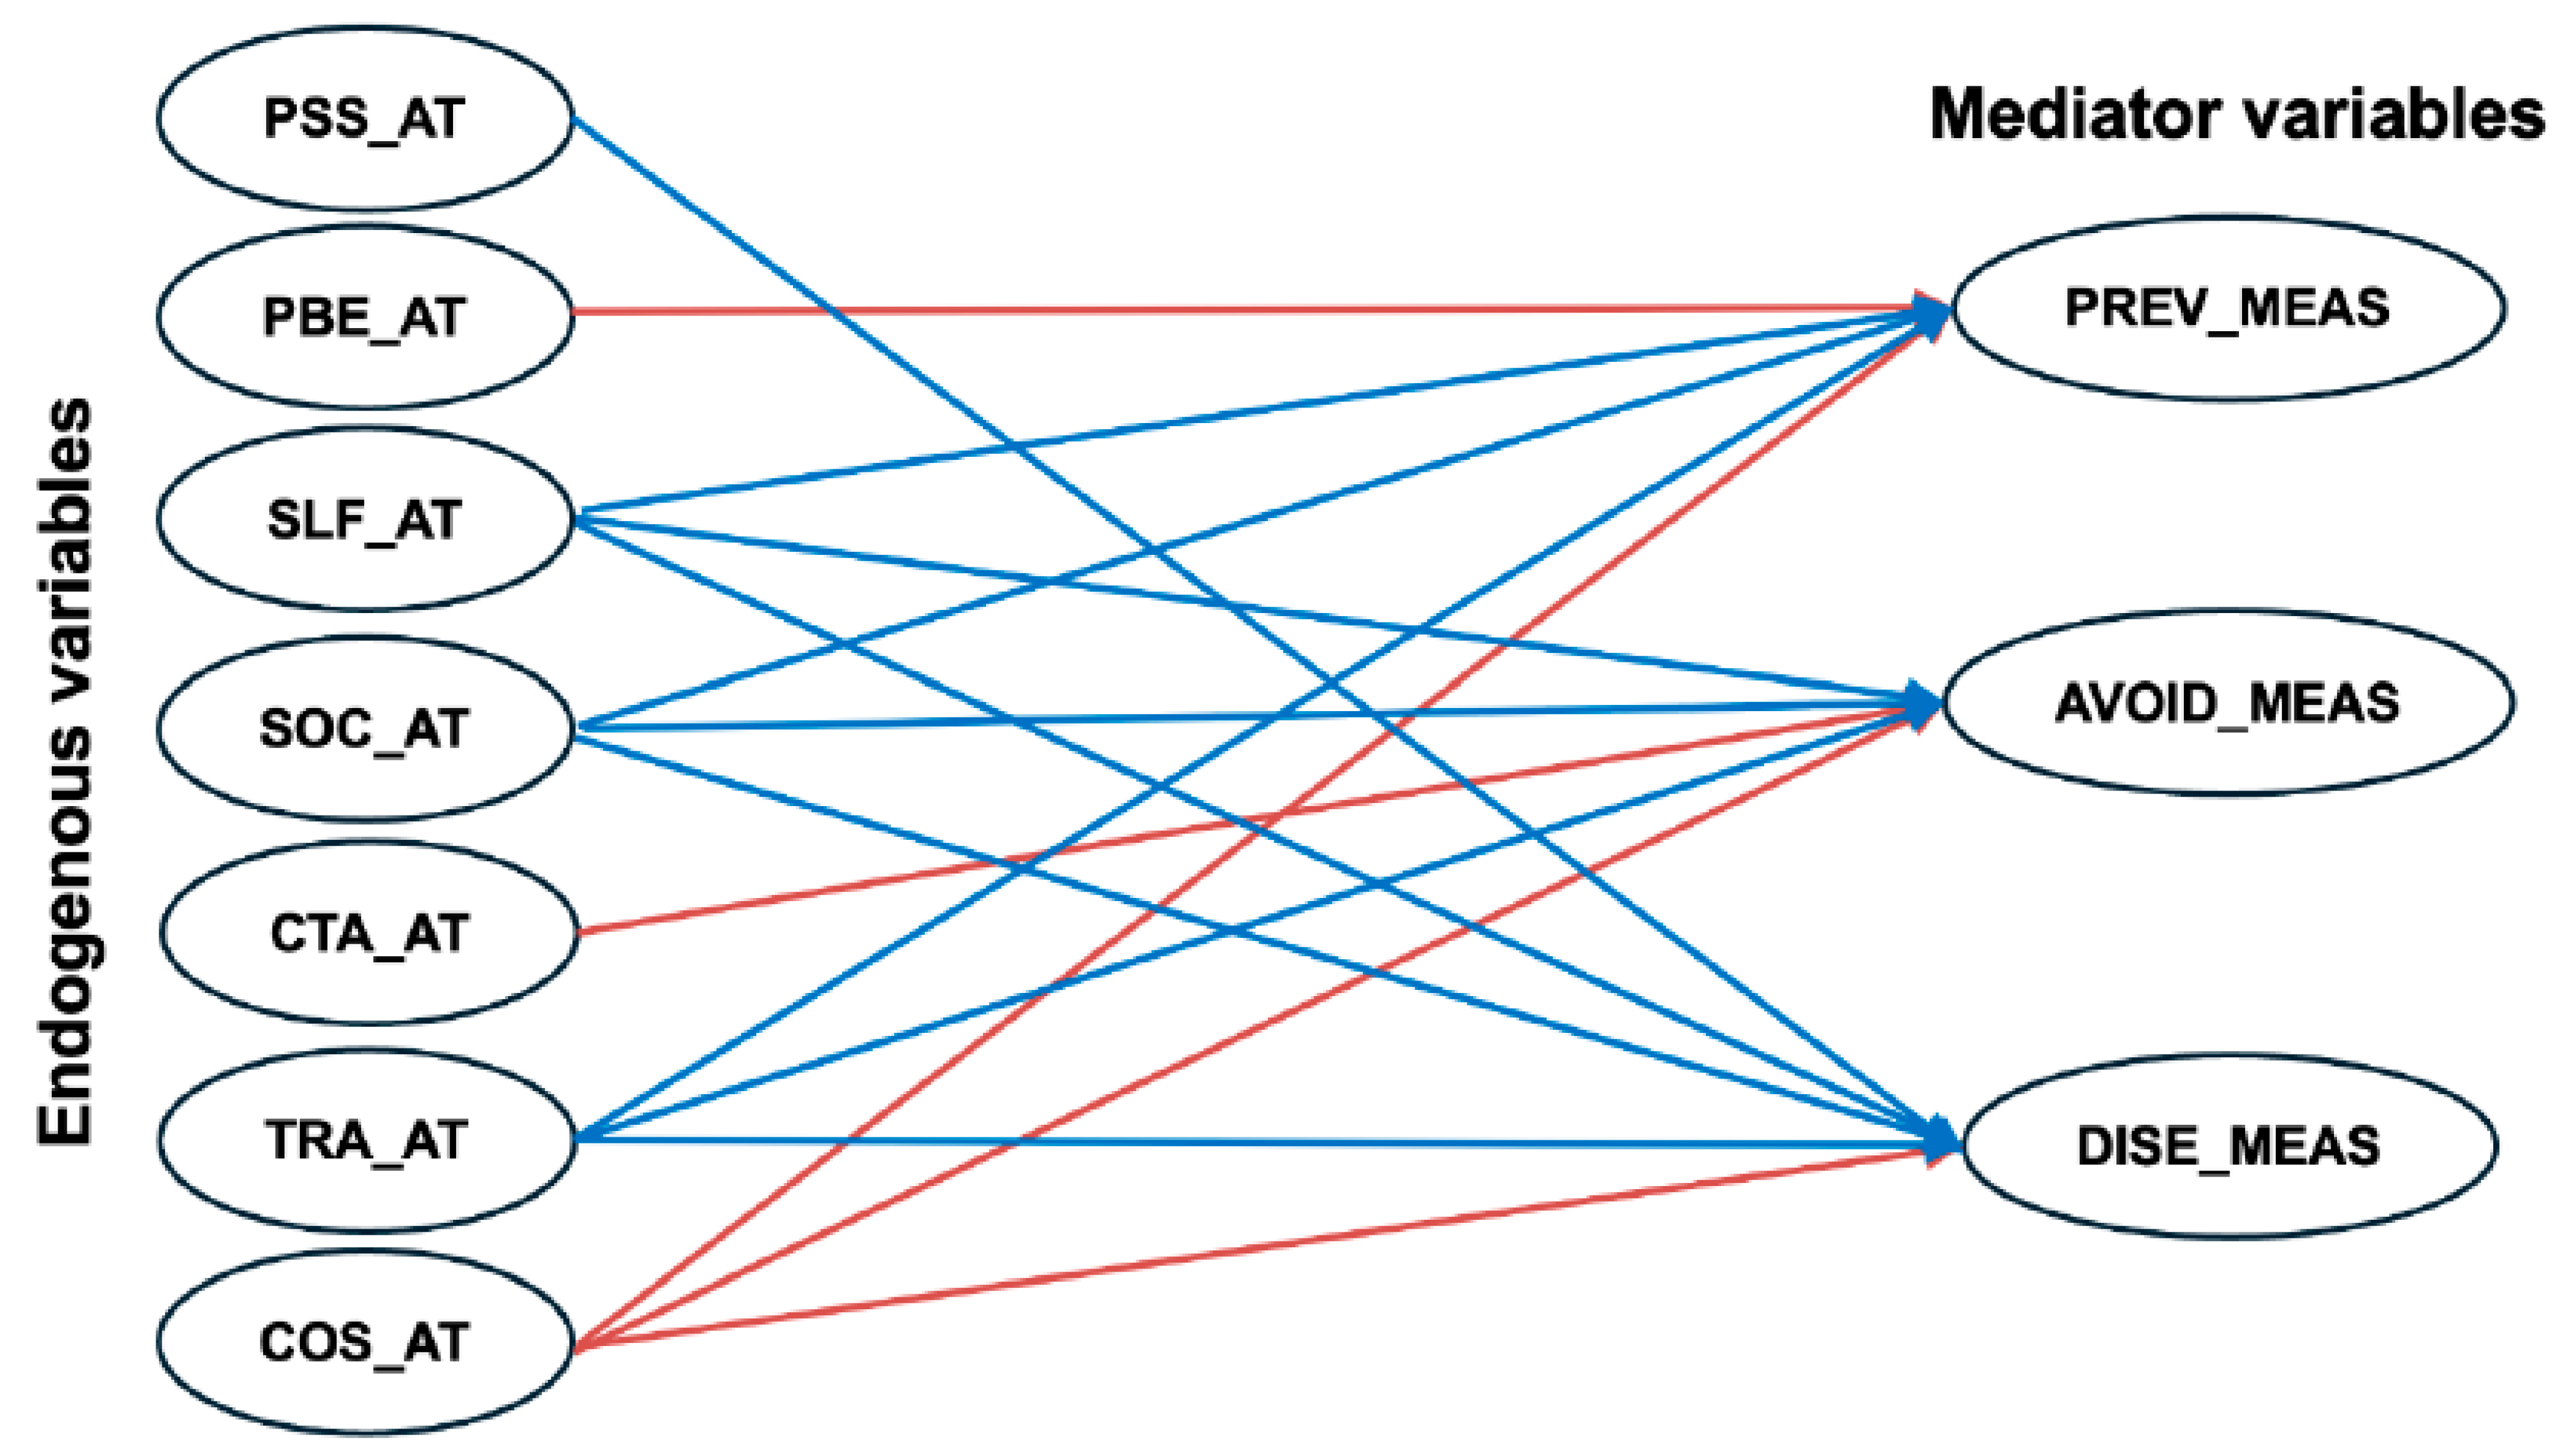
As the model was proven to fit the data, the coefficients and relationships between the constructs were assessed. Table 4 shows the path regression coefficients between the constructs for the suggested model. Analysis showed that adopting preventive behaviours was significantly associated with the attitudinal constructs of perceived efficacy of behaviour, perceived self-efficacy, social pressure, trust in authority and the perceived cost (p-value < 0.05). Avoidance behaviours were significantly associated with perceived self-efficacy, social pressure, cue to action, trust in authority and the perceived cost of behaviour, see Table 4. Lastly, all attitudinal constructs significantly influenced COVID-19 awareness measures and behaviours except for the perceived efficacy of behaviour and cue to action constructs, see Table 4. The significant associations between attitudinal and behavioural constraints could be used to predict behaviours related to COVID-19, see Table 4 and Figure 2.
Table 4.
Path regression coefficients between the constructs for the suggested model.
Figure 2.
The statistically significant path coefficient relationships between the endogenous variables (behaviours) and the mediator variables (attitudes); red indicates negative associations, while blue indicates positive associations.
3.3.2. The Relationship Between Mediator and Exogenous Variables
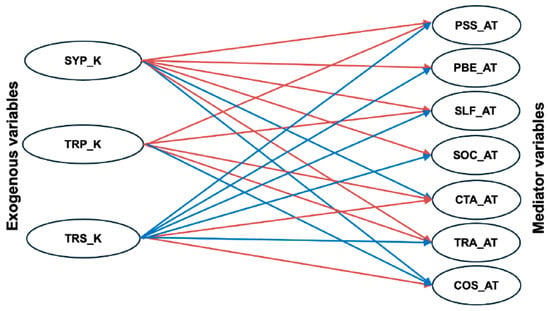
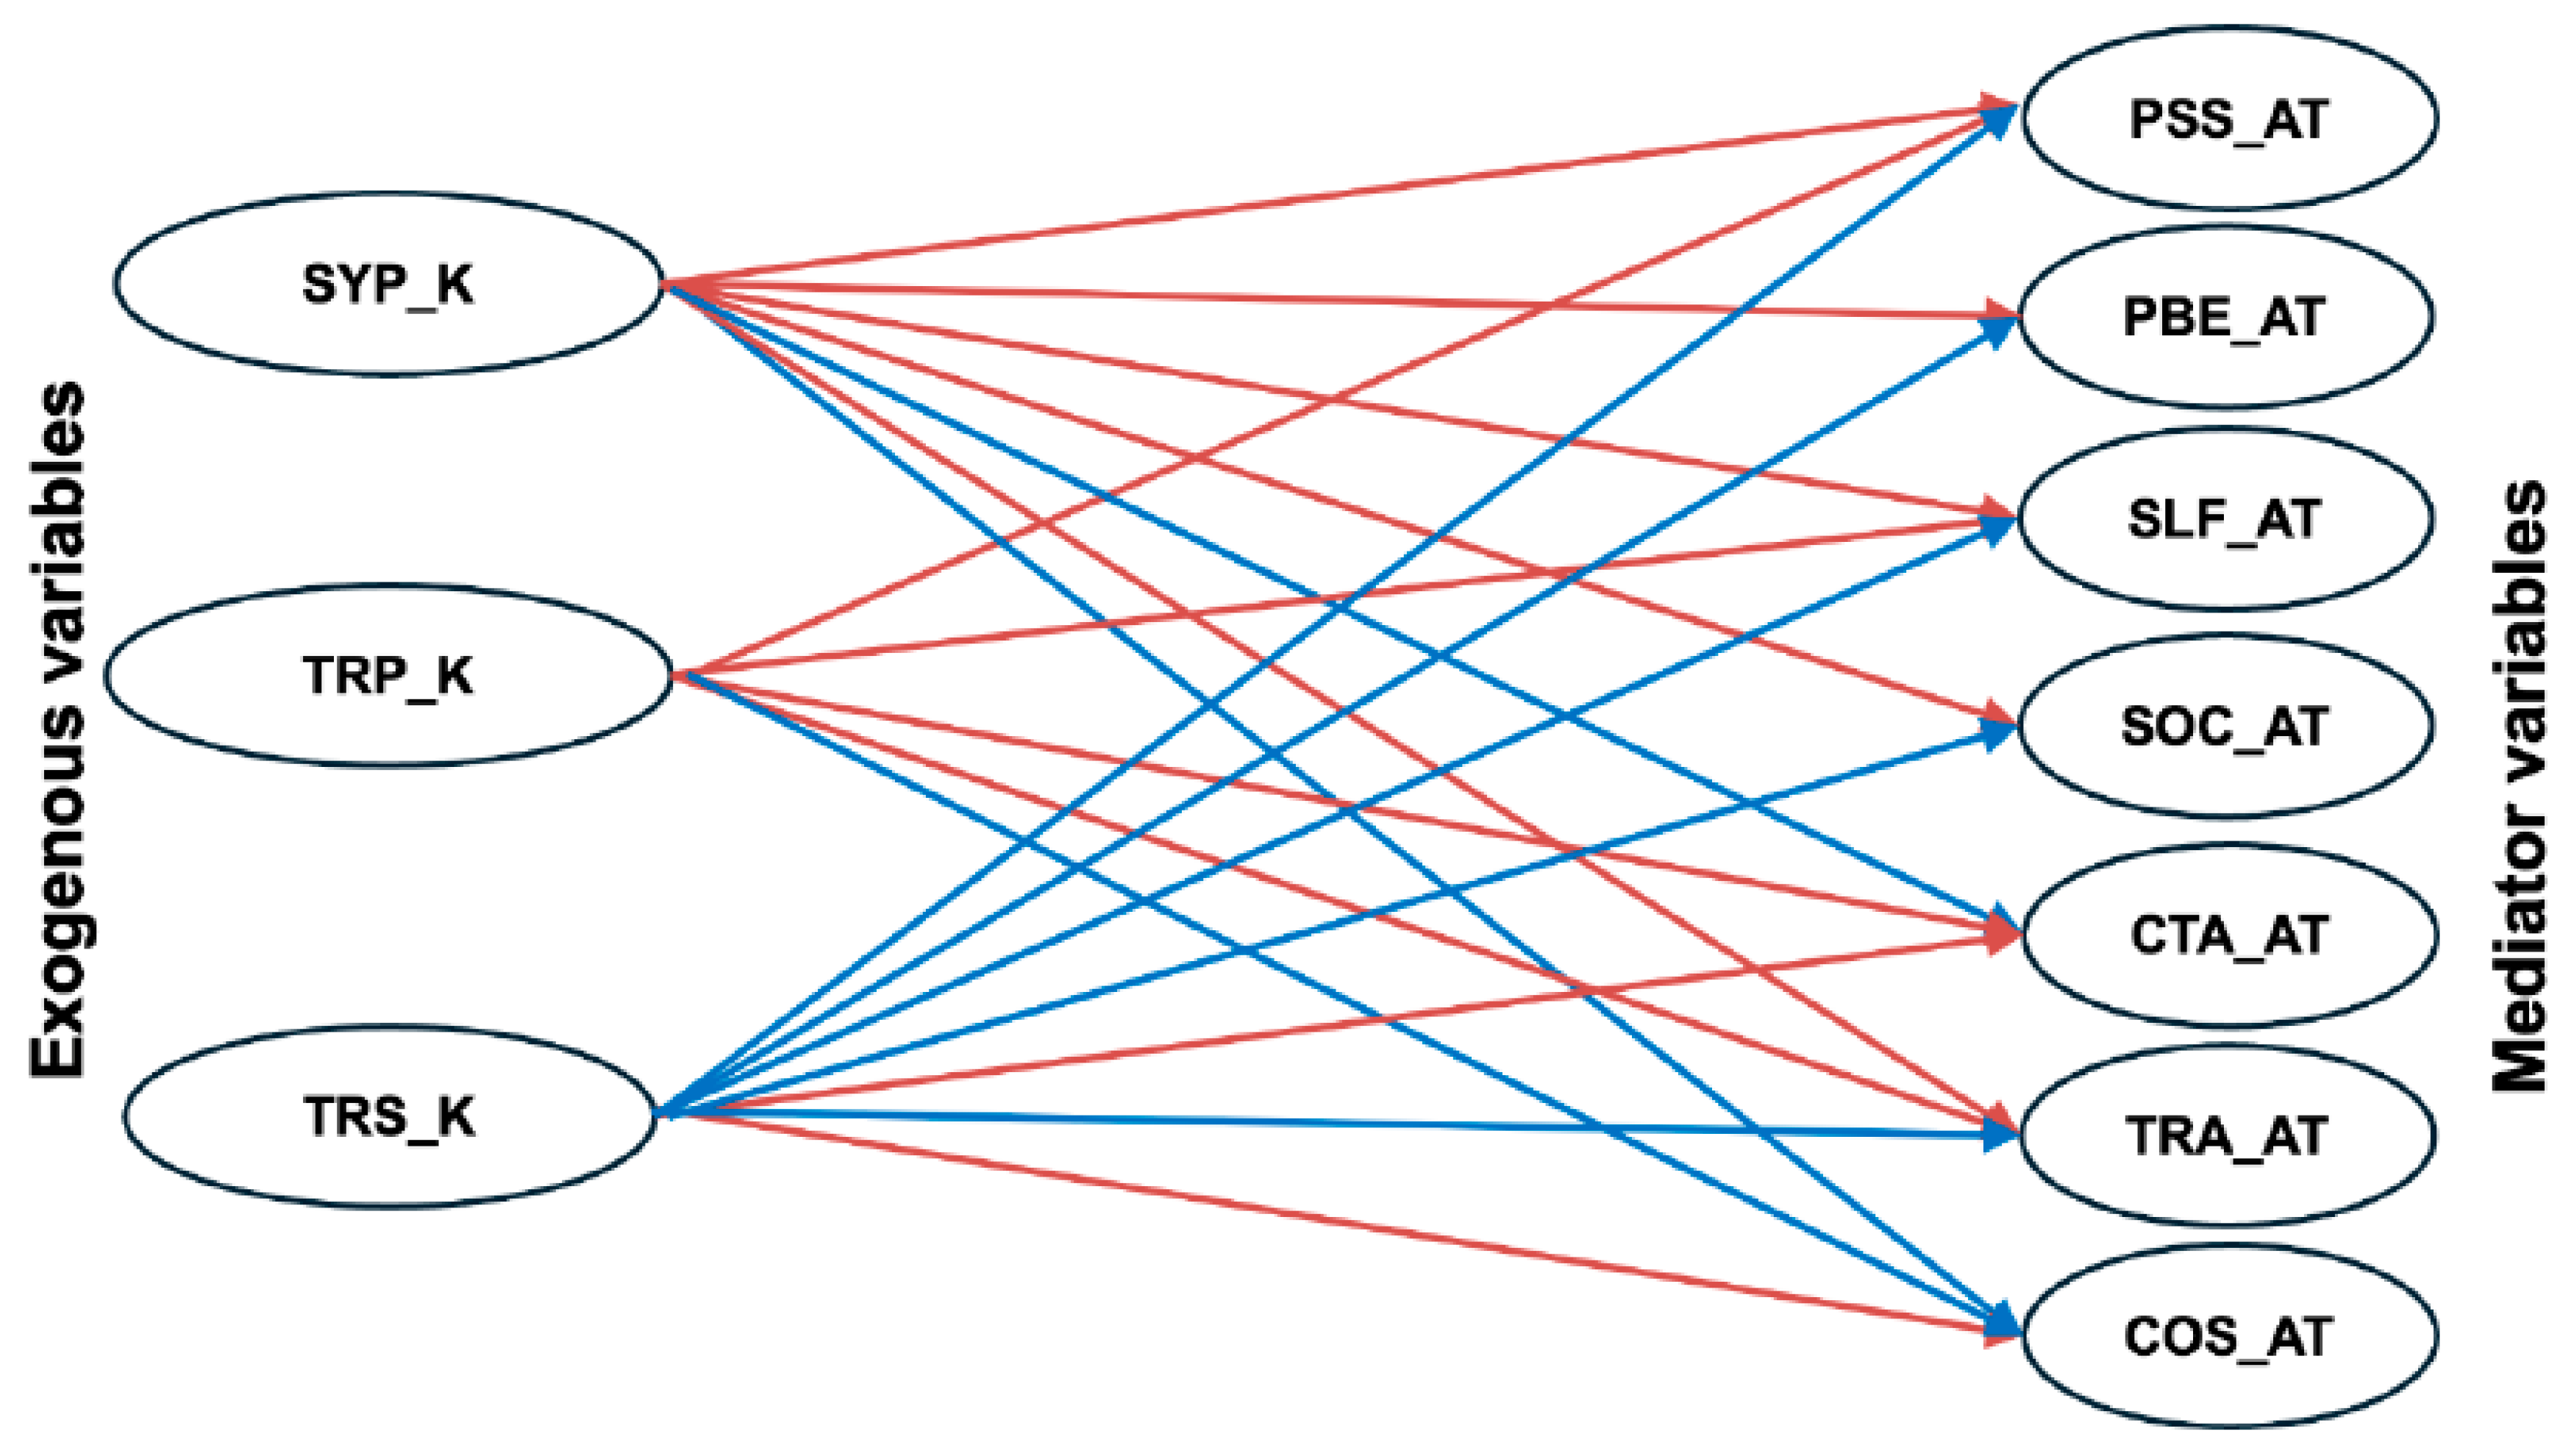
The associations between the exogenous variable constructs (knowledge) and the mediator variable constructs (attitude) showed that all knowledge constructs significantly influenced all attitudinal constructs except for perceived self-efficacy and social pressure, which were not influenced by COVID-19 treatment knowledge, see Table 4 and Figure 3.
Figure 3.
The statistically significant path coefficients between the exogenous variables (knowledge) and the mediator variables (attitudes); red indicates negative associations, while blue indicates positive associations.
4. Discussion
Using a validated tool, this study evaluated undergraduate students’ knowledge, attitudes, and behaviours on COVID-19 hygiene and preventive measures, examining associations between knowledge, attitude, and behaviour.
The demographic characteristics of the study’s population, where the majority were female and enrolled in humanitarian faculties, were comparable to the national-level gender and discipline composition [42,43]. In theory, demographic characterisation is a key determinant of health behaviours, as suggested by health behaviour scholars and theorists, where factors such as gender and educational level and background influence self-efficacy, behavioural control and normative beliefs [22].
Females are more likely to have a higher health literacy coupled to a more positive attitude and/or a higher compliance with healthy behaviours and practices [44,45,46]. Emerged evidence confirmed gender-based differences, as female respondents were significantly more inclined to adopt positive COVID-19-related behaviours than males (p-value = 0.02). These findings emphasise the importance of demographic and social characteristics in guiding and shaping individuals’ knowledge, attitudes and behaviours. Additionally, policymakers should take into consideration the impact of demographic and societal factors in designing health promotion and awareness programmes.
The observed significant differences in knowledge, attitudes and behaviours among students from three different fields highlight variability in health literacy and adherence to behavioural guidelines based on academic discipline. Participants from health and science faculties exhibited a higher understanding of COVID-19 symptoms, transmission and treatment and significantly lower negative attitude towards COVID-19 preventive measures compared to humanities students. This is consistent to the findings of other studies, suggesting that health science students typically had a better understanding of health-related matters and were therefore more likely and willing to comply with recommended health behaviours [47,48]. The observed differences between disciplines could be attributed to the academic curricula’s nature and components, as health science academic programmes strongly emphasise public health measures for prevention [49,50]. Conversely, students enrolled in scientific and humanitarian faculties exhibited diminished levels of knowledge and less uniform attitudes. These findings align with previous studies documenting reduced participation in health-promoting behaviours among non-health students [51,52,53,54,55], highlighting the need for customised educational interventions that target specific disciplines and cultivate favourable attitudes in various academic fields. This approach will be crucial to ensure that all students, regardless of their chosen field of study, possess the necessary skills to engage in effective health-promoting behaviours during public health emergencies [56,57,58,59,60,61]. Despite the data collection period being approximately one year after the COVID-19 outbreak, which was a period characterised by an extensive awareness campaign related to COVID-19 led by the WHO, the Jordanian Ministry of Health and public-health-related agencies [62,63], the results were worrisome, as almost 90% of the study population had a low level of knowledge related to SARS-CoV-2 transmission, symptoms and treatment. The observed lack of knowledge indicates that despite widespread public health campaigns and abundant information across many media platforms, there remained a significant disparity in students’ comprehension of COVID-19 symptoms, treatment and viral transmission dynamics. This knowledge gap aligns with previous research that highlighted comparable patterns in younger demographics, wherein misinformation and conflicting information from many sources can result in confusion and poor understanding of basic principles [64,65].
Despite low knowledge levels, most participants showed positive behaviours, with over one-third adhering to recommended preventive, avoidance, and disease awareness-seeking behaviours. This contradicts the idea that knowledge is the primary catalyst for health-protective behaviours, suggesting that other factors like societal standards and confidence in authority could also impact behaviour [66]. The Health Belief Model (HBM) suggests that individuals are more likely to adopt health-promoting behaviours when they perceive themselves as at-risk, have confidence in the recommended actions, and feel capable of performing them [66]. Health behaviour scholars argue that authoritative mandates and restrictions are more influential in guiding health behaviour than knowledge and awareness [15,22,66,67].
The analysis supports the hypothesis of a connection between COVID-19 knowledge, attitudes, and behaviours. It demonstrates that knowledge significantly influences attitudes, which in turn influences behaviours. This aligns with the KAB model, which suggests that understanding a health issue shapes attitudes [68,69].
Moreover, the significant associations between knowledge- and attitude-related constructs that emerged from this study echoed the findings of earlier studies, albeit in different contexts [32], including that an increased understanding of disease frequently results in more favourable attitudes towards preventive measures, subsequently promoting the adoption of protective behaviours [47,50]. Increased knowledge about COVID-19 symptoms, treatment and transmission is strongly linked to more positive attitudes towards preventive behaviours. The linkage includes trusting authority and the perceived self-efficacy to take action, which are essential factors in promoting health-protective behaviours during pandemics [70,71].
Furthermore, the substantial path coefficients linking attitudes and behaviours emphasise the mediating function of attitudes in the KAB model. The role of attitudes as a mediator between knowledge and action has been extensively studied in health behaviour research [22,72]. In the COVID-19 context, there is a substantial correlation between good attitudes towards preventative behaviours, such as perceiving that wearing masks and maintaining social distance are effective, and practising these behaviours [56,57,58,59,60]. The analysis provides evidence for the proposed correlation between knowledge and behaviour, mediated by attitudes. This finding emphasises the need to improve knowledge and attitudes to promote behaviour change. This notion is strongly supported by the HBM and the theory of planned behaviour [22,25]. These models highlight that although knowledge is fundamental, the attitudes, influenced by perceived risks, benefits and self-efficacy, ultimately dictate whether individuals participate in health-promoting behaviours.
The study found that perceived susceptibility and severity were not significantly associated with any behavioural or knowledge construct, possibly due to a low knowledge level of COVID-19 symptoms, transmission, and treatment. Accurate assessment of the likelihood of acquiring COVID-19 requires understanding the disease symptoms, complications, and transmission mode [32,73,74,75,76,77].
This study comprehensively assessed COVID-19-related knowledge, attitudes, and behaviours of students from various academic fields, and it investigated the associations between the KAB model’s domain using structural equation modelanalysis, which provided evidence of mediational mechanisms that underline behavioural adherence and compliance. The study’s sample size allows for a reliable analysis of the factors influencing students’ reactions to the pandemic. Moreover, the involvement of students from various faculties provided valuable insights into how educational contexts impact health-related behaviours.
However, the study has several limitations and shortcomings related to its design, sampling and conduct. First, the study’s cross-sectional design limits its ability to establish causal relationships. Additionally, the study did not consider the influence of external factors such as media, government regulations, or the different stages of the pandemic. Second, the sampling framework and the study population, Yarmouk University students, might hinder and limit the possibility of result generalisability and evidence transferability. Third, the reliance on the self-administration approach in data collection could introduce social desirability and recall bias, which could have affected participants’ responses and feedback. Therefore, caution should be practised when interpreting and reporting the findings of this study.
5. Conclusions
The findings highlight the urgent need for customised health education and communication strategies that address the unique needs and attributes of different academic fields. Health students could benefit from specialised training, while scientific and humanitarian students require more fundamental instruction on preventative measures and risk perceptions [50]. Health policymakers should collaborate with educational institutions to create adaptive learning environments that accommodate the changing needs of students from various academic backgrounds, emphasising the issue’s urgency [70]. Additionally, the study confirmed the proposed sequential influence between knowledge, attitudes and behaviours, which is consistent with the KAB model. The reported gender- and discipline-based differences emphasised the role of context in shaping individuals’ attitudes and behaviours.
Author Contributions
S.A.: survey and study design, acquisition of data, interpretation of data, drafting original and final submission, preparing figures and tables. A.E.-O.: survey and study design, interpretation of data, drafting original and final submission. M.A.: survey and study design, acquisition of data, analysing and interpretation of data, drafting original and final submission, preparing figures and tables. All authors have read and agreed to the published version of the manuscript.
Funding
Austen El-Osta is supported by the National Institute for Health and Care Research (NIHR), Applied Research Collaboration (ARC), northwest London. The views expressed are those of the authors and not necessarily those of the NHS or the NIHR or the Department of Health and Social Care.
Institutional Review Board Statement
This study was reviewed and approved by the Institutional Review Board at Jordan University of Science and Technology (JUST) and King Abdulla University Hospital (KAUH), Irbid, Jordan (reference number: 119/12/2020; date of approval: 2 September 2020). Before participating in this study, participants received an information letter and electronically signed a consent form.
Data Availability Statement
Research data will be available upon request to the corresponding author Saja A. Alnahar.
Acknowledgments
The research team would like to thank all the study participants for their participation in and support for this study. The research team would also like to thank the reviewers and assessors for their help in developing and validating the questionnaire instrument.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
| A | Attitude |
| CHERRIES | Checklist for Reporting Results of Internet E-Surveys |
| CFI | Comparative Fit Index |
| COVID-19 | Coronavirus Disease of 2019 |
| B | Behaviour |
| HBM | Health Belief Model |
| HEI | Higher Education Institution |
| K | Knowledge |
| KAB | Knowledge, Attitude and Behaviour model |
| MoH | Ministry of Health |
| RMSEA | Root Mean Square Error of Approximation |
| SARS-CoV-2 | Severe Acute Respiratory Syndrome Coronavirus 2 |
| SEM | Structural Equation Model |
| SRMR | Standardised Root Mean Square Residual |
| TLI | The Tucker–Lewis Index |
| WHO | World Health Organisation |
References
- The World Health Organisation (WHO). WHO Director-General’s Opening Remarks at the Media Briefing on COVID-19–11 March 2020: WHO. 2020. Available online: https://www.who.int/news-room/speeches/item/who-director-general-s-opening-remarks-at-the-media-briefing-on-covid-19---11-march-2020 (accessed on 31 August 2022).
- The World Health Organisation (WHO). Naming the Coronavirus Disease (COVID-19) and the Virus That Causes It: WHO. 2020. Available online: https://www.who.int/emergencies/diseases/novel-coronavirus-2019/technical-guidance/naming-the-coronavirus-disease-(covid-2019)-and-the-virus-that-causes-it (accessed on 31 August 2022).
- The World Health Organisation (WHO). Off-Label Use of Medicines for COVID-19: WHO. 2020. Available online: https://www.who.int/news-room/commentaries/detail/off-label-use-of-medicines-for-covid-19 (accessed on 31 August 2022).
- The World Health Organisation (WHO). Responding to Community Spread of COVID-19: Interim Guidance, 7 March 2020; World Health Organization: Geneva, Switzerland, 2020. [Google Scholar]
- Nussbaumer-Streit, B.; Mayr, V.; Dobrescu, A.I.; Chapman, A.; Persad, E.; Klerings, I.; Wagner, G.; Siebert, U.; Ledinger, D.; Zachariah, C.; et al. Quarantine alone or in combination with other public health measures to control COVID-19: A rapid review. Cochrane Database Syst. Rev. 2020, 4, CD013574. [Google Scholar]
- US Department of Health-Human Services. Interim Pre-Pandemic Planning Guidance: Community Strategy for Pandemic Influenza Mitigation in the United States—Early Targeted Layered Use of Nonpharmaceutical Interventions; US Department of Health and Human Services: Washington, DC, USA, 2007.
- Tanne, J.H.; Hayasaki, E.; Zastrow, M.; Pulla, P.; Smith, P.; Rada, A.G. COVID-19: How doctors and healthcare systems are tackling coronavirus worldwide. BMJ 2020, 368, m1090. [Google Scholar] [CrossRef] [Scilit]
- Bedford, J.; Enria, D.; Giesecke, J.; Heymann, D.L.; Ihekweazu, C.; Kobinger, G.; Lane, H.C.; Memish, Z.; Oh, M.D.; Schuchat, A.; et al. COVID-19: Towards controlling of a pandemic. Lancet 2020, 395, 1015–1018. [Google Scholar] [CrossRef] [Scilit]
- Al Sharif, O. Jordan Announces Lockdown in Effort to Contain Coronavirus; Al-Monitor: Washington, DC, USA, 2020. [Google Scholar]
- The World Health Organisation (WHO). Coronavirus Disease (COVID-19) Advice for the Public: Mythbusters: WHO. 2020. Available online: https://www.who.int/emergencies/diseases/novel-coronavirus-2019/advice-for-public/myth-busters (accessed on 31 August 2022).
- Centers for Disease Control and Prevention (CDC). Learn About COVID-19 and How It Spreads the United States (USA): Centers for Disease Control and Prevention (CDC). 2024. Available online: https://www.cdc.gov/covid/about/index.html?CDC_AA_refVal=https%3A%2F%2Fwww.cdc.gov%2Fcoronavirus%2F2019-ncov%2Fprevent-getting-sick%2Fhow-covid-spreads.html (accessed on 17 August 2024).
- The World Health Organisation (WHO). Coronavirus Disease (COVID-19): How Is It Transmitted? Geneva the World Health Organisation 2021. Available online: https://www.who.int/news-room/questions-and-answers/item/coronavirus-disease-covid-19-how-is-it-transmitted (accessed on 17 August 2024).
- Chu, D.K.; Akl, E.A.; Duda, S.; Solo, K.; Yaacoub, S.; Schünemann, H.J.; El-Harakeh, A.; Bognanni, A.; Lotfi, T.; Loeb, M.; et al. Physical distancing, face masks, and eye protection to prevent person-to-person transmission of SARS-CoV-2 and COVID-19: A systematic review and meta-analysis. Lancet 2020, 395, 1973–1987. [Google Scholar] [CrossRef] [Scilit]
- Gormley, M.; Marawska, L.; Milton, D. It is time to address airborne transmission of coronavirus disease 2019 (COVID-19). Clin. Infect. Dis. 2020, 71, 2311–2313. [Google Scholar] [CrossRef] [Scilit]
- Bavel, J.J.V.; Baicker, K.; Boggio, P.S.; Capraro, V.; Cichocka, A.; Cikara, M.; Crockett, M.J.; Crum, A.J.; Douglas, K.M.; Druckman, J.N.; et al. Using social and behavioural science to support COVID-19 pandemic response. Nat. Hum. Behav. 2020, 4, 460–471. [Google Scholar] [CrossRef] [Scilit]
- Abdelrahman, M. Personality traits, risk perception, and protective behaviors of Arab residents of Qatar during the COVID-19 pandemic. Int. J. Ment. Health Addict. 2022, 20, 237–248. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zickfeld, J.H.; Schubert, T.W.; Herting, A.K.; Grahe, J.; Faasse, K. Correlates of health-protective behavior during the initial days of the COVID-19 outbreak in Norway. arXiv 2020, arXiv:11:564083. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brehm, S.S.; Brehm, J.W. Psychological Reactance: A Theory of Freedom and Control; Academic Press: Cambridge, MA, USA, 2013. [Google Scholar]
- Geller, E.S. The challenge of increasing proenvironment behavior. Handb. Environ. Psychol. 2002, 2, 525–540. [Google Scholar]
- Locke, E.A. Self-efficacy: The exercise of control. Pers. Psychol. 1997, 50, 801. [Google Scholar]
- Matson-Koffman, D.M.; Brownstein, J.N.; Neiner, J.A.; Greaney, M.L. A site-specific literature review of policy and environmental interventions that promote physical activity and nutrition for cardiovascular health: What works? Am. J. Health Promot. 2005, 19, 167–193. [Google Scholar] [CrossRef] [Scilit]
- Ajzen, I. The theory of planned behavior. Organ. Behav. Hum. Decis. Process. 1991, 50, 179–211. [Google Scholar] [CrossRef] [Scilit]
- Okan, O.; Bauer, U.; Levin-Zamir, D.; Pinheiro, P.; Sørensen, K. International Handbook of Health Literacy: Research, Practice and Policy Across the Lifespan; Policy Press: Bristol, UK, 2019. [Google Scholar]
- Gochman, D.S. Health Behavior: Plural Perspectives. Health Behavior: Emerging Research Perspectives; Springer: Berlin/Heidelberg, Germany, 1988; pp. 3–17. [Google Scholar]
- Rosenstock, I.M. Historical origins of the health belief model. Health Educ. Monogr. 1974, 2, 328–335. [Google Scholar] [CrossRef] [Scilit]
- Azlan, A.A.; Hamzah, M.R.; Sern, T.J.; Ayub, S.H.; Mohamad, E. Public knowledge, attitudes and practices towards COVID-19: A cross-sectional study in Malaysia. PLoS ONE 2020, 15, e0233668. [Google Scholar] [CrossRef] [Scilit]
- Limbu, D.K.; Piryani, R.M.; Sunny, A.K. Healthcare workers’ knowledge, attitude and practices during the COVID-19 pandemic response in a tertiary care hospital of Nepal. PLoS ONE 2020, 15, e0242126. [Google Scholar] [CrossRef] [Scilit]
- Tang, C.S.-K.; Wong, C.-Y. Factors influencing the wearing of facemasks to prevent the severe acute respiratory syndrome among adult Chinese in Hong Kong. Prev. Med. 2004, 39, 1187–1193. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morrison, L.G.; Yardley, L. What infection control measures will people carry out to reduce transmission of pandemic influenza? A focus group study. BMC Public Health 2009, 9, 258. [Google Scholar] [CrossRef] [Scilit]
- Jones, J.H.; Salathe, M. Early assessment of anxiety and behavioral response to novel swine-origin influenza A (H1N1). PLoS ONE 2009, 4, e8032. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yap, J.; Lee, V.J.; Yau, T.Y.; Ng, T.P.; Tor, P.-C. Knowledge, attitudes and practices towards pandemic influenza among cases, close contacts, and healthcare workers in tropical Singapore: A cross-sectional survey. BMC Public Health 2010, 10, 442. [Google Scholar] [CrossRef] [Scilit]
- Bish, A.; Michie, S. Demographic and attitudinal determinants of protective behaviours during a pandemic: A review. Br. J. Health Psychol. 2010, 15, 797–824. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- The World Health Organization (WHO). A Guide to Developing Knowledge, Attitude and Practice Surveys; WHO Library Cataloguing-in-Publication Data: Geneva, Switzerland, 2008.
- Rubin, G.J.; Bakhshi, S.; Amlôt, R.; Fear, N.; Potts, H.W.; Michie, S. The design of a survey questionnaire to measure perceptions and behaviour during an influenza pandemic: The Flu TElephone Survey Template (FluTEST). Health Serv. Deliv. Res. 2014, 2, 1–146. [Google Scholar] [CrossRef] [Scilit]
- Khang, L.H.; Peng, T.L.; Mohamad, M.A.; Rajdi, N.Z.I.M.; Goni, M.D. Assessment of knowledge, attitude, and practice regarding ticks and tick borne diseases among horse keepers in Malaysia. Discov. Public Health 2025, 22, 529. [Google Scholar] [CrossRef] [Scilit]
- Bloom, B.S. Learning for Mastery. Instruction and Curriculum. Regional Education Laboratory for the Carolinas and Virginia, Topical Papers and Reprints, Number 1. Eval. Comment 1968, 1, n2. [Google Scholar]
- Bentler, P.M.; Chou, C.-P. Practical issues in structural modeling. Sociol. Methods Res. 1987, 16, 78–117. [Google Scholar] [CrossRef] [Scilit]
- Kline, R.B. Principles and Practice of Structural Equation Modeling; Guilford Publications: New York, NY, USA, 2015. [Google Scholar]
- Hu, L.T.; Bentler, P.M. Cutoff criteria for fit indexes in covariance structure analysis: Conventional criteria versus new alternatives. Struct. Equ. Model. Multidiscip. J. 1999, 6, 1–55. [Google Scholar] [CrossRef] [Scilit]
- Schumacker, R.E.; Lomax, R.G. A Beginner’s Guide to Structural Equation Modeling; Psychology Press: East Sussex, UK, 2004. [Google Scholar]
- Devlieger, I.; Talloen, W.; Rosseel, Y. New developments in factor score regression: Fit indices and a model comparison test. Educ. Psychol. Meas. 2019, 79, 1017–1037. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Idris, M.; Alkhawaja, L.; Ibrahim, H. Gender disparities among students at Jordanian universities during COVID-19. Int. J. Educ. Dev. 2023, 99, 102776. [Google Scholar] [CrossRef] [Scilit]
- The Ministry of Higher Education. Annual Statistical Report; The Ministry of Higher Education: Amman, Jordan, 2020.
- Bailey, S.C.; Serper, M.; Opsasnick, L.; Persell, S.D.; O’Conor, R.; Curtis, L.M.; Benavente, J.Y.; Wismer, G.; Batio, S.; Eifler, M.; et al. Changes in COVID-19 knowledge, beliefs, behaviors, and preparedness among high-risk adults from the onset to the acceleration phase of the US outbreak. J. Gen. Intern. Med. 2020, 35, 3285–3292. [Google Scholar] [CrossRef] [Scilit]
- Quinn, S.C.; Kumar, S. Health inequalities and infectious disease epidemics: A challenge for global health security. Biosecurity Bioterrorism Biodefense Strategy Pract. Sci. 2014, 12, 263–273. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, Y.; Zhang, J. Consumer health information seeking in social media: A literature review. Health Inf. Libr. J. 2017, 34, 268–283. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ferdous, M.Z.; Islam, M.S.; Sikder, M.T.; Mosaddek, A.S.M.; Zegarra-Valdivia, J.A.; Gozal, D. Knowledge, attitude, and practice regarding COVID-19 outbreak in Bangladesh: An online-based cross-sectional study. PLoS ONE 2020, 15, e0239254. [Google Scholar] [CrossRef] [Scilit]
- Zhong, B.-L.; Luo, W.; Li, H.-M.; Zhang, Q.-Q.; Liu, X.-G.; Li, W.-T.; Li, Y. Knowledge, attitudes, and practices towards COVID-19 among Chinese residents during the rapid rise period of the COVID-19 outbreak: A quick online cross-sectional survey. Int. J. Biol. Sci. 2020, 16, 1745. [Google Scholar] [CrossRef] [Scilit]
- Chang, J.-H.; Han, D.; Wang, D. Comparison of Mental Health Status and Behaviour of Chinese Medical and Non-Medical College Students During the Coronavirus Disease 2019 (COVID-19) Pandemic. Psychosom. Med. Res. 2021, 3, 42–52. [Google Scholar] [CrossRef] [Scilit]
- Zhu, X.; Liu, J. Education in and after COVID-19: Immediate responses and long-term visions. Postdigital Sci. Educ. 2020, 2, 695–699. [Google Scholar] [CrossRef] [Scilit]
- Wang, X.; Hegde, S.; Son, C.; Keller, B.; Smith, A.; Sasangohar, F. Investigating mental health of US college students during the COVID-19 pandemic: Cross-sectional survey study. J. Med. Internet Res. 2020, 22, e22817. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Peng, Y.; Pei, C.; Zheng, Y.; Wang, J.; Zhang, K.; Zheng, Z.; Zhu, P. A cross-sectional survey of knowledge, attitude and practice associated with COVID-19 among undergraduate students in China. BMC Public Health 2020, 20, 1292. [Google Scholar] [CrossRef] [Scilit]
- Zhang, M.; Li, Q.; Du, X.; Zuo, D.; Ding, Y.; Tan, X.; Liu, Q. Health behavior toward COVID-19: The role of demographic factors, knowledge, and attitude among Chinese college students during the quarantine period. Asia Pac. J. Public Health 2020, 32, 533–535. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rosenstock, I.M.; Strecher, V.J.; Becker, M.H. Social learning theory and the health belief model. Health Educ. Q. 1988, 15, 175–183. [Google Scholar] [CrossRef] [Scilit]
- Adli, I.; Widyahening, I.S.; Lazarus, G.; Phowira, J.; Baihaqi, L.A.; Ariffandi, B.; Putera, A.M.; Nugraha, D.; Gamalliel, N.; Findyartini, A. Knowledge, attitude, and practice related to the COVID-19 pandemic among undergraduate medical students in Indonesia: A nationwide cross-sectional study. PLoS ONE 2022, 17, e0262827. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pather, N.; Blyth, P.; Chapman, J.A.; Dayal, M.R.; Flack, N.A.; Fogg, Q.A.; Green, R.A.; Hulme, A.K.; Johnson, I.P.; Meyer, A.J.; et al. Forced disruption of anatomy education in Australia and New Zealand: An acute response to the COVID-19 pandemic. Anat. Sci. Educ. 2020, 13, 284–300. [Google Scholar] [CrossRef] [Scilit]
- Gardanova, Z.; Belaia, O.; Zuevskaya, S.; Turkadze, K.; Strielkowski, W. Lessons for medical and health education learned from the COVID-19 pandemic. Healthcare 2023, 11, 1921. [Google Scholar] [CrossRef] [Scilit]
- Ross, D.A. Creating a “quarantine curriculum” to enhance teaching and learning during the COVID-19 pandemic. Acad. Med. 2020, 95, 1125–1126. [Google Scholar] [CrossRef] [Scilit]
- Boutros, P.; Kassem, N.; Nieder, J.; Jaramillo, C.; von Petersdorff, J.; Walsh, F.J.; Bärnighausen, T.; Barteit, S. Education and training adaptations for health workers during the COVID-19 pandemic: A scoping review of lessons learned and innovations. Healthcare 2023, 11, 2902. [Google Scholar] [CrossRef] [Scilit]
- Bults, M.; Beaujean, D.J.; Richardus, J.H.; Voeten, H.A. Perceptions and behavioral responses of the general public during the 2009 influenza A (H1N1) pandemic: A systematic review. Disaster Med. Public Health Prep. 2015, 9, 207–219. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reuben, R.C.; Danladi, M.M.; Saleh, D.A.; Ejembi, P.E. Knowledge, attitudes and practices towards COVID-19: An epidemiological survey in North-Central Nigeria. J. Community Health 2021, 46, 457–470. [Google Scholar] [CrossRef] [Scilit]
- World Health Organisation (WHO). WHO Strategic Preparedness and Response Plan for the Novel Coronavirus (2019-nCoV). Available online: https://www.who.int/publications/i/item/strategic-preparedness-and-response-plan-for-the-new-coronavirus (accessed on 31 August 2022).
- Al-Tammemi, A.B. The Battle Against COVID-19 in Jordan: An Early Overview of the Jordanian Experience. Available online: https://www.frontiersin.org/journals/public-health/articles/10.3389/fpubh.2020.00188/full (accessed on 17 August 2024).
- Rana, M.M.; Karim, M.R.; Wadood, M.A.; Kabir, M.M.; Alam, M.M.; Yeasmin, F.; Islam, M.R. Knowledge of prevention of COVID-19 among the general people in Bangladesh: A cross-sectional study in Rajshahi district. PLoS ONE 2020, 15, e0243410. [Google Scholar] [CrossRef] [Scilit]
- Rabbani, M.G.; Akter, O.; Hasan, M.Z.; Samad, N.; Mahmood, S.S.; Joarder, T. COVID-19 knowledge, attitudes, and practices among people in Bangladesh: Telephone-based cross-sectional survey. JMIR Form. Res. 2021, 5, e28344. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Champion, V.L.; Skinner, C.S. The health belief model. Health Behav. Health Educ. Theory Res. Pract. 2008, 4, 45–65. [Google Scholar]
- Huang, J.; Zheng, R.; Emery, S. Assessing the impact of the national smoking ban in indoor public places in China: Evidence from quit smoking related online searches. PLoS ONE 2013, 8, e65577. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kaliyaperumal, K. Guideline for conducting a knowledge, attitude and practice (KAP) study. AECS Illum. 2004, 4, 7–9. [Google Scholar]
- Launiala, A. How much can a KAP survey tell us about people’s knowledge, attitudes and practices? Some observations from medical anthropology research on malaria in pregnancy in Malawi. Anthropol. Matters 2009, 11. [Google Scholar] [CrossRef] [Scilit]
- Rimal, R.N.; Real, K. Perceived risk and efficacy beliefs as motivators of change: Use of the risk perception attitude (RPA) framework to understand health behaviors. Hum. Commun. Res. 2003, 29, 370–399. [Google Scholar] [CrossRef] [Scilit]
- Schwarzer, R. Modeling health behavior change: How to predict and modify the adoption and maintenance of health behaviors. Appl. Psychol. 2008, 57, 1–29. [Google Scholar] [CrossRef] [Scilit]
- Fishbein, M.; Yzer, M.C. Using theory to design effective health behavior interventions. Commun. Theory 2003, 13, 164–183. [Google Scholar] [CrossRef] [Scilit]
- Jiang, X.; Elam, G.; Yuen, C.; Voeten, H.; de Zwart, O.; Veldhuijzen, I.; Brug, J. The perceived threat of SARS and its impact on precautionary actions and adverse consequences: A qualitative study among Chinese communities in the United Kingdom and the Netherlands. Int. J. Behav. Med. 2009, 16, 58–67. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goodwin, R.; Haque, S.; Neto, F.; Myers, L.B. Initial psychological responses to Influenza A, H1N1 (“ Swine flu”). BMC Infect. Dis. 2009, 9, 166. [Google Scholar] [CrossRef] [Scilit]
- Cava, M.A.; Fay, K.E.; Beanlands, H.J.; McCay, E.A.; Wignall, R. Risk perception and compliance with quarantine during the SARS outbreak. J. Nurs. Scholarsh. 2005, 37, 343–347. [Google Scholar] [CrossRef] [Scilit]
- Brug, J.; Aro, A.R.; Oenema, A.; De Zwart, O.; Richardus, J.H.; Bishop, G.D. SARS risk perception, knowledge, precautions, and information sources, the Netherlands. Emerg. Infect. Dis. 2004, 10, 1486. [Google Scholar] [CrossRef] [Scilit]
- Barr, M.; Raphael, B.; Taylor, M.; Stevens, G.; Jorm, L.; Giffin, M.; Lujic, S. Pandemic influenza in Australia: Using telephone surveys to measure perceptions of threat and willingness to comply. BMC Infect. Dis. 2008, 8, 117. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.