


Abstract
Low levels of physical activity (PA) and sleep disruption are commonly seen in older adult inpatients and are associated with poor health outcomes. Wearable sensors allow for objective continuous monitoring; however, there is no consensus as to how wearable sensors should be implemented. This review aimed to provide an overview of the use of wearable sensors in older adult inpatient populations, including models used, body placement and outcome measures. Five databases were searched; 89 articles met inclusion criteria. We found that studies used heterogenous methods, including a variety of sensor models, placement and outcome measures. Most studies reported the use of only one sensor, with either the wrist or thigh being the preferred location in PA studies and the wrist for sleep outcomes. The reported PA measures can be mostly characterised as the frequency and duration of PA (Volume) with fewer measures relating to intensity (rate of magnitude) and pattern of activity (distribution per day/week). Sleep and circadian rhythm measures were reported less frequently with a limited number of studies providing both physical activity and sleep/circadian rhythm outcomes concurrently. This review provides recommendations for future research in older adult inpatient populations. With protocols of best practice, wearable sensors could facilitate the monitoring of inpatient recovery and provide measures to inform participant stratification and establish common objective endpoints across clinical trials.
1. Introduction
Low levels of physical activity (PA) are commonly seen in older adult inpatients [1,2,3,4], with many inpatients spending long periods of time resting in bed, regardless of their diagnosis [3]. This can have a negative impact on functional capacity, such as walking, dressing, toileting and independent transfer (e.g., movement without assistance to get in or out of bed or a chair) [5,6,7,8]. Reduced PA is associated with increased risk of hospital readmissions [9], institutionalisation [8] and mortality [10].
Increased daytime sleep and napping often occurs in older adults and is frequently associated with disrupted night-time sleep [11,12]. Older inpatients commonly experience frequent night-time awakenings and disturbance [13,14] due to factors such as noise, lighting, medical care interruptions and pain [14,15,16]. Loss of sleep has been linked to increased risk of poor health outcomes [16] including high blood pressure [17], delirium [18], reduced immunity [19] and mortality [20]. Disrupted rest–activity patterns (circadian rhythm) such as fragmented night-time sleep and greater daytime sleep are also linked with negative health outcomes in older inpatients [21,22]. Measuring both PA and sleep/circadian rhythm (SCR) constructs concurrently allows a more nuanced approach for studying hospital-based recovery patterns.
Standard measures of physical activity and sleep constructs, such as activity logs and sleep diaries, have inherent recall and reporting bias [23,24] particularly evident when used in older adults with cognitive impairment [24]. Polysomnography (PSG) is the criterion measure for sleep analysis; however, this only provides information for short periods in controlled environments. This method is also costly, requires trained staff and relies on patient compliance (e.g., for the overnight attachment of electrodes and wires) and hence is generally impractical for hospitalised patients [25]. Wearable sensors are small, non-invasive and provide a continuous and objective method of measuring both PA and SCR outcomes collectively [26]. A wide range of objective metrics can be obtained, including the frequency, intensity and duration of physical activity, to further constructs such as sedentary behaviour, rest–activity and sleep patterns [27]. Wearable sensors have been used in large community-based epidemiologic studies [28,29] and in various clinical populations such as: stroke patients [30], older adults within residential care facilities [31,32] and in individuals with cognitive impairment [31,32,33]. However, hospitalized older adults are often frailer and more unwell than community-based adults, which questions the feasibility of using wearable sensors in this population.
Numerous studies have used wearable sensors in inpatient populations; however, there is no consensus as to protocol use (e.g., which sensors to use, the number, body position, duration of wear) or optimal measures. This review aimed to consolidate the methods of studies that used wearable sensors to measure unscripted (free living) physical activity and sleep behaviour in the hospital setting with all older adult subject populations. Specifically, this review aimed to identify and categorise the study population and to report on the sensor placements, sensor models, monitoring protocol and outcome measures. Secondly, this review aimed to explore the acceptability of the sensors in terms of compliance, and usability in older inpatients.
2. Materials and Methods
2.1. Search Method
Five databases were searched from earliest records to February 2021: PubMed, Ovid Embase, Scopus, Web of Science and Cochrane database. The reporting of this systematic review was guided by the standards of the Preferred Reporting Items for Systematic Review and Meta-Analysis (PRISMA) Statement [34]. The search strategy was developed in PubMed using medical subject headings (MeSH) based on the key concepts of the research question “wearable sensor”, “hospital” and “older adult” (Supplementary Materials, Table S1). To ensure a comprehensive search a list of synonyms was identified from the MeSH terms and from previous reviews. Duplicates were removed from the compiled articles and the titles and abstracts were then reviewed independently by two reviewers (GB and CK). If it was unclear if the paper met the inclusion criteria, the full text was reviewed.
2.2. Inclusion and Exclusion Criteria
Inclusion criteria included inpatients, defined as a facility away from the participants own home/community setting which provided a level of service/specialised care, as either elective or emergency admission, with an overall study mean or median age of ≥65 years, or a clearly defined subsample of the study being of ≥65 years. The study criteria included objectively assessed, non-protocolled wearable sensor outcomes to measure activity, movement, or sleep. Studies were excluded if they used scripted activities. We did not exclude studies based on healthcare condition, including participants with dementia, or prognosis. Articles that focused on day cases (<24-h admissions) or long-term rehabilitation, defined as expected stay of over two weeks, were excluded. In studies which included community dwelling settings, such as older adult residential care settings or repeated measures to include the home environment, only the hospital setting outcomes were used for data extraction. Articles were excluded if the sample size was n ≤ 10, written in other languages than English, were conference abstracts, case reports, literature reviews, meta-analysis, grey literature or study protocols.
2.3. Data Extraction
Data were independently extracted by two reviewers (GB and CK) using a standardised data extraction form. Key outcomes included the study setting, clinical population, type and model of sensor, body placement, participant acceptability/compliance and the sensor measures derived. Any discrepancies in screening or extraction were resolved by an independent reviewer (RAL or RZUR). Due to the mixed study designs included in this review, a customised quality appraisal form was produced adapted from Downs and Black [35] for health interventions and the National Institutes of Health (2014) Quality Assessment Tool for Observational Cohort and Cross-sectional Studies [36]. Assessments were completed independently by GB and CK and an average quality score was derived (Supplementary Materials, Table S1).
3. Results
3.1. Search Yield
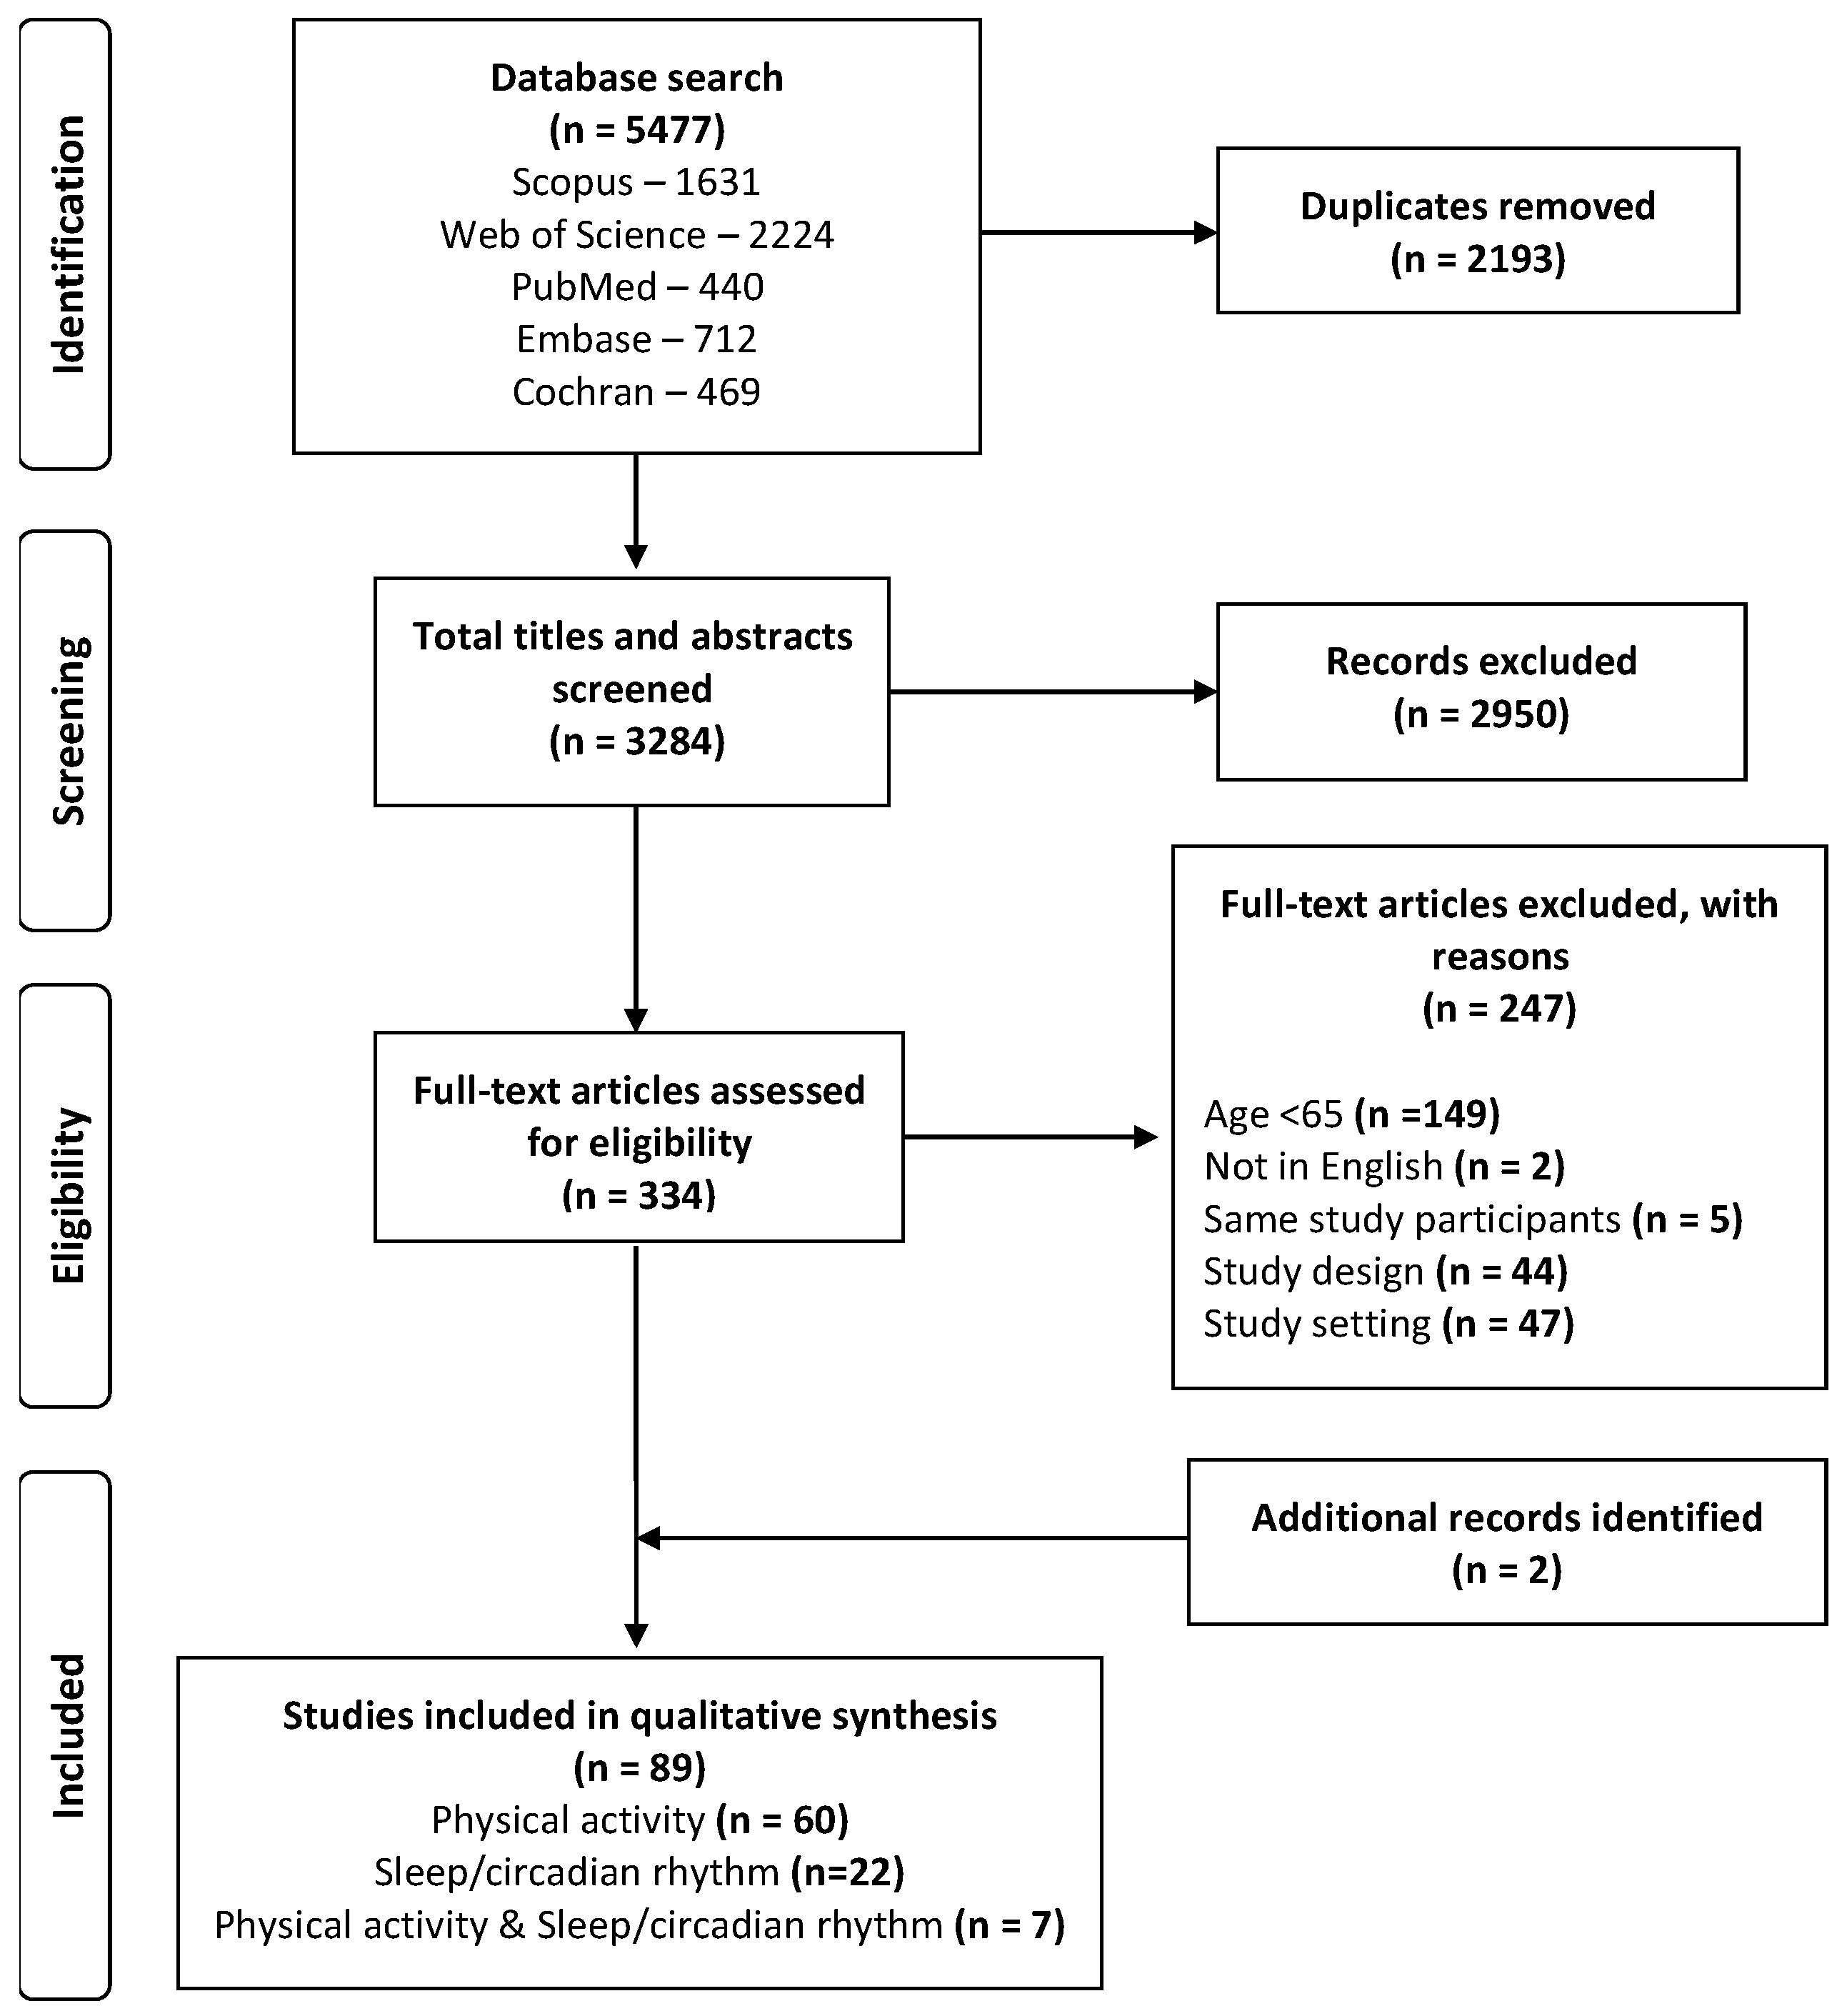
The search yielded 5477 papers (Figure 1); after duplicates were removed 3284 papers were screened by title and abstract, 2950 papers met exclusion criteria and the full text was reviewed in the remaining 334 articles. From the full text review, n = 247 articles were excluded due to study participants were less than 65 years old (n = 149), the full text not being available in English (n = 2), the articles comprised the same study participants (n = 5), protocolled/scripted sensor activity measures were included (n = 44) and study setting involved long term rehabilitation or an expected stay of less than 24 h (n = 47). In addition, two further papers were identified from reviewing the reference lists of the studies [37,38]. The final sample comprised 89 articles, 60 articles on PA measures only, 22 articles on SCR measures only and seven articles which included both PA and SCR measures. To provide a framework for data synthesis, the seven studies that report on both PA and SCR outcomes were considered separately. A summary of all included studies with PA outcomes is presented in Appendix A, Table A1 and all studies with SRC outcomes in Table A2.
Figure 1.
PRISMA flow diagram.
3.2. Study Characteristics
Of the 89 articles, the quality review identified 6 studies that were rated excellent, n = 60 studies rated as good, n = 22 rated as moderate and one study rated as poor [39], all articles were included in this review (Supplementary materials, Table S2). The review captured 74 (83%) observational studies (Appendix A; Table A1 and Table A2), 11 (12%) studies used an experimental design [40,41,42,43,44,45,46,47,48,49,50] and 5 (6%) studies were randomised controlled trials [40,44,46,48,49]. Four were validation studies in which wearable sensors were correlated against PA questionnaires [51], clinical scales [52], treadmill [53] or polysomnography [54].
Studies were conducted across 20 countries (Appendix A; Table A1 and Table A2), the majority were in the United States of America (n = 19) followed by Denmark (n = 10) and Japan (n = 9). Studies included 40 emergency admissions [4,9,10,22,33,46,55,56,57,58,59,60,61,62,63,64,65,66,67,68,69,70,71,72,73,74,75,76,77,78,79,80,81,82,83,84,85,86,87,88], 18 elective [37,38,39,41,44,47,89,90,91,92,93,94,95,96,97,98,99,100], 6 mixed [52,53,101,102,103,104], 5 rehabilitation [51,105,106,107,108] and in n = 20 it was unclear [3,40,42,43,45,48,49,50,54,109,110,111,112,113,114,115,116,117,118,119].
Participants came from 11 study populations (Appendix A; Table A1 and Table A2): older adults (n = 17: PA n = 16, SCR n = 2) [3,4,10,45,46,59,60,61,62,63,101,106,107,113,114,115,116], mixed admissions (delirium and dementia) (n = 12: PA n = 8, SCR n = 7) [33,38,42,43,65,66,67,68,93,94,95,119], orthopaedic surgery/fractures (n = 12: PA n = 11, SCR n = 2) [41,52,69,70,71,72,73,96,97,98,99,102], cardiac medical/surgical patients (n = 10: PA n = 7, SCR n = 4) [39,50,53,74,75,100,103,104,117,118], mixed medical admissions (n = 9: PA n = 3, SCR n = 6) [9,22,55,56,57,58,105,111,112], stroke patients (n = 9: PA n = 8, SCR n = 1) [79,80,81,82,83,84,85,86,87], respiratory patients (n = 6; PA n = 6) [40,51,76,77,78,88], oncology (n = 6: PA n = 4, SCR n = 3) [37,47,90,91,109,110], patients in intensive care (n = 4: PA n = 1, SCR n = 3) [48,49,54,64], other surgery (n = 3: PA n = 2, SCR n = 1) [44,92,108] and patients with Parkinson’s disease (n = 1: PA n = 1) [89].
3.3. Sensor Placement
The wrist was the most common sensor placement across all studies (n = 40: PA n = 21, SCR n = 27) (Table 1), followed by the thigh (PA n = 21) [3,4,40,41,47,59,67,69,71,73,75,80,81,82,86,87,101,102,106,107,114] and ankle (n = 16: PA n = 16, SCR n = 2) [3,9,10,39,45,49,53,61,63,68,69,70,75,79,112,113]. A single sensor was used in 52 (78%) of the PA studies (Appendix A; Table A1). Two sensors were used in (n = 12) PA studies, this included both wrists [83,84], wrist and ankle [61], thigh and ankle [3,69], waist and ankle [53], wrist and thigh [67], chest and thigh [40,47,81] and lower leg and thigh [4,114]. In two studies, three sensors were placed this included the wrist, ankle and arm [68] and the thigh, ankle and waist [75]. One study placed five sensors on each participant to include bilateral wrists and ankles and hip [79].
Table 1.
The sensor placement sites, and physical behaviour outcomes identified in the review.
The wrist was the sole and preferred sensor attachment site in all but four of the SCR studies (Table 1). Chen et al. [49] used the wrist or ankle for securement, Macfarlane et al. [56] used the upper arm, Enomoto et al. [57] secured the sensor at the waist and Davoudi et al. [68] used three sensors on the wrist, ankle and arm.
3.4. Sensor Model
Twenty-five different sensor models were identified (Supplementary material, Table S3). All but four studies [40,43,50,74] described the make or model of the sensor used. All studies used sensors that comprised of an accelerometer (to measure linear acceleration) apart from Stubbs et al. [43] reporting the use of a pedometer (providing no further detail). The most commonly used sensor model for the PA studies was ActivPAL identified in 15 studies [47,59,67,71,73,75,80,81,82,86,87,101,102,106,107] followed by Actigraph (n = 6) [44,46,58,67,68,94] and Fitbit (n = 5) [39,53,62,91,96]. For the SCR identified studies the most commonly used includes: Motionlogger—Ambulatory Monitoring Inc., Ardsley, NY, USA, (n = 9) [55,65,85,95,105,109,110,115,118], Actiwatch (Philips Respironics) (n = 9) [37,48,54,97,98,104,111,116,119] and Actigraph (n = 3) [49,68,92] Actiwatch (Cambridge Neurotechnology, Cambridge, UK) (n = 3) [22,38,93], SenseWear Armband (n = 1) [56] and Lifecorder (n = 1) [57]. Two studies reported using a sensor with an added gyroscope, Thorup et al. [53] using a Shimmer 3 and Denkinger et al. [52] using a Physilog activity monitor (Appendix A, Table A1). Six studies used sensor models that provided accessible raw accelerometer data (gravitational acceleration rather than brand defined units), this includes: Axivity [69,70,114], Misfit Shine [69], GeneActive [60], Shimmer [53] and Physlog [52].
3.5. Monitoring Protocol
In PA studies, sensors were protocolled to be worn continuously in 56 (84%) studies (Appendix A; Table A1). Data were collected or analysed for daytime hours only in ten (15%) studies [43,51,52,73,78,87,88,89,90,117] with the continuity of monitoring not defined in one study [39]. The overall sensor wear-time period varied between the PA studies, with wear time defined as simply during admission in fifteen (22%) studies [9,41,62,75,89,90,91,94,96,101,108,112,116,117,118]. More specifically, only 1 daytime period (≤12 h) was defined in 3 studies [52,73,88], 24 h (or at least) of wear time was defined in 13 (19%) of the PA studies [10,40,53,58,60,61,63,67,69,83,86,106,107], 5 studies specified 2 days [78,82,84,91,114], 4 days were defined in 1 study [103], 3 days (or at least 3 days) were defined in 10 studies [43,44,51,66,70,76,80,81,98,109], 5 days in 3 studies [78,100,102] and 1 study each for 8 days [99], 10 days [33] and 14 days [42]. The monitoring period was not clearly defined in two PA studies [39,87]. A maximum wear time was reported in 16 (24%) studies (range 3–20 days) [3,4,38,45,46,47,53,61,64,68,71,72,77,79,80,113].
For SCR studies, the sensors were protocolled to be worn continuously in 24 (83%) studies (Appendix A; Table A2). Night-time only data collection occurred in five (17%) of the SCR studies [37,49,54,56,65]. Eight studies defined wear time/analysis period as during admission [22,48,50,65,111,116,118,119] with five studies providing a wear time cut off point (range 6–10 nights) [33,38,68,92,93]. More specifically, 24 h/one night was defined in six SCR studies [37,54,55,56,74,98], two nights defined in three studies [49,57,97], three nights in four studies [85,95,109,110], five nights in one study [104] and seven nights in two studies [105,115].
3.6. Physical Activity Outcomes
Twenty-seven separate physical activity definitions were identified across the PA studies (Table 2) (Supplementary material, Figure S1). The volume of PA, defined as the time spent in PA for a specified time frame, was included in 65 (97%) of the identified studies. Number of steps/step counts was the most common outcome measure across studies (n = 32, 48%) [9,10,39,43,44,45,46,47,51,53,61,62,63,66,72,73,74,75,76,77,78,82,87,90,91,99,100,102,103,108,112,113], followed by time spent standing and/or walking (n = 25, 37%) [3,4,40,41,47,52,59,61,63,66,67,71,73,75,78,80,81,82,86,87,88,102,106,107,114] and time spent lying and/or sitting (n = 16, 24%) [3,4,40,47,66,73,75,78,80,81,82,86,87,88,106,114]. The intensity (metabolic demand of PA) was included in 15 (22%) of the studies. Active minutes defined by various metrics was the most common intensity outcome identified in seven studies (10%) [46,58,60,61,69,70,102], followed by minutes of moderate or above intensity (n = 4, 6%) [76,91,100,102], MET minutes active per day/week (n = 3, 4%) [76,100,108] and active energy expenditure/calories per day (n = 3, 4%) [51,89,103]. The distribution of PA per day (pattern) was included in 18 (27%) studies, with nine (13%) [38,42,59,64,68,77,94,118] identified as night-time activity outcomes, seven (10%) [38,42,59,64,68,94,118] as day-time activity outcomes and five (7%) [39,41,79,81,89] as daily variation outcomes.
Table 2.
Summary of physical activity domains and metrics.
3.7. Sleep and Circadian Rhythm Outcomes
Twenty-five separate sleep and circadian rhythm definitions were identified across the SRC studies (Table 3) (Supplementary material, Figure S1). Total sleep time at night was the most common sleep outcome, identified in 22 (76%) of the studies [37,48,49,54,55,56,57,65,68,74,85,92,93,95,97,98,104,105,109,111,116,119], followed by sleep efficiency (n = 14, 48%) [37,48,54,55,56,57,74,92,97,104,109,111,116,119]. Wake after sleep onset (WASO) [37,48,74,85,93,95,109,119], total sleep time during the day [68,74,85,98,104,105,109,115] and number of awakenings [33,37,49,54,55,85,95,105] were each identified in eight (31%) of the studies.
Table 3.
Summary of sleep and circadian rhythm domains and metrics.
The most common circadian rhythm outcome was activity amplitude identified in three (10%) studies [22,38,68] (Table 3). Each of the remaining circadian rhythm outcomes were identified in one study: Cosinor parameters (acrophase, amplitude, mesor, percent rhythm) based on fitting each 24 h data with a (co)sine curve [118], Highest mean activity in any ten hours (M10), Lowest mean activity in any five hours (L5) [68], restlessness index (RI) [38], interdaily stability (IS), intradaily variability (IV) [22], rest activity counts less than the median activity during the rest span (I < 0) [49] and 24 h autocorrelation coefficient R24 [109].
The criteria defining the sleep period and time for the intention to sleep varied between studies, this included a sleep diary/log [37,92,93,95,97,109,110,111,116] or, time of light on/off to define bedtime and final awakening [56,98,119]. Sleep periods were set by the experimenter in five studies [55,65,74,85,104] or reported by observation in three studies [49,54,57]. In three studies, definitions were unclear or ill-defined [48,50,105]; or outcomes were directly provided by proprietary software [33,49].
3.8. Acceptability and Tolerance
Participant views and feedback regarding wearing the sensors were not reported in any of the SCR studies and in only three of the PA studies [61,75,114] (Appendix A; Table A1 and Table A2). The comfort of the sensors and the compatibility with hospital technology/medical care were the themes reported from a semi structured interview [75]. Using feedback from a questionnaire, Lim et al. [61] reported that the acceptability for both the wrist and ankle sensor was high, with 96% of participants tolerating the wrist sensor and 83% tolerating the ankle sensor. One study used a short participant questionnaire and found no discomfort or sleep disruption when using a thigh and lower leg sensor, with 96% of the participants agreeing to wear the sensors again [114].
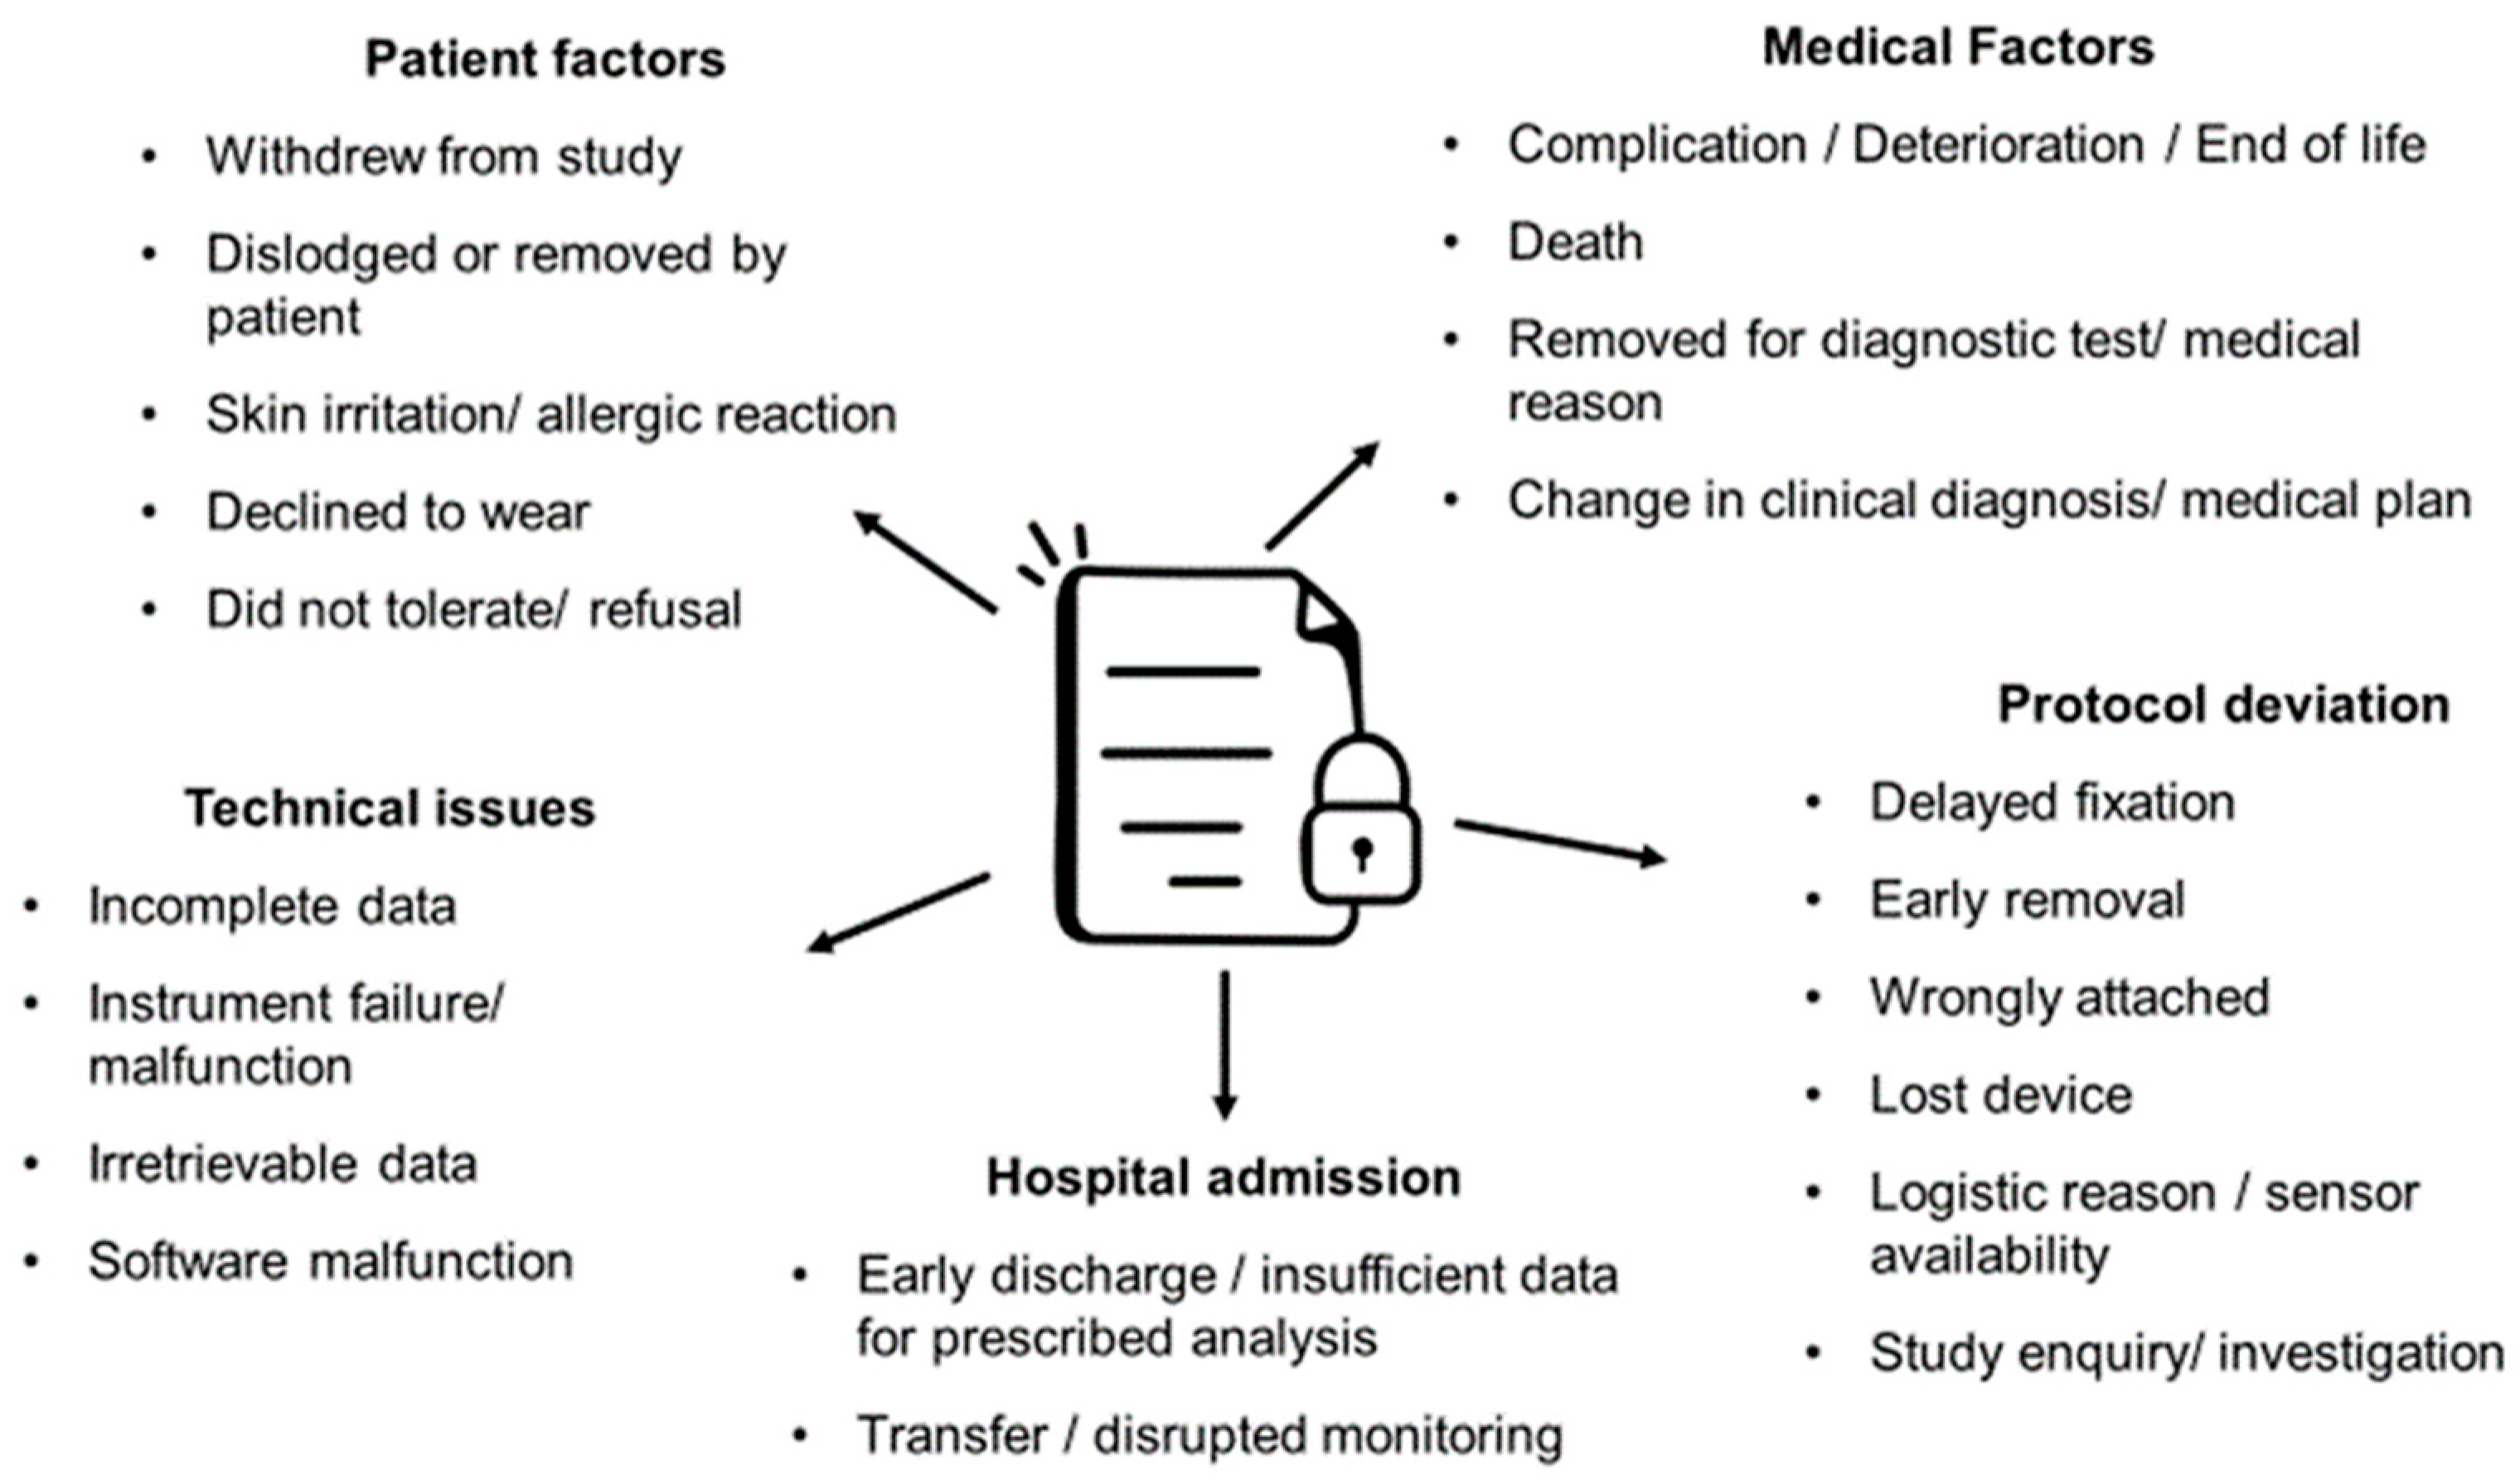
Recruitment information was provided in 34 (38%) of the identified studies (recruitment rate: range 25–100%), with 61 (69%) of the studies providing information for retention (retention rate: range 47–100%) (Appendix A; Table A1 and Table A2). Sources of missing or incomplete sensor data were reported with varying levels of detail and described in some capacity for 69 (78%) of the studies (Figure 2). Most commonly reported reasons for missing data were participant withdrawing from the study reported in 17 (19%) [3,40,42,43,45,50,52,53,59,66,80,86,87,88,91,93,100] studies, sensor malfunction/instrument failure reported in 16 (18%) [41,44,46,73,77,79,80,84,86,90,94,95,96,111,112,116] studies, early discharge in 15 (19%) [9,44,45,47,48,50,52,53,78,81,87,88,89,93,114] studies and also death in 15 (19%) [22,37,39,45,46,62,64,71,78,85,86,87,91,93,104] studies. Skin irritation was reported in six (7%) studies [40,50,76,82,91,102], with sensors reported as lost in four (5%) studies [39,67,106,112].
Figure 2.
Reasons for missing, incomplete, or withdrawn sensor data across studies.
4. Discussion
To our knowledge, this is the first study to provide a comprehensive overview of the use of wearable sensors in older adult inpatients. Studies included a range of older adult hospital populations using heterogenous methods, including a variety of sensor models, placement and outcome measures. Wearable sensors have been used mainly to derive PA outcomes in older adult inpatients as opposed to the more limited number of studies addressing sleep or circadian rhythm outcomes. The inclusion of both PA and SCR outcomes in this review has highlighted the paucity of studies that derive both outcomes concurrently.
4.1. Sensor Placements
A variety of sensor body locations were identified, with the wrist or thigh location each being used in a third of PA studies and the wrist location predominantly used in all but three of the SCR studies. The wrist location was the preferred sensor placement for sleep measures in this review, and has historically been used as it is more reflective of movements of the total trunk and less of movements involved in performing specific tasks [120]. Sensors provide measures of movement reflective of the area they are secured, which is important to consider when research planning. For example, to characterise movement of the impaired and non-impaired arm of stroke patients, Gebruers et al. [84] and Iacovelli et al. [83] secured sensors to both wrists to capture arm movement. When research design is focused on general mobility, e.g., magnitude or intensity of physical activity, sensors are commonly placed on the trunk of the body close to the centre of mass to represent full body movement (rather than general limb movement) [121]. In this review the wrist position was commonly used to provide general mobility measures, relying on arm movement to estimate activity and sedentary behaviour. This may pose significant challenges for measurement accuracy, particularly for quantifying sedentary behaviour [122]. However, in older inpatients who are generally frail and unwell, wrist placement may be less intrusive and a more practical option.
In over a half of studies that reported walking outcomes, the sensor was placed at the thigh or ankle, which has historically been favoured as it is close to the impact site when walking [123]. Four studies each used the wrist for step count estimation [46,62,91,96] or the upper arm [51,76,77,100] which may not provide accurate measures in people with limitations in mobility or slow walking speed [124], as commonly seen in older inpatients. Further locations were identified in the review to quantify steps which included the lower back [66,78], waist [44,90,99,103,108,117] and hip [72] each using different sensor models and protocols.
The sensor was placed on the thigh to provide postural outcomes such as time spent sitting and standing, and sit to stand transitions. Only two studies that used a sensor placed at the thigh focused on step count and activity intensity with no reported postural outcomes [69,102]. A combination of sensor placements; thigh and trunk [40,47,81], thigh and ankle/lower leg [3,4] and thigh, trunk and ankle [75] were used to provide orientation information to help distinguish between time spent sitting and lying and to characterise postural transitions. Securing more than one sensor enabled Evenson et al. [67] to capture wrist movement while sitting to represent restlessness in older adults with delirium. Sensor placement combinations has the potential to provide richer data allowing for further activity characterisation; however, further research is needed into the acceptability and compliance of using wearable sensors in different body locations.
4.2. Sensor Models
Accelerometer-based sensors were predominantly used for physical behaviour monitoring across studies with twenty-five sensor models identified. This is greater than the seven sensor models identified in a previous review [125]; however, this was limited to acute general medical inpatients, excluding specific neurological conditions (such as stroke and Parkinson’s disease). The Activpal was used in almost a quarter of studies deriving PA outcomes, while the Motionlogger and Actiwatch were each used in a third of the sleep/circadian rhythm studies. Two studies in this review included sensors with an additional gyroscope [52,53], these are known as inertial measurement units (IMU’s) and provide a measure of angular velocity [126]. With advances in technology, newer generations of sensors exist which accounts for the many sensor models and versions identified in the review. Many sensor manufacturers provide proprietary software with specific algorithms to derive physical behaviour measures; however, most are not made publicly available. This provides a challenge comparing measures across studies. This review identified six studies that used sensors able to provide raw acceleration data [52,53,60,69,70,114]. Using sensors that allow access to raw data compatible with open-source software is advised as it could potentially standardise analysis across studies to allow more meaningful comparisons. Wrist derived raw accelerometer data from the sensor models GENEActiv, ActiGraph and Axivity can be processed using GGIR, for example, which is an open source R package that can generate both physical activity and sleep outcomes concurrently [121].
4.3. Sensor Outcomes
A number of wearable sensor outcomes were identified with time spent stepping/step count identified in almost half of the physical activity studies. Such ambulatory measures may not be the most insightful or appropriate, as many older adult inpatients commonly spend limited time mobile [3]. If able to mobilise, older adult inpatients generally do so with a slow walking speed in which steps may not be accurately identified by many wearable sensors [127]. Furthermore, the use of walking aids and devices could hinder step count recognition [128]. Characterising various body positions allows for behaviour that is seen more commonly at the patient bedside, such as transferring from lying in bed to sitting in a chair or sitting to standing and may provide a more authentic activity measure for many older inpatients. Over one third of the PA studies in this review reported time spent upright (either alongside step measures or as a stand-alone measurement) and as expected in older adult inpatients physical activity levels are low. Postural recognition can also provide a measure for non-ambulatory or sedentary behaviour. Time spent lying or sitting was reported in 24% of the PA studies. This is an area of increasing interest due to the link established between sedentary behaviour (rather than activity) and poor health outcomes [129,130].
Research based on community dwelling older adults suggests that the pattern of activity and sedentary time and how this is accumulated (i.e., prolonged vs. shorter bouts) is also of importance for health outcomes [131]. This review found only 27% of the PA studies included measures associated with the distribution of physical activity, defined as total activity or time in postural positions, over specified time periods such as night, day, or hourly. Only one study by Norvang et al. [81] provided outcomes relating to bouts of activity and reported the duration and time for sitting, lying and upright bouts. Further pattern-based measures of physical behaviour in older adult inpatients may provide richer information to add to the growing literature.
Sleep disruption and periodical awakenings is common in many older adult inpatients and are associated with various negative health outcomes including high blood pressure [17], delirium [18], reduced immunity [19] and mortality [20]. Only 29 studies reported measures based upon sleep or rest activity patterns (circadian rhythm outcomes). Twenty-five separate measures were reported, with total sleep time at night and sleep efficiency (percentage of time asleep between being in bed and final awakening) being the most used. The criteria defining these measures differed greatly between studies, with the start of the sleep interval and the intention to sleep conceptualised and measured in various ways, ranging from diary recorded time to bed [37,92,93,95,97,109,110,111,116] or lights off [56,98,119], to times set by the experimenter [55,65,74,85,104], observations by clinical staff [49,54,57] and times derived by software algorithms [33,49]. It has been suggested that such loosely defined criteria and measures can adversely affect behavioural clinical interventions and sleep outcome research [132]. A standard reporting method which establishes intention to sleep is needed to allow for more meaningful comparisons across studies.
A focus on rest activity patterns (circadian rhythm measure), provides a broader measure of physical behaviour and relates to the degree of synchronisation of rest and activity to the 24-h cycle. Greater daytime rest episodes alongside pronounced activity at night suggests a disrupted rest–activity pattern (circadian rhythm) and has been linked to negative health outcomes [21,22]. Only six studies reported circadian rhythm measures in this review, with activity amplitude (the difference between the least active 5-hr period and the most active 10-hr period within each 24-hr period) most common and reported in three of the studies. Implementing such measures moves away from the sleep classification concerns associated with low levels of movement seen in older inpatients; in which motionless wake could be misclassified as sleep [133,134], providing more valid outcome measures.
Sensors were protocolled to be worn continuously in 84% of the studies in this review; however, only 8% reported both PA and SCR outcomes. With the building evidence to suggest an interdependent relationship between PA and SCR [135,136] deriving both measures simultaneously in future studies may provide a more nuanced approach to behaviour monitoring and warrants further investigation.
4.4. Acceptability
Limited information was reported regarding the acceptance and compliance of wearing the sensors. Recruitment rates were reported in only 38% of studies, with 69% reporting retention rates. However, caution is advised if using retention rates to inform study planning, as this was defined differently across studies, depending on whether any missing sensor data were considered to compare between the number of participants recruited to analysed. Direct participant feedback was reported in only three studies [61,75,114]. This feedback suggests that wearables were well tolerated in older inpatients; however, this did not include feedback from individuals with cognitive impairment which can be a common exclusion criterion. Reasons for missing, incomplete or withdrawn sensor data were varied, but most frequently was participant withdrawal from the study, alongside factors relating to the hospital setting, such as early discharge and death. Of particular interest, 18% of studies reported sensor malfunction/instrument failure as reasons for missing data. These factors are particularly relevant for research planning.
4.5. Limitations
To our knowledge, this review is the first study to provide a comprehensive overview of the use of wearable sensors to measure both physical activity and sleep behaviour in older adult inpatients, yet this should be considered in light of several limitations. Firstly, we excluded articles not available in English. Therefore, relevant papers may have been missed; however, we undertook a comprehensive and rigorous search of the literature (Supplementary Materials, Table S1) and believe this review includes the key findings in this area.
Secondly, the sample size of the studies ranged from eleven to n = 777. A small number of studies investigated sleep/circadian rhythm outcomes compared to PA with only seven studies investigating both PA and sleep/circadian rhythm concurrently. With non-uniformity of study numbers across groups it is difficult to compare and generalize study findings.
We included a quality assessment to ascertain the methodological quality, and rigor of the studies included. However, we acknowledge the large methodological heterogeneity in included studies, making it difficult to compare the validity across studies. Although most studies did show moderate to good quality, the reporting of the data processing methods and addressing the validity of the sensor outcomes varied. Many studies do use proprietary software for data processing and manufacturers generally do not publish their algorithms, this may explain the limited detail reported. However, when a manufacturer allows for pre-programming input (e.g., sampling frequency and epoch length), this should be reported for reproducibility [137]. In addition, different sensor may be limited due to battery life which may impact on the duration in which studies could collect data. Caution is needed when assessing the validity of the sensor outcomes, as validation studies are commonly based on healthy populations and may not adequately represent older adults particularly in inpatient settings [138]. Cut points used to establish physical intensity levels, such as light or moderate energy expenditure and sleep wake thresholds for sleep analysis, are population specific [139] and are dependent on physiological factors, attachment site and processing protocols [138]. As demonstrated in this review this can vary greatly in the older adult hospital population.
5. Conclusions
In summary, this review highlights the heterogenous methods used for monitoring older adult inpatients including a variety of sensor models, placement and outcome measures, making it a challenge to compare findings across studies. A limited number of studies measure both physical activity and sleep/circadian rhythm constructs concurrently, and this requires further attention. The use of a wrist sensor has the potential to provide both sleep measures and rest activity patterns that have not been readily investigated in older inpatients. Combining a wrist sensor with a sensor positioned to allow postural differentiation, such as thigh or lower back, would provide richer data for physical behaviour characterisation in older inpatients. The use of sensors that provide access to raw data compatible with open-source software is advised, as this would help to standardise analysis across studies to allow more meaningful comparisons. Further research should include population specific validation studies to help inform standard guidance on which sensors to use and the most appropriate body locations. Although sensor model and placement site are dependent on the outcome measures required, consideration must be given to the study population. Finally, further research is needed to explore the acceptability and compliance of the sensors worn at different body locations, which is crucial for future research planning. With standardised protocols of best practice, wearable sensors could facilitate the monitoring of older adult inpatient recovery and rehabilitation by providing measures to inform participant stratification or to establish common objective endpoints in future clinical trials.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/s23104881/s1, Table S1: Search terms used for the review; Table S2: Quality assessment for all included studies; Table S3: The sensor models and versions used to assess physical activity and sleep/circadian rhythm outcomes. Figure S1: The frequency of papers assessing (a) Physical activity metrics (b) Sleep/circadian rhythm metrics.
Author Contributions
Conceptualization, R.A.L., S.D.D., A.J.Y., Y.G. and G.L.B.; methodology, G.L.B., R.A.L., S.D.D., A.J.Y. and Y.G.; formal analysis, G.L.B., C.K., R.Z.U.R. and R.A.L.; writing—original draft preparation, G.L.B.; writing—review and editing, C.K., R.Z.U.R., R.A.L., S.D.D., A.J.Y. and Y.G.; funding acquisition, R.A.L., S.D.D., A.J.Y. and Y.G. All authors have read and agreed to the published version of the manuscript.
Funding
G.L.B. is supported by the Medical Research Council (DiMeN DTP): MR/N013840/1. R.A.L. is supported by a Janet Owens Parkinson’s UK Senior Research Fellowship (F-1801). S.D.D. and A.J.Y. are supported by the National Institute for Health and Care Research (NIHR) Newcastle Biomedical Research Centre (BRC) based at Newcastle Upon Tyne Hospital NHS Foundation Trust, Newcastle University and the Cumbria, Northumberland and Tyne and Wear (CNTW) NHS Foundation Trust. The work was also supported by the NIHR/Wellcome Trust Clinical Research Facility (CRF) infrastructure at Newcastle upon Tyne Hospitals NHS Foundation Trust. All opinions are those of the authors and not the funders. S.D.D. and A.J.Y. are also supported by the Innovative Medicines Initiative 2 Joint Undertaking (IMI2 JU) project Mobilise-D that has received funding from the Innovative Medicines Initiative 2 Joint Undertaking (JU) under grant agreement No. 820820. This JU receives support from the European Union’s Horizon 2020 research and innovation program and the European Federation of Pharmaceutical Industries and Associations (EFPIA). S.D.D. and A.J.Y. are also supported by the Innovative Medicines Initiative 2 Joint Undertaking (IMI2 JU) project IDEA-FAST—Grant Agreement 853981. Content in this publication reflects the authors’ view and neither IMI nor the European Union, EFPIA, or any Associated Partners are responsible for any use that may be made of the information contained herein.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Data may be shared upon request.
Conflicts of Interest
S.D.D. reports consultancy activity with Hoffman La Roche Ltd. outside of this study.
Appendix A
Table A1.
Studies identified in the review for physical activity outcomes.
Table A2.
Studies identified in the review for sleep/circadian rhythm outcomes.
References
- Fisher, S.R.; Graham, J.E.; Brown, C.J.; Galloway, R.V.; Ottenbacher, K.J.; Allman, R.M.; Ostir, G.V. Factors that differentiate level of ambulation in hospitalised older adults. Age Ageing 2012, 41, 107–111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Villumsen, M.; Jorgensen, M.G.; Andreasen, J.; Rathleff, M.S.; Molgaard, C.M. Very Low Levels of Physical Activity in Older Patients During Hospitalization at an Acute Geriatric Ward: A Prospective Cohort Study. J. Aging Phys. Act. 2015, 23, 542–549. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brown, C.J.; Redden, D.T.; Flood, K.L.; Allman, R.M. The underrecognized epidemic of low mobility during hospitalization of older adults. J. Am. Geriatr. Soc. 2009, 57, 1660–1665. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pedersen, M.M.; Bodilsen, A.C.; Petersen, J.; Beyer, N.; Andersen, O.; Lawson-Smith, L.; Kehlet, H.; Bandholm, T. Twenty-four-hour mobility during acute hospitalization in older medical patients. J. Gerontol. A Biol. Sci. Med. Sci. 2013, 68, 331–337. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boyd, C.M.; Landefeld, C.S.; Counsell, S.R.; Palmer, R.M.; Fortinsky, R.H.; Kresevic, D.; Burant, C.; Covinsky, K.E. Recovery of Activities of Daily Living in Older Adults After Hospitalization for Acute Medical Illness. J. Am. Geriatr. Soc. 2008, 56, 2171–2179. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Covinsky, K.E.; Pierluissi, E.; Johnston, C.B. Hospitalization-associated disability: “She was probably able to ambulate, but I’m not sure”. Jama 2011, 306, 1782–1793. [Google Scholar] [CrossRef] [Scilit]
- Lafont, C.; Gérard, S.; Voisin, T.; Pahor, M.; Vellas, B.; The Members of IAGG/AMPA Task Force. Reducing “iatrogenic disability” in the hospitalized frail elderly. J. Nutr. Health Aging 2011, 15, 645–660. [Google Scholar] [CrossRef] [Scilit]
- Zisberg, A.; Shadmi, E.; Sinoff, G.; Gur-Yaish, N.; Srulovici, E.; Admi, H. Low mobility during hospitalization and functional decline in older adults. J. Am. Geriatr. Soc. 2011, 59, 266–273. [Google Scholar] [CrossRef] [Scilit]
- Fisher, S.R.; Graham, J.E.; Ottenbacher, K.J.; Deer, R.; Ostir, G.V. Inpatient Walking Activity to Predict Readmission in Older Adults. Arch. Phys. Med. Rehabil. 2016, 97, S226–S231. [Google Scholar] [CrossRef] [Scilit]
- Ostir, G.V.; Berges, I.M.; Kuo, Y.F.; Goodwin, J.S.; Fisher, S.R.; Guralnik, J.M. Mobility activity and its value as a prognostic indicator of survival in hospitalized older adults. J. Am. Geriatr. Soc. 2013, 61, 551–557. [Google Scholar] [CrossRef] [Scilit]
- Roepke, S.K.; Ancoli-Israel, S. Sleep disorders in the elderly. Indian J. Med. Res. 2010, 131, 302–310. [Google Scholar] [PubMed]
- Lee, C.Y.; Low, L.P.; Twinn, S. Understanding the sleep needs of older hospitalized patients: A review of the literature. Contemp. Nurse 2005, 20, 212–220. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Missildine, K. Sleep and the sleep environment of older adults in acute care settings. J. Gerontol. Nurs. 2008, 34, 15–21. [Google Scholar] [CrossRef] [Scilit]
- Yoder, J.C.; Staisiunas, P.G.; Meltzer, D.O.; Knutson, K.L.; Arora, V.M. Noise and sleep among adult medical inpatients: Far from a quiet night. Arch. Intern. Med. 2012, 172, 68–70. [Google Scholar] [CrossRef] [Scilit]
- Stewart, N.H.; Arora, V.M. Sleep in Hospitalized Older Adults. Sleep Med. Clin. 2018, 13, 127–135. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Delaney, L.J.; Currie, M.J.; Huang, H.C.; Lopez, V.; Van Haren, F. “They can rest at home”: An observational study of patients’ quality of sleep in an Australian hospital. BMC Health Serv. Res. 2018, 18, 524. [Google Scholar] [CrossRef] [Scilit]
- Arora, V.M.; Chang, K.L.; Fazal, A.Z.; Staisiunas, P.G.; Meltzer, D.O.; Zee, P.C.; Knutson, K.L.; Van Cauter, E. Objective Sleep Duration and Quality in Hospitalized Older Adults: Associations with Blood Pressure and Mood. J. Am. Geriatr. Soc. 2011, 59, 2185–2186. [Google Scholar] [CrossRef] [Scilit]
- Inouye, S.K.; Bogardus, S.T., Jr.; Charpentier, P.A.; Leo-Summers, L.; Acampora, D.; Holford, T.R.; Cooney, L.M., Jr. A multicomponent intervention to prevent delirium in hospitalized older patients. N. Engl. J. Med. 1999, 340, 669–676. [Google Scholar] [CrossRef] [Scilit]
- Prather, A.A.; Hall, M.; Fury, J.M.; Ross, D.C.; Muldoon, M.F.; Cohen, S.; Marsland, A.L. Sleep and antibody response to hepatitis B vaccination. Sleep 2012, 35, 1063–1069. [Google Scholar] [CrossRef] [Scilit]
- Martin, J.L.; Fiorentino, L.; Jouldjian, S.; Mitchell, M.; Josephson, K.R.; Alessi, C.A. Poor self-reported sleep quality predicts mortality within one year of inpatient post-acute rehabilitation among older adults. Sleep 2011, 34, 1715–1721. [Google Scholar] [CrossRef] [Scilit]
- Wu, L.; Sun, D. Sleep duration and falls: A systemic review and meta-analysis of observational studies. J. Sleep Res. 2017, 26, 293–301. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vinzio, S.; Ruellan, A.; Perrin, A.E.; Schlienger, J.L.; Goichot, B. Actigraphic assessment of the circadian rest-activity rhythm in elderly patients hospitalized in an acute care unit. Psychiatry Clin. Neurosci. 2003, 57, 53–58. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sallis, J.F.; Saelens, B.E. Assessment of physical activity by self-report: Status, limitations, and future directions. Res. Q. Exerc. Sport 2000, 71 (Suppl. 2), 1–14. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hauer, K.; Lord, S.R.; Lindemann, U.; Lamb, S.E.; Aminian, K.; Schwenk, M. Assessment of Physical Activity in Older People with and without Cognitive Impairment. J. Aging Phys. Act. 2011, 19, 347–372. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hoey, L.M.; Fulbrook, P.; Douglas, J.A. Sleep assessment of hospitalised patients: A literature review. Int. J. Nurs. Stud. 2014, 51, 1281–1288. [Google Scholar] [CrossRef] [Scilit]
- Chen, K.Y.; Bassett, D.R., Jr. The technology of accelerometry-based activity monitors: Current and future. Med. Sci. Sport. Exerc. 2005, 37, S490–S500. [Google Scholar] [CrossRef] [Scilit]
- Migueles, J.H.; Cadenas-Sanchez, C.; Ekelund, U.; Delisle Nyström, C.; Mora-Gonzalez, J.; Löf, M.; Labayen, I.; Ruiz, J.R.; Ortega, F.B. Accelerometer Data Collection and Processing Criteria to Assess Physical Activity and Other Outcomes: A Systematic Review and Practical Considerations. Sport. Med. 2017, 47, 1821–1845. [Google Scholar] [CrossRef] [Scilit]
- Doherty, A.; Jackson, D.; Hammerla, N.; Plötz, T.; Olivier, P.; Granat, M.H.; Wareham, N.J. Large scale population assessment of physical activity using wrist worn accelerometers: The UK biobank study. PLoS ONE 2017, 12, e0169649. [Google Scholar] [CrossRef] [Scilit]
- Menai, M.; van Hees, V.T.; Elbaz, A.; Kivimaki, M.; Singh-Manoux, A.; Sabia, S. Accelerometer assessed moderate-to-vigorous physical activity and successful ageing: Results from the Whitehall II study. Sci. Rep. 2017, 8, 45772. [Google Scholar] [CrossRef] [Scilit]
- Bernaldo de Quirós, M.; Douma, E.H.; van den Akker-Scheek, I.; Lamoth, C.J.C.; Maurits, N.M. Quantification of Movement in Stroke Patients under Free Living Conditions Using Wearable Sensors: A Systematic Review. Sensors 2022, 22, 1050. [Google Scholar] [CrossRef] [Scilit]
- Ancoli-Israel, S.; Clopton, P.; Klauber, M.R.; Fell, R.; Mason, W. Use of wrist activity for monitoring sleep/wake in demented nursing-home patients. Sleep 1997, 20, 24–27. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mc Ardle, R.; Sverdrup, K.; Del Din, S.; Lord, S.; Kerse, N.; Rochester, L.; Taylor, L. Quantifying physical activity in aged residential care facilities: A structured review. Ageing Res. Rev. 2021, 67, 101298. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Valembois, L.; Oasi, C.; Pariel, S.; Jarzebowski, W.; Lafuente-Lafuente, C.; Belmin, J. Wrist Actigraphy: A Simple Way to Record Motor Activity in Elderly Patients with Dementia and Apathy or Aberrant Motor Behavior. J. Nutr. Health Aging 2015, 19, 759–764. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Downs, S.H.; Black, N. The feasibility of creating a checklist for the assessment of the methodological quality both of randomised and non-randomised studies of health care interventions. J. Epidemiol. Community Health 1998, 52, 377–384. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- National Institutes of Health. Quality Assessment Tool for Observational Cohort and CrossSectional Studies. Available online: https://www.nhlbi.nih.gov/health-topics/study-quality-assessment-tools (accessed on 10 May 2021).
- Jakobsen, G.; Engstrom, M.; Thronaes, M.; Lohre, E.T.; Kaasa, S.; Fayers, P.; Hjermstad, M.J.; Klepstad, P. Sleep quality in hospitalized patients with advanced cancer: An observational study using self-reports of sleep and actigraphy. Support. Care Cancer 2020, 28, 2015–2023. [Google Scholar] [CrossRef] [Scilit]
- Osse, R.J.; Tulen, J.H.M.; Bogers, A.J.J.C.; Hengeveld, M.W. Disturbed circadian motor activity patterns in postcardiotomy delirium. Psychiatry Clin. Neurosci. 2009, 63, 56–64. [Google Scholar] [CrossRef] [Scilit]
- Cook, D.J.; Thompson, J.E.; Prinsen, S.K.; Dearani, J.A.; Deschamps, C. Functional recovery in the elderly after major surgery: Assessment of mobility recovery using wireless technology. Ann. Thorac. Surg. 2013, 96, 1057–1061. [Google Scholar] [CrossRef] [Scilit]
- Dall, C.H.; Andersen, H.; Povlsen, T.M.; Henriksen, M. Evaluation of a technology assisted physical activity intervention among hospitalised patients: A randomised study. Eur. J. Intern. Med. 2019, 69, 50–56. [Google Scholar] [CrossRef] [Scilit]
- van Dijk-Huisman, H.C.; Weemaes, A.T.; Boymans, T.A.; Lenssen, A.F.; de Bie, R.A. Smartphone App with an Accelerometer Enhances Patients’ Physical Activity Following Elective Orthopedic Surgery: A Pilot Study. Sensors 2020, 20, 4317. [Google Scholar] [CrossRef] [Scilit]
- Mahlberg, R.; Walther, S.; Eichmann, U.; Tracik, F.; Kunz, D. Effects of rivastigmine on actigraphically monitored motor activity in severe agitation related to Alzheimer’s disease: A placebo-controlled pilot study. Arch. Gerontol. Geriatr. 2007, 45, 19–26. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stubbs, B.; Cooper-Evans, M.S.; Durran, M.; Montenegro, J.M. An exploration of walking activity among older psychiatric inpatients. Int. J. Ther. Rehabil. 2007, 14, 532–537. [Google Scholar] [CrossRef] [Scilit]
- Jonsson, M.; Hurtig-Wennlöf, A.; Ahlsson, A.; Vidlund, M.; Cao, Y.; Westerdahl, E. In-hospital physiotherapy improves physical activity level after lung cancer surgery: A randomized controlled trial. Physiotherapy 2019, 105, 434–441. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cohen, Y.; Zisberg, A.; Chayat, Y.; Gur-Yaish, N.; Gil, E.; Levin, C.; Rand, D.; Agmon, M. Walking for Better Outcomes and Recovery: The Effect of WALK-FOR in Preventing Hospital-Associated Functional Decline Among Older Adults. J. Gerontol. A Biol. Sci. Med. Sci. 2019, 74, 1664–1670. [Google Scholar] [CrossRef] [Scilit]
- Moreno, N.A.; de Aquino, B.G.; Garcia, I.F.; Tavares, L.S.; Costa, L.F.; Giacomassi, I.W.S.; Lunardi, A.C. Physiotherapist advice to older inpatients about the importance of staying physically active during hospitalisation reduces sedentary time, increases daily steps and preserves mobility: A randomised trial. J. Physiother. 2019, 65, 208–214. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Porserud, A.; Aly, M.; Nygren-Bonnier, M.; Hagströmer, M. Objectively measured mobilisation is enhanced by a new behaviour support tool in patients undergoing abdominal cancer surgery. Eur. J. Surg. Oncol. 2019, 45, 1847–1853. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arttawejkul, P.; Reutrakul, S.; Muntham, D.; Chirakalwasan, N. Effect of Nighttime Earplugs and Eye Masks on Sleep Quality in Intensive Care Unit Patients. Indian J. Crit. Care Med. 2020, 24, 6–10. [Google Scholar]
- Chen, J.H.; Chao, Y.H.; Lu, S.F.; Shiung, T.F.; Chao, Y.F. The effectiveness of valerian acupressure on the sleep of ICU patients: A randomized clinical trial. Int. J. Nurs. Stud. 2012, 49, 913–920. [Google Scholar] [CrossRef] [Scilit]
- Gimenez, M.C.; Geerdinck, L.M.; Versteylen, M.; Leffers, P.; Meekes, G.J.; Herremans, H.; de Ruyter, B.; Bikker, J.W.; Kuijpers, P.M.; Schlangen, L.J. Patient room lighting influences on sleep, appraisal and mood in hospitalized people. J. Sleep Res. 2017, 26, 236–246. [Google Scholar] [CrossRef] [Scilit]
- Donaire-Gonzalez, D.; Gimeno-Santos, E.; Serra, I.; Roca, J.; Balcells, E.; Rodríguez, E.; Farrero, E.; Antó, J.M.; Garcia-Aymerich, J.; PAC-COPD Study Group. Validation of the Yale Physical Activity Survey in Chronic Obstructive Pulmonary Disease Patients. [Spanish]. Arch. De Bronconeumol. 2011, 47, 552–560. [Google Scholar] [CrossRef] [Scilit]
- Denkinger, M.D.; Flick, S.E.; Nikolaus, T.; Becker, C.; Aminian, K.; Lindemann, U. Assessing physical activity in inpatient rehabilitation—Sensor-based validation of the PAIR. Eur. Rev. Aging Phys. Act. 2014, 11, 133–139. [Google Scholar] [CrossRef] [Scilit]
- Thorup, C.B.; Andreasen, J.J.; Sorensen, E.E.; Gronkjaer, M.; Dinesen, B.I.; Hansen, J. Accuracy of a step counter during treadmill and daily life walking by healthy adults and patients with cardiac disease. BMJ. Open 2017, 7, e011742. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beecroft, J.M.; Ward, M.; Younes, M.; Crombach, S.; Smith, O.; Hanly, P.J. Sleep monitoring in the intensive care unit: Comparison of nurse assessment, actigraphy and polysomnography. Intensive Care Med. 2008, 34, 2076–2083. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Missildine, K.; Bergstrom, N.; Meininger, J.; Richards, K.; Foreman, M.D. Sleep in hospitalized elders: A pilot study. Geriatr. Nurs. 2010, 31, 263–271. [Google Scholar] [CrossRef] [Scilit]
- Macfarlane, M.; Rajapakse, S.; Loughran, S. What prevents patients sleeping on an acute medical ward? An actigraphy and qualitative sleep study. Sleep Health 2019, 5, 666–669. [Google Scholar] [CrossRef] [Scilit]
- Enomoto, M.; Tsutsui, T.; Higashino, S.; Otaga, M.; Higuchi, S.; Aritake, S.; Hida, A.; Tamura, M.; Matsuura, M.; Kaneita, Y.; et al. Sleep-related problems and use of hypnotics in inpatients of acute hospital wards. Gen. Hosp. Psychiatry 2010, 32, 276–283. [Google Scholar] [CrossRef] [Scilit]
- Chaboyer, W.; Mills, P.M.; Roberts, S.; Latimer, S. Physical activity levels and torso orientations of hospitalized patients at risk of developing a pressure injury: An observational study. Int. J. Nurs. Pract. 2015, 21, 11–17. [Google Scholar] [CrossRef] [Scilit]
- Theou, O.; Kehler, D.S.; Godin, J.; Mallery, K.; MacLean, M.A.; Rockwood, K. Upright time during hospitalization for older inpatients: A prospective cohort study. Exp. Gerontol. 2019, 126, 110681. [Google Scholar] [CrossRef] [Scilit]
- Tasheva, P.; Kraege, V.; Vollenweider, P.; Roulet, G.; Méan, M.; Marques-Vidal, P. Accelerometry assessed physical activity of older adults hospitalized with acute medical illness—An observational study. BMC Geriatr. 2020, 20, 382. [Google Scholar] [CrossRef] [Scilit]
- Lim, S.E.; Dodds, R.; Bacon, D.; Sayer, A.A.; Roberts, H.C. Physical activity among hospitalised older people: Insights from upper and lower limb accelerometry. Aging Clin. Exp. Res. 2018, 30, 1363–1369. [Google Scholar] [CrossRef] [Scilit]
- Kolk, D.; Aarden, J.J.; MacNeil-Vroomen, J.L.; Reichardt, L.A.; van Seben, R.; van der Schaaf, M.; Wold, J. Factors Associated with Step Numbers in Acutely Hospitalized Older Adults: The Hospital-Activities of Daily Living Study. J. Am. Med. Dir. Assoc. 2021, 22, 425–432. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fisher, S.R.; Goodwin, J.S.; Protas, E.J.; Kuo, Y.F.; Graham, J.E.; Ottenbacher, K.J.; Ostir, G.V. Ambulatory activity of older adults hospitalized with acute medical illness. J. Am. Geriatr. Soc. 2011, 59, 91–95. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Estrup, S.; Kjer, C.K.W.; Vilhelmsen, F.; Poulsen, L.M.; Gogenur, I.; Mathiesen, O. Physical function and actigraphy in intensive care survivors-A prospective 3-month follow-up cohort study. Acta Anaesthesiol. Scand 2019, 63, 647–652. [Google Scholar] [CrossRef] [Scilit]
- Tanev, K.S.; Winokur, A.; Pitman, R.K. Sleep Patterns and Neuropsychiatric Symptoms in Hospitalized Patients with Dementia. J. Neuropsychiatry Clin. Neurosci. 2017, 29, 248–253. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fleiner, T.; Gersie, M.; Ghosh, S.; Mellone, S.; Zijlstra, W.; Haussermann, P. Prominent physical inactivity in acute dementia care: Psychopathology seems to be more important than the dose of sedative medication. Int. J. Geriatr. Psychiatry 2019, 34, 308–314. [Google Scholar] [CrossRef] [Scilit]
- Evensen, S.; Bourke, A.K.; Lydersen, S.; Sletvold, O.; Saltvedt, I.; Wyller, T.B.; Taraldsen, K. Motor activity across delirium motor subtypes in geriatric patients assessed using body-worn sensors: A Norwegian cross-sectional study. BMJ Open 2019, 9, e026401. [Google Scholar] [CrossRef] [Scilit]
- Davoudi, A.; Malhotra, K.R.; Shickel, B.; Siegel, S.; Williams, S.; Ruppert, M.; Rashidi, P. Intelligent ICU for Autonomous Patient Monitoring Using Pervasive Sensing and Deep Learning. Sci. Rep. 2019, 9, 8020. [Google Scholar] [CrossRef] [Scilit]
- Schmal, H.; Holsgaard-Larsen, A.; Izadpanah, K.; Brønd, J.C.; Madsen, C.F.; Lauritsen, J. Validation of Activity Tracking Procedures in Elderly Patients after Operative Treatment of Proximal Femur Fractures. Rehabil. Res. Pract. 2018, 2018, 3521271. [Google Scholar] [CrossRef] [Scilit]
- Marsault, L.V.; Ryg, J.; Madsen, C.F.; Holsgaard-Larsen, A.; Lauritsen, J.; Schmal, H. Objectively Measured Physical Activity and Its Association with Functional Independence, Quality of Life and In-Hospital Course of Recovery in Elderly Patients with Proximal Femur Fractures: A Prospective Cohort Study. Rehabil. Res. Pract. 2020, 2020, 5907652. [Google Scholar] [CrossRef] [Scilit]
- Kronborg, L.; Bandholm, T.; Palm, H.; Kehlet, H.; Kristensen, M.T. Physical Activity in the Acute Ward Following Hip Fracture Surgery is Associated with Less Fear of Falling. J. Aging Phys. Act. 2016, 24, 525–532. [Google Scholar] [CrossRef] [Scilit]
- Keppler, A.M.; Holzschuh, J.; Pfeufer, D.; Neuerburg, C.; Kammerlander, C.; Böcker, W.; Fürmetz, J. Postoperative physical activity in orthogeriatric patients—New insights with continuous monitoring. Injury 2020, 51, 628–632. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davenport, S.J.; Arnold, M.; Hua, C.; Schenck, A.; Batten, S.; Taylor, N.F. Physical Activity Levels During Acute Inpatient Admission After Hip Fracture are Very Low. Physiother Res. Int. 2015, 20, 174–181. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Takaesu, Y.; Futenma, K.; Kobayashi, M.; Komada, Y.; Tanaka, N.; Yamashina, A.; Inoue, Y. A preliminary study on the relationships between diurnal melatonin secretion profile and sleep variables in patients emergently admitted to the coronary care unit. Chronobiol. Int. 2015, 32, 875–879. [Google Scholar] [CrossRef] [Scilit]
- Floegel, T.A.; Allen, K.D.; Buman, M.P. A pilot study examining activity monitor use in older adults with heart failure during and after hospitalization. Geriatr. Nurs. 2019, 40, 185–189. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsai, L.L.; Alison, J.A.; McKenzie, D.K.; McKeough, Z.J. Physical activity levels improve following discharge in people admitted to hospital with an acute exacerbation of chronic obstructive pulmonary disease. Chron. Respir Dis. 2016, 13, 23–32. [Google Scholar] [CrossRef] [Scilit]
- Orme, M.W.; Harvey-Dunstan, T.C.; Boral, I.; Chaplin, E.J.; Hussain, S.F.; Morgan, M.D.; Steiner, M.C.; Singh, S.J.; Greening, N.J. Changes in physical activity during hospital admission for chronic respiratory disease. Respirology 2019, 24, 652–657. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Borges, R.C.; Carvalho, C.R.F. Physical activity in daily life in Brazilian COPD patients during and after exacerbation. COPD 2012, 9, 596–602. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Strømmen, A.M.; Christensen, T.; Jensen, K. Quantitative measurement of physical activity in acute ischemic stroke and transient ischemic attack. Stroke 2014, 45, 3649–3655. [Google Scholar] [CrossRef] [Scilit]
- Sheedy, R.; Kramer, S.F.; Johnson, L.; Shields, N.; Churilov, L.; Cadilhac, D.A.; Bernhardt, J. Acute Hospital Admission for Stroke Is Characterised by Inactivity. Stroke Res. Treat. 2020, 2020, 5879295. [Google Scholar] [CrossRef] [Scilit]
- Norvang, O.P.; Hokstad, A.; Taraldsen, K.; Tan, X.; Lydersen, S.; Indredavik, B.; Askim, T. Time spent lying, sitting, and upright during hospitalization after stroke: A prospective observation study. BMC Neurol. 2018, 18, 138. [Google Scholar] [CrossRef] [Scilit]
- Kerr, A.; Rowe, P.; Esson, D.; Barber, M. Changes in the physical activity of acute stroke survivors between inpatient and community living with early supported discharge: An observational cohort study. Physiotherapy 2016, 102, 327–331. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iacovelli, C.; Caliandro, P.; Rabuffetti, M.; Padua, L.; Simbolotti, C.; Reale, G.; Ferrarin, M.; Rossini, P.M. Actigraphic measurement of the upper limbs movements in acute stroke patients. J. Neuroeng. Rehabil. 2019, 16, 153. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gebruers, N.; Truijen, S.; Engelborghs, S.; De Deyn, P.P. Predictive value of upper-limb accelerometry in acute stroke with hemiparesis. J. Rehabil. Res. Dev. 2013, 50, 1099–1106. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bakken, L.N.; Kim, H.S.; Finset, A.; Lerdal, A. Stroke patients’ functions in personal activities of daily living in relation to sleep and socio-demographic and clinical variables in the acute phase after first-time stroke and at six months of follow-up. J. Clin. Nurs. 2012, 21, 1886–1895. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Askim, T.; Bernhardt, J.; Churilov, L.; Fredriksen, K.R.; Indredavik, B. Changes in physical activity and related functional and disability levels in the first six months after stroke: A longitudinal follow-up study. J. Rehabil. Med. 2013, 45, 423–428. [Google Scholar] [CrossRef] [Scilit]
- Kunkel, D.; Burnett, M.; Ashburn, A. Physical inactivity post-stroke: A 3-year longitudinal study. Disabil. Rehabil. 2015, 37, 304–310. [Google Scholar] [CrossRef] [Scilit]
- Pitta, F.; Troosters, T.; Probst, V.S.; Spruit, M.A.; Decramer, M.; Gosselink, R. Physical activity and hospitalization for exacerbation of COPD. Chest 2006, 129, 536–544. [Google Scholar] [CrossRef] [Scilit]
- Ito, H.; Yokoi, D.; Kobayashi, R.; Okada, H.; Kajita, Y.; Okuda, S. The relationships between three-axis accelerometer measures of physical activity and motor symptoms in patients with Parkinson’s disease: A single-center pilot study. BMC Neurol. 2020, 20, 340. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morikawa, A.; Naito, T.; Sugiyama, M.; Okayama, T.; Aoyama, T.; Tanuma, A.; Omae, K.; Takahashi, T. Impact of Cancer Cachexia on Hospitalization-associated Physical Inactivity in Elderly Patients with Advanced Non-small-cell Lung Cancer. Asia Pac. J. Oncol. Nurs. 2018, 5, 377–382. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jonker, L.T.; Hendriks, S.; Lahr, M.M.; van Munster, B.C.; de Bock, G.H.; van Leeuwen, B.L. Postoperative recovery of accelerometer-based physical activity in older cancer patients. Eur. J. Surg. Oncol. 2020, 46, 2083–2090. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ida, M.; Onodera, H.; Yamauchi, M.; Kawaguchi, M. Preoperative sleep disruption and postoperative functional disability in lung surgery patients: A prospective observational study. J. Anesth. 2019, 33, 501–508. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Todd, O.M.; Gelrich, L.; MacLullich, A.M.; Driessen, M.; Thomas, C.; Kreisel, S.H. Sleep Disruption at Home As an Independent Risk Factor for Postoperative Delirium. J. Am. Geriatr. Soc. 2017, 65, 949–957. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maybrier, H.R.; King, C.R.; Crawford, A.E.; Mickle, A.M.; Emmert, D.A.; Wildes, T.S.; ENGAGES Study Investigators. Early Postoperative Actigraphy Poorly Predicts Hypoactive Delirium. J. Clin. Sleep Med. 2019, 15, 79–87. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leung, J.M.; Sands, L.P.; Newman, S.; Meckler, G.; Xie, Y.; Gay, C.; Lee, K. Preoperative Sleep Disruption and Postoperative Delirium. J. Clin. Sleep Med. 2015, 11, 907–913. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Twiggs, J.; Salmon, L.; Kolos, E.; Bogue, E.; Miles, B.; Roe, J. Measurement of physical activity in the pre- and early post-operative period after total knee arthroplasty for Osteoarthritis using a Fitbit Flex device. Med. Eng. Phys. 2018, 51, 31–40. [Google Scholar] [CrossRef] [Scilit]
- Miller, A.; Roth, T.; Roehrs, T.; Yaremchuk, K. Correlation between sleep disruption on postoperative pain. Otolaryngol.—Head Neck Surg. 2015, 152, 964–968. [Google Scholar] [CrossRef] [Scilit]
- Krenk, L.; Jennum, P.; Kehlet, H. Activity, sleep and cognition after fast-track hip or knee arthroplasty. J. Arthroplast. 2013, 28, 1265–1269. [Google Scholar] [CrossRef] [Scilit]
- Hayashi, K.; Kako, M.; Suzuki, K.; Takagi, Y.; Terai, C.; Yasuda, S.; Nishida, Y. Impact of variation in physical activity after total joint replacement. J. Pain Res. 2018, 11, 2399–2406. [Google Scholar] [CrossRef] [Scilit]
- Mungovan, S.F.; Singh, P.; Gass, G.C.; Smart, N.A.; Hirschhorn, A.D. Effect of physical activity in the first five days after cardiac surgery. J. Rehabil. Med. 2017, 49, 71–77. [Google Scholar] [CrossRef] [Scilit]
- Evensen, S.; Sletvold, O.; Lydersen, S.; Taraldsen, K. Physical activity among hospitalized older adults—An observational study. BMC Geriatr. 2017, 17, 110. [Google Scholar] [CrossRef] [Scilit]
- Peiris, C.L.; Taylor, N.F.; Shields, N. Patients receiving inpatient rehabilitation for lower limb orthopaedic conditions do much less physical activity than recommended in guidelines for healthy older adults: An observational study. J. Physiother. 2013, 59, 39–44. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Izawa, K.P.; Watanabe, S.; Hirano, Y.; Matsushima, S.; Suzuki, T.; Oka, K.; Akashi, Y.J. Gender-related differences in maximum gait speed and daily physical activity in elderly hospitalized cardiac inpatients: A preliminary study. Medicine 2015, 94, e623. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amofah, H.A.; Brostrom, A.; Fridlund, B.; Bjorvatn, B.; Haaverstad, R.; Hufthammer, K.O.; Kuiper, K.K.; Ranhoff, A.H.; Norekval, T.M.; Investigators, C. Sleep in octogenarians during the postoperative phase after transcatheter or surgical aortic valve replacement. Eur. J. Cardiovasc. Nurs. 2016, 15, 168–177. [Google Scholar] [CrossRef] [Scilit]
- Alessi, C.A.; Martin, J.L.; Webber, A.P.; Alam, T.; Littner, M.R.; Harker, J.O.; Josephson, K.R. More daytime sleeping predicts less functional recovery among older people undergoing inpatient post-acute rehabilitation. Sleep 2008, 31, 1291–1300. [Google Scholar] [PubMed]
- Norheim, K.L.; Cullum, C.K.; Andersen, J.L.; Kjaer, M.; Karlsen, A. Inflammation Relates to Resistance Training-induced Hypertrophy in Elderly Patients. Med. Sci. Sport. Exerc. 2017, 49, 1079–1085. [Google Scholar] [CrossRef] [Scilit]
- Klenk, J.; Wekenmann, S.; Schwickert, L.; Lindemann, U.; Becker, C.; Rapp, K. Change of Objectively-Measured Physical Activity during Geriatric Rehabilitation. Sensors 2019, 19, 5451. [Google Scholar] [CrossRef] [Scilit]
- Matsuo, T.; Sakaguchi, T.; Ishida, A.; Yuguchi, S.; Saito, K.; Nakajima, M.; Ujikawa, T.; Morisawa, T.; Chikazawa, G.; Takahashi, T. Effect of in-hospital physical activity on cardiovascular prognosis in lower extremity bypass for claudication. J. Phys. Sci. 2015, 27, 1855–1859. [Google Scholar] [CrossRef] [Scilit]
- Fernandes, R.; Stone, P.; Andrews, P.; Morgan, R.; Sharma, S. Comparison between fatigue, sleep disturbance, and circadian rhythm in cancer inpatients and healthy volunteers: Evaluation of diagnostic criteria for cancer-related fatigue. J. Pain Symptom Manag. 2006, 32, 245–254. [Google Scholar] [CrossRef] [Scilit]
- Chang, W.P.; Smith, R.; Lin, C.C. Age and rest-activity rhythm as predictors of survival in patients with newly diagnosed lung cancer. Chronobiol. Int. 2018, 35, 188–197. [Google Scholar] [CrossRef] [Scilit]
- Shear, T.C.; Balachandran, J.S.; Mokhlesi, B.; Spampinato, L.M.; Knutson, K.L.; Meltzer, D.O.; Arora, V.M. Risk of sleep apnea in hospitalized older patients. J. Clin. Sleep Med. 2014, 10, 1061–1066. [Google Scholar] [CrossRef] [Scilit]
- Sallis, R.; Roddy-Sturm, Y.; Chijioke, E.; Litman, K.; Kanter, M.H.; Huang, B.Z.; Shen, E.; Nguyen, H.Q. Stepping toward discharge: Level of ambulation in hospitalized patients. J. Hosp. Med. 2015, 10, 384–389. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McCullagh, R.; Dillon, C.; Dahly, D.; Horgan, N.F.; Timmons, S. Walking in hospital is associated with a shorter length of stay in older medical inpatients. Physiol. Meas. 2016, 37, 1872–1884. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hartley, P.; Keevil, V.L.; Westgate, K.; White, T.; Brage, S.; Romero-Ortuno, R.; Deaton, C. Using Accelerometers to Measure Physical Activity in Older Patients Admitted to Hospital. Curr. Gerontol. Geriatr. Res. 2018, 2018, 3280240. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dzierzewski, J.M.; Fung, C.H.; Jouldjian, S.; Alessi, C.A.; Irwin, M.R.; Martin, J.L. Decrease in daytime sleeping is associated with improvement in cognition after hospital discharge in older adults. J. Am. Geriatr. Soc. 2014, 62, 47–53. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beveridge, C.; Knutson, K.; Spampinato, L.; Flores, A.; Meltzer, D.O.; Van Cauter, E.; Arora, V.M. Daytime Physical Activity and Sleep in Hospitalized Older Adults: Association with Demographic Characteristics and Disease Severity. J. Am. Geriatr. Soc. 2015, 63, 1391–1400. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Takahashi, T.; Kumamaru, M.; Jenkins, S.; Saitoh, M.; Morisawa, T.; Matsuda, H. In-patient step count predicts re-hospitalization after cardiac surgery. J. Cardiol. 2015, 66, 286–291. [Google Scholar] [CrossRef] [Scilit]
- Redeker, N.S.; Wykpisz, E. Effects of age on activity patterns after coronary artery bypass surgery. Heart Lung 1999, 28, 5–14. [Google Scholar] [CrossRef] [Scilit]
- Jaiswal, S.J.; Kang, D.Y.; Wineinger, N.E.; Owens, R.L. Objectively measured sleep fragmentation is associated with incident delirium in older hospitalized patients: Analysis of data collected from an randomized controlled trial. J. Sleep Res. 2020, 30, e13205. [Google Scholar] [CrossRef] [Scilit]
- Middelkoop, H.A.; van Dam, E.M.; Smilde-van den Doel, D.A.; Van Dijk, G. 45-hour continuous quintuple-site actimetry: Relations between trunk and limb movements and effects of circadian sleep-wake rhythmicity. Psychophysiology 1997, 34, 199–203. [Google Scholar] [CrossRef] [Scilit]
- Migueles, J.H.; Rowlands, A.V.; Huber, F.; Sabia, S.; van Hees, V.T. GGIR: A Research Community–Driven Open Source R Package for Generating Physical Activity and Sleep Outcomes From Multi-Day Raw Accelerometer Data. J. Meas. Phys. Behav. 2019, 2, 188–196. [Google Scholar] [CrossRef] [Scilit]
- Rosenberger, M.E.; Haskell, W.L.; Albinali, F.; Mota, S.; Nawyn, J.; Intille, S. Estimating activity and sedentary behavior from an accelerometer on the hip or wrist. Med. Sci. Sport. Exerc. 2013, 45, 964–975. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mannini, A.; Sabatini, A.M. On-line classification of human activity and estimation of walk-run speed from acceleration data using support vector machines. Annu. Int. Conf. IEEE Eng. Med. Biol. Soc. 2011, 2011, 3302–3305. [Google Scholar] [PubMed]
- Moore, C.C.; McCullough, A.K.; Aguiar, E.J.; Ducharme, S.W.; Tudor-Locke, C. Toward Harmonized Treadmill-Based Validation of Step-Counting Wearable Technologies: A Scoping Review. J. Phys. Act. Health 2020, 17, 840–852. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lim, S.E.R.; Ibrahim, K.; Sayer, A.A.; Roberts, H.C. Assessment of Physical Activity of Hospitalised Older Adults: A Systematic Review. J. Nutr. Health Aging 2018, 22, 377–386. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chernbumroong, S.; Cang, S.; Yu, H. Genetic algorithm-based classifiers fusion for multisensor activity recognition of elderly people. IEEE J. Biomed. Health Inf. 2015, 19, 282–289. [Google Scholar] [CrossRef] [Scilit]
- Tedesco, S.; Sica, M.; Ancillao, A.; Timmons, S.; Barton, J.; O’Flynn, B. Accuracy of consumer-level and research-grade activity trackers in ambulatory settings in older adults. PLoS ONE 2019, 14, e0216891. [Google Scholar] [CrossRef] [Scilit]
- Floegel, T.A.; Florez-Pregonero, A.; Hekler, E.B.; Buman, M.P. Validation of Consumer-Based Hip and Wrist Activity Monitors in Older Adults with Varied Ambulatory Abilities. J. Gerontol. A Biol. Sci. Med. Sci. 2017, 72, 229–236. [Google Scholar] [CrossRef] [Scilit]
- Ekelund, U.; Tarp, J.; Steene-Johannessen, J.; Hansen, B.H.; Jefferis, B.; Fagerland, M.W.; Whincup, P.; Diaz, K.M.; Hooker, S.P.; Chernofsky, A.; et al. Dose-response associations between accelerometry measured physical activity and sedentary time and all cause mortality: Systematic review and harmonised meta-analysis. BMJ. 2019, 366, l4570. [Google Scholar] [CrossRef] [Scilit]
- Owen, N.; Sparling, P.B.; Healy, G.N.; Dunstan, D.W.; Matthews, C.E. Sedentary behavior: Emerging evidence for a new health risk. Mayo. Clin. Proc. 2010, 85, 1138–1141. [Google Scholar] [CrossRef] [Scilit]
- Dohrn, I.-M.; Gardiner, P.A.; Winkler, E.; Welmer, A.-K. Device-measured sedentary behavior and physical activity in older adults differ by demographic and health-related factors. Eur. Rev. Aging Phys. Act. 2020, 17, 8. [Google Scholar] [CrossRef] [Scilit]
- Reed, D.L.; Sacco, W.P. Measuring Sleep Efficiency: What Should the Denominator Be? J. Clin. Sleep Med. 2016, 12, 263–266. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marino, M.; Li, Y.; Rueschman, M.N.; Winkelman, J.W.; Ellenbogen, J.M.; Solet, J.M.; Dulin, H.; Berkman, L.F.; Buxton, O.M. Measuring sleep: Accuracy, sensitivity, and specificity of wrist actigraphy compared to polysomnography. Sleep 2013, 36, 1747–1755. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sivertsen, B.; Omvik, S.; Havik, O.E.; Pallesen, S.; Bjorvatn, B.; Nielsen, G.H.; Straume, S.; Nordhus, I.H. A Comparison of Actigraphy and Polysomnography in Older Adults Treated for Chronic Primary Insomnia. Sleep 2006, 29, 1353–1358. [Google Scholar] [CrossRef] [Scilit]
- Holfeld, B.; Ruthig, J.C. A longitudinal examination of sleep quality and physical activity in older adults. J. Appl. Gerontol. 2014, 33, 791–807. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vanderlinden, J.; Boen, F.; van Uffelen, J.G.Z. Effects of physical activity programs on sleep outcomes in older adults: A systematic review. Int. J. Behav. Nutr. Phys. Act. 2020, 17, 11. [Google Scholar] [CrossRef] [Scilit]
- Montoye, A.H.K.; Moore, R.W.; Bowles, H.R.; Korycinski, R.; Pfeiffer, K.A. Reporting accelerometer methods in physical activity intervention studies: A systematic review and recommendations for authors. Br. J. Sport. Med. 2018, 52, 1507. [Google Scholar] [CrossRef] [Scilit]
- Migueles, J.H.; Cadenas-Sanchez, C.; Alcantara, J.M.A.; Leal-Martín, J.; Mañas, A.; Ara, I.; Glynn, N.W.; Shiroma, E.J. Calibration and Cross-Validation of Accelerometer Cut-Points to Classify Sedentary Time and Physical Activity from Hip and Non-Dominant and Dominant Wrists in Older Adults. Sensors 2021, 21, 3326. [Google Scholar] [CrossRef] [Scilit]
- Watson, K.B.; Carlson, S.A.; Carroll, D.D.; Fulton, J.E. Comparison of accelerometer cut points to estimate physical activity in US adults. J. Sport. Sci. 2014, 32, 660–669. [Google Scholar] [CrossRef] [Scilit]


Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).