


Abstract
The intrinsic subtype of triple-negative breast cancer (TNBC) is based on genomic evaluation. In this study, we report the survival and pathological complete response (pCR) rates of TNBC patients subtyped by IHC and treated with neoadjuvant chemotherapy (NACT). A retrospective cohort of 187 TNBC patients who received NACT between 2008 and 2017 was used, and IHC subtyping was performed on biopsy specimens before chemotherapy. The subtyping revealed predominantly basal-like tumors (IHC-BL, 61%), followed by basal-like immune-suppressed tumors (IHC-BLIS, 31%), mesenchymal tumors (12.5%), luminal androgen receptor tumors (IHC-LAR, 12%), and basal-like immune-activated tumors (IHC-BLIA, 10.9%). The pCR rate varied among subtypes, with IHC-BLIA showing the highest (30.0%) and IHC-LAR showing the lowest (4.5%). IHC-BLIS led in recurrence sites. Overall and disease-free survival analyses did not show significant differences among subtypes, although IHC-BLIA demonstrated a trend toward better survival, and IHC-mesenchymal, worse. Patients who achieved pCR exhibited significantly better disease-free survival and overall survival than non-responders. This study underscores the potential of IHC-based subtyping in TNBC management, highlighting distinct response patterns to neoadjuvant chemotherapy and potential implications for treatment strategies. Further research is warranted to validate these findings and explore tailored therapeutic approaches for specific TNBC subtypes.
1. Introduction
According to Cancer Research UK, triple-negative breast cancer (TNBC) accounts for approximately 15% of malignancies affecting the breast. Characterized by the absence of estrogen, progesterone, and Her2 receptor positivity, it is usually associated with a poor prognosis, and chemotherapy remains the main basis of systemic treatment [1]. In the last decade, the relevant benefits of chemotherapy combined with immunotherapy and targeted therapy for patients with pathogenic germline BRCA mutations have positively impacted outcomes in both curative and palliative settings [2].
However, TNBC represents a heterogeneous group of several subtypes with distinct drivers, survival outcomes, and responses to systemic therapy [3]. Several classifications have been proposed and validated, largely based on genomic evaluation of the tumors [4]. In 2011, Lehmann et al. characterized seven subtypes by gene expression, including one unstable. Basal-like 1 (BL1) is associated with genomic repair pathway deficiencies; basal-like 2 (BL2) is enriched in growth factor signaling-related genes; immunomodulatory (IM) is enriched in immunological signaling; and mesenchymal (MES) and mesenchymal stem–like (MSL) are enriched in components and pathways related to cell motility and the luminal androgen receptor (LAR), and androgen and metabolism genes are enriched [5]. Later, in 2015, Burstein described four subtypes, namely, LAR, MES, basal-like immune-suppressed (BLIS), and immune-activated (BLIA) subtypes [6]. One year later, the FUSCC classification introduced the immune-modulatory (IM) subtype, along with the known MES, BLIS and LAR subtypes [7].
All the above classifications are based on molecular profiling, which could be valuable at the patient level for precision medicine approaches once some mutations predict the benefit of targeted therapy. However, for most patients, the treatment options will remain limited. Moreover, technical challenges, such as the need for fresh tissue, the length of time needed to perform the analysis, and the significantly high costs, impact its wide use in standard practice [8,9].
Immunohistochemistry (IHC) is an established laboratory method for evaluating the presence of antigens that is widely used in breast cancer and is pivotal for tailoring systemic treatments (e.g., the human epidermal growth factor receptor 2—HER2) [10]. Moreover, IHC is significantly less expensive and laborious than gene expression and has been evaluated in several studies as a surrogate marker of established intrinsic genomic-based subtyping assays, as summarized in Table 1 [11,12,13,14,15,16,17,18]. Although some studies have provided survival data amongst the subtypes, the effect of chemotherapy on the pathological complete response, and if it serves as surrogate biomarker of survival, has not been reported.
Table 1.
Retrospective studies evaluating IHC as a surrogate for TNBC subtyping.
In this study, we report the survival and pCR rates of patients who underwent IHC subtyping using our panel and who received neoadjuvant chemotherapy.
2. Results
One hundred eighty-seven women were included in this analysis; the mean age was 52.43 (SD = 12.79) years, the mean tumor size was 47.64 (SD = 53.61) millimeters, and the patients’ characteristics are summarized in Table 2.
Table 2.
Clinical and pathological summary.
After balancing pros and cons from the antibodies used by studies presented in Table 1, we chose the following four for our analysis: IDO-1—Indoleamine 2,3-dioxygenase (IDO-1), Forkhead Box C1 (FOX-C1), claudin-3 [19], and androgen receptor. Staining for all 4 markers was possible in 98.4% (184s) of the patients and partially in 3 patients due to tissue exhaustion. We successfully identified the characteristics of 4 subtypes in 96.3% (183) of patients. Overall, the frequency of the IHC-basal-like (BL) subtype was 61% (114). The percentages of basal subtypes identified by IHC-BLIS and IHC-BLIA were 31% (57) and 10.9% (20), respectively. The second most common subtype was IHC-MES 12.5% (23), followed by IHC-LAR 12.0% (22) and IHC-mixed 11.4% (21) (Table 2).
Among the 28 (15%) patients who achieved pCR, 75% exhibited an IHC-BL, 14.28% exhibited an IHC-MES feature, and 7.4% exhibited an IHC-LAR feature. The pCR rate in the IHC-BLIA group was the highest (30%), and that in the IHC-LAR group was the lowest (4.5%) (p = 0.24) (Table 3).
Table 3.
Summary of the characteristics of patients who achieved a pathological complete response.
Patients who achieved pCR had a significantly better median disease-free (mDFS) survival NR (not reached) (CI—confidence interval: >50%) vs. no-pCR 30 m (months) (CI: 18-NR) (p = 0.00022). Overall, it was also significantly greater in patients who achieved pCR according to the NR (CI: >50%) than in those who did not achieve pCR according to the 58-m (CI: 40-NR) no-pCR (p = 0.00018). (Supplementary Figures S1 and S2).
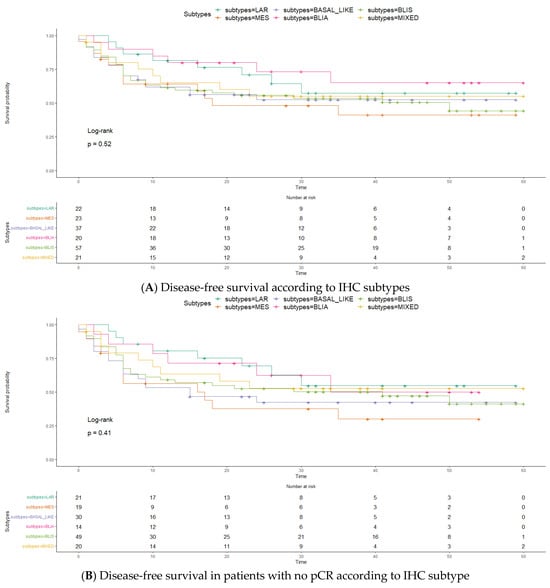
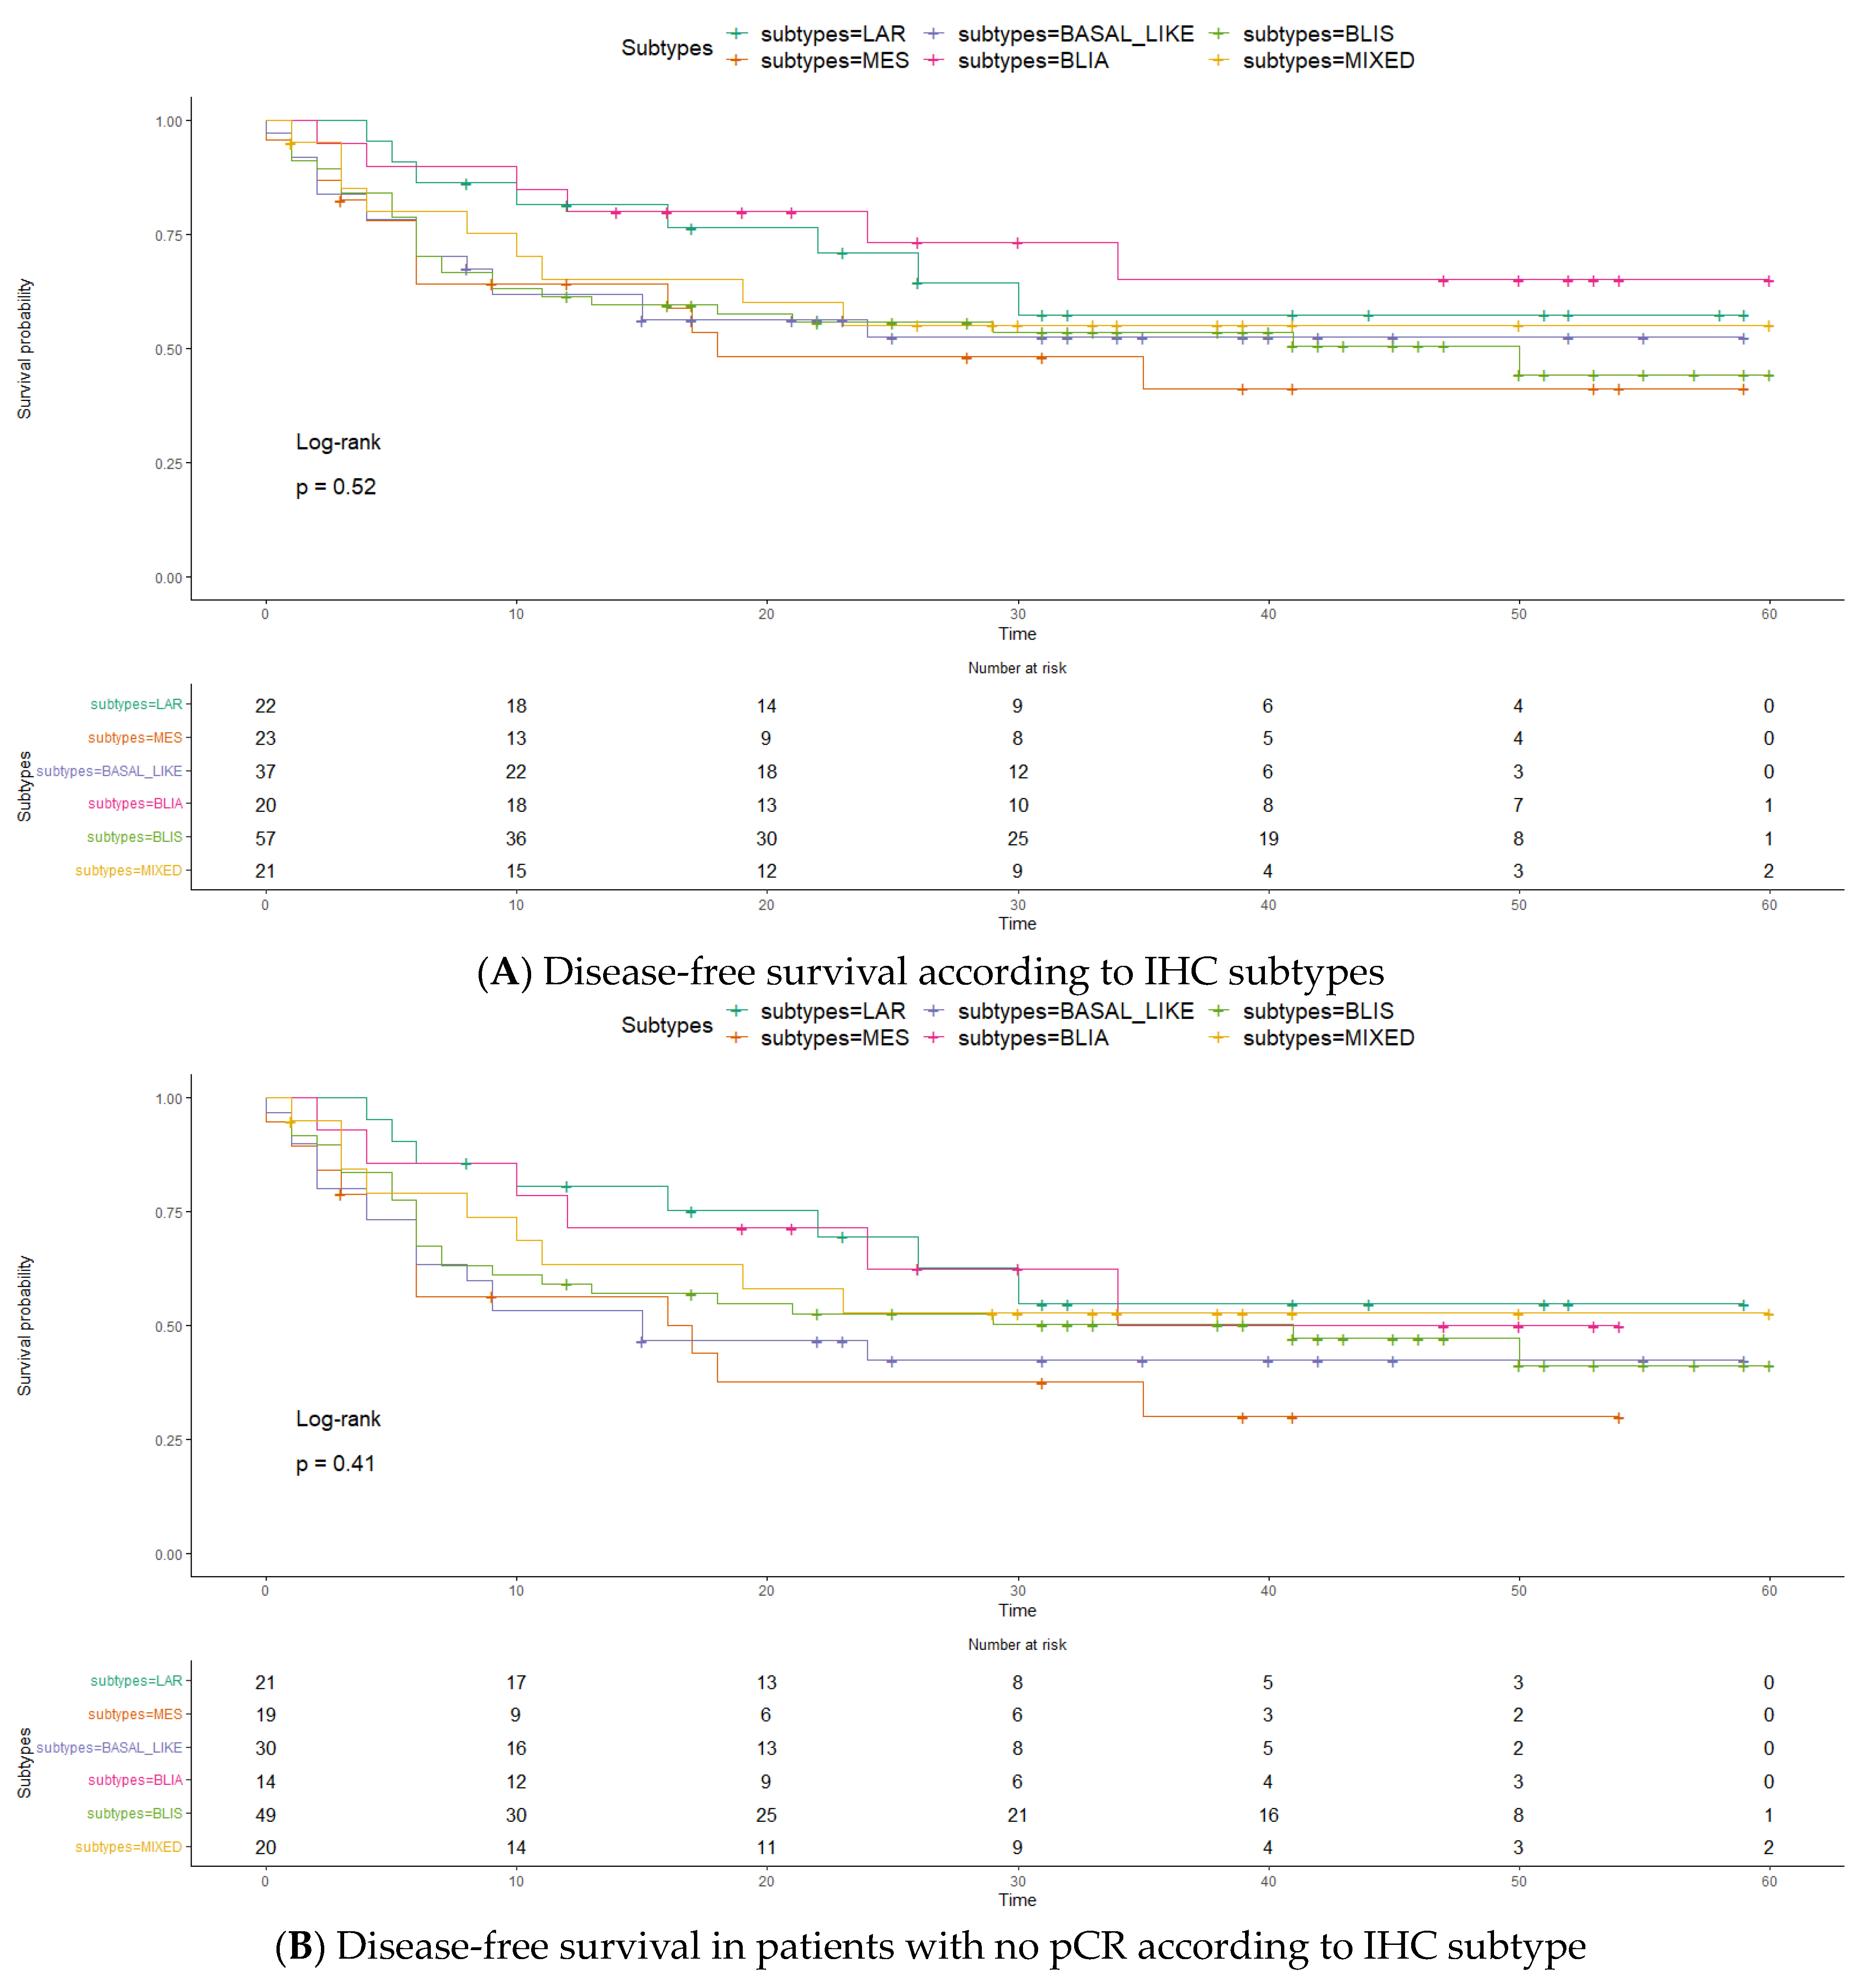
Most of the recurrences occurred in the first 20 months following surgery. mDFS did not significantly differ among subtypes (p = 0.52). (Figure 1A) IHC-BLIA demonstrated a greater mDFS for patients with NR (CI: 34-NR) than for patients with all other subtypes (CI: 23-NR). The mDFS was also NR for the IHC-LAR, IHC-mixed, and IHC-BL groups. IHC-BLIS patients had the second worst mDFS, 50 m (CI: 11-NR), and IHC-MES patients had a markedly short mDFS, 16 m (CI: 6-NR). Interestingly, the mDFS curves for patients who did not achieve pCR were less distinct among subtypes, suggesting that pCR has a crucial role regardless of intrinsic subtype. IHC-MES followed by IHC-BL showed worse survival: respectively, 17 m (CI: 6-NR) and 15 m (CI: 6-NR) (p = 0.41) (Figure 1B).
Figure 1.
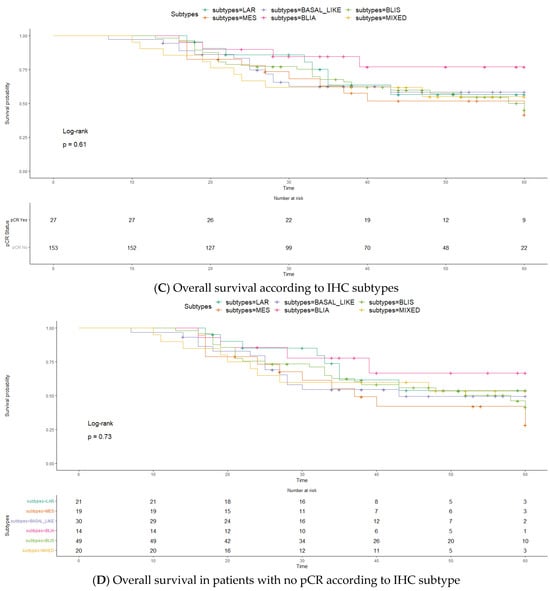
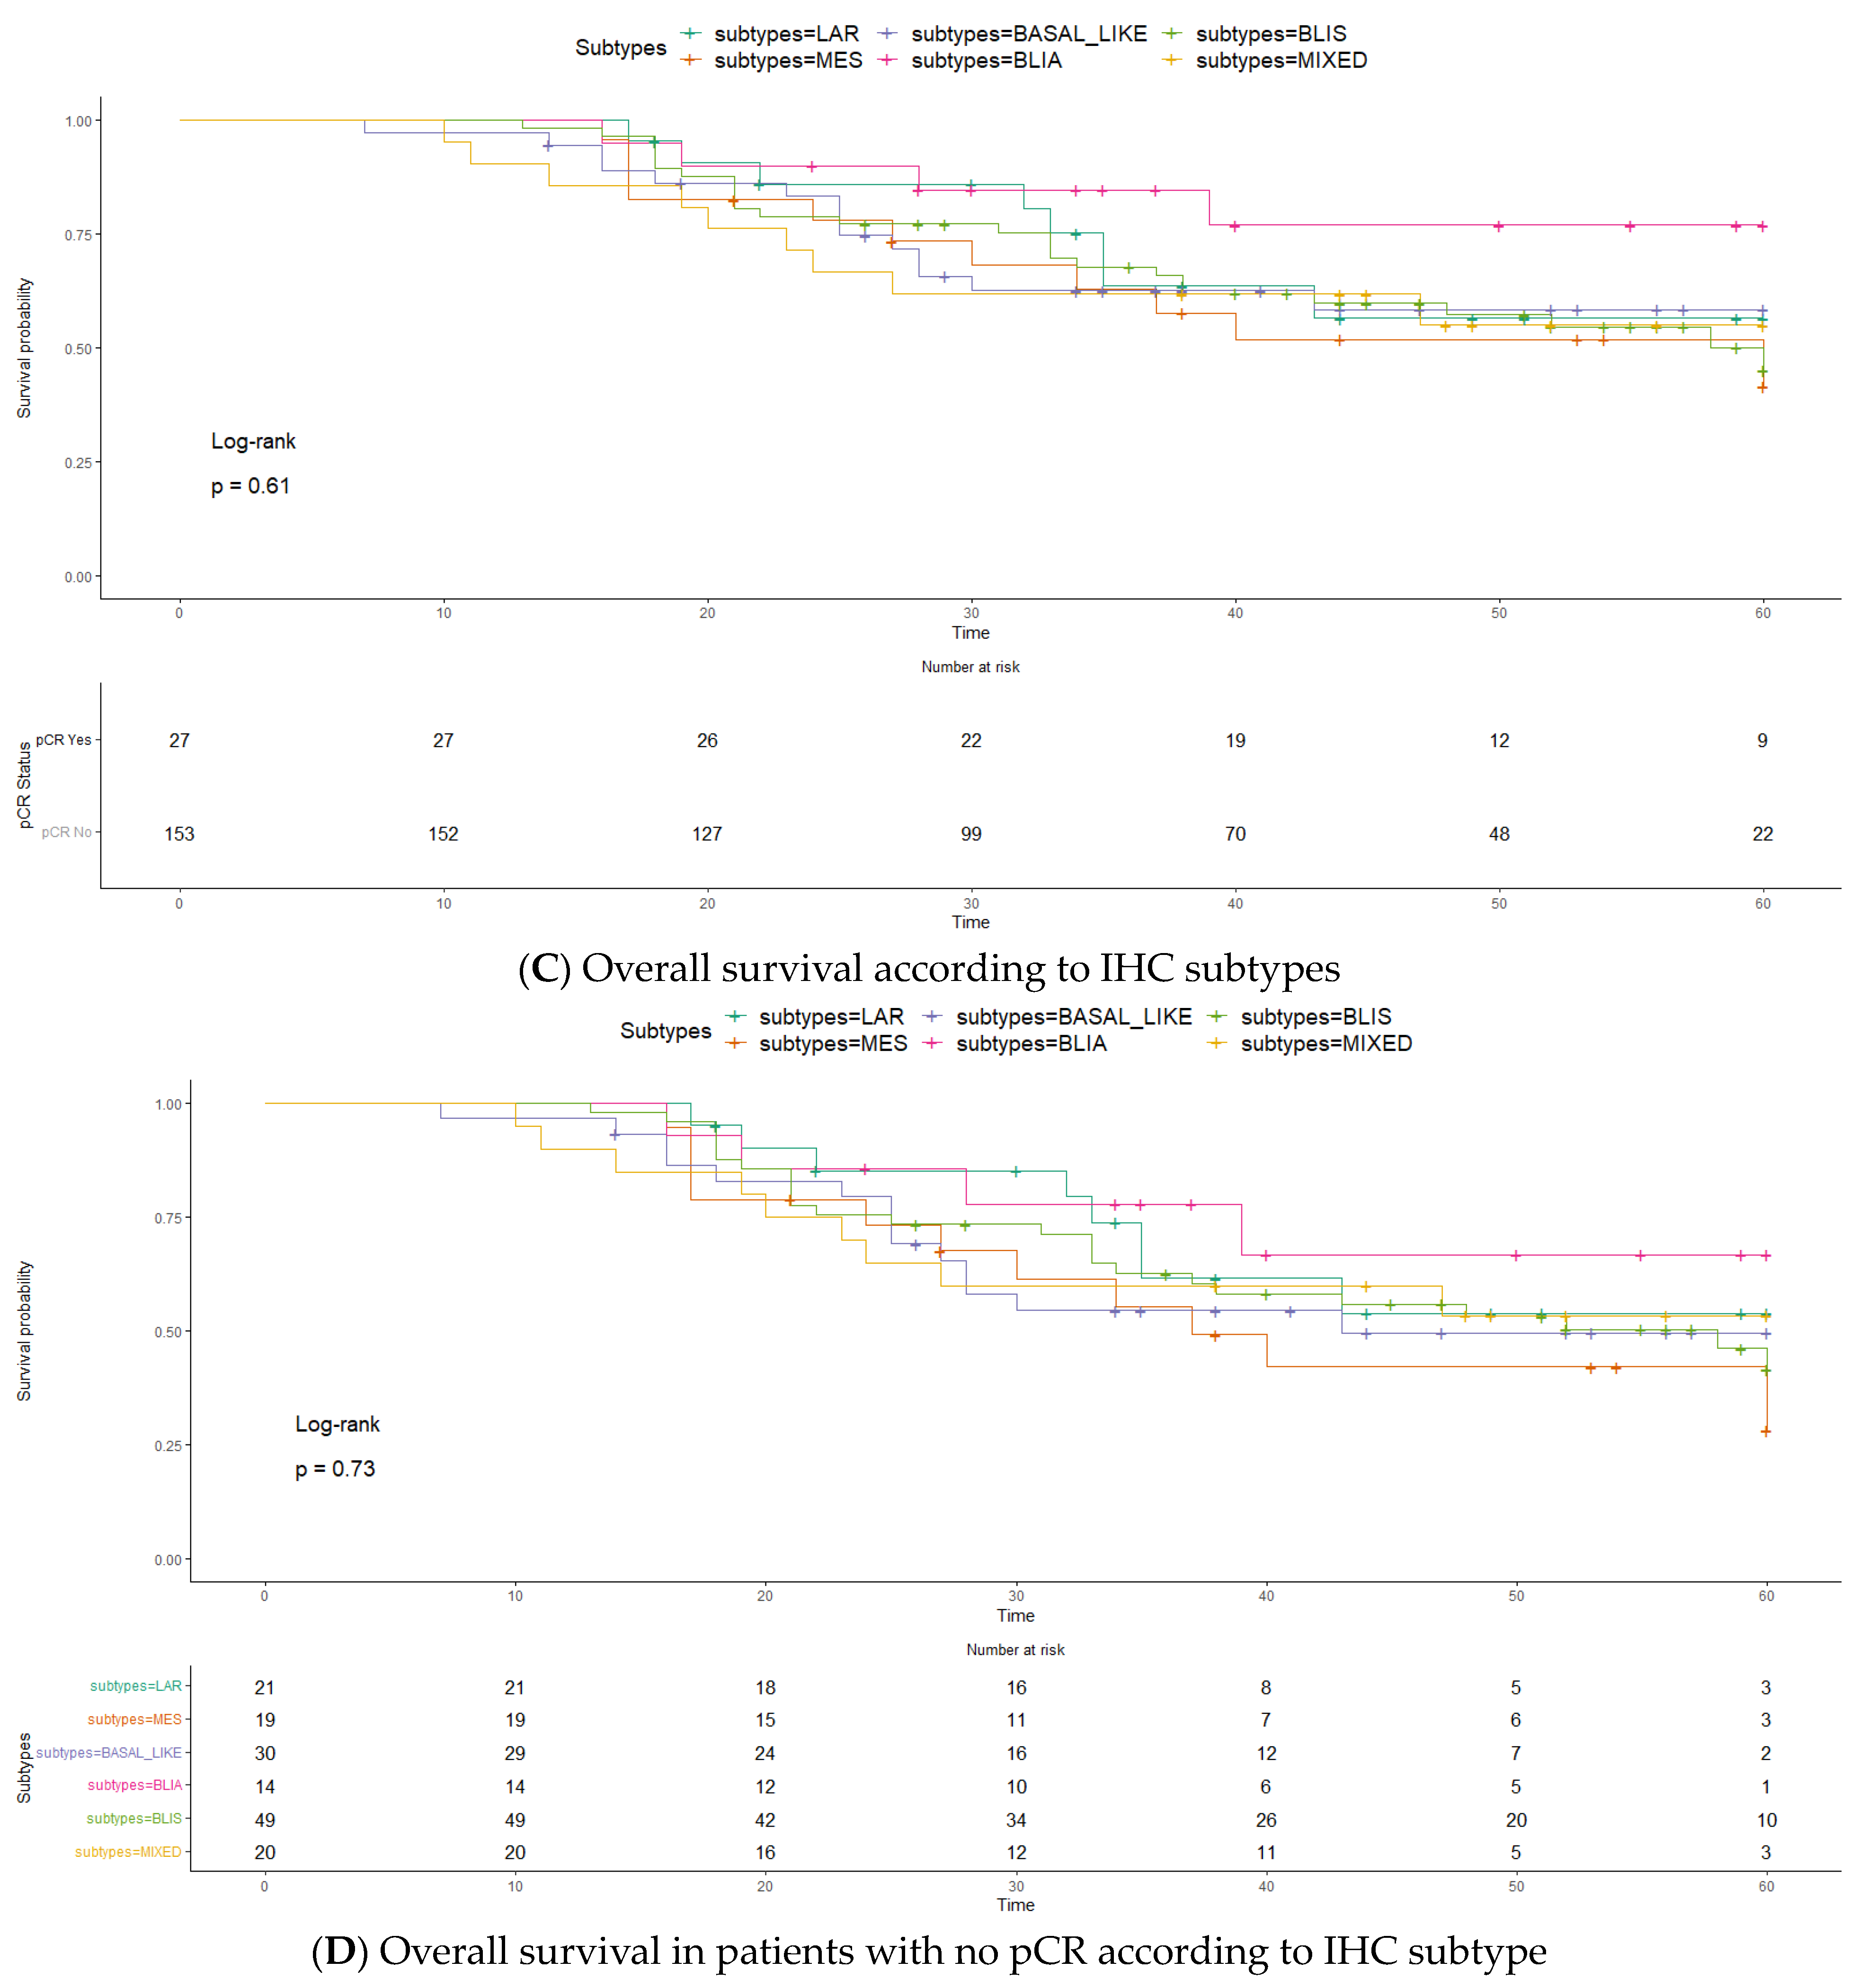
Legend: BLIS basal-like immunosuppressed; BLIA—basal-like immunoactivated; LAR—luminal androgen receptor; MES—mesenchymal. The time, expressed in months.
Overall survival analysis also revealed no significant differences among subtypes (p = 0.61) (Figure 1C). IHC-BLIA had a greater mOS, NR (95% CI: NR > 50%) than the other subtypes at 60 m (95% CI: 48-NR) (p = 0.081). IHC-BLIA exhibit the graphically highest mOS, with an NR (95% CI: 39-NR) mOS for patients who did not achieve pCR and IHC-MES was associated with a worse survival with 37 m (95% CI: 27-NR) (p = 0.73) (Figure 1D).
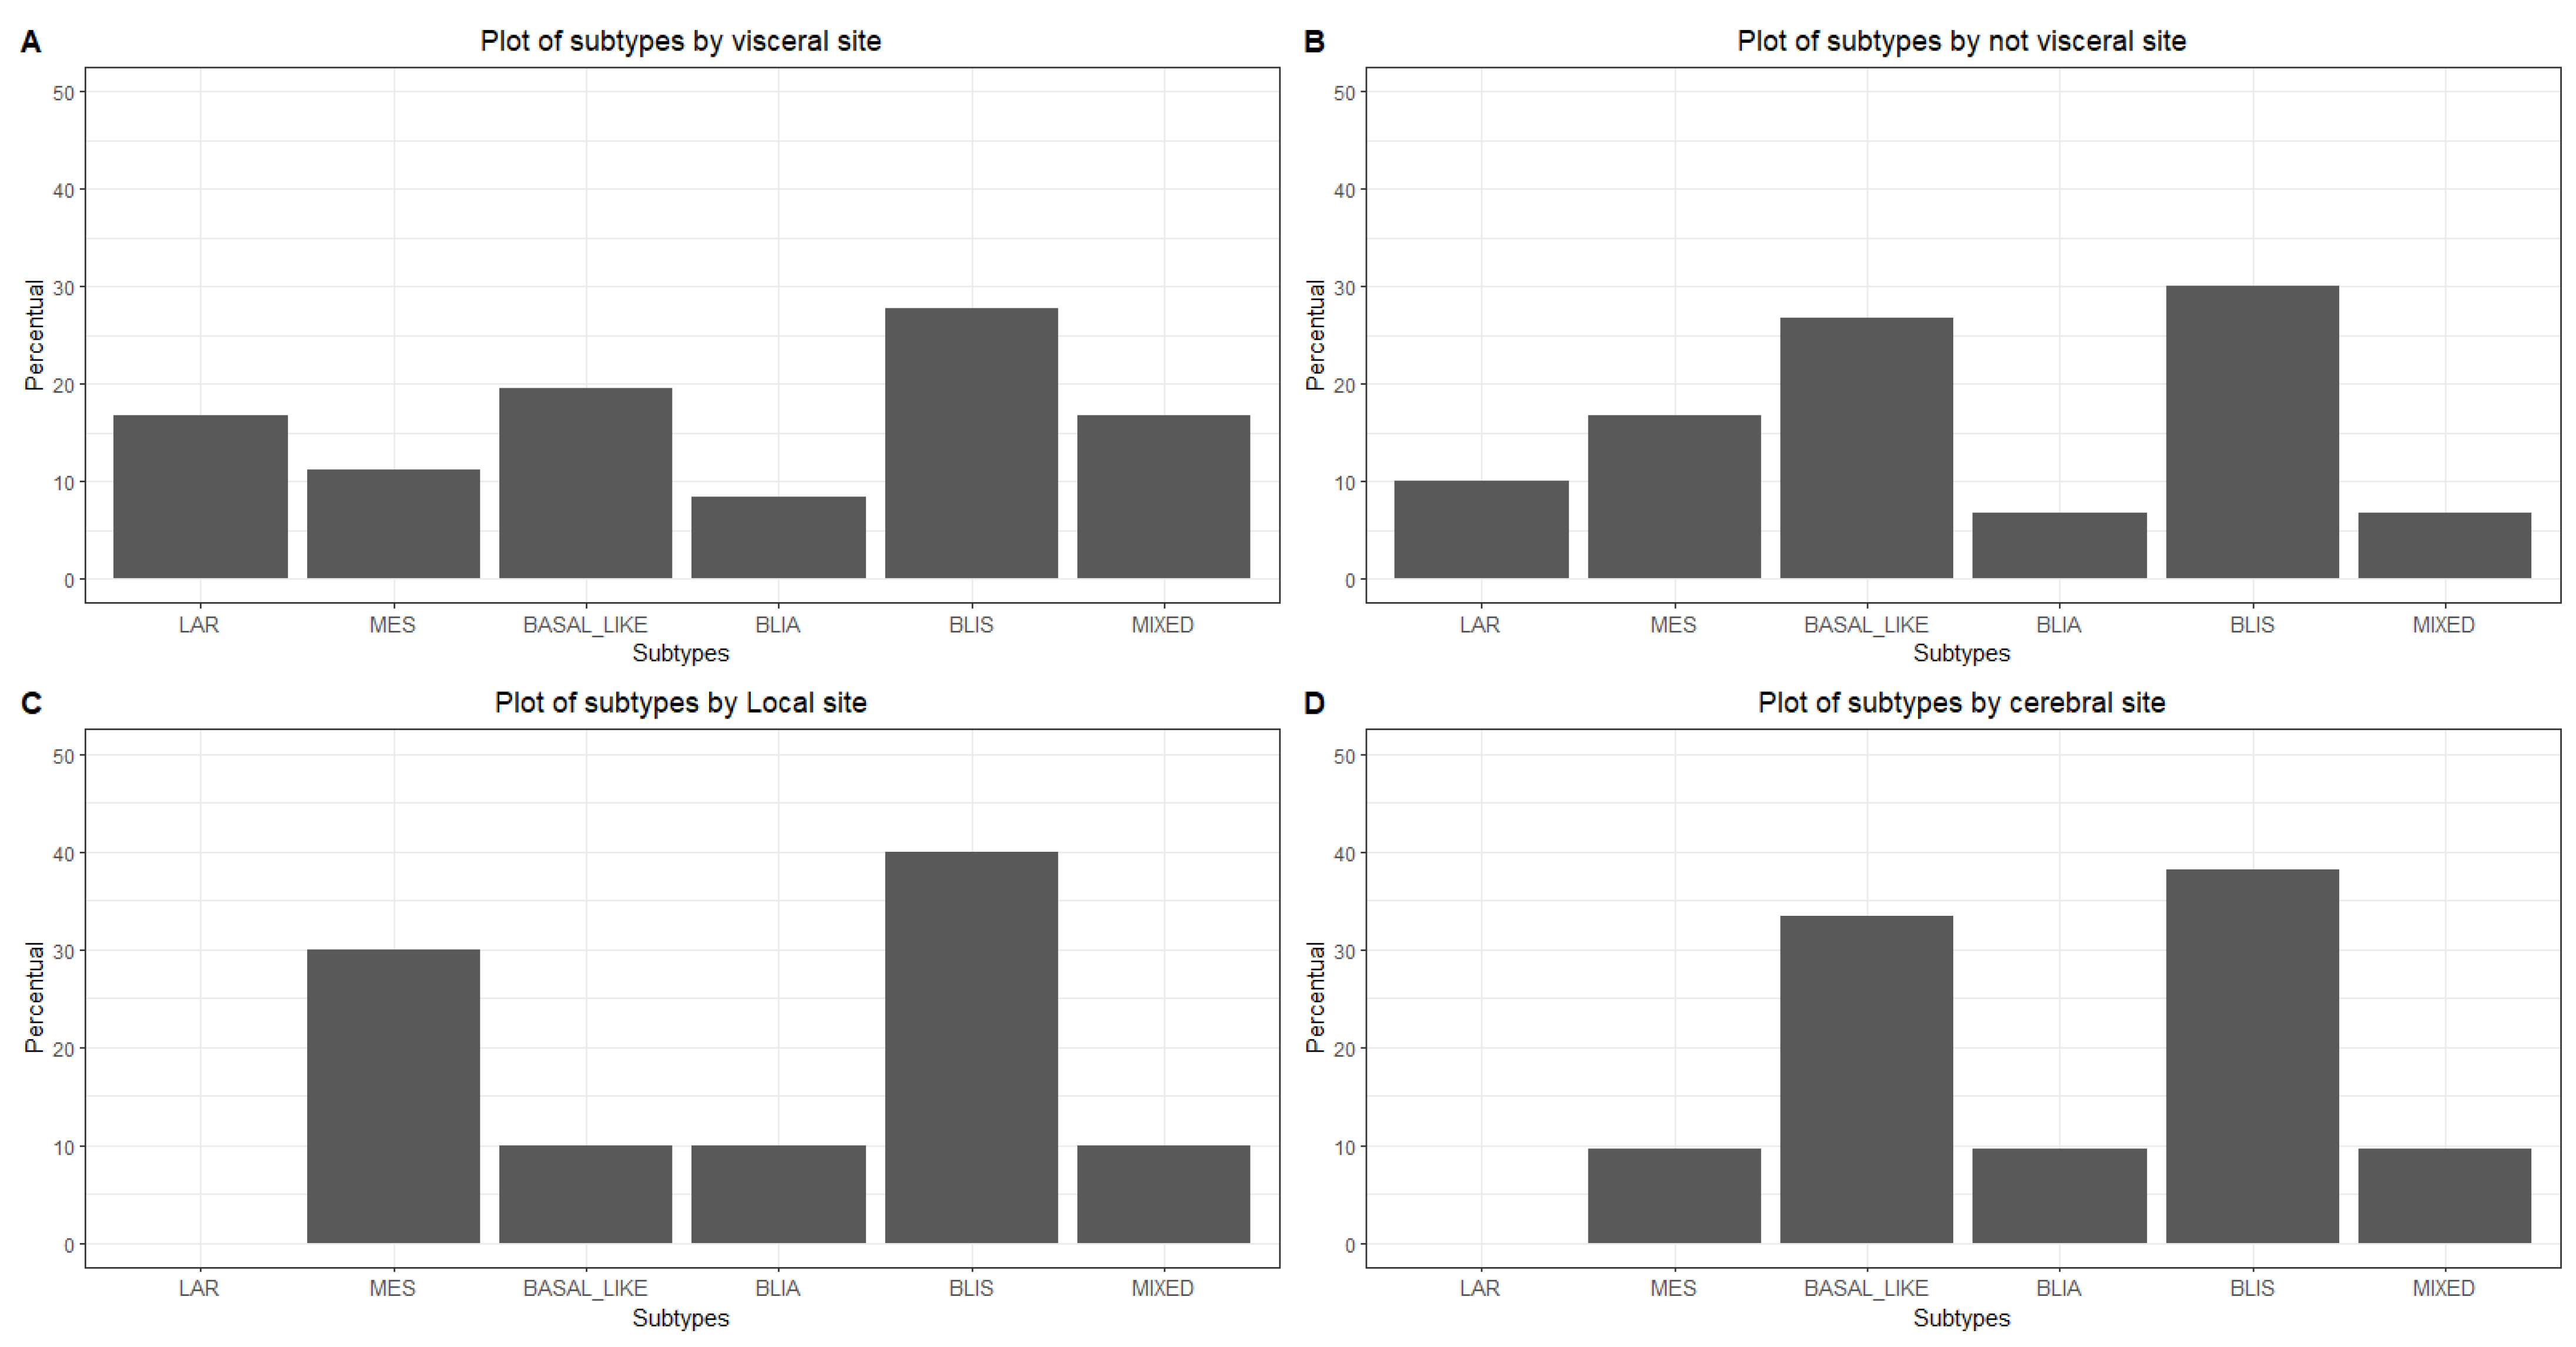
The pattern of recurrence was graphically distinct among subtypes, although not statistically significant. IHC-BLIS led recurrence in each category, and interestingly, no local or cerebral relapse occurred in patients with the IHC-LAR subtype (Figure 2).
Figure 2.
Pattern of recurrence among IHC subtypes. Legend: (A) Visceral recurrence; (B) Non-visceral/non-local/non-cerebral recurrence; (C) Local recurrence; (D) Cerebral recurrence. BLIS—basal-like immunosuppressed; BLIA—basal-like immunoactivated; LAR—luminal androgen receptor; MES—mesenchymal.
3. Discussion
This study is groundbreaking in terms of demonstrating pCR rates among TBNC subtypes using IHC. We found numerically higher pCR rates in the IHC-BLIA (30%) subgroup and a trend toward longer DFS and OS, while in the IHC-MES subgroup, survival was worse despite the pCR rate (17.4%) being closer to that of the whole population analyzed (15.0%). Achieving pCR was associated with longer disease-free and overall survival.
The basal-like subtype was predominant in our sample, with 61.5% of the tumors harboring a basal component. In 2010, Oakman, C. et al. reported higher rates of the BL phenotype in TNBC patients (71–91%) [20]. Interestingly, Lehmann et al. in 2011 reported that 49% of BL cases were characterized by intrinsic subtyping, but IHC seems to indicate a higher percentage (88%), and very likely, only half of these cases would correlate with the intrinsic BL subtype [5]. We observed rates somewhat closer to those reported by Zhao et al. and Jing Liang et al. [14,16] Identifying basal-like TNBC is clinically relevant, as data showed a benefit from adjuvant chemotherapy for patients with non-basal-like tumors and residual disease following surgery, despite the use of neoadjuvant chemotherapy [21,22].
We identified a predominance of IHC-BLIS (31.0%) over IHC-BLIA (10.9%) in our population, which likely contributed to the overall modest pathological response rate of 15.0%. Although our IHC-BLIS rates are somewhat comparable to the values found by the authors performing IHC subtyping, the overall percentage of patients with the IHC-BLIA subtype is markedly lower (Table 1). On the other hand, we found a numerically higher pCR rate in IHC-BLIA (30.0%) than the pCR rate in IHC-BLIS (14.0%), although not statistically significant. Based on recent publications, the new standard of care for early and high-risk TNBC patients includes immunotherapy alongside a taxane-platinum-based dose-dense chemotherapy, regardless of the presence of immune receptors/markers [23]. However, data are still needed to understand the efficacy of these regimens in TNBC patient subpopulations.
Immuno-inflammation occurred solely at the IHC-IM subtype according to Jing Lian et al. (2022), but a significant proportion of the other subtypes are immune-excluded, which raises the question of whether those subjects would benefit from immunotherapy in clinic [16].
IHC-MES was the second most common subtype, and numerically, it was associated with worse mDFS and mOS, which is consistent with the findings in the literature [13,14,15]. Unfortunately, the benefit of conventional adjuvant systemic treatment for this subtype is often poor, if any, given its specific molecular characteristics, which has motivated researchers to consider regimens mimicking sarcomatous disease [24]. Moreover, given the preclinical and clinical activity of mTOR, PI3K, SRC/ABL, and angiogenesis inhibitors, we believe that tailored treatment for this subtype could be warranted [2].
The IHC-LAR subtype had the lowest pCR rate (4.5%) and was the third most common subtype in our sample. A long-standing effort has been made to offer anti-androgen targeting for this subtype, with no translation in registrational approvals. The main challenges might include the unreliable behavior of AR as a driver in TNBC, compared to that of ER in HR+ disease, as well as the cutoff of AR intensity to trigger intervention and the high-bar endpoints chosen in clinical trials to evaluate the AR-targeting effect [25]. As mentioned above, the current best adjuvant treatment for patients with residual disease is capecitabine; however, for specific subtypes, such as LAR, the benefit is unclear. Therefore, to answer this question and by leveraging our knowledge of prostate cancer, where androgen deprivation therapy plus androgen receptor pathway inhibitors can be combined with docetaxel, we believe that a cohort of patients with IHC-LAR in a potential umbrella trial for intrinsic subtypes of TNBC should be considered to receive adjuvant capecitabine plus ARPI [26].
The pattern of recurrence we observed in our IHC-based subtyping cohort aligned with that expected in the literature (Table 1). Notably, brain relapse, a known independent factor of poor prognosis, occurred in 8% of the patients with IHC-MES, 14% in IHC-BLIS, and approximately 10% of those with the other IHC subtypes, but interestingly, no patients with IHC-LAR experienced brain relapse. There is a longstanding discussion on how to optimize relapse monitoring in high-risk breast tumors, but no clear consensus has been reached. Our data could assist in identifying patients with a greater risk of recurrence, which could deserve more individualized monitoring given specific patterns of disease relapse and therefore might benefit from brain and visceral imaging, as well as promising emerging techniques, such as circulating tumor DNA, in addition to the current recommended approaches [27].
Our study demonstrated a low percentage of unclassifiable (2.2%) and IHC-mixed (11.4%) compared to the other studies mentioned in Table 1. In a study conducted by Yoo in 2022, the majority of patients with IHC-unclassifiable had presented with mesenchymal subtype on genomic classification [15]. Interestingly, Zhao et al., Leeha et al., and Hu et al. did not report mixed subtypes by using their IHC panels [14,17,18]. We believe IHC-unclassifiable and IHC-mixed should be expected given the IHC assay limitations, and support the heterogeneous features of a significant proportion of TNBCs [28]. Although this population is smaller, we are conducting further research to elucidate how they should be handled, and, more specifically, the role of additional testing to better define this population.
Although the results of this study are promising, they should be interpreted in light of these limitations. Our retrospective design imposes challenges in survival analysis including selection and recall bias. The eventual changes in TNBC treatment protocols over the study period could introduce a confounding variable to the outcomes evaluated, as well as other variables not analyzed, such as comorbidities and genomic background. In the case of implementation, our proposed IHC panel will eventually increase in cost compared to the current standard of practice recommendation and could eventually cause delays in standard of practice results delivery. Moreover, there are several technical hurdles linked to standardizing IHC protocols for diagnostic protocols, including their validation and approval by regulatory bodies, which would be required before the panel we proposed is considered outside of a research environment. There is no consensus about the use of an IHC subtyping panel, and IHC staining was performed utilizing archival tumor tissue from 2008 onward, which could have impacted the performance of the assay and requires validation using an established method for intrinsic genomic subtyping.
4. Materials and Methods
4.1. Sample Selection and Outcome Definitions
Patients with localized or locally advanced TNBC who were treated with neoadjuvant chemotherapy followed by curative surgery at the same institution between January 2008 and December 2017 and who had available biopsy and surgical specimens met the inclusion criteria for this retrospective cohort.
From medical files, clinical and pathological data were collected to construct a database using an electronic case report form (Supplementary file S1.).
For this study, TNBC was defined as estrogen and progesterone receptor < 1% and HER2-negative +1 or +2 without fish amplification. Pathological complete response (pCR) was defined as the absence of invasive cancer on surgical specimens from the breast and axilla (ypT0/Tis pN0). Disease-free survival (DFS) was defined as the time between the day of the cycle of one day of chemotherapy regimen administration until cancer recurrence or cancer-related death. Overall survival (OS) was defined as the time between the day of the cycle one day after chemotherapy regimen administration until death related to any cause. In the case of loss of follow-up, the appointment date at the NCI, which contains information about disease and survival, was used to censor the patient for the analysis.
4.2. IHC Analysis and Interpretation
Tissue samples were converted into histological sections on previously salinized slides. Evaluation of the cellular atypia pattern was performed by hematoxylin-eosin (HE) staining. The evaluated tumor area was selected by a pathologist, and the in situ regions within the invasive tumors were also delineated to allow a better evaluation of the stains. Tissue sections were immunoassayed with a Polymer Detection System (RE7150-K, Leica Biosystems Newcastle Ltd., Balliol Business Park West, Benton Lane, Newcastle Upon Tyne NE12 8EW, UK) according to the protocol established by the manufacturer. Primary antibodies were incubated with the tissues for 18 h at 4 °C at different dilutions determined by titration, as shown in Table 4.
Table 4.
Antibodies used in the analysis.
The antibody panel was adapted from studies reported in Table 1 and interpretation of the singleplex IHC staining results was performed by the author F.R., as shown in Table 5.
Table 5.
Immunohistochemistry analysis and interpretation.
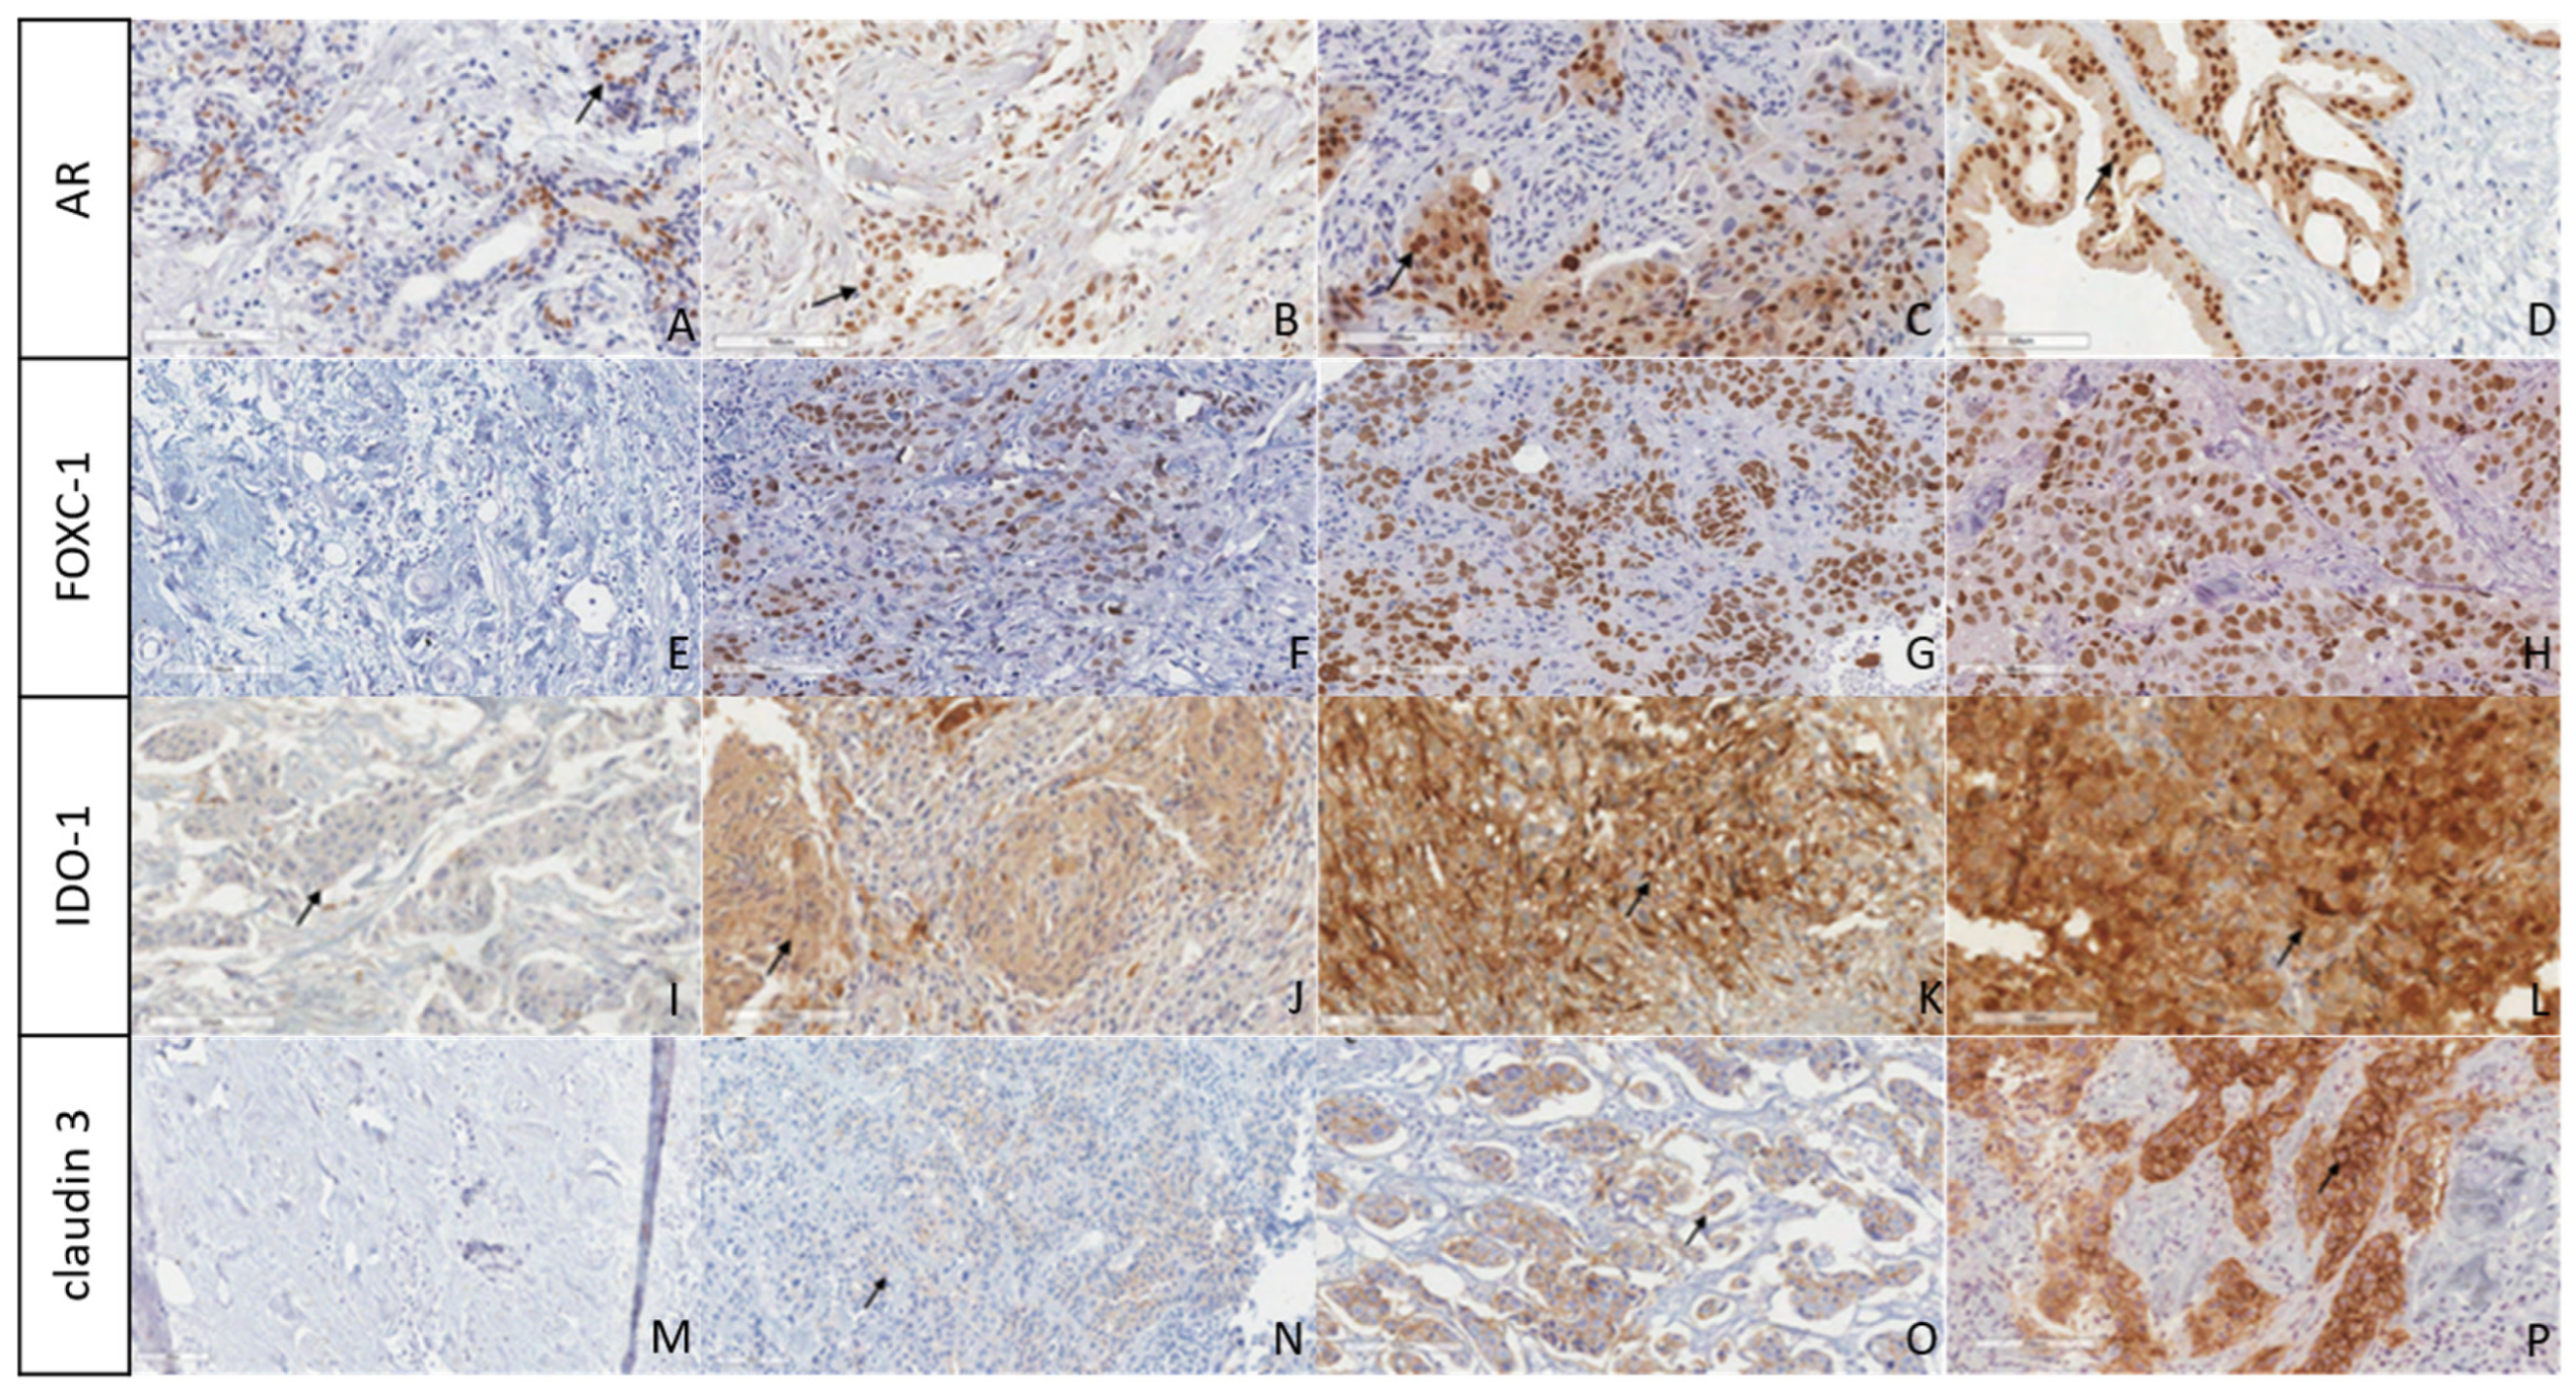
The scoring was reviewed by the senior authors E.A., and the final scores agreed between F.R. and E.A. The digitalization was performed using the Aperio Scanner and a representative illustration of the staining is shown in Figure 3.
Figure 3.
Immunostaining panel of tumor samples. Legend: Anti-AR immunostaining nuclear expression was observed in 10–30% (A), 31–50% (B), 51–75% (C), and 76–100% (D). Anti-FOXC1 immunostains were stratified according to nuclear staining intensity: negative (E), 4+ (F), 6+ (G), and 8+ (H). Anti-IDO1 immunostains were stratified according to the intensity of cytoplasmic staining in the tumor region as: ≤10% (I), 50% (J), 80% (K), and 100% (L). Anti-claudin immunostains were stratified according to the intensity of membrane staining in the tumor region as negative (M), weak (N), moderate (O), and intense (P). Magnification: 20×. Scale bar: 100 µm.
For positive controls, tissues suggested by the antibody manufacturer’s datasheets were used. The reaction was visualized using diaminobenzidine (DAB), followed by hematoxylin counterstaining. Negative controls were prepared without the primary antibody. The positivity of the staining was analyzed in ten random fields and determined by manual counting using ImageJ version 1.54 [29] software according to the preestablished equation below.
Sc represents the number of stained cells in each field, where s = [1, 2, ∙∙∙, 10]; Tc represents the total number of cells in each field, where t = [1, 2, ∙∙∙, 10]; and p represents the mean percentage of positivity.
4.3. Statistical Analysis
Continuous variables are shown as the mean and standard deviation, and categorical variables are shown as the total value and percentage of the total value.
The time to overall survival was computed as the time of diagnosis until death or the last patient contact, and the disease-free survival time was computed as the time of surgery until recurrence or last patient contact.
The Kaplan–Meier method was sed to estimate survival curves, and the log rank test was performed to evaluate whether there were differences in covariate levels via univariate analysis. The significance level adopted to reject the null hypothesis was alpha equal to 0.05. A bar plot was used to demonstrate the frequency of subtypes at each site.
5. Conclusions
We successfully demonstrated that an affordable and widely reproducible panel of IHC assays can be used to subtype TNBC. Moreover, we were the first to demonstrate the pCR rate among IHC subtypes.
Supplementary Materials
The supporting information can be downloaded at https://www.mdpi.com/article/10.3390/ijms25115825/s1.
Author Contributions
Conceptualization, B.d.P., S.C. and E.A.; methodology, B.d.P., S.C., P.V., F.R., C.A.M.d.S. and E.A.; software, B.d.P., C.A.M.d.S. and E.A.; validation, P.V. and E.A.; formal analysis, B.d.P., S.C., C.A.M.d.S. and E.A.; investigation, B.d.P., S.C., P.V., F.R., C.A.M.d.S. and E.A.; resources, B.d.P., S.C., P.V., F.R., C.A.M.d.S. and E.A.; data curation, B.d.P., S.C., C.A.M.d.S. and E.A.; writing—original draft preparation, B.d.P., S.C., C.A.M.d.S. and E.A.; writing—review and editing, B.d.P., S.C., P.V., F.R., C.A.M.d.S. and E.A.; visualization, B.d.P., S.C., C.A.M.d.S. and E.A.; supervision, S.C. and E.A.; project administration, B.d.P., S.C., C.A.M.d.S. and E.A.; funding acquisition, E.A. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by the Conselho Nacional de Desenvolvimento Cientifico e Tecnologico (CNPq) grant no. 210.462/2021.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki and approved by the Institutional Review Board (or Ethics Committee) of the National Cancer Institute (NCI) in Rio de Janeiro Brazil Ethics Committee, under the number CAAE: 22893219.1.0000.5274.
Informed Consent Statement
Patient consent was waived due to the retrospective nature of this research and lack of impact on the clinical decision, which was already taken before the study.
Data Availability Statement
Authors are open to discuss data sharing on the terms of the National Cancer Institute.
Acknowledgments
We acknowledge the support of patients treated at NCI Brazil, which contributed to this research, as well as the site personnel’s dedication to research.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Cancer Research UK. Triple Negative Breast Cancer; Cancer Research UK: London, UK, 2023; Available online: https://www.cancerresearchuk.org/about-cancer/breast-cancer/types/triple-negative-breast-cancer (accessed on 1 March 2023).
- de Paula, B.; Kieran, R.; Koh, S.S.; Crocamo, S.; Abdelhay, E.; Muñoz-Espín, D. Targeting Senescence as a Therapeutic Opportunity for Triple-Negative Breast Cancer. Mol. Cancer Ther. 2023, 22, 583–598. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rala de Paula, B.H.; Kumar, S.; Morosini, F.M.; Cardoso, D.E.C.; de Sousa, C.A.; Crocamo, S. Real-world assessment of the effect of impact of tumor size on pathological complete response rates in triple negative breast cancer after neoadjuvant chemotherapy. Chin. Clin. Oncol. 2020, 9, 78. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marra, A.; Trapani, D.; Viale, G.; Criscitiello, C.; Curigliano, G. Practical classification of triple-negative breast cancer: Intratumoral heterogeneity, mechanisms of drug resistance, and novel therapies. NPJ Breast Cancer 2020, 6, 54. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lehmann, B.D.; Bauer, J.A.; Chen, X.; Sanders, M.E.; Chakravarthy, A.B.; Shyr, Y.; Pietenpol, J.A. Identification of human triple-negative breast cancer subtypes and preclinical models for selection of targeted therapies. J. Clin. Investig. 2011, 121, 2750–2767. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Burstein, M.D.; Tsimelzon, A.; Poage, G.M.; Covington, K.R.; Contreras, A.; Fuqua, S.A.; Savage, M.I.; Osborne, C.K.; Hilsenbeck, S.G.; Chang, J.C.; et al. Comprehensive Genomic Analysis Identifies Novel Subtypes and Targets of Triple-Negative Breast Cancer. Clin. Cancer Res. 2015, 21, 1688–1698. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, Y.-R.; Jiang, Y.-Z.; Xu, X.-E.; Yu, K.-D.; Jin, X.; Hu, X.; Zuo, W.-J.; Hao, S.; Wu, J.; Liu, G.-Y.; et al. Comprehensive transcriptome analysis identifies novel molecular subtypes and subtype-specific RNAs of triple-negative breast cancer. Breast Cancer Res. 2016, 18, 33. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bianchini, G.; De Angelis, C.; Licata, L.; Gianni, L. Treatment landscape of triple-negative breast cancer—Expanded options, evolving needs. Nat. Rev. Clin. Oncol. 2022, 19, 91–113. [Google Scholar] [CrossRef] [Scilit]
- Yang, R.; Li, Y.; Wang, H.; Qin, T.; Yin, X.; Ma, X. Therapeutic progress and challenges for triple negative breast cancer: Targeted therapy and immunotherapy. Mol. Biomed. 2022, 3, 8. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rossi, C.; Fraticelli, S.; Fanizza, M.; Ferrari, A.; Ferraris, E.; Messina, A.; Della Valle, A.; Anghelone, C.A.P.; Lasagna, A.; Rizzo, G.; et al. Concordance of immunohistochemistry for predictive and prognostic factors in breast cancer between biopsy and surgical excision: A single-centre experience and review of the literature. Breast Cancer Res. Treat. 2023, 198, 573–582. [Google Scholar] [CrossRef] [Scilit]
- Choi, J.; Jung, W.-H.; Koo, J.S. Clinicopathologic features of molecular subtypes of triple negative breast cancer based on immunohistochemical markers. Histol. Histopathol. 2012, 27, 1481–1493. [Google Scholar]
- Kim, S.; Moon, B.-I.; Lim, W.; Park, S.; Cho, M.S.; Sung, S.H. Feasibility of Classification of Triple Negative Breast Cancer by Immunohistochemical Surrogate Markers. Clin. Breast Cancer 2018, 18, e1123–e1132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumar, S.M.; Bal, A.M.; Das, A.M.; Bhattacharyya, S.; Laroiya, I.; Khare, S.; Singh, G. Molecular Subtyping of Triple Negative Breast Cancer by Surrogate Immunohistochemistry Markers. Appl. Immunohistochem. Mol. Morphol. 2020, 29, 251–257. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, S.; Ma, D.; Xiao, Y.; Li, X.-M.; Ma, J.-L.; Zhang, H.; Xu, X.-L.; Lv, H.; Jiang, W.-H.; Yang, W.-T.; et al. Molecular Subtyping of Triple-Negative Breast Cancers by Immunohistochemistry: Molecular Basis and Clinical Relevance. Oncologist 2020, 25, e1481–e1491. [Google Scholar] [CrossRef] [Scilit]
- Yoo, T.-K.; Kang, J.; Lee, A.; Chae, B.J. A triple-negative breast cancer surrogate subtype classification that correlates with gene expression subtypes. Breast Cancer Res. Treat. 2022, 191, 599–610. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lian, J.; Ma, H.-X.; Xu, E.-W.; Bu, P.; Yun, K.-M.; Xi, Y.-F. Subclassifying triple-negative breast cancers and its potential clinical utility. Virchows Arch. 2022, 481, 13–21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leeha, M.; Kanokwiroon, K.; Laohawiriyakamol, S.; Thongsuksai, P. Immunohistochemistry-based molecular subtyping of triple-negative breast cancer and its prognostic significance. Pathol. Oncol. Res. 2023, 29, 1611162. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hu, H.; Tong, K.; Tsang, J.; Ko, C.; Tam, F.; Loong, T.; Tse, G. Subtyping of triple-negative breast cancers: Its prognostication and implications in diagnosis of breast origin. ESMO Open 2024, 9, 102993. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jääskeläinen, A.; Soini, Y.; Jukkola-Vuorinen, A.; Auvinen, P.; Haapasaari, K.-M.; Karihtala, P. High-level cytoplasmic claudin 3 expression is an independent predictor of poor survival in triple-negative breast cancer. BMC Cancer 2018, 18, 223. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oakman, C.; Viale, G.; Di Leo, A. Management of triple negative breast cancer. Breast 2010, 19, 312–321. [Google Scholar] [CrossRef] [Scilit]
- Lluch, A.; Barrios, C.H.; Torrecillas, L.; Ruiz-Borrego, M.; Bines, J.; Segalla, J.; Guerrero-Zotano, Á.; García-Sáenz, J.A.; Torres, R.; de la Haba, J.; et al. Phase III Trial of Adjuvant Capecitabine After Standard Neo-/Adjuvant Chemotherapy in Patients with Early Triple-Negative Breast Cancer (GEICAM/2003-11\_CIBOMA/2004-01). J. Clin. Oncol. 2020, 38, 203–213. [Google Scholar] [CrossRef] [Scilit]
- Mayer, I.A.; Zhao, F.; Arteaga, C.L.; Symmans, W.F.; Park, B.H.; Burnette, B.L.; Tevaarwerk, A.J.; Garcia, S.F.; Smith, K.L.; Makower, D.F.; et al. Randomized Phase III Postoperative Trial of Platinum-Based Chemotherapy Versus Capecitabine in Patients with Residual Triple-Negative Breast Cancer Following Neoadjuvant Chemotherapy: ECOG-ACRIN EA1131. J. Clin. Oncol. 2021, 39, 2539–2551. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Han, H.S.; Vikas, P.; Costa, R.L.; Jahan, N.; Taye, A.; Stringer-Reasor, E.M. Early-Stage Triple-Negative Breast Cancer Journey: Beginning, End, and Everything in Between. Am. Soc. Clin. Oncol. Educ. B 2023, 43, e390464. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yin, L.; Duan, J.-J.; Bian, X.-W.; Yu, S. Triple-negative breast cancer molecular subtyping and treatment progress. Breast Cancer Res. 2020, 22, 61. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, M.; Yuan, Y.; Yan, P.; Jiang, J.; Ma, P.; Niu, X.; Ma, S.; Cai, H.; Yang, K. Prognostic Significance of Androgen Receptor Expression in Triple Negative Breast Cancer: A Systematic Review and Meta-Analysis. Clin. Breast Cancer 2020, 20, e385–e396. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fizazi, K.; Foulon, S.; Carles, J.; Roubaud, G.; McDermott, R.; Fléchon, A.; Tombal, B.; Supiot, S.; Berthold, D.; Ronchin, P.; et al. Abiraterone plus prednisone added to androgen deprivation therapy and docetaxel in de novo metastatic castration-sensitive prostate cancer (PEACE-1): A multicentre, open-label, randomised, phase 3 study with a 2 × 2 factorial design. Lancet 2022, 399, 1695–1707. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aldrich, J.; Canning, M.; Bhave, M. Monitoring of Triple Negative Breast Cancer After Neoadjuvant Chemotherapy. Clin. Breast Cancer 2023, 23, 832–834. [Google Scholar] [CrossRef] [Scilit]
- Asleh, K.; Riaz, N.; Nielsen, T.O. Heterogeneity of triple negative breast cancer: Current advances in subtyping and treatment implications. J. Exp. Clin. Cancer Res. 2022, 41, 265. [Google Scholar] [CrossRef] [Scilit]
- Schneider, C.A.; Rasband, W.S.; Eliceiri, K.W. NIH Image to ImageJ: 25 years of image analysis. Nat. Methods 2012, 9, 671–675. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).