


Abstract
Background: Recent advancements in heart failure (HF) therapy have significantly enhanced the management of patients across all phenotypes of left ventricular ejection fraction. However, these multidrug regimens frequently induce alterations in renal function by influencing intrarenal hemodynamics, thereby modifying glomerular capillary pressure. This phenomenon could result in a mild to moderate decline in estimated glomerular filtration rate (eGFR), often classified as “worsening kidney function.” This nomenclature stems from consistent observations of eGFR reductions recorded during HF treatment in clinical trials. This narrative review aims to elucidate why the observed eGFR declines in clinical practice may represent either loss of functioning glomeruli or pharmacologically mediated reductions in intraglomerular pressure that ultimately safeguards long-term renal and cardiovascular outcomes. Methods: By a comprehensive re-examination of data from HF clinical trials conducted with various classes of medications, all affecting eGFR, we sought to provide evidence that the decline in eGFR is associated with the activation of specific mechanisms that collectively contribute to a reduction in glomerular filtration pressure, a prominent factor in maladaptive neurohormonal responses. Results: From the investigation of angiotensin-converting enzyme inhibitors to the more recent non-steroidal mineralocorticoid receptor antagonist, the renal effects of these therapeutic regimens correlate with improvements in patient outcomes. The data consistently indicate that an early decline in eGFR, when coupled with an enhancement in HF outcomes, is associated with a more gradual decline in eGFR during long-term follow-up. Conclusions: Clinicians should recognize early declines in eGFR as indicators of favorable intraglomerular hemodynamic adjustments that mitigate maladaptive neurohormonal responses and contribute to improved long-term outcomes in patients with HF.
1. Introduction
Recent advances in heart failure (HF) therapies have revolutionized patient management across the spectrum of left ventricular ejection fraction (LVEF). However, changes in renal function—reflected by alterations in creatinine levels and glomerular filtration rate (GFR)—are commonly observed during treatment with evidence-based multidrug regimens. This is expected, given the close physiological interplay between the heart and kidneys in HF. Chronic kidney disease (CKD) markedly worsens HF outcomes [1], while HF itself is a leading driver of CKD progression in the general population [2]. Consequently, CKD is the most prevalent comorbidity among patients with HF [3].
Moreover, specific pharmacodynamic properties of HF therapies influence intrarenal hemodynamics, affecting the kidney’s capacity to maintain glomerular filtration pressure and regulate electrolyte and protein handling. This can lead to reductions in GFR, termed “worsening renal function” (WRF), often associated with HF medications endorsed by international guidelines [4].
Numerous studies have consistently reported declines in estimated GFR (eGFR) during HF treatment, ranging from 5–10 mL/min/1.73 m2 with angiotensin-converting enzyme inhibitors (ACEis) [5] and angiotensin receptor blockers (ARBs) [6], to approximately 4 mL/min/1.73 m2 with sodium glucose cotransporter 2 inhibitors (SGLT2is) [7] and 2.4–6 mL/min/1.73 m2 with mineralocorticoid receptor antagonists (MRAs) [8].
Notably, WRF has been defined by an increase in serum creatinine or estimated GFR (eGFR), but there is no univocal definition of WRF. Initially, a creatinine increase of ≥0.3 mg/dL, with graded severity, was used. However, eGFR-based assessment has since been preferred because the creatinine–GFR relation is nonlinear and severity strata better predict mortality and hospitalization than a single binary cutoff. The minimal entity of eGFR reduction considered relevant for prognostic purposes is 20–25% [9], but in randomized controlled trials, greater percentage reductions have also been considered. Moreover, the term WRF also encompasses acute declines in renal function that may occur during decongestive therapy. Importantly, it is essential to distinguish these hemodynamically driven reductions in GFR from progressive, irreversible declines due to pathological loss of functioning glomeruli. The implications of WRF arising from structural nephron loss differ substantially from those of GFR reductions observed during guideline-directed HF therapy, which often raise concerns among clinicians, particularly when CKD coexists [10]. Understanding the underlying pathophysiological mechanisms during HF treatment is critical to accurately interpreting changes in GFR and serum creatinine (sCr), thereby optimizing the use of available therapies to improve HF outcomes.
2. Renal Physiology and Heart Failure Hemodynamics
At birth, each kidney contains approximately 950,000 nephrons, with no capacity for new-nephron formation. As individuals mature, nephron size increases to meet rising metabolic demands. Despite significant fluctuations in systemic blood pressure, renal physiology maintains stable filtrate production through autoregulatory mechanisms [11].
This autoregulation, governed by the renal Starling forces, preserves glomerular filtration by modulating glomerular capillary pressure and filtration rate. Local and systemic neurohormonal pathways adjust the tone of the afferent arteriole (AA), efferent arteriole (EA), as well as podocytes and mesangial cells within the glomerular capillary network [12,13]. This intricate system maintains the hydraulic conductivity of the filtration barrier, allowing plasma molecules of up to 42 nm to pass into the filtrate while restricting larger molecules, such as albumin (approximately 75 nm) [14,15]. The oncotic pressure generated by plasma albumin counteracts the hydrostatic filtration pressure, finely tuning the filtration rate and capillary surface area. The coordinated function of these glomerular components enables efficient filtration even amid systemic hemodynamic variations. For simplicity, assuming constant barrier conductivity and stable oncotic forces tied to plasma albumin, the single-nephron GFR primarily depends on glomerular capillary pressure.
Loss of nephrons due to injury or aging leads to compensatory increases in filtration pressure and glomerular hypertrophy, preserving the “renal reserve” via Starling adaptations [13,14,15]. However, in HF, reduced cardiac output and arterial underfilling activate baroreceptors, signaling diminished effective circulating volume to the kidneys. This triggers a nephron-centric response characterized by elevated norepinephrine spillover and excessive activation of the renin–angiotensin–aldosterone system (RAAS). These processes preferentially dilate the AA via adenosine action generated by the breakdown of adenosine triphosphate to adenosine in the tubuloglomerular apparatus while constricting the EA by effect of angiotensin II, thereby sustaining glomerular filtration pressure to preserve filtrate production [16].
This compensatory mechanism, however, becomes maladaptive. The intimate link between glomerular filtration dynamics and neurohormonal activation fosters sodium retention, volume overload, and further renal endocrine stimulation [14,16,17]. During acute HF decompensation, venous congestion, rather than reduced cardiac output, is the principal driver of renal dysfunction. Elevated central venous and intra-abdominal pressures raise renal venous pressure, lowering effective perfusion and impairing glomerular and tubular function [18]. Autoregulatory increases in filtration fraction preserve the GFR but the resultant surge in glomerular filtration pressure often leads to functional proteinuria, especially when preexisting damage impairs mesangial, podocyte, or tubular integrity. Excessive intraglomerular pressure compromises the filtration barrier, accelerating nephron loss [14,17]. In this setting, true hypoperfusion causes renal injury mainly in cardiogenic shock [18].
Multiple factors disrupting glomerular filtration homeostasis help explain why different endogenous modulators may independently elevate the single-nephron GFR, influencing renal reserve and contributing to GFR decline.
By comparing the pathophysiology of heart failure with reduced ejection fraction (HFrEF) with that of heart failure with preserved ejection fraction (HFpEF), it becomes evident that the two conditions share more differences than similarities. Heart failure with reduced ejection fraction is primarily characterized by low cardiac output, which significantly impairs renal perfusion, thus activating RAAS and the sympathetic nervous system. Consequently, renal excretory function becomes highly dependent on increased intraglomerular filtration pressure. HFpEF, in contrast, is characterized by endothelial dysfunction, systemic and myocardial inflammation, and normal or near-normal resting cardiac output. A hallmark of HFpEF is the rapid rise in pulmonary pressure with minimal exertion, reflecting an exaggerated increase in left ventricular end-diastolic pressure, leading to pulmonary vascular congestion and high central venous pressure [18]. This disruption of pulmonary and systemic hemodynamic balance explains why in HFpEF, renal function typically improves with effective decongestion rather than with increases in forward perfusion.
This narrative review aims to elucidate why the observed eGFR declines in clinical practice may represent either loss of functioning glomeruli or pharmacologically mediated reductions in intraglomerular pressure that ultimately safeguards long-term renal and cardiovascular outcomes [19]. From a methodological point of view, all randomized controlled trials evaluating ACEis/ARBs/ARNis, MRAs, and SGLT2is in CHF patients were identified by searching MEDLINE, Embase, CENTRAL, and ClinicalTrials.gov.
3. Angiotensin-Converting Enzyme Inhibitors (ACEis) and Angiotensin Receptor Blockers (ARBs)
Renal concerns in advanced heart failure (HF) have been noted since the CONSENSUS trial in 1987, which first evaluated ACE inhibitors (ACEis) in HF. sCr initially increased by 10–15% (10–20 mmol/L) within three weeks, persisting up to six months. At 24 weeks, sCr rose by 20% in patients with baseline sCr < 1.43 mg/dL versus 11% in those with baseline values > 1.43 mg/dL, with low blood pressure being the strongest predictor of sCr rise in severe HF [20].
A 2000 analysis of the SOLVD trial in patients with HF, reduced ejection fraction (HFrEF) and moderate renal impairment treated with enalapril found declining creatinine clearance was associated with increased mortality (HR per 30 mL/min decrease, 1.24; 95%CI 1.09–1.42) [21], raising concerns over ACEi-induced creatinine increases. However, a subsequent SOLVD analysis over a decade later showed that early eGFR declines (>20% at day 14) were not linked to worse outcomes, and continued therapy conferred survival benefits (HR 0.66; 95%CI 0.5–0.9) [22]. A later post hoc SOLVD analysis confirmed lower hazard rates with enalapril, whereas placebo was associated with higher mortality, concluding that early renal worsening with ACEi initiation is generally benign and does not negate long-term benefits. Moreover, the rate of kidney function decline during follow-up independently predicted mortality, regardless of baseline renal function or HF worsening [23].
The introduction of ARBs further clarified the impact of angiotensin II blockade. In the CHARM trial, involving patients with HFrEF (<40% LVEF) or HF with mildly reduced (HFmrEF) or preserved (HFpEF) ejection fraction (>40% LVEF) and creatinine < 3.0 mg/dL, eGFR was a stronger prognostic indicator than LVEF. Risks of the primary endpoint (cardiovascular death or hospitalization for HF) and all-cause mortality significantly increased when eGFR was <60 mL/min/1.73 m2, independent of ARB treatment effects [24].
Further CHARM analyses showed greater eGFR declines with candesartan versus placebo in both HFrEF and HFpEF, without a treatment-by-outcome interaction [25]. An evaluation of vo revealed that microalbuminuria (30%) and macroalbuminuria (11%) were prevalent across phenotypes and associated with increased hazard ratios (HR 1.43; 95%CI 1.21–1.69 and HR 1.75; 95%CI 1.39–2.20, respectively), underscoring urinary albumin–creatinine ratio (UACr) as a robust HF outcome marker [26].
The Valsartan in HF Trial (Val-HeFT) data on HFrEF patients highlighted proteinuria’s independent association with mortality (HR 1.2; 95%CI 1.01–1.62) and first morbid event (HR 1.28; 95%CI 1.06–1.55), independently of CKD status [23]. Valsartan similarly reduced eGFR in CKD (mean of −3.6 mL/min/1.73 m2) and non-CKD (mean of −4.0 mL/min/1.73 m2) patients but still lowered adverse event risks, distinguishing drug-induced eGFR changes from disease progression [27,28].
4. Angiotensin Receptor Neprilysin Inhibitor (ARNI; Sacubitril/Valsartan)
In the PARADIGM-HF trial, sacubitril/valsartan reduced the primary composite outcome and all-cause mortality by ~20% compared with enalapril in HFrEF [29]. The cohort had a mean eGFR of 70 ± 20 mL/min/1.73 m2, 33% had CKD and 24% had micro/macroalbuminuria. During the run-in, eGFR declined more with enalapril (−0.6 vs. 0.0 mL/min/1.73 m2), suggesting potential long-term renal benefits. However, during follow-up, sacubitril/valsartan showed slower eGFR decline (−1.61 vs. −2.04 mL/min/1.73 m2/year) despite a greater increase in UACr (1.20 vs. 0.90 mg/mmol) [30].
This pattern mirrored the PARAMOUNT findings [31], with albuminuria increases being attributed to heightened natriuretic peptide activity, as also seen in studies where atrial natriuretic peptide raised albuminuria, which reversed upon ARNI withdrawal [32]. A PARADIGM-HF subanalysis stratified by KDIGO risk showed that patients with high/very-high risk (26%) had the highest CV event rates (HR 14.9 per 100 person-years; 95%CI 12.7–17.6). Across KDIGO strata, sacubitril/valsartan maintained a consistent safety and efficacy profile [33,34].
The PARAGON-HF trial in HFpEF nearly reached statistical significance for reducing heart failure hospitalizations (hHFs) or CV mortality (HR 0.87; 95%CI 0.75–1.01). Sacubitril/valsartan reduced renal decline by 1.4% vs. 2.7% with valsartan (HR 0.50; 95%CI 0.33–0.77) [35]. The eGFR initially fell in ~10% of PARAGON-HF versus 11% of PARADIGM-HF run-in participants but partially recovered by week 16 regardless of treatment changes [36].
Longitudinal analyses showed that sacubitril/valsartan consistently slowed chronic eGFR decline versus valsartan (−2.0 vs. −2.7 mL/min/1.73 m2/year) [37]. Further evaluation indicated that accelerated eGFR decline started 12 months before hHF, continued thereafter, and only modestly slowed in patients without subsequent hospitalizations [38]. These findings emphasize sacubitril/valsartan’s nephroprotective role and their renal contributions to cardiovascular benefits [39].
Notably, in PARAGON-HF, women (51.6% of HFpEF patients) experienced greater early eGFR dips with ARNIs (p = 0.006) yet derived pronounced reductions in hHF risk (HR 0.67; 95%CI 0.53–0.85), a benefit not seen in men (HR 1.07; 95%CI 0.85–1.34) [36,40]. This suggests that early eGFR declines in women should not deter guideline-recommended ARNI use.
Table 1 summarizes the effects of ACEis, ARBs and ARNIs.
Table 1.
Effects on glomerular filtration rate and cardiovascular outcome in main studies performed with inhibitors of renin angiotensin system.
5. Mineralocorticoid Receptor Antagonists (MRAs)
5.1. Steroid MRAs
Early studies in the 1950s demonstrated that spironolactone, the first steroidal MRA, effectively reduced salt retention and cardiac necrosis in animal models [41]. However, it was not until the RALES trial in 1999 that the clinical benefits of spironolactone in HFrEF were firmly established. This landmark study, which enrolled 1663 patients with LVEF < 35% and NYHA class III–IV symptoms, found that spironolactone (25 mg/day) reduced all-cause mortality by 30% compared with placebo (HR 0.70; 95%CI, 0.60–0.82), leading to early termination due to efficacy despite an acceptable rise in hyperkalemia [42].
Following RALES, spironolactone prescriptions surged, but this was accompanied by a sharp increase in hyperkalemia-related hospitalizations, rising from 2.4 per 1000 patients in 1994 to 11.0 per 1000 in 2001, with mortality climbing from 0.3 to 2.0 per 1000 [43]. This trend was likely due to spironolactone use in patients with advanced CKD, a group excluded from RALES.
To improve safety, eplerenone, a next-generation steroidal MRA with greater receptor selectivity and reduced affinity for progesterone and androgen receptors, was developed to mitigate hyperkalemia risk. The EMPHASIS-HF trial, published in 2011, investigated eplerenone in 2737 patients with NYHA class II symptoms, LVEF < 30%, eGFR > 30 mL/min/1.73 m2, and serum potassium < 5.0 mmol/L, all receiving ACEis/ARBs and beta-blockers. Eplerenone significantly reduced all-cause mortality (HR 0.76; 95%CI, 0.62–0.93), cardiovascular death (HR 0.76; 95%CI, 0.61–0.94), and hHF, with a modest increase in hyperkalemia (8% vs. 3.7%) [44].
Despite these strong outcomes, MRA use remained limited, primarily due to concerns over hyperkalemia and WRF in high-risk patients. A prespecified analysis showed that with careful monitoring, eplerenone was both safe and beneficial even in patients at elevated risk of hyperkalemia or WRF [45] (Table 2).
MRA underutilization is also linked to the 2014 TOPCAT trial, which evaluated spironolactone in HFpEF (LVEF > 40%) [46]. Although the study narrowly missed its primary endpoint (HR 0.89; 95%CI, 0.77–1.04) for hHF and cardiovascular mortality, critiques centered on regional variations and adherence issues. Subgroup analyses revealed reductions in cardiovascular mortality and HF events among patients with lower natriuretic peptide levels and among women [47,48]. However, elevated rates of hyperkalemia (18.7% vs. 9.1%) and increased serum creatinine led to discontinuation in roughly one-third of participants, limiting guideline endorsement even after post hoc analyses demonstrated benefit in North American cohorts [49] (Table 2).
Despite this, a TOPCAT subanalysis in patients with repeated UACr measurements found that spironolactone reduced UACr by 39% overall and by 76% in those with microalbuminuria at one year. These reductions correlated with declines in hHF (HR 0.90; 95%CI, 0.82–0.98) and all-cause mortality (HR 0.91; 95%CI, 0.84–0.98), highlighting the association between eGFR decline, albumin leakage, and HF outcomes [50] (Table 3).
5.2. Non-Steroid MRAs
Given the antialbuminuric effects of MRAs, research has focused on developing non-steroidal agents to minimize adverse effects. Finerenone, a novel non-steroidal MRA, has lower affinity for sex hormone receptors and a reduced risk of hyperkalemia [51].
Initial trials, FIDELIO-DKD and FIGARO-DKD, assessed finerenone’s impact on renal and cardiovascular outcomes in patients with T2D and CKD. Finerenone led to an early eGFR decline at 4 months (−3.18 vs. −0.73 mL/min/1.73 m2), but by the study end, the treated group showed less decline compared with controls (−2.66 vs. −3.97 mL/min/1.73 m2), alongside significant reductions in CKD progression, albuminuria, and cardiovascular events, including a 22% reduction in hHF (HR 0.78; 95%CI, 0.66–0.92), independent of baseline HF status [52].
A pooled analysis of EMPHASIS-HF and TOPCAT confirmed an acute eGFR decline (average of 2–2.4 mL/min/1.73 m2) after steroidal MRAs without long-term differences in slope versus placebo, indicating no sustained renal harm [8]. Encouraged by these findings, finerenone was evaluated in HF patients in the FINEARTS-HF trial, which enrolled 6001 patients with HFpEF or HFmrEF (mean eGFR of 63 mL/min/1.73 m2; 45% women; 45.5% with diabetes). Finerenone significantly reduced total HF events and cardiovascular death (HR 0.84; 95%CI, 0.74–0.95), with low rates of significant hyperkalemia (>6.0 mmol/L: 3% vs. 1.4%) [53].
Interestingly, 23.0% of finerenone-treated patients experienced >15% eGFR declines, compared with 13.4% in the placebo group (HR 1.95; 95%CI, 1.69–2.24). However, increased risk of adverse outcomes was only seen with eGFR declines in the placebo arm (adjusted HR 1.50; 95%CI, 1.20–1.89), not with finerenone (adjusted rate ratio 1.07; 95%CI, 0.84–1.35; p interaction = 0.04), suggesting finerenone’s renal safety across eGFR trajectories and LVEF ranges [54] (Table 2).
The FINEARTS-HF study revealed an early, drug-induced eGFR decline that stabilized by 90 days, mirroring sustained reductions in albuminuria (−30%) and risk of new-onset micro- and macroalbuminuria (−38%). Although the composite renal endpoint was not significantly affected, the parallel changes in UACr and eGFR slopes underscored their interconnected pathophysiology [55].
A subsequent meta-analysis in The Lancet confirmed the prognostic benefits of MRAs across HF phenotypes, despite an increased frequency of eGFR declines > 30% in treated groups. Importantly, large MRA trials typically excluded patients with eGFR < 45 mL/min/1.73 m2, highlighting the context needed when interpreting these declines [56] (Table 2 and Table 3).
Collectively, these data indicate that eGFR declines under MRA therapy often reflect reductions in intraglomerular pressure, particularly in patients with diabetes or HF, where decreased albuminuria translates into long-term renal and cardiovascular benefits [26,27,28,52,54].
Table 2.
Effect or mineralocorticoid receptor antagonists on renal function and cardiovascular outcome in heart failure patients.
Table 3.
Table reports data generated by post hoc analysis of heart failure trials and evaluating the effects of albuminuria on outcome and on therapy renal effect. Of note, heart failure study design did not include albuminuria among the prespecified protocol analysis criteria.
6. Sodium Glucose Cotransporter Type 2 Inhibitors (SGLT2is)
Initially developed as glucose-lowering agents, SGLT2 inhibitors (SGLT2is, or gliflozins) demonstrated unexpected cardiovascular and renal benefits in diabetic patients, as shown in the EMPA-REG OUTCOME, DECLARE, CANVAS, and CREDENCE trials. These findings led to their application in patients with HF and CKD, resulting in reduced risk of HF progression and CKD worsening [59]. Although early benefits were attributed to natriuretic effects, subsequent research highlighted more complex renal mechanisms [60], with consistent efficacy across HF phenotypes, irrespective of diabetes or CKD status.
Administration of SGLT2is typically induces a modest, transient decline in eGFR (approximately −3 to −5 mL/min/1.73 m2 within 2–4 weeks), reflecting reduced intraglomerular pressure.
Since the largest proportion of sodium reabsorption occurs in the proximal tubule segment, it affects the electrolyte concentration reaching the tubuloglomerular apparatus. The SGLT2 inhibition-driven eGFR decline, by decreasing filtrate production, attenuates the reabsorption of sodium and glucose and rebalances the sodium concentration that reaches the tubuloglomerular apparatus, allowing for the restoration of the tubuloglomerular feedback [61,62]. Unlike angiotensin II blockade, this mechanism complements sacubitril–valsartan, particularly in patients with reduced ejection fraction [63]. Importantly, this early eGFR dip signals hemodynamic efficacy and is associated with long-term cardiovascular and renal protection, not harm [61,62,64].
Following this initial dip, the eGFR tends to stabilize or improve, and long-term therapy slows GFR decline relative to placebo across diverse cohorts [Table 4]. In DAPA-HF, dapagliflozin led to a smaller eGFR decrease (−1.09 vs. −2.85 mL/min/1.73 m2 with placebo) [65]. Similar patterns emerged in DELIVER (HFmrEF/HFpEF) [66] and in EMPEROR-Reduced and EMPEROR-Preserved, where treated patients consistently experienced less decline [67,68].
Table 4.
Effects on glomerular filtration rate and cardiovascular outcome in main studies performed with inhibitors of sodium glucose cotransporter type 2.
Conversely, post hoc analyses linked spontaneous eGFR decreases in placebo groups to higher cardiovascular, renal, and mortality risks [67,68], as noted in DAPA-HF [65]. In EMPEROR trials, the eGFR rose after SGLT2i discontinuation, aligning treated patients with placebo outcomes within 30 days [69], mirroring reversibility seen in diabetes studies [70].
Empagliflozin also reduced macroalbuminuria incidence (HR 0.81; 95%CI: 0.70–0.94) and increased regression to normo- or microalbuminuria (HR 1.31; 95%CI: 1.07–1.59), particularly in diabetic patients with higher baseline UACr [58] [Table 3]. Additionally, SGLT2is lowered acute kidney injury rates and HF events across all investigated settings [59].
These drugs consistently produced early reductions in primary endpoints (by 21–25% within 30 days), with benefits comparable in scale to ACE inhibitors when first introduced for HF [62,71]. The direct modulation of renin release by SGLT2 inhibition may further explain these additive effects [62,64].
SGLT2 inhibitors also attenuate glomerular filtration pressure, evidenced by reduced albuminuria in diabetic and non-diabetic populations [59]. This albuminuria reduction likely plays a crucial role in slowing HF progression, given its strong association with adverse HF outcomes [25,26,27].
7. Discussion
CKD is the most prevalent comorbidity in patients with HF, followed by diabetes, which compounds disease burden [3,72,73,74]. Clinicians often interpret eGFR declines from evidence-based therapies as alarming signs of “worsening kidney function,” implying imminent renal failure. However, this overlooks the kidney’s physiological role in volume and toxin regulation and its unique vascular architecture—receiving 25% of cardiac output while comprising just 0.7% of body mass—to rapidly adjust filtration in response to circulatory demands [64,74,75].
To maintain a typical GFR near 125 mL/min, the kidney activates mechanisms—chiefly RAAS and sympathetic responses—whenever blood flow decreases. These adaptations elevate intraglomerular pressure to sustain filtration but at the cost of potential long-term damage, masking CKD progression while preserving a GFR of up to 130–140 mL/min/1.73 m2 [14,64,65,75,76,77,78,79].
Therapies such as ACEis/ARBs, ARNIs, MRAs, and SGLT2is should thus be viewed not merely as agents altering the GFR but also as modulators restoring physiologic intraglomerular pressure. Large trials consistently show that despite early eGFR variability, these agents preserve renal function and improve HF outcomes in patients with and without diabetes [14,55,59,61,64,65,75]. Notably, eGFR declines are usually reversible, infrequently linked to adverse renal events and rarely >30% [4,69,70,73].
The extent and timing of eGFR dips vary by drug mechanism, patient characteristics, background therapy, and trial design. Larger acute eGFR reductions often occur in patients with better baseline kidney function yet may still be beneficial in advanced CKD [59]. For instance, in type 2 diabetes studies, those with the greatest eGFR declines during early RAAS blockade had the best long-term renal preservation [79].
However, inconsistent definitions of WRF across HF trials have muddled interpretation of renal outcomes and drug effects on CKD progression [63,69,71,78]. A secondary analysis of over 28,000 HF patients from six trials of steroidal MRAs, ARNIs, and SGLT2is demonstrated that under standardized kidney endpoints, these therapies had neutral or beneficial impacts on renal outcomes [80]. This underscores the need for harmonized definitions, especially as most HF trials exclude patients with advanced CKD (stage IV), focusing on milder renal impairment. Consequently, HF events typically dictate trial endpoints, often censoring patients before long-term renal changes manifest [2,81].
Analyzing eGFR slopes offers a more robust indicator of drug effects than discrete events, though it requires adequate power and consistent analytic standards [2,81]. In HF patients with preserved eGFR, the early “dip” with SGLT2is often predicts longer-term benefits, as shown by improvements in both HF events and chronic eGFR trajectories [59,62,70,78,79,82,83]. The FINEARTS-HF trial further supported this, with a win ratio of 1.17 (95%CI: 1.04–1.32) that remained favorable despite early declines, stabilizing after roughly 12 months [84].
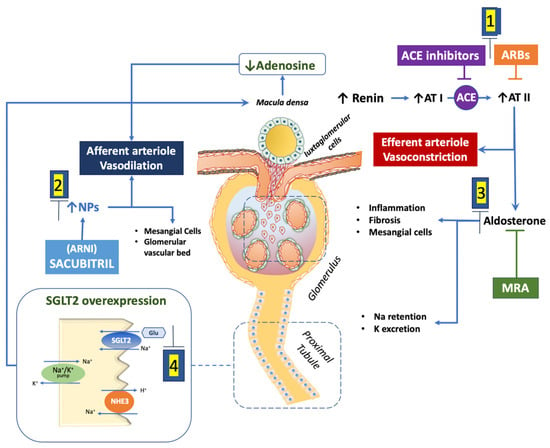
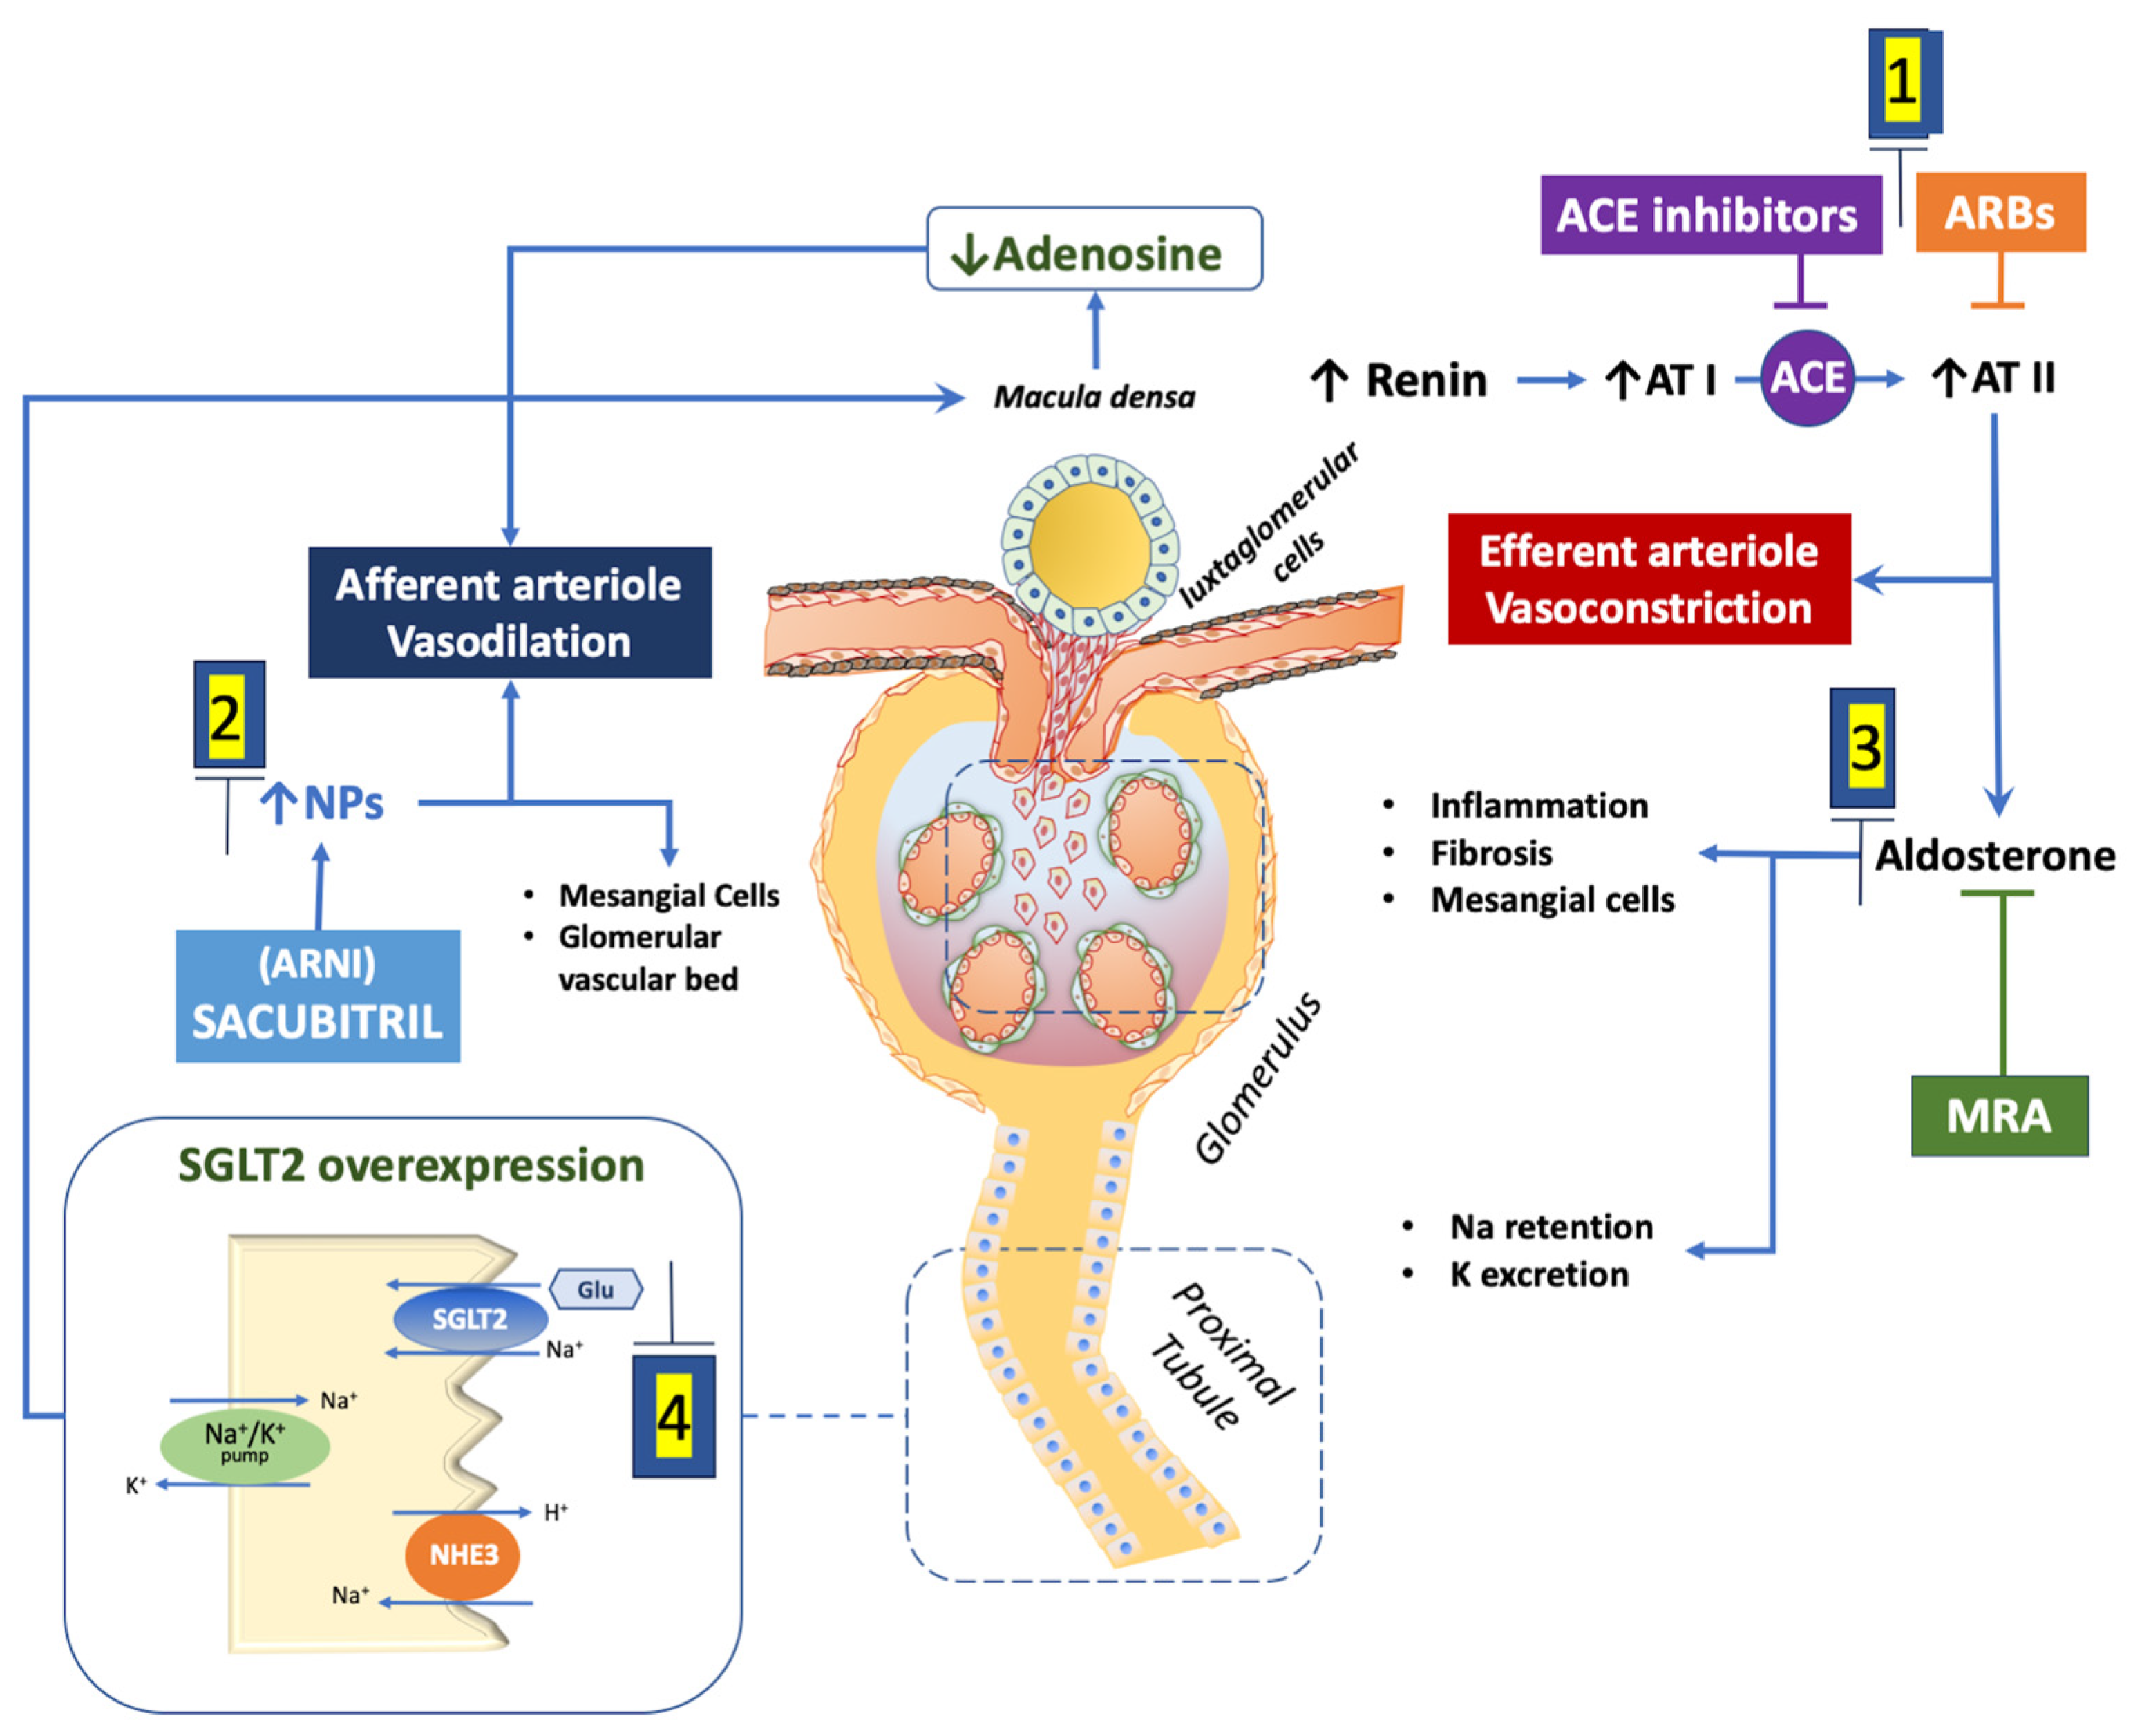
Albuminuria, a marker of glomerular injury driven by hypertension, insulin resistance, and hyperglycemia, is strongly linked to incident HF and exacerbations, especially with low eGFRs [85]. RAAS and SGLT2 inhibitors mitigate albuminuria through distinct hemodynamic pathways (Figure 1), supporting combination strategies in HF management. Caution is needed in interpreting early rises in UACr with ARNIs, often reflecting mesangial relaxation from natriuretic peptide effects rather than structural damage [30,31,32].
Figure 1.
1. ACEis and ARBs, by inhibiting the angiotensin-converting enzyme, prevent angiotensin vasoconstrictive action on the efferent arteriole, thereby avoiding the rise in the intraglomerular pressure gradient that leads to hyperfiltration. 2. The ARNI molecule combines the action of the ARB valsartan with the sacubitril-mediated inhibition of neprylisin, which is responsible for atrial natriuretic peptide degradation. Natriuretic peptides not only exert fast natriuretic action but also induce mesangial structure relaxation, allowing for the filtration of a mild amount of albumin that can be detected in the urine. By being a physiology-related effect, the albumin leak does not impact HF outcome but correlates with the intraglomerular vascular resistance decrease. 3. MRAs not only reduce sodium reabsorption in the renal collecting tubule but also concur to balance the intraglomerular filtration pressure by potent anti-inflammatory, anti-oxidation and anti-fibrotic action on the glomerular mesangial structure. This shields the delicate sieve deputed to select plasma solutes that have to be preserved from filtration (i.e., albumin) and the amounts of electrolytes and molecules generating the filtrate. 4. In the early segment of the glomerular tubule, SGLT2 is primarily involved in the reabsorption of filtered glucose. However, any condition entailing a rise in filtrate production results in an immediate increase in SGLT2 expression coupled with the activity of NHE3, located in the apical membrane of the proximal tubule section. Their combined action is responsible for a larger reabsorption of sodium and largely impoverishes the sodium content in the filtrate. The low sodium concentration, by reaching the juxtaglomerular apparatus, reduces the production of adenosine. SGLT2 inhibitors, by counteracting the disproportioned glucose and sodium reabsorption in the proximal tubule, restore adenosine effects, thus leading to the restraint of the vessel section and tapering down intraglomerular pressure (see text for details).
Longitudinal UACr monitoring, as recommended by KDIGO categories, enables better risk stratification and timely therapeutic adjustments [33,73,74,86]. Evidence from post hoc analyses shows that effective therapy rapidly alters albuminuria, linking changes to improved HF and renal outcomes [27,28,29,49,52,54,59,73,85].
Finally, it is crucial to challenge misconceptions that a modest slowing of eGFR decline with RAAS or SGLT2 inhibitors lacks clinical significance. EMPA-Kidney demonstrated that greater relative benefits in chronic slope occur among higher-risk patients, emphasizing the value of this metric even when short-term changes appear modest [86].
Regarding thresholds, while an eGFR < 30 mL/min/1.73 m2 often precludes RAAS or SGLT2 initiation, observational data suggest potential benefits with cautious monitoring, including in advanced CKD. Finerenone demonstrated safety and efficacy down to an eGFR of 25, while dapagliflozin and empagliflozin were safe and effective in HF patients with an eGFR as low as 20–25 [52,53,56,60]. Nonetheless, steroidal MRA benefits wane near eGFRs of 30, and careful management is required to avoid limiting other key HF therapies [55,86].
8. Conclusions
Renal function plays a pivotal role in the progression, management, and outcomes of heart failure (HF), often complicating treatment strategies. The complex interplay among cardiac, renal, and metabolic systems frequently leads clinicians to rely on glomerular filtration rate (GFR) changes as primary indicators of therapeutic tolerance. This narrow focus can obscure a true understanding of drug efficacy in clinical practice. As a result, neurohormonal therapies are frequently underdosed or prematurely discontinued, particularly when the eGFR approaches 30 mL/min/1.73 m2 [10]. Conversely, robust data from studies in diabetic patients with moderate renal impairment and albuminuria demonstrate that evidence-based treatments maintain a favorable safety profile even in these populations. This underscores the need to prioritize therapy optimization over eGFR fluctuations.
Misinterpretation of treatment-induced eGFR changes often places HF patients with CKD at greater risk by withholding essential therapies, thereby exacerbating their prognosis relative to patients without CKD [4,75,86]. This issue is compounded by inadequate clinical monitoring, which prevents timely dose adjustments and contributes to unnecessary treatment withdrawal.
Clinicians must appreciate that renal physiology is inherently designed to maintain filtration under varying circulatory conditions. The kidneys continuously monitor blood pressure and flow, rapidly deploying compensatory mechanisms to sustain glomerular filtration pressure and preserve filtrate production. While this response is initially protective, in chronic cardiovascular disease, it becomes maladaptive, perpetuating neurohormonal activation and contributing to HF onset and progression.
By adhering to patient selection criteria established in major clinical trials and ensuring diligent follow-up, clinicians should recognize early declines in eGFR as indicative of favorable intraglomerular hemodynamic adjustments. These changes mitigate maladaptive neurohormonal responses and ultimately support improved long-term outcomes in patients with HF. It is important to recall that drug-induced WRF is essentially a hemodynamic phenomenon affecting glomerular circulatory dynamics. It is typically characterized by early onset, a mild rise in serum creatinine, normal urinalysis, and rapid stabilization. This process is reversible and does not involve structural nephron injury. In contrast, true WRF is characterized by a progressive increase in serum creatinine, often exceeding 30%, and is not reversible. In such cases, abnormal findings on urinalysis and structural changes on renal imaging are commonly present.
Author Contributions
Conceptualization, E.G.; methodology, E.G., M.I., A.P., S.C., and A.A.; data curation, E.G., M.I., A.P., S.C., and A.A.; writing—original draft preparation, E.G., M.I., A.P., and A.A.; writing—review and editing, S.C., D.G., and L.T.; visualization, E.G., M.I., A.P., S.C., A.A., D.G., and L.T.; supervision, D.G. and L.T. All authors have read and agreed to the published version of the manuscript.
Funding
This research study received no external funding.
Data Availability Statement
Not applicable.
Conflicts of Interest
Author Arduino Arduini works in Iperboreal Pharma. The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| AA | Afferent arteriole |
| ACEi | Angiotensin-converting enzyme inhibitor |
| ARB | Angiotensin receptor blocker |
| ARNI | Angiotensin receptor neprilysin inhibitor |
| CKD | Chronic kidney disease |
| EA | Efferent arteriole |
| eGFR | Estimated glomerular filtration rate |
| HF | Heart failure |
| hHF | Heart failure hospitalizations |
| HFmrEF | Heart failure with mildly reduced ejection fraction |
| HFpEF | Heart failure with preserved ejection fraction |
| HFrEF | Heart failure with reduced ejection fraction |
| LVEF | Left ventricular ejection fraction |
| MRA | Mineralocorticoid receptor antagonist |
| RAAS | Renin angiotensin aldosterone system |
| sCr | Serum creatinine |
| SGLT2i | Sodium glucose cotransporter 2 inhibitor |
| WRF | Worsening renal function |
| UACr | Urinary albumin–creatinine ratio |
References
- Damman, K.; Valente, M.A.; Voors, A.A.; O’Connor, C.M.; van Veldhuisen, D.J.; Hillege, H.L. Renal impairment, worsening renal function, and outcome in patients with heart failure: An updated meta-analysis. Eur. Heart J. 2014, 35, 455–469. [Google Scholar] [CrossRef] [Scilit]
- Mark, P.B.; Carrero, J.J.; Matsushita, K.; Sang, Y.; Ballew, S.H.; Grams, M.E.; Coresh, J.; Surapaneni, A.; Brunskill, N.J.; Chalmers, J.; et al. Major cardiovascular events and subsequent risk of kidney failure with replacement therapy: A CKD Prognosis Consortium study. Eur Heart J. 2023, 44, 1157–1166. [Google Scholar] [CrossRef] [Scilit]
- van Deursen, V.M.; Urso, R.; Laroche, C.; Damman, K.; Dahlstrom, U.; Tavazzi, L.; Maggioni, A.P.; Voors, A.A. Co-morbidities in patients with heart failure: An analysis of the European Heart Failure Pilot Survey. Eur. J. Heart Fail. 2014, 16, 103–111. [Google Scholar] [CrossRef] [Scilit]
- Damman, K. When Kidney Function Declines But Therapy Still Works: The Case for Nonsteroidal MRA Therapy in Heart Failure. J. Am. Coll. Cardiol. 2025, 85, 186–189. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McCallum, W.; Tighiouart, H.; Ku, E.; Salem, D.; Sarnak, M.J. Trends in Kidney Function Outcomes Following RAAS Inhibition in Patients with Heart Failure with Reduced Ejection Fraction. Am. J. Kidney Dis. 2020, 75, 21–29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Damman, K.; Perez, A.C.; Anand, I.S.; Komajda, M.; McKelvie, R.S.; Zile, M.R.; Massie, B.; Carson, P.E.; McMurray, J.J. Worsening renal function and outcome in heart failure patients with preserved ejection fraction and the impact of angiotensin receptor blocker treatment. J. Am. Coll. Cardiol. 2014, 64, 1106–1113. [Google Scholar] [CrossRef] [Scilit]
- Zannad, F.; Ferreira, J.P.; Pocock, S.J.; Zeller, C.; Anker, S.D.; Butler, J.; Filippatos, G.; Hauske, S.J.; Brueckmann, M.; Pfarr, E.; et al. Cardiac and Kidney Benefits of Empagliflozin in Heart Failure Across the Spectrum of Kidney Function: Insights From EMPEROR-Reduced. Circulation 2021, 143, 310–321. [Google Scholar] [CrossRef] [Scilit]
- Vaduganathan, M.; Ferreira, J.P.; Rossignol, P.; Neuen, B.L.; Claggett, B.L.; Pfeffer, M.A.; McMurray, J.J.V.; Pitt, B.; Zannad, F.; Solomon, S.D. Effects of steroidal mineralocorticoid receptor antagonists on acute and chronic estimated glomerular filtration rate slopes in patients with chronic heart failure. Eur. J. Heart Fail. 2022, 24, 1586–1590. [Google Scholar] [CrossRef] [Scilit]
- Damman, K.; Tang, W.H.; Testani, J.M.; McMurray, J.J. Terminology and definition of changes renal function in heart failure. Eur. Heart J. 2014, 35, 3413–3416. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shahim, A.; Linde, C.; Savarese, G.; Dahlstrom, U.; Lund, L.H.; Hage, C. Implementation of guideline-recommended therapies in heart failure with reduced ejection fraction according to heart failure duration: An analysis of 55 581 patients from the Swedish Heart Failure (SwedeHF) Registry. Eur. J. Heart Fail. 2025, 27, 421–431. [Google Scholar] [CrossRef] [Scilit]
- Dalal, R.; Bruss, Z.S.; Sehdev, J.S. Physiology, Renal Blood Flow and Filtration. In StatPearls [Internet]; StatPearls Publishing: Treasure Island, FL, USA, 2025. Available online: https://www.ncbi.nlm.nih.gov/books/NBK482248/ (accessed on 4 March 2026).
- Zhu, X.; Gao, D.; Albertazzi, V.; Zhong, J.; Ma, L.J.; Du, L.; Shyr, Y.; Kon, V.; Yang, H.C.; Fogo, A.B. Podocyte-Related Mechanisms Underlying Survival Benefit of Long-Term Angiotensin Receptor Blocker. Int. J. Mol. Sci. 2022, 23, 6018. [Google Scholar] [CrossRef] [Scilit]
- Dzau, V.J. Theodore Cooper Lecture: Tissue angiotensin and pathobiology of vascular disease: A unifying hypothesis. Hypertension 2001, 37, 1047–1052. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pollak, M.R.; Quaggin, S.E.; Hoenig, M.P.; Dworkin, L.D. The glomerulus: The sphere of influence. Clin. J. Am. Soc. Nephrol. 2014, 9, 1461–1469. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Romagnani, P.; Remuzzi, G.; Glassock, R.; Levin, A.; Jager, K.J.; Tonelli, M.; Massy, Z.; Wanner, C.; Anders, H.J. Chronic kidney disease. Nat. Rev. Dis. Primers 2017, 3, 17088. [Google Scholar] [CrossRef] [Scilit]
- Packer, M. Why do the kidneys release renin in patients with congestive heart failure? A nephrocentric view of converting-enzyme inhibition. Eur. Heart J. 1990, 11, 44–52. [Google Scholar] [CrossRef] [Scilit]
- Butt, L.; Unnersjo-Jess, D.; Hohne, M.; Edwards, A.; Binz-Lotter, J.; Reilly, D.; Hahnfeldt, R.; Ziegler, V.; Fremter, K.; Rinschen, M.M.; et al. A molecular mechanism explaining albuminuria in kidney disease. Nat. Metab. 2020, 2, 461–474. [Google Scholar] [CrossRef] [Scilit]
- Mullens, W.; Nijst, P. Cardiac Output and Renal Dysfunction: Definitely More Than Impaired Flow. J. Am. Coll. Cardiol. 2016, 67, 2209–2212. [Google Scholar] [CrossRef] [Scilit]
- Benghanem Gharbi, M.; Elseviers, M.; Zamd, M.; Belghiti Alaoui, A.; Benahadi, N.; Trabelssi, E.H.; Bayahi, R.; Ramdani, B.; De Broe, M.E. Chronic kidney disease, hypertension, diabetes, and obesity in the adult population of Morocco: How to avoid “over”- and “under”-diagnosis of CKD. Kidney Int. 2016, 89, 1363–1371. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ljungman, S.; Kjekshus, J.; Swedberg, K. Renal function in severe congestive heart failure during treatment with enalapril (the Cooperative North Scandinavian Enalapril Survival Study [CONSENSUS] Trial). Am. J. Cardiol. 1992, 70, 479–487. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dries, D.L.; Exner, D.V.; Domanski, M.J.; Greenberg, B.; Stevenson, L.W. The prognostic implications of renal insufficiency in asymptomatic and symptomatic patients with left ventricular systolic dysfunction. J. Am. Coll. Cardiol. 2000, 35, 681–689. [Google Scholar] [CrossRef] [Scilit]
- Testani, J.M.; Kimmel, S.E.; Dries, D.L.; Coca, S.G. Prognostic importance of early worsening renal function after initiation of angiotensin-converting enzyme inhibitor therapy in patients with cardiac dysfunction. Circ. Heart Fail. 2011, 4, 685–691. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khan, N.A.; Ma, I.; Thompson, C.R.; Humphries, K.; Salem, D.N.; Sarnak, M.J.; Levin, A. Kidney function and mortality among patients with left ventricular systolic dysfunction. J. Am. Soc. Nephrol. 2006, 17, 244–253. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hillege, H.L.; Nitsch, D.; Pfeffer, M.A.; Swedberg, K.; McMurray, J.J.; Yusuf, S.; Granger, C.B.; Michelson, E.L.; Ostergren, J.; Cornel, J.H.; et al. Candesartan in Heart Failure: Assessment of Reduction in Mortality and Morbidity (CHARM) Investigators. Renal function as a predictor of outcome in a broad spectrum of patients with heart failure. Circulation 2006, 113, 671–678. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Damman, K.; Solomon, S.D.; Pfeffer, M.A.; Swedberg, K.; Yusuf, S.; Young, J.B.; Rouleau, J.L.; Granger, C.B.; McMurray, J.J. Worsening renal function and outcome in heart failure patients with reduced and preserved ejection fraction and the impact of angiotensin receptor blocker treatment: Data from the CHARM-study programme. Eur. J. Heart Fail. 2016, 18, 1508–1517. [Google Scholar] [CrossRef] [Scilit]
- Jackson, C.E.; Solomon, S.D.; Gerstein, H.C.; Zetterstrand, S.; Olofsson, B.; Michelson, E.L.; Granger, C.B.; Swedberg, K.; Pfeffer, M.A.; Yusuf, S.; et al. Albuminuria in chronic heart failure: Prevalence and prognostic importance. Lancet 2009, 374, 543–550. [Google Scholar] [CrossRef] [Scilit]
- Anand, I.S.; Bishu, K.; Rector, T.S.; Ishani, A.; Kuskowski, M.A.; Cohn, J.N. Proteinuria, chronic kidney disease, and the effect of an angiotensin receptor blocker in addition to an angiotensin-converting enzyme inhibitor in patients with moderate to severe heart failure. Circulation 2009, 120, 1577–1584. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gerstein, H.C.; Mann, J.F.; Yi, Q.; Dinneen, S.F.; Hoogwerf, B.; Hallé, J.P.; Young, J.; Rashkow, A.; Joyce, C.; Nawaz, S.; et al. Albuminuria and risk of cardiovascular events, death, and heart failure in diabetic and nondiabetic individuals. JAMA 2001, 286, 421–426. [Google Scholar] [CrossRef] [Scilit]
- McMurray, J.J.; Packer, M.; Desai, A.S.; Gong, J.; Lefkowitz, M.P.; Rizkala, A.R.; Rouleau, J.L.; Shi, V.C.; Solomon, S.D.; Swedberg, K.; et al. Angiotensin-neprilysin inhibition versus enalapril in heart failure. N. Engl. J. Med. 2014, 371, 993–1004. [Google Scholar] [CrossRef] [Scilit]
- Damman, K.; Gori, M.; Claggett, B.; Jhund, P.S.; Senni, M.; Lefkowitz, M.P.; Prescott, M.F.; Shi, V.C.; Rouleau, J.L.; Swedberg, K.; et al. Renal Effects and Associated Outcomes During Angiotensin-Neprilysin Inhibition in Heart Failure. JACC Heart Fail. 2018, 6, 489–498. [Google Scholar] [CrossRef] [Scilit]
- Voors, A.A.; Gori, M.; Liu, L.C.; Claggett, B.; Zile, M.R.; Pieske, B.; McMurray, J.J.; Packer, M.; Shi, V.; Lefkowitz, M.P.; et al. Renal effects of the angiotensin receptor neprilysin inhibitor LCZ696 in patients with heart failure and preserved ejection fraction. Eur. J. Heart Fail. 2015, 17, 510–517. [Google Scholar] [CrossRef] [Scilit]
- Ruggenenti, P.; Remuzzi, G. Combined neprilysin and RAS inhibition for the failing heart: Straining the kidney to help the heart? Eur. J. Heart Fail. 2015, 17, 468–471. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- House, A.A.; Wanner, C.; Sarnak, M.J.; Pina, I.L.; McIntyre, C.W.; Komenda, P.; Komenda, P.; Kasiske, B.L.; Deswal, A.; deFilippi, C.R.; et al. Heart failure in chronic kidney disease: Conclusions from a Kidney Disease: Improving Global Outcomes (KDIGO) Controversies Conference. Kidney Int. 2019, 95, 1304–1317. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chatur, S.; Neuen, B.L.; Claggett, B.L.; Beldhuis, I.E.; Mc Causland, F.R.; Desai, A.S.; Rouleau, J.L.; Zile, M.R.; Lefkowitz, M.P.; Packer, M.; et al. Effects of Sacubitril/Valsartan Across the Spectrum of Renal Impairment in Patients with Heart Failure. J. Am. Coll. Cardiol. 2024, 83, 2148–2159. [Google Scholar] [CrossRef] [Scilit]
- Solomon, S.D.; McMurray, J.J.V.; Anand, I.S.; Ge, J.; Lam, C.S.P.; Maggioni, A.P.; Martinez, F.; Packer, M.; Pfeffer, M.A.; Pieske, B.; et al. Angiotensin-Neprilysin Inhibition in Heart Failure with Preserved Ejection Fraction. N. Engl. J. Med. 2019, 38, 1609–1620. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chatur, S.; Claggett, B.L.; McCausland, F.R.; Rouleau, J.; Zile, M.R.; Packer, M.; Pfeffer, M.A.; Lefkowitz, M.; McMurray, J.J.V.; Solomon, S.D.; et al. Variation in Renal Function Following Transition to Sacubitril/Valsartan in Patients with Heart Failure. J. Am. Coll. Cardiol. 2023, 81, 1443–1455. [Google Scholar] [CrossRef] [Scilit]
- Mc Causland, F.R.; Lefkowitz, M.P.; Claggett, B.; Anavekar, N.S.; Senni, M.; Gori, M.; Jhund, P.S.; McGrath, M.M.; Packer, M.; Shi, V.; et al. Angiotensin-Neprilysin Inhibition and Renal Outcomes in Heart Failure with Preserved Ejection Fraction. Circulation 2020, 142, 1236–1245. [Google Scholar] [CrossRef] [Scilit]
- Chatur, S.; Vaduganathan, M.; Peikert, A.; Claggett, B.L.; McCausland, F.R.; Skali, H.; Pfeffer, M.A.; Beldhuis, I.E.; Kober, L.; Seferovic, P.; et al. Longitudinal trajectories in renal function before and after heart failure hospitalization among patients with heart failure with preserved ejection fraction in the PARAGON-HF trial. Eur. J. Heart Fail. 2022, 24, 1906–1914. [Google Scholar] [CrossRef] [Scilit]
- Pontremoli, R.; Borghi, C.; Perrone Filardi, P. Renal protection in chronic heart failure: Focus on sacubitril/valsartan. Eur. Heart J. Cardiovasc. Pharmacother. 2021, 7, 445–452. [Google Scholar] [CrossRef] [Scilit]
- McMurray, J.J.V.; Jackson, A.M.; Lam, C.S.P.; Redfield, M.M.; Anand, I.S.; Ge, J.; Lefkowitz, M.P.; Maggioni, A.P.; Martinez, F.; Packer, M.; et al. Effects of Sacubitril-Valsartan Versus Valsartan in Women Compared with Men with Heart Failure and Preserved Ejection Fraction: Insights From PARAGON-HF. Circulation 2020, 141, 338–351. [Google Scholar] [CrossRef] [Scilit]
- Selye, H.; Hall, C.E.; Rowley, E.M. Malignant Hypertension Produced by Treatment with Desoxycorticosterone Acetate and Sodium Chloride. Can. Med. Assoc. J. 1943, 49, 88–92. [Google Scholar]
- Pitt, B.; Zannad, F.; Remme, W.J.; Cody, R.; Castaigne, A.; Perez, A.; Palensky, J.; Wittes, J. The effect of spironolactone on morbidity and mortality in patients with severe heart failure. Randomized Aldactone Evaluation Study Investigators. N. Engl. J. Med. 1999, 341, 709–717. [Google Scholar] [CrossRef] [Scilit]
- Juurlink, D.N.; Mamdani, M.M.; Lee, D.S.; Kopp, A.; Austin, P.C.; Laupacis, A.; Redelmeier, D.A. Rates of hyperkalemia after publication of the Randomized Aldactone Evaluation Study. N. Engl. J. Med. 2004, 351, 543–551. [Google Scholar] [CrossRef] [Scilit]
- Zannad, F.; McMurray, J.J.; Krum, H.; van Veldhuisen, D.J.; Swedberg, K.; Shi, H.; Vincent, J.; Pocock, S.J.; Pitt, B.; EMPHASIS-HF Study Group. Eplerenone in patients with systolic heart failure and mild symptoms. N. Engl. J. Med. 2011, 364, 11–21. [Google Scholar] [CrossRef] [Scilit]
- Eschalier, R.; McMurray, J.J.; Swedberg, K.; van Veldhuisen, D.J.; Krum, H.; Pocock, S.J.; Shi, H.; Vincent, J.; Rossignol, P.; Zannad, F.; et al. Safety and efficacy of eplerenone in patients at high risk for hyperkalemia and/or worsening renal function: Analyses of the EMPHASIS-HF study subgroups (Eplerenone in Mild Patients Hospitalization And SurvIval Study in Heart Failure). J. Am. Coll. Cardiol. 2013, 62, 1585–1593. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pitt, B.; Pfeffer, M.A.; Assmann, S.F.; Boineau, R.; Anand, I.S.; Claggett, B.; Clausell, N.; Desai, A.S.; Diaz, R.; Fleg, J.L.; et al. Spironolactone for heart failure with preserved ejection fraction. N. Engl. J. Med. 2014, 370, 1383–1392. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Merrill, M.; Sweitzer, N.K.; Lindenfeld, J.; Kao, D.P. Sex Differences in Outcomes and Responses to Spironolactone in Heart Failure with Preserved Ejection Fraction: A Secondary Analysis of TOPCAT Trial. JACC Heart Fail. 2019, 7, 228–238. [Google Scholar] [CrossRef] [Scilit]
- Anand, I.S.; Claggett, B.; Liu, J.; Shah, A.M.; Rector, T.S.; Shah, S.J.; Desai, A.S.; O’Meara, E.; Fleg, J.L.; Pfeffer, M.A.; et al. Interaction Between Spironolactone and Natriuretic Peptides in Patients with Heart Failure and Preserved Ejection Fraction: From the TOPCAT Trial. JACC Heart Fail. 2017, 5, 241–252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pfeffer, M.A.; Claggett, B.; Assmann, S.F.; Boineau, R.; Anand, I.S.; Clausell, N.; Desai, A.S.; Diaz, R.; Fleg, J.L.; Gordeev, I.; et al. Regional variation in patients and outcomes in the Treatment of Preserved Cardiac Function Heart Failure with an Aldosterone Antagonist (TOPCAT) trial. Circulation 2015, 131, 34–42. [Google Scholar] [CrossRef] [Scilit]
- Selvaraj, S.; Claggett, B.; Shah, S.J.; Anand, I.; Rouleau, J.L.; O’Meara, E.; Desai, A.S.; Lewis, E.F.; Pitt, B.; Sweitzer, N.K.; et al. Prognostic Value of Albuminuria and Influence of Spironolactone in Heart Failure with Preserved Ejection Fraction. Circ. Heart Fail. 2018, 11, e005288. [Google Scholar] [CrossRef] [Scilit]
- Bayer Healthcare Pharmaceuticals Inc. KERENDIA (Finerenone) Prescribing Information. Available online: https://labeling.bayerhealthcare.com/html/products/pi/Kerendia_PI.pdf (accessed on 17 August 2021).
- Filippatos, G.; Anker, S.D.; Pitt, B.; Rossing, P.; Joseph, A.; Kolkhof, P.; Lambelet, M.; Lawatscheck, R.; Bakris, G.L.; Ruilope, L.M.; et al. Finerenone and Heart Failure Outcomes by Kidney Function/Albuminuria in Chronic Kidney Disease and Diabetes. JACC Heart Fail. 2022, 10, 860–870. [Google Scholar] [CrossRef] [Scilit]
- Solomon, S.D.; McMurray, J.J.V.; Vaduganathan, M.; Claggett, B.; Jhund, P.S.; Desai, A.S.; Henderson, A.D.; Lam, C.S.P.; Pitt, B.; Senni, M.; et al. Finerenone in Heart Failure with Mildly Reduced or Preserved Ejection Fraction. N. Engl. J. Med. 2024, 391, 1475–1485. [Google Scholar] [CrossRef] [Scilit]
- Matsumoto, S.; Jhund, P.S.; Henderson, A.D.; Bauersachs, J.; Claggett, B.L.; Desai, A.S.; Brinker, M.; Schloemer, P.; Viswanathan, P.; Mares, J.W.; et al. Initial Decline in Glomerular Filtration Rate with Finerenone in HFmrEF/HFpEF: A Prespecified Analysis of FINEARTS-HF. J. Am. Coll. Cardiol. 2025, 85, 173–185. [Google Scholar] [CrossRef] [Scilit]
- Mc Causland, F.R.; Vaduganathan, M.; Claggett, B.L.; Kulac, I.J.; Desai, A.S.; Jhund, P.S.; Henderson, A.D.; Brinker, M.; Perkins, R.; Scheerer, M.F.; et al. Finerenone and Kidney Outcomes in Patients with Heart Failure: The FINEARTS-HF Trial. J. Am. Coll. Cardiol. 2025, 85, 159–168. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jhund, P.S.; Talebi, A.; Henderson, A.D.; Claggett, B.L.; Vaduganathan, M.; Desai, A.S.; Lam, C.S.P.; Pitt, B.; Senni, M.; Shah, S.J.; et al. Mineralocorticoid receptor antagonists in heart failure: An individual patient level meta-analysis. Lancet 2024, 404, 1119–1131. [Google Scholar] [CrossRef] [Scilit]
- Ferreira, J.P.; Pitt, B.; McMurray, J.J.V.; Pocock, S.J.; Solomon, S.D.; Pfeffer, M.A.; Zannad, F.; Rossignol, P. Steroidal MRA Across the Spectrum of Renal Function: A Pooled Analysis of RCTs. JACC Heart Fail. 2022, 10, 842–850. [Google Scholar] [CrossRef] [Scilit]
- Ferreira, J.P.; Zannad, F.; Butler, J.; Filippatos, G.; Pocock, S.J.; Brueckmann, M.; Brinker, M.; Schloemer, P.; Viswanathan, P.; Mares, J.W.; et al. Association of Empagliflozin Treatment with Albuminuria Levels in Patients with Heart Failure: A Secondary Analysis of EMPEROR-Pooled. JAMA Cardiol. 2022, 7, 1148–1159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nuffield Department of Population Health Renal Studies Group; SGLT2 inhibitor Meta-Analysis Cardio-Renal Trialists’ Consortium. Impact of diabetes on the effects of sodium glucose co-transporter-2 inhibitors on kidney outcomes: Collaborative meta-analysis of large placebo-controlled trials. Lancet 2022, 400, 1788–1801. [Google Scholar] [CrossRef] [Scilit]
- Marton, A.; Saffari, S.E.; Rauh, M.; Sun, R.N.; Nagel, A.M.; Linz, P.; Lim, T.T.; Takase-Minegishi, K.; Pajarillaga, A.; Saw, S.; et al. Water Conservation Overrides Osmotic Diuresis During SGLT2 Inhibition in Patients with Heart Failure. J. Am. Coll. Cardiol. 2024, 83, 1386–1398. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cherney, D.Z.; Perkins, B.A.; Soleymanlou, N.; Maione, M.; Lai, V.; Lee, A.; Fagan, N.M.; Woerle, H.J.; Johansen, O.E.; Broedl, U.C.; et al. Renal hemodynamic effect of sodium-glucose cotransporter 2 inhibition in patients with type 1 diabetes mellitus. Circulation 2014, 129, 587–597. [Google Scholar] [CrossRef] [Scilit]
- Gronda, E.; Iacoviello, M.; Arduini, A.; Benvenuto, M.; Gabrielli, D.; Bonomini, M.; Tavazzi, L. Gliflozines use in heart failure patients. Focus on renal actions and overview of clinical experience. Eur. J. Intern. Med. 2025, 132, 1–8. [Google Scholar] [CrossRef] [Scilit]
- Packer, M.; Anker, S.D.; Butler, J.; Filippatos, G.; Ferreira, J.P.; Pocock, S.J.; Rocca, H.B.; Janssens, S.; Tsutsui, H.; Zhang, J.; et al. Influence of neprilysin inhibition on the efficacy and safety of empagliflozin in patients with chronic heart failure and a reduced ejection fraction: The EMPEROR-Reduced trial. Eur. Heart J. 2021, 42, 671–680. [Google Scholar] [CrossRef] [Scilit]
- Vallon, V.; Kim, Y.C. Protecting the Kidney: The Unexpected Logic of Inhibiting a Glucose Transporter. Clin. Pharmacol. Ther. 2022, 112, 434–438. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Adamson, C.; Docherty, K.F.; Heerspink, H.J.L.; de Boer, R.A.; Damman, K.; Inzucchi, S.E.; Køber, L.; Kosiborod, M.N.; Martinez, F.A.; Petrie, M.C.; et al. Initial Decline (Dip) in Estimated Glomerular Filtration Rate After Initiation of Dapagliflozin in Patients with Heart Failure and Reduced Ejection Fraction: Insights From DAPA-HF. Circulation 2022, 146, 438–449. [Google Scholar] [CrossRef] [Scilit]
- Mc Causland, F.R.; Claggett, B.L.; Vaduganathan, M.; Desai, A.S.; Jhund, P.; de Boer, R.A.; Docherty, K.; Fang, J.; Hernandez, A.F.; Inzucchi, S.E.; et al. Dapagliflozin and Kidney Outcomes in Patients with Heart Failure with Mildly Reduced or Preserved Ejection Fraction: A Prespecified Analysis of the DELIVER Randomized Clinical Trial. JAMA Cardiol. 2023, 8, 56–65. [Google Scholar] [CrossRef] [Scilit]
- Zannad, F.; Ferreira, J.P.; Gregson, J.; Kraus, B.J.; Mattheus, M.; Hauske, S.J.; Butler, J.; Filippatos, G.; Wanner, C.; Anker, S.D.; et al. Early changes in estimated glomerular filtration rate post-initiation of empagliflozin in EMPEROR-Reduced. Eur. J. Heart Fail. 2022, 24, 1829–1839. [Google Scholar] [CrossRef] [Scilit]
- Rastogi, T.; Ferreira, J.P.; Butler, J.; Kraus, B.J.; Mattheus, M.; Brueckmann, M.; Butler, J.; Filippatos, G.; Wanner, C.; Anker, S.D.; et al. Early changes in estimated glomerular filtration rate post-initiation of empagliflozin in EMPEROR-Preserved. Eur. J. Heart Fail. 2024, 26, 885–896. [Google Scholar] [CrossRef] [Scilit]
- Packer, M.; Butler, J.; Zeller, C.; Pocock, S.J.; Brueckmann, M.; Ferreira, J.P.; Filippatos, G.; Usman, M.S.; Zannad, F.; Anker, S.D. Blinded Withdrawal of Long-Term Randomized Treatment with Empagliflozin or Placebo in Patients with Heart Failure. Circulation 2023, 148, 1011–1022. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heerspink, H.J.; Perkins, B.A.; Fitchett, D.H.; Husain, M.; Cherney, D.Z. Sodium Glucose Cotransporter 2 Inhibitors in the Treatment of Diabetes Mellitus: Cardiovascular and Kidney Effects, Potential Mechanisms, and Clinical Applications. Circulation 2016, 134, 752–772. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, K.; Nie, Z.; Shi, R.; Yu, D.; Wang, Q.; Shao, F.; Wu, G.; Wu, Z.; Chen, T.; Li, C. Time to Benefit of Sodium-Glucose Cotransporter-2 Inhibitors among Patients with Heart Failure. JAMA Netw. Open 2023, 6, e2330754. [Google Scholar] [CrossRef] [Scilit]
- Marx, N.; Federici, M.; Schott, K.; Muller-Wieland, D.; Ajjan, R.A.; Antunes, M.J.; Christodorescu, R.M.; Crawford, C.; Di Angelantonio, E.; Eliasson, B.; et al. 2023 ESC Guidelines for the management of cardiovascular disease in patients with diabetes. Eur. Heart J. 2023, 44, 4043–4140. [Google Scholar] [CrossRef] [Scilit]
- Beldhuis, I.E.; Lam, C.S.P.; Testani, J.M.; Voors, A.A.; Van Spall, H.G.C.; Ter Maaten, J.M.; Damman, K. Evidence-Based Medical Therapy in Patients with Heart Failure with Reduced Ejection Fraction and Chronic Kidney Disease. Circulation 2022, 145, 693–712. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gaziano, L.; Sun, L.; Arnold, M.; Bell, S.; Cho, K.; Kaptoge, S.K.; Song, R.J.; Burgess, S.; Posner, D.C.; Mosconi, K.; et al. Mild-to-Moderate Kidney Dysfunction and Cardiovascular Disease: Observational and Mendelian Randomization Analyses. Circulation 2022, 146, 1507–1517. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tonneijck, L.; Muskiet, M.H.; Smits, M.M.; van Bommel, E.J.; Heerspink, H.J.; van Raalte, D.H.; Joles, J.A. Glomerular Hyperfiltration in Diabetes: Mechanisms, Clinical Significance, and Treatment. J. Am. Soc. Nephrol. 2017, 28, 1023–1039. [Google Scholar] [CrossRef] [Scilit]
- Fliser, D.; Franek, E.; Joest, M.; Block, S.; Mutschler, E.; Ritz, E. Renal function in the elderly: Impact of hypertension and cardiac function. Kidney Int. 1997, 51, 1196–1204. [Google Scholar] [CrossRef] [Scilit]
- Ritz, E.; Fliser, D. The kidney in congestive heart failure. Eur. Heart J. 1991, 12, 14–20. [Google Scholar] [CrossRef] [Scilit]
- Neuen, B.L.; Tighiouart, H.; Heerspink, H.J.L.; Vonesh, E.F.; Chaudhari, J.; Miao, S.; Chan, T.M.; Fervenza, F.C.; Floege, J.; Goicoechea, M.; et al. Acute Treatment Effects on GFR in Randomized Clinical Trials of Kidney Disease Progression. J. Am. Soc. Nephrol. 2022, 33, 291–303. [Google Scholar] [CrossRef] [Scilit]
- Holtkamp, F.A.; de Zeeuw, D.; Thomas, M.C.; Cooper, M.E.; de Graeff, P.A.; Parving, H.H.; Brenner, B.M.; Shahinfar, S.; Lambers Heerspink, H.J. An acute fall in estimated glomerular filtration rate during treatment with losartan predicts a slower decrease in long-term renal function. Kidney Int. 2011, 80, 282–287. [Google Scholar] [CrossRef] [Scilit]
- Butt, J.H.; McMurray, J.J.V.; Claggett, B.L.; Jhund, P.S.; Neuen, B.L.; McCausland, F.R.; Desai, A.S.; Lam, C.S.P.; Pitt, B.; Pfeffer, M.A.; et al. Therapeutic Effects of Heart Failure Medical Therapies on Standardized Kidney Outcomes: Comprehensive Individual Participant-Level Analysis of 6 Randomized Clinical Trials. Circulation 2024, 150, 1858–1868. [Google Scholar] [CrossRef] [Scilit]
- Inker, L.A.; Heerspink, H.J.L.; Tighiouart, H.; Levey, A.S.; Coresh, J.; Gansevoort, R.T.; Simon, A.L.; Ying, J.; Beck, G.J.; Wanner, C.; et al. GFR Slope as a Surrogate End Point for Kidney Disease Progression in Clinical Trials: A Meta-Analysis of Treatment Effects of Randomized Controlled Trials. J. Am. Soc. Nephrol. 2019, 30, 1735–1745. [Google Scholar] [CrossRef] [Scilit]
- Khan, M.S.; Bakris, G.L.; Packer, M.; Shahid, I.; Anker, S.D.; Fonarow, G.C.; Wanner, C.; Weir, M.R.; Zannad, F.; Butler, J. Kidney function assessment and endpoint ascertainment in clinical trials. Eur. Heart J. 2022, 43, 1379–1400. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gronda, E.; Palazzuoli, A.; Iacoviello, M.; Benevenuto, M.; Gabrielli, D.; Arduini, A. Renal Oxygen Demand and Nephron Function: Is Glucose a Friend or Foe? Int. J. Mol. Sci. 2023, 24, 9957. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kondo, T.; Jhund, P.S.; Henderson, A.D.; Claggett, B.L.; Desai, A.S.; Brinker, M.; Lay-Flurrie, J.; Schloemer, P.; Viswanathan, P.; Amarante, F.; et al. The efficacy of finerenone on hierarchical composite endpoint analysed using win statistics in patients with heart failure and mildly reduced or preserved ejection fraction: A prespecified analysis of FINEARTS-HF. Eur. J. Heart Fail. 2025, 27, 1459–1471. [Google Scholar] [CrossRef] [Scilit]
- Vaduganathan, M.; Neuen, B.L.; McCausland, F.; Jhund, P.S.; Docherty, K.F.; McMurray, J.J.V.; Solomon, S.D. Why Has it Been Challenging to Modify Kidney Disease Progression in Patients with Heart Failure? J. Am. Coll. Cardiol. 2024, 84, 2241–2245. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- EMPA-KIDNEY Collaborative Group. Effects of empagliflozin on progression of chronic kidney disease: A prespecified secondary analysis from the empa-kidney trial. Lancet Diabetes Endocrinol. 2024, 12, 39–50. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.